Many of my readers had one Covid a long time ago, or never had Covid, are not having another Covid so far, and may not realize how badly are things going in Covid-land in Europe and highly vaccinated areas of USA.
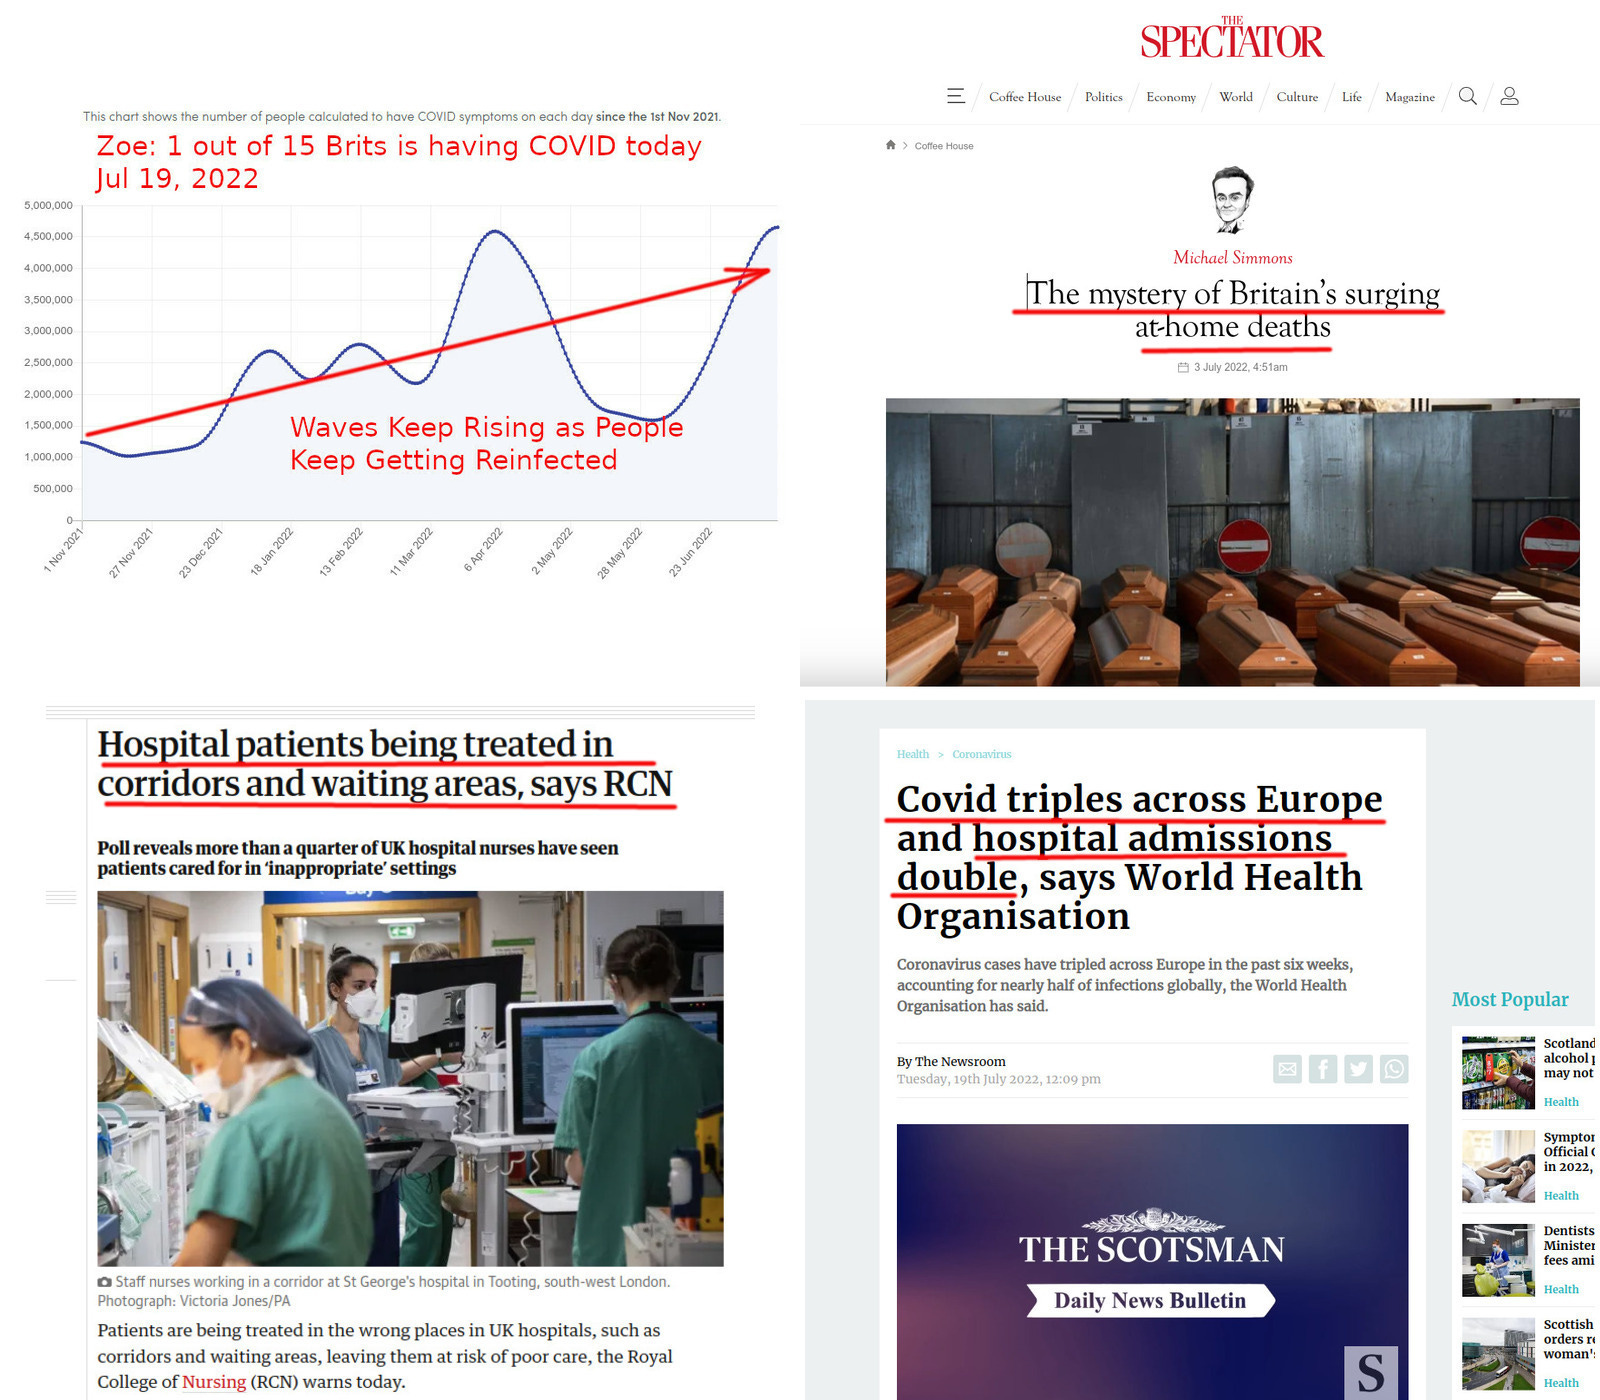
More than one out of 15 Brits is having COVID today (Jul 19, 2022). This is higher than ever before. An “unexpected” largest-ever wave of a yet-another variant Ba.5 is reinfecting highly-vaccinated countries one more time. Hospitals are strained, because sick, force-injected health care workers are staying home due to their Covid reinfections, and patients are hospitalized at record rates. Excess mortality is rising.
People are, naturally, becoming worried as they or their relatives have two-week-long bouts of Covid reinfections that do not feel mild to them and leave them exhausted. My own opinion is that we are on the verge of significant increases in overall mortality. I am quite worried about that.
Rumblings of discontent are appearing. The powers-to-be are wondering what to do.
So, the so-called “Independent SAGE” just came up with a “seven-point plan” to combat COVID. The plan is so spectacularly stupid that it reads like a parody. Here it is, from the British Medical Journal no less.
This plan is the product of supposedly the “best Covid minds”, the leading thinkers of UK science, whose recommendations influence UK policy. What did these minds produce? Let’s look.
They are proposing to do more of same!
The “clear and consistent messaging” is a theme of the pandemic, it relates to a bad idea that all officials should parrot one line during a so-called “emergency”, to avoid confusing the public. The result of this policy was a lack of independent thinking, as well as censorship of any dissenting voices, that led to groupthink. What message, pray tell, should such “clear and consistent messaging” convey? The seven-point plan?
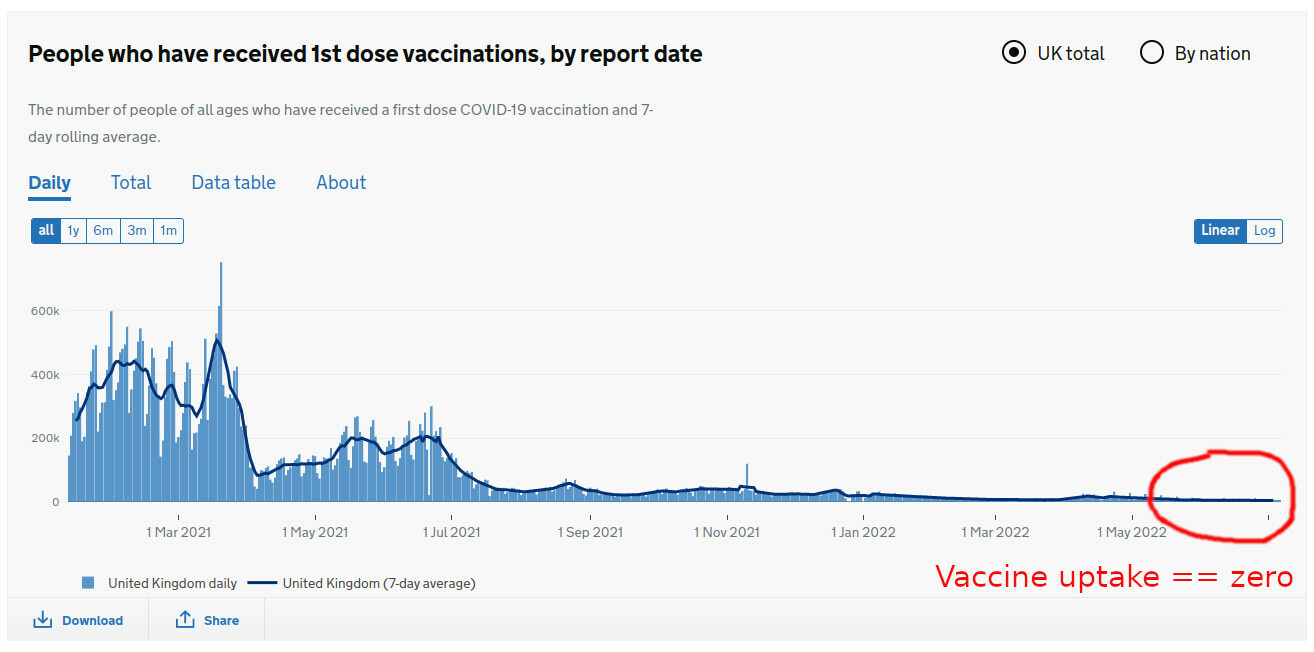
The efforts to promote “vaccine uptake” are particularly laughable in July of 2022. Here’s how vaccine uptake looks in the UK:
Of special interest is a need to have a “clear long-term plan to address waning immunity and immune escape”. What they are saying is that they do not have such a plan. They merely want to have a plan, which they do not have, as of now.
The concept of “air filtration” refers to a sincerely expressed, but misguided idea that retrofitting buildings with “air filtration devices” will stop the pandemic. While I personally like almost all people who advocate it, I also recognize that it is largely futile, for many reasons having to do with physics and gas dynamics.
Air filtration that could effectively capture airborne virions, would need to turn over enormous volumes of air every minute, through the finest filters, continuously. This is not compatible with existing buildings’ HVAC systems. It would also cost a fortune in electric bills and create a lot of heat. I do not want to get into this discussion too much, but “air filtration” of that kind is not possible in most establishments or homes.
The “FFP3 masks” are obvious non-starters because of difficulties wearing them. Making the public wear such masks in 2022 is impossible.
The worst part of this proposal is the so-called “equitable global provision of vaccines”. This is a code word for bribing governments of poor countries into forcing their citizens to take “vaccines” that these wise but poor people refuse to take voluntarily. The countries with unvaccinated majorities are the future of humanity, in my opinion. They are largely at herd immunity precisely because they refused to vaccinate. Yet, Independent SAGE wants to inject them with non-working “vaccines” in the name of “equity”. Why?
The crazy “Independent SAGE” advisers are anything but sage, are actually stupid, and I am very sorry that they have been UK’s thought leaders since 2020.
Here’s a clip from “Idiocracy”. While it is funny, it shows President Camacho actually solving his country’s problem of dying plants, with his three-point plan of hiring the smartest person in the world named Not Sure. Not Sure figured out the problem and proceeded to stop using Brawndo to water plants.
Brawndo’, which owned the FDA, went bankrupt. The plants started growing, given clean water. Any parallels with the present?
P.S. Please do not think that I am badmouthing the UK by criticizing British Covid experts: Covid experts in the USA are so much worse and could not even come up with a “seven-point plan”. So there is no “USA Covid plan” that I could criticize.
The medical establishment professes to know an awful lot. A few days before lockdown in March 2020, it knew that covid was not a High Consequence Infectious Disease and downgraded it accordingly. Exhibiting an Orwellian capacity for doublethink, it also knew that societies ought to be bludgeoned with lockdowns to prevent the spread of the not so highly consequential, and therefore downgraded, pathogen. In addition, it somehow just knew, without being able to explain why, that a cost-benefit analysis would be superfluous, so none was done. Until July 2020, it knew, based on decades of established science, that masking in community settings was useless in preventing the spread of respiratory illnesses. Then, with no new science to support a 180-degree turn, it just knew that masks had to be mandated.
It was so certain that mass vaccination with the experimental injections was the only course of action to take in the face of the not so highly consequential covid disease that it suppressed alternative cheap, safe and effective treatments. It was also quite sure that it had to censor and threaten doctors like Sam White with debarment because he expressed concerns about mass vaccination with the shoddily tested and hastily marketed novel ‘vaccines’. It somehow reasoned that doctors expressing genuine concern for patient safety was a threat to patient safety and that the only way to guarantee patient safety was for every single doctor, journalist and media outlet to sing from the same Big Pharma-sponsored hymn sheet.
Granted, the medical establishment’s stance during covid has not been underpinned by rational considerations, but that is precisely what has given it so much latitude to respond to ‘the crisis’. There is no limit to what you can know and do when you don’t have to prove rationally how you came to know it. Life is a never-ending carousel of trade-offs. You can either plod through things methodically and get it right or you can blast ahead at Warp Speed with the misplaced confidence of Joe Biden on a bicycle.
So, given the medical establishment’s boundless knowledge in times of crisis, it’s more than a little odd that it does not know why young and apparently healthy adults all over the world are dying in unprecedentedly large numbers. It is uncharacteristically stumped: it professes that there are simply no clues whatsoever to this disturbing phenomenon.
It is in the grip of such uncharacteristic knowledge paralysis that it seems incapable of exploring obvious lines of enquiry, such as asking questions like: when was the last time that governments all over world put a jackboot on the neck of every adult citizen to inject them with novel ‘vaccines’ employing an experimental gene-based technology tested under quality control conditions that would have run-of-the-mill crack dealers shaking their heads in disbelief?
What’s in a name?
Once you unlock the mystery of the medical establishment’s peculiar brand of epistemology, you begin to understand that how it comes to ‘know’ things is directly related to how it defines the problems it is trying to solve. For people who think in straitjackets, the problem of young people dying inexplicably is a medical problem. But, for the unbounded thinkers in charge of the medical establishment, it is a Public Relations problem. Through that lens, the obvious line of enquiry into experimental mass vaccination gets ruled out because it is too rational, too much of a threat to its reputation and too unprofitable.
The solution to this PR problem is to repackage it in such a way that it is seen as an insoluble medical mystery, as insoluble as the mystery of life itself – a mystery that one can debate in philosophical terms but never get to grips with in any practical way. The most insoluble mysteries are those that have been around since the dawn of time and yet continue to evade unravelling. This is axiomatic to the quality of insolubility – Plato, Seneca, Aquinas, Voltaire and Heidegger will have all given it their best shot and yet here we are today, none the wiser. The seed must be sown in the public mind that this is not a new problem that arose coterminously with mass global experimental covid vaccination but has been ‘a thing’ since the dawn of medical things.
The key to all successful narrative management is naming the problem. When Edward Bernays, the father of propaganda, was tasked by the tobacco industry in the early 20th century with breaking the taboo against women smoking cigarettes, he didn’t call them cancer sticks. He called them torches of freedom. With one ingenious stroke of the naming pen, the tobacco industry doubled its market overnight and women won the right to lung cancer.
In a similar vein, society must understand that young adults inexplicably dying before their time is the result of a bona fide disease of unfathomable cause – a mysterious and yet proper medical thing – and not a possible crime against humanity.
At first glance, the name they’ve hit on does not fill you with confidence that the best medical minds were enlisted in the brainstorming session. But it certainly has an air of does-what-it-says-on-the-tin. It is partly for that reason that Sudden Adult Death Syndrome (“SADS”) is a stroke of marketing genius. It’s got an easy acronym that chimes flippantly with the tragic outcome and yet is also readily accessible to authoritative tones after three pints in the pub. This is 90 per cent of the battle in getting the public to understand in no uncertain terms that SADS is ‘a thing’. A serious thing. It trips off the tongue very easily and yet is not so silly that it sounds like the lead-in to a crazy story developed by a contestant in an episode of BBC One’s Would I Lie to You.
As far as the medical establishment is concerned, the perception that SADS on this scale is a recent global phenomenon must be resisted on the grounds that it could become associated with a big new event – like mass global experimental covid vaccination. So no, SADS is not new. It’s been a thing for eons. And for sure, a Google search seems to suggest that SADS has been around for as long as cancer. But Allan Stevo’s investigation using his “8.6 pound Webster’s Encyclopaedic Unabridged Dictionary of the English Language from 1992” – which is impervious to algorithmic re-engineering – reveals that the term did not exist in 1992. But who are you going to trust – the colourful, digital pages of Google or the crumbling ancient parchments of Webster’s Encyclopaedic Unabridged Dictionary of the English Language?
I’m not saying there have never been mysterious unexplained deaths of young and apparently healthy adults. They were just so rare that they weren’t on the radar, even of dictionaries whose job it is to define all things known to the vast bulk of humanity. Surely this merits delving into a little deeper?
Whatever you do, don’t solve the problem – autopsies die a sudden death
One way to solve the apparently insoluble problem of sudden adult death would be to conduct autopsies on as many sudden adult deaths as resources will allow. It turns out that the Chief Pathologist at the University of Heidelberg, Dr. Peter Schirmacher, was doing just that very thing. In the summer of 2021, his team had just finished conducting 40 autopsies on people who had died within two weeks of vaccination and concluded that 30-40% of them died from the vaccine. He was pushing for many more autopsies of vaccinated people.
His claims were naturally dismissed by the German Government. From Dr. Schirmacher’s perspective, the dismissal by bureaucrats of his professional autopsy findings must have felt like being an army private in the battlefield reporting by radio to a lieutenant that he’d just been shot in the leg, only to have the lieutenant ask, “How can you be sure?”. But the powerful bureaucrats must have had good reason to dismiss his professional work although these reasons weren’t made clear.
Calls by the Federal Association of German Pathologists pushing for more autopsies of vaccinated people were also treated with disdain. No other autopsies have been performed apart from 15 done by Dr. Arne Burkhardt towards the end of 2021, which found “clear evidence of vaccine-induced autoimmune-like pathology in multiple organs” in 14 of 15 cases, all of which were ignored by all health authorities and mainstream media. No further autopsies have been reported and Dr. Schirmacher and his colleagues have gone quiet, after being so emphatic about the risks and the need for as many autopsies as possible.
On the face of it, the only way to prove what is causing the uptick in mysterious sudden deaths has died a sudden death. But the sensible and mature conclusion to draw from the silence of the autopsy doctors is that they have realised they were wrong and that the powerful bureaucrats and MSM journalists, who know nothing about autopsies, were right. Only a ‘conspiracy theorist’ would think there was a cover-up going on, right?
Public Relations – The Mail Online takes a proper gander at SADS
In any case, why bother with autopsies when, according to this article in the Mail Online, the best medical minds in Australia are getting to grips with the problem by “opening up a new national register”. Yes, that’s right, they’re at the cutting edge of the Fourth Industrial Revolution (4IR) in which all our problems will be solved by data, algorithms, AI and registers. We’re leaving behind the grime of autopsies, post-mortems and diagnosing diseased patients by prodding them with stethoscopes and asking them time-wasting questions. We’ve got registers now.
Now, at first glance it might seem that the article would not be out of place in The Onion or the Babylon Bee because of idiotic tautologies like this one:
But pointing out that SADS, a death syndrome, is fatal is not cheap satire. It is a reminder that contained in SADS is both the disease and its inescapable prognosis of death.
Another reason why SADS is more of a thing than any other medical thing is that a diagnosis of SADS can never be wrong. It can only be given after death has occurred and only three boxes need to be ticked – did the deceased die without warning; was the deceased an adult in the prime of life and, crucially; do we intend to follow 4IR protocols to establish cause of death by doing nothing other than entering some data in a register? Yes, to all three? Job done. The clever cardiologist who is quoted extensively in the article jokes that SADS is a “diagnosis of nothing” but, once she has taken her tongue out of her cheek, I’m sure she is only too aware of how clever a diagnosis this is.
After correctly informing the reader that this particular death syndrome is fatal, the article recounts how a typical sudden death unfolds. The victim doesn’t come down for breakfast, but no one is concerned because we (white-collar workers at least) all work from home these days so having a lie-in is par for the course. The whole tone of the description of the tragic death of a young person in the peak of life is bizarrely deadpan. Again, you would be wrong to interpret this apparently tasteless approach as cheap satire. The banal tone is deliberately intended to drive home the point that SADS is just another puzzle in the countless puzzles that the universe, with its twisted sense of humour, flings at humanity on a regular basis.
The article contains pictures of very young actors clutching at their hearts with distressed expressions. Again, you would be wrong to think this is cheap and tasteless. How else are we to understand that SADS really is a thing? I think the visual message here is that if you’re under 40 and find yourself clutching at your heart while out jogging, be appropriately but not overly distressed because, while your heart may stop beating and no-one will ever know exactly why, SADS is definitely a thing. And the national register will never forget you.
Because the article is intended to be as informative as possible, it shares some very helpful warning ‘signs’ of SADS. Top warning sign number one is a family history of a SADS diagnosis. The happy smiley cardiologist who was selected to educate the public about SADS advises that your SADS clock might be silently ticking down if any of the following things have happened to you: fainting from exercise, over-excitement or just being ‘startled’. If you are one of those people who faints at the mere thought of exercise, you would have obviously been on the SADS register a very long time ago, had it been in operation. Your continued existence is actually more of a mystery than SADS itself, but let’s not complicate things any further. Suffice to say your clock is ticking down and your housemates should not be too surprised if you don’t come down for breakfast in the next couple of weeks. At least the Mail Online has prepared them. And you, come to think of it.
If you are wondering why I refer to the cardiologist as “the happy smiley doctor”, click the link to the article and it will be as clear to you as her sparkling eyes and teeth. There is a photo of her beaming as though she has just been awarded the Nobel Prize for medicine when in fact, she is being quizzed about the grizzly business of young people dying for reasons that cannot be fathomed by the best brains in medicine. Why is she happy and smiley instead of sombre and uneasy? Is this another tactless error by the Mail Online inadvertently making the whole article look like cheap satire? Not at all. World War II propaganda used the very same technique to placate the masses in times of great uncertainty. Here is a WWII poster of a woman exuding the same brand of devil-may-care insouciance in the face of adversity:
Ok, so I’ve chosen a Nazi propaganda poster to compare with the happy smiley Australian doctor. Is this in bad taste? Personally, I don’t think so. Today’s brave new world of forced masking, forced lockdowns and forced medical experimentation must be met head-on with bold comparisons. Yesterday’s Nazis weren’t big on bodily autonomy and nor are today’s Australians (or Canadians, or Austrians, or French for that matter). Am I saying, rather unsubtly, that the Western world is becoming the very thing it fought 75 years ago? Only if you believe that people were robbed of the human right to voluntary informed consent by being coerced into taking the ‘vaccines’. ‘Vaccines’ which, let’s be clear, have absolutely nothing to do with the current spate of sudden adult deaths all over the world.
Am I unsubtly hinting that the Mail Online’s proper gander at SADS is actually propaganda for the medical establishment? Only if you believe that the responsible thing to do would be to show a picture of a doctor holding her head in her hands, tears of shame flowing from her eyes for failing to at least consider one potential and obvious cause of the mysterious deaths. I think we’re all in agreement here – that would not be responsible journalism. Far better to show a happy beaming doctor exuding the confidence of someone who is certain that SADS really is a thing, that it’s been a big thing for quite some time and that, while getting a ‘diagnosis’ of SADS is indeed the end of the world for you, you will die knowing that we are getting on top of this very real thing because we’re fighting it with a register and not with futile autopsies.
There’s a mention in the article about the role of genes because you can’t have a totally mysterious and fatal death syndrome (if the Mail Online can get away with this clever tautology, why can’t I?) without genes playing a role. Of course they haven’t, and never will, find a SADS gene, but that’s beside the point when proffering genes causality. Genes are the building blocks of life; your life ends suddenly without warning, ergo there must have been something wrong with your building blocks.
The ‘best advice’ the happy smiley cardiologist can give is: if you’re related to anyone who’s had an unexplained death, ‘it’s extremely recommended you see a cardiologist.’ Which seems pointless because a SADS diagnosis rests entirely on you having no detectable condition right up to the point you clutch your heart in desperation and keel over. If the condition was a recognised detectable one, mitigation strategies would likely kick in pre-heart clutching and, even if you ended up dying from that condition, your death would be labelled something other than SADS by virtue of its having been detected. SADS is the ultimate catch-22 – the doctors don’t know what’s wrong with the patient before they die and there’s no way of knowing afterwards (autopsies now being off the table) so the patient gets a posthumous SADS ‘diagnosis’, and is successfully entered on a register.
The Mail Online article is perfect except for that flawed bit of advice which seems to fail to recognise the complex circular nature of SADS. Telling people to have a thorough check-up before SADS threatens the very existence of SADS. Being cynical, I would say this advice is a ruse to give a boost to the happy smiley doctor’s billings.
As I’ve repeated ad nauseum here at the Daily Sceptic, excess mortality provides a far better measure of the pandemic’s impact on mortality than the ‘official’ Covid death rate.
When it comes to cross-country comparisons, the ‘official’ Covid death rates are particularly deficient. Testing and diagnosis vary dramatically, so two countries with the same actual death tolls may still have very different ‘official’ death tolls – just because one tested more or had broader criteria for diagnosis.
Excess mortality, as most readers are no-doubt aware, is the difference between the number of deaths observed during the pandemic and the number that were expected, based on previous years. A five-year average is often used for the number of expected deaths – though one can use a linear trend or more complicated extrapolation instead.
Here’s a very simple example. Suppose a country had roughly 100,000 deaths per year in 2015, 2016, 2017, 2018 and 2019. Then in 2020, it records 120,000 deaths. In that case, excess mortality would be 20,000 deaths.
But of course, if we want to compare this country to other countries, the ‘20,000 deaths’ isn’t very useful. Larger countries will have more excess deaths just because there are more people at risk of death. And this is something we need to account for when making comparisons, or else we’ll conclude that all the small countries did well and all the large ones did badly.
So why not just divide the ‘20,000 deaths’ figure by the country’s population, thereby obtaining ‘excess deaths per 100,000 people’? Indeed, that’s exactly what the WHO did for its recent estimates of excess deaths associated with the pandemic (which were widely covered in the media).
Well, there’s a problem with this method of adjustment: countries have different age structures. And this matters because the risk of death (from both Covid and everything else) is far higher in older age-groups than in younger age-groups.
Consider two countries with the same number of excess deaths, say 20,000. One has a population of 10 million and one has a population of 12 million. Suppose the 2 million ‘extra’ people in the second country are all under the age of 40. So above the age of 40, the two countries have identical age structures.
Using the WHO’s method of adjustment, excess mortality would be 200 per 100,000 in the first country, but only 167 per 100,000 in the second country. Yet this clearly ‘rewards’ the second country. Why? Very few deaths occur among people under 40, so including them in the denominator artificially pulls down the rate of excess mortality.
Rather than dividing by the country’s population, there’s a much better way of making excess mortality figures comparable: divide by the number of expected deaths. This gives you a percentage, which is neither biased against large countries, nor against countries with aging populations.
As a matter of fact, the WHO’s decision to divide by the country’s population may help to explain its widely-reported (but almost certainly wrong) finding that Britain had less excess mortality than Germany. Estimates based on percentages clearly show that Britain had more excess mortality. Yet because Germany’s population pyramid has a narrower base, the denominator in the WHO’s calculation will have been smaller.
Having said that, I doubt the WHO’s estimates are substantially different from those based on percentages. But that’s not the point. The point is they used a bad method of adjustment, when an equally simple and better one was available.
What would be your prediction for those who are both unvaccinated against COVID-19 and never previously infected? Let’s say those of working age(20 – 55) in fairly good health.
Should they be worried about Avian Flu and Monkeypox, since they have not experienced an infection by SARS-CoV-2?
Are they at risk for serious illness from these more infectious (and future more virulent) SARS-CoV-2 mutants?
Answer:
It would be quite unbelievable that they didn’t get exposed to SC-2 given the high infectiousness of previously and currently circulating variants. Ideally, they should have their Abs tested (anti-S would be sufficient since they’re not vaccinated). They can also have their Abs tested against Flu. If all this is negative (which would point to poor activation of natural immunity), they can just take one shot of a live attenuated measles or mumps or rubella or varicella vaccine (or all together in one shot) to boost their innate immune response. (However, they should only do so if they got MMR(V)-vaccinated in the past. The better their innate immune status, the lower the likelihood they are going to catch severe disease from these viruses. But anyhow, for a person in good health, it is highly unlikely to develop severe disease from Monkeypox (as it is – for now(!) – not highly infectious) or from Avian Flu as they must at least have had contact with Flu viruses in the past and hence, have some ‘Flu-trained’ innate immunity.)
Unvaccinated can now largely forget about contracting severe C-19 disease as the next big mutation will most likely make the unvaccinated resistant to the virus. However, if they have not yet been infected at all by any of these highly infectious variants, they could still contract C-19 disease (before that new variant emerges) and become seriously ill (but not ‘severely ill’ as longas they are in good health with no comorbidities and predisposing factors). To avoid this, they should either prevent risky contacts (difficult) till the next variant appears (in my opinion, just a matter of weeks) or take Ivermectin or HCQ as soon as symptoms manifest (but not prophylactically).
The BBC is either the worst media organisation on Earth or the best, depending upon your perspective. On the one hand it is a truly world-class propaganda machine. On the other it is completely incapable of challenging government narratives or power because it is effectively a branch of the UK government and is itself beholden to power.
As an agency of the state, the BBC has actively sought to destabilise overseas governments around the world. It is a master of propaganda and frequently lies to the public, either overtly or by omission, with the goal of convincing the people to accept whatever falsehood or agenda it has been tasked to sell.
From top to bottom, the BBC’s commitment to journalistic integrity is missing. It is simply a mouthpiece for the ruling cartel. It comprehensively fails to deliver the most crucial social function of journalism: holding power to account.
According to the corporation’s published values, “trust is the foundation of the BBC.” The Oxford English Dictionary offers a pejorative meaning of the word “trust”: “acceptance of the truth of a statement without evidence or investigation.”
This definition of “trust” seems appropriate for the BBC. While it declares itself to be “independent, impartial and truthful,” it routinely trots out claimed “facts” that lack supporting evidence and produces investigative reports absent any real investigation. Indeed, the BBC broadcasts appalling lies as a matter of course.
And so it is with a certain degree of mirth that we now learn from the BBC that it intends to air a “documentary” about a phenomenon it has already opted to call “vaccine hesitancy.” (Bear in mind: A “documentary” is “a film or television or radio programme that gives facts and information about a subject.”)
The producer of the upcoming programme, due to air on the 20th of July, Craig Hunter, explains:
Moving beyond the often misrepresented debate, this programme reveals why some people remain vaccine hesitant.
The deprecatory word “hesitant” means “tentative, unsure, or slow in acting.” There is no room in the programme-maker’s minds for the possibility that people who chose to remain “unvaccinated” have considered the risk-benefit of these shots, have looked at the available evidence and have decisively concluded that they don’t want a COVID-19 jab.
Hunter’s statement absolutely “misrepresents” the debate. As Craig is the producer of the forthcoming BBC documentary, it seems the chance of the programme delivering a balanced exploration of the issue is remote to non-existent. There is little reason to expect the BBC to provide anything that is “independent, impartial and truthful.”
Indeed, objectively discussing any facet of the alleged pandemic is way beyond the reach of the BBC. As a state propaganda operation, all it can do is parrot the official narrative spouted by the government and its partners, who are, in this instance, the pharmaceutical corporations.
. . . confronting the latest science and statistics to emerge in the field and dissecting how misinformation spreads on social media.
The BBC cannot succeed in this task because the science and the statistics rarely support the disinformation it has been commissioned to spread. Consequently, it must deceive and misdirect its audience to make sure they believe its propagandist tripe. More to the point, the BBC is itself one of the most prolific distributors of online misinformation.
For example, in its press release the BBC says:
After multiple lockdowns and more than 197,000 deaths, experts are warning we’re now entering a fifth wave of the pandemic. So why are five million adults in the UK still yet to receive a single dose of the vaccine?
Putting aside for the moment that there are actually more than eleven million UK adults yet to receive a single dose of the vaccine and the fact that the BBC itself reported that there were just three million less than a week later, the rest of this claim assumes, without good reason, that there was a “pandemic” in the first place. We now know there is very little evidence that a genuine pandemic ever occurred, yet the BBC keeps up its charade by omitting key facts.
Here is one such key fact: In 2009 the World Health Organisation (WHO) suddenly and radically changed its long-time definition of the word “pandemic.” It removed the defining phrase “several, simultaneous epidemics worldwide with enormous numbers of deaths and illness,” replacing it with reference to a disease for which “most people do not have immunity.” Under this definition, practically any new disease can be declared a pandemic. But the BBC won’t inform its audience of the WHO’s changed definition nor the fact that under the original, and more valid, definition, COVID-19 disease could never have been described as a pandemic.
The BBC has left its audience in the dark about a number of other important facts: (1) as of the 19th of March 2020, UK public health authorities did not consider COVID-19 to be “a high-consequence infectious disease” due to its low mortality; (2) all-cause mortality (the overall death rate) in 2020, the year of the so-called “outbreak,” ranked as only the 9th highest death rate in the first two decades of the 21st century; (3) people with injured limbs and stomach pain were being admitted to hospital as registered COVID-19 patients, thus giving an entirely false impression of a severe pandemic disease; (4) there is no statistical evidence of any beneficial effect from any supposed COVID-19 vaccine; and (5) many deaths have been caused, not by any single disease, but by the policy response to an alleged pandemic.
In the press release for its upcoming “documentary,” the BBC refers to the figure of 197,000 UK deaths from COVID-19 as if that figure is scientifically or statistically indisputable. Not only can it be questioned, it has been! So why doesn’t the BBC mention this?
By deliberately using the largest possible figure, the BBC is attempting to elicit an emotional reaction to the highly questionable number of supposed COVID deaths. The BBC is playing on people’s emotions in order to avoid any objective analysis of the data. Its intention is to manipulate its audience into unquestioning acceptance of a story about a severe pandemic which does not stand up to scrutiny.
Let’s pause to make an important point: The collection, analysis and reporting of COVID-19 mortality data has been deliberately altered and manipulated by governments around the world, all of which worked and continue to work in partnership with the WHO. Nowhere has this manipulation been more pronounced than in the UK, where the engineering of COVID-19 mortality statistics has been quite remarkable.
Mainstream media outlets, especially the BBC, have perpetuated baseless fearmongering. For example, for the first time in the history of reporting deaths from a respiratory disease, propagandists like the BBC are reporting cumulative deaths instead of the annual mortality rates or the more common seasonal variation in these figures. If the same were done for, say, influenza, total flu deaths would be measured in millions, depending on the chosen start date for the accumulation of the mortality data.
Another example: The BBC has chosen to report what the government claims to be “deaths with COVID-19 on the death certificate.” While some of these likely were genuine COVID-19 deaths, the expansive, all-encompassing methodology that the government and the WHO created to attribute as many deaths as possible to COVID-19 renders the bulk of these statistics virtually meaningless. In truth, we don’t know how many people in the UK have died as a direct consequence of COVID-19, though estimates in the region of 20,000 – 25,000 seem reasonable.
The BBC never questions the mortality statistics. It simply takes the figures from the government and reports them without any investigation or analysis. This is essentially the BBC’s purpose: to report whatever it is told to report.
In announcing its faux documentary, the BBC says:
In this timely, eye-opening investigation [. . .] Professor Hannah Fry seeks to understand why eight percent of the population remain unvaccinated against Covid-19.
In reality, more than twenty percent of adults in the UK are “unvaccinated.” The BBC can’t even write a press release for its forthcoming documentary without publishing deceptive statistics. So it is safe to say the “documentary” itself will be little more than a marketing promotion for the jabs.
Statistics from the UK Health Security Agency (UKHSA) on vaccine coverage in England show that the actual percentage of the “unvaccinated” population is very close to thirty percent, not the eight percent the BBC alleges. The English figures are broadly representative of the UK as a whole and can be extrapolated.
Jab uptake increases with age. Thus, if we exclude children under 18, then more than twenty percent of the UK adult population are unvaccinated.
The subsequent uptake of booster jabs has declined markedly from the one-and-two dose uptake. Millions of Brits decided, for whatever reason, that two shots was their limit. Only fifty-two percent have elected to have the first booster (the third jab).
Speaking in December 2021, then-Health Secretary Sajid Javid said that, in order to be considered fully vaccinated for the proposed “covid pass,” one would need to have three jabs. If three becomes the definition of “fully vaccinated,” which seems unlikely given the lack of interest, then currently forty-eight percent of the total UK population, and more than thirty-five percent of the adult population, are not “fully vaccinated.”
The BBC launched its “documentary” by trying to deceive its audience into believing that there is only a tiny fringe minority of indecisive folk who don’t want the COVID jabs. In point of fact, it is nearly half of the UK population.
Not only has the BBC lied about the statistics in its press release, it has even misrepresented the debate it proposed to examine by calling the millions of people who made an informed decision not to have the jabs “hesitant.” But that’s because the BBC is all about propaganda, not journalism.
When some diligent independent researchers did what real journalists are supposed to do and picked up on the BBC’s deception, the BBC simply changed its press release. Since citing real statistics was a bit too tricky for the BBC—after all, it only has an annual budget of around £5 billion—the revisedweb page now reads:
In this timely, eye-opening investigation [. . .] Professor Hannah Fry seeks to understand why a portion of the population remain unvaccinated against Covid-19.
Despite there being no reason to trust anything the BBC ever says, the broadcaster implores its viewers to “trust” it simply by pronouncing its own trustworthiness. For the BBC, your “trust” demonstrates your “faith,” allowing it to tell you stories without the need for investigative journalism or even supporting evidence. By contrast, the evidence invariably reveals that the BBC is completely untrustworthy.
According to BBC, its so-called “documentary” is going to be based on bombarding seven hapless unvaccinated lay people with a barrage of pro-vaccine “experts.” Once browbeaten into submission by these authoritative opinions, the victims will then be subject to the BBC’s logical fallacy tactic of appeal to authority. In other words, these high priests of “the science” will explain how the BBC’s seven victims have been misled by “anti-vaxxer” propaganda.
It is highly likely that even if the seven subjects cogently explain why they have decided not to be injected with experimental concoctions, the BBC will edit out any and all valid points they make—and/or deny whatever evidence they cite. We can make these predictions with relative ease, simply by noting the extraordinary level of deceit already present in the BBC’s press release announcing its “programme.”
We can make still further forecasts about the BBC’s alleged “investigation.” For one thing, it won’t honestly report on the current status of the vaccine trials.
Namely, it will neglect to inform its audience that the NCT04368728 trial of the Pfizer-BioNTech jab isn’t finished. And it will not reveal that neither the NCT04470427 trial of Moderna’s mRNA jab nor Johnson & Johnson’s NCT04614948 Jansen trials have posted any results, because these trials, too, are incomplete. Moreover, the BBC will strenuously avoid pointing out the implication of these facts—probably by not reporting them.
Unless the recipients of these drugs were told that the jabs they were about to receive were experimental, they couldn’t possibly have given their informed consent. Consequently, whenever they weren’t informed, administration of the jab contravened nearly every known medical ethic, including those outlined in the Nuremberg Code. But the BBC won’t mention this, either.
It is also safe to say that the BBC will not tell its audience that AstraZeneca concluded the NCT04516746 trial of its AZD1222 adenovirus jab more than a year before schedule by not bothering to conduct a quality control review, rendering its so-called vaccine trial results practically meaningless.
The BBC will not tell anyone that the British Medical Journal (BMJ)disclosed that both Moderna and Jansen (J&J) confirmed that they had given the jabs to their placebo control groups, ending any prospect of their trials ever meeting the basic standards for randomised controlled studies. When the BMJ asked Pfizer if it had done the same, Pfizer declined comment.
Instead, the BBC will almost certainly claim that the jabs have been through extensive clinical trials. It will just omit the part about them having failed to properly complete any.
The BBC will not acknowledge the freedom of information requests and subsequent court ruling in the US that overturned the Food and Drug Administration’s (FDA) decision to delay release of Pfizer’s primary safety monitoring data for 75 years. The Federal Court forced the FDA to release the damning results of Pfizer’s own early monitoring of adverse reactions following the jab rollout in the US and Europe.
In the space of just a couple of months, there were approximately 42,000 adverse reactions to the Pfizer mRNA jab alone, with just over 25,000 of those confirmed by medical exam and the other 16,000+ unconfirmed. Of these, more than 1,200 injuries resulted in death. More than 11,000 of the injured had not recovered from their serious adverse event at the time of reporting.
The BBC certainly won’t report the Israeli study, the results of which indicate that the Pfizer jab prompts a marked decline in male fertility.
Nor will the BBC mention that Pfizer’s own research shows that, contrary to all of Pfizer’s marketing claims, the corporation knew during the trial phase that the lipid nanoparticles used in its jabs found their way into the liver, adrenal glands and spleen and, in particular, accumulated in female recipients’ ovaries.
The BBC may well have to acknowledge the more-than-38,000 possible vaccine deaths reported to the US VAERS system, the 2,200 deaths reported in the UK and the 46,000 deaths recorded by the European Medicines Agency. Its “experts” will point out that there is no evidence that these deaths are caused by the vaccines and will say that the risk of the disease COVID-19 is far higher than any known risks from the COVID-19 jabs.
The BBC will almost certainly make extraordinary and extremely silly claims about how many lives the jabs have allegedly saved. Again these claims will be based upon nothing but baseless assumptions about what could have happened according to some spurious “predictive model.” Rather like claiming your anti-unicorn spray has stopped a million unicorns from grazing your lawn because you don’t have any unicorns in your garden.
As we have just discussed, the risks of harm from COVID-19 claimed by the government and its propaganda outlets—the BBC foremost—are so implausible they verge on absurd. Yet the BBC will not inform its audience that, to date, not one of the regulators has produced a comprehensive risk-benefit analysis for any of the jabs. So the inevitable BBC claims that the jab benefits outweigh the risks will literally be based upon nothing at all.
The BBC will not go anywhere near reporting the findings of a team of eminent German pathologists who performed autopsies on 40 corpses of people who died within two weeks of vaccination—and who identified the vaccine as the likely cause of death in one-third of the cases.
Nor will the BBC report statements like those from the UK regulator, the MHRA, that adverse reactions, including deaths, are significantly undereported, with just ten percent of serious reactions and between two percent and four percent of non-serious reactions recorded.
What the BBC will do instead is rely upon carefully cherry-picked scientific papers, a narrow band of selected “expert opinion,” speculative statistics and emotionally charged anecdotes to convince its audience that the seven victims of its hit piece, though well meaning, are all hopelessly deluded due to the scourge of online disinformation. It may well try to squeeze in reference to the proposed Online Safety Act and suggest that this government policy is essential to tackle the disinformation problem fabricated in its documentary.
Of course, if the BBC were serious about its professed wish to “fully explore this complex and deeply divisive debate,” it wouldn’t simply subject a group of ordinary men and women to a tirade of unchallenged claims from its hand-picked group of “experts.” If it really wanted to tackle the debate with any objectivity or journalistic integrity, it would also report the views of some of the many eminently qualified scientists and physicians who do question the COVID-19 narrative and the alleged safety and efficacy of the vaccines.
It would be genuinely interesting to see people like Professor Sucharit Bhakdi, Dr. Mike Yeadon, Professor Carl Heneghan and Professor Arne Burkhardt explain some of their reservations. Perhaps other scientists, physicians and experts who have questioned the vaccines and the COVID-19 pandemic could be heard.
Maybe the statistician and Nobel Laureate Professor Michael Levitt; epidemiologists like Professor John Ioannidis or Professor Knut Wittkowski; experts in clinical drug development such as Alexandra (Sasha) Latypova; or physicians such as Dr. Peter McCullough or Dr. Roger Hodkinson could be invited to challenge the BBC’s preferred experts.
The audience and the seven subjects of the BBC’s attack could then hear both sides of the argument. But that won’t happen.
Alas, many won’t get to see the BBC’s vaccine marketing programme because they have already decided that they will no longer pay for its propaganda to be beamed into their heads. These numbers are swelling all the time, hence the deceptive plan to allegedly end the BBC license fee while a desperate workaround is conjured up to make sure the BBC’s coffers remain stuffed with gargantuan amounts of public money.
Still, we might get to watch “Unvaccinated, with Professor Hannah Fry” when it finds its way on to Odysee, BitChute, Rumble or some other worthy video-sharing platform. If so, it will perhaps be interesting for some to see how accurate or inaccurate this article is.
In the meantime, let’s give the Beeb the benefit of the doubt and hope this post is way off the mark. Instead of the awful propagandist drivel we might expect, let’s hope the BBC proves that these suspicions are born of nothing but unfounded, anti-BBC bias.
YOU may have noticed that it’s impossible to walk down a city street and not see smartphones everywhere. The interminable fiddling, the addictive near-impossibility for most people of not taking them everywhere they go. While recognising the dazzling technological ingenuity of these slimline contraptions, I’ve come to see them for what I truly believe them to be: an increasing threat to our freedom.
This claim is not made lightly, and I’ve never been a Luddite about modern technology.
It’s not what they are that is the danger, but what they will become, and what they will be used for.
You’ll probably recall the harrowing, nightmarish scenes in Shanghai, with the hazmat-suited, violent, robot-like police. And what’s the other thing you’ll notice? Almost every protester is waving a smartphone, apparently impotently, at the utterly indifferent zombies of the CCP.
The Chinese authorities clearly feel that they have nothing to fear from having their ghastly activities filmed by their unfortunate citizens, or for those terrible scenes to be broadcast to the world. And how are the people of Shanghai (and other places) controlled, in a manner unpleasantly reminiscent of social insects? Smartphones.
The unconcealed intention of the WEF globalist totalitarians is to impose a digital ID surveillance state which no one can evade and from which no one can escape.
The obvious addictiveness of smartphones, and their ubiquity, makes them the ideal tool for control and oppression.
The so-called ‘Vaccine Passport’ is a euphemism for what will be, and is intended to be, a Slave’s Passport on the Chinese model. If you have difficulty believing that this might be true, peruse the list of information about you that a ‘passport’ (supposedly containing a record of your jabs and boosters) will contain: all manner of personal details, including your political views, who you associate with, your criminal record and your private medical details. It’s precisely the same list the CCP use to control their citizens’ lives down to the last detail. Simply put, if you don’t comply to the last jot and tittle with the government, you are excluded from society, shunned, shamed and increasingly unable to buy essential supplies, even food. Like the people in Shanghai.
Is this all too far-fetched for you? Slightly older readers might like to try a thought experiment: recall that life continued well enough before smartphones came into all-too-common use. It really did.
Don’t make the dangerously naive assumption that ‘this is Britain and Shanghai could never happen here’. Your addiction to your smartphone could end up trapping you and, through your compliance, all of us, in the nightmare vision of a totalitarian world that Schwab, Gates, the WEF and the WHO have long planned and are assiduously cultivating, step by step.
Your smartphone is nothing less than the shackle that will imprison you, irrevocably, in the Great Reset. Have the courage to dump it.
Some residents of Beijing are pushing back against a Covid tracking device they are required to wear on their wristbands. Anyone returning to Tiantongyuan, a residential district in northern Beijing, is required to wear the device all day for seven days.
The device records someone’s temperature every five minutes. According to China Daily, the device’s corresponding app has access to the phone’s microphone, location, and camera.
Those forced to wear the device have raised concerns about how it monitors the location and what is done with the data collected. The development of the device was a collaboration between the government and Beijing Microchip Sensing Technology, which is backed by China’s tech giant Tencent.
One of the people that received the wristband was Dahongmao, a tech blogger who shared his experience with the device on social media.
“If this bracelet can connect to the internet, it definitely can record my movements and it’s almost like wearing electronic handcuffs. I don’t want to wear it,” he said.
“The issuer said it’s a requirement from higher up and that I shouldn’t make it difficult for her. I said I would not want to make it difficult for her but she could tell those above her that I won’t wear it. If you insist that I wear it, you’ll have to come up with the documents that prove that it’s a Beijing government requirement and that this is not some unlicensed company trying to make a profit.”
China Daily and South China Morning Post were separately told by a Beijing COVID-19 hotline that the use of the devices was at the discretion of the residential community.
Earlier this week, Hong Kong announced it would roll out tracking bracelets to enforce its mandatory one-week home isolation.
The December 2020 resignation of Dr. Deborah Birx, White House Coronavirus Response Coordinator under Trump, revealed predictable hypocrisy. Like so many other government officials around the world, she was caught violating her own stay-at-home order. Therefore she finally left her post following nine months of causing unfathomable amounts of damage to life, liberty, property, and the very idea of hope for the future.
Even if Anthony Fauci had been the front man for the media, it was Birx who was the main influence in the White House behind the nationwide lockdowns that did not stop or control the pathogen but have caused immense suffering and continue to roil and wreck the world. So it was significant that she would not and could not comply with her own dictates, even as her fellow citizens were being hunted down for the same infractions against “public health.”
In the days before Thanksgiving 2020, she had warned Americans to “assume you’re infected” and to restrict gatherings to “your immediate household.” Then she packed her bags and headed to Fenwick Island in Delaware where she met with four generations for a traditional Thanksgiving dinner, as if she were free to make normal choices and live a normal life while everyone else had to shelter in place.
The Associated Press was first out with the report on December 20, 2020.
Birx acknowledged in a statement that she went to her Delaware property. She declined to be interviewed.
She insisted the purpose of the roughly 50-hour visit was to deal with the winterization of the property before a potential sale — something she says she previously hadn’t had time to do because of her busy schedule.
“I did not go to Delaware for the purpose of celebrating Thanksgiving,” Birx said in her statement, adding that her family shared a meal together while in Delaware.
Birx said that everyone on her Delaware trip belongs to her “immediate household,” even as she acknowledged they live in two different homes. She initially called the Potomac home a “3 generation household (formerly 4 generations).” White House officials later said it continues to be a four-generation household, a distinction that would include Birx as part of the home.
So it was all a sleight-of-hand: she was staying home; it’s just that she has several homes! This is how the power elite comply, one supposes.
The BBC then quoted her defense, which echo the pain experienced by hundreds of millions:
“My daughter hasn’t left that house in 10 months, my parents have been isolated for 10 months. They’ve become deeply depressed as I’m sure many elderly have as they’ve not been able to see their sons, their granddaughters. My parents have not been able to see their surviving son for over a year. These are all very difficult things.”
Indeed. However, she was the major voice for the better part of 2020 for requiring exactly that. No one should blame her for wanting to get together with family; that she worked so hard for so long to prevent others from doing so is what is at issue.
The press piled on and she announced that she would be leaving her post and not seeking a position at the Biden White House. Trump tweeted that she will be missed. It was the final discrediting – or should have been – of a person that many in the White House and many around the country had come to see as an obvious fanatic and fake, a person whose influence wrecked the liberties and health of an entire country.
It was a fitting end to a catastrophic career. So it would make sense that people might pick up her new book to find out what it was like to go through that kind of media storm, the real reasons for her visit, what it was like to know for sure that she must violate her own rules in order to bring comfort to her family, and the difficult decision she made to throw in the towel knowing that she has compromised the integrity of her entire program.
One slogs through her entire book only to find this incredible fact: she never mentions this. The incident is missing entirely from her book.
Instead at the moment in the narrative at which she would be expected to recount the affair she says almost in passing that “When former vice president Biden was declared the winner of the 2020 election, I’d set a goal for myself—to hand over responsibility for the pandemic response, with all its many elements, in the best possible place.”
At that point, the book skips immediately to the new year. Done. It’s like Orwell, the story, even though it was reported for days in the world press and became a defining moment in her career, is just wiped out from the history book of her own authorship.
Somehow it makes sense that she would neglect to mention this. Reading her book is a very painful experience (all credit to Michael Senger’s review) simply because it seems to be weaving fables on page after page, strewn with bromides, completely lacking in self awareness, punctuated by revealing comments that make the opposite point of what she is seeking. Reading it is truly a surreal experience, astonishing especially because she is able to maintain her delusionary pose for 525 pages.
Recall that it was she who was tasked – by Anthony Fauci – with doing the really crucial thing of talking Donald Trump into green-lighting the lockdowns that began on March 12, 2020, and continued to their final hard-core deployment on March 16. This was the “15 Days to Flatten the Curve” that turned into two years in many parts of the country.
Her book admits that it was a two-level lie from the beginning.
“We had to make these palatable to the administration by avoiding the obvious appearance of a full Italian lockdown,” she writes. “At the same time, we needed the measures to be effective at slowing the spread, which meant matching as closely as possible what Italy had done—a tall order. We were playing a game of chess in which the success of each move was predicated on the one before it.”
Further:
“At this point, I wasn’t about to use the words lockdown or shutdown. If I had uttered either of those in early March, after being at the White House only one week, the political, nonmedical members of the task force would have dismissed me as too alarmist, too doom-and-gloom, too reliant on feelings and not facts. They would have campaigned to lock me down and shut me up.”
In other words, she wanted to go full CCP just like Italy but didn’t want to say that. Crucially, she knew for sure that two weeks was not the real plan. “I left the rest unstated: that this was just a starting point.”
“No sooner had we convinced the Trump administration to implement our version of a two-week shutdown than I was trying to figure out how to extend it,” she admits.
“Fifteen Days to Slow the Spread was a start, but I knew it would be just that. I didn’t have the numbers in front of me yet to make the case for extending it longer, but I had two weeks to get them. However hard it had been to get the fifteen-day shutdown approved, getting another one would be more difficult by many orders of magnitude. In the meantime, I waited for the blowback, for someone from the economic team to call me to the principal’s office or confront me at a task force meeting. None of this happened.”
It was a solution in search of evidence she did not have. She told Trump that the evidence was there anyway. She actually tricked him into believing that locking down a whole population of people was somehow magically going to make a virus to which everyone would inevitably be exposed somehow vanish as a threat.
Meanwhile, the economy was wrecked domestically and then all over the world, as most governments in the world followed what the US did.
Where did she come up with the idea of lockdowns? By her own report, her only real experience with infectious disease came from her work on AIDS, a very different disease from a respiratory virus that everyone would eventually get but which would only be fatal or even severe for a small cohort, a fact that was known since late January. Still, her experience counted for more than science.
“In any health crisis, it is crucial to work at the personal behavior level,” she says with the presumption that avoidance at all costs was the only goal. “With HIV/AIDS, this meant convincing asymptomatic people to get tested, to seek treatment if they were HIV-positive, and to take preventative measures, including wearing condoms; or to employ other pre-exposure prophylaxis (PrEP) if they were negative.”
She immediately hops to the analogy with Covid. “I knew the government agencies would need to do the same thing to have a similar effect on the spread of this novel coronavirus. The most obvious parallel with the HIV/AIDS example was the message of wearing masks.”
Masks = condoms. Remarkable. This “obvious parallel” remark sums the whole depth of her thinking. Behavior is all that matters. Just stay apart. Cover your mouth. Don’t gather. Don’t travel. Close the schools. Close everything. Whatever happens, don’t get it. Nothing else matters. Keep your immune system as unexposed as possible.
I wish I could say her thought is more complex than that but it is not. This was the basis for lockdowns. For how long? In her mind, it seems like it would be forever. Nowhere in the book does she reveal an exit strategy. Not even vaccines qualify.
From the very beginning, she revealed her epidemiological views. On March 16, 2020 at her press conference with Trump, she summarized her position: “We really want people to be separated at this time.” People? All people? Everywhere? Not one reporter raised a question about this obviously ridiculous and outrageous statement that would essentially destroy life on earth.
But she was serious – seriously deluded not only about how society functions but also about infectious disease of this sort. Only one thing mattered as a metric to her: reducing infections through any means possible, as if she on her own could cobble together a new kind of society in which exposure to air-born pathogens was made illegal.
Here is an example. There was a controversy about how many people should be allowed to gather in one space, as in home, church, store, stadium, or community center. She addresses how she came up with the rules:
The real problem with this fifty-versus-ten distinction, for me, was that it revealed that the CDC simply didn’t believe to the degree that I did that SARS-CoV-2 was being spread through the air silently and undetected from symptomless individuals. The numbers really did matter. As the years since have confirmed, in times of active viral community spread, as many as fifty people gathered together indoors (unmasked at this point, of course) was way too high a number. It increased the chances of someone among that number being infected exponentially. I had settled on ten knowing that even that was too many, but I figured that ten would at least be palatable for most Americans—high enough to allow for most gatherings of immediate family but not enough for large dinner parties and, critically, large weddings, birthday parties, and other mass social events.
She puts a fine point on it: “if I pushed for zero (which was actually what I wanted and what was required), this would have been interpreted as a ‘lockdown’—the perception we were all working so hard to avoid.”
What does it mean for zero people to gather? A suicide cult?
In any case, just like that, from her own thinking and straight to enforcement, birthday parties, sports, weddings, and funerals came to be forbidden.
Here we gain insight into the sheer insanity of her vision. It is nothing short of a marvel that she somehow managed to gain the amount of influence she did.
Notice her above mention of her dogma that asymptomatic spread was the whole key to understanding pandemic. In other words, on her own and without any scientific support, she presumed that Covid was both extremely fatal and had a long latency period. To her way of thinking, this is why the usual tradeoff between severity and prevalence did not matter.
She was somehow certain that the longest estimates of latency were correct: 14 days. This is the reason for the “wait two weeks” obsession. She held onto this dogma throughout, almost like the fictional movie “Contagion” had been her only guide to understanding.
Later in the book, she writes that symptoms mean next to nothing because people can always carry around the virus in their nose without being sick. After all, this is what PCR tests have shown. Instead of seeing that as a failure of PCR, she saw this as a confirmation that everyone is a carrier no matter what and therefore everyone has to lock down because otherwise we’ll deal with a black plague.
Somehow, despite her astonishing lack of scientific curiosity and experience in this area, she gained all influence over the initial Trump administration response. Briefly, she was godlike.
But Trump was not and is not a fool. He must have had some sleepless nights wondering how and why he had approved the destruction of that which he had seen as his greatest achievement. The virus was long here (probably from October 2019), it presented a specific danger to a narrow cohort, but otherwise behaved like a textbook flu. Maybe, he must have wondered, his initial instincts from January and February 2020 were correct all along.
Still, he very reluctantly approved a 30-day extension of lockdowns, entirely on Birx’s urging and with a few other fools standing around. Having given in a second time – still, no one thought to drop an email or make a phonecall for a second opinion! – this seemed to be the turning point. Birx reports that by April 1, 2020, Trump had lost confidence in her. He might have intuited that he had been tricked. He stopped speaking to her.
It would still take another month before he would fully rethink everything that he had approved at her behest.
It made no difference. The bulk of her book is a brag fest about how she kept subverting the White House’s push to open up the economy – that is, allow people to exercise their rights and freedoms. Once Trump turned against her, and eventually found other people to provide good advice like the tremendously brave Scott Atlas – it was five months later when he arrived in an attempt to save the country from disaster – Birx turned to rallying around her inner circle (Anthony Fauci, Robert Redfield, Matthew Pottinger, and a few others) plus assembling a realm of protection outside of her that included CNN reporter Sanjay Gupta and, very likely, the virus team at the New York Times (which gives her book a glowing review).
Recall that for the remainder of the year, the White House was urging normalcy while many states kept locking down. It was an incredible confusion. The CDC was all over the map. I gained the distinct impression of two separate regimes in charge: Trump’s vs. the administrative state he could not control. Trump would say one thing on the campaign trail but the regulations and disease panic kept pouring out of his own agencies.
Birx admits that she was a major part of the reason, due to her sneaky alternation of weekly reports to the states.
After the heavily edited documents were returned to me, I’d reinsert what they had objected to, but place it in those different locations. I’d also reorder and restructure the bullet points so the most salient—the points the administration objected to most—no longer fell at the start of the bullet points. I shared these strategies with the three members of the data team also writing these reports. Our Saturday and Sunday report-writing routine soon became: write, submit, revise, hide, resubmit.
Fortunately, this strategic sleight-of-hand worked. That they never seemed to catch this subterfuge left me to conclude that, either they read the finished reports too quickly or they neglected to do the word search that would have revealed the language to which they objected. In slipping these changes past the gatekeepers and continuing to inform the governors of the need for the big-three mitigations—masks, sentinel testing, and limits on indoor social gatherings—I felt confident I was giving the states permission to escalate public health mitigation with the fall and winter coming.
As another example, once Scott Atlas came to the rescue in August to introduce some good sense into this wacky world, he worked with others to dial back the CDC’s fanatical attachment to universal and constant testing. Atlas knew that “track, trace, and isolate” was both a fantasy and a massive invasion of people’s liberties that would yield no positive public-health outcome. He put together a new recommendation that was only for those who were sick to test – just as one might expect in normal life.
After a week-long media frenzy, the regulations flipped in the other direction.
Birx reveals that it was her doing:
This wasn’t the only bit of subterfuge I had to engage in. Immediately after the Atlas-influenced revised CDC testing guidance went up in late August, I contacted Bob Redfield… Less than a week later, Bob [Redfield] and I had finished our rewrite of the guidance and surreptitiously posted it. We had restored the emphasis on testing to detect areas where silent spread was occurring. It was a risky move, and we hoped everyone in the White House would be too busy campaigning to realize what Bob and I had done. We weren’t being transparent with the powers that be in the White House…
One might ask how the heck she got away with this. She explains:
[T]he guidance gambit was only the tip of the iceberg of my transgressions in my effort to subvert Scott Atlas’s dangerous positions. Ever since Vice President Pence told me to do what I needed to do, I’d engaged in very blunt conversations with the governors. I spoke the truth that some White House senior advisors weren’t willing to acknowledge. Censoring my reports and putting up guidance that negated the known solutions was only going to perpetuate Covid-19’s vicious circle. What I couldn’t sneak past the gatekeepers in my reports, I said in person.
Most of the book consists of her explaining how she headed a kind of shadow White House dedicated to keeping the country in some form of lockdown for as long as possible. In her telling, she was the center of everything, the only person truly correct about all things, given cover by the VP and assisted by a handful of co-conspirators.
Largely missing from the narrative is any discussion of the science gathering outside the bubble she so carefully cultivated. Whereas anyone could have noted the studies pouring out from February onward that threw cold water on her entire paradigm – not to mention 15 years, or make that 50 years, or perhaps 100 years of warnings against such a reaction – from scientists all over the world with vastly more experience and knowledge than she. She cared nothing about it, and evidently still does not.
It’s very clear that Birx had almost no contact with any serious scientist who disputed the draconian response, not even John Iaonnidis who explained as early as March 17, 2020, that this approach was madness. But she didn’t care: she was convinced that she was in the right, or, at least, was acting on behalf of people and interests who would keep her safe from persecution or prosecution.
For those interested, Chapter 8 provides a weird look into her first real scientific challenge: the seroprevalence study by Jayanta Bhattacharya published April 22, 2020. It demonstrated that the infection fatality rate – because infections and recovery was far more prevalent than Birx and Fauci were saying – was more in line with what one might expect from a severe flu but with a much more focused demographic impact. Bhattacharya’s paper revealed that the pathogen eluded all controls and would likely become endemic as every respiratory virus before. She took one look and concluded that he had unnamed “fundamental flaws in logic and methodology” and “damaged the cause of public health at this crucial moment in the pandemic.”
And that’s it: that’s Birx grappling with science. Meanwhile, the article was published in the International Journal of Epidemiology and has over 700 citations. She saw all differences of opinion as an opportunity to go on the attack in order to intensify her cherished commitment to the lockdown paradigm.
Even now, with scientists the world over in outrage, with citizens furious at their governments, with governments falling, with regimes toppling and anger reaching a fevered pitch, while studies pour out by the day showing that lockdowns made no difference and that open societies at least protected their educational systems and economies, she is unmoved. It’s not even clear she is aware.
Birx dismisses all contrary cases such as Sweden: Americans could not take that route because we are too unhealthy. South Dakota: rural and backwater (Birx is still mad that the brave Governor Kristi Noem refused to meet with her). Florida: oddly and without evidence she dismisses that case as a killing field, even though its results were better than California while the population influx to the state sets new records.
Nor is she shaken by the reality that there is not one single country or territory anywhere on the planet earth that benefitted from her approach, not even her beloved China which still pursues a zero-Covid approach. As for New Zealand and Australia: she (probably wisely) doesn’t mention them at all, even though they followed the Birx approach exactly.
The story of the lockdowns is a tale of Biblical proportions, at once evil and desperately sad and tragic, a story of power, scientific failure, intellectual insularity and insanity, outrageous arrogance, feudalistic impulses, mass delusion, plus political treachery and conspiracy. It is real-life horror for the ages, a tale of how the land of the free became a depostic hellscape so quickly and unexpectedly. Birx was at the center of it, confirming all of your worst fears right here in a book anyone can buy. She is so proud of her role that she dares to take all credit, fully convinced that the Trump-hating media will love and protect her perfidies from exposure and condemnation.
There is no getting around Trump’s own culpability here. He never should have let her have her way. Never. It was a case of fallibility matched by ego (he has still not admitted error), but it is a case of enormous betrayal that played off presidential character flaws (like many in his income class, Trump had always been a germaphobe) that ended up wrecking hope and prosperity for billions of people for many years to come.
I’ve tried for two years to put myself in that scene at the White House that day. It’s a hothouse with only trusted souls in small rooms, and the people there in a crisis have the sense that they are running the world. Trump might have drawn on his experience running a casino in Atlantic City. The weather forecasters come to say a hurricane is on the way, so he needs to shut it down. He doesn’t want to but agrees in order to do the right thing.
Was this his thinking? Perhaps. Perhaps too someone told him that China’s President Xi Jinping managed to crush the virus with lockdowns so he can too, just as the WHO said in its February 26 report. It’s also difficult in that environment to avoid the rush of omnipotence, temporarily oblivious to the reality that your decision would affect life from Maine to Florida to California. It was a catastrophic and lawless decision based on pretense and folly.
What followed seems inevitable in retrospect. The economic crisis, inflation, the broken lives, the desperation, the lost rights and lost hopes, and now the growing hunger and demoralization and educational losses and cultural destruction, all of it came in the wake of these fateful days. Every day in this country, even two and a half years later, judges are struggling to regain control and revitalize the Constitution after this disaster.
The plotters usually admit it in the end, taking credit, like criminals who cannot resist returning to the scene of the crime. This is what Dr. Birx has done in her book. But there are clearly limits to her transparency. She never explains the real reason for her resignation – even though it is known the world over – pretending like the entire Thanksgiving fiasco never happened and thus attempting to write it out of the history book that she wrote.
There is so much more to say and I hope this is one review of many because the book is absolutely packed with shocking passages. And yet her 525-page book, now selling at a 50% discount, does not contain a single citation to a single scientific study, paper, monograph, article, or book. It has zero footnotes. It offers no go-to authorities and displays not even a hint of humility that would normally be part of any actual scientific account.
And it nowhere offers an honest reckoning for what her influence over the White House and the states foisted on this country and on the world. As the country masks up yet again for a new variant, and is gradually being groomed for another round of disease panic, she can collect whatever royalties come from sales of her book while working at her new gig, a consultant to a company that makes air purifiers (ActivePure). In this latter role, she makes a greater contribution to public health than anything she did while she held the reins of power.
Jeffrey A. Tucker is Founder and President of the Brownstone Institute and the author of many thousands of articles in the scholarly and popular press and ten books in 5 languages, most recently Liberty or Lockdown. He is also the editor of The Best of Mises.
Pfizer’s Paxlovid was granted emergency use authorization to treat mild to moderate COVID-19 in December 2021.1 The drug consists of nirmatrelvir tablets — the antiviral component — and ritonavir tablets, which are intended to slow the breakdown of nirmatrelvir.2
What started out as a slow rollout — only 40,000 or fewer prescriptions were written for the drug in the U.S. each week through April 2022 — has gained steam, with more than 160,000 Paxlovid prescriptions now being issued each week.3 As of June 30, 2022, 1.6 million courses of Paxlovid have been prescribed in the U.S. since its emergency use approval in December.4
Yet, this increase in prescribing could be contributing to one of the significant downfalls of the drug — the creation of selective pressure on SARS-CoV-2, which promotes mutations that could make it resistant to the drug.5 The U.S. Centers for Disease Control and Prevention also issued a warning to health care providers and public health departments about the potential for COVID-19 rebound after Paxlovid treatment.6
This recently happened to Dr. Anthony Fauci, director of the U.S. National Institute of Allergy and Infectious Diseases (NIAID), who experienced a return of COVID-19 symptoms after taking Paxlovid. He then took a second course of the drug, which could trigger even more mutations in the virus.
Paxlovid Triggers Fauci’s COVID-19 Rebound
Fauci said he tested positive for COVID-19, with only minimal symptoms. As his symptoms increased, he took Paxlovid for five days, after which he tested negative for three consecutive days. On the fourth day of testing, he tested positive for COVID-19 again, with symptoms worse off than they were the first time.
“It was sort of what people are referring to as a Paxlovid rebound,” he said. “… Over the next day or so I started to feel really poorly, much worse than in the first go around.”7 He was then prescribed a second course of Paxlovid.
On June 30, he stated, “I went back on Paxlovid, and right now I am on my fourth day of a five-day course of my second course of Paxlovid. Fortunately, I feel reasonably good. I mean, I’m not completely without symptoms, but I certainly don’t feel acutely ill.”8 In the CDC’s health advisory regarding COVID-19 rebound after Paxlovid treatment it’s stated:9
“Recent case reports document that some patients with normal immune response who have completed a 5-day course of Paxlovid for laboratory-confirmed infection and have recovered can experience recurrent illness 2 to 8 days later, including patients who have been vaccinated and/or boosted …
These cases of COVID-19 rebound had negative test results after Paxlovid treatment and had subsequent positive viral antigen and/or reverse transcriptase polymerase chain reaction (RT-PCR) testing.”
COVID-19 Still Spreads During Paxlovid Rebound
People who take Paxlovid can still transmit COVID-19 to others, even if they’re asymptomatic, according to a preprint study.10 Study author Dr. Michael Charness of the Veterans Administration Medical Center in Boston told CNN, “People who experience rebound are at risk of transmitting to other people, even though they’re outside what people accept as the usual window for being able to transmit.”11
The CDC12 and Pfizer13 have suggested that sometimes COVID-19 naturally comes back after a person tests negative, implying that COVID-19 rebound is spontaneous and not necessarily linked to Paxlovid. However, Charness and colleagues didn’t find this to be the case. When they analyzed 1,000 cases of COVID-19 diagnosed among members of the National Basketball Association — none of whom took Paxlovid — no cases of COVID-19 rebound were found.14
Research published in Clinical Infectious Diseases15 looked into why Paxlovid may be leading to rebound symptoms and suggests it could be the result of insufficient exposure to the drug.16 “Not enough of the drug was getting to infected cells to stop all viral replication,” UC San Diego Health reported. “They suggested this may be due to the drug being metabolized more quickly in some individuals or that the drug needs to be delivered over a longer treatment duration.”17
Pfizer Seeks FDA Approval for Paxlovid
Despite the many questions regarding Paxlovid’s association with rebound infections, Pfizer is moving ahead and seeking full approval of the drug from the FDA.18 The drug’s emergency use authorization restricts who the drug can be sold and marketed to. Once full FDA approval is granted, Pfizer can market the drug directly to consumers.
Paxlovid’s emergency use authorization allows it to be prescribed for adults and children ages 12 and older who are at high risk for progression to severe COVID-19.19 Pfizer estimates that up to 60% of the U.S. population meets these criteria and has at least one risk factor for severe illness, such as obesity or diabetes, making them eligible for the drug.20
However, concerns have risen over whether Paxlovid, which is said to cut the risk of hospitalization or death by 86% in high-risk patients, when taken within five days of symptoms starting,21 is effective in people who are not high-risk.
In fact, Pfizer stopped a large trial of Paxlovid in standard-risk patients because it didn’t show significant protection against hospitalization or death in this group.22 According to a news release from Pfizer:23
“In previously reported interim analyses, the company disclosed that the novel primary endpoint of self-reported, sustained alleviation of all symptoms for four consecutive days was not met, and a non-significant 70% relative risk reduction was observed in the key secondary endpoint of hospitalization or death (treatment arm: 3/428; placebo: 10/426).
An updated analysis from 1,153 patients enrolled through December 2021 showed a non-significant 51% relative risk reduction (treatment arm: 5/576; placebo: 10/569). A sub-group analysis of 721 vaccinated adults with at least one risk factor for progression to severe COVID-19 showed a non-significant 57% relative risk reduction in hospitalization or death (treatment arm: 3/361; placebo: 7/360).”
Is Paxlovid Triggering SARS-CoV-2 Mutations?
Initial reports have suggested that SARS-CoV-2 is not mutating and becoming resistant to Paxlovid, but some experts believe it’s only a matter of time before this occurs — and emerging research suggests it’s already happened.
David Ho, a virologist at the Aaron Diamond AIDS Research Center at Columbia University, was among the first to document resistance mutations in HIV 30 years ago and believes the same may be coming with SARS-CoV-2.24 He’s also experienced post-Paxlovid COVID-19 rebound firsthand. Bloomberg reported:25
“Ho said he came down with COVID on April 6 … His doctor prescribed Paxlovid, and within days of taking it, his symptoms dissipated and tests turned negative. But 10 days after first getting sick, the symptoms returned and his tests turned positive for another two days.
Ho said he sequenced his own virus and found that both infections were from the same strain, confirming that the virus had not mutated and become resistant to Paxlovid. A second family member who also got sick around the same time also had post-Paxlovid rebound in symptoms and virus, Ho says.
‘It surprised the heck out of me,’ he said. ‘Up until that point I had not heard of such cases elsewhere.’ While the reasons for the rebound are still unclear, Ho theorizes that it may occur when a small proportion of virus-infected cells may remain viable and resume pumping out viral progeny once treatment stops.”
Studies Show COVID-19 Virus Developing Paxlovid Resistance
Two separate studies cultured SARS-CoV-2 in a lab and exposed it to low levels of nirmatrelvir, which would kill some, but not all, of the virus. “Such tests are meant to simulate what might happen in an infected person who doesn’t take the whole regimen of the drug or an immunocompromised patient who has trouble clearing the virus,” Science reported.26
One of the studies revealed that SARS-CoV-2 developed three mutations after 12 rounds of nirmatrelvir treatment — “at positions 50, 166 and 167 in the string of amino acids that make up MPRO.”27 The mutations amounted to a 20-fold reduction in the virus’ susceptibility to nirmatrelvir.28 The other study29 also found mutations at positions 50 and 166, revealing that when they occurred together, SARS-CoV-2 became 80 times less susceptible to nirmatrelvir. According to the study:30
“Reverse genetic studies in a homologous infectious cell culture system revealed up to 80-fold resistance conferred by the combination of substitutions L50F and E166V. Resistant variants had high fitness increasing the likelihood of occurrence and spread of resistance.”
Lead study author Judith Margarete Gottwein with the University of Copenhagen told Science, “This tells us what mutations we should be looking for [in patients].”31 Ho, who was not involved in these studies, agreed that it appeared mutations were an inevitable outcome.
He told Science, “when you put pressure on the virus it escapes … Given the amount of infections out there, it’s going to come.”32 It’s also completely unknown what may happen when two courses of Paxlovid are taken in quick succession to treat COVID-19 rebound — as occurred with Fauci. It’s possible that ever-mutating COVID-19 variants could be created.
Other antivirals on the market to treat COVID-19 have also led to concerns over mutations. Molnupiravir (sold under the brand name Lagevrio) was developed by Merck and Ridgeback Therapeutics and approved by the FDA for emergency use December 23, 2021, for high-risk patients with mild to moderate COVID symptoms.
However, not only might it contribute to cancer and birth defects, it may also supercharge the rate at which the virus mutates inside the patient, resulting in newer and more resistant variants.33
Other Early COVID-19 Treatments Ignored
Using drugs that cause high rates of organ failure, like remdesivir, and drugs that cause the virus to rebound with a vengeance, like Paxlovid, and potentially trigger mutations don’t seem to be in the best interest of public health. The fact that U.S. health authorities have focused on these drugs to the exclusion of all others, including older drugs with high rates of effectiveness and superior safety profiles, sends a very disturbing message.
An investigation by Cornell University, posted on the University’s preprint server January 20, 2022, found ivermectin outperformed 10 other drugs against COVID-19, making it the most effective against the Omicron variant.34 It even outperformed Paxlovid, yet it’s been vilified by health officials and mainstream media.
Remdesivir costs between $2,340 and $3,120,35 and nirmatrelvir costs $529 per five-day treatment,36 while the average treatment cost for ivermectin is $58.37 Do you think this has anything to do with ivermectin’s vilification?
Paxlovid alone has cost U.S. taxpayers $5.29 billion,38 while safe and less expensive options exist. Dr. Pierre Kory, who is part of the group that formed the Front Line COVID-19 Critical Care Working Group (FLCCC) to advance early treatments for COVID-19, pleaded with the U.S. government early on in the pandemic to review the expansive data on ivermectin to prevent COVID-19, keep those with early symptoms from progressing and help critically ill patients recover — to no avail.39,40
However, if you’d like to learn more about its potential uses for SARS-CoV-2, FLCCC’s I-MASK+ protocol can be downloaded in full,41 giving you step-by-step instructions on how to prevent and treat the early symptoms of COVID-19.
‘Boris’ Johnson loyalist Nadine Dorries appears to have admitted that the Government, which now prides itself on having imposed restrictions more lightly than others, considered tearing “mothers and fathers and families and children” from their homes if they ‘tested positive’ for Covid during lockdowns to be sent to isolation centres.
A health minister at the time, Ms Dorries was approached by former Health Secretary Jeremy Hunt and told to adopt this ‘zero Covid’ approach, she told GB News.
The now-Culture Secretary told Dan Wootton, who decided not to dig deeper into the claims:
“[Jeremy] said ‘you’ve got to speak to Matt [Hancock]’. It was at the time Nightingale hospitals were being built. ‘You’ve got to tell him that you don’t put sick people in the hospitals, you follow a “zero Covid” policy… When someone tests positive, you take them from their home and you take them to an isolation centre and you leave them there… That’s the only way you can beat Covid.’”
Ms Dorries said she responded:
“‘The British public will not stand for mothers and fathers and families and children being removed from their family and their home and put in isolation.’ He said: ‘Who said they won’t?’ I said: ‘The behaviour and insights team who I’ve discussed this with. They won’t wear it.’” (My emphasis – video below)
This is quite revealing. Anyone with an ounce of humanity would have rejected this outright, whether they thought the public would accept it or not.
Remember, also, that those officials in SAGE believed the British people wouldn’t accept being ‘locked down’ at all until Italy made it clear that they would.
Professor Neil Ferguson told The Times in December 2020:
“[China] is a communist one party state, we said. We couldn’t get away with it in Europe, we thought… and then Italy did it. And we realised we could.”
So has Ms Dorries revealed that the only reason we weren’t pulled away from our families after seeing two red lines was because other Europeans weren’t first?
Hong Kong is set to introduce electronic tracking bracelets for citizens who decide to quarantine at home after testing positive for Covid-19, the health chief has announced. Violators of the isolation rules face hefty fines and possibly even jail time.
The territory’s secretary for health, Lo Chung-mau, announced the move during a Monday press briefing, saying the bracelets are meant to stop infected people from spreading the illness further and will operate on the ‘Leave Home Safe’ app rolled out last year.
“We have to make sure that home isolation is more precise while being humane,” Lo said, adding that the trackers will be introduced on Friday.
Breaching Hong Kong’s quarantine order could result in fines up to $3,200 and a maximum of six months behind bars. Individuals who are able to isolate at home must do so for two weeks, though will be allowed to leave if they test negative for two days in a row and have their first pair of vaccine doses.
While the territory previously required overseas arrivals to use bracelets with unique QR codes to check in and account for their movements, the gadgets were later replaced with genuine tracking tech. The system is set to be expanded, though the government has not said what type of bracelet it will use for the latest initiative.
The health secretary also noted that Hong Kong will implement a color-coded system similar to the one in place in mainland China, which labels different levels of infection risk as yellow or red. Those with the red designation will face heavy restrictions on their movement, including outright bans on entering public venues, while yellow entails lesser limits.
However, the city’s recently inaugurated chief executive, John Lee, has since stressed that the traffic light system would only apply to “a specific and small number of people,” but nonetheless argued that Hong Kong needs “some identification method” to distinguish citizens with active infections from those quarantining as a precaution.
Local officials continue to warn that Hong Kong’s Covid-19 outbreak remains “very serious,” urging residents to minimize travel and observe social distancing rules, which were just extended for another two weeks on Tuesday.
The Department of Health said it recorded 2,558 new local coronavirus cases on Tuesday, as well as another 211 infections among travelers from abroad. It did not offer a daily update for fatalities, but noted the territory had tallied 9,420 deaths in total throughout the pandemic, most of them occurring this year.
By portraying Chinese characters as perpetrators of ruthless violence while casting Japanese Self-Defense Forces (SDF) intelligence operatives as defenders, the season 2 of the Japanese drama Vivant has recently drawn criticism from Chinese netizens, who argue that its depiction turns historical reality on its head while ignoring Japan’s wartime atrocities.
The TBS drama series – a spy suspense story in which an alleged unofficial intelligence unit of the SDF operates across the globe — has attracted a passionate fanbase. Its currently airing season 2 opened with a household rating of 18.8 percent, the highest for a TV drama this year, according toa commentary article by Japanese media Toyo Keizai.
What draws attention is the portrayal of the enemies in the series, the article noted. Scenes in which the Chinese organization subjects kidnapped members of the SDF unit to brutal torture are repeated with unrelenting intensity.
It is rare for Japanese TV dramas to explicitly portray a real-life country as the enemy, the article noted.
Japanese Prime Minister Sanae Takaichi also made a reference to the drama, saying that she has been recording Vivant and hopes to binge-watch it over the year-end and New Year holidays, according to Japanese media outlets.
China’s CCTV News report on Sunday revealed that the drama features scenes in which Chinese personnel cut off the fingers of and stab Japanese intelligence operatives in the abdomen. Such acts bear striking similarities to the torture inflicted on Chinese nationals by invading Japanese troops during the World War II.
The drama distorts the truth by attributing these atrocities to modern Chinese characters. Beneath the surface, it subtly glorifies Japan’s cross-border overseas operations, blurs the functional boundaries of the SDF and implicitly promotes an expansionist narrative, per CCTV News. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.