Recipients of repeated COVID-19 mRNA vaccinations may have fully damaged their immune system’s capacity to protect them from severe effects from the disease. Each successive booster shot may actually worsen protection.
But now new mice research (Gao et al., 2022) provides damning evidence that continued COVID-19 booster vaccinations “negatively impact the immune response” and “fully impair the… neutralizing efficacy” of COVID-19 antibodies and memory.
Scientists warn that continuing the course of booster COVID-19 mRNA vaccinations may pose risks of “enhanced disease severity” for those re-infected with COVID-19 and thus the administration of boosters “should be preceded with caution.”
“Our findings revealed that repeated dosing after the establishment of vaccine response might not further improve the antigen-specific reactivity; instead, it could cause systematic tolerance and inability to generate effective humoral and cellular immune responses to current SARS-CoV-2 variants.”
In other words, health authorities have mandated young people get a shot that may fully impair their immune system’s capacity to protect them from the very variants the shots were intended to neutralize.
Covid mRNA vaccines are “clearly the most failing medical product in the history of medical products, both in terms of efficacy and safety” and should be withdrawn immediately as they cause “an unprecedented level of harm including the death of young people and children”, a top drug safety expert has said.
Professor Retsef Levi, an expert in analytics, risk management and health systems at Massachusetts Institute of Technology, released a video this morning where he set out the alarming findings of his investigations and how they have been completely ignored by the Israeli Government. The video was tweeted by leading cardiologist Dr. Aseem Malhotra.
There follows a complete transcript of Professor Levi’s video.
Hi. My name is Retsef Levi, and since 2006 I’ve been a faculty member at MIT in Cambridge, Massachusetts. I have more than 30 years of experience as a practitioner and an academic in using data analytics to assess and manage risk, particularly in the context of health systems and health policies, as well as the management of safety and quality of manufacturing of biological products.
I’m filming this video to share my strong conviction that at this point in time all COVID-19 mRNA vaccination programmes should stop immediately. They should stop because they completely fail to fulfil any of their advertised promises regarding efficacy. And more important they should stop because of the mounting and indisputable evidence that they cause an unprecedented level of harm, including the death of young people and children.
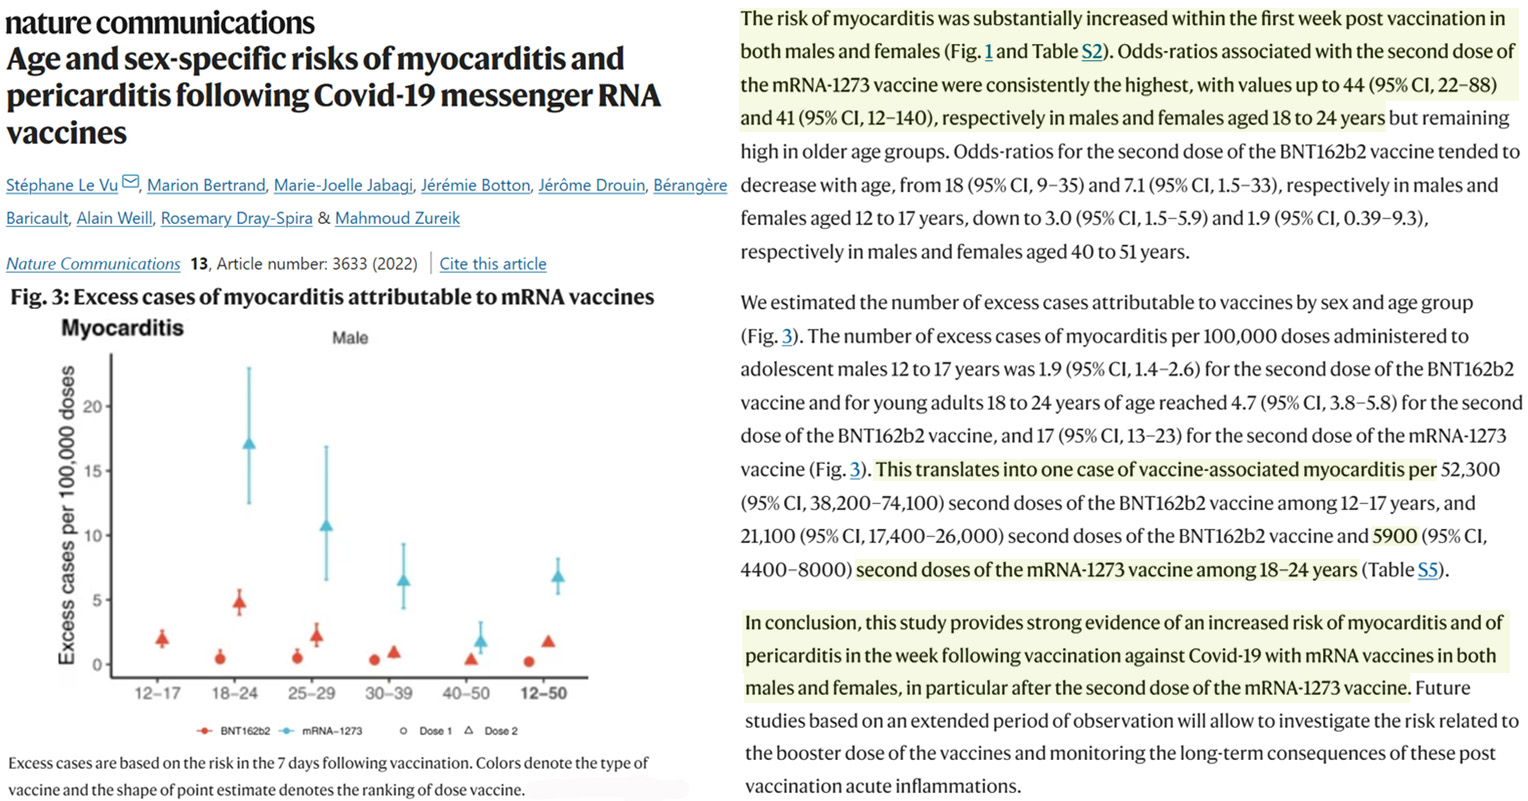
I personally became concerned with the vaccine safety around the middle of 2021, when it became known that the mRNA vaccines cause myocarditis, an inflammation of the heart.
Since myocarditis is known to be hard to diagnose, because it often has vague symptoms or can even be subclinical with no symptoms – it’s also known to be a frequent cause of out-of-hospital sudden cardiac arrest, especially among young people – I was very concerned that it will not be detected by the existing vaccine safety surveillance systems.
Motivated by that, we decided to analyse the Israel national EMS [emergency services] data to see if there are any signals of increased out-of-hospital adverse events. The analysis of the EMS cause and diagnosis data from 2019 throughout the first half of 2021 revealed some very concerning signals. We detected an increase of 25% in the cause ‘with cardiac arrest’ diagnosis among ages 16-39 in the first half of 2021, exactly when the vaccination campaign in Israel was launched. A smaller increase was also detected in the older ages. Moreover, we also detected a statistically significant temporal correlation between the number of the Pfizer vaccine doses administered to this population and the number of EMS calls with cardiac arrest diagnosis.
Interestingly, we did not find any statistically significant correlation with the number of COVID-19 infections during this period of time. While this is not a proof of causal relationship, it left us very concerned, especially given the known suspected mechanism. And we called for an immediate thorough investigation by the Israeli Ministry of Health to investigate what are the underlying causal mechanisms of this observed increase in the cardiac arrest calls.
Unfortunately, to the best of my knowledge, such thorough investigation was never conducted. By now I believe that the cumulative evidence is conclusive and confirms our concern that the mRNA vaccines indeed cause sudden cardiac arrest as a sequel of vaccine-induced myocarditis. And this is potentially only one mechanism by which they cause harm. Data from the U.K., Scotland and Australia replicate the data from Israel. Additional data from Israel indicate that in 2021 the EMS service in Israel conducted more than 3,000 more resuscitations compared to 2019, which amounts to an increase of 27%.
Two prospective studies from Thailand and Switzerland in which vaccinees were tested before and after they received the vaccine indicate that the rates of heart damage are likely to be significantly higher than the rates detected by clinical diagnosis. This is exactly the same finding that the U.S. military found in 2015 when it conducted a similar study on the smallpox vaccine. Another study from Harvard Medical School detected in the blood of children with vaccine-induced myocarditis an entire spike [protein], which is another indication of the underlying mechanism of harm, but in fact has even broader implications about the safety of the vaccine given the repeated evidence that we have that the mRNA and the lipids are actually penetrating the blood system.
And finally, autopsies of people that die closely after they receive the vaccine indicate that with the enlarged number of cases, there is strong evidence that the death was caused by vaccine-induced myocarditis.
So presented with all of this evidence, I think that there is no other ethical or scientific choice but to pull out of the market these medical products and stop all the mRNA vaccination programmes. This is clearly the most failing medical product in the history of medical products, both in terms of efficacy and safety. And we need to investigate and think hard: How did we end up in a situation that it’s also the most profitable medical product in the history of medical products?
Will Thailand become the first country to take Pfizer to court claiming fraud and declare the contracts null and void?
Professor Sucharit Bhakdi seems to think so. He claims to have talked to officials high up in government and told them that the contracts were fraudulent. According to him, the Thais want to be the first country in the world to declare the contracts null and void. If this goes ahead and found to be true in the courts, it will mean a significant sum of damages will have to be paid by Pfizer and set off a chain of events that will likely bankrupt the company.
23 days after the Thai King’s daughter had her booster, she collapsed and is still in a coma. Officially she has a bacterial infection but many claim she is the victim of vaccine damage. If the Thais do take Pfizer to court, will this have been the reason?
The National Institute of Health’s grant AI23946-08 issued to Dr. Ralph Baric at the University of North Carolina at Chapel Hill (officially classified as affiliated with Dr. Anthony Fauci’s NIAID by at least 2003) began the work on synthetically altering the Coronaviridae (the coronavirus family) for the express purpose of general research, pathogenic enhancement, detection, manipulation, and potential therapeutic interventions targeting the same. As early as May 21, 2000, Dr. Baric and UNC sought to patent critical sections of the coronavirus family for their commercial benefit.1 In one of the several papers derived from work sponsored by this grant, Dr. Baric published what he reported to be the full length cDNA of SARS CoV in which it was clearly stated that SAR CoV was based on a composite of DNA segments. “Using a panel of contiguous cDNAs that span the entire genome, we have assembled a full-length cDNA of the SARS-CoV Urbani strain, and have rescued molecularly cloned SARS viruses (infectious clone SARS-CoV) that contained the expected marker mutations inserted into the component clones.”2 On April 19, 2002 – the Spring before the first SARS outbreak in Asia – Christopher M. Curtis, Boyd Yount, and Ralph Baric filed an application for U.S. Patent 7,279,372 for a method of producing recombinant coronavirus. In the first public record of the claims, they sought to patent a means of producing, “an infectious, replication defective, coronavirus.” This work was supported by the NIH grant referenced above and GM63228.
In short, the U.S. Department of Health and Human Services was involved in the funding of amplifying the infectious nature of coronavirus between 1999 and 2002 before SARS was ever detected in humans.
This dossier is by no means exhaustive. It is, however, indicative the numerous criminal violations that may be associated with the COVID-19 terrorism.
Scientists are scrambling to explain why the continent of Antarctica has shown Net Zero warming for the last seven decades and almost certainly much longer. The lack of warming over a significant portion of the Earth undermines the unproven hypothesis that the carbon dioxide humans add to the atmosphere is the main determinant of global climate.
Under ‘settled’ science requirements, the significant debate over the inconvenient Antarctica data is of necessity being conducted well away from prying eyes in the mainstream media. Promoting the Net Zero political agenda, the Guardian recently topped up readers’ alarm levels with the notion that “unimaginable amounts of water will flow into oceans”, if temperatures in the region rise and ice buffers vanish. The BBC green activist-in-chief Justin Rowlatt flew over parts of the region and witnessed “an epic vision of shattered ice”. He described Antarctica as the “frontline of climate change”. In 2021, the South Pole had its coldest six-month winter since records began in 1957, a fact largely ignored in the mainstream. One-off bad weather promoter Reuters subsequently ‘fact checked’ commentary on the event in social media. It noted that a “six-month period is not long enough to validate a climate trend”.
A recent paper from two climate scientists (Singh and Polvani) accepts that Antarctica has not warmed in the last seven decades, despite an increase in the atmospheric greenhouse gases. It is noted that the two polar regions present a “conundrum” for understanding present day climate change, as recent warming differs markedly between the Arctic and Antarctic. The graph below shows average Antarctica surface temperatures from 1984-2014, compared to a base period 1950-1980.
The scientists note that over the last seven decades, the Antarctica sea ice area has “modestly expanded” and warming has been “nearly non-existent” over much of the ice sheet. NASA estimates current Antarctica ice loss at 147 gigatons a year, but with 26,500,000 gigatons still to go, this works out at annual loss of 0.0005%. At current NASA ice loss melt, it will all be gone in about 200,000 years, although the Earth may well have gone through another ice age, or two, before then.
Most alarmist commentary centres around the cyclical loss of sea ice around the coast and some warming on parts of the west of the continent. But sea ice cover is running at levels seen around 50 years ago, as the graph below shows. Small rises and falls in the early 2010s have been followed by a reversion to the mean.
The warmth to the west, seen in the first graph, could have been caused by any number of natural localised events including warmer oceanic waters and the effects of under-water volcanic activity. It has, of course, attracted widespread alarmist interest – in particular, the fate of the Thwaites ice stream, also known as the ‘Doomsday Glacier’. However, recently a group of oceanographers discovered that Florida-sized Thwaites had retreated at twice the rate in the past, when human-caused CO2 could not have been a factor. The retreat could have occurred centuries ago and is said to have been “exceptionally fast”.
Much of climate science today seems to suffer from confirmation bias. Few grants are available to those who don’t start with the premise that the climate is changing mostly, or entirely, due to humans burning fossil fuel. But many present, historic and paleo climate observations fail to establish a clear connection between temperatures and CO2 levels. In the past, the life-enhancing gas has occupied a space in the atmosphere up to 20 times higher, without evidence of huge temperature rises.
Singh and Polvani’s explanation for expected warming in Antarctica is the depth of the continent’s ice. To this end, they use two climate models that purport to show that the “high ice sheet orography” robustly decreases the climate sensitivity to extra CO2, and that “a flattened Antarctic ice sheet would experience significantly greater surface warming than the present-day Antarctica ice sheet”. This conclusion comes from computer models, but later in the paper is an admission that they fail to agree on significant matters. It is revealed that one of the models predicts less sea ice retreat in a flattened Antarctica when CO2 doubles, and the other one, more retreat.
In the science blog No Tricks Zone there has been an interesting debate on the lack of Antarctica warming. It was noted that NASA also tends to support the role of higher elevation of the ice as an explanation. For the rest of the world, states NASA, “the greenhouse effect still works as expected”. The average ice thickness in Antarctica is about 2,160 metres and compares with Greenland at around 1,600. The fact that Greenland has warmed of late might lead to the cynical observation that Antarctica has the wrong type of ice. One correspondent summarised the paper as the “lack of warming in spite of greenhouse gases is the wrong conclusion. The lack of warming is because of the increased greenhouse gases.” Another sighting, it would appear, of the old chestnut, “global cooling is caused by global warming”.
The science, as always, must be out. Attempting to connect every natural variation in weather and long-term climate to just one trace gas produced by humans leads to some unconvincing explanations, not least when climate models are involved.
Chris Morrison isthe Daily Sceptic’s Environment Editor.
A shadowy unit of the British Army, as well as secretive ‘disinformation’ agencies within Whitehall, spied on British citizens who challenged the Government’s pandemic response, including Peter Hitchens and me. These revelations are contained in a report by Big Brother Watch due to be published tomorrow, which includes the results of subject access and freedom of information requests submitted by me and others. The Mail on Sundayhas more.
A shadowy Army unit secretly spied on British citizens who criticised the Government’s Covid lockdown policies, The Mail on Sunday can reveal.
Military operatives in the UK’s ‘information warfare’ brigade were part of a sinister operation that targeted politicians and high-profile journalists who raised doubts about the official pandemic response.
They compiled dossiers on public figures such as ex-Minister David Davis, who questioned the modelling behind alarming death toll predictions, as well as journalists such as Peter Hitchens and Toby Young. Their dissenting views were then reported back to No. 10.
Documents obtained by the civil liberties group Big Brother Watch, and shared exclusively with this newspaper, exposed the work of Government cells such as the Counter Disinformation Unit, based in the Department for Digital, Culture, Media and Sport, and the Rapid Response Unit in the Cabinet Office.
But the most secretive is the MoD’s 77th Brigade, which deploys ‘non-lethal engagement and legitimate non-military levers as a means to adapt behaviours of adversaries’.
According to a whistleblower who worked for the brigade during the lockdowns, the unit strayed far beyond its remit of targeting foreign powers.
They said that British citizens’ social media accounts were scrutinised – a sinister activity that the Ministry of Defence, in public, repeatedly denied doing.
Papers show the outfits were tasked with countering ‘disinformation’ and ‘harmful narratives… from purported experts’, with civil servants and artificial intelligence deployed to ‘scrape’ social media for keywords such as ‘ventilators’ that would have been of interest.
The information was then used to orchestrate Government responses to criticisms of policies such as the stay-at-home order, when police were given power to issue fines and break up gatherings.
It also allowed Ministers to push social media platforms to remove posts and promote Government-approved lines.
How did the Government manage to convince these supposedly independent state agencies, with powers to monitor the activities of British citizens, that critics of its barmy lockdown policy were enemies of the state? And does this mean James Delingpole has been right all along? We will discuss tomorrow on London Calling and I’m going to write about it for this week’s Spectator.
This letter has been signed by Dr. Rachel Corbett, Dr. George Fareed, Dr. Melanie Gisler, Dr. Brian Hooker, Dr. Pierre Kory, Dr. Katarina Lindley, Dr. James Lyons-Weiler, Dr. Robert Malone, Dr. Peter McCullough, Dr. Liz Mumper, Dr. Meryl Nass, Dr. David Rasnick, Dr. Richard Urso and hundreds more physicians, scientists and medical professionals.
The original authors are Michael Kane and Meryl Nass, M.D., and it is being distributed by Children’s Health Defense. Medical and scientific professionals can sign the letter, which is a basic statement of principles that should be at the core of medicines but which have sidelined or violated since the beginning of the crisis.
Executive Summary
There is no scientific rationale for continuing any COVID-19 mandates in 2023 and beyond.
Mask and vaccine exemptions must be offered at the discretion of the physician and patient as opposed to one-size-fits-all government edicts.
Parental rights and decisions must be preserved to ensure the health and well-being of their children.
The ability of medical professionals to speak freely to their patients and the public must not be compromised.
Informed consent is the basis of medical ethics. Shared decision-making is a model of the patient-physician relationship that is considered the most desirable by both the US and UK government health establishments. Patients want to make their own medical decisions, and they have the legal right to do so. They expect their physicians to share knowledge with their patients to inform the best choices.
The corollary to informed consent is that medical decisions ought to be made by individual patients based on their individual situation and personal best interest. ‘One-size-fits-all’ medicine is incongruent with these principles. It denies informed consent and personal autonomy.
During the last three years, we have experienced unprecedented interference with the doctor-patient relationship by the government. Considerable financial incentives were paid to medical industries and medical providers to offer certain treatments and to refuse others.
When financial incentives did not achieve universal vaccination, mandates were imposed. One way this was done was by requiring COVID-19 vaccinations for healthcare workers whose employers received Medicare payments after we had learned that vaccinations did not protect patients or coworkers from infection.
Grants to school districts were conditioned on mask mandates in schools. These newly imposed incentives, and punishments for noncompliance, fly in the face of long-established medical ethics, especially informed consent and shared decision-making. They must end.
COVID-19 Mandates
There is general agreement that all available COVID-19 vaccines fail to prevent viral transmission and only briefly reduce cases. After several months, people who are vaccinated become more susceptible to COVID-19 infections than the unvaccinated. Therefore, mandates for COVID-19 vaccines are scientifically and logically indefensible.
In response, the Centers for Disease Control and Prevention (CDC) adapted its guidelines for managing COVID-19, quietly suggesting that both vaccinated and unvaccinated Americans should be treated identically with respect to isolation, quarantining and testing. Yet the CDC continues to exhort Americans to receive more COVID-19 vaccine booster doses and supports federally imposed vaccine mandates.
Essentially everyone in our country has been exposed to COVID-19 by now, and nearly everyone has been infected at least once. We can anticipate that the US will continue to face evolving COVID-19 variants, but we can also anticipate that COVID-19’s severity will keep weakening over time.
Yet patients and doctors are still not permitted to choose the COVID-19 therapies best suited to each patient. Mandates must end, and patients and doctors must reassert their human and legal rights to determine the medical care each patient receives.
Vaccine and Mask Exemptions
Patients are individuals. They experience different risks from vaccinations and may have medical or psychological issues that preclude safe masking. Pretending that these differences don’t exist is denying reality. Historically, doctors were able to issue waivers for masks and vaccinations, as they were considered to have the best knowledge and judgment to issue such waivers.
Although every state by law accepts that doctors can issue medical waivers for vaccines and masks, many health and education departments have started nullifying these waivers, superseding physician authority. States have also been investigating and punishing doctors for issuing medical waivers. It appears that federal and state governments want to make themselves the arbiters of these medical decisions. This must not stand.
Parental Rights
States decide on the age of consent, and until that age is reached, parents are wholly responsible for their children, with a few limited exceptions. But during the past two years, we have seen a dangerous trend. State requirements that parents must consent to vaccinations given to their underage children are being ignored in multiple jurisdictions. This happened in Washington, DC, for children ages 11 and older by order of the Mayor and City Council. The law they passed kept the fact that their children had a medical procedure secret from the parents. While Congress, which oversees the law in the District of Columbia, could have said no, it instead failed to act. A lawsuit challenging this law was won in November 2021, so the law no longer stands in DC.
However, in Philadelphia, PA, San Francisco, CA and Kings County, WA, the local health officers issued guidelines in early 2021 allowing local medical providers to vaccinate children as young as age 12 without parental permission, which still stand.
This is a dangerous usurpation of parental rights by local public health authorities. It also violates state and federal law. Furthermore, there has been a recent accompanying trend by ‘medico-legal’ professionals to assert in published journal articles that 12-year-olds have the maturity to decide on their own medical procedures.
Most states don’t allow children to consent to use tanning salons or get tattoos below the age of consent. To bypass parents and allow underage children to decide what gets injected into them is inconsistent with state laws, medical ethics, common sense, and optimal medical care of children. It needs to end.
Free Speech for Medical Professionals
An attack on the free speech of doctors and medical scientists is being waged across America today. While controversy is inherent in scientific advancement, and scientific knowledge continuously evolves, disagreement with the federal public health recommendations has led to draconian censorship and suppression. Doctors have been investigated, lost their specialty board certifications, and even lost their medical licenses for speaking out publicly against federal guidelines.
Yet no health authority is infallible, and the COVID-19 pandemic proved this. In fact, both the World Health Organization (WHO), NIH and CDC changed their COVID-19 policies, guidelines, and recommendations numerous times throughout the pandemic.
The suppression of medical professionals’ speech is illegal, according to the First Amendment and state statutes, and must immediately end.
Julie Gamble had a fulfilling life: a stable career, the freedom to travel, and three children and one grandbaby to cherish.
But that life was disrupted in the spring and summer of 2021 when Gamble developed severe adverse reactions after getting the two-shot COVID-19 vaccine primary series — which resulted in her losing her job.
Gamble, now 53, spoke to The Defender about the vaccine injuries she sustained, the symptoms and challenges she is still experiencing, the ongoing difficulties finding doctors willing to treat her and classify her symptoms as vaccine-related, and the supportive role online groups for vaccine-injured individuals have had in her life.
The Defender reviewed documentation and photographic evidence verifying Gamble’s claims prior to publishing her story.
‘I felt really, really tired … anesthetic tired’
Gamble, who lives in Ontario, Canada, received the first dose of the Pfizer-BioNTech COVID-19 vaccine on May 17, 2021. For the second dose, she received the Moderna vaccine on July 18, 2021.
Her symptoms appeared almost immediately after the first dose, she said:
“I came home and I was really, really tired. It felt like an anesthetic tired, it didn’t feel like a ‘regular’ tired.
“I had developed a rash all over my body. I was itchy and my eyelids swelled up. I recall the bottoms of my feet being extremely itchy, more so than anywhere else, and I was sweating profusely. I started getting Charley horses in my calves. So, of course I was drinking a lot of water. I recall losing my vision in my right eye.”
Variations of the symptoms lasted for about a week after her first dose. She called a pharmacist who told her to take an antihistamine and, “if my tongue started to swell up, go to the ER.”
Soon afterward, Gamble developed other symptoms, including weakness in her ankles and a fluctuating heart rate.
“I also recall I was wearing my Fitbit. I’d walk into work, and I’d check my heart rate and sometimes it was at 140 and then it would drop down to regular, about 70 beats per minute. I’d be sitting down and I felt a little odd and I’d look at my Fitbit and my heart rate would shoot right up and then it would come right back down. And I stopped wearing it because I assumed my Fitbit was broken.”
The leg cramps kept getting worse, but Gamble attributed them to dehydration because where she worked “was quite hot, and so that’s what I thought was happening.”
‘I felt guilted’ into getting second dose
Gamble said her reactions to the Pfizer shot made her “leery” of getting a second dose — even her pharmacist recommended against it, she said.
“I spoke to the pharmacist about it, and I told him what had happened to me and about my muscles cramping up,” Gamble said. Her pharmacist recommended she see an immunologist before he would administer the second shot.
However, the doctor Gamble saw was far less sympathetic, she said:
“I didn’t have a family doctor, so I went down to the hospital thinking the receptionist or somebody would just book me an appointment with an immunologist.
“Instead, they put me in a waiting room. I saw a doctor and he told me right from the get-go he was not going to give me an exemption, he wasn’t going to give me an appointment with an immunologist. He told me to take an antihistamine and I would be fine.”
A combination of “nudging” from her doctor and Canada’s strict COVID-19-related restrictions led Gamble to go ahead with the second dose — especially after her doctor lectured her about “being a good citizen and not killing people,” she said.
“So, I felt guilted into it, and I knew I couldn’t leave Canada unless I was fully vaccinated.”
Gamble’s pharmacist was uncomfortable administering the second dose but proceeded on the doctor’s recommendation. Though Gamble didn’t develop a rash this time, she did experience fatigue and blurry vision again.
“I felt like, okay, I’m going to sleep this off. And once again, after about three days I started to feel a little bit better. But then I started dropping things all over the place. At first, I just kind of thought it was weird.
“But then I noticed my sense of perception was off. I’d go to open a door and where I thought the door was, my hand would be two inches away from the door. I started having brain zaps. I still tried to work, and so I was at work, and I tried to write a report and I could barely hold my pen. My hands were cramping up.”
Gamble also noticed slurred speech and changes in her ability to swallow food. “At that point, I decided obviously I can’t go to work. And I noticed muscles were starting to atrophy between my pinky finger and my ring finger.”
A neurologist at her local hospital, the London Health Sciences Centre in London, Ontario, “looked at my hands and said, ‘There’s something going on here.’” He admitted her for the night.
However, in the morning, another doctor dismissed her concerns, telling her she was ‘bending my arms too much.” She then made an appointment with a doctor she had seen during a previous adverse reaction to medication. But by that point, her condition had deteriorated further.
“I was losing the muscles rapidly,” Gamble said. “Within two months, I went from having normal-looking hands to completely skeleton-looking hands. The muscles in my arms started to atrophy, [and] in my feet behind my kneecaps. I could really feel it. My balance was off. My blood pressure was low.”
Trying to get a diagnosis ‘has been hell’
During one of several hospital visits, Gamble said doctors were particularly dishonest to her.
“One of the doctors said to me that some people are getting Guillain-Barré syndrome and he was going to check me for that. So, he gave me blood work.” But Gamble later learned that’s not even the right test for Guillain-Barré.
“They have to do it with a spinal tap,” she said. “I kind of feel like every doctor I saw had a reason to try to make up something different other than it was the vaccine.”
Gamble is still having trouble finding a doctor willing and able to treat her — and medication that will be effective and not cause further adverse reactions.
Meanwhile, she is dealing with multiple health-related challenges. “Just trying to get to the bottom of what is going on has been hell,” she said.
She has since found a family doctor who prescribed prednisone, but Gamble said she had a “horrible” reaction to it. “My hands turned blue, my tongue turned blue, I was getting brain zaps. I was passing out and my husband took me to the hospital.”
Doctors then told Gamble she had Raynaud’s disease, but “I don’t have that because [the symptoms were] on both sides of my hands and on my tongue,” she said.
She added:
“They sent me home like that. I tried to get help at one point, and I couldn’t get help. My husband, I guess I got a message out to him, but it was all gibberish. He came home thinking I’d had a stroke. He took me to the hospital; they did a CT scan, and everything came back normal. Apparently, my blood work comes back normal.”
Canada’s healthcare system, in conjunction with the country’s COVID-19-related restrictions, has made it challenging to even get treatment, Gamble said.
“I’m just trying to figure out what happened and am trying to get medical care,” Gamble said, “but I’m just hitting roadblocks everywhere. I figured maybe I could start physiotherapy, but in Canada you have to be 16 and under, or 65 and over, in order to qualify for free physiotherapy.”
Gamble said the pressure on doctors to look the other way when it comes to potential vaccine injury cases, and “a whole lot of doctor drama,” has been “frustrating.”
A neuromuscular doctor who previously worked at the London Health Sciences Centre confided in Gamble that she “got in trouble” with the Royal College of Physicians and Surgeons of Canada for writing COVID-19 vaccination exemptions. “And so, her hands are tied, pretty much,” Gamble said.
Meanwhile, Gamble’s symptoms continue to evolve, and doctors continue to reject the possibility that the vaccines are to blame. Recently, her tongue started “turning white and swelling up” and her ears became “really itchy and scabby.”
“My doctor thought this must be an allergy, so I went and I saw an immunologist,” she said. “But as soon as I showed him my hands and said, ‘vaccine,’ he told me he wasn’t interested in that. He was only interested in things that put you in instant anaphylactic shock.”
Gamble asked for a second appointment, during which it was noted that her heart rate had dropped to between 44 and 52 beats per minute. Doctors suggested she was experiencing a reaction to the prednisone.
Gamble asked to be tested for an allergy to polyethylene glycol, or PEG, because it’s unusual to have a reaction to prednisone, she said.
“The second doctor tested me and I said to him, since I’ve had this vaccine, I’m not doing well with certain foods or medications,” said Gamble. “And I talked to him about the muscle wasting, and he looked at my hands and he said he didn’t see it, which is ridiculous because it’s so obvious.”
Instead, the doctor “kind of wondered if it was psychosomatic,” said Gamble. She responded with, “no, I’ve had the nerve conduction studies done. It’s proven that my muscles are wasting.”
Gamble also saw a spine surgeon “who said she believes it’s a back injury.”
But one doctor Gamble saw later — a rheumatologist — was willing to draw a connection between her injuries and her vaccination.
“[The] rheumatologist said, ‘I don’t know what the big issue is. This is a vaccine injury.’ And she wrote me a letter to show people that I can’t be boosted.”
‘You kind of lose everything, don’t you?’
Unfortunately, Gamble said, Canada’s COVID-19 regulations restrict the extent to which exemptions are recognized.
Gamble told The Defender :
“I still can’t get a legal exemption, which is kind of important in a way because in Canada you can be refused a job. So, if I get better and I’m hoping I can go find employment again, they have the right to tell me that they’re not going to hire me because I’m not up to date on my booster. Or even traveling to another country — it’s up to them if they’re going to let me in if I’m not up to date on all this stuff.
“This government doesn’t seem to want to acknowledge the neurological damage. They only — from what I was told — give you an exemption if it’s a PEG allergy or if you have myocarditis, but not for neurological damage.”
As a result, said Gamble, “I’m going in circles here.” She described being told by a doctor that she “just happen[s] to be one of the people who ‘fall through the cracks’” — an obstacle that has also prevented her from collecting employment insurance.
She said:
“I don’t qualify for anything in my own country. And they have a vaccination injury support program, but very few people are getting paid out from that. It has to be ‘severe’ and it has to be permanent, and I don’t know if they’re going to consider this ‘severe,’ but right now I can’t work because I have no muscles left in my hands.”
Gamble did get severance pay, she said, but everything else “has been denied, denied.”
“The government in Canada, they certainly aren’t doing anything for people who are injured by the vaccine,” Gamble said. “So, you kind of lose everything, don’t you? And then you’re put in this category that you never wanted to be a part of.”
Despite these challenges and obstacles, Gamble perseveres, even though she can’t work.
“There are things that I want to do,” she said. “I want to start exercising, but I’m even scared of that because you see these videos [of people who] died suddenly … a lot of people apparently have died while they’ve been playing sports. So that’s a little bit concerning for me, and just in general, just still not knowing what happened to me.”
Online support groups for vaccine-injured individuals ‘a godsend’
In contrast to her experience with most doctors and many friends, who dismissed her condition, Gamble praised the support she’s received from members of online support groups for vaccine-injured individuals.
“It’s been a godsend,” she said. “For the first seven or eight months, I’m on my couch and I’m feeling my muscles wasting and I’m struggling to walk. Anybody that I tried to talk to that didn’t have an injury, they assumed it had to be something else, because they’ve been told that these vaccines are ‘safe and effective.’”
But participation in online groups, such as the Vaccine Injury/Side Effects Support Group on Facebook, has allowed Gamble to interact with “decent” people who “don’t judge” and who have experienced similar symptoms and conditions as her.
“I have found a few women with the exact same injuries that I have,” she said. “It was nice to know that there are other people out there, that you’re not alone. We don’t all share the same symptoms, but we share a lot of similar symptoms, and so I can say, ‘so-and-so tried this, well I’m going to try it.’”
Gamble said she’s not sure the medical system will ever regain her trust. But she had some advice for others experiencing vaccine injuries.
“People need to realize if they get injured by this vaccine, probably medically they’re not going to get a lot of help or [doctors] are going to try to tell them it wasn’t the vaccine.”
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
Whenever I republish my newspaper op-eds on this Substack, I tend to introduce them with some comments on “how I really feel,” instead of the more staid language and arguments used in those pieces. In this one, I essentially argued that the new Select Subcommittee on the Weaponization of the Federal Government should be ground zero for investigating how the administration is using COVID-19 to wage war on doctors who won’t follow its orthodoxy.
Although I am not under the delusion that its actions will actually result in meaningful changes in public health policy, I felt I should provide some guidance to them in the support we doctors (and thus patients) really need. I highlighted some of the most harmful actions taken to silence and suppress physicians, which would have been absolutely unthinkable a few years ago but now are becoming the norm, what with Clownifornia’s new bill (which just got slapped with an injunction!) threatening doctors’ livelihoods if their speech does not support the dominant consensus, er, I mean “narrative.”
I am doing this while every week new data piles up showing the immense toxicity and lethality and negative effectiveness of the latest vaccines. Yet the Biden administration and its allies in media and medicine only push them harder, inventing batshit crazy narratives to explain their shortcomings. Imagine their gratitude learning about this Canadian physician’s discovery of a “stroke season!”
By now we all understand that these profoundly anti-scientific, unethical positions are driven by an unholy and terrifying alliance of government, the pharmaceutical industry, and media. The evidence is damning in how they have co-opted public health institutions to suppress dissent so they can continue raking in astronomical profits. The American Board of Internal Medicine (ABIM), a nonprofit organization that certifies physicians’ medical licenses, is chief among the once-trusted institutions that has bent the knee.
Last year, the ABIM accused myself, Paul Marik, and Peter McCullough of spreading “misinformation” and threatened our ability to practice medicine, ignoring the ever-widening disconnect between the Biden administration’s statements and the reality on the ground.
As an aside, although it is devastating to do so, I think that everyone should read Mark Crispin Miller’s Substack and his daily series entitled “In Memory of Those Who Died Suddenly.” He compiles and presents media reports of human deaths at a frequency and regularity that is difficult to behold (especially for an expert in sudden cardiac death, a subject I studied deeply during my years as an expert in therapeutic hypothermia in post-arrest patients, an event which was distinctly rare in active healthy people outdoors prior to the vaccination campaign).
I feel responsible to read/witness what he is presenting to the world. I am tired of dueling and conflicting medical papers and agency data, cherry-picked or manipulated to support the dominant delusion that these vaccines are benign. When you read Mark’s Substack, you are faced daily with reading about the untimely and sudden ends to the lives of real people, every day, around the world, amidst this terror of a global vaccination campaign.
They are dying “unexpectedly” at enormous rates and falling ill with cancer at enormous rates. He seems to be the only one who is presenting these data in such a human, highly personal way by compiling individual media stories of the sudden ending of human lives at ever younger ages with an unimaginable regularity. Unfortunately, as per the most visited English language media outlet in the world, doctors don’t know why yet and the vaccines are not even mentioned as a possibility in this clown article published in the Daily Mail.
Unrelenting reports of people in largely perfect health, out in society doing routine or pleasurable activities and then dropping dead or unconscious, often being captured on television studio sets, auditorium stages, subway platforms, street surveillance cameras, playgrounds, sporting events, athletic fields, and even broadcaster desks. To date, I am not aware of a single newspaper report (even from tiny local papers) which openly implicates the vaccine as even a possible cause let alone an almost certain one. An unimaginably dystopian nightmare all around us… while society seemingly carries on as normal.
Back to the ABIM: despite its status as a private organization with no statutory authority (insane right?), the ABIM has morphed into an “enforcement” arm of the government, wielding the ability to control certification and the livelihood of doctors, who are subject to career-ending threats for trying to alert the public to all the death and disability resulting from the vaccine campaign. Paul and I are fighting those charges tooth and nail. I am looking forward to soon sharing on this Substack the brilliant response we worked on with our assassin of an FLCCC lawyer, Alan Dumhof. I predict a clown world of a response and will share with you as soon as we get it.
Anyway, here is my Op-Ed:
Two years of one-party rule in Washington are over, and the new Republican House majority must now restore balance through vigorous oversight. The Select Subcommittee on the Weaponization of the Federal Government is expected to focus on allegations of collusion between social media companies and the Biden administration.
But it should expand its focus to include the government’s use of COVID to wage war against doctors — which continues to this day.
The suppression of doctors’ freedom to advise and treat patients began early in the pandemic. Promising alternative courses of treatment, such as generic drugs like ivermectin or hydroxychloroquine, were shouted down by false news narratives.
Media companies took their cues from public health agencies, which exaggerated concerns over people using medicines to treat COVID in ways that were not intended and against medical advice. Positive clinical data was ignored.
The next major front in the war on doctors opened up with the vaccine rollout. President Joe Biden, Dr. Anthony Fauci and other public officials promised these novel, rushed vaccines would prevent illness and even transmission.
Biden’s declaration that, “If you get vaccinated, you won’t get COVID” has now been exposed as a lie, but it’s crucial to understand how it came to this.
In the past, broad skepticism would have greeted plans to mass distribute a “safe and effective” vaccine that was developed and approved in just 12 months.
And society would have flatly rejected government mandates that pushed people to get vaccinated or risk losing their jobs and becoming social outcasts. Science and medicine, practiced correctly, should challenge the powers that be, not blindly follow them.
But in our ongoing ordeal, no skepticism has been allowed, no discussion, no options. Those who raised questions or suggested different approaches were smeared as “deniers” or even worse, “anti-vaxxers.”
Even as the public learned more about the virus’s actual threat, the vaccines’ disappointing performance, and the tragic reality of vaccine injuries which began occurring at an unprecedented scale, the political imperative from Biden and Fauci never wavered.
They continued to preach a single-minded focus on the experimental vaccines. More and more vaccine products were rushed through Emergency Use Authorizations from the Food and Drug Administration, resulting in astronomical profits for their manufacturers.
This unholy alliance of government, the pharmaceutical industry and media deprived the public of full and fair advice from the medical community. The American Board of Internal Medicine (ABIM), a nonprofit organization that certifies physicians’ medical licenses, has issued letters to me and my colleagues threatening our ability to practice medicine.
They accused us of spreading “misinformation” — ignoring the huge disconnect between the government’s statements and the medical reality on the ground. Despite their status as a private organization with no statutory authority, the ABIM has morphed into the “enforcement” arm of the government, wielding the ability to control certification and the livelihood of doctors, who are subject to career-ending threats for veering from the government’s narrow and singular approach.
And this month, California’s new law empowering state agencies to disbar medical professionals who deviate from the party line has taken effect. Gov. Gavin Newsom recently called California the “True Freedom State.” The scores of its residents—and its doctors—fleeing for Florida and Texas know better.
A “one-size-fits-all” approach to vaccines, or to any other health issue, is almost never warranted. Here, proponents of vaccine (and of government and Big-Tech coercion and censorship) flatly refuse to consider patient factors, such as age, medical history, and overall health, to determine who needs what treatment.
By virtue of their professional training, doctors must advise patients on available treatments and known risks of any treatment or procedure. By threatening doctors who might provide information different than their preferred worldview, ABIM is disrupting the doctor-patient relationship.
When allowed to practice their craft freely, physicians can prevent societal disaster by focusing on individual patients, informed by clinical experience.
Groups like the ABIM, and public medical officials like Fauci, should support and encourage evidence-based debate and patient-centered care.
Instead, they have suppressed both that debate and treatment approach by persecuting its proponents. This campaign must be stopped, its origins and evolution must be thoroughly documented, and it must never be allowed to recur. Physician autonomy must be restored lest all patients suffer.
Oversight is a core congressional function, and it’s particularly important when the government is under divided party control.
The new Select Subcommittee has a long to-do list, but the people deserve a thorough accounting of the ongoing war on doctors.
Pierre Kory is a Pulmonary and Critical Care Specialist, Teacher/Researcher. He is also the President and Chief Medical Officer of the non-profit organization Front Line COVID-19 Critical Care Alliance whose mission is to develop the most effective, evidence/expertise-based COVID-19 treatment protocols.
Replacing fossil fuel with hydrogen seems like an ideal solution to make transportation environmentally friendly and to provide a backup for intermittent energy sources like solar and wind. But how environmentally friendly is hydrogen really? And how sustainable is it, given that hydrogen fuel cells rely on supply of rare metals like platinum and iridium? In this video, we have collected all the relevant numbers for you.
The CDC recently codified International Classification of Disease (ICD) codes for Covid-19 vaccine status. ICD codes are extensively used in medical records, medical insurance data and health research to classify precisely disease states as well as injuries from exogenous agents such as accidents, medication and medical device injuries, toxic chemicals, etc. Vaccination status is not a disease or an injury state, yet CDC has rationalized creating ICD codes for it. The coding is set to become effective on April 1, 2023.
As described by Dr. Robert Malone, “The ICD classification system is run by the World Health Organization, not the US government.” The vaccine status ICD codes were developed by the US Centers for Medicare and Medicaid Services (CMS) some nine months ago, and CDC is implementing them.
The coding scheme, Z28.xxx, includes both vaccination status and possible reasons for the status. However, there does not appear to be a code for “fully vaccinated,” only for various states of “not fully vaccinated.”
The code Z28.0 means “immunization not carried out because of contraindication.” Z28.1 means “immunization not carried out because of patient decision for reasons of belief or group pressure.”
Z28.2 means “immunization not carried out because of patient decision for other and unspecified reason.”
Z28.8 means “immunization not carried out for other reason” which because of code Z28.2 must refer to reasons not attributable to patient decisions.
Finally, Z28.39 means “other underimmunization status,” including “Delinquent immunization status” and “Lapsed immunization schedule status.”
However, a potential contradiction arises because code Z28.310 means “unvaccinated for COVID-19.”
In order to reconcile this, the Z28 codes in the previous paragraph must refer to vaccines other than for Covid-19. The only other Covid-19 code is Z28.311 which means “partially vaccinated for COVID-19,” where “partial” refers to the CDC definition for “fully vaccinated” at the time when the patient visits the health-care provider who records the vaccination status in the medical chart.
It is apparent that the details of reasons for patient choices for vaccine status are not specified in codes for Covid-19 vaccines, but the CDC has some two months to fix this. There are no specific codes yet for “refused to divulge COVID-19 vaccination status” or “unknown COVID-19 vaccination status,” but these codes are likely to be added at some point.
What is the usage for which this information is planned? There is certainly a public health rationale for agencies to be able to monitor population vaccination status. Personal health information is routinely analyzed by public health agencies, insurance companies and health researchers, but in anonymized and grouped formats. The identifiable information is recorded in the databases, however HIPAA and other laws strictly protect identifiable health information and regulate how such information may be used for analyses.
In theory, vaccination status could be no different. Medical records already know your age, gender and race, where you reside, about your obesity, diabetes, your smoking and alcohol usage and your HIV status. Some of this information could be stigmatizing if released publicly, but at present there are no politicized or other circumstances to force unwanted choices on members of the public based on this compiled personal information.
Imagine, however, that one day, government agents are pounding on your door at 6am, telling you that you are required to take smoking cessation medications, under penalty of forced residence in a “smoking-cessation hotel” until you submit to the government’s requirement.
The medications have built-in transmitters that are activated when exposed to stomach acid, so taking them is recorded. After all, 500,000 Americans die every year from smoking-related diseases and their end-of-life medical care is an expense for which the government no longer wants to pay. Your smoking is economically hurting the medical care that grandma needs. Or something.
But Covid-19 and its vaccination are different. The Covid vaccines and their boosters were created under emergency-use authorization (EUA) protocols and are not fully licensed. The Biologics License Application (BLA) versions, e.g., Comirnaty, are not generally available in the US. This licensing chicanery has not gone unnoticed by the American public and a substantial fraction of people find the vaccines controversial.
Many people have seen their multiple-vaccinated friends and relatives get Covid, some multiple times. Many have also seen friends and relatives harmed by the vaccines, and most people know of the incessant daily deaths of healthy athletes, deaths discussed as caused by “coincidence.” People have seen the vaccines touted as solutions to the pandemic, yet utterly fail across the population to suppress transmission of the infection.
And, people have been bombarded with daily narratives for two solid years that the vaccines are “safe and effective” and that they must be taken, and that unvaccinated people are “bad,” “selfish,” demonized as doing damage to society, and should be shunned.
That is, personal vaccination status today is the most stigmatizing personal data of modern times, surpassing having AIDS. As such, any government compilation must be “bulletproof” against hacking and misuse. As well, the government must be trusted to maintain the data for use only as other personal medical data have been used.
Given the two-plus years of massive government propaganda about the vaccines, about their adverse effects, about Covid, about early Covid treatment, and the government collusion with social media companies in suppression of valid dissenting medical and scientific opinions and data, there is no empirical reason to support trusting the government with such sensitive, stigmatizing data.
There is no reason to believe that the government will not release the status information to insurance companies or other companies doing large business with the American public. Further, there is no recourse should the government actually release such confidential data. Thus, nothing may stop such companies from restricting activities based on the stigmatized data. For example, public travel could be blocked; bank accounts could be blocked; purchasing could be blocked.
The free pursuit of happiness is enshrined in our Declaration of Independence. The government cannot lawfully interfere with normal transactions of everyday life. But private companies working at the government’s behest, with government-supplied personal status information, could very well do it.
As has been seen from the FOIA documents, hundreds of government employees have spent the pandemic years doing exactly this unconstitutional behavior in getting social media companies to suppress Americans’ freedom of speech.
Furthermore, there is now no rational government interest in compiling vaccination status at all. At a time when vaccination was generally thought (incorrectly) to reduce Covid-19 transmission across the population, there might have been a rationale for doing so.
However, on August 11, 2022, the CDC stated publicly that the Covid-19 vaccines do not work as a public health measure to control virus transmission. They said, “Receipt of a primary series alone, in the absence of being up to date with vaccination* through receipt of all recommended booster doses, provides minimal protection against infection and transmission (3,6).” “Being up to date with vaccination provides a transient period of increased protection against infection and transmission after the most recent dose, although protection can wane over time.”
The fact that such benefit is “transient” and wanes implies that after some short period, boosters fail to reduce risk of transmission and thus that vaccine mandates are invalid.
The only government interest in mandating Covid vaccines, and thus in compiling personal information about vaccination status, is that the vaccines reduce transmission. They don’t.
Secondly, the CDC’s August 11th policy guidance does not distinguish between vaccinated and unvaccinated people in any way for any policy. There is thus no compelling government purpose in defining people as vaccinated or unvaccinated. It would be like the government compiling personal information on hair color, except that hair color is not stigmatizing and vaccination status is extremely stigmatizing.
The government itself—through the CDC—has determined that vaccination status is not of policy importance. There can thus be no compelling interest for the government to forcibly collect this information against the wishes of the population, even were it not stigmatizing. So much more so after the government has spent the last two years publicly demonizing unvaccinated people for their rational and legitimate personal health choices.
Harvey Risch, Senior Scholar at Brownstone Institute, is a physician and a Professor Emeritus of Epidemiology at Yale School of Public Health and Yale School of Medicine. His main research interests are in cancer etiology, prevention and early diagnosis, and in epidemiologic methods.
You might argue that to say the world is warming is an obvious fact. ‘But,’ as Sherlock Holmes remarked to Dr Watson*, ‘there is nothing more deceptive than an obvious fact.’
The meteorological fraternity tell us that as emissions keep growing the temperature of our earth will keep rising. Some of the effects, they say, can be seen in extreme weather such as floods, droughts and storms. However, research has shown the apparent escalation of this kind of event is far more likely to be due to a greater facility for reporting every incident over the last fifty years. Even more doubt lies in the fact that we have been widely recording weather details for about 150 of the 11,000 years since the last ice age. Any claims of records being broken can refer only to that brief period.
Assessing the rate of global warming, then, and any decision as to whether there is a climate ‘emergency’, rests almost entirely on measurement of the global temperature. This is always given as a difference relative to a previous period, and not only to tenths of a degree (which is how it is measured at every recording station), but to hundredths of a degree.
The UK Met Office’s global temperature for 2021 was 0.76 ± 0.04 deg C above the 1961-1990 average. The World Meteorological Organisation (WMO) said the year was about 1.11 ± 0.13 deg C warmer than the 1850-1900 average. First worrying thought: why was such a precise measurement prefaced by that word ‘about’?
The Met Office’s figure for 2022 was 0.80 ± 0.04 °C above the 1961-1990 average and 1.16 ± 0.08 °C above the pre-industrial 1850-1900 average. The World Meteorological Organisation uses six international data sets to provide an authoritative assessment of global temperature change. They report that ‘2022 was about 1.15 (1.02 to 1.27) °C above the pre-industrial (1850-1900) levels’. There’s that curious word again.
The climatologists claim to be measuring the temperature of the earth, over land and sea, night and day, for a whole year, and giving us the result to a second place of decimals, with a tolerance of only a few hundredths of a degree Celsius. That is unbelievable.
The US National Oceanic and Atmospheric Administration (NOAA) website does admit that ‘the concept of an average temperature for the entire globe . . . may seem like nonsense’. It certainly does. It would be difficult to measure the average temperature of a small garden for a whole year to that level of accuracy, unless there were thermometers recording maximum and minimum every day in each square metre.
Why is it always a difference measurement? The NOAA website explains: ‘Because [the scientists’] goal is to track changes in temperature, measurements are converted from absolute temperature readings to temperature anomalies – the difference between the observed temperature and the long-term average temperature for each location and date.’
Subsequent paragraphs shed more light on the data, and are worth quoting at length (my italics). ‘Across inaccessible areas that have few measurements, scientists use surrounding temperatures and other information to estimate the missing values . . . climatologists average data from individual stations with data from other stations in the area. When combining observations, the values for each station are mathematically weighted to account for the fraction of the averaging area they represent.’
Those four words ‘estimate’, ‘average’, ‘combining’ and ‘weighted’ all cast serious doubts on the final two places of decimals. Then there is the obvious question: how well are the recording stations covering the land and sea areas of the earth?
For measurements taken on the earth’s surface, the WMO says there are ‘well over 10,000 manned and automatic surface weather stations . . . 7,000 ships, 100 moored and 1,000 drifting buoys’.
The Climatic Research Unit (CRU) of the University of East Anglia confirms that its global temperature series (CRUTEM5.0) uses data from only 8,000 of the land-based weather stations because the others ‘did not have sufficient data to estimate a 1961-1990 mean’.
The land area of the earth is 148,300,000 km2. The 8,000 recording stations would therefore each represent a huge 18,500 km2 chunk of the earth’s land surface. But they are not uniformly spread. According to the CRU, ‘coverage is denser over the more populated parts of the world, particularly the United States, southern Canada, Europe and Japan. Coverage is sparsest over the interior of the South American and African continents and over Antarctica’.
The sea area of the earth is 361,700,000 km2. The number of ships and buoys (8,100) means that each represents around 44,600 km2 of the sea surface, and even then the accuracy of the data largely depends on where the ships (moving steadily) and buoys (drifting slowly) happen to be. Additionally, the buoys and ships are measuring sea water temperatures, not that of the air over the sea: how exactly are pre-industrial temperatures of the sea calculated for comparison?
Every year several very well-known climatological and scientific institutions tell us the earth’s annual average global temperature. The world waits anxiously for their pronouncements. But even the first decimal place is doubtful, let alone the second. The accuracy has been generated solely by way of mathematics: first the average of each station’s daily maximum and minimum is calculated, then the weekly and monthly average which is converted to an anomaly for the station, mathematical weighting is carried out if necessary, estimations added for missing values, and only then is the final annual figure achieved for that particular station over the last twelve months.
(The process is actually even more complex: see, for instance, NASA’s ‘Raw Truth on Global Temperature Records’.)
Presumably all the station annual average figures, around 16,000 for both land and sea for the whole world, are then added and a grand average figure is produced. It is that final averaging that can produce as many decimal points as you want. But by then it is meaningless.
For such a vast area of land and sea, and over such a long period of time, it is surely impossible to determine a sensible average temperature, let alone one given with such apparent accuracy. They must be right, we are supposed to think, because they are given to the nearest hundredth of a degree Celsius.
The Met Office has already forecast this year’s (2023’s)global average temperature to be between 1.08 °C and 1.32°C (with a central estimate of 1.20 °C) above the average for the pre-industrial period (1850-1900). Here are the two decimal places again, with a tolerance of a fifth of a degree Celsius, for a year that has hardly started.
All these supposedly carefully measured temperatures are surely open to some considerable doubt, but unfortunately they are treated as the ultimate and unequivocal proof of rapid climate change.
If these figures are indeed of dubious authenticity, and if bouts of extreme weather may or may not indicate any change in our climate, then how much do we really know for certain?
The CDC and FDA have sounded an alarm of an increased risk of strokes for over 65’s after their mRNA booster shot. Still no transparency with the data as the public forced yet again to take the word of agencies with rapidly waning integrity and trust.
By Mahdi Darius NAZEMROAYA | Strategic Culture Foundation | 30.03.2015
The United States and the Kingdom of Saudi Arabia became very uneasy when the Yemenese or Yemenite movement of the Houthi or Ansarallah (meaning the supporters of God in Arabic) gained control of Yemen’s capital, Sanaa/Sana, in September 2014. The US-supported Yemenite President Abd-Rabbuh Manṣour Al-Hadi was humiliatingly forced to share power with the Houthis and the coalition of northern Yemenese tribes that had helped them enter Sana. Al-Hadi declared that negotiations for a Yemeni national unity government would take place and his allies the US and Saudi Arabia tried to use a new national dialogue and mediated talks to co-opt and pacify the Houthis.
The truth has been turned on its head about the war in Yemen. The war and ousting of President Abd-Rabbuh Manṣour Al-Hadi in Yemen are not the results of «Houthi coup» in Yemen. It is the opposite. Al-Hadi was ousted, because with Saudi and US support he tried to backtrack on the power sharing agreements he had made and return Yemen to authoritarian rule. The ousting of President Al-Hadi by the Houthis and their political allies was an unexpected reaction to the takeover Al-Hadi was planning with Washington and the House of Saudi. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.




 Aletho News