WHO Sneak Attack
CHD.TV: “This is the big one. They’re going for broke… I think we may only have potentially until May before one or both of these documents gets voted on” — Meryl Nass, M.D. and James Corbett continue their discussion on the WHO’s proposed International Health Regulation Amendments + potentially legally-binding ‘Zero Draft Treaty’ currently being drawn up in secret meetings behind closed doors. As the WHO touts the solution to worldly problems as possible through their ‘One Health’ approach — one wonders if a world in which humans, animals, agriculture, and weather are dominated by state depicted notions of the highest attainable standard of ‘health’ may secretly be a trojan horse to dominate as much of the sovereign world as possible — usurping power from individual countries and thrusting it into the hands of a mad-with-power agency which seeks to control Earth’s resources, ecosystems, food, animals, and plants.
VIDEO COURTESY Bitchute CHD.TV / RUMBLE
SHOW NOTES:
PREVIOUS TALK: The Weaponization of the WHO on CHD TV
WHO Member States Agree To Develop Zero Draft Of Legally Binding Pandemic Accord In Early 2023
Review Committee Regarding Amendments To The International Health Regulations (2005)
CDC’s One Health Office: What We Do
One Health Joint Plan Of Action Launched And Presented By WHO And The Quadripartite Partners
One Health Joint Plan Of Action Launched And Presented By WHO And The Quadripartite Partners
Please Stop The Ride To A Biotech Food Takeover – Transcript
James Roguski Substack — THE TOP 100 REASONS TO #StopTheTreaty, #StopTheAmendments, And #ExitTheWHO.
The Lancet has become a laughing stock

By Norman Fenton and Martin Neil | Where are the numbers? | January 14, 2023
In summary:
- On 6 May 2021 The Lancet published a blatantly flawed study of the effectiveness of the Pfizer covid vaccine on the population of Israel, claiming it was 95% effective.
- On 17 May 2021 we submitted a rapid response 250 word letter explaining why the study was flawed.
- After an initial response saying they would ask the authors for a response to our letter we heard nothing until 20 months later.
- On 8 January 2023 we got an email out of the blue from The Lancet Senior Editor Josefine Gibson apologising for never having got back to us about the letter, saying that they had asked the lead author Dr Sharon Alroy-Preis (SA-P) to respond to our letter but, because she did not provide any formal response, they have decided not to publish our letter.
- We tweeted The Lancet’s response and within 24 hours it got over one million impressions. We also published a substack article highlighting the fact we were now aware of additional problems with the paper relating to SA-P’s relationship with Pfizer.
- On 10 January 2023 we got an unsolicited email from Josefine Gibson (which we can only assume was a result of the reputation hit they got from our tweet) saying “Thank you for bringing your letter from May 2021 back to our attention. We are looking into next steps and will get back to you as soon as we can.”
- On 11 January 2023 (at 10:58) we sent an email to The Lancet’s Editor-in-Chief Richard Horton directing him to our substack article (which highlighted these new problems relating to SA-P’s relationship with Pfizer) stating that The Lancet was clearly taking a credibility hit surrounding the publication of the Israel-Pfizer study and its response to criticisms of it.
- On 11 January 2023 (at 11:21) we got an email from Josefine Gibson apologising for the ‘sub standard experience’ we had with The Lancet. She said that, after discussing it with Horton, they were now inviting us to publish the original letter or an update to it, suggesting the update ‘reflect more current experience with the vaccine’.
- On 12 January 2023 we submitted our updated letter (of an agreed 350 words).
- On 13 January 2023 we got a response from Josefine Gibson saying they had decided against publishing the letter.
Here is the full narrative and January 2023 correspondence in date order (personal details redacted)… continue
Insider reveals truth about Covid-19 pandemic from within the National Health Service
How the misdiagnosis of deaths occurred and was due to changes from 2016
The Naked Emperor’s Newsletter | January 15, 2023
An ex-director at one of the largest hospital trusts in the UK decided they wanted to reveal what really happened during the pandemic. They have kindly allow me to reproduce their thoughts. The catalyst for this revelation, according to the insider, was Dr. Malhotra speaking out about cardiac problems post vaccination.
This is an interesting take on what happened inside the National Health Service (NHS) and confirms, with more details, what we already knew and suspected.
Introduction (Long but important to understand the rest)
In 2016, the British Government proposed & piloted a change to the process of how deaths were certified across all hospitals in the UK. I have attached a link to this Department of Health (DoH) document.
The DoH document proposed a switch to the “Medical Examiner” (ME) System and was sent to a number of different audiences for feedback and consultation. The ME system was already being piloted at two hospitals up north. The results of the consultation are here.
Prior to the Covid-19 Pandemic, the death certification process involved treating doctors of a patient to attend Bereavement Services/Patient Affairs to discuss the death and either:
a) refer the death to the Coroner or
b) write a Medical Certificate of Cause of Death (MCCD).
The MCCD states the cause of death. Whereby a direct cause (1a) or contributing causes (1b) (1c) (1d) are stated along with co-morbidities (not directly causing the death) being written in (2) on the MCCD. The MCCD is only ever a probable cause of death, it is not definitive.
The only definitive way of determining an accurate and plausible cause of death is to refer the deceased patient to HM Coroner (if certain criteria is met), for HM Coroner to accept and take on the case, resulting in a Post Mortem (PM) being conducted by a Histopathologist. When a death is seen as natural and there is nothing untoward, the MCCD is written by the treating doctor of a deceased patient. Usually this is an F1, F2, SHO or Registrar that attends. It is rare for a treating Consultant to attend, but they will finalise the cause of death.
A strict hospital hierarchy exists within the NHS for doctors. It is as follows – from lowest to highest rank: Foundation Year 1 (FY1), Foundation Year 2 (FY2), Senior House Officer (SHO), Registrar (Reg), Consultant, Clinical Lead, Medical Director. Junior doctors will very rarely speak up or challenge their seniors. A senior decision is seen as final and it will be carried out and executed without any hesitance or questioning. In my 5.5 years of experience in End of Life Care, I have only ever seen one junior doctor disagree with a proposed cause of death and challenge their consultant.
With the number of deaths that occur in a hospital, as you can imagine, there is a great deal of variation with regards to causes of death, as we have numerous different doctors writing an MCCD and coming up with various different potential diseases in different orders.
The proposed ME system would change this, as the government would now hire and pay one Medical Examiner, to sit in every hospital and write all MCCD’s for all deceased patients. This would effectively eliminate any variation in causes of death.
In 2016, when I heard of this proposal, I worked as a Bereavement Officer at a hospital in Central London. My mentor/line manager at the time was a former Chief Nurse who managed Bereavement Services and all hospital deaths would be controlled by her and the department.
We essentially carried a huge amount of power with regards to decision making, as we would go through all patient notes following the death of a patient, and essentially guide and advise doctors on what would need to be written with regards to an MCCD or Coroners Referral.
In my personal opinion, our role was to sit on the fence and act in the best interests of a deceased patient (and their families), but also protect the hospital and our doctors from any potential negligence. As you can imagine many battles were fought over decisions about a cause of death of a patient or a referral to the coroner with a vast amount of doctors over the years.
F2’s and SHO’s were particularly the worst with regards to carrying an arrogance of knowing what should be written on an MCCD or stating that a patient didn’t need to be referred to the Coroner (often stating that their Consultant had given them instructions). It is worth noting that Consultants are also only human and can be incorrect at times too. We have to remember that they are succeeded in hierarchy by a Clinical Lead and beyond that a Medical Director. Who have far more experience and knowledge.
When I asked my mentor in 2016, how the ME system would change things, I was told that Bereavement Services/Patient Affairs would become purely administrative and that the clinical judgement would fall to the Medical Examiner.
The power and decision making with regards to MCCD/Coroners Referrals was being taken away not only from treating doctors but also from Bereavement Services/Patient Affairs/Bereavement Officers/Bereavement Service Managers/Directors of End of Life Care.
This decision making power was being handed solely to the Medical Examiner, who has not been involved in the treatment of a patient during an admission. I took all this information in at the time and acquired as much knowledge as I could from my mentor/line manager.
In 2016, I also happened to make a move and take up an opportunity to manage my own Bereavement Services at one of the largest hospital trusts in the whole of the UK. On average, I would oversee MCCD/Coroner Referrals for approx 1750 deaths on an annual basis. I developed a very close working relationship and friendship with one of the Medical Directors (a doctor with the highest ranking in a hospital). This was especially helpful when having to challenge doctors with regards to MCCDs/Coroners Referrals.
Progressing to Director of End of Life Care, I became involved with the reporting of mortality rates, conducting mortality reviews and writing hospital policies. I had also developed an excellent working relationship with the HM Coroner who oversaw our Trust. HM Coroner holds the power to investigate any hospital or trust with regards to a death or a number of deaths. A slight problem may arise, in that HM Coroner has an allegiance to the Crown and the Government.
When a death is reported to the Coroner. This was previously reported via telephone call by the treating doctor. A discussion was had with the Coroners Office and a direct outcome and instruction would come from the Coroner’s Office, by way of HM Coroner (via a phone call).
There is a fundamental flaw to this system, as there is no documentation of the decision and instruction from the Coroner’s. It comes via word of mouth. There is always room for error without any electronic documentation. Every Hospital/Trust & HM Coroner will have a different system of reporting deaths. I personally made a decision to safeguard my hospital and the trust, by developing an electronic coroners referral form, which I proposed to our Coroner and developed after their agreement. We now had documentation of every death being reported and every outcome.
When reporting a death, the Coroner will look at a proposed cause of death and accept it, or reject the cause of death and take on the case (death of the patient), leading to an Inquest or a PM.
In 2019, our Medical Director, came into my office one morning and stated that the Board of Directors at the Hospital had made a decision to switch to the Medical Examiner System. Hearing the words ME system was a massive case of Déjà vu (conversation with my mentor in 2016). I knew exactly what the ME system was, but I chose instead, to play the fool and enquire what exactly the ME system was and what it meant for our service, my staff and our roles. Everything the Medical Director mentioned to me that day was a carbon copy of what I already knew
I knew that my time in End of Life Care had come to an end. I’d reached the top and there was no more progress for me. Losing all power and decision making to any ME coming into the hospital did not appeal to me. I’d already made up my mind that I needed to leave. Seeking a new challenge and experience, I made a move in 2019 to another major hospital in Central London, this time side tracking into operational management. I was in charge of the operational management of Nephrology, Rheumatology, Dermatology and Diabetes & Endocrinology.
2020 – Covid Arrives
In Jan 2020, I remember hearing about the first case of Covid-19 at our hospital, with a patient arriving from China and walking into our A&E. A&E was shutdown and steam cleaned that day, I recollect the moment I heard about this. In my mind, I saw the reporting of Covid-19 in the media as nothing more than Bird Flu or Ebola, which had caused panic but yet passed. I wasn’t worried in the slightest bit.
Things began to escalate around in Feb 2020, around the time I was going on holiday. Due to the reporting by the media, I bought N95 masks as a precaution for my trip and to give to my parents and younger sister. I was blessed to have had an opportunity to spend a few days in Sri Lanka for a wedding and then nearly a whole month in Australia (March 2020). I watched as the narrative of a deadly infectious disease continued to grow with every day that passed. I made a decision to cut my holiday short by a couple of days so that I could make sure I got back to my family and not end up being stranded in Australia.
Upon returning to the UK in late March 2020. One of the immediate things that struck me was the lack of any temperature monitoring or questioning at Heathrow Airport. This seemed odd for a potentially deadly infectious disease that was spreading around the world. This was especially odd, as Sri Lanka & Australia had questioned me/checked temperatures upon arrival, with even Singapore monitoring temperatures during transit.
My mother had just recovered from Cancer, my father was over 70 and my younger sister was born with Down’s Syndrome alongside having multiple other conditions. I had three high risk individuals to Covid-19 in my family and I was scared/fearful of giving them Covid-19. I asked my hospital to allow me to work from home. They refused. I wasn’t deemed high risk, although I lived with my parents at the time. I needed to help my mum and my sister. The hospital held no regard for the safety of it’s employees. They forced me to come into work. I spent two months isolating in my bedroom, I barely came out of my room, for fear of spreading an infectious disease. Never once did I think about the situation or my prior experience or knowledge, I was just reacting to the media frenzy. I was full of panic and stress.
The first irregularity I noticed, was the government and media stating that Covid-19 was an infectious disease. However just before the first lockdown was implemented, I noted that the government had downgraded the status of Covid-19 stating it was no longer infectious. This made no sense to me. Why would we need to isolate if they downgraded the status? My circle of friends contained many medics and dentists. They were all panicking at the time, saying they had inadequate surgical masks and that they needed N95 masks.
N95 masks were seen as the only way to prevent medical professionals from becoming infected with Covid-19. The public being asked to wear surgical masks made no sense to me. The virus would be able to go straight through. Something didn’t seem right.
I ended up meeting and dating an FY1 doctor (my ex gf) around October 2020. We clicked because she was different from every other doctor, I had previously spoken to about Covid-19. She also had her suspicions and believed it wasn’t as infectious as it was made out to be. We both started to slowly realise that Covid-19 was a real disease (as it was showing up on X-rays in patients) but that it wasn’t infectious at all [NE – I have since confirmed with them that they mean not as infectious as was being made out], despite all the reporting in the media.
I needed to experience working in a Covid-19 hotspot and see all the action for myself. In March 2021, I quit my job at the hospital in Central London and took up an opportunity to manage A&E and AMU (Acute Medical Unit) at a hospital in South London. The 6 months that I spent working in A&E/AMU confirmed all my suspicions and culminated in my decision to end my career in the NHS.
The entire 6 months, I was not tested once with a PCR Test, despite walking into wards full of Covid-19 Positive patients on a daily basis. Yet we were required to test multiple times when visiting another country.
The PCR Test that the NHS was using to test patients, is known to have false-positive results. This is shown in numerous studies which can be found online, an example of which is:
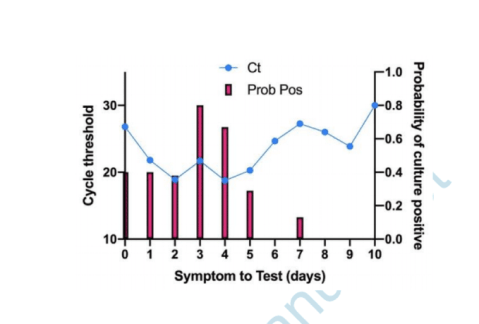
Are you infectious if you have a positive PCR test result for COVID-19? – The Centre for Evidence-Based Medicine.
If a patient tests positive for Covid-19 with a PCR Test, this doesn’t mean they are infected. If tested again, they may well turn out with a negative test. However in the NHS, patients are only tested once and this stays on their record throughout their admission. Hospital policies were changed alongside the implementation of the Medical Examiner System, to ensure that any patient who died within 30 days of positive test, would have to have Covid-19 as their primary cause of death. This was regulated by the Medical Examiner.
The highest cause of death at every hospital per annum pre Covid-19 is Pneumonia. Pneumonia is a Respiratory Disease like Covid-19. Pneumonia can be broken down into 4 different causes of death: Bronchopneumonia, Aspiration Pneumonia, Community Acquired Pneumonia & Hospital Acquired Pneumonia.
These four causes when added together kill the largest number of people on an annual basis prior to the pandemic.
The Medical Examiner (one individual in each hospital), was certifying all these Pneumonia deaths as Covid-19 deaths. When 4 different diseases being grouped and now being called Covid-19, you will inevitably see Covid-19 with a huge death rate.
The mainstream media was reporting on this huge increase in Covid-19 deaths due to the Medical Examiner system being in place. Patients being admitted and dying with very common conditions such as Old Age, Myocardial Infarctions, End Stage Kidney Failure, Haemorrhages, Strokes, COPD & Cancer etc were all now being certified as Covid-19 via the Medical Examiner System.
Hospitals were switching to and from the Medical Examiner system and the Pre Pandemic System as when they pleased. When Covid-19 deaths needed to be increased, the hospital would switch to the Medical Examiner System. Doctors were one week being told they needed to complete an MCCD, to then be told the following week that they weren’t required to fill out an MCCD, as the Medical Examiner was handling this.
Hospitals were incentivised to report Covid-19 deaths over normal deaths, as the government was paying hospitals additional money for every Covid-19 death that was being reported. The Medical Examiner system ensured that Covid-19 was being put down as the cause of death. The government sends out the annual NHS budget to Primary Care Trusts. This is split to fund Hospitals and GP Surgeries. A clinical coding team at each hospital will assign codes to each treatment or death, so that money is paid out to the hospitals.
Any doctor who argued against Covid-19 as a cause of death was bullied and vilified. The General Medical Council maintains a register of all doctors within the UK. This ensures that there is a fear of being struck off for speaking out against an agenda. The GMC effectively controls all doctors in the UK. Even if a doctor realises what is going on and wants to speak out. They will think twice about talking, as they would be risking their entire career and everything that they’ve worked so hard for.
Doctors essentially have their hands tied, many have families, kids, mortgages and mouths to feed. If I was in their situation, I would think twice about speaking out, for fear of being struck off by the GMC and losing everything.
The NHS Track & Trace App, which was introduced to try and control the spread of the virus, did not apply to medical professionals. We were all asked to turn this off, as Doctors and staff isolating for 14 days disrupted patient flow, beds and the discharge of patients.
Any doctor that I spoke to regarding taking the Covid-19 vaccine, were insistent that they were going to wait for a period of time, before taking it themselves, to ensure that it was safe. How is it ethical to give a vaccine to your patients, but not want to take it yourself? In my 12 years of NHS service, never has a doctor pushed or influenced the public to take a vaccine. Yet on social media, I was seeing close friends who were doctors, starting to post on social media that they have taken the vaccine and that the public should. I wouldn’t be surprised if doctors were being forced to promote the vaccine by their superiors or if they were receiving monetary gain in doing so.
I have no doubt in my mind, that the Government has planned the entire pandemic since 2016, when they first proposed the change to medical death certification. Stress leads to disease and illness. Panic leads to people following whatever orders and instructions that are given to them by authority, such as prolonged mask use, which leads to an increase in admissions in to the NHS system due to hypoxia and bacterial pneumonia.
The NHS treatment pathway involved patients being placed onto ventilators. There is a 50% chance of death from this clinical decision alone. How many innocent people have died from the clinical decision to place them onto a ventilator.
During boardrounds (where every admitted patient is discussed), we were seeing patients on a daily basis being admitted due to suffering from adverse affects of taking the vaccine. Patients were blacking out after taking the vaccine or suffering from clots or strokes.
The NHS is all about money and making money. The safety of a patient didn’t seem like the most important thing. It was more about how do we make more beds available so that another patient can be treated. Patients with no next of kin are discharged to nursing homes with care packages. I can’t comment on what happened to these patients in nursing homes, during the pandemic, as I have no experience of their inner workings.
Patients are seen as money, even upon death, hospitals receive money for each death. Is there an actual concern for patient health and safety? I know numerous doctors who are driven primarily by money and monetary gain.
THE REASON WHY I LEFT THE NHS in 2021
56 yr old male, admitted into A&E with end stage kidney failure, has a previous history of regular dialysis treatment for this. No respiratory symptoms on admission and no temperature. However when tested with a PCR Test he unfortunately tests positive. This stays on his record throughout his admission. Our hospital is relatively small in comparison to others I have worked at, we have no dialysis machine as a result. We urgently need to transfer this patient to another hospital otherwise this patient will die. Our treating doctor calls up larger hospitals with a dialysis machine to organise his transfer. All doctors pick up the phone and request the Covid-19 status of the patient. A transfer is declined due to a Covid-19 infection protocol. Our doctors again reiterate the point that this patient will die without dialysis. We are told there is nothing that can be done and that the patient cannot be accepted for transfer.
This gentleman ended up dying without dialysis. Now please tell me what goes on the MCCD….
1a) Covid-19
2) End Stage Kidney Failure
Not written by the treating doctor who disagreed with this cause of death, but by a medical examiner, put in place by the government and the hospital.
When innocent people are being killed by a corrupt organisation and system, for pure monetary gain, I can’t stand by and be part of this anymore. My conscience was clear and I no longer wanted to be a part of this anymore. I am very blessed and lucky that I was in a position to walk away. I’ve been able to speak out, because my hands are not tied and I am not regulated by any organisation or governing body. I believe in speaking the truth and in doing so, I am only just an instrument for God.
I joined the NHS, 12 years ago because I had a desire to help those in need, but the moment I realised that I was not doing this anymore was the time for me to walk away. I apologise to you all if the above thread is confusing with regards to terminology or you cannot understand it’s contents. I’m hoping that at the very least, it can be understood by my fellow medical professionals or by journalists who would like to report the truth.
Turtles All the Way Down: Vaccine Science and Myth
Edited by Zoey O’Toole and Mary Holland
 If you are reading this, you are probably aware of the fierce debate surrounding vaccination and looking for information that will allow you to make the best decisions for yourself and your loved ones. Whether you are a parent or a parent to be, sorting through the many arguments on vaccines can be daunting. Still, you need an answer, a definitive one, to the crucial question: Who has it right in the great vaccine debate – the critics, who claim that vaccines often cause serious harm, or the medical establishment, which tells us that vaccines are safe and effective and the science is settled?
Rest assured, you have come to the right place. “Turtles All the Way Down: Vaccine Science and Myth” will resolve the vaccine question for you, once and for all. By the time you finish reading, not only will you see the answer clearly for yourself, you will also have the scientific references and specific quotes at your disposal that prove it — more than 1,200 of them – all from mainstream scientific papers and textbooks, the official publications of relevant government agencies, or manufacturers’ documents.
The book consolidates a great deal of information (accompanied by detailed analysis) that is scattered in hundreds of medical articles, books, and websites. All discussion is presented in clear and easy-to-understand language, so no medical education is required. It presents several original concepts in addition to laying a robust scientific foundation for the more established ones.
Some of the fundamental vaccine safety issues covered in the book are:
- How is safety demonstrated before a new vaccine is licensed? What technique do vaccine manufacturers use in clinical trials to make vaccines appear safer than they actually are?
- What “last ditch” technique is employed when the above one cannot be, and what are its grave (and damning) ethical implications?
- What is the scientific foundation of the safety of vaccination, and what practical tools does this body of science provide physicians to anticipate, diagnose, and treat vaccine injury?
- What fundamental flaws are built into vaccine adverse events reporting systems, and how are these systems used (or misused) by health authorities to support their safety claims?
- What kinds of post-marketing vaccine studies are conducted, and how can they be manipulated by researchers to produce “favorable” outcomes?
- Why would researchers want to skew vaccine research, and how could skewed results be promulgated by the scientific community?
- Why would medical journals publish faulty vaccine science? What is the role of the famed “peer review” in this process?
- What are “the studies that will never be done” by the medical establishment and how long it has resisted doing them? (Hint: more than 100 years!)
- What key CDC-recommended childhood vaccination guidelines were arbitrarily set, without an adequate scientific basis?
In addition, three cornerstones of vaccination lore are covered in depth:
- What is herd immunity, and how does it apply (or not) to the vaccines on the childhood schedule?
- What role did vaccines actually play in the historical decline of infectious disease?
- Was the paralysis associated with polio actually caused by the poliovirus? Is there a better explanation for the great paralysis epidemics of the 20th century? What are the “19 polio mysteries”?
The book is intended for parents overwhelmed by conflicting messaging on this important topic, but it is also an excellent reference for medical researchers and professionals who seek a better understanding of vaccine safety science. Whether you are new to the vaccine debate or a “veteran” seeking a deeper grasp of the science, this book is a must-read. It also serves as an excellent primer on vaccination to share with friends and relatives who may benefit from a deep dive into the subject.
Who designed global guidelines for puberty blockers?
Free West Media | January 13, 2023
Clinics around the world follow guidelines from the Netherlands for gender treatments in children. The basis for this is, among other things, a much-criticized study sponsored by a German hormone manufacturer.
More and more children and young people believe they have to question their gender identity. Some 60 minors were treated in the Netherlands in 2010, but the number has increased to around 1,600 last year. Another 1,800 people under the age of 18 were on the waiting list because gender clinics in the country are full.
Institutions around the world use a standard procedure developed in Amsterdam in the 1990s when it comes to the drug treatment of supposedly transsexual children.
A report by the Dutch newspaper NRC Handelsblad has meanwhile cast doubt on the directive and the independence of gender research at the Amsterdam UMC hospital. As strict as the conditions for treatment may appear, several complications have been overlooked: The terrible side effects of the heavy drug has been brushed off by doctors as being the lesser evil.
Hormone manufacturer sponsored ‘puberty blocker’ study
The approach with puberty inhibitors has since been known internationally as the “Dutch protocol”. The protocol has become the basis for the “gender-affirming standard of care” used throughout the world. Tens of thousands of children are affected worldwide, and in the Netherlands certainly several hundreds, although no precise figures are available.
Scientists investigated whether hormone treatment in transsexuals is more successful if their puberty was initially suppressed with medication. The sponsor of the study was the German hormone manufacturer.
Ferring Pharmaceuticals, the company that markets the drug Triptorelin as a puberty inhibitor had a strong commercial interest in the outcome. Primarily, treatment relies on administering hormones from the opposite sex: men are given oestrogen to become more feminine, women testosterone to become more masculine. But teenagers are additionally administered puberty inhibitors, which prevent boys from developing a low voice and beard growth and girls from developing breasts and other feminine shapes.
There are many criticisms of the study. Questionnaires were inconsistent, there was no control group at all, and the researchers used random samples from the 196 treated children for the results.
Several countries are moving away from ‘puberty blockers’
In the meantime, there is objection in more and more countries to the treatment of children with “puberty blockers”. Not only are they said to impair the physical sexual development of minors, but they can also cause osteoporosis, anorgasmia and infertility. According to the NRC, the drug is said to sometimes even impair the ability to make rational decisions.
Worldwide, there is increasing criticism of the scientific content and non-existent empirical basis of the Dutch protocol developed at the gender clinic of the Free University of Amsterdam. In several countries, health authorities have already decided to treat children mainly psychologically and prescribe puberty inhibitors only exceptionally. In Sweden, they concluded that “the risks currently outweigh the possible benefits” and spoke of possibly the country’s “worst medical scandal”.
In the UK, criticism of the Dutch protocol was so serious that the Tavistock gender clinic, the largest in the world, was closed by the authorities.
Sweden, Finland and Great Britain only want to prescribe the drug in rare, particularly severe cases. Instead, they are increasingly relying on psychological support for patients.
Since February last year, Sweden’s National Board of Health and Welfare has followed the Karolinska Institute’s policy regarding hormonal interventions for gender-dysphoric minors. Karolinska’s pediatric gender services at Astrid Lindgren Children’s Hospital (ALB) has ended the practice of prescribing puberty blockers and cross-sex hormones to gender-dysphoric patients under the age of 18.
Marketing redundant drugs for the wrong condition
In the US, Texas Attorney General Ken Paxton has been investigating two pharmaceutical companies for advertising puberty blockers to children. This is a condition they are not approved to treat.
In December, Paxton announced investigations under the Texas Deceptive Trade Practices Act into Endo Pharmaceuticals and AbbVie Inc., the two companies that sell puberty blockers. The drugs were approved to treat precocious puberty and forms of prostate cancer but were being marketed and prescribed off-label to treat gender dysphoria.
“These drugs were approved for very different purposes and can have detrimental and even irreversible side effects,” Paxton said. “I will not allow pharmaceutical companies to take advantage of Texas children.”
Pro-mask propaganda cranks up a couple of notches
By Gary Sidley | Coronababble | January 11, 2023
It’s happening again. After a period of welcome sanity – where those covering their faces in community settings could accurately be described as a deviant minority – the pro-mask propaganda machine has gone into overdrive. In what seems to be a co-ordinated enterprise, in the last couple of weeks our mainstream media has spread a variety of news stories pushing for more of us to hide our faces behinds strips of cloth and plastic. These include:
1. The announcement, at the end of 2022, that Northampton and Kettering General Hospitals have decided to re-impose mask requirements on all patients and visitors. This policy change provides further evidence of the mask postcode lottery operating within our healthcare system, where the decisions are left to the whims of local bureaucrats.
2. The pro-mask baton was taken up in the new year when Professor Susan Hopkins (chief medical advisor at the UK Health Security Agency) urged people who feel ill to wear a mask should they venture outside. In the grand scheme of masking zealotry, this was a modest recommendation, but – ominously – it does perpetuate the dubious assertion that wearing face coverings in the community reduces viral transmission, as well as preparing the ground for further incremental restrictions.
3. Throughout 2020/21, fear porn was highly effective in leveraging compliance with Covid restrictions, so no wear-a-mask propaganda drive would be complete without some scary stories and images from China. Our mainstream media were only too keen to oblige, with headlines about Covid deaths soaring, funeral homes overwhelmed and bodies being burnt in the streets in the aftermath of China’s relaxing of restrictions.
4. And then – predictably – the arch ‘nudgers’ (aka behavioural scientists) put their heads above the parapet, pushing their collectivist agenda. In a Guardian article, Professor Stephen Reicher repeated the tired trope that those opposed to mass masking were right-wing activists engaged in a culture war. He then urges the psychological manipulation of the masses by equating mask wearing with virtue (otherwise known as the ‘ego’ nudge) when he recommends, ‘reframing mask wearing as a community issue: less about individuals exercising personal responsibility; more about a collective exercising social responsibility, looking after each other, making sure we all come through this well’.
Meanwhile, Professor David Halpern (chief executive of the Behavioural Insights Team, the UK’s ‘Nudge Unit’) was promoting a similar narrative. In an interview for the Daily Telegraph (funded by the Reckitt Global Hygiene Institute), Halpern celebrates the use of ‘informal social pressure’ to get people to wear masks throughout the Covid era, and champions the concept of a ‘collectivist mindset’.
In effect, these two high-profile behavioural scientists are urging more covert shaming and peer pressure to get people to do the ‘right’ thing.
5. Reinforcements for the pro-mask push then arrived in the form of spokespeople for the World Health Organisation (WHO) – a prominent mouthpiece for the global pandemic industry – who have been doing the rounds again, regurgitating the messages we heard throughout the Covid era. For instance, Dr Maria Van Kerkove (an epidemiologist at the WHO’s ‘Health Emergencies Program’) has been popping up on social media sharing scary stories about variants and urging us all to mask up when ‘around other people’. While Dr Abdirahman Mahamud (an ‘Incident Manager’ at the WHO) stridently proclaims that ‘masking saves lives’, a preposterous assertion that would – in a rational world – send the official fact-checkers into overdrive.
6. If – God forbid – mask mandates were to return, public transport is likely to be the first target. So a story highlighting the risks associated with air travel would be gold dust for the propagandists. And, hey presto, we have one. Evidently, some researchers have been rummaging in the waste-water systems of 29 aeroplanes and found that, in 28 of them, they contained the virus responsible for Covid-19. (I wonder how many millions of other bugs they would have found among the excrement?).
7. And to cap it all, Nicola Sturgeon – the mask matriarch from north of the border – appears again at a press conference to urge us all to wear masks on public transport.
If our public health specialists had been following the science, the requirement to wear masks in community settings would never have been imposed; the bulk of the more robust, real-world evidence concludes that community masking has no appreciable impact on viral transmission. Also, it is apparent that the mask U-turn in 2020 – when our experts shifted from a ‘masks don’t work’ narrative to an authoritarian one involving mandates – was driven by ideology rather than empirical research. Taking these two observations into account, it is now morally appropriate to resist this latest push by the pro-mask lobby for the re-imposition of this ineffectual and dehumanising restriction.
And what would be the most effective way to counter further mask mandates? DO NOT COMPLY.
CHD Defeats NY State Healthcare Workers COVID Mandate!
Children’s Health Defense | January 13, 2023
In a groundbreaking decision filed today, NY State (NYS) Supreme Court Judge Gerard Neri held that the COVID-19 vaccine mandate for healthcare workers is now “null, void, and of no effect.” The court held that the NYS Dept. of Health lacked the authority to impose such a mandate as this power is reserved to the state legislature. Furthermore, the court found that the mandate was “arbitrary and capricious” as COVID-19 vaccines do not stop transmission, vitiating any rational basis for a mandate.
Children’s Health Defense (CHD) financed this lawsuit on behalf of Medical Professionals for Informed Consent and several individual healthcare workers. Sujata Gibson, lead attorney, said, “This is a huge win for New York healthcare workers, who have been deprived of their livelihoods for more than a year. This is also a huge win for all New Yorkers, who are facing dangerous and unprecedented healthcare worker shortages throughout New York State.”
CHD President Mary Holland stated, “We are thrilled by this critical win against a COVID vaccine mandate, correctly finding that any such mandate at this stage, given current knowledge is arbitrary. We hope that this decision will continue the trend towards lifting these dangerous and unwarranted vaccine mandates throughout the country.”
We are off to a great start in 2023.
Children’s Health Defense is a 501(c)(3) non-profit organization.
WHO Proposals Could Strip Nations of Their Sovereignty, Create Worldwide Totalitarian State, Expert Warns
By Michael Nevradakis, Ph.D. | The Defender | January 13, 2023
Secretive negotiations took place this week in Geneva, Switzerland, to discuss proposed amendments to the World Health Organization’s (WHO) International Health Regulations (IHR), considered a binding instrument of international law.
Similar negotiations took place last month for drafting a new WHO pandemic treaty.
While the two are often conflated, the proposed IHR amendments and the proposed pandemic treaty represent two separate but related sets of proposals that would fundamentally alter the WHO’s ability to respond to “public health emergencies” throughout the world — and, critics warn, significantly strip nations of their sovereignty.
According to author and researcher James Roguski, these two proposals would transform the WHO from an advisory organization to a global governing body whose policies would be legally binding.
They also would greatly expand the scope and reach of the IHR, institute a system of global health certificates and “passports” and allow the WHO to mandate medical examinations, quarantine and treatment.
Roguski said the proposed documents would give the WHO power over the means of production during a declared pandemic, call for the development of IHR infrastructure at “points of entry” (such as national borders), redirect billions of dollars to the “Pharmaceutical Hospital Emergency Industrial Complex” and remove mention of “respect for dignity, human rights and fundamental freedoms of people.”
Francis Boyle, J.D., Ph.D., professor of international law at the University of Illinois, said the proposed documents may also contravene international law.
Boyle, author of several international law textbooks and a bioweapons expert who drafted the Biological Weapons Anti-Terrorism Act of 1989, recently spoke with The Defender about the dangers — and potential illegality — of these two proposed documents
Other prominent analysts also sounded the alarm.
Proposals would create ‘worldwide totalitarian medical and scientific police state’
Meeting in Geneva between Jan. 9-13, the WHO’s IHR Review Committee worked to develop “technical recommendations to the [WHO’s] Director-General on amendments proposed by State Parties to the IHR,” according to a WHO document.
The IHR was first enacted in 2005, in the aftermath of SARS-CoV-1, and took effect in 2007. They constitute one of only two legally binding treaties the WHO has achieved since its inception in 1948 — the other being the Framework Convention on Tobacco Control.
As previously reported by The Defender, the IHR framework already allows the WHO director-general to declare a public health emergency in any country, without the consent of that country’s government, though the framework requires the two sides to first attempt to reach an agreement.
According to the same WHO document, the recommendations of the IHR Review Committee and the member states’ Working Group on Amendments to the International Health Regulations (2005) (WGIHR) will be reported to WHO Director-General Tedros Adhanom Ghebreyesus by mid-January, in the leadup to the WHO’s 76th World Health Assembly in late May.
Boyle said he questioned the legality of the above documents, citing for instance the fact that “the proposed WHO treaty violates the Vienna Convention on the Law of Treaties,” which was ratified in 1969, and which Boyle described as “the international law of treaties for every state in the world.”
Boyle explained the difference between the latest pandemic treaty and IHR proposals. “The WHO treaty would set up a separate international organization, whereas the proposed regulations would work within the context of the WHO we have today.”
However, he said, “Having read through both of them, it’s a distinction without a difference.” He explained:
“Either one or both will set up a worldwide totalitarian medical and scientific police state under the control of Tedros and the WHO, which are basically a front organization for the Centers for Disease Control and Prevention (CDC), Tony Fauci, Bill Gates, Big Pharma, the biowarfare industry and the Chinese Communist government that pays a good chunk of their bills.
“Either they’ll get the regulations or they’ll get the treaty, but both are existentially dangerous. These are truly dangerous, existentially dangerous and insidious documents.”
Boyle, who has written extensively on international law and argued cases on behalf of Palestine and Bosnia in the International Court of Justice, told The Defender he has “never read treaties and draft international organizations that are so completely totalitarian as the IHR regulations and the WHO treaty,” adding:
“Both the IHR regulations and the WHO treaty, as far as I can tell from reading them, are specifically designed to circumvent national, state and local government authorities when it comes to pandemics, the treatment for pandemics and also including in there, vaccines.”
Talks for both the proposed pandemic treaty and the proposed IHR amendments appear to follow a similar timeline, in order to be submitted for consideration during the WHO’s World Health Assembly May 21-30.
“It’s clear to me they are preparing both the regulations and the treaty for adoption by the World Health Assembly in May of 2023,” Boyle said. “That’s where we stand right now as I see it.”
According to the WHO, the International Negotiating Body (INB) working on the Pandemic Treaty will present a “progress report” at the May meeting, with a view toward presenting its “final outcome” to the 77th World Health Assembly in May 2024.
Boyle: proposed legally-binding pandemic treaty violates international law
Commenting on the pandemic treaty, Tedros said, “The lessons of the pandemic must not go unlearned.” He described the current “conceptual zero draft” of the treaty as “a true reflection of the aspirations for a different paradigm for strengthening pandemic prevention, preparedness, response and recovery.”
Roguski, in his analysis of the “Pandemic Treaty,” warned that it will create a “legally binding framework convention that would hand over enormous additional, legally binding authority to the WHO.”
The WHO’s 194 member states would, in other words, “agree to hand over their national sovereignty to the WHO.” This would “dramatically expand the role of the WHO,” by including an “entirely new bureaucracy,” the “Conference of the Parties,” which would include not just member states but “relevant stakeholders.”
This new bureaucracy, according to Roguski, would “be empowered to analyze social media to identify misinformation and disinformation in order to counter it with their own propaganda.”
The WHO currently partners with numerous such organizations, such as “fact-checking” firm NewsGuard, for these purposes.
Roguski said the pandemic treaty also would speed up the approval process for drugs and injectables, provide support for gain-of-function research, develop a “Global Review Mechanism” to oversee national health systems, implement the concept of “One Health,” and increase funding for so-called “tabletop exercises” or “simulations.”
“One Health,” a brainchild of the WHO, is described as “an integrated, unifying approach to balance and optimize the health of people, animals and the environment” that “mobilizes multiple sectors, disciplines and communities” and “is particularly important to prevent, predict, detect, and respond to global health threats such as the COVID-19 pandemic.”
In turn, “tabletop exercises” and “simulations” such as “Event 201,” were remarkably prescient in “predicting” the COVID-19 and monkeypox outbreaks before they actually occurred.
Roguski said the pandemic treaty would provide a structure to redirect massive amounts of money “via crony capitalism to corporations that profit from the declarations of Public Health Emergencies of International Concern” (‘pandemics’) and “the fear-mongering that naturally follows such emergency declarations.”
Boyle warned that the treaty and proposed IHR regulations go even further. “The WHO, which is a rotten, corrupt, criminal, despicable organization, will be able to issue orders going down the pike to your primary care physician on how you should be treated in the event they proclaim a pandemic.”
Moreover, Boyle said, the pandemic treaty would be unlike many other international agreements in that it would come into immediate effect. He told The Defender :
“If you read the WHO Treaty, at the very end, it says quite clearly that it will come into effect immediately upon signature.
“That violates the normal processes for ratification of treaties internationally under the Vienna Convention on the Law of Treaties, and also under the United States Constitution, requiring the United States Senate to give its advice and consent to the terms of the treaty by two-thirds vote.”
Indeed, Article 32 of the proposed treaty regarding its “Provisional application” states:
“The [treaty] may be applied provisionally by a Party that consents to its provisional application by so notifying the Depository in writing at the time of signature or deposit of its instrument of ratification, acceptance, approval, formal confirmation or accession.
“Such provisional application shall become effective from the date of receipt of the notification by the Secretary-General of the United Nations.”
“Whoever drafted that knew exactly what they were doing to bring it into force immediately upon signature,” said Boyle. “Assuming the World Health Assembly adopts the treaty in May, Biden can just order Fauci or whoever his representative is there to sign the treaty, and it will immediately come into effect on a provisional basis,” he added.
“I don’t know, in any of my extensive studies of international treaties, let alone treaties setting up international organizations, of any that has a provision like that in it,” said Boyle. “It’s completely insidious.”
Proposed amendments to IHR described as a WHO ‘power grab’
According to Roguski, who said the WHO is “attempting a power grab,” the proposed amendments to the IHR may be even more concerning than the pandemic treaty.
Roguski wrote that while he believes the pandemic treaty is “an important issue,” he also thinks it is “functioning as a decoy that is designed to distract people from the much larger and more immediate threat to our rights and freedoms, which are the proposed amendments to the International Health Regulations.”
The IHR Review Committee working on the proposed amendments “began its work on 6 October 2022,” according to a WHO document, and has convened five times since then, including this week’s meetings in Geneva. Access to the meetings was prohibited for the unvaccinated.
The final proposals of the IHR Review Committee and the WGIHR will be presented to Tedros in mid-January and to the World Health Assembly in May. According to Roguski, “If the proposed amendments are presented to the 76th World Health Assembly, they could be adopted by a simple majority of the 194 member nations.”
As a result, Roguski said, compared to the proposed pandemic treaty, “The amendments to the International Health Regulations are a much more immediate and direct threat to the sovereignty of every nation and the rights and freedoms of every person on earth.”
According to Roguski, “The proposed amendments would seek to remove 3 very important aspects of the existing regulations,” including “removing respect for dignity, human rights and fundamental freedoms” from the text of the IHR, changing the IHR from “non-binding” to “legally binding” and obligating nations to “assist” other nations.
“Essentially, the WHO’s Emergency Committee would be given the power to overrule actions taken by sovereign nations,” Roguski said.
According to Boyle, similarly to the pandemic treaty, “again, Biden can instruct his representative in May, assuming they adopt the regulations, to sign the regulations. And then, the Biden administration will treat that as a binding international agreement, just like they did with the 2005 regulations,” referring to the original IHR ratified that year.
He added:
“Those [the 2005 IHR] were signed and the U.S. State Department at that time considered them to be a legally binding international executive agreement that they list in the official State Department publication, ‘Treaties in Force.’
“In other words, they treat the 2005 regulations as if they were a treaty that never received the advice and consent of the United States Senate, and therefore the supreme law of the land under Article 6 of the United States Constitution that would be binding upon all state and local governments here in the United States, even if they are resisting, the IHR regulations or the WHO treaty.”
According to Roguski, “The proposed amendments would implement a great number of changes that everyone should absolutely disagree with.”
These changes include “dramatically expand[ing] the scope of the International Health Regulations from dealing with actual risks to dealing with anything that had the potential to be a risk to public health,” which Roguski said “would open up the doors wide to massive abuse beyond anything we have seen over the past three years.”
The proposed amendments also would shift the WHO’s focus “away from the health of real people” to “place primary preference upon the resilience of health care systems,” and would establish a “National Competent Authority” that “would be given great power to implement the obligations under these regulations,” Roguski said.
If the amendments come to pass, Roguski said, “The WHO will no longer need to consult any sovereign nation in which an event may or may not be occurring within that nation before declaring that there is a Public Health Emergency of International Concern within the borders of that nation.”
“Intermediate Public Health Alert[s],” “Public Health Emergenc[ies] of Regional Concern” and “World Alert and Response Notice[s]” could also be declared by the WHO’s director general, while the WHO would be recognized “as the guidance and coordinating authority during international emergencies.”
During such real or “potential” emergencies, the amendments would empower the WHO to mandate a variety of policies globally, which would be legally binding on member nations.
These policies could include requiring medical examinations or proof of such exams, requiring proof of vaccination, refusing travel, implementing quarantine and contact tracing or requiring travelers to furnish health declarations, to fill out passenger locator forms and to carry digital global health certificates.
“Competent health authorities” would also be empowered to commandeer aircraft and ships, while surveillance networks to “quickly detect public health events” within member nations would also be set up, as per the proposed amendments.
The WHO would also be empowered to be involved in the drafting of national health legislation.
The proposed amendments would give the WHO the power to develop an “Allocation Plan,” allowing it to commandeer the means of production of pharmaceuticals and other items during an “emergency,” and would oblige developed nations to provide “assistance” to developing nations.
“The proposed amendments … would facilitate digital access to everyone’s private health records,” Roguski said, and similar to the proposals in the pandemic treaty, would “also facilitate the censorship of any differing opinions under the guise of mis-information or dis-information.”
Roguski said the proposals are being made despite a “lack of input from the general public” by “unknown and unaccountable delegates” using vague and “undefined terminology” and vague criteria “by which to measure preparedness.”
He said the proposals would “trample our rights and restrict our freedoms,” including the right to privacy, to choose or refuse treatment, to express one’s opinions, to protect one’s children, to be with family and friends and to be free from discrimination, including discrimination on the basis of one’s vaccination status.
“The finality of decisions made by the Emergency Committee” foreseen by the amendments “would be a direct attack on national sovereignty,” Roguski said.
How did we get here?
According to the WHO, the members of the INB — during a meeting in Geneva July 18-21, 2022 — reached a “consensus,” agreeing that any new “convention, agreement or other international instrument on pandemic prevention, preparedness and response” would be “legally binding” on member states.
For Boyle, this is the WHO’s response to the “enormous opposition” to the COVID-19-related restrictions of the past three years. He told The Defender :
“As far as I can figure out what happened here was this: As you know, there has been enormous opposition here in the United States [against] these totalitarian edicts coming out, and this was under both Trump and Biden.
“These totalitarian edicts coming out of the federal government, the White House, the CDC, everyone else on this pandemic and also the vaccine mandates, there’s enormous grassroots opposition. And so, as far as I can tell what happened, this culminated in Trump pulling us out of the WHO, which I think was a correct decision.
“So you know, I’m a political independent. I’m just looking at this subjectively. Now, what happened was then, when Biden came to power, his top scientific advisor was Tony Fauci. So Biden put us back into the WHO and then appointed Fauci as the U.S. representative on the Executive Committee of the WHO.
“That’s where both the IHR regulations and the WHO treaty come from: to circumvent the enormous grassroots opposition to the handling of the edicts coming out of the federal government with respect to the pandemic and the vaccine mandates.”
Boyle explained what “legally binding” would mean in this context, if either set of proposals comes to pass:
“What will happen is the WHO will come up with an order, this new organization will come up with an order that they will then send to Washington, D.C., whereupon the Biden administration will enforce it as a binding international obligation of the United States of America under Article 6 of the United States Constitution, and it will usurp the state and local health authorities, who generally have constitutional authority to deal with public health under the 10th Amendment to the United States Constitution.
“The Biden administration will then argue that either the regulations or the treaty will usurp the 10th Amendment to the United States Constitution and state and local health authorities, governors, attorney generals, public health authorities will have to obey [any] order coming out of the WHO.”
Referring to his remarks about the illegality of the two proposals under the Vienna Convention on the Law of Treaties, Boyle clarified that under Article 18 of the convention, “a treaty does not come into force when signed. When the state has signed the treaty, it is only obligated to act in a manner that does not defeat the object and purpose of the treaty.”
Article 18 states:
“A State is obliged to refrain from acts which would defeat the object and purpose of a treaty when: (a) it has signed the treaty or has exchanged instruments constituting the treaty subject to ratification, acceptance or approval, until it shall have made its intention clear not to become a party to the treaty.”
According to Boyle a state’s signature “does not provisionally bring the treaty into force.”
Boyle also described the proposals as “a massive power grab by Fauci, the CDC, the WHO, Bill Gates, Big Pharma, the biowarfare industry and Tedros.”
He added:
“I’ve never seen anything like this in any of my research, writing, teaching, litigating international organizations going back to the First Hague Peace Conference of 1899, up until today.”
Roguski and Boyle argued that the U.S. — and other countries — should exit the WHO. Boyle told The Defender :
“I’m not a supporter of President Trump, but I think we have to go back to pulling out of the WHO right away. In the last session of Congress, there was legislation introduced pulling us out of the WHO. We need that legislation reintroduced immediately, in this new session of Congress.
“I think the House of Representatives has to make it clear that they object, that there’s no way they are going to go along with any orders coming out of the WHO, the World Health Assembly [WHA] or this new international pandemic organization, and that they have the power of the purse and that they will defund anything related to the WHO.”
However, for Boyle, this is not just a matter for federal lawmakers. “We need, certainly, the state governments here in the United States to take the position that they will not comply with any decisions coming out of the WHO, the WHA or this new international pandemic organization,” adding that he recently made such recommendations to Florida Gov. Ron DeSantis.
“We need that replicated all over the United States, on a state-by-state basis,” said Boyle, “and I think we need it right away because they’re trying to rush through these WHO regulations and the [pandemic] treaty for the WHO assembly in May.”
Close cooperation with Gates Foundation, others
According to the WHO, the INB discussions are taking place not just among all member states, but also with “relevant stakeholders” listed in document A/INB/2/4.
Who are these stakeholders? One example is GAVI, The Vaccine Alliance, listed as an “Observer” alongside the Holy See (Vatican), Palestine and the Red Cross.
As previously reported by The Defender, GAVI proclaims a mission to “save lives and protect people’s health,” and states it “helps vaccinate almost half the world’s children against deadly and debilitating infectious diseases.”
GAVI describes its core partnership with various international organizations, including names that are by now familiar: the WHO, UNICEF, the Bill & Melinda Gates Foundation and the World Bank, and with the ID2020 Alliance, which supports the implementation of “vaccine passports.”
ID2020’s founding members include the Gates Foundation, Microsoft and the Rockefeller Foundation.
In turn, the Gates Foundation, alongside Bloomberg Philanthropies, the Clinton Health Access Initiative, the Rockefeller Foundation, the International Air Transport Association (IATA — think “vaccine passports”) and the Population Council — founded by John D. Rockefeller and known for its “population control” initiatives — are listed in the same WHO document under Annex C as “non-state actors in official relations with WHO.”
“Other stakeholders, as decided by the INB, invited to attend [and] speak at open sessions of meetings of the INB [and] provide inputs to the INB” include IATA, the International Civil Aviation Organization and the World Bank Group.
“Open Philanthropy” and George Soros’ Open Society Foundations, and “nonprofit consumer advocacy organization” Public Citizen, are among the groups listed in the WHO document as “other stakeholders” that can “provide inputs to the INB,” alongside two Russian state-affiliated health organizations.
Lead U.S. negotiator for the pandemic treaty, Pamela Hamamoto — previously an investment banker with Goldman Sachs and Merrill Lynch — “helped coordinate early responses to the Ebola outbreak in West Africa in 2015 … and a strengthened WHO response.”
Hamamoto also was “instrumental in the 2014 launch of the Global Health Security Agenda” (GHSA), a “global effort … focused on strengthening the world’s ability to prevent, detect, and respond to infectious disease threats,” spearheaded by the CDC and founded with the purpose of accelerating the IHR passed in 2005.
The World Bank, the Global Health Security Consortium, the Private Sector Roundtable and the WHO are part of the GHSA’s steering group. AstraZeneca and Johnson & Johnson, manufacturers of COVID-19 vaccines, are members of the Private Sector Roundtable.
Advising the GHSA is the “GHSA Consortium,” which includes within its steering committee the Johns Hopkins Bloomberg School of Public Health (which hosted Event 201) and the Nuclear Threat Initiative (NTI).
As previously reported by The Defender, the NTI organized a “tabletop exercise” that predicted a “fictional” May 2022 monkeypox outbreak with remarkable accuracy. “Open Philanthropy” funded the final report for this exercise.
General members of the GHSA Consortium include the Gates Foundation, Amazon Web Services (which maintained COVID-19 immunization databases for the CDC), Boston University and the institution’s National Emerging Infectious Diseases Laboratories (NEIDL), and Emergent BioSolutions.
As previously reported by The Defender, NEIDL is where “a new strain of COVID-19 that killed 80% of the mice infected with the virus” was recently developed.
Emergent BioSolutions, which produced the Johnson & Johnson vaccine and attained infamy for losing a $600 million federal contract after millions of vaccine doses were ruined, is connected to the 2001 Dark Winter anthrax simulation.
In June 2022, with the support of the U.S., Italy (current chair of the GHSA) and then-G20 president Indonesia, the World Bank announced the launch of a $1 billion “pandemic fund.”
In November 2022, Indonesian Minister of Health Budi Gunadi Sadikin, at the G20 meeting held in Bali, pushed for an international “digital health certificate acknowledged by the WHO” to enable the public to “move around.” Indonesia is also a permanent member of the GHSA’s steering group.
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Ivermectin’s Effectiveness Proven Again; 72% Efficacy
800,000 people died in the USA for nothing
By Igor Chudov | January 11, 2023
You are not a horse! You are not a cow! That’s what the FDA told us to dissuade us from taking Ivermectin.

Fortunately, we are also not sheep and did not believe the FDA. Many of us stocked up on Ivermectin, and most found it helpful. While I did not use it when I had my Covid in Nov 2020, it worked great for my wife in Dec 2021 and other family members during the summer of 2022.
Ivermectin, a cheap and safe generic medication, was of little interest to profit-minded pharmaceutical giants like Pfizer and Merck. Therefore, they conspired with the FDA to lie that it did not work and instead pushed expensive Covid vaccines and non-working drugs like mutagenic Molnupiravir and rebound-causing Paxlovid.
MedinCell conducted a randomized controlled trial of their version of Ivermectin and found that it reduces Covid infections by 72%!

The study was very well designed because the participants were EXPOSED to the Covid infection within five days. Given the exposure, the outcomes were more likely to happen and thus were easier to compare between groups, giving the trial greater statistical power.
The 72% reduction in infection is much MORE effective than the “covid vaccine.”
The trial encompassed the period of Mar-Nov 2022, thus giving us the real-world effectiveness of Ivermectin against the Omicron variant.
While I am happy at the finding, there are several things to be NOT happy about.
- If we are to believe official numbers, about 1,121,000 people died of Covid in the USA. Given published effectiveness estimates of Ivermectin coming from honest studies, Ivermectin could have saved eight hundred thousand of those lives. The intentional suppression of Ivermectin cost us so dearly.
- Given a 72% reduction in infection, natural immunity with Ivermectin would likely have stopped the pandemic entirely in 2020.
- Had Ivermectin been recognized as an effective antiviral, the “Covid vaccines” could not get EUA approval, and thus we would avoid thousands of vaccine victims and destroyed immune systems.
- Second-largest Democratic donor and the largest crypto thief Sam Bankman-Fried donated 18 million dollars to the Together trial after it falsely demonstrated a finding that Democrat-aligned Covid vaccine pushers wanted, namely that Ivermectin allegedly was useless.
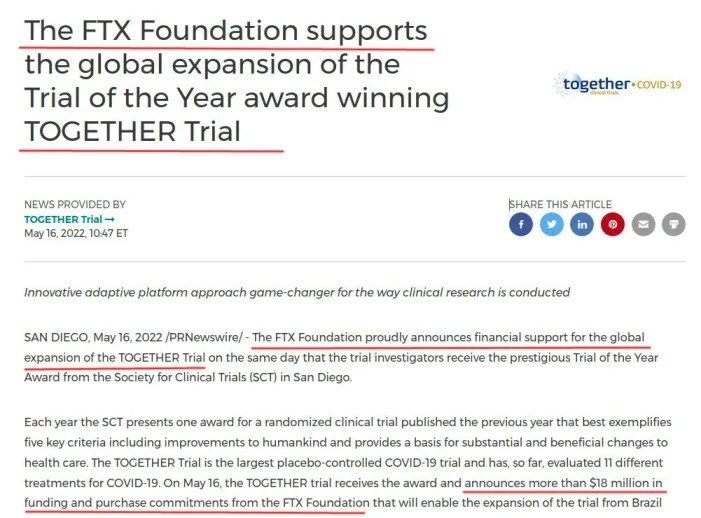
The good news here is that Ivermectin works.
Here are some of my other articles about Ivermectin — with honest trials showing a comparable reduction in illness and death.
So, thousands of people died of Covid. Thousands of people died of Covid vaccines. The pandemic, prolonged by vaccination, is raging and reinfects people with immunity disabled by mystery genetic treatments. My prediction from last March, unfortunately, is coming true.
AIDS-Like “Chronic Covid” is Taking Over Europe, Australia and NZ
All of this happened because of the recklessness and greed of the biomedical-industrial complex, which developed Sars-Cov-2 and then pushed an unproven, ineffective vaccine that worsened the pandemic.
While the above paragraph is upsetting, the good news is that Ivermectin was validated, and “we have the tools” to manage a Covid infection or exposure.
Lastly, take a minute to think about millions of victims of suppression of Ivermectin worldwide, who died to make a few companies and foundations richer and more powerful.
Will Ivermectin ever be recommended officially? And do we even care about such approval if we can still order it online?
Featured Video

or go to
Aletho News Archives – Video-Images
Book Review
The Zeolite Book — First Edition, 2026, Paperback
The volcanic mineral medicine will not patent — for the toxic burden medicine will not name
Lies are Unbekoming – October 30, 2026
 Zeolite is old. It is in Roman concrete that has held for two thousand years. It’s in the water filters of ancient cisterns. It’s in the stomachs of Pacific livestock whose keepers knew, somehow, that this grey crumbling rock made the animals healthier. It’s in Soviet clinical protocols from the 1960s. It’s in the standard emergency response to the Chernobyl explosion.
In 1986, after the Chernobyl reactor failure, the Soviet Union manufactured and distributed natural zeolite at industrial scale — for soil remediation, for livestock feed, for human consumption, for the cleanup itself. Karl Hecht, who had been director of the Institute for Experimental and Clinical Pathophysiology at the Charité of Humboldt University Berlin, spent the six decades after that building the clinical research base — on silicon’s role in human health, on zeolite’s clinical safety, on its applications in ageing. In 2018, Pavelić and colleagues published a comprehensive clinical safety review of natural clinoptilolite in Frontiers in Pharmacology. In 2019, Mastinu analysed its binding affinities. In the Western medical literature, these works sit largely uncited.
What has not been treated at book length, until now, is how a volcanic mineral with six decades of Soviet clinical work behind it, two major peer-reviewed Western reviews, and ongoing clinical use across the former Eastern Bloc, remains almost entirely absent from Western medical practice — and what the toxic burden it’s meant to address actually is.
The Zeolite Book gathers the Soviet clinical record, the Western peer-reviewed studies, three contemporary practitioner voices, and three serious counterviews into one honest treatment. That’s why the book runs to seven appendices. 288 pages, four parts, three practitioner voices, three counterviews, seven appendices. The honest treatment is the argument.
Blog Roll
 Aletho News
- Wrong, AP and NPR: Europe’s 50,000 Heat Deaths Are a Computer-Model Estimate, Not a Real Body Count
- Questioning Your Doctor Is Now Considered A Psychological Problem (Seriously)
- London tourism expo promotes Israeli agency linked to theft of Palestinian land
- Dockworkers launch global strike against Israeli and US military shipments
- Europe facing gas price shock – Gazprom chief
- Ukraine continues recruiting people with disabilities
- Weaponized Journalism: 2021 Sayer Ji Interview with NPR
- Beyond Netanyahu: what Israel’s election means for Palestinians
- Lithuania plans universal conscription
- Lies, Damn Lies, and Ukraine News
- If Americans Knew
- 1,300 will gather in Palo Alto on Nov. 1 for Z3 Conference on Zionism
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- The Long Arm of AIPAC
- Genocidal intent behind Hebron assault, rights group says
- This week, Israel killed 8-year-old who survived bombing that wiped out her family
- DAILY UPDATE: Latest essential news on Palestine, Israel, & region
- Israeli soldier poses at damaged Lebanon church, sparking anger
- New Report. Manufacturing the Great Replacement: Is Israel behind one of the largest racist influence campaigns ever documented?
- ‘Arab voice doesn’t count’: Jewish Israeli blocs reject Palestinian support
- Whether Bibi Stays or Goes, the ‘Special Relationship’ Must End
- No Tricks Zone
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!

