If Hospitals Are Currently Under Pressure, They Only Have Themselves to Blame
By In-house doctor | The Daily Sceptic | April 10, 2022
There follows a guest post by our in-house doctor, a former senior NHS medic, who says the latest ‘perfect storm’ causing pressure on the health service in parts of the country is more a self-induced squall.
In the middle of last week, several NHS Trusts issued warnings about the acute strain their services were under. The South Central Ambulance Service went so far as to declare a critical incident – normally reserved for a situation in which demands on the service exceed the capacity to manage those demands. I was surprised that so many NHS bodies spread over a wide geographical area issued public warnings about their failure to cope at the same time. Statements referred to high demand on services (hardly news) and lacked any specific detail about critical capacity constraints. Accordingly, the Daily Sceptic asked me to interrogate the available data to work out the extent to which a Covid resurgence might be responsible for the latest ‘perfect storm’ to hit the NHS.
Graph 1 shows daily admissions of Covid positive patients from the community. Admissions have risen in the last few weeks, but seem to be tailing off. Data from Graph 1 have been the subject of hysterical articles in the mainstream press implying the latest Omicron BA.2 subvariant may be triggering a new wave of acute Covid infections. It’s not sensible to interpret Graph 1 as a stand-alone figure without considering contextual information from other datasets.
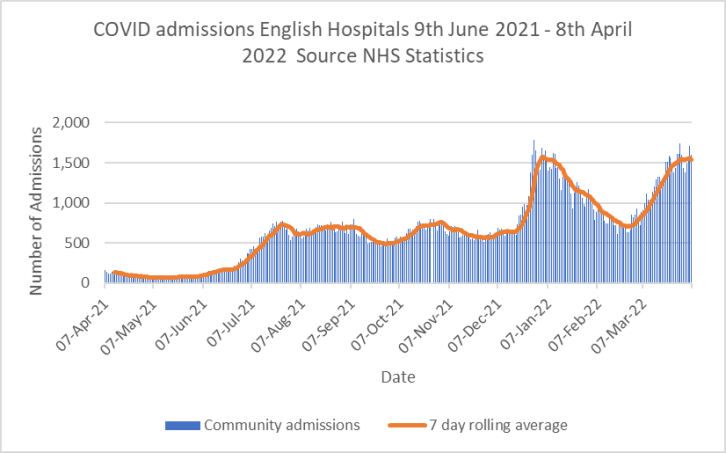
Graph 1
Graph 2 for example shows information from the Primary Diagnosis dataset. Regular readers will recall this set shows the numbers of patients admitted suffering from acute Covid compared to the patients testing positive for Covid but admitted for another condition. The grey line shows the ratio is gradually falling – in other words the headline figures in Graph 1 are misleading, because nearly 60% of those patients are not actually ill with Covid but admitted for other reasons.
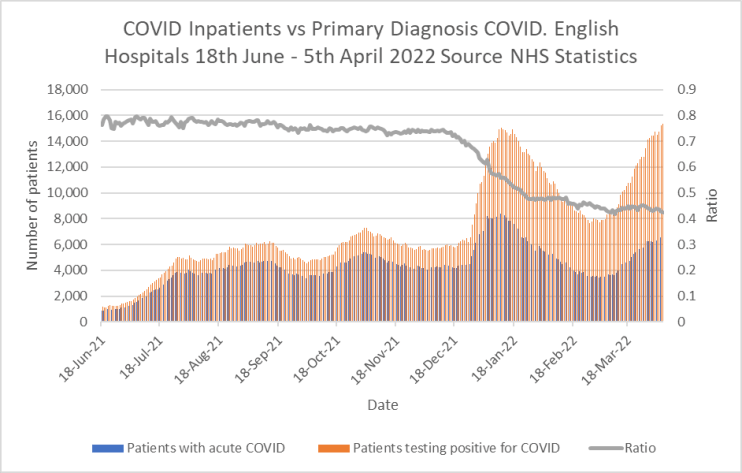
Graph 2
Graph 3 shows the numbers of patients testing positive for Covid in intensive care departments. The rise in cases seen in Graph 1 since the beginning of March 2022 is absent – so although there are more hospital inpatients testing positive for Covid than at the end of February, they are not ending up in critical care. Further, the data from the most recent ICNARC report reveal that the latest tranche of Covid ICU patients have lower oxygen requirements and better respiratory ratios than the cohort from this time last year – in other words, they are not as acutely ill.
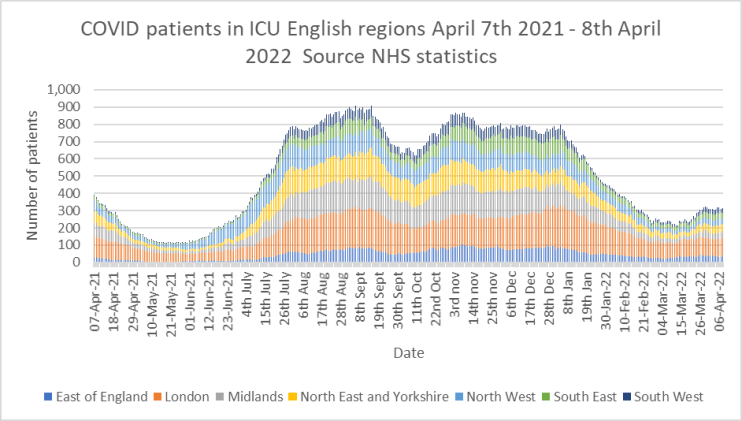
Graph 3
Graph 4 is very instructive. It shows the average length of stays of Covid patients up to the end of December 2021. This data was released in March and unfortunately is only complete up to the end of 2021, but it is reasonable to infer that current length of stay is unlikely to be worse now than in December of 2021, due to increased availability of new monoclonal antibody drugs which reduce disease severity for the highest risk patients. Graph 4 expresses average length of stay as the mean average (blue bars) and the median average (orange bars). Both these averages are steadily reducing with the median length of stay being down to four days by the end of December 2021. For the information of statistically curious readers, the median average in this case is probably more representative of the situation as the mean average can easily be skewed to the upside by a small number of very long-stay patients.
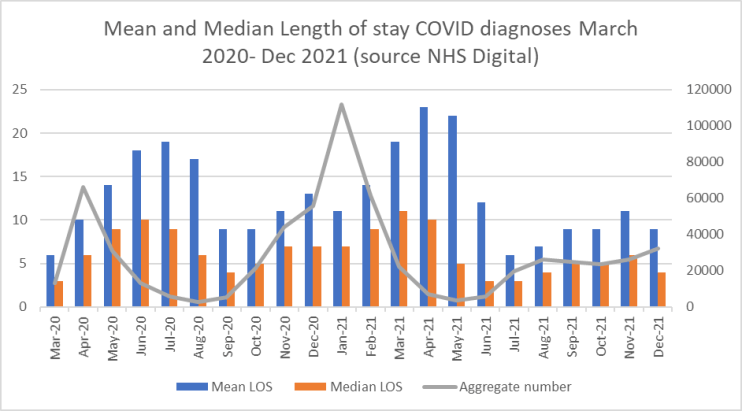
Graph 4
Overall, from the available Covid-specific patient data, we see a rise in total positive Covid tests on admission from the community, but fewer than half of these patients are symptomatic for Covid. Very few patients are ill enough to need ICU care and the length of stay for acutely ill Covid patients continues to fall. The vast majority require a few days of supplementary oxygen, intravenous steroids and monoclonal antibody infusion (or other adjunctive therapies) before being fit to discharge. So where is the problem?
Last week Saffron Cordery, deputy CEO of NHS providers, commented that staff absences played a part in the current crisis. Graph 5 shows the data for Covid related staff absences up to March 2nd (the latest figures released) – they don’t seem to have changed much lately and were on a downward trend since the turn of the year. It’s possible they may have started to increase again, but the figures are not yet released for public scrutiny.
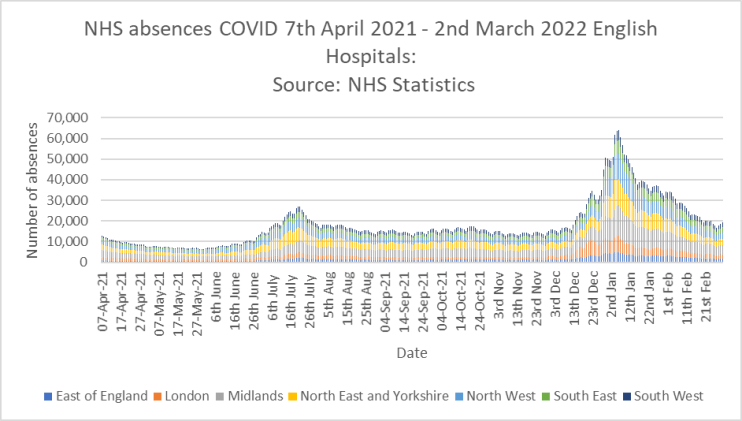
Graph 5
My personal suspicion is that Graph 6 shows the main issue causing trouble in hospitals. Graph 6 shows the number of patients in hospitals deemed medically fit for discharge. It is shown as a stacked bar chart, so the blue bar represents the patients who actually were discharged and the orange bar shows patients who were fit for discharge but had to remain in hospital for administrative reasons (often referred to as ‘bed blocking’). Readers will readily notice the ‘weekend effect’ in the figures, and that about 11,000 patients per day are in hospital when they are fit to be discharged – about 10% of the total NHS bed stock.
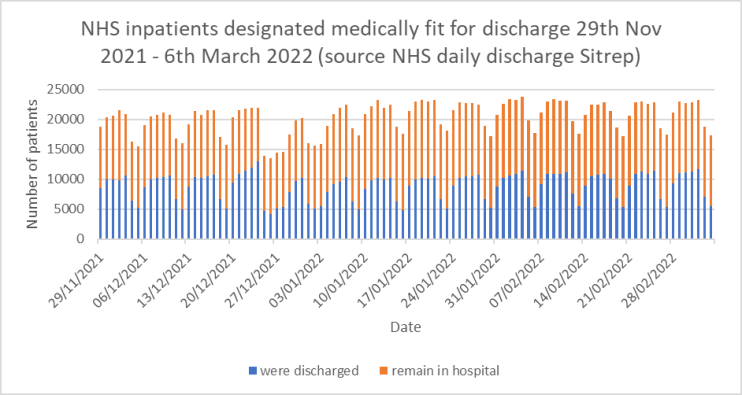
Graph 6
Over two years into the pandemic, the NHS does not yet seem to have solved fundamental administrative problems in relation to patient flow through the system. I am also aware from personal communication with colleagues that most NHS trusts are still imposing unnecessary Covid protocols which add to the time taken to complete basic episodes of care such as routine operations. This reduces efficiency still further in a healthcare system not renowned for operational efficiency in the first place.
Speaking about the latest crisis, Mark Ainsworth, Director of Operations at the South Central Ambulance Service, said declaring a critical incident meant it could focus its resources on the neediest patients.
Discharging medically fit patients from hospital and exercising a modicum of common sense when compiling Standard Operating procedures might achieve the same effect.
Putting Big Pharma on Trial in the COVID-19 Era, Part 4
The Hypocrisy of “Misinformation”
By Rebecca Strong · February 16, 2022
I find it interesting that “misinformation” has become such a pervasive term lately, but more alarmingly, that it’s become an excuse for blatant censorship on social media and in journalism. It’s impossible not to wonder what’s driving this movement to control the narrative. In a world where we still very clearly don’t have all the answers, why shouldn’t we be open to exploring all the possibilities? And while we’re on the subject, what about all of the COVID-related untruths that have been spread by our leaders and officials? Why should they get a free pass?
Fauci, President Biden, and the CDC’s Rochelle Walensky all promised us with total confidence the vaccine would prevent us from getting or spreading COVID, something we now know is a myth. (In fact, the CDC recently had to change its very definition of “vaccine ” to promise “protection” from a disease rather than “immunity”— an important distinction). At one point, the New York State Department of Health (NYS DOH) and former Governor Andrew Cuomo prepared a social media campaign with misleading messaging that the vaccine was “approved by the FDA” and “went through the same rigorous approval process that all vaccines go through,” when in reality the FDA only authorized the vaccines under an EUA, and the vaccines were still undergoing clinical trials. While the NYS DOH eventually responded to pressures to remove these false claims, a few weeks later the Department posted on Facebook that “no serious side effects related to the vaccines have been reported,” when in actuality, roughly 16,000 reports of adverse events and over 3,000 reports of serious adverse events related to a COVID-19 vaccination had been reported in the first two months of use.
One would think we’d hold the people in power to the same level of accountability — if not more — than an average citizen. So, in the interest of avoiding hypocrisy, should we “cancel” all these experts and leaders for their “misinformation,” too?
Vaccine-hesitant people have been fired from their jobs, refused from restaurants, denied the right to travel and see their families, banned from social media channels, and blatantly shamed and villainized in the media. Some have even lost custody of their children. These people are frequently labeled “anti-vax,” which is misleading given that many (like the NBA’s Jonathan Isaac) have made it repeatedly clear they are not against all vaccines, but simply making a personal choice not to get this one. (As such, I’ll suggest switching to a more accurate label: “pro-choice.”) Fauci has repeatedly said federally mandating the vaccine would not be “appropriate” or “enforceable” and doing so would be “encroaching upon a person’s freedom to make their own choice.” So it’s remarkable that still, some individual employers and U.S. states, like my beloved Massachusetts, have taken it upon themselves to enforce some of these mandates, anyway. Meanwhile, a Feb. 7 bulletin posted by the U.S. Department of Homeland Security indicates that if you spread information that undermines public trust in a government institution (like the CDC or FDA), you could be considered a terrorist. In case you were wondering about the current state of free speech.
The definition of institutional oppression is “the systematic mistreatment of people within a social identity group, supported and enforced by the society and its institutions, solely based on the person’s membership in the social identity group.” It is defined as occurring when established laws and practices “systematically reflect and produce inequities based on one’s membership in targeted social identity groups.” Sound familiar?
As you continue to watch the persecution of the unvaccinated unfold, remember this. Historically, when society has oppressed a particular group of people whether due to their gender, race, social class, religious beliefs, or sexuality, it’s always been because they pose some kind of threat to the status quo. The same is true for today’s unvaccinated. Since we know the vaccine doesn’t prevent the spread of COVID, however, this much is clear: the unvaccinated don’t pose a threat to the health and safety of their fellow citizens — but rather, to the bottom line of powerful pharmaceutical giants and the many global organizations they finance. And with more than $100 billion on the line in 2021 alone, I can understand the motivation to silence them.
The unvaccinated have been called selfish. Stupid. Fauci has said it’s “almost inexplicable” that they are still resisting. But is it? What if these people aren’t crazy or uncaring, but rather have — unsurprisingly so — lost their faith in the agencies that are supposed to protect them? Can you blame them?
Citizens are being bullied into getting a vaccine that was created, evaluated, and authorized in under a year, with no access to the bulk of the safety data for said vaccine, and no rights whatsoever to pursue legal action if they experience adverse effects from it. What these people need right now is to know they can depend on their fellow citizens to respect their choices, not fuel the segregation by launching a full-fledged witch hunt. Instead, for some inexplicable reason I imagine stems from fear, many continue rallying around big pharma rather than each other. A 2022 Heartland Institute and Rasmussen Reports survey of Democratic voters found that 59% of respondents support a government policy requiring unvaccinated individuals to remain confined in their home at all times, 55% support handing a fine to anyone who won’t get the vaccine, and 48% think the government should flat out imprison people who publicly question the efficacy of the vaccines on social media, TV, or online in digital publications. Even Orwell couldn’t make this stuff up.

Photo credit: DJ Paine on Unsplash
Let me be very clear. While there are a lot of bad actors out there — there are also a lot of well-meaning people in the science and medical industries, too. I’m lucky enough to know some of them. There are doctors who fend off pharma reps’ influence and take an extremely cautious approach to prescribing. Medical journal authors who fiercely pursue transparency and truth — as is evident in “The Influence of Money on Medical Science,” a report by the first female editor of JAMA. Pharmacists, like Dan Schneider, who refuse to fill prescriptions they deem risky or irresponsible. Whistleblowers, like Graham and Jackson, who tenaciously call attention to safety issues for pharma products in the approval pipeline. And I’m certain there are many people in the pharmaceutical industry, like Panara and my grandfather, who pursued this field with the goal of helping others, not just earning a six- or seven-figure salary. We need more of these people. Sadly, it seems they are outliers who exist in a corrupt, deep-rooted system of quid-pro-quo relationships. They can only do so much.
I’m not here to tell you whether or not you should get the vaccine or booster doses. What you put in your body is not for me — or anyone else — to decide. It’s not a simple choice, but rather one that may depend on your physical condition, medical history, age, religious beliefs, and level of risk tolerance. My grandfather passed away in 2008, and lately, I find myself missing him more than ever, wishing I could talk to him about the pandemic and hear what he makes of all this madness. I don’t really know how he’d feel about the COVID vaccine, or whether he would have gotten it or encouraged me to. What I do know is that he’d listen to my concerns, and he’d carefully consider them. He would remind me my feelings are valid. His eyes would light up and he’d grin with amusement as I fervidly expressed my frustration. He’d tell me to keep pushing forward, digging deeper, asking questions. In his endearing Bronx accent, he used to always say: “go get ‘em, kid.” If I stop typing for a moment and listen hard enough, I can almost hear him saying it now.
People keep saying “trust the science.” But when trust is broken, it must be earned back. And as long as our legislative system, public health agencies, physicians, and research journals keep accepting pharmaceutical money (with strings attached) — and our justice system keeps letting these companies off the hook when their negligence causes harm, there’s no reason for big pharma to change. They’re holding the bag, and money is power.
I have a dream that one day, we’ll live in a world where we are armed with all the thorough, unbiased data necessary to make informed decisions about our health. Alas, we’re not even close. What that means is that it’s up to you to educate yourself as much as possible, and remain ever-vigilant in evaluating information before forming an opinion. You can start by reading clinical trials yourself, rather than relying on the media to translate them for you. Scroll to the bottom of every single study to the “conflicts of interest” section and find out who funded it. Look at how many subjects were involved. Confirm whether or not blinding was used to eliminate bias. You may also choose to follow Public Citizen’s Health Research Group’s rule whenever possible: that means avoiding a new drug until five years after an FDA approval (not an EUA, an actual approval) — when there’s enough data on the long-term safety and effectiveness to establish that the benefits outweigh the risks. When it comes to the news, you can seek out independent, nonprofit outlets, which are less likely to be biased due to pharma funding. And most importantly, when it appears an organization is making concerted efforts to conceal information from you — like the FDA recently did with the COVID vaccine — it’s time to ask yourself: why? What are they trying to hide?
In the 2019 film “Dark Waters” — which is based on the true story of one of the greatest corporate cover-ups in American history — Mark Ruffalo as attorney Rob Bilott says: “The system is rigged. They want us to think it’ll protect us, but that’s a lie. We protect us. We do. Nobody else. Not the companies. Not the scientists. Not the government. Us.”
Words to live by.
Report on the FDA’s 4/6/22 Advisory Committee (VRBPAC) meeting on the selection of future boosters
While the committee got nowhere on the choice of next boosters, there were a few very important reveals
By Meryl Nass, MD | April 10, 2022
Authorizing vaccine for the 6 months to 5 year old group was never mentioned. Can it be that FDA is finally grappling with the awful data, the longterm risks of vaccination, and will turn away from unleashing these vaccines on our youngest kids? Or is there simply too much money at stake, too many promised school mandates, too many done deals behind closed doors?
Important takeaways
1. Many members and presenters agreed that antibody levels (aka titers) are not a valid measure of immunity (they are not a correlate of protection, and there is currently NOTHING measurable in the blood that is considered a valid reflection of immunity). This admission is HUGE, as it reveals that neutralizing antibody titers can no longer be used to authorize or approve COVID vaccines.
2. Therefore the only way to determine vaccine effectiveness is a clinical trial.
3. No one at the meeting (nearly 30 people) ventured a guess as to what strain might cause the next COVID wave. All seemed to agree there would be another wave, but this was just a guess. However, without a variant you can’t make a vaccine and you can’t conduct a clinical trial to see if the vaccine works. And you can’t possibly do this by June, to make vaccine available for the fall, when FDA and the VRBPAC expect it will be needed.
4. Dr. Peter Marks, the director of the FDA’s vaccine division, CBER, admitted that the 4th booster dose authorized last week was a “stopgap measure”– in other words, he claims it was to kick the waning vaccine efficacy can down the road.
5. Claims were repeatedly made that vaccine still protects against severe outcomes and death, but FDA’s lead scientist for this presentation, Doran Fink, admitted that efficacy is also waning for severe outcomes. I’ll say it is.
6. NO data was presented at all regarding strain choice/prediction of what to use as the antigen(s) for a newer vaccine. It was as if everyone just got the idea to begin thinking about this yesterday.
7. It appeared that neither CDC, FDA nor the VRBPAC advisors wanted to take any initiative or responsibility in figuring out what kind of a vaccine comes next (with the exception of Dr. Kim, who did show initiative about prescribing a way forward). I am not sure any of them wanted to find a way forward.
8. Was everyone dancing around the strain/variant choice because in fact no one really wants a newer vaccine, or because no one wanted to be responsible for picking a loser? I could not tell whether this was a deliberate slow-roll as a means of squeezing out of the COVID vaccine disaster, or whether we were watching an agency and advisors who are highly risk-averse but have no problems with the vaccines.
9. The Public Comments from about 1:30 pm to 2:30 pm (about 5 hours into the meeting) were evidence of outstanding work by independent scientists and heart-rending testimonies by the vaccine injured. There were only 2 people who favored vaccines in the group, one a top Moderna scientist (Dr. Rita Das) who did not actually belong there… had FDA begged Moderna to find someone to speak in favor of boosters?
10. The word transparency was used a lot. Which was peculiar since FDA’s COVID vaccine data, deliberations and decisions have been anything but transparent. Even the reason for today’s meeting is murky.
The link below is to my live blog of the all day meeting.
https://live.childrenshealthdefense.org/admin/fda-advisory-committee/fullscreen-chat
———————-
Of course, what the FDA needs to say, no doubt in some slowly unrolling, self-serving fashion, is that:
- The mRNA platform was the best we could do under the circumstances, but it didn’t actually work out that well.
- Coronaviruses are mutating or lab-tating too quickly to be able to vaccinate effectively against them.
- While we still have contracts for 5 or 10 doses per person, we are going to cancel them and try early treatments.
What they won’t way is that these vaccines sickened many thousands, or millions, and the US will now establish clinics to evaluate and treat the injured Americans who did what their government asked of them, cover their medical expenses and pay them disability.
PS. When the Japanese found that the HPV vaccines caused similar severe injuries, about 8 or 10 years ago, clinics were established to take care of the injured.
Unless FullFact.org Says So Then It’s Not True, The UK Government Advises
By Rhoda Wilson – The Exposé – April 7, 2022
Most of us are aware that it’s not only online but also things published by corporate media that aren’t always what they seem. However, a major difference between government or corporate media reports and independent or citizen reports shared online, is the latter allows for public discourse and open debate, providing they are not censored, while corporate media and their fact-checking services do not – they prefer a top-down “above all” approach.
Denying public debate negates the all-important diversity of thought in a liberal and democratic society. Silencing counterarguments that challenge their preferred storyline enables governments and corporate media to create a one-sided narrative. A narrative that, left unchallenged, moves further and further away from the truth. But here’s a fact that you will not find on either GOV.UK or Full Fact: a lie cannot become truth, no matter how often it is repeated.
The SHAREChecklist attempts to provide advice on what to share and what not to share apparently for the good of others. Information that does not originate from their sources could be “harmful to share with our friends and families,” the UK government claims.
It’s important to understand that we, the people, are in the midst of an information war. One which began in earnest at the start of 2020. A battle in the public space for complete and truthful information while governments and their advisors attempt to manipulate our perceptions and behaviours so we obey their instructions, without question, even when those instructions prove to be harmful.
Even the most trusting know that governments and politicians hide the truth, manipulate the truth and even outright lie – it’s merely the extent that varies. We know that governments use mass media – television, radio and online – as tools to roll out their narratives to the public en masse. Additional government tools include initiatives such as their SHAREChecklist campaign.
At the very least corporate media is biased but as they sink deeper into an ever-narrowing storyline it is becoming apparent that reports are being manufactured and that they are activists seeking to implement an agenda, they are not journalists.
Fact-checking services do not provide facts they provide opinions. Last year, Facebook admitted in court that its “fact checks” are nothing more than statements of opinion. Not experts’ opinions but those of the “fact-checkers.” And self-described “fact-checkers” are not independent. They are dependent on donations from large corporations, the same corporations that work to craft a narrative and silence public debate through censorship.
The SHAREChecklist
As we work through the checklist what will become apparent is that in no way does the government advise, or even so much as hint at encouraging: critical thinking, comparing a variety of sources, open dialogue or debate. The checklist leads readers along a path to following a narrative set by a centralised coterie – the government or whoever is “advising” them.

The Government’s first bit of advice is to “make sure information comes from a trusted source.” This is common sense and something we should all be doing, and most likely instinctively are. What each of us believes are “trusted sources” is decisive.
A source that has been proven to lie without remorse is not a source to be trusted. Any source that consistently and persistently promotes Covid injections as “safe and effective” and so roll up your sleeve for another shot, for example, is not to be trusted. Within these sources, the lies are pathological and systemic. Such a source – the BBC, SAGE or UK government, for example – does not suddenly and inexplicably switch from being wanton liars to being truthful.

The second bit of advice the Government has to offer is to read beyond the headline – yet more common sense. A headline cannot contain all the substantive information that an article contains.
Additionally, clickbait headlines, for example, are common practice in all forms of media. To avoid a knee jerk response to the attention-seeking text we should not take an article, or post online, at its headline. Corporate media, as with marketing agencies, are particularly adept at clickbait headlines, texts and thumbnails. And, of course, the UK government has SPI-B and the Nudge Unit to advise them on how to use psychology to maximise public “engagement” and “cooperation.” The checkmark or tick symbol incorporated into the SHAREChecklist logo is an example of typical Nudge Unit behavioural psychology.

Again, in its third bit of advice, the Government advises some additional common sense: “check the facts.” What is notable about this point is that, according to the UK government, there are a limited number of sources that provide these “facts.” Actually, there are only two: themselves, of course, and “fact-checkers,” namely Full Fact.
The BBC frequently and repeatedly tells its viewers that it is a trusted source, bringing you the all facts. Yet, SHAREChecklist does not recommend them as a source to “check the facts.” This may or may not be an indication of how the Government views BBC’s “fact-based” reporting or, possibly, recognition that the public has, by and large, lost its trust in the BBC.
Taking on board the first two bits of advice – “trusted source” and “read beyond the headline,” in this case the Government’s headline – we take a brief look at the Government recommended “fact-checker” Full Fact later in this article.

The fourth bit of the Government’s advice is as true for images and videos shared online as it is for images and videos shown on television. There have been many examples of dubious images and videos published by corporate media over the past two years that deserve to be questioned. There is no source of information, “official” or unofficial, that we should not test for accuracy and reliability. Stay sceptical. Criticism is not only legitimate, it is necessary.

The final bit of advice the Government gives is that typos could be an indication that the information is false. How are those with dyslexia or learning difficulties supposed to feel reading that? For those who find it hard to express their thoughts and ideas in writing, you’re in good company. While Albert Einstein loved mathematics and science, he disliked grammar and had problems with spelling.
After singling out typos, then comes the sneaky bit: “official guidance” – in other words, the Government’s or the centralised coterie’s guidance – has been “carefully checked” presumably for spelling and grammatical errors. So naturally, the Government’s typo-free publications must be true – of course! On that basis, if you want to avoid being censored download Grammarly now!
Who Is Full Fact?

Full Fact’s website states: “We’re developing world-leading technology and new research to spot repeated claims, and find out how bad information can be tackled at a global scale. And we campaign for change that will make bad information rarer and less harmful.”
Who are the people and organisations behind Full Fact? Who are they campaigning for? Who is determining what information is “bad”?
In 2012, UK Column published an article about Full Fact, ‘Faux Facts – The disturbing Truth About fullfact.org’, digging a little deeper into “this interesting little non-profit company, headed by Tory Party donor and Anne Freud Centre Chairman Michael Samuel.”
In 2019 Daily Mail wrote that Full Fact was at the centre of an election row with the Tories and was forced to defend its credibility after it stepped into a social media war after an election debate between Jeremy Corbyn and Boris Johnson. Daily Mail quoted Dominic Raab: “Who said Final Fact is the final arbiter of what the public gets to see as the truth? There’s no god-given right, set in law.”
“Foundations set up by eBay creator Pierre Omidyar and left-wing investor George Soros have also joined tech giants in giving six-figure sums to London-based Full Fact along with thousands of unnamed individual donors paying between £25 and £5,000 each,” Daily Mail reported.
A 2021 article published in The Critic noted the board of trustees included Labour peer Baroness Janet Royall, Lib-Dem peer Lord John Sharkey and former Conservative Party member Lord Richard Inglewood. These three peers are still trustees and Michael Samuel is still chairman.
The Critic article goes on to note that Full Fact is a charity with a small output of research compared to its size, funded primarily by big-tech and staffed to a large extent by former public sector workers or ex-reporters from left-wing media. “Full Fact’s website reports that they were paid £1.1 million by Facebook and £206,500 by Google in 2019, plus a monthly payment of £7,300 worth of free advertising by the search giant. The funding by big-tech in 2019 makes up roughly 70% of their declared funding for the year,” The Critic wrote.
As you can see for yourself in the table below Full Fact is still predominantly funded, and so their opinions are influenced, by the notorious online censor organisations – Facebook, which includes WhatsApp, and Google, which includes YouTube. In 2021, almost 40% of Full Fact’s “donations” came from Facebook and Google.

Full Fact Funders 2021
Full Fact does not pass the government’s SHAREChecklist test and, according to UK government advice, their articles may be “harmful” if shared with friends and families – do not share them.
| Full Fact Funding 2021 retrieved 6 April 2022 | ||
| £305,119.64 | Third Party Fact Checking programme | |
| £116,352.14 | Framework for collaboration during misinformation crises | |
| £59,634.83 | Health fellowship | |
| Hundreds of individual donors and gift aid | £370,148.00 | Core funding |
| Mohn Westlake Foundation | £250,000.00 | Core funding |
| Google AI for Good Impact Challenge | £235,222.77 | Automated fact checking |
| Nuffield Foundation | £100,000.00 | Fact checking and annual report |
| Luminate | £75,789.87 | Core funding |
| Esmée Fairbairn Foundation | £68,333.33 | Core funding |
| £61,809.84 | WhatsApp fact checking service | |
| International Fact Checking Network & WhatsApp | £53,737.20 | Vaccine Grant Program |
| Baillie Gifford | £50,000.00 | Core funding |
| John Ellerman Foundation | £50,000.00 | Core funding |
| Joseph Rowntree Charitable Trust | £50,000.00 | Core funding |
| The Buchanan Programme | £49,801.68 | Core funding |
| The Dulverton Trust | £35,000.00 | Core funding |
| Gill Family Foundation | £30,000.00 | Core funding |
| James Padolsey | £30,000.00 | Core funding |
| International Fact Checking Network & National Endowment for Democracy | £26,576.58 | Fact-Checkers Working Together Research Program |
| Colefax Charitable Trust | £25,000.00 | Core funding |
| The M J Samuel Charitable Trust | £17,500.00 | Core funding |
| International Fact Checking Network & YouTube | £17,064.56 | Fact Checking Development Grant |
| Highway One Trust | £10,000.00 | Policy team |
| William de Winton | £10,000.00 | Core funding |
| Reed Foundation | £9,000.00 | Core funding |
| Good Thinking Society | £8,000.00 | Core funding |
| Dorothy Bishop | £6,000.00 | Core funding |
| Cecil Pilkington Charitable Trust | £5,000.00 | Core funding |
| Tinsley Charitable Trust | £5,000.00 | Core funding |

Putting Big Pharma on Trial in the COVID-19 Era, Part 3
Backing the Big Four: Big Pharma and the FDA, WHO, NIH, CDC
By Rebecca Strong | February 16, 2022
I know what you’re thinking. Big pharma is amoral and the FDA’s devastating slips are a dime a dozen — old news. But what about agencies and organizations like the National Institutes of Health (NIH), World Health Organization (WHO), and Centers for Disease Control & Prevention (CDC)? Don’t they have an obligation to provide unbiased guidance to protect citizens? Don’t worry, I’m getting there.
The WHO’s guidance is undeniably influential across the globe. For most of this organization’s history, dating back to 1948, it could not receive donations from pharmaceutical companies — only member states. But that changed in 2005 when the WHO updated its financial policy to permit private money into its system. Since then, the WHO has accepted many financial contributions from big pharma. In fact, it’s only 20% financed by member states today, with a whopping 80% of financing coming from private donors. For instance, The Bill and Melinda Gates Foundation (BMGF) is now one of its main contributors, providing up to 13% of its funds — about $250–300 million a year. Nowadays, the BMGF provides more donations to the WHO than the entire United States.
Dr. Arata Kochi, former head of WHO’s malaria program, expressed concerns to director-general Dr. Margaret Chan in 2007 that taking the BMGF’s money could have “far-reaching, largely unintended consequences” including “stifling a diversity of views among scientists.”
“The big concerns are that the Gates Foundation isn’t fully transparent and accountable,” Lawrence Gostin, director of WHO’s Collaborating Center on National and Global Health Law, told Devex in an interview. “By wielding such influence, it could steer WHO priorities … It would enable a single rich philanthropist to set the global health agenda.”

Bill Gates, Francis Collins, Anthony Fauci. Photo credit: National Institutes of Health
Take a peek at the WHO’s list of donors and you’ll find a few other familiar names like AstraZeneca, Bayer, Pfizer, Johnson & Johnson, and Merck.
The NIH has the same problem, it seems. Science journalist Paul Thacker, who previously examined financial links between physicians and pharma companies as a lead investigator of the United States Senate Committee, wrote in The Washington Post that this agency “often ignored” very “obvious” conflicts of interest. He also claimed that “its industry ties go back decades.” In 2018, it was discovered that a $100 million alcohol consumption study run by NIH scientists was funded mostly by beer and liquor companies. Emails proved that NIH researchers were in frequent contact with those companies while designing the study — which, here’s a shocker — were aimed at highlighting the benefits and not the risks of moderate drinking. So, the NIH ultimately had to squash the trial.
And then there’s the CDC. It used to be that this agency couldn’t take contributions from pharmaceutical companies, but in 1992 they found a loophole: new legislation passed by Congress allowed them to accept private funding through a nonprofit called the CDC Foundation. From 2014 through 2018 alone, the CDC Foundation received $79.6 million from corporations like Pfizer, Biogen, and Merck.
Of course, if a pharmaceutical company wants to get a drug, vaccine, or other product approved, they really need to cozy up to the FDA. That explains why in 2017, pharma companies paid for a whopping 75% of the FDA’s scientific review budgets, up from 27% in 1993. It wasn’t always like this. But in 1992, an act of Congress changed the FDA’s funding stream, enlisting pharma companies to pay “user fees,” which help the FDA speed up the approval process for their drugs.
A 2018 Science investigation found that 40 out of 107 physician advisors on the FDA’s committees received more than $10,000 from big pharma companies trying to get their drugs approved, with some banking up to $1 million or more. The FDA claims it has a well-functioning system to identify and prevent these possible conflicts of interest. Unfortunately, their system only works for spotting payments before advisory panels meet, and the Science investigation showed many FDA panel members get their payments after the fact. It’s a little like “you scratch my back now, and I’ll scratch your back once I get what I want” — drug companies promise FDA employees a future bonus contingent on whether things go their way.
Here’s why this dynamic proves problematic: a 2000 investigation revealed that when the FDA approved the rotavirus vaccine in 1998, it didn’t exactly do its due diligence. That probably had something to do with the fact that committee members had financial ties to the manufacturer, Merck — many owned tens of thousands of dollars of stock in the company, or even held patents on the vaccine itself. Later, the Adverse Event Reporting System revealed that the vaccine was causing serious bowel obstructions in some children, and it was finally pulled from the U.S. market in October 1999.
Then, in June of 2021, the FDA overruled concerns raised by its very own scientific advisory committee to approve Biogen’s Alzheimer’s drug Aduhelm — a move widely criticized by physicians. The drug not only showed very little efficacy but also potentially serious side effects like brain bleeding and swelling, in clinical trials. Dr. Aaron Kesselheim, a Harvard Medical School professor who was on the FDA’s scientific advisory committee, called it the “worst drug approval” in recent history, and noted that meetings between the FDA and Biogen had a “strange dynamic” suggesting an unusually close relationship. Dr. Michael Carome, director of Public Citizen’s Health Research Group, told CNN that he believes the FDA started working in “inappropriately close collaboration with Biogen” back in 2019. “They were not objective, unbiased regulators,” he added in the CNN interview. “It seems as if the decision was preordained.”
That brings me to perhaps the biggest conflict of interest yet: Dr. Anthony Fauci’s NIAID is just one of many institutes that comprises the NIH — and the NIH owns half the patent for the Moderna vaccine — as well as thousands more pharma patents to boot. The NIAID is poised to earn millions of dollars from Moderna’s vaccine revenue, with individual officials also receiving up to $150,000 annually.
Operation Warp Speed
In December of 2020, Pfizer became the first company to receive an emergency use authorization (EUA) from the FDA for a COVID-19 vaccine. EUAs — which allow the distribution of an unapproved drug or other product during a declared public health emergency — are actually a pretty new thing: the first one was issued in 2005 so military personnel could get an anthrax vaccine. To get a full FDA approval, there needs to be substantial evidence that the product is safe and effective. But for an EUA, the FDA just needs to determine that it may be effective. Since EUAs are granted so quickly, the FDA doesn’t have enough time to gather all the information they’d usually need to approve a drug or vaccine.
Pfizer CEO and chairman Albert Bourla has said his company was “operating at the speed of science” to bring a vaccine to market. However, a 2021 report in The BMJ revealed that this speed might have come at the expense of “data integrity and patient safety.” Brook Jackson, regional director for the Ventavia Research Group, which carried out these trials, told The BMJ that her former company “falsified data, unblinded patients, and employed inadequately trained vaccinators” in Pfizer’s pivotal phase 3 trial. Just some of the other concerning events witnessed included: adverse events not being reported correctly or at all, lack of reporting on protocol deviations, informed consent errors, and mislabeling of lab specimens. An audio recording of Ventavia employees from September 2020 revealed that they were so overwhelmed by issues arising during the study that they became unable to “quantify the types and number of errors” when assessing quality control. One Ventavia employee told The BMJ she’d never once seen a research environment as disorderly as Ventavia’s Pfizer vaccine trial, while another called it a “crazy mess.”
Over the course of her two-decades-long career, Jackson has worked on hundreds of clinical trials, and two of her areas of expertise happen to be immunology and infectious diseases. She told me that from her first day on the Pfizer trial in September of 2020, she discovered “such egregious misconduct” that she recommended they stop enrolling participants into the study to do an internal audit.
“To my complete shock and horror, Ventavia agreed to pause enrollment but then devised a plan to conceal what I found and to keep ICON and Pfizer in the dark,” Jackson said during our interview. “The site was in full clean-up mode. When missing data points were discovered the information was fabricated, including forged signatures on the informed consent forms.”
A screenshot Jackson shared with me shows she was invited to a meeting titled “COVID 1001 Clean up Call” on Sept. 21, 2020. She refused to participate in the call.
Jackson repeatedly warned her superiors about patient safety concerns and data integrity issues.
“I knew that the entire world was counting on clinical researchers to develop a safe and effective vaccine and I did not want to be a part of that failure by not reporting what I saw,” she told me.
When her employer failed to act, Jackson filed a complaint with the FDA on Sept. 25, and Ventavia fired her hours later that same day under the pretense that she was “not a good fit.” After reviewing her concerns over the phone, she claims the FDA never followed up or inspected the Ventavia site. Ten weeks later, the FDA authorized the EUA for the vaccine. Meanwhile, Pfizer hired Ventavia to handle the research for four more vaccine clinical trials, including one involving children and young adults, one for pregnant women, and another for the booster. Not only that, but Ventavia handled the clinical trials for Moderna, Johnson & Johnson, and Novavax. Jackson is currently pursuing a False Claims Act lawsuitagainst Pfizer and Ventavia Research Group.
Last year, Pfizer banked nearly $37 billion from its COVID vaccine, making it one of the most lucrative products in global history. Its overall revenues doubled in 2021 to reach $81.3 billion, and it’s slated to reach a record-breaking $98-$102 billion this year.
“Corporations like Pfizer should never have been put in charge of a global vaccination rollout, because it was inevitable they would make life-and-death decisions based on what’s in the short-term interest of their shareholders,” writes Nick Dearden, director of Global Justice Now.
As previously mentioned, it’s super common for pharmaceutical companies to fund the research on their own products. Here’s why that’s scary. One 1999 meta-analysis showed that industry-funded research is eight times less likely to achieve unfavorable results compared to independent trials. In other words, if a pharmaceutical company wants to prove that a medication, supplement, vaccine, or device is safe and effective, they’ll find a way.
With that in mind, I recently examined the 2020 study on Pfizer’s COVID vaccine to see if there were any conflicts of interest. Lo and behold, the lengthy attached disclosure form shows that of the 29 authors, 18 are employees of Pfizer and hold stock in the company, one received a research grant from Pfizer during the study, and two reported being paid “personal fees” by Pfizer. In another 2021 study on the Pfizer vaccine, seven of the 15 authors are employees of and hold stock in Pfizer. The other eight authors received financial support from Pfizer during the study.
As of the day I’m writing this, about 64% of Americans are fully vaccinated, and 76% have gotten at least one dose. The FDA has repeatedly promised “full transparency” when it comes to these vaccines. Yet in December of 2021, the FDA asked for permission to wait 75 years before releasing information pertaining to Pfizer’s COVID-19 vaccine, including safety data, effectiveness data, and adverse reaction reports. That means no one would see this information until the year 2096 — conveniently, after many of us have departed this crazy world. To recap: the FDA only needed 10 weeks to review the 329,000 pages worth of data before approving the EUA for the vaccine — but apparently, they need three-quarters of a century to publicize it.
In response to the FDA’s ludicrous request, PHMPT — a group of over 200 medical and public health experts from Harvard, Yale, Brown, UCLA, and other institutions — filed a lawsuit under the Freedom of Information Act demanding that the FDA produce this data sooner. And their efforts paid off: U.S. District Judge Mark T. Pittman issued an order for the FDA to produce 12,000 pages by Jan. 31, and then at least 55,000 pages per month thereafter. In his statement to the FDA, Pittman quoted the late John F. Kennedy: “A nation that is afraid to let its people judge the truth and falsehood in an open market is a nation that is afraid of its people.”
As for why the FDA wanted to keep this data hidden, the first batch of documentation revealed that there were more than 1,200 vaccine-related deaths in just the first 90 days after the Pfizer vaccine was introduced. Of 32 pregnancies with a known outcome, 28 resulted in fetal death. The CDC also recently unveiled data showing a total of 1,088,560 reports of adverse events from COVID vaccines were submitted between Dec. 14, 2020, and Jan. 28, 2022. That data included 23,149 reports of deaths and 183,311 reports of serious injuries. There were 4,993 reported adverse events in pregnant women after getting vaccinated, including 1,597 reports of miscarriage or premature birth. A 2022 study published in JAMA, meanwhile, revealed that there have been more than 1,900 reported cases of myocarditis — or inflammation of the heart muscle — mostly in people 30 and under, within 7 days of getting the vaccine. In those cases, 96% of people were hospitalized.
“It is understandable that the FDA does not want independent scientists to review the documents it relied upon to license Pfizer’s vaccine given that it is not as effective as the FDA originally claimed, does not prevent transmission, does not prevent against certain emerging variants, can cause serious heart inflammation in younger individuals, and has numerous other undisputed safety issues,” writes Aaron Siri, the attorney representing PHMPT in its lawsuit against the FDA.
Siri told me in an email that his office phone has been ringing off the hook in recent months.
“We are overwhelmed by inquiries from individuals calling about an injury from a COVID-19 vaccine,” he said.
By the way — it’s worth noting that adverse effects caused by COVID-19 vaccinations are still not covered by the National Vaccine Injury Compensation Program. Companies like Pfizer, Moderna, and Johnson & Johnson are protected under the Public Readiness and Emergency Preparedness (PREP) Act, which grants them total immunity from liability with their vaccines. And no matter what happens to you, you can’t sue the FDA for authorizing the EUA, or your employer for requiring you to get it, either. Billions of taxpayer dollars went to fund the research and development of these vaccines, and in Moderna’s case, licensing its vaccine was made possible entirely by public funds. But apparently, that still warrants citizens no insurance. Should something go wrong, you’re basically on your own.
To be continued…
Research Shows Persons With Vitamin D Levels Under 20 nmol/l Are 18 Times More Likely To Die From Covid!
By P Gosselin – No Tricks Zone – April 8, 2022
In his book “Herdengesundheit” (Herd Health), German physician and molecular geneticist Dr. Michael Nehls says “Vitamin D would have prevented severe cases of disease and also most Covid-related deaths”.
He is convinced: Vitamin D is the game-changer and suggests the simple act of eliminating the great Vitamin D deficits much of the population now suffers would be far more effective than the current COVID vaccines.
Vitamin D is an important factor in our immune system’s ability to ward off viral infections. To illustrate this Dr. Nehls presents here a chart depicting how much higher mortality is in times of low Vitamin D (November to April):
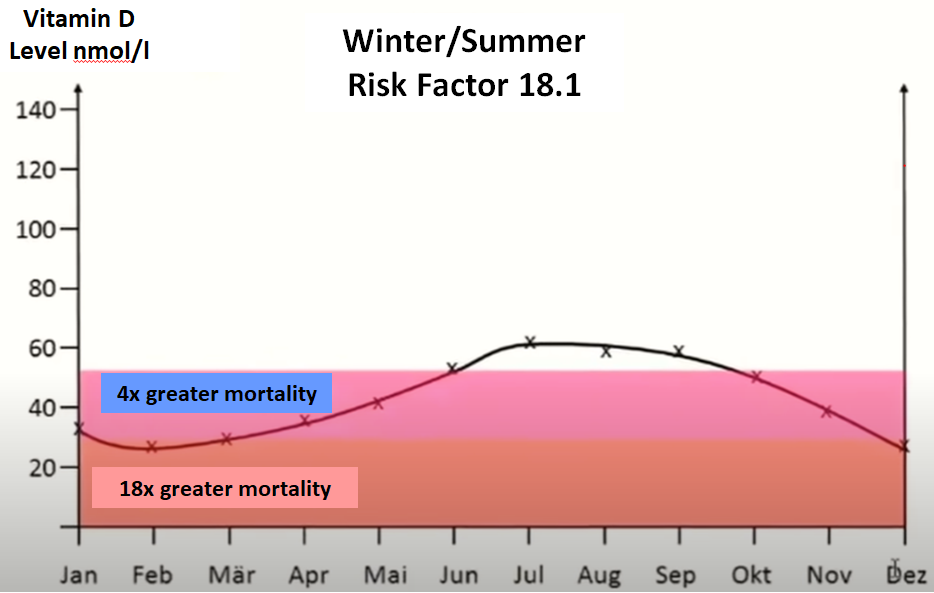
Source: here.
18 times higher mortality risk
Citing a Belgian study and a Heidelberg study, Nehls reports that in the wintertime, when vitamin D levels are well under 50 nmol/l, you have a four times greater chance of dying from COVID, independent of age or preexisting conditions. And prospects become very dire for persons with a Vitamin D level of less than 20 nmol/l, where the risk of mortality in case of a covid infection is 18 times higher!
Statistically, researchers calculated that with a Vitamin D level of 120 nmol/l, a level that Nehls says is our natural level, a zero mortality rate from respiratory viral infections would be nearly achieved.
Much less infectious
Another interesting feature about Vitamin D levels is that the likelihood of testing positive on a PCR test drops more 50% for a person with a Vitamin D level of over 125 compared to a person with 50 nmol/l. That alone would mean having a healthy Vitamin D level would make you far less infectious. Not even the “vaccines” have been able to achieve that:
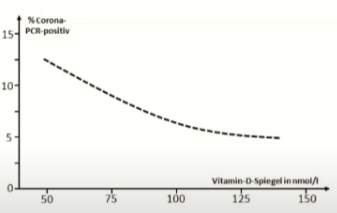
Percent corona PCR positive vs. Vitamin D level nmol/l. Source here,
Public health gross negligence
In the interview, Dr Nehls says that the government’s failure to make sure the immune system of people stays strong by ensuring healthy Vitamin D levels is “grossly negligent.” Moreover, health authorities are aware that the Vitamin D levels for the general population are far to low, but they choose to do nothing about it.
“A lack of Vitamin D leads to chronic disease” says Nehls. “With chronic disease the most money gets made. I can imagine there’s an interest not to make the recommendation, and that doesn’t apply just to Vitamin D.”
Nehls recommends taking Vitamin K2 along with Vitamin D to avoid possible side effects.
Beware of “cleverly manipulated” studies
Nehls criticizes studies that claim Vitamin D provides no real health benefit, accusing the authors of improperly conducting the studies in order to get a predetermined result. One study, Nehls said, was “very cleverly manipulated in order to encourage people not to bother taking Vitamin D”.
When asked if it would be recommendable to take Vitamin D as a way to treat vaccine injury, Nehls says “absolutely” and that it is urgently advised to have vitamin D levels of 125 nmol/l if you get vaccinated, which he then says wouldn’t be necessary because at that Vitamin D level, the chances of a serious COVID illness are practically zero.
Putting Big Pharma on Trial in the COVID-19 Era, Part 2

“Nurse prepares to vaccinate children” by World Bank Photo Collection is licensed under CC BY-NC-ND 2.0
By Rebecca Strong | February 16, 2022
Big Pharma Lawsuits, Scandals, and Cover-Ups
While the OxyContin craze is undoubtedly one of the highest-profile examples of big pharma’s deception, there are dozens of other stories like this. Here are a few standouts:
In the 1980s, Bayer continued selling blood clotting products to third-world countries even though they were fully aware those products had been contaminated with HIV. The reason? The “financial investment in the product was considered too high to destroy the inventory.” Predictably, about 20,000 of the hemophiliacs who were infused with these tainted products then tested positive for HIV and eventually developed AIDS, and many later died of it.
In 2004, Johnson & Johnson was slapped with a series of lawsuits for illegally promoting off-label use of their heartburn drug Propulsid for children despite internal company emails confirming major safety concerns (as in, deaths during the drug trials). Documentation from the lawsuits showed that dozens of studies sponsored by Johnson & Johnson highlighting the risks of this drug were never published.
The FDA estimates that GSK’s Avandia caused 83,000 heart attacks between 1999 and 2007. Internal documents from GSK prove that when they began studying the effects of the drug as early as 1999, they discovered it caused a higher risk of heart attacks than a similar drug it was meant to replace. Rather than publish these findings, they spent a decade illegally concealing them (and meanwhile, banking $3.2 billion annually for this drug by 2006). Finally, a 2007 New England Journal of Medicine study linked Avandia to a 43% increased risk of heart attacks, and a 64% increased risk of death from heart disease. Avandia is still FDA approved and available in the U.S.
In 2009, Pfizer was forced to pay $2.3 billion, the largest healthcare fraud settlement in history at that time, for paying illegal kickbacks to doctors and promoting off-label uses of its drugs. Specifically, a former employee revealed that Pfizer reps were encouraged and incentivized to sell Bextra and 12 other drugs for conditions they were never FDA approved for, and at doses up to eight times what’s recommended. “I was expected to increase profits at all costs, even when sales meant endangering lives,” the whistleblower said.
When it was discovered that AstraZeneca was promoting the antipsychotic medication Seroquel for uses that were not approved by the FDA as safe and effective, the company was hit with a $520 million fine in 2010. For years, AstraZeneca had been encouraging psychiatrists and other physicians to prescribe Seroquel for a vast range of seemingly unrelated off-label conditions, including Alzheimer’s disease, anger management, ADHD, dementia, post-traumatic stress disorder, and sleeplessness. AstraZeneca also violated the federal Anti-Kickback Statute by paying doctors to spread the word about these unapproved uses of Seroquel via promotional lectures and while traveling to resort locations.
In 2012, GSK paid a $3 billion fine for bribing doctors by flying them and their spouses to five-star resorts, and for illegally promoting drugs for off-label uses. What’s worse — GSK withheld clinical trial results that showed its antidepressant Paxil not only doesn’t work for adolescents and children but more alarmingly, that it can increase the likelihood of suicidal thoughts in this group. A 1998 GSK internal memo revealed that the company intentionally concealed this data to minimize any “potential negative commercial impact.”
In 2021, an ex-AstraZeneca sales rep sued her former employer, claiming they fired her for refusing to promote drugs for uses that weren’t FDA-approved. The employee alleges that on multiple occasions, she expressed concerns to her boss about “misleading” information that didn’t have enough support from medical research, and off-label promotions of certain drugs. Her supervisor reportedly not only ignored these concerns but pressured her to approve statements she didn’t agree with and threatened to remove her from regional and national positions if she didn’t comply. According to the plaintiff, she missed out on a raise and a bonus because she refused to break the law.
At the top of 2022, a panel of the D.C. Court of Appeals reinstated a lawsuit against Pfizer, AstraZeneca, Johnson & Johnson, Roche, and GE Healthcare, which claims they helped finance terrorist attacks against U.S. service members and other Americans in Iraq. The suit alleges that from 2005–2011, these companies regularly offered bribes (including free drugs and medical devices) totaling millions of dollars annually to Iraq’s Ministry of Health in order to secure drug contracts. These corrupt payments then allegedly funded weapons and training for the Mahdi Army, which until 2008, was largely considered one of the most dangerous groups in Iraq.
Another especially worrisome factor is that pharmaceutical companies are conducting an ever-increasing number of clinical trials in third-world countries, where people may be less educated, and there are also far fewer safety regulations. Pfizer’s 1996 experimental trials with Trovan on Nigerian childrenwith meningitis — without informed consent — is just one nauseating example. When a former medical director in Pfizer’s central research division warned the company both before and after the study that their methods in this trial were “improper and unsafe,” he was promptly fired. Families of the Nigerian children who died or were left blind, brain damaged, or paralyzed after the study sued Pfizer, and the company ultimately settled out of court. In 1998, the FDA approved Trovan only for adults. The drug was later banned from European markets due to reports of fatal liver disease and restricted to strictly emergency care in the U.S. Pfizer still denies any wrongdoing.
But all that is just the tip of the iceberg. If you’d like to dive a little further down the rabbit hole — and I’ll warn you, it’s a deep one — a quick Google search for “big pharma lawsuits” will reveal the industry’s dark track record of bribery, dishonesty, and fraud.
In fact, big pharma happens to be the biggest defrauder of the federal government when it comes to the False Claims Act, otherwise known as the “Lincoln Law.” During our interview, Panara told me she has friends still working for big pharma who would be willing to speak out about crooked activity they’ve observed, but are too afraid of being blacklisted by the industry. A newly proposed update to the False Claims Act would help to protect and support whistleblowers in their efforts to hold pharmaceutical companies liable, by helping to prevent that kind of retaliation and making it harder for the companies charged to dismiss these cases. It should come as no surprise that Pfizer, AstraZeneca, Merck, and a flock of other big pharma firms are currently lobbying to block the update. Naturally, they wouldn’t want to make it any easier for ex-employees to expose their wrongdoings, potentially costing them billions more in fines.
Something to keep in mind: these are the same people who produced, marketed, and are profiting from the COVID-19 vaccines. The same people who manipulate research, pay off decision-makers to push their drugs, cover up negative research results to avoid financial losses, and knowingly put innocent citizens in harm’s way. The same people who told America: “Take as much OxyContin as you want around the clock! It’s very safe and not addictive!” (while laughing all the way to the bank).
So, ask yourself this: if a partner, friend, or family member repeatedly lied to you — and not just little white lies, but big ones that put your health and safety at risk — would you continue to trust them?
To be continued…
Vaccinated Have Up To SIX Times the Infection Rate of Unvaccinated, NZ Government Data Show
By Amanuensis | The Daily Sceptic | April 9, 2022
New Zealand is a fascinating country – amazing geography, likeable population, and, unlike its neighbour Australia, most of its wildlife isn’t planning on killing you at the slightest opportunity. It is also fascinating with respect to Covid because its population has a very high vaccination rate across all age groups (well, down to five), but up until recently there has been negligible natural immunity to Covid. Because of these two factors, New Zealand was always going to be of interest as soon as Covid arrived properly, if only to see how its vaccination efforts had protected its population.
For those who missed it, since the end of last year New Zealand has had a succession of Covid waves. These started small, but in the most recent wave, taking place during February and March, infection rates were enormous – if we had these infection rates in the U.K. we’d have peaked at approximately 350,000 cases per day (rather than around 200,000). What’s more, it looks like New Zealand exceeded its testing capacity during that wave, suggesting that peak infections were probably even higher. It is relevant to note that during February and March, New Zealand had over 90% of all the cases it has ever had and most of the rest occurred in January – prior to 2022 New Zealand reported very few Covid infections.
So much for the Covid vaccines protecting against infection – but what do the data look like in detail?
Cases
New Zealand is somewhat helpful in that it does publish daily cases, hospitalisations and deaths by vaccine status; somewhat because it doesn’t allow easy access to anything other than the current day’s report. Thankfully, the Wayback Machine ensures that at least some web pages aren’t forever lost to history. These data were collated for dates since mid February 2022 and smoothed with a seven-day moving average to create a time series of Covid cases by vaccine status.
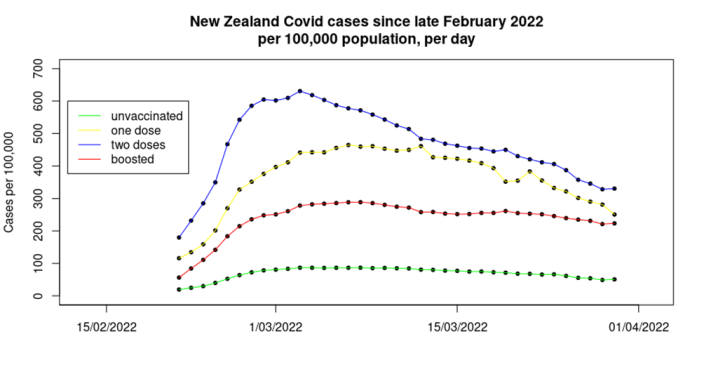
The first time the above graph popped up on my computer screen I had to go and double check all the data sources – and then I triple checked them. The data shown on the graph are notable for several reasons:
- Firstly the obvious one – during the most recent Covid wave there was a much lower infection rate in the unvaccinated, compared with those that had been given one, two or three doses of vaccine. What’s more, this isn’t a small effect – over the period shown approximately:
- 10% of the triple vaccinated in New Zealand were infected.
- 14% of the single vaccinated were infected.
- An astounding 18% of the double vaccinated were infected.
- Yet only 3% of the unvaccinated appear to have been infected.
- The order of the effect is unexpected – for some time in the U.K. the highest case rates have been found in the triple vaccinated, with case rates in the single and double jabbed much lower. In New Zealand the highest rates are seen in the double vaccinated.
- The data for cases in the double dosed appear to have an earlier peak than seen in the data for the unvaccinated, single jabbed and triple jabbed.
- The fall from peak cases to the most recent data point is also interesting. Case rates in the unvaccinated, single dosed and the double dosed have all fallen approximately 45% since their respective peaks, however, case rates in the triple vaccinated have only fallen approximately 20% since their peak. This is rather concerning, as it suggests that we might find that the boosted population maintain a viral reservoir for Covid, ensuring that case rates take much longer to fall to trivial levels and hindering attempts to get society back to a post-Covid normal.
The infections data from New Zealand allow us to estimate the vaccine effectiveness for the Covid vaccines in the absence of natural immunity.
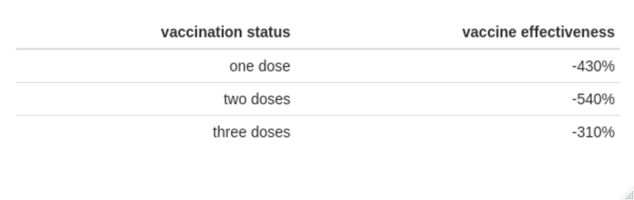
Unadjusted estimates of vaccine effectiveness against infection as at end of March 2022
These data are in contrast to recent data from the U.K., which show one and two doses of vaccine to have a VE of minus-50% to minus-100%, and the booster to have a VE of around minus-300%. While this sounds counterintuitive, it is possible that we’re seeing a complex interplay between a waning of the impact of the vaccine and the impact of additional vaccine doses:
- The U.K. vaccinated early, allowing for the impact of those early vaccine doses to have waned significantly for those choosing not to top-up their ‘protection’.
- The Covid vaccines appear to have a period of approximately two to three months where their impact on the immune system is different than in later periods; this is possibly due to the creation of short-lived IgA (mucosal) antibodies. In the U.K., booster vaccinations were given in autumn 2021, and thus most individuals will have been beyond this period when the Omicron variant’s first wave appeared in December.
In New Zealand, the timescales are very different: those given the booster dose will still be in the two-three month period where short-lived immune responses dominate; those given two doses will be in the proposed period of maximal vaccine negative impact; while those that chose not to accept the offer of a second vaccine dose will be in the period where vaccine effects are waning.
There’s one more point to add for cases in New Zealand, and it relates to the U.K. For months, the UKHSA has been telling us that one possible reason for us seeing far fewer cases in the unvaccinated compared with the vaccinated is because the unvaccinated have natural immunity following high infection rates previously (presumably because the unvaccinated are reckless and didn’t follow lockdown rules – I imagine that they also ride motorcycles too quickly, set off fireworks indoors and play with matches while filling up the car). These data from New Zealand, which at the time had very few individuals previously infected with Covid, show lower case rates in the unvaccinated without any significant levels of natural immunity, contradicting the claim of the UKHSA and eliminating one of its reasons for ignoring the alarming data.
Hospitalisations
Analysis of the hospitalisations data offered by the New Zealand authorities is made complex by there being no stratification of the hospitalisations by age group, and the lack of complete vaccinations data by age. However, U.K. data show that in recent weeks approximately 95% of hospitalisations were in those aged over 60; assuming that this will also hold true for the New Zealand population allows us to offer a indicative analysis of the likely impact for that age group of the vaccines on hospitalisations in the country.
The analysis is also hindered by the data on vaccine coverage for those aged over 60 not differentiating between those that have had only one dose of vaccine and those that are unvaccinated. This might in isolation from other data appear to be ‘sensible’ – after all, the single dosed have the ‘least protection’ as well as ‘the longest time for protection to wane’. However, the data shown in the previous section suggest that the unvaccinated and those having taken a single dose of vaccine are in no way comparable, and that considering them as a single group could lead to misleading conclusions. Nevertheless, that’s the hand that’s been dealt for us.
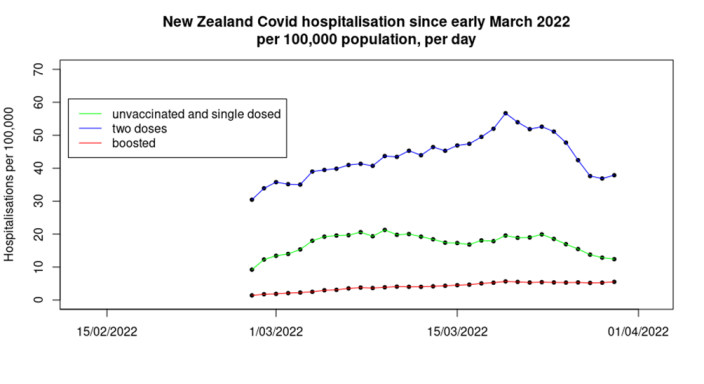
The data are somewhat surprising. While those given a booster dose of vaccine seem to have lower levels of hospitalisations than found in the group containing the unvaccinated and those given only one dose of vaccine – as might be expected – the double dosed have significantly higher hospitalisation rates.
Also interesting is the trend in the data:
- Hospitalisations in the unvaccinated/single-dosed appear to peak earliest – we have also seen this effect in U.K. data, usually in the form of dire warnings early in each Covid wave that the only people being hospitalised are the unvaccinated, only for the warnings to go quiet later in the Covid wave when the data move in the opposite direction.
- Hospitalisations in those given two doses of vaccine appear to peak towards the end of the period shown.
- Hospitalisations in the boosted population appear to show little signs of slowing down, let alone reducing, over the period in question. Note also that this group saw a fourfold increase over the time period shown, whereas the double dose and single-dose/unvaccinated group both saw a 25% increase, albeit with an intermediate period with higher hospitalisation rates.
It was not possible to properly disentangle the hospitalisations data for the unvaccinated, but the data suggest that in aggregate those having taken two or three doses of vaccine (when the two groups are put together) have approximately 45% lower risk of hospitalisation than the unvaccinated/single-dosed. It is worth noting that in the U.K. data we see higher hospitalisation rates in the single vaccinated in those aged over 60, compared with the unvaccinated. It is possible that the same pattern is found in New Zealand, only ‘covered up’ by the co-mingling of the data. If this is the case then the apparent protection offered by the vaccine in the two or three dose individuals will be somewhat lower than 45%.
Deaths
The mortality data from New Zealand are also complicated because the health authorities lump together into one group all the unvaccinated and those having taken a single dose of vaccine. Beyond that complication, deaths data can be tricky to analyse, because there are such huge differences in death rates from (or with) Covid by age. Fortunately, the mortality data offered by the New Zealand authorities do include deaths by age group, which allows a finer analysis than was possible with the infections and hospitalisations data.
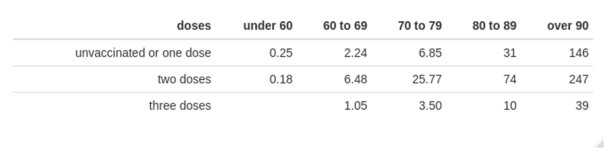
Covid mortality per 100,000 per week, by vaccination status and age
The above table suggests that while those given three doses of vaccine have a decreased risk of death from (or with) Covid compared with the mortality rate in the strange group called ‘unvaccinated or one dose’, the risk of death is greatest in those given two doses of vaccine.
However, it is possible that New Zealand’s data have a similar pattern to that seen in the U.K. (and elsewhere), where dose effects are complicated by the health of those given each vaccine, namely that those closest to death were spared a dose of vaccine, and thus concentrated deaths into the very small number left in the prior dose group. A comparison of the data for ‘unvaccinated or one dose’ with ‘two or three doses’ suggests that the vaccines do still protect against death, but only to a very low degree in younger age groups.
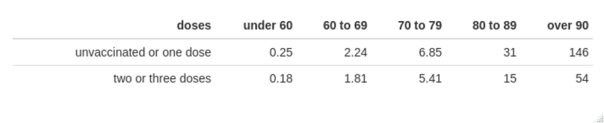
Covid mortality per 100,000 per week, by vaccination status and age
The data above support the use of vaccination to protect against death from (or with) Covid for those aged over 80. On the other hand, the mortality rate in those aged under 60 is very low, and the estimated vaccine effectiveness in protecting against death for those aged under 80 is only approximately 30% – once again, the real-world vaccine effectiveness estimate is rather low. It is also of note that these rather poor figures for the protection offered by the vaccines against mortality come from a country that started vaccination rather late (summer 2021) and where most of the population were only given their booster doses two to three months ago. These data suggest that the vaccines simply do not offer substantive protection against death for newer Covid variants, rather than it simply being a case of waning vaccine protection.
It is also important to note that the data on the benefits of the vaccine in protecting against death shown above should be treated with caution:
- Data on deaths in the unvaccinated and those given a single dose of vaccine are co-mingled; the New Zealand hospitalisation data suggest that death rates might be greater in the single-jabbed.
- The vaccinated appear to have significant increased risk of catching Covid, which contributes to overall risk of serious disease and death.
- These calculations do not include any consideration of the risk of side-effects and complications following vaccination.
Overall mortality
One other aspect of the data coming from New Zealand that is of interest relating to Covid is excess mortality. These data are of interest because New Zealand managed to keep itself more-or-less clear of Covid until the last few months of 2021, and even then case numbers were very low until 2022, with the result that Covid deaths were negligible prior to 2022. With that in mind, its excess death data between the start of 2020 and the end of 2021 are very interesting.
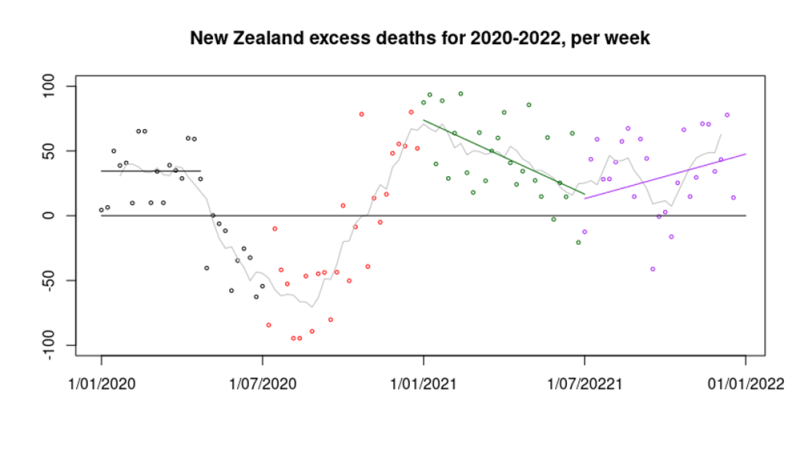
Many countries around the world had a peak in excess deaths in the first quarter of 2020, followed by a significant reduction in deaths into mid 2020. There has been speculation that this pattern was seen because Covid infections in early 2020 killed the most vulnerable, leaving a period in which there were fewer people left to die. However, New Zealand also has this pattern of excess deaths in the first half of 2020 (black data points in the graph above) without Covid infections, suggesting that the reduction in deaths seen in mid 2020 were a result of lockdown. The reason for the excess deaths in New Zealand in the first quarter of 2020 are not at all clear.
Most countries then saw an increase in deaths towards the end of 2020; this has been explained by a resurgence in Covid cases. However, New Zealand saw a similar pattern without Covid infections (red data points). It is possible that this increase was caused by the impact of the reduced healthcare provision during the extreme lockdown – though there are no data to support this supposition. There are reports that the New Zealand healthcare system experienced its busiest summer (January and February) on record with hospitals across the country reaching ‘crisis point’ and several emergency departments at capacity. The cause of this healthcare pressure is unclear, however.
Perhaps the most interesting data in the graph above are seen in 2021. During the first half of 2021 excess deaths slowly reduced from the high seen at the start of 2021 (green data points), perhaps a result of healthcare provision returning to normal. However, around mid-year the trend reversed and excess deaths started to climb again (purple data points). Again, it must be pointed out that there were very few Covid cases in New Zealand at this time, and negligible deaths. Just about the only unusual things occurring in the country at that time were a lack of international travel, restrictions in day-to-day activities for the population and an enormous mass vaccination campaign using novel, under-tested vaccines.
During 2020-2022, there were approximately 2,000 excess deaths in New Zealand, a significant number in a country with a population of five million. We don’t know the proportion that occurred because of lockdown, vaccines or something else; all that we do know is that they weren’t a result of Covid.
Note on data analysis methods. Infection, hospitalisation and mortality data were obtained from the New Zealand Ministry for Health (using Wayback Machine for historical data). Vaccination data were also obtained from the NZ Ministry for Health. Population data were obtained from Stats.govt.nz. Vaccination data were offset by seven days for the infections analysis to account for the Ministry for Health’s definition of vaccine status at infection. An additional seven days offset was applied for hospitalisation, and 14 days for death, to account for the typical timescales of disease progression.
Amanuensis is an ex-academic and senior Government scientist. He blogs at Bartram’s Folly.
The Hypocrisy of Medical Experts

By Vinay Prasad | April 3, 2022
On the one hand, there are many biomedical faculty who are passionately arguing why 2-4 year olds should be forced to wear cloth masks. (NY City is fighting this in the courts). Even though there is no randomized data, even though cloth masks failed in adults (let alone toddlers), even though it contradicts the WHO, even though it fails common sense, we must keep doing this!
On the other hand, doctors post pictures of them attending industry sponsored academic conferences. Getting drinks and partying. Packed in tight rooms. No masks. Praising each other for their work. Drenched in financial conflict of interest and pro-new and pro-costly bias.
How can both these things be true?
We are facing such a health emergency that we have to mask toddlers by force of law AND we can continue to enjoy entirely superfluous medical gatherings that risk viral spread.
Don’t say it’s vaccines.
Because the vaccinated, boosted 50 year old, elevated BMI doc with comorbidities has far higher risk than the healthy, unvax’d 4 year old.
Don’t say it’s about spreading the virus.
Both can spread the virus to others.
Don’t say it’s about the activities, importance.
The adult’s entirely excessive medical conference is less important than the child’s early education.
COVID-19 policy reveals the selfishness of adults, the indifference to kids, and the hypocrisy of medicine. It’s disgusting to witness and history will judge it poorly.
The British are now officially hiding Covid vaccine data
… and they are lying about the reason why
By Alex Berenson | April 7, 2022
Until last week, the British government offered the best source of raw data on the efficacy of the Covid vaccines. Each Thursday, the UK Health Security Agency reported the number of new infections, hospitalizations, and deaths by vaccine status.
Since last fall, and especially since the Omicron variant hit, the reports have presented an increasingly dismal picture of vaccine efficacy. Last week’s report showed that in March, nearly 90 percent of adults hospitalized for Covid were vaccinated. And OVER 90 percent of deaths were in the vaccinated:
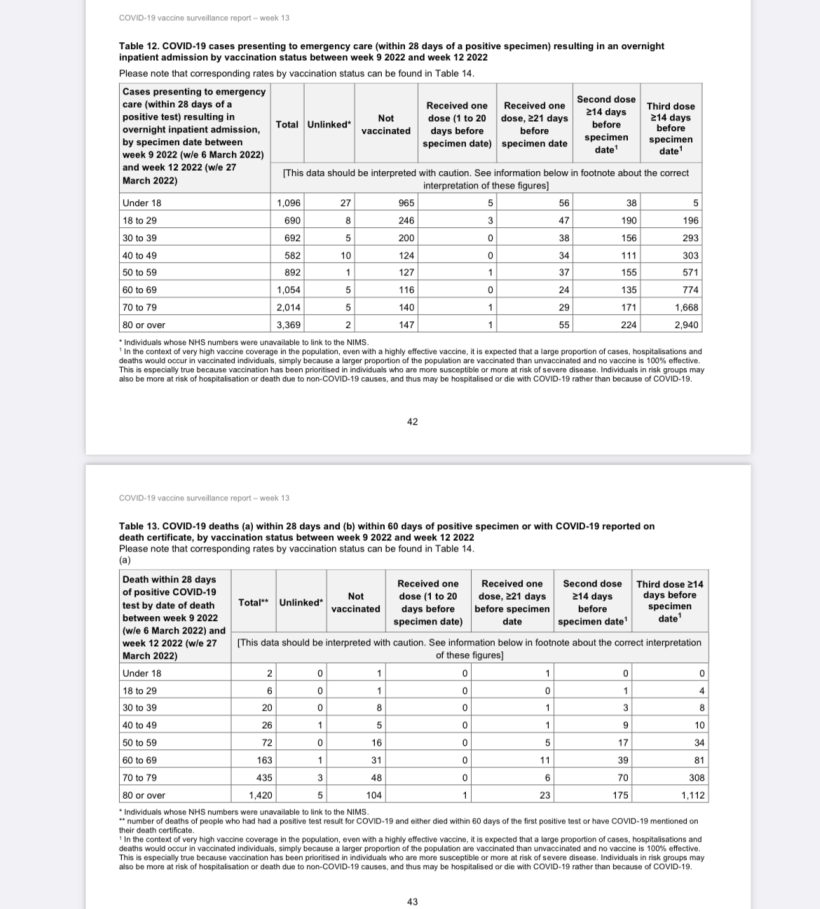
The importance of these reports is hard to overstate.
They were the single best source of raw data about how well the Covid vaccines were or were not working anywhere in the world. It was a long-running sequential series with clearly defined rules from a large country with high vaccine coverage.
Plus, because the British have national health insurance, the government could determine with near-certainty who had been vaccinated. As you can see, fewer than 1 percent of the people in the reports are called “unlinked” – meaning their vaccine status was undetermined.
AS OF THIS WEEK’S REPORT THE BRITISH GOVERNMENT IS NO LONGER PROVIDING THESE CHARTS.
The British government is offering the nonsensical excuse that it can no longer provide the figures because it has ended free universal testing for Covid: Such changes in testing policies affect the ability to robustly monitor COVID-19 cases by vaccination status, therefore, from the week 14 report onwards this section of the report will no longer be published.
The British government is lying.
Even if the end of free testing somehow affected its ability to provide “robust” data about infections, it would make no difference to the hospitalization or death figures, which are far more important. Unless Covid patients are going to be hospitalized anonymously, the Health Security Agency will still be able to match their names (and the names on death certificates) against vaccination records.
In fact the British government would be derelict not to continue to collect the data, and it surely will. But the public will no longer see it.
Why?
One reason and one reason only. Ever since I mentioned the existence of these reports to Joe Rogan in October, they have become an embarrassment. They are impossible to spin, and the clearest possible signal of vaccine failure.
But hiding the numbers won’t make the vaccines work better. It will just make people less likely to believe anything else public health authorities tell them about Covid and the vaccines – if that’s even possible at this point.
Featured Video

Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
or go to
Aletho News Archives – Video-Images
New Book
Trans agenda is ‘normalization of sadism’ – US author

RT | September 23, 2026
The US Democratic Party has embraced a transgender agenda that amounts to “the normalization of sadism,” author A.J. Rice has said, warning that radical trans policies would return if the party is allowed to regain power.
Speaking to RT’s America First host Scotty Nell Hughes about his new book, ‘The Curse of the Bearded Lady: How the Trans Mafia Whacked American Sanity’, Rice argued that activists have gained significant influence in schools, medicine, and corporate America while people who questioned the agenda have faced pressure to stay silent.
The author described the “trans mafia” as the sprawling network of people and institutions that have helped the movement gain influence. He singled out parts of academia, wealthy backers, and corporations, and stated that providers of transition-related treatment also have a financial incentive to keep young people in their care indefinitely.
Rice argued that the consequences of these policies ultimately fall on children who are being drawn toward gender-affirming medical treatments and on girls who are expected to share locker rooms or compete in sports with biological males.
He noted that while voters rejected the Democrats’ approach to gender in 2024, the party, which has been “captured by madness,” has since only doubled down and is seeking what is effectively “the normalization of sadism.” … Full report
Blog Roll
 Aletho News
- ‘We don’t seek permission to defend our country’: Snippets from President Pezeshkian’s UNGA address
- NATO chief wants Europeans to fight American wars [for Israel]
- German chemicals giant reveals details of downsizing
- Refaat Al-Areer Was The Canary In The Coal Mine In Israel’s War On The Truth
- Israeli election committee bars candidate from Knesset race over Gaza war opposition
- French-Lebanese man files war crimes complaint over Israeli attacks
- Mahan Air Flight Lands in China Despite US Threat against Iranian Airlines
- US eyes $10bn fund to rebuild war-battered Gulf infrastructure
- Trump meets Rodríguez near Maduro’s prison as Venezuela’s oil flows to US
- Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
- If Americans Knew
- Caught on Tape: AIPAC CEO Boasted of Controlling Trump’s National Security Officials
- Why Hamas Attacked Israel in October 2023 – Israeli professor Ilan Pappé
- They see them, then kill them: Israeli quadcopters track, deliberately target civilians in Gaza
- Winter could turn Gaza’s treacherous, war-damaged buildings into deathtraps
- Majority of Democratic Voters Want to Prosecute Both Biden and Trump Administration Officials Over Gaza
- As Gaza languishes, world leaders gather at the UN – Daily Update
- Sanctions are collective punishment: immoral and self-defeating
- Phosphorus Munitions Fired by Israel Burn Groves, Orchards in Southern Lebanon
- Israel Carries Out New Ceasefire Violations Across Gaza
- AI – Emphasis on the ‘I’: Israel Is Funding AI Chatbot Propaganda
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

