The worst of Covid advertising
The Naked Emperor’s Newsletter | April 16, 2022
Advertising / propaganda played a massive part in keeping citizens compliant and afraid. Quite frankly, advertising companies should feel ashamed with the amount of societal manipulation they caused in exchange for government coin.
Early on in the pandemic, the Scientific Advisory Group for Emergencies (SAGE) in the UK called for an increase in the perceived threat of Covid by using hard-hitting emotional messages. However, it has since been revealed that government contracts and messages were in place weeks before lockdowns were even suggested.
These adverts were produced in collaboration with behavioural scientists, trying to nudge people to do what they wanted using tactics that operate below the level of awareness.
The UK spent over £240 million on these adverts in 2020 and up to £320 million in 2021. Obscene amounts of money. To put this in context, the government spent £46 million on advertising “Get Ready for Brexit” in 2019, the biggest spend since the second world war.
I have posted some of the worst images from the UK below. They made people feel guilty, ashamed, worried that they would kill people and angry against those who did not precisely follow the rules.




April 16, 2022 Posted by aletho | Civil Liberties, Deception, Science and Pseudo-Science, Timeless or most popular | Covid-19, Human rights, UK | Leave a comment
What defines a good drug?
By Sebastian Rushworth, M.D. | April 14, 2022
Most people will naturally assume that when a doctor prescribes them a drug, it’s because the doctor thinks they will receive a meaningful benefit from it. Most people have never heard the term NNT, which stands for Number Needed to Treat, or to put it another way, the number of people who need to take a drug for one person to see a noticeable benefit. It’s a bit of a counterintuitive concept for people outside medicine, since most people probably assume the NNT for all drugs is 1, right? If I’m getting this drug, it must be because it is going to help me. Well, wrong.
Before we move on, I want you to perform two small thought experiments:
Say you were suffering from depression, and there was a drug that could potentially improve your mood. But it’s not certain that the drug will work for you. And there’s a catch – the drug has side effects, which you are likely to experience regardless of whether you get the benefits of the drug or not. This particular drug causes a reduction in sexual desire and increased difficulty achieving orgasm during sex.
It also causes subtle changes to your personality, making you more prone to take risks, less emotional, and less empathic. It increases your tendency to engage in addictive behaviours, and it’s been known to cause addictions to alcohol and gambling. Additionally, withdrawal is common, so many people have trouble getting off the drug once they’re on it.
How good would the NNT for this drug need to be for you to be willing to take it? Would you want absolute certainty that it would end your depression, considering the harms? or would 50:50 odds be enough? Or even less?
Keep whatever odds you decide on in mind. If you, for example, think one in two odds are good enough, then that gives an NNT of 2 (you need to treat two people to get a noticeable benefit in one of them).
Ok, next scenario. Say you’d had a heart attack, and there was a drug that could decrease your risk of another heart attack. But just as with the previous drug, there are no certainties that you will actually get any benefit from taking this drug. And this drug also has side effects. Many people who take the drug develop chronic aches and pains. The drug also causes noticeable cognitive impairment in a proportion of those taking it, and some even end up being diagnosed with dementia – how big the risk is unfortunately isn’t known, because proper studies haven’t been carried out that could answer that question. Additionally, the drug causes blood sugar levels to rise, resulting in type 2 diabetes in around 2% of those taking the drug – it is in fact one of the most common causes of type 2 diabetes.
How good would the NNT for heart attack prevention need to be for you to take this drug?
Again, keep the number in mind.
As many of you have probably guessed, the first drug I described is an SSRI (examples of this type of drug are sertraline, citalopram, and fluoxetine). Currently, around 15% of adults in western countries take an SSRI every day.
So, what is the actual NNT for SSRI’s when used as a treatment for depression?
It’s seven.
In other words, you need to treat seven people for one to experience a noticeable effect on their depression. The other six just get the side effects but no benefit. And when I say “effect”, I don’t mean that the depression resolved in the one person lucky enough to see a benefit. Far from it. I mean that on a certain numerical rating scale (MADRS, if you must know), they experienced an improvement in mood that was just big enough to be detectable using statistical methods.
What NNT number did you choose? Are 7:1 odds good enough for you to take an SSRI if you get depressed, knowing the harms?
When a doctor prescribes an SSRI to a depressed patient, they (hopefully) know that the odds of the patient benefitting even slightly are only 1/7 (or 14%). Which doesn’t seem like a very good deal to me. Yet SSRI’s are widely considered to be an “effective” drug.
The second drug, as many of you have probably also guessed, is a statin (examples include atorvastatin, simvastatin, and pravastatin). More than a quarter of adults over the age of 40 take a statin every day in western countries.
So, what is the NNT for statins?
Well, if you’ve already had a heart attack, i.e. you’ve already been established to be at high risk for heart attacks, then the NNT over five years of treatment is 40. In other words, 39 of 40 people taking a high dose statin for five years after a heart attack won’t experience any noticeable benefit. But even if they’re not the lucky one in 40 who gets to avoid a heart attack, they’ll still have to contend with the side effects.
What NNT did you decide on personally? Are 40:1 odds good enough for you to decide the benefits of a statin outweigh the harms?
Of course, patients rarely get presented with this type of information, and are thus rarely able to make an informed choice of their own. I once sat in on a conversation between a cardiologist and a patient who’d recently had a heart attack. The patient was skeptical about statins. He said that he’d read on the internet that they had side effects, and he wasn’t sure he wanted to take one.
The cardiologist gave the patient a long, withering stare, and then responded that there’s a lot of misinformation on the internet, and that the statin was the number one most important thing he could do if he wanted to not die prematurely.
Which I thought was a bit arrogant. Why?
Because the probability that the statins would prevent a future heart attack, let alone premature death, was in the low single digits, and the patient might quite reasonably have felt that that marginal benefit was outweighed by the various harms (which the cardiologist incidentally hadn’t mentioned at all – and which the patient thus wouldn’t have even known about if he hadn’t read “misinformation” on the internet).
Doctors have been conditioned by the pharmaceutical industry to think that drugs that provide very low probability of benefit are effective. An NNT of 10 is often considered good, and an NNT of 5 is considered excellent. Even an NNT of over 100 is often considered acceptable! Patients are rarely informed that the odds of them getting any benefit from the new drug they’re being prescribed are far less than 50:50. And they’re rarely informed about what the harms are, and how likely they are to experience them.
Just in case you think I’m picking on a few particularly ineffective drugs with my two examples, I’m not. NNT’s of five or worse are typical for many of the most commonly prescribed drugs.
What that means is that the average 70 year old who is on five drugs continuously will probably at best only benefit in any measurable way from one of those drugs. The other four are not providing any benefit, they’re just contributing to side effects (which become increasingly likely, and increasingly deadly, the older you get). Things get even worse when you consider that drugs interact in unpredictable ways to increase the risk of side effects, so the risk of harms increases exponentially with each additional drug added. Which is why it used to be considered bad form to have a patient on more than five drugs simultaneously.
The number of drugs the average person is on has increased massively over the last few decades. Polypharmacy (people taking multiple different drugs continuously) is now one of the top five leading causes of death in the western world – which is a little ironic when you consider that people are taking all those drugs in order to live longer. The best way to avoid becoming another polypharmacy death statistic is to be careful about which drugs you take, and only take those for which it’s clear that the benefits outweigh the harms.
From my perspective, a good drug is a drug for which the benefits clearly outweigh the harms. I’m not saying that all drugs with high NNT’s are inherently useless. A drug with an NNT of 40 might be worth taking, if the risks of harm are sufficiently low and the outcome is sufficiently important. Only the patient can make that decision.
Whether a drug is good for you as an individual is clearly context specific. The decision whether or not to take a certain drug requires a deep understanding of the drug (provided by the physician) and a deep understanding of personal values and wishes (provided by the patient). It requires a holistic perspective and a meeting of two minds that is literally the opposite of what doctors are asked to practice today, where we’re continuously pestered with various treatment guidelines and targets that turn physicians in to unthinking automatons and patients in to featureless blobs.
April 16, 2022 Posted by aletho | Science and Pseudo-Science, Timeless or most popular | Leave a comment
How Dangerous Are Masks for Children?
BY PAUL ELIAS ALEXANDER | BROWNSTONE INSTITUTE | APRIL 15, 2022
Our public health agencies such as the CDC and NIH, and television medical experts seem unable to address key health messages that could have a dramatic effect in reducing risk of severe sequelae in higher-risk populations such as the minority and African-American population to the scourge of SARS-CoV-2.
These agencies and media echo chambers squandered many opportunities to inform the public on simple yet very effective messaging (vitamin D supplementation, obesity control, early treatment etc.) that could have reduced morbidity and saved lives. They continue to. Not just for Covid-19, but for many other illnesses.
For example, obesity emerged as a potent super-loaded risk factor behind age in the harmful sequelae and a human target for SARS-CoV-2 in most studies, in addition to being elderly, frail and having comorbid conditions. Being younger with comorbid conditions also placed one at risk.
We knew this data very early on, maybe one month post-March 2020 yet the CDC etc. failed to either read the data, understand the data, or act on the data. It would have behooved our agencies to have addressed these risks in large-scale education programs for the populace and especially by calling for a reduction in body weight and particularly for the minority sub-groups (African-Americans).
In a similar light, studies showed that vitamin D supplementation for African-Americans has been associated with a lowered risk of severe disease and mortality from SARS-CoV-2. So the evidence was there; just the action by health agencies was absent.
Early ambulatory outpatient treatment with successful combination and sequenced antiviral agents, corticosteroids, and anti-clotting therapeutics should be used (and should have been used) widely to help the people at risk. The African-American community is aware that “Covid (is) a killer for the obese: like pouring gasoline on top of a fire.”
Unfortunately, more than two years into the pandemic, the manifest issue of public health education and sound policy decisions remain absent and aloof, given the erratic and confusing responses from the health and governing officials.
Now we face another looming concern: the potential danger of the chlorine, polyester, and microplastic components of the face masks (surgical principally but any of the mass-produced masks) that have become part of our daily lives due to the Covid-19 pandemic.
Emergent reports, albeit nascent and anecdotal but nevertheless vitally important (and will be clarified and defined in time) regarding the manufacture of masks, where, “many of them (face masks) are made of polyester, so you have a microplastic problem… many of the face masks would contain polyester with chlorine compounds… if I have the mask in front of my face, then of course I inhale the microplastic directly and these substances are much more toxic than if you swallow them, as they get directly into the nervous system.”
A very recent 2022 British publication (Jenner et al. Detection of microplastics in human lung tissue using μFTIR spectroscopy) focused on polypropylene that is a component of the face masks and reported that such “microplastics were identified in all regions of the human lungs using μFTIR analysis.” Furthermore, “polypropylene and polyethylene terephthalate fibres were the most abundant.” Researchers concluded that inhalation was “a route of MP exposure.” And that this study “is the first to report MPs within human lung tissue samples, using μFTIR spectroscopy.”
There were also early reports of toxic mold, fungi, and bacteria that can pose a significant threat to the immune system by potentially weakening it. Of particular concern to us is the recent report of breathing in synthetic fibers in the face masks. This is of serious concern.
“Loose particulate was seen on each type of mask. Also, tight and loose fibers were seen on each type of mask. If every foreign particle and every fiber in every facemask is always secure and not detachable by airflow, then there should be no risk of inhalation of such particles and fibers. However, if even a small portion of mask fibers is detachable by inspiratory airflow, or if there is debris in mask manufacture or packaging or handling, then there is the possibility of not only entry of foreign material to the airways, but also entry to deep lung tissue, and potential pathological consequences of foreign bodies in the lungs.”
Reports are that “Graphene is a strong, very thin material that is used in fabrication, but it can be harmful to lungs when inhaled and can cause long-term health problems.”
There is a risk of potential inflammatory/fibrotic lung diseases because we are inhaling these materials in the masks now for two years with more duration to come and no end in sight. These substances might also be highly carcinogenic. Not just for us as adults but we must be very concerned about the risks especially to our children since they depend on us as mentors and guides for their decision-making.
These blue surgical masks pervade our lives. They remain ubiquitous. “Health Canada issued a warning about blue and gray disposable face masks, which contain an asbestos-like substance associated with “early pulmonary toxicity.” The warning is specific to potentially toxic masks distributed within schools and daycares across Quebec. Health Canada (and full praise to them)….“discovered during a preliminary risk assessment that the masks contain microscopic graphene particles that, when inhaled, could cause severe lung damage.”
Reports are and were that “for a while now, some daycare educators had expressed suspicion about the masks, which were causing children to feel as though they were swallowing cat hair while wearing them. We now know that instead of cat hair, children were inhaling the equivalent of asbestos all day long.”It appears to be a substance known as graphene.
What is indeed alarming is that “the SNN200642 masks that were being used all across Canada in school classrooms had never been tested for safety or effectiveness.” This is indeed a catastrophic failure by the regulators as these surgical face masks are linked to early pulmonary toxicity.
What is indeed frightening is that all of these blue and similar surgical face masks cause plastic fiber inhalation and the outcomes could be devastating, especially to our children. Yet it has pervaded and persons making Covid policy decisions do not seem to care about the harmful implications. These face mask plastics will degrade very slowly over time and as such, in the lungs it may remain and just build up to dangerous levels.
We do not even know what is an ‘acceptable’ level, for there should be none. There is debate that the immune system can attack such foreign objects, thus driving prolonged inflammation which may lead to diseases such as cancer. And reused masks which pervade our daily lives, and based on our personal experiences, do produce more loosened fibers.
Dr. Richard Urso showed us just how dangerous these are by putting them under a microscope, revealing the melt-blown polypropylene plastic. Some masks even contain fiberglass and this is very dangerous as we know to inhale. We as parents make these decisions; we have to step back and question many of these decisions we are making that seem suboptimal. If it does not seem right, then you have to push back and question and demand the science, demand the data from these seemingly untethered experts.
We certainly did not get (across the last two years) and are not presently getting the due diligence and protection from public health experts, the relevant health agencies, and policy makers that we need.
Moreover, the mass media seems incapable of doing the investigative type of journalism to fully inform the populace on what the public needs to know. We close by reiterating the warning in the JAMA publication that “Face masks should not be worn by healthy individuals to protect themselves from acquiring respiratory infection because there is no evidence to suggest that face masks worn by healthy individuals are effective in preventing people from becoming ill.”
Every act has a consequence, and there is always risk. It is therefore imperative to weigh the consequences before embarking on a specific course of action. These are risk management decisions especially for parents and not because a Dr. Fauci type tells you to do something means that it is accurate or necessary. Just consider the nonsense we heard about double masking where he said use them one day only to then retract on another day.
Children come with a potent innate immune system that works tremendously well. At the same time and similarly, their immune systems are still being developed, and we have forced lockdowns, school closures, and masking on a developing child. We have no prior experience on the subsequent outcomes pertaining to children’s development, health, and well-being.
We may be faced with catastrophic consequences of what we did to our children over the last two years of unsound Covid restrictive policies, and allowed government technocrats to force these upon them. These are matters too important to nonchalantly disregard.
Dr. Paul Alexander is an epidemiologist focusing on clinical epidemiology, evidence-based medicine, and research methodology. He has a bachelor’s in epidemiology from McMaster University, and a master’s degree from Oxford University. He earned his PhD from McMaster’s Department of Health Research Methods, Evidence, and Impact. Paul is a former WHO Consultant and Senior Advisor to US Department of HHS in 2020 for the COVID-19 response.
April 15, 2022 Posted by aletho | Science and Pseudo-Science, Timeless or most popular | CDC, Covid-19, NIH, United States | Leave a comment
More Than 1 Million COVID Vaccine Injuries, Nearly 27,000 Deaths Reported to VAERS: CDC Data
By Megan Redshaw | The Defender | April 15, 2022
The Centers for Disease Control and Prevention (CDC) today released new data showing a total of 1,226,314 reports of adverse events following COVID vaccines were submitted between Dec. 14, 2020, and April 8, 2022, to the Vaccine Adverse Event Reporting System (VAERS). VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
The data included a total of 26,976 reports of deaths — an increase of 277 over the previous week — and 219,865 serious injuries, including deaths, during the same time period — up 2,564 compared with the previous week.
Excluding “foreign reports” to VAERS, 805,921 adverse events, including 12,471 deaths and 79,811 serious injuries, were reported in the U.S. between Dec. 14, 2020, and April 8, 2022.
Foreign reports are reports foreign subsidiaries send to U.S. vaccine manufacturers. Under U.S. Food and Drug Administration (FDA) regulations, if a manufacturer is notified of a foreign case report that describes an event that is both serious and does not appear on the product’s labeling, the manufacturer is required to submit the report to VAERS.
Of the 12,471 U.S. deaths reported as of April 8, 17% occurred within 24 hours of vaccination, 21% occurred within 48 hours of vaccination and 59% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 564 million COVID vaccine doses had been administered as of April 8, including 334 million doses of Pfizer, 212 million doses of Moderna and 19 million doses of Johnson & Johnson (J&J).
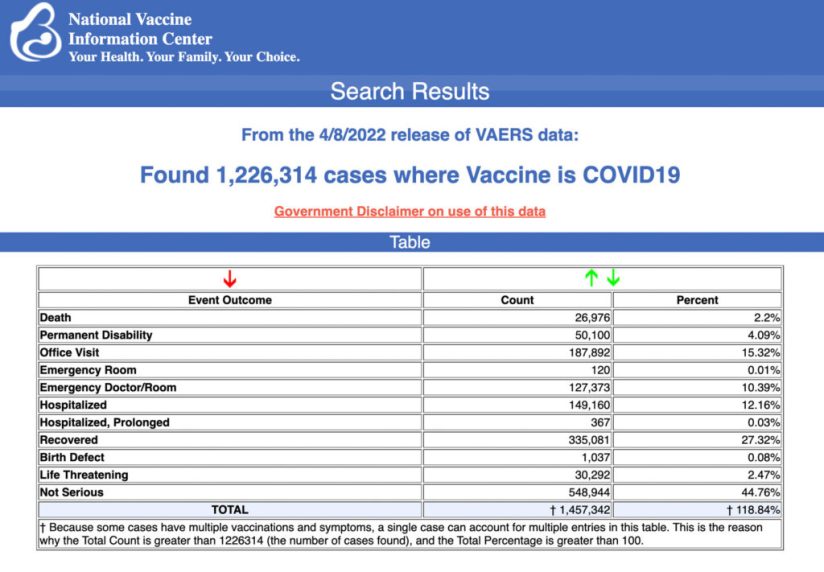
Every Friday, VAERS publishes vaccine injury reports received as of a specified date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed.
Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
U.S. VAERS data from Dec. 14, 2020, to April 8, 2022, for 5- to 11-year-olds show:
- 10,216 adverse events, including 242 rated as serious and 5 reported deaths.
- 18 reports of myocarditis and pericarditis (heart inflammation).
The CDC uses a narrowed case definition of “myocarditis,” which excludes cases of cardiac arrest, ischemic strokes and deaths due to heart problems that occur before one has the chance to go to the emergency department. - 39 reports of blood clotting disorders.
U.S. VAERS data from Dec. 14, 2020, to April 8, 2022, for 12- to 17-year-olds show:
- 31,048 adverse events, including 1,792 rated as serious and 44 reported deaths.
- 67 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases attributed to Pfizer’s vaccine.
- 651 reports of myocarditis and pericarditis, with 639 cases attributed to Pfizer’s vaccine.
- 166 reports of blood clotting disorders, with all cases attributed to Pfizer.
U.S. VAERS data from Dec. 14, 2020, to April 8, 2022, for all age groups combined, show:
- 20% of deaths were related to cardiac disorders.
- 54% of those who died were male, 41% were female and the remaining death reports did not include the gender of the deceased.
- The average age of death was 73.
- As of April 8, 5,404 pregnant women reported adverse events related to COVID vaccines, including 1,6936 reports of miscarriage or premature birth.
- Of the 3,647 cases of Bell’s Palsy reported, 51% were attributed to Pfizer vaccinations, 40% to Moderna and 8% to J&J.
- 860 reports of Guillain-Barré syndrome, with 42% of cases attributed to Pfizer, 30% to Moderna and 28% to J&J.
- 2,373 reports of anaphylaxis where the reaction was life-threatening, required treatment or resulted in death.
- 1,671 reports of myocardial infarction.
- 13,755 reports of blood-clotting disorders in the U.S. Of those, 6,169 reports were attributed to Pfizer, 4,911 reports to Moderna and 2,654 reports to J&J.
- 4,124 cases of myocarditis and pericarditis with 2,531 cases attributed to Pfizer, 1,402 cases to Moderna and 181 cases to J&J’s COVID vaccine.
Woman develops fatal brain disease after second Moderna dose
Carol Beauchine died from sporadic Creutzfeldt-Jakob Disease (CJD), a rapidly evolving, fatal degenerative brain disorder she developed after her second dose of Moderna’s COVID vaccine.
In an exclusive interview with The Defender, Carol’s son, Jeffrey Beauchine, said it was excruciating to watch his 70-year-old mother — who was healthy until she got the vaccine — die from a disease he believes the vaccine caused.
Beauchine said Carol received her first dose of Moderna on Feb. 16, 2021, and didn’t report any complaints. After getting the second dose on March 17, Carol immediately said she “felt different.” She developed numbness that spread throughout the entire left side of her body, blindness and hearing loss. She lost the ability to walk and communicate, and her brain degenerated until she passed away on Aug. 2, 2021 — just five months after receiving her second dose of Moderna.
The family submitted a report to VAERS, but the CDC has not followed up on Carol’s death. The Defender has received numerous reports of people who died from sporadic CJD after receiving a COVID vaccine — all women who were between the ages of 60 and 70, including Cheryl Cohen and Jennifer Deason Sprague.
Biden administration extends COVID public health emergency needed to keep vaccines under EUA
The Biden administration on Wednesday extended the COVID public health emergency, now two years old, for an additional 90 days — allowing vaccines and other drugs to remain under Emergency Use Authorization (EUA). Keeping COVID vaccines and other countermeasures under EUA shields pharmaceutical companies from liability for the harms caused by their products.
According to Reuters, a public health emergency was initially announced in January 2020, when the COVID pandemic began. It has been renewed each quarter since and was due to expire on April 16.
The Department of Health and Human Services (HHS) said in a statement it was extending the public health emergency and will give states 60 days’ notice prior to termination or expiration. This may be the last time HHS Secretary Xavier Becerra extends it, according to policy experts.
Pfizer to seek authorization from FDA for COVID booster shot for kids 5 to 11 years old
Pfizer and BioNTech Thursday said they plan to apply for EUA of a COVID booster dose for healthy 5- to 11-year-olds based on the results of a small study that has not been published or analyzed by independent experts.
Pfizer said in a press release the third dose of its vaccine produced significant protection against the Omicron variant in children 5 to 11 in a small Phase 2/3 clinical trial. The study was based on data from only 140 children 5 through 11 years old who received a booster dose six months after the second dose of Pfizer-BioNTech’s COVID vaccine as part of the primary series.
Pfizer claimed a closer look at 30 children showed a 36-fold increase in virus-fighting antibodies — levels high enough to fight the Omicron variant, and that a third dose was “well tolerated with no new safety signals observed.”
Although Pfizer said more than 10,000 children under the age of 12 have participated in clinical trials investigating Pfizer’s COVID vaccine, only 140 were selected for the study forming the basis for the company’s EUA request.
CDC launches internal review over failed COVID response
The CDC announced Monday it was launching a month-long comprehensive agency-wide review following widespread criticism of the agency’s response to the COVID pandemic.
The agency plans to evaluate its structure, systems and processes, CDC Director Dr. Rochelle Walensky told staff in an email obtained by The Washington Post. Walensky said the goal of the review is to “modernize” the agency and “to position CDC, and the public health community, for greatest success in the future.”
The review will be conducted by Jim Mcrae, associate administrator for primary healthcare at the Health Resources and Services Administration (HRSA). The HRSA and the CDC are part of the Department of Health and Human Services.
Last month, the CDC’s decision to remove from its data tracker website tens of thousands of deaths linked to COVID — including nearly a quarter of the deaths the agency said had occurred among children — eroded public trust in the CDC’s handling of case counts.
Children’s Health Defense asks anyone who has experienced an adverse reaction, to any vaccine, to file a report following these three steps.
April 15, 2022 Posted by aletho | Science and Pseudo-Science | COVID-19 Vaccine, United States | Leave a comment
Pfizer to Ask FDA to Allow 3rd COVID Shot for Healthy 5- to 11-Year-Olds, Based on Study of 140 Kids
By Megan Redshaw | The Defender | April 14, 2022
Pfizer and BioNTech today said they plan to apply for Emergency Use Authorization (EUA) of a COVID-19 booster dose for healthy 5- to 11-year-olds based on results of a small study that has not been published or analyzed by independent experts.
The companies also plan to request authorization from the European Medicines Agency and other regulatory agencies around the world as soon as possible.
Pfizer said in a press release the third dose of its vaccine produced significant protection against the Omicron variant in children 5 to 11 in a small Phase 2/3 clinical trial.
The study was based on data from only 140 children 5 through 11 years old who received a booster dose six months after the second dose of Pfizer-BioNTech’s COVID vaccine as part of the primary series.
A closer look at 30 children showed a 36-fold increase in virus-fighting antibodies — levels high enough to fight the Omicron variant, ABC News reported.
Pfizer claimed the third dose was “well tolerated with no new safety signals observed.”
Although Pfizer said more than 10,000 children under the age of 12 have participated in clinical trials investigating Pfizer’s COVID vaccine, only 140 were selected for the study forming the basis for the company’s EUA request.
Commenting on the news, Dr. Brian Hooker said, “The clinical trial used to support the notion of a COVID-19 booster for 5- to 11-year-olds is entirely inadequate to make any such recommendation.”
Hooker, chief science advisor at Children’s Health Defense (CHD), added:
“This small-scale, limited-time trial contains only 140 patients, which is not sufficiently sized to assess vaccine adverse events at all, especially rarer injuries such as the devastating medical maladies sustained by Maddie de Garay — an adolescent injured in the original Pfizer clinical trial.”
Hooker said he was also concerned there are “no data on the prevention of COVID-19 infection, only neutralizing antibody titers, which are not necessarily predictive of transmission and severity of the disease.”
Dr. Liz Mumper, a pediatrician, said, “Once again, Pfizer does science by press release.” Mumper said the rise in antibody titers is just one small piece of the story of kids and COVID.
“The more important issue is that, on the basis of careful risk-versus-benefit analysis, healthy children do not need a COVID vaccine,” Mumper said, because many kids already had COVID and developed robust and durable antibodies.
CHD President Mary Holland accused Pfizer of reaching “a new low” by seeking authorization of booster shots for children based on an “unpublished, non-peer-reviewed study of 140 children.”
Holland said:
“Following the science on COVID vaccination shows that the risks outweigh the benefits for COVID shots for kids, let alone boosters. One suspects this is simply a misguided ploy to use up Pfizer’s vaccine inventory before its expiration.”
Pfizer tested its booster dose while Omicron was the dominant variant this winter. In recent weeks, BA.2 has become the dominant COVID variant. It has not been determined whether a third dose provides any protection against the new variant.
The U.S. Food and Drug Administration (FDA) in October 2021 authorized the Pfizer-BioNTech COVID vaccine for children 5 through 11 and recently authorized a booster dose for teens 12 through 15 and older and also immunocompromised children 5 and older.
According to a study published late last month in The New England Journal of Medicine, Pfizer’s vaccine showed “reduced effectiveness” against the Omicron variant among children 12 and older.
According to an analysis of Centers for Disease Control and Prevention (CDC) data by the American Academy of Pediatrics, as of April 6, 2022, 9.7 million U.S. children ages 5 to 11 had received at least one dose of a COVID vaccine — representing 34% of 5- to 11-year-olds.
Approximately 7.8 million U.S. children ages 5 to 11 completed the 2-dose primary vaccination series — representing 28% of 5- to 11-year-olds.
About 18.7 million children 5 to 11 had yet to receive their first COVID vaccine dose.
Seventeen million U.S. adolescents ages 12 to 17 have received at least one dose of a COVID vaccine — representing 68% of 12- to 17-year-olds.
Only 58% completed the 2-dose vaccination series and 8.1 million adolescents in this age group have yet to receive a COVID vaccine.
There are 72.8 million children under age 18 in the U.S., which is 22% of the U.S. population. Children aged 5 to 11 represent 8.6% of the U.S. population.
The FDA has not authorized any COVID vaccines for use in children under 5.
According to the latest data from the CDC’s Vaccine Adverse Events Reporting System (VAERS), between Oct. 1, 2021, and April 1, 2022, 10,157 adverse events, including 239 rated as serious and 5 reported deaths after COVID vaccines, were reported in the 5- to 11-year-old age group.
Although reports submitted to VAERS require further investigation before a causal relationship can be confirmed, the system has been shown to report only 1% of actual vaccine adverse events.
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
April 15, 2022 Posted by aletho | Science and Pseudo-Science, Timeless or most popular, War Crimes | COVID-19 Vaccine | Leave a comment
The Face Mask Cult

The Daily Sceptic | April 13, 2022
There follows a post by Hector Drummond, a former academic who worked in risk, who says when he came to research his new book The Face Mask Cult on the effectiveness of masks against COVID-19 the evidence was threadbare.
In 2021 I decided to write an FAQ on all aspects of Covid, lockdowns and non-pharmaceutical interventions (NPIs). I started with face masks, as they seemed to be the easiest issue to deal with, thinking that the whole mask situation could be summed up in five to six pages. After a few days work I had twenty pages of text, and another twenty pages of reminder notes on further aspects of face masks that I needed to consider and research. Those notes ballooned out in the next few weeks, and I realised that the use of face masks to prevent the spread of COVID-19 was a far bigger topic than I had appreciated, and would require substantial amounts of writing, and months of research and literature-reading.
It took until the next year before I decided I’d written enough on the topic. I had read an enormous number of scientific papers and other articles on masks, and gone through some of them with a fine-tooth comb (see Part 3 of the book, for instance). I had spent considerable time analysing, synthesising and rewriting, and my short FAQ article had become a comprehensive 400-page book that tackled all aspects of the issue, as well as a unique resource with its extensive scientific literature review section.
In all my researches I failed to come across very much in the way of convincing evidence that masks work. The papers that were supposed to show that they did all turned out to be poor pieces of science. None were randomly-controlled peer-reviewed trials. Some were observational studies, with inadequate controls for dealing with the possibility of faulty or biased recollection. Some were ‘modelling’ studies, in which a computer program was used to ‘model’ the effect of face masks on disease spread. Modelling studies are generally hopeless at providing any confirming evidence for the effectiveness of face masks as they require the modellers to make assumptions about how effective the masks are when writing their programs. Some were mannequin studies, in which a dummy in a lab with artificial breathing functions, rather than a real person in the real world, was used. Some were simply tests of the porosity of various materials in regard to salt aerosols.
Most studies ignored the issue of face mask gaps, despite it being well-known in the field that gaps around the sides of masks will let such large amounts of virions in and out that any effect that the masks do have will be completely negated. (This is why medical institutions require ‘fit tests’ for masks – not that fit tests are very reliable, as I explain in the book.)
Even these dubious studies that claimed to show an effect for masks didn’t show much of an effect. The less wild ones would typically claim that the cloth masks would stop 5% to 15% of virions, but they never presented any reason to believe the further claim that was often made that this would cause a 5% to 15% reduction in cases, or a 5% to 15% reduction in deaths. The closest such studies got to doing so was when an author would occasionally speculate, in an airy fashion, that if the disease in question’s R0 rate happened to be close to 1.0, then maybe widespread mask use (assuming masks had some small effect) would be enough to push the R0 rate below 1.0, in which case the disease would die out, although of course even if all their assumptions were true and masks did push the disease’s R0 rate below 1.0 it doesn’t follow that the disease would die out anytime soon. It could well be that the disease’s R0 rate would quickly come back over 1.0 again as soon as we stop masking, and so in order to stop the disease spreading again we would have to wear masks for years on end, or even indefinitely.
But what about all those government reports written by distinguished scientists assuring us that there were now truckloads of research proving that masks work? This is perhaps the most shocking part of the whole face mask con. The 2020 DELVE report and its updates, the 2020 Royal Society report, and the 2022 Department for Education’s Evidence Summary were disgraceful pieces of misinformation, as I show in detail in the book. Even more shocking, perhaps, is the fact that there have been so many acts of wrongdoing in the last two years that the scientific butchery committed in these reports is completely unknown to the general public. The fact, for instance, that the Royal Society’s report relied heavily upon a low-grade Chinese study, written in Chinese only, and published in an obscure Chinese journal, which reported fantastically unrealistic results, is never even going to briefly flit through the mind of the average person, because the average person will never come across any reference to this shameful affair in the mainstream media.
I felt vindicated as I put the finishing touches to the book when several prominent advocates of masks, such as Trish Greenhalgh, Jeremy Howard and many others, started to admit that cloth masks were useless. Not that they wanted us to stop wearing masks – they now wanted us to move onto medical-grade respirator masks, like N95s and FFP2s, as Germany required. Needless to say, these mask fanatics didn’t bother to mention that Germany’s stringent mask policy has been a complete failure.
The book I finished up with is a serious corrective to the endless propaganda we have been fed about masks. It lays out the case against masks in detail, considers the harms done by mask-wearing (harms which are usually ignored by scientists and governments), closely examines many claims made about masks by both sides, and backs it all up with an enormous number of references to the scientific literature. Whenever anyone who wants you to wear a mask says, “Follow the Science”, just show them this book and say, “I already did”.
You can buy the book here in paperback and on Kindle.
April 15, 2022 Posted by aletho | Book Review, Deception, Science and Pseudo-Science, Timeless or most popular | Covid-19 | Leave a comment
Smiling US health chief shrugs off her Covid blunders
By James Rogers | TCW Defending Freedom | April 14, 2022
Dr Rochelle Walensky is director of the Centers for Disease Control and Prevention (CDC), the national public health agency of the United States.
Just over a year ago, on March 29, 2021, Dr Walensky publicly stated: ‘Vaccinated people do not carry the virus . . . and do not get sick.’
She also claimed that the Pfizer jab was 95 per cent effective at preventing Covid-19. Last month Dr Walensky answered questions at Washington University, St Louis, during which she admitted that her claim of 95 per cent Pfizer jab-effectiveness came from CNN, which based its report on a press release from Pfizer.
Walensky also claimed she was unaware the shots might lose effectiveness over time. Yet she’s a highly qualified public health official, and even 15-year-old science students know that cold/flu viruses are prone to mutations, which go a long way to altering a vaccine’s effectiveness. It was quite galling to hear her talk about ‘waning jab efficacy’, then casually smile, shrug her shoulders and say: ‘Science is not black and white, it’s not immediate . . . science is grey’ i.e. that nobody could be certain.
Contrary to Dr Walensky’s position in spring 2022, throughout 2021, the US authorities (and elsewhere) were so certain of jab efficacy that they insisted that everyone had to get jabbed. Never mind the psychological pressure and moral blackmail, they threatened serious consequences: fines, imprisonment, ‘no jab, no job’ and ‘no jab, no school’ mandates. They were so certain about jab efficacy that they threatened peoples’ livelihoods, careers, businesses and education. They were certain enough to foment severe discord in society, creating disputes and anxiety that damaged, fractured and destroyed marriages, families and friendships.
They pushed the jabs this hard, but they had no real idea how well they worked. Now we know that they don’t work at all; we also strongly suspect that the jabs actually make infection levels and illnesses worse, and this does not include jab-related deaths, conditions and illnesses that should result in the total withdrawal of these chemicals.
The Walenskys of this world were so certain, yet it in reality they were so wrong, so her airy dismissal of these errors in her interview was absolutely breath-taking.
A few questions also spring to mind:
Dr Walensky has a BA in biochemistry and molecular biology and a masters in public health from Harvard. She is a scientist. How is it possible that someone with such qualifications, and holding a position of such responsibility, doesn’t know that cold/flu viruses mutate?
Dr Walensky is also a MD. Has she forgotten the ethics and principles of informed consent? We’ll return to this point.
Why was the director the CDC accepting information about a new drug from its manufacturer (Pfizer) via CNN? Should the CDC accept the manufacturer’s own assessment and then tell the whole population with certainty that it is ‘safe and effective’? Shouldn’t they be doing their own thorough investigations and evaluations? Especially since mRNA technology was so new and untested.
Did it not occur to Dr Walensky that if the new, ‘safe and effective’ mRNA-based jab was not ‘effective’, it might not be all that ‘safe’ either? Did the possibility that the drug’s emergency authorisation ought to be withdrawn not occur to her? If it didn’t, her competence must be questioned. If it did, and she discussed it, we need to know a lot more details. If it did, and she dismissed it, she ought to be asked a lot more questions.
The US-based Informed Consent Action Network (ICAN) pressure group has obtained data revealing that 70 per cent of the CDC staff who got Covid from August last year onwards were fully vaccinated. This raises other questions:
With such evidence in front of Dr Walensky, why didn’t the CDC withdraw support for government mandates?
Why didn’t Dr Walensky tell President Biden that he might think again before dishonourably discharging members of the armed services for declining a jab?
Why didn’t the CDC inform the American public that claims about jab efficacy were completely and utterly unreliable? Had they known that being jabbed didn’t stop people getting C-19 or passing it on, then many people may well have decided to decline consent to be jabbed – at least to their second and third shots – and thereby avoid post-jab effects, serious medical problems or even death.
Was it not completely unethical for Dr Walensky to withhold this important information? Was she not expressly bound to inform the public that there are risks involved in accepting an untested synthetic compound – and that it did not work as intended anyway? Did she wilfully deprive them of information that would have facilitated ‘informed consent’?
Dr Walensky has also publicly discredited the Vaccine Adverse Event Reporting System (VAERS), which is co-administered by the FDA and the CDC. Does she not know that VAERS has revealed that the Covid jabs are the most damaging ever created? How can she pooh-pooh these VAERS figures when they are supported by WHO statistics: 2,457,386 reports of adverse reaction to C-19 jabs 2020-21, against 6,891 adverse reactions after smallpox jabs 1968-2021. Of course, smallpox is/was a much bigger threat than C-19.
How can Dr Walensky not know these numbers? Why has she not halted the jab roll-out? No matter how well she is supported by the American authorities and the MSM – who insist that criticism is ‘misinformation’ – this isn’t going to go away, especially if they insist that more jabs are needed every year or every six months.
People have stopped believing and are recovering belief in their own judgement, hopefully in sufficient numbers that dissuades them from jabbing their kids.
Surely Rochelle Walensky must resign. Given the damage that has been done to the physical, emotional and economic health of tens of millions, it’s not good enough to shrug one’s shoulders and say, ‘We weren’t sure’.
April 14, 2022 Posted by aletho | Science and Pseudo-Science, Timeless or most popular, War Crimes | CDC, COVID-19 Vaccine, Rochelle Walensky | Leave a comment
6 Double Standards Public Health Officials Used to Justify COVID Vaccines
Madhava Setty, M.D. | The Defender | April 13, 2022
We are not only in an epidemiological crisis, we also are in an epistemological crisis. How do we know what we know? What differentiates opinion from a justified belief?
For nearly two years, the public has been inundated by a sophisticated messaging campaign that urges us to “trust the science.”
But how can a non-scientist know what the science is really saying?
Legacy media sources offer us an easy solution: “Trust us.”
Legions of so-called “independent” fact-checking sites that serve to eliminate any wayward thinking keep those with a modicum of skepticism in line.
“Research” has been redefined to mean browsing Wikipedia citations.
Rather than being considered for their merit, dissenting opinions are more easily dismissed as misinformation by labeling their source as untrustworthy.
How do we know these sources are untrustworthy? They must be if they offer a dissenting opinion!
This form of circular reasoning is the central axiom of all dogmatic systems of thought. Breaking the spell of dogmatic thinking is not easy, but it is possible.
In this article I describe six examples of double standards medical authorities have used to create the illusion their COVID-19 narrative is logical and sensible.
This illusion has been used with devastating effect to raise vaccine compliance.
Rather than citing scientific publications or expert opinions that conflict with our medical authorities’ narrative — information that will be categorically dismissed because it appears on The Defender — I will instead demonstrate how, from the beginning, the official narrative has been inconsistent, hypocritical and/or contradictory.
1. COVID deaths are ‘presumed,’ but vaccine deaths must be ‘proven’
As of April 8, VAERS included 26,699 reports of deaths following COVID vaccines.
The Centers for Disease Control and Prevention (CDC) officially acknowledges only nine of these.
In order to establish causality, the CDC requires autopsies to rule out any possible etiology of death before the agency will place culpability on the vaccine.
But the CDC uses a very different standard when it comes to identifying people who died from COVID.
The 986,000 COVID deaths reported by the CDC here are, as footnote [1] indicates, “Deaths with confirmed or presumed [emphasis added] COVID-19.”
If a person dies with a positive PCR test or is presumed to have COVID, the CDC will count that as COVID-19 death.
Note that in the CDC’s definition, a COVID fatality does not mean the person died from the disease, only with the disease.
Why is an autopsy required to establish a COVID vaccine death but not to establish a COVID death?
Conversely, why is recent exposure to SARS-CoV-2 prior to a death sufficient to establish causality — but recent exposure to a vaccine considered coincidental?
2. CDC uses VAERS data to investigate myocarditis yet claims VAERS data on vaccine deaths is unreliable
On June 23, 2021, the CDC’s Advisory Committee on Immunization Practices met to assess the risk of peri/myocarditis following COVID vaccination, especially in young males.
This was the key slide in this presentation:
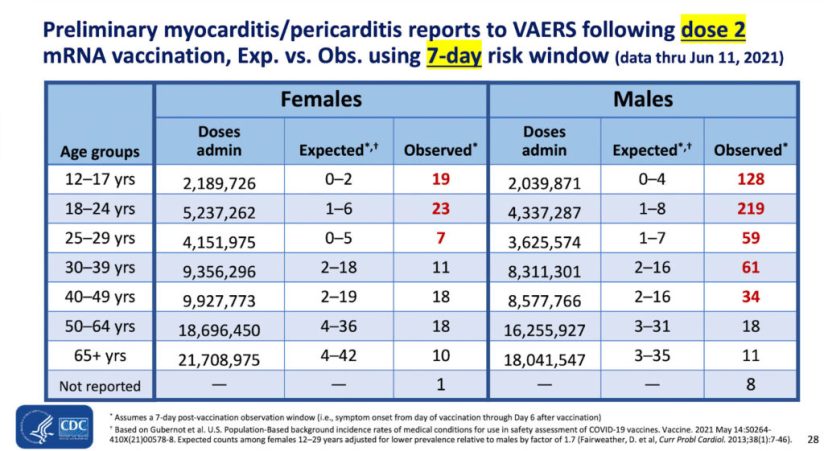
The observed risk of myocarditis is 219 in about 4.3 million second doses of COVID vaccine in males 18 to 24 years old.
The CDC is fine with using VAERS data to assess risk of myocarditis following vaccination — yet the agency rejects all but nine of the 26,699 reports of deaths following the vaccines.
Why does the CDC trust the peri/myocarditis data in VAERS but not the data on deaths?
One reason may be because the onset of myocarditis symptoms is closely tied to the time of vaccination.
In other words, because this condition closely follows inoculation the two events are highly correlated and suggestive of causation.
For example, here is another slide from the same presentation:
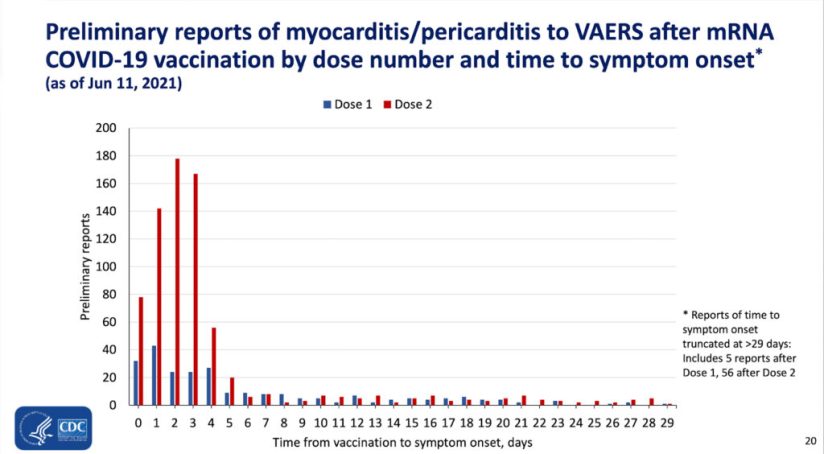
The majority of cases of vaccine-induced peri/myocarditis suffered symptoms within the first few days after injection. As explained above, this is highly suggestive of a causative effect of the vaccine.
A recent study in The Lancet included a similar graph, taken directly from VAERS, on deaths following vaccination:
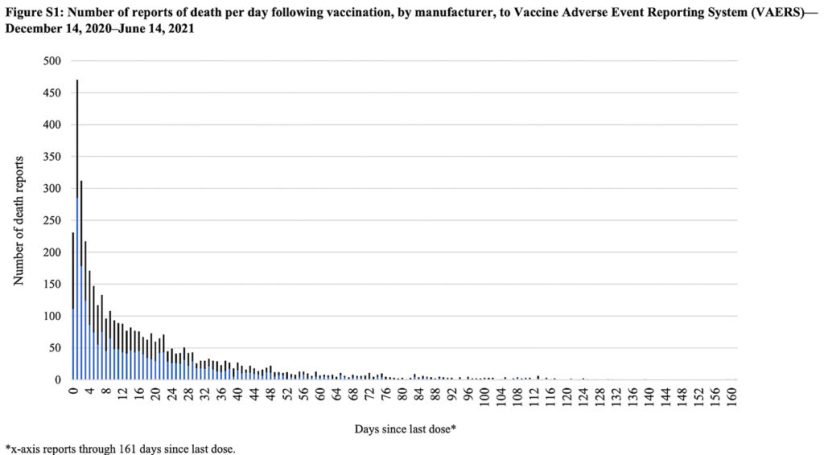
Once again, the event (death) closely follows vaccination in the majority of cases.
As we regard the two graphs above we should acknowledge that the temporal relationship between the injection and the adverse event is suggestive of causation but does not stand as proof of such.
However, it is also important to note that if the vaccination caused the deaths, that is exactly what the plot would look like.
It should be clear that the CDC has no justification for dismissing VAERS deaths if the agency is willing to accept reports of myo/pericarditis from the very same reporting system.
3. CDC pushes ‘relative risk’ for determining vaccine efficacy, but uses ‘absolute risk’ to downplay risk of adverse events
In Pfizer’s Phase 3 trial, nine times more placebo recipients developed severe COVID than those vaccinated during the short period of observation. This constitutes a relative risk reduction of 90%.
This seemed an encouraging finding and was used as a major talking point to compel the public to accept this experimental therapy despite the absence of any long-term data.
However, the risk of a trial participant contracting severe COVID (Table S5) was 1 in 21,314 (0.0047%) if they were vaccinated.
If they received the placebo, the risk was still only 9 in 21,259 (0.0423%).
The vaccine reduced the absolute risk of contracting severe disease by 0.038%.
Mainstream media and the CDC never mentioned the minuscule reduction in absolute risk of contracting severe COVID by getting inoculated.
Moreover, with 0.6% of vaccine recipients in the trial suffering a serious vaccine injury (one that results in death, medical or surgical intervention, hospitalization or an impending threat to life), approximately 16 serious adverse events will result for every serious case of COVID prevented by vaccination.
However, when it comes to risk of myo/pericarditis, the CDC states, “Myocarditis and pericarditis have rarely been reported, especially in adolescents and young adult males within several days after COVID-19 vaccination.”
The CDC further states, “While absolute risk remains small, the risk for myocarditis is higher for males ages 12 to 39 years…”
In other words, the risk of adverse events is being considered in absolute terms, not relative.
The CDC presentation slide above (Table 1) indicates the relative risk of contracting myo/pericarditis in males 18 to 24 is 27 to more than 200 times higher than expected in (unvaccinated) young men that age.
When assuaging the public’s fear around vaccine-induced myocarditis, the CDC finds it useful to cite absolute risk — yet when promoting the efficacy of the vaccine, the CDC emphasizes relative risks.
This double standard has been quietly and masterfully employed to reduce vaccine hesitancy and encourage compliance.
4. FDA requires randomized control studies for early treatment medications — but not for boosters
The CDC reports that as of April 8, 98.3 million Americans had received a COVID booster.
On March 29, the U.S. Food and Drug Administration (FDA) authorized a second booster for the immunocompromised and adults over age 50.
These authorizations were made not because of solid evidence the boosters are effective but rather to remedy the fact that the primary vaccine series has been widely shown to have waning efficacy within a few months.
As reported by The Defender, Dr. Peter Marks, director of the FDA’s vaccine division, Center for Biologics Evaluation and Research, admitted the fourth booster dose approved last week was a “stopgap measure” — in other words, a temporary measure to be implemented until a proper solution may be found in the future.
Despite the lack of solid evidence, the FDA continues to recommend and authorize boosters.
Yet when it comes to early treatment options, the agency holds medicines — including those the agency has already licensed and approved for other uses — to a different standard.
In this CNN interview from August 2021, Dr. Anthony Fauci, head of the National Institute of Allergy and Infectious Diseases, warns people not to take ivermectin for COVID because “there is no clinical evidence that this works.”
With regard to hydroxychloroquine, Fauci said, “We know that every single good study — and by good study, I mean randomized control study in which the data are firm and believable — has s shown that hydroxychloroquine is not effective in the treatment of Covid-19”, as reported by the BBC on July 29, 2020.
Where, then, are the randomized control studies in which the data are firm and believable that show boosters are effective at preventing COVID?
There aren’t any. None have been done.
As of today, the FDA still refuses to authorize the use of ivermectin and hydroxychloroquine to treat COVID despite hundreds of studies that demonstrate significant benefits (ivermectin, hydroxychloroquine) in prevention as well as early and late treatment.
The double standard here is blatant. There are no randomized control studies that show boosters are effective in preventing COVID.
Nevertheless, these experimental therapies have the FDA’s blessing while inexpensive, highly effective safe and proven medicines are ignored despite the enormous evidence that supports their use.
5. FDA uses immunobridging to justify Pfizer shots for young kids, but rejects antibodies as indicative of immune protection from COVID
Immunobridging is a method of inferring a vaccine’s effectiveness in preventing disease by assessing its ability to elicit an immune response through the measurement of biochemical markers, typically antibody levels.
The FDA asserts the presence of SARS-COV-2 antibodies is not necessarily indicative of immune protection from COVID.
Moreover, the FDA’s Vaccine and Related Biologics Product Advisory Committee reached a consensus last week that antibody levels cannot be used as a correlate for vaccine effectiveness.
Their decision is consistent with the CDC’s executive summary of a science brief released on October 29, 2021:
“Data are presently insufficient to determine an antibody titer threshold that indicates when an individual is protected from infection.”
Nevertheless, the FDA used immunobridging as a means to justify authorization of the Pfizer vaccine to children ages 5 to 11, as explained in The Defender here and here.
Because there were no deaths or serious cases of COVID in the pediatric trial, the FDA chose to reject its own position (and that of its advisory committee) regarding antibody titers as a correlate for vaccine efficacy.
6. Causation must be proven for vaccine injuries, but correlation suffices for proving vaccine efficacy
When it comes to vaccine injuries the public is often reminded that correlation does not equal causation.
In other words, just because an injury was preceded by inoculation doesn’t mean the vaccine caused the injury.
But what constitutes causation in medicine? A mechanism of action needs to be identified and pathological studies must confirm this mechanism while eliminating other potential causative factors. Causation can be proven only on a case-by-case basis.
Proving causation requires an enormous burden of proof in medicine.
For example, does smoking cause lung cancer? The answer is yes, it can. That doesn’t mean that it will.
However, when it comes to the benefit of medical intervention, such as a vaccine, causation does not have to be established. Correlation suffices.
In the COVID vaccine trials, fewer vaccinated people contracted COVID than unvaccinated ones. Yet there were those who received the vaccine who contracted the disease anyway.
To be fair, this is how all new medical interventions are evaluated. The benefit doesn’t have to be caused by the vaccine in the strictest sense, there just has to be a correlation between vaccination and a relative protective effect.
The more often this happens, the more confident we can be that the outcome wasn’t simply a coincidence.
Likewise, when it comes to assessing the harm of medical intervention, the most sensible outcome to consider is mortality. After all, what would be the point of introducing a vaccine that prevented some deaths while causing more?
Nevertheless, this is, in fact, what we have done with the Pfizer product. The interim results from the Phase 3 trial demonstrated that all-cause mortality in the vaccinated cohort was higher than in the placebo.
This glaring problem gets brushed aside because there were two deaths from COVID in the placebo arm versus just one in the vaccinated cohort, allowing the vaccine manufacturer to claim a 50% efficacy in preventing this outcome.
However, if we attribute a protective benefit to the vaccine in preventing this one fatality, we must also conclude that the vaccine was responsible for the extra death when considering mortality from all causes.
Doing otherwise would be applying yet another double standard.
How the pandemic could have played out differently
To summarize how devastating the use of these double standards in crafting the “safe and effective” narrative was, let’s look at how different the situation would be if we had adopted the opposite standard:
- There would have been an extremely low number of deaths from COVID. Very few, if any, autopsies have definitively confirmed that a fatality was caused by SARS-CoV-2. If confirmation by autopsy is the standard, there have been essentially zero deaths from COVID during the pandemic.
On the other hand, if we presume the deaths registered in VAERS are in fact vaccine-induced fatalities — similar to how the CDC presumed many deaths from COVID — we can affirm there have been more than 26,000 vaccine deaths. - Using absolute risk reduction as a measure of efficacy, vaccines would have been widely rejected as ineffective, providing only a 0.038% risk reduction for contracting severe COVID.
- Ivermectin and hydroxychloroquine would have been readily available for people who got COVID. And for those who got the vaccine but got COVID anyway, these medicines would have been a great alternative to boosters, which wouldn’t have been approved due to the lack of a single randomized control study proving they work.
- No children between the ages of 5 and 11 would have received this risky, experimental vaccine as it wouldn’t have been authorized for this age group — because Pfizer’s pediatric trials did not demonstrate any meaningful outcomes in children ages 5 to 11.
- The Pfizer vaccine would no longer be in use because interim data demonstrated that all-cause mortality is higher in the vaccinated.
Madhava Setty, M.D. is senior science editor for The Defender.
April 14, 2022 Posted by aletho | Deception, Science and Pseudo-Science, Timeless or most popular | CDC, Covid-19, COVID-19 Vaccine, FDA | Leave a comment
Real James Bond villains wear cardigans
Bill Gates, the WEF, and the WHO are not done with us. It’s time we were done with them.
el gato malo – bad cattitude – april 13, 2022
in history as in literature, a special place of contempt is held for the grand vizier, the guy behind the throne, the power behind the power. it’s a position of great influence but zero accountability, especially if you can subvert the ruler you puppet past the point of being able to scapegoat you.
buying or leading a politician and getting goodies is a process as old as politics, probably older as it was likely the reason the first politician was elected in the first place…
but the truly discerning james bond villain level vizier, well, they just go right ahead and buy their own NGO’s. that’s how you take over the world. space lasers and earthquake machines may be cool, but real conquest usually banal.
get to about the 1 minute mark in this video where you can hear bill speak about talking to donald trump in the white house.

trump asks about looking into some of the ill effects of vaccines.
gates tells him “that’s a dead end, that would be a bad thing, don’t do that.”
this is not a man giving well intentioned advice.
this is a man covering up a crime committed in the service of crony capitalism.
the gates foundation has a longstanding relationship with vaccines that is more than a little sketchy. they were pushing oral polio vaccines in africa LONG after they were known to be unsafe and had actually become the leading cause of polio in the world.
“The Gates Foundation is a leading funder of oral polio vaccination in Africa and around the world, having dedicated nearly $4 billion to such efforts by the end of 2018. As discussed in Forbes in May 2019, Gates has “personally [driven] the development” of new oral polio vaccines and plays a “strategic role beyond funding.”
the US uses ONLY injected IPV polio vaccines. both the US and the EU discontinued use of orals because of side effects including actually causing polio.
A year ago, news outlets briefly shone a light on the fact (a fact that makes public health officials squirm) that oral polio vaccines are causing polio outbreaks. With reports streaming in throughout 2019 regarding the circulation of vaccine-derived polioviruses in numerous African and Asian countries, a CDC virologist confessed, “We have now created more new emergences of the virus than we have stopped.”
… there were 400 recorded cases of vaccine-derived polio in more than 20 countries worldwide.
(author’s note: that’s ~3X the total of all natural polio cases worldwide and of those, only 29 occurred outside of pakistan and 100% of those were in afghanistan. this vaccines caused multiples more polio than the virus itself)
This week, the same story is making the same headlines, with the WHO’s shamefaced announcement that the oral polio vaccine is responsible for an alarming polio outbreak in Sudan—“linked to an ongoing vaccine-sparked epidemic in Chad”—with parallel outbreaks in a dozen other African countries. In fact, between August 2019 and August 2020, there were 400 recorded cases of vaccine-derived polio in more than 20 countries worldwide. Ironically, WHO disclosed this “setback” barely a week after it declared the African continent to be free of wild poliovirus—which has not been seen in Africa since 2016. While African epidemiologists cheerily claim that these outbreaks can “be brought under control with further immunization,” and Sudan prepares to launch a mass polio vaccination campaign, WHO is warning that “the risk of further spread of the vaccine-derived polio across central Africa and the Horn of Africa” is high.
but gates kept pushing them in africa anyway, probably because so many of his pals owned the production and that’s what the gates foundation does. that’s what all these guys do. big business and billionaires are not friends of free markets. they want sure things and it’s cheaper to twist and break arms and buy mandated markets than to compete on a fair playing field.
i have (on excellent, direct authority from a personal friend who i trust implicitly and who spoke directly to the folks involved) the following story about the gates foundation in india:
gates himself came in to speak with the health ministers. he offered them a vaccine for a disease they already had one for. they told him, “no thank you, we already have that one covered.” he told them “well, you need to switch to this vaccine or there will be no gates foundation investment for india.” the one he wanted them to switch to was owned by a “friend of his.” this story was relayed by extremely liberal folks who literally run vaccine programs in india. they heard this conversation directly and have no reason to lie. they were horrified. it was a pay to play stick up. (they still declined)
this is not the sort of conflict of interest that’s helpful in a guy telling the president not to look into vaccine issues. it also stands testament to his morality and inclination. bill gates is as amoral as he is rich. always has been. much of microsoft was stolen from his less machiavellian partners.
i’m presuming this interview above and the discussion with trump were pre-covid because it’s never mentioned and had this been post covid, i find it hard to believe that it would not have been, but it seems more apropos now that ever. obviously, the conflicts of interest certainly did not stop back then and vaccine ill effects are looking like quite the hot topic just now.
and gates is, as ever, right smack in the middle of the dirtiest, most profitable part of it.
it was september 2019. SARSCOV-2 was still not really on the radar. according to many, there was not even an outbreak yet.
that same month, billy made a large investment in a company called bioNtech to allegedly pursue HIV and tuberculosis vaccines. if memory serves, he bought about 1/3 of the company which was entirely preclinical in infectious diseases at the time. they were mostly a phase 1-2 oncology company. this looks like a sweetheart valuation.
obviously, this became a very big deal in a very big hurry. it was their mRNA payload that was licensed by pfizer for their vaccine, a product that went on to be the most profitable drug per unit time in human history. (and possibly the most profitable altogether) bioNtech minted money.
lots of things about this investment have long smelled fishier than a sushi bar dumpster.
but then a funny thing happened with a now vexingly familiar cast of characters.

(read more HERE)
even months later in january 2020, folks like osterholm were still buying the “no signs of human to human transmission” line.
yet somehow, 4 months earlier (and who knows when the due diligence started. might have been 6 or more), gates was putting his money right on the one obscure square that would pay out 100 to one. at a company with near zero footprint in infectious disease. for a virus no one was focused on. whose genetic code would not (allegedly) be initially characterized for 4 more months.
then, in the same odd, sudden miracle that got moderna the NIH science they licensed for their vaccine, bioNtech also had a product and pfizer jumped to license it.
alone, having a wargame for the war that had, unbeknownst to most, already started, might raise eyebrows, but it might also be a coincidence.
but when the folks coming to that wargame have been making big bets on the kinds of weapons that that precise (and only that precise) sort of war would use, well, one might start to sharpen the points on one’s pointy questions.
just what was informing what here?
this idea that “mRNA is magic and you can develop a vaccine in weeks” is complete nonsense. it’s never been true and the rest of the mRNA vaccine timelines stand testament to it. no other vaxx has been forthcoming.
this HAD to have been in the works for a significant period beforehand.
the fix appears to have been deeply in here. somebody was getting some VERY early looks at some tech to vaccinate against a virus no one else even had a copy of. the awareness not just of the pathogen, but the way to code for its spike protein and the impending pandemic seems to have been loose in certain circles long before the rest of us were told.
the NIH seeded moderna. i still do not have confirmation on where bioNtech got theirs, but i have a hunch and it rhymes with “silly plates” and that this might explain the sweetheart deal.
there is really only one story that makes sense to me here on covid origins, and that story is this:
NIH funded eco health alliance run by daszak and in cahoots with folks like baric colored outside the lines with fauci’s grant money. they, in collaboration with the wuhan institute of virology hotwired the hell out of covid viruses from bats engaging in gain of function work WAY outside of safe limits. this was not a weapon. it was work on inoculation. that was daszak’s longstanding focus. we’ll probably never know what happened in wuhan, but the breadcrumbs here are AWFULLY provocative and the sudden appearance of 2 mRNA vaccines, one with the NIH folks that funded EHA at the WIV, one with bioNtech, looks like an offshoot of it. (lots of detail HERE and HERE on the breadcrumbs)
wrapped up in this from the very beginning were load of the WEF gang (who had just run an oddly timely pandemic wargame for a disease an awful lot like covid) and the WHO.
billy gates is neck deep in both, a charter member of the cool kids crony capitalist table at davos and a top funding source for the WHO, donating more than 10% of its budget. it’s clearly a great investment for him as it poops golden eggs in terms of early information and hard sell opportunities for poor countries. it’s a seat at every table that makes you look like a philanthropist while in reality being a lead pipe wielding coercive corporatist.
gates is not a good guy.
he’s a sociopathic nerd with the most unsavory of associates.
and he knows how to play the crony capitalist game with the absolute best of them. the gates foundation has become a barely veiled international influence organization masquerading as a charity.
between gates and china, the WHO will dance to whatever song the two play. and oh, how they will dance.
remember this gem? (i do)

this was a big part of what got the out of control abandonment of 100 years of science based pandemic guidelines rolling.
“hey, let’s throw all the science, data, and history out the window and copy a terrifying authoritarian regime with a human rights record that would make myanmar blush!”
yeah, well, we all remember how THAT worked out…
but this is government. it’s worse than government, it’s trans-national organizational government. these are the people who invented “failing up” where the bigger your screw ups, the higher you get promoted. (if you doubt me, look at who runs the IMF and the world bank some time…)
and so, despite having cheer led for nothing uty pseudoscience, failure, and human ruin, the current plan being put forward is, wait for it, “hey, let’s give the WHO massive, unaccountable globalist powers!”
of course, this was clearly the plan all along if you were paying attention.

note the direct parrot of the WEF “build back better” taking point.
this gang sees every crisis as a chance to try to grab control of the world. and they are at it again.
In a consensus decision aimed at protecting the world from future infectious diseases crises, the World Health Assembly today agreed to kickstart a global process to draft and negotiate a convention, agreement or other international instrument under the Constitution of the World Health Organization to strengthen pandemic prevention, preparedness and response.
Dr Tedros Adhanom Ghebreyesus, WHO Director-General, said the decision by the World Health Assembly was historic in nature, vital in its mission, and represented a once-in-a-generation opportunity to strengthen the global health architecture to protect and promote the well-being of all people.
“The COVID-19 pandemic has shone a light on the many flaws in the global system to protect people from pandemics: the most vulnerable people going without vaccines; health workers without needed equipment to perform their life-saving work; and ‘me-first’ approaches that stymie the global solidarity needed to deal with a global threat,” Dr Tedros said.
they will also force licensing, break patents, and drive health policy at the highest levels.
but here’s the full blown worst of it:

The World Health Organization (WHO) has contracted German-based Deutsche Telekom subsidiary T-Systems to develop a global vaccine passport system, with plans to link every person on the planet to a QR code digital ID.
Indeed, despite the minuscule threat posed by new variants and dubious-at-best vaccine efficacy, the WHO is adamant that a global QR code-based vaccine passport system is vital for all future health emergencies, not just COVID.
“COVID-19 affects everyone. Countries will therefore only emerge from the pandemic together. Vaccination certificates that are tamper-proof and digitally verifiable build trust. WHO is therefore supporting member states in building national and regional trust networks and verification technology,” says unit head of the WHO’s Department of Digital Health and Innovation Garrett Mehl.
“The WHO’s gateway service also serves as a bridge between regional systems. It can also be used as part of future vaccination campaigns and home-based records.”
got that? this one is going to be digitally verifiable and global. nowhere to run, nowhere to hide, universal, mandatory, trans-national, and administered by an agency completely unaccountable to you and beholden to proven kleptocrats, authoritarians, and crony corporatists. they are basically a subsidiary of china and gates inc.
they will not get any better or more honest next time.
we’re talking about taking one of the most corrupt, captured, and incompetent agencies in the history of bureaucratic bloviation and giving them the keys to the world crisis machine and to an electronic health passport that will be your right to travel and work and eat out and shop and who knows what else. this is the cornerstone of an international social credit system. wait until they add your ESG score and your carbon footprint.
giving this team universal chicken little rights and direct links at highest levels to public policy is bad enough. letting them enable fine grained access into permission to have anything resembling a life will have you eating bugs and tweeting what you’re told faster than you can say #grasshoppers #yummy!
they promised you that in the future you’d have no privacy and own nothing and that you’d been happy.
guess which two promises they’re going to keep?
and government will fall all over themselves to help and to outsource the imposition of the infinite personal tracking and permissioning they have so long salivated over under the pretext of pandemic preparedness. (oops, look, another trojan framing of subjugating masquerading as safety. told you these were EVERYWHERE…)
this is not going to be acceptable or even tolerable.
this group should be disbanded, not granted greater remit.
and they are not done, because the power behind these thrones is ever hungry.
you might be thinking “wow, that was awful” but they are all thinking “wow, that was surprisingly easy. i wonder what we could do if we had some time to get set up beforehand and really run the table?”
these are not good people.
they do not have noble aims nor your best interests at heart.
they are a global aristocracy of surpassing ruthlessness telling scare stories so they can mandate alleged solutions.
they tell you it’s about saving you.
it isn’t.
read the fine print.
follow the money.

the super rich do not like to guess. they do not like to be surprised by trends. it is far more certain and therefore more profitable to force you to buy that which they are selling. the public health grift and the climate grift are all one grift: use government and trans-government to frighten and force people into buying the needless products that you’re going to produce for them.
small investors talk their book. titanic investors force you to buy it.
- if it’s a vaccine, mandate it and bar all useful therapeutics from market.
- if it’s a windmill, kill nuclear and inflict absurdist carbon taxes.
- never let any of it be properly assessed.
- use fear to drive compliance and compliance to drive mandate.
they will sell you your own collar and leash and demand your gratitude for having done so.
and if you don’t wake up pretty soon, they’re going to get it from you. by force. and you will be powerless to stop it.
the confluence of a global health passport and central bank digital currencies is an extinction level event for personal liberty and privacy.
and make no mistake: gates wants it. the WEF wants it. and most western governments want it.
but they also know that you do not want it. so they need a pretext and a plan and a pile of boring, technocratic yammering to hide it behind. they learned from last time. they saw the cracks we squirmed through and how we got away. and they do not plan to let it happen again. the next one will be air tight. they’ll have the WHO ready to both be able to declare a global emergency and impose ready made verified global digital ID using that fear as a pretext.
if you let them get these pieces into place, you are NOT going to like the endgame.
this has reached the email length limit. check the substack page for an addendum.
April 13, 2022 Posted by aletho | Corruption, Deception, Science and Pseudo-Science, Timeless or most popular, War Crimes | Covid-19, COVID-19 Vaccine, NIH, WEF, WHO | Leave a comment
Jive Talking Journals: Why the conclusions sometimes don’t match the data in scientific papers

By a Biomedical Scientist | The Exposé | April 13, 2022
Biomedical research papers are being published in which the abstract, the discussion section, and even the title contradict the content within the paper.
This is unlikely to be happening because the authors don’t understand their own data. It’s more likely that the authors are being pressured by their financial backers and the editorial staff of journals to reach conclusions that advance the prevailing narrative.
It’s a well thought out deception that uses seemingly intellectual analysis to lead the undiscerning reader into believing the wrong conclusion. Skewing statistics is easy to accomplish simply by using the wrong statistical test, using a weak test when a stronger one should apply or just about any other trick to misrepresent the data.
Medical journals have become financially dependent on their advertisers, which are almost exclusively the big pharmaceutical companies. With enough money, they can buy a scientific study that says what they want it to say.
Sometimes these studies are “ghost” written by people working for industry with credentialed unscrupulous scientists and doctors names misattributed as authors when in fact they did none of the writing.
The pharmaceutical industry uses its profits to control biomedical science at every level, from researchers to journal editors, to government regulatory agencies, and to the media who are supposed to interpret science for the public.
Pressure is being placed on independent researchers by the journal editors and peer reviewers, many of whom have ties to Big Pharma. Valid studies, honestly reported, can be rejected for publication if they convey a message that threatens corporate profits. Many scientific authors know how difficult it is to get a paper through peer review at most “reputable” medical journals when the results are not in line with the official narrative.
Many biomedical scientists have become shills for the pharmaceutical companies. Rigging clinical trials the old-fashioned way is expensive, time-consuming, uncertain, and recent legislation makes it more difficult. Sometimes the truth emerges even if a study is designed to hide it. Even a study that is designed to fail might succeed when the inconvenient truths are stubborn enough.
It’s easier to report the actual results and then tack on an abstract and a discussion section that convey the right message, regardless of the data in the main body of the article. This can then be used in the “citation bluff” fraud, that depends on people not carefully reading supposed supportive evidence, to perpetuate the false narrative.
Often the cited evidence in support of a particular narrative doesn’t really support the narrative being advanced. In fact, the supposed supportive evidence can sometimes even completely contradict the narrative being pushed.
This is something to bear in mind the next time you get into an argument with someone demanding to see peer-reviewed evidence and rejecting any evidence that has not been peer-reviewed regardless of its merits.
Journals and the peer review process have been corrupted by powerful vested interests.
April 13, 2022 Posted by aletho | Corruption, Deception, Science and Pseudo-Science, Timeless or most popular | Leave a comment
Testing Mania: Illogical and Harmful
BROWNSTONE INSTITUTE | APRIL 12, 2022
This adapted excerpt is from Dr. Scott W. Atlas’ bestselling book, A Plague Upon Our House, published by Bombardier.
By the time I arrived at the end of July 2020, the administration had already developed a massive testing capacity from scratch. Nearly a million tests per day were being conducted. The effort was led by Admiral Giroir, who was assigned the thankless task of overseeing that project.
I understood why the VP was so excited when he had displayed that simplistic chart on my first visit. And over the next weeks the administration continued to successfully facilitate and distribute tens of millions of point-of-care PCR tests and, later, rapid antigen tests. This was a significant accomplishment, but it was clear from the beginning that the White House did not understand how or when to use testing. To my thinking, it was a response to political pressure more than anything else.
From my very first meeting in the Oval Office back in July and again over subsequent meetings, President Trump expressed great frustration about testing. It was easy to see why. You could not turn on the news, even the most superficial talk show, without the lead story admonishing the administration for “the lack of testing.” For months, the country had been inundated with that message—not just from public health types who had now become household names, but from every pundit, talk show host, and news anchor. It became pure groupthink. Celebrities who had no understanding or expertise at all were now stridently opining about the unquestionable urgency of massive, widespread, on-demand testing.
Reminiscent of stock market frenzies, esoteric technical terms that had formerly been unknown to the public like “contact tracing” now became common parlance. Testing for this virus had turned into a national, indeed, international obsession. And to me, that obsession was not just misguided, it was harmful, creating more fear, more frenzy, more irrational policies. Yes, testing was an essential tool in the pandemic. And yes, months before I was involved in any way in Washington, there had been a failure to develop and deliver enough tests when they were needed the most. But by the time I came to DC at the end of July, a massive capacity to test had been quickly developed. The problem now was that it was not being leveraged to save lives. Schools and businesses were closed; people were cowering in their homes. Meanwhile, older people kept dying by the thousands.
Criticizing the administration about testing was more than a natural extension of that obsessive mindset. It was low-hanging fruit for the president’s political opponents. There had been almost no preexisting testing capacity from the outset, so naturally it would take some time to meet the challenge. The obsessive demand for testing rapidly escalated into a hyperpartisan issue. I remembered Pelosi’s mantra—“test, test, test; trace, trace, trace!”—as if she, or any politician for that matter, had any understanding of the appropriate testing policy. She was not alone, though. That mantra was echoed on every news network, regardless of political leaning. No dissenting opinion was even visible to most Americans.
That political heat provoked the expected reaction in the White House. Long before my arrival, testing became Priority Number One. Beyond an important public health policy question, it was an election season, and a contentious one at that. This environment elevated testing into the priority of the president’s closest counselors, his political advisors at the highest levels, and operationally, therefore, the vice president’s Task Force. Presumably, like all politicians, the president was politically motivated, too.
The conflict, the misjudgment about issues like testing and other advice coming out of the Task Force, occurred when the president was swayed too much by his political advisors instead of believing in his own common sense. That advice matched the message of the Task Force, especially that coming from Redfield and Birx, whose decision-making background was tied almost exclusively to testing. That was one of the many problems stemming from the HIV backgrounds of Birx and Redfield. SARS2 had already spread to millions, and it spread by breathing in close proximity; the role and practical application of testing in a virus like HIV couldn’t have been more different. In the end, it was easy to see how the advice to the president was to focus on testing.
Understandable for everyone, that is, except the president. He never agreed, because to him it made no sense. He couldn’t understand why we would test people who were not sick. It was as simple as that. President Trump talked to me privately in the Oval Office about many different things, but almost always, our discussions came back to the subject of testing. The president spoke very bluntly and resorted to common sense rather than any data. He knew nothing specific about the medical rationale for testing. He went with his gut feeling and placed no filter on stating his opinions.
“Why are we testing healthy, younger people? Why don’t we just test sick people?” he would ask.
“And if we test more, we find more cases. But those people aren’t sick!” he would point out, exasperated, echoing what he said many times to the press.
And that seemed rather straightforward, on its face. His point was simple logic—test and you shall discover “cases,” especially with COVID, since a large number, maybe half or more, of infections were asymptomatic. He was also correct that in clinical medicine, the definition of a “case”—a patient—is not generally based on a test seeking out something in a healthy, asymptomatic person.
That is not how medicine is practiced, a point I tried to explain time and again to the Task Force troika of doctors. I had that perspective, because I am a doctor who has been an expert for decades on the significance of diagnostic tests showing abnormalities without symptoms. And wasn’t it also important to consider that the overwhelming majority of people did not have a serious illness, even when symptomatic? As for mildly ill patients with COVID, “standard of care” for them was strict isolation, with or without testing.
Testing, though, was the way—the only way—to find infected people who had no symptoms. In high-risk settings, contagious people with asymptomatic infections would be critical to find, no doubt. But the goal, the rationale for testing, became a key point of confusion and disagreement. We needed to protect high-risk people, absolutely. The question was how. We knew who was at risk, so there were two alternatives: 1) indirectly protecting the “vulnerable” by confining and locking down everyone else, or 2) doing everything to protect high-risk people directly.
By the time I set foot in the White House, the nation, with few exceptions, had already been using the Birx-Fauci lockdown restrictions—the indirect strategy—for months. Why was there no admission that the lockdown strategy did not work? It undeniably failed to protect the elderly. Nursing home deaths were piling up, comprising up to 80 percent of total deaths in some states—and in the meantime the lockdown policy was destroying everyone and everything else. Einstein may or may not have said it, but everyone knew it: “The definition of insanity is doing the same thing over and over and expecting different results.”
Yet the strategy was to continue doubling down on the failed lockdowns that were devastating to so many, especially those outside the “elite.” Reality was being denied, and that remains the case today. Regardless, the answer to the failure, the available tool for those all-in on stopping all cases, was more testing!
Unbeknownst to the White House, several top epidemiologists and infectious disease experts had opined that massive testing of healthy people in settings that were not high-risk was not appropriate at this stage of a pandemic. That was apparent to me from months of lengthy discussions with leading epidemiologists at Stanford and elsewhere. There were already tens of millions of Americans who had been infected; even the CDC estimated a tenfold larger number compared to the confirmed number, as verified by early studies on SARS2 antibodies.
Contact tracing was also “futile” at this point, as Dr. Bhattacharya later wrote in a paper I distributed at a Task Force meeting. Contact tracing was a tool for newly emerging pandemics, new outbreaks perhaps. Oxford’s Sunetra Gupta, a world-renowned epidemiologist, repeatedly stressed the lack of logic in mass testing at this stage and the irrationality of focusing on cases by positive tests. Moreover, PCR tests were detecting virus fragments or dead virus in people who were not even contagious. Yet no one in the Task Force would even entertain this discussion.
The question about the role of testing was fundamental. It wasn’t simply surveillance for the purpose of knowledge—testing was the key to a strategic policy. It was not enough to consider testing through the limited prism of an epidemiologist, the way Birx and Fauci did (even though they, like me, are not epidemiologists). In medical practice, if you referred a patient with low back pain to a neurosurgeon, the most likely outcome was surgery. That’s exactly why I always referred patients to neurologists first—they had more perspective. Some might think of the adage “to someone with a hammer, everything looks like a nail.” Testing was the main tool in the epidemiology toolbox, their only tool, really. That was very limiting in defining its role in overall policymaking.
At this juncture, the testing was not being done to yield statistically valid surveillance information—a legitimate use of testing in the midst of a pandemic. This was diagnostic testing, with broad-reaching policy aims. In this pandemic, a positive test was a major driver of the policy of quarantining and isolating healthy people with low-risk profiles—shuttering businesses, closing schools— in short, a key to locking down the country. That’s why health policy experts like myself with a broader scope of expertise than that of epidemiologists and basic scientists are needed. Because no one with a medical science background who also considered the impacts of the policies was advising the White House. That lack of perspective was the main source of the tunnel-vision focus on preventing the spread of infections to the exclusion of all other considerations.
It was baffling to me, an incomprehensible error of whoever assembled the Task Force, that there were zero public health policy experts and no experts with medical knowledge who also analyzed economic, social, and other broad public health impacts other than the infection itself. Shockingly, the broad public health perspective was never part of the discussion among the Task Force health advisors other than when I brought it up. Even more bizarre was that no one seemed to notice.
The president clearly understood that testing healthy people for a disease that did not make them sick made little sense and would only lead to confining them. I agreed with that common sense view, although with important exceptions, and sitting in the Oval Office I explained the absurd extension of the logic of “test, test, test.” What was the “necessary” number, anyway? One million per day? Not even close. One hundred million per day? Nope. How about everyone in the country—330 million per day, every day.
Even if you could accomplish that goal, the tests themselves were only a snapshot in time. Seconds later, any given person could become infected. So 330 million per day, every fifteen minutes—maybe that would satisfy the testing mania! No matter how many tests were performed, there would never be enough.
The need for increased testing, but in a smarter, more targeted way, still needed to be explained to the president. And I did just that, repeatedly, whenever I had a chance—in concise, short doses. As always, he listened intently. But he had no time or patience for a detailed presentation. That is one reason why we got along well. I was capable of speaking succinctly, articulating the bottom line. More importantly, he knew I spoke directly, no BS.
From day one, I always reminded myself—if, and whenever, the president of the United States asks for my opinion, I am going to give it.
No holds barred—otherwise, what was I there for? Even on my very first visit to the Oval Office, when he complained about wide-spread testing, I bluntly told him, “You are a hamster on a wheel,” knowing that others in the room would probably recoil at hearing that. But President Trump knew it, even repeating the phrase later himself.
There was, I explained, a more nuanced approach to the policy of testing. There were serious reasons to test, important reasons to actually increase testing, but in a strategic way. The question was how to leverage that testing capability to have the most impact—to save the most lives and to facilitate reopening the country, which was the right goal from both a health perspective and the president’s stated policy.
I thought my approach was obvious. This was simple logic, and it reiterated exactly what I had written months before: let’s focus testing on where it really mattered, and increase it. High-risk environments, where high-risk people lived and worked. Nursing homes, a tinderbox of risk for its elderly, frail residents, were an obvious target. Knowing that cases were brought in by the staff, they needed to be tested, and tested far more frequently, perhaps every day. I also pushed for more point-of-care tests in places independent-living seniors frequented, like senior centers; visiting nurses taking care of seniors at home; and historically Black colleges and universities (HBCUs), where high-risk faculty members were more concentrated.
While the president understood and fully supported this, he remained frustrated, as did I, because his most trusted advisors didn’t fully sign on to a strategic approach to testing. At one point he offhandedly remarked, “You’ll have to convince my son-in-law of that.” Naturally, Kushner and everyone else had been deferring to Fauci and Birx on all things medical. To make matters worse, the Fauci-Birx testing strategy was not merely unfocused; their strategy bizarrely prioritized more testing in the lowest-risk people and the lowest-risk environments—students and schools—while letting the deaths continue in nursing homes and assisted living facilities, where a once-per-week schedule was assumed to be effective.
Politics seemed to be the main driver of those in the inner circle advising the president—that was their job. But the politics were irrelevant to me. The frenzy about testing everyone, everywhere, at all times, including low-risk people in low-risk settings, was incorrect, illogical, and harmful.
The funny thing was that while almost everyone assumed the president was only making excuses, somehow covering up for an “inadequate” testing capacity, there were valid reasons to use testing very differently in order to maximize its benefits. Despite the clamor of the “experts” in the public sphere, and almost the entire media narrative pushing the opposite view, the president happened to be correct. Instead of massively testing everyone on demand, testing should be leveraged to do what everything should have been geared toward in the first place—protecting the high-risk, saving lives, and opening society up as soon as possible.
What was most remarkable to me from the inside was that even though the president expressed his points about testing very clearly, and many top epidemiology experts agreed, the COVID Huddles and other strategic operations were run in a different world. The messaging, the public events, the operational strategy, and the communications team pushed ahead with a focus on producing and delivering more testing to low-risk environments, schools, and communities. Reminiscent of Catch-22, when 150 million antigen tests became available weeks later, I was asked by several people in the COVID Huddle, “Well, now that we have these tests, what do we do with them?”
Scott W. Atlas, M.D., is the Robert Wesson Senior Fellow in health care policy at the Hoover Institution of Stanford University and a fellow at Hillsdale College’s Academy for Science and Freedom.
April 13, 2022 Posted by aletho | Book Review, Science and Pseudo-Science, Timeless or most popular | Covid-19, United States | Leave a comment
Vaccine is linked to long-term child heart problems, but still the jabbing goes on
By Guy Hatchard | TCW Defending Freedom | April 12, 2022
AN American follow-up study of children suffering the heart muscle inflammation myocarditis after having their second dose of the Pfizer mRNA vaccine was published in the Journal of Pediatrics on March 25 this year.
The research at the Seattle Children’s Hospital looked at 16 males, with an average age of 15, three to eight months after their initial diagnosis with myocarditis a short time after vaccination.
The authors used electrocardiograms (ECG) and cardiac magnetic resonance (CMR) scans to examine abnormalities in the heart such as myocardial scarring, fibrosis, strain, and reduced ventricular muscle extension, which can be associated with reduced capacity to pump blood and increased risk of heart attack.
They found that although there was some measure of resolution after three to eight months, most subjects still had some persistent abnormalities.
‘Although (initial) symptoms (such as chest pain, and exercise intolerance) were transient and most patients appeared to respond to treatment (solely with NSAIDS – non-steroidal anti-inflammatory drugs – such as ibuprofen), we demonstrated persistence of abnormal findings on CMR at (three to eight months) follow-up in most patients, albeit with improvement in extent of LGE.’
LGE is late gadolinium enhancement, a measure of the heart’s capacity to pump efficiently.
The authors warned: ‘The presence of LGE is an indicator of cardiac injury and fibrosis and has been strongly associated with worse prognosis in patients with classical acute myocarditis.
‘A meta-analysis including eight studies found that presence of LGE is a predictor of all-cause death, cardiovascular death, cardiac transplant, rehospitalisation, recurrent acute myocarditis and requirement for mechanical circulatory support.’
For those who wish to review a detailed evaluation of this study by a medical expert, you can watch this video.
Here in New Zealand, the latest Medsafe Adverse Effects Report #41 lists 12,000 people who have experienced chest discomfort and 6,000 shortness of breath (all ages) following mRNA vaccination – both classic symptoms of myocarditis.
The authors of the Seattle study concluded: ‘In the cohort of adolescents with Covid-19 mRNA vaccine-related myopericarditis (a complication of acute pericarditis), a large portion have persistent LGE abnormalities, raising concerns for potential longer-term effects.’
It is clear that little has been done in New Zealand to follow up those stricken by adverse effects. Many reporting to emergency departments or GPs with chest pain, tachycardia (rapid heartbeat), or shortness of breath have been told that everything will be OK without clinical assessment. In many cases these symptoms were not even registered with CARM, the national database of adverse reactions to medicines and vaccines.
Even though the Seattle study had few participants, it red-flags the possibility of subsequent cardiac events. It raises the possibility that sub-clinical adverse effects of mRNA vaccination may have serious longer-term impacts on health.
Until now, these have been classified as non-serious in New Zealand. Persistent reports of cardiac events in the weeks and months following mRNA vaccination among ostensibly fit and healthy people of all age groups and genders, but especially men, can no longer be ignored or dismissed as unrelated. They need to be investigated.
This underlines the fact that the Pfizer mRNA vaccination roll-out has been undertaken in the absence of long-term follow-up testing, which often requires the use of sophisticated equipment such as CMR and MRI (magnetic resonance imaging) scans.
Moreover, heart disease is not the only category of serious illness whose incidence may be increased by mRNA vaccination, as other recent studies suggest.
Possible long-term adverse effects include cancer, kidney and liver disease, and neurological conditions. A recent court-ordered document release shows Pfizer, and probably the New Zealand government, is aware of cases.
But our government is still persisting with advertising suggesting that mRNA vaccination is safe and effective. This is not supported by research – the jab comes with some serious risks.
Moreover, the government was well aware of the risks from the start. An internal document released under the Official Information Act dated February 10, 2021 and signed by Ashley Bloomfield, Director-General of Health and Chris Hipkins, Covid Response Minister, discussing provisions for the vaccination of border workers, says: ‘Current data suggests severe adverse reactions are less than 1.1 per cent.’
Following ten million injections, as we have had in New Zealand, that would amount to more than 100,000 adverse reactions (a figure not inconsistent with the grossly under-reported 55,000 adverse reactions registered with CARM).
Did either Ashley Bloomfield, Prime Minister Jacinda Ardern, or Chris Hipkins ever hint to the public or the media that this was the expected outcome?
No they did not. They told the public the vaccine was completely safe and effective. They hid facts. More than this, Ardern deleted the 33,000 reports of adverse effects that were posted on her Facebook page. She gaslighted the public.
In the light of the Seattle study and other recent findings of potential long-term health issues associated with mRNA vaccination, we will now look at the very recent official advice given to New Zealand’s Prime Minister and Cabinet.
A letter dated March 13, 2022 has been sent by the Strategic Covid-19 Public Health Advisory Group (the David Skegg committee) to Dr Ayesha Verrall, Associate Minister of Public Health.
It is entitled Vaccine Mandates and aims to review the government’s strategy for minimising harms to health, society and the economy caused by the Covid-19 pandemic. The committee assured the minister: ‘We have been able to take a completely fresh look at the evidence.’
The signatories to the letter are Dr David Skegg, an epidemiologist; Dr Maia Brewerton, a clinical immunologist, allergist and immunopathologist; Professor Philip Hill, an epidemiologist and public health expert; Dr Ella Iosua, a biostatistician; Professor David Murdoch, a clinical microbiologist and Dr Nikki Turner, an immunologist interested in preventive child health. All are vaccine advocates.
Point 29 of the letter calls for more measures to encourage children to be vaccinated. Point 12 asserts: ‘As we now deal with a large Omicron outbreak, vaccination is undoubtedly reducing the numbers of people who are becoming seriously ill and require hospital treatment.’
However, current New Zealand data discussed in articles at the Hatchard Report reveal that the rates of hospitalisation are equivalent for vaxxed and unvaxxed.
Not a single scientific reference is included in this letter. Not a single reference is made to adverse effects of vaccination (currently running at 30 to 50 times higher than that of any previous vaccine).
Not a single reference is made to any need for informed consent prior to vaccination. The theme running throughout the letter is a need to normalise the use of vaccination mandates when they are needed in New Zealand in future.
The right of employers to enforce vaccine mandates is described as ‘common’. High vaccination rates are said to reduce absenteeism and the collapse of public services and commercial businesses.
The letter admits that the protection provided by the Covid-19 vaccines wanes after a few months and says the term ‘booster’ should be avoided. It recommends the needed number of mRNA vaccinations should be described as a course, and raises the imminent desirability of a fourth vaccine dose for at least some people.
Point 28 says: ‘For some cases, it would be appropriate for vaccination to be a condition for new employment.’ This clause recommends the broad use and normalisation of vaccine requirements in New Zealand for many illnesses and in many service sectors.
Unaccountably, the letter says: ‘Encouraging vaccination in the general population was not one of the specific objectives of vaccine mandates.’
It also says that vaccine hesitancy has been much less in New Zealand than other countries and that people ‘have been prepared to accept redeployment and redundancy’. In essence, denying the obvious coercion involved in mandates.
The letter recommends that mandates continue in use for health care workers, aged and disabled caregivers, corrections workers and border staff. There will be a review in six months.
The overall content of the letter appears to suggest that vaccines have been the key element ensuring low Covid-19 incidence. It completely fails to discuss the obvious point that this success has been achieved through border controls and contact tracing, not mRNA vaccination.
The long-term health effects of mRNA vaccination are becoming more obvious through published research findings. Meanwhile, the government advisers have their heads in the sand. Their careers have been built upon vaccination and now it seems that, to save the government, they are prepared to ignore the obvious deficiencies of mRNA vaccination.
One Chicago professor commented this week: ‘New Zealand science is circling the drain.’
April 12, 2022 Posted by aletho | Civil Liberties, Corruption, Deception, Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine, Human rights, New Zealand | Leave a comment
Featured Video
Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
or go to
Aletho News Archives – Video-Images
New Book
Trans agenda is ‘normalization of sadism’ – US author

RT | September 23, 2026
The US Democratic Party has embraced a transgender agenda that amounts to “the normalization of sadism,” author A.J. Rice has said, warning that radical trans policies would return if the party is allowed to regain power.
Speaking to RT’s America First host Scotty Nell Hughes about his new book, ‘The Curse of the Bearded Lady: How the Trans Mafia Whacked American Sanity’, Rice argued that activists have gained significant influence in schools, medicine, and corporate America while people who questioned the agenda have faced pressure to stay silent.
The author described the “trans mafia” as the sprawling network of people and institutions that have helped the movement gain influence. He singled out parts of academia, wealthy backers, and corporations, and stated that providers of transition-related treatment also have a financial incentive to keep young people in their care indefinitely.
Rice argued that the consequences of these policies ultimately fall on children who are being drawn toward gender-affirming medical treatments and on girls who are expected to share locker rooms or compete in sports with biological males.
He noted that while voters rejected the Democrats’ approach to gender in 2024, the party, which has been “captured by madness,” has since only doubled down and is seeking what is effectively “the normalization of sadism.” … Full report
Blog Roll
-
Join 2,352 other subscribers
Visits Since December 2009
- 7,725,555 hits
Looking for something?
Archives
Calendar
Categories
Aletho News Civil Liberties Corruption Deception Economics Environmentalism Ethnic Cleansing, Racism, Zionism Fake News False Flag Terrorism Full Spectrum Dominance Illegal Occupation Mainstream Media, Warmongering Malthusian Ideology, Phony Scarcity Militarism Progressive Hypocrite Russophobia Science and Pseudo-Science Solidarity and Activism Subjugation - Torture Supremacism, Social Darwinism Timeless or most popular Video War Crimes Wars for IsraelTags
Afghanistan Africa AIPAC al-Qaeda Australia BBC Benjamin Netanyahu Brazil Canada CDC Central Intelligence Agency China CIA CNN Covid-19 COVID-19 Vaccine Donald Trump Egypt European Union Facebook FBI FDA France Gaza Germany Google Hamas Hebron Hezbollah Hillary Clinton Human rights Hungary India Iran Iraq ISIS Israel Israeli settlement Japan Jerusalem Joe Biden Korea Latin America Lebanon Libya Middle East National Security Agency NATO New York Times North Korea NSA Obama Pakistan Palestine Poland Qatar Russia Sanctions against Iran Saudi Arabia Syria The Guardian Turkiye Twitter UAE UK Ukraine United Nations United States USA Venezuela Washington Post West Bank WHO Yemen Zionism
Aletho News- ‘We don’t seek permission to defend our country’: Snippets from President Pezeshkian’s UNGA address
- NATO chief wants Europeans to fight American wars [for Israel]
- German chemicals giant reveals details of downsizing
- Refaat Al-Areer Was The Canary In The Coal Mine In Israel’s War On The Truth
- Israeli election committee bars candidate from Knesset race over Gaza war opposition
- French-Lebanese man files war crimes complaint over Israeli attacks
- Mahan Air Flight Lands in China Despite US Threat against Iranian Airlines
- US eyes $10bn fund to rebuild war-battered Gulf infrastructure
- Trump meets Rodríguez near Maduro’s prison as Venezuela’s oil flows to US
- Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
If Americans Knew- Caught on Tape: AIPAC CEO Boasted of Controlling Trump’s National Security Officials
- Why Hamas Attacked Israel in October 2023 – Israeli professor Ilan Pappé
- They see them, then kill them: Israeli quadcopters track, deliberately target civilians in Gaza
- Winter could turn Gaza’s treacherous, war-damaged buildings into deathtraps
- Majority of Democratic Voters Want to Prosecute Both Biden and Trump Administration Officials Over Gaza
- As Gaza languishes, world leaders gather at the UN – Daily Update
- Sanctions are collective punishment: immoral and self-defeating
- Phosphorus Munitions Fired by Israel Burn Groves, Orchards in Southern Lebanon
- Israel Carries Out New Ceasefire Violations Across Gaza
- AI – Emphasis on the ‘I’: Israel Is Funding AI Chatbot Propaganda
No Tricks Zone- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
Contact:
atheonews (at) gmail.com
Disclaimer
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.
