Hurricane Katrina and the “Angels of Mercy”
Ethical boundaries in medical decision-making
By Jonathan Engler and Jessica Hockett | HART | August 21, 2023
The debate as to how much “pandemic” harm was caused not by a virus, but rather by the dystopian response to the perceived threat of a virus, has been raging for some time now.
Jonathan tweeted about this last year in relation to Lombardy and that thread was turned into this Panda article.
An analysis of the spatial characteristics of deaths during the spring 2020 wave in Northern Italy was carried out by him along with a Panda colleague; this suggested that it looked nothing like a spreading virus, and more like the sudden imposition of a policy response.
More recently, Jessica has essentially come to the same conclusions about New York: that something terrifyingly unnatural appears to have happened, which cannot be explained by the sudden spread of a deadly virus.
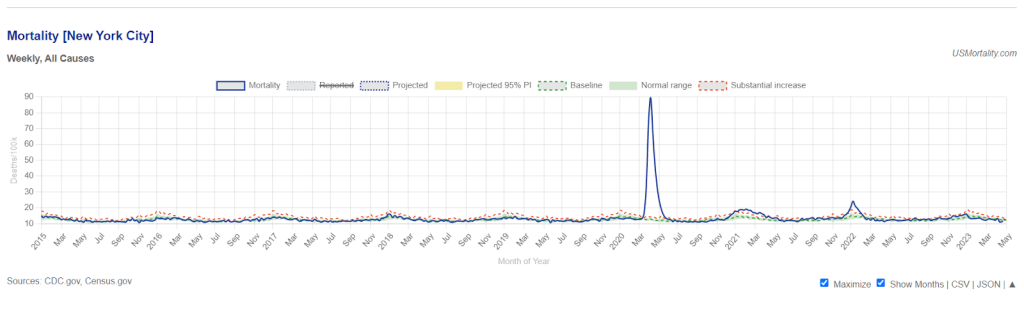
It surely does not require any scientific understanding whatsoever to glance at the below graph of total mortality rate in NYC going back to 2015 and see that what happened in a few weeks during spring 2020 suggests an abrupt episode of ferocious lethality which was at odds not only with anything observed anywhere at the time or thereafter, but also with even the highest estimates of the infection fatality rate alleged to have caused “the pandemic”.
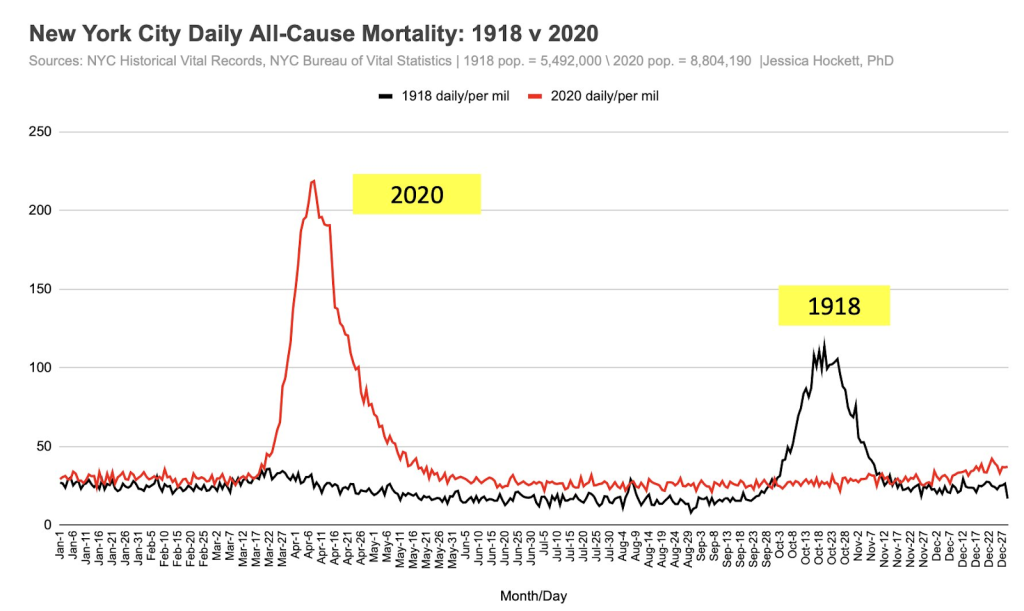
If we look back even further, it can be seen that the reported spring 2020 mortality spike in New York is actually around double that observed in the autumn of the 1918 pandemic. But other places in 2020 did not see waves of deaths anywhere near those observed during the 1918 pandemic.
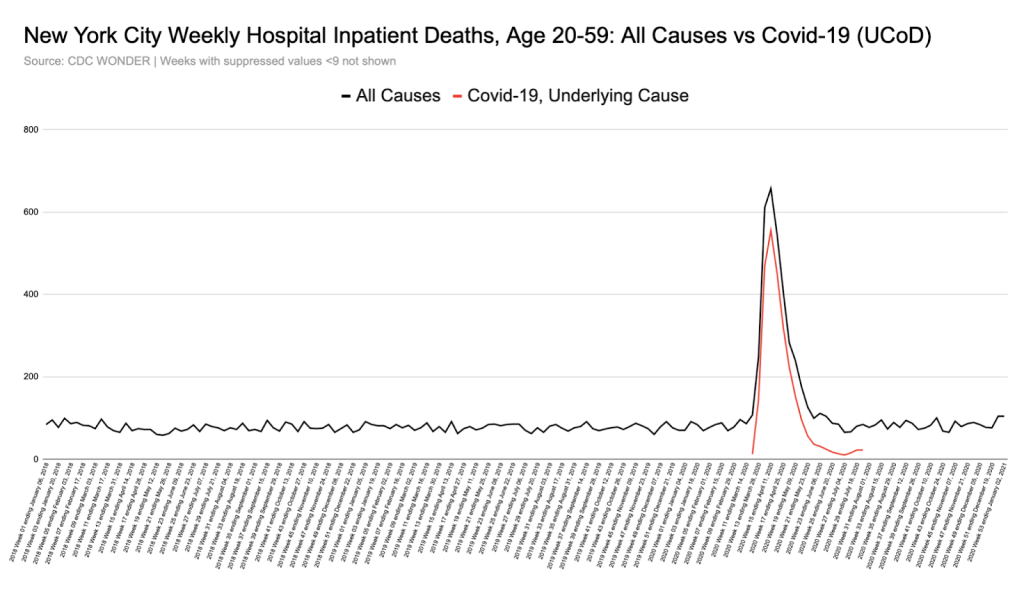
Moreover, unlike elsewhere, the increase in deaths was seen across a younger demographic, not exclusively in the elderly.
As shown in the graph below, all-cause hospital inpatient weekly death counts in the 20-59 age group were dramatically elevated for a short period, by a shocking 6-fold at their peak, with nearly all these deaths being coded as ‘covid’.
In fact, in New York, the % increase in all-cause deaths during the spring “1st wave” period was the same in the 20-69 year old age group as in the 70s and over:
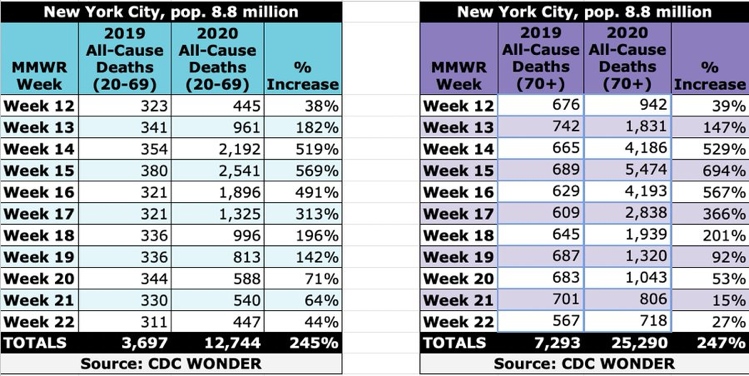
In other places, however, what we were told was the same disease caused by the same virus left the younger age groups largely untouched, with nearly all deaths being in the elderly.
This discrepancy remains completely unexplained. It seems unarguable that certain difficult questions certainly need asking about what happened in New York in 2020 if we are to unravel the truth about what happened there.
Of course, the narratives emerging from Northern Italy and New York in 2020 were instrumental in driving fear and hysteria worldwide. Moreover, the number of deaths in both places informed early estimates of the IFR. These inciting incidents directly sparked much of the worldwide exaggerated, fear-driven response to what we now know was (if anything) a virus mainly affecting the frail and elderly, to which most people already had sufficient immunity to prevent severe illness.
For these reasons, it is essential that particular attention is paid to try to ascertain precisely what happened in these specific places.
It’s worth detailing – as evidence for the deeply dystopian mindset operating at the time – just some of the many deviations from normality that adversely affected human health and immunity, or which constituted sudden changes to healthcare practice.
These included (but were not limited to):
- Stress and anxiety from confinement (being told to stay home) and fear propaganda
- Discouragement to attend hospitals if ill
- Reduced community prescribing of broad-spectrum antibiotics
- Low staff levels in healthcare settings due to self-isolation of those “testing positive,” even with no symptoms
- Isolating the elderly
- Barring loved ones from hospital and care homes
- Fear (on the part of HCWs) of tending to covid positive patients, compromising basic medical and care needs.
- Early and inappropriate invasive ventilation
- Overuse of midazolam and opiates
Inevitably, and rightly, some researchers have started to perform post-pandemic autopsies analysing the motives and reasoning used to justify policies and other changes in behaviour and to examine their real world consequences.
Some medical practitioners have taken umbrage at any suggestion that the stressful environment and sudden expectations and pressures laid upon them may have resulted in well-meaning medical staff crossing ethical lines, or violating the Hippocratic Oath.
Those who wish to point out that there is historical precedent for medical staff behaving diabolically while thinking they are doing good often invoke atrocities during the 1930s and 1940s (and receive opprobrium as a result).
However, there is a much more recent example, and one which we were oblivious to until recently, despite this incident being totally “out in the open”, the subject of a lengthy investigative article, book, and a TV mini-series: the post Hurricane Katrina incident at Memorial Hospital Center in New Orleans in 2006.
Wikipedia provides the basic facts:
In the hurricane aftermath, the basement of Memorial Hospital Center flooded, power failed, and battery power for essential equipment started to run out. Most, but not all, patients were successfully evacuated.
The hurricane occurred on 29th August. A shocking finding was made in the aftermath, as described in the Wikipedia article:
On September 11, mortuary workers recovered 45 bodies from the hospital. Toxicology tests were performed on 41 bodies, and 23 tested positive for one or both of morphine and the fast-acting sedative midazolam [branded as Versed in the US], although few of these patients had been prescribed morphine for pain.
In the following weeks, it was reported that staff had discussed euthanizing patients. Some reports went further; Bryant King, an internist at Memorial, told CNN that he believed “the discussion of euthanasia was more than talk.”
LifeCare told the state Attorney General’s office that nine of their patients might “have been given lethal doses of medicines by a Memorial doctor and nurses.”
King publicly charged that one or more healthcare workers had killed patients, based on conversations with other health care workers. King told CNN that when he believed a doctor was about to kill patients, he boarded a boat and left the hospital. King explained his actions in terms of his opposition to Pou’s alleged actions, arguing “I’d rather be considered a person who abandoned patients than someone who aided in eliminating patients.”
Following an investigation into the deaths described above, the local DA (“District Attorney”) decided there was sufficient evidence to charge three medical staff with four counts of second-degree murder. Charges against two were later dropped in exchange for testimony.
The prosecution was deeply unpopular. Despite substantial evidence of deliberate actions taken to terminate lives – indeed, enough to satisfy the legal definition for homicide – many members of the public felt medical staff were simply “doing their best” under very trying circumstances. According to a local reporter the incident “ignited a furious debate in New Orleans and elsewhere about whether sharp ethical boundaries can be drawn around decisions on patient comfort made in a crisis.”
The DA failed to win re-election, and when the new DA convened a Grand Jury* at an undisclosed location, much of the previously amassed evidence was not presented and some of the key witnesses not called. The Grand Jury decided that charges should be dropped.
Unsurprisingly, several commentators (e.g., Loyola University Law Professor Dane Ciolono) opined that the Grand Jury was convened and run in such a way as to ensure charges would be dropped while providing “cover” for such an outcome.
Whatever actually occurred at Memorial Hospital, or whatever the staff’s motives, the incident speaks to an unsettling, yet undeniable truth: during a crisis, “ethical red lines” – however deeply held and valued – may be easily crossed. Society may judge those decisions acceptable or understandable, as appears to have happened with the Memorial Hospital case.
In summary, it would appear that the legal process was manipulated to assure an outcome which accorded with public opinion – that is to say to extinguish the possibility of prosecution while maintaining the pretence of due legal process. In this way, facing up to the stark reality – that as a society we mete out justice arbitrarily when we wish to – was avoided. Perhaps the well-ordered rules-based system suggested by statutory definitions of what actions constitute crimes, is to some extent just “for show”.
The Memorial Hospital case obliterates – with a relatively recent example – the notion that doctors and nurses all have the same ethical boundaries which they simply will not cross under any circumstances.
Could such boundaries have been crossed during the recent covid event?
A number of commentators are considering the possibility that changes in the policies and practices around the use of certain drugs (midazolam and opiates), and procedures (invasive ventilation) – sometimes in combination – may have contributed to the high mortality reported, at least in some specific places.
In relation to drugs, in an article published on his Substack last year, the blogger known as Bartram’s Folly explored the possibility that (in the UK) sheer fear and panic may well have driven medical staff to use midazolam and opiates more liberally in patients with covid, which may have encompassed anyone with a positive covid test.
In the UK one such mechanism which may have encouraged this measure is the NICE Guideline NG163 (no longer on their website but available here or as PDF download here), about which others have also written in detail. This guideline effectively transposed the advice for treating end-stage cancer patients with midazolam and opiates into that for covid patients. More detail on this here.
Of the guideline, Bartram said,
“… the NICE guidelines appear to have introduced a pathway for doctors which allowed for (perhaps even encouraged) more than a gentle nudge for those who were ill with Covid towards death, some of whom might well have survived given the chance. This iatrogenesis hypothesis would mean that at least some of the deaths recorded as with Covid might well have been a direct result of the care guidelines as set out by NICE.“
Later, Bartram makes the point that the pretext of a crisis situation or emergency may establish the grounds for ethical boundaries to be crossed or disregarded, at least temporarily, under the auspices of ignorance or ‘doing one’s best’ with the information said to be known or available at the time:
It is important to note that in the iatrogenesis hypothesis it isn’t necessary for some people to have had an evil intent – it is entirely possible that individuals promoted and exercised a policy that resulted in needless deaths while believing that they were ‘doing the right thing’ (e.g., see Hannah Arendt’s concept of the banality of evil).
In particular, ‘petty bureaucrats’ appear to be readily able to think up policies without seeing the need to consider the full consequences, and when these consequences are eventually revealed will usually point to the minutes from endless meetings with other petty bureaucrats to show that they weren’t personally responsible for the policy and they were simply following process.
Of course, once a framework had been decided front-line staff might have been grateful for the guidance offered given the challenging times, at least until the negative consequences of the guidance became painfully clear.
It should also be remembered that – in the US at least – certain extraordinary policy measures may have been important factors. For example, during the emergency NYC Governor Cuomo issued executive orders and suspended laws which gave doctors and nurses immunity and absolved hospitals of the responsibility to keep close patient records. (The order itself can be found here, and some legal commentary on it here.) Articles in JAMA can be interpreted as giving ethical permission for physicians to issue unilateral DNR orders, avoid CPR, and ration ventilators and critical care beds.
Moreover there are numerous examples of doctors, nurses and others in the US who later said they were following guidance, learning as they went. (See this interesting essay by Dr Kory, for example.) Under these circumstances it is easy to see how they could assume that something which ordinarily might have been questionable would become acceptable as “everyone else was doing it”.
Evidence of increased midazolam use can be seen in the US as well as in the UK. This graph from a study describing the use of 7 specific drugs in 47 hospitals in NY shows the daily count of patients (blue) who received midazolam and the disproportionate quantities used (orange) between March 1 and May 16, 2020.
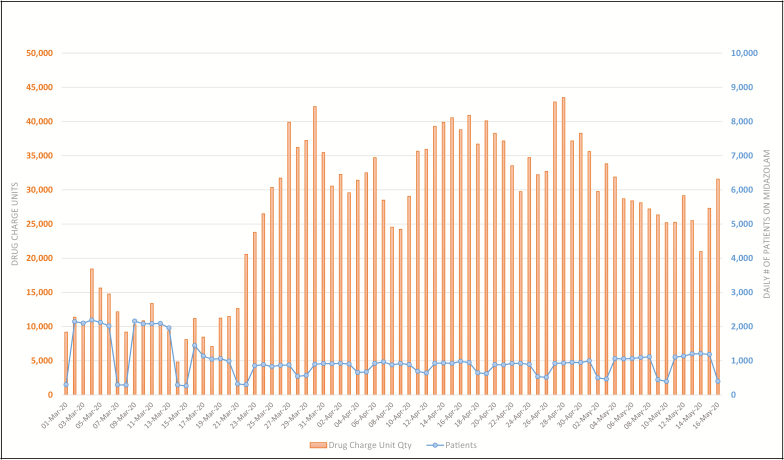
Moreover, midazolam is currently listed by the FDA to have been in short supply since 2 April 2020:

This Guardian article from 13 April 2020 reports on a letter sent by “a group of prominent medical practitioners and experts” to capital punishment states imploring them to:
“release their stocks of essential sedatives and paralytics that they hoard for executions” so that they can be “used for intubations and mechanical ventilation of the most severely ill coronavirus patients who cannot breathe for themselves”.
The tone of this letter can be taken to illustrate the sense of sheer panic prevailing at the time – certainly not conducive to rational decision-making – combined with the assumption that invasive ventilation was going to be extensively required and used.
This takes us to the question of invasive ventilation, whether it might have been used too often, inappropriately, and why.
As well as panic, the role of fear on the part of healthcare workers cannot be underestimated. Here is Dr Vinay Prasad stating that:
“It is a unique situation in medicine. In our whole medical career, doctors have never been personally afraid the way they were [with covid].”
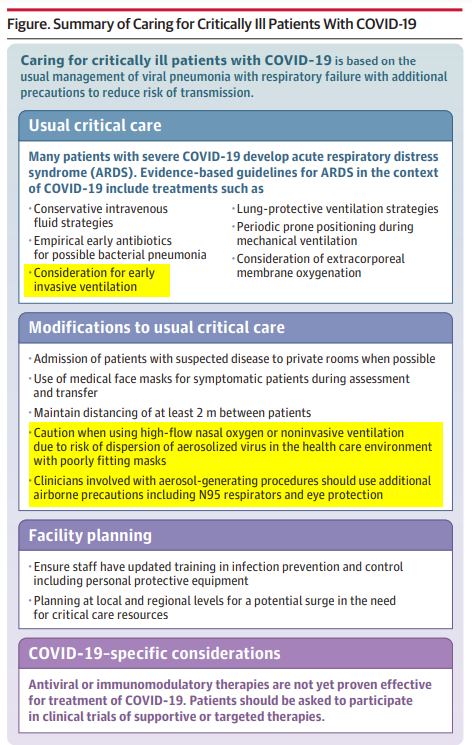
Official guidance (see for example this from a British anaesthetists’ professional association) certainly reinforced the idea that one of the benefits of early intubation was to reduce the aerosolization of virus, such that it would be safer for those caring for the patients, compared to when non-invasive forms of ventilation were used.
This JAMA Clinical Update “Care for Critically Ill Patients With COVID-19” published on 11 March 2020 strongly supports the idea that the thinking was very much that non-invasive oxygen augmentation could be dangerous for healthcare workers:
The journalist Alex Berenson was early to point out that ventilator shortage may have more to do with overuse “to protect staff” than to being overwhelmed by patients in respiratory failure.
It seems like fear may well have been augmented by official guidance to result in significant overuse of this measure.
It is important to understand the differences between the Memorial Hospital incident and what may have happened in the early stages of the covid crisis. In New Orleans, it may indeed have been reasonable to assume that it was going to be impossible to evacuate the patients (who were given midazolam and opiates to ease suffering) in time, and that they were indeed unsaveable due to the extraordinary circumstances. (Whether or not this was actually the case will probably never be known, because of the legal shenanigans described above.)
However, whether that applies to all, some, or just a few of those who died in spring 2020 after being administered the same or other drugs (or placed on mechanical ventilators or issued a unilateral DNR, etc.) is still a matter of debate whereas for sure, Hurricane Katrina was self-evidently an extreme weather event that created devastation and emergency conditions in its fury and wake.
Certainly, it seems clear that personal fear and a belief in the lethality of this infection drove much medical decision-making in the early days. It is not hard to imagine actions being taken which were then rationalised by imagining the suffering that had been prevented, limited resources preserved, and many lives saved. The deaths witnessed could easily have acted as positive reinforcement in the minds of healthcare workers as to how serious the illness was. These protocols could lead to the deaths of patients who were not particularly old and frail and thus reinforce the message that the virus was potentially fatal even in such people
The decisions that healthcare workers made, and the influences on and factors involved in those decisions, will be discussed and dissected for decades to come. When humanity is ready to confront what occurred – and admit that ethical inversions in hospitals and care homes contributed to unintentional iatrogenic death, we can move toward keeping it from happening again.
* (A Grand Jury in the US is a specific type of court empowered by law to determine whether probable cause exists to support criminal charges for a suspect in a crime. Louisiana – in which New Orleans is situated – is one of 23 US states that use grand juries for indictments in serious crimes.)
Battle for Climate Earth
ClimateCraze | July 5, 2021
There is no climate crisis — just climate alarmism.

Greg Tucker-Kellogg publishes fraudulent study to attack ivermectin
Tucker-Kellogg aimed to review research conducted in Brazil and conclude that ivermectin was ineffective against Covid-19. In order to do so, he and his colleagues had to fabricate over 250 fatalities.

Illustration. Reproduction photo from Greg’s YouTube channel.
Médicos Pela Vida | August 17, 2023
Greg Tucker-Kellogg, from the Department of Biological Sciences at the National University of Singapore, who receives compensation from YouTube for creating content against scientific misinformation, along with two other authors, Ana Carolina Peçanha and Robin Mills, published a study on the Medrxiv platform on August 15th. The study used fraudulent data with the aim of undermining the research on ivermectin conducted in Itajaí, located on the coast of Santa Catarina, Brazil.
The study conducted in Itajaí, peer-reviewed and published in the prestigious Cureus journal in early 2022, concluded the effectiveness of ivermectin in its prophylactic use against COVID-19. The results were positive: among individuals who took ivermectin preventively, there were 68% fewer deaths, 56% fewer hospitalizations, and 44% fewer infections.
The False Data
Tucker-Kellogg and colleagues’ study, which aimed to recalculate and nullify the positive results, used fraudulent data to achieve its goal. In the article, they claim that the data is official.
The authors stated that 499 individuals died between July and December 2020, a period during which the effectiveness of ivermectin was studied in the city.

However, the data of 499 COVID-19 deaths during the six months of the study in Itajaí is indeed false. In order to achieve their desired outcome, the number of deaths had to be inflated. You can verify the original PDF of the reanalysis here on page 3.
How We Investigated
The purported 499 deaths in six months, used as a basis for the calculations, raised suspicions due to being an unusually high number for the period in a city with just over 200,000 inhabitants. Consequently, the first step we took was to research the city’s epidemiological bulletins during that timeframe.
The official epidemiological bulletin, published on the Itajaí city government’s website on December 28, 2020, stated that a total of 254 individuals had died since the beginning of the pandemic. This figure represents deaths from when the virus first spread in the city in early 2020. Therefore, the deaths between July and December were even fewer, far from the reported 499.
In a second attempt to verify the numbers, we accessed consolidated data from the Brazilian Unified Health System (Sistema Único de Saúde or SUS) through the OpendataSUS database, which is considered one of the most comprehensive and accurate in the world. As Brazil has a publicly funded healthcare system, data for all patients in the country is rigorously monitored.
The OpenDataSUS Numbers:
Deaths caused by Severe Acute Respiratory Syndrome (SARS), with dates ranging from July to December 2020, among residents of the city. Database downloaded on March 13, 2023.
Based on the date of hospitalization:
Total SARS-related deaths: 234
Deaths due to Covid-19 only: 222
Based on the date of symptom onset:
Total SARS-related deaths: 256
Deaths due to Covid-19 only: 237
Based on the date of data entry:
Total SARS-related deaths: 240
Deaths due to Covid-19 only: 222
The Numbers from Brasil.IO
According to the information from the Brasil.IO database, which compiles data from confirmed cases and deaths from the bulletins of the State Health Departments (Secretarias Estaduais de Saúde or SES), during the period of the Itajaí study, the data were as follows:
Total Covid-19 deaths: 227
Fraudulent Study Used for Attacks
The authors of the original study have a long history in science and impeccable reputations. Lucy Kerr, the lead author, is the daughter of the late Warwick Stevam Kerr, and she deeply values his legacy. Warwick was the Scientific Director of FAPESP, served as the president of the Brazilian Society for the Advancement of Science, and received the Order of Scientific Merit in the Grand Cross category. Other authors include Dr. Flavio Cadegiani, a researcher with several COVID-19 studies, Dr. Fernando Baldi, a professor at the São Paulo State University (UNESP), Dr. Pierre Kory, an American medical professor, and Dr. Jennifer A. Hibberd from the University of Toronto, among others.

Following the publication of the reanalysis with fraudulent data, the attacks on the authors’ reputations turned defamatory. “There are people who prefer to keep believing in charlatans,” said Chloé Pinheiro, a journalist from Veja, one of Brazil’s major magazines.
Leandro Tessler, a professor at Unicamp, who represents the respected university in classifying true or false news on the internet and has admitted to not reading studies on cheap, generic, and unpatented treatments that he criticized, claimed that the original positive study had “cooked data.” Furthermore, Leandro criticized the journal’s quality by saying, “It’s something for Cureus.”
“Statistical trickery,” said Julio Ponce, a doctor in epidemiology and host of the podcast “Escuta a Ciência,” in response to the positive results of the original study.
Isaac Schrarstzhaupt, coordinator of the Rede Análise, criticized the quality of the Cureus journal. He stated that the original publication falls among the “lesser journals,” and he phrased it this way “to avoid using other terms.“
Original Authors Always Prioritized Transparency
The authors of the original study on ivermectin in Itajaí, responding to a call from the BMJ – British Medical Journal, which requested the publication of public data from studies on medications and vaccines, decided to make their raw data available for reanalysis.
This action was highly praised. “It’s excellent that they have released their data anonymously. They have true confidence in the results of their analyses. This is how good science is carried out,” stated Dr. Harvey Risch, a professor of epidemiology at Yale University, USA, emphasizing that patients’ personal data had been preserved.
Previously, the scientific community had speculated that the authors would not make their data available.
The doctor has been attacking the authors for some time
Ana Carolina, one of the authors of the study, has been attacking Dr. Flavio Cadegiani for some time. He is also the author of other studies involving different medications against Covid-19, such as those involving proxalutamide. She claims that those researches are a “hoax.” Regarding the study she chose to reanalyze now, inserting fraudulent data, Ana Carolina had already committed in early 2022 to disqualify it. She referred to it as an “international embarrassment” at the time and used quotation marks to refer to the researchers, seemingly implying doubt about their work.
“They had already decided that ivermectin doesn’t work. So, they tried – and made a great effort – to find calculations that ‘fit’ their pre-established conclusion. This is the exact opposite of what science is, which involves accepting results whether they contradict or support the hypothesis. In their quest to find the desired data, they most likely forgot to look at their own analyses – and even worse, at basic numbers. Furthermore, it seems to me that they didn’t quite understand the study, as I couldn’t find analyses related to rates derived from infections, matched with Propensity Score Matching,” stated Dr. Flavio Cadegiani, one of the authors of the Itajaí study.
“The most important thing is that this ‘study,’ by demonstrating its inability to invalidate us, has only reinforced our findings, and for that, we cannot help but be grateful,” he added.
MPV Comment
Scientific fraud is presenting unverified data as if it were official. And this wasn’t a small error. It was the central data point used to generate the result. It’s not a minor mistake that wouldn’t affect the studied outcomes. In order for the authors to attack the study and arrive at the conclusion of inefficacy, they needed to increase the number of deaths.
All those who subsequently attacked, even labeling the authors as “charlatans,” supposedly had the capacity and training to spot the fraudulent numbers. They are doctors, professors, epidemiologists, and data scientists. They either didn’t see it or feigned ignorance.
So far, all the scientific frauds published during the pandemic have targeted inexpensive, generic, and unpatented medications, or they were frauds promoting expensive and patented drugs. Surely, this is just a coincidence.
This is the second time the Itajaí study has been attacked without valid scientific arguments. In June 2022, the USP – University of São Paulo journal attacked it, even spreading false information. Our analysis can be read here: “COVID-19: USP Journal Lies and Distorts Science to Attack Ivermectin. Read the full analysis.” (portuguese).
We, at MPV (Médicos pela Vida) – Doctors for Life, are grateful for the collaboration of Professor Daniel Tausk from USP, for compiling data from official databases. His collaboration was essential for the report. Additionally, we thank the French researcher Massimaux, who prefers to remain anonymous on Twitter, for quickly pointing out fraudulent data. According to him, it was a “sanity check.” It didn’t pass.
Sources
Data from OpendataSUS
Data from Brasil.IO
Epidemiological Bulletin of Itajaí
US Guantanamo judge dismisses ‘confession’ obtained by torture

Press TV – August 19, 2023
A US military judge has rejected a “confession” coerced out of a young Guantanamo Bay captive through torture following the September 11, 2001 highly suspicious terror attacks in Washington and New York that led to military invasion of Afghanistan and Iraq.
The judge in the military tribunals held for captives still held in the Cuba-based US Guantanamo Bay military prison and torture facility ruled that the “confession” obtained from Abd al-Rahim al-Nashiri, accused of masterminding the 2000 bombing attack on the USS Cole warship in Yemen that killed 17 American sailors, was tainted by years of abuse and torture inflicted on him at the hands of the CIA and FBI intelligence agents and operatives.
“Exclusion of such evidence is not without societal costs,” wrote the judge, Col. Lanny Acosta, in handing down his ruling.
“However, permitting the admission of evidence obtained by or derived from torture by the same government that seeks to prosecute and execute the accused may have even greater societal costs.” Acosta further emphasized.
Attorneys for both Nashiri and five other suspects — accused of involvement in the September 11 attacks and held captive and tortured for decades without trial or legal representation — have struggled for over 10 years now in the Guantanamo military court to exclude evidence against them that was coerced through torture.
The six were captured separately after the 2001 attacks and shuttled through CIA-run “black sites” in numerous US-allied countries across the globe, such as Thailand and Poland, where they were subjected to intense torture techniques, including waterboarding, physical beatings and sleep deprivation.
Following the arrival of the captives at the Guantanamo military prison, some of them, including Nashiri were again subjected to intense interrogation and torture by FBI agents in early 2007 and other instances.
The judge’s decision comes as obtaining confession from prisoners through torture remains a major violation of international law.
The US military has accused Nashiri of being an al-Qaeda recruiter that plotted various attacks on American interests in the Arabian Peninsula.
US forces captured Nashiri in 2002 and transferred him to the Guantanamo prison in 2006 after he remained for four years in the custody of CIA interrogators and repeatedly tortured.
In September 2011, he was charged by a US military commission on nine counts related to his alleged involvement in planning al-Qaeda attacks.
His military trial showcased by the very entity that captured and tortured him has repeatedly faced delays, due to insistence by his assigned military lawyers that he suffered repeated torture while under detention of the CIA spy agency collaborating with US military forces occupying Afghanistan and Iraq.
The WHO’s Proposed Amendments Will Increase Man-Made Pandemics
By Meryl Nass | Brownstone Institute | August 17, 2023
This report is designed to help readers think about some big topics: how to really prevent pandemics and biological warfare, how to assess proposals by the WHO and its members for preventing and responding to pandemics, and whether we can rely on our health officials to navigate these areas in ways that make sense and will help their populations. We start with a history of biological arms control and rapidly move to the COVID pandemic, eventually arriving at plans to protect the future.
Weapons of Mass Destruction: Chem/Bio
Traditionally, the Weapons of Mass Destruction (WMD) have been labelled Chemical, Biological, Radiologic, and Nuclear (CBRN).
The people of the world don’t want them used on us—for they are cheap ways to kill and maim large numbers of people quickly. And so international treaties were created to try to prevent their development (only in the later treaties) and use (in all the biological arms control treaties). First was the Geneva Protocol of 1925, following the use of poison gases and limited biological weapons in World War I, banning the use of biological and chemical weapons in war. The US and many nations signed it, but it took 50 years for the US to ratify it, and during those 50 years the US asserted it was not bound by the treaty.
The US used both biological and chemical weapons during those 50 years. The US almost certainly used biological weapons in the Korean War (see this, this, this and this) and perhaps used both in Vietnam, which experienced an odd outbreak of plague during the war. The use of napalm, white phosphorus, agent orange (with its dioxin excipient causing massive numbers of birth defects and other tragedies) and probably other chemical weapons like BZ (a hallucinogen/incapacitant) led to much pushback, especially since we had signed the Geneva Protocol and we were supposed to be a civilized nation.
In 1968 and 1969, two important books were published that had a great influence on the American psyche regarding our massive stockpiling and use of these agents. The first book, written by a young Seymour Hersh about the US chemical and biological warfare program, was titled Chemical and Biological Warfare; America’s Hidden Arsenal. In 1969 Congressman Richard D. McCarthy, a former newspaperman from Buffalo, NY wrote the book The Ultimate Folly: War by Pestilence, Asphyxiation and Defoliation about the US production and use of chemical and biological weapons. Prof. Matthew Meselson’s review of the book noted,
Our operation, “Flying Ranch Hand,” has sprayed anti-plant chemicals over an area almost the size of the state of Massachusetts, over 10 per cent of its cropland. “Ranch Hand” no longer has much to do with the official justification of preventing ambush. Rather, it has become a kind of environmental warfare, devastating vast tracts of forest in order to facilitate our aerial reconnaissance. Our use of “super tear gas” (it is also a powerful lung irritant) has escalated from the originally announced purpose of saving lives in “riot control-like situations” to the full-scale combat use of gas artillery shells, gas rockets and gas bombs to enhance the killing power of conventional high explosive and flame weapons. Fourteen million pounds have been used thus far, enough to cover all of Vietnam with a field effective concentration. Many nations, including some of our own allies have expressed the opinion that this kind of gas warfare violates the Geneva Protocol, a view shared by McCarthy.
A Biological Weapons Convention
Amid great pushback over US conduct in Vietnam, and seeking to burnish his presidency, President Nixon announced to the world in November 1969 that the US was going to end its biowarfare program (but not the chemical program). Following pointed reminders that Nixon had not eschewed the use of toxins, in February 1970 Nixon announced we would also get rid of our toxin weapons, which included snake, snail, frog, fish, bacterial, and fungal toxins that could be used for assassinations and other purposes.
It has been claimed that these declarations resulted from careful calculations that the US was far ahead technically of most other nations in its chemical and nuclear weapons. But biological weapons were considered the “poor man’s atomic bomb” and required much less sophistication to produce. Therefore, the US was not far ahead in the biological weapons arena. By banning this class of weapon, the US would gain strategically.
Nixon told the world that the US would initiate an international treaty to prevent the use of these weapons ever again. And we did so: the 1972 Convention on the Prohibition of the Development, Production and Stockpiling of Bacteriological (Biological) and Toxin Weapons and on their Destruction, or Biological Weapons Convention (BWC) for short, which entered into force in 1975.
But in 1973 genetic engineering (recombinant DNA) was discovered by Americans Herbert Boyer and Stanley Cohen, which changed the biological warfare calculus. Now the US had regained a technological advantage for this type of endeavor.
The Biological Weapons Convention established conferences to be held every 5 years to strengthen the treaty. The expectation was that these would add a method to call for ‘challenge inspections’ to prevent nations from cheating and would add sanctions (punishments) if nations failed to comply with the treaty. However, since 1991 the US has consistently blocked the addition of protocols that would have an impact on cheating. By now, everyone accepts that cheating occurs and is likely widespread.
A leak in an anthrax production facility in Sverdlovsk, USSR in 1979 caused the deaths of about 60 people. While the USSR tried a sloppy cover-up, blaming contaminated black market meat, this was a clear BWC violation to all those knowledgeable about anthrax.
US experiments with anthrax production during the Clinton administration, detailed by Judith Miller et al. in the 2001 book Germs, were also thought by experts to have transgressed the BWC.
It has taken over 40 years, but in 2022 all declared stocks of chemical weapons had been destroyed by the USA, by Russia, and the other 193 member nation signatories. The chemical weapons convention does include provisions for surprise inspections and sanctions.
Pandemics and Biological Warfare Receive Funding from Same Stream
It is now 2023, and during the 48 years the Biological Weapons Convention has been in force the wall it was supposed to build against the development, production, and use of biological weapons has been steadily eroded. Meanwhile, especially since the 2001 anthrax letters, nations (with the US at the forefront) have been building up their “biodefense” and “pandemic preparedness” capacities.
Under the guise of preparing their defenses against biowarfare and pandemics, nations have conducted “dual-use” (both offensive and defensive) research and development, which has led to the creation of more deadly and more transmissible microorganisms. And employing new verbiage to shield this effort from scrutiny, biological warfare research was renamed as “gain-of-function” research.
Gain-of-function is a euphemism for biological warfare research aka germ warfare research. It is so risky that funding it was banned by the US government (but only for SARS coronaviruses and avian flu viruses) in 2014 after a public outcry from hundreds of scientists. Then in 2017 Drs. Tony Fauci and Francis Collins lifted the moratorium, with no real safeguards in place. Fauci and Collins even had the temerity to publish their opinion that the risk from this gain-of-function research was ‘worth it.’
What does gain-of-function actually mean? It means that scientists are able to use a variety of techniques to turn ordinary or pathogenic viruses and bacteria into biological weapons. The research is justified by the claim that scientists can get out ahead of nature and predict what might be a future pandemic threat, or what another nation might use as a bioweapon. The functions gained by the viruses or other microorganisms to turn them into biological warfare agents consist of two categories: enhanced transmission or enhanced pathogenicity (illness severity).
1) improved transmissibility may result from:
a) needing fewer viral or bacterial copies to cause infection,
b) causing the generation of higher viral or bacterial titers,
c) a new mode of spread, such as adding airborne transmission to a virus that previously only spread through bodily fluids,
d) expanded range of susceptible organs (aka tissue tropism); for example, not only respiratory secretions but also urine or stool might transmit the virus, which was found in SARS-CoV-2,
e) expanded host range; for example, instead of infecting bats, the virus is passaged through humanized mice and thus acclimated to the human ACE-2 receptor, which was found in SARS-CoV-2,
f) improved cellular entry; for example, by adding a furin cleavage site, which was found in SARS-CoV-2,
2) increased pathogenicity, so instead of causing a milder illness, the pathogen would be made to cause severe illness or death, using various methods. SARS-CoV-2 had unusual homologies (identical short segments) to human tissues and the HIV virus, which may have caused or contributed to the late autoimmune stage of illness, impaired immune response and ‘long COVID.’
Funding for (Natural) Pandemics, Including Yearly Influenza, was Lumped Together with Biological Defense Funding
Perhaps the comingling of funding was designed to make it harder for Congress and the public to understand what was being funded, and how much taxpayer funding was going to gain-of-function work, which might lead them to question why it was being done at all, given its prohibition in the Biological Weapons Convention, and additional questions about its value. Former CDC Director Robert Redfield, a physician and virologist, told Congress in March of 2023 that gain-of-function research had not resulted in a single beneficial drug, vaccine, or therapeutic to his knowledge.
Nonprofits and universities like EcoHealth Alliance and its affiliated University of California, Davis veterinary school were used as intermediaries to obscure the fact that US taxpayers were supporting scientists in dozens of foreign countries, including China, for research that included gain-of-function work on coronaviruses.
Perhaps to keep the lucrative funding going, fears about pandemics have been deliberately amplified over the past several decades. The federal government has been spending huge sums on pandemic preparedness over the past 20 years, routing it through many federal and state agencies. President Biden’s proposed 2024 budget requested “$20 billion in mandatory funding across DHHS for pandemic preparedness” while the DHS, DOD, and the State Department have additional budgets for pandemic preparedness for both domestic and international spending.
Although the 20th century experienced only 3 significant pandemics (the Spanish flu of 1918-19 and 2 influenza pandemics in 1957 and 1968) the mass media have presented us with almost non-stop pandemics during the 21st century: SARS-1 (2002-3), avian flu (2004-on), swine flu (2009-10), Ebola (2014, 2018-19), Zika (2016), COVID (2020-2023), and monkeypox (2022-23). And we are incessantly told that more are coming, and that they are likely to be worse.
We have been assaulted with warnings and threats for over 2 decades to induce a deep fear of infectious diseases. It seems to have worked.
The genomes of both SARS-CoV-2 and the 2022 monkeypox (MPOX) virus lead to suspicion that both were bioengineered pathogens originating in laboratories. The group of virologists assembled by Drs. Fauci and Farrar identified 6 unusual (probably lab-derived) parts of the SARS-CoV-2 genome as early as February 1, 2020 and more have been suggested subsequently.
I do not know if these viruses leaked accidentally or were deliberately released, but I am leaning toward the conclusion that both were deliberately released, based on the locations where they first appeared, the well-orchestrated but faked videos rolled out by the mass media for COVID, and the illogical and harmful official responses to each. In neither case was the public given accurate information about the infections’ severity or treatments, and the responses by Western governments never made scientific sense. Why wouldn’t you treat cases early, the way doctors treat everything else? It seemed that our governments were trading on the fact that few people knew enough about viruses and therapeutics to make independent assessments about the information they were being fed.
Yet by August 2021, there was no corresponding course correction. Instead, the federal government doubled down, imposing vaccine mandates on 100 million Americans in September 2021 in spite of ‘the science.’ There has been no accurate statement yet from any federal agency about the lack of utility of masking for an airborne virus (which is probably why the US government and WHO delayed acknowledging airborne spread by COVID for 18 months), the lack of efficacy of social distancing for an airborne virus, and the risks and poor efficacy of 2 dangerous oral drugs (paxlovid and molnupiravir) purchased by the US government for COVID treatment, even without a doctor’s prescription.
Never have any federal agencies acknowledged the truth about the COVID vaccines’ safety and efficacy. Instead, the CDC turns definitional and statistical cartwheels so it can continue to claim they are “safe and effective.” Even worse, with all that we know, a third generation COVID vaccine is to be rolled out for this fall and the FDA has announced that yearly boosters are planned.
All this goes on, even a year after we learned (with continuing corroborations) that children and working age adults are dying at rates 25 percent or more above the expected averages, and the vascular side effects of vaccination are the only reasonable explanation.
Maiming with Myocarditis
Both of the two US monkeypox/smallpox vaccines (Jynneos and ACAM2000) are known to cause myocarditis, as do all 3 COVID vaccines currently available in the US: the Pfizer and Moderna COVID-19 mRNA vaccines and the Novavax vaccine. The Novavax vaccine was first associated with myocarditis during its clinical trial, but this was downplayed and it was authorized and rolled out anyway, intended for those who refused the mRNA vaccines due to the use of fetal tissue in their manufacture.
Here is what the FDA’s reviewers wrote about the cardiac side effects noted in the Jynneos clinical trials:
Up to 18.4% of subjects in 2 studies developed post-vaccination elevation of troponin [a cardiac muscle enzyme signifying cardiac damage]. However, all of these troponin elevations were asymptomatic and without a clinically associated event or other sign of myopericarditis. p. 198
The applicant has committed to conduct an observational, post-marketing study as part of their routine PVP. The sponsor will collect data on cardiac events that occur and are assessed as a routine part of medical care. p. 200
In other words, while the only way to cause an elevated troponin level is to break down cardiac muscle cells, the FDA did not require a specific study to evaluate the extent of cardiac damage that might be caused by Jynneos when it issued its 2019 license. How frequently does myocarditis occur after these vaccines? If you use elevated cardiac enzymes as your marker, ACAM2000 caused this in one in thirty people receiving it for the first time. If you use other measures like abnormal cardiac MRI or echo, according to the CDC it occurs in one in 175 vaccinees. I have not seen a study with rates of myocarditis for Jynneos, but there was an unspecified elevation of cardiac enzymes in 10 percent and 18 percent of Jynneos recipients in two unpublished prelicensure studies available on the FDA website. My guess for the mRNA COVID vaccines is that they cause myocarditis in this general range, the vast majority of which remain undiagnosed and probably asymptomatic.
Why would our governments push 5 separate vaccines all known to cause myocarditis on young males who have been at extremely low risk from COVID, and who simply get a few pimples for 1-4 weeks from monkeypox unless they are immunocompromised? It’s an important question. It does not make medical sense. Especially when the vaccine probably does not work—Jynneos didn’t prevent infection in the monkeys in whom it was tested nor did it do well in people. And the CDC has failed to publish its trial of Jynneos vaccine in the ~1,600 Congolese healthcare workers on whom the CDC tested it for efficacy and safety in 2017. The CDC made the mistake of announcing the trial, and posting it to clinicaltrials.gov as required, but has not informed its advisory committee that reviewed the vaccine, nor the public, of the trial’s results.
There can be no question about it: our health agencies are guilty of malfeasance, misrepresentation, and deliberate infliction of harm on their own populations. The health agencies first incited terror with apocalyptic predictions, then demanded patients be medically neglected, and finally enforced vaccinations and treatments that were tantamount to malpractice.
COVID Vaccines: The Chicken or the Egg?
The health authorities could have just been ignorant — that could possibly explain the first few months of the COVID vaccines’ rollout. But once they figured out, and even announced in August 2021 that the vaccines did not prevent catching COVID or transmitting it, why did our health authorities still push COVID vaccines on low-risk populations who were clearly at greater risk from a vaccine side effect than from COVID? Particularly as time went on and newer variants were less and less virulent?
Once you acknowledge these basic facts, you realize that maybe the vaccines were not made for the pandemic, and instead the pandemic was made to roll out the vaccines. While we cannot be certain, we should at least be suspicious. And the fact that the US contracted for 10 doses per person (review purchases here, here, here, here and here) and so did the European Union (here and here) and Canada should make us even more suspicious – there is no justification for agreeing to purchase so many doses for vaccines at a time when the vaccines’ ability to prevent infection and transmission was questionable, and its safety suspect or worrying.
Why would governments want ten doses per person? Three maybe. But ten? Even if yearly boosters were expected, there was no reason to sign contracts for enough vaccine for the next nine years for a rapidly mutating virus. Australia bought 8 doses per person. By December 20, 2020 New Zealand had secured triple the vaccines it needed, and offered to share some with nearby nations. No one has come forward to explain the reason for these excessive purchases.
Furthermore, you don’t need a vaccine passport (aka digital ID, aka a phone app that in Europe included a mechanism for an electronic payments system) unless you are giving out regular boosters. Were the vaccines conceived of as the means for putting our vaccinations, health records, official documents–and most importantly, shifting our financial transactions online, all managed on a phone app? This would be an attack on privacy as well as the enabling step to a social credit system in the West. Interestingly, vaccine passports were already being planned for the European Union by 2018.
A Pandemic Treaty and Amendments: Brought to You by the Same People who Mismanaged the Past 3 Years, to Save us from Themselves?
The same US and other governments and the WHO that imposed draconian measures on citizens to force us to be vaccinated and take dangerous, expensive, experimental drugs, withheld effective treatments, and refused to tell us that most people who required ICU care for COVID were vitamin D-deficient and that taking vitamin D would lessen COVID’s severity–decided in 2021 we suddenly needed an international pandemic treaty. Why? To prevent and ameliorate future pandemics or biological warfare events… so we would not suffer again as we did with the COVID pandemic, they insisted. The WHO would manage it.
To paraphrase Ronald Reagan, the words, “I’m from the WHO, and I’m here to help” should be the most terrifying words in the English language after the COVID fiasco.
What the WHO and our governments conveniently failed to mention is that we suffered so badly because of their medical mismanagement and our governments’ merciless economic shutdowns and mismanagement. According to the World Bank, an additional 70 million people were forced into extreme poverty in 2020 alone. This was due to policies issued by our nations’ rulers, their elite advisers and the World Health Organization, which came out with guidance to shut down economic activity that most nations adopted without question. The WHO is acutely aware of the consequences of economic lockdowns, having published the following:
Malnutrition persisted in all its forms, with children paying a high price: in 2020, over 149 million under-fives are estimated to have been stunted, or too short for their age; more than 45 million – wasted, or too thin for their height…
Starvation may have killed more people than COVID, and they were disproportionately the youngest, rather than the oldest. Yet the WHO prattles on about equity, diversity, and solidarity—having itself caused the worst food crisis in our lifetime, which was not due to nature but was man-made.
How can anyone take seriously claims by the same officials who mishandled COVID that they want to spare us from another medical and economic disaster–by using the same strategies they applied to COVID, after they masterminded the last disaster? And the fact that no governments or health officials have admitted their errors should convince us never to let them manage anything ever again. Why would we let them draw up an international treaty and new amendments to the existing International Health Regulations (IHR) that will bind our governments to obey the WHO’s dictates forever?
Those dictates, by the way, include vaccine development at breakneck speed, the power to enforce which drugs we will be directed to use, and which drugs will be prohibited, and the requirement to monitor media for “misinformation” and impose censorship so that only the WHO’s public health narrative will be conveyed to the public.
The WHO’s Pandemic Treaty Draft Requires the Sharing of Potential Pandemic Pathogens. This is a Euphemism for Bioweapons Proliferation.
Obviously, the best way to spare us from another pandemic is to immediately stop funding gain-of-function (GOF) research and get rid of all existing GOF organisms. Let all nations build huge bonfires and burn up their evil creations at the same time, while allowing other nations to inspect their biological facilities and records.
But the WHO in its June 2023 Bureau Text of the Draft Pandemic Treaty has a plan that is the exact opposite of this. In the WHO’s draft treaty, which most nations’ rulers appear to have bought into, all governments will share all viruses and bacteria they come up with that are determined to have “pandemic potential” — share them with the WHO and other governments, putting their genomic sequences online. No, I am not making this up. (See screenshots from the draft treaty below.) Then the WHO and all the Fauci’s of the world would gain access to all the newly identified dangerous viruses. Would hackers also gain access to the sequences? This pandemic plan should make you feel anything but secure.
Fauci, Tedros, and their ilk at the WHO, and those managing biodefense and biomedical research for nation states are on one side, the side that gains access to ever more potential biological weapons, and the rest of us are on the other, at their mercy.
This poorly conceptualized plan used to be called proliferation of weapons of mass destruction—and it is almost certainly illegal. (For example, see Security Council resolution 1540 adopted in 2004.) But this is the plan of the WHO and of many of our leaders. Governments will all share the weapons.
The Genomic Sequencing Conundrum
And governments are to commit to building biolabs that must include genomic sequencing. No explanation has been forthcoming about why each nation needs to install its own genome sequencing laboratories. Of course, they would sequence the many viruses that will be detected as a result of the pathogen surveillance activities nations must perform, according to the WHO treaty draft. But the same techniques can be used to sequence human genomes. The fact that the EU, UK, and US are currently engaged in projects to sequence about 2 million of their citizens’ genomes provides a hint they may want to collect additional genomes of Africans, Asians, and others.
This might fly as simply sharing state-of-the-art science with our less-developed neighbors. But it is curious that there is so much emphasis on genomics, compared to an absence of discussion about developing repurposed drugs for pandemics in the draft treaty or IHR amendments.
But we can’t forget that virtually all developed nations, in lockstep, restricted the use of safe generic hydroxychloroquine, ivermectin, and related drugs during the pandemic. In retrospect, the only logical explanation for this unprecedented action was to preserve the market for expensive patentable drugs and vaccines, and possibly to prolong the pandemic.
Genomes offer great potential profits, as well as providing the substrate for transhumanist experiments that could include designer babies.
The latest version (aka the WHO Bureau draft) of the pandemic treaty can be accessed here. I provide screenshots to illustrate additional points.

Draft pages 10 and 11:




The WHO Treaty Draft Incentivizes Gain-of-Function Research
What else is in the Treaty? Gain-of-Function research (designed to make microorganisms more transmissible or more pathogenic) is explicitly incentivized by the treaty. The treaty demands that administrative hurdles to such research must be minimized, while unintended consequences (aka pandemics) should be prevented. But of course, when you perform this type of research, leaks and losses of agents can’t always be prevented. The joint CDC-USDA Federal Select Agent Program (FSAP) which keeps track of research on potential pandemic pathogens collects reports of about 200 accidents or escapes yearly from labs situated in the US. The FSAP annual report for 2021 notes:
“In 2021, FSAP received 8 reports of losses, 177 reports of releases, and no reports of thefts.”
Research on deadly pathogens cannot be performed without risks both to the researchers and the outside world.
Draft page 14:

Vaccines Will be Rolled Out Speedily Under Abbreviated Future Testing Protocols
Vaccines normally take 10-15 years to be developed. In case you thought the COVID vaccines took too long to be rolled out (326 days from availability of the viral sequence to authorization of the first US COVID vaccine) the WHO treaty draft has plans to shorten testing. There will be new clinical trial platforms. Nations must increase clinical trial capacity. (Might that mean mandating people to be human subjects in out-of-the-way places like Africa, for example?) And there will be new “mechanisms to facilitate the rapid interpretation of data from clinical trials” as well as “strategies for managing liability risks.”
Draft page 14:


Manufacturer and Government Liability for Vaccine Injuries Must be “Managed”
Nations are supposed to use “existing relevant models” as a reference for compensation of injuries due to pandemic vaccines. Of course, most countries do not have vaccine injury compensation schemes, and when they do the benefits are usually minimal.
Is the US government’s program to be a model of what gets implemented internationally?
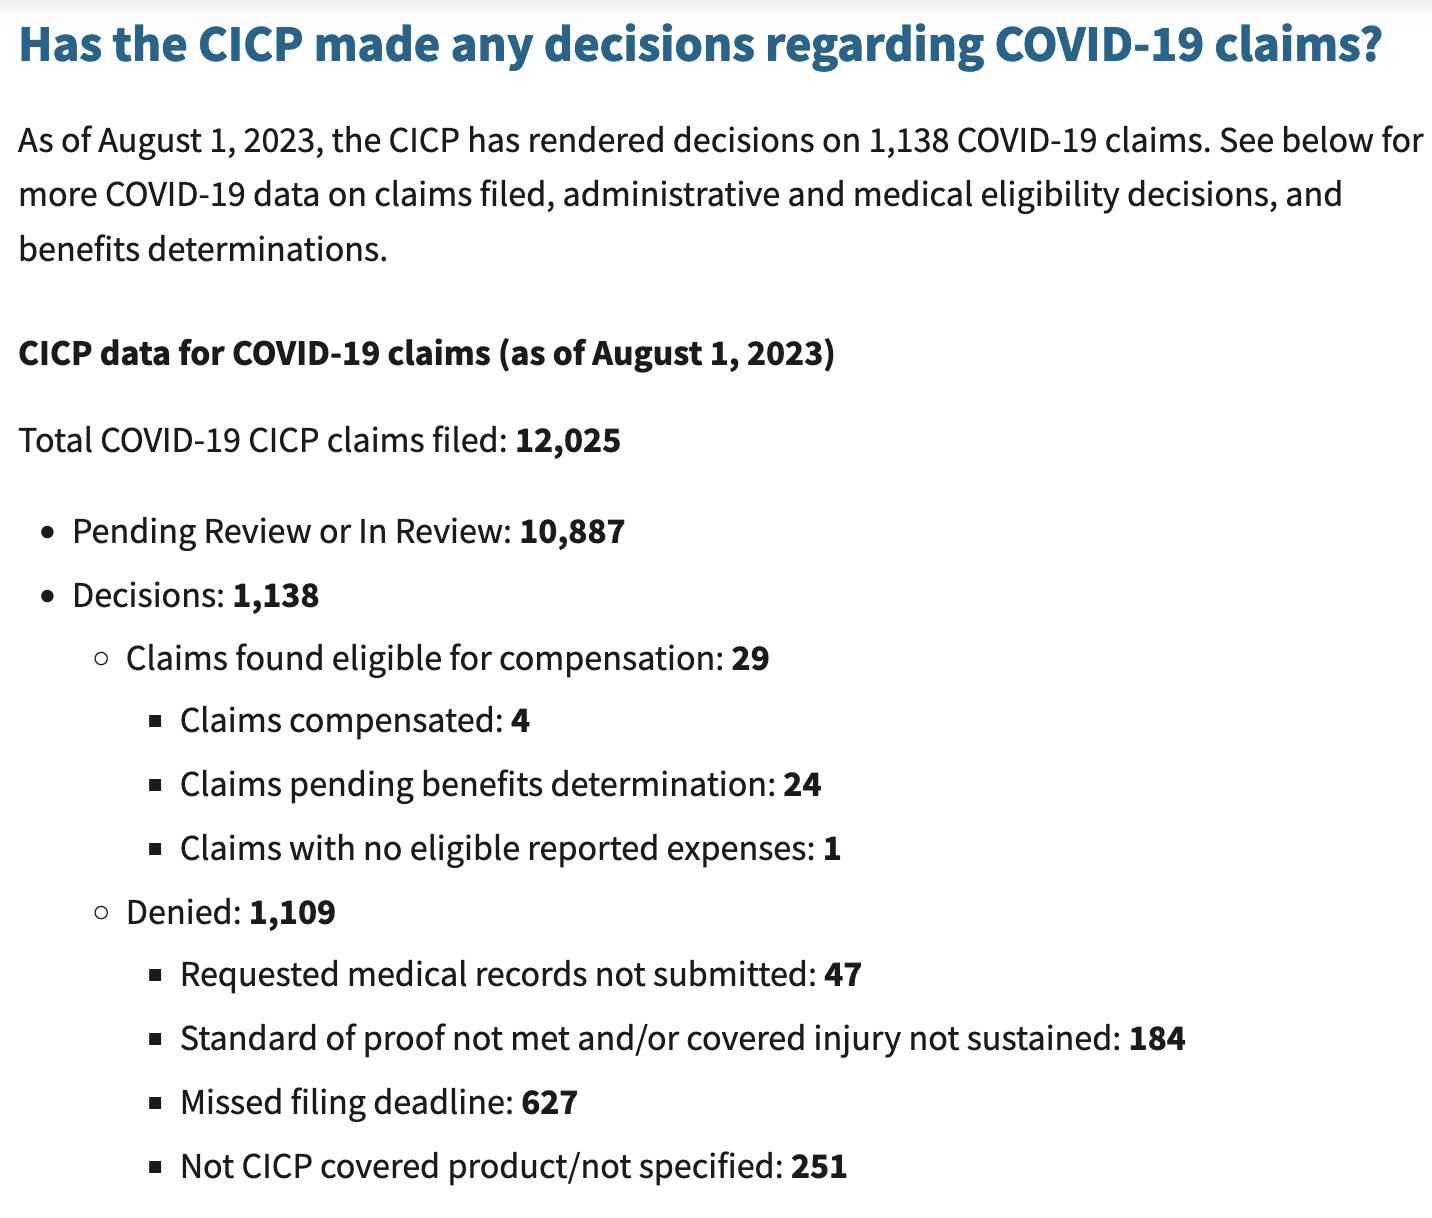
The US government scheme for injuries due to COVID pandemic products (the Countermeasures Injury Compensation Program or CICP) has compensated exactly 4 (yes, four) of the 12,000 claimants for COVID product-related injuries as of August 1, 2023. All pandemic EUA drugs and vaccines convey a liability shield to the government and manufacturers (this includes monoclonal antibodies, pre-licensure remdesivir, paxlovid, molnupiravir, some ventilators and all COVID vaccines) and the only avenue for injury compensation is through this program.
Slightly over 1,000 of the 12,000 claims have been adjudicated while 10,887 are pending review. Twenty claims were deemed eligible and await a benefits review. Benefits are only paid for uncovered medical expenses or lost income. A total of 983 people, or 98 percent of those whose claims have been adjudicated had their claims denied, many because they missed the brief one-year statute of limitations. Below are the latest data from this program:
The treaty draft also demands weakening the strict regulation of medical drugs and vaccines during emergencies, under the rubric of “Regulatory Strengthening.” As announced in the UK last week, where ‘trusted partner’ approvals will be used to speed licensure, this is moving toward a single regulatory agency approval or authorization, to be immediately adopted by other nations (p 25).

Next Up: Vaccines Developed in 100 Days
A plan to develop vaccines in 100 days and have them manufactured in 30 additional days has been widely publicized by the vaccine nonprofit CEPI, founded in 2017 by Sir Dr. Jeremy Farrar, who is now the WHO’s Chief Scientist. The plan has been echoed by the US and UK governments and received some buy-in from the G7 in 2021. This timeframe would only allow for very brief testing in humans, or would, more likely, limit testing to animals. Why would any country sign up for this? Is this what we the people want?
The plan furthermore depends on the vaccines only being tested for their ability to induce antibodies, which is termed immunogenicity, rather than being shown to actually prevent disease, at least for the initial rollout. My understanding of FDA regulation was that antibody levels were not an acceptable surrogate for immunity unless they had been demonstrated to actually correlate with protection. However, the FDA’s recent vaccine decisions have scrapped all that and vaccines are now being approved based on antibody titers alone. The FDA’s vaccine advisory committee has asked it for better indicators of efficacy than this, but the advisers have also voted to approve or authorize vaccines in the absence of any real measures showing that they work. I learned this because I watch the FDA vaccine advisory meetings and provide a live blog of them.
We all know how long it took for the public to become aware that the COVID vaccines failed to prevent transmission and only prevented cases for a period of weeks to months. The US government has still not officially admitted this, even though CDC Director Rochelle Walensky told CNN’s Wolf Blitzer the truth about transmission on August 6, 2021.
It is critical for the public to understand that safety testing can only be accomplished in human beings, as animals react differently to drugs and vaccines than humans do. Therefore, limited testing in animals would mean there was no actual safety testing. But testing vaccines in humans for only short periods is also unacceptable.
Testing vaccines during brief trials in humans (the Pfizer trials only followed a “safety subset” of trial subjects for a median of two months for safety) allowed COVID vaccines to be rolled out without the public being aware they could cause myocarditis and sudden deaths, most commonly in athletic young males in their teens and twenties, or a myriad of other conditions.
Finally, following this rapid manufacturing plan, thorough testing for potential failures in the manufacturing process could not be performed. With the current plan for far-flung, decentralized manufacturing facilities that are said to be necessary to achieve vaccine equity for all, there are nowhere near enough regulators who could inspect and approve them.
Will the WHO Respect Human Rights?
The need to respect “human rights, dignity, and freedom of persons” is embedded in the current International Health Regulations (IHR), as well as other UN treaties. However, the language guaranteeing human rights, dignity, and freedom of persons was peremptorily removed from the proposed IHR Amendments, without explanation. The removal of human rights protections did not go unnoticed, and the WHO has been widely criticized for it.
The WHO apparently is responding to these criticisms, and so the language guaranteeing human rights that was removed from the drafts of the International Health Regulations has been inserted into the newest version of the pandemic treaty.
Conclusions
As long predicted by science fiction, our bio- and cyber-scientific achievements have finally gotten away from us. We can produce vaccines in 100 days and manufacture them in 130 days–but there will be no guarantees that the products will be safe, effective, or adequately manufactured. And we can expect large profits but no consequences for the manufacturers.
Our genes can be decoded, and the fruits of personalized medicine made available to us. Or perhaps our genes will be patented and sold to the highest bidder. We might be able to select for special characteristics in our children, but at the same time, a human underclass could be created.
Our electronic communications can be completely monitored and censored, and uniform messaging can be imposed on everyone. But for whom would this be good?
New biological weapons can be engineered. They can be shared. Maybe that will speed up the development of vaccines and therapeutics. But who really benefits from this scheme? Who pays the price of accidents or deliberate use? Wouldn’t it be better to end so-called gain-of-function research entirely through restrictions on funding and other regulations, rather than encouraging its proliferation?
These are important issues for humanity, and I encourage everyone to become part of the conversation.
Dr. Meryl Nass, MD is an internal medicine specialist in Ellsworth, ME, and has over 42 years of experience in the medical field. She graduated from University of Mississippi School of Medicine in 1980.
U.S. Lawyers Reiterate Claim Ivermectin was never prohibited for treating COVID-19
Attorneys restate claim that FDA merely advised doctors against IVM for dying patients, but did NOT prohibit it.
BY JOHN LEAKE | COURAGEOUS DISCOURSE | AUGUST 14, 2023
Last November, I wrote the following post:
The Epoch Times recently reported an astonishing statement by a U.S. government lawyer in a federal court in Texas, where the FDA is being sued by Dr. Paul Marik of Virginia, Dr. Mary Bowden of Texas, and Dr. Robert Apter of Arizona. The three plaintiffs claim the FDA illegally prohibited them from prescribing the drug to their patients. At a November 1 hearing, U.S. lawyer Isaac Belfer argued for the defendant:
The cited statements were not directives. They were not mandatory. They were recommendations. They said what parties should do. They said, for example, why you should not take ivermectin to treat COVID-19. They did not say you may not do it, you must not do it. They did not say it’s prohibited or it’s unlawful. They also did not say that doctors may not prescribe ivermectin.”
If Belfer’s assertion is true, it raises a very urgent question: On what legal grounds did hospitals all over the United States refuse to administer ivermectin to severely ill COVID-19 patients, even when patients and their family members begged for the drug to be administered?
If ivermectin was not prohibited by the FDA or any other U.S. medical authority for treating COVID-19, why did Dr. Paul Marik’s hospital prohibit him from administering the drug to his dying patients? Why was Dr. Mary Bowden reported to the Texas Medical Board for disciplinary action when she prescribed it? Why did many pharmacists fear losing their licenses if they filled ivermectin prescriptions for treating COVID-19?
In our book, The Courage to Face COVID-19: Preventing Hospitalization and Death While Battling the Bio-Pharmaceutical Complex, Dr. McCullough and I document numerous instances of hospitals flatly refusing to grant the wishes of dying patients and their family members for ivermectin.
All these patients asked for was to be allowed to try the drug (FDA-approved for River Blindness, Elephantiasis, and Scabies) for COVID-19. The patients and their kin gladly indemnified the hospitals and arranged to have their independent primary care doctors deliver and administer the drug. Nevertheless:
- Hospital administrators absolutely refused to grant this wish.
- Hospital attorneys fought tooth and nail against using ivermectin to treat COVID-19 patients, doing everything in their power to challenge patient lawsuits and appeal court orders to administer the drug.
- Even when hospital doctors acknowledged that the patients were dying, they insisted it was better to let the disease take its natural course rather than allow patients to try ivermectin.
- Even when patients’ families succeeded in getting a court orders to administer the drug, many hospitals still refused, even at the risk of being held in contempt of court.
Several readers have told us that our chapters covering this shameful scandal— Chapters 38: Begging for the Wonder Drug and Chapter 40: Graduating into Eternity—are horrifying beyond belief.
Now we hear U.S. government lawyers arguing in court that the FDA never prohibited using ivermectin to treat COVID-19 patients, but merely recommended not using it. This indicates that hospitals had no legal grounds for denying sick patients a drug that could have helped them. How is withholding medicine from a sick man any different from withholding a life ring from a man who has fallen overboard in high seas?
For families who watched their loved ones slip away after being denied the right to try ivermectin, U.S. attorney Isaac Belfer’s statement may be interpreted as declaring open season for lawsuits against hospital administrators and doctors.
After I wrote the above post, I exchanged an e-mail with Dr. Marik in which he expressed profound discouragement about U.S. Judge Jeffrey Vincent Brown’s granting of the government’s Motion to Dismiss the case on the grounds of sovereign immunity.
Nevertheless, Dr. Marik and his co-plaintiffs, Robert L. Apter and Mary Talley Bowden, appealed the dismissal and are now being heard before a three-judge panel of the 5th U.S. Circuit Court of Appeals.
Once again, attorneys for the U.S. government are in the hot seat about their mendacious claims about the FDA’s directive to doctors and hospitals against prescribing or administering Ivermectin, either to outpatients or to patients dying in hospital.
Instead of acknowledging the obvious reality that the FDA did indeed DIRECT doctors and hospitals against administering Ivermectin, U.S. attorneys continue to insist that the FDA’s communiques were mere advice.
This preposterous argument not only overlooks the plain language of the FDA’s communiques, it also overlooks the salient fact that numerous doctors (like Paul Marik) were fired from their jobs for administering ivermectin to their dying patients, and the fact that many State Medical Boards revoked doctors’ licenses for doing the same. If these punitive actions taken against doctors were NOT based on the FDA’s directives, on what grounds were they taken?
As was just reported by Just the News columnist Greg Piper:
The 5th Circuit panel seemed skeptical of Civil Division Appellate Attorney Ashley Honold’s argument that the FDA’s “informational statements” against ivermectin, including its conflation of human and animal dosages, were “merely quips” about reported problems after “self-medicating” rather than “prohibit[ing] anyone” from using ivermectin.
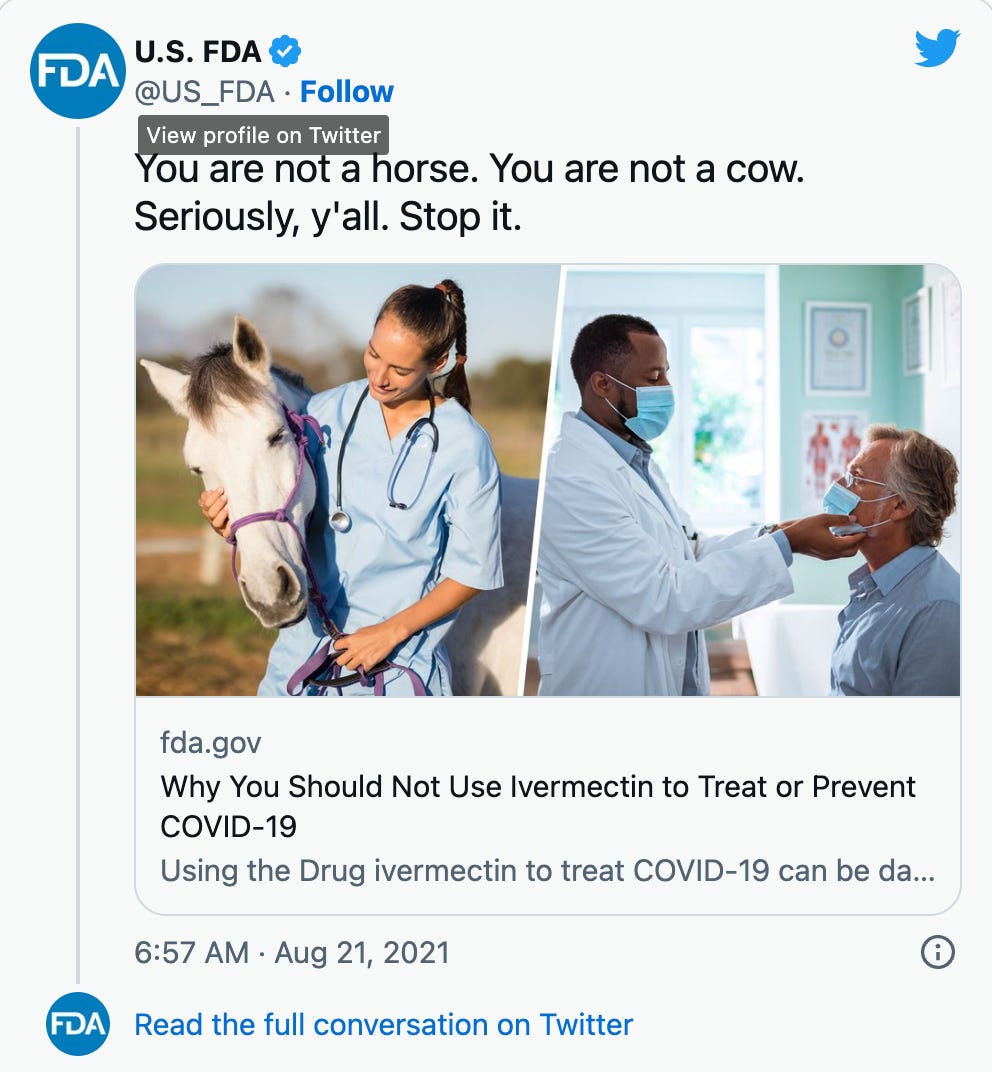
Judge Jennifer Walker Elrod cited the phrase “Stop it” in the agency’s viral “You are not a horse” post on X, then known as Twitter. “If you were in English class, they would say that was a command. … That is different than ‘we’re providing helpful information,'” she told Honold.
Readers of this Substack will probably agree with my sentiment that enough is enough of lying and obfuscating U.S. government agency officials and their mercenary lawyers. It’s time for the grown-up, reasonable citizenry of this country to join Marik, Bowden, et al. in suing the pants off the FDA and other U.S. agencies against whom there is a preponderance of evidence that they have unlawfully interfered with the doctor-patient relationship and committed negligent homicide, fraud, and concealment.
Cry havoc and let slip the plaintiffs’ attorneys! Sue the FDA; sue doctors and hospital administrators; and sue the medical boards. Let them pay for the damages they have inflicted on the families of patients who were denied ivermectin until their last breaths. Let them pay for the massive damage and distress they have caused for courageous doctors like Paul Marik and his colleagues who tried to help their patients.
Featured Video

Deep Dive Intel Briefing 6/20/2026 Lt Col Daniel Davis
or go to
Aletho News Archives – Video-Images
From the Archives
Because no animal reservoir has been found for SARS-CoV-2, it cannot properly be termed a zoonosis.* Should we call it a labnosis? And what does that mean?
By Meryl Nass, MD | July 12, 2021
After a year and a half of seeking but not finding SARS-2 in any wildlife anywhere (apart from domesticated or zoo animals that appear to have caught it from humans) is it time to say, yes, it didn’t just escape from a lab. It was created, built, assembled in a lab. Or many labs
Coronavirus scientists have been constructing new viruses out of bits and pieces of other viruses for a long time.
Why did they do it? … continue
Blog Roll
 Aletho News
- Deep Dive Intel Briefing 6/20/2026 Lt Col Daniel Davis
- The Targeted Assassination of Studies Showing Vaccines Cause Injury
- BMJ Probe Into Excess Mortality Study Drags On for Two Years With No Resolution
- Securing Peace with Iran Compels Trump to Divorce Israel
- Old Iraq war architects rise up to wag finger at Trump’s Iran deal
- Strait of Hormuz closed over Israeli aggression on Lebanon
- Keir Starmer arson mysteries multiply
- IRAN WAR “ON PAUSE” – w/ Prof. Glenn Diesen
- Zelensky threatens to attack Belarus
- UK to send Ukraine 150,000 drones
- If Americans Knew
- Israelis Invaded Lebanon And Then Cried Victim When Their Soldiers Got Killed
- FARA Docs: Israel is Spying On Millions Of Christian Americans In Their Churches
- Why US presidents from both parties end up cursing Benjamin Netanyahu
- Israel Asked Facebook to Censor Iran War Content, Internal Documents Show
- Deaths in Gaza undercounted, possibly by 100s of thousands; “Psychopath” Ben-Gvir talks trash – Daily Update
- UNICEF: “Trauma is woven into the very fabric of childhood in Gaza”
- 15 articles a day: The extent of the Israeli army’s media interference
- Greek Orthodox Patriarchate denounces Israeli seizure of church land in Jerusalem
- How Hillel International uses antisemitism training and ‘campus climate’ concerns to attack Palestine solidarity
- Old Iraq war architects rise up against Trump’s Iran deal
- No Tricks Zone
- German Wind Turbines Face Regulatory Shutdown Due To Excessive Noise
- New Study: Chile’s Relative Sea Level Was 3.2 Meters Higher Than Today During The Mid-Holocene
- Beyond The Pitch: Why FIFA’s World Cup Is One Of Humanity’s Best Investments
- Climate Alarmists Now Using Natural Phenomena To Support Their Claims
- New Study: Significant CO2 Fluxes From Non-Volcanic Sources Are Largely Neglected In Carbon Budgets
- Women Climate Scientists Being Harassed, Insulted By Skeptics, Claims Berkeley Earth Researcher
- Germany’s Longterm Spring Climate Data Show “No Climate Trend”
- New Study: Solar Photovoltaic, Wind Power Fail To Meet Annual Energy Demands 62% Of The Time
- Germany’s Die Welt: “Too Much Is Too Much” … Green Energies Are Cannabalizing Each Other!
- Germany’s Ecological Holocaust… Once Fairy Tale Forests Getting Cleared For Wind Turbines
 Aletho News
