With President Biden succumbing to the CIA’s demand to continue keeping the CIA’s records relating to the Kennedy assassination secret, the question naturally arises: What is the CIA still hiding? (See my blog post of yesterday entitled “Surprise! Biden Continues the CIA’s JFK Assassination Cover-Up.”)
To understand what they are still hiding and why they are still hiding it, it’s necessary to go back to the 1990s during the era of the Assassination Records Review Board — and even further back than that to November 22, 1963 — the day that Kennedy was assassinated.
People often say that if the CIA and the Pentagon had orchestrated the assassination of President Kennedy, someone would have talked by now.
That’s just not true. When it comes to murder, people don’t talk. They know that if they do talk, they run the risk of themselves being murdered, maybe their families too. People who participate in murder schemes know that they had better keep their mouths shut or else.
One example is Mafia figure Jimmy Hoffa. We still don’t know who killed Hoffa. That’s because no one talked. Another example is Johnny Roselli, the liaison in the CIA-Mafia partnership to assassinate Cuban leader Fidel Castro. We still don’t know who murdered Roselli. No one has ever talked.
People who talk also run the risk of being prosecuted because there is no statute of limitations for murder. A good recent example is real-estate heir Robert Durst. He was recently convicted of murdering a person twenty-one years ago.
So, it was always a safe bet that the CIA and the Pentagon would be able to keep their regime-change operation in Dallas sealed in secrecy.
However, not so with respect to the fraudulent autopsy that the Pentagon carried out on President Kennedy’s body on the evening of the assassination. When the ARRB released people who had participated in the autopsy during the 1990s, they talked.
The problem that the plotters had, however, is that in order to carry out this part of the cover-up, they had to enlist the assistance of many people within the vast national-security establishment who played no role in the assassination. Since all those people were innocent and mostly unwitting participants to the cover-up, they didn’t have the same incentive to stay quiet as the people who knowingly participated in the assassination itself.
The military did its best to keep everyone quiet by telling the autopsy participants that what they were doing was classified. Everyone in the military knows what that means — people are expected to take classified secrets to the grave with them. Participants to the autopsy were required to sign written secrecy oaths. They were also threatened with court martial or criminal prosecution if they ever revealed what they had done or seen.
As I pointed out in The Kennedy Autopsy, the scheme for a fraudulent autopsy was actually set into motion at Parkland Hospital in Dallas. Immediately after Kennedy was declared dead, the Dallas County Medical Examiner, Dr. Earl Rose, announced his intent to conduct an autopsy on the president’s body, as Texas law required. That was when a team of armed Secret Service agents, brandishing guns, told Rose in no uncertain terms that they would not permit him to do the autopsy. Forcing their way out of Parkland Hospital, they took the body to Dallas’s Love Field, where new President Lyndon Johnson was waiting for it. Johnson then took the body back with him to Andrews Air Force Base in Maryland, where he delivered it into the hands of the military.
Although the mainstream media always treated all this as normal, given the dominant role that the national-security establishment was playing in Cold War America, it was actually quite bizarre and aberrant. The military never had any jurisdiction or legal authority to conduct the autopsy. At that time, killing a president was not a federal crime. The United States was not at war with any nation state. Kennedy was not killed on the field of battle. His killing was a straight murder case under Texas state law. Any criminal prosecution for the assassination would take place in Dallas. A genuinely honest autopsy would be a critically important part of that criminal prosecution, especially since a sharp team of criminal-defense lawyers would inevitably be defending the accused.
The military was mostly, but not entirely, able to keep its fraudulent autopsy secret for some 30 years, until the ARRB began releasing people who had participated in the autopsy from their vows of secrecy. As the ARRB began forcing the military to release its records relating to the autopsy, the dam of secrecy surrounding the autopsy broke wide open. That’s when the fraud became apparent. That’s why the JFK Records Act was such a nightmare for the Pentagon and the CIA. If it hadn’t been for that law, there is no doubt that the military’s fraudulent autopsy would still be shrouded in secrecy today.
What the Pentagon and the CIA learned from the era of the ARRB is that the community of assassination researchers is composed of some very smart people. By analyzing the evidence that the ARRB was succeeding in getting released, assassination researchers were able to put together the pieces of the puzzle that established a fraudulent autopsy, along with lots of other pieces of circumstantial evidence establishing that what occurred on November 22, 1963, was a highly sophisticated national-security state regime-change operation.
The leading figure in this endeavor was Douglas Horne, who served on the ARRB staff. Anyone who reads Horne’s five-volume book Inside the Assassination Records Review Board will inevitably conclude that the autopsy that the military conducted on the Kennedy’s body a few hours after the assassination was fraudulent to the core.
At the risk of belaboring the obvious, there is no innocent explanation for a fraudulent autopsy being conducted on President Kennedy’s body, especially given that the scheme for a fraudulent autopsy was launched at the moment Kennedy was declared dead.
It stands to reason that if a government agency is being forced to reveal records relating to a regime-change operation, that agency is going to keep the most incriminating evidence secret for as long as possible. We still don’t know what the CIA is still hiding, but we can safely assume that there is a good reason why the CIA does not want to let those super-smart assassination researchers get a hold of it.
That’s why the national-security establishment will fight tooth and nail for permanent secrecy on their remaining JFK assassination-related records. Oh, the Pentagon and the CIA will most likely authorize Biden and the National Archives to release some innocuous records for appearance’s sake. But make no mistake about it: They will make certain that Biden, the National Archives, and all future presidents comply with their demand for permanent secrecy on what they need to hide on a permanent basis.
An FDA vaccine advisory panel on Tuesday voted unanimously 17-0 in favor shooting up kids aged 5-11 with Pfizer’s experimental mRNA injection with panelist Dr Eric Rubin stating, “we’re never going to learn about how safe this vaccine is unless we start giving it.”
The panel voted in favor of experimenting on tens of millions of helpless children with zero long-term data on side effects because 94 children between 5 and 11 have died with COVID-19 (they claimed “of”) and “all have names. All of them had mothers,” to quote the emotional gobbledegook uttered by panelist Patrick S. Moore.
“To me, it seems that it is a hard decision but a clear one,” said Patrick S. Moore, a University of Pittsburgh microbiologist and committee member. He noted that 94 children between 5 and 11 have died of covid-19, and “all have names. All of them had mothers.”
Members of the FDA’s vaccine-advisory panel supported Moderna’s booster dose even though the evidence for it was from a small study and had mixed results.
“It’s more a gut feeling rather than based on really truly serious data,” said Patrick Moore, a member of the committee and a professor of molecular genetics and biochemistry at the University of Pittsburgh School of Medicine. “The data itself is not strong, but it is certainly going in the direction that is supportive of this vote.”
To review: We have now had ten months of mass vaccination against SARS-CoV-2. Nearly 7 billion doses have been administered worldwide. This unprecedented campaign has not eradicated Corona; it has not even suppressed infections. Instead, case statistics have ballooned almost everywhere. While the vaccinated appear to enjoy some protection against severe outcomes, skyrocketing transmission means most countries have seen little benefit, on balance, from their universal vaccination campaigns. The most pressing question has become, simply: What is going on?
I’ve explored a few different possibilities. First, there seems to be a Marek Effect at work. We might imagine that all viruses have an optimal level of population-wide virulence – an advantageous degree of aggression at which they can spread effectively, while not driving their hosts underground too soon. Certain Delta sub-strains, previously punished for their excessive aggression in unvaccinated populations, have likely been favoured by the vaccines, which reduce symptoms in the vaccinated without preventing infection for more than a few months. Our vaccines reduced the average virulence of SARS-2, and the virus adapted to reattain the prior, optimal balance.
But the virus and its interactions with human hosts constitute a complex system. In such systems, it is very unlikely that any effect can be put down to a single cause. The Public Health England data provide powerful reasons to suspect that the vaccines may be compromising immunity to SARS-2 via Original Antigenic Sin. This is not a crazy internet fantasy, but a well-observed limitation of human immunity. It is the primary reason that respiratory viruses like influenza return again and again. Despite multiple reinfections across the whole population, we are never quite immune to the flu, because its strategy is to exploit the way our immune systems learn.
The mechanisms of Original Antigenic Sin are not fully understood, but we have a rough idea of what might be happening. When a virus infects your body for the first time, your naive memory B cells imprint on specific virus proteins, or antigens, presented to them. These B cells then become either memory B cells or plasma cells. Forever after, they specialise in producing antibodies against those specific antigens. When a slightly mutated form of the virus arrives, these memory B-cells begin pouring forth the antibodies they learned to produce during the first infection. These antibodies bind to multiple epitopes on the virus particles, and in the process they give the slower-moving naive B-cells little chance to learn about any new, mutant virus features.
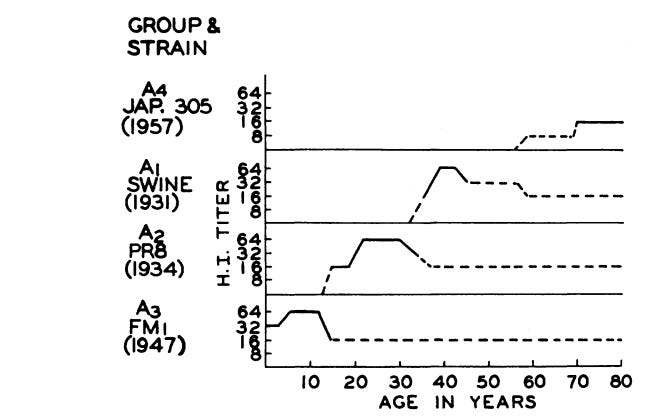
Original Antigenic Sin was most influentially described by Thomas Francis in 1960. He noted that, regardless of whatever influenza A strains were in circulation, subjects tended to have dominant antibody responses to the strains that were current in their early childhood:
The antibody of childhood is largely a response to … the virus causing the first Type A influenza infection of the lifetime. As the group grows older and subsequent infections take place, antibodies to additional families of virus are acquired. But … the antibody which is first established continues to characterize that cohort of the population throughout its life. The antibody forming mechanisms have been highly conditioned by the first stimulus, so that later infections with strains of the same type successively enhance the original antibody to maintain it at the highest level at all times in that age group. The imprint established by the original virus infection governs the antibody response thereafter. This we have called the doctrine of original antigenic sin.
An important consequence of this childhood conditioning, is that different age cohorts within the population have overlapping or layered immunity to different influenza strains. This is an important if subtle aspect of our population-wide immunity to influenza A. It looks like this:
As older cohorts die, their immunity to older strains dies with them. These old strains, long suppressed, are then positioned to return, for very few human immune systems remember them any longer. Francis believed this was the mechanism underlying periodic cycles of pandemic influenza. The 1957 influenza pandemic, for example, featured a strain of flu against which only the oldest cohorts – those in their 70s – had specific antibodies. As these “immunological veterans” disappeared, this older, long-suppressed type of influenza was free to return and cause another pandemic event.
In conclusion, Francis proposed that optimised influenza vaccines might be administered to children before their first infection. He envisioned vaccines designed to confer immunity against “known or anticipated recurrent strains” and hoped that “In this manner the original sin of infection could be replaced by an initial blessing of induced immunity.”
Strategic vaccination conferring immunity against likely future strains is of course exactly the opposite of our current efforts to give every last living human multiple vaccinations against an extinct strain of SARS-2.
*
The existence of Original Antigenic Sin has been confirmed by generations of research, and the literature is full of curious findings. A major reason flu shots don’t work, for example, is that they are powerless to redirect adult immune systems against novel influenza strains. Most people who get flu shots are adults, with immune systems long since primed by childhood infection. Hence this old Lancet case study of influenza outbreaks among boys at Christ’s Hospital in Sussex in the 1970s:
In each outbreak, the protective effect of inactivated influenza-A vaccine was limited to those boys, not already immune, who were vaccinated for the first time with the most up-to-date strain. Revaccination with the same strain did not increase the degree of protection, and revaccination with a later strain did not afford protection against subsequent challenge.
The flu vaccines, in other words, work great if you’ve never had the flu before. Otherwise they don’t do anything.
And consider these remarks, from a 2005 article in Nature Medicine:
It is often difficult to further increase antibody levels, specificity and the quality of the immune response in individuals who have been repeatedly immunized through either vaccination or recurrent exposure to infectious agents or cross-reacting microbial antigens. This has been a particular concern for aging adults in the context of the antigenic drift of influenza virus, in view of their annual exposure to antigens of new but related influenza variants through either infection or vaccination. After exposure to a new but cross-reacting antigenic variant, such individuals may respond by producing antibodies that are primarily directed at antigens characterizing influenza viruses encountered during earlier epidemics.
The authors go on to write that the “impact” of Original Antigenic Sin “on protection is far from established,” noting earlier research showing substantial all-cause mortality reductions from flu shots. Later work, though, has shown that the mortality reduction of influenza vaccines is largely an illusion of selection effects. For a variety of reasons, those most likely to die of influenza are far less likely than healthier groups to be vaccinated.
Original Antigenic Sin has been famously implicated in dengue fever. This is considered to be an extreme case of the phenomenon, with “considerable bearing on vaccine strategies.” Here the conclusions are ominous and full of implications for our own situation:
Once a response has been established, it is unlikely that repeat boosting will be able to change its scope, meaning that balanced responses against the four virus serotypes will need to be established with the first vaccine dose.
The danger is that immunity to one strain alone may lead to permanently impaired immune response to the three other serotypes, causing worse and longer illness.
*
Influenza had been infecting humans for generations before anybody came up with the notion of influenza vaccines. Despite the efforts of public health authorities everywhere, most people catch the flu before they are ever vaccinated, and so flu shots have little opportunity to undermine population-wide immunity to influenza A.
The complex system constituted by SARS-CoV-2 and its interactions with the human immune system, on the other hand, remains barely understood. In chasing an empty fantasy of herd immunity, authorities are denying human populations everywhere the opportunity to develop the layered, population-wide resistance against successive SARS-2 strains that is the foundation of our immunity against other respiratory viruses. Aside from the minority that have managed to recover from natural infection before the vaccinators got to them, most humans will have their crucial, primary immune response conditioned by the spike protein of SARS-2 in its vintage 2020 configuration.
It is a near certainty that this immunity will attenuate antibody responses to the spike protein of current and future variants, forever. Mutant spike proteins will increasingly escape vaccine-conferred immunity, and breakthrough infections will elicit only partial response to the new epitopes. Insofar as the data also suggest that our vaccines will attenuate immunity to other virus proteins beyond spike, mass vaccination will lead to ever more volatile waves of infection – in exchange for limited and fading protection against severe outcomes.
The most dangerous thing to do, at this point, would be to vaccinate children. The virus is not a threat to them, and if they are infected by the new forms of SARS-2 that are sure to emerge every winter, we will begin to establish – through them and the as yet unvaccinated – the layered immunity that is the only way of coming to terms with SARS-2 in the longer term. As long as the vaccinators are permitted to continue their radical and increasingly insane campaign, though, nothing will improve. Indeed, their policies threaten to bring about a semi-permanent pandemic state for generations to come.
Mortality data tells us information about deaths in Australia and is usually released every 6 weeks. For an unexplained reason, the latest data is over 15 weeks overdue.
As Government becomes more and more powerful, anyone who challenges the current policies is smeared and censored. The legacy media happily parrots the propaganda, afraid of losing government funding.
Unreliable, intermittent wind and solar energy will leave Australian families sitting in the dark without coal-fired power to back them. ‘Renewables’ only farm taxpayer money, not energy.
There has been major pushback against a Texas state education official who said that if schools are adhering to a new state law that mandates teaching alternative points of view on controversial issues having a course and a book on the holocaust, for example, would suggest providing material that reflects other interpretations of that historical event. The comment came from a Texas school district administrator named Gina Peddy in the Carroll Independent School District in Southlake, which is in the Dallas-Fort Worth area, who was in a training session explaining to teachers her directive regarding which books can be available in classroom libraries. She told teachers that if they have books about the Holocaust in their classrooms, they should also have books that offer “opposing” or “other” viewpoints on the subject.
Reportedly a staff member who was present secretly made an audio recording of the training session which was then shared with NBC News, which broke the story.
The Texas law was and is intended to lessen the impact of the current “woke” campaign by progressive educators to rewrite American and international history to reflect the dark side, notably by emphasizing issues like slavery and oppression of minorities. Texas legislators insist, not unreasonably, that presenting an essentially negative view of American history as envisioned by Critical Race Theory (CRT) must be balanced by having a curriculum that also includes discussion of the many positive achievements of the United States of America. In the recording, Peddy, the school district’s executive director of curriculum and instruction, told the teachers that the new law applies to any “widely debated and currently controversial” issues. She was quoted as saying “And make sure that if you have a book on the Holocaust, that you have one that has an opposing, that has other perspectives.”
Predictably, on such a hot wire issue Peddy has had little or no support from her peers either locally or in the education establishment. The school district Superintendent Lane Ledbetter posted on Facebook an “apology regarding the online article and news story.” He said Peddy’s comments were “in no way to convey that the Holocaust was anything less than a terrible event in history. Additionally, we recognize there are not two sides of the Holocaust. We also understand this bill does not require an opposing viewpoint on historical facts.”
Clay Robison, a spokesman for the Texas State Teachers Association, responded “We find it reprehensible for an educator to require a Holocaust denier to get equal treatment with the facts of history. That’s absurd. It’s worse than absurd. And this law does not require it.” Republican state Senator Bryan Hughes, who wrote the bill that became the law, denied that anyone should come up with alternative views on what he called matters of “good and evil” or to remove books that offer only one perspective on the Holocaust.
Jews in Peddy’s school district and elsewhere in both Texas and nationally have inevitably also risen to the bait, denouncing any attempt made to challenge what they view as an issue fundamental to their understanding of their place in the world and in history. One Jewish former student Jake Berman asserted that “The facts are that there are not two sides of the Holocaust. The Nazis systematically killed millions of people.”
Ledbetter, Robison and Hughes should perhaps consider that they are suggesting that their new law should only apply on “controversial” racial issues, not on other historical developments and it is curious that educated people should consider a multi-faceted transnational historical event that has inter alia a highly politicized context a “fact.” The holocaust narrative in and of itself is the creation of men and women after the fact with an agenda to justify the creation and support for the State of Israel and should be subject to the same inquiry as any other facet of the Second World War and what came after.
The tale of “the holocaust” is essentially a contrived bit of history that serves a political objective wrapped up in what purports to be a powerful statement regarding man’s inhumanity to man. Jewish groups generally speaking consider the standard narrative with its highly questionable six million dead, gas chambers, extermination camps, and soap made from body fat to be something like sacred ground, with its memorialization of the uniqueness of Jewish suffering. Serious scholars who have actually looked at the narrative and the numbers and sequences of events are not surprisingly skeptical of many of the details.
As a first step, it is helpful to look at controversial Professor Norman Finkelstein’s carefully documented book The Holocaust Industry: Reflections on the Exploitation of Jewish Suffering. Finkelstein, to be sure, believes there was something like a genocide of European Jews and even lost some family members due to it. He does not, however, necessarily believe many of the details provided by the standard narrative and official promoters of that story to include the numerous holocaust museums. In his view, powerful interests have hijacked “the Holocaust,” and use it to further their own objectives. He wrote “Organized Jewry has exploited the Nazi holocaust to deflect criticism of Israel’s and its own indefensible policies. Nazi genocide has been used to justify criminal policies of the Israeli state and US support for these policies.”
And there is also a money angle, as there often is. Per Finkelstein, Jewish organizations in the US have also exploited the situation of the dwindling number of aging holocaust survivors to extort “staggering sums of money from the rest of the world. This is not done not for the benefit of needy survivors but for the financial advantage of these organizations.”
As taking courses in the holocaust are mandated in the public school systems of twenty states (and soon to be more due to pressure from local Jewish groups) and is used to validate the billions of US taxpayer dollars given annually to the state of Israel it would seem that supporters of the narrative should have the confidence as well as sufficient integrity to defend their product. But that is, of course, not the case. They would prefer to have their chosen narrative unchallenged, raising the usual claims of anti-Semitism and “holocaust denial” to silence critics. One of the “textbooks” frequently used in public schools that mandate holocaust education is Night by Elie Wiesel, whom Finkelstein has dubbed “the high huckster of the holocaust.” “Night” claims to be autobiographical but is full of errors in time and place. It is at least in part a work of fiction. Similarly, the “Diary of Anne Frank” was published after editing by her survivor father and parts of it have been challenged.
As a general rule, contentious issues where advocates attempt to silence opponents by claiming that what they are promoting is based on fact and cannot be challenged should be challenged. In Europe, powerful Jewish constituencies have even made it illegal to criticize or deny the holocaust narrative. In America, that day may soon be coming as Jewish groups increasingly seek to criminalize questioning of the factual basis of the holocaust as well as any criticism of Israel.
Philip M. Giraldi, Ph.D., is Executive Director of the Council for the National Interest, a 501(c)3 tax deductible educational foundation (Federal ID Number #52-1739023) that seeks a more interests-based U.S. foreign policy in the Middle East. Website is https://councilforthenationalinterest.orgaddress is P.O. Box 2157, Purcellville VA 20134 and its email is inform@cnionline.org
Where to even begin with the FDA’s preposterous risk-benefit analysis of Pfizer’s mRNA COVID-19 “vaccine” in children ages 5 to 11?
Let’s start with my bona fides. I have a year of undergraduate statistics at one of the best liberal arts colleges in America (Swarthmore). I have a year of graduate statistics at the masters program rated #1 for policy analysis (UC Berkeley). And I have a Ph.D. in political economy from one of the top universities in the world (University of Sydney). My research focus is on corruption in the pharmaceutical industry so I’ve read scientific studies in connection with vaccines nearly every day for 5 years. Earlier in my career I worked professionally tearing apart shoddy cost-benefit analyses prepared by corporations that were trying to get tax breaks, contracts, and other concessions from local government. Suffice it to say I’ve thought a lot about risk-benefit analysis and I’m better equipped than most to read one of these documents.
The FDA’s risk-benefit analysis in connection with Pfizer’s Emergency Use Authorization (EUA) application to inject children ages 5 to 11 with their COVID-19 vaccine is one of the shoddiest documents I’ve ever seen.
Let’s take it from the top:
🚩 COVID-19 rates in children ages 5 to 11 are so low that there were ZERO cases of severe COVID-19 and ZERO cases of death from COVID in either the treatment (n= 1,518) or control group (n= 750). So any claims you see in the press about the Pfizer vaccine being “90% effective” in children are meaningless because they are referring to mild cases from which children usually recover quickly (and then have robust broad spectrum immunity). So there is literally no emergency in this population for which one could apply for Emergency Use Authorization. Pfizer’s application should be dead on arrival if the FDA actually followed the science and their own rules. We will return to this topic below.
🚩 Pfizer’s clinical trial in kids was intentionally undersized to hide harms. This is a well known trick of the pharmaceutical industry. The FDA even called them out on it earlier this summer and asked Pfizer to expand the trial and Pfizer just ignored them because they can. (Pfizer fudged it by importing data from a different study but this other study only monitored adverse outcomes for 17 days so if anything the new data polluted rather than clarified outcomes). To put it simply, if the rate of particular adverse outcome in kids as a result of this shot is 1 in 5,000 and the trial only enrolls 1,518 in the treatment group then one is unlikely to spot this particular harm in the clinical trial. Voilà “Safe & Effective(TM)”.
🚩 Pfizer only enrolled “participants 5-11 years of age without evidence of prior SARS-CoV-2 infection.” Does the Pfizer mRNA shot wipe out natural immunity and leave one worse-off than doing nothing as shown in this data from the British government? Pfizer has no idea because children with prior SARS-CoV-2 infection were excluded from this trial. This was by design. Toxic polluters have learned to not ask questions that they do not want the answers to, lest they wind up staring at their own smoking gun in a future court case.
“What the British are saying is they are now finding the vaccine interferes with your body’s innate ability after infection to produce antibodies against not just the spike protein but other pieces of the virus. Specifically, vaccinated people don’t seem to be producing antibodies to the nucleocapsid protein, the shell of the virus, which are a crucial part of the response in unvaccinated people. This means vaccinated people will be far more vulnerable to mutations in the spike protein EVEN AFTER THEY HAVE BEEN INFECTED AND RECOVERED ONCE (or more than once, probably). It also means the virus is likely to select for mutations that go in exactly that direction because those will essentially give it an enormous vulnerable population to infect. And it probably is still more evidence the vaccines may interfere with the development of robust long-term immunity post-infection.”
🚩 Did Pfizer LOSE CONTACT with 4.9% of their clinical trial participants? The FDA risk-benefit document states: “Among Cohort 1 participants, 95.1% had safety follow-up ≥2 months after Dose 2 at the time of the September 6, 2021 data cutoff.” So what happened with those 4.9% who did not have safety follow-up 2 months after Dose 2? Were they in the treatment or control group? We have no idea because Pfizer isn’t saying. Given the small size of the trial, failing to follow up with 4.9% of the participants potentially skews the results.
🚩 The follow up period was intentionally too short. This is another well-know trick of the pharmaceutical industry designed to hide harms. Cohort 1 appears to have been followed for 2 months, cohort 2 was only monitored for adverse events for 17 days. Many harms from vaccines including cancer and autoimmune disorders take much longer to show up. As the old saying goes, “you can have it quick or you can have it done right, but you cannot have both.” Pfizer chose quick.
🚩 The risk-benefit model created by the FDA only looks at one known harm from the Pfizer mRNA shot — myocarditis. But we know that the real world harms from the Pfizer mRNA shot go well beyond myocarditis and include anaphylaxis, Bell’s Palsy, heart attack, thrombocytopenia/ low platelet, permanent disability, shingles, and Guillain-Barré Syndrome (GBS) to name a few. Cancer, diabetes, endocrine disruption, and autoimmune disorders may show up later. But the FDA does not care about any of that because they have a vaccine to sell so they just ignore all of those factors in their model.
🚩 Pfizer intentionally wipes out the control group as soon as they can by vaccinating all of the kids who initially got the placebo. They claim that they are doing this for “ethical reasons”. But everyone knows that Pfizer’s true aim is to wipe out any comparison group so that there can be no long term safety studies. Wiping out the control group is a criminal act and yet Pfizer, Moderna, J&J, and AZ do this as standard practice with the blessing of the FDA/CDC.
🚩 Given all of the above, how on earth did the FDA claim any benefits at all from this shot? You should probably sit down for this part because it’s a doozy! Here’s the key sentence:
Vaccine effectiveness was inferred by immunobridging SARS-CoV-2 50% neutralizing antibody titers (NT50, SARS-CoV-2 mNG microneutralization assay).
Wait, what!? I’ll explain. There were ZERO cases of severe COVID-19 in the clinical trial of children ages 5 to 11. So Pfizer and the FDA just ignored all of the actual health outcomes (they had to, there is no emergency, so the application is moot). INSTEAD Pfizer switched to looking at antibodies in the blood. In general, antibodies are a poor predictor of immunity. And the antibodies in the blood of these 5 to 11 year old children tell us nothing because again, there were zero cases of severe COVID-19 in this study (none in the treatment group, none in the control group). So Pfizer had to get creative! What they came up with is “immuno-bridging”. Pfizer looked at the level of antibodies in the bloodwork of another study, this one involving people 16 to 25 years old, figured out the level of antibodies that seems to be protective in that population, then figured out how many kids ages 5 to 11 had similar levels of antibodies in their blood, and then came up with a number for how many cases, hospitalizations, ICU admissions, and deaths would be prevented by this shot in the 5 to 11 population in the future, based on the antibody levels and health outcomes from the 16 to 25 year old population. If your head hurts from that tortured logic, it should, because such chicanery is unprecedented in a risk-benefit analysis.
So when the FDA uses this tortured logic at the beginning of their briefing document, all of the calculations that stem from this will be flat out wrong. Not just wrong but preposterous and criminally wrong.
The whole ballgame comes down to Table 14 on page 34 of the FDA’s risk-benefit document. And there the red flags come fast and furious.
🚩 The FDA model only assesses the benefits of vaccine protection in a 6-month period after completion of two doses. Furthermore it assumes constant vaccine efficacy during that time period. This is problematic on several counts.
First, reducing mild cases in children is not a desired clinical outcome. As Dr. Geert Vanden Bossche points out, mass vaccination turns kids into shedders of more infectious variants.
“Under no circumstances should young and healthy people be vaccinated as it will only erode their protective innate immunity towards Coronaviruses (CoV) and other respiratory viruses. Their innate immunity normally/ naturally largely protects them and provides a kind of herd immunity in that it dilutes infectious CoV pressure at the level of the population, whereas mass vaccination turns them into shedders of more infectious variants. Children/ youngsters who get the disease mostly develop mild to moderate disease and as a result continue to contribute to herd immunity by developing broad and long-lived immunity. If you are vaccinated and get the disease, you may develop life-long immunity too but why would you take the risk of getting vaccinated, especially when you’re young and healthy? Firstly, there is the risk of potential side effects; secondarily, there is the ever increasing risk that your vaccinal antibodies will no longer be functional while still binding to the virus, thereby increasing the likelihood of ADE or even severe disease….”
Second, we know that vaccine efficacy in the month after the first dose is negative because it suppresses the immune system and it begins to wane after 4 months so all of the FDA’s estimates of vaccine efficacy are inflated.
Third, the harms of myocarditis from these shots will likely unfold over the course of years. Robert Malone, the inventor of mRNA technology notes that the FDA is admitting that children will be injected twice a year forever (hence the six month time frame in the FDA risk-benefit model). But the risks of “adverse events such as cardiomyopathy will be cumulative.” So any model that only looks at a six month time frame is hiding the true adverse event rate.
🚩 The FDA/Pfizer play fast and loose with their estimates of myocarditis. First they estimate “excess” (read: caused by the shot) myocarditis using data from the private “Optum health claim database” instead of the public VAERS system (p. 32). So it’s impossible for the public to verify their claims. Then, when it comes to estimating how many children with vaccine-induced myocarditis will be hospitalized and admitted to the ICU they use the Vaccine Safety Datalink (see page 33). Why switch to a different database for those estimates? Finally, there is no explanation for how they calculated “excess” myocarditis deaths, so they just put 0. Red flag, red flag, red flag.
The FDA estimates that there will be 106 extra myocarditis cases per 1 million double-jabbed children 5-11. There are 28,384,878 children ages 5 to 11 in the U.S. The Biden administration wants to inject Pfizer mRNA shots into all of them and has already purchased enough doses to do just that (even though only 1/3rd of parents want to jab their kids with this shot). So (if the Biden administration has its way) 106 excess myocarditis cases per 1 million x 28.38 million people would be 3,009 excess myocarditis cases post-vaccination if the Pfizer vaccine is approved.
And over the course of several years many of those children will die.
Dr. Anthony Hinton (“Consultant Surgeon with 30 years experience in the NHS”) points out that myocarditis has a 20% fatality rate after 2 years and a 50% fatality rate after 5 years:
Viral myocarditis results in 2 in 10 people dead after 2 years and 5 in 10 after 5 years. It’s not mild. It’s dead heart muscle. https://t.co/ixRmk48rja
So the FDA has it exactly backwards — they want to prevent mild COVID in children which reduces herd immunity and they just flat out lie about the harms from myocarditis.
I’ve taken the liberty to correct the FDA’s Table 14 with actual real world data and extended it over 5 years. It looks like this:
A study by Harvard Pilgrim Healthcare for the U.S. Department of Health and Human Services estimated that VAERS only captured 1% of actual vaccine injuries. Steve Kirsch has done elaborate modeling that puts the Under-Reporting Factor of COVID-19 vaccine deaths at 41 (so multiply the above numbers by 41). And myocarditis is just one of a multitude of possible harms from COVID-19 vaccines. Dr. Jessica Rose recently calculated an Under-Reporting Factor of 31 for all severe adverse events following vaccination.
Conclusion
The Pfizer vaccine fails any honest risk-benefit assessment in connection with its use in children ages 5 to 11. The FDA’s risk-benefit analysis of Pfizer’s mRNA vaccine in children ages 5 to 11 is shoddy. It used tortured logic (that would be rejected by any proper academic journal) in order to reach a predetermined result that is not based in science. The FDA briefing document is a work of fiction and it must be withdrawn immediately. If the FDA continues with this grotesque charade it will cause irreparable harms to children and the FDA leadership will one day be prosecuted for crimes against humanity.
The U.S. Food and Drug Administration’s (FDA) advisory committee today endorsed Pfizer’s COVID vaccine for children ages 5 to 11, despite strong objections raised during the meeting by multiple scientists and physicians.
The vote passed with 17 supporting it and one abstention.
Before the shots can be rolled out, the FDA will have to formally authorize the vaccine, and the Centers for Disease Control and Prevention (CDC) must also weigh in with its own recommendations — but the Biden administration’s announcement last week that it has already ordered 68 million doses of the pediatric vaccine suggests Pfizer’s request will sail through.
According to the FDA website, as of Oct. 25, the agency had received 139,470 comments from the public prior to today’s meeting — a number federal officials described as strikingly high.
As he opened the meeting, Dr. Peter Marks, director of the FDA’s Center for Biologics Evaluation and Research (CBER), said, “I want to acknowledge the fact that there are strong feelings that have clearly been expressed by members of the public both for and against” authorization.
The dose for younger children would be one-third the strength given to people 12 and older, with two shots given three weeks apart.
Based on CDC data presented during the meeting, among children 5 to <12 years of age, there have been approximately 1.8 million confirmed and reported COVID cases since the beginning of the pandemic, and only 143 COVID-related deaths in the U.S. through Oct. 14.
In this same age group, there were 8,622 COVID-related hospitalizations through Sept 18.
“This translates to cumulative incidence rates of approximately 6,000 and 30 per 100,000 for confirmed COVID cases and COVID-related hospitalizations, respectively, among children 5 to <12 years of age,” Pfizer’s application said.
Children with underlying medical conditions, such as asthma, diabetes and obesity, made up two-thirds of severe COVID cases.
Pfizer provided safety data on two study cohorts of children ages 5 to 11, both of roughly equal size. The first group was followed only for about two months, the second for only two-and-a-half weeks.
The two-month cohort included 2,268 children ages 5 to 11. Of the 2,268 children, 1,518 received the vaccine and 750 received a placebo. Each received two shots spaced three weeks apart.
Pfizer’s study found its vaccine was about 91% effective against symptomatic COVID in children, based on 16 cases of COVID in the placebo group and three cases in the vaccinated group over the brief follow-up period.
Most side effects occurred within a couple of days and included pain at the injection site, fatigue, headache, muscle pains and chills, Pfizer said.
According to Pfizer, the number of participants in the current clinical development program was “too small to detect any potential risks of myocarditis associated with vaccination.”
Long-term safety of Pfizer’s COVID-19 vaccine “to evaluate long-term sequelae of post-vaccination myocarditis/pericarditis” in participants 5 to <12 years of age will not be studied until after the vaccine is authorized for children,” Pfizer’s application noted.
Pfizer data insufficient, kids’ risk of vaccine injury greater than COVID risk, experts say
Experts raised concerns over the lack of safety and efficacy data presented by Pfizer for use of its COVID vaccine in younger children, and they pointed to increasing safety signals based on reports to the Vaccine Adverse Event Reporting System (VAERS).
They also questioned the need to vaccinate children — whose risk of dying from COVID is “almost nil” — at all.
According to Dr. Meryl Nass, member of the Children’s Health Defense Scientific Advisory Panel, Pfizer once again did not use all of the children who participated in the trial in their safety study.
“Three thousand children received Pfizer’s COVID vaccine, but only 750 children were selectively included in the company’s safety analysis,” Nass said. “Studies in the 5-11 age group are essentially the same as the 12-15 group — in other words, equally brief and unsatisfying, with inadequate safety data and efficacy data, with no strong support for why this type of immuno-bridging analysis is sufficient.”
Nass said, “All serious adverse events were considered unrelated to the vaccine.”
During the meeting and in its FDA application, Pfizer argued children should be vaccinated to prevent SARS-CoV-2 transmission, yet the company did not assess asymptomatic transmission.
Dr. Ofer Levy, a VRBPAC member, asked for evidence that Pfizer’s vaccine prevents transmission.
Dr. William Gruber, senior vice president of Pfizer Vaccine Clinical Research and Development, said they did not assess whether the vaccine prevents transmission, but said there is evidence the vaccine prevents transmission in adults.
When questioned further, Gruber was unable to cite specific evidence to back his assertion.
Steve Kirsch, founder of the COVID-19 Early Treatment Fund, asked the panel how they could do a risk-benefit analysis with Pfizer’s COVID vaccine if they did not know the CDC’s VAERS under-reporting factor (URF).
Kirsch asked:
“How can you do a risk-benefit of analysis of COVID vaccines if you don’t know the URF? This is extremely, extremely important. You have been assuming it has been one. It is not one. Using a URF of 41, which is calculated using CDC methodology, we find over 300,000 excess deaths in VAERS. If the vaccine didn’t kill these people, what did?”
“How many Americans have to die before you pull the plug?” Kirsch asked.
Kirsch also questioned the panel on why Maddie de Garay’s severe adverse reaction to the Pfizer vaccine, which left her paralyzed, was not reported by the company to the FDA.
Dr. Jessica Rose, viral immunologist and biologist, told the panel EUA of biological agents requires the existence of an emergency and the nonexistence of alternate treatment.
“There is no emergency and COVID-19 is exceedingly treatable,” Rose said.
In a peer-reviewed study co-authored by Rose, myocarditis rates were significantly higher in people 13 to 23 years old within eight weeks of the COVID vaccine rollout.
In 12- to15-year-olds, Rose said, reported cases of myocarditis were 19 times higher than background rates.
“In an act of censorship, this paper has been temporarily removed and it has now been killed without criticism of the work,” Rose said, noting the timing of the removal was strange.
Rose said tens of thousands of reports have been submitted to VAERS for children ages 0 to 18.
Rose explained:
“In this age group, 60 children have died — 23 of them were less than 2 years old. It is disturbing to note that “product administered to patient of inappropriate age was filed 5,510 times in this age group. Two children were inappropriately injected, presumably by a trained medical professional, and subsequently died.”
Dr. Josh Guetzkow, a senior lecturer at the Hebrew University of Jerusalem, said expanding the EUA to children is unnecessary, premature and will do more harm than good.
Guetzkow said there is no emergency for children, especially healthy ones whose risk of severe illness and death is “almost nil.”
Guetzkow said kids with pre-existing conditions and prior COVID infections were not included in Pfizer’s study, so including them in the EUA is negligence.
“Pfizer’s trial is woefully underpowered to detect specific safety concerns, such as myocarditis, just like the adolescent study was, and if they weren’t able to detect an unexpected safety concern there, they wouldn’t be able to here,” Guetzkow said.
Guetzkow said:
“In Pfizer’s study, only .5% of controls were dropped due to important protocol violations, versus 3% in the treatment group. The odds of that happening by chance are 1 in 10,000. This deviation is poorly explained with no ITT analysis. The study is not double-blind and may be subject to bias. Most VSD safety monitoring programs have not reported results, why not wait?”
Guetzkow said, “from CDC reports, we can expect that for every 18 child hospitalizations prevented, at least 43 will end up in the hospital for all causes following vaccination,” yet, the “FDA’s risk-benefit analysis only counts myocarditis hospitalization.”
“Why ignore the V-safe data, and shouldn’t FDA verify Pfizer’s efficacy and immunobridging analysis first?” he asked.
Guetzkow said VAERS shows alarming safety signals, which cannot be attributed to increased vaccination, simulated reporting or COVID infections.
“We calculated the ratio of adverse events reported per million Pfizer vaccinations to reports per million flu vaccinations among teenagers to see what to expect in children. Serious events are reported 51% more often for Pfizer, deaths 47 times, life-threatening conditions 49 times,” Guetzkow said.
Guetzkow asked the panel to look at the data on COVID vaccines compared to flu vaccines. Pointing to the data on reproductive organs, Guetzkow asked, “why would we expect children to take these risks to protect adults?”
There are more than 900 types of adverse events reported after Pfizer vaccination that have never been reported after flu vaccines, including 11 cases of multisystem-inflammatory syndrome (MS-C) that occurred without previous history of COVID infection, Guetzkow said.
He added that if the panel was considering authorizing Pfizer’s COVID vaccine to prevent MS-C — as Pfizer’s application suggested as one of the reasons they should — the panel should reconsider.
During another part of the meeting, Julia Barnes-Weise, director of the Global Healthcare Innovation Alliance Accelerator, said pharmaceutical companies have concerns.
“One of them is, especially for a not-yet-approved vaccine, that they could be held liable for any injury that that vaccine seems to have caused,” Barnes-Weise said.
In a preliminary analysis last week, FDA reviewers said protection would “clearly outweigh” the risk of a very rare side effect in almost all scenarios of the pandemic, PBS News Hour reported.
Children’s Health Defense (CHD) said yesterday it would take legal action against the FDA if it granted EUA for the Pfizer-BioNTech vaccine for children 5- to 11- years old.
In a letter signed by Robert F. Kennedy, Jr., CHD chairman and chief legal counsel, and Nass, Kennedy and Nass wrote:
“CHD will seek to hold you accountable for recklessly endangering this population with a product that has little efficacy but which may put them, without warning, at risk of many adverse health consequences, including heart damage, stroke, and other thrombotic events and reproductive harms.”
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
PHARMACOVIGILANCE: the practice of monitoring the effects of medical drugs after they have been licensed for use, especially in order to identify and evaluate previously unreported adverse reactions.
Pages 34-35 of the FDA review of Pfizer’s data for the 5-11 year olds provides the pretense of truly caring about identifying and quantifying adverse events from the vaccine. Just look at all the “activities” Pfizer and its partner must do. Well, of course they have to do them, since their clinical trial was so underpowered (not enough subjects) and only ran 2 months for about half the kids and 2.5 weeks for the rest. Duh?
Not only that, but Pfizer presented its data to FDA on October 6, and FDA already had completed its review and written its 39 page report by October 23, 17 days later. Fast work. But then again, we are only talking about the health of 28 million elementary school kids. And millions more overseas whose countries follow FDA advice.
And lest I forget, we are also talking about their education, because it seems they won’t be able to attend school soon, if unjabbed. Gavin Newsome said so. And a bill is being introduced in the District of Columbia for the same purpose.
Clearly, the stakes are pretty low, so a pretend Pfizer clinical trial and a pretend FDA review are good enough, right?
Below is part of FDA’s presentation. What is missing is the most important information, revealed in an Aug 23 letter from FDA. And that is, that the trials FDA demands Pfizer undertake to find out how dangerous its vaccines actually are, will not be reported to FDA until 2024 and 2025–presumably after most of the world’s children have already received 2 or 4 or 6 or 8 doses.
9 PHARMACOVIGILANCE ACTIVITIES
Pfizer submitted a revised Pharmacovigilance Plan (PVP) to monitor safety concerns that could be associated with BNT162b2 in individuals 5-11 years of age. The PVP includes the following safety concerns:
• Important Identified Risks: anaphylaxis, myocarditis, and pericarditis
• Important Potential Risks: Vaccine-associated enhanced disease (VAED), including vaccine-associated enhanced respiratory disease (VAERD).
Pfizer-BioNTech plans to conduct passive and active surveillance to monitor the postauthorization safety for the Pfizer-BioNTech COVID-19 Vaccine, including: 35
• Mandatory reporting by the Sponsor under the EUA for the following events to VAERS within 15 days: SAEs (irrespective of attribution to vaccination); COVID-19 disease resulting in hospitalization or death; multisystem inflammatory syndrome (MIS)
• Adverse event reporting in accordance with regulatory requirements for the licensed vaccine, COMIRNATY
• Additionally, following approval of COMIRNATY, the Sponsor was also asked to submit reports of myocarditis and pericarditis as 15-day reports to VAERS.
• Periodic safety reports containing an aggregate review of safety data including assessment of AEs; vaccine administration errors, whether or not associated with an AE; and newly identified safety concerns.
• Post-authorization observational studies, that would be modified to encompass the evaluation of children 5-11 years of age include active surveillance safety studies using large health insurance claims and/or electronic health record database(s):
– Study C4591009: A non-interventional post-approval safety study of the Pfizer-BioNTech COVID-19 mRNA Vaccine in the United States
Objective: To assess the occurrence of safety events of interest, including myocarditis and pericarditis, in the general U.S. population of all ages, pregnant women, the immunocompromised, and persons with a prior history of COVID-19 within selected data sources participating in the U.S. Sentinel System.
– Study C4591021: Post-conditional approval active surveillance study among individuals in Europe receiving the Pfizer-BioNTech Coronavirus Disease 2019 (COVID-19) Vaccine
Objective: To assess the potential increased risk of AESIs, including myocarditis/pericarditis, after being vaccinated with at least one dose of the PfizerBioNTech COVID-19 Vaccine.
– Study C4591021 Substudy: Substudy to describe the natural history of myocarditis and pericarditis following administration of COMIRNATY
Objective: To describe the natural history of post-vaccination myocarditis/pericarditis, including recovery status, risk factors, and/or identification of serious cardiovascular outcomes within one year of myocarditis/pericarditis diagnosis among individuals vaccinated with BNT162b2 as well as individuals not vaccinated with a COVID-19 vaccine.
– Study C4591036: Prospective cohort study with at least 5 years of follow-up for potential long-term sequelae of myocarditis after vaccination (in collaboration with Pediatric Heart Network [PHN]). Working title: Myocarditis/pericarditis follow-up study within the Pediatric Heart Network
Objective: To characterize the clinical course, risk factors, resolution, long-term sequelae, and quality of life in children and young adults <21 years with acute postvaccine myocarditis/pericarditis. Pfizer-BioNTech also plans to include vaccine effectiveness analyses among individuals 5-11 years of age in Study C4591014 entitled “Pfizer-BioNTech COVID-19 BNT162b2 Vaccine Effectiveness Study Kaiser Permanente Southern California.”
1. We cannot vaccinate ourselves out of the Covid problem. Mass vaccination is forcing the virus to produce variants, which escape any protection provided by the jab (see here for a report covering 68 countries). Instead, the vaccine should be offered only to those most vulnerable, such as the very elderly.
2. It is especially wrong to give it to children. They are at almost zero risk from Covid but subject to a real risk of damage from this particular vaccine, unrecognised during its development.
3. Cheap and effective treatment is available which keeps the vast majority of patients out of hospital. Health officials and regulators should support doctors who want to use these treatments, and to educate patients in how to strengthen their responses to the virus.*
4. Lockdowns and official fear-inducing propaganda have blighted the lives of millions, especially children, and must never be repeated.
The discussion is a must view for concerned individuals. It offers a completely different perspective from that of the NHS chiefs now calling for booster jabs and the return of Covid restrictions.
These edited contributions give a flavour of the discussion:
Dr Robert Malone, key architect of the mRNA technology that made possible the most commonly used Covid vaccines: ‘The virus is evolving very rapidly. This is akin to what happens if you overuse antibiotics. With universal vaccination, we’re driving towards an endpoint of vaccine-resistant mutants. The vaccines need to be used intelligently.
‘This set of vaccines that we have right now are gene therapy-based, and they have a common problem: they only have one antigen. It’s the spike antigen. When they were developing them, they didn’t realise the spike was biologically active. No fault of theirs. Everybody was in a rush.
‘But now it’s time to take a breath and say, “Hey, does this really make sense?” We don’t have to be just Left or Right, pro- or anti-vaccine. There’s a middle ground. We, as a community, need to protect people at high risk, not just here in our community, in our states; in my opinion, we need to protect the elders throughout the world. We don’t need to hoard all the vaccine for people that don’t really need it.
‘I’m not an anti-vaxxer, I’m a guy who’s spent the majority of my adult life developing vaccines. This is a technology platform that has enormous promise. And right now it’s in its infancy. The safety of the underlying technology is not yet fully demonstrated.
‘People did what they did in good faith and focused on a protein that they thought was fully safe – spike. But now, over a year later, we know that in the virus, this protein is responsible for much of the disease – the pathology in your vascular endothelial cells [blood vessel linings], the coagulation. And it’s unfortunate that this particular protein, in what appears to be a biologically active form, was used in these vaccines.’
Dr Richard Urso, ophthalmologist, Texas: ‘When people say, “They died of Covid”, they died of an inflammatory, thrombotic disease. They didn’t die from the virus running through their body. There’s a bunch of drugs that can be used for the purpose of inflammation in this disease. There’s a bunch of drugs for thrombosis. Hopefully at some point we’ll have a really good, early treatment that’s directed to the virus itself. Right now we have other, very effective treatments.
‘About 330 children have died of Covid in a year and a half [under-19s in the US]. Typically, about 50,000 children a year die – many from drownings, from car accidents. You need to look at that as you look at the risk to children. And do they spread? – No, at least seven different studies show that children spreading to adults is close to zero.’
Dr Brian Tyson, family doctor, California, who has successfully treated more than 6,000 Covid patients and now finds children are getting sick from typical winter illnesses, rather than Covid: ‘With treatment started from day 1 to 7, I have had zero deaths. From treatment started from day 7 to 14, I have four – two died the same day they showed up at the clinic, and two died in hospital.
‘Under that data Dr Urso was talking about, not one healthy child died from Covid-19. It was children who had four or five risk factors – morbid obesity being number one, diabetes number two, weakened immune system number three; kids on chemotherapy and things like that. So yes, they’re going to have opportunistic infections, but that’s no different than would normally take out these kids anyway, unfortunately.’
Dr Heather Gessling, family doctor, Missouri: ‘My numbers exactly match up with Brian’s. I’ve treated about 1,500 and I’ve had one death, because there was some delay in treatment.’
Dr Mark McDonald, child psychiatrist, Los Angeles: ‘Fear has been the driving force of this pandemic from the very beginning. What’s driving the fear now is propaganda. I see kids all day long. The developmental stage that children need to go through – babies, toddlers, young adults – is being foreclosed on them.
‘Brown University department of paediatrics published a study that found babies born after January 1, 2020, have an IQ drop of 20 points. Why? They don’t see faces. They don’t play. They don’t have exposure to friends. They don’t go to school. They’re basically locked in their homes, looking at their parents for a year and a half. And their brains have not developed.
‘My concern is that we are building a generation of young people who are so traumatised that they will never fully recover. They’re always going to be scarred emotionally.
‘I don’t mean to be depressing. I mean to be alarming, so everyone can finally say, “Stop!” We’ve got to stop the damage, and then figure out what to do about it.’
Dr Gessling: ‘I think “Stop the damage!” means to acknowledge what we have done wrong. We should reverse all the measures that have been implemented. Patients, families, parents, should take it upon themselves to feel empowered. We need to get back to the basics, because we’ve done this wrong for so long.
‘One of the books we all had in medical school was Harrison’s Principles of Internal Medicine. This is what we have forgotten: “Many specific host factors influence the likelihood of acquiring an infectious disease: age, immunisation history, prior illnesses, level of nutrition, pregnancy status, coexisting illnesses and perhaps emotional state – all have some impact on the risk of infection after exposure to a potential pathogen.” All we have done is focus on one of those: immunisation history.
‘The ability to provide early, effective treatment should make us feel empowered. We should not feel afraid any more.’
Dr Pierre Kory, pulmonary and critical care specialist; founding member and president, the Front Line Covid-19 Critical Care Alliance; co-author of two Covid prevention and treatment protocols: ‘My hopes are that more and more attention is going to be paid to early treatment strategies, especially now the vaccinated are getting sick. Many people were led to believe that if you get your vaccine, we’re going to end this thing, you don’t have to worry about it, you can carry on with your lives.
‘But guess what? My colleagues are talking about even scarier variants that are coming. And so we need more tools to fight this. The positive message is, we have them, and they can handle any variant that comes at us. We just need to get that message out. I don’t believe anybody has died who’s had effective early treatment.’
Dr John Littell, family doctor, Florida: ‘What we’re seeing now is that patients are getting early treatment with ivermectin, hydroxychloroquine and a host of other medications, because of this free exchange of ideas in this group of physicians and others around the world.
‘Dr Tyson, Dr Gessling and myself are family physicians, OK? So we’re the folks who have been in those front lines getting the phone calls in the middle of the night from concerned parents. And what you’ve just heard from Dr Kory and from us is that is that if you take the right preventive treatment, you’re approaching zero per cent mortality.’
Dr Kory: ‘If we have effective treatments, why aren’t they being recognised and disseminated across the world? I think we’re up against two forces.
‘The first is that in general, our health agencies are suffering what’s called regulatory capture. They’re largely driven by financial interests that are making sure that the solution to the pandemic is one that is profitable. Vaccines are profitable.
‘The other, somewhat overlapping challenge is that in academia, in the last ten years, there’s been this increasing belief that the only proof of efficacy of a drug has to come out of a large, double-blind, randomised controlled trial. You have to make the diagnosis – everyone has to have a positive test; they have to have symptoms; they have to be enrolled, consented, randomised, and then the drug is delivered. Each one of those steps takes time. So it’s often very delayed, and under-dosed – they’re using doses that I was using six months ago.’
Dr Ryan Cole, medical director, Cole Diagnostics, Idaho, who has done more than 100,000 Covid tests in the past year: ‘Covid is a clotting disease. When we give a spike protein [through the vaccine], that is an active biologic molecule. We chose the wrong molecule, which causes disease.
‘So what do I see under the microscope? We see clotting under the skin, in the lungs, in the blood vessels, in the brain – not from the virus, but from the spike from the vaccine itself.
‘Now consider the numerator and the denominator. Are most people going to be fine? Yes. And I want to emphasise that.
‘[But] in our data from around the world, from the United States, from the UK, from EudraVigilance in Europe, we have seen more death and damage from this one medical product than all other vaccines combined in the last several decades, in just a short, eight-month window of time. It has done more damage than any other medical product, therapy, shot, modality, of anything we’ve ever allowed to stay on the market to this point.
‘Do I mean to sound alarmist? No, I’m being factual. And when I look at it under the microscope and I see the parts of people – or people that are no longer with us – the damage and the disease is caused by that spike protein. It is present.
‘A virus is a humanitarian issue. When we divide ourselves in thought and don’t listen to science any more, we’re going down the wrong paths.
‘We are forgetting what our amazing immune system does. How many of you had chickenpox when you were a kid? And how many of you have ever had it again? Did you need a shot? No. Grandma had measles – has grandma ever had it again? No, because her immune system works.
‘Half of kids in the US have already had Covid. We’re not antibody testing – we’re treating everybody with this terrible oppression of, “You’ve got to wear a mask . . . you’ve got to stay home if somebody in your classroom tests positive.” It denies basic science.
‘Under age 50 with no co-morbidities, your chances of dying from this disease are about nil, and if you get early treatment they are even closer to nil. So if you are a Covid recoverer, you don’t need a shot.
‘The shot can damage the hearts of children. There are more children who’ve had myocarditis – and there’s never such a thing as mild myocarditis. That’s inflammation of the heart. Once you get inflammation, you get scarring. Those kids’ hearts are damaged for life. Kids have died of heart attacks after the shot, and there are more kids that have had myocarditis than have died from Covid. Kids aged zero to 18 survive this virus at a statistical 100 per cent – 99.997 per cent. So why are we punishing kids for a virus they survive?’
*For up-to-date guides to home treatment of Covid, see here and here.
IT’S OFFICIAL: Most of the UK’s vaccinated population are suffering far higher rates of infection than the unvaccinated, and it is getting worse by the day.
The UK’s Health Security Agency publishes detailed Covid statistics, which, for the last 7 weeks, have been tabulated by age-group and vaccination status. This now allows important questions to be answered.
The Agency says most vaccinated suffer substantially higher rates of infection, and their latest chart provides a snap-shot:
All of the UK’s 30-and-over vaccinated now endure far higher rates of infection than their unvaccinated counterparts. But as a snap-shot, this tells us nothing of how this arose, or how it may yet develop. Here we re-present the agency’s data in a time-series, to promote better understanding of the trends and implications.
The UK has vaccinated its population mostly in age order, from oldest to youngest, and very recently began vaccinating its under-18-year-old cohort. Being the UK’s most freshly vaccinated, they exhibit a very high degree of resistance to Covid infection: –
This very recently vaccinated cohort benefits from a 90% improvement in their infection rates, meaning their case incidence is 10 times better than that of their unvaccinated counterparts. This is impressive, and leads us to ask how long this high degree of protection might last?
The answer, unfortunately, seems to be not very long:
The previous UK age-group to be vaccinated was the 18–29-year-old cohort, of which half was fully vaccinated by some 9 weeks ago. While still doing better than the unvaccinated of their age, they have nevertheless lost the greater part of their relative resistance to infection. If they continue their trajectory, week 12 will see that benefit completely gone.
The earlier vaccinated age-group was the 30–39 cohort. Half was fully vaccinated around week 27, and by week 39 (again some 12 weeks later) had lost their enhanced infection resistance. For at least for these two cohorts, it would seem their vaccine induced resistance reduced to zero in under 3 months.
Unfortunately, it does not stop there; Following the data shows the vaccinated descend well into negative territory, which may prompt us to ask how all earlier vaccinated cohorts are now doing?
In terms of vulnerability to infection, the answer is not so well:
The entire 40-79 vaccinated cohort is deeply negative, now below minus 50%, meaning they suffer more than double the infection rate of their unvaccinated counterparts, and there is no obvious end in sight; Given the consistent and strongly negative continuing trend for all adult cohorts, it is impossible to guess where or when these trajectories might bottom out.
But does the trend result from increased vulnerability amongst the vaccinated, or is improved resistance developing amongst the unvaccinated? The answer appears to be both:
Unvaccinated adults are enjoying significantly lowered infection rates, but the vaccinated are very clearly headed in the opposite direction:
This begs the question: Why should the vaccinated suffer mounting infection rates, while case-rates of the unvaccinated both declined and are lower? Surely, we should expect the vaccinated to do better – certainly no worse?
Yet, for all but one adult cohort, the exact opposite is true, and even for them, it seems likely for not much longer:
It has been suggested infection amongst the unvaccinated has induced robust natural immunity leading towards their herd-immunity. That may well be a factor, but, as we have seen, the vaccinated have similarly been infected, and at least for the 40-79 cohort, at much higher rates. Why should this not benefit the vaccinated as well?
Are we to understand infection after vaccination may not produce similar broad immunity?
Vaccination is intended to alter subsequent immune response to infection, which is, of course, the whole point; It is conceivable this altered response may mute the development of broad long-lasting immunity that otherwise typically results from natural infection. That might then leave the vaccinated more open to re-infection, and might help explain these results. But this remains speculation, we simply do not know today.
What we do know from the UK data, is that anyone vaccinated more than few months ago is at greatly higher risk of Covid infection, and is therefore greatly more likely to be infected than their unvaccinated counterparts.
Much has been said and written to show the vaccinated are equally capable of transmitting Covid. But because their symptoms are often muted, they are also more likely to be out and about; add this to escalating infection rates, and there can be little doubt the vaccinated now constitute by far the greatest Covid transmission risk.
In light of this, vaccine passports are clearly senseless; They are nothing more than an invitation to infection, for which no justification can now possibly remain.
Before I address President Biden’s decision last Friday to continue the national-security establishment’s cover-up of its November 22, 1963, regime-change operation in Dallas, I wish to make one thing perfectly clear: I am not Nostradamus.
Yes, I fully realize that I repeatedly predicted that Biden would never order the release of those 60-year-old assassination-related records that the CIA has steadfastly been keeping secret from the American people. (See here and here.) But that prediction doesn’t make me Nostradamus.
In fact, any reasonable person who has studied the Kennedy assassination could have easily made the same prediction. There has got to be a good reason why the CIA does not want people to see those 60-year-old secret records. That’s why they didn’t disclose them during the era of the Assassination Records Review Board in the 1990s. That’s why they demanded that President Trump continue keeping them secret in 2017. That’s why they demanded that Biden extend the secrecy.
After all, think about it: If Donald Trump, who the national-security establishment loathed, buckled and surrendered to the CIA’s demand for continued secrecy, it’s a no-brainer that Biden, who is owned lock, stock, and barrel by the national-security establishment, would do the same.
It’s probably worth recalling the candid words of U.S. Senator Charles Schumer: “Let me tell you, you take on the intelligence community, they have six ways from Sunday at getting back at you.” Undoubtedly, Trump, Biden, and the National Archives were all fully aware of the truthfulness of Schumer’s decision in granting the CIA its demand for continued secrecy.
At the risk of belaboring the obvious, those 60-year-old secret records obviously contain incriminating evidence — evidence that consists of more pieces to the puzzle pointing to a regime-change operation in Dallas.
After all, as I have repeatedly pointed out, the notion that the release of 60-year old records could constitute a grave threat to “national security” is nonsensical on its face. Is there anyone who really believes such nonsense?
There can be no doubt that the release of those long-secret records would constitute a grave threat to the CIA, the Pentagon, and the rest of the national-security establishment. But that’s different from constituting a threat to “national security,” whatever meaning one places on that nebulous, meaningless term.
But that’s what Biden stated in his decision last Friday. Biden cited that time-honored term that has become the most important term in the political lexicon of the American people in our time: “national security.”
That’s not all he said. He said that the COVID-19 pandemic had interfered with the National Archives’s ability to coordinate with the CIA, the Pentagon, and other national-security agencies to ascertain whether those records really do constitute a threat to “national security.”
That’s just plain silly. It reminds me of the kid who claimed that his dog ate his homework.
In the 1990s, the CIA and the Pentagon had to set forth the reasons why they wanted another 25 years of secrecy for those records. In 2017, they again had to set forth the specific reasons to Trump as why they were demanding that Trump grant them another five years of secrecy.
Nothing has changed. There are no new reasons for continued secrecy. All that the National Archives needed to do is make a copy of those previously cited reasons and send them to Biden. How in the world could the COVID-19 pandemic have impeded doing that? It couldn’t have. It just another ruse to continue the coverup — and a ridiculous one at that.
Now, let me make something else very clear. I’m not suggesting that those records contain a CIA or Pentagon confession of wrongdoing. From the very start of the CIA, when it began specializing in the dark arts of state-sponsored assassinations and cover-ups, its policy was to never put any of its assassination plots into writing.
What I am saying though is that the records undoubtedly contain incriminating circumstantial evidence that further fills out this particular regime-change mosaic. If I had to predict what that would be, I would say it most likely relates to the operation in Mexico City, where accused assassin Lee Harvey Oswald was supposed to have met with Soviet and Cuban officials.
That part of the regime-change operation clearly went awry, including, for example, producing a photograph of a man who was supposed to be Oswald in Mexico City but who clearly was someone else. Or a tape-recording of a man who was supposed to be Oswald talking to one of those embassies and clearly was the voice of someone else.
In the 1970s, when two young lawyers, Dan Hardway and Ed Lopez, were investigating the Kennedy assassination for the U.S. House Select Committee on Assassinations, they were pressing the CIA for its records relating to Mexico City. In response, the CIA called out of retirement a loyal CIA agent named George Joannides. His job? To block Hardway and Lopez from getting to those records.
That’s not the only place that Joannides pops up in the JFK assassination. Immediately after the assassination, a group called the DRE published a press release advertising Oswald’s communist bona-fides arising out of his time in New Orleans shortly before his trip to Mexico City.
More than 30 years later, it would be discovered that the DRE was a secret CIA front organization that the CIA was secretly funding with very generous amounts of U.S. taxpayer money . And take a wild guess who the CIA agent was who was monitoring and controlling the DRE. That would be the same George Joannides who was called out of retirement in the 1970s to block Hardway and Lopez from accessing those secret Mexico City records. For more on Joannides see FFF’s book Morley v. CIA: My Unfinished JFK Investigation by former Washington Post reporter Jefferson Morley.
Biden extended the time for continued secrecy for those long-secret CIA assassination-related records to December 2022. I strongly advise everyone not to hold your breath. I make the following prediction: When that date rolls around, Biden will decree more secrecy, perhaps because his dog has eaten all the records.
On February 13, 1960, France carried out its first nuclear test in Algeria’s southern Reggane region. According to official statistics, 17 nuclear tests were carried out in total over the next 6 years. The area remains affected, and local scientists say that radioactive contamination has caused genetic mutations and irreversibly changed the region.
There are no official statistics on the number of victims. The only figures can be found in the records kept by the French representative of the local church, which lists 42,000 victims of nuclear tests. Three years ago, the French Ministry of Defense issued a statement, putting the number at 27,000 people. The victims include French soldiers as well as local Algerians who lived in the surrounding areas. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.