With Democrat Back in White House, MSNBC Returns to Ignoring U.S.-Backed War in Yemen

By Adam Johnson | The Column | November 24, 2021
A review of MSNBC’s coverage from Nov. 3, 2020 to Nov. 22, 2021 shows MSNBC hasn’t run a single segment on the U.S.-backed war still raging in Yemen.
To the extent MSNBC did cover Yemen’s “civil war” during this time frame it was exclusively to pass along, without skepticism, claims last spring from Democrats that President Biden had “ended U.S. support for the war”—which turned out to not be true in any meaningful sense, a fact evident at the time but not met with any questioning from MSNBC reporters or pundits.
Since then, it’s become increasingly clear little has changed in the status quo. While the U.S. has halted some forms of assistance, like mid-air refueling of aircraft, other forms of vital participation remain, including: green-lighting of weapons transfers, maintaining spare parts for Saudi war planes, sharing some forms of intelligence, and training the Royal Saudi Navy, which is enforcing a catastrophic blockade on Yemen.
And then there is the political cover that the Biden administration is giving the Saudi-led coalition, a vital form of support that noted in September by Annelle R. Sheline and Bruce Riedel at The Brookings Institute—hardly a far-left bastion of anti-imperial polemic:
Biden’s broken promise on Yemen
… Unfortunately, Biden’s approach is fatally flawed. The president stated that he would “end U.S. support for offensive operations in Yemen.” Yet the Saudi-led war on Yemen by definition, is an offensive operation. Saudi Arabia is bombing and blockading another country: Between March 2015 and July 2021, the Saudis conducted a minimum of 23,251 air raids, which killed or injured 18,616 civilians. The Houthis, known formally as Ansarallah, launch missiles in retaliation but if Saudi airstrikes ceased, the Houthis would have little reason to provoke their powerful neighbor. As long as the U.S. materially and rhetorically backs the Saudis’ war of choice, Biden’s assertion that the U.S. would end support for offensive operations is a lie.
The second crucial flaw in Biden’s approach is that he did not call for an immediate end to the Saudi blockade of Yemen. The blockade primarily blocks fuel from entering the Houthi-controlled Hodeida port; the Saudis also prevent the use of Sanaa International Airport. Blockades cannot be defensive: they are offensive operations, and therefore U.S. involvement should have ended following Biden’s declaration in February. The U.S. tacitly cooperated with the blockade by not challenging it, and the U.S. Navy occasionally announces it has intercepted smuggled weapons from Iran, suggesting a more active role than the administration admits. Congress should investigate.
Just this week, the Biden White House and State Department announced the US will be selling another $650 million in weapons to Saudi Arabia, hiding behind the nonsensical talking point that the weapons are “purely defensive.”
There was a time when MSNBC media personalities did act like they cared about what the UN calls the “world’s worst humanitarian disaster,” which has killed almost a quarter of a million people.
MSNBC ignored the war almost completely during the Obama years and early Trump years. But after the Saudi coalition bombed a school bus in August 2018, and Saudi dictator Mohammad bin Salman ordered the killing of Washington Post columnist Jamal Khashoggi in October 2018, they—like much of the U.S. media—finally began reporting on the regime’s human rights abuses. For a while.
MSNBC ran multiple segments on the war in the second half of 2018 when it was considered very much Trump’s war.
- Aug 9 2018 – All in with Chris Hayes: Dozens of children killed in school bus bombing in Yemen
- Aug 10 2018 – Velshi & Ruhle: An airstrike in Yemen struck a school bus, killing children
- Oct 21 2018 – All in with Chris Hayes: 14 Million People On Brink Of Starvation In Yemen
- Nov 15 2018 All in with Chris Hayes: Trump boosts authoritarians, as war rages in Yemen
- Sept 2018 – All in with Chris Hayes: WSJ: Pompeo backed continuing US role in war in Yemen
- Nov 28 2018 – All in with Chris Hayes: Senate advances bill to end support for war in Yemen
- Dec 12 2018: All in with Chris Hayes: Rep. Chris Murphy on what’s at stake with vote on Yemen
- Dec 12 2018 – All in with Chris Hayes: Paul Ryan’s Cowardly Act On Yemen
- Dec 13 2018 – Andrea Mitchell Reports: Bernie Sanders: Congress must determine U.S. involvement in Yemen crisis
- Dec 13 2018 – Ali Velshi: Senate votes to end U.S. support for Saudi-led war in Yemen
After this spasm of concern in late 2018, the coverage largely died out. As I noted in FAIR at the time, when activist pressure to pass a resolution compelling an end to U.S. support for the war was at its most urgent in March 2019, MSNBC ignored the effort altogether. There was a brief aside about Trump’s veto of said Yemen war powers act by Rachel Maddow on April 16, 2019, but it amounted to little more than a passing mention.
The next—and it turns out last—time an actual segment aired on the Yemen war was on Morning Joe in July 2020. This report, by NBC News’ Keir Simmons, did mention the war and the U.S.’s role in it, with a focus on how Covid was killing Yemenis. But since the July 2020 Morning Joe report, there have been no segments aired on MSNBC about the U.S.-backed Saudi bombing of Yemen.
In over 18 months, our nominally progressive cable network has not dedicated a single news report, roundtable debate, or segment to the world’s worst humanitarian disaster, which continues to be aided and armed by the U.S. government. When it was Trump’s war—and the Saudi regime fell out of favor with U.S. elites—their hearts bled. Now that we’re back to business as usual and the war is being armed and supported by a Democratic White House, it’s simply a non-issue.
In February 2021, President Joe Biden announced the U.S. was ending its support for “offensive” operations in Yemen, a deliberately vague and ultimately meaningless distinction that appears to have been designed to confuse progressives into declaring victory and moving on. Much to the White House’s liking, one can assume, the gambit seems to have worked, with MSNBC shelving the issue altogether and treating the U.S.-funded and backed war crime like it was wrapped up and out of our hands.
But it’s far from it. At any time, the Biden administration could cancel a U.S. program that provides maintenance for Saudi warplanes, the same warplanes that are still dropping bombs on civilians, including the recent bombing of a plastics factory in Sana’a. The Biden administration could reject the sale of U.S. air-to-air missiles, which can be used to shoot down airplanes and are one more tool the Saudi-led coalition can use to menace humanitarian workers who want to deliver supplies, or people trying to get their ill loved ones out of the country for treatment. And, it is an extremely low bar, but, at any point, Biden could clarify what is meant by support for “defensive” operations, and disclose the full extent of U.S. participation in the blockade, something he has repeatedly declined to do, even after 16 senators requested more transparency and robust action. These are all things the Biden administration is declining to do, thereby providing material and political support that is contributing to Saudi Arabia’s ability to continue the war.
After his six-month period in 2018 of breathlessly and repeatedly pronouncing the urgency of the issue, Chris Hayes’ show ‘All In’ has not run a segment on Yemen at all since December 2018.
Hayes hasn’t even mentioned the topic on Twitter since Biden took office Jan 20, 2021.
Mehdi Hasan, a consistent, long-time critic of Saudi Arabia and the war prior to joining MSNBC Feb 28 2021, did a segment on his online-only Peacock show after the election on Dec. 3 featuring prominent Yemen war critics Prof. Shireen Al-Adeimi and journalist Spencer Ackerman. In this segment, Hasan suggests in his opening that a Biden presidency would turn a page on the U.S.-Saudi relationship and end the war, neither of which happened (though both of his guests expressed profound skepticism). Also on his Peacock online-only show, he asked questions about continued U.S. support for Saudi Arabia, some quite skeptical, to guests Sen. Chris Murphy (D-Conn.) in April 2021 and Rep. Mark Pocan (D-Wisc.) in May 2021. But none of this was on his main cable show on MSNBC.
Hasan has not done a single segment on the Yemen war for his MSNBC show since his show first aired Feb 28 2021. On March 14 2021, he did ask White House Chief of Staff Ron Klain about the White House going soft on Saudi Arabia in general and in a one “minute rant” from May 2021, Hasan did take about 6 seconds to mention the U.S. selling arms to Saudi Arabia that are used in Yemen.
But this is the full extent of Hasan’s—and thus MSNBC’s—Yemen coverage. It goes without saying that multimillionaire MSNBC personalities Lawrence O’Donnell and Rachel Maddow haven’t done any segments on the war since Biden took office because, in the more than six years since it’s been raging, they haven’t mentioned it at all. To their credit, at least their indifference to the world’s largest humanitarian crisis isn’t motivated by partisan gotchas—they just don’t care in general.
In November 2020, Hasan insisted “we” needed to hold Biden to his promises that he would end US support for the war in Yemen.
Now that it’s been over a year since Biden’s election, and the U.S. is openly backing the Saudi blockade starving Yemenis, selling $650 million weapons to Saudi Arabia just this week, and continues to back SaudiArabia at the UN, perhaps media personalities with large platforms at nominally progressive cable networks should do just that.
New Zealand Doctors Speaking out with Science
NZDSOS – 15/11/2021
‘NZ Doctors Speaking out with Science’ featuring Drs Alison Goodwin, Matt Shelton, and Emanuel Garcia. News Conference 15th November, 2021.
See also:
Lethal Injection; Frontline E.R. Doctor Gives Chilling Account of Unusual Vaccine-Induced Illness
BY MIKE WHITNEY • UNZ REVIEW • NOVEMBER 20, 2021
“Americans are scared to death… People are walking off the job, not because they want to lose their jobs, but they don’t want to die from the vaccine! … They say, ‘Listen, I don’t want to die. That’s the reason I’m not taking the vaccine.’ It’s that clear.” Dr. Peter McCullough
A report in the U.K. Telegraph explains how the Covid-19 vaccine has led to a sharp rise in excess deaths. Here’s an excerpt from the article:
“Nearly 10,000 more people than usual have died in the past four months from non-Covid reasons, as experts called for an urgent government inquiry into whether the deaths were preventable…
Latest figures from the Office for National Statistics showed that England and Wales registered 20,823 more deaths than the five-year average in the past 18 weeks. Only 11,531 deaths involved Covid.” (“Alarm grows as mortuaries fill with thousands of extra non-Covid deaths,” UK Telegraph )
Mortality is rising because more people are dying. And more people are dying because more people have been vaccinated. There’s a link between rising mortality and the Covid-19 vaccine. Naturally, the media wants to shift responsibility for the fatalities to “delayed treatments” and “the lack of preventable care”. But this is just a diversion. The primary cause of death is the injection of a toxic pathogen into the bloodstreams of roughly 70% of the population. That’s what’s causing the clotting, the bleeding, the pulmonary embolisms, the heart attacks, the strokes, and the premature deaths. It’s the vaccine. Here’s more
“Weekly figures for the week ending November 5 showed that there were 1,659 more deaths than would normally be expected at this time of year. Of those, 700 were not caused by Covid.
The excess is likely to grow as more deaths are registered in the coming weeks.
Data from the UK Health Security Agency show there have been thousands more deaths than the five-year average in heart failure, heart disease, circulatory conditions and diabetes since the summer.
The number of deaths in private homes is also 40.9 per cent above the five-year average, with 964 excess deaths recorded in the most recent week, which runs up to November 5.” (“Alarm grows as mortuaries fill with thousands of extra non-Covid deaths“, UK Telegraph )
The sudden surge in mortality is not a meaningless blip on the radar. It’s a red flag indicating a significant break in the five-year trend. Something has gone terribly wrong. Mass vaccination was supposed to reduce the number of cases, hospitalizations and deaths. Instead, the fatalities continue to rise.
Why?
The answer to that question can be found in the data itself. As the author admits, there has been a sharp uptick in heart failure, heart disease, circulatory conditions and strokes. (Diabetes is the outlier) These are precisely the ailments one would expect to see if one had just injected millions of people with a clot-generating biologic that triggers a violent immune response that attacks the inner lining of the blood vessels inflicting severe damage to the body’s critical infrastructure. So, yes, all-cause mortality is up, and it is certain to climb even higher as more people are vaccinated and gradually succumb to the (frequently) delayed effects of a hybrid concoction that is the cornerstone of a malign plan to dramatically reduce global population. Check out this chart followed by a brief comment by diagnostic pathologist, Dr Claire Craig:
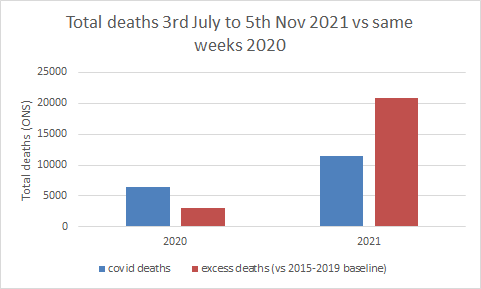
Dr Clare Craig @ClareCraigPath
“Since summer there have been twice as many covid deaths, but seven times as many excess deaths as last year.” (Twitter)
And here’s another blurb from Craig:
“If you start at week 22 and add up all the deaths since for each year, then something very abnormal is happening this year among 15-19 yr old males.”
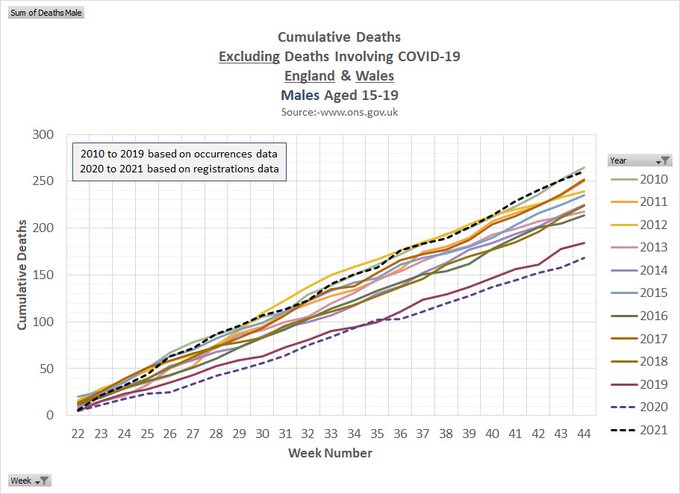
So, not only are more people dying, but the demographic has shifted downwards as younger and younger people are drawn into the vaccine vortex. Simply put, the number of young people dying from vaccine-inflicted cardiac arrest and myocarditis continues to increase with no end in sight.
Not surprisingly, all-cause mortality is higher among the vaccinated than the unvaccinated which, again, makes it easier to trace the problem back to its root, a cytotoxic “poison-death shot” that suppresses the innate immune system, damages vital organs and shaves years off the lives of normal, healthy people.
Perhaps, you’ve seen one of the many short videos of fit, young athletes who suddenly have dropped dead on the field of play or been rushed to hospital shortly after getting injected. If not, here’s a link to two of them. (Athletes collapse following vaccination: See here and here)
According to Israeli Real-Time News, there has been a “500% increase in deaths of players in 2021… Since December, 183 professional athletes and coaches have suddenly collapsed! 108 of them died!”
“500% increase in the deaths” of athletes?!? What are we to make of this?
For starters; the Covid-19 vaccine is not a medication. It is the essential component in the elitist plan for industrial-scale extermination. It is designed to inflict severe physical injury on the people who take it. It’s shocking that people are so deep in denial that they can’t see what’s going on right before their eyes. (Please, watch the video clips of the athletes. These are the fittest people on the planet and, yet, they are being struck down by the mystery substance in the vaccine.) Here’s how South African doctor Shankara Chetty summed it up in a recent video posted on Bitchute:
“The pathogen that is causing all the deaths from the illness is the spike protein. And the spike protein is what the vaccine is supposed to make in your body. … Spike protein is one of the most contrived poisons that man has ever made. And, the aim of this toxin, is to kill billions of people without anyone noticing it. So it is a poison with an agenda.” (“South African Physician Dr. Shankara Chetty Talks about “The Bigger Plan”, Bitchute)
There it is in a nutshell. And Chetty is not alone in linking the vaccine to the agenda of the globalist elites who plan to use the cover of a pandemic to implement their “population management” scheme. Former Pfizer vice president, Mike Yeadon, offered a similar view just days ago on his website. He said:
“We are in the midst of the biggest depopulation program the world has ever seen, where most of humanity are acting as useful idiots to it and to their own demise.”
Indeed, and we have tried to provide as much information as possible on the biologic agent that is being used to pursue this malign agenda, the spike protein. In early reports we passed along the research of Dr. Patrick Whelan who grasped the danger of the spike protein before anyone else. Here’s a brief recap of his analysis from a letter he submitted to the FDA on December 8, 2020:
“I am concerned about the possibility that the new vaccines aimed at creating immunity against the SARS-CoV-2 spike protein have the potential to cause microvascular injury to the brain, heart, liver, and kidneys in a way that does not currently appear to be assessed in safety trials of these potential drugs.
… Meinhardt et al…. show that the spike protein in brain endothelial cells is associated with formation of microthrombi (clots)… In other words, viral proteins appear to cause tissue damage without actively replicating virus…. The Pfizer/BioNTech vaccine (BNT162b2) is composed of an mRNA that produces a membrane-anchored full-length spike protein. The mouse studies suggest that an untruncated form of the S1 protein like this may cause a microvasculopathy in tissues that express much ACE2 receptor.
… it appears that the viral spike protein… is also one of the key agents causing the damage to distant organs that may include the brain, heart, lung, and kidney. Before any of these vaccines are approved for widespread use in humans, it is important to assess in vaccinated subjects the effects of vaccination on the heart…. As important as it is to quickly arrest the spread of the virus by immunizing the population, it would be vastly worse if hundreds of millions of people were to suffer long-lasting or even permanent damage to their brain or heart microvasculature as a result of failing to appreciate in the short-term an unintended effect of full-length spike protein-based vaccines on these other organs. (“FDA shrugs off dire warning about lethal spike protein“, Truth in the Age of Covid)
From the very beginning, government regulators and their allies in the public health establishment have ignored (or censored) the warnings of capable physicians and researchers. They also waved-off career immunologist and vaccinologist, Dr Byram Bridle who was the first in his profession to identify the spike protein as “a specific causative agent of disease”; aka–“a pathogen”. Here’s Bridle:
“‘We have known for a long time that the spike protein is pathogenic… It is a toxin. It can cause damage in our body if it’s in circulation. Now, we have clear-cut evidence that . . . the vaccine itself, plus the protein, gets into blood circulation.’”
Once that happens, the spike protein can combine with receptors on blood platelets and with cells that line our blood vessels. This is why, paradoxically, it can cause both blood clotting and bleeding. ‘And of course the heart is involved, as part of the cardiovascular system… That’s why we’re seeing heart problems. The protein can also cross the blood-brain barrier and cause neurological damage…
‘In short,… we made a big mistake. We didn’t realize it until now. We didn’t realize that by vaccinating people we are inadvertently inoculating them with a toxin.”… (“Vaccine scientist: ‘We’ve made a big mistake’“, TCW Defending Freedom )
Here again, we have a highly-regarded immunologist, with more than 3 decades of experience under his belt, who offered his informed and evidence-based research on an issue that should have been of great interest to the regulators that were making decisions about the long-term safety of the experimental drug they were foisting on millions of people across the country. But there was no interest at all. Despite the fact that the science supported his conclusions, Bridle was viciously attacked, censored, dragged through the mud, and forced to leave his place of employment.
Why?
Because he drew the same conclusions as Dr. Patrick Whelan. There’s really no substantive difference between the two except that Bridle’s comments attracted more attention in the media which made him a greater threat to the “universal vaccination” strategy. That was his real crime; he discovered the truth and made his findings available to the public, basically alerting them to the dangers of the “poison-death shot”. For that he was crushed.
Bridle has since made other claims that should concern anyone whose cancer might be in remission. Here’s what he said in a recent interview:
“What I’ve seen way too much of is people who had cancers that were in remission, or that were being well controlled; their cancers have gone completely out of control after getting this vaccine. And we know the vaccine causes a drop in T-cell numbers, and those T-cells are part of our immune system and they are part of the critical weapons our immune system has to fight off cancer cells; so there’s a potential mechanism there. All I can say, is I’ve had way too many people contact me with these reports for me to feel comfortable. I would say that is my newest major safety concern, and it’s also the one that’s going to be the most under-reported in the adverse data base, because if someone has had cancer before the vaccine, there’s no way public health officials will ever link it to the vaccine.” (“Dr Byram Bridle speaks”, Bitchute, :55 second-mark)
So, the vaccine suppresses the immune system?
Yes, it does, and author Alex Berenson provided evidence of this just recently in an article he posted on Substack. Here’s an excerpt:
“… the British government… admitted today, in its newest vaccine surveillance report, that:
“N antibody levels appear to be lower in people who acquire infection following two doses of vaccination.” (Page 23)
What’s this mean?…
What the British are saying is they are now finding the vaccine interferes with your body’s innate ability after infection to produce antibodies against not just the spike protein but other pieces of the virus…
This means vaccinated people will be far more vulnerable to mutations in the spike protein EVEN AFTER THEY HAVE BEEN INFECTED AND RECOVERED ONCE…
… it probably is still more evidence the vaccines may interfere with the development of robust long-term immunity post-infection.” (“URGENT: Covid vaccines will keep you from acquiring full immunity EVEN IF YOU ARE INFECTED AND RECOVER”, Alex Berenson, Substack)
Berenson’s observations square with research that was compiled earlier in the year by scientists in The Netherlands and Germany who:
“… warned that the … (COVID-19) vaccine induces complex reprogramming of innate immune responses that should be considered in the development and use of mRNA-based vaccines… the research team from Radboud University Medical Center and Erasmus MC in the Netherlands… showed that the vaccine altered the production of inflammatory cytokines by innate immune cells following stimulation with both specific (SARS-CoV-2) and non-specific stimuli.
Following vaccination, innate immune cells had a reduced response to toll-like receptor 4 (TLR4), TLR7 and TLR8 – all ligands that play an important role in the immune response to viral infection…. an unexplored area is whether BNT162b2 vaccination has long-term effects on innate immune responses …
This could be very relevant in COVID-19, in which dysregulated inflammation plays an important role in the pathogenesis and severity of the disease,” writes the team. “Multiple studies have shown that long-term innate immune responses can be either increased (trained immunity) or down-regulated (innate immune tolerance) after certain vaccines or infections.” (Research suggests Pfizer-BioNTech COVID-19 vaccine reprograms innate immune responses, new-medical-net)
Berenson’s finding also align with with cutting-edge research showing that the spike protein greatly “impedes adaptive immunity” by preventing DNA from repairing damaged cells. The paper suggests that the spike protein does in fact “impact on the nucleus of the cell, where we store our DNA, our core genetic material.” Here’s more from Berenson’s breakdown of the paper:
“… our cells have mechanisms to repair their own DNA.
But – at least in the experiments these two scientists ran – the spike protein appeared to interfere with our own DNA repair proteins: “Mechanistically, we found that the spike protein localizes in the nucleus and inhibits DNA damage repair by impeding key DNA repair protein BRCA1 and 53BP1 recruitment to the damage site.”
To be clear, the scientists did NOT prove the spike protein was causing these problems in people, or even animals… Nonetheless, at a time when advanced countries that have high mRNA (and DNA/AAV) vaccination rates are seeing unusually full hospitals and higher-than-normal death rates, they are yet more cause for concern. As the authors explained:
“Our findings reveal a potential molecular mechanism by which the spike protein might impede adaptive immunity and underscore the potential side effects of full-length spike-based vaccines.” (“URGENT: Worrisome paper about the spike protein’s impact on DNA and DNA repair”, Alex Berenson, Substack)
Bottom line: If the vaccine does in fact inhibit the body’s innate immune response, then people are going to get alot sicker from seasonal infections that routinely spread through the population. Their path to recovery will also be alot more difficult.
But rather than belabor the immunity angle, let’s move on to the research of Dr Charles Hoffe who was the first physician to provide hard evidence that the vaccines generate blood clots by triggering an immune response in which the body attacks the thin layer of cells lining the walls of the blood vessels. Hoffe found that 62% of his patients that had been vaccinated tested positive for blood clots on a D-dimer test. Naturally, he was alarmed by what he found, particularly since the vaccine “was causing serious neurological events, and even death. When he raised his concerns with the BC College of Physicians, they immediately implemented a gag order, and reprimanded him in an attempt to intimidate, and silence him.”
Hoffe has been interviewed a number of times and always provides a detailed and riveting account of his findings. In a recent interview, he predicted that some vaccinees suffering from clot-related issues would likely die in just three years. Here’s what he said:
“… once you block off a significant number of blood vessels to your lungs, your heart must pump at a much greater resistance to get the blood through your lungs. That causes a condition called pulmonary artery hypertension, which is high blood pressure in your lungs because so many of the blood vessels in your lungs are blocked. And the terrifying thing about this is that people with pulmonary artery hypertension usually die of right-sided heart failure in three years… And not only is the long-term outlook very grim, but with each successive shot, the damage will add and add and add. It’s going to be cumulative because you are getting more and more damaged capillaries.” (“Shock: Doctor Warns That Majority Of Vaccinated Patients Could HavePermanent Heart Damage, Some May Die Within Three Years”Permanent Heart Damage, Some May Die Within Three Years”, Infowars; Minute 6:10)
Once again, there is no discrepancy between the analysis of Whelan, Bridle and Hoffe. And while the focus of their attention might vary slightly, their conclusions are the same. These experimental injections pose serious risks for anyone who allows himself to be inoculated.
Now check out how similar Hoffe’s analysis is to Dr. Rochagne Kilian who was an Emergency Room physician at the GBHS hospital until she resigned in protest. This is a particularly important video as it describes the “oddball” symptoms and exceedingly rare conditions that are now presenting in emergency rooms everywhere following the mass vaccination of millions of people with the “poison-death shot”. (I transcribed the video myself, so there could be errors.)
Dr Rochagné Kilian – Blows the Whistle on Covid-19 Vaccines and D-Dimer Levels
“What I was seeing in my ER department especially in the last 8 to 9 months is related to the D-Dimer levels. We use D-Dimers specifically related to pulmonary embolisms as well as Deep Vein Thrombosis. D-Dimer detects any thrombosis (clots) in the body but it doesn’t give you a diagnosis it gives you a basis for going further and doing an ultrasound and CT scan to either confirm or deny the presence of a pulmonary embolism or Deep Vein Thrombosis.
The first part of 2020 was probably the slowest ever in the emergency department, but when we went into 2021 and the vaccination rollout started, we ended up seeing an increase in stroke, transient ischemic attacks and stroke like presentations. (There were) definitely significant larger numbers of those people coming in. I ended up doing D-dimer tests on these people and never before in my clinical experience had I seen D-dimers and the amount of people with positive D-dimers higher than 2,000, higher than 3,000 and higher than 5,000. My clinical experience told me a needed to go look for a large clot either in their legs or their lungs. And I ended up doing a CT scan on these people. Most of them, and I will say almost all of them, had negative scans which started making me think that if there was not a significant clot in their lungs, but my D-dimer was so much higher than what I was usually seeing, it might not be concentrated in one clot. But that it is multiple micro-thrombi extended throughout the body, and that is so easy to miss because the CT scan is not going to pick it up.
“These people coming into the ER were all people anywhere from about a week to four months after receiving their 2nd injections. There are certain factors that can influence a D-dimer test that can give you a sense of a higher level than would be expected in the body. That said, the patients I was doing D-Dimer tests on did not have a level of maybe a positive 500 or 400 reading. It was more than 3500, more than 5000 ng/ml. So those are significantly positive without any proof of having a pulmonary embolism. If I was seeing high levels of D-dimer without a definite diagnosis, I needed to ask more questions.
One study said, never ignore extremely elevated D-dimer levels. They are specific for serious illness, including venous thrombosis, sepsis, and/or cancer. Even if sharply elevated D-dimer are a seemingly solitary finding, clinical suspicion of severe underlying disease should be maintained.
There were two conditions that stood out and the first one was disseminated intravascular coagulation also known as DIC. The second one is antiphosphlipid syndrome. Both of these conditions are related to an abnormality in either the initiation or the feedback of the coagulation pathway as well as thrombosis or the thrombosis cycle where clots are being broken down. DIC is a serious sometimes life threatening situation in which the proteins in the blood involved in blood clotting become overactive. It’s a cascade that’s difficult to stop once it’s reached a certain level. There are certain conditions that trigger DIC; significant sepsis, underlying viruses, trauma, major surgery, pregnancy and childbirth. And less common causes toxic drug reaction, blood transfusion reaction, and organ transplants. So there was a connection with intravascular products and a possible DIC.
Most cases of DIC are diagnosed rapidly and suddenly which is the acute presentation. But there are cases where it develops gradually, occurring over a longer period of time. This is known as a chronic form of DIC and I would go as far to say a subacute form of DIC that is very easy to miss. Simultaneous clotting and bleeding can occur with chronic DIC. The bleeding part comes in blood in the urine, headaches and other symptoms associated with brain bleeds, bruising, inflammation of red, small dots on the limbs, bleeding at sites of wounds and mucosal bleeding. which means bleeding out of the gums and nose. I definitely saw an increase in nose bleeds and bleeding from previous wound sites. ulcers, as well as rashes that couldn’t be explained. Blood clotting symptoms and signs were symptoms like chest pains, heart attacks, strokes, TIAs, and headaches either related to bleeding or not. As well as symptoms related to kidney failure, because of the clotting of those smaller blood vessels that go to the kidneys. Antiphosphlipid syndrome is a very similar type of condition. But the basis of the antiphosphlipid syndrome is an autoimmune disorder meaning that the body’s immune system makes proteins–known as antibodies–that mistakenly attacks its own body or tissues. That gives the skin the cascading effect of clotting disorder but it is linked to an autoimmune trigger. Basically, it presented in exactly the same way; high blood pressure which I was seeing alot of; first diagnosis of high blood pressure, heart attacks, strokes, TIAs, heart valve problems, repeated headaches or migraines, vision loss, balance and mobility problems, difficulty concentrating or thinking clearly,
The astute listener would start forming a picture of what we’ve been told about Covid-19, and there are research papers connecting Covid 19 with an underlying vascular disease. One of these was a study called “Covid 19; unraveling the clinical progression of Nature’s Virtually perfect Biological weapon.”
“SARS-Cov-2, presenting as Covid-19 syndrome, was not a respiratory basis, but an underlying vascular basis. which had certain phases of incubation, pulmonary phase, pro inflammatory phase, (which once again comes into a cytotoxic inflammation process) then moves into a protothrombic phase . Covid-19 is a thrombotic disease. implications for prevention, antithrombotic therapy and follow up…
This picture shows us certain risk factors, Homeostatic Abnormalities, as well as clinical outcomes. It indicates increased D-dimer levels. It also mentions Venous Thromboembolism, Myocardial Infarction, and Disseminated Intravascular Coagulation that is connected to postulated mechanisms of coagulathopy as well as parthenogenesis of thrombosis in Covid-19…
I started asking the question, if we are able to detect certain connections between vascular abnormalities and Covid-19, and we based our proposed treatment on the spike protein, which includes the Pfizer and Moderna injections, shouldn’t we be looking for similar side effects or complications from that same injection?
If we are mandating certain treatments, we do need to do the due diligence to make sure what the side effects and complications especially in a time where there has not been long term studies.”And that’s what led me to focusing on D-dimers.” (“Dr Rochagné Kilian – Blows the Whistle on Covid-19 Vaccines and D-Dimer Levels“, Bitchute)
Kilian’s statement should be read over and over again. It is the most detailed description we have of the mysterious and deeply sinister machinations of a laboratory-engineered bioweapon that, in effect, turns the vascular and immune systems against the person who was vaccinated. Disseminated intravascular coagulation and antiphosphlipid syndrome are names that are entirely unknown to the American people, and yet, these freakish conditions are now responsible for a growing number of patients that are experiencing bleeding, clotting, headaches, rashes, bruising, high blood pressure, and inflammation . And– in more extreme cases– chest pains, heart attacks, strokes, heart-valve problems, and brain bleeds. One can only guess how the media will try to cover-up these extraordinarily-rare and potentially life-threatening conditions??
When Kilian asks:
“If we are able to detect certain connections between vascular abnormalities and Covid-19… shouldn’t we be looking for similar side effects or complications from that same injection?”
Bingo! If the spike protein produced by the vaccines, inflicts the same internal damage as Covid-19, then shouldn’t doctors expect to see the same symptoms?
Yes, they should. And if the symptoms are the same, then there’s a good chance that vaccine-induced injuries are being misdiagnosed as Covid-19.
Think about that for a minute. That would be the perfect scenario for the pandemic managers and their billionaire backers who’d love to see the impending mountain of carnage blamed on the waning virus instead of on their own poison-death shot.
And that is the evil-genius of the globalist strategy; to remove the fingerprints from the smoking gun before the investigators even arrive at the scene of the crime.
The amount of planning that must have gone into this scam, is simply breathtaking.

This perverse ban on ivermectin, cheap and proven to work
By Kathy Gyngell | TCW Defending Freedom | November 23, 2021
GIVEN the feared winter resurgence of Covid infection despite, or because of, the government’s mass vaccination programme, the continued ban on ivermectin in this country becomes ever more perverse.
It beggars belief that the British public is still denied access to this proven prophylactic and treatment. If the public health authorities are genuinely worried about pressure on hospitals, why have not the Medicines and Health products Regulatory Agency (MHRA), Public Health England, the NHS and Department of Health all gone flat out over this last year to approve ivermectin with the same zeal they gave emergency authorisation to the limited trialled, novel gene therapy, Covid vaccines?
The answer is widespread misinformation from the top down. Put ‘ivermectin’ into the Google search box and what do you come up with? Topping the list is a warning from the US Food and Drug Administration (FDA) why it should NOT be used to treat or prevent Covid-19. Their reason? It’s as simple as the fact that they have not approved it and, because they have not approved, it cannot be used. Trials are ongoing they say. Maybe some are. But plenty have been completed, as Dr Pierre Kory’s paper (he was the lead author) ‘Review of the Emerging Evidence Demonstrating the Efficacy of Ivermectin in the Prophylaxis and Treatment of Covid-19’, published by the American Journal of Therapeutics earlier this year, made quite clear.
By contrast with this detailed review of the evidence the FDA’s substantive concern appears to rest on random reports of harms deriving from self-medication with ivermectin.
The BBC not to be behindhand entered the fray with its customary selective and biased take on ‘the science’. Its recent report entitled ‘How false science created a Covid ‘miracle’ drug‘ made not even the most minimal of checks on the veracity of their assertions, which are pulled apart here. A letter sent to a programme journalist in response to their request for information (in advance of transmission) by Dr Tess Lawrie, the Director of the British Ivermectin Recommendation Development Group (BIRD), an advocacy group of clinicians and scientists from around the world, setting out the science behind the case for authorising it, was completely ignored. Her letter can be found here.
How the BBC came not to ask how it was that remdesivir – a standard medication for Covid in the UK – was approved on the basis of one study when ivermectin, with 63 studies, of them 31 Randomised Controlled Trials (RCT), 7 meta-analyses, 32 Observational Controlled Trials (OCT), multiple country case studies, expert opinion, patient testimony ALL pointing in favour of the medication, was not, is inexplicable.
This is the news source the public is still told to trust.
A blog posted on BIRD last week asked whether there are indeed any genuine gripes about the quality of the evidence, as the FDA and others suggest?
No, there are not. The author argues it is down to a misinformation campaign based on misleading information produced by high profile public health agencies, like the World Health Organisation, itself a victim of disinformation tactics, that has been ‘perpetrated by a minority of corporations to manipulate and delay government action on matters that would adversely affect their income and profit’. Speculation of course. But every indication points that way.
As reported extensively in TCW Defending Freedom, for example here, the WHO is subject to the huge financial influence of the Bill and Melinda Gates Foundation, the organisation’s second biggest donor. Since one of the BMGF’s long-term interest is in delivering vaccines, why would they show any interest in promoting the use of cheap, old repurposed medications in the treatment and prevention of Covid-19? It’s for the very same reason that ivermectin has proved of so little interest to Big Pharma -it’s hardly the money spinner that indemnified world-wide vaccination is.
Worse perhaps than what these big interests have not done is what they have actively done to discredit ivermectin. The BIRD blog relays an analysis by Dr Kory setting out what the WHO ‘did’ with the ivermectin evidence. He says it:
· Failed to publish a pre-established protocol for data exclusion
· Excluded two ‘quasi-randomised’ controlled trials (RCTs) with lower mortality
· Excluded two RCTs that compared ivermectin to or gave it together with other medications, all reporting lower mortality
· Excluded seven other available ivermectin RCT results
· Excluded all RCTs and observational controlled trials (OCTs) investigating ivermectin in the prevention of Covid-19
· Excluded 13 OCTs, more than 5,500 patients, that showed reductions in mortality
· Excluded numerous published and pre-print epidemiologic studies.
The bottom line, however, remains – if ivermectin is good enough and provenly effective for the more than 20 lower-income countries which do distribute it and also benefit from lower Covid rates, why are the populations of wealthier nations and individuals still being denied?
It’s a point that clearly has bothered the chairman of the Tokyo Medical Association, Dr Haruo Ozaki, who would recommend ivermectin for Covid patients, noting that the parts of Africa that use ivermectin to control parasites have a Covid death rate of just 2.2 per 100,000 population, compared with 13 times that death rate among African countries that do not use ivermectin.
‘I would like,’ said Dr Ozaki, ‘the government to consider treatment at the level of the family doctor’ with the informed consent of the patient. So would we.
Vaccinated English adults under 60 are dying at twice the rate of unvaccinated people the same age
And have been for six months. This chart may seem unbelievable or impossible, but it’s correct, based on weekly data from the British government.
By Alex Berenson | Unreported Truths | November 20, 2021
The brown line represents weekly deaths from all causes of vaccinated people aged 10-59, per 100,000 people.
The blue line represents weekly deaths from all causes of unvaccinated people per 100,000 in the same age range.

I have checked the underlying dataset myself and this graph is correct. Vaccinated people under 60 are twice as likely to die as unvaccinated people. And overall deaths in Britain are running well above normal.
I don’t know how to explain this other than vaccine-caused mortality.
The basic data is available here, download the Excel file and see table 4.
Germany’s vakzine fail
Despite over 67% fully vaxxed covid looks worse than 2020
el gato malo | bad cattitude | november 20, 2021
germany reached 50% fully vaxxed on july 27th. that figure is now over 67%.
it is making NO difference.
all else equal, just given prior surges and the greater past generation of natural immunity you’d expect a drop.
but we’re seeing a major rise instead.
to make this easier to see, i grabbed the our world in data data and plotted it year against year starting august 1.
cases are MUCH higher. they are currently 124% higher as a 7 day moving average than this date last year.

as they have been higher throughout, i also plotted this as cumulative cases.
those are 122% higher overall.
they have had well over twice the full period case count vs a year ago.

this is not an artifact of testing.
testing is actually down year on year.
so the reality is actually worse than described above if one were to adjust for sample rate.

cases would be more like triple last year’s count.
so much for “stopping spread.” that looks like spread acceleration (which was predictable)
that is WAY too big a variance to be a 20-45% difference in variant infectiousness.
but that ship had largely sailed.
few with any real familiarity with this data are still claiming that these vaccines stop spread. the evidence has been clear for some time and even the CDC has stopped arguing it.
but perhaps it works on severity?
nope. on a societal scale, it does not seem to. the hospitalization data was sparse and incomplete for germany, so i looked at deaths instead.
they have been higher all along and are basically indistinguishable now.

taken as a cumulative, deaths are 84% higher than the same time span a year ago despite a variant with notably lower CFR.

much of this may be higher case count. higher cases with lower CFR could land you here. it could also be consistent with some vaccine efficacy.
we’re into the realm of error bars too big to do any useful math on that, but it seems plausible to me that we’re seeing a situation like the UK where despite some VE on death, it’s being swamped by the vaccinated being at higher risk for cases and by a leaky vaccine increasing CFR on delta variant so even the vaccinated have become more likely overall to die of covid.
(if you have triple the cases and triple the CFR vs what you would have had, you’d need 89% VE just to break even. none of these vaccines are even close to that in practice)
we’re obviously playing a bit of a mosaic game here, that would be my odds on bet.
this is the shape of the disaster starting to play out all over the world.
these vaccines have not attenuated covid. they have rekindled its spread.
the vaccinated have become a potent vector to carry the disease and to actually make the disease itself worse because leaky vaccines invert the evolutionary gradient and select for hotter rather than milder strains.
this is going to keep happening as regions come into season. people will blame “the variants” but the fact is that the reason delta case fatality rate basically tripled on an age cohorted basis over the summer (when it should have been dropping) IS the vaccines.

this was not exogenous to human action. it did not “just happen.” this is such an outlier outcome that it might as well be water flowing uphill. when you see that, you have to suspect external forcing and there is an obvious culprit, the timing matches, and we know that this is what leaky vaccines do.
boosting is just going to make it worse and invert the viral gradient even further. any short term help from boosted antibodies (at the price of another round of dangerous adverse events) will just run up a bigger bigger bill to pay when it comes due later, and it’s far from clear that this booster strategy even provides short term help.
in fact, there is basically no evidence that their high vaxx rates, green pass, and heavy restrictions accomplished ANYTHING when compared to the neighbors.
i see no way to look at this and say “vaccines worked.”
this is the outcome no one wanted but that many (including certain internet felines) warned against.
rolling out a functionally untested vaccine t this sort of scale was a wildly reckless global epidemiological joyride. it’s not going well.
i wish i had better news here, but this is unfortunately playing out just as one would predict for a vaccine accelerated double dip pandemic driven by hotter substrain selection and reduction of sterilizing immunity.
i suspect the OAS issue here is very real (and possibly permanent in the vaccinated even post live virus exposure and recovery).
there are going to be some rotten surprises for those who thought they had vaxxed their way out of this.
this was not a fire extinguisher.
more and more, it looks like it was gasoline.
Another major red flag about Covid vaccines and death
By Alex Berenson | Unreported Truths | November 18, 2021
People appear to die at rates 20 percent or more above normal for weeks after receiving their second Covid vaccine dose, according to data from a huge Swedish study.
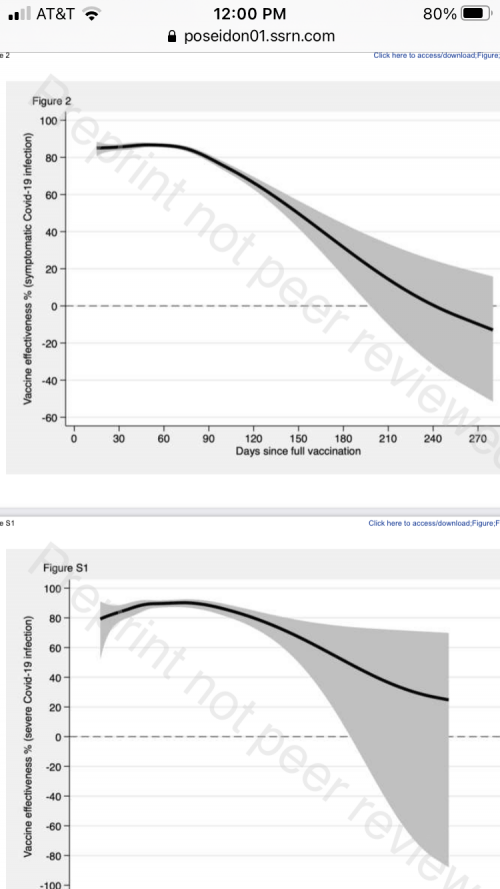
The figures are buried in a preprint paper on vaccine effectiveness released last month. The headline finding of the paper was that protection against Covid, including severe cases, plunged after six months.
The researchers did not explicitly examine deaths from all causes – which have risen since the summer in many countries that have highly vaccinated populations.
But on page 32 of the 34-page report, a chart shows that 3,939 of 4.03 million Swedes who received the second dose died less than two weeks later.
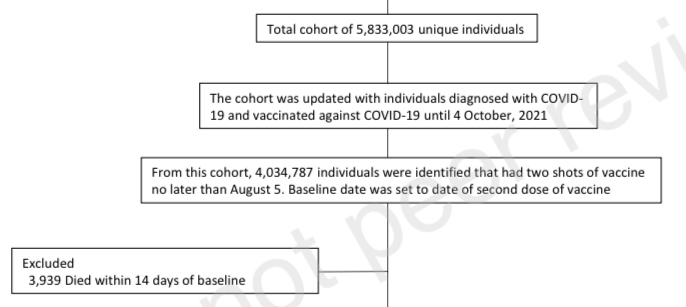
(SOURCE: https://papers.ssrn.com/sol3/papers.cfm?abstract_id=3949410)
Over a one-year period, that rate of death would translate into an annual mortality rate of about 2.5 percent a year – 1 person in 40 – almost three times the overall Swedish average. In a typical year, about 1 in 115 Swedes dies.
Of course, that huge gap does not account for an important confounding factor: younger people, who have a much lower risk of death, were less likely to be vaccinated.
But Sweden also provides detailed data on overall deaths nationally, making a crude baseline comparison possible.
That data shows that from an average of about 1,650 Swedes died every week between 2015 and 2019 between April 1 and early August, the period in which almost all of those 4 million Swedes in the study received their second dose. Death rates hardly varied over those years.
(SOURCE: https://www.scb.se/en/finding-statistics/statistics-by-subject-area/population/population-composition/population-statistics/)
In other words, during the spring and summer, Sweden normally has about 3,300 deaths every two weeks – not just in the people who received vaccines, but in all 10.6 million of its people.
So let’s make an incredibly conservative assumption, one that strongly favors the vaccines. (The next couple paragraphs are a bit tricky, but I hope the payoff is worth taking the time to read and think through them.)
Assume that the group of people who received vaccines were so much older and unhealthier than those who didn’t that they would have accounted for every single death in Sweden whether or not they were vaccinated. In other words, assume that even if the vaccines did not exist, every person in Sweden who died would have been part of that group of 4.03 million people the researchers tracked – while not one other person would have died.
In that case, those 4.03 million people “should” have about 3,300 deaths every two weeks. They CANNOT HAVE MORE – because all of Sweden does not have more.
But the vaccines do exist. Those 4.03 million people received them. And in the two weeks after receiving the second vaccine dose, as a group, the researchers reported they had not about 3,300 deaths, but 3,939.
And 3,939 deaths is about 20 percent more deaths than “should” have occurred in those two post-vaccine weeks. Again, the 20 percent figure understates the real gap, because in the real world some deaths will occur in the 6.6 million unvaccinated people too, so the actual baseline number for the vaccinated group is not 3,300 deaths but somewhat lower.
Unfortunately, the researchers did not report any details on the deaths, so it is impossible to know if they are disproportionately cardiovascular. It is also impossible to know whether one particular vaccine was disproportionately linked to deaths. (Sweden used mostly the Pfizer mRNA vaccine, as well as some of AstraZeneca’s DNA/AAV vaccine, which is not available in the United States, and a small amount of Moderna’s mRNA vaccine.)
Of course, it is just possible the extra deaths are due to chance. Or that the handful of elderly Swedes who received vaccines in February and March accounted for a hugely disproportionate number of the post-vaccine deaths. (Because per-week Swedish death rates are higher in the winter, a large number of post-vaccine deaths in those months would somewhat reduce the strength of the signal, though it would still exist.)
But the caveats aside, the Swedish figures offer a very large real-world dataset apparently showing a notable increase in all-cause mortality directly following Covid vaccination.
They are yet another piece of evidence in an increasingly worrying picture – alongside case and anecdotal reports, a known link to heart inflammation in young men, the updated Pfizer clinical trial data revealing a numerical imbalance in deaths in vaccinated people, and most importantly the general rise in all-cause mortality in many countries.
And all of these red flags come for vaccines that – if the Swedish data are correct – may actually raise the risk of Covid infection after about eight months.
Yes, RAISE. See how that black line drops below the zero level on the top chart? That represents negative effectiveness, which is another way to say people who are vaccinated are MORE likely to be infected than those who aren’t.
And, as the second chart shows, effectiveness against severe Covid infection is also spiraling towards zero.
Yet the Biden Administration and governments across Europe continue to try to force more people to take these vaccines.
Why?
Dutch deaths more than 20 percent higher than previous year average
Free West Media | November 21, 2021
Last week the number of deaths was more than 20 percent higher than usual for this time of year. The Dutch Central Bureau of Statistics (CBS) reported 3,750 deaths, nearly 850 more than expected.
According to the statistical office, the higher mortality can be seen in all age groups.
Statistics Netherlands does not yet have an explanation for the higher mortality. More deaths of Corona patients were registered at RIVM last week.
According to the CBS, the excess mortality has clearly increased in recent weeks. But since the beginning of August, the mortality has already been above the usual numbers during this period.
It is estimated that 2,100 people aged 80 and older died last week. That is almost 500 more than expected. Mortality in this age group has been remarkably high for four weeks. This also applies to people aged 65 to 80. In this age group, 1,200 people died last week, nearly 300 more than expected. Among people under the age of 65, the death rate last week was an estimated 450, more than 50 more than expected.
In the Netherlands, 85 percent of people over the age of 18 are fully vaccinated, and many had their jabs only recently. Vaccine salespeople maintain that the shots offer protection in the first few months before the “protection” starts to wane. They blame the unvaccinated for the rise in deaths. This is obviously false.

The number of people getting infected has never been worse, despite the high vaccination rate. The jabs are evidently not doing what had been promised.
In total, 23,680 cases were reported on Thursday, the fourth day in a row of record-setting case numbers following a week that broke the record for the highest number of new infections (110,000) since the pandemic began – a 44 percent rise over the week before, and this week’s figures have not yet been added.
Dutch officials have started injecting those over 80 with boosters on Thursday, weeks earlier than planned.
Anke Huckriede, professor of vaccinology at the University of Groningen, said the intramuscular jabs do not offer protection in the upper respiratory tract, where the virus enters our bodies.
With only some 15 percent of the adult population unvaccinated, the Dutch have a higher vaccine uptake than the majority of the world. But Bas van den Putte, professor of health communication at the University of Amsterdam and a member of the scientific advisory board of the RIVM’s Corona Behavioural Unit admitted that he could not explain the dramatic rise in deaths.
 Other “experts” sadly had no explanation for vaccine failure either.
Frits Rosendaal, professor of clinical epidemiology at the Leiden University Medical Center, blamed geography and population density while Huckriede said she had no idea why this was happening. “We just don’t know.”
Based on weekly data from the Office of National Statistics (ONS) in the UK, vaccinated people under 60 are twice as likely to die as unvaccinated people. And overall deaths in Britain are far above normal.
As in Germany, Swedes also appear to die at rates 20 percent or more above normal for weeks after receiving their second Covid jab, according to data from a Swedish study.
Despite the hard evidence piling up of a complete public health failure on a global scale, governments and politicians continue to stick to their useless mandates.
Featured Video

False Flags and the Dawn of Bioterrorism
or go to
Aletho News Archives – Video-Images
From the Archives
How 1960’s French Nuclear Tests Are Still Claiming Lives in Algeria
Sputnik – 15.02.2018
On February 13, 1960, France carried out its first nuclear test in Algeria’s southern Reggane region. According to official statistics, 17 nuclear tests were carried out in total over the next 6 years. The area remains affected, and local scientists say that radioactive contamination has caused genetic mutations and irreversibly changed the region.
There are no official statistics on the number of victims. The only figures can be found in the records kept by the French representative of the local church, which lists 42,000 victims of nuclear tests. Three years ago, the French Ministry of Defense issued a statement, putting the number at 27,000 people. The victims include French soldiers as well as local Algerians who lived in the surrounding areas. … continue
Blog Roll
 Aletho News
- Using nuclear weapons, the US-Israeli alliance still can’t beat Iran
- Sunset on the Quality of Western Propaganda: Arrival of the Dr Strangelove Moment
- Ukrainian general accused of protecting crime bosses
- US-‘Israel’ alliance faces growing rupture after midterms
- GOP’s Crushing Midterm Loss Could Reshape US Political Landscape – Analyst
- Midterm loss gives Congress power to rein in US war on Iran
- Midterms Were ‘Vote of No Confidence’ in GOP, But Iran Has No Illusions About Democrats – Marandi
- Israeli Soldiers Inadvertently Prove Their Own Genocidal Guilt
- Ukraine arrests woman who exposed Azov battalion’s ‘torture chamber’
- Did Israel lose the midterms?
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago

