Anthony Fauci’s National Institutes of Health once experimented on foster children with AIDS, testing experimental drugs on the children while almost always failing to provide an independent advocate to make sure the children remain safe and healthy. This happened throughout the late 1980s and 1990s, and the practice was exposed in 2005.
According to Anthony Fauci’s biography page on the official NIH website, the longest-serving government employee began working for the NIH in 1968. In 1984, Fauci became the Director of NIAID, a position he still holds today.
As Director of NIAID, Fauci oversees research to “prevent, diagnose, and treat infectious and immune-mediated diseases, including HIV/AIDS” according to the website. In 1988, Fauci became the first Director of the Office of AIDS research.
While Fauci was in these roles, it was revealed in 2005, the NIH oversaw the enrollment of thousands of foster children with AIDS into controversial programs that allowed them to receive experimental drugs designed to combat the illness. Some of these children later died, and most were not given independent advocates that were promised.
According to John Soloman, then reporting for the Associated Press, the NIH “promised in writing to provide an independent advocate to safeguard the kids’ well-being as they tested potent AIDS drugs,” however, these advocates failed to materialize for almost every child involved. The subjects – foster children without stable home lives – ranged from infants to late teens.
Solomon wrote that, with a general lack of oversight, “Several studies that enlisted foster children reported that patients suffered side effects such as rashes, vomiting and sharp drops in infection-fighting blood cells, and one reported a ‘disturbing’ higher death rate among children who took higher doses of a drug, records show.” (READ MORE: NIH Quietly Changes Definition Of ‘Gain-Of-Function’ Amid Fauci, Wuhan Lab Scandal Fallout)
“Some foster children died during studies,” reported Solomon after noting that the majority of children appear to not have received an advocate. “State or city agencies said they could find no records that any deaths were directly caused by the experimental treatments,” he noted.
A 2009 articlefromThe New York Times claims that no New York City children “died as a result of the trials” and that children in the city were not selected for the trials based on their race.
Still, the Times found “that the agency had not always followed its own protocols and kept poor records.” The Times also discovered that some of the children died, but those involved with the research asserted the deaths were unrelated to the experimental drugs.
In 2018, only two years before the mainstream media would lionize Fauci via its nonstop coverage of COVID-19, then-82-year-old AIDS activist Larry Kramer described Fauci as “The consummate manipulative bureaucrat who speaks out of too many sides of his mouth.’’ Kramer died in May of 2020.
We also know that Fauci was actively, personally engaged in AIDS research around the time the foster children were being used for experiments. In fact, Fauci told NPR earlier this year that, in the 1980s, he would clandestinely visit gay bath houses, bars, and night clubs with the goal of physically witnessing the transmission of HIV live and in person.
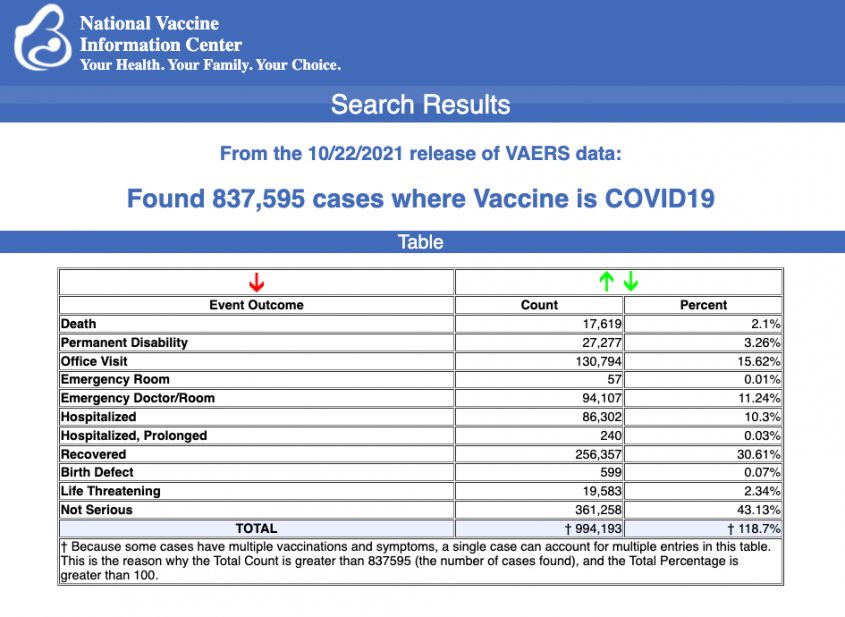
Data released Friday by the Centers for Disease Control and Prevention (CDC) showed that between Dec. 14, 2020, and Oct. 22, 2021, a total of 837,595 adverse events following COVID vaccines were reported to the Vaccine Adverse Event Reporting System (VAERS).
The data included a total of 17,619 reports of deaths — an increase of 491 over the previous week. There were 127,457 reports of serious injuries, including deaths, during the same time period — up 4,624 compared with the previous week.
Of the 8,068 U.S. deaths reported as of Oct. 22, 11% occurred within 24 hours of vaccination, 15% occurred within 48 hours of vaccination and 27% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 411.6 million COVID vaccine doses had been administered as of Oct. 15. This includes: 242 million doses of Pfizer, 154 million doses of Moderna and 15 million doses of Johnson & Johnson (J&J).
The data come directly from reports submitted to VAERS, the primary government-funded system for reporting adverse vaccine reactions in the U.S.
Every Friday, VAERS makes public all vaccine injury reports received as of a specified date, usually about a week prior to the release date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed.
Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
This week’s U.S. data for 12- to 17-year-olds show:
Another recent death includes a 15-year-old male who died six days after receiving his first dose of Pfizer’s COVID vaccine. According to his VAERS report (VAERS I.D. 1764974), the previously healthy teen complained of brief unilateral shoulder pain five days after receiving his COVID vaccine. The next day he played with two friends at a community pond, swung on a rope swing, flipped into the air, and landed in the water feet first. He surfaced, laughed and told his friends “Wow, that hurt!” He then swam toward shore underwater, as was his usual routine, but did not re-emerge.
An autopsy showed no external indication of a head injury, but there was a small subgaleal hemorrhage — a rare, but lethal bleeding disorder — over the left occiput. In addition, the boy had a mildly elevated cardiac mass, increased left ventricular wall thickness and small foci of myocardial inflammation of the lateral wall of the left ventricle with myocyte necrosis consistent with myocardial infarction.
58 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases
attributed to Pfizer’s vaccine.
539 reports of myocarditis and pericarditis (heart inflammation) with 531 cases attributed to Pfizer’s vaccine.
125 reports of blood clotting disorders, with all cases attributed to Pfizer.
This week’s U.S. VAERS data, from Dec. 14, 2020, to Oct. 22, 2021, for all age groups combined, show:
19% of deaths were related to cardiac disorders.
54% of those who died were male, 41% were female and the remaining death reports did not include gender of the deceased.
FDA grants Emergency Use Authorization for Pfizer Vaccine for 5- to 11-year-olds
The U.S. Food and Drug Administration (FDA) today granted Emergency Use Authorization (EUA) for the Pfizer-BioNTech COVID vaccine for children 5 to 11 years old, The Associated Press reported.
The announcement followed Tuesday’s recommendation by the FDA’s vaccine advisory committee that the agency grant Pfizer’s request. The advisory committee vote passed with 17 in support, and one abstention.
“The vaccine was not granted FDA approval, but instead an emergency use authorization. Emergency authorizations are used when the secretary of health and human services has declared a public health emergency to more quickly clear the use of vaccines, treatments, and diagnostic tests. These authorizations lapse when the state of emergency ends. Pfizer’s vaccine was fully approved for those age 16 and older in August, and was previously granted an emergency use authorization for use in adolescents ages 12 to 15.”
The dose for younger children will be one-third the strength given to people 12 and older, with two shots given three weeks apart. Before the shots can be rolled out, the CDC must weigh in with its own recommendations.
Based on CDC data presented during the meeting, among children 5 to <12 years of age, there have been approximately 1.8 million confirmed and reported COVID cases since the beginning of the pandemic, and only 143 COVID-related deaths in the U.S. through Oct. 14.
Pfizer provided safety data on two study cohorts of children ages 5 to 11, both of roughly equal size. The first group was followed for only about two months, the second for only two-and-a-half weeks.
Pfizer said “post-vaccination myocarditis/pericarditis” in participants 5 to <12 years of age will not be studied until after the vaccine is authorized for children.
Pfizer vaccine ‘failed any reasonable risk-benefit calculus in connection with children,’ scientist says Brian Dressen, Ph.D., is one of the scientists who testified Tuesday during the FDA advisory committee’s 8-hour hearing. Dressen is also the husband of Brianne Dressen, who in 2020 developed a severe neurological injury during the Utah-based portion of the U.S. AstraZeneca COVID vaccine.
During his 3-minute testimony, Dressen, a chemist with an extensive background in researching and assessing the degree of efficacy in new technologies, told the FDA advisory panel Pfizer’s vaccine “failed any reasonable risk-benefit calculus in connection with children.”
Dressen said the decision to authorize for 5- to 11-year-olds is being rushed and is based on “incomplete data from underpowered trials, insufficient to predict rates of severe and long-lasting adverse reactions.”
Dressen urged the committee to reject the EUA modification and direct Pfizer to perform trials that decisively demonstrate the benefits outweigh the risks for children.
Dressen’s wife was severely injured last November after receiving her first and only dose of a COVID vaccine administered during a clinical trial.
“Because study protocol requires two doses, she was dropped from the trial, and her access to the study app deleted,” Dressen said. “Her reaction is not described in the recently released clinical trial report — 266 participants are described as having an adverse event leading to discontinuation, with 56 neurological reactions tallied.”
CDC updates guidance allowing immunocompromised to get a fourth COVID shot
Immunocompromised adults who received a third dose of either the Pfizer-BioNTech or Moderna COVID vaccine will become eligible for a fourth booster shot six months after receiving their third dose, according to CDC guidance issued Monday.
“In such situations, people who are moderately and severely immunocompromised may receive a total of four vaccine doses,” with the fourth coming at least six months after the third, the CDC’s new guidelines said.
However, a third dose is now considered part of the primary series, rather than a booster. The earliest that immunocompromised people who received a third mRNA vaccine shot can get a fourth shot as a booster would be February.
The agency said people could select that booster from any of the three COVID vaccines available in the U.S, including J&J, but specified a fourth dose of Moderna’s vaccine should be half the size of a normal dose.
Double-vaccinated can still spread the virus at home
Fully vaccinated people are catching COVID and passing it on to those they live with, warn experts in the UK. A British study published in the Lancet Oct. 29, showed individuals who have had two vaccine doses can be just as infectious as those who have not been jabbed.
Even if they are asymptomatic or have few symptoms, the chance of transmitting the virus to other unvaccinated housemates is about two in five, or 38%. This drops to one in four, or 25%, if housemates are also fully vaccinated.
“By carrying out repeated and frequent sampling from contacts of COVID-19 cases, we found that vaccinated people can contract and pass on an infection within households, including to vaccinated household members,” said Dr. Anika Singanayagam, co-lead author of the study.
“Our findings provide important insights into … why the Delta variant is continuing to cause high COVID-19 case numbers around the world, even in countries with high vaccination rates.
Vaccinated contacts who tested positive for COVID on average received their shots longer ago than those who tested negative, which the authors said was evidence of waning immunity and supported the need for booster shots.
Neil Ferguson, an Imperial epidemiologist, said the transmissibility of Delta meant that it was unlikely Britain would reach herd immunity for long.
“That may happen in the next few weeks: If the epidemic’s current transmission peaks and then starts declining, we have by definition in some sense reached herd immunity, but it is not going to be a permanent thing,” Ferguson told reporters.
16-year-old girl develops severe vulvar ulcers after second Pfizer shot
According to the report, a 16-year-old non-sexually active female presented to the pediatric gynecology clinic with vaginal pain six days after receiving her second dose of Pfizer’s COVID vaccine.
Within 24 hours of receiving the vaccine, the girl developed fever, fatigue, myalgias and “sores” in her vaginal area. Over the next two days, right-sided lesions in her vaginal area coalesced and became more painful. The teen went to the urgent care with a fever of 105 degrees. She was diagnosed with a Bartholin gland abscess.
Despite antibiotic therapy, her symptoms worsened and her lesions were covered in exudate with a necrotic, ring-like border. In the gynecology clinic, the patient’s lesions were exquisitely painful, resulting in difficulty with urination, defecation and walking. She had no respiratory symptoms and no history of COVID exposure.
The report said the findings “were consistent with vulvar aphthous ulcers in association with influenza-like symptoms following Pfizer BioNTech (BNT162b2) COVID-19 vaccination.”
“Our patient had typical clinical features of aphthous ulcer, including an influenza-like prodrome and characteristic dermatologic manifestations which occurred after receiving the Pfizer COVID vaccine,” the authors wrote. According to the report, the girl’s case was submitted to VAERS “due to the temporal relationship with COVID vaccine administration.”
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
In early 2020, as scientists were analyzing the SARS-CoV-2 virus, it was theorized the virulence and infectivity could be explained by gain-of-function research. Months of lab analyses and political arguments ensued over whether the virus was leaked from the lab or developed naturally in the wild.
Despite public outcry and denials from top health experts that the virus was created, the preponderance of the evidence indicates the virus was manipulated in the lab.1 Then, the United States Agency for International Development (USAID), publicly announced October 5, 2021, they would grant Washington State University $125 million “to detect emerging viruses.”2
This is far greater than the $7.4 million Newsweek 3 reported was granted to the NIAID for gain-of-function work on bat coronavirus in Wuhan, China. Dr. Kanta Subbarao is from the Laboratory of Infectious Disease at the National Institute of Allergy and Infectious Diseases (NIAID) at the National Institutes of Health (NIH).4
According to Subbarao, these experiments “are routine virological methods” and “emphasized that such experiments in virology are fundamental to understanding the biology, ecology and pathogenesis of viruses and added that much basic knowledge is still lacking for SARS-CoV and MERS-CoV.”
Historically, the NIH had funded gain-of-function research, but this was paused in October 2014. December 19, 2017, the NIH announced they would lift the funding pause on gain-of-function research and stated:5
“We have a responsibility to ensure that research with infectious agents is conducted responsibly, and that we consider the potential biosafety and biosecurity risks associated with such research.”
As Newsweek reported, the “second phase of the project, beginning that year [2019], included additional surveillance work but also gain-of-function research for the purpose of understanding how bat coronaviruses could mutate to attack humans. The project was run by EcoHealth Alliance, a nonprofit research group, under the direction of president Peter Daszak.”6
After months of public and political debate, argument and division, the U.S. government agency USAID stepped into the spotlight again and awarded millions to a university “to make sure the world is better prepared.”7
University Accepts $125 Million for Gain-of-Function Research
Washington State University published a press release8 October 5, 2021, announcing they had been awarded $125 million from USAID. Called a “cooperative agreement,” the university is heading up a new five-year global project in which they have been asked to9 “… detect and characterize unknown viruses which have the potential to spill over from wildlife and domestic animals to human populations.”
The project will partner with 12 countries throughout Africa, Latin America and Asia. The idea is to carry out animal surveillance within the country’s borders using their facilities. USAID announced the project “to detect unknown viruses with pandemic potential” as part of Discovery & Exploration of Emerging Pathogens Viral Zoonoses (DEEP VZN).10
The organization believes that SARS-CoV-2 has demonstrated how infectious diseases threaten society. This is especially true of viruses that have been manipulated to increase virulence and infectivity in humans.11 The goal of the project is to collect over 800,000 samples over five years from wildlife and then determine the zoonotic potential of these viruses.12
“The project will focus on finding previously unknown pathogens from three viral families that have a large potential for viral spillover from animals to humans: coronaviruses, the family that includes SARS-CoV-2 the virus that causes COVID-19; filoviruses, such as the Ebola virus; and paramyxoviruses which includes the viruses that cause measles and Nipah.”
Ebola virus was first discovered in 1976 and has since led to several deadly outbreaks in African countries. The CDC13 writes that scientists do not know where Ebola virus comes from. However, the virus can spread through direct contact with body fluids and tissues of infected animals.
Nipah was first discovered in 199914 and the first outbreak resulted in 300 human cases and more than 100 deaths. The animal host is believed to be the fruit bat that can spread the disease to animals and humans. The infection also spreads from person to person and can range from mild to severe. Up to 70% of those infected between 1998 and 2018 have died.
The project expects to find between 8,000 a nd 12,000 new viruses, “which researchers will then screen and sequence the genomes of the ones that pose the most risk to animal and human health.”15 In case this sounds familiar, as Breaking Points anchor emphasizes, this has been “code” for gain-of-function research,16 or detecting viruses that have not yet “emerged.”
Documents Reveal Virus Was Manipulated to Increase Virulence
An ongoing Freedom of Information Act litigation brought by The Intercept17 against the NIH resulted in the release of over 900 pages of previously undisclosed documents that detailed the work of EcoHealth Alliance as a subcontractor of gain-of-function research on bat coronavirus through the Wuhan Institute of Virology.
It’s important to note that the moratorium on federal funding of gain-of-function research instituted in 2014 was initiated on the heels of a high-profile lab mishap at the CDC and controversial experiments over deadly bird flu virus that was manipulated to be more contagious.18
Reportedly, the goal was to determine if bird flu could mutate in the wild and start a pandemic. David Relman, a microbiologist from Stanford University, stated the obvious when he said,19 “I don’t think it’s wise or appropriate for us to create large risks that don’t already exist.”
The new documents released under the FOIA request by The Intercept contained previously unpublished proposals by the NIAID and updates to the EcoHealth Alliance’s research. As reported in The Intercept,20
“The documents contain several critical details about the research in Wuhan, including the fact that key experimental work with humanized mice was conducted at a biosafety level 3 lab at Wuhan University Center for Animal Experiment — and not at the Wuhan Institute of Virology, as was previously assumed.
The documents raise additional questions about the theory that the pandemic may have begun in a lab accident, an idea that Daszak has aggressively dismissed.”
According to The Intercept, Richard Ebright, molecular biologist at Rutgers University, also reviewed the documents released in the FOIA. He told The Intercept that the documents contained vital Information about the research being conducted in the Wuhan lab. He wrote:21
“The viruses they constructed were tested for their ability to infect mice that were engineered to display human type receptors on their cell. While they were working on SARS-related coronavirus, they were carrying out a parallel project at the same time on MERS-related coronavirus.”
In other words, the lab was doing parallel research on two types of coronaviruses that were able to infect humanized mice. In a series of posts on Twitter, Ebright goes on to say:22
“The materials further reveal for the first time that one of the resulting novel, laboratory-generated SARS-related coronaviruses — one not been previously disclosed publicly — was more pathogenic to humanized mice than the starting virus from which it was constructed … and thus not only was reasonably anticipated to exhibit enhanced pathogenicity, but, indeed, was *demonstrated* to exhibit enhanced pathogenicity.
The documents make it clear that assertions by the NIH Director, Francis Collins, and the NIAID Director, Anthony Fauci, that the NIH did not support gain-of-function research or potential pandemic pathogen enhancement at WIV are untruthful.”
This new information again questions the origins of COVID-19, which many scientists proposed was from a wet market in China where humans and animals are in close contact. However, bioscience safety experts have long suspected a lab origin. It appears that some in the U.S. government and some scientists have not learned from the gain-of-function research in Wuhan and have brought the problem home to roost.
International Athletes Willfully Exposed to Lab-Leaked Virus
Whether the virus was released intentionally or accidentally is a question for another day. Long before the outbreak, scientists had expressed concerns that these kinds of experiments may end up creating the thing they were reportedly working against. As the Intercept reports,23 in 2014 a grant was awarded to EcoHealth Alliance titled “Understanding the Risk of Bat Coronavirus Emergence.”
Part of the grant money was earmarked to identify and alter bat coronaviruses suspected of being able to infect humans. In the grant the writers acknowledged concerns stating, “Fieldwork involves the highest risk of exposure to SARS or other CoVs, while working in caves with high bat density overhead and the potential for fecal dust to be inhaled.”24
In the USAID announcement, the government agency gives an overview of the goals in one sentence:25 “The Biden-Harris Administration is committed to advancing global health security, international pandemic preparedness and global health resilience.” As a Breaking Points anchor in this video says,26 “So essentially, we have learned nothing.”
August 1, 2021, Rep Michael McCaul, R-Texas, the ranking member of the House Foreign Affairs committee, published an addendum to the investigation into the origins of SARS-CoV-2. The investigation concluded:27
“… the preponderance of evidence suggests SARS-CoV-2 was accidentally released from a Wuhan Institute of Virology laboratory sometime prior to September 12, 2019. The virus, or the viral sequence that was genetically manipulated, was likely collected in a cave in Yunnan province, PRC, between 2012 and 2015.
Researchers at the WIV, officials within the CCP, and potentially American citizens directly engaged in efforts to obfuscate information related to the origins of the virus and to suppress public debate of a possible lab leak.”
By the end of August 2021, the White House released a statement from President Biden essentially calling the intelligence report inconclusive,28 “while this review has concluded, our efforts to understand the origins of this pandemic will not rest.”
Multiple pieces of information led the committee to conclude there was ample evidence to support genetic modification of the coronavirus and there was a cover-up which “likely turned what could have been a local outbreak into a global pandemic.”29 The cover-up involved the 2019 Military Games held October 18, 2019, in Wuhan China.
The report demonstrated that by October 2019, health officials in Wuhan were well aware of an outbreak of infectious disease. The athletes reported that the city appeared to be in lockdown30 while they were there. The games drew over 9,000 athletes from 109 countries. The Chinese government had 236,000 volunteers, 90 hotels, three railroad stations and more than 2,000 drivers available for the athletes.
The report included a quote from a Canadian Armed Forces personnel who participated in the games, which appeared in The Financial Post.31 He was told the lockdown in the city was to make it easier for the participants in the games to get around. Twelve days after arrival in Wuhan, he was sick with fever, chills, vomiting and insomnia.
He reported that on the flight home to Canada, 60 athletes were isolated at the back of the plane for the 12-hour flight with a range of symptoms including coughing and diarrhea. After returning home, the same service member found his family members got ill, which the report finds is:32
“… consistent with both human-to-human transmission of a viral infection and COVID-19. Similar claims about COVID-19 like symptoms have been made by athletes from Germany, France, Italy, and Sweden.”
Funding Gain-of-Function Research Out in the Open
Following the release of The Intercept report and additional grant documentation, some GOP members are calling for Dr. Anthony Fauci to resign while others want him fired from his position on the White House COVID-19 response team.33
U.S. Sen. Rand Paul, R-Ky. has referred Fauci to the Department of Justice for an investigation for possible perjury charges relating to his Congressional testimony in May 202134 and July 2021,35 when he vehemently denied ever having funded gain-of-function research.
Paul specifically asked the DOJ36 to investigate whether Fauci violated 18 U.S. Code § 10012137 — which makes it a federal crime to make “any materially false, fictitious or fraudulent statement or representation” as part of “any investigation or review” conducted by Congress — or any other statute.
How much genetic manipulation and gain-of-function research that occurs as a result of the $125 million grant to the university may not come to light for years. However, it is incumbent on our government to ensure biosafety in the labs doing the research and, for the public, to call for a halt of this type of research that “create[s] large risks that don’t already exist.”38
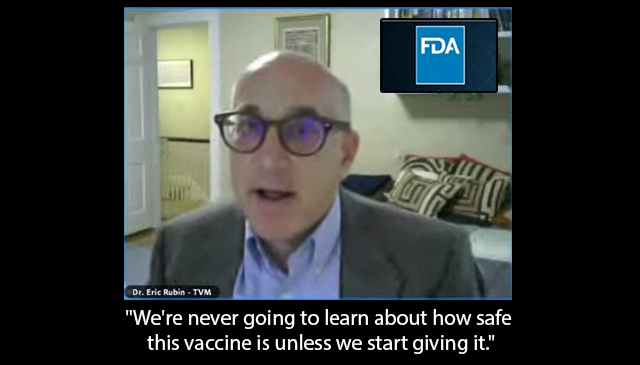
An FDA vaccine advisory panel on Tuesday voted unanimously 17-0 in favor shooting up kids aged 5-11 with Pfizer’s experimental mRNA injection with panelist Dr Eric Rubin stating, “we’re never going to learn about how safe this vaccine is unless we start giving it.”
The panel voted in favor of experimenting on tens of millions of helpless children with zero long-term data on side effects because 94 children between 5 and 11 have died with COVID-19 (they claimed “of”) and “all have names. All of them had mothers,” to quote the emotional gobbledegook uttered by panelist Patrick S. Moore.
“To me, it seems that it is a hard decision but a clear one,” said Patrick S. Moore, a University of Pittsburgh microbiologist and committee member. He noted that 94 children between 5 and 11 have died of covid-19, and “all have names. All of them had mothers.”
Members of the FDA’s vaccine-advisory panel supported Moderna’s booster dose even though the evidence for it was from a small study and had mixed results.
“It’s more a gut feeling rather than based on really truly serious data,” said Patrick Moore, a member of the committee and a professor of molecular genetics and biochemistry at the University of Pittsburgh School of Medicine. “The data itself is not strong, but it is certainly going in the direction that is supportive of this vote.”
Mortality data tells us information about deaths in Australia and is usually released every 6 weeks. For an unexplained reason, the latest data is over 15 weeks overdue.
As Government becomes more and more powerful, anyone who challenges the current policies is smeared and censored. The legacy media happily parrots the propaganda, afraid of losing government funding.
Unreliable, intermittent wind and solar energy will leave Australian families sitting in the dark without coal-fired power to back them. ‘Renewables’ only farm taxpayer money, not energy.
Where to even begin with the FDA’s preposterous risk-benefit analysis of Pfizer’s mRNA COVID-19 “vaccine” in children ages 5 to 11?
Let’s start with my bona fides. I have a year of undergraduate statistics at one of the best liberal arts colleges in America (Swarthmore). I have a year of graduate statistics at the masters program rated #1 for policy analysis (UC Berkeley). And I have a Ph.D. in political economy from one of the top universities in the world (University of Sydney). My research focus is on corruption in the pharmaceutical industry so I’ve read scientific studies in connection with vaccines nearly every day for 5 years. Earlier in my career I worked professionally tearing apart shoddy cost-benefit analyses prepared by corporations that were trying to get tax breaks, contracts, and other concessions from local government. Suffice it to say I’ve thought a lot about risk-benefit analysis and I’m better equipped than most to read one of these documents.
The FDA’s risk-benefit analysis in connection with Pfizer’s Emergency Use Authorization (EUA) application to inject children ages 5 to 11 with their COVID-19 vaccine is one of the shoddiest documents I’ve ever seen.
Let’s take it from the top:
🚩 COVID-19 rates in children ages 5 to 11 are so low that there were ZERO cases of severe COVID-19 and ZERO cases of death from COVID in either the treatment (n= 1,518) or control group (n= 750). So any claims you see in the press about the Pfizer vaccine being “90% effective” in children are meaningless because they are referring to mild cases from which children usually recover quickly (and then have robust broad spectrum immunity). So there is literally no emergency in this population for which one could apply for Emergency Use Authorization. Pfizer’s application should be dead on arrival if the FDA actually followed the science and their own rules. We will return to this topic below.
🚩 Pfizer’s clinical trial in kids was intentionally undersized to hide harms. This is a well known trick of the pharmaceutical industry. The FDA even called them out on it earlier this summer and asked Pfizer to expand the trial and Pfizer just ignored them because they can. (Pfizer fudged it by importing data from a different study but this other study only monitored adverse outcomes for 17 days so if anything the new data polluted rather than clarified outcomes). To put it simply, if the rate of particular adverse outcome in kids as a result of this shot is 1 in 5,000 and the trial only enrolls 1,518 in the treatment group then one is unlikely to spot this particular harm in the clinical trial. Voilà “Safe & Effective(TM)”.
🚩 Pfizer only enrolled “participants 5-11 years of age without evidence of prior SARS-CoV-2 infection.” Does the Pfizer mRNA shot wipe out natural immunity and leave one worse-off than doing nothing as shown in this data from the British government? Pfizer has no idea because children with prior SARS-CoV-2 infection were excluded from this trial. This was by design. Toxic polluters have learned to not ask questions that they do not want the answers to, lest they wind up staring at their own smoking gun in a future court case.
“What the British are saying is they are now finding the vaccine interferes with your body’s innate ability after infection to produce antibodies against not just the spike protein but other pieces of the virus. Specifically, vaccinated people don’t seem to be producing antibodies to the nucleocapsid protein, the shell of the virus, which are a crucial part of the response in unvaccinated people. This means vaccinated people will be far more vulnerable to mutations in the spike protein EVEN AFTER THEY HAVE BEEN INFECTED AND RECOVERED ONCE (or more than once, probably). It also means the virus is likely to select for mutations that go in exactly that direction because those will essentially give it an enormous vulnerable population to infect. And it probably is still more evidence the vaccines may interfere with the development of robust long-term immunity post-infection.”
🚩 Did Pfizer LOSE CONTACT with 4.9% of their clinical trial participants? The FDA risk-benefit document states: “Among Cohort 1 participants, 95.1% had safety follow-up ≥2 months after Dose 2 at the time of the September 6, 2021 data cutoff.” So what happened with those 4.9% who did not have safety follow-up 2 months after Dose 2? Were they in the treatment or control group? We have no idea because Pfizer isn’t saying. Given the small size of the trial, failing to follow up with 4.9% of the participants potentially skews the results.
🚩 The follow up period was intentionally too short. This is another well-know trick of the pharmaceutical industry designed to hide harms. Cohort 1 appears to have been followed for 2 months, cohort 2 was only monitored for adverse events for 17 days. Many harms from vaccines including cancer and autoimmune disorders take much longer to show up. As the old saying goes, “you can have it quick or you can have it done right, but you cannot have both.” Pfizer chose quick.
🚩 The risk-benefit model created by the FDA only looks at one known harm from the Pfizer mRNA shot — myocarditis. But we know that the real world harms from the Pfizer mRNA shot go well beyond myocarditis and include anaphylaxis, Bell’s Palsy, heart attack, thrombocytopenia/ low platelet, permanent disability, shingles, and Guillain-Barré Syndrome (GBS) to name a few. Cancer, diabetes, endocrine disruption, and autoimmune disorders may show up later. But the FDA does not care about any of that because they have a vaccine to sell so they just ignore all of those factors in their model.
🚩 Pfizer intentionally wipes out the control group as soon as they can by vaccinating all of the kids who initially got the placebo. They claim that they are doing this for “ethical reasons”. But everyone knows that Pfizer’s true aim is to wipe out any comparison group so that there can be no long term safety studies. Wiping out the control group is a criminal act and yet Pfizer, Moderna, J&J, and AZ do this as standard practice with the blessing of the FDA/CDC.
🚩 Given all of the above, how on earth did the FDA claim any benefits at all from this shot? You should probably sit down for this part because it’s a doozy! Here’s the key sentence:
Vaccine effectiveness was inferred by immunobridging SARS-CoV-2 50% neutralizing antibody titers (NT50, SARS-CoV-2 mNG microneutralization assay).
Wait, what!? I’ll explain. There were ZERO cases of severe COVID-19 in the clinical trial of children ages 5 to 11. So Pfizer and the FDA just ignored all of the actual health outcomes (they had to, there is no emergency, so the application is moot). INSTEAD Pfizer switched to looking at antibodies in the blood. In general, antibodies are a poor predictor of immunity. And the antibodies in the blood of these 5 to 11 year old children tell us nothing because again, there were zero cases of severe COVID-19 in this study (none in the treatment group, none in the control group). So Pfizer had to get creative! What they came up with is “immuno-bridging”. Pfizer looked at the level of antibodies in the bloodwork of another study, this one involving people 16 to 25 years old, figured out the level of antibodies that seems to be protective in that population, then figured out how many kids ages 5 to 11 had similar levels of antibodies in their blood, and then came up with a number for how many cases, hospitalizations, ICU admissions, and deaths would be prevented by this shot in the 5 to 11 population in the future, based on the antibody levels and health outcomes from the 16 to 25 year old population. If your head hurts from that tortured logic, it should, because such chicanery is unprecedented in a risk-benefit analysis.
So when the FDA uses this tortured logic at the beginning of their briefing document, all of the calculations that stem from this will be flat out wrong. Not just wrong but preposterous and criminally wrong.
The whole ballgame comes down to Table 14 on page 34 of the FDA’s risk-benefit document. And there the red flags come fast and furious.
🚩 The FDA model only assesses the benefits of vaccine protection in a 6-month period after completion of two doses. Furthermore it assumes constant vaccine efficacy during that time period. This is problematic on several counts.
First, reducing mild cases in children is not a desired clinical outcome. As Dr. Geert Vanden Bossche points out, mass vaccination turns kids into shedders of more infectious variants.
“Under no circumstances should young and healthy people be vaccinated as it will only erode their protective innate immunity towards Coronaviruses (CoV) and other respiratory viruses. Their innate immunity normally/ naturally largely protects them and provides a kind of herd immunity in that it dilutes infectious CoV pressure at the level of the population, whereas mass vaccination turns them into shedders of more infectious variants. Children/ youngsters who get the disease mostly develop mild to moderate disease and as a result continue to contribute to herd immunity by developing broad and long-lived immunity. If you are vaccinated and get the disease, you may develop life-long immunity too but why would you take the risk of getting vaccinated, especially when you’re young and healthy? Firstly, there is the risk of potential side effects; secondarily, there is the ever increasing risk that your vaccinal antibodies will no longer be functional while still binding to the virus, thereby increasing the likelihood of ADE or even severe disease….”
Second, we know that vaccine efficacy in the month after the first dose is negative because it suppresses the immune system and it begins to wane after 4 months so all of the FDA’s estimates of vaccine efficacy are inflated.
Third, the harms of myocarditis from these shots will likely unfold over the course of years. Robert Malone, the inventor of mRNA technology notes that the FDA is admitting that children will be injected twice a year forever (hence the six month time frame in the FDA risk-benefit model). But the risks of “adverse events such as cardiomyopathy will be cumulative.” So any model that only looks at a six month time frame is hiding the true adverse event rate.
🚩 The FDA/Pfizer play fast and loose with their estimates of myocarditis. First they estimate “excess” (read: caused by the shot) myocarditis using data from the private “Optum health claim database” instead of the public VAERS system (p. 32). So it’s impossible for the public to verify their claims. Then, when it comes to estimating how many children with vaccine-induced myocarditis will be hospitalized and admitted to the ICU they use the Vaccine Safety Datalink (see page 33). Why switch to a different database for those estimates? Finally, there is no explanation for how they calculated “excess” myocarditis deaths, so they just put 0. Red flag, red flag, red flag.
The FDA estimates that there will be 106 extra myocarditis cases per 1 million double-jabbed children 5-11. There are 28,384,878 children ages 5 to 11 in the U.S. The Biden administration wants to inject Pfizer mRNA shots into all of them and has already purchased enough doses to do just that (even though only 1/3rd of parents want to jab their kids with this shot). So (if the Biden administration has its way) 106 excess myocarditis cases per 1 million x 28.38 million people would be 3,009 excess myocarditis cases post-vaccination if the Pfizer vaccine is approved.
And over the course of several years many of those children will die.
Dr. Anthony Hinton (“Consultant Surgeon with 30 years experience in the NHS”) points out that myocarditis has a 20% fatality rate after 2 years and a 50% fatality rate after 5 years:
Viral myocarditis results in 2 in 10 people dead after 2 years and 5 in 10 after 5 years. It’s not mild. It’s dead heart muscle. https://t.co/ixRmk48rja
So the FDA has it exactly backwards — they want to prevent mild COVID in children which reduces herd immunity and they just flat out lie about the harms from myocarditis.
I’ve taken the liberty to correct the FDA’s Table 14 with actual real world data and extended it over 5 years. It looks like this:
A study by Harvard Pilgrim Healthcare for the U.S. Department of Health and Human Services estimated that VAERS only captured 1% of actual vaccine injuries. Steve Kirsch has done elaborate modeling that puts the Under-Reporting Factor of COVID-19 vaccine deaths at 41 (so multiply the above numbers by 41). And myocarditis is just one of a multitude of possible harms from COVID-19 vaccines. Dr. Jessica Rose recently calculated an Under-Reporting Factor of 31 for all severe adverse events following vaccination.
Conclusion
The Pfizer vaccine fails any honest risk-benefit assessment in connection with its use in children ages 5 to 11. The FDA’s risk-benefit analysis of Pfizer’s mRNA vaccine in children ages 5 to 11 is shoddy. It used tortured logic (that would be rejected by any proper academic journal) in order to reach a predetermined result that is not based in science. The FDA briefing document is a work of fiction and it must be withdrawn immediately. If the FDA continues with this grotesque charade it will cause irreparable harms to children and the FDA leadership will one day be prosecuted for crimes against humanity.
The U.S. Food and Drug Administration’s (FDA) advisory committee today endorsed Pfizer’s COVID vaccine for children ages 5 to 11, despite strong objections raised during the meeting by multiple scientists and physicians.
The vote passed with 17 supporting it and one abstention.
Before the shots can be rolled out, the FDA will have to formally authorize the vaccine, and the Centers for Disease Control and Prevention (CDC) must also weigh in with its own recommendations — but the Biden administration’s announcement last week that it has already ordered 68 million doses of the pediatric vaccine suggests Pfizer’s request will sail through.
According to the FDA website, as of Oct. 25, the agency had received 139,470 comments from the public prior to today’s meeting — a number federal officials described as strikingly high.
As he opened the meeting, Dr. Peter Marks, director of the FDA’s Center for Biologics Evaluation and Research (CBER), said, “I want to acknowledge the fact that there are strong feelings that have clearly been expressed by members of the public both for and against” authorization.
The dose for younger children would be one-third the strength given to people 12 and older, with two shots given three weeks apart.
Based on CDC data presented during the meeting, among children 5 to <12 years of age, there have been approximately 1.8 million confirmed and reported COVID cases since the beginning of the pandemic, and only 143 COVID-related deaths in the U.S. through Oct. 14.
In this same age group, there were 8,622 COVID-related hospitalizations through Sept 18.
“This translates to cumulative incidence rates of approximately 6,000 and 30 per 100,000 for confirmed COVID cases and COVID-related hospitalizations, respectively, among children 5 to <12 years of age,” Pfizer’s application said.
Children with underlying medical conditions, such as asthma, diabetes and obesity, made up two-thirds of severe COVID cases.
Pfizer provided safety data on two study cohorts of children ages 5 to 11, both of roughly equal size. The first group was followed only for about two months, the second for only two-and-a-half weeks.
The two-month cohort included 2,268 children ages 5 to 11. Of the 2,268 children, 1,518 received the vaccine and 750 received a placebo. Each received two shots spaced three weeks apart.
Pfizer’s study found its vaccine was about 91% effective against symptomatic COVID in children, based on 16 cases of COVID in the placebo group and three cases in the vaccinated group over the brief follow-up period.
Most side effects occurred within a couple of days and included pain at the injection site, fatigue, headache, muscle pains and chills, Pfizer said.
According to Pfizer, the number of participants in the current clinical development program was “too small to detect any potential risks of myocarditis associated with vaccination.”
Long-term safety of Pfizer’s COVID-19 vaccine “to evaluate long-term sequelae of post-vaccination myocarditis/pericarditis” in participants 5 to <12 years of age will not be studied until after the vaccine is authorized for children,” Pfizer’s application noted.
Pfizer data insufficient, kids’ risk of vaccine injury greater than COVID risk, experts say
Experts raised concerns over the lack of safety and efficacy data presented by Pfizer for use of its COVID vaccine in younger children, and they pointed to increasing safety signals based on reports to the Vaccine Adverse Event Reporting System (VAERS).
They also questioned the need to vaccinate children — whose risk of dying from COVID is “almost nil” — at all.
According to Dr. Meryl Nass, member of the Children’s Health Defense Scientific Advisory Panel, Pfizer once again did not use all of the children who participated in the trial in their safety study.
“Three thousand children received Pfizer’s COVID vaccine, but only 750 children were selectively included in the company’s safety analysis,” Nass said. “Studies in the 5-11 age group are essentially the same as the 12-15 group — in other words, equally brief and unsatisfying, with inadequate safety data and efficacy data, with no strong support for why this type of immuno-bridging analysis is sufficient.”
Nass said, “All serious adverse events were considered unrelated to the vaccine.”
During the meeting and in its FDA application, Pfizer argued children should be vaccinated to prevent SARS-CoV-2 transmission, yet the company did not assess asymptomatic transmission.
Dr. Ofer Levy, a VRBPAC member, asked for evidence that Pfizer’s vaccine prevents transmission.
Dr. William Gruber, senior vice president of Pfizer Vaccine Clinical Research and Development, said they did not assess whether the vaccine prevents transmission, but said there is evidence the vaccine prevents transmission in adults.
When questioned further, Gruber was unable to cite specific evidence to back his assertion.
Steve Kirsch, founder of the COVID-19 Early Treatment Fund, asked the panel how they could do a risk-benefit analysis with Pfizer’s COVID vaccine if they did not know the CDC’s VAERS under-reporting factor (URF).
Kirsch asked:
“How can you do a risk-benefit of analysis of COVID vaccines if you don’t know the URF? This is extremely, extremely important. You have been assuming it has been one. It is not one. Using a URF of 41, which is calculated using CDC methodology, we find over 300,000 excess deaths in VAERS. If the vaccine didn’t kill these people, what did?”
“How many Americans have to die before you pull the plug?” Kirsch asked.
Kirsch also questioned the panel on why Maddie de Garay’s severe adverse reaction to the Pfizer vaccine, which left her paralyzed, was not reported by the company to the FDA.
Dr. Jessica Rose, viral immunologist and biologist, told the panel EUA of biological agents requires the existence of an emergency and the nonexistence of alternate treatment.
“There is no emergency and COVID-19 is exceedingly treatable,” Rose said.
In a peer-reviewed study co-authored by Rose, myocarditis rates were significantly higher in people 13 to 23 years old within eight weeks of the COVID vaccine rollout.
In 12- to15-year-olds, Rose said, reported cases of myocarditis were 19 times higher than background rates.
“In an act of censorship, this paper has been temporarily removed and it has now been killed without criticism of the work,” Rose said, noting the timing of the removal was strange.
Rose said tens of thousands of reports have been submitted to VAERS for children ages 0 to 18.
Rose explained:
“In this age group, 60 children have died — 23 of them were less than 2 years old. It is disturbing to note that “product administered to patient of inappropriate age was filed 5,510 times in this age group. Two children were inappropriately injected, presumably by a trained medical professional, and subsequently died.”
Dr. Josh Guetzkow, a senior lecturer at the Hebrew University of Jerusalem, said expanding the EUA to children is unnecessary, premature and will do more harm than good.
Guetzkow said there is no emergency for children, especially healthy ones whose risk of severe illness and death is “almost nil.”
Guetzkow said kids with pre-existing conditions and prior COVID infections were not included in Pfizer’s study, so including them in the EUA is negligence.
“Pfizer’s trial is woefully underpowered to detect specific safety concerns, such as myocarditis, just like the adolescent study was, and if they weren’t able to detect an unexpected safety concern there, they wouldn’t be able to here,” Guetzkow said.
Guetzkow said:
“In Pfizer’s study, only .5% of controls were dropped due to important protocol violations, versus 3% in the treatment group. The odds of that happening by chance are 1 in 10,000. This deviation is poorly explained with no ITT analysis. The study is not double-blind and may be subject to bias. Most VSD safety monitoring programs have not reported results, why not wait?”
Guetzkow said, “from CDC reports, we can expect that for every 18 child hospitalizations prevented, at least 43 will end up in the hospital for all causes following vaccination,” yet, the “FDA’s risk-benefit analysis only counts myocarditis hospitalization.”
“Why ignore the V-safe data, and shouldn’t FDA verify Pfizer’s efficacy and immunobridging analysis first?” he asked.
Guetzkow said VAERS shows alarming safety signals, which cannot be attributed to increased vaccination, simulated reporting or COVID infections.
“We calculated the ratio of adverse events reported per million Pfizer vaccinations to reports per million flu vaccinations among teenagers to see what to expect in children. Serious events are reported 51% more often for Pfizer, deaths 47 times, life-threatening conditions 49 times,” Guetzkow said.
Guetzkow asked the panel to look at the data on COVID vaccines compared to flu vaccines. Pointing to the data on reproductive organs, Guetzkow asked, “why would we expect children to take these risks to protect adults?”
There are more than 900 types of adverse events reported after Pfizer vaccination that have never been reported after flu vaccines, including 11 cases of multisystem-inflammatory syndrome (MS-C) that occurred without previous history of COVID infection, Guetzkow said.
He added that if the panel was considering authorizing Pfizer’s COVID vaccine to prevent MS-C — as Pfizer’s application suggested as one of the reasons they should — the panel should reconsider.
During another part of the meeting, Julia Barnes-Weise, director of the Global Healthcare Innovation Alliance Accelerator, said pharmaceutical companies have concerns.
“One of them is, especially for a not-yet-approved vaccine, that they could be held liable for any injury that that vaccine seems to have caused,” Barnes-Weise said.
In a preliminary analysis last week, FDA reviewers said protection would “clearly outweigh” the risk of a very rare side effect in almost all scenarios of the pandemic, PBS News Hour reported.
Children’s Health Defense (CHD) said yesterday it would take legal action against the FDA if it granted EUA for the Pfizer-BioNTech vaccine for children 5- to 11- years old.
In a letter signed by Robert F. Kennedy, Jr., CHD chairman and chief legal counsel, and Nass, Kennedy and Nass wrote:
“CHD will seek to hold you accountable for recklessly endangering this population with a product that has little efficacy but which may put them, without warning, at risk of many adverse health consequences, including heart damage, stroke, and other thrombotic events and reproductive harms.”
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
The rediscovery of a series of grisly experiments on beagle puppies has galvanized social media users into demanding the arrest of “America’s doctor” Anthony Fauci. But where was everyone when his work was harming humans?
Images of a sad pair of beagle puppies, their heads encased in square cages as they lie hopelessly on a table, have yanked at America’s heartstrings since they were shoved back into the national spotlight by White Coat Waste Project, a group that calls out US government labs for animal cruelty and other misuse (and abuse) of citizens’ money.
Millions of taxpayer dollars were used to essentially torture the puppies to death in labs in and out of the US, according to the organization, which unearthed evidence of the cruelty in the form of over $21 million spent on a total of four experiments – none of which was medically necessary. One involved severing 44 puppies’ vocal cords so that their pained barking and whining wouldn’t bother the scientists; another deliberately infected them with sand flies over the course of 22 months, restricting their movements by locking their heads in boxes so that they could not even swat the insects away as they were being eaten alive.
It’s horrific stuff by any measure, beyond cartoonish levels of evil. Indeed, even Texas Senator Ted Cruz (R) claimed he thought the tweets he’d read about Fauci “literally ‘torturing puppies’” had to be “metaphorical.”
But while the outrage is justified, it’s also old news. One could ask why the masses have turned against Fauci only now, when his National Institute for Allergies and Infectious Diseases has been funding the torture of puppies for years, with one of the horrific experiments dating from 2016. The most recent grant dated from 2020, meaning Fauci’s agency was vivisecting helpless furry animals at the University of Georgia even while he was being worshiped as America’s Doctor™ and posing for photos with other people’s dogs.
Even White Coat Waste Project refers to its own revelations as “Fauci’s other international scandal,” implying knowledge of a better-known episode in the fame-hungry doctor’s life.
One must ask why the popular outrage against Fauci over animal cruelty is not matched by an equal (if not more forceful) outrage over the doctor’s crimes against humanity. From his enthusiastic support of gain-of-function studies to his efforts to sideline a cheap, effective drug that could have saved thousands of lives during the AIDS epidemic in favor of a highly toxic alternative, Fauci’s hands are covered in the blood of humans as well as that of canines.
Indeed, Fauci’s behavior during the Covid-19 outbreak – trashing cheap but effective treatments in favor of expensive alternatives lacking proof of efficacy – eerily mirrors his actions during the early years of AIDS. Thousands of people have died in both cases after Fauci pushed deadly or ineffective medications – most notably the failed cancer drug AZT in the 1980s and the failed Ebola drug remdesivir in the last two years – while safer and more efficacious remedies sat on the shelf.
Discoveries that members of the National Institutes of Health, parent of Fauci’s NIAID, had hefty investments in Gilead, maker of remdesivir, as well as in Moderna, one of the manufacturers of an mRNA vaccine for Covid-19, have only raised more questions about Fauci’s motives during the coronavirus pandemic.
Fauci has also been caught lying repeatedly about his involvement in gain-of-function research aimed at making bat coronaviruses more infectious in humans. Despite his profuse denials of even funding such research in recent months, he previously defended the work by arguing that any knowledge gained from bolstering the infectious potential of such pathogens was “worth the risk” of unleashing a pandemic. Whether or not his NIAID-funded research played a part in the Covid-19 outbreak has not been proven, but Fauci’s furious tap-dancing around any questions regarding the Wuhan lab or gain-of-function research in general does him no favors.
Yet, somehow, none of this elicits anything like the howls of rage coming from dog-lovers on social media. The same outrage-on-demand contingent who demand countries like China and Vietnam stop eating dog meat, signing a petition with one hand while biting into a well-done burger with the other, insist on the closure of “barbaric” wet markets like the one we were told spawned the novel coronavirus in late 2019. This group’s problem is less animal cruelty than being reminded of that cruelty. They’d rather wait until their meat is shrink-wrapped and frozen in a supermarket than pick out the tastiest-looking chicken in the bunch and have it slaughtered then and there.
Ultimately, Fauci being arrested is an endpoint that animal rights activists, human rights activists, and the normally comatose members of Congress – 24 of whom actually signed a letter demanding answers from the once-untouchable Coronavirus Pope – should see eye-to-eye on. But the diminutive doctor must not be permitted to skate on his real crimes – whether it’s pandemic profiteering, bankrolling gain-of-function research in China that was at the time illegal to perform in the US, or allegedly perjuring himself in congressional testimony. Fauci has much to answer for. Dozens of dead puppies are just the tip of the iceberg.
Unfortunately, like other gleeful architects of the Covid-19 police state who’ve been caught in the midst of scandal – former New York Governor Andrew Cuomo, for example – arresting Fauci on the basis of popular rage over dead puppies is likely to close the book on further prosecution, no matter how heinous his “real” crimes.
Just as Cuomo is unlikely to ever be held to account for the thousands of elderly New Yorkers who died because of his nursing-home order to house Covid-positive patients with the helpless elderly, Fauci will be permitted to enjoy his retirement – and big fat pension – in peace. Americans who have lost everything to his mismanagement of the Covid-19 pandemic must not let that happen.
Helen Buyniski is an American journalist and political commentator at RT. Follow her on Telegram
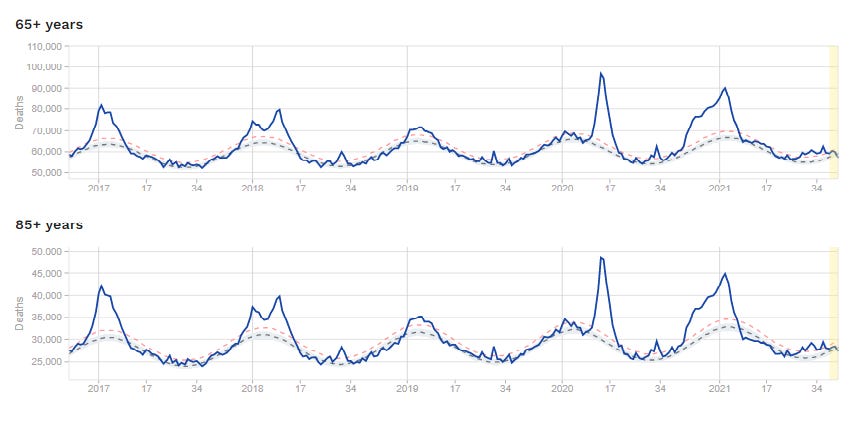
It wouldn’t take much to push a population of such elderly and frail people into a life-threatening situation. Lock them up for months on end. Deny them human contact on pain of arrest and fines they couldn’t hope to pay. Withdraw medical treatment. Quarantine their carers. Terrorise them with propaganda about a civilisation-ending disease. Order them to stay at home and avoid the contact of other people like the plague. Tell them hospitals standing empty are on the verge of being overwhelmed. Turn medical centres into places to fear, the breeding grounds of a deadly new disease. That should be more than enough. It has been more than enough.
To preserve the elderly, the world has used the young – who suffered no pandemic – as a shield.
The young have lost their jobs, their childhoods, their right to breathe air freely, their right to say no to experimental medicine they do not need.
And now they appear to be dying for the elderly too:
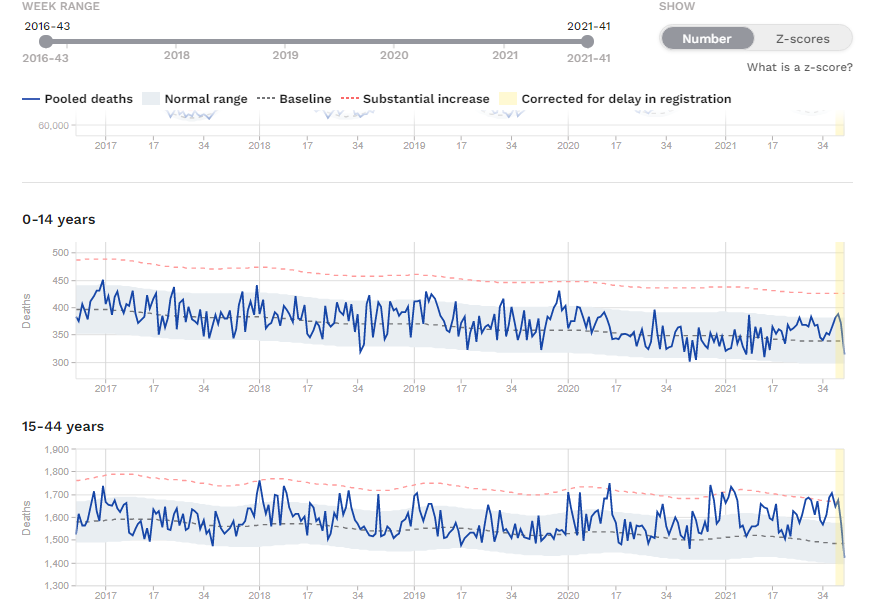
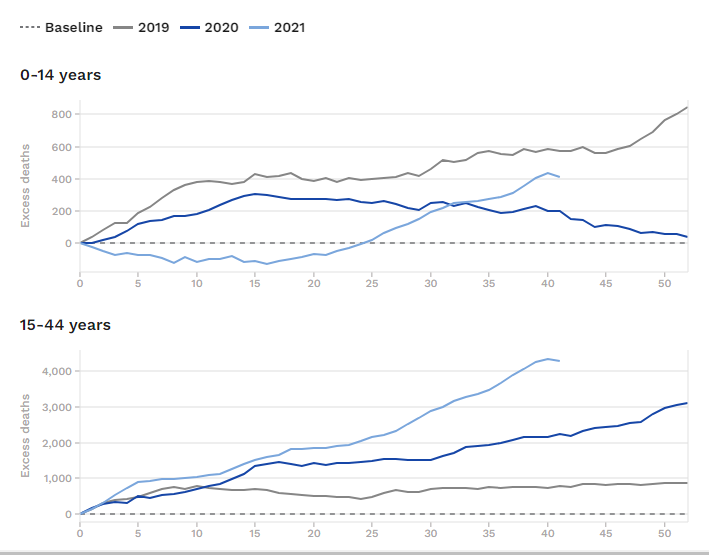
Please can somebody explain why deaths are rising so steeply in European youth?
They did not suffer from historically excess death in the middle of the pandemic.
Why are they dying now?
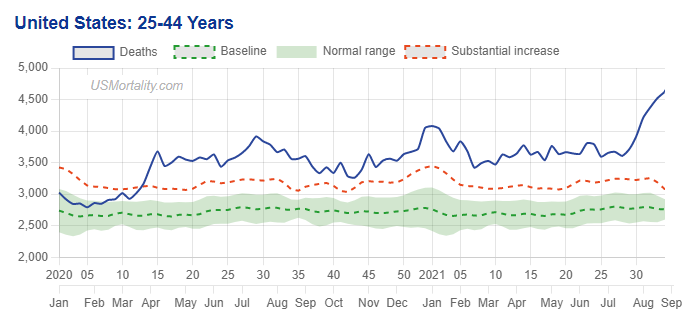
And it is not only them – US young people are suffering the same fate:
PHARMACOVIGILANCE: the practice of monitoring the effects of medical drugs after they have been licensed for use, especially in order to identify and evaluate previously unreported adverse reactions.
Pages 34-35 of the FDA review of Pfizer’s data for the 5-11 year olds provides the pretense of truly caring about identifying and quantifying adverse events from the vaccine. Just look at all the “activities” Pfizer and its partner must do. Well, of course they have to do them, since their clinical trial was so underpowered (not enough subjects) and only ran 2 months for about half the kids and 2.5 weeks for the rest. Duh?
Not only that, but Pfizer presented its data to FDA on October 6, and FDA already had completed its review and written its 39 page report by October 23, 17 days later. Fast work. But then again, we are only talking about the health of 28 million elementary school kids. And millions more overseas whose countries follow FDA advice.
And lest I forget, we are also talking about their education, because it seems they won’t be able to attend school soon, if unjabbed. Gavin Newsome said so. And a bill is being introduced in the District of Columbia for the same purpose.
Clearly, the stakes are pretty low, so a pretend Pfizer clinical trial and a pretend FDA review are good enough, right?
Below is part of FDA’s presentation. What is missing is the most important information, revealed in an Aug 23 letter from FDA. And that is, that the trials FDA demands Pfizer undertake to find out how dangerous its vaccines actually are, will not be reported to FDA until 2024 and 2025–presumably after most of the world’s children have already received 2 or 4 or 6 or 8 doses.
9 PHARMACOVIGILANCE ACTIVITIES
Pfizer submitted a revised Pharmacovigilance Plan (PVP) to monitor safety concerns that could be associated with BNT162b2 in individuals 5-11 years of age. The PVP includes the following safety concerns:
• Important Identified Risks: anaphylaxis, myocarditis, and pericarditis
• Important Potential Risks: Vaccine-associated enhanced disease (VAED), including vaccine-associated enhanced respiratory disease (VAERD).
Pfizer-BioNTech plans to conduct passive and active surveillance to monitor the postauthorization safety for the Pfizer-BioNTech COVID-19 Vaccine, including: 35
• Mandatory reporting by the Sponsor under the EUA for the following events to VAERS within 15 days: SAEs (irrespective of attribution to vaccination); COVID-19 disease resulting in hospitalization or death; multisystem inflammatory syndrome (MIS)
• Adverse event reporting in accordance with regulatory requirements for the licensed vaccine, COMIRNATY
• Additionally, following approval of COMIRNATY, the Sponsor was also asked to submit reports of myocarditis and pericarditis as 15-day reports to VAERS.
• Periodic safety reports containing an aggregate review of safety data including assessment of AEs; vaccine administration errors, whether or not associated with an AE; and newly identified safety concerns.
• Post-authorization observational studies, that would be modified to encompass the evaluation of children 5-11 years of age include active surveillance safety studies using large health insurance claims and/or electronic health record database(s):
– Study C4591009: A non-interventional post-approval safety study of the Pfizer-BioNTech COVID-19 mRNA Vaccine in the United States
Objective: To assess the occurrence of safety events of interest, including myocarditis and pericarditis, in the general U.S. population of all ages, pregnant women, the immunocompromised, and persons with a prior history of COVID-19 within selected data sources participating in the U.S. Sentinel System.
– Study C4591021: Post-conditional approval active surveillance study among individuals in Europe receiving the Pfizer-BioNTech Coronavirus Disease 2019 (COVID-19) Vaccine
Objective: To assess the potential increased risk of AESIs, including myocarditis/pericarditis, after being vaccinated with at least one dose of the PfizerBioNTech COVID-19 Vaccine.
– Study C4591021 Substudy: Substudy to describe the natural history of myocarditis and pericarditis following administration of COMIRNATY
Objective: To describe the natural history of post-vaccination myocarditis/pericarditis, including recovery status, risk factors, and/or identification of serious cardiovascular outcomes within one year of myocarditis/pericarditis diagnosis among individuals vaccinated with BNT162b2 as well as individuals not vaccinated with a COVID-19 vaccine.
– Study C4591036: Prospective cohort study with at least 5 years of follow-up for potential long-term sequelae of myocarditis after vaccination (in collaboration with Pediatric Heart Network [PHN]). Working title: Myocarditis/pericarditis follow-up study within the Pediatric Heart Network
Objective: To characterize the clinical course, risk factors, resolution, long-term sequelae, and quality of life in children and young adults <21 years with acute postvaccine myocarditis/pericarditis. Pfizer-BioNTech also plans to include vaccine effectiveness analyses among individuals 5-11 years of age in Study C4591014 entitled “Pfizer-BioNTech COVID-19 BNT162b2 Vaccine Effectiveness Study Kaiser Permanente Southern California.”
Here come jabs in schools without parental consent.
“Bonnie J. Fraser Henry OBC FRCPC is a Canadian physician who is the Provincial Health Officer for British Columbia, the first woman in this position. Henry is also a clinical associate professor at the University of British Columbia. She was a family doctor and is a specialist in public health and preventive medicine.”
In fact, the politicians have worked on this for years, and enshrined it in legislation, she says.
Looks like you can garner lots of awards when your heart is a stone, Bonnie.
And, like Presidential wannabe Governor Cuomo, she even had time to write a book about her leadership in the pandemic, titled Be Kind, Be Calm, Be Safe. Do these people know what they are, or are they high on their own supply?
Here someone collected her telling the truth about masks last year and flip-flopping later:
A Pakistani taxi driver will leave US detention at Guantanamo Bay after 17 years behind bars. Mistaken for a wanted terrorist, the man suffered horrific torture in American custody, despite never being charged with any crime.
Ahmed Rabbani’s release was announced on Friday by Reprieve, a human rights NGO. Rabbani had been unanimously cleared for release by the prison’s Periodic Review Board, made up of senior officials from six US agencies, including the State Department and Department of Homeland Security.
Rabbani’s journey through the underbelly of the US’ post-9/11 security infrastructure began in Karachi, Pakistan, in 2002. Mistaken for wanted terrorist Hassan Ghul, the taxi driver was arrested by Pakistani authorities outside Ghul’s apartment complex and sold to American personnel in the country.
Information gleaned from an associate of Rabbani arrested on the same day was used to arrest several suspected Al-Qaeda operatives, including a supposed member of Osama Bin Laden’s security detail. However, Rabbani was never charged with any crime, and is not believed to be involved in terrorism.
Nevertheless, he spent more than 545 days after his arrest being tortured in a CIA ‘black site’ in Afghanistan. The torture inflicted there on Rabbani was detailed in the US Senate’s 2014 torture report, and included long periods of being shackled with his hands outstretched over his head, an agonizing position that led Rabbani to try to cut off his own hand to end the pain.
Testimony from multiple detainees held in the same CIA prison describes permanent darkness, cells flooded with excrement and infested with vermin, beatings, sleep deprivation, being buried in simulated graves, being stripped naked and doused with cold water, and being denied bathing facilities for months on end.
According to Reprieve, Rabbani’s interrogators knew that “they had the wrong man,” but tortured him anyway. After more than a year in the CIA facility, Rabbani was transferred to the Guantanamo Bay detention camp on US territory in Cuba. He would spend the next 17 years there, without a charge or trial date.
His case attracted international attention, and in 2018, Rabbani wrote an op-ed published in the Los Angeles Times describing physical and sexual abuse by guards, force-feeding, and repeated hunger strikes to protest the conditions of his imprisonment. At the time of the op-ed, Rabbani said that he was suffering from “stomach problems so acute that I cannot consume hard food without vomiting blood,” and was being denied digestible food.
Conditions in Guantanamo chipped away at Rabbani’s mental health. “There is no morning and no evening,” he wrote. “There is only despair.”
“Ahmed’s clearance is long overdue,” said Reprieve attorney Mark Maher. “For those of us who have supported him, the feeling is one of relief, tempered with sadness for all he has lost… but we won’t celebrate until he is back with his family in Pakistan and able to hug his 19-year-old son for the first time.”
Of the 780 people detained in Guantanamo Bay since the facility opened in 2002, 732 have been transferred elsewhere or released, 38 remain there, and nine have died in custody. President Joe Biden has promised to close the notorious prison before he leaves office, a promise that was made, but not kept, by his former boss Barack Obama.
It is now nearly three decades since the Unites States adopted the policy of dual containment of Iran and Iraq. While much has been written about the containment of Iraq, there has been very little in-depth analysis of this policy when it comes to Iran. In a book that is going to be released on March 31, 2008, entitled The United States and Iran: Sanctions, Wars and the Policy of Dual Containment (Routledge), I attempt to address this shortcoming by investigating when and why the US policy of containment of Iran came about, how it evolved, and where it stands today.[1] To the extent that Israel has been involved in US policy making, the study will also include the role that Israel has played in the containment of Iran. Also, since the fate of Iran has been inextricably linked to that of Iraq, occasionally the investigation will overlap with the containment of Iraq.
The policy of dual containment of Iran and Iraq originated during the Carter Administration, but it was not until the Clinton Administration that the expression “dual containment” became popular. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.