CDC lies again–it will now try to impose universal Hepatitis B vaccination of adults!
By Meryl Nass, MD | November 7, 2021
The criminals at CDC began 30 years ago to appropriately target iv drug abusers, sex workers and others with a high risk of Hepatitis B to be vaccinated. There were not enough takers, according to CDC, so the public health officials set their sites on newborns, aimed and fired.
Hepatitis B is a viral disease transmitted via intercourse, iv drugs, or from mother to baby. All mothers are supposed to be tested for it during pregnancy, and less than 1% are positive. Mothers and their newborns who test positive are treated for it with vaccinations and immune globulin.
But that did not suffice for the science-light, pharma-heavy CDC. So some dim bulb decided that ALL newborns should be vaccinated for hepatitis B, within a few hours after birth. This practice was never shown to be safe, but it pleased public health officials, who could impose the vaccinations on babies while their moms were still recovering and dopey from the birth, the babies were stuck in a hospital, and the newborns were basically chickens to be plucked.
No one ever explained why newborns whose moms were negative needed to be protected from a disease that only affected those with more than one sex partner (primarily gay men) and those using dirty needles. But the CDC decided this was a great way to get everyone vaccinated, and it would protect those newborns when they did become old enough for sex and needles.
A bell should have gone off when it turned out their immunity waned after a few years–even though those poor infants had suffered 3 doses of a vaccine they had no need for, starting in the first moments of life. But the dim bulbs at CDC ignored it.
The thing is, rates of Hepatitis B in the US are low. They are high in east Asia, but the US is not east Asia. Rates have fallen since vaccine has been available over the past 30 years.
If you look at CDC’s Figure 2.5 below you will see that reported new Hepatitis B cases are 1 per 100,000 per year in women, and 1.5 per 100,000 in men in 2018, the last year for which CDC provides data.

In 2018, a total of 3,322 cases of acute hepatitis B were reported to CDC, for an overall incidence rate of 1.0 cases per 100,000 population.
The rate of reported acute HBV infections declined approximately 90% since recommendations for HepB vaccination were first issued, from 9.6 cases per 100,000 population in 1982 to 1.0 cases per 100,000 population in 2018.
So why in heaven’s name would CDC want to start vaccinating everyone when rates are very low and have fallen dramatically? However…
On Wednesday November 3, CDC briefed its supine advisory committee on the imaginary need for hepatitis vaccines. CDC briefers are trained to scare the pants off you to get the votes they want. Here is what was said:
CDC medical officer Mark K. Weng, MD, MSc, FAAP, who leads the ACIP’s hepatitis vaccines work group, presented data on the importance of vaccinating adults against HBV.
“In the U.S. every year, there are 20,700 estimated acute hepatitis B infections, and over $1 billion dollars spent on hepatitis B-related hospitalizations,” Weng said. “There are almost two million people estimated to be living with chronic hepatitis B in the U.S., of whom there’s a [15% to 25%] risk of premature death from cirrhosis or liver cancer.”
How did he get these deadly numbers? Well, CDC claimed that only about one tenth of the cases get reported, that is how. CDC used its dubious estimates to claim cases were ten times greater than reported–something they never claimed before. How do they know this? They never tell. They can’t give us a number to multiply the VAERS reports by to find out the rate of adverse vaccine events, but they are quick to come up with a magic multiplier when they want new vaccine programs to be approved.
What happened? The ACIP sleepwalkers voted to vaccinate all adults for hepatitis B–even those who are monogamous and don’t take any drugs. Why? Because they can, and they get pharma contracts when the advisory committee members behave.
So, this is what is next. Get ready to fight against more mandates. The elites are making war on us.
ACIP recommends universal hepatitis B vaccination for adults aged 19 to 59 years
CDC Advisors Unanimously Endorse Pfizer’s COVID Vaccine for Kids 5-11 Despite Expert Concerns Over Clinical Data
By Megan Redshaw | The Defender | November 2, 2021
The Centers for Disease Control and Prevention’s (CDC) vaccine advisory panel today unanimously recommended Pfizer’s COVID vaccine for children 5 to 11, despite concerns raised during the meeting about Pfizer’s clinical data, the fact that children who previously acquired natural immunity to COVID were included in clinical trials and evidence showing COVID poses little risk to children.
If Dr. Rochelle Walensky, the CDC’s director signs off on the decision, children ages 5 through 11 could start receiving COVID vaccines as early as tonight.
The younger age group will receive one-third of the dose authorized for those 12 and older in two shots at least three weeks apart. The doses will be delivered by smaller needles and stored in smaller vials to avoid a mix-up with adult doses.
The CDC’s guidelines for the vaccine’s use are not legally binding, but heavily influence the medical community’s practice.
Prior to today’s decision by the CDC’s Advisory Committee on Immunization Practices (ACIP) the Biden administration enlisted more than 20,000 pediatricians, family doctors and pharmacies to administer the vaccines — with 15 million doses already packed with dry ice, loaded into small specialized containers and shipped via airplanes and trucks to vaccination sites across the country, federal officials said on Monday.
Walensky sent a clear signal during the ACIP meeting about where she stands, CNN reported. “We have been asking when we will be able to expand this protection to our younger children,” Walensky said in opening comments to the committee.
“As you review the data today, it will be key to keep in mind the specific risks to children from this virus and the pandemic, and to put that risk into context of other vaccine-preventable diseases,” Walensky said.
Walensky noted that children are routinely vaccinated against diseases like chickenpox — which results in far fewer hospitalizations and deaths in children compared to COVID.
During today’s meeting, ACIP members reviewed and discussed the science behind the U.S. Food and Drug Administration’s (FDA) authorization last week of Pfizer’s COVID vaccine in all children 5-11 years old.
That authorization was based mostly on a Pfizer-BioNTech study of 4,600 children worldwide, of whom approximately 3,100 got the low-dose vaccine and about 1,500 got a placebo.
These studies showed the vaccine is about 91% effective against COVID. The immune system response to the vaccine, as measured by antibodies, was comparable to the response seen in 16- to 25-year-olds, NPR reported.
During the meeting, the CDC said 745 children under 18 have died of COVID since the beginning of the pandemic — although the COVID-19 team admitted 79% were confirmed to be hospitalized for COVID, while the rest were hospital admissions for other causes.
“The chance that a child will have severe COVID, require hospitalization or develop a long-term complication like MIS-C [multisystem inflammatory syndrome] remains low, but still the risk is too high and too devastating to our children, and far higher than for many other diseases for which we vaccinate children,” Walensky said.
Efficacy of Pfizer’s COVID vaccine in children
The CDC said Pfizer’s COVID vaccine was 90.9% effective against symptomatic COVID and none of the adverse events experienced during clinical trials were assessed by “the investigator” as related to the vaccine.
To determine the efficacy of the Pfizer-BioNTech COVID vaccine, Pfizer measured the blood of 264 children for antibodies.
“There were 3,000 vaccinated children in the trial. Why isn’t blood from the other 2,700-plus being measured for antibodies?” asked Dr. Meryl Nass, a member of the Children’s Health Defense Scientific Advisory Panel.
“Pfizer never explains why, when they have an important clinical trial in which over 3,000 children were injected in this age group, only a subset of less than 10% were used to assess efficacy,” Nass said.
Nass explained:
“Pfizer claims three cases of COVID in the vaccinated group versus 16 in the placebo group show efficacy of the vaccine. But the FDA did not accept this claim. Note that all cases were mild, none hospitalized or died. So are they planning to vaccinate 28 million kids to prevent colds?”
Nass noted Pfizer also enrolled kids who had prior evidence of having had COVID in the clinical trial, “which should never have been allowed.”
“Of the kids who were already immune at the start of the trials, none developed COVID,” Nass said. “About 150 kids in the placebo group were recovered and none got COVID.”
Nass said kids with preceding COVID infection did not have their antibody levels checked after the first dose, as Pfizer stated they did not collect the data because they “tried to minimize blood draws in children.”
“The real reason they did not want to collect data is because it might support the fact that kids who already had COVID might only need one vaccine dose, or none at all,” Nass said.
During the brief public comment session, Patricia Neuenschwander, a registered nurse noted there was no prevention of hospitalization, death or multisystem inflammatory syndrome in children — a condition being used to justify vaccinating younger children against COVID, despite numerous cases of MIS-C having been reported after receipt of a COVID vaccine.
Neuenschwander reminded the ACIP that vaccinations do not prevent infection or transmission. It is a mild illness in the vast majority of children, she said, and prior immunity is being ignored — the expansion group was only followed for 17 days.
David Wiseman, a research scientist with a background in pharmacy, pharmacology and experimental pathology, asked the CDC panel why the efficacy study was not validated by the FDA, and why Pfizer changed the buffer [see page 14] in the vaccine but did not test it in animals or kids — planning to use an untested version of the vaccine in 5 to 11-year-olds.
Wiseman said the FDA abandoned its responsibility, and he asked if the ACIP would do the same.
Myocarditis and COVID in 5- to 11-year-olds
One side effect that generated considerable discussion at today’s meeting was myocarditis — a form of heart inflammation.
The CDC said 1,640 cases of myocarditis have been reported to the CDC’s Vaccine Adverse Event Reporting System in people under age 30 after having received a COVID vaccine, but only 877 met the CDC’s case definition.
The CDC said there were nine reported deaths in people with myocarditis, but then the agency reduced the number to three, with two cases pending evaluation and one case without adequate information.
“I have to say that it is beyond belief that CDC could whittle down 877 cases reported in young people to three actual cases. Where did the rest go?” Nass asked.
“According to the CDC’s Vaccine Safety Datalink, 7 of 16 12- to 17-year-olds with myocarditis were still on exercise restriction three months after diagnosis — that is 44% could not exercise three months later,” Nass said. “This is huge.”
Nass further noted 25% of 250 myocarditis cases were still symptomatic at three months, and only 74% of cases were designated by cardiologists as definitely resolved at 3 months.
As it pertains to safety, some who testified during a public comment period, as well as other commentators, questioned whether the study used by the FDA to grant Emergency Use Authorization is large enough to assure parents that the vaccine is safe in young children.
“The bottom line is getting COVID, I think, is much riskier to the heart than getting this vaccine,” said Dr. Matthew Oster, a pediatric cardiologist at Children’s Hospital of Atlanta.
Dr. Tom Shimabukuro covered vaccine safety monitoring from the CDC’s surveillance system in children. Shimabukuro said COVID is getting the “most intensive vaccine monitoring program in history,” yet he did not go into detail on surveillance data.
Acknowledging that some parents are hesitant about vaccinating their children right away, Dr. Matthew Daley, a member of the ACIP said, “we hear you loud and clear and of course you only want what’s best for your child. I encourage you to talk to your family physician or pediatrician, they can walk through this with you.”
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
What is the Number Needed to Vaccinate to prevent a single COVID fatality in kids 5 to 11 based on Pfizer’s EUA application?
And what are the risks that go along with injecting that many kids?
By Toby Rogers | October 31, 2021
Number Needed to Vaccinate (NNTV), the standard policy tool that Pharma, the FDA, & CDC no longer want to talk about
A funny thing happened this afternoon. Not funny as in “haha”. More like funny as in, “ohhhhh that’s how the FDA rigs the process.”
I was reading the CDC’s “Guidance for Health Economics Studies Presented to the Advisory Committee on Immunization Practices (ACIP), 2019 Update” and I realized that the FDA’s woeful risk-benefit analysis in connection with Pfizer’s EUA application to jab children ages 5 to 11 violates many of the principles of the CDC’s Guidance document. The CDC “Guidance” document describes 21 things that every health economics study in connection with vaccines must do and the FDA risk-benefit analysis violated at least half of them.
Today I want to focus on a single factor: the Number Needed to Vaccinate (NNTV). In four separate places the CDC Guidance document mentions the importance of coming up with a Number Needed to Vaccinate (NNTV). I did not recall seeing an NNTV in the FDA risk-benefit document. So I checked the FDA’s risk-benefit analysis again and sure enough, there was no mention of an NNTV.
Because the FDA failed to provide an NNTV, I will attempt to provide it here.
First a little background. The Number Needed to Treat (NNT) in order to prevent a single case, hospitalization, ICU admission, or death, is a standard way to measure the effectiveness of any drug. It’s an important tool because it enables policymakers to evaluate tradeoffs between a new drug, a different existing drug, or doing nothing. In vaccine research the equivalent term is Number Needed to Vaccinate (NNTV, sometimes also written as NNV) in order to prevent a single case, hospitalization, ICU admission, or death (those are 4 different NNTVs that one could calculate).
Pharma HATES talking about NNTV and they hate talking about NNTV even more when it comes to COVID-19 vaccines because the NNTV is so ridiculously high that this vaccine could not pass any honest risk-benefit analysis.
Indeed about a year ago I innocently asked on Twitter what the NNTV is for coronavirus vaccines.

Pharma sent a swarm of trolls in to attack me and Pharma goons published hit pieces on me outside of Twitter to punish me for even asking the question. Of course none of the Pharma trolls provided an estimate of the NNTV for COVID-19 shots. That tells us that we are exactly over the target.
Various health economists have calculated a NNTV for COVID-19 vaccines.
- Ronald Brown, a health economist in Canada, estimated that the NNTV to prevent a single case of coronavirus is from 88 to 142.
- Others have calculated the NNTV to prevent a single case at 256.
- German and Dutch researchers, using a large (500k) data set from a field study in Israel calculated an NNTV between 200 and 700 to prevent one case of COVID-19 for the mRNA shot marketed by Pfizer. They went further and figured out that the “NNTV to prevent one death is between 9,000 and 100,000 (95% confidence interval), with 16,000 as a point estimate.”
You can see why Pharma hates this number so much (I can picture Pharma’s various PR firms sending out an “All hands on deck!” message right now to tell their trolls to attack this article). One would have to inject a lot of people to see any benefit and the more people who are injected the more the potential benefits are offset by the considerable side-effects from the shots.
Furthermore, the NNTV to prevent a single case is not a very meaningful measure because most people, particularly children, recover on their own (or even more quickly with ivermectin if treated early). The numbers that health policy makers should really want to know are the NNTV to prevent a single hospitalization, ICU admission, or death. But with the NNTV to prevent a single case already so high, and with significant adverse events from coronavirus vaccines averaging about 15% nationwide, Pharma and the FDA dare not calculate an NNTV for hospitalizations, ICU, and deaths, because then no one would ever take this product (bye bye $93 billion in annual revenue).
Increased all cause mortality in the Pfizer clinical trial of adults
As Bobby Kennedy noted in personal correspondence with me, Pfizer’s clinical trial in adults showed alarming increases in all cause mortality in the vaccinated :
In Pfizer’s 6 month clinical trial in adults — there was 1 covid death our of 22,000 in the vaccine (“treatment”) group and 2 Covid deaths out of 22,000 in the placebo group (see Table s4). So NNTV = 22,000. The catch is there were 5 heart attack deaths in the vaccine group and only 1 in placebo group. So for every 1 life saved from Covid, the Pfizer vaccine kills 4 from heart attacks. All cause mortality in the 6 month study was 20 in vaccine group and 14 in placebo group. So a 42% all cause mortality increase among the vaccinated. The vaccine loses practically all efficacy after 6 months so they had to curtail the study. They unblinded and offered the vaccine to the placebo group. At that point the rising harm line had long ago intersected the sinking efficacy line.
Former NY Times investigative reporter Alex Berenson also wrote about the bad outcomes for the vaccinated in the Pfizer clinical trial in adults (here). Berenson received a lifetime ban from Twitter for posting Pfizer’s own clinical trial data.
Pfizer learned their lesson with the adult trial and so when they conducted a trial of their mRNA vaccine in children ages 5 to 11 they intentionally made it too small (only 2,300 participants) and too short (only followed up for 2 months) in order to hide harms.
Estimating an NNTV in children ages 5 to 11 using Pfizer’s own clinical trial data
All of the NNTV estimates above are based on data from adults. In kids the NNTV will be even higher (the lower the risk, the higher the NNTV to prevent a single bad outcome). Children ages 5 to 11 are at extremely low risk of death from coronavirus. In a meta-analysis combining data from 5 studies, Stanford researchers Cathrine Axfors and John Ioannidis found a median infection fatality rate (IFR) of 0.0027% in children ages 0-19. In children ages 5 to 11 the IFR is even lower. Depending on the study one looks at, COVID-19 is slightly less dangerous or roughly equivalent to the flu in children.
So how many children would need to be injected with Pharma’s mRNA shot in order to prevent a single hospitalization, ICU admission, or death?
Let’s examine Pfizer’s EUA application and the FDA’s risk-benefit analysis. By Pfizer’s own admission, there were zero hospitalization, ICU admissions, or deaths, in the treatment or control group in their study of 2,300 children ages 5 to 11.
So the Number Needed to Vaccinate in order to prevent a single hospitalization, ICU admission, or death, according to Pfizer’s own data, is infinity. ∞. Not the good kind of infinity as in God or love or time or the universe. This is the bad kind of infinity as in you could vaccinate every child age 5 to 11 in the U.S. and not prevent a single hospitalization, ICU admission, or death from coronavirus according to Pfizer’s own clinical trial data as submitted to the FDA. Of course Pfizer likes this kind of infinity because it means infinite profits. [Technically speaking the result is “undefined” because mathematically one cannot divide by zero, but you get my point.]
Estimating an NNTV and risk-benefit model in children ages 5 to 11 using the limited data that are available
Everyone knows that Pfizer was not even trying to conduct a responsible clinical trial of their mRNA shot in kids ages 5 to 11. Pfizer could have submitted to the FDA a paper napkin with the words “Iz Gud!” written in crayon and the VRBPAC would have approved the shot. They are all in the cartel together and they are all looking forward to their massive payoff/payday.
But let’s not be like Pharma. Instead, let’s attempt to come up with a best guess estimate based on real world data. Over time, others will develop a much more sophisticated estimate (for example, Walach, Klement, & Aukema, 2021 estimated an NNTV for 3 different populations based on “days post dose”). But for our purposes here I think there is a much easier way to come up with a ballpark NNTV estimate for children ages 5 to 11.
Here’s the benefits model:
- As of October 30, 2021, the CDC stated that 170 children ages 5 to 11 have died of COVID-19-related illness since the start of the pandemic. (That represents less than 0.1% of all coronavirus-related deaths nationwide even though children that age make up 8.7% of the U.S. population).
- The Pfizer mRNA shot only “works” for about 6 months (it increases risk in the first month, provides moderate protection in months 2 through 4 and then effectiveness begins to wane, which is why all of the FDA modeling only used a 6 month time-frame). So any modeling would have to be based on vaccine effectiveness in connection with the 57 (170/3) children who might otherwise have died of COVID-related illness during a 6-month period.
- At best, the Pfizer mRNA shot might be 80% effective against hospitalizations and death. That number comes directly from the FDA modeling (p. 32). I am bending over backwards to give Pfizer the benefit of considerable doubt because again, the Pfizer clinical trial showed NO reduction in hospitalizations or death in this age group. So injecting all 28,384,878 children ages 5 to 11 with two doses of Pfizer (which is what the Biden administration wants to do) would save, at most, 45 lives (0.8 effectiveness x 57 fatalities that otherwise would have occurred during that time period = 45).
- So then the NNTV to prevent a single fatality in this age group is 630,775 (28,384,878 / 45). But it’s a two dose regimen so if one wants to calculate the NNTV per injection the number doubles to 1,261,550. It’s literally the worst NNTV in the history of vaccination.
If you inject that many children, you certainly will have lots and lots of serious side effects including disability and death. So let’s look at the risk side of the equation.
Here’s the risk model:
- Because the Pfizer clinical trial has no useable data, I have to immuno-bridge from the nearest age group.
- 31,761,099 people (so just about 10% more people than in the 5 to 11 age bracket) ages 12 to 24 have gotten at least one coronavirus shot.
- The COVID-19 vaccine program has only existed for 10 months and younger people have only had access more recently (children 12 to 15 have had access for five months; since May 10) — so we’re looking at roughly the same observational time period as modeled above.
- During that time, there are 128 reports of fatal side effects following coronavirus mRNA injections in people 12 to 24. (That’s through October 22, 2021. There is a reporting lag though so the actual number of reports that have been filed is surely higher).
- Kirsch, Rose, and Crawford (2021) estimate that VAERS undercounts fatal reactions by a factor of 41 which would put the total fatal side effects in this age-range at 5,248. (Kirsch et al. represents a conservative estimate because others have put the underreporting factor at 100.)
- With potentially deadly side effects including myo- and pericarditis disproportionately impacting youth it is reasonable to think that over time the rate of fatal side effects from mRNA shots in children ages 5 to 11 might be similar to those in ages 12 to 24.
So, to put it simply, the Biden administration plan would kill 5,248 children via Pfizer mRNA shots in order to save 45 children from dying of coronavirus.
For every one child saved by the shot, another 117 would be killed by the shot.
The Pfizer mRNA shot fails any honest risk-benefit analysis in children ages 5 to 11.
Even under the best circumstances, estimating NNTV and modeling risk vs. benefits is fraught. In the current situation, with a new and novel bioengineered virus, where Pfizer’s data are intentionally underpowered to hide harms, and the FDA, CDC, & Biden Administration are doing everything in their power to push dangerous drugs on kids, making good policy decisions is even more difficult.
If the FDA or CDC want to calculate a different NNTV (and explain how they arrived at that number) I’m all ears. But we all know that the FDA refused to calculate an NNTV not because they forgot, but because they knew the number was so high that it would destroy the case for mRNA vaccines in children this age. Your move CDC — your own Guidance document states that you must provide this number.
FDA approves Pfizer jab for kids, but even they don’t seem sure it’s safe
By Helen Buyniski | RT | November 1, 2021
American children have no choice but to act as experimental test subjects for the Pfizer Covid-19 vaccine to determine the jab’s safety, the Food and Drug Administration has apparently concluded. Good luck, kids!
“We’re never going to learn about how safe the vaccine is unless we start giving it,” editor of the New England Journal of Medicine and Harvard adjunct professor Eric Rubin argued last week, his words buried within the eight-hour barrage of presentations and discussions that swirled around the FDA advisory panel’s approval of the mRNA jab for children aged five to 11.
The FDA followed up on the advisory panel’s 17-0 recommendation with approval, as it typically does, on Friday. If the Centers for Disease Control and Prevention follows suit, some 28 million American children will be quickly served up as fresh-faced fodder for a smaller dose of the Covid-19 vaccine already poised to inject some 100 million American adults. That is, as soon as President Joe Biden is able to whip up a legally-binding demand he can submit to the Occupational Safety and Health Administration.
Friday’s FDA approval means only the CDC stands between American children and a warp-speed rollout of the Pfizer jab. However, the rush to approval doesn’t necessarily mean there are no concerns. A disturbingly large portion of the FDA committee’s members are connected to Pfizer in some way or another, leading vaccine skeptics to cry foul. Meanwhile, a growing portion of the country continues to denounce the mandates in general, insisting everyone should be able to make their own decision regarding whether or not they wish to get injected.
Echoing the newly-reanimated pro-choice slogan, mandate protesters recently swarmed the Brooklyn Bridge declaring ‘My body, my choice’ as New York City employees faced the potential loss of their jobs as firefighters, police officers, sanitation handlers, and corrections officers due to Mayor Bill de Blasio’s insistence that all municipal employees get vaxxed or be relegated to the purgatory of open-ended unpaid leave.
The FDA’s effort to put the cart so far in front of the horse mirrored the words of House Speaker Nancy Pelosi during the congressional tug-of-war over Obamacare in 2010. Faced with a phonebook-sized, dubiously-legal bill unlike anything Congress had passed before and no realistic timeframe to wrangle with the details, Pelosi suggested Congress would have to “pass the bill to find out what’s in it, away from the fog of controversy.”
Since then, legislation by brute force has only grown as the means by which laws are passed in the US, as ever-more-polarized parties refuse to give an inch and betray the appearance of weakness. Allowing the ‘other side’ to be seen as achieving even the slightest victory is unconscionable, and that framework remains in place in the vaccination arena – where it makes less sense than anywhere else.
After all, it was former President Donald Trump’s Operation Warp Speed that brought the world the Pfizer shot, even if the jab itself wasn’t rolled out until shortly (some would say deliberately) after the 2020 election and vaccine mandates have since become a cause celebre of the Democratic Party.
With half the US up in arms about the other half’s supposed refusal to roll up its sleeves and submit to an intensely politicized needle, anyone who hesitates is denounced posthaste in a 21st-century witch hunt – to be fired, if not set on fire; outfitted with the scarlet A for anti-vaxxer, not adulteress; and otherwise chased out of the public square – deplatformed from Twitter, YouTube and Facebook, if not chased physically with pitchforks and torches. Similar divisions have erupted across Europe, and countries like Italy and France have pushed the issue even further, barring the unvaccinated from so much as entering grocery stores to buy food.
While the US study of the Pfizer vaccine’s effects on children five to 11 failed to turn up any deadly side effects, critics argued its population size was too small to be effective for such a purpose. Parents of some jab recipients have observed disturbing symptoms in their offspring in the hours and days following the shots and filmed heartbreaking testimonials describing their downfall from healthy children to pain-wracked perma-patients experiencing near-constant seizures, facial distortions, debilitating heart problems, or other dire health issues.
Another doctor on the FDA committee, Michael Kurilla of the National Institutes of Health, abstained from voting on recommending Pfizer-BioNTech’s vaccine entirely, citing a lack of evidence that all children need the shot, and while Kurilla, an infectious disease and pathology expert, was the only panel member to abstain from voting, he was not the only member to openly express misgivings about doling out the jab to young Americans. His colleague, Dr. Cody Meissner of Tufts University, suggested that it would be an “error” to mandate the jab for children to return to school until there was more hard data.
“We simply don’t know what the side effects are going to be,” he said, acknowledging the shot – like its adult equivalent – probably wouldn’t prevent transmission of the virus. While he was not opposed to administering the shot to certain vulnerable subgroups inside the 5-11 age group, Meissner was concerned approving the shot for everyone in that category would lead to a heavy-handed mandate the likes of which is currently being wielded against American adults.
Children who receive the Pfizer-BioNTech jab may actually get less immunity and face more risk than supplied by getting and recovering from a current strain of Covid-19, Kurilla told the Daily Mail, referring to the Delta variant and other current strains of Covid-19 circulating among the population. “The question really becomes, does this vaccine offer any benefits to them at all?” he asked rhetorically during the FDA committee meeting. He would have voted ‘yes’ if the FDA had merely proposed opening up access to the vaccine to a ‘subset’ of those ages five to 11, but he disagreed with administering it to all children within that age group.
Two other panel members voted to approve despite their misgivings. Meissner argued that a “very small percent of otherwise healthy six-to-11-year-old children…might derive some benefit,” while President and CEO of Meharry Medical College James Hildreth agreed that “vaccinating all of the children…seems a bit much for me,” pointing to the relatively low risk of hospitalization and near-zero risk of death by Covid-19 for children.
Speaking up against the jab, even circumstantially, has become the kiss of death in the medical community, with even medical rock stars like Robert Malone, one of the inventors of mRNA as a drug, cast into the dustbin of history for expressing skepticism that his invention was being incorrectly used to deliver the Covid-19 vaccine.
However, governments worldwide are setting themselves up for civil war as populations are forced to choose one ‘side’ or another. Even many of the vaccinated have acknowledged that the jab should not be forced on anyone, while entire industries like shipping, air travel, defense, and the like grind to a halt as mandates run up against the stubborn will of their employees. Southwest Airlines was allegedly forced to cancel thousands of flights earlier this month, due to a reported mass ‘sickout’ by air traffic controllers unwilling to get vaxxed, though the airline itself has denied this, and rumors of trucker strikes from Australia to America have food sellers panicking at the thought of empty shelves.
As it stands, parents who were willing to submit themselves to experimental shots in the name of convenience and retaining employment may not be so willing to offer up their children as sacrifices to a company once denounced by the US Justice Department as the worst fraudster in the pharmaceutical industry.
Governments that have shown themselves as profoundly untrustworthy throughout the Covid-19 pandemic are unlikely to change their behavior at the last minute, and parents are wise to take care in where they place their trust.
CDC’s Committee Member Dr. Chen Should Be Removed Immediately Due to Conflict of Interest
By Toby Roger Ph.D. | The Defender | November 1, 2021
Dr. Wilbur H. Chen wants you to know that he’s very upset (see comment’s section)!
He’s upset the peasants have access to email!
He’s upset the peasants have access to common sense and reason!
He’s upset the peasants actually read scientific studies for themselves!
And he’s very upset that the peasants are speaking to him without his express written permission!
Apparently, he’s also clairvoyant (like Santa) because he knows what you are writing before you even send it to him, so he has set up an auto-reply on his email account to let you know he’s very important, he gets lots of emails and he does not like “misinformation.”
Chen defines “misinformation” as anything that contradicts the Pharma narrative. Chen is adamant that nothing be allowed to pierce his protective Pharma information bubble.
I’m reminded of the phrase, “Methinks thou doth protest too much.”
What Chen is actually mad about is that he got caught with his hand in the cookie jar.
A search of the government website Open Payments reveals Chen accepted $437,250.70 from Emergent BioSolutions and GlaxoSmithKline (GSK) in 2020.
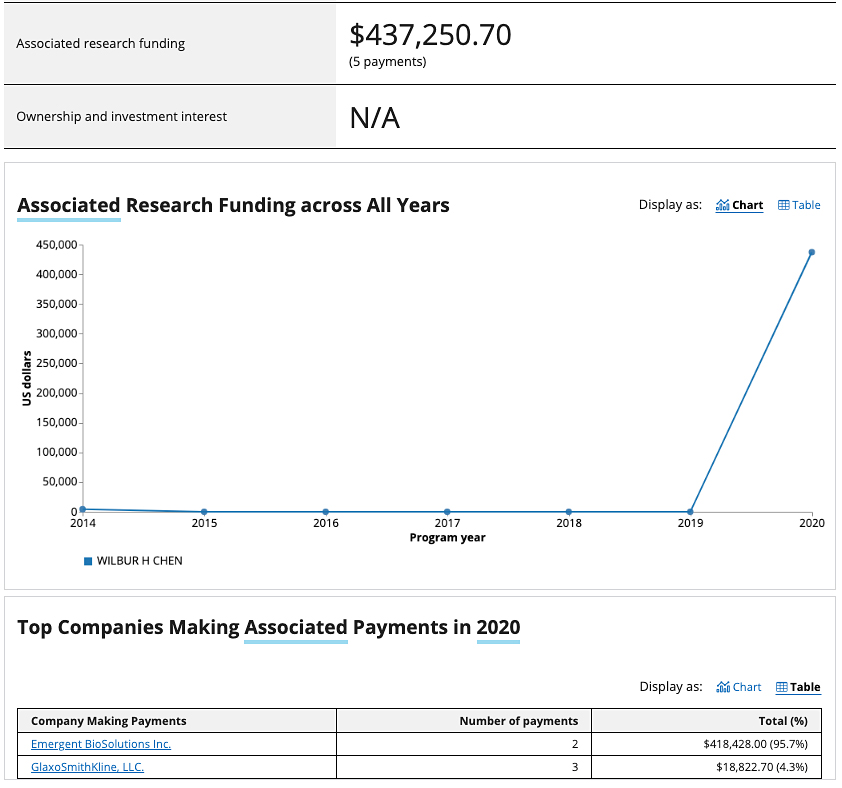
GSK is one of the four largest vaccine makers in the world. GSK makes the incredibly toxic Hep B vaccine (Engerix-B), the troubled HPV vaccine (Cervarix), a meningococcal vaccine that is loaded with aluminum (Bexsero) and various flu vaccines among others.
GSK is also working on a COVID-19 vaccine that is now in Phase 3 clinical trials.
All of GSK’s products must go before the Centers for Disease Control and Prevention (CDC) Advisory Committee on Immunization Practices (ACIP), that Chen sits on, in order to be approved.
Emergent BioSolutions is a contract manufacturer that makes vaccines for others including the Johnson & Johnson (J&J) COVID-19 vaccine that has been linked to blood clots and a bleeding disorder.
Emergent BioSolutions has an abysmal safety record. Even though federal regulators are generally like Mr. Magoo when it comes to spotting safety problems, the issues at Emergent’s plant in Baltimore were so egregious that earlier this year the U.S. Food and Drug Administration shut down the plant and ordered J&J to take it over and run it themselves.
The FDA also ordered 75 million doses of COVID-19 vaccines manufactured at that plant be destroyed because of contamination. All of the vaccines manufactured at the Emergent BioSolutions plant must first be approved by the ACIP where Chen is a member.
This is completely unacceptable. According to the Bureau of Labor Statistics, there were 27,550 pediatricians employed in the U.S. There is absolutely no reason for the ACIP to utilize a person with such extensive financial conflicts of interest.
The CDC must be above reproach in order to have any credibility with the general public. Sadly the CDC appears to do whatever it can get away with — a classic example of the fox guarding the henhouse.
The fact that these decisions involve the health of our children makes corruption all the more appalling.
Please contact the following four officials (as well your elected representatives) to let them know that you are troubled by Chen’s extensive financial conflicts of interest and please ask that he be removed from the ACIP before it meets on Tuesday, Nov. 2.
Dr. Rochelle Walensky
Director, Centers for Disease Control and Prevention
Roybal Building 21, Rm 12000
1600 Clifton Rd, Atlanta, GA 30333
phone: (404) 639-7000
Aux7@cdc.gov
Xavier Becerra
Secretary, Health and Human Services
200 Independence Avenue S.W., Washington, D.C. 20201
c/o Sean McCluskie
sean.mccluskie@hhs.gov
Captain Amanda Cohn
Chief medical officer
National Center for Immunizations and Respiratory Diseases
Centers for Disease Control and Prevention
1600 Clifton Rd, Atlanta, GA 30333 MS C-09
phone: (404) 639-6039
fax: (404) 315-4679
acohn@cdc.gov
anc0@cdc.gov
Grace Lee, M.D.
Chair, Advisory Committee on Immunizations Practices
Center for Academic Medicine
Pediatric Infectious Diseases, Mail Code: 5660
453 Quarry Road, Stanford, CA 94304
phone: (650) 497-0618
phone: (650) 498-6227
fax: (650) 725-8040
It is beyond alarming that the ACIP has failed to properly monitor financial conflicts of interest amongst its members. All prior ACIP votes involving Chen should be reviewed by an independent outside review board to see if they must be thrown out because of this blatant corruption.
The CDC should also examine and release publicly all financial conflict of interest statements from all remaining ACIP members to determine if there are additional problems before Tuesday.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Recovered immunity is weak “Because science”/CDC
By Meryl Nass, MD | October 24, 2021
“Because science” is new slang terminology that refers to bogus explanations or justifications for why things are done a certain way during the pandemic.
I have come to love the term because it encapsulates the contempt for the public evidenced by officials who usually know little about science but regurgitate “the science” to justify some unjustifiable policy.
Aaron Siri, a wonderful attorney, has challenged US health agencies on many of their illogical and often illegal pandemic policies.
He just posted the exchange he has had with CDC over its refusal to acknowledge the presence of immunity to COVID in the recovered.
While the whole document is interesting, the very end contains some of CDC’s “because science” answers.
Let me explain what CDC has been doing over the past year: whenever there is strong evidence that shows a CDC claim or policy is dead wrong, CDC’s “scientists” conduct a bogus study which can involve cherrypicking endpoints, choosing specially selected time periods, and a variety of other shenanigans to produce “evdience” that calls into question the real science. They have done this with masks, lockdowns, recovered immunity, and vaccines for children, that I can recall off the bat. I worked with a group of scientists who tried to reproduce the CDC’s calculations. But we couldn’t, because even though the CDC “scientists” were friendly and seemingly open, they never would provide enough information on their data set and their algorithm(s) for us to check their work. Clearly that was CDC policy, even though it flies in the face of standard ICMJE medical publication standards.
And that is what they did in this case. Despite mountains of evidence regarding the strength of recovered immunity, CDC just cited its own bogus study, while leaving the door open in case “the science” changed in the future. Where is the shame?
And, the agencies don’t mind dragging litigation on forever, since it is your money that is paying for it.
FDA and CDC Ignore Damning Report that over 90% of a Hospital’s Admissions were Vaccinated for Covid-19
By Aaron Siri | October 17, 2021
A concerned Physician Assistant, Deborah Conrad, convinced her hospital to carefully track the Covid-19 vaccination status of every patient admitted to her hospital. The result is shocking.
As Ms. Conrad has detailed, her hospital serves a community in which less than 50% of the individuals were vaccinated for Covid-19 but yet, during the same time period, approximately 90% of the individuals admitted to her hospital were documented to have received this vaccine.
These patients were admitted for a variety of reasons, including but not limited to COVID-19 infections. Even more troubling is that there were many individuals who were young, many who presented with unusual or unexpected health events, and many who were admitted months after vaccination.
One would think that after an association was identified by a healthcare professional, our health authorities would at least review this finding, right? Sadly, when Ms. Conrad reached out to health authorities herself, she was ignored. My firm then sent a letter to the CDC and FDA on July 19, 2021 on Ms. Conrad’s behalf (see letter below), yet neither agency has responded. Even worse, when doctors came to Ms. Conrad for assistance with filing VAERS report for their patients, the hospital prohibited her from filing these reports.
That the CDC and FDA failed to respond is arguably not surprising – they have been cheerleading this vaccine for months. Admitting almost any harm now would be akin to asking them to turn a gun on themselves.
This again highlights the importance of never permitting government coercion and mandates when it comes to medical procedures.
Full letter to the CDC and FDA:

Letter exchange with the hospital:

In-depth interview with Ms. Conrad on the Highwire:

In 20 Years of Practicing Medicine, ‘I’ve Never Witnessed So Many Vaccine-Related Injuries’
The Defender | October 13, 2021
In a letter dated Sept. 28 to officials at the U.S. Food and Drug Administration (FDA) and Centers for Disease Control and Prevention (CDC), an ICU physician detailed her concerns about the adverse reactions, including deaths, she witnessed in people who had received a COVID vaccine.
Dr. Patricia Lee, a licensed physician in California, said her experience with patients harmed by the vaccine “does not comport with claims made by federal health authorities regarding the safety of COVID-19 vaccines.”
In the letter, Lee described observing “entirely healthy individuals suffering serious, often fatal, injuries,” including transverse myelitis, resulting in quadriplegia, pneumocystis pneumonia, multi-system organ failure, cerebral venous sinus thrombosis, postpartum hemorrhagic shock and septic shock.
Lee, a practicing physician for more than 20 years, said she “never witnessed so many vaccine-related injuries until this year.”
Lee told Dr. Peter Marks, director of the FDA’s Center for Biologics Evaluation and Research, and Dr. Tom Shimabukuro with the CDC’s COVID-19 Vaccine Task Force Vaccine Safety Team, that while “causation is difficult to prove definitively, it is my clinical judgment that each of these injuries were caused by a COVID-19 vaccine, because there was no other plausible explanation for these injuries other than the fact that the patients had recently been vaccinated.”
Lee acknowledged that her report reflects the experience of a single physician. However, she wrote, it appears “statistically improbable” that any one physician should witness this many COVID-19 vaccine injuries if the federal health authority claims regarding the vaccines’ safety were accurate.
“I can no longer silently accept the serious harm being caused by the COVID-19 vaccines,” Lee concluded. “It is my sincere hope that the reaction to this letter will not be to focus on me, but rather to focus on addressing the serious safety issues with these products that, without doubt, you have either missed or are choosing to ignore.”
Since the issuing of the original letter, Lee’s attorneys sent another letter to the CDC and FDA saying that the agencies’ “failure to respond is highly concerning,” adding that they are seeking a response so they can “arrange a discussion and information gathering session between Dr. Lee and the appropriate representatives at the CDC and FDA.”
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Dr. Mercola’s Latest Response to CNN’s Hit Piece
By Dr. Joseph Mercola | October 5, 2021
CNN reporter Randi Kaye visited my home unannounced, then tracked me down as I bicycled around my home town in August 2021. Her purpose was to publish a hit piece further labeling me as a “super-spreader of COVID-19 misinformation,”1 based primarily on the opinions of foreign agent Imran Ahmed, founding CEO Center for Countering Digital Hate (CCDH),2 which is a recently spun up front group funded by dark money.
After that story aired, she again contacted me, this time via email, to request an interview regarding my latest book, “The Truth About COVID-19: Exposing The Great Reset, Lockdowns, Vaccine Passports, and the New Normal.” Interview questions were provided via email, as were my responses. CNN ran this new story October 4, 2021.
In the interest of transparency, below I’ll post the email exchange so you can read my response to her questions firsthand. You can tell from the leading questions that this “story” isn’t true journalism but rather another hit piece manipulated to fit a preformed agenda.
CNN Interview Request for My Latest Book
August 26, 2021, Kaye emailed, “Here are the questions we would like answered about Dr. Mercola’s new book. We would welcome responses by 5pm tomorrow, please.” The questions, which are clearly accusatory, are as follows:
“You say in your book that “A large amount of data strongly suggests the COVID – 19 vaccine may be completely unnecessary, which means the global population is being bamboozled into participating in a dangerous and unprecedented experiment for no good reason whatsoever.” Can you please point us to that data that suggests the covid vaccines are unnecessary or dangerous?
You say in your book that “vaccine trials are rigged.” What proof do you have of that? Which trials? How many? Who rigged them and for what purpose?
You say in your book, “Common sense dictates that if the vaccines cannot prevent or reduce infection and transmission, hospitalization, or death, then they cannot possibly end the pandemic.” And that “There’s no telling whether they will ultimately prevent hospitalizations and deaths.”
Can you please provide us with the source and support for your statements since the CDC says vaccines are nearly 100% effective at preventing severe disease and death and greatly reduce infection.
How do you explain statements from hospitals and government officials that nearly all those who are getting sick and dying now are the unvaccinated?
Do you feel responsible for the spread of misinformation by writing a book full of conspiracy theories and false claims?
What were you paid for this book deal by the publisher?
Are you donating 100% of the earnings from your book?
If so, to which organization? Are you concerned this book will cost people their lives?”
My Response to CNN
Media organizations contact Mercola.com regularly, sometimes to challenge us on the researched, fact-checked articles we post for our readers. In CNN’s case, the information they were seeking was directly related to my book, which was the No. 1 best seller in all categories for four straight days with thousands of five-star ratings.
Much like the information on Mercola.com, the information in my book is thoroughly referenced, but Kaye, ironically, engaged in the dissemination of misinformation herself by describing my book as being “full of conspiracy theories and false claims.” My response to her questions follows:
“Many studies and other literature offer support for my position in answering several of your questions, which are combined since they can be answered with the same literature. Here are the important points that drive my book:
The vaccines are just 39% effective and waning, and the CDC’s Advisory Committee on Immunization Practices has now advised booster doses to the mRNA vaccines in immunocompromised persons. CDC’s goal is to begin offering booster doses to everyone else beginning this fall.3,4,5,6
Additionally, breakthrough infections among fully vaccinated persons are becoming more and more prevalent around the world. Evidence is beginning to mount that people with breakthrough infections can spread the Delta variant more easily.7,8,9,10,11,12,13
Most recently, researchers in Israel report that fully vaccinated persons are up to 13 times more likely to get infected than those who have had a natural COVID infection.
As explained by ScienceMag: The study “found in two analyses that people who were vaccinated in January and February were, in June, July and the first half of August, six to 13 times more likely to get infected than unvaccinated people who were previously infected with the coronavirus.
In one analysis, comparing more than 32,000 people in the health system, the risk of developing symptomatic COVID-19 was 27 times higher among the vaccinated, and the risk of hospitalization eight times higher.”14
The study also said that, while vaccinated persons who also had natural infection did appear to have additional protection against the Delta variant, the vaccinated were still at a greater risk for COVID-19-related-hospitalizations compared to those without the vaccine, but who were previously infected.
Vaccinees who hadn’t had a natural infection also had a 5.96-fold increased risk for breakthrough infection and a 7.13-fold increased risk for symptomatic disease.
“This study demonstrated that natural immunity confers longer lasting and stronger protection against infection, symptomatic disease and hospitalization caused by the Delta variant of SARS-CoV-2, compared to the BNT162b2 two-dose vaccine-induced immunity,” study authors said.15
A majority of gravely ill patients in Israel are double vaccinated.16 A majority of deaths over 50 in England are also double vaccinated.17 Also, mass vaccination of the population with the highly mutating coronavirus will only evolve perfectly vaccine-resistant strains of the virus.”18
Injection Trials Included COVID-19 Infections as Successes
The next part of my response focused more specifically on the vaccine trials, which were problematic from the start since they did not include prevention of infection as an endpoint. Instead, all study endpoints required infection with SARS-CoV-2, and “successes” included subjects with confirmed COVID-19 cases. The difference measured wasn’t whether or not the vaccines prevented COVID-19 but whether, and how, they modified symptoms among those infected.19
Also problematic is the unblinding of the vaccine trials, which means the placebo groups were removed. As medical investigative journalist Jeanne Lenzer wrote in the BMJ, “The data are now likely to be scanty and less reliable given that the trials are effectively being unblinded.”20 This is the next section of my response to Kaye:
“Regarding the vaccine trials: The vaccine trials were designed specifically to succeed for profit. The public health authorities and media like CNN are utilizing fear of the virus to induce psychological stress that promotes obedience and servitude.21
Additionally, proof that the trials are “rigged” can be shown by virtue of the fact that they’ve done away with the control groups — who were getting a placebo but who were then offered the vaccine, which virtually does away with the ability to compare adverse reactions including deaths. Pfizer’s own vaccine insert for Comirnaty admits that the control group hasn’t existed since December 2020:
Section 6.1 — “Upon issuance of the Emergency Use Authorization (December 11, 2020) for COMIRNATY, participants were unblinded to offer placebo participants COMIRNATY. Participants were unblinded in a phased manner over a period of months to offer placebo participants COMIRNATY.”22
NPR has noted that removing the placebo groups from vaccine trials will prevent accurate data from long-term studies from being known.23
Additionally, the CDC is being dishonest by utilizing data from the beginning of this year when the vaccine campaign had just been initiated to conflate their claim. They are using data that were scant early in the year because so few were vaccinated, as opposed to using current information.24
Proceeding with the FDA approval of Comirnaty this week was unprecedented. No other vaccine has ever received approval this fast — and without public comment being allowed through ACIP [the CDC’s Advisory Committee on Immunization Practices] or VRBPAC [the FDA’s Vaccines and Related Biological Products Advisory Committee] before approval was issued.
The approval is unconscionable because over 600,000 adverse reactions and 6,000 deaths [now over 14,500 deaths25] have been reported in the U.S. to VAERS. A majority of these reports are filed by medical professionals.
This shows that the safety of these vaccines is not proven. Besides, the experiments are continuing through 2027 as the FDA APPROVAL requires Pfizer to submit study results analyzing risk of myocarditis and pericarditis, and risk to long-term infant development in pregnant women. Study results will be submitted to the FDA for review on Oct 31, 2025 and May 31, 2027 respectively.”26
Lifesaving Information That CNN Won’t Share
CNN and other media outlets have the power to share lifesaving information that could turn the pandemic around and save lives in the process — but they won’t. Instead, the media are ignoring the basics of healthy immune function and the importance of early COVID-19 treatment to continue to push the narrative that the only solution is to get an injection.
The last part of my response to Kaye includes empowering steps that virtually everyone can take to support their health and reduce their risk of infectious disease. This includes having supplies from the Front Line COVID-19 Critical Care Working Group (FLCCC) I-MASK+ protocol on hand in the event you do get COVID-19.
FLCCC’s I-MASK+ protocol can be downloaded in full,27 giving you step-by-step instructions on how to prevent and treat the early symptoms of COVID-19. FLCCC also has protocols for at-home prevention and early treatment, called I-MASS, which involves ivermectin, vitamin D3, a multivitamin and a digital thermometer to watch your body temperature in the prevention phase and ivermectin, melatonin, aspirin and antiseptic mouthwash for early at-home treatment.
I also recommend getting a nebulizer, and the moment you feel a sniffle or something coming on, use nebulized hydrogen peroxide. Having a pulse oximeter on hand is also wise, as it’s a noninvasive way to measure the oxygen levels in your blood, allowing you to monitor your levels and help gauge whether a trip to the ER is truly in order.
As I told Kaye, taking control of your health continues to be the “secret” that I strive to share with the masses. The remainder of my response to CNN follows:
“I am donating all proceeds to the National Vaccine Information Center. I encourage every person to fully educate themselves to make individual decisions about medical risk-taking by talking with their personal physician and comparing the risks and benefits to make an informed decision that includes all the information on how these vaccines are working (or not working) and what all the possible side effects may be.
This pandemic is a direct reflection of the health of our population: 95% of COVID deaths have multiple comorbidities. Obesity, vitamin D deficiency and metabolic dysfunction are at the core of this pandemic and can be resolved by taking control of your health by following science-based dietary and lifestyle recommendations.
Since building up your health can’t be done overnight, what you can do beginning right now is avoid linoleic acid, check to ensure your vitamin D levels are above 40ng/ml, exercise, get fresh air and proper sun exposure, and restrict your eating window to a 6- to 8-hour time frame each day.
If you do get COVID-19, early treatment is crucial. Follow the Front Line Critical Care Alliance iMASK+ or MATH+ treatment protocols.”28
Sources and References
- 1 YouTube August 5, 2021
- 2 Twitter Josh Hawley July 20, 2021
- 3 CNBC July 23, 2021
- 4 KHN Morning Briefing August 26, 2021
- 5 Contagion Live August 14, 2021
- 6 U.S. CDC, COVID-19 Vaccine Booster Shot September 1, 2021
- 7 CNBC July 30, 2021
- 8 NPR August 23, 2021
- 9 MSN August 27, 2021
- 10 Reuters August 20, 2021
- 11 CIDRAP July 29, 2021
- 12 Reuters August 25, 2021
- 13 National Geographic August 20, 2021
- 14 Science August 26, 2021
- 15 medRxiv August 25, 2021
- 16, 17 Science August 16, 2021
- 18 LiveScience August 6, 2021
- 19, 21 Forbes September 23, 2020
- 20 BMJ 2020;371:m4956
- 22 FDA, Comirnaty Highlights of Prescribing Information
- 23 NPR February 19, 2021
- 24 Undercurrents, The Lies Behind the “Pandemic of Unvaxxed”
- 25 MedAlerts September 3, 2021
- 26 thebmjopinion August 23, 2021
- 27 FLCCC Alliance, I-Mask+
- 28 FLCCC Alliance, I-Mask+ Prevention & Early Outpatient Treatment Protocol for COVID-19
Featured Video

Iran spent $1 million to wipe out $30 billion in data center plans, and take down Amazon in the ME
or go to
Aletho News Archives – Video-Images
From the Archives
A short history of British torture
ICC | December 2005
When the House of Commons was debating how much to increase the time limit for detention without trial the question of torture came up. Officially this was limited to the nice considerations of whether it was all right to send people to places where torture is used and whether Britain can use information collected by the use of torture in other countries. This discussion gave an impression of democratic Britain as the home of civilised behaviour where the very idea of torture is repugnant to our legislators – unlike, say, the US with its secret CIA jails… In reality, the British state has a long history of using and developing a whole range of torture techniques. … continue
Blog Roll
 Aletho News
- Iran spent $1 million to wipe out $30 billion in data center plans, and take down Amazon in the ME
- Zionist billionaire pressure to silence Macklemore sparks exodus from Ed Sheeran tour
- House Votes to End Iran War for Third Time
- North Korea Slams US Plan for ‘AUKUS 2.0’ with South Korea and Japan
- Prolonging US-Iran Conflict Not Meeting Interests of Int’l Community – China’s Wang Yi
- EU bans former Zelensky aide from parliament
- NATO-backed Kosovo separatist ‘responsible for war crimes’
- US destroying international space law
- SCO Calls for Binding Global Deal to Prevent Arms Race in Space
- Iran & Its Allies Are Threatening Every Route for Saudi Oil
- If Americans Knew
- Groups urge Americans to support Van Hollen legislation on Israel’s killing of Americans & Palestinians
- Trump administration plans to send 40,000 tons of bombs to Israel: report
- Sanctions Target Iran’s Government, But Kill Hospitalized 23-Year-Old Woman
- An alternative view on the book “Israel’s Lobby: America in the Grip of a Foreign Power”
- Ed Sheeran’s band Beoga, other opening acts quit tour after Macklemore was dropped over his pro-Palestinian comments
- The assassination attempt on President Trump in Butler and the various Israeli connections to it
- “We Want That the Whole Land Be Jewish”
- BREAKING: Building collapse in Gaza kills at least 20 as they sleep – Daily Update
- ‘School is Life’: 1.5 Million Palestinian Children Face Fourth Year of Shattered Education
- Pentagon admits Iran war caused ammunition shortages, cost US $33.4bn
- No Tricks Zone
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
- End-Of-August Arctic Sea Ice Extent Hasn’t Fallen In 20 Years, Official Data Show!
- News-Making Nepal Region Has Had As-Warm Or Warmer Periods Than The 2000s In The 1600s, 1700s, 1800s
 Aletho News
