From Florida’s Surgeon General, a devastating indictment of the vaccine and its pushers
By Neville Hodgkinson | TCW Defending Freedom | June 22, 2023
When it comes to error correction, the USA’s 50 sovereign states offer more opportunity for an authoritative challenge to the misuse of power than we enjoy in the UK. Dr Joseph Ladapo, the Florida Surgeon General, has made public a letter excoriating federal health officials over their promotion of the mRNA Covid vaccines. The government, he said, ‘has relentlessly forced a premature vaccine into the arms of the American people with little or no concern for the adverse ramifications’.
The letter was to Drs Robert Califf, head of the Food and Drug Administration, and Rochelle Walensky, director of the Centers for Disease Control and Prevention. Lapado wrote: ‘Your ongoing decision to ignore many of the risks associated with mRNA Covid-19 vaccines, alongside your efforts to manipulate the public into thinking they are harmless, have resulted in deep distrust in the American health care system.’
As reported here earlier this year, senior American scientists have called for a ‘bipartisan, scientifically minded Covid-19 commission so the public health disaster of the past three years is not repeated’. They face an uphill struggle in achieving that aim, but Ladapo’s no-holds-barred letter means that at least some of Florida’s 22.6million citizens have a chance of knowing the jabs are not ‘safe and effective’, as the British public are constantly being told.
Ladapo would surely have been less forthright if Ron DeSantis, Florida’s Republican governor and a possible future US president, were not also on the warpath over the Biden administration’s handling of the pandemic. The Florida Supreme Court has approved DeSantis’s request to convene a grand jury to investigate ‘wrongdoings’ associated with the vaccines.
But DeSantis is not alone. The Texas Attorney General has launched an investigation into whether Pfizer, Moderna and Johnson & Johnson, the companies producing the jabs, misrepresented their safety and efficacy and manipulated trial data. The investigation could open the door to lawsuits by people injured by the mRNA products.
Meanwhile, what hope of redress do Britons have, not just for vaccine damage but for the lives shattered by cruel and unprecedented lockdowns?
The public inquiry led by Baroness Hallett looks likely to be worse than useless, as Laura Dodsworth, author of the best-selling A State of Fear: How the UK Government Weaponised Fear During the Covid-19 Pandemic, has described.
It is in ‘the wise and noble tradition of the great British public inquiry’, Rod Liddle commented in the Sunday Times last weekend. That is, keep the public away from it for as long as possible, and say nothing useful or meaningful unless ‘at least 20 years after whatever it is that they are inquiring about, at which point most of the relevant people are stiff as a stoat’.
The headline on Liddle’s article declared: ‘The data is clear: lockdowns are useless. But you won’t hear that from the inquiry.’
Sadly, neither the Sunday Times nor its daily stablemate, nor just about any of the mainstream media in the UK, have yet ventured into questioning the ‘safe and effective’ narrative about the vaccines. So let’s look at what Ladapo, who as state surgeon general can hardly be dismissed as a conspiracy theorist, has told the American public.
‘Data are unequivocal,’ Ladapo wrote. ‘After the Covid-19 vaccine rollout, the Vaccine Adverse Events Reporting System (VAERS) reporting increased by 1,700 per cent, including a 4,400 per cent increase in life-threatening conditions.
‘Dismissing this pronounced increase as being solely due to reporting trends is a callous denial of corroborating scientific evidence also pointing to increased risk and a poor safety profile. It also fails to explain the disproportionate increase in life-threatening adverse events for the mRNA vaccines compared to all adverse events.
‘Based on the CDC’s own data, rates of incapacitation after mRNA vaccination far surpass other vaccines.’
Ladapo cited a recent study which found an excess risk of serious adverse events ‘of special interest’ for 1 in 550 people after mRNA vaccination. He wrote: ‘As you are aware, this is extraordinarily high for a vaccine. In comparison, the risk of serious adverse events after influenza vaccination is much lower. For you to claim that serious adverse events such as these are “rare” when Pfizer and Moderna’s clinical trial data indicate they are not, is a startling exercise in disinformation.
‘I want to re-emphasise that these questions could have been answered if you had required vaccine manufacturers to perform and report adequate clinical trials . . . I anticipate with regret that you will repeat past mistakes and prematurely promote new therapies to Americans without accurately and truthfully weighing data on risks and benefits.’
Ladapo then asked Califf and Walensky to answer 12 questions relating to the safety data, and concluded: ‘Your organisations are the main entities promoting vaccine hesitancy – Florida promotes the truth. It is our duty to provide all information within our power to individuals so they can make their own informed health care decisions. A lack of transparency only harms Americans’ faith in science.’
Regular readers of TCW as well as The Daily Sceptic know that numerous scientists support Ladapo’s position, such as reported here, here, here, here, here, here and here.
At present, however, the FDA and CDC, like the NHS, continue to ignore such reports, asserting that ‘the known and potential benefits of these vaccines clearly outweigh their known and potential risks, and that ‘being up to date on vaccinations saves lives compared with individuals who did not get vaccinated’.
What’s Wrong With This Study? CDC Finds COVID Shots ‘Safe and Effective’ for Kids Under 4
By Angelo DePalma, Ph.D. | The Defender | June 16, 2023
An analysis published earlier this month in Pediatrics concluded the COVID-19 mRNA vaccines are safe and effective in preschool-age children — a conclusion trumpeted by media outlets such as Parents and Medscape.
But the study, conducted by Kaiser Permanente researchers with funding from the Centers for Disease Control and Prevention (CDC), raises more questions than it answers.
Researchers followed children (mostly 4 years old or younger) who collectively received more than 245,000 doses of either the Pfizer or Moderna mRNA products and “found no indications of serious side effects,” according to a Kaiser Permanente news release.
Using a form of surveillance monitoring known as rapid cycle analysis, investigators performed weekly sequential analyses for 19 safety signals, including myocarditis, pericarditis, seizures, heart attack, Bell’s palsy, neurological inflammatory conditions, anaphylaxis and several others.
The study period was from June 2022 to March 2023.
Instead of using a comparable group of unvaccinated children as the control, the authors compared adverse events occurring 1-21 days after vaccination in one group, with outcomes among children in another group who had received the shot at some point between 22 and 42 days previously.
Time since inoculation was the only distinguishing feature, and the only factor that might account for inter-group differences.
The study, therefore, boils down to the question of whether children who received an mRNA shot about 10 days previously experienced more or fewer adverse events than children who received their jab about 32 days previously.
Data were mined from the Vaccine Safety Datalink (VSD), a repository of patient data from eight private healthcare systems, which included five Kaiser Permanente regions and three other large health entities.
Up to three doses of the Pfizer-BioNTech product were given to 135,000 children, ages 6 months to 5 years, while 112,000 children, ages 6 months to 6 years, got the Moderna gene therapy.
Subject demographics more or less reflected the populations served by these healthcare companies.
The authors wrote that their safety surveillance over nine months “did not detect a safety signal for any outcome during the 21 days after vaccination. Importantly, no cases of myocarditis or pericarditis occurred after vaccination.”
The accompanying press release framed the conclusion even more positively. According to corresponding author Dr. Nicola Klein:
“Parents can be assured that this large study found no serious side effects from the mRNA vaccines. … Parents can protect their young children from COVID-19 in the same way they vaccinate their children to protect from other serious childhood diseases.”
Perhaps anticipating the long list of questions regarding their work, the researchers discussed the potential limitations of their analysis, which they said included:
- Reduced statistical power, particularly for rare outcomes.
- Low vaccine uptake in the evaluated age group (“only” 24.7% of the eligible population received at least one shot).
- Surveillance did not include “all potential safety concerns.”
And the kicker:
“We may have underestimated or missed potential safety concerns if the biologically plausible risk interval for an outcome differed from our specified risk interval.”
Together, the choice of control group and the time period selected almost guaranteed “reduced statistical power,” particularly when comparing the two groups.
In a 2022 paper Klein noted reports from “worldwide” sources of myocarditis/pericarditis after mRNA COVID-19 treatments “especially among younger male persons [italics mine] 0 to 7 days after receiving dose 2.”
Although the incidence of heart inflammation was low in the 0-5 age group for the Pfizer product (14.4 per million doses, mostly after the second shot), the incidence of serious cardiac events rose markedly for older groups.
No data were available in the 2022 study for the Moderna shot.
For 18- to 29-year-old males — the youngest age group for which both Pfizer and Moderna data were available — Klein reported, based on VSD numbers, a cumulative myocarditis/pericarditis incidence of 135 cases per million for children who had received the two injections plus the booster.
For the Moderna product, the incidence was 185 per million. For females, the rates were about 10 per million for both mRNA shots.
Given the serious long-term consequences of heart inflammation, and its known occurrence among vaccinated teenagers and young adults, one wonders at the wisdom of giving mRNA shots to children who are even younger than those known to get sick from the treatments.
COVID-19 itself has been blamed for the rise in heart inflammation, but a search for data from very early in the pandemic, before this storyline emerged (possibly to hide the incidence of “vaccine” injuries), shows this to be a red herring.
A 2022 Italian study comparing myocarditis/pericarditis incidence pre- and post-COVID-19 reported that the annual incidence of myocarditis was significantly higher before the pandemic than during, with a rate of about 80 per million “pre” and 60 per million “during.”
The authors made a point to emphasize that “the incidence of myocarditis was significantly lower in COVID than in PRECOVID in the class of age 18-24 years” than for their general study population, which averaged 40 years of age.
The incidence of pericarditis was unchanged between the two time periods, at about 45 per million.
Comparing data from two far-flung studies should be undertaken with caution. However, the difference between a baseline of fewer than 60 cases per million for 18- to 24-year-old adults (the Italian study) and the 185 per million for “male persons” between 18 and 29 post-mRNA treatment (Klein et al.) clearly and inconveniently shatters the “safe and effective” narrative.
The lack of statistical power in Klein’s 2023 study, despite a very large “denominator” (total patients studied), is almost certainly due to the relatively small number of cases — which is exactly what one would expect when uncommon (but serious) side effects over such short time periods are compared.
True, this is an apples-to-apples comparison — but in this case, investigators pretty much used the exact same apples and reported their similarities as somehow noteworthy.
Klein’s data source(s) raise additional questions. Although the VSD is connected to the national Vaccine Adverse Event Reporting System (VAERS), how much of her raw data came from VAERS and how much came from VSD is unclear.
Eleven of VSD’s 13 participating commercial and academic hubs are “data reporting sites” whose contributions presumably include vaccine side effect reports.
The concern here is about motives and incentives. VAERS data are based mainly on self-reporting and are known to be gross underestimates of the actual number of incidents.
By contrast, hospitals and healthcare systems, e.g. those participating in VSD, were robustly incentivized to promote and administer the COVID-19 shots.
Along those lines, note that one author “received funding from Janssen Vaccines and Prevention for a study unrelated to coronavirus disease 2019 vaccines.” And lead investigator Klein “received grants from Pfizer for coronavirus disease 2019 vaccine clinical trials and from Merck, GSK, and Sanofi Pasteur for study work unrelated to the current study work.”
The rationale for immunizing children against COVID-19 has been hotly debated since the shots were first available to older adults in late 2020.
But by the time these treatments were authorized for children, it was already clear that kids do not get very sick from COVID-19 and are not a significant source of infection, either for the community or for “grandma” in her rocking chair at home.
As of early 2021, with the huge wave of Delta-variant fatalities in freefall, the number of U.S. pediatric COVID-19 deaths reported by the CDC was close to zero, both in terms of absolute cases and as a percentage of all deaths.
Yet in her interview with her institution’s media department, lead author Klein said:
“Even as the COVID-19 emergency has ended, we know that the coronavirus poses a long-term, serious threat to all ages, including children. Vaccinating children against COVID-19 benefits them by reducing the burden of illness, avoiding spreading the virus to family and others, and mitigating the small but real risk of serious illness.”
Angelo DePalma, Ph.D., is a contributing editor for The Defender.
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
‘Reckless in the Extreme’: FDA Panel Recommends New RSV Shot for Use in Healthy Infants

By Michael Nevradakis, Ph.D. | The Defender | June 9, 2023
Advisors to the U.S. Food and Drug Administration (FDA) on Thursday recommended approval of AstraZeneca’s new monoclonal antibody, which the drugmaker said is designed to protect infants and toddlers up to age 2 from respiratory syncytial virus (RSV).
The drug, nirsevimab, would be delivered to newborns in a single shot at birth or “just before the start of a baby’s first RSV season, or as a larger dose in a second RSV season in children who are highly vulnerable,” CNN reported.
Members of the independent committee, which includes several pediatricians, “were enthusiastic about the potential” of the antibody, STAT reported, as was Thomas Triomphe, executive vice president of vaccines at Sanofi, which will market the drug in the U.S.
In a statement, Triomphe said:
“Most babies hospitalized with RSV are born at term and healthy, which is why interventions specifically designed to protect all infants are likely to result in the greatest impact.
“We are encouraged by the advisory committee’s positive vote based on the compelling clinical development program supporting nirsevimab and its breakthrough potential to reduce the magnitude of annual RSV burden.”
But medical experts interviewed by The Defender raised a number of concerns, including what they said was inadequate safety testing.
“It’s preposterous to give this drug prophylactically, especially without adequate safety testing,” said Brian Hooker, Ph.D., P.E., senior director of science and research for Children’s Health Defense (CHD).
AstraZeneca reported only 48% efficacy for the drug. And Hooker noted that the “circulating half-life of the antibodies is probably less than one month so the protection would be minimal at best.”
Hooker also commented on the fact that 12 infant deaths were recorded during the clinical trial, which the FDA committee claimed were “unrelated” to the antibody:
“It appears that this vote was meant to bolster uptake and popularity of the RSV vaccines that are now approved for maternal use. The very low rate of effectiveness for such a therapy is troubling as the conservative estimate is below 50%, which is usually a hard metric for drug approval.
“Also, it seems odd that four infants in the trial would die of cardiac arrest — with no information given, it leaves one to wonder why these children would die in such a way. Also, there should be further investigation into the two SIDS [sudden infant death syndrome] deaths that occurred during the trial.”
Dr. Meryl Nass, an internist, biological warfare epidemiologist and member of CHD’s scientific advisory committee, told The Defender,“It is reckless in the extreme to inject very young babies with an inadequately tested monoclonal antibody drug to prevent a condition that for most of them will be no more than a cold.”
Cardiologist Dr. Peter McCullough told The Defender that while monoclonal antibodies are “generally safe” for children, he questioned the benefit of such a treatment for what he called a “mild” infection. He said:
“Monoclonal antibodies are generally safe in children and adults; however, I am concerned broad infant population uptake may disrupt normal thymus and immune system development that easily handle infections such as RSV, influenza, rhinovirus, adenovirus and SARS-CoV-2.
“RSV is a characteristically mild infantile infection easily resolved with conventional nebulizers. I believe nirsevimab would not be clinical-indicated for all infants and likely would be utilized in high-risk babies with congenital heart or lung disease, such as cystic fibrosis, or those with prior thoracotomies for heart surgery, where respiratory mechanics would be compromised.”
The FDA committee’s positive recommendation for nirsevimab, also known as Beyfortus, comes just weeks after the agency approved GlaxoSmithKline Biologicals’ Arexvy, the first-ever RSV vaccine for older adults, and recommended Abrysvo, Pfizer’s RSV vaccine for pregnant women.
According to CNBC, the FDA is expected to make a final decision on nirsevimab in the third quarter of this year.
Nass told The Defender that while the FDA is not obligated to follow the panel’s advice, “it almost always does so.”
FDA: Infant deaths during clinical trial ‘unrelated’ to the treatment
CNBC reported that the FDA review identified no safety concerns with nirsevimab, but also reported that 12 infants died during the trials.
According to CNBC:
“Four died from cardiac disease, two died from gastroenteritis, two died from unknown causes but were likely cases [of] sudden infant death syndrome, one died from a tumor, one died from COVID, one died from a skull fracture, and one died of pneumonia.”
Dr. Melissa Baylor, who according to CNBC is “an FDA official,” said, “Most deaths were due to an underlying disease. None of the deaths appeared to be related to nirsevimab.”
But according to STAT, “There are questions that remain to be answered” about nirsevimab that require “further study.”
For instance, no data are available “about whether giving nirsevimab to a baby whose mother was vaccinated against RSV during pregnancy would give the infant more protection or would be a waste of the product.”
STAT noted that several members of the FDA committee “worried that the dose given in the first year of life might be too small to benefit a baby who was 8 months or older when receiving the injection, depending on the size of the baby.”
Baylor also expressed concerns about how nirsevimab would interact with vaccines in development — such as Pfizer’s Abrysvo — that confer protective antibodies to the fetus by administering the shot to the mother.
CNBC reported that “Other monoclonal antibodies have been associated with serious allergic reactions, skin rashes and other hypersensitivity reactions.”
According to Baylor, the FDA did not identify “any cases of serious allergic reactions in the nirsevimab trials,” while “cases of skin rash and hypersensitivity reactions were low in infants who received the antibody.” She added that cases of such side effects are expected to be observed if the treatment receives FDA approval.
Manish Shroff, AstraZeneca’s head of patient safety, said, “Safety is of utmost importance” to the drugmaker and that it will “keep a close eye” on the safety of nirsevimab via a “global monitoring system,” CNBC reported.
According to Endpoints News, nirsevimab has already received regulatory approval in the EU, U.K. and Canada, but “it has not yet launched in any of those markets.”
According to CNBC, “Nirsevimab is administered as a single injection with the dose depending on the infant’s weight.”
Infants weighing less than 5 kilograms will receive a 50 mg dose for their first RSV season, while those over 5 kilograms will receive a 100 mg injection. Children under age 2 who “remain at risk for severe RSV” in their second season would then receive an additional 200 mg injection of the antibody.
Nirsevimab is not the first monoclonal antibody for RSV. According to STAT, AstraZeneca’s Synagis (palivizumab) is approved in the U.S. and EU, and “protects against infection in high-risk infants.”
According to CNBC, it is intended “only for preterm infants and those with lung and congenital heart conditions that are [at] high risk of severe disease” and is administered monthly, whereas nirsevimab “would be administered to healthy infants.”
Endpoints News reported that “AstraZeneca leads all development and manufacturing activities” for nirsevimab, “while Sanofi is responsible for marketing activities and revenue recognition” — for which the drugmaker paid $129 million “to be part of the collaboration.”
Is RSV really a danger for most infants?
CNBC previously reported that the U.S. “suffered an unusually severe RSV season” this past winter. The New York Times reported on a “tripledemic” involving RSV, flu and COVID-19, “that swamped children’s hospitals and some I.C.U. wards.”
One U.S. county — Orange County, California — declared a local health emergency and issued a proclamation of local emergency in November 2022, citing rising RSV cases among children in the region, and the Biden administration subsequently declared a public health emergency that month.
According to the U.S. Centers for Disease Control and Prevention (CDC), nearly all children are infected with RSV before the age of 2.
While CNBC characterized RSV as a “public health threat” that “kills nearly 100 babies in the United States every year,” Nass questioned the danger it poses to most infants.
In May, Nass wrote that the CDC published a paper on RSV deaths in infants between 2009 and 2021, which found “were only a total of 300 deaths in children less than one year over the 12 years, or 25 on average per year.”
Nass added that the number of injuries that may be caused by vaccines or other treatments during pregnancy “is almost certainly going to outweigh the loss of 25 babies a year from RSV.”
In her remarks to The Defender, Nass drew comparisons with the hepatitis B vaccine for children, saying that adverse effects from the treatment may appear later in childhood and are not likely to be connected to the drug:
“The hepatitis B vaccine, recommended for all children at birth in the US, and received by about 75%, was never tested for babies’ safety — over more than a few days — before the program started, or since.
“Because no one can know what a very young baby will become at birth, it is impossible to attribute a lower IQ, hyperactivity, less nimble limbs or any other problem that shows up later, to an injected drug given shortly after birth. So those connections, if any, are unlikely to be identified.”
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Beware of Studies Concluding Autism is Not Associated with Childhood Vaccination
By Peter A. McCullough, MD, MPH | Courageous Discourse | June 3, 2023
As an epidemiologist, I can tell you it takes considerable training and scholarship to determine whether or not a study is valid and to determine if the conclusions are supported by the data. When it comes to childhood vaccines, the world is becoming skeptical of the vaccine industry since the CDC ACIP panel has added the EUA unsafe, ineffective mRNA COVID-19 vaccines for infants starting at 6 months of age.
With the ever expanding ACIP schedule of vaccine quantity and intensity of injections there has been a skyrocketing rate of autism. This has triggered scientists to go back and look at the studies published at the time to reassure parents that routine vaccines did not cause autism. Because so many shots are given at once, it is probably not any individual product that is the culprit, rather “hyper-vaccination” of a bundle of vaccine products that invokes a neurotropic, cytokine mediated inflammatory reaction that in some causes febrile seizures, autism, and immediate death. There are factors related to susceptibility including older parents and siblings with autism, but it remains that hyper-vaccination is a likely provocateur.
Madsen et al used Danish automated health data to evaluate the association of the MMR at age 15 months and autism. Only 40/422 had charts reviewed to verify the diagnosis of autism. Because it is an important diagnosis, all 422 cases should have been adjudicated by two blinded expert child psychiatrists. This study was unlikely to find an association from the outset since not all the vaccines where considered as a “bundle” and compared to children who went “natural” meaning completely unvaccinated with any product.

Madsen KM, Hviid A, Vestergaard M, Schendel D, Wohlfahrt J, Thorsen P, Olsen J, Melbye M. A population-based study of measles, mumps, and rubella vaccination and autism. N Engl J Med. 2002 Nov 7;347(19):1477-82. doi: 10.1056/NEJMoa021134. PMID: 12421889.
To make matters worse, the authors found 18% had missed the MMR at 15 months. That proportion seemed high to me so I checked another source. In 2015-2016 Holt et al performed a chart review and found that 55% of those MMR “unvaccinated” in the Danish system were indeed received the MMR documented in the medical record. Hence the Madsen analysis is invalid since both groups had largely received the MMR shot at age 15 months and there was no reporting of the true control group of interest—completely unvaccinated children.

Holt N, Mygind A, Bro F. Danish MMR vaccination coverage is considerably higher than reported. Dan Med J. 2017 Feb;64(2):A5345. PMID: 28157059.
In studies that are using unadjudicated, automated sources of data, misclassification often biases the results to the null hypothesis making a Type II error, that is, failing to find an association when indeed it is present.
Here is a summary of why Madsen does not rule out MMR or hyper-vaccination as a cause of autism:
- non-randomized study with no true placebo group
- all 442 cases of autism were not adjudicated by at least two independent child psychiatrists to confirm the diagnosis
- Danish automated data due no capture all the MMR vaccinations; some (~55%) of the “unvaccinated” had received the MMR vaccine
- MMR was not considered as part of the multi-injection bundle of hyper-vaccinated children compared to completely natural unvaccinated kids, which is the real control group of interest for autism
A similar paper using the same data sources, nearly identical study design, and equally flawed analysis was published similarly in Annals of Internal Medicine in 2019 (Hviid et al). In summary, we cannot rely on the Madsen or Hviid studies to rule out the MMR as a partial determinant of autism. Moreover, studies that make strong conclusions with such faulty data are suspect for investigator bias—meaning the authors intentionally wanted to rule out the association perhaps to advance the vaccine agenda, appease their institutions or research sponsors, or otherwise wished to be willfully blind to the possibility that childhood hyper-vaccination is a determinant of autism.
Occurrence of Convulsions and Death After DTP Childhood Vaccination
Data Published Over 20 Years Ago Signaled Concern
By Peter A. McCullough, MD, MPH | Courageous Discourse | May 27, 2023
When the CDC ACIP Panel added the unsafe, ineffective, mRNA COVID-19 vaccines to the routine pediatric childhood schedule without full FDA licensure and with no assurances on long-term safety, the entire schedule was called into question from the perspectives of clinical indication, medical necessity, safety, and efficacy. Is it possible since the release of older vaccines that the medical community and CDC ACIP panel ignored solid data and safety concerns with established vaccines? I was participating in the Novel Coronavirus Southwestern Intergovernmental Committee deliberations in the Arizona Senate building, when a paper published over 20 years ago was presented on the diphtheria, tetanus, and pertussis vaccines. The results were astonishing.
Geier and Geier published a massive study and one of the first of its kind at the time using the CDC Vaccine Adverse Events Reporting System. The hypothesis was that febrile convulsions were more likely to occur with combined vaccine products that in some cases it would lead to death. Here is what they did: “The incidence rates calculated in this study are based on the estimates by the CDC of the number of doses administered during the study period: 121,954,137 doses of whole-cell DTP; 54,611,651 doses of acellular DTP (DTaP); and 9,335,142 doses of DT were administered. The background rate of development of convulsions by children is based on the estimates of the 1991 report by the Institute of Medicine of 0.2 per million children per day.”
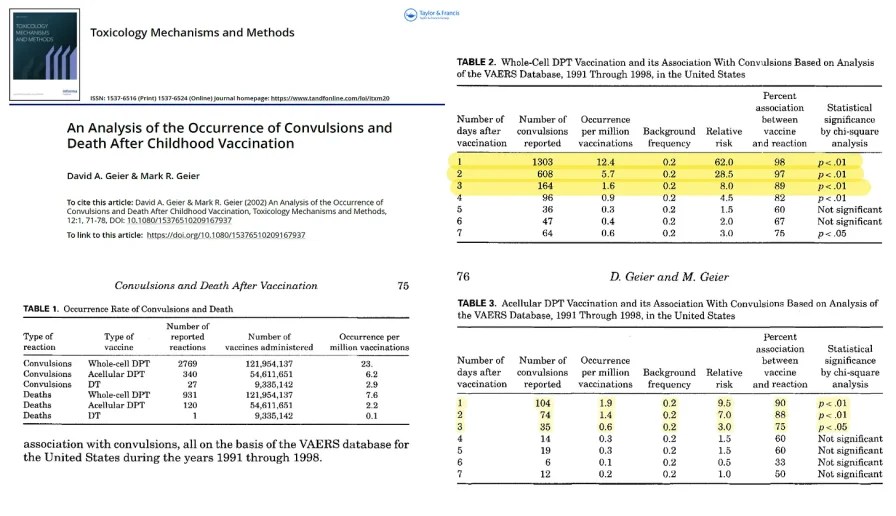
Geier DA, Geier MR. An analysis of the occurrence of convulsions and death after childhood vaccination. Toxicol Mech Methods. 2002;12(1):71-8. doi: 10.1080/15376510209167937. PMID: 20597817.
They found more cases (occurrence/million) of febrile seizures and death after whole-cell DTP, DTaP, DT alone, in a descending, nonlinear graded fashion, and the risks were in a tight temporal relationship. This is concerning because of the associations between post-vaccine febrile seizures and childhood/adult epilepsy requiring medications and with the development of neuropsychiatric conditions including autism.
In summary, no vaccine is perfectly safe. Combining multiple products into single shots increases the reactogenicity and the risk of a catastrophic outcome. As parents and doctors begin to make more discerning choices they may consider going to less complex products, spreading them out, and giving them at later ages.
Alternatively, some parents and doctors may choose for a child to “go natural” or completely unvaccinated, which has the best overall outcomes in contemporary studies at this time. Diphtheria and pertussis are easily treated with antibiotics, so prompt recognition and treatment if such a rare infection occurs is always an option for parents. Tetanus is avoided with good wound care and antibiotics for deep tissue lacerations and puncture wounds.
Her Father Got COVID and Died — But She Believes the CDC, NIH and Hospital Protocols Are What Really Killed Him

By Michael Nevradakis, Ph.D. | The Defender | May 16, 2023
Ralph Marxen Jr. had just turned 70 and was enjoying life with his wife of 49 years, Lynda, and his adult children and grandchildren. The Minnetonka, Minnesota, native was in good health and, according to his daughter, Nicole Riggs, walked long distances daily and wasn’t on any medications.
In August 2021, several members of Riggs’ household contracted COVID-19, including, presumably, her parents. A week later, while most family members were recovering, Marxen’s condition deteriorated leading him to be admitted to Abbott Northwestern Hospital in Minneapolis on Aug. 23, 2021.
Marxen would never leave the hospital — he died there on Sept. 7, 2021.
During his stay, Marxen, who had not received a COVID-19 vaccine, was administered more than 50 medications, including remdesivir, vancomycin, fentanyl and midazolam, and in the days prior to his death, he was placed on a ventilator.
At the time of his death, Marxen had “multiple organ system failure including renal failure, endocarditis, hyperkalemia, MRSA [methicillin-resistant Staphylococcus aureus] pneumonia, MRSA bacteremia and sepsis,” Riggs said.
Riggs told The Defender the treatments she and her family requested for Marxen, including ivermectin, monoclonal antibodies and vitamins, were refused.
She said she did not believe her father’s refusal of the COVID-19 vaccines played a role in his illness — in fact, she argued that her father’s non-vaccinated status — and the COVID-19 protocols prescribed by the Centers for Disease Control and Prevention (CDC) and the National Institutes of Health (NIH) — were factors in the treatment he received from the hospital and its medical staff.
‘Is this a hospital or a prison?’
“My dad went to the ER seeking help for dizziness and nausea,” Riggs said. “He was 70 years old and took no daily meds. He was unvaccinated and refused to take their unreliable PCR tests.”
In a separate interview with Minnesota’s Alpha News, Riggs said that two of her father’s friends had gotten vaccinated “and they both got vax-injured.” As a result, “He was adamant that he was not going to get the vaccine.”
“I think this played a part in him not getting good care,” Riggs told The Defender.
Riggs recounted the chain of events that led her father to end up in the hospital.
“In the middle of August 2021, my household of four, plus my parents, became ill with fever and fatigue, and a few of us had chest congestion,” Riggs said. “Myself, my husband and my two boys were spit-tested for COVID and were all told we were positive for COVID. We assumed my parents had the same.”
But after a week of being sick, she said they noticed that her father “didn’t seem to be bouncing back like the rest of us. He was having trouble walking to the bathroom because he was so weak and dehydrated.”
Due to his older age, his family “decided to call the ambulance and get him checked out,” Riggs said. Paramedics recommended Marxen go to the hospital for further evaluation, so he was admitted on Aug. 23, 2021, after an ER visit.
“From the beginning, the medical records indicate they wanted to get him on remdesivir even though they couldn’t get him to PCR test,” Riggs said.
“Within a day, a friend of the family who had been working with COVID patients for the past year told us to call the hospital and request that my dad be given monoclonal antibodies (a.k.a. Regeneron),” Riggs said. However, the nurse treating her father said he “had never heard of that before, and that was the end of that discussion.”
“That seemed strange to me, but I still trusted them at that time,” Riggs said.
The day after her father was admitted to the hospital, her mother also was admitted, after her oxygen levels dropped to the low 90s.
“My parents were soon hospital room neighbors,” Riggs said. “COVID medications were started, which we later learned was hospital protocol with remdesivir and dexamethasone.”
Despite being in neighboring rooms though, Riggs’ parents could not visit each other. “My mom wanted to go see my dad since he was in the room right next door, but she realized that her bed had an alarm that sounded when she tried to get up. She also learned that both of them were locked in their rooms as well,” Riggs said.
She added:
“My mom’s nurse thought ‘it wasn’t appropriate,’ and refused to let her go see my dad. They had to wait until that nurse was off her shift before the doctor would OK my mom to go into my dad’s room for a short visit.
“Is this a hospital or a prison?”
It wasn’t long before Riggs began to receive more disturbing updates about the treatment her parents were receiving in the hospital.
She told The Defender :
“My brother started a CaringBridge site to keep our whole family updated. It wasn’t long before I started to receive unsettling messages from people I knew and trust. One was from my dad’s old neurological chiropractor, saying ‘no remdesivir and no ventilator, that’s asking to die.’ He also sent me information on how to get a lawyer involved.
“It was then that I started to research and realize the dangers of the deadly hospital protocols put in place by the NIH and CDC, especially for those on Medicare, as the hospital is given a 20% bonus payment if certain steps are followed with those patients, starting with a positive COVID PCR test.”
According to Riggs, this was evident in her father’s medical records.
“One of the doctors actually wrote this in the medical records: ‘I don’t think it’s impossible to use remdesivir without a PCR positive,’” Riggs said, adding, “My dad initially refused a nasal PCR test because he knew they could be inaccurate and wanted to be treated by symptoms, not a PCR positive COVID test result.”
However, the hospital told Marxen and his family this was not possible. According to Riggs, the doctor said, “Certain treatments may not be available without PCR-proven COVID, and that if his condition worsened such that he required intubation, we would run the nasopharyngeal swab.”
“Basically, my dad was told he wouldn’t get access to ‘certain treatments’ until he submitted to their request to be PCR tested,” Riggs said. “And if he got bad enough, they would test him anyway.”
The hospital also told them if Marxen’s condition deteriorated enough that they needed to put him on a ventilator, they would do the test without his permission.
Her father finally “relented” and tested positive for COVID-19. That’s when the hospital administered remdesivir “and many other harmful drugs,” Riggs said, and denied their request for safer alternatives.
‘It all happened so fast’
From this point forward, “It all happened so fast,” Riggs said. Her father was transferred to progressive care on Aug. 26, 2021, and to the ICU the next day.
“My dad was denied visitation by anyone under the guise of ‘COVID isolation,’” Riggs said. “Even my mom, who was in the same hospital with COVID.”
Marxen’s condition quickly deteriorated. “My dad was told he needed to get on the ventilator so he could get relief and a feeding tube,” Riggs said. “By this time, my dad hadn’t slept in two days and hadn’t eaten in five days.”
“After two days in the ICU, he was freaking out, pulling off his mask and pulling out his IV,” Riggs said. “They got him ‘reoriented’ and brought in the doctor. If you knew my dad, you would know that this was totally out of character for him. He was the kindest, most loving man and father. He was one of my best friends.”
“Soon, he felt he had no other option but to be put on a ventilator,” Riggs said. “A decision he had to make scared and alone because we were kept from him … They had finally got him desperate enough to submit to getting on a ventilator.”
Marxen was intubated on Aug. 29, 2021, and placed on fentanyl and propofol, Riggs said, “even though, reading the records, they knew that wasn’t the solution, but they did it anyway.”
Riggs said she and her family again requested monoclonal antibodies be administered, “but were denied because it was too late in the progression of the disease to be a benefit.”
They also requested “vitamin C, vitamin D, zinc, hydroxychloroquine, ivermectin,” but were denied “and told they refused to go off of protocol, ‘because the one time we did that, the patient died,’” Riggs added.
“My dad’s medical records indicate vitamin D was ‘deemed not appropriate during this admission,’” Riggs noted. “We asked them to take him off vancomycin because that can make you retain fluid and he was already doing that. They told us no, and that the drug was ‘the gold standard.’”
‘He was kept from everyone that truly loved him’
According to Riggs, she would call the hospital every day at 6 p.m. for updates, and her brother would do so daily at 6 a.m. This continued until Sept. 7, 2021, the day her father would be placed “off quarantine” and allowed to see family members again.
However, “on Sept. 7, we were told that the ‘infectious disease team’ said he needed another seven days of quarantine,” Riggs said. “This decision was not even made by his ICU doctor.”
Instead, Riggs and her family were told “the nurses would set up a Facetime for us for the evening of Sept. 7,” Riggs said. “After that call, I was crying and pacing in my house. My thoughts were, ‘Are we going to just leave him in there to die alone?’ I needed to actually do something.”
Riggs said she decided to request her father’s medical records from the hospital, “so I could see exactly what was going on there.” However, she was told the records could not be released “unless he signed the release form” — even though her father was sedated and on a ventilator “and it wasn’t possible for him to sign anything.”
In response, the hospital told Riggs that she “would need to provide his death certificate for the records if we hadn’t already set up power of attorney.”
“So, he had to die before I could access his records?” Riggs asked. “How did this nightmare become our reality?”
Within a few hours of this exchange, Riggs received a call that her father was “actively dying” and if they wanted to see him, they needed to do it soon, because he would pass away during that night.
“Now that he was dying, we were able to come see him — but hours before we couldn’t? This made zero sense to me,” Riggs said.
On arriving at the hospital, she and other family members “were required to wear space-like soft helmets, which made it impossible to even kiss my dad goodbye.”
According to Riggs, she and her family “gave the OK to remove him from the ventilator so we could pray scripture over him through his transition.”
“I thought removing him from the ventilator would cause him to pass away because he couldn’t live without it,” Riggs said. “But I can’t help but wonder if that’s really how it went down. His records show that he was given fentanyl at 5:10 p.m. and midazolam at 5:32 p.m. He passed away at 6:22 p.m.”
Riggs said the “official” cause of death was determined to be “respiratory failure with underlying COVID-19.”
When her father died, he had multi-system organ failure. Riggs said she did not believe her father died of COVID-19, but instead due to the CDC- and NIH-approved protocols.
“He was isolated and kept from everyone that truly loved him for 16 days,” Riggs said. “Then, under the guise of ‘palliative care,’ he was finished off with fentanyl and midazolam.”
According to Alpha News, the price tag from the hospital for the treatment her father received during those 16 days was $1.2 million.
A statement provided by Abbott Northwestern to Alpha News said the following:
“Allina Health respects the privacy of its patients and is unable to comment on specific patient care.
“We have great confidence in the exceptional care our medical teams provide to our patients, which is administered according to evidence-based practices by our talented and compassionate care teams.”
‘To honor my dad, I have put my grief into action’
Riggs said her father’s death had knock-on effects on her and her family.
“Now my mom, who survived remdesivir, can’t afford to keep their home,” Riggs said. “She had to sell almost all of their possessions accumulated over 50 years to move into one of the bedrooms of my two-bedroom home. Two of my boys … now share a bedroom in our living room.”
“She can hardly make the bed without being out of breath and she struggles mentally with what they endured and getting a grasp on her new life without my dad in it,” Riggs added.
Despite these challenges, Riggs said that “to honor my dad, I have put my grief into action,” getting involved in activism for victims of hospital protocol deaths.
Riggs is now the Minnesota chair of the FormerFedsGroup Freedom Foundation, a national coalition that has documented cases involving COVID-19 care protocols at hospitals.
“I don’t want the families … to be isolated and alone in their pain of losing their loved one,” Riggs said, adding that she has launched weekly Zoom calls for Minnesota families and survivors of hospital protocols, and is also launching in-person meetups.
Riggs also recently attended the Halt Hospital Homicide rally, which she described as the “first national rally for hospital protocol deaths.”
She drew parallels with those who died of COVID-19 vaccine injuries. “The vax-injured are ignored and not believed, just like those of us who have had a family member die or get injured by the hospital protocols,” she said.
“My dad, Ralph, will go on in our memories as a wonderful husband of 50 years, dad, grandpa and great-grandpa, as well as a fun fisherman and the best homemade French fry maker around.”
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Farewell Questions for Rochelle Walensky An open letter to Congress
BY EL GATO MALO | BAD CATTITUDE | MAY 15, 2023
The history of the CDC during covid has been, at best, a checkered one.
Given what we now know about the complete failure of covid vaccines to provide sterilizing immunity, stop infection, or stop spread as well as the fact that such issues were not even tested for in the drug trials that approved them, certain questions would seem overdue in the asking:
Just what was this “Data from the CDC today” that suggested that “Vaccinated people do not carry the virus?”
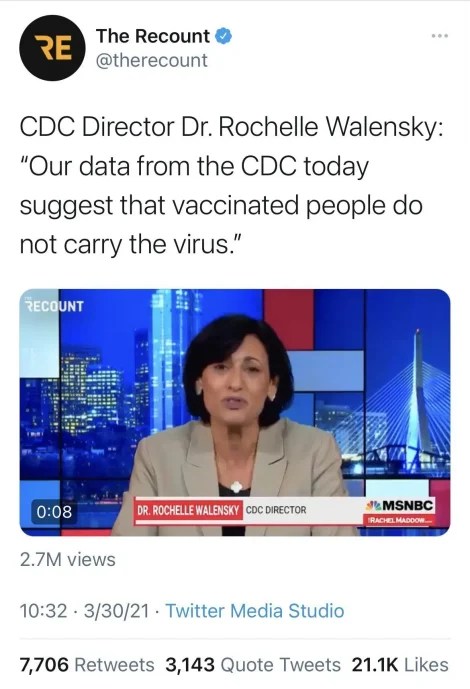
Was there, in fact, any data at all?
Or was this a completely fabricated claim used to underpin the mass rollout of a product that failed so spectacularly right out of the gates and:
- Where the sorts of safety and inefficacy signals that would have pulled any other vaccine in history off the market were ignored.
- Where the data collection was rigged to make known adverse events difficult to find, report, and aggregate in the V-safe system by removing them from searchable database fields and placing them in free text response.
- And where the mandated safety assessments were not being performed until long after problems were evident, allowing the CDC to miss the most blatant safety signal in history.
There seems to be an awfully large body of claims made by CDC that appear to have lacked foundation in fact or data. Both Dr Walensky and her predecessor Robert Redfield would seem to have a great deal to answer for here.
“The covid vaccine will make the vaccinated a dead end for the virus.”
This talking point was simply everywhere all at once.
Pfizer CEO Albert Bourla certainly pushed this narrative. Presumably, the fact that he was allowed to do so (itself quite an exceptional situation) implies the acquiescence of FDA, CDC, and other regulators.
Upon what was this seemingly widespread consensus based?
The matter appears to have never even been studied at the time the claims were made.
Why were the usually strict and fastidious US regulators so sanguine about such unusually aggressive and certain statements?
This is a most unusual situation and such an extraordinary outcome would seem to demand an extraordinary explanation.
Yet none seems forthcoming.
“The mRNA and the spike protein do not last long in the body” constitutes another key early safety claim similarly rooted in opaque or absent evidence or perhaps simply assumed or invented. (before being quietly retracted later).
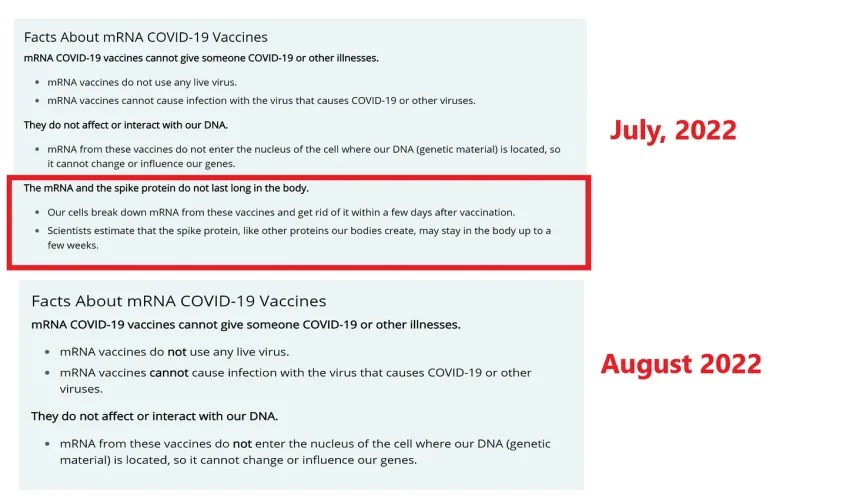
This claim also proved extravagantly incorrect.
Wherever one looks, it seems one finds that these grand claims of safety and efficacy were underpinned by a paucity or utter absence of supporting evidence.
Even the definitions themselves such as “Any positive for trace covid from a PCR test at a 40 Cycle Threshold is covid” or “No disease outcomes from vaccines are to be counted until 2 weeks after the second (or third) dose” which left a large window (4-6 weeks) during a period of known immune suppression from the jabs uncounted or even, in many cases, attributed to the unvaccinated in a manner that can make placebo look like high efficacy preventative are so unusual and inconsistent with past practice or sound science as to demand the most pointed of questions as to how such practices came to be and who the decision makers who put them in place were.
This series of unfounded claims and distortionary definitions seems both a poor and a deeply dangerous practice for Public Health.
If we are to have any hope of restoring faith in this field, we must ask and answer the pointed questions of “How did this happen?” and “At whose behest?”
Someone made these choices for some reason. Who and why would seem to be the bare minimum of post mortem here.
It is oft opined that a bad map is worse than no map at all and in this, I must wholeheartedly agree. The public health agencies in America have become the most calamitous of cartographers.
If we would seek to have the agents of public health act as something other than a marketing arm and apologist for the revolving door of Pharma with whom they seem to so regularly swap staff and sinecure then it must once more be turned to serve the public. It may do so only if it regains the public trust and such trust, once lost, may only be restored by asking the hard questions and diligently following the answers wherever so they may lead until we may understand what went wrong, hold the malefactors to account, and effect the means to prevent this from happening again.
Please make no mistake, if nothing is done and this is swept beneath some august Congressional rug or societal memory hole, it will happen again. And soon. This is not a choice I would have for America and one I do not believe you should countenance.
Public health runs on public trust.
I ask you to restore it.
One Health: A Plan to ‘Surveil and Control Every Aspect of Life on Earth’?
This is part two of a two-part series on the One Health initiative. Read part one here.
By Michael Nevradakis, Ph.D. | The Defender | May 8, 2023
The World Health Organization (WHO) defines “One Health,” as “an integrated, unifying approach that aims to sustainably balance and optimize the health of people, animals and ecosystems,” as they are “closely linked and interdependent” — a concept that on the surface appears to promote noble goals interlinking human and environmental health.
However, some scientists and medical experts are concerned about One Health’s vague goals. Arguing that the concept has been “hijacked,” they question the intent of those involved with the development and global rollout of the concept — including the WHO, the Centers for Disease Control and Prevention (CDC) and the World Bank.
Experts who spoke with The Defender also raised questions about other aspects of the One Health concept, including a biosecurity agenda, a global surveillance system, vaccine passports and restrictions on human behavior.
While these goals are underpinned by a vaguely defined “Theory of Change,” experts told The Defender that major financial interests are at the heart of the One Health agenda, which appears to be closely linked to climate change and sustainable development initiatives promoted by the same global organizations.
One Health objectives include a ‘global takeover of everything’
In a May 1 article, Dr. Joseph Mercola connected the One Health concept, as promoted by global organizations, to the policies and restrictions pursued in response to COVID-19, describing it as an attempted “global takeover of everything.”
Mercola tied the One Health concept to key entities that have supported gain-of-function research. According to Mercola:
“Interestingly, the term ‘One Health,’ which was formally adopted by the WHO and the G20 health ministers in 2017, was first coined by the executive vice president of the EcoHealth Alliance, the same firm that appears to have had a hand in the creation of SARS-CoV-2.”
During the 2019 lecture “Can One Health Help Prevent the Next Pandemic?” EcoHealth Alliance President Peter Daszak, Ph.D., commissioner in The Lancet’s One Health Commission, said “emerging infectious diseases” are “a growing global threat.”
He also argued that many of these emerging diseases are “zoonotic — spread from animals to humans.”
Francis Boyle, J.D., Ph.D., professor of international law at the University of Illinois and a bioweapons expert who drafted the Biological Weapons Anti-Terrorism Act of 1989, questioned this narrative, telling The Defender :
“All these ‘emerging infectious diseases’ are emerging out of their offensive biological warfare weapons programs conducted in their BSL4 [biosecurity level 4] and BSL3 laboratories.
“If you look at the people on the WHO advisory committee dealing with ‘emerging infectious diseases,’ that’s exactly what they are doing — ‘emerging’ them from their labs.”
One example is that of Marion Koopmans, DVM, Ph.D., director of the WHO Collaborating Centre for emerging infectious diseases at Erasmus Medical Centre in the Netherlands and member of the WHO’s One Health High-Level Expert Panel (OHHLEP).
According to Boyle, “Erasmus is where this offensive Nazi biowarfare gain-of-function death science dirty work first became notorious under Fouchier, [who] started the entire controversy over his gain-of-function work there.”
Boyle was referring to Ron Fouchier, Ph.D., who also is deputy head of Erasmus’ Viroscience Department and who, according to Science, “alarmed the world” in 2011, after he and other researchers “separately modified the deadly avian H5N1 influenza virus so that it spread between ferrets” — an early example of gain-of-function research.
Dr. Meryl Nass, an internist and biological warfare epidemiologist who is a member of the Children’s Health Defense scientific advisory committee, said such objectives are kept deliberately vague. She referred to a CDC document that stated:
“Successful public health interventions require the cooperation of human, animal, and environmental health partners … Other relevant players in a One Health approach could include law enforcement, policymakers, agriculture, communities, and even pet owners.
“By promoting collaboration across all sectors, a One Health approach can achieve the best health outcomes for people, animals, and plants in a shared environment.”
Nass wrote on her blog, “I anticipate that One Health will be used to impose changes in the way humans and animals interact … most likely based on the needs of the WEF [World Economic Forum]/elites and not the needs of the people or the animals that will be affected.”
Reggie Littlejohn, founder and president of Women’s Rights Without Frontiers and co-chair of the Stop Vaccine Passports Task Force, told The Defender, “It’s not clear that One Health is prioritizing human health.”
Highlighting the “vague” language employed by the global organizations promoting One Health, Littlejohn said that one goal may be to “govern farm animal health in addition to human health,” through which “they could do things like forcing vaccines on livestock.”
One Health means ‘surveilling everything’
The experts who spoke with The Defender expressed concerns over the biosecurity agenda that is associated with the stated objectives of One Health.
According to Nass, this reflects how the WHO “has been changing into a biosecurity agency,” adding that “the justification, apparently, for the WHO’s director-general to take over jurisdiction of healthcare during pandemics, but also potentially ecosystems, animals and plants, is through One Health.”
Nass noted that One Health “is mentioned several times in the National Defense [Authorization] Act for Fiscal Year 2023” (NDAA), which includes 18 pages on “pandemic preparedness” and a formal definition of the “One Health approach” on page 952 of the act.
Independent journalist and researcher James Roguski also highlighted the prominent placement of One Health in the NDAA and noted that, by formally defining the concept within the act, it is now part of the Code of Federal Regulations.
However, Roguski said the NDAA goes even further:
“The U.S. has pledged a billion dollars a year to the World Bank Pandemic Fund in support of the global health security agenda. The WHO is one of 14 intermediaries who will receive and redistribute some of that billion dollars.
“Basically, it’s capitalism, it’s corruption, it’s an abomination from a health perspective. Let’s just throw money at pharmaceutical companies, build out the infrastructure in these nations and, if you’re making tons of products locally, you’re going to be able to convince the local government to stick them in people’s arms or shove it down their throat.
“And none of it really has shown to be of any health benefit. It’s damage to people’s health.”
Associated with the promotion of a global biosecurity agenda is the development of a global surveillance infrastructure that would purportedly protect human and animal health and the environment. An Oct. 3, 2022, WHO document states:
“The emergence of the SARS-CoV-2 virus that caused COVID-19 has underlined the need to strengthen the One Health approach, with a greater emphasis on connections to animal health and the environment …
“… It uses the close, interdependent links among these fields to create new surveillance and disease control methods. …
“We now have an unprecedented opportunity to strengthen collaboration and policies across these many areas and reduce the risk of future pandemics and epidemics while also addressing the ongoing burden of endemic and non-communicable diseases
“Surveillance that monitors risks and helps identify patterns across these many areas is needed.”
Remarking on this, Littlejohn said One Health’s proponents talk about “interoperable, integrated surveillance systems.” She told The Defender :
“I believe … these surveillance systems of people, animals, plants, and the environment are going to be coordinated by some kind of a global surveillance system that is interoperable globally and integrated.
“Whoever’s running this show, the WHO, the Chinese Communist Party … the Bill and Melinda Gates Foundation, who are the people who really appear to be running the show at the WHO, are going to be able to tap into and see all of our private information. Not just us, but animals and plants.”
Dr. David Bell, a public health physician and biotech consultant and former director of global health technologies at Intellectual Ventures Global Good Fund, told The Defender that what global organizations intend is “surveilling everything.” He said:
“It means surveilling everything, surveilling the climate for possible threats, surveilling animal population, surveilling wildlife, surveilling the soil to see if there’s new traces of virus or bacteria in river systems, et cetera.
“This allows you to ‘discover’ what we already know is nature, and then turn nature into a potential threat or into a threat. The more surveillance you have and the wider it is, the more inevitable ‘threats’ you’ll find … because you can make an argument that almost any new variant virus is a ‘threat.’
“It will allow them to keep a constant kind of fear which then allows you to introduce authoritarian controls such as central bank digital currencies and digital passports … that allow them to monetize the human population more effectively.”
Nass noted that global actors such as the WHO “talk about sharing of specimens during a pandemic … so they can try to make vaccines too. However, they don’t talk about performing surveillance on human beings. But what they did say, which let the cat out of the bag, is that they would want to get informed consent from countries for sharing of genomic data, rather than from individuals.”
Part of this surveillance infrastructure also would include vaccine passports, which figure prominently in the pandemic treaty and amendments to the International Health Regulations (IHR) currently under negotiation at the WHO.
According to Littlejohn:
“I believe that they laid the infrastructure during the COVID-19 crisis, and we’re having a little bit of a ‘break’ here between pandemics, but that structure, that infrastructure is going to snap shut with the next pandemic if we don’t stop it. That structure has to do with vaccine passports.
“It could be called a ‘smart health card’ or ‘digital health ID,’ or even a mandatory digital driver’s license can serve as the platform for a China-style social credit system. And there’s a new bill in front of the Senate right now … the Improving Digital Identity Act of 2023 … It’s a mandatory national ID that’s going to be interoperable, coordinated, integrated and can serve as the same platform as China’s social credit system … to surveil us.”
Restrictions on human behavior could lower humans to the level of animals
The WHO’s Oct. 3, 2022, document also claimed that “Some 60% of emerging infectious diseases that are reported globally come from animals, both wild and domestic,” adding that “human activities and stressed ecosystems have created new opportunities for diseases to emerge and spread.”
Such stressors “include animal trade, agriculture, livestock farming, urbanization, extractive industries, climate change, habitat fragmentation and encroachment into wild areas,” according to the WHO.
“To the extent that carbon emissions due to transportation within cities would contribute to climate change, then the ‘15-minute city’ would be a way of addressing that,” Littlejohn said. “The danger is that they will enforce it by having surveillance cameras everywhere to make sure you don’t go outside of your district without permission.”
In a March 30 article, “Your Daughter for a Rat,” Bell cited a One Health editorial published in The Lancet stating that “all life is equal, and of equal concern.” In response, Bell suggested that One Health aims to lower humans to the level of animals.
The same Lancet article described One Health as “a call for ecological, not merely health, equity” and called for a “subtle but quite revolutionary shift of perspective” away from “anthropocentrism”: “All life is equal, and of equal concern.”
“It looks like this is going to be the justification for moving people down to the value of animals,” Nass said in response; a sentiment shared by Boyle, who said, “One Health relates the healthcare of human beings to the healthcare of animals and thus reduces healthcare for human beings to the level of healthcare for animals.”
According to Bell, “suggesting that we have a duty as a species on this planet to look after every species equally and treat them more equally [is] becoming sort of a religion or dogma. It defies what any rational society in the history of humanity” has practiced and is “a very unusual approach and potentially very scary.”
One Health: Follow the money
The WHO has attempted to give theoretical credence to the One Health concept by developing a so-called “Theory of Change” (ToC).
Although the WHO says the ToC is designed to provide “a conceptual framework” for “organisations, agencies and initiatives working towards similar One Health goals” and a “common narrative of coherence,” the theory itself does not appear to have a clear definition.
“They want to be able to do whatever they want,” Littlejohn said. “If you define it, then you can hold them to the definition … one of the tactics is just to be really obscure and incomprehensible.”
“This is a term that is used in these circles,” Bell added. “It’s stating the obvious, that if you do a certain act, you’ll have a certain outcome. It’s a fancy way of saying that.”
Bell also referred to the “fallacy that is being pushed that humans are having increasing contact with wildlife,” supposedly leading to “this threat of viruses jumping from wildlife to humans.”
Calling it a “ludicrous claim,” Bell said that “when humans move into wildlife habitats, the wildlife don’t start living with humans. They die out.”
Noting that “it used to be very common” for people to live with farm animals, Bell added that the claim that pandemics are becoming more common due to increased contact with animals is itself “not true,” but is “used to instill fear and to try to get people to buy into this One Health, constant health emergency agenda.”
Nass said One Health proponents “don’t actually have any evidence” to support their claims, offering the example of antimicrobial resistance in bacteria found in meat consumed by humans, as a result of antibiotics administered to livestock. “That’s been the hook that One Health has been hung on,” Nass said.
However, Nass said this problem “could be solved in a heartbeat if the U.S. Food and Drug Administration or the U.S. Department of Agriculture just told farmers they can’t put antibiotics into animal feed anymore, they can only use them when an animal gets sick.”
In his recent article, Mercola suggested following the money. “Private interests wield immense power over the WHO, and a majority of the funding is ‘specified,’ meaning it’s earmarked for particular programs. The WHO cannot allocate those funds wherever they’re needed most.”
As a result, this “massively influences what the WHO does and how it does it. So, the WHO is an organization that does whatever its funders tell it to do,” naming organizations such as the Gates Foundation as prime funders of the WHO.
Bell said that supporters of One Health include “those who have been pushing the COVID agenda … and enriching themselves from it,” including “private foundations who are on the bandwagon” and “corporations who stand to gain from controlling the food chain and controlling agriculture and pharmaceuticals, et cetera.”
“It’s corporate authoritarians that have benefited themselves from public health through COVID and the certainly inappropriate COVID response,” Bell added. “And it’s the same and it’s not disconnected with the climate emergency agenda.”
One prominent financial actor closely involved with the development of the One Health agenda is the World Bank, as WHO documents indicate.
At a November 2022 OHHLEP meeting, Franck Berthe, the World Bank’s senior livestock specialist, introduced the World Bank’s Financial Intermediary Fund, which would “allow countries to borrow funds to strengthen their health system and promote the OH [One Health] approach.”
According to Nass, “the WHO and the World Bank have helped form this financing operation for the biosecurity agenda,” while Boyle told The Defender, “There is nothing humanitarian about these backers and the WHO promoting the One Health agenda.”
Both Nass and Bell said the One Health agenda is closely tied to the UN’s Sustainable Development Goals and Agenda 2030. Bell said that the One Health agenda attempts to deal with a supposed “existential threat to human health” that “must be dealt with in a centralized way, rather than giving people a choice.”
One Health closely tied to WHO pandemic treaty, IHR amendments
Experts who spoke with The Defender also emphasized the connections between the One Health concept and the pandemic treaty and IHR amendments under negotiation.
Mercola wrote that through the One Health agenda, which recognizes “a very broad range of aspects of life and the environment [that] can impact health and therefore fall under the ‘potential’ to cause harm,” the WHO “will be able to declare climate change as a health emergency and subsequently require climate lockdowns.”
Roguski, who has extensively researched the pandemic treaty and IHR amendments, said that in amendments the EU recently proposed for the pandemic treaty, the term “One Health” appears 29 times, including calling upon countries to develop and regularly update pandemic prevention plans via the One Health approach.
Referring to the need to prevent potential “pandemic situations,” the proposals also call for strengthening global public health surveillance “using a One Health approach,” which will also “address the drivers of the emergence and re-emergence of disease at the human-animal-environment interface, including but not limited to climate change, land use change, wildlife trade, desertification and antimicrobial resistance.”
The proposals also suggest the One Health approach could be used “to produce science-based evidence, and support, facilitate and/or oversee the correct, evidence-based and risk-informed implementation of infection prevention and control,” and go as far as to suggest targets on “antimicrobial consumption/use.”
Roguski told The Defender that the latest draft of the pandemic treaty refers to One Health 13 times. Such language would “be used to take over complete control of our lives,” Roguski added.
For example, one proposal states, “Each Party shall, in accordance with national law, adopt policies and strategies, supported by implementation plans, across the public and private sectors and relevant agencies, consistent with relevant tools, including, but not limited to, the International Health Regulations, and strengthen and reinforce public health functions for: (c) surveillance (including using a One Health approach).”
Other proposals include:
“The Parties commit to strengthen multi-sectoral, coordinated, interoperable and integrated One Health surveillance systems … to identify and assess the risks and emergence of pathogens and variants with pandemic potential, in order to minimize spill-over events, mutations and the risks associated with zoonotic neglected tropical and vector-borne diseases, with a view to preventing small-scale outbreaks in wildlife or domesticated animals from becoming a pandemic.
“Each Party shall … develop and implement a national One Health action plan on antimicrobial resistance that strengthens antimicrobial stewardship in the human and animal sectors, optimizes antimicrobial consumption, increases investment in, and promotes equitable and affordable access to, new medicines, diagnostic tools, vaccines and other interventions, strengthens infection prevention and control in health care settings and sanitation and biosecurity in livestock farms, and provides technical support to developing countries.”
Roguski said the phrase “One Health” doesn’t directly appear in documents related to the proposed IHR amendments, but he added the WHO “is going to try to get them both to prevail,” referring to both the treaty and IHR amendments.
Littlejohn said, the One Health approach and the proposed language in the treaty “gives them the right to surveil and potentially control every aspect of life on earth.”
Noting that the proposed treaty also calls for a “commitment to counteract ‘misinformation,’ ‘disinformation,’ and ‘false news,’” Littlejohn added, “they’re going to surveil our social media … and if any of us steps out of line by contradicting what the WHO says, then we could be censored.”
“That’s what I think is in mind with this commitment to ‘coordinated, interoperable and integrated’ One Health surveillance systems,” Littlejohn added. “I think that’s how it could end up being deployed. Ultimately, globalist entities, such as the World Economic Forum and the UN are using the WHO as their way of establishing global control.”
“The reason that health is such a good pretext is that people can become terrified,” Littlejohn added. “To the extent that their minds are paralyzed if they think they could die or get really sick, they’re willing to give up freedoms that they would not be willing to give up in other contexts.”
Roguski told The Defender :
“They made a lot of bad decisions. They gave a lot of bad advice [and] they caused a lot of harm to a lot of people. You can’t just give those people more power, authority and control without looking at what they did and going, ‘no, you should not be in charge of any of this.’”
In turn, Mercola wrote that “The globalist takeover hinges on the successful creation of a feedback loop of surveillance for virus variants, declaration of potential risk followed by lockdowns and restrictions, followed by mass vaccinating populations to ‘end’ the pandemic restrictions, followed by more surveillance and so on.”
And according to Bell, One Health “is part of a much bigger picture of finding ways to pull apart the intrinsic ideas that most societies have been built on.”
“I think that this is part of a move to undo these sorts of ideas and to replace them with a sort of religion of fear of our surroundings and denigration of other humans that can then be used by very greedy people to increase their wealth and power,” Bell said. “It’s taken over public health to a large extent.”
Michael Nevradakis, Ph.D., based in Athens, Greece, is a senior reporter for The Defender and part of the rotation of hosts for CHD.TV’s “Good Morning CHD.”
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
When the trading gets rough, the pros go insider
The farm to table vertical integration of the gates foundation investing racket
by el gato malo – bad cattitude – may 6, 2023
in the aftermath of great events, “who knew what and when did they know it?” is always an interesting question.
the US intelligence community (michael spenger substack ) was suspected to have caught wind of covid back in november 2019.

astonishingly, the IC itself denies this and claims they were in the dark until later
Every official interviewed by the Committee—from working level analysts at NCMI to an official with relevant knowledge at the NSC—said that their first indication of a novel virus came with the publication of the ProMED notice published at 11:59 p.m. on December 30, 2019 that reported the announcement of a novel virus by the Wuhan Municipal Health Committee.
In sum, the first warnings of COVID-19 came from the non-IC based public health track—in this case disease surveillance conducted by local public health authorities in Wuhan.
but this invites some pretty pointy questions about their competence, no?
because it sure looks like pretty much everyone on the super special inside track of business and finance CLEARLY knew by then.
bill gates knew. the WEF and team davos knew. and they were making big plays to make big money months before the intelligence community is even claimed, much less claims to have known what was going on.
it does make one wonder…

bill gates bought $55 million (with an option for $100mm) of bioNtech stock in september of 2019 right before they suddenly had the intellectual property for the most profitable vaccine in history.
they were not working on vaccines previously.
i wonder where they got the tech?
no one seems to know.
but it sure looks like billy g knew.
so, here’s a fun little nugget from the bill and melinda gates foundation investment into bioNtech, from whom pfizer licensed the IP for the covid vaccine.
pretty prescient for september 2019.

source
does this seem like “boilerplate?”
because it seems oddly specific (but deniable) as a “partnership” on something unrelated that could suddenly be “covid.”
and the timing is awfully provocative especially in light of some other events.
he did well getting out as well.
gates sold in 2021, banking $260 million, pretty much right at the top and has since changed his tune on mRNA vaccines, but this is hardly uncommon for “investors talking their book.”
the rest of this fact pattern looks a bit nastier though, more like the 3.0 sand hill road model of “buy up companies in a space and then mandate the adoption of their products.”
this has been the great game out there since even before kleiner perkins hired al gore to shill and lobby for their greentech portfolio. they are currently playing a similar (and more subtle) game playing hungry hungry hippos with HVAC companies and then pushing through new “air handling mandates” for new buildings, schools, offices, etc. cuz “public health.”
but the gates foundation makes them look like pikers.
if you’re going to make a big push into selling vaccines and drugs, why buy mere lobbyists when you can buy the WHO? gates is by far their largest private donor, 25X the size of the next biggest and was their number 2 donor overall.

$531 million buys A LOT of access and control. it’s perfect. the WHO is not only on the ground all over, but they also give advice and set policy/terms for assistance. so gates gets all the info instantly about what’s happening in diseases and then gets to tell the WHO what to tell everyone to do about it. play the hero and add a zero (to your bank balances).
it’s a truly great grift and few dare call it out as the nasty, hard-knuckle lobbying and advocacy it is because it looks like philanthropy.
weaponized philanthropy to be sure, but “philanthropy” and tax free to boot.
not only did bill get early word on wuhan and reach out and place big money on the one subtle square that was going to pay out huge by suddenly having the answer to the most asked question on earth and coming out of obscure nowhere to partner with pharma titan pfizer, but he went a full step further and actually held a pandemic war game under the auspices of john’s hopkins that gathered top policy makers and thought leaders to assess a global outbreak of an “imaginary” disease that happened to look exactly like SARS-cov2. this was the now infamous “event 201.”
and look who threw the party: the WEF and the gates foundation.
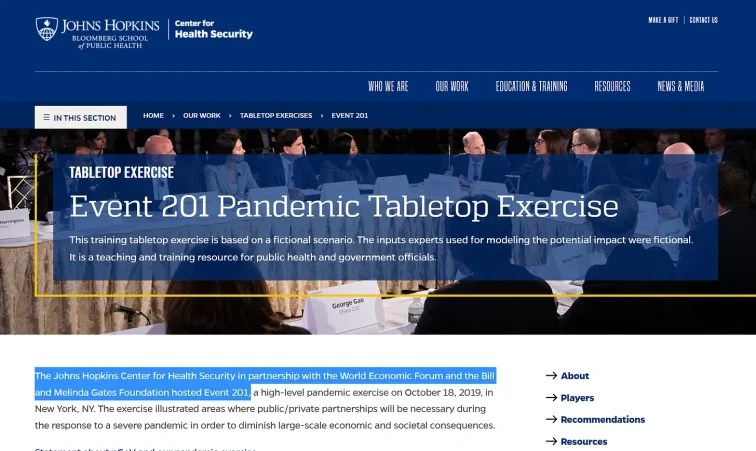
it’s obvious that they knew exactly what was coming. this was the overt planning plenary for covid. it was not pretend. and many/most those attending must have known that. this is the same time gates was buying bioNtech.
the bioNtech investment was 9/4/19. event 201 was 10/18, five weeks later.
who knows how much earlier the due diligence and planning must have begun, especially for the investment.
there’s getting lucky, and there’s putting the fix in because you know what others do not.
tell me that this “imaginary scenario” 2-3 months before the whole world knew what was happening was just a lucky guess.
the “players” were a high powered gang including big business, healthcare companies, the UN, the head of china’s CDC, a number of academics, the head of US CDC preparedness and response, monetary authorities, and media firms.
Featured Video

Iran & Its Allies Are Threatening Every Route for Saudi Oil
or go to
Aletho News Archives – Video-Images
From the Archives
A short history of British torture
ICC | December 2005
When the House of Commons was debating how much to increase the time limit for detention without trial the question of torture came up. Officially this was limited to the nice considerations of whether it was all right to send people to places where torture is used and whether Britain can use information collected by the use of torture in other countries. This discussion gave an impression of democratic Britain as the home of civilised behaviour where the very idea of torture is repugnant to our legislators – unlike, say, the US with its secret CIA jails… In reality, the British state has a long history of using and developing a whole range of torture techniques. … continue
Blog Roll
 Aletho News
- US destroying international space law
- SCO Calls for Binding Global Deal to Prevent Arms Race in Space
- Iran & Its Allies Are Threatening Every Route for Saudi Oil
- ‘40,000 tons of bombs’: Report shows Trump planning ‘largest bomb transfer in modern US history’ to Israel
- Amazon says cloud infrastructure in Bahrain, UAE ‘beyond saving’
- How Europe became an accessory to CIA torture
- Trump says Iran urgently seeks deal, Tehran sets conditions for talks
- The Andean Shadow Army
- Russia Wants to End Ukraine Conflict – Lavrov
- US Flaunts On-Orbit Weapon to Supercharge Space Arms Race
- If Americans Knew
- Sanctions Target Iran’s Government, But Kill Hospitalized 23-Year-Old Woman
- An alternative view on the book “Israel’s Lobby: America in the Grip of a Foreign Power”
- Ed Sheeran’s band Beoga, other opening acts quit tour after Macklemore was dropped over his pro-Palestinian comments
- The assassination attempt on President Trump in Butler and the various Israeli connections to it
- “We Want That the Whole Land Be Jewish”
- BREAKING: Building collapse in Gaza kills at least 20 as they sleep – Daily Update
- ‘School is Life’: 1.5 Million Palestinian Children Face Fourth Year of Shattered Education
- Pentagon admits Iran war caused ammunition shortages, cost US $33.4bn
- 37 Palestinian journalists held in Israeli jails, rights group says
- Israel’s Hilltop Youth Recruits Minors to Terrorize Palestinians (with video)
- No Tricks Zone
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
- End-Of-August Arctic Sea Ice Extent Hasn’t Fallen In 20 Years, Official Data Show!
- News-Making Nepal Region Has Had As-Warm Or Warmer Periods Than The 2000s In The 1600s, 1700s, 1800s
 Aletho News
