Pfizer drip feeds data from its pregnancy trial of covid-19 vaccine
Analysis of the data so far shows the trial was underpowered, poorly designed and incomplete
BY MARYANNE DEMASI, PHD | AUGUST 24, 2023
In January 2021, in the absence of any human data in pregnancy, the CDC stated on its website that mRNA vaccines were “unlikely to pose a specific risk for people who are pregnant.”
Former CDC director Rochelle Walensky backed it up with a full-throated endorsement of covid-19 vaccination in pregnancy.
“There is no bad time to get vaccinated,” said Walensky.
“Get vaccinated while you’re thinking about having a baby, while you’re pregnant with your baby or after you’ve delivered your baby,” she added.
Behind the scenes however, Pfizer was scrambling to conduct a clinical trial of its vaccine in pregnant women.
By February 2022, Pfizer revealed it still did “not yet have a complete data set.” Its statement read:
“The environment changed during 2021 and by September 2021, COVID-19 vaccines were recommended by applicable recommending bodies (e.g., ACIP in the U.S.) for pregnant women in all participating/planned countries, and as a result the enrollment rate declined significantly.”
This month, Pfizer finally posted some trial results on clinicaltrials.gov.
The data do not appear in a peer-reviewed journal or a pre-print, nor has it been submitted to the FDA for evaluation.
I spoke with experts who have analysed the data with a fine-tooth comb and made some alarming observations.
Pfizer originally planned to recruit 4000 healthy women aged 18 or older who were 24 to 34 weeks pregnant. Half would be randomised to the vaccine and the other half to a saline placebo.
The efficacy and safety of the vaccine would be determined by assessing covid-19 cases, antibody responses, and adverse events.
Peculiarly, Pfizer planned to vaccinate all the mothers in the placebo group, one month after giving birth to their babies.
Retsef Levi, a professor at the Massachusetts Institute of Technology Sloan School of Management said that vaccinating mothers in the placebo group during the assessment period would introduce a new variable into the experiment and “corrupt” the data.
“We now know that mRNA from the vaccine is detected in the breast milk, so those babies born from mothers who were all vaccinated after giving birth, are also potentially exposed to mRNA through breastfeeding,” explained Levi.
“This corrupts the comparison of the two groups of babies because you don’t have a true control group anymore,” he added.
Less than 10% of the originally planned 4000 study participants ended up in the trial.
“Only 348 women were recruited – 174 in each arm – meaning that the trial was never going to have the statistical power, particularly when analysing potential harms,” said Levi.
Notably, study protocols indicate that Pfizer was given the green light as early as May 2021 by drug regulators to scale back the trial and reduce the sample size.

“To me, the wording in the protocol suggests that the FDA or another regulator basically gave Pfizer permission to do less,” remarked Levi.
“It’s not surprising though. The vaccine had already been recommended for pregnant women and many have taken it, so there is no upside to completing a trial that may detect signals of potential harms. It can only create problems for them, right?” he added.
Given that pregnant women were being vaccinated with a product that had not undergone rigorous safety testing in pregnancy, the FDA was asked if and why it allowed Pfizer to scale back the trial.
The FDA replied, “As a general matter, FDA does not comment on interactions it may or may not be having with sponsors about their clinical trials.”
Angela Spelsberg, an epidemiologist and medical director at the Comprehensive Cancer Center Aachen in Germany agreed that the integrity of the study had been compromised.
“There are just not enough babies in this trial to detect rare or very rare adverse events. We learned from studies in animals that lipid nanoparticles in the vaccine can deposit in many organs including the ovaries, so we must be extremely cautious about the potential negative impacts of the vaccine on reproductive health,” said Spelsberg.
“The scientific community urgently needs access to the pregnancy study data on the patient level for transparency and independent scrutiny of vaccine safety and efficacy because regulatory oversight is failing,” she added.
The small sample size may have been the result of the strict selection process.
Pfizer recruited participants with an impeccable pregnancy history, and most were in their third trimester (27-34 weeks gestation), a stage when the baby’s major development has already occurred.
“It appears that they cherry picked the mothers to get the best results,” said Levi. “We have no idea what impact this vaccine has on the early stages of development of an embryo or foetus, because all the women had advanced pregnancies when they were recruited.”
Spelsberg agreed.
“The first trimester is particularly vulnerable to adverse reproductive health outcomes,” she said.
“Based on only weak observational evidence, regulators have reassured the public that the vaccines are safe throughout pregnancy. However, we don’t have reliable evidence on the vaccine’s impact on miscarriages, malformation, foetal deaths, and maternal health risks because they excluded pregnant women from pivotal trials,” added Spelsberg.
Levi also noticed that “only partial data” were published.
“It doesn’t include any important metrics such as covid infections or antibody levels and its says we must wait until July 2024 for those results. It’s disturbing to say the least,” said Levi.
Also missing from the dataset was a full account of birth outcomes. Of the 348 women in the trial, Pfizer only reported on the birth of 335 live babies.
Of the 13 pregnancies unaccounted for, Pfizer reported one foetal death (stillbirth) in the vaccine group and the outcome of the other 12 pregnancies remains unknown.
“This is unacceptable,” said Levi. “Failing to report the outcome of 12 pregnancies could mask a potentially concerning signal of the vaccine in pregnancy. What happened to the babies, did they all die? Were their mothers vaccinated or unvaccinated?”
Finally, there were quite a few babies that were lost to follow-up in the trial.
“Twenty-nine babies in the placebo arm didn’t get to the end of the 6-month surveillance period, versus 15 babies in the vaccine arm. That’s almost double. Again, this is concerning and requires a detailed and transparent explanation,” said Levi.
Overall, both Levi and Spelsberg say the delays and failure to disclose vital data are unacceptable.
“Pfizer took a year to publish the data. When they finally did, it is incomplete. And we are expected to wait until July 2024 for the next batch of results, while authorities continue to recommend the vaccine in pregnant women,” said Levi.
“We still don’t have solid scientific evidence whether this vaccine is safe for pregnant women and their babies,” said Spelsberg. “It’s a tragedy and a scandal that vaccine use has been recommended, even mandated to women before, during and after pregnancy.”
Questions were put to Pfizer, but the company did not respond by the deadline.
Moderna is also conducting a clinical trial of its mRNA vaccine in pregnancy, but no data are available.
CDC Now Refusing New COVID Vaccine Adverse Event Reports in Its V-Safe Program
By David Gortler | Brownstone Institute | August 24, 2023
The Centers for Disease Control and Prevention (CDC) V-safe website quietly stopped collecting adverse event reports with no reason or explanation. The V-safe website simply states: “Thank you for your participation. Data collection for COVID-19 vaccines concluded on June 30, 2023.” If you go there today, V-safe directs users to the FDA’s VAERS website for adverse event reporting, even though officials continually derided VAERS as “passive” and “unverified.”

VAERS and V-safe are mutually exclusive safety collection databases operated by the FDA and CDC, respectively. VAERS is an older way of collecting safety data where one can fill out a form online, or manually, or by calling a toll-free number, whereas V-safe is a device “app” which requires online registration. Both VAERS and V-safe collect personal information, lot numbers, dates and associated information, but V-safe was an active collection system geared towards a younger app-using demographic.
Does this mean that the CDC believes that the mRNA Covid-19 injections are so safe, there is no need to monitor adverse event reports any longer? What is the argument against continued monitoring, especially since the V-safe website was already up and paid for?
While CDC’s V-safe was stealthily and abruptly turned off, refusing to accept new safety reports, to this very day the CDC continues to urge everyone ages 6 months and older to stay up to date with COVID-19 vaccines and boosters.
As a drug safety expert, I personally can’t cite another example of any agency or manufacturer halting collection of safety data. It seems even worse because mRNA technology is relatively new with long-term manifestations unknown. On top of this, both manufacturers and the FDA refuse to share the list of ingredients, such as lipid nanoparticles, which could affect individuals differently and take a long time to manifest clinically.
Safety Data Collection Should Never Stop:
Now, contrast that with the fact that the National Highway Traffic and Safety Administration (NHTSA) will still accept a safety report for a 30-year-old Ford Bronco II. Indeed, this is an oddly specific example, but only because I drove this exact vehicle as a family hand-me-down as a student, through my residency, fellowship, for my tenure as a Yale professor on the mean streets of New Haven and even during my years at the FDA as a medical officer /senior medical analyst.
Like mRNA shots, Bronco IIs are still available on the market and people are still using them up to this very day. My Bronco became an intermittent topic of conversation with friends and FDA colleagues. One day, I was informed by a patrolling security guard at the FDA that it was the oldest car on campus.
I didn’t know much about cars (or mRNA technology) back then, but when a fellow FDA-er informed me that my Bronco II had noteworthy safety problems and that the NHTSA still had their eye on this vehicle (rollover accidents were more common and more fatal) I addressed the problem: I got rid of the reliable relic, even though I really liked it. NHTSA Is still accepting safety reports three decades later.
CDC No longer accepting safety reports despite rapidly increasing safety findings:
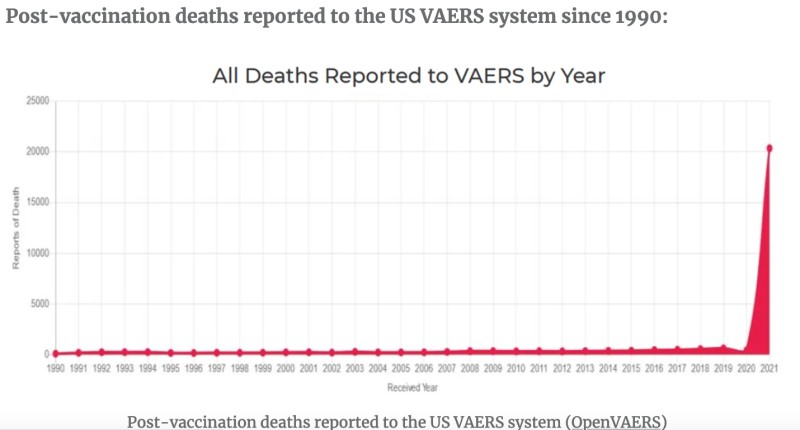
Unlike my old Bronco, mRNA injections have only been on the market for about two years, and according to the FDA Vaccine Adverse Event Reporting System (VAERS) database, mRNA “vaccines” have been named the primary suspect in over 1.5 million adverse event reports, of which there are >20,000 heart attacks and >27,000 cases of myocarditis and pericarditis just in the USA alone. Worldwide numbers would be greater. According to many references, including an FDA-funded study out of Harvard, VAERS reports represent fewer than 1 percent of vaccine adverse events that actually occur.
Interestingly, the NHTSA link above on my Ford Bronco II only shows: one parts recall, one investigation and 23 complaints, and still features a button in the upper right hand corner for submitting new complaints.
Wikipedia defines an humanitarian crisis or humanitarian disaster as a: “singular event or a series of events that are threatening in terms of health, safety or well-being of a community or large group of people.” Based on VAERS and previous V-safe findings, adverse events from mRNA shots in the USA alone could be considered a humanitarian crisis.
Despite those alarming clinical findings, the CDC has concluded that collecting new safety reports is somehow no longer in the interest of America’s public health. Existing data from the V-safe site showed around 6.5 million adverse events/health impacts out of 10.1 million users, with around 2 million of those people unable to conduct normal activities of daily living or needing medical care, according to a third-party rendering of its findings. In other words, despite mRNA shots still being widely available and the CDC promoting its continued use, it’s “case closed” with regards to collecting new safety reports, under today’s federal public health administration.
Will the CDC opine on the existing data or justify its halting of collecting new safety data? To the best of my knowledge, stopping the collection of public health information doesn’t have a clinical justification or scientific precedence — especially when it comes to an actively marketed product.
In George Orwell’s 1984, characters were told by The Party to “reject the evidence of your eyes and [your] ears.” Now, the CDC isn’t even allowing that evidence to be collected for viewing (and prospective rejecting). It’s a terrible idea for any product, let alone novel mRNA technologies.
Dr. David Gortler, a 2023 Brownstone Fellow, is a pharmacologist, pharmacist, research scientist and a former member of the FDA Senior Executive Leadership Team who served as senior advisor to the FDA Commissioner on matters of: FDA regulatory affairs, drug safety and FDA science policy. He is a former Yale University and Georgetown University didactic professor of pharmacology and biotechnology, with over a decade of academic pedagogy and bench research, as part of his nearly two decades of experience in drug development. He also serves as a scholar at the Ethics and Public Policy Center.
Passing the Talmud Torch: New CDC Director
By Karl Haemers | Taboo Truth | August 21, 2023
The previous Director of the Centers for Disease Control and Prevention, Rochelle Walensky, submitted a letter of resignation to the Biden administration on May 5. On June 16, the Biden White House announced its “Intent to Appoint Dr. Mandy Cohen as Director of the Centers for Disease Control and Prevention.” Walensky’s term officially ended on June 30. At this moment of writing, the date is August 20. Mandy Cohen has been the official Director of the CDC for seven weeks.

Out With the Old Boss
Walensky’s term from January 2021 to the end of June 2023 was a period of devastating ineptitude combined with profiteering and reckless power projection by herself and the agency she led. This was the period of the vaccine roll-out, and Walensky pushed vaccines as the only treatment for an over-hyped threat of a SARS-CoV-2 virus. AP said Walensky “was brought in to raise morale at the CDC, to rebuild public trust in the agency and to improve its sometimes-bumbling response to the pandemic.”
Instead Walensky claimed vaccination was necessary for everyone to prevent the spread, then later after the virus panic was diminished, the CDC declared that the vaccines never had the ability to prevent spread, only reduce symptoms. Walensky declared that it was “urgent” for pregnant “persons” (she would not say “mothers” or “women”) to get the vaccine to protect their babies and themselves. A careful reading of the CDC study Walensky referenced as a source for her recommendation stated no such thing, but declared that some safety concerns had arisen for pregnant “people” including over 20% pre-birth death of the fetus. Especially in the first and second trimester, insufficient data was available to make any recommendation. More data was needed. Walensky urged pregnant “persons” to get vaccinated anyway, making the nation’s pregnant mothers test subjects in the vaccine trial.
It was Walensky who spouted the slogan “a pandemic of the unvaccinated,” to describe her claim that hospital beds were filled overwhelmingly with unvaccinated people, and that the great percentage of deaths were among the unvaccinated. See the official Press Briefing by White House COVID-19 Response Team and Public Health Officials, timestamp 37:00. “There is a clear message that is coming through: This is a pandemic of the unvaccinated.”
The CDC’s own study showed the exact opposite, with 74% of cases in the fully vaccinated. Studies out of Israel, one of the most heavily vaccinated nations in the world at the time, also showed the great majority of people allegedly sick and dead from covid were vaccinated. Walensky was also a strong promoter of mask-wearing, even for vaccinated children attending school, when data showed children were at almost no low risk of death from the dreaded covid disease.
In a move of chutzpah, Walensky announced in August 2022 that she would “shake up” the CDC with extensive changes referred to as a “reset,” because the $12 billion agency “needs to become more nimble.” Walensky said it was her “responsibility to lead this agency to a better place.”
‘It’s not lost on me that we fell short in many ways’ responding to the coronavirus, Walensky said. ‘We had some pretty public mistakes…’
Some had hope at the time Walensky would acknowledge the CDC’s large over-reach and over-reaction to an over-hyped pandemic, doing more public health harm than good with its extreme lockdown measures — but that was false hope. Instead Walensky implemented “Increasing use of preprint scientific reports to get out actionable data, instead of waiting for research to go through peer review and publication by the CDC journal Morbidity and Mortality Weekly Report.” Walensky said she would “get rid of some of the reporting layers that exist, and I’d like to work to break down some of the silos.” Both of these measures sound like lowering the scientific standards upon which the CDC reacts, not raising them. “Altering the agency’s organization chart to undo some changes made during the Trump administration,” and establishing a new “health equity” department hardly sound like improvements either.
One critic of Walensky’s “reset,” James Lyons-Weiler, Ph.D., “research scientist and author, said the changes are just an escalation of the deeper problem of governmental agencies colluding with pharmaceutical companies to lower scientific testing standards.”
Robert F Kennedy Jr.’s Children’s Health Defense called Walensky’s time as Director of the CDC a “contentious reign” in its “CDC Director Walensky Resigns, Ending Contentious Reign Over COVID Vaccine Policies.” This provides an accurate summary of the damage Walensky’s covid policies inflicted on American school children, businesses, families and lives.
Under Walensky, the CDC also gave false information on vaccine safety monitoring, added the COVID-19 vaccines to the childhood vaccine schedule despite known harms, withheld data on boosters from the agency’s own advisers and told pregnant women the vaccine was safe — just days after Pfizer reportedly finalized a report demonstrating it wasn’t, among other things that have outraged critics.
In her letter of resignation, Walensky said “I have never been prouder of anything I have done in my professional career.”
The White House issued its brief “Statement from President Biden on Dr. Rochelle Walensky” on the same day it received Walensky’s resignation letter, which must be seen to be believed.
“Dr. Walensky has saved lives with her steadfast and unwavering focus on the health of every American. As Director of the CDC, she led a complex organization on the frontlines (sic) of a once-in-a-generation pandemic with honesty and integrity. She marshalled (sic) our finest scientists and public health experts to turn the tide on the urgent crises we’ve faced.
“Dr. Walensky leaves CDC a stronger institution, better positioned to confront health threats and protect Americans. We have all benefited from her service and dedication to public health, and I wish her the best in her next chapter.”
Walensky’s next chapter should be spent in prison for betraying the trust of the American people. She gave no clear reason for her resignation, except to note the “waning of the covid-19 pandemic” and “the nation is at a moment of transition as emergency declarations come to an end.” On the same day of Walensky’s announced resignation, May 5, the WHO officially ended the covid “global emergency.” The U.S. ended its covid “public health emergency” on May 11.
Two days after the director transfer, on July 2, Walensky had the further chutzpah to give an interview with the Wall Street Journal, “Departing CDC Director Rochelle Walensky Warns of Politicized Science,” in which “she says public needs to be wary of misinformation.” Once again Children’s Health Defense details why this is another act of astounding hypocrisy showing how Walensky’s CDC itself highly politicized the “science” and spread dangerous misinformation.
Rochelle Walensky is Jewish, as chronicled in an essay on substack Taboo Truth. It examines previous Jewish CDC Directors Jeffrey Koplan, Tom Frieden and Anne Schuchat and their various scandals, and other Jews within the agency’s historic infrastructure, including massive funding lobbied by Jewish Home Depot owner Bernard Marcus which expanded the CDC to the bureaucratic leviathan it is today.

Our new director of the CDC is also Jewish. Her name is Mandy Cohen, and in its June 16 “Intent to Appoint Dr. Mandy Cohen as Director of the Centers for Disease Control and Prevention,” the Biden White House presents her credentials (most recent listed first).
- Secretary of North Carolina’s Department of Health and Human Services
- transformation of North Carolina’s Medicaid program and Medicaid expansion.
- Chief Operating Officer and Chief of Staff of the Centers for Medicare and Medicaid Services
- Acting-Director of the Center for Consumer Information and Insurance Oversight
- Affordable Care Act policy development and implementation
- medical degree from Yale School of Medicine and a Master’s (sic) in Public Health from the Harvard School of Public Health
Walensky was also a graduate of Harvard School of Public Health. Just as Walensky, Jewish Mandy Cohen is married to a Jewish man, Samuel Cohen, a health care regulatory attorney. He is:
“Managing Director of Health Policy at Curi Advisory, which is a full-service advisory firm that serves physicians and medical practices. Equal parts fierce physician advocates, smart business leaders, and thoughtful partners, Curi’s advisory, capital, and insurance offerings deliver valued advice…”
Mandy’s maiden name is Krauthamer, spelled differently and not likely a relation except by tribe to the Jewish Neo-Con war-monger journalist Charles Krauthammer. Mandy’s Jewish mother Susan was a nurse practitioner in an emergency room on Long Island, who inspired Mandy onto a public health path. Her Jewish father was a high school guidance counselor.
An extensive and detailed profile of Mandy Cohen emerged in the first year of the covid pandemic when she was Secretary of the North Carolina Department of Health and Human Services (NCDHHS). Titled “She’s the face of NC’s fight against COVID-19. Meet Dr. Mandy Cohen, Tar Heel of the Year,” it announces “Cohen is The News & Observer’s 2020 Tar Heel of the Year, an honor that recognizes a North Carolina resident who has made lasting and significant contributions in the state and beyond.” This humanizing puff piece states, “Cohen has become the figurative and literal face of North Carolina’s ongoing fight against COVID-19.”
“It is a fight in which she’s relied most upon data and science and something less easily quantified: the sense of empathy and compassion that some closest to her say make her a perfect fit for her position. It is a fight that’s challenged her to balance competing interests — one that at times has brought fierce criticism from skeptics who dismiss science or downplay the virus — while maintaining the goal of preserving the health and lives of North Carolinians.”
According to North Carolina Dept. of Health and Human Services, using my own simple calculation, over the past year the case fatality rate from Covid-19 amounts to .4%. This means 3,903 people in North Carolina died with covid over the past year (not necessarily from covid, and according to flawed PCR test diagnostics acknowledged by the CDC itself). Open VAERS shows that 179 people in North Carolina have been reported slain by the vaccine since its roll-out in early 2021 until June 16 of this year (the same date the White House announced intention to appoint Cohen CDC director).
Recall that the Vaccine Adverse Reporting System (VAERS) was shown by the CDC’s own funded study in 2010 to report less than 1% of actual adverse vaccine events. The number of people slain in North Carolina by the vaccine could be more honestly at least 18,000. To compare these numbers—covid-killed vs. vaccine-killed—we should divide 18,000 by 2.5, since the covid-killed number is only for one year (the mildest year), and the vaccine-killed for 2.5 years. Answer: at least 7,200 vaccine-killed per year compared to under 4,000 per year covid-killed. The cure may have been at least almost twice as lethal as the disease.
As the Pfizer and Moderna vaccines were scheduled to arrive in North Carolina, Cohen addressed her staff. “So that tells me a couple things… One, no one else is talking about vaccines and sort of setting the stage and being transparent. So, A-plus, team. … We’re setting expectations. We’re sharing what we know. We’re being concrete. We’re talking about all our plans, so I’m really pleased.”
Yes, A-plus, team. Mandy is really pleased you were talking about vaccines and being transparent. Unfortunately for the thousands slaughtered by the vaccines in North Carolina and their families, you were not transparent about the carnage the vaccines could cause in the state. Cohen’s “sense of empathy and compassion” made her a perfect fit for that job.
Cohen’s Jewish identity is featured:
“She spent most of the next hour listening to her staff members detail their work. By the time the meeting was ending, Cohen had changed her virtual background to that of a picture of her family for some Throwback Thursday show-and-tell. The picture was from her oldest daughter’s baby-naming ceremony, a Jewish ritual, and the family was standing in front of a menorah.
“‘Throwback Thursday and Hanukkah,’ Cohen said with some excitement, introducing her family.
“Like her family, her faith has played an important role in helping her navigate the pandemic. She wears a necklace with the chai (pronounced like “high”) symbol around her neck. The symbol represents the Hebrew word for life and health.
“When Cohen and her husband moved to North Carolina, they did not know anyone. The synagogue they chose became a second home. “And I also joke with the rabbi that I think Jews were public health people before they knew what public health was,” Cohen said, referencing Jewish dietary restrictions, and how even before the pandemic there was “a lot of washing your hands in Jewish ritual practices.
“Back on the work call, Cohen wished a Happy Hanukkah to those celebrating. It was the first night of the festival, and she needed to hurry home.”
If Cohen’s “faith” is even remotely Talmudic-influenced, the chai symbol represents the Hebrew word for life and health to Jews, and death and sickness for Goyim. Washing hands in Jewish rituals may sometimes be a necessity to cleanse away the blood from the male genital mutilation ceremony of circumcision, cruel animal sacrifices, and Jewish Ritual Murder that includes drinking the blood of raped, tortured and slaughtered children. Cohen of course does not allude specifically to these Talmudic blood rituals, but the hand-washing associated with them could hardly have made such extreme Talmudic fundamentalist Jews “public health people.”

Cohen cannot be accused of these Judaic horrors, but just as with Walensky, nor can she be trusted with a “sense of empathy and compassion” while wearing a Hebrew symbol of life and health. Chai means “to live and walk in the Jewish cultural lifestyle,” and also “the lowest (closest to the physical plane) emanation of God.” She may be worshiping a Hebrew god who seems more like a demon, demanding blood, insanely jealous, viciously punitive to a genocidal extent, and intolerably racist.

The ever-alert Children’s Health Defense, in commenting on Cohen’s appointment to CDC director, did not take its criticism so far, but it is indicative that CHD called Cohen “fanatic.” In “‘Fanatic?’: Biden’s New CDC Director Was Strong Proponent of Pandemic Mandates, Masks and Lockdowns,” author Michael Nevradakis, Ph.D. quotes critics who have emerged throughout the covid years 2020-21 as voices of medical scientific reason.
“Cohen appears to be fully entrenched in the ‘bio-pharmaceutical complex.’ She was on the wrong side of every pandemic public health intervention, failed to recognize early therapeutics and natural immunity, and to date has not acknowledged the safety disaster unfolding with the COVID-19 mass, indiscriminate, vaccination program.”
-Dr. Peter McCullough, author The Courage to Face COVID-19: Preventing Hospitalization and Death While Battling the Bio-Pharmaceutical Complex
“(Cohen is) a public health COVID authoritarian and the worst possible person to become the next CDC head.”
-Alex Berenson, commentator and former New York Times journalist
Berenson is Jewish, and in his own article, “URGENT: Joe Biden is about to pick the worst possible person to become the next CDC head,” said something Nevradakis did not include:
“Apparently diversity mandates haven’t hit the CDC yet. Cohen is a lot like Walensky, a nice Jewish* doctor** from the Northeastern suburbs with all the right degrees.
“(*I can say it, I’m Jewish)
“(**The actual expression is “nice Jewish girl” but I don’t want to get in trouble)”
Berenson is suing Andy Slavitt, Jewish (not found in “early life and education,” but at the end in Categories, “American Jews”), over censorship infringements. Slavitt started out at Goldman-Sachs investment bank, and ended up senior adviser on President Joe Biden’s coronavirus response team.
Returning to quotes in the CHD article:
“Going through [Cohen’s] timeline is a strange blast from the past of heartbreaking fear-mongering, pseudo-science, and propaganda. She passed with flying colors all three tests of compliance: closures, masking, and vaccine mandates.”
– Jeffrey A. Tucker, founder and president of the Brownstone Institute
In his essay, “New CDC Director Is Another Lockdowner,” Tucker starts by telling us that in order to have power and influence in the Soviet Union, one needed to be a member of the Communist party.
“We are headed this way in the US today. The party in question is the lockdown party. … That’s my best read on why Mandy Cohen is being pulled away from her perch in North Carolina, where she led a catastrophic pandemic response, to be the replacement for Rochelle Walensky as head of the Centers for Disease Control and Prevention. She is a faithful member of the lockdown party and thus demonstrates her willingness to do it again should the occasion arise.”
My best read is that both Walensky and Cohen are members of the Jewish party, with lockdowns as their strategy to advance Jewish profit and control objectives. Their willingness to do it again is rooted in their faithfulness to Jews and Judaic indoctrination. The occasion will arise because they will engineer one again. For a wider analysis of the Jewish role in covid, see the TOO book review “New Covid Book Tackles Taboo Truths.”
CHD/Nevradakis: “Cohen was ‘the top choice of Jeffrey D. Zients,’ the Biden administration’s former COVID-19 response coordinator.”

Zients is of course Jewish as well, suggesting the well-known phenomenon of Jewish tribal nepotism in appointing Cohen. Zients went from COVID-19 response coordinator, “charged with rolling out a massive vaccine program nationwide in early 2021,” to the current White House Chief of Staff, “like the chief operating officer for the government.”
Zients replaces Ron Klain, also Jewish.
“Jewish Ron Klain has been Joe Biden’s political alter ego for many of the last 40 years, regardless of his position or Biden’s interaction with Jews and Israel,” Democratic Party strategist Steve Rabinowitz said, adding: “Along the way, Klain has proven himself as friendly to our community and to Israel as we are with his old/new boss.”
Closely similar to Zients, and generally similar to Walensky and Cohen, Klain formerly took charge of a “pandemic response” to another disease scare in 2014, as Obama’s “Ebola Czar,” according to the Jewish Forward. Given the general Jewish hatred of the Russian Czars, I struggle to understand why these Jews apply this term to themselves when they lead “pandemic response” efforts. Perhaps to further defame the long-dead Czars, but doesn’t this also defame themselves?
CHD/Nevradakis quotes:
“Dr. Mandy Cohen during her tenure as North Carolina’s HHS secretary pushed through the most draconian COVID-19 measures imaginable.
“With her at the helm of the CDC, I expect we will just get more lying and hiding regarding the agency’s abysmal response to the pandemic and horrific track record in general.”
-Brian Hooker, Ph.D., P.E., senior director of science and research for Children’s Health DefenseCohen was particularly harsh on children in North Carolina, imposing mask mandates in school regardless of vaccination status, extending school closures longer than most other states, and threatening to sue a county school board if it did not “rescind a new policy that eliminates COVID-19 quarantine measures for most students and staff.” All this after it was known that children were at almost zero risk from covid. In “studies of children (that) are the most comprehensive yet anywhere in the world,” 2 in a million children died of covid, and most of those had “co-morbidities.”
Combine Walensky’s damage to unborn babies in the womb with Cohen’s damage to school-age children, and these two Jewish lockdown/vaccine “fanatics” covered the entire childhood age range with trauma and death, for no valid reason.
Adolescent suicides spiked during the pandemic. In North Carolina under Cohen’s lockdown reign, “youth” suicides spiked, attempts up 46% among 10-14 year old girls in 2021. Cohen continued to impose among the harshest school lockdown measures in the nation, motivated no doubt by her Jewish “sense of empathy and compassion.”
When they heard rumors that the Biden Administration—itself overwhelmingly Jewish—was planning to propose Cohen as CDC director, a group of 28 Congresspeople (24 men including a Senator and a Representative from North Carolina, and 4 women including Marjorie Taylor Greene) issued a joint letter to the President dated June 13 2023. They state:
“Dr. Cohen is unfit for the position. Throughout her career, Dr. Cohen has politicized science, disregarded civil liberties, and spread misinformation about the efficacy and necessity of COVID vaccinations … and the necessity of masks.
“… Dr. Cohen was a proponent of unnecessary, unscientific COVID restrictions on school children… After a North Carolina school district followed the science by declining to institute unscientific mask mandates and voted with an overwhelming majority to end “contact tracing” and curtail other unproven and largely hysterical quarantine policies, Dr. Cohen threatened to bring legal action against the district. Dr. Cohen’s willingness to threaten the school district put politics over the well-being of children and is just another example of the litany of public health abuses the American people endured at the hands of bureaucrats throughout the COVID-19 pandemic.”
The letter continues:
“Dr. Cohen has an extensive history of publicly… supporting radical, left-wing policies … (She) endorsed an unconstitutional ban on semi-automatic rifles and lobbied to classify climate change as a ‘public health crisis.’”
“Given her strong affiliation with… the COVID-19 lockdowns, it will be difficult for the American people to trust Dr. Cohen to run the CDC as a nonpartisan actor who makes objective decisions rooted in scientific data, and not in political expediency.”
Or Jewish Talmudic “science tikkun” as espoused by militant Jewish vaccine promoter Peter Hotez. In 2020 as secretary of NCDHHS, Cohen said in an interview with Religious News Service : “There’s so much of what I do in the health and human services space that’s so aligned with Jewish values of healing the world.” Healing the world is dangerously close to the Judaic concept of tikkun olam: fixing the world. The article further states: “It (wearing the Hebrew Chai necklace) is a testament to her faith — she is Jewish — and, in this strange pandemic moment, to her religious values.”
And: “As the Jewish High Holidays approach, Cohen said she looks forward to the time of reflection and introspection — the themes of Rosh Hashana and Yom Kippur — especially as they relate to her public work.” This ten day period between Judaic holy days includes a day of judgment where the fate of the wicked is decided. It is a time of reflection and repentance. As the wicked witch of North Carolina health and death, Cohen had much upon which to reflect and repent.
Dale Folwell is running for North Carolina governor. He tweeted:
“… the actions of Dr. Mandy Cohen during Covid resulted in more disease, death, poverty and illiteracy. As NC Governor, I would be hard pressed to ever follow her lead at CDC if chosen by the POTUS.”
The tweet was on June 2, two days after Cohen officially became Director of the CDC.
Private Sector, Monied Interests
In the short time between her resignation from NCDHHS in November 2021 and her appointment to CDC Director on July 1, 2023, Cohen was the Executive Vice President of Aledade, “the nation’s largest network of independent primary care practices.” She was also the Chief Executive Officer of Aledade Care Solutions, “the company’s new health services unit.” Aledade’s Executive Team’s webpage still lists Cohen as EVP and CEO of the Care Solutions new unit.

The Department of Justice lists under Government Ethics, Conflicts of Interest:
“An employee is prohibited from participating personally and substantially in a matter in which he, his spouse, minor child, or a general partner, or an organization of which he is an officer, director, trustee, partner or employee has a financial interest.”
Or she, in Cohen’s case. We must watch her closely for conflicts of interest, since her Jewish predecessor Walensky was identified in just such a conflict in 2021 soon before and after her appointment to CDC director. In “CDC Director Walensky’s Husband Received $5 Million in HHS Grants – and That’s Just the Start of It,” we see the insider connections, including Fauci, and another NIAID official who was on the oversight committee that approved the grant, both of whom worked with Rochelle in her time at CDC before she became director. They funneled a large research grant to Rochelle’s husband Loren’s private biotech firm Lytica Therapeutics. He is shown on the Team webpage as “Scientific Cofounder” and his bio states he is “Professor Pediatrics at Harvard Medical School, and Director of the Harvard/MIT MD-PhD Program.”
Also on the team is a Daniel Cohen, PhD, Associate Principal Scientist, Protein Chemistry. Mandy’s Wikipedia entry shows in its Early Life section, she “has two younger siblings.” The “Tar Heel of the Year” article says, “Her brother’s family just had a baby in May…” Certainly we see many Cohens throughout the Jewish power structure, and cannot verify that Daniel has any direct relation to Mandy except by tribe.


Hebrew name Cohen means Priest, descended from Aaron.
Cohen’s CDC Promotes “Chest Milk”
Such speculation is unnecessary. Cohen’s depravity emerged within a week of taking office when numerous news reports quoted the CDC stating: “transgender and nonbinary-gendered individuals may give birth and breastfeed or feed at the chest (chestfeed).” This ignited outrage from the nation’s mothers, Republican party candidates, Fox News and many others.
Not surprisingly, links to the CDC statement in these reports go nowhere or in circles now, but one prominent mention found on the CDC official website says under “Priority Breastfeeding Strategy: Continuity of Care” – “Review (of) Continuity of Care in Breastfeeding Support; a Blueprint for Communities” document: “Create community environments that proactively promote, protect, and support chest/breastfeeding.”
It is under “Health Equity Considerations” where we find the horrifying statement under “Pronoun Use – Remember That:” There is more. “An individual does not need to have given birth to breastfeed or chestfeed. Some families may have other preferred terminology for how they feed their babies, such as nursing, chestfeeding, or bodyfeeding.”
In an established pattern of recklessness endangering the nation’s children and mothers, Cohen failed to warn of the dangers to babies from synthetic hormone-induced “chest milk.” The synthetic hormone no longer recommended for increasing natural female lactation but recommended (not by name) for transsexual “chest feeding” Domperidone is a known risk to babies.
Cohen’s tribal colleagues the Jewish Pritzker family rules the transsexual transition industry with billions of dollars in grants, investments, donations and profits to impose the unholy inhuman agenda. Family oligarch Tom Pritzker was only one of two names listed in Jewish Epstein’s notorious black book with a special hand-written note: “Numero Uno.”

Caution: Another Jew Leads CDC
We have seen excessive evidence that the new CDC director Mandy Cohen will inflict whatever catastrophic lockdown measures and vaccine mandates the next contrived disease panic offers to further Jewish objectives, just as previous CDC director Rochelle Walensky.
May we all take caution. Not viruses, but certain Jews acting in coordination have infected the governmental power structure with the capability of inducing sickness and death by unelected, arbitrary and capricious decree. The cure is truly worse than the disease. The new CDC director Mandy Cohen, driven by her Judaic faith, now leads the most powerful Federal agency imposing public health/death measures.
May we turn to a more natural, holistic health model to survive her impending reign of terror at CDC.
CDC, Pharma Giants Angle for Annual COVID Shots Despite ‘Unclear’ Science
By Monica Dutcher | The Defender | August 7, 2023
The U.S. House of Representatives Select Subcommittee on the Coronavirus Pandemic wants to know more about plans by the Centers for Disease Control and Prevention (CDC) to recommend annual COVID-19 vaccines.
During a July interview with Spectrum News, CDC Director Mandy Cohen said she “anticipate[s] that COVID will become similar to flu shots, where … you get your annual flu shot and you get your annual COVID shot.”
As part of the House investigation into federal COVID-19 vaccination mandates and policies, Rep. Brad Wenstrup (R-Ohio) last week sent a letter to Cohen, stating:
“It is unclear if the science supports such a recommendation. If this anticipated CDC recommendation occurs, it will mark a significant change in federal policy and guidance regarding COVID-19 vaccines and the way in which they are utilized.”
Wenstrup requested all documents and communications about any annual — “or any other time-based iteration” — recommendation for COVID-19 booster shots, including correspondence between or among the CDC, U.S. Department of Health and Human Services (also under the subcommittee’s investigation), the White House, the CDC Foundation, CDC contractors and any other CDC stakeholders.
Pfizer, Moderna and Novavax are slated in September to release new single-strain COVID-19 shots targeting the Omicron subvariant XBB.1.5. These vaccines are not yet approved by the U.S. Food and Drug Administration (FDA), but manufacturers are following the June 15 recommendations of the FDA’s Vaccines and Related Biological Products Advisory Committee (VRBPAC).
The committee of 21 independent advisers in June voted unanimously that any new vaccine should protect against just one strain of the virus — a departure from the available bivalent vaccines — and should target one of the three Omicron subvariants currently circulating, including XBB.1.5.
The XBB.1.5 variant spread globally in the first quarter of 2023, reaching dominance in North America, and other parts of the world by April, according to the FDA’s briefing document for the June meeting.
‘We really don’t know what the COVID season is’
FDA advisers in January raised concerns about shifting to a yearly schedule for COVID-19 vaccines. Unlike the flu, which thrives in the winter months, COVID-19’s spread has proved erratic, consistently mutating into new variants.
Dr. Mark Sawyer, professor of clinical pediatrics at the University of California, San Diego, told CNBC that describing COVID-19 as seasonal “could be problematic” because “we really don’t know what the COVID season is.”
Dr. Peter McCullough, author of “The Courage to Face COVID-19: Preventing Hospitalization and Death While Battling the Bio-Pharmaceutical Complex,” told The Defender :
“COVID-19 respiratory illness is now like a mild head cold. There is no seasonal pattern. The COVID-19 vaccines have failed to stop transmission or protect against hospitalization and death.
“The products on the market have theoretical efficacy of less than six months. Annual COVID-19 shots have no clinical indication, medical necessity, are not durable for 12 months and have never been tested for use on a yearly schedule.
“On Dec. 7, 2022 in a U.S. Senate panel on vaccines, I called for all COVID-19 vaccines to be removed from the market because they are not safe for human use. There has been no objection to that testimony from public health officials.”
NBC News reported that Dr. Peter Marks, the FDA’s top vaccine regulator, acknowledged during an FDA advisory committee meeting in January that “simplifying the COVID-19 vaccine schedule to be exactly like the flu may not be possible.”
Pfizer hopes otherwise. The drug company’s chief scientific officer, Dr. Mikael Dolsten, thinks an annual COVID-19 vaccine would improve vaccine sentiment, telling CNBC the public grew dissatisfied with mandates during the earlier stages of the pandemic.
He said:
“Unfortunately some people see vaccines as part of that [the mandates].
“I think of it like the introduction of seat belts for cars. People didn’t want to wear them at first, but over time they realized how much seat belts protect them. Now everyone uses them today. That’s kind of how the vaccine story needs to be reimagined.”
An annual schedule, Dolsten added, may help people view COVID-19 shots as another “very natural part” of protecting their health.
CDC director ‘very worried about parents not vaccinating kids’
In addition to the ambiguity surrounding COVID-19 vaccine scheduling, there is no consensus among medical experts on which patients would be recommended for an annual jab.
Dr. Paul Offit, a vaccine scientist, professor of pediatrics in the Division of Infectious Diseases at the Children’s Hospital of Philadelphia and a member of VRBPAC, took issue with not only the annual model but also with administering COVID-19 vaccines to low-risk groups.
Offit told CNN:
“If the goal of the vaccine is the stated goal, which is protection against severe disease, do you really need a yearly vaccine for otherwise healthy people less than 75? I mean, is this the flu model? Because I would argue it shouldn’t be.”
Health advocacy groups and doctors argue against authorizing mRNA shots in young children and babies. As of July 28 — when data were last updated in the Vaccine Adverse Event Reporting System (VAERS) — there were 6,591 reports of adverse events following COVID-19 vaccination in children under age 6.
Cohen said she is “very worried about parents not vaccinating kids,” telling Spectrum News, “There’s plenty of other things that are hard as parents that we can’t do. This is one we can do to protect our kids.”
McCullough described Cohen as “fully entrenched in the bio-pharmaceutical complex” and “on the wrong side of every pandemic public health intervention.”
Jeffrey A. Tucker, founder and president of the Brownstone Institute, said Cohen’s career has been punctuated by “heartbreaking fear-mongering, pseudo-science, and propaganda,” adding that “she passed with flying colors all three tests of compliance: closures, masking, and vaccine mandates.”
Reduced trust in vaccines and the CDC concerns Cohen, who plans to rehabilitate that trust by focusing on “transparency, execution and building relationships with the public, health leaders and politicians.”
A survey by the Harvard T.H. Chan School of Public Health published in the journal Health Affairs found that roughly a quarter of Americans have little to no trust in the CDC for health information, including 10% who do not trust the agency at all.
The CDC currently recommends the primary series of mRNA shots, or the first two doses of the updated vaccine be given weeks apart, followed months later by a booster shot. The FDA updated its guidance for these shots in August 2022 to contain a bivalent formulation targeting the original viral strain plus the BA.4 and BA.5 Omicron subvariants.
Pfizer is working on a combined flu/COVID-19 vaccine, expected to be available after 2024. Moderna is also working on a “next-gen flu-COVID combo” vaccine. Other vaccine makers are following suit.
Monica Dutcher is a Maryland-based senior reporter for The Defender.
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
1,700+ demand retraction of influential COVID-19 origins paper after emails reveal authors doubted their own conclusions

By Suzanne Burdick, Ph.D. | The Defender | July 26, 2023
More than 1,700 people have signed a petition calling for the retraction of the seminal scientific correspondence paper, “The proximal origin of SARS-CoV-2,” that claimed COVID-19 was “not a laboratory construct or a purposefully manipulated virus.”
The paper — sometimes referred to as the “Proximal Origins” paper or the “Nature Medicine paper” — was published March 17, 2020, in Nature Medicine journal.
It was used by former National Institute of Allergy and Infectious Diseases Director Anthony Fauci, former National Institutes of Health Director Francis Collins, and other federal public health officials in 2020 and beyond to dismiss the possibility of a lab leak.
Biosafety Now — a nongovernmental organization that “advocates for reducing numbers of high-level biocontainment laboratories and for strengthening biosafety, biosecurity, and biorisk management for research on pathogens” — on July 19 launched the petition, stating, “It is imperative that this clearly fraudulent and clearly damaging paper be removed from the scientific literature.”
Biosafety’s leadership team includes 27 experts in biomedicine, mathematics, public health, public policy, public advocacy, law and social science.
Fraudulent paper ‘played an influential role’ in driving official narrative
Bryce Nickels, Ph.D., co-founder of Biosafety Now and professor of genetics at Rutgers University, said the petition seeks “to expose a clear case of scientific fraud and misconduct that has had a major impact on public opinion and policy.”
Nickels told The Defender :
“The removal of ‘Proximal Origins’ from the scientific literature is the first step in a long process needed to repair the damage this paper has caused to public trust in science.”
According to the petition, “This paper played an influential role — indeed, the central role — in communicating the false narrative that science established that SARS-CoV-2 entered humans through natural spillover, and not through research-related spillover.”
The petition continues:
“Email messages and direct messages via the messaging program Slack among authors of the paper obtained under FOIA [Freedom of Information Act] or by the U.S. Congress and publicly released in full in July 2023 … show, incontrovertibly, that the authors did not believe the conclusions of the paper at the time the paper was written, at the time the paper was submitted for publication, and at the time the paper was published.”
The recently-released internal communications show the paper “was, and is, the product of scientific fraud and scientific misconduct,” the petition said.
Commenting on the petition, investigative journalist Paul Thacker said:
“The thing that’s really the most troubling, which is why it should be retracted … [is] the ghostwriting and the undue influence [of federal public health officials on the drafting of the paper], which we know from the emails by Francis Collins, by Anthony Fauci, and from Jeremy Farrar.”
Thacker — who noted that within only a few days the petition had already garnered more than 1,300 signatures and set the hashtag #RetractProximalOrigins trending on Twitter — told The Defender :
“These guys basically ordered up a piece of science — or some sort of publication — that they could then point to, which they all did afterwards, as definitive proof that this thing could not have come from the lab.
“The whole thing was orchestrated for political purposes. It has nothing to do with science.”
Little more than a ‘political piece of propaganda’
Thacker is a former fellow at the Safra Center for Ethics at Harvard University whose investigative writing has appeared in The New York Times, The BMJ, the Journal of the American Medical Association and The Washington Post.
He explained that weeks prior to the paper’s publication, Kristian Andersen, Ph.D. — one of the co-authors of the “Proximal Origins” paper — emailed Fauci and Collins a draft of the manuscript, thanking them for their “advice and leadership” on the paper.
Andersen also invited Fauci and Collins to comment and offer suggestions about the paper — but neither are mentioned in the acknowledgments section of the final version published by Nature Medicine. According to Thacker:
“Both Collins and Fauci then promoted the Nature Medicine paper as evidence of ‘independent science’ pointing against a possible lab accident — Collins in a post for the NIH Director’s blog that alleged the study left ‘little room’ for argument in favor of a lab accident, and Anthony Fauci in a White House press briefing.
“In both cases, neither Collins nor Fauci disclosed their involvement in orchestrating Andersen’s study. This last March, Congress released further emails showing that Fauci helped to orchestrate the Nature Medicine paper.”
Thacker pointed out that the paper — which “has been called everything from ‘research paper’ to ‘analysis’ to ‘study’” — was “really just correspondence” that was later turned into a “political piece of propaganda that people could then reference, which they did.”
Describing the recent about-face regarding the paper’s importance, Thacker said:
“Now the editor-in-chief of Nature Medicine is saying, ‘Oh, well, it was just a viewpoint … like he’s trying to dismiss what it was when they [federal public officials] used it for completely different purposes. They used it as some definitive piece of scientific research that put to rest any idea this thing could have come from a lab.
“Then we find out internally that none of them who wrote it believed that in the first place. … Quite frankly, from the very beginning, none of the scientific evidence in any direction means anything about how this pandemic started. It’s always been the internal documents and the money that have mattered more.”
Thacker added, “This entire drama and discussion has nothing to do with science. It has everything to do with corruption and a coverup.”
On July 25 Thacker tweeted:
Writers Curtis Schube and Gary Lawkowski in a July 24 op-ed for The Hill pointed out that when the Centers for Disease Control and Prevention responded to the FOIA request to release Fauci’s “explosive” email showing his involvement with the Nature Medicine paper, the agency completely redacted the email.
Moreover, Thacker alleged that Andersen submitted false testimony at the July 11 hearing of the House Select Subcommittee on the Coronavirus Pandemic, which is investigating the origins of the COVID-19 pandemic.
Andersen’s allegation that Fauci and Collins were provided the paper only after it had been “accepted” and was in “proof” is false, Thacker said. “Emails impeach this portion of Andersen’s testimony,” he added.
Thacker also pointed out that The Intercept last week published newly revealed documents showing Andersen and his co-author — Tulane virologist Robert Garry, Ph.D. — both lied to Congress during the House hearing. The alleged lies covered the fact that both had pending federal grants controlled by Fauci — money that could have been used to influence their positions on the lab-leak theory.
Robert F. Kennedy Jr.’s latest book, “The Wuhan Cover-up: How US Health Officials Conspired with the Chinese Military to Hide the Origins of COVID-19,” is due out in September. The book is available now for preorder. Kennedy is the founder and chairman on leave from Children’s Health Defense.
Suzanne Burdick, Ph.D., is a reporter and researcher for The Defender based in Fairfield, Iowa. She holds a Ph.D. in Communication Studies from the University of Texas at Austin (2021), and a master’s degree in communication and leadership from Gonzaga University (2015). Her scholarship has been published in Health Communication. She has taught at various academic institutions in the United States and is fluent in Spanish.
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Walensky Warns Public to Beware of ‘Misinformation’ and ‘Politicized Science’
By Brenda Baletti, Ph.D. | The Defender | July 5, 2023
As she ended her tenure last week as director of the Centers for Disease Control and Prevention (CDC), Dr. Rochelle Walensky warned the American public to be on guard against “misinformation” and the “politicization of science.”
Walensky told The Wall Street Journal she hopes Americans will make health decisions based on “their own risk assessment and their own personal risks, but not through politics,” emphasizing that public health recommendations also shouldn’t be politicized.
“Ironically, this comes after two-and-a-half years of Walensky misinforming the public and politicising the science,” investigative journalist Maryanne Demasi, Ph.D., wrote on her Substack.
Demasi and many others took to Twitter to remind people of Walensky’s false statements and politicized decision-making.
Walensky last week published a farewell op-ed in The New York Times, in which she wrote that public health is critically important in the U.S., and yet she “fear[s] the despair from the pandemic is fading too quickly from our memories.”
She complained that “the agency [CDC] has been sidelined, chastened by early missteps with Covid and battered by persistent scrutiny.”
She also told the WSJ that public health shouldn’t fall along partisan lines.
Yet stark political partisanship defined her time at the CDC. The WSJ reported that a recent KFF poll showed political affiliation was the strongest demographic predictor of COVID-19 vaccination. And about one-quarter of Americans don’t trust the CDC’s health recommendations, according to a 2022 survey published in the journal Health Affairs.
Walensky acknowledged “missteps in communicating” by the CDC, which, she said, “could have done a better job” making it clear to the public that the agency’s message could change during the pandemic.
But, she told the WSJ, the CDC has a plan to regain public trust in the future — by working directly with media organizations to discuss how to best shape public opinion prior to releasing scientific information to the public.
She said the CDC plans to use a method called “prebunking,” where they will communicate directly with media organizations before they release information to let the media know which details about public health might be “misconstrued.”
According to The Associated Press (AP) “prebunking” by public health agencies allows the agencies to define something as “misinformation” before readers have an opportunity to encounter it elsewhere as possibly true.
Then search engines such as Google prioritize “credible websites” like the U.S. Food and Drug Administration’s (FDA) or the CDC’s in its searches.
FDA Commissioner Robert Califf, the Virality Project and Google are among those who have promoted prebunking as a way to combat misinformation.
Journalist Kim Iversen proposed a different approach Walensky might take to restoring public trust in the CDC.
She said:
“Well, the way to do it is to apologize, to own up to your lies, to own up to the mistakes that you made and to discuss why you did that, why the agency followed such political partisanship when they should have been following science, why they ignored the science that was right in front of them.”
CDC broadcast a long list of ‘misinformation’ during Walensky’s tenure
Throughout her tenure at the CDC, which began when Biden took office in January 2021, Walensky made a series of public statements that have proven to be false.
Evidence has since emerged that Walensky knew many of these statements were false when she made them.
In March 2021, Walensky famously told Rachel Maddow, that “vaccinated people do not carry the virus, don’t get sick.”
The CDC was forced to walk back her statements a few days later. But that message was the basis for vaccine mandates imposed later that year by the Biden administration, businesses, universities and public venues throughout the country.
In a mid-June congressional hearing, Walensky defended her March statements, claiming they were true at the time.
But the Washington Examiner reported on June 20 that emails obtained through a Freedom of Information Act request showed Walensky and Dr. Francis Collins were aware of and discussed “breakthrough cases” of COVID-19 in January 2021 — just before the vaccines became widely available — and yet continued to tell the public the vaccines would prevent transmission.
In that same congressional testimony, Walensky also defended the mask mandates, saying that the summary of Cochrane’s review — which found wearing masks in the community “probably makes little to no difference” in preventing viral transmission — had been “retracted.”
But it was neither retracted nor had the authors of the review changed the language in the summary, Demasi reported.
In June 2021, Walensky told “Good Morning America” that the risk of myocarditis was extremely rare, and there was overwhelming data the vaccines were safe for children — even after hundreds of cases of myocarditis had been reported and the CDC had been aware of a safety signal since February.
Under Walensky, the CDC also gave false information on vaccine safety monitoring, added the COVID-19 vaccines to the childhood vaccine schedule despite known harms, withheld data on boosters from the agency’s own advisers and told pregnant women the vaccine was safe — just days after Pfizer reportedly finalized a report demonstrating it wasn’t.
In a March study by Krohnert and others, researchers compiled instances of errors in data presented by the CDC during the COVID-19 pandemic in publications, press releases, interviews and Twitter. The authors reported 25 instances where the agency under Walensky promoted demonstrably false numbers.
In most (80%) cases, the CDC exaggerated the severity of the pandemic. For example, Walensky gave a briefing on June 23, 2022, during which she claimed COVID-19 was a “top 5 cause of death” in children, which was untrue.
Most recently, the House Select Subcommittee on the Coronavirus Pandemic gave Walensky until July 12 to turn over phone records involving American Federation of Teachers (AFT) President Randi Weingarten. The House is investigating potential political interference on the part of AFT with the CDC’s school reopening recommendations during the COVID-19 pandemic, The Defender reported.
Walensky warns of ‘future threats’
Walensky warned at the end of her Times op-ed:
“I want to remind America: The question is not if there will be another public health threat, but when. The C.D.C. needs public and congressional support if it is going to be prepared to protect you from future threats.”
To take on these “future threats” the Biden administration nominated Dr. Mandy Cohen, an internal medicine physician and former state health secretary of North Carolina, to replace Walensky.
But critics warn Cohen is “a public health COVID authoritarian” who is “fully entrenched in the ‘bio-pharmaceutical complex.’”
Dr. Peter McCullough told The Defender that during the COVID-19 pandemic, Cohen failed to recognize therapeutics and natural immunity, and supported lockdowns, vaccine mandates and masking.
Cohen comes to the CDC from the private sector, where she is executive vice president of Aledade and CEO of Aledade Care Solutions, whose executive leadership and board of directors includes people with connections to the World Economic Forum and the Bill & Melinda Gates Foundation.
Walensky congratulated Cohen on her nomination, describing her as “a respected public health leader who helped North Carolina successfully navigate” COVID-19, and whose “unique experience and accomplished tenure in North Carolina … make her perfectly suited to lead CDC as it moves forward by building on the lessons learned from COVID-19 to create an organization poised to meet public health challenges of the future.”
Brenda Baletti Ph.D. is a reporter for The Defender. She wrote and taught about capitalism and politics for 10 years in the writing program at Duke University. She holds a Ph.D. in human geography from the University of North Carolina at Chapel Hill and a master’s from the University of Texas at Austin.
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Serious adverse events from Pfizer’s mRNA vaccine are not “rare”
Maryanne Demasi, reports | June 27, 2023
Drug regulators and public health agencies have saturated the airways with claims that serious harms following covid vaccination are “rare.”

But there has been very little scrutiny of that claim by the media, and I could not find an instance where international agencies actually quantified what they meant by the term “rare” or provided a scientific source.
The best evidence so far, has been a study published in one of vaccinology’s most prestigious journals, where independent researchers reanalysed the original trial data for the mRNA vaccines.
The authors, Fraiman et al, found that serious adverse events (SAEs) – i.e. adverse events that require hospitalisation – were elevated in the vaccine arm by an alarming rate – 1 additional SAE for every 556 people vaccinated with Pfizer’s mRNA vaccine.
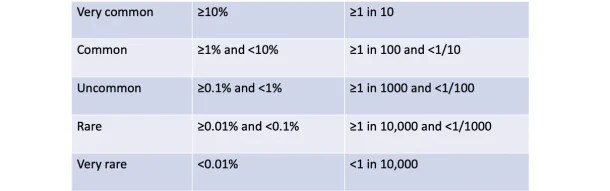
According to a scale used by drug regulators, SAEs occurring at a rate of 1 in 556 is categorised as “uncommon,” but far more common than what the public has been told.
Therefore, I asked eight drug regulators and public health agencies to answer a simple question: what is the official calculated rate of SAEs believed to be caused by Pfizer’s mRNA vaccine, and what is the evidence?
The agencies were FDA, TGA, MHRA, HC, PEI, CDC, ECDC and EMA.
The outcome was startling.
Not a single agency could cite the SAE rate of Pfizer’s vaccine. Most directed me to pharmacovigilance data, which they all emphasised does not establish causation.
The Australian TGA, for example, referred me to the spontaneous reporting system but warned, “it is not possible to meaningfully use these data to calculate the true incidence of adverse events due to the limitations of spontaneous reporting systems.”
Both the German regulator (PEI) and European CDC referred me to the European Medicines Agency which, according to its own report, saw no increase at all in SAEs. “SAEs occurred at a low frequency in both vaccinated and the placebo group at 0.6%.”
The UK regulator MHRA went so far as to state it “does not make estimations of a serious adverse event (SAE) rate, or a rate for adverse reactions considered to be causally related for any medicinal product.”
The US FDA, on the other hand, did conceded that SAEs after mRNA vaccination have “indeed been higher than that of influenza vaccines,” but suggested it was justified because “the severity and impact of covid-19 on public health have been significantly higher than those of seasonal influenza.”
Despite analysing at the same dataset as Fraiman, the FDA said it “disagrees with the conclusions” of the Fraiman analysis. The agency did not give specifics on the areas of disagreement, nor did it provide its own rate of SAEs.
In response to the criticism, Joe Fraiman, emergency doctor and lead author on the reanalysis said, “To be honest, I’m not that surprised that agencies have not determined the rate of SAEs. Once these agencies approve a drug there’s no incentive for them to monitor harms.”
Fraiman said it’s hypocritical for health agencies to tell people that serious harms of the covid vaccines are rare, when they have not even determined the SAE rate themselves.
“It’s very dangerous not to be honest with the public,” said Fraiman, who recently called for the mRNA vaccines to be suspended.
“These noble lies may get people vaccinated in the short term but you’re creating decades or generations of distrust when it’s revealed that they have been misleading the public,” added Fraiman.
Dick Bijl, a physician and epidemiologist based in the Netherlands, agreed. “It goes to show how corrupted these agencies are. There is no transparency, especially since regulators are largely funded by the drug industry.”
Bijl said it’s vital to know the rate of SAEs for the vaccines. “You must be able to do a harm:benefit analysis, to allow people to give fully informed consent, especially in young people at low risk of serious covid or those who have natural immunity.”
Bijl said the mainstream media has allowed these agencies to make false claims about the safety of vaccines without interrogating the facts.
“The rise of alternative media is strongly related to the lies being told by the legacy media, which just repeats government narratives and industry marketing. In the Netherlands, there is a lot of discussion about the distrust in public messaging,” said Bijl.
Featured Video

Iran & Its Allies Are Threatening Every Route for Saudi Oil
or go to
Aletho News Archives – Video-Images
From the Archives
A short history of British torture
ICC | December 2005
When the House of Commons was debating how much to increase the time limit for detention without trial the question of torture came up. Officially this was limited to the nice considerations of whether it was all right to send people to places where torture is used and whether Britain can use information collected by the use of torture in other countries. This discussion gave an impression of democratic Britain as the home of civilised behaviour where the very idea of torture is repugnant to our legislators – unlike, say, the US with its secret CIA jails… In reality, the British state has a long history of using and developing a whole range of torture techniques. … continue
Blog Roll
 Aletho News
- US destroying international space law
- SCO Calls for Binding Global Deal to Prevent Arms Race in Space
- Iran & Its Allies Are Threatening Every Route for Saudi Oil
- ‘40,000 tons of bombs’: Report shows Trump planning ‘largest bomb transfer in modern US history’ to Israel
- Amazon says cloud infrastructure in Bahrain, UAE ‘beyond saving’
- How Europe became an accessory to CIA torture
- Trump says Iran urgently seeks deal, Tehran sets conditions for talks
- The Andean Shadow Army
- Russia Wants to End Ukraine Conflict – Lavrov
- US Flaunts On-Orbit Weapon to Supercharge Space Arms Race
- If Americans Knew
- The assassination attempt on President Trump in Butler and the various Israeli connections to it
- “We Want That the Whole Land Be Jewish”
- BREAKING: Building collapse in Gaza kills at least 20 as they sleep – Daily Update
- ‘School is Life’: 1.5 Million Palestinian Children Face Fourth Year of Shattered Education
- Pentagon admits Iran war caused ammunition shortages, cost US $33.4bn
- 37 Palestinian journalists held in Israeli jails, rights group says
- Israel’s Hilltop Youth Recruits Minors to Terrorize Palestinians (with video)
- 100 Colonial Plans Advance in West Bank Since Start of 2026
- New Maps Show How Israel Has Thwarted Hopes for a Palestinian State
- Israel trying to ‘eliminate’ living conditions for Palestinians in West Bank
- No Tricks Zone
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
- End-Of-August Arctic Sea Ice Extent Hasn’t Fallen In 20 Years, Official Data Show!
- News-Making Nepal Region Has Had As-Warm Or Warmer Periods Than The 2000s In The 1600s, 1700s, 1800s
- 2025 Study: ‘There Exists No Unequivocal Experimental Evidence For The CO2 Greenhouse Effect’
 Aletho News
