An invitation to visit New Zealand
By Guy Hatchard | TCW Defending Freedom | May 14, 2022
AFTER two years of being closed for business, New Zealand has re-opened its borders. The outcome: unprecedented numbers are leaving rather than arriving. The question is, are you willing to take their place?
For those of you in the UK who are worried that there is one law for the government and another for the people, spare a thought for the people of New Zealand where the government is actually following its own advice.
At least in the UK you can look at your leaders partying and think ‘If they can do that, so can I’. We have to listen to the voices of our leaders filtered through a mask, and then follow them.
Last week I visited Wellington, seat of government and dull party central of the civil service. It was an extraordinary experience. Conformity to the fore. Masking was as near 100 per cent as makes no difference.
This has happened despite there being almost no evidence that masking reduces the spread of infection, and a great deal of evidence that it harms our health.
Medical mask exemptions will soon have to prominently display your name. Fines and jail sentences related to masking non-compliance are slated to be introduced.
Students still have to be fully vaxxed to enrol in universities. Many, if not most, apprenticeship schemes require Covid vaccination.
The government has allowed businesses to continue to enforce vaccination mandates, and many have. In some industries, even employees working from home are being required to show proof of Covid vaccination – to no one.
Just imagine if you are watching The Chase on TV and between every contestant you are subjected to a 60-second government Covid vaccine ad advising you to ‘keep your family safe’with an ineffective mRNA vaccine known to be dangerous. Not only do you know that it is borrowed money paying for this saturation government messaging, but you and your children are going to have to repay it for decades. You are not told that government statistics show that boosted individuals are more likely to end up in hospital with Covid than the unvaccinated – too embarrassing to warrant a media mention.
Can you imagine the level of despair if the leader of the opposition is also a vaccination freak? Ours is on record before the pandemic saying that single mothers should lose benefits if their children are unvaccinated.
Third party leader David Seymour (ACT Party) told people who have lost their jobs due to coercive mandates that it was their choice. So no joy there either.
The Green Party is more pro-mandate than the government and additionally would have us all back on bicycles. Their deputy leader struggled to hospital riding a bicycle to give birth while already in labour, presumably just to show us retirees how it is done.
Undercover surveillance is on the increase. Anti-mandate bloggers have had visits from the police.
Last week a 78-year-old farmer was fined $30,000 (£15,300) for selling a pail of raw milk to a government undercover agent who, along with his back-up team, had taken weeks to worm his way into the veteran farmer’s confidence. In contrast, France has made an international business success out of selling cheese made from raw milk. NZ, dairy capital of the world, has opted out of opportunity.
The government is ready and willing to encourage habits that damage health. Jacinda has famously said that NZ is on track to stamp out smoking within a decade but she forgot to mention that the government has encouraged the switch to vaping. A survey completed in November found an unprecedented and alarming 26 per cent of NZ school students vaped during the previous week. Another good markup for commercial pharma.
There is no end to our nanny state. This week it was suggested that the government would enter the supermarket business. We may soon be collecting our meagre processed rations from them.
So if it’s still on your bucket list and you will be visiting us, well done. Put on a brave face. You will need to test prior to departure and three more after landing. You may not know if anyone you meet is smiling or not, but you can always imagine that you are part of a fan club for the Mask of Zorro.
Oh, and by the way, our Labour tourism minister says NZ now wants to give preference to wealthy tourist. You may think that is a bit rich, or just a sign of an antisocial illness.
Nearly 30,000 Deaths After COVID Vaccines Reported to VAERS, CDC Data Show
By Megan Redshaw | The Defender | May 13, 2022
The Centers for Disease Control and Prevention (CDC) today released new data showing a total of 1,261,149 reports of adverse events following COVID-19 vaccines were submitted between Dec. 14, 2020, and May 6, 2022, to the Vaccine Adverse Event Reporting System (VAERS). VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
The data included a total of 27,968 reports of deaths — an increase of 210 over the previous week — and 228,477 serious injuries, including deaths, during the same time period — up 1,774 compared with the previous week. There were 5,794 additional total adverse events reported to VAERS over the previous week.
Excluding “foreign reports” to VAERS, 815,384 adverse events, including 12,899 deaths and 81,830 serious injuries, were reported in the U.S. between Dec. 14, 2020, and May 6, 2022.
Foreign reports are reports foreign subsidiaries send to U.S. vaccine manufacturers. Under U.S. Food and Drug Administration (FDA) regulations, if a manufacturer is notified of a foreign case report that describes an event that is both serious and does not appear on the product’s labeling, the manufacturer is required to submit the report to VAERS.
Of the 12,899 U.S. deaths reported as of May 6, 16% occurred within 24 hours of vaccination, 20% occurred within 48 hours of vaccination and 59% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 578 million COVID-19 vaccine doses had been administered as of May 6, including 341 million doses of Pfizer, 218 million doses of Moderna and 19 million doses of Johnson & Johnson (J&J).

Every Friday, VAERS publishes vaccine injury reports received as of a specified date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed.
Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
U.S. VAERS data from Dec. 14, 2020, to May 6, 2022, for 5- to 11-year-olds show:
- 10,560 adverse events, including 272 rated as serious and 5 reported deaths.
- 20 reports of myocarditis and pericarditis (heart inflammation).
The CDC uses a narrowed case definition of “myocarditis,” which excludes cases of cardiac arrest, ischemic strokes and deaths due to heart problems that occur before one has the chance to go to the emergency department.
The Defender has noticed over previous weeks that reports of myocarditis and pericarditis have been removed by the CDC from the VAERS system in this age group. No explanation was provided. - 43 reports of blood clotting disorders.
U.S. VAERS data from Dec. 14, 2020, to May 6, 2022, for 12- to 17-year-olds show:
- 31,504 adverse events, including 1,812 rated as serious and 43 reported deaths. VAERS reported 44 deaths in the 12- to 17-year-old age group last week.
- 65 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases attributed to Pfizer’s vaccine.
- 650 reports of myocarditis and pericarditis with 638 cases attributed to Pfizer’s vaccine.
- 166 reports of blood clotting disorders with all cases attributed to Pfizer.
U.S. VAERS data from Dec. 14, 2020, to May 6, 2022, for all age groups combined, show:
- 20% of deaths were related to cardiac disorders.
- 54% of those who died were male, 41% were female and the remaining death reports did not include the gender of the deceased.
- The average age of death was 73.
- As of May 6, 5,503 pregnant women reported adverse events related to COVID-19 vaccines, including 1,720 reports of miscarriage or premature birth.
- Of the 3,629 cases of Bell’s Palsy reported, 51% were attributed to Pfizer vaccinations, 40% to Moderna and 8% to J&J.
- 873 reports of Guillain-Barré syndrome, with 42% of cases attributed to Pfizer, 30% to Moderna and 29% to J&J.
- 2,331 reports of anaphylaxis where the reaction was life-threatening, required treatment or resulted in death.
- 1,698 reports of myocardial infarction.
- 13,922 reports of blood-clotting disorders in the U.S. Of those, 6,248 reports were attributed to Pfizer, 4,972 reports to Moderna and 2,661 reports to J&J.
- 4,183 cases of myocarditis and pericarditis with 2,562 cases attributed to Pfizer’s, 1,424 cases to Moderna’s and 184 cases to J&J’s COVID-19 vaccines.
Pfizer’s COVID efficacy fades rapidly just weeks after second and third doses
Second and third doses of Pfizer’s COVID-19 vaccine provide protection against the Omicron variant for only a few weeks, according to peer-reviewed research published today in JAMA Network Open.
“Our study found a rapid decline in Omicron-specific serum neutralizing antibody titers only a few weeks after the second and third doses of [the Pfizer-BioNTech] BNT162b2,” the authors of the research letter wrote.
The authors said their findings “could support rolling out additional booster shots to vulnerable people as the variant drives an uptick in new cases across the country,” Forbes reported.
Danish researchers studied adults who received two or three doses of BNT162b2 between January 2021 and October 2021, or were previously infected prior to February 2021 and then vaccinated.
They found that after an initial increase in Omicron-specific antibodies after the second Pfizer shot, levels dropped rapidly, from 76.2% at week 4, to 53.3% at weeks 8 to 10, and 18.9% at weeks 12 to 14.
After the third shot, neutralizing antibodies against Omicron fell 5.4-fold between week 3 and week 8.
Megan Redshaw is a staff attorney for Children’s Health Defense and a reporter for The Defender.
Twitter bans Ontario Party leader Derek Sloan over Covid tweet
By Cindy Harper | Reclaim The Net | May 12, 2022
Derek Sloan, a former member of Canada’s parliament and now the leader of the Ontario Party, was permanently suspended from Twitter over alleged violations of the platform’s policies.
The permanent ban came after he criticized comments made by the Canadian Chief Public Health Officer Theresa Tam about long Covid symptoms.
On Sunday, Rebel News board member Efron Monsanto posted a clip of Tam claiming that about half of the people getting Covid have long Covid symptoms, which refers to displaying symptoms of Covid for months.
“We probably anticipate that the impacts of long COVID is going to be quite substantial,” said Tam, adding that the solution is booster shots.
Replying to the tweet, Sloan wrote: “Their next move will be to rebrand the symptoms of COVID vaccine injury as ‘long COVID.’
The cure for ‘long COVID’ will be more vaccine boosters, which will create more ‘long COVID.’ Public health isn’t on your side.”
Following the comments, Sloan’s account was immediately suspended.
“This account will not be restored. This case will now be closed and replies will not be monitored,” Twitter told Sloan.
Speaking to LifeSiteNews, Sloan said he hopes Elon Musk will reinstate his account once he takes over in the next few months.
Meanwhile Sloan is campaigning for the provincial elections to be held on June 2. He said the campaign is going “very well.”
“People are really resonating to our main messages, no World Economic Forum, Digital ID, no foreign buying of real estate or farmlands, medical privacy, no censorship, and free votes,” Sloan told LifeSiteNews.
“Education not indoctrination,” he added.
The vaccine cajolers, Part 3: Recruiting trusted sales staff
By Paula Jardine | TCW Defending Freedom | May 13, 2022
This is the third instalment of Paula Jardine’s five-part investigation into the planning behind ensuring vaccine acceptance and countering vaccine ‘hesitancy’. You can read Part 1, published on Wednesday, here, and Part 2, published yesterday, here.
IN 2018 the Wellcome Trust reported that vaccine scepticism is highest in high income industrialised countries where over 80 per cent of all global vaccine sales occur. Months before Covid-19 was declared a Public Health Emergency, the World Health Organisation had listed vaccine hesitancy as one of ten threats to global health, threatening to reverse progress made in tackling vaccine-preventable diseases: ‘Given that the majority of parents accept vaccines, pro-vaccine messages may be needed to reinforce and support positive sentiment and help prevent emerging hesitancy from expanding.’
In fact they had been working for years trying to shore up positive sentiments, in 2003 establishing the WHO endorsed global network of websites called the Vaccine Safety Net to provide ‘trustworthy’ information to ‘counterbalance websites that provide unbalanced, misleading and alarming information on vaccine safety’.
A decade later, in 2013, this counterbalancing programme had not proved enough for some. David Ropeik, who taught risk communication at Harvard School of Public Health, chillingly said, ‘What’s dangerous about widely broadcast vaccine debates, in a sense, is the debate itself: by putting out misleading information to people with little fundamental understanding of the performance and value of vaccines, the anti-vaccine movement and its social media echo chambers create doubt when, in fact, there is not a true scientific debate.’
So certain was Ropeik of the absence of a debate that he called for punitive measures, including restricting the ability of the unvaccinated to participate fully in community activities, to be used as a means of achieving full vaccination, long before Covid saw countries introduce such restrictions by way of vaccine passes.
Dr Emily Brunson, an anthropologist who like Dr Heidi Larson, referred to yesterday, studies vaccine confidence issues, was less absolutist than Ropeik. ‘I think we need to avoid the trap of thinking that information or knowledge is enough, because for a lot of the people, and when you look at hesitancy and parental vaccine hesitancy in the US, the group who is most likely to purposefully choose to not vaccinate are highly educated . . . these are people who have read the primary literature themselves, and they’re correctly interpreting it, so it’s not a misunderstanding. They have other concerns that go beyond the traditional public health message of “This is what you should be doing”.’
Communications strategies that are ‘vaccine positive’ and developed with input from the vaccine confidence teams are disseminated around the world today. Larson and Brunson were both members of the expert panel convened by the US National Institute of Health (NIH) to develop communications guidance as the Covid-19 vaccines rollout under emergency use authorisations began. They both contributed to a Vaccine Communications Principles guide published by the Centre for Public Interest Communications which describes its mission as ‘building communications strategies for the common good’.
Larson was also a member of the WHO Scientific Advisory Group of Experts (SAGE) working group on vaccines that developed a model to address hesitancy based on what it calls the three Cs: confidence, complacency and convenience. The key to confidence, they observed, lies with health workers, who are trusted by the public and able to influence vaccination decisions.
Over recent years, seasonal and pandemic influenza vaccine uptake has become the bellwether for vaccine confidence amongst health care workers. One lesson learned from the 2009 swine flu pandemic was that many of these workers began to exhibit less than universal enthusiasm for vaccines. In the United States fewer than half accepted the swine flu vaccine. Of course, if they were not taking the vaccines themselves, they couldn’t be relied upon as recruiting sergeants for the War on Microbes. Some needed more than education, they needed pressganging. So health departments and employers began mandating vaccines as a pre-condition of employment. Others stopped short of mandates, requiring instead that unvaccinated staff wear masks so that they could be more easily identified.
In England, where annual flu vaccine uptake by NHS staff hovers around 64 per cent overall with a wide variation in uptake between trusts, a different ‘inducement’ approach was introduced. In 2016, NHS England began offering financial incentives to the trusts linked to the number of staff inoculated. Behavioural modification tactics courtesy of the behavioural psychologists were deployed including ‘social norming’, that is creating peer pressure to make people think ‘if everyone else is doing it, I should too’. As NHS England explains, ‘Even something as simple as a sticker to show they have had their jab can be worn as a sign of pride and signal to others that they should have the flu vaccination.’
Whether volunteers or conscripts for the War on Microbes, the job of these trusted voices is to sell to the public products that are meant to be a long-term investment in their own health or their children’s health. The 2019 Global Vaccination Summit said more could be done to support them to provide ‘trusted, credible information on vaccines’ by giving more prominence to vaccination and communication skills in medical curricula and by increasing continuing professional training on vaccination issues.
The question is, what exactly are they being taught?
Google introduces new wallet with support for digital IDs and vaccine cards
Digital ID cards are being normalized by Big Tech
By Tom Parker | Reclaim The Net | May 11, 2022
Google will be integrating digital ID cards and proof of vaccination cards into a new Google Wallet app that’s set to be released in a few weeks.
Google revealed the new digital wallet app at its Google I/O ‘22 keynote. Sameer Samat, Google’s Vice President of Product Management, said the tech giant is working with US states and governments around the world to bring digital IDs to Google Wallet and that driver’s licenses will be the first type of ID to be digitized in the app.
Samat noted that items with highly personal information, such as vaccine cards, are stored on device and “not shared with anyone, not even Google.”
Google’s embrace of digital IDs and vaccine cards follows Apple introducing the tech last year when it partnered with several US states and the Transport Security Administration (TSA) to digitize driver’s licenses and then stuck taxpayers with part of the bill for the rollout.
When it started digitizing driver’s licenses, Apple insisted that users could present their ID without needing to unlock, show, or hand over their device. Samat made similar claims at Google I/O ‘22 and said users can share information from driver’s licenses that are stored in Google Wallet without having to give the phone to another person by either using near-field communication (NFC) or a quick response (QR code).
Digital vaccine cards have also started to be normalized by two of the world’s biggest phone manufacturers – Apple and Samsung.
As these powerful tech companies embrace digital IDs and vaccine cards, national governments and influential international organizations are also pushing for greater adoption of this tech.
FDA announces FIVE meetings in June to push Novavax in adults, Moderna in kids 0-17, and Pfizer in kids under 5
The blitzkrieg culminates with a “Future Framework” to automatically deem all reformulated Covid-19 shots as “safe and effective” WITHOUT further clinical trials
By Toby Rogers | May 11, 2022
I. FDA goes full Shock & Awe in the attempt to get several toxic shots authorized in quick succession
In a little noticed article in the Washington Post, the FDA revealed that they are going to hold FIVE meetings of the Vaccines and Related Biological Products Advisory Committee (VRBPAC) in June. FIVE! The meetings have not been officially announced on the FDA website yet but the best guess at this point is as follows:
June 7, Novavax in adults
June 8, Moderna in adolescents (delayed for a year because of myocarditis concerns)
June 21, Moderna in kids <6
June 22, Pfizer in kids <5
June 28, “Future Framework” for Covid-19 shots
This is very troubling. It means that the FDA is shifting into Shock & Awe military strategy to try to push through five authorizations in quick succession — so that the public does not have time to think and react. This is not the proper way to do science, it is an attack on democracy, and if they succeed, the FDA will kill and injure millions of American for years to come.
Let’s talk about what we know about each of these shots and then talk about what we can do to stop the FDA from destroying our country.
II. Novavax is terrible and useless
Novavax is a protein subunit vaccine. Fellow Substacker Robyn Chuter has done the best deep dive that I’ve seen on Novavax:
Robyn reviewed 3 Novavax clinical trials and the results are always terrible:
• No reductions in hospitalizations.
• No reductions in deaths.
• Tiny absolute risk reduction for a couple months (and then, after six months, the control group gets injected too so there is no long term data).
• Significant risk of adverse events in the vaccinated group.
This is not a surprise. The SARS-CoV-2 virus was never a good candidate for a vaccine (in the same way that HIV and the common cold have never had a successful vaccine in spite of decades of efforts). Recombinant proteins are not safer nor more effective than mRNA — they just fails in different ways. Novavax also uses a proprietary new adjuvant, “Matrix M”, that is not well studied.
III. Moderna mRNA shots in adolescents and kids are useless and terrible
A few days ago, I did a deep dive into the problems with the Moderna mRNA shot in kids. To summarize briefly:
• The Moderna application to inject adolescents has been held up since June 2021, because the Moderna shot increases the risk of myocarditis.
• Finland, Sweden, Denmark, and Norway have all suspended the use of the Moderna mRNA shot in teenagers because it leads to myocarditis. Finland and Sweden even suspended its use in men under 30 years old.
• We have no data from the Moderna clinical trial in kids younger than 12 other than selective leaks to the NY Times. But we know that even with Moderna rigging the trials, the shot made no difference on clinically significant outcomes including infection, hospitalization, ICU visits, or death.
However the Moderna shot did cause fevers in 15% to 17% of kids and fevers over 104 degrees in 0.2% of kids (which, if you multiply that by the 18 million kids they want to inject = 36,000 kids with potentially permanent neurological injury from a shot that provides no benefit).
IV. Pfizer mRNA shots in kids under 5 are useless and terrible
I’ve done several articles on the dangers of Pfizer mRNA shots in kids under 5. To summarize briefly:
• There is no Covid emergency for children under five years old. The CDC’s own research shows that 74.2% of kids 0-11 already had natural immunity. That was as of February 2022 — by now the number is probably closer to 100%.
• The Pfizer mRNA shot does not work very well in kids. The Pfizer clinical trial in kids 6 months to four years old failed in December 2021 and failed again in February 2022. A study by the NY State Department of Health shows that against the Omicron variant, after one month the Pfizer shot was only 12% effective in kids 5 to 11. After 6 weeks, vaccine effectiveness was a shocking MINUS 41% (vaccinated children were significantly more likely to catch Covid than the unvaccinated).
• The harms from the Pfizer mRNA shot in children are catastrophic. There are now 47,736 VAERS reports of adverse events in children following Covid-19 shots. These reports likely understate harms by a factor of 41 to 100. There are numerous reports of fatalities in children following Covid-19 shots (including reports that mysteriously disappear).
For those who want more details, Michael Palmer, MD; Sucharit Bhakdi, MD; and Wolfgang Wodarg, MD produced a 50 page guide, “On the use of the Pfizer and the Moderna COVID-19 mRNA vaccines in children and adolescents.”
V. The FDA’s proposed “Future Framework” for Covid-19 Vaccines is the worst idea in the history of public health
The “Future Framework” is how the FDA plans to rig the process in perpetuity. The “Future Framework” will take the” “flu strain selection process” that is used every year — and apply it to future (reformulated) Covid-19 shots.
Manufacturers love this because then all future Covid-19 shots will be deemed automatically “safe and effective” WITHOUT FURTHER CLINICAL TRIALS because they are “biologically similar” to existing Covid-19 shots.
This approach does not work with the flu shot (last year the flu shot was somewhere between 0% and 14% effective) and it will not work with Covid-19 shots either.
Moderna is already signaling that they want to manufacture a Covid-19 shot with Wuhan and Beta strains — even though neither strain is still in widespread circulation.
If the “Future Framework” is approved, there will be no future clinical trial data submitted to the FDA in connection with Covid-19 shots in perpetuity.
VI. What is to be done. Talking points.
I imagine we are all tempted to just say/write:
• No Novavax in adults.
• No Moderna in adolescents.
• No Moderna in little kids.
• No Pfizer in little kids.
• No “Future Framework”.
The problem with that approach is that negating a frame reinforces a frame. So the more we just say NO, the more we reinforce the very thing we are trying to stop.
Furthermore, we do not want to leave the bougiecrats in an existential abyss because they are incapable of original thought. So if we just say no, they will not know what to do with themselves and will become panicked and vengeful and start lashing out.
So let’s find a way to reframe and give our country a path out of this valley of misery. My proposed talking points are as follows.
1. The FDA must revoke the existing authorizations for Moderna, Pfizer, and J&J Covid-19 shots and withdraw them from the market immediately. SARS-CoV-2 was never a good candidate for a vaccine. These shots do not stop infection, transmission, hospitalization, nor death. They appear to have negative efficacy and are driving the evolution of variants that evade vaccines. The pandemic will never stop as long as the FDA and CDC are promoting shots that lack sterilizing immunity.
2. The FDA and CDC must pivot to therapeutics. This was always the answer. The CDC’s own research showed that chloroquine is safe and effective for prophylaxis and early treatment of SARS coronaviruses (hydroxychloroquine is even safer than chloroquine). The best frontline doctors have found that ivermectin is a life saver if used early. About twenty off-the-shelf treatments are more effective than vaccines. Get these safe and effective medicines to people who need them and let doctors be doctors again and treat patients based on their own best clinical judgment.
3. Vaccine safety assessments must be based on actual science. That means:
• Large (50,000+ person) double blind randomized controlled trials with inert saline placebos conducted by an independent third party.
• Safety and efficacy studies for two years prior to any application followed by 20 years of follow up (with the control group intact).
• Greater than 90% efficacy with less than 1% Grade 3 Adverse Events.
• Proper monitoring for carcinogenesis, mutagenesis, and impairment of fertility.
VII. What is to be done. Whom to contact:
Please reach out and find a way to awaken the moral core of these 36 people:
You can use the talking points from above or share your own story and insights.
Political appointees:
Xavier Becerra
Secretary, Health & Human Services
200 Independence Avenue S.W.
Washington, D.C. 20201
c/o Sean McCluskie
sean.mccluskie@hhs.gov
https://twitter.com/XavierBecerra
Robert Califf
FDA Commissioner
Food and Drug Administration
Mail stop: HF-1
10903 New Hampshire Ave.
Silver Spring MD 20993-0002
phone: (301) 796-5400
fax: (301) 847-8752
commissioner@fda.hhs.gov
https://twitter.com/DrCaliff_FDA
Ashish K. Jha, MD, MPH
White House Covid Czar
Brown University School of Public Health
121 South Main Street
Providence RI 02903
DeanofPublicHealth@brown.edu
https://twitter.com/ashishkjha
Rochelle Walensky
Director, Centers for Disease Control and Prevention
Roybal Building 21, Rm 12000
1600 Clifton Rd
Atlanta, GA 30333
phone: (404) 639-7000
Aux7@cdc.gov
https://twitter.com/CDCDirector
FDA staff:
Peter Marks
Director, Center for Biologics Evaluation and Research
FDA, Mail stop: HFM-2
10903 New Hampshire Ave., WO71-7232
Silver Spring MD 20993-0002
phone: (240) 402-8116
fax: (301) 595-1310
Peter.Marks@fda.hhs.gov
Hong Yang
Biologist, FDA/CBER/OBE
Building WO71, Room 5338
Mail stop: HFM-210
Silver Spring MD 20993-0002
phone: (240) 402-8836
fax: (301) 595-1240
Hong.Yang@fda.hhs.gov
Richard Forshee
Associate Director, FDA/CBER/OBE
Building, WO71, Room 5342
Silver Spring MD 20993-0002
phone: (240) 402-8631
fax: (301) 595-1240
Richard.Forshee@fda.hhs.gov
Hui-Lee Wong
Associate Director for Innovation and Development,
Office of Biostatistics and Epidemiology,
Center for Biologics Evaluation and Research
White Oak Building 71, Room 5222
Silver Spring MD 20993-0002
phone: (240) 402-0473
Huilee.Wong@fda.hhs.gov
Leslie Ball
Office of Vaccines Research and Review
Division of Vaccines and Related Products Applications,
Center for Biologics Evaluation and Research
Building WO22, Room 6156
Silver Spring MD 20993-0002
phone: (301) 796-3399
Leslie.Ball@fda.hhs.gov
Doran L. Fink
Deputy Director – Clinical
Division of Vaccines and Related Products Applications
Office of Vaccines Research and Review, CBER
Mail stop HFM-475
Building WO71, Room 3314
Silver Spring MD 20993-0002
phone: (301) 796-1159
Doran.Fink@fda.hhs.gov
Hana El Sahly, M.D., Chair VRBPAC
Associate Professor
Department of Molecular Virology and Microbiology
Department of Medicine
Section of Infectious Diseases
Baylor College of Medicine
Houston, TX 77030
713-798-2058
hanae@bcm.edu
Paula Annunziato, M.D.
Vice President and Therapeutic Area Head
Vaccines Clinical Research
Merck
North Wales, PA 19454
paula.annunziato@merck.com
Adam C. Berger, Ph.D.
Director, Division of Clinical and Healthcare Research Policy
Office of Science Policy
Office of the Director
National Instituters of Health
6705 Rockledge Drive, Suite 630
Bethesda, MD 20892
(301) 827-9676
adam.berger@nih.gov
Henry H. Bernstein, D.O.
Professor of Pediatrics
Zucker School of Medicine at Hofstra/Northwell
Department of Pediatrics
Cohen Children’s Medical Center
New Hyde Park, NY 11042
phone: (516) 838-6415 (office)
fax: (516) 465-5399
hbernstein@northwell.edu
Captain Amanda Cohn
Chief Medical Officer
National Center for Immunizations and Respiratory Diseases
Centers for Disease Control and Prevention
1600 Clifton Rd
Atlanta, GA 30333 MS C-09
phone: (404) 639-6039
fax: (404) 315-4679
acohn@cdc.gov
anc0@cdc.gov
Holly Janes, Ph.D.
Fred Hutchinson Cancer Research Center •
Vaccine and Infectious Disease Division
1100 Fairview Avenue North,
M2-C200
P.O. Box 19024
Seattle, Washington 98109 U.S.A.
phone: (206) 667.6353
hjanes@fredhutch.org
Hayley Gans, M.D.
Professor of Pediatrics
Department of Pediatrics
Stanford University Medical Center
Stanford, CA 94305
phone: (650) 723-5682
fax: (650) 725-8040
hgans@stanford.edu
David Kim, M.D.
CAPT, U.S. Public Health Services
Office of Infectious Disease and HIV/AIDS Policy
Office of the Assistant Secretary for Health
U.S. Department of Health and Human Services
330 C Street SW, Suite L600
Washington, DC 20024
phone: (202) 795-7636
david.kim@hhs.gov
Arnold Monto, M.D.
Professor Emeritus
Department of Epidemiology
University of Michigan School of Public Health
Ann Arbor, MI 48109
phone: (734) 764-5453
fax: (734) 764-3192
asmonto@umich.edu
Paul Offit, M.D.
Professor of Pediatrics
Division of Infectious Diseases
Abramson Research Building
The Children’s Hospital of Philadelphia
Philadelphia, PA 19104
phone: (215) 590-2020
offit@chop.edu
https://twitter.com/DrPaulOffit
Steven Pergam, M.D.
Medical Director
Infection Prevention
Seattle Cancer Care Alliance
Seattle, WA 98109
phone: (206) 667-7126
spergam@fredhutch.org
https://twitter.com/PergamIC
Jay Portnoy, M.D.
Director, Division of Allergy, Asthma & Immunology
Children’s Mercy Hospitals & Clinics
2401 Gillham Road
Kansas City, MO 64108
phone: (816) 960-8885
fax: (816) 960-8888
Jportnoy@cmh.edu
Eric Rubin, M.D., Ph.D.
Editor-in-Chief
New England Journal of Medicine
Adjunct Professor
Harvard TH Chan School of Public Health
665 Huntington Ave
Building 1, Room 811
Boston, MA 02115
phone: (617) 432-3335
erubin@hsph.harvard.edu
erubin@nejm.org
Andrea Shane, M.D.
Professor of Pediatrics
Emory University School of Medicine
2015 Uppergate Drive NE, Rm. 504A
Atlanta, GA 30322
phone: (404) 727-9880 (direct)
(404) 727-5642 (main)
fax: (404) 727-8249
ashane@emory.edu
Geeta K. Swamy, M.D.
Senior Associate Dean
Vice Chair for Research & Faculty Development
Associate Professor, Department of Obstetrics & Gynecology
Division of Maternal-Fetal Medicine
Duke University
Box 3967 Med Ctr,
Durham, NC 27710
phone: (919) 681-5220
swamy002@mc.duke.edu
Temporary VRBPAC members (but their votes count just the same):
A. Oveta Fuller, Ph.D.
Associate Professor of Microbiology and Immunology,
University of Michigan Medical School
Ann Arbor, MI 48109
phone: (734) 647-3830
fullerao@umich.edu
Randy Hawkins, M.D.
Charles Drew University
1731 E. 120th St.
Los Angeles, CA 90059
(323) 563-4800
RandyHawkins@cdrewu.edu
James Hildreth, Sr., Ph.D., M.D.
Professor
Department of Internal Medicine
School of Medicine
President and Chief Executive Officer
Meharry Medical College
Nashville, TN 37205
officeofthepresident@mmc.edu
Jeannette Lee, Ph.D.
Professor Department of Biostatistics
University of Arkansas for Medical Sciences
Little Rock, AR 72701
phone: (501) 526-6712
JYLee@uams.edu
Ofer Levy, M.D., Ph.D.
Staff Physician & Principal Investigator
Director, Precision Vaccines Program
Division of Infectious Diseases
Boston Children’s Hospital
Professor,
Harvard Medical School Associate Member
phone: (617) 919-2900
fax: (617) 730-0254
ofer.levy@childrens.harvard.edu
Wayne Marasco
Dana-Farber Cancer Institute
450 Brookline Avenue
Jimmy Fund 824
Boston, MA 02215
Phone: (617) 632-2153
fax: (617) 632-3889
wayne_marasco@dfci.harvard.edu
H. Cody Meissner, M.D.
Professor of Pediatrics
Tufts University School of Medicine
Director, Pediatric Infectious Disease
Tufts Medical Center
Boston, MA 02111
phone: (617) 636-5227
fax: (617) 636-4300
cmeissner@tuftsmedicalcenter.org
Michael Nelson, M.D., Ph.D.
Professor of Medicine
Asthma, Allergy and Immunology Division
UVA Division of Asthma, Allergy & Immunology
PO Box 801355
Charlottesville, VA 22908
phone: (434) 297-8399
fax: (434) 924-5779
mrn8d@virginia.edu
Stanley Perlman, M.D., Ph.D.
Professor of Pediatrics
University of Iowa
3-712 Bowen Science Building (BSB)
51 Newton Rd
Iowa City, IA 52242
phone: (319) 335-8549
stanley-perlman@uiowa.edu
Mark Sawyer, M.D.
Professor of Clinical Pediatrics
8110 Birmingham Way
Bldg. 28, 1st Floor
San Diego, CA 92123
phone: (858) 966-7785
fax: (858) 966-8658
mhsawyer@ucsd.edu
Melinda Wharton, M.D., MPH
Associate Director for Vaccine Policy
National Center for Immunization and Respiratory Diseases,
Centers for Disease Control and Prevention,
1600 Clifton Road, Mailstop E05,
Atlanta, GA 30333
phone: (404) 639.8755
fax: (404) 639.8626
mew2@cdc.gov
I know that we’re all weary. We’ve been battling Pharma fascism for the last two years and battling against the FDA every day for the last few months. I imagine it’ll take about an hour to call or write to all 36 people on this list. It’s a heavy lift. But that’s the price of liberty. This is what it’s going to take to save our Republic. So let’s fire up our computers and get out our phones and generate the largest response in the history of the movement. Let’s make history together!
The Vaccine Cajolers, Part 1: How jab zealots set out to stifle sceptics
THIS is the first of a special five-part investigation into the way in which, and why, winning ‘vaccine confidence’ became the primary goal of world health agencies, regardless of need, efficacy or risk.
By Paula Jardine | TCW Defending Freedom | May 11, 2022
Since the UK’s Covid-19 vaccine programme began in December 2020, 140million doses have been administered to 55million people, representing 73 per cent of the population.
The high level of acceptance of these vaccines, which were developed in one tenth of the normal time frame – and in the case of the mRNA vaccines using a novel technology never previously licensed for use in either humans or animals – is a remarkable testament to the level of public trust in vaccines.
It is arguably the end product of two decades of work, first by GAVI, the Global Alliance for Vaccines and Immunisations (now called The Vaccine Alliance) and recently by initiatives such as that of the London-based Vaccine Confidence Project, established to deliver the goal of universal childhood vaccination set 40 years ago by UNICEF, the United Nations children’s welfare organisation.
GAVI was set up in 1999 ‘to save children’s lives and protect people’s health through the widespread use of safe vaccines, with a particular focus on the needs of developing countries.’
It was founded at the instigation of Dr Seth Berkeley, its current CEO, who was then working for the Rockefeller Foundation. ‘We will have an outside body that can bring in industry (which the World Health Organisation can’t legally do), do advocacy and build a truly international alliance,’ he said.
The Vaccine Alliance, a public-private partnership financed by vaccine manufacturers, the Bill and Melinda Gates Foundation and national governments, aimed to give impetus to the universal vaccination campaign and to revitalise the fortunes of a stagnating market for new vaccines. The UK government is currently is largest single donor, having made a five-year pledge in 2020 of £1.65billion.
Its initial focus was on gaining the ‘long-term commitment of client governments and donors to full immunisation’, the latter implying vaccination on schedule and for every possible disease. This was different to its twin, the concept of universal vaccination.
When GAVI was launched, a UNICEF employee and anthropologist, Dr Heidi Larson – who would later found the Vaccine Confidence Project – was chosen to lead its vaccine communications and advocacy work.
She later explained how the nature of the advocacy was soon to evolve away from the initial focus on client governments.
‘There was a growing epidemic of individuals and communities and even some government officials questioning and refusing vaccines,’ she said. ‘I ended up getting the nickname “Director of UNICEF’s Fire Department,” because it turned out to be a crisis management position, because people weren’t taking vaccines.
‘I saw what seemed to be a trend: The northern Nigeria boycott of the polio program made it into the international press, but it wasn’t one place, it was everywhere.
‘I didn’t have time in my day job to investigate what was going on there, because there was not a quick fix. That’s when I put together a proposal and got some seed money and founded the Vaccine Confidence Project.’
There is no seminal document laying out a case for universal vaccination. As a public policy objective, it originated with the Rockefeller Foundation (RF). Its end goal is to eradicate diseases one-by-one via vaccination, the so-called vertical approach to public health introduced by the RF soon after its founding in 1913. It was part of a package of cheap, technological quick fixes for health care in developing countries originally called Selective Primary Health Care.
These interim measures were necessary because matching the industrialised world’s standards of sanitation, clean water, nutrition and health care to reduce the disease burden was ‘prohibitively expensive’.
An RF trustee, James P Grant, had been appointed executive director of UNICEF in 1980, operating it as a rival to the vaccine-agnostic World Health Organisation of his era.
In 1980, in an article on the eradication of smallpox, WHO director-general Dr Halfdan Mahler did not even mention vaccines. Rather, he stressed: ‘Smallpox eradication is a sign, a token, of what can be achieved in breaking out of the cycle of ill-health, disease and poverty.’
But Grant engaged in what the New York Times called ‘tireless, peripatetic proselytising’, using his UNICEF pulpit to zealously promote vaccination.
With rearguard reinforcement from the US Centres for Disease Control (CDC), by 1984 he had brought the WHO, the agency meant to provide the technical lead, on board with ‘universal’ vaccination.
Today, UNICEF is a quasi-arm of the pharmaceutical industry. Figures in its most recent Immunisation Roadmap document show it is now responsible for distributing 40 per cent of vaccines in developing countries, while its 659 staff spend more than half their time managing immunisation programmes and supply chain logistics.
In Part 2 tomorrow, I will explain how GAVI’s ten-year strategic plan, the Decade of the Vaccine, set out to eliminate vaccine scepticism.
Increased deaths in England for the age-range given the spring booster dose of Covid vaccine
Bartram’s Folly | May 5, 2022
I’ve mentioned previously that the roll out of a dose of vaccine has been associated with an increase in excess deaths (eg, here), and we seem to have seen the same effect in March.
At around the 21st March (week 12) England started to roll out the spring booster doses for those aged over 75 (and other vulnerable individuals). By the 7th April (week 14) the NHS had congratulated itself with the announcement that over 1 million doses had been given.
Here’s the data (from Euromomo) for excess deaths in England for those aged 75-85 since the start of the year:
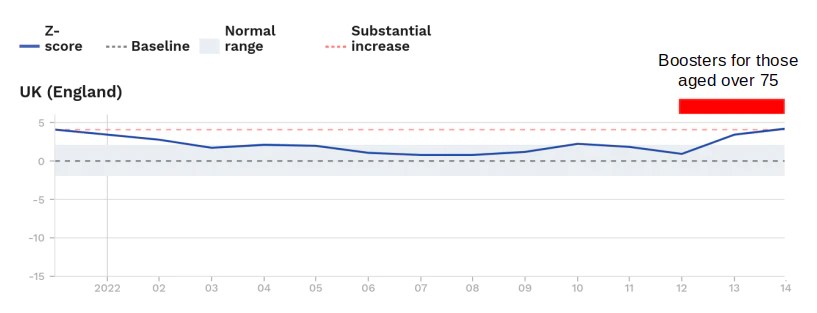
I’ve highlighted the period where the million booster doses were delivered.
I note that we managed to get through the Omicron wave in the UK with normal levels of excess deaths in those aged 75-85, but as soon as the booster doses were rolled out we rapidly hit the threshold for a ‘substantial increase’.
Of course, it might be a coincidence — we have had rather a lot of coincidences over the last 15 months.
Featured Video

When Israel Is Mighty
or go to
Aletho News Archives – Video-Images
From the Archives
US murdering 1 million Iraqis is democracy, Iran giving yogurt to Iraq is “domination”
By Ali Salaam | American Herald Tribune | July 31, 2017
The New York Times, owned by the Zionist Jewish supremacist Ochs-Sulzberger family, has no problem with Iraqi suffering as long as Iran is not the one behind it.
The Iraq War was a genocide of the Iraqi people by Zionist supremacists in the Bush administration. Over 1 million innocent people were killed based on a lie. American soldiers died in an Israeli war and now an average of 22 soldiers commit suicide every day because their consciences cannot cope with the fact they committed crimes in an illegal war that served no purpose other than to benefit Israel, not America.
Benjamin Netanyahu, Prime Minister of the Zionist regime, once said “We are benefiting from one thing, and that is the attack on the Twin Towers and Pentagon, and the American struggle in Iraq.”
Paul Wolfowitz had his sights on Iraq since his time in the first Bush administration. Former Israeli official and Bush administration official Richard Perle had his eyes on Iraq since at least his authorship of the Clean Break white paper. The Zionist regime had their eyes on Iraq since the 1980s when strategist Oded Yinon wrote his white paper in support of dividing the Arab-Muslim world along ethnic and sectarian lines. The global Zionist lobby has had their eyes on Iraq since Theodor Herzl stated that Eretz Israel’s true borders go from the Nile River in Egypt to the Euphrates River in Iraq. … continue
Blog Roll
 Aletho News
- MEP blasts ‘Euro-Gestapo’ for lecturing Russia on democracy
- Syria May Send Troops to Saudi Arabia Amid War with Ansar Allah
- UK whines about losing billions to ‘Putin tax’
- Baghaei to Rubio: Distorted narratives cannot erase US record of broken commitments
- Houthis Don’t Have to Conquer Saudi Arabia to Make It Pay
- MOE: Nearly 22,000 Students and Education Workers Killed
- Guterres in Islamabad: Genocide, cowardice, and the cage of Imran Khan
- Johnson, Marandi say Yemen holds upper hand over Saudi Arabia
- False flags won’t save aggressors, Iran FM spokesman says
- The Makkah Pact Enters Into Force: The End of American Dominance or Its New Form?
- If Americans Knew
- Report claimed Mark Levin used by Israeli government to influence Trump
- Over 2,000 Gazans have died awaiting medical evacuation amid Israel’s continued siege
- How a U.S. Diplomat Suppressed and Altered Reports Critical of Israel
- 5 Palestinians Die from Israeli Strikes in Gaza as Relentless Attacks Continue
- Report: Ceasefire Slows Killing but Leaves Devastation Intact
- Country Music Singer Zach Bryan Breaks Attendance Record at Robert Kraft’s Gillette Stadium While Wearing ‘Free Palestine’ Shirt for Second Night in a Row
- Three years of death and devastation: Israel’s war on Gaza in pictures
- Why Hamas believed the status quo was more dangerous than its 7 October gamble
- Debunking Israel’s latest list of ‘terrorist’ journalists in Gaza
- In Gaza, focus is on survival, “every step is a struggle” – Daily Update
- No Tricks Zone
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative

