The Sun newspaper is claiming this morning that it has seen “core planning documents,” which lay out plans to vaccinate children from September, in a bid to prevent a third wave of coronavirus.
A government source told The Sun that vaccinating children as young as five years-old is also being considered. The source told the newspaper that;
“Plans are in place to vaccinate children aged 12 upwards, and senior government officials have been briefed. Though controversial, it is deemed necessary to stop the UK regressing in its remarkable fight against Covid.”
The core planning documents also suggest that everyone over 50 should be offered a booster jab in the Autumn.
Children are virtually unaffected by coronavirus, but government scientists believe that they can pass it on to elderly relatives or vulnerable people. There is absolutely no evidence to support this claim.
Transmission rates did not increase when schools were reopened last Autumn, nor when they were reopened last month. There is zero evidence to back up the claim that asymptomatic people can spread the virus.
Why is the government hell-bent on vaccinating children for an illness that doesn’t affect them? Where are the paediatricians? The silence is deafening. The media, typically, is absent.
April 23, 2021
Posted by aletho |
Science and Pseudo-Science | Covid-19, COVID-19 Vaccine, UK |
Leave a comment
It’s the wrong time for US youths with higher education aspirations in mind.
On increasing numbers of US campuses, it’s hazardous to their health and well-being to enroll at colleges and universities whose policies may irreversibly harm them near-or-longer-term.
After Rutgers in March required students to be jabbed with experimental, high-risk, unapproved, rushed to market, DNA altering Pfizer or Moderna mRNA technology that risks irreversible harm to health, a dozen or more US schools of higher education went the same way.
By mandating the above, they’re putting their student body in harm’s way — irresponsibly and recklessly endangering them.
Affected students should transfer to a school that respects their health, and legal right to decide all things related to their well-being.
Schools mandating covid jabs are in breach of federal law and the Nuremberg Code.
The former requires that individuals may “accept or refuse administration of” experimental, unapproved drugs.
According to the Nuremberg Code, voluntary consent is required on all things related to health.
By ignoring the above, US schools that require students to be involuntarily jabbed for covid are in flagrant breach of these standards and contemptuous of the health and rights of their student body.
They include Rutgers, Northeastern, Fort Lewis College, St, Edward’s, Roger Williams, Nova Southeastern, Brown, Cornell, Yale, Columbia, and Columbia College, Chicago.
My esteemed alma mater Harvard University strongly urges students to be jabbed for covid, short of mandating it so far, saying:
“We continue to strongly recommend that you seek vaccination opportunities from all sources available to you to prevent further delay,” falsely adding the following:
“The safety of (covid jabs) is a top government priority (sic).”
Fact: Polar opposite is true, what Harvard suppressed.
Fact: Government mandates and recommendations since last year are intended to inflict harm on individuals following them, not the other way around.
Fact: They’re all about instituting draconian control.
Fact: Experimental covid mRNA technology and vaccines are bioweapons to depopulate the US and other nations of individuals dark forces want eliminated.
Covid jabs “will help protect you from getting” the viral infection (sic).
Fact: Jabs increase the likelihood of being infected. Harvard falsely claimed otherwise.
“(Y)ou may experience some side effects after receiving the injection (sic).
“This is a normal sign that your body is building protection (sic).”
Fact: Toxic jabs risk serious harm to health and no protection.
Fact: The more jabs, the greater the risk.
Fact: Jabs risk contraction of any number of serious diseases short-term or later on.
Fact: For the elderly with weak immune systems, allergic individuals and others, they can kill.
“The cost of the vaccine is covered by the government.”
Fact: To encourage mass-jabbing, US dark forces are incentivizing uninformed Americans to self-inflict harm.
Covid jabs “are one of many important tools to help us stop this pandemic (sic).”
“Once you’ve received your jab, continue to wear your mask and socially distance in public places (sic).
Fact: No pandemic exists, just normal annual outbreaks of seasonal flu-renamed covid to scare us into self-inflicting harm by following draconian mandates and recommendations.
Fact: Masks don’t protect and risk serious harm to health when worn longterm.
Fact: Social distancing provides no protection. It undermines normal interactions — essential to every day life.
Fact: It’s unnecessary and destructive of interpersonal relations, while providing nothing beneficial.
Voice of America, part of the US worldwide propaganda system, falsely said the following:
“The US Food and Drug Administration (FDA) has approved use of the Pfizer-BioNTech and Moderna vaccines (sic).”
False on two counts! These drugs are NOT vaccines.
They’re hazardous, experimental, unapproved DNA altering mRNA technology — given emergency use authorization when no emergency exists.
According to American College Health Association’s Covid Task Force co-chair Gerri Taylor:
“We would love for all our students to be vaccinated before they go home to either places in the US or places in other countries, because if they go there unvaccinated, they could actually carry the virus to their families and communities (sic).”
All of the above claims are part of the most widespread ever state-sponsored mass deception campaign to convince maximum numbers of unwitting people to follow a high-risk with no reward protocol.
Protecting and preserving health requires rejecting it.
Above all, it’s vital to health and well-being to refuse being jabbed with what’s unneeded and may cause irreversible harm if used as directed.
When I was on campus long ago — circa 1950s — nothing remotely like the above existed.
In college and graduate school, I recall no health-related mandates of any kind.
None should exist today beyond encouraging students not to self-inflict harm by following good health practices — not the other way around like what’s going on today.
A Final Comment
According to draconian Yale and Columbia diktats, students unwilling to be jabbed for covid will be barred from classrooms and prohibited from coming on campus — except for those with medical, religious or other exemptions.
Unacceptable policies instituted by the above colleges and universities may likely be mandated at many others in the coming weeks and months.
Instead of protecting students, they’ll be harmed near-or-longer-term, proving what’s unthinkable.
In the US, higher education is becoming hazardous to students instead of protecting and preparing them for endeavors they seek to pursue.
April 23, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science | Covid-19, COVID-19 Vaccine, Human rights, United States |
Leave a comment
While reports of side effects from COVID-19 gene therapies, including life-threatening effects and deaths, continue to climb at breakneck speed,1 a one-sided narrative of safety and effectiveness permeates mainstream media and medical news.
These “vaccines” are so safe and so effective, according to this narrative, that keeping control groups intact for long-term study and comparison of outcomes is now being derided as “unethical,” despite the fact that there is absolutely no non-fraudulent data to support their perverse assertions. Truly, what we’re watching is the active destruction of basic medical science in a surreal dystopian nightmare.
Vaccine Makers to Ditch Control Groups
Consider this report in JAMA by Rita Rubin, senior writer for JAMA medical news and perspectives, for example.2 According to Rubin, the launch of “two highly efficacious” COVID-19 vaccines has “spurred debate about the ethics, let alone the feasibility, of continuing or launching blinded, placebo-controlled trials …”
Rubin recounts how Moderna representatives told a Food and Drug Administration advisory panel that rather than letting thousands of vaccine doses to go to waste, they planned to offer them to trial participants who had received placebo.
Pfizer representatives made a similar announcement to the advisory panel. According to a news analysis published in The BMJ,3 the FDA and U.S. Centers for Disease Control and Prevention are both onboard with this plan, as is the World Health Organization.4
In the JAMA report by Rubin, Moncref Slaoui, Ph.D., chief scientific adviser for Operation Warp Speed, is quoted saying he thinks “it’s very important that we unblind the trial at once and offer the placebo group vaccines” because trial participants “should be rewarded” for their participation.
All of these statements violate the very basics of what a safety trial needs, which is a control group against which you can compare the effects of the drug or vaccine in question over the long term. I find it inconceivable that unblinding is even a consideration at this point, seeing how the core studies have not even concluded yet. The only purpose of this unblinding is to conceal the fraud that these vaccines are safe.
None of the COVID-19 vaccines currently on the market are actually licensed. They only have emergency use authorization — which, incidentally, also forbids them from being mandated, although this is being widely and conveniently ignored — as trials are still ongoing.
At the earliest, they may be licensed two years from now, at the completion of the follow-up studies.5 This is why those in the military are allowed to refuse it, and refuse they have. Among Marines, the refusal rate is nearly 40%.6
So, before the initial studies are even completed, vaccine makers and regulatory agencies are now deciding to forgo long-term safety evaluations altogether by giving placebo recipients the real McCoy, and so-called bioethicists are actually supporting this madness. As reported in The BMJ :7
“Although the FDA has granted the vaccines emergency use authorization, to get full license approval two years of follow-up data are needed. The data are now likely to be scanty and less reliable given that the trials are effectively being unblinded.”
Hypocrisy Abounds
It’s ironic in the extreme, because vaccine mandates are being justified on the premise that the benefit to the community supersedes the risk of individual harm. In other words, it’s OK if some people are harmed by the vaccine because the overall benefit to society is more important.
Yet here they’re saying that participants in the control groups are being harmed by not getting the vaccine, so therefore vaccine makers have an obligation to give it to them before the long-term studies are completed. This is the complete opposite argument used for mandatory vaccination.
If we are to accept the “greater good” justification for vaccination, then people who agree to participate in a study, and end up getting a placebo, need to roll the dice and potentially sacrifice their health “for the greater good.” Here, the greater good is the study itself, the results of which are of crucial importance for public health decisions.
Without this data, we will never know whether the vaccines work in the long term and/or what their side effects are. If an individual in the control group gets COVID-19, then that’s the price of scientific participation for the greater good of society, just as when a vaccinated person gets harmed, that’s considered an acceptable price for creating vaccine-induced herd immunity.
Put another way, when it comes to mandating vaccines, harm to the individual is acceptable, but when it comes to doing proper safety studies, all of a sudden, harm to the individual is not acceptable, and protecting the controls is more important than protecting the integrity of the research. The fact that they’re this inconsistent in their “ethics” could be viewed as proof positive that public health isn’t even a remote concern.
Scientific Ethics Are Eroding
Apparently, concern about risk to the individual only matters when vaccine makers have everything to gain. By eliminating control groups, we’ll have no way of really proving the harm that these “vaccines” might impart over time, as all participants will be in the same proverbial boat.
I remain confident that we’ll continue to see many more health problems and deaths develop in time, but without control groups, these trends can more easily be written off as “normal” and/or blamed on something else. As noted by Dr. Steven Goodman, associate dean of clinical and translational research at Stanford University, who is quoted in Rubin’s JAMA article:8
“By unblinding trial participants, ‘you lose a valid comparison group,’ Goodman said. ‘There will be this sense, and it will be sort of true, that the study is over.’ Unlike, say, a highly effective cancer drug, ‘the vaccine is not literally a life-and-death issue today and tomorrow’ for most trial participants, Goodman said.
So, he noted, those running COVID-19 vaccine trials shouldn’t feel obligated to unblind participants and vaccinate placebo recipients right away. Doing so implies ‘you can just blow up the trial’ on the basis of promising preliminary results, establishing ‘an ethical model for future trials that we maybe don’t want to set,’ Goodman said.”
Indeed, this strategy will set a dangerous precedent that will probably lead to vaccine and drug studies being conducted without control groups in the future, which could spell the end of medical science as we know it. At bare minimum, future variations of the current COVID-19 vaccine trials are likely to be conducted without control groups.
Trial Participants Told Not to Unblind Themselves
Goodman is also quoted in another article,9 this one in MedPage Today, discussing the problems with trial participants unblinding themselves by taking an antibody test:
“‘There is no good scientific reason for someone to do this,’ he told MedPage Today. ‘I can understand why they want that information, but it can only serve to diminish the value of the trial. Getting tested is not right unless there is a pressing need for unblinding for health reasons.'”
Here, yet another hypocritical irony arises, as the reason they don’t want trial participants to unblind themselves is because if they know they got the vaccine, they’re statistically more likely to take more risks that might expose them to the virus.
This, then, will skew the results and “could make the vaccine look less effective than it is,” Dr. Elizabeth McNally of Northwestern University explained to MedPage Today.10 So, whether vaccine scientists agree with unblinding or not, unblinding really only has to do with whether it will skew results in their favor.
Trial participants unblinding themselves might make the vaccine appear less effective if they alter their behavior as a consequence, whereas vaccine makers unblinding the entire control group will allow them to hide side effects, even if participants alter their behavior.
Justification for Elimination of Controls Is Flimsy at Best
While pro-vaccine advocates insist the elimination of control groups is justified on the “moral grounds” that it’s unethical to not provide volunteers with something of value, this argument completely ignores the undeniable fact that no vaccine is 100% safe.
Getting the active vaccine comes with risk, not merely benefit. This is particularly true for the novel mRNA technology used in COVID-19 vaccines. Historical data are troubling to say the least, and the U.S. Vaccine Adverse Event Reporting System (VAERS) is rapidly filling up with COVID-19 vaccine-related injury reports and deaths.
Reports of Side Effects and Deaths Are Piling Up
As reported by The Defender,11 as of April 1, 2021, VAERS had received 56,869 adverse events following COVID-19 vaccination, including 7,971 serious injuries and 2,342 deaths. Of those deaths, 28% occurred within 48 hours of vaccination! The youngest person to die was 18 years old. There were also 110 reports of miscarriage or premature birth among pregnant women.
As reported in “COVID-19 Vaccine To Be Tested on 6-Year-Olds,” between January 2020 and January 2021, COVID-19 vaccines accounted for 70% of the annual vaccine deaths, even though these vaccines had only been available for less than two months!
In my view, it’s unconscionable and morally reprehensible to not take these data into account. Clearly, these “vaccines” have risks. Pretending like they don’t, and that all placebo recipients in vaccine trials are at a distinct disadvantage simply isn’t true.
Keep in mind that we still do not know the percentage of adverse effects being reported. Is it between 1%12 and 10%13 as past inquiries into VAERS reporting have shown, or is it higher?
If only 10% are reported, we may be looking at 23,420 deaths, but if it is as low as 1%, it jumps to more than 230,000 deaths. We will never know because there are major attempts to suppress this information, as we have already witnessed with the deaths of sport celebrities Hank Aaron and Marvin Hagler, both of whom died shortly after COVID vaccinations.
Regardless, it’s hard to justify even a single death of an otherwise healthy individual, seeing how the survival rate for COVID-19 across all age groups is 99.74%. If you’re younger than 40, your survival rate is 99.99%.14
There’s every reason to suspect that these reports account for just a small percentage of actual side effects. Just think of all those who get the vaccine at grocery stores or temporary vaccination sites, for example. First of all, are all Americans even aware that VAERS exists and that they need to file a report if they suffer an adverse reaction post-COVID vaccination?
Who is going to file the adverse report if you get vaccinated in a grocery or convenience store? Will they return to the pharmacist and report their side effects? Will the pharmacist file the report? Who’s responsible for filing the report if you go to a temporary vaccination site?
Full article
April 22, 2021
Posted by aletho |
Deception, Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine |
Leave a comment
The Israeli People Committee (IPC), a civilian body made of leading Israeli health experts, has published its April report into the Pfizer vaccine’s side effects. The findings are catastrophic on every possible level.
Their verdict is that “there has never been a vaccine that has harmed as many people.” The report is long and detailed. I will outline just some of the most devastating findings presented in the report.
“We received 288 death reports in proximity to vaccination (90% up to 10 days after the vaccination), 64% of those were men.” Yet the report states, “according to data provided by the Ministry of Health, only 45 deaths in Israel were vaccine related.” If the numbers above are sincere then Israel, which claimed to conduct a world experiment, failed to genuinely report on its experiment’s results. We often hear about blood clots caused by the AstraZeneca vaccine. For instance, we learned this morning about 300 cases of blood clots in of Europe. However, if the IPC’s findings are genuine, then in Israel alone the Pfizer vaccine may be associated with more deaths than AstraZeneca’s in the whole of Europe.
“According to Central Bureau of Statistics data during January-February 2021, at the peak of the Israeli mass vaccination campaign, there was a 22% increase in overall mortality in Israel compared with the previous year. In fact, January-February 2021 have been the deadliest months in the last decade, with the highest overall mortality rates compared to corresponding months in the last 10 years.”
The IPC finds that “amongst the 20-29 age group the increase in overall mortality has been most dramatic. In this age group, we detect an increase of 32% in overall mortality in comparison with previous year.”
“Statistical analysis of information from the Central Bureau of Statistics, combined with information from the Ministry of Health, leads to the conclusion that the mortality rate amongst the vaccinated is estimated at about 1: 5000 (1: 13000 at ages 20-49, 1: 6000 at ages 50-69, 1: 1600 at ages 70+). According to this estimate, it is possible to estimate the number of deaths in Israel in proximity of the vaccine, as of today, at about 1000-1100 people.”
Again, if this statistical analysis is correct then the numbers reported by the Israeli health authorities are misleading by more than 22-fold.
Those who follow my writing are aware of my work on the undeniable correlation between vaccination, Covid-19 cases, deaths and the spread of mutant strains. The IPC confirms my observation, providing more crucial information regarding age groups. “There is a high correlation between the number of people vaccinated per day and the number of deaths per day, in the range of up to 10 days, in all age groups. Ages 20-49 – a range of 9 days from the date of vaccination to mortality, ages 50-69 – 5 days from the date of vaccination to mortality, ages 70 and up – 3 days from the date of vaccination to mortality.”
The IPC also reveals that the “the risk of mortality after the second vaccine is higher than the risk of mortality after the first vaccine.”
But death isn’t the only risk to do with vaccination. The IPC reveals that “as of the date of publication of the report, 2066 reports of side effects have accumulated in the Civil Investigation Committee and the data continue to come in. These reports indicate damage to almost every system in the human body.…Our analysis found a relatively high rate of heart-related injuries, 26% of all cardiac events occurred in young people up to the age of 40, with the most common diagnosis in these cases being Myositis or Pericarditis. Also, a high rate of massive vaginal bleeding, neurological damage, and damage to the skeletal and skin systems has been observed. It should be noted that a significant number of reports of side effects are related, directly or indirectly, to Hypercoagulability (infarction), Myocardial infarction, stroke, miscarriages, impaired blood flow to the limbs, pulmonary embolism.”
In Israel, the government is desperate to vaccinate children. The IPC stresses that such a move can be disastrous. “In light of the extent and severity of side effects, we would like to express the committee’s position that vaccinating children may also lead to side effects in them, as observed in adults, including the death of completely healthy children. Since the coronavirus does not endanger children at all, the committee believes that the Israeli government’s intention to vaccinate the children endangers their lives, health and their future development.”
The IPC stresses that “there has never been a vaccine that has affected so many people! The American VARES system presents 2204 mortality reports of vaccinated people in the United States in the first quarter of 2021, a figure that reflects an increase of thousands of percent from the annual average, which stood at 108 reports per year.”
I should mention that there has been very little coverage of the IPC’s work in the Israeli press. Those health experts are engaged in brave work, knowing that their license to work in the medical profession and livelihoods are at severe risk.
April 22, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine, Israel |
Leave a comment
A report from Yahoo News notes that airlines won’t be calling the imminent vaccine passports by that name because “It carries too many connotations,” according to one aviation CEO.
The forthcoming ‘digital certificates’ that will show COVID-19 vaccination status won’t be referred to as vaccination passports says Delta Air Lines CEO Ed Bastian, because that would turn people off.
Bastian declared that airlines are “more focused on a credential, travel credential, if you will, to indicate that you’ve been vaccinated and or tested based on the regulatory requirements.”
The CEO added that he expects “Either a vaccination or a test,” to be a requirement to travel, and airlines are “working with a number of technology providers to be able to facilitate that in an open source way.”
Right. A vaccine passport then.
That is exactly what the ID will be, but never mind, just call it something else to placate the sheeple and hope they remain only dimly aware of a certain unease in the air.
It’s the exact same policy that the UK government is adopting for the system which is slated not only for international travel but also domestically. We are also reliably informed that the vast majority of Brits are willing to accept vaccine passports in order to engage in basic day to day activities, and that they are willing to go along with the digital ID card system PERMANENTLY.
Recent surveys also indicate that almost half of Americans support the introduction of vaccine passports in order to get “back to normal.”
Airline consultant Mike Boyd warned that the companies “would rather not deal with this, but they need to express their points of view very carefully,” adding that creating a global protocol to enforce vaccine passports “could resemble a DMV [Department of Motor Vehicles] on steroids.”
The EU is already ensconced on the vaccine passport road, with a bloc wide ‘Digital Green Certificate’ system set to be rolled out in June.
April 21, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science | Covid-19, COVID-19 Vaccine, Human rights, UK, United States |
Leave a comment
In late March, Rutgers University president Jonathan Holloway explained the following:
Students arriving on campus this fall will be required to be jabbed for covid.
According to Holloway, it’s to “provide a safer and more robust college experience for our students (sic).”
There’s nothing remotely safe and effective about experimental, unapproved, hazardous mRNA technology or vaccines.
Covid is seasonal flu renamed.
Despite years of research, scientists never located an alleged SARS-CoV-2 virus claimed responsible for causing covid.
If not found, perhaps it doesn’t exist.
How then can what may not exist produce a virus or anything else harmful to health?
Covid and seasonal flu/influenza are two names for the same viral illness.
Their symptoms include coughing, shortness of breath, fatigue, sore throat, runny nose, muscle pains, body aches, headache, loss of taste, appetite, and/or smell, and at times vomiting and diarrhea.
Symptoms can be mild or more serious, the latter more likely for individuals over age-70.
Serious complications can include pneumonia, respiratory failure, sepsis, acute respiratory distress syndrome, cardiac injury, multiple organ failure, worsening of chronic medical conditions, inflammation of heart, brain or muscle tissues and secondary bacterial infections.
When occur, the elderly or others with weakened immune systems are most vulnerable.
Years earlier when flu killed up to 650,000 people worldwide in a six-month season, no shutdowns, quarantines, masks, social distancing, and mass-jabbing were called for and heavily promoted by media propaganda.
Yet all of the above and other draconian policies have been in place in the West and elsewhere since seasonal flu underwent a name change early last year.
In mid-April, Chicago-based Columbia College announced the following covid mass-jabbing policy:
For the fall semester beginning September 7:
Students residing on campus are required to be jabbed for covid before “mov(ing) in (to their) residence halls” this September.
All “Fall 2021” students must be jabbed for covid.
“International students already vaccinated in another country with a vaccine not approved by the (FDA) will not be required to be (jabbed), but (jabbing) will be made available to them.”
“The college’s health experts at Rush University Medical Center… advised… that it is safe (sic) for a person (jabbed) with another (covid drug) to be re-(jabbed) with (an) existing USFDA-approved” one.
There are none at this time, and Columbia failed to explain — FDA emergency use authorization alone when no emergency exists.
“International students who arrive (unjabbed) from another country will be required to begin a (jabbing) course upon arrival to campus.”
“(T)he college expects to start offering (covid mass-jabbing) on campus over the next two weeks.”
“The college anticipates its initial batch of doses to be the Pfizer” experimental, rushed to market, high-risk, DNA-altering mRNA technology Columbia falsely called a “vaccine.”
“Future doses may be Moderna(’s) (mRNA technology) or Pfizer.”
“Use of the Johnson & Johnson vaccine is currently suspended by federal and local health authorities.”
According to the CDC’s Vaccine Adverse Event Reporting System (VAERS), nearly 800 — potentially life-threatening — blood clots were experienced by individuals in the US jabbed with Pfizer, Moderna, or J & J covid drugs.
Overall from mid-December to April 8, over 68,000 adverse events and more than 2,600 deaths were reported.
According to HHS, these numbers captured “fewer than 1% of injuries.”
Actual numbers of adverse events over 100-times more than reported totals — harm on a massive scale, rising exponentially as long as this uncontrolled madness continues.
Columbia College added that “faculty and staff will not be required (to be jabbed for covid), but will be strongly encouraged.”
As explained to me by a Columbia faculty member on April 20, “compuls(ory) weekly PCR testing (will be) institute(d) for (unjabbed) faculty and staff…who will be on campus.”
What Rutgers announced weeks earlier, Columbia is now instituting — perhaps many more US colleges, universities, and public schools to follow.
Instituting this policy breaches federal law 21 USC § 360bbb-3(e)(1)(A)(ii)(III).
It requires that individuals may “accept or refuse administration of” experimental, unapproved drugs.
According to the Nuremberg Code, voluntary consent is required on all things related to health.
The FDA’s Fact Sheet on Pfizer’s mRNA technology states:
“It is your choice to receive or not receive (it). Should you decide not to receive it, it will not change your standard medical care.”
The same holds for other experimental covid jabs.
The Congressional Research Service states:
Private businesses (and other entities) are subject to civil liability unless they comply “with applicable directions, guidelines, or recommendations by the (HHS) secretary…”
Mandating covid jabs with experimental, unapproved drugs flagrantly breaches US federal law and the Nuremberg Code.
Yet unjabbed Columbia students — as well as faculty and staff not complying with weekly PCR tests — most likely will be barred from campus.
These policies — and today’s brave new world regimen — show indifference to health and well-being by ignoring the legal right of individuals to choose on all things related to health and well-being.
A Final Comment
Columbia College, my residential building, and other public places follow draconian/harmful to health federal, state of Illinois, as well as Chicago guidelines and mandates.
They include:
Masks that don’t protect and risk harm to health from longterm use.
PCR tests not designed to diagnose viral infections.
Social distancing that disrupts normal interactions.
Restrictions on numbers of people permitted to gather in public.
Disinfecting public places.
Travel restrictions.
Personal hygiene requirements and recommendations.
Workplace requirements.
Testing, jabbing and tracking.
Federal, state, and local policies are all about instituting social control, along with manipulating people to self-inflict harm.
They’re unrelated to protecting and preserving public health.
If that aim was prioritized, none of the above policies would have been instituted.
Not intended to be short-term, they’re highly likely to be in place longterm — perhaps permanently.
Forever mass-jabbing was planned, promoted by Pharma and their media press agents.
Two jabs aren’t enough. Drug companies called for annual or semi-annual booster jabs instead of flu shots — no longer needed after renaming the seasonal illness covid.
Left unexplained is that repeated jabs increase the risk of serious harm to health near-or-longer-term.
Protecting and preserving health requires refusal to play fast and loose with what’s too precious to lose.
April 21, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science, Timeless or most popular | Covid-19, COVID-19 Vaccine, Human rights, United States |
Leave a comment
Immoral vaccine passports serve the purpose of creating a biosecurity state with both government and private sector invasion of our rights.
April 21, 2021
Posted by aletho |
Civil Liberties, Timeless or most popular, Video | COVID-19 Vaccine |
Leave a comment
Nick Hudson, an actuary and private equity investor, co-founded Pandemics ~ Data & Analytics (PANDA) in response to the many threats to civil rights and freedoms that have occurred during the COVID-19 pandemic response. While media and public health institutions have engaged in a campaign of smoke and mirrors — one that is perpetuating paralyzing fear, needlessly, to this day — data and facts don’t lie.
Hudson and his team at PANDA, which include a data analyst, economist, medical doctors, big data analyst and public health experts, are using live data1 and open science to empower the public to exercise freedom of choice and preserve free societies.2
Hudson spoke at the inaugural BizNews Investment Conference in March 2021, and his keynote address is above. He explains the ugly truth about COVID-19, which is that the world is being crippled by fear due to a false narrative. Anyone who challenges that narrative is being labeled as a lunatic, a menace or a danger to society, which is furthering the repression and unjustified fear.
Bringing COVID-19 Truth to Light
George Washington famously said, “Truth will ultimately prevail where there are plans taken to bring it to light.”3 With that in mind, Hudson saw the “seeds of a great tragedy” being planted with the false COVID-19 narrative, and has made it a mission to get the truth out. So, what is the reality about the pandemic? According to Hudson:4
- A virus that presents high risk to few and negligible risk to most hit some regions
- Few are susceptible to severe disease
- There are several available treatments
- Asymptomatic people are not major drivers of disease
- Lockdowns and mask mandates haven’t worked and instead caused great harm
- The vulnerable were hurt instead of helped
The misinformation has been spewed from the beginning, including by World Health Organization director-general Tedros Adhanom Ghebreyesus. In a March 3, 2020, media briefing, he stated, “Globally, about 3.4% of reported COVID-19 cases have died. By comparison, seasonal flu generally kills far fewer than 1% of those infected.”5
But according to Hudson, the 3.4% represents case fatality rate (CFR), which is the number of deaths from COVID-19 divided by the number of cases of COVID-19, while the 1% is infection fatality rate (IFR), or the number of deaths divided by all infected individuals.
“By conflating these two separate points (CFR and IFR),” Hudson said, “Tedros was effectively lying.” Quantitative scientist John Ioannidis, professor of medicine at the Stanford Prevention Research Center, calculated the IFR for COVID-19 in a review of 61 seroprevalence studies, which was a median of 0.23%, and 0.05% in people younger than 70.6
Based on this, the IFR for COVID-19 is lower than that of the flu. And wouldn’t you know it, in a New England Journal of Medicine editorial published March 26, 2020, Dr. Anthony Fauci, director of the National Institute of Allergy and Infectious Diseases (NIAID), and colleagues wrote that “the overall clinical consequences of Covid-19 may ultimately be more akin to those of a severe seasonal influenza.”7
The media have suppressed this fact, Hudson noted, along with the fact that there’s a 1,000 times difference in mortality among those younger than 19 and those older than 70 — something that should have been taken into account in the pandemic response.
Is COVID-19 Really a ‘Novel Virus’?
Further inflaming widespread fear is the idea that COVID-19 is a “novel virus,” which makes it sound like it’s something humans have never encountered before. But is it really? According to Hudson:
“The reality is that the coronavirus is a very close relative, not even a separate subspecies, a very close relative of the 2003 SARS virus. There are seven related coronaviruses known to cause disease in humans, probably many others, and four of them are in general circulation.
Annual, global circulation. So the naming of this disease is terribly inconsistent. This is really a rose by any name, SARS. A variant of SARS. It’s not novel.”
One study even found that 81% of people not exposed to SARS-CoV-2, the virus that causes COVID-19, were still able to mount an immune response against it, which “suggests at least some built-in immune protection from SARS-CoV-2 …”8
Nonetheless, Maria Van Kerkhove, WHO’s technical lead for the COVID-19 pandemic, stated that “a majority of the world’s population is susceptible to infection from this virus.”9 This is the first of two key elements that, Hudson said, lead to “homosapienophobia” — the idea that everyone is dangerous until proven healthy.
The idea of universal susceptibility to COVID-19 is nonsense, Hudson noted, as was demonstrated early on with the Diamond Princess cruise ship. Among the 3,711 passengers and crew onboard the Diamond Princess, 712 (19.2%) tested positive for SARS-CoV-2, and of these 46.5% were asymptomatic at the time of testing. Of those showing symptoms, only 9.7% required intensive care and 1.3% (nine) died.10
PANDA data also showed that, starting in February 2021, there was not universal susceptibility to the virus. Their data showed cumulative COVID-19 deaths per million people. In Africa, Southeast Asia and Oceania, the population fatality rate was 112 per million compared to 710 per million in Europe and the Americas.
As for Africa, Southeast Asia and Oceania, Hudson said, “the population fatality rate there almost isn’t an epidemic. In a typical year, they’d have 10,000 deaths per million from all causes.”
Fear Mongering Over Asymptomatic Spread
The second element that enables the doctrine of “everyone being a danger” to continue is the idea of asymptomatic spread driving disease. “I was absolutely aghast to find out the poor quality of the science” behind it, Hudson said.
One of the seminal papers involved one woman who reportedly infected 16 colleagues while she was asymptomatic.11 The study was widely used to suggest that asymptomatic spread was occurring, but controversy later ensued over whether the woman was actually asymptomatic when the others were infected or if she was symptomatic and being treated for flu-like symptoms at the time.12
In June 2020, Kerkhove also made it very clear that people who have COVID-19 without any symptoms “rarely” transmit the disease to others. But in a dramatic about-face, WHO then backtracked on the statement just one day later. June 9, 2020, Dr. Mike Ryan, executive director of WHO’s emergencies program, quickly backpedaled Van Kerkhove’s statement, saying the remarks were “misinterpreted or maybe we didn’t use the most elegant words to explain that.”13
“It’s utter, utter nonsense,” Hudson said, adding that Fauci also stated in January 2020, “asymptomatic transmission has never been the driver of outbreaks. The driver of outbreaks is always a symptomatic person.”14
A JAMA Network Open study later found, in December 2020, that asymptomatic transmission is not a primary driver of infection within households.15 A study in Nature Communications also found “there was no evidence of transmission from asymptomatic positive persons to traced close contacts.”16
Lockdown Madness
The myth of widespread asymptomatic spread is what was used to justify worldwide lockdowns of healthy people. “Bruce Aylward will go down in history as a criminal of immense stature,” Hudson said, referring to Aylward’s role as the head of a WHO team that visited Wuhan, China, and concluded lockdowns were working to stop COVID-19 spread.17
“He takes a delegation to China, spends a few days, then comes back and says everyone should follow China’s response, the doctrine of universal susceptibility,” Hudson said. Yet, prior to the COVID-19 pandemic official guidelines for pandemic response plans recommend against large-scale quarantine of the healthy.
In fact, WHO wrote that during an influenza pandemic, quarantine of exposed individuals, entry and exit screening and border closure are “not recommended in any circumstance.”18
Likewise, in 2021 a study published in the European Journal of Clinical Investigation found no significant benefits on COVID-19 case growth in regions using more restrictive nonpharmaceutical interventions (NPIs) such as mandatory stay‐at‐home and business closure orders (i.e., lockdowns).19
Data compiled by PANDA also found no relationship between lockdowns and COVID-19 deaths per million people. The disease followed a trajectory of linear decline regardless of whether or not lockdowns were imposed.
What isn’t a lie, however, is that lockdowns cause a great deal of harm. Infant mortality, poverty, starvation and joblessness are on the rise, as are delays in medical treatment and diagnosis, psychological disorders among youth, suicide and deaths of despair.
Education has been disrupted for an estimated 1.6 billion children, Hudson said, and a survey of 2,000 U.S. adults revealed that 1 in 6 Americans started therapy for the first time during 2020. Nearly half (45%) of the survey respondents confirmed that the COVID-19 pandemic was the driving reason that triggered them to seek a therapist’s help.20 According to Hudson:
“Perhaps the hardest thing for me to swallow about all of this is in undergraduate epidemiology, it is a well-known finding that when you are confronted with a disease with sharp edge graduation, as you are with coronavirus, measures to generally suppress the spread of the disease have the effect, reliably, of shifting the disease burden onto the vulnerable, who we should be protecting. They worsen coronavirus mortality.”
Mask Rhetoric Is Misleading
It’s been touted that face masks are essential to stopping the spread of COVID-19 and could save 130,000 lives in the U.S. alone.21 But in 2019, the World Health Organization analyzed 10 randomized controlled trials and concluded, “there was no evidence that facemasks are effective in reducing transmission of laboratory-confirmed influenza.”22
Only one randomized controlled trial has been conducted on mask usage and COVID-19 transmission, and it found masks did not statistically significantly reduce the incidence of infection.23
You may remember that in the early days of the pandemic, face masks were not recommended for the general public. In February 2020, Christine Francis, a consultant for infection prevention and control at WHO headquarters, was featured in a video, holding up a disposable face mask.
She said, “Medical masks like this one cannot protect against the new coronavirus when used alone … WHO only recommends the use of masks in specific cases.”24 As of March 31, 2020, WHO was still advising against the use of face masks for people without symptoms, stating that there is “no evidence” that such mask usage prevents COVID-19 transmission.25
But by June 2020, the rhetoric had changed. Citing “evolving evidence,” WHO reversed their recommendation and began advising governments to encourage the general public to wear masks where there is widespread transmission and physical distancing is difficult.26 Yet that same day, June 5, 2020, WHO published an announcement stating:27
“At present, there is no direct evidence (from studies on COVID-19 and in healthy people in the community) on the effectiveness of universal masking of healthy people in the community to prevent infection with respiratory viruses, including COVID-19.”
The U.S. Centers for Disease Control and Prevention did a similar about-face on mask usage, citing a study of two hair dressers in Missouri, who were reportedly symptomatic with COVID-19 and styled 139 clients’ hair.
None of the clients tested positive for COVID-19, which the CDC suggested was because they and the stylists wore masks.28 Hudson believes, however, that the customers were probably young and not susceptible to the virus in the first place.
Another study published in the CDC’s journal Emerging Infectious Diseases stated, “We did not find evidence that surgical-type face masks are effective in reducing laboratory-confirmed influenza transmission, either when worn by infected persons (source control) or by persons in the general community to reduce their susceptibility.”29
PANDA data also showed no differences in transmission in states with mask mandates and those without. Still, health officials are now advising you should double or triple up on masks to make them work better.
Vaccines Being Sold as a Ticket to Freedom
People who stand to make countless billions out of COVID-19 vaccines are now selling them as a ticket to freedom, Hudson states:
“How convenient that we now have a logic that tells us that we need to vaccinate 7.8 billion people for a disease that has a mean survival rate of 99.95% for people under the age of 70. The profiteering here is naked. It is transparent.”
It’s a sad situation when teenagers, who aren’t at high risk, are lining up for vaccines just to get their freedoms back, he adds. When you add in all the other inconsistencies and lies — PCR tests that are not capable of diagnosing infectiousness, inflated death numbers, restrictions on travel, media propaganda and arbitrary rules, like the CDC’s recent change in physical distancing in classrooms from 6 feet to 3 feet30 — it’s as though we’re living in an Orwellian reality.
With looming vaccine passports, the loss of personal liberties is at an unprecedented level, while people are generally “enslaved by fear” — fear of infection or reinfection, “long COVID,” resurgence and mutant variants. “The underpinnings of our civilization are under threat,” Hudson noted, and we have a choice. “We’ve been pushed up against a precipice, will we be pushed off or will we push back?”
He urges people to support the Great Barrington Declaration, which calls for “focused protection” and finding a middle ground between locking down an entire economy and just “letting it rip.” As of April 4, 2021, the declaration has collected 41,890 signatures from medical practitioners and over 13,796 signatures from medical and public health scientists.31
In addition, the declaration is open for public signatures and has collected 764,089 from concerned citizens around the world. The website allows you to read and sign the declaration, answers many frequently asked questions, shares the science behind the recommendations and explains how the declaration was written.
PANDA also published a protocol for reopening society “to provide a road map out of the damaging cycle of lockdowns.”32 Hudson quoted Nelson Mandela, who stated courage is not the absence of fear, but the triumph over it. We all need to strive for courage and support awareness campaigns aimed at stopping the harmful narrative, relieving fear and protecting future freedom.
Sources and References
April 20, 2021
Posted by aletho |
Civil Liberties, Deception, Science and Pseudo-Science, Timeless or most popular | Covid-19, COVID-19 Vaccine |
Leave a comment
@DRutter: INVITE https://odysee.com/$/invite/@DRutter:9
https://odysee.com/@DRutter:9/moderna-vaccine-wreaks-havoc-on-lytton:7
Please listen to and share this powerful front-line testimony. Dr. Charles Hoffe of Lytton, British Columbia tells how the Moderna “vaccine” has decimated the health of his small town, after they had no trouble naturally fending off Covid last year. Now, many residents can’t sleep, their nerves burn with pain, their muscles won’t move properly, and their condition is worsening by the week. He lists his many concerns with these experimental products, and talks about how government officials have already sought to silence him. The interview was uploaded by Laura-Lynn Thompson.
Frontline Workers Testimonies & VAERs Reports 26 MAR 2021 – [PDF DOC]
https://odysee.com/@SixthSense-Truth-Search-Labs:0/informed-consent-matters:7
Polyethylene glycol as a cause of anaphylaxis [ingredient in COVID injections!] – PDF DOC
https://odysee.com/@SixthSense-Truth-Search-Labs:0/s13223-016-0172-7:f
Evidence for a Connection between COVID-19 and Exposure to Radiofrequency Radiation from Wireless Telecommunications [PDF DOC]
https://odysee.com/@SixthSense-Truth-Search-Labs:0/Rubik-Brown-COVID-19-and-RFR-SUBMITTED:f
COVID-19 RNA Based Vaccines and the Risk of Prion Disease – PDF DOC
https://odysee.com/@SixthSense-Truth-Search-Labs:0/covid19-rna-based-vaccines-and-the-risk-of-prion-disease-1503(2):b
Dr. Charles D. Hoffe, BSc, MB, BCh, LMCC
Lytton Medical Clinic
Lytton BC V0K 1Z0
5 April, 2021
OPEN LETTER
Dr. Bonnie Henry,
British Columbia Provincial Health Officer
Ministry of Health
1515 Blanchard Street
Victoria, BC, V8W 3C9
Dear Dr. Henry,
The first dose of the Moderna vaccine has now been administered to some of my patients in the community of Lytton, BC. This began with the First Nations members of our community in mid-January, 2021. 900 doses have now been administered.
I have been quite alarmed at the high rate of serious side-effects from this novel treatment.
From this relatively small number of people vaccinated so far, we have had:
- Numerous allergic reactions, with two cases of anaphylaxis.
- One (presumed) vaccine induced sudden death, (in a 72 year old patient with COPD. This patient complained of being more short of breath continually after receiving the vaccine, and died very suddenly and unexpectedly on day 24, after the vaccine. He had no history of cardiovascular disease).
- Three people with ongoing and disabling neurological deficits, with associated chronic pain, persisting for more than 10 weeks after their first vaccine. These neurological deficits include: continual and disabling dizziness, generalised or localized neuromuscular weakness, with or without sensory loss. The chronic pain in these patients is either generalised or regional, with or without headaches.
So in short, in our small community of Lytton, BC, we have one person dead, and three people who look as though they will be permanently disabled, following their first dose of the Moderna vaccine. The age of those affected ranges from 38 to 82 years of age.
So I have a couple of questions and comments:
- Are these considered normal and acceptable long term side-effects for gene modification therapy? Judging by medical reports from around the world, our Lytton experience is not unusual.
- Do you have any idea what disease processes may have been initiated, to be producing these ongoing neurological symptoms?
- Do you have any suggestions as to how I should treat the vaccine induced neurological weakness, the dizziness, the sensory loss, and the chronic pain syndromes in these people, or should they be all simply referred to a neurologist? I anticipate that many more will follow, as the vaccine is rolled out. This was only phase one, and the first dose.
- In stark contrast to the deleterious effects of this vaccine in our community, we have not had to give any medical care what-so-ever, to anyone with Covid-19. So in our limited experience, this vaccine is quite clearly more dangerous than Covid-19.
- I realize that every medical therapy has a risk-benefit ratio, and that serious disease calls for serious medicine. But we now know that the recovery rate of Covid-19, is similar to the seasonal flu, in every age category. Furthermore, it is well known that the side effects following a second shot, are significantly worse than the first. So the worst is still to come.
- It must be emphasised, that these people were not sick people, being treated for some devastating disease. These were previously healthy people, who were offered an experimental therapy, with unknown long-term side-effects, to protect them against an illness that has the same mortality rate as the flu. Sadly, their lives have now been ruined.
- It is normally considered a fundamental principal of medical ethics, to discontinue a clinical trial if significant harm is demonstrated from the treatment under investigation.
- So my last question is this: Is it medically ethical to continue this vaccine rollout, in view of the severity of these life altering side-effects, after just the first shot? In Lytton, BC, we have an incidence of 1 in 225 of severe life altering side-effects, from this experimental gene modification therapy.
I have also noticed that these vaccine induced side effects are going almost entirely unreported, by those responsible for the vaccine rollout. I am aware that this is often a problem, with vaccines in general, and that delayed side-effects after vaccines, are sometimes labelled as being “coincidences”, as causality is often hard to prove. However, in view of the fact that this is an experimental treatment, with no long-term safety data, I think that perhaps this issue should be addressed too.
Furthermore I have noticed, that the provincial vaccine injury reporting form, which was clearly designed for conventional vaccines, does not even have any place to report vaccine injuries of the nature and severity that we are seeing from this new mRNA therapy.
It is now clearly apparent with medical evidence from around the world, that the side-effect profiles of the various gene modification therapies against Covid-19, have been vastly understated by their manufacturers, who were eager to prove their safety.
Thank you for attention to this critically urgent public health matter.
Yours sincerely,
Dr. Charles Hoffe
April 20, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular, Video | Canada, COVID-19 Vaccine, Human rights |
Leave a comment
Will a vaccine to SARS-CoV-2 actually make the problem worse? Although not a certainty, all of the current data says that this prospect is a real possibility that needs to be paid careful attention to. If you stay with me, I’ll explain why.
First, let’s set aside the debate surrounding the topic of whether vaccines work and the negative health consequences due to the components of the vaccine. No matter where you stand on the vaccine issue, I’m not asking anyone to capitulate on this point. I’m just asking that this issue be set aside, because in this instance this argument is completely irrelevant. Even without bringing any other issue into the vaccine debate, a coronavirus vaccine is a highly dangerous undertaking due to a peculiar trojan horse mechanism known as Antibody Dependent Enhancement (ADE). Regardless of someone’s conviction about vaccines, this point needs to be acknowledged. In the remaining portion of this article, I’m going to explain how ADE works and the future perils it may bring.
For a vaccine to work, our immune system needs to be stimulated to produce a neutralizing antibody, as opposed to a non-neutralizing antibody. A neutralizing antibody is one that can recognize and bind to some region (‘epitope’) of the virus, and that subsequently results in the virus either not entering or replicating in your cells.
A non-neutralizing antibody is one that can bind to the virus, but for some reason, the antibody fails to neutralize the infectivity of the virus. This can occur, for example, if the antibody doesn’t bind tightly enough to the virus, or the percentage of the surface area of the virus covered by the antibody is too low, or the concentration of the antibody is not high enough. Basically, there is some type of generic binding of the antibody to the virus, but it fails to neutralize the virus.
In some viruses, if a person harbors a non-neutralizing antibody to the virus, a subsequent infection by the virus can cause that person to elicit a more severe reaction to the virus due to the presence of the non-neutralizing antibody. This is not true for all viruses, only particular ones. This is called Antibody Dependent Enhancement (ADE), and is a common problem with Dengue Virus, Ebola Virus, HIV, RSV, and the family of coronaviruses. In fact, this problem of ADE is a major reason why many previous vaccine trials for other coronaviruses failed. Major safety concerns were observed in animal models. If ADE occurs in an individual, their response to the virus can be worse than their response if they had never developed an antibody in the first place.
An antibody can be rendered a non-neutralizing antibody simply because it doesn’t bind to the right portion of the virus to neutralize it, or the antibody binds too weakly to the virus. This can also occur if a neutralizing antibody’s concentration falls over time and is now no longer of sufficient concentration to cause neutralization of the virus. In addition, a neutralizing antibody can subsequently transition to non-neutralizing antibody when encountering a different strain of the virus.
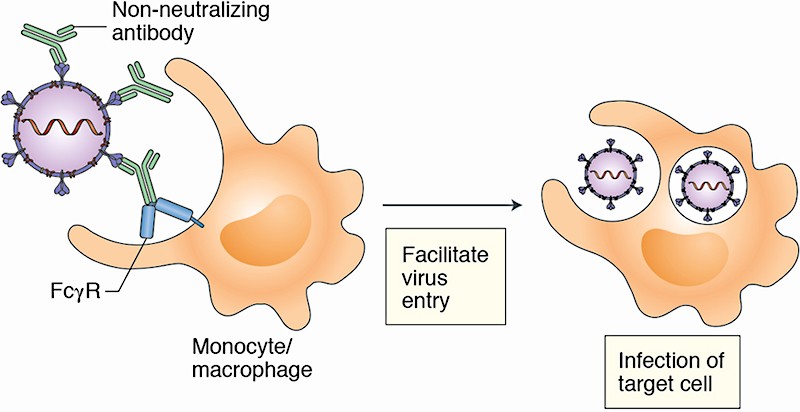
What does ADE entail? The exact mechanism of ADE in SARS is not known, but the leading theory is described as follows: In certain viruses, the binding of a non-neutralizing antibody to the virus can direct the virus to enter and infect your immune cells. This occurs through a receptor called FcγRII. FcγRII is expressed on the outside of many tissues of our body, and in particular, in monocyte derived macrophages, which are a type of white blood cell. In other words, the presence of the non-neutralizing antibody now directs the virus to infect cells of your immune system, and these viruses are then able to replicate in these cells and wreak havoc on your immune response. One end of the antibody grabs onto the virus, and the other end of the antibody grabs onto an immune cell. Essentially, the non-neutralizing antibody enables the virus to hitch a ride to infect immune cells. You can see this in the picture above.
This can cause a hyperinflammatory response, a cytokine storm, and a general dysregulation of the immune system that allows the virus to cause more damage to our lungs and other organs of our body. In addition, new cell types throughout our body are now susceptible to viral infection due to the additional viral entry pathway facilitated by the FcγRII receptor, which is expressed on many different cell types.
What this means is that you can be given a vaccine, which causes your immune system to produce an antibody to the vaccine, and then when your body is actually challenged with the real pathogen, the infection is much worse than if you had not been vaccinated.
Again, this is not seen in all viruses, or even in all strains of a given virus, and there is a great deal that scientists don’t understand about the complete set of factors that dictate when and if ADE may occur. It’s quite likely that genetic factors as well as the health status of the individual may play a role on modulating this response. That being said, there are many studies (in the reference section below) that demonstrate that ADE is a persistent problem with coronaviruses in general, and in particular, with SARS-related viruses. Less is known, of course, with respect to SARS-CoV-2, but the genetic and structural similarities between the SARS-CoV-2 and the other coronaviruses strongly suggests that this risk is real.
ADE has proven to be a serious challenge with coronavirus vaccines, and this is the primary reason many have failed in early in-vitro or animal trials. For example, rhesus macaques who were vaccinated with the Spike protein of the SARS-CoV virus demonstrated severe acute lung injury when challenged with SARS-CoV, while monkeys who were not vaccinated did not. Similarly, mice who were immunized with one of four different SARS-CoV vaccines showed histopathological changes in the lungs with eosinophil infiltration after being challenged with SARS-CoV virus. This did not occur in the controls that had not been vaccinated. A similar problem occurred in the development of a vaccine for FIPV, which is a feline coronavirus.
For a vaccine to work, vaccine developers will need to find a way to circumvent the ADE problem. This will require a very novel solution, and it may not be achievable, or at the very least, predictable. In addition, the vaccine must not induce ADE in subsequent strains of SARS-CoV-2 that emerge over time, or to other endemic coronaviruses that circulate every year and cause the common cold.
A major trigger for ADE is viral mutation. Changes to the amino acid sequence of the Spike Protein (which is the protein on the virus that facilitates entry into our cells via the ACE2 receptor) can cause antigenic drift. What this means is that an antibody that was once neutralizing can become a non-neutralizing antibody because the antigen has slightly changed. Therefore, mutations in the Spike protein that naturally occur with coronaviruses could presumably result in ADE. Since these future strains are not predictable, it is impossible to predict if ADE will become a problem at a future date.
This inherent unpredictability problem is highlighted in the following scenario: A coronavirus vaccine may not be dangerous initially. If the initial testing looks positive, mass vaccination efforts would presumably be administered to a large portion of the population. In the first year or two, it may appear that there is no real safety issue, and over time, a greater percentage of the world population will be vaccinated due to this perceived “safety”. During this interim period, the virus is busy mutating. Eventually, the antibodies that vaccinated individuals have floating around in their bloodstream are now rendered non-neutralizing because they fail to bind to the virus with the same affinity due to the structural change resulting from the mutation. Declining concentrations of the antibody over time would also contribute to this shift towards non-neutralization. When these previously vaccinated people are infected with this different strain of SARS-CoV-2, they could experience a much more severe reaction to the virus.
Ironically, in this scenario, this vaccine made the virus more pathogenic rather than less pathogenic. This is not something that vaccine producers would be able predict or test for with any level of real confidence at the outset, and it would only become evident at a later time.
If and when this does occur, who will be liable?
Does this vaccine industry know about this problem? The answer is yes, they do.
Quoting a Nature Biotechnology news article published on June 5th, 2020:
““It’s important to talk about it [ADE],” says Gregory Glenn, president of R&D at Novavax, which launched its COVID-19 vaccine trial in May. But “we can’t be overly cautious. People are dying. So we need to be aggressive here.””
And from the same article:
“ADE “is a genuine concern,” says virologist Kevin Gilligan, a senior consultant with Biologics Consulting, who advises thorough safety studies. “Because if the gun is jumped, and a vaccine is widely distributed that is disease enhancing, that would be worse than actually not doing any vaccination at all.””
The vaccine industry is aware of this problem. The degree to which they are taking it seriously, is another question.
While many vaccine developers are aware of the problem, some of them are approaching the problem with more Laissez-faire attitude. They see this problem as “theoretical,” and not guaranteed, with the idea that animal trials should rule out the potential of ADE in humans.
As a side note, it is not ethical to conduct “challenge” studies in humans. However, challenge studies are conducted in animals. In other words, a clinical trial for a vaccine does not include administering the vaccine to a person, and then exposing this person to the virus post-vaccination to monitor their reaction. In clinical trials, humans are only given the vaccine, they are not “challenged” with the virus afterward. In animal studies, they do conduct a challenge test to observe how the animals respond to being infected with the actual virus after being vaccinated.
Will conducting animal studies solve the issue and remove the risk?
Not at all.
Anne De Groot, CEO of EpiVax argues that testing for vaccine safety in primates does not guarantee safety in humans, mainly because primates express different major histocompatibility complex (MHC) molecules, which alters epitope presentation and the immune response. Animals and humans are similar, but they are also very different. In addition, as pointed out above, the development of different viral strains in subsequent years could present a major problem not noticeable during the initial safety trials in either humans or animals.
What about unvaccinated people who are naturally infected with the virus and develop antibodies? Could these people experience ADE to a future strain of SARS-CoV-2?
The ADE response is actually much more complicated than the picture I outlined above. There are other competing and non-competing factors in our immune system that contribute to the ADE response, many of which are not fully understood. Part of that equation is a variety of different types of T-cells that modulate this response, and these T-Cells respond to other portions (epitopes) of the virus. In a vaccine, our body is normally presented with a small part of the virus (like the Spike protein), or a modified (attenuated or dead) virus which is more benign. A vaccine does not expose the entirety of our immune system to the actual virus.
These types of vaccines will only elicit antibodies that recognize the portion of the virus which is present in the vaccine. The other portions of the virus are not represented in the antibody pool. In this scenario, it is much more likely that the vaccine-induced antibodies can be rendered as non-neutralizing antibodies, because the entire virus is not coated in antibodies, only the portion that was used to develop the vaccine.
In a real infection, our immune system is exposed to every nook and cranny of the entire virus, and as such, our immune system develops a panacea of antibodies that recognize different portions of the virus and, therefore, coat more of the virus and neutralize it. In addition, our immune system develops T-Cell responses to hundreds of different peptide epitopes across the virus; whereas in the vaccine the plethora of these T-Cell responses are absent. Researchers are already aware that the T-Cell response plays a cooperative role in either the development of, or absence of, the ADE response.
Based on these differences and the skewed immunological response which is inherent with vaccines, I believe that the risk of ADE is an order of magnitude greater in a vaccine-primed immune system rather than a virus-primed immune system. This will certainly become more apparent as COVID-19 progresses over the years, but the burden of proof rests on the shoulders of the vaccine industry to demonstrate that ADE will not rear its ugly head in the near term or the far term. Once a vaccine is administered and people develop antibodies to some misrepresentation of the virus, it cannot be reversed. Again, this is a problem that could manifest itself at a later date.
Although this article focused on the problem of ADE, it is not the only pathway or mechanism that could present a problem for people being infected after vaccination. Another pathway is governed by Th2 immunopathology, in which a defective T-cell response initiates an allergic inflammation reaction. A second pathway is based on the development of faulty antibodies that form immune complexes, which then activate the complement system a consequently damage the airways. These pathways are also potential risks for SARS-CoV-2.
Right now, the fatality rate of the virus is estimated to be approximately 0.26%, and this number seems to be dropping as the virus is naturally attenuating itself through the population. It would be a great shame to vaccinate the entire population against a virus with this low of a fatality rate, especially considering the considerable risk presented by ADE. I believe this risk of developing ADE in a vaccinated individual will be much greater than 0.26%, and, therefore, the vaccine stands to make the problem worse, not better. It would be the biggest blunder of the century to see the fatality rate of this virus increase in the years to come because of our sloppy, haphazard, rushed efforts to develop a vaccine with such a low threshold of safety testing and the prospect of ADE lurking in the shadows. I would hope (and this is a big hope), that this vaccine WILL NOT BE MANDATORY.
Hopefully, you now know a little more about the topic of Antibody Dependent Enhancement, and the real, unpredictable dangers of a coronavirus vaccine. In the end, your health should be your decision, not some bureaucrat’s that doesn’t know the first thing about molecular biology.
REFERENCES
Garber K. Coronavirus vaccine developers wary of errant antibodies. Nature Biotechnology. 2020 Jun 5.
Wan, Yushun, et al. “Molecular mechanism for antibody-dependent enhancement of coronavirus entry.” Journal of virology 94.5 (2020)
Yang, Zhi-yong, et al. “Evasion of antibody neutralization in emerging severe acute respiratory syndrome coronaviruses.” Proceedings of the National Academy of Sciences 102.3 (2005): 797-801.
Ulrich, Henning, Micheli M. Pillat, and Attila Tárnok. “Dengue Fever, COVID‐19 (SARS‐CoV‐2), and Antibody‐Dependent Enhancement (ADE): A Perspective.” Cytometry Part A (2020).
Wang, Sheng-Fan, et al. “Antibody-dependent SARS coronavirus infection is mediated by antibodies against spike proteins.” Biochemical and biophysical research communications 451.2 (2014): 208-214.
Tseng C Te, Sbrana E, Iwata-Yoshikawa N, Newman PC, Garron T, Atmar RL, et al. Immunization with SARS coronavirus vaccines leads to pulmonary immunopathology on challenge with the SARS virus. PLoS ONE. (2012) 7:35421.
Tetro, Jason A. “Is COVID-19 receiving ADE from other coronaviruses?.” Microbes and infection 22.2 (2020): 72-73
Hohdatsu, Tsutomu, et al. “Antibody-dependent enhancement of feline infectious peritonitis virus infection in feline alveolar macrophages and human monocyte cell line U937 by serum of cats experimentally or naturally infected with feline coronavirus.” Journal of veterinary medical science 60.1 (1998): 49-55.
Leung, Hiu-lan, Nancy. Mechanism of antibody-dependent enhancement in severe acute respiratory syndrome coronavirus infection (Thesis). The University of Hong Kong Libraries.
Yip, M. S., et al. “Antibody-dependent enhancement of SARS coronavirus infection and its role in the pathogenesis of SARS.” Hong Kong Med J 22.3 Suppl 4 (2016): 25-31.
Yip, Ming Shum, et al. “Antibody-dependent infection of human macrophages by severe acute respiratory syndrome coronavirus.” Virology journal 11.1 (2014): 1-11.
Corapi, WAYNE V., C. W. Olsen, and FREDRIC W. Scott. “Monoclonal antibody analysis of neutralization and antibody-dependent enhancement of feline infectious peritonitis virus.” Journal of virology 66.11 (1992): 6695-6705.
Takano, Tomomi, et al. “Antibody-dependent enhancement of serotype II feline enteric coronavirus infection in primary feline monocytes.” Archives of virology 162.11 (2017): 3339-3345.
Yip, Ming S., et al. “Investigation of Antibody-Dependent Enhancement (ADE) of SARS coronavirus infection and its role in pathogenesis of SARS.” BMC Proceedings. Vol. 5. No. S1. BioMed Central, 2011.
Fierz, Walter, and Brigitte Walz. “Antibody dependent enhancement due to original antigenic sin and the development of SARS.” Frontiers in immunology 11 (2020).
Ricke, Darrell, and Robert W. Malone. “Medical countermeasures analysis of 2019-nCoV and vaccine risks for antibody-dependent enhancement (ADE).” Available at SSRN 3546070 (2020).
Jaume, Martial, et al. “Anti-severe acute respiratory syndrome coronavirus spike antibodies trigger infection of human immune cells via a pH-and cysteine protease-independent FcγR pathway.” Journal of virology 85.20 (2011): 10582-10597.
Peron, Jean Pierre Schatzmann, and Helder Nakaya. “Susceptibility of the Elderly to SARS-CoV-2 Infection: ACE-2 Overexpression, Shedding, and Antibody-dependent Enhancement (ADE).” Clinics 75 (2020).
Yong, Chean Yeah, et al. “Recent advances in the vaccine development against Middle East respiratory syndrome-coronavirus.” Frontiers in microbiology 10 (2019): 1781.
Wang, Qidi, et al. “Immunodominant SARS coronavirus epitopes in humans elicited both enhancing and neutralizing effects on infection in non-human primates.” ACS infectious diseases 2.5 (2016): 361-376.
Olsen, CHRISTOPHER W., et al. “Monoclonal antibodies to the spike protein of feline infectious peritonitis virus mediate antibody-dependent enhancement of infection of feline macrophages.” Journal of virology 66.2 (1992): 956-965.
Hotez, Peter J., Maria Elena Bottazzi, and David B. Corry. “The potential role of TH17 immune responses in coronavirus immunopathology and vaccine-induced immune enhancement.” (2020).
Morens DM. Antibody-dependent enhancement of infection and the pathogenesis of viral disease. Clin Infect Dis. (1994) 19:500–12
Liu L, Wei Q, Lin Q, Fang J, Wang H, Kwok H, Tang H, Nishiura K, Peng J, Tan Z, et al. Anti‐spike IgG causes severe acute lung injury by skewing macrophage responses during acute SARS‐CoV infection. JCI Insight.2019;4(4):e123158.
de Alwis R, Chen S, Gan ES, Ooi EE. Impact of immune enhancement on Covid‐19 polyclonal hyperimmune globulin therapy and vaccine development. EBioMedicine2020;55:102768.
April 18, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine |
Leave a comment
When the United States government’s Food and Drug Administration earlier this week called for temporarily halting the giving of Johnson & Johnson’s experimental coronavirus vaccine shots because of the developing of blood clots in people who have received the shots, I asked if we were seeing an example of regulatory favoritism for the new mRNA technology shots over more traditional vaccine shots such as the Johnson & Johnson shots. The question arises because the US government is still encouraging everyone to take experimental mRNA “vaccines” from Moderna and Pfizer-BioNTech regarding which there are also many reports of injury and death.
While a variety or injuries and deaths have been reported after people have taken experimental coronavirus vaccine shots developed respectively by the three companies, if you focus in on just blood clot problems, those problems appear to arise after Moderna and Pfizer-BioNTech experimental coronavirus shots as well as after Johnson & Johnson shots.
Megan Redshaw wrote Friday at the Children’s Health Defense website regarding adverse events reported to the Vaccine Adverse Event Reporting System (VAERS) related to the blood clots in people who had taken any one of the three companies’ experimental vaccines:
Children’s Health Defense queried the VAERS data for a series of adverse events associated with the formation of clotting disorders and other related conditions. VAERS yielded a total of 795 reports for all three vaccines from Dec. 14, 2020, through April 8.Of the 795 cases reported, there were 400 reports attributed to Pfizer, 337 reports with Moderna and 56 reports with J&J — far more than the eight J&J cases under investigation, including the two additional cases added Wednesday.
As The Defender reported today, although the J&J and AstraZeneca COVID vaccines have been under the microscope for their potential to cause blood clots, mounting evidence suggests the Pfizer and Moderna vaccines also cause clots and related blood disorders. U.S. regulatory officials were alerted to the problem as far back as December 2020.
So why the different treatment for the Moderna and Pfizer-BioNTech shots?
Copyright © 2021 by RonPaul Institute
April 17, 2021
Posted by aletho |
Corruption, Science and Pseudo-Science | COVID-19 Vaccine, United States |
Leave a comment

 Aletho News

