Before 2020, evidence for the efficacy of community masking – that is, asking ordinary members of the public to wear cloth or surgical masks when going about their business – was shaky at best.
This evidence was reviewed in detail by Jeffrey Anderson, a former director of the Bureau of Justice Statistics. He notes that:
of the 14 RCTs that have tested the effectiveness of masks in preventing the transmission of respiratory viruses, three suggest, but do not provide any statistically significant evidence in intention-to-treat analysis, that masks might be useful. The other eleven suggest that masks are either useless—whether compared with no masks or because they appear not to add to good hand hygiene alone—or actually counterproductive.
In another piece that’s well worth reading, Professor Steve Templeton provides a list of quotations from what he calls “the BP era” (Before Things Got Political). Each quotation, taken from one or other expert, testifies to the lack of evidence that community masking works against respiratory pathogens.
For example, in a systematic review published early last year, Jingyi Xiao and colleagues “did not find evidence that surgical-type face masks are effective in reducing laboratory-confirmed influenza transmission, either when worn by infected persons… or by persons in the general community to reduce their susceptibility”.
This is presumably why, at the start of the COVID-19 pandemic, health authorities in both the U.K. and the U.S. advised against community masking.
For example, on 4th March 2020, Chris Whitty told Sky News that “wearing a mask if you don’t have an infection reduces the risk almost not at all”. And as late as 3rd April, Jonathan Van Tam said “there is no evidence that general wearing of face masks… affects the spread of the disease”.
Likewise, in a tweet sent on 27th February, the CDC said that it “does not currently recommend the use of facemasks”. And two days later, the U.S. Surgeon General urged people to “STOP BUYING MASKS” because they are “NOT effective” at preventing the general public from catching coronavirus.
In a video interview from May of 2019, Anthony Fauci actually laughed at the notion of wearing a face mask. The interviewer asks him, “The best way for me to prevent getting an infectious disease… is what? Wearing a mask?” To which Fauci replies, “No, no no… you avoid all the paranoid aspects.”
Yet by the summer of 2020, the health authorities in both countries had done an about-face, and were now recommending face masks to the public. These recommendations subsequently became mandates.
‘The Science,’ in other words, had changed. But what prompted this change? The charitable answer is that new evidence emerged suggesting that community masking does work against SARS-CoV-2. However, this new evidence looks just as shaky – if not shakier – than the pre-Covid evidence.
I suspect that something else happened. Back in the spring of 2020, all Western countries were on the same upward trajectory, with cases doubling every few days. Meanwhile, Japan, Korea, Hong Kong and Singapore had all manged to ‘flatten the curve’, despite eschewing draconian lockdowns.
Commentators were searching around for an explanation, and ‘masks’ seemed like a good one. After all, Western health authorities had advised against masks. Yet many East Asians had been wearing them for years.
If you were on social media at that time, you probably remember seeing a version of this chart, which went viral numerous times:
Putting ‘correlation doesn’t equal causation’ aside, it appears to suggest that masks are the crucial factor for bringing COVID under control. Of course, the subsequent imposition of mask mandates in Western countries didn’t forestall large winter outbreaks, which rather undermines the mask theory.
Nonetheless, it seemed plausible enough at the time. And articlesbeganappearinginmajornewsoutlets that questioned the West’s reluctance to wear face masks. On social media, commentators asked why we shouldn’t follow the East Asian countries, given their far greater success in handling the pandemic.
I suspect this pressure had more to do with the health authorities’ about-face than any fundamental change in the quality of evidence. It was another case of ‘politician’s logic’. ‘Something must be done; mask-wearing is something; therefore we must do it.’
In a matter of weeks, ‘The science’ went from ‘don’t do X’ to ‘do X’. And yet it took another whole year for the first RCT of community masking to be published. The theory I’ve outlined is speculative, of course. But I don’t see what else can account for such a sudden shift in public health advice.
This week, the Australian Federal Health Minister announced a commitment to COVID-19 vaccines for kids aged 5 to 11 years pending TGA-approval, after Pfizer claimed, in a press release, that it had obtained “favourable” results.
Pfizer’s ongoing Phase 2/3 trial apparently showed the vaccine “was safe, well tolerated and showed robust neutralising antibody responses”. However, the results were not submitted to the drug regulator, nor were they published in a medical journal, so for now, we must take their word for it.
Pfizer registered the trial plan, showing that it tested a lower dose (10µg) as well as two higher doses (20µg and 30µg) in 5- to 11-year-olds. Whether the vaccine can provide protection against symptomatic disease or severe COVID-19 remains to be seen.
The manufacturer also claimed that the vaccine had a “favourable safety profile”, however, it is important to note that the trial has not enrolled enough children (2,268) to detect any rare but serious harms that might arise from the vaccine
Only healthy kids were recruited in the trial – children with known or suspected immunodeficiency, a history of autoimmune disease, any condition associated with prolonged bleeding, anyone receiving treatment with immunosuppressive therapy or corticosteroids were excluded from the trial.
Notably, these are the same cohort of children who have been prioritised for the vaccine.
Despite little to no data available for its safety and efficacy, the Israeli Ministry of Health gave the green light to start vaccinating high risk 5- to 11-year olds with the lower-dose (10µg) of the vaccine.
Pfizer senior vice-president Dr Bill Gruber said he felt “a great sense of urgency” in the process, and Pfizer’s CEO Albert Bourla said trial data would be submitted to the various international drug regulators for “immediate authorisation.”
The language of Pfizer executives, the frenzied press coverage, and the political will of Governments, is all designed to pressure drug agencies to fast-track authorisations.
Younger than 5 years old?
Pfizer announced that trial data involving children under 5 are expected later this year.
Last week, Cuba began vaccinating toddlers as young as 2, using its homegrown vaccine, the Soberana 02, from the Finlay Vaccine Institute administered at adult doses. To my knowledge, there has been no data from Phase III trials published in the peer-reviewed literature in children as young as 2 with this vaccine.
China’s drug agency has cleared three COVID-19 vaccines produced by Sinopharm and Sinovac and is vaccinating children aged 3 years and older, under emergency use authorisation.
12- to 15-year-olds
Most major western nations have authorised COVID-19 vaccines for those aged 12 years and older.
In Australia for example, children aged 12 to 15 years began receiving the mRNA vaccines last week. According to the NSW Premier, 20% of children in the state of NSW have already had their first jab.
They require a two-dose regimen, the same dose given to adults, which aligns with the US FDA and Health Canada advisories on vaccines for this age group. (See my previous analysis for 12-15yr olds)
This does not align with the UK’s more cautious approach. After significant political and media pressure, UK chief medical officers recommended a single dose of the Pfizer vaccine, because of concerns about rare side effects such as heart inflammation.
Brazil appears to be an outlier at the moment. It was reported that the Minister for Health called for the suspension of the COVID-19 immunisation of people aged 12 to 17 after the death of a 16-year old girl named Isabelli Borges Valentim, eight days after she received the Pfizer shot. Authorities are still investigating the incident but the drug regulator denies any link to the vaccine.
Myocarditis/Pericarditis
This issue has stirred up some heated debate.
Now that real world data is becoming widely available, myocarditis (inflammation of the heart muscle) and pericarditis (inflammation of the membrane surrounding the heart) are being reported as rare harms related to the Pfizer & Moderna mRNA vaccines.
Israel, because of its fast vaccine roll-out, was first to raise the alarm – 148 cases of myocarditis were reported within 30 days of immunisation, more commonly after the second jab. It prompted the Israeli Ministry of Health to launch an investigation into any possible link between these cases of myocarditis and vaccination.
Since then, other countries such as the UK, the US and Canada have corroborating data.
In June, the US FDA decided that the link between the mRNA vaccines and myocarditis, particularly in young males, was sufficiently clear that it revised its vaccine fact sheets to include a warning.
The CDC released data showing the incidence of “expected” versus “observed” incidences of myocarditis and pericarditis and found a significant increase in the observed rates. The graph shows the higher rates in red (see table numbers circled in red).
Another study, published in JAMA which looked at data from 40 hospitals in the US showed a similar pattern to the CDC, although at higher incidences, suggesting that the vaccine’s adverse events were being underreported.
Researchers then took a more granular look at the database for reported adverse events (VAERS database) between 1 January and 18 June, and found boys aged 12-15 years vaccinated with their second shot of the mRNA vaccine, with no underlying medical conditions were 4 to 6 times more likely to develop a cardiac adverse event, than ending up in hospital with COVID-19.
The study was published as a pre-print online but it ignited a twitter storm, with critics claiming the study ‘over-estimated’ the risk and it was biased because one of the authors belonged to a group that did not support making vaccines compulsory.
Sceptics say that most of the myocarditis cases are mild, and that children recover quickly from hospitalisation. Others are not so quick to dismiss the potential risk of ‘sub-clinical disease’ (myocarditis without symptoms) in children.
Notably, a retrospective multi-centre study across 16 US hospitals including patients <21 years of age with a diagnosis of myocarditis following COVID-19 vaccination, found concerning abnormalities in heart tissue (the left ventricle) (See image with yellow arrows).
Jain SS, et al doi: 10.1542/peds.2021-053427.
Careful monitoring is required to see if these abnormalities lead to fibrosis, which can have long-term implications for young patients.
Early findings suggest that post-vaccination myocarditis could be mediated by the toxicity of ‘spike protein’ on heart muscle cells or from circulating spike proteins in plasma after vaccination.
The risk of myocarditis associated with contracting COVID-19 infection may be higher than that after vaccination, but more research is needed to weigh harms against benefit.
If we don’t vaccinate kids, what about long COVID?
The fear of long-COVID has been a major impetus behind vaccinating kids.
A recent review by Monash University, analysing 14 international studies on long COVID in children and adolescents, found no difference in the symptoms reported by those who had experienced COVID-19 and those who had not.
Lead researcher on the study, Professor Nigel Curtis told newsGP the review’s findings should be reassuring for parents and carers.
Similarly, a webinar hosted by The BMJ revealed the results of the largest citizen-scientist participation study to date in young children. It used a smartphone app to monitor the illness and symptoms of children after testing positive to COVID-19.
The researchers found that the median duration of illness was 6 days. Only 4.4% of children had illness duration >28 days and 1.8% had symptoms >56 days. Encouragingly, their symptom ‘burden’ was greatly reduced by this time (none became worse) with the most common symptoms being headache and fatigue.
The researchers looked at neurological symptoms such as epileptic seizures, convulsions, impaired attention and concentration, but none were reported.
Lead investigator on the study, Prof Emma Duncan from Kings College in London concluded “Long illness duration of COVID-19 in children is uncommon.”
Vaccine Mandates for kids
Despite COVID-19 vaccine mandates for teachers in places such as New York and Australia (Victoria and New South Wales), no Federal government has announced plans to make the vaccines compulsory for children (yet).
Canadian and English professors have argued that making COVID-19 vaccines mandatory for children, will “encourage uptake”.
U.S. Surgeon General Vivek Murthy has also suggested that COVID-19 vaccine mandates for students could happen at the state and local level in the US, once they have been approved for paediatric use by the US FDA.
In a surprise announcement this week, the Los Angeles public school system said students aged 12 and older will now have to be double-vaccinated by the end of the year, to attend classes on campus or take part in sports and other extracurricular activities. It remains to be seen whether other school districts will follow.
Consent from kids
Before the age of 14, minors are generally thought to lack the cognitive capacity and maturity to make rational judgments about their health.
In fact, most US state laws presume that minors lack medical decision-making capacity and therefore require parental consent for most health care decisions, including vaccination, with some exceptions.
However, in the case of COVID-19, under what is termed ‘Gillick competency’, those under 16 years can make independent decisions about a medical treatment if they can demonstrate they have the capacity to consent, even if their parent withholds consent.
This applies to every Australian state and territory as part of the ‘common law’ and in the UK.
The Victorian government has produced ‘communication packs’ for teachers and educators on how to ‘promote’ COVID-19 vaccines to minors.
Hopefully, the conversations about COVID-19 vaccines, between health professionals and minors, are conducted without coercion, pressure or judgment.
Not surprisingly, this has raised the age-old question about who is better placed to determine the best medical treatment for a child – a parent or a Government minister?
The debate will continue and experts will need to wade through muddy waters to find a balance between protecting children’s health and the uncertainty over the long-term harms of the vaccine.
The Met Office’s website describes the work they do, rambling on about forecasting the weather and world leading science. Nowhere can I find any reference to publishing fake news or disseminating misleading propaganda.
According to the Cambridge Dictionary:
Decline = change to a lower amount
Continues = keeps happening
So the meaning of that headline is crystal clear:
Arctic sea ice keeps getting less.
One look at their graph shows this is patently not true, despite grossly misleading linear fit, intended to fool people.
It is very easy to show that Arctic sea ice has stabilised. As their graph itself shows, there have only been three years since 2007 with lower ice extent than that year, and eleven have had higher extents.
Also the average of the last ten years is higher than 2007’s extent.
In itself, this is too short a period to make any meaningful judgements. But that is no excuse for the Met Office to publish such a manifest falsehood.
I have left a comment on their blog, but as is usual it is blocked. Maybe Richard Betts would care to comment!
The British government is expected start adding fluoride to the drinking water all over the country according to a story in the Guardian.
The story focuses on a joint statement the Chief Medical Officers (CMOs) of England, Scotland, Wales and Northern Ireland published on Thursday, which recommends everyone, everywhere should have fluoride added to their water supply.
The report was already praised in a tweet from UK Health Secretary Sajid Javid:
Good to see UK CMOs examining how water fluoridation can improve oral health & prevent tooth decay which disproportionately affects more deprived groups.
Reinforces why our Health and Care Bill will make it simpler to expand water fluoridation schemes.https://t.co/jKCqGtFmMr
While fluoridation is already in place in some parts of the UK, it has always been considered a matter for local government and currently affects less than 10% of the country.
Proposed changes to the regulations in sections 128-129 of the new Health and Care Bill would centralise this power, taking the decision out of the hands of local councils and handing it to the Health Secretary.
The authors of the report, including England’s CMO Chris Whitty (who we are more than familiar with, thanks to Covid) are not subtle in their attempts to cloak the proposed policy in “progressive” camouflage.
Statistics on tooth decay in children and the working class are trotted out so fluoridation could be sold as both “protecting children” and tackling “entrenched inequality”.
But what is the real risk-reward situation for fluoridated tap water?
Well, the only potential benefit of fluoride is preventing tooth decay. That’s it. (And even then, over-exposure to fluoride can actually damage your teeth through dental fluorosis).
The potential side effects of fluoride toxicity are far more dangerous than needing a root canal.
There is some evidence fluoride could increase the risk of cancer – a 2006 study found an increased risk of osteosarcoma in young boys – but the most serious problem associated with fluoride is developmental neurotoxicity.
In 2012 a study from the Harvard School of Public Health found fluoride exposure is detrimental to the intellectual development of children, with an author of the study saying [emphasis added]:
Fluoride seems to fit in with lead, mercury, and other poisons that cause chemical brain drain. The effect of each toxicant may seem small, but the combined damage on a population scale can be serious, especially because the brain power of the next generation is crucial to all of us.”
The results found that children raised in areas with widespread water fluoridation had markedly lower average IQs than children from areas with no fluoride in the water:
This pilot study in a community with stable lifetime fluoride exposures supports the notion that fluoride in drinking water may produce developmental neurotoxicity
To sum up: Fluoride in the water could potentially make future generations of people compliant, gullible and stupid.
Or, in other words, it’s the perfect thing to start pumping into the water when you’ve just tried to launch a global coup, and not enough people are falling for it.
It’s official: I am spouting misinformation about the Covid vaccines. Full Fact – the Google, Facebook and George Soros-funded outfit that Ofcom has said it relies on to tell it what to censor regarding COVID-19 – has ‘fact checked‘ my recent piece on PHE data showing negative vaccine effectiveness in August and branded it “incorrect”.
Writer Leo Benedictus – henceforth to be known as the Oracle – takes particular issue with the headline, which he says “falsely claims that a report from Public Health England (PHE) shows the COVID-19 vaccines having ‘negative effectiveness’ in the over-40s”.
“This is not true about the COVID-19 vaccines – nor is it true that the PHE report shows this,” the Oracle declares. Except it is. The data contained in the report is completely clear, and the calculation of unadjusted vaccine effectiveness from that data is straightforward.
According to the Oracle, however, this is not a valid way of estimating vaccine effectiveness. Benedictus quotes the PHE report stating as much – “The vaccination status of cases, inpatients and deaths is not the most appropriate method to assess vaccine effectiveness and there is a high risk of misinterpretation” – and notes that I too quote this. What he fails to acknowledge, though, is that I also examine the reason PHE gives for this claim and counter it.
The only substantive reason PHE gives that vaccine effectiveness might be underestimated in its data is that “vaccination has been prioritised in individuals who are more susceptible or more at risk of severe disease”. In other words, the high-risk are over-represented in the vaccinated and this skews the sample. I countered that the large majority of the older age groups are now vaccinated so this bias should be very much reduced. Of course, we also need to ask why, if this is supposedly the key confounder of the data presented, we are not also provided with the necessary data on risk categories so that it can be duly quantified and accounted for.
Benedictus reiterates PHE’s claim that vaccine effectiveness should only be estimated via the published studies. However, as I noted in my article, these studies are riddled with serious problems and inconsistencies that bring their findings into question. They are also out of date since they don’t cover the Delta surge, which is the first time the vaccines have really been stress-tested in the U.K.
Benedictus spends half the ‘fact check’ in a bizarre attempt to argue that my vaccine effectiveness calculation is wrong because I used the data PHE itself used for the size of the unvaccinated population. He points out it is different to the ONS figures on this. Er, take that one up with PHE, Leo.
It does seem at times that Benedictus is fact-checking the PHE report rather than my article. At one point he takes the report to task because one of its charts sowed confusion as it “seemed to show for the month in question (August 9th to September 5th) that people in their 40s, 50s, 60s and 70s were more likely to test positive for Covid if they had been vaccinated than if they hadn’t”.
Except the chart didn’t ‘seem’ to show that; it did show that. Again though we are told that this data does “not give a reliable estimate of vaccine effectiveness” because of biases in the samples.
But who defines what makes an estimate of vaccine effectiveness ‘reliable’ enough to be permitted without being labelled false? All vaccine efficacy estimates have limitations arising from the limitations of the data, including those produced by PHE. I was careful to acknowledge the limitations of the estimates I was making, saying they were unadjusted for risk factors – though argued that this shouldn’t matter so much anymore given high coverage. There’s also the point that being high-risk may affect the risk of serious disease and death but there’s no reason to think it will have an impact on infection rates (save for the small number of immuno-compromised).
The unmistakable impression here is of a gatekeeping exercise by the Government and its outriders to ensure it controls the concept of vaccine effectiveness and no one unauthorised is allowed to make an estimate of it. Thus the availability of the data is carefully controlled and we only get a month at a time and without the additional data that would allow us to control for the supposed biases that the report tells us the data includes and which ‘invalidate’ any attempt to make an unauthorised calculation of vaccine effectiveness.
None of this concept-policing does anything to alter the facts, however. In recent weeks reported infection rates have been higher in the double vaccinated than in the unvaccinated for the over-40s. That means that, for this period, (unadjusted) vaccine effectiveness is negative in those age groups.
PHE has published two new reports since my article and in each the unadjusted vaccine efficacy has declined further. Here is the table using data from the latest report, covering August 23rd to September 19th (the related chart from the report itself is above).
It shows that in the two weeks since my article the vaccine effectiveness has dropped further, with unadjusted vaccine effectiveness in the over-40s now hitting as low as minus-53% among people in their 60s. This means that, on this data for this age group, the double vaccinated experienced a 53% higher reported infection rate than the unvaccinated in the past month. And that’s a fact.
Stop Press: Professor Norman Fenton and Professor Martin Neil on the Probability and Risk site have used age-adjusted all-cause mortality to estimate vaccine effectiveness and found that mortality rates are currently higher in the vaccinated than the unvaccinated.
Stop Press 2: Professor David Paton has produced a good Twitter thread responding to one of the more well-informed critics of this (and other) pieces citing the PHE data.
The scene: a British nuclear submarine. A detective has been sent to investigate the death of a sailor. When she asks the Naval Commander why there needs to be so much secrecy, as Britain is not at war, he responds ‘That is an illusion. We have always been at war’.
The series, entitled ‘Vigil’ is the BBC’s most watched drama of the year, and has been well publicised, attracting an audience of 10.2 million over its first week. It depicts a fight with an illusive, ruthless adversary that successfully manages to infiltrate a UK submarine to ‘knock out Britain’s nuclear deterrent’, killing British citizens in the process. The murder weapon of choice is a nerve agent; can you guess who the enemy is yet?
Of course it’s Russia. Nuclear submarines, nerve agent, a treacherous opponent; from the opening sequence with video footage of Vladimir Putin and Dmitry Medvedev projected onto a submarine, the audience is under no illusion as to who this adversary is. Nowadays, the British public almost expects it to be Russia.
For years now the UK population has been schooled on ‘evil Russia’ across all media platforms – from the news to TV dramas to films – with the line between fiction and reality becoming increasingly blurred. One of the most Googled questions about the ‘Vigil’ drama series is ‘is it real?’ This is hardly surprising given the sheer volume of anti-Russian content, with cinema often dramatising real life events and vice versa.
Take the Skripal case, for instance. The apparent poisoning with ‘Novichok’ of the former spy Sergei Skripal and his daughter took place just a few months after a British/American TV series ‘Strike Back’ was released, in which a ‘rogue Russian biochemist‘ was working on a substance of the very same name. That was probably the first time that western audiences had ever heard the word ‘Novichok’, and yet, by extraordinary coincidence, it was to appear on our TV screens just a few months later, in the news. The finger of blame was immediately pointed at Moscow, just as preparations were being made for Russia to host the 2018 world cup. The timing could not have been worse for the Kremlin, and yet it helped Britain considerably in its bid to discredit Russia in its hosting of the sporting event.
TV and cinema being used by governments as instruments to sway and foster public opinion is nothing new. In the book ‘Propaganda and empire: the manipulation of British public opinion, 1880-1960’ John M MacKenzie explores the plethora of ways the British government promoted imperialism throughout the empire’s existence, not only through cinema, but using everything from cigarette cards to school textbooks. During the war, the British Ministry of Information also pumped out films with instructive government messaging under the direction of Humphrey Jennings. These documentaries were more about what to do and what not to do, promoting slogans such as ‘grow your own’ and ‘make do and mend’ to aid the war effort on the home front.
The ‘Vigil’ drama obviously had a considerable budget. And its political function is twofold; it highlights the ‘threat’ from Russia, and the question of the Trident’s future in an independent Scotland. By playing up the idea of a real, imminent danger from Russia, it persuades the viewer of the importance of retaining Britain’s nuclear deterrent. As tensions grow between East and West, and Boris Johnson pursues his ‘Global Britain’ strategy, we will no doubt see more programmes emphasising Britain’s military strength countering Russia and let’s not forget, China. Sadly, such manipulation of the population doesn’t encourage understanding between peoples and instead, fosters division and discrimination. At best it is Britain using Russia as a scapegoat to bolster its sense of national pride; at worse, it is laying the groundwork for a future conflict with Russia.
Johanna Ross is a journalist based in Edinburgh, Scotland.
Did you see the recent hype on the latest cholesterol-lowering confection from Pharma? No data whatsoever to suggest it will improve heart disease outcomes, but UK NICE body has pronounced that billions will be spent on it regardless? Well here Dr. Aseem Malhotra and Dr. Malcolm Kendrick lay bare the latest lipid scam on GB news!
With all medical eyes on COVID19, a cardiovascular drug with no proven benefit – at all – has been approved by NICE (The UK National Institute for Health and Care Excellence). Once a drug is approved by NICE it can, and will, be prescribed by doctors in England and Wales and Northern Ireland.
… approving drugs, or launching drugs before you have any evidence that they do anything – other than having a favourable effect on an established lipid biomarker – is ridiculous. But never mind, longer term studies on Inclisiran will be completed by 2023, and 2026. When will they actually be published?
Who cares, by the time they are published, Inclisiran will have made billions, and no-one will care if the results are positive, or negative, as it will have become established as ‘standard’ treatment.
A number of us found the NICE approval of Inclisiran so ridiculous that we wrote them a letter. … Read full article
England’s Chief Medical Officer Chris Whitty wants to add fluoride to the nations’s water supply. Whitty is a prominent member of SAGE, the group of scientists that has been advising the government since the beginning of the scamdemic.
Whitty recently overruled the Joint Committee on Vaccination and Immunisation (JCVI) on jabbing 12 to 15 year-olds. The JCVI said there was little benefit to the kids being jabbed. Whitty and his mates said, “We’ll just see about that.”
On Wednesday, Dr. Caroline Johnson asked Whitty why he was so hellbent on jabbing kiddies. She asked him to explain why he wasn’t testing youngsters first, to see if they’d had covid-19. Her logic being, that if they’d had the virus, they’d hardly need the jab.
Whitty floundered. He had no answer. He was also at a loss to explain why half the literature being presented to the parents of children, made no mention of the risk (1 in 6,000) of myocarditis. Whitty is desperately keen to jab the UK’s children. Whitty is one sinister and creepy little dude.
The Guardian is reporting this morning, that Whitty intends to fluoridate the UK’s drinking water. Apparently, he’s concerned about tooth decay. The Guardian reports:
Chris Whitty, the chief medical officer for England, and his counterparts in Wales, Scotland and Northern Ireland cited estimates by Public Health England that adding more fluoride to water supplies would reduce cavities by 17% among the richest children and 28% among the poorest.
They also dismissed safety concerns saying there is no evidence that ionised form of the element fluorine causes cancer and condemned “exaggerated and unevidenced” suggestions about health risks.
Chris Whitty and the UK’s chief medical officers represent a clear and present danger to the country’s children. Fluoride can be devastating for the neurodevelopment of youngsters. Whitty and his pals know this. They know it.
In 2012, Harvard University’s Department of Environmental Health, led by Anna Choi, published a study that claimed fluoride exposure led to lower IQ’s in children. Harvard found that on average, children with higher fluoride exposure performed poorer in IQ tests.
Nutritional psychologist Tetsuo Nakamoto published a paper in 2018, that investigated how fluoride exposure in the young can lead to disease in later life. Nakamoto’s team collated all the existing studies on fluoride and reviewed them.
He concluded that there is evidence that fluoride exposure can lead to lower IQ’s in children. He also acknowledged that fluoride accumulates in the pineal gland which can lead to calcification. The pineal gland produces melatonin, a hormone which regulates sleep.
Two years ago, a Canadian study of prenatal fluoride exposure found that there is a link between fluoride exposure during pregnancy and IQ. Expecting mothers exposed to the chemical were more likely to have children with lower than average IQ’s.
The UK’s chief medical officers know all of this. They KNOW. So why are they calling for fluoride to be added to the nation’s water supply? I think the answer is obvious. I’ll be getting into this in more detail on The Richie Allen Show next week.
It seems that ever since Hillary Clinton lost to Donald Trump in the U.S. presidential election of 2016 the western media and numerous politicians have been working especially hard to convince the world that the Russian government is little better than a modern version of Josef Stalin’s USSR. Part of the effort can be attributed to the Democratic Party’s desire to blame someone other than the unattractive candidate Hillary for the defeat, but there is also something more primitive operating behind the scenes, something like a desire to return to a bipolar world in which one knew one’s enemies and one’s friends.
The anti-Russian bias has manifested itself in a number of ways, to include the fabricated libel referred to as Russiagate, but it also featured personal denigration of the Russian leadership as a rogue regime inclined to employ assassination by poisoning against its critics and political opponents.
The first widely publicized assassination of a Russian dissident took place in London in 2006. Alexander Litvinenko, a former Federal Security Service (FSB) officer and critic of the government who had sought asylum in England, died after he met two Russian acquaintances in a hotel bar and was reportedly poisoned by a dose of radioactive polonium inserted into his cup of tea. The Russians whom he had met with were named by the British police but the Russian government refused extradition requests. Without any evidence, the British media claimed that Litvinenko had been killed under orders from Putin personally.
More recently, the poisoning of former Russian intelligence agent Sergei Skripal and his daughter Yulia on March 4th, 2018 made headlines around the world. Sergei was living near Salisbury England and his daughter was visiting from Moscow when they were found unconscious on a park bench. A policeman later investigating the incident also suffered from the effects of what appeared to be a nerve agent, which investigative sources claimed had been sprayed on to the front door handle of the Skripal residence. Both Sergei and Yulia survived the incident.
There was quite a bit that was odd about the Skripal case, which came at a time when there was considerable tension between Russia and the NATO allies over issues like Syria and Ukraine. Russian President Vladimir Putin was regularly demonized, seen in the western media as a malevolent presence stalking the world stage.
Observers noted that the British investigation of the poisoning relied from the start “… on circumstantial evidence and secret intelligence.” And there was inevitably a rush to judgment. British Foreign Secretary Boris Johnson blamed Russia before any chemical analysis of the alleged poisoning could have taken place. British Prime Minister Theresa May told Parliament shortly thereafter to blame the Kremlin and demand a Russian official response to the event in 36 hours, declaring that the apparent poisoning was “very likely” caused by a made-in-Russia nerve agent referred to by its generic name novichok. The British media was soon on board, spreading the government line that such a highly sensitive operation would require the approval of President Putin himself. Repeated requests by Russia to obtain a sample of the alleged nerve agent for testing were rejected by the British government in spite of the fact that a military grade nerve agent would have surely killed both the Skripals as well as anyone else within 100 yards.
The expulsion of scores of Russian diplomats and imposition of sanctions soon followed with the United States and other countries following suit. The report of the new sanctions was particularly surprising as Yulia Skripal had subsequently announced that she intends to return to her home in Russia, leading to the conclusion that even one of the alleged victims did not believe the narrative being promoted by the British and American governments.
The response within the United States was also immediate and threatening. A New York Timeseditorial on March 12th entitled Vladimir Putin’s Toxic Reach thundered: “The attack on the former spy, Sergei Skripal, who worked for British intelligence, and his daughter Yulia, in which a police officer who responded was also poisoned, was no simple hit job. Like the 2006 murder of Alexander Litvinenko, another British informant, who was poisoned with radioactive polonium 210, the attack on Mr. Skripal was intended to be as horrific, frightening and public as possible. It clearly had the blessing of President Vladimir Putin, who had faced little pushback from Britain in the Litvinenko case. The blame has been made clearer this time and this attack on a NATO ally needs a powerful response both from that organization and, perhaps more important, by the United States.”
But the story of the poisoning of the Skripals began to come apart very quickly. Former UK Ambassador Craig Murray detailed how the narrative was cooked by “liars” in the government to make it look as if the poisoning had a uniquely Russian fingerprint. Meanwhile prize winning U.S. investigative reporter Gareth Porter summed up the actual evidence or lack thereof, for Russian involvement, suggesting that the entire affair was “based on politically-motivated speculation rather than actual intelligence.”
The head of Britain’s own top secret chemical weapons facility Porton Down even contradicted claims made by May and Johnson, saying that he did not know if the nerve agent was actually produced in Russia as the chemical formula was revealed to the public in a scientific paper in 1992 and there were an estimated twenty countries capable of producing it. Some speculated that a false flag operation by the British themselves, the CIA or Mossad, was not unthinkable. Development of novichok type poisons is known to have taken place at both Porton Down and at the U.S. chemical weapon facility Fort Dietrich Maryland.
But the most damning evidence opposing a Russian role in the alleged poisonings was that Moscow had no motive to kill a former British double agent who had been released from a Kremlin prison in a spy swap after ten years in prison and who was no longer capable of doing any damage. If Moscow had wanted him dead, they could have killed him while he was still in Russian custody. Putin had an election coming up and Russia was to be the host of the World Cup in the summer, an event that would be an absolute top priority to have go smoothly without any complications from a major spy case.
There is now new evidence that the claims of Russian involvement in the alleged assassination attempt were fraudulent, engineered by the British government, possibly in collusion with American intelligence, to smear Vladimir Putin in particular. Bulgarian investigative journalist Dilyana Gaytandzhieva has written an article entitled “UK Defense Ministry Document Reveals Skripals’ Blood Samples Could have been Manipulated.”
Relying on a series of British-version Freedom of Information Act queries, Gaytandzhieva determined that there was a considerable gap between the time when it was claimed the Skirpals’ blood was drawn and the time when it was actually tested for possible poisons at Porton Down. The gap is inexplicable and means in legal terms that the chain of custody was broken. It further suggests that the samples could have been deliberately diverted and tampered with.
Gaytandzhieva, who provides copies of the relevant government documents in her article, sums up her case as “New evidence has emerged of gross violations during the UK investigation into the alleged poisoning of Sergei and Yulia Skripal in Salisbury on 4th March 2018.” The Ministry of Defense, which is in charge of the British military laboratory DSTL Porton Down which analyzed the Skripals blood samples responded to a request that “Our searches have failed to locate any information that provides the exact time that the samples were collected.” The samples “were collected at some point between 16:15 on 4 March 2018 and 18:45 on 5 March 2018. Even the time of arrival at Porton Down is indicated as “approximate.”
She also cites some expert testimony, “A British toxicologist [commented] that ‘It is inconceivable that with such a visibility case, and the obvious significance of any and all biological samples, normal and expected sample logging and documentation did not take place. The person drawing the sample, in any clinical or forensic setting knows that the date and time must be recorded, and the donor positively identified. In a criminal case, evidence gleaned from these samples would be thrown out as inadmissible… This lack of protocol is either very sloppy or clandestine.”
If the Skripals case sounds very similar to the recent alleged poisoning of Russian dissident Alexei Navalny it should, as the same rush to judgement by many of the same players took place. Navalny became ill while on a flight from Tomsk to Moscow on August 20th, 2020 and was taken to a hospital in Omsk after an emergency landing. The Russian hospital could not find any poison in his blood and attributed his condition to metabolic disorder. Two days later, the Russian government allowed Navalny to be transported to a hospital in Germany which then announced that the Putin government had poisoned Navalny with novichok, which became the story that was read and televised worldwide. Interestingly, there is now evidence that the air medevac team was standing by and ready even before anyone knew Navalny was ill, suggesting that it was planned in advance. Once in Germany, as in the case of the Skripal poisoning, the evidence of the crime mysteriously disappeared for a while. Blood samples and water bottles allegedly containing the novichok were sent to the Organization for the Prohibition of Chemical Weapons offices for verification. They took five days to arrive.
The doubts regarding both the Skripals and Navalny poisonings might suggest that the Cold War never really ended, at least from the Anglo-American perspective. Whatever Vladimir Putin has been doing for the past three years hardly touches on genuine U.S. or British interests, unless one considers the governance of places like Ukraine and Syria to be potentially threatening. That someone, somewhere, somehow seems to be making an effort to isolate and delegitimize President Putin by making him an international poisoner is tragedy elevated by its absurdity to the level of farce. It serves no purpose and, in the end, can only lead to mistrust on all sides that can in turn become very, very ugly.
Between 29 November and 1 December 2021, member states are meeting in a special session with the World Health Organisation to discuss, possibly sign, a new treaty on pandemic preparedness and response.
This decision was taken in March 2021 and backed by 26 nations, among which Australia, Canada, Iceland, Norway, Republic of Korea, South Africa, Ukraine, United Kingdom, United States, Uruguay and Member States of the European Union.1
To be noted is the absence of Russia, China, and India among these 26.
The International Health Regulations (2005)[i] signed by 196 countries already provide States the legal right to:
“– review travel history in affected areas;
– review proof of medical examination and any laboratory analysis;
– require medical examinations;
– review proof of vaccination or other prophylaxis;
– require vaccination or other prophylaxis;
– place suspect persons under public health observation;
– implement quarantine or other health measures for suspect persons;
– implement isolation and treatment where necessary of affected persons;
– implement tracing of contacts of suspect or affected persons;
– refuse entry of suspect and affected persons;
– refuse entry of unaffected persons to affected areas; and
– implement exit screening and/or restrictions on persons from affected areas.”
In other words, all the measures applied round the world since 2020, including mandatory vaccination, are in effect legal under this former treaty.
In particular, it critically changes the definition of “quarantine” from that in the 1969 IHR. There, it is used only in the expression “in quarantine” defined to be a “state or condition during which measures are applied by a health authority to a … means of transport or container, to prevent the spread of disease, reservoirs of disease or vectors of disease from the object of quarantine”.[i]
The 2005 revised IHR use the term by itself, and define it as “the restriction of activities and/or separation from others of suspect persons who are not ill or of suspect baggage, containers, conveyances or goods in such a manner as to prevent the possible spread of infection or contamination”.
This represents a subtle but critical shift from protection of the community to restriction of individual liberties.
The implementation of quarantine and other coercive measures on all, including surveillance and vaccination, is legalized: the expression “suspect persons” criminalizes every individual, both healthy and unhealthy.
Indeed, it covers anyone “considered by a State Party as having been exposed, or possibly exposed, to a public health risk and that could be a possible source of spread of disease”. Of significance is the use of “possibly” and “possible”, hence not just anyone definitely known to be a risk factor.
So Why The Need For A New Treaty?
The answer was given by WHO Director-General Tedros Adhanom Ghebreyesus. “It’s the one major change, Tedros said, that would do the most to boost global health security and also empower the World Health Organization.”[i]
The 2005 revised IHR still leave some authority to States and require certain conditions for a health event in a particular State to be considered sufficiently serious globally for the State to be forced to communicate it to WHO. Once communicated, it becomes the prerogative of the director general of WHO to determine whether it “constitutes a public health emergency”, but in collaboration with that particular State.
Although it should be added that in case of disagreement, the director general decides after consultation with the emergency committee of WHO, and passed a certain period no State can reject or emit reservations about the IHR or any later amendments. Still, to some extent, measures implemented remain the result of a dialogue between “IHR focal points” in each country and “WHO IHR contact points”.
What is particularly important is that the above listed measures, although rendered legal by the IHR, can under this treaty, only be recommended by the WHO, not imposed, and that it is up to the States to proceed towards their imposition, and to verify they are followed by means already existing in their respective countries.[ii]
The new treaty would address the above “weaknesses” of the IHR as they are considered to be, by ensuring “independent verification, monitoring, and compliance”. Given the clearly expressed end of empowering the WHO, should one conclude that “independent” means under the authority of WHO rather than the States themselves?[i]
Further the IHR cover “public health hazards and public health emergencies of international concern”, whereas the treaty will concern “all hazards”, not just pandemics. In the latter case, it would take over from the IHR once a pandemic is officially declared by the WHO.[ii]
This said, the treaty would presumably also make clear the idea expressed in the 2007 CDC “Interim Pre-pandemic planning guidance”,[i] namely overruling the need of a pandemic to implement restrictive measures. All that would be needed would be for an event to be declared a “public health emergency of pandemic potential”.
Given that any future event is always hypothetical, does this enable the maintenance of the measures for an indeterminate period? For it can always be claimed that a pandemic will occur especially were the measures lifted. This raises many questions, all the more so as the event would no long need to be of “international concern as in the current IHR”. “Measures”, as advised, should also go beyond the current scope of IHR”, in particular to cover the production and supply of vaccines, diagnostics, and treatments”.[ii]
The treaty would unlike the IHR also go beyond sanitary issues and allow the implementation of measures against “social and economic disruptions” as well as “broader disaster risk”.[i]
Would this in effect not only make it legal to put an end to criticisms, and thus to the freedom of expression, and make it possible to control any public antagonism against restrictive measures through “urgent international assistance”,[ii] namely not just by national police or military forces, but international ones?
In short, would the treaty not provide the international legal framework for derogation from the civil and political rights guaranteed “even in time of emergency threatening the life of the nation” by The Syracuse Principles on the Limitation and Derogation Provisions in the International Covenant on Civil and Political Rights drafted in 1984,[iii] namely:
“the right to life; freedom from torture, cruel, inhuman or degrading treatment or punishment, and from medical or scientific experimentation without free consent; freedom from slavery or involuntary servitude; the right not be be imprisoned for contractual debt; the right not to be convicted or sentenced to a heavier penalty by virtue of retroactive criminal legislation; the right to recognition as a person before the law; and freedom of thought, conscience and religion. These rights are not derogable under any conditions even for the asserted purpose of preserving the life of the nation”?
For the Syracuse Principles only ensure that “No state party shall” in any circumstance “derogate from the Covenant’s” above guarantees”. However, according to the new treaty, would the WHO, possibly together with the help of other international bodies, not become an occupying planetary power, with each State a collaborating subservient unit, like France in 1940, and hence without any power to ensure that non-derogable rights are protected?
Last but not least, “[t]rying to revise the IHR would be a long process and take several years. … In addition, any amendment made to the IHR will enter into force only two years after its adoption. A world in crisis cannot afford to wait this long.”[i] Why such a rush to get the treaty ratified?
It should not be forgotten that among the main contributors of WHO are the Bill and Melinda Gates foundation and the vaccine alliance (GAVI). It established in 2000 and whose initial funding it essentially provided – a “unique public-private partnership … bring[ing] together key UN agencies, governments, the vaccine industry, private sector and civil society”.[i]
Dalek-like cries of ‘Vaccinate! Vaccinate!’ are everywhere, and yet many reputable doctors and scientists have warned for months of existing hazards from the jab, including deaths and injuries linked to its unique and experimental mode of action, and future risks that may be even more dire. (See also here and here.)
I have written some 35 articles on Covid over the past year, first for Lockdown Sceptics, now renamed The Daily Sceptic, and then for The Conservative Woman, now renamed TCW Defending Freedom. Both these daily newsletters, with associated websites, run largely by volunteers, are doing a far better job than any of the well-funded mainstream media or indeed academic journals in consistently questioning and challenging Covid orthodoxy, from a strong ethical as well as factual basis. It is a dynamic field, and they have risen to the challenge magnificently.
With some sadness, I have decided I must step back from the controversy for a while. As with ‘HIV’/Aids, another scientific nonsense which I covered as a journalist but which survived for decades because it suited so many powerful interests, Covid-19 has gripped the public imagination and discourse in such a way that facts, reason and ethics are playing little part in the global response to the crisis.
To see a recent example of how crazy things have become, please watch this five-minute video by Julie Ponesse, a professor of ethics at the University of Western Ontario. She recorded it for first-year students, having been threatened with dismissal after 20 years because ‘I will not submit to having an experimental vaccine injected into my body’.
‘My job is to think critically,’ she says. ‘To ask questions. Questions like, Says who? Who is the authority giving this order? Should I trust them with my body?
‘As a professor, I don’t have to watch the news to find out if the Covid vaccines are safe. I read medical journals, and I consult my colleagues who are professors of science and medicine. I’ve learned from doctors that there are serious questions about how safe these vaccines really are. There are questions about how well they work. Nobody is promising that I won’t get Covid, or transmit Covid, if I get the vaccine.
‘But ultimately, none of that matters to me. Because I am a professor of ethics, and I am a Canadian. I’m entitled to make choices about what does and does not enter my body, regardless of my reasons.
‘If I’m allowed back into my university, it’s my job to teach my students that this is wrong. It is ethically wrong to impose an experimental medical procedure as a condition of employment. This is my first, and potentially my last, lesson of the year.’
On September 7, Ponesse was dismissed. Now Joe Biden is threatening 80million unvaccinated Americans with mandatory jabs – more than he is threatening the Taliban, as a Fox News commentator put it.
Most of my former medical and science correspondent colleagues, and indeed the social media giants such as Facebook and Google (whose ad department has just de-platformed TCW Defending Freedom), have been drawn into the false belief that we are in a war that can be won only if everyone gets the jab.
That belief has been supported and promoted from the start by a scientific establishment seeking to assuage its guilt over the fact that science itself gave us SARS-CoV-2. The virus was clearly a product of genetic engineering by American and Chinese scientists, but a high-level decision was taken to try to hide this fact from the public.
Top UK scientists, including Sir Jeremy Farrar of the Wellcome Trust and Sir Patrick Vallance, former president of research and development at global pharmaceutical company GlaxoSmithKline and now chief scientific adviser to the Government, took part in secret talks the day after Covid-19 was declared a global health emergency to decide how to respond.
Bibles of the scientific world such as Nature and The Lancet vigorously promoted the idea that the virus jumped across to humans from an animal host, and I believed them myself at first, in common with most reporters.
For all this time, since the pandemic began, it has been left to individual ‘maverick’ researchers – often barred from official channels of communication – to demonstrate that years of laboratory work brought about the modifications which turned a bat virus into a danger for humans.
Yet nearly 18 months ago, an Anglo-Norwegian team of vaccine researchers using electron microscopy described six ‘unique fingerprints . . . indicative of purposive manipulation’ in the virus’s spike protein, enabling it to enter a wide range of human cells. They warned that the protein in itself was hazardous and that specific precautions would be needed when using it in any vaccine candidate.
Their report was suppressed, and even today the scientific community continues to avoid considering its devastating implications, which include an explanation for the blood clotting belatedly acknowledged as an adverse effect from vaccines based on the spike.
Was Covid a plandemic? High-level, international pandemic scenario planning did precede the arrival of SARS-CoV-2, but the evident panic in China when the first cases emerged, and attempted cover-up of British and American involvement, speak more to an accidental escape than a planned crisis.
However, immensely influential foundations, whose own financial interests and investments are served as they fund campaigns for so-called ‘global health security’ and ‘pandemic preparedness’ (see for example here, here, here and here) have contributed to the crisis. They have helped bring into being the very threats they were supposed to counter. Unless and until these influences are exposed, and the malign consequences acknowledged, we look set to perpetuate the mistakes.
At least in the UK, ministers may be realising that lockdowns intended to ‘save’ our NHS had the opposite result. The service is on its knees, with many staff dispirited, and millions are awaiting care and treatment. Children and old people have especially suffered.
Yet public opinion has been whipped into such a frenzy of fear that there is widespread acquiescence in the face of proposals for more punishing controls, especially surrounding Covid vaccines.
This is despite a lack of clear evidence as to whether Covid vaccination is truly ‘safe and effective’, as we are constantly assured by government scientists, or may actually be doing more harm than good. The issue has become so political that it is difficult to sort out facts from propaganda, but I believe that Public Health England, while promoting vaccine passports and ‘no jab, no job’ policies, has its head in the sand over evidence that we may face a disaster of unimaginable proportions.
It tries to justify lives lost to the jab by plucking huge numbers of ‘lives saved’ and ‘infections avoided’ out of thin air. Data showing declining vaccine effectiveness and a need for booster shots tell us that these claims are at best, huge overestimates. The latest experience of highly vaccinated Israel (see here and here) is discouraging, to say the least.
Before I learned of the toxicity of the spike protein and the way it is carried through the blood and distributed throughout the body, accumulating especially in the ovaries and potentially damaging fertility, I admired the ingenuity of the RNA vaccines and hoped they would work.
Today, however, despite being aged 77, I would far prefer to take my chances with the virus, which we now know is dealt with successfully by most people’s natural immune mechanisms, than with the jab, which is designed to bypass the body’s first defences.
The human body has astonishing resilience and intelligence, and I am sure most of the millions who have received and recovered from the jab, usually without more than a day or two of discomfort, will be fine.
Yet now the NHS is gearing up to roll out the jab for 12- to 15-year-olds, and teachers’ leaders are all for it. Objections by experts who know that healthy children are at essentially zero risk from the virus, while the jab itself can injure or kill, have been acknowledged, but set aside, by the UK’s four chief medical officers. This is despite heartfelt pleas such as from the UK Medical Freedom Alliance.
Vaccinating 12-year-olds with an experimental jab of certain toxicity, even against their parents’ wishes? How could we have reached a state of such stupidity as even to contemplate such measures?
And it won’t necessarily end there. Pfizer and Moderna are both seeking authorisation to extend the jab drive to 5-11-year-olds.
An element that has surprised and distressed me is the almost complete lack of Parliamentary oversight of the handling of the crisis. It is as if our elected representatives have been reduced to a single party, and even that party has been dancing to the tune of unelected advisers and officials.
I wondered about writing to Labour leaders to urge them to challenge the Government much more strongly, but then read a long essay, The Unions and the U-turns, which provides an important piece of the puzzle as to why ministers have stumbled along so disastrously for so long, usually with cries of ‘Too late!’ or ‘Hit harder!’ from the Opposition.
Written by philosopher, author and campaigner Ben Irvine, it describes the driving role that public sector unions have played, largely behind the scenes, in what Irvine calls the ‘coronapanic debacle’ in Britain. Understanding the role of socialists in pushing the Prime Minister into repeated U-turns on Covid policy, he writes, ‘is key to unlocking this whole sorry mess’.
For instance, you may not know that the first lockdown was set in motion the day after the largest teaching union threatened unilateral schools closures. Or that numerous teaching unions refused to return to work during the first lockdown. Or that in the summer of 2020 a transport workers’ union threatened to strike unless the government mandated masks on trains. Or that in the same summer a retail workers’ union threatened to strike unless the government mandated masks in shops. Or that the third lockdown happened the day after there was a colossal teaching mutiny with hundreds of thousands of teachers refusing to return to work in January 2021. Or that the reason why children have been cruelly masked in schools was that mutinous teaching unions demanded it.
In the time I now intend to take out, I want to explore what is missing in the human spirit that makes us vulnerable to such madness.
Greed plays a part. It is obvious that Big Pharma, with its friends in government and the World Health Organisation, has been well placed to capitalise on the crisis.
How much better it would have been if the incredible £400billion cost to the nation of the UK’s handling of the crisis to date had been spent on strengthening immunity to the virus through nutritional and social support structures, rather than poured into furlough schemes, mass testing with dodgy kits, and untested vaccines.
But the discovery that powerful unions helped amplify the disaster makes me realise it is not just scientific embarrassment, and capitalist greed, driving the policy errors, but also the false compassion to which those on the Left seem especially vulnerable. ‘Save Lives – Stop Living’ is one of my favourite slogans from these Orwellian times.
In the early years of Aids, I joined media colleagues in raising the alarm about a virus that we were told put all sexually active people at risk because of a long time lag between infection and illness. We were happy to feel we were contributing to the public health effort.
But thanks to the work of ‘dissident’ scientists in the USA and Australia, I gradually learned that ‘HIV’ was not a genuine pathogen. ‘HIV/Aids’ was a concept, marketed with skill and urgency by American government scientists with support from colleagues in the UK and elsewhere, after a period in which the plight of early Aids victims had been cruelly neglected.
The virus theory democratised the illness and brought compassion in place of condemnation. Gay Lib leaders had fought for years to end discriminatory laws and attitudes and when Aids came along, its early characterisation as a ‘gay plague’ linked to promiscuous anal sex and heavy drug use threatened to derail the movement.
Then big money, combined with political correctness, created a monolithic belief system, never fully dismantled, that caused enormous harm. Under the leadership of the US ‘Aids czar’ Anthony Fauci, now playing a similar role with Covid, HIV/Aids became a business worth hundreds of billions of dollars, supporting countless well-meaning NGOs as well as science journals and researchers.
The use of unvalidated test kits bequeathed poor African countries with a false belief that the continent was in the grip of a terrible epidemic. A lethal, hugely expensive, US government-sponsored drug marketed by Burroughs Wellcome killed and tortured thousands of gay men, as well as ‘HIV’-positive children, and patients with the blood clotting disorder haemophilia. (SeePoIson By Prescription – The AZT Story, by John Lauritsen, published by Asklepios, New York, 1990.) A futile search for a vaccine to a non-existent virus continues to this day – 35 years on!
The scientific community fiercely resisted challenge and never owned up to the mistakes at the heart of the HIV paradigm, which I have summarised here.
When the then Sunday Times editor Andrew Neil persisted in publishing Aids heresies, the response was censorship, suppression and ridicule. Other mass media, notably the BBC, Guardian, Independent and Observer, bayed for our blood. The Health Education Council started an Aids journalism award specifically in our dishonour. The science journal Nature contemplated picketing the ST offices.
This was despite challenges from top scientists, including Nobel laureates such as Kary Mullis, inventor of the PCR test widely used in Aids research and now (grossly misused) in purportedly diagnosing Covid, who insisted there was zero scientific evidence of HIV being the cause of the collapse of the immune system seen in the syndrome.
I learned at that time that the bigger the evidence vacuum, the greater the intolerance of dissenting views and the tighter the attempted mind control.
Doctors who sought to treat aids by means other than the official drug, called AZT, were struck off the medical register or otherwise hounded out of the profession. Scientists who advocated different ways of tackling Aids were unable to publish.
The censorship was absolute. At one point, a major paper deconstructing the HIV theory was accepted by a well-respected journal. But the defenders of the HIV/Aids faith got to hear of it, the editor was removed, and his successor withdrew the paper from the publication pipeline. Even patients who dared question the orthodoxy were viciously lied against and abused, sometimes with lethal results.
It took 25 years for the WHO to acknowledge that there was no world pandemic among heterosexuals, although it continued to maintain that sub-Saharan Africa was being devastated by the disease. That too was untrue, as I learned in 1993 during several weeks reporting from supposed Aids hotspots in Africa. I found that scarce resources were being misdirected to an imaginary epidemic created by the unvalidated ‘HIV’ test. The scientific and medical establishments went into a frenzy over these reports but they were never refuted.
Unlike ‘HIV’/Aids, Covid-19 is all too real. For reasons that are not well understood, the disease comes in definite though generally short-lived waves, and it can be lethal in people who are already near death’s door through other illnesses or because of old age.
I am sure that those who knew of its genetically engineered status when it first escaped from the Wuhan lab feared the worst, and that was why a global alert was sounded.
However it has been known since late last year that overall the proportion of virus-infected patients who die is less than 0.2 per cent, not much more than in a bad year for flu, and far lower than was initially thought.
By that time, though, full-scale fearmongering propaganda was under way. An uncalibrated diagnostic test had been rushed out, giving the false impression that ‘cases’ were rampant when in fact many of those who tested positive were in good health.
Deaths among the elderly were reclassified as Covid even when from cancer or heart disease or inappropriate drug use (see this funeral director’s report for a moving account of this scandal).
Just as with ‘HIV’/Aids, cheap treatment approaches such as vitamin D and ivermectin that were being used by some doctors to keep patients out of hospital were officially rubbished and even banned.
Mask mandates, lockdowns and enforced separations were used indiscriminately, and largely without scientific justification, to bring about a completely disproportionate fear.
Now, in what seems to me to be a continuing effort to divert attention from the laboratory-induced, chimeric status of the Covid virus, scientists are telling us there are many more like SARS-CoV-2, jumping from animals into humans all the time and potentially causing new pandemics.
They also talk up the threat posed by genetic changes in the virus, when in fact the variations are generally insignificant and natural, as explained here by Oxford University’s Professor Sunetra Gupta.
They ignore evidence that ‘natural immunity not only confers robust, durable and high-level protection against Covid, but also provides better protection than vaccine-induced immunity’.
And meanwhile, the so-called variants provide a convenient excuse for the failure of the existing vaccines and an argument for booster shots which could become the basis of a never-ending bonanza for the pharmaceutical companies.
Is there any hope that we may come to our senses sooner with Covid than with Aids?
Government agencies worldwide, including the UK’s (Bill Gates and Big Pharma funded) Medicines and Healthcare products Regulatory Agency (MHRA), have been supine in the face of a huge range of adverse effects potentially related to the Covid jab. More than 1,500 deaths and thousands of injuries have been reported under the UK’s ‘yellow card’ scheme, and many thousands more in the US, but the regulators have shown extreme reluctance to acknowledge the harm being caused.
One big difference from the ‘HIV’/Aids era is that the internet has enabled critics of Covid orthodoxy to post challenging data and opinion, despite online censorship.
When celebrity rapper Nicki Minaj, with 22.6million followers, tweeted that her cousin’s friend became impotent through swollen testicles after receiving the Covid vaccine, she was almost universally mocked. But as analyst Steve Kirsch reported in TrialSite News, Minaj was right and all the world’s experts wrong: there are more than 60 cases of testicular swelling on the US database of adverse reactions to the Covid jab.
Information that could end the ‘vaccine dystopia’ is out there. It is present in a multitude of sources, including the UK’s own TCW Defending Freedom and The Daily Sceptic, but is still largely withheld from the wider public by governments, their advisers, and the mainstream media.
I do not share the view that there is a depopulation agenda at work, or that super-prisons are being built to house the unvaccinated, or that microchips are to be implanted in us by crazed technocrats. But I can understand how such theories gain credence while top scientists who funded the work that created the virus remain in denial about what they have done, and world leaders who were informed of SARS-CoV-2’s laboratory origin remain in the panic mode that brought such a disastrous response.
Our leaders, both scientific and political, have barricaded themselves behind a wall that is preventing them from seeing and hearing the reality. This time, unlike in the tragic ‘HIV’/Aids story, perhaps the fourth estate will soon recognise that it can step back from its own well-intentioned panic stations, and bring that wall down.
Palestine Action is, as its name implies, involved in direct action against some of the arms trade’s most deadly production lines, notably Israel’s Elbit Systems. Since it burst onto the scene, quite a few members have been arrested at some of Elbit’s ten known factories and offices in Britain.
Elbit Systems is Israel’s largest arms company; it makes deadly “unmanned aerial vehicles”, known as drones. Palestine Action’s trademark calling card is deep red paint; it has used gallons since last year, symbolising the blood of innocents spilled in drone strikes.
Recently, the group has expanded its brief from targeting weapons factories to spraying the tented entrance of Britain’s biggest arms fair — DSEI at London’s ExCel Centre — to remind those seeking to buy weapons of the bloodshed caused by the products marketed within. Key exhibitors such as Elbit Systems, Raytheon, BAE Systems, and Lockheed Martin use arms fairs to market their deadly technology and products to governments from around the world. Perhaps they should be the focus of police interest rather than members of Palestine Action.
Palestine Action activists dyed security tent blood red and threw red and green flares on the Excel exhibition centre in London – Sunday, Sept 12, 2021 [VX Photo/ Vudi Xhymshiti]
Like many others, I am sick and tired of half-hearted apologies from the armed forces which use (or misuse) their weaponry. There’s nothing “smart” about a precision-guided missile which kills innocent civilians as — and I hate this term — collateral damage. There is no such thing as a clinical kill, a point agreed by several protest groups which have criticised the arms fair for its role in enabling the destructive US-UK war in Afghanistan over the past twenty years.
According to US policy, attacks by drones are not to go ahead if there is a probability that innocent civilians will be killed or injured. As we found out a few days ago, the US doesn’t really have a clue who it’s blowing up. Call me naïve, but it seems that the only certain thing when a drone takes to the air is, that innocent civilians will die, whether they’re Afghani, Iraqi, Pakistani, Yemeni, Syrian, or Palestinian.
Drone attacks were much favoured by Barack Obama who joked about their efficiency. One news story illustrated how much he ordered their use by pointing out that it would take the former US president more than three years to get through them all if he apologised to one innocent person a day. Human rights groups have demanded transparency from all US presidents since the Bush administration launched its drone wars, but there remains very little clarity on the number of civilians killed.
I’ve suspected this for many years. After the most recent US apology for killing civilians, I had a sense of déjà vu. In April 2003, I travelled solo to Paktika in Afghanistan after hearing rumours of an atrocity against innocent civilians in a district called Bermal. All eyes were focused on Iraq so even though I got the story, it was difficult to find someone to publish it. There’s only so much injustice against the people of Asia and the Middle East that the media is prepared to broadcast or publish.
While I was investigating the atrocity in southern Afghanistan, a senior US army officer was also in the district with hush money to keep Afghan villagers quiet. He did not want people talking to me in case I found out that America had killed eleven children in another deadly blunder.
The Pentagon had claimed that it destroyed a Taliban stronghold when, in fact, US forces had destroyed a house. The grieving mother — Sawara was her name —lost all of her nine children in the attack. She was like an empty shell when I finally spoke to her.
She and her husband Mawes Khan had put their children to bed in the family home they shared with his brother Sardar, and his wife and their seven children. By morning, the corpses of eleven brothers, sisters, and cousins lay in a neat row in the courtyard. The Americans realised the full extent of their mistake and gave the family the equivalent of £6,350 and an apology.
That happened two years into the war when the number of dead Afghan civilians was not deemed important enough to register. How much compensation will the Americans pay to Zemari Ahmadi after wiping out ten members of his family, including eight children? The admission of guilt and an apology were only forthcoming because the world’s media was in Kabul on the day of the attack and had access to the scene of devastation as well as eyewitnesses and survivors to interview.
The media in Washington was briefed about how an unnamed ISIS-Khorasan fighter had been in a vehicle with an associate at the time of the strike, which was carried out by an MQ-9 Reaper drone. Captain Bill Urban, spokesman for US Central Command, assured journalists that the military had used specially chosen precision munitions in order to minimise civilian casualties. In essence, the compliant media was being fed propaganda packed with deceptive euphemisms.
The drone attack on the eve of the departure of the last US troops had come three days after Isis-Khorisan terrorists killed dozens of Afghan civilians, nearly 30 Taliban soldiers, and thirteen members of the US military in a suicide bombing at the gates of Kabul Airport. Civilians always suffer when the US rushes in to wreak revenge.
This week we heard US Defence Secretary Lloyd Austin apologise for a “horrible mistake” after he admitted: “We now know that there was no connection between Mr Ahmadi and Isis-Khorasan, that his activities on that day were completely harmless and not at all related to the imminent threat we believed we faced, and that Mr Ahmadi was just as innocent a victim as were the others tragically killed.”
Compare this with the narrative pushed out on 29 August when the US military claimed triumphantly to have taken out ISIS terrorists and that there had been “significant secondary explosions from the vehicle”, suggesting that explosives were on board. Journalists were told that there were “no indications” of civilian casualties. As I said, America would have got away with the lies had there not been so many foreign journalists on the ground.
It emerged that Zemari Ahmadi is an engineer for aid group Nutrition and Education International. He was observed placing large water bottles or jugs into the back of his white car. US intelligence (surely a contradiction in terms) interpreted this as an ISIS-K member packing explosives into a vehicle for another suicide mission.
It is time for the world to accept that there’s no such thing as a surgical strike and that unmanned drones are among the worst weapons for producing civilian casualties. It would, therefore, make more sense to listen to groups like Palestine Action rather than deploy deadly weapons which have a track record of killing innocent people.
The theme of the DSEI fair at the ExCel Centre was “Integrated Response to Future Threats”, with a focus on drone warfare and surveillance technology. Palestine Action says that this will mean a greater role for drones in British policing as the government enters new procurement and training contracts with the likes of Elbit Systems. According to the activists’ press release, the London fair and a similar exhibition in Liverpool “serve a similar purpose of normalising these firms’ operations and providing an open market for the exchange of the weapons of war. Palestine Action is calling for the cancellation of both events and the ceasing of these firms’ operations on British soil, failing which direct action will continue and will escalate.”
Drone strikes outside the declared war zones of Afghanistan and Iraq are the province of the CIA and the secretive US Joint Special Operations Command. Various US administrations have treated them as official secrets. In the absence of justice for the families of those killed accidentally and/or targeted in drone strikes, civil disobedience and resistance is thus the duty of all reasonable people in war zones like Palestine, Afghanistan, Syria, Yemen, Iraq, Somalia, and elsewhere.
It is easy for governments to demonise dead civilians as “terrorists” because most are killed in remote areas where the absence of justice or journalists makes it easier for the authorities to bury their mistakes. With governments prepared to lie or twist the facts, weapons manufacturers should be careful about those to whom they sell their arms, or be ready to be accused of complicity in war crimes.
We now suspect that the Palestinian children killed while playing on a beach in Gaza in 2014 were hit by an Israeli drone strike. The manufacturers are surely just as complicit as the Israeli soldiers who targeted young boys. Again, had journalists not been in an adjacent hotel when the strike took place, Israel might have got away with insulting everyone’s intelligence by claiming that Hamas “terrorists” were on active duty that day.
These are the sort of crimes that British police officers should be investigating, instead of arresting the people who draw attention to international war crimes and criminal negligence which led to the killing of Palestine’s 9-year-old Ismayil Bahar, 10-year-old Aed Bahar, 10-year-old Zacharia Bahar, and 11-year-old Muhammed Bahar on that Gaza beach; the Ahmadi family in Kabul earlier this month; and the Khan’s eleven children in Bermal in 2003, as well as the tens of thousands of others in-between. The law of universal jurisdiction exists to allow states to prosecute those responsible for international crimes committed elsewhere. The fact that few, if any such prosecutions go ahead, signals a degree of complicity at the highest levels of governments and judiciaries.
In such cases, it is not always the law that is an ass, but the people charged with implementing it and ensuring that justice is seen to be done for people like the Bahar, Ahmadi, and Khan families. Apologies and compensation are simply not good enough.
By Mahdi Darius NAZEMROAYA | Strategic Culture Foundation | 30.03.2015
The United States and the Kingdom of Saudi Arabia became very uneasy when the Yemenese or Yemenite movement of the Houthi or Ansarallah (meaning the supporters of God in Arabic) gained control of Yemen’s capital, Sanaa/Sana, in September 2014. The US-supported Yemenite President Abd-Rabbuh Manṣour Al-Hadi was humiliatingly forced to share power with the Houthis and the coalition of northern Yemenese tribes that had helped them enter Sana. Al-Hadi declared that negotiations for a Yemeni national unity government would take place and his allies the US and Saudi Arabia tried to use a new national dialogue and mediated talks to co-opt and pacify the Houthis.
The truth has been turned on its head about the war in Yemen. The war and ousting of President Abd-Rabbuh Manṣour Al-Hadi in Yemen are not the results of «Houthi coup» in Yemen. It is the opposite. Al-Hadi was ousted, because with Saudi and US support he tried to backtrack on the power sharing agreements he had made and return Yemen to authoritarian rule. The ousting of President Al-Hadi by the Houthis and their political allies was an unexpected reaction to the takeover Al-Hadi was planning with Washington and the House of Saudi. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.

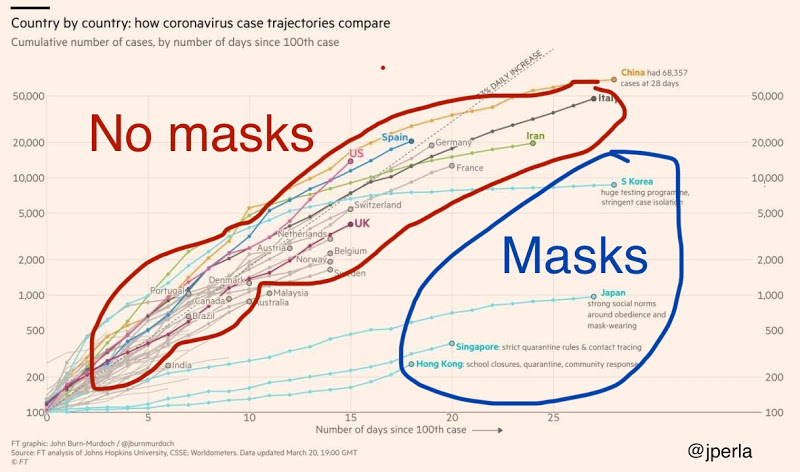

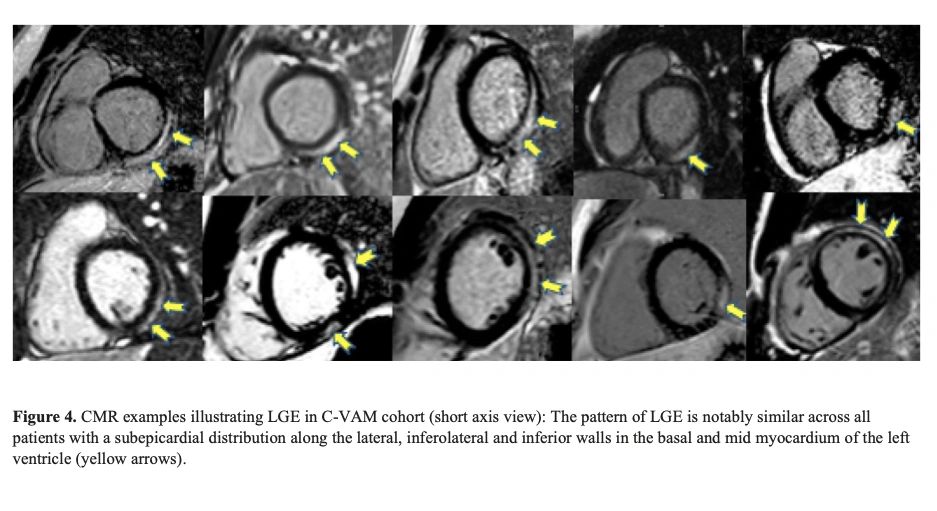


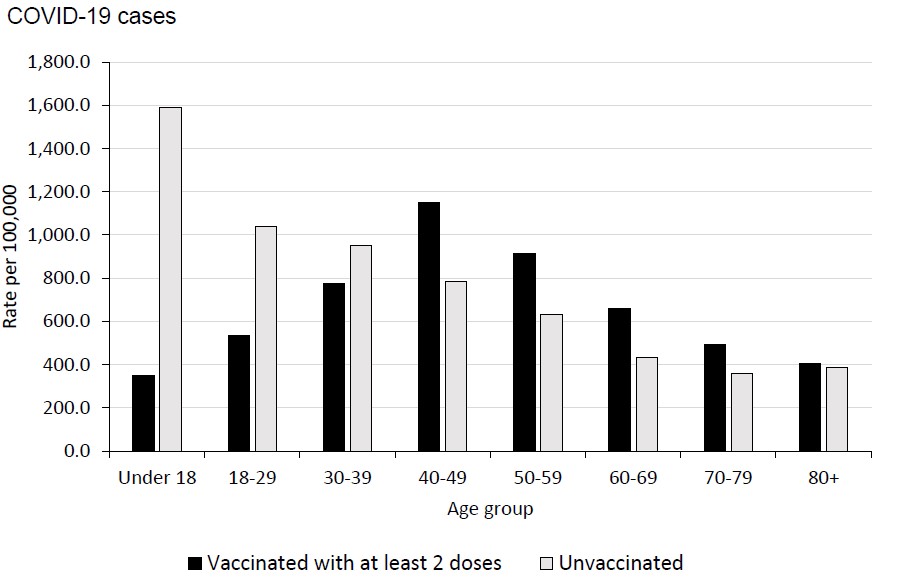
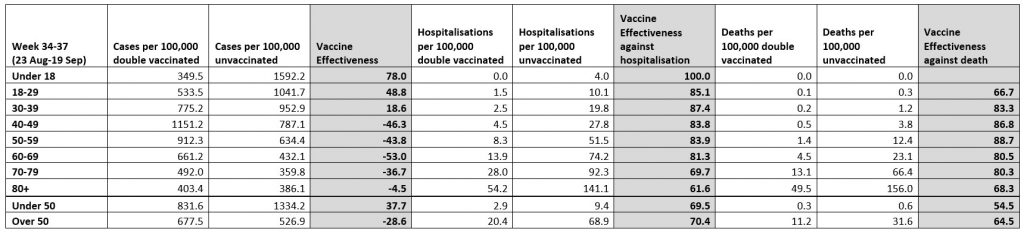



 Aletho News
