The tide is turning: former pro-vax PhDs are now refusing the booster
Want to know what changed their minds?
By Steve Kirsch | December 12, 2021
People are starting to wake up.
Recently, I received news that top researchers at multiple highly respected institutions (including Harvard) who had earlier been publicly promoting the vaccine have now changed their minds and are privately refusing to get the booster.
How is that possible? Did we finally convince them with the data? Most of my truthteller friends have been censored and/or deplatformed. So what is causing these people to shift their views so quickly?
The credit for the attitude shift goes our best convincer: the vaccine itself.
These researchers are seeing first hand how dangerous the vaccine is because they are involved in studies in hospitalized and/or outpatients and they see the numbers first hand.
Of course, they can’t say anything officially since they would be fired or have their funding taken away.
I just wanted you to know that people are finally waking up to what is really going on here.
First Comply, Then We’ll Grant You Some Rights
BY STACEY RUDIN | BROWNSTONE INSTITUTE | DECEMBER 5, 2021
More and more people feel like something is “off” about our response to the “Covid” pandemic. This pandemic is claimed by political establishment prophets to be the first time in history that we need universal, worldwide “vaccination” to dissipate a respiratory pathogen. The proffered “vaccines” do not provide sterilizing immunity; rather, they lead to regular “breakthrough” infections. Yet we are directed to “mix and match” them as we like, on a regular basis, in order to eat in restaurants and attend events.
Having recovered from the disease itself does not suffice to maintain your rights. The ability to prove that you are not susceptible to the pathogen due to inherent good health does not suffice. To maintain freedom of movement, you must submit to the injections.
Something is off. They want us to take these “vaccines” very badly. They want to build a QR/tracking infrastructure on this “safety” premise very badly. One must ask: did they ever have a legitimate basis to lead us to this point? Did they really believe they could “save grandma” with a lockdown?
By picking apart the superficially flawed justification they gave to the terrified world population for first imposing universal house arrest, we can see that they did not. Both the WHO and the Imperial College modeler Neil Ferguson called for lockdowns specifically based on China’s Wuhan lockdown of January 2020. They admitted that “lockdown” was something no one previously believed would work. When “Xi Jinpeng succeeded,” they abruptly reversed course 180 degrees, calling for the entire world to “copy China.”
“It’s a communist one party state, we said. We couldn’t get away with it in Europe, we thought… and then Italy did it. And we realised we could…If China had not done it, the year would have been very different.” — Neil Ferguson
Six weeks after the discovery of the first case, the WHO, during a press conference, sold the world on lockdown by claiming that “Wuhan’s curve is flatter” compared to other regions of China. The data it used to make this case — a case that it knew would devastate world economies and any individual human who could not earn money by sitting in front of a computer screen— was presumably provided via the communist dictator.
“So here’s the outbreak that happened in the whole country on the bottom. Here’s what the outbreak looked like outside of Hubei. Here are the areas of Hubei outside of Wuhan. And then the last one is Wuhan. And you can see this is a much flatter curve than the others. And that’s what happens when you have an aggressive action that changes the shape that you would expect from an infectious disease outbreak. This is extremely important for China, but it’s extremely important for the rest of the world . . .
The Chinese government and the Chinese people have used the non-pharmaceutical measures (or the social measures) [to] effectively change […] the course of the disease, as evidenced by the epidemic curves… In the report we have recommended this method to the international community.”
This superficially pleasing explanation — one easily accepted by a trusting scared person — raises huge red flags on closer analysis. First, how was the testing in the various regions conducted? Was it randomized throughout the population, or were only those who presented at clinics or hospitals tested? How many tests were conducted per capita? Was that number standard throughout the regions? How can we be sure “asymptomatic” cases were captured?, and so forth. In short, each curve could simply have depicted testing protocol — the tester could quite literally have compiled any curve it wanted.
Even worse, there is a logical flaw so breathtaking that it is impossible to believe it could have been overlooked by all lockdown-imposing world governments. Of the thousands of national, state, and local political and media actors cheering on the lockdowns, at least one must have noticed that while the curve may have been “flatter in Wuhan,” the disease still went away in all of China. The supposed “flatter” curve in Wuhan had zero net benefit. The residents there suffered through the pain of lockdown, neighboring regions did not, and they all ended up at the same point.
China has not reported any Covid cases in nearly four months. Prior to that, its cases were flatlined for fifteen months, since March 2020. China’s disease “curve” would be comedic if the rest of the world had not given up democracy and precious constitutional rights to “fight the virus”:
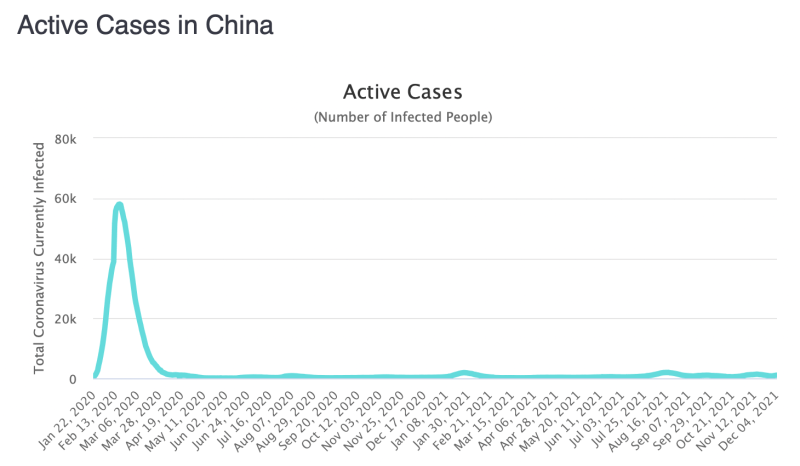
Contrast this with the rest of the world — particularly the countries that tried the hardest to replicate the Chinese example — such as Peru, Israel, Australia, Singapore, New Zealand, and Canada. All of them have reported multiple “waves” of Covid despite all of the pain of lockdown. Even mass vaccination has not “stopped” waves of cases. China is the only country with a perfectly flat “curve,” and it did that with a single-city lockdown, despite reporting the presence of the virus in many other regions. Magic.
World governments clearly know about this. They do not trust the communist dictator. If they really believed the disease was serious and China underreported cases, they would not be firing doctors and nurses who refuse the “vaccine” after working safely with covid patients for 18 months. Rather, they know that the rules have no effect. The disease curves rise and fall, rise and fall — it would be absurd and perverse to conclude the rules work sometimes and fail at other times.
Yet they keep imposing rules. The population complies, conditioned to an illusion of control; a superstitious belief that “because we did something, it must have had an effect.” But facts are facts: even the “vaccines” have not stopped the virus, there are “breakthrough infections.” Desiring to be “good people,” everyone stays unthinkingly on the track that started with Wuhan’s lockdown.
They are trying to save grandma, but grandma’s fate is sealed. What is actually happening is they are paving the way to routine universal mandatory vaccination. The political establishment intends to make “the unvaccinated” second-class citizens, to dehumanize them and deny them basic rights many generations have taken for granted. This conditions the population to movement restrictions based on behavior. Compliance gets you rights, like a dog earning treats.
In this system — which is steadily getting underway in country after country — a person who weighs 350 pounds, is completely sedentary, and eats a steady stream of Big Macs is considered “healthy” and accepted in society. The decisive factor is obedience: he dutifully takes all of the “boosters.” By contrast, a world-class athlete such as Novak Djokovic cannot play tennis at the Australian Open. He is deemed an “infection risk” because he insists on maintaining his body using eastern-style health practices, the same ones that made him into the greatest tennis player of all time. (The establishment would rather he copy the Big Mac devotee described above, because it earns them — not him —more profits).
The political establishment is so devoted to this cause that it is hard to see how we can extricate ourselves. Accepting the first lockdown was the decisive point. We sacrificed our rights due to fear, and nearly two years later, we still don’t have them back. It was as obvious then as it is now: power is never seized and then voluntarily returned.
Australia now has “quarantine camps.” “Unvaccinated” Canadians cannot use mass transit. Austrians who refuse the jab cannot leave their homes. It bears repeating: world governments are holding law-abiding adults in house arrest for refusing to take an injection. This is not a drill.
Combine this real-life dystopia with the twisted “logic” used to launch the lockdowns, and it is hard to ignore the sinking feeling that lockdown was a preconceived pathway to where we are now: staring down the barrel at permanent, regular, mandatory adult vaccination — your immune system is now a subscription service — and corresponding movement “passports.”
Why do they want to inject us so badly? Certainly not for our own good. They act in their own self-interest, under cover of fake, “grandma-saving” goodwill. They are stealing from us — from you. How much more will you let them take?
Stacey Rudin is an attorney and writer in New Jersey, USA.
Greece plans to send troops to the Sahel
By Lucas Leiroz | December 2, 2021
In a recent statement, the Greek government confirmed Athens’ interest in sending troops to cooperate with the French armed forces in the African Sahel. The project is still under consideration but tends to be approved due to the strong pressure that Greece receives from Paris to “compensate” French efforts to protect Greek territorial integrity in tensions with Turkey. The move sounds truly anti-strategic for Greece, considering that the country will have enemies it previously did not have and will enter conflicts that have nothing to do with Greek geopolitical interests.
In a recent press conference, Greek Defense Minister Nikos Panagiotopoulos said that his country’s political and military leaders are currently discussing the feasibility of sending troops to Africa, where soldiers will join French military bases in order to assist in the Paris-led campaign against insurgent groups that are proliferating in the Sahel and across the region between the Sahara Desert and the West Coast.
These were some of his words: “We are considering sending a group of combat soldiers to Sahel. These are not military advisers, we already have such in the area, these are permanent combat members of the Armed Forces (…) If Turkey tries to attack and we ask for help from France, based on the military agreement we have signed, then the French forces will be there, they must be there (…) We are for them and they are for us”.
When talking about this possibility of mutual assistance, Panagiotopoulos is mentioning the recent bilateral defense cooperation agreement signed by both countries in October, which determine a series of measures to be implemented in order to strengthen the Franco-Greek military partnership. The agreement establishes that both countries must cooperate militarily with each other in conflict scenarios and also enumerates forms of commercial cooperation through measures such as, for example, the requirement that the Greek State buy frigates produced by the French naval industry.
Panagiotopoulos categorically states that sending Greek troops to Africa is a strategic measure for Greece, since, as a way of complying with the agreement signed with Paris, it would create a favorable precedent in bilateral relations and compel the French to repay the kindness, in case tensions escalate with Turkey in the future. However, Panagiotopoulos’ premise is absolutely wrong. It is not Greece that is setting this type of condition, but France. Athens is not freely proposing to send its soldiers to the Sahel – it is France that is demanding it, so there is no reason to consider this type of maneuver profitable in any way for the Greeks.
In the same sense, this type of cooperation would never benefit Greece for the simple fact that there is no military equivalence between both countries. France is one of the greatest military powers in the world, with high combat power and even nuclear weapons, maintaining an active expansionist policy in Africa and the Mediterranean, in addition to occupying a leading and prominent role in the European Union. The current situation of the Greek State is that of a country with very low military capacity, which is under constant pressure from an insurgent and expansionist power (Turkey) and which seeks alliances with France in order to defend its territorial integrity in the face of imminent threats. For France to demand “retribution” from Greece for its support on the Turkish issue is truly absurd, considering that Greece already has enough problems and difficulties just in its tensions with Turkey. Sending soldiers to Africa will significantly weaken Greece’s defense potential and leave the country even more vulnerable in its regional conflicts. So, Paris is acting abusively by requesting Greek troops in the Sahel.
Obviously, if both countries already have an agreement, this must be accomplished – or vetoed. The attitude that most benefits Greek strategic interests would be to find non-direct ways of cooperating with France on the Sahel, perhaps with logistical or intelligence support, but renouncing active military participation. If France continued to demand the deployment of troops, Athens would simply have to abandon the bilateral agreement and find another, less abusive way to establish partnerships. The current situation seems unsustainable. France will be weakening Greece with the demand for troops in African territory, and there is no sense for Athens to continue in a military agreement, whose objective is to strengthen the defense.
For years, France has maintained troops in the Sahel without any success in controlling the region. Paris is unable to maintain an occupation policy throughout the Sahel due to the immensity of the territory, which makes the area vulnerable to occupation by insurgent groups. Clandestine militias – some of them terrorists – currently control much of the Sahel zone and French troops are failing to pacify the region.
Furthermore, it is necessary to remember that in recent months a wave of indignation has started on the part of African communities against the French occupation. The main cities of West Africa are experiencing demonstrations in favor of the expulsion of the French armed forces due to the chaos and widespread, inefficient violence while being unable to contain the spread of terrorism in the region. In fact, it has become increasingly complicated for France to maintain its expansionism on African soil and now Paris seems interested in handing over to Athens a part of the responsibility of managing the chaos created by the French in the Sahel.
The Greek government has nothing to gain by engaging in civil wars on another continent that have absolutely nothing to do with Athens’ geopolitical interests. France is acting abusively by delegating the responsibility for this conflict to the Greeks. It is up to the Greek government to act prudently and avoid further conflicts, seeking to strengthen the country to face the current problems.
Lucas Leiroz is a research fellow in international law at the Federal University of Rio de Janeiro.
First Meeting of WHO Body to Discuss New Pandemics Treaty to Be Held on 1 March: Tedros
Sputnik – December 1, 2021
Director-General of the World Health Organization (WHO) Tedros Adhanom Ghebreyesus said on Tuesday that the first meeting of the organization’s commission to discuss a new treaty on the COVID-19 pandemic will take place on 1 March 2022, and its final document will be presented in 2024.
“I welcome your commitment to hold the first meeting of the INB [intergovernmental negotiating body] no later than the first of March 2022, and to submit its outcome for consideration to the World Health Assembly in 2024. And I give you my commitment that the Secretariat will support this process,” Tedros said at the end of the WHO assembly special session.
He also expressed his support for the the decision to establish a negotiating body to discuss a WHO convention on the COVID-19 pandemic response.
“I welcome the decision you have adopted today, to establish an intergovernmental negotiating body to draft and negotiate a WHO convention, agreement or other international instrument on pandemic prevention, preparedness and response,” Tedros said.
Opposition candidate Xiomara Castro claims election victory in Honduras

Xiomara Castro of the opposition Liberty and Refoundation Party (Libre) and vice presidential candidate Salvador Nasrala after the closing of the general election, November 29, 2021. (Photo: Reuters)
Press TV – November 29, 2021
Leftist opposition candidate, Xiomara Castro, has claimed victory in Honduras’ presidential election, with preliminary results putting her in pole position against the ruling party candidate.
With 38% of the voting tally complete, the Liberty and Refundation Party (LIBRE) candidate is in the lead with over 53 percent votes. Her main rival, Nasry Asfura of the ruling conservative National Party, currently has nearly 34% of the vote, according to the National Electoral Council (CNE).
If Castro holds on to the lead, she would become the first female president of the Central American country, ending the conservative party’s 12-year stint in power.
“We win! We win!” Castro, 62, told cheering party supporters on Sunday evening. “Today the people have made justice. We have reversed authoritarianism.”
In a brief victory address, Castro vowed to form a government of “reconciliation,” and to strengthen direct democracy with referendums, adding that “there will be no more abuse of power in this country.”
“We can’t stay home. This is our moment. This is the moment to kick out the dictatorship,” said Castro, who is making third bid at the presidency. She is the wife of former President Manuel Zelaya, whose government was toppled by a civilian-military alliance in 2009.
The outgoing President, Juan Orlando Hernandez, was accused by a US court of having ties to powerful drug trafficking gangs. However, he has denied the allegations.
Hernandez has faced stiff opposition in Honduras since he claimed a second term in a highly-divisive election at the end of 2017, which sparked widespread protests after both sides declared victory.
Unlike Hernandez, who was a conservative US ally, Castro has said that she would have diplomatic relations with China.
According to the electoral council, the voting saw a historic turnout of more than 68 percent.
The election is the latest political flashpoint in Central America, a major source of growing US-bound migrants fleeing chronic poverty, unemployment and persecution.
The spiraling crisis of hunger and homelessness in Honduras has placed it among the world’s most violent countries.
Alongside the presidency, the country’s 128-member Congress, and officials for some 300 local governments, are also being voted in these elections.
Are NHS scaremongers using out-of-date Covid figures?
By Will Jones | TCW Defending Freedom | November 29, 2021
THE Sunday Times has added its authority to the Guardian’s unsubstantiated claims about hospitals being deluged with unvaccinated Covid patients.
ICU is full of the unvaccinated – my patience with them is wearing thin | Anonymous | The Guardian
It published an article yesterday stating that intensive care beds are ‘filled with unvaccinated Covid patients’. The paper quotes Professor Stephen Powis, the National Medical Director of NHS England, saying: ‘Data shows that the overwhelming majority of people admitted to intensive care with Covid are not fully vaccinated. Since July one in four critical beds have been consistently occupied by a Covid patient, with the latest statistics available showing three quarters of them are unvaccinated.’
What ‘data’ and ‘latest statistics’ is Powis referring to? The Sunday Times article containing his quote doesn’t say, but if you click on the words ‘overwhelming majority’ it takes you to another piece in yesterday’s paper, this one by Dr Rachel Clarke. The subhead of that article is ‘Some 75 per cent of those suffocating in intensive care with the coronavirus are unvaccinated’ and she repeats this claim in her piece, stating: ‘Of the Covid patients treated in intensive care in recent months, the majority – nearly 75 per cent according to the latest data – have chosen not to be vaccinated.’
Daily Sceptic editor Toby Young asked Rachel Clarke on Twitter if she could point him towards the ‘data’ she’s referring to and she replied by citing the latest Intensive Care National Audit & Research Centre (ICNARC) report.
Is this the data both she and Professor Powis are referring to or just Dr Clarke? A similar tweet from Toby Young to Stephen Powis went unanswered, but it’s not unreasonable to assume they’re both citing the latest ICNARC report, not least because it includes for the first time a breakdown of vaccinated and unvaccinated patients receiving critical care in English NHS hospitals. (Clarke refers to separate NHSE data showing the same thing, but I can’t find anything on the internet.)
Now there’s a slight problem with the ICNARC data Clarke cites, which is that it only covers the period May 1 to July 31.
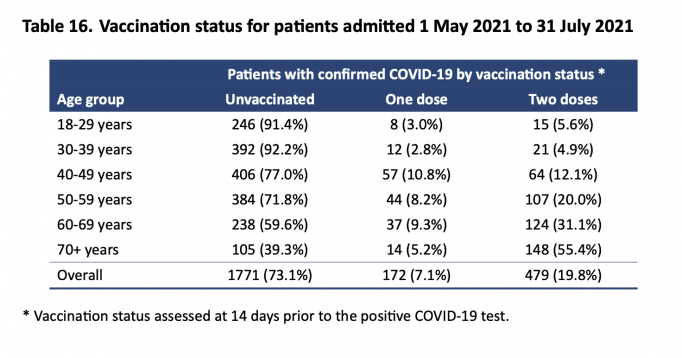
So is the data for May 1 to July 31 what Professor Powis means by ‘since July’ and what Dr Clarke means by ‘recent months’?
The problem with extrapolating from this ICNARC data to make sweeping statements about the current ratio of unvaccinated to vaccinated Covid patients in ICU – as the Sunday Times subhead and Dr Clarke do, and Professor Powis appears to – is that it stops before the Delta wave gets properly under way and before the surge in infections in the vaccinated over the summer, when the epidemic became dominated by vaccinated people.
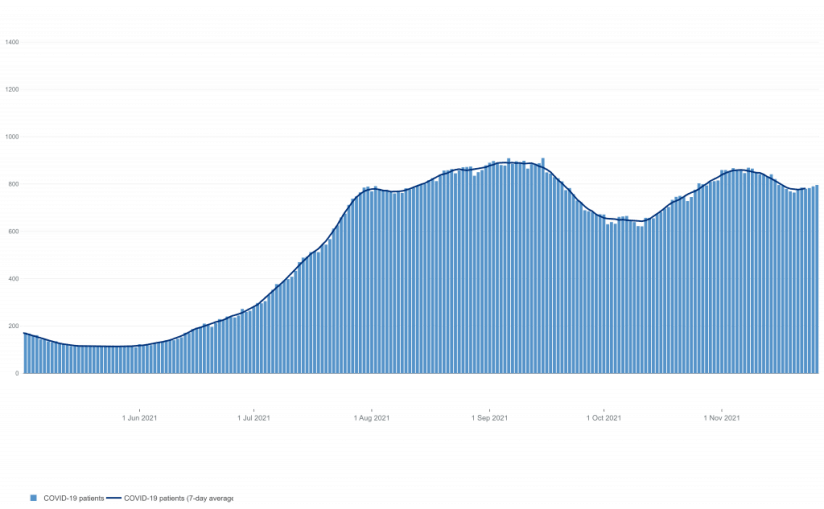
Covid ICU patients in England (UK Government)
If this is what’s going on, it’s reminiscent of the ‘sleight of hand’ by NHS England chief Amanda Pritchard earlier this month, when she claimed that: ‘We have had 14 times the number of people in hospital with COVID-19 than we saw this time last year.’ It quickly turned out that by ‘this time last year’ she was referring to August rather than October or November, and was widely ridiculed for such an obviously incorrect and scaremongering statement when Covid hospital admissions at the time were plainly lower than in autumn 2020. She never apologised and instead tried to make it look as if she was misunderstood, which, if Powis’s latest intervention is of a similar kind, suggests there may be no intention in the upper echelons of the health service to communicate clearly and accurately about the current risks posed by the virus.
In fact, given the data from UKHSA over the autumn showing a higher proportion of Covid hospitalisations and deaths in the vaccinated (67 per cent and 82 per cent respectively in the week 46 report), it seems most unlikely that three-quarters of Covid ICU patients in the same reporting period were unvaccinated. Why, though, do we not have data in the public domain more recent than July so we can see for ourselves rather than having to extrapolate and speculate? We have up-to-date data on hospitalisations and deaths by vaccination status, so why doesn’t the UKHSA add a column to its table for ICU admissions as well?
The biggest problem with Powis’s statement is not that it appears to be a misleading way of communicating statistics, but that it is being used against the unvaccinated in what seems to be a concerted effort to turn them into scapegoats and pariahs. ‘These are beds that would have historically been used to provide life-saving surgeries for the most seriously ill patients,’ he says. This echoes the words of the anonymous medic in the Guardian last week: ‘If everyone got vaccinated, hospitals would be under much less pressure; this is beyond debate. Your wait for your clinic appointment/operation/diagnostic test/A&E department would be shorter. Your ambulance would arrive sooner. Reports of the pressure on the NHS are not exaggerated, I promise you . . . Most of the resources that we are devoting to Covid in hospital are now being spent on the unvaccinated.’
This is an ugly and dangerous road. Not only is there currently no publicly available data to back up these assertions – at least, nothing more recent than July 31 – but even if there was it would be no excuse to demonise and delegitimise the minority who, for whatever reason, remain unvaccinated. Our health service chiefs, and the journalists who report on their comments, need to do better than this.
A longer version of this article appeared in the Daily Sceptic on November 28, 2021.
how to manufacture a hospital crisis…
… and set off the next round of panic and upheaval so you can keep your emergency powers
el gato malo – bad cattitude – november 27, 2021
kathy hochul has been more or less (to use a technical term of psychiatric art) bonkers since the moment she assumed the mantle of empire state gubernatorial power from andy “let’s lie to the justice department about what happened to grandma” cuomo.
remember her terrifying rant about how the vaccines are from god and that there could be no religious exceptions because all religious leaders agree that you need the jab?
if that did not bring up the hairs on your arms, i shudder to think what would.
(full discussion HERE)
clearly, this woman is more than a few fries short of a happy meal. she seems deeply determined to prove her self to be the “fire” to señor andy’s “frying pan.” so here is the next volley:
the new variant (of which NY currently has zero cases) and that, frankly, looks more like hype than substance, is already a NY emergency.
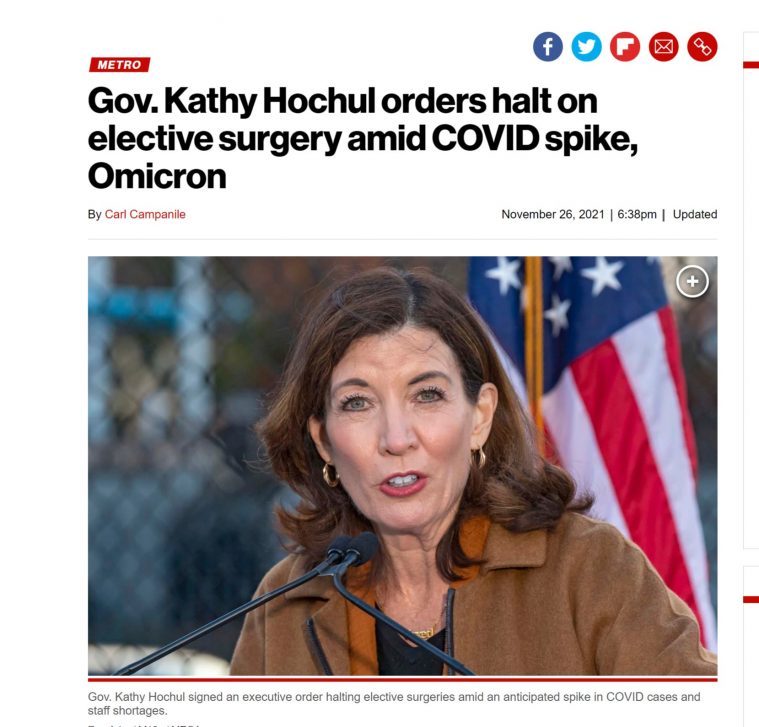
the goal here is to limit elective procedures and free up hospital capacity. but read that bottom caption closely:
“and staff shortages.”
one might be forgiven for doubting the earnestness of her claims and fears about the covid emergency here for one simple reason: the staffing shortages are of her own making and she could fix them with the stroke of a pen.
this is being driven by vaccine mandates that have forced healthcare workers out of hospitals. (just like so many of us said they would)

leaving aside the literal lunacy of not allowing health care workers to make their own health choices, this is obviously a severe issue for staffing. on the order of 20% of hospital staff have expressed unwillingness to vaccinate. it ramps to more like 30% in assisted living facilities and nursing homes.
those are HUGE numbers. crippling numbers. impossible numbers.
no hospital can run 20% short staffed without inviting calamity.
and NY (and NYC in particular) hospitals are basket cases in the best of times. they are inadequate in number and lurch from near crisis to near collapse. it’s their basic operating condition.

and obviously, we’re seeing issues with operational capability already.
and we’re only here:
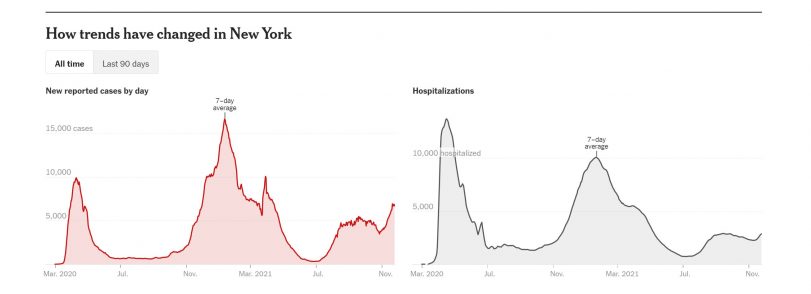
the seasonal ramp in hospitalization is just starting.
meanwhile, hospital bed capacity has dropped 12% since the beginning of the year (through 11/12, so not yet capturing the effects of some mandates biting). ICU beds are down 18%.
98% of over 65’s in NY have had a covid vaccine. 89% of 12 and up. kathy pushes them as the solution, but clearly does not trust them to save the hospitals that she seems intent on ensuring are short staffed. this seems an odd response to an “emergency.”
in an emergency, you want all hands on deck. you don’t send a big swathe of your experienced professionals home.

nothing in her behavior makes any sense. push a vaxx you don’t trust to save the hospitals you just hamstrung because of an emergency that you do not seem to actually believe in to grab fiat powers over who gets access to medical care? really?
this smacks more of crisis accentuating cosplay than of crisis management.
and NY is FAR from the only place this is going on.
it’s going to be fascinating watching new yorkers flee to florida to get surgery.
there’s a debacle brewing here, and it’s one of government and governance, not epidemiology.
this idiocy has become endemic.
it’s like watching the brandon administration curtail drilling then freak out about high gasoline prices and tap the strategic reserve or mandating unpopular vaccines and wondering why there’s a trucker shortage or paying people more not to work than they could make working and wondering why no one can hire.
it’s like half the leaders in the US have become intent on ramming pumps into the spikes of the world then wondering why we fell down.
either they are world class fools or they are wreckers intent on knocking things down so that they may pretend to “build them back better” in spasm of crony capitalism and cargo cult thinking.
a modest proposal:

Covid jab compensation claims soar in Australia
RT | November 17, 2021
Australia’s government could be forced to spend tens of millions in payouts after receiving more than 10,000 compensation claims from people who suffered side effects and loss of income due to Covid-19 vaccines.
Under its no-fault indemnity scheme, eligible claimants can apply for compensation amounts between AU$5,000 (US$3,646) to AU$20,000 (US$14,585) to cover medical costs and lost wages as a result of being hospitalized after getting the shot. The scheme’s online portal is scheduled to be launched next month.
Official figures suggest, however, that over 10,000 people have already indicated their intention to make a claim since registration opened on the health department’s website in September. If each claim was approved, the government could face a bill of at least AU$50 million (US$36.46 million).
There were around 78,880 adverse events to Covid-related vaccination in Australia as of November 7, according to the Therapeutic Goods Administration, which regulates national health products. The majority of side effects were minor, including headaches, nausea, and arm soreness.
Only people who experienced a moderate to significant adverse reaction that resulted in a hospital stay of at least one night are eligible for coverage under the government’s scheme. Those seeking $20,000 or less have to provide proof their claims are vaccine-related – although there has been no information as yet on exactly what evidence would be acceptable.
“Adverse events, even though they happen to a tiny proportion of people, for the people it does impact it’s really quite devastating,” Clare Eves, the head of medical negligence at injury compensation firm Shine Lawyers, told the Sydney Morning Herald.
Among the adverse reactions covered are the blood clotting disorder “thrombosis with thrombocytopenia syndrome (TTS)” linked to the AstraZeneca vaccine and the “myocarditis and pericarditis” heart conditions associated with the Pfizer vaccine. Other reportedly accepted side effects are Guillain-Barré syndrome, a rare neurological condition, and immune thrombocytopenia (excessive bleeding due to low platelet levels).
Claims for over $20,000, including those for vaccine-related deaths, will be assessed by an independent legal panel of legal experts and compensation paid on its recommendations. Nine people have reportedly died after an adverse reaction to one of the three vaccines in the country.
Eves told the Morning Herald that her firm was representing a number of litigants over the vaccine side effects, including several who are not eligible for the scheme.
Governor Grewsome re-emerges
Irish Savant | November 10, 2021
Well that particular mystery is solved. Or is it? We all know that vaxx evangelist Gavin Newsom disappeared from public view for nearly two weeks, cancelling a number of high-profile engagements, immediately after publicly taking his booster. He has now re-emerged but according to some reports appears to ‘look haggard’ and with shaking hands. All very interesting and couldn’t happen to a nicer guy.
But I’m intrigued by the thought that he actually did take the deadly shot. If he did it seriously undermined my whole Weltanschauung (I occasionally like to add a touch of class to this blog) – that our overlords know what the vaxx is really for and would under no circumstances inflict it on themselves. But if Newsom did actually take it rather than some saline-based alternative it means that, and this is a terrifying thought, he actually believes what he says. Can this be true?
Same question arises with Israel. Again, my working assumption was that only the goyim would benefit from the jab, that the Chosen Ones would, as is their wont, altruistically forego their share for our benefit. But no, they’re one of the most vaxxed countries in the world, and like all other highly-vaxxed countries, enjoying skyrocketing rates of infection. And presumably the accompanying reduced fertility levels?
Well no, actually. Popular commentator Flanders has supplied us with the following fascinating findings.

Yes, of all the highly-jabbed states only Israel hasn’t suffered from reduced fertility.
The plot thickens.
CDC Admits Crushing Rights of Naturally Immune Without Proof They Transmit the Virus
By Aaron Siri | Injecting Freedom | November 11, 2021
You would assume that if the CDC was going to crush the civil and individual rights of those with natural immunity by having them expelled from school, fired from their jobs, separated from the military, and worse, the CDC would have proof of at least one instance of an unvaccinated, naturally immune individual transmitting the COVID-19 virus to another individual. If you thought this, you would be wrong.
My firm, on behalf of ICAN, asked the CDC for precisely this proof (see below). ICAN wanted to see proof of any instance in which someone who previously had COVID-19 became reinfected with and transmitted the virus to someone else. The CDC’s incredible response is that it does not have a single document reflecting that this has ever occurred. Not one. (See below.)
In contrast, there are endless documents reflecting cases of vaccinated individuals becoming infected with and transmitting the virus to others. Such as this study. And this study. And this study. And this study. It goes on and on…
But it gets worse. The CDC’s excuse for not having a shred of evidence of the naturally immune transmitting the virus is that “this information is not collected.” What?! No proof! But yet the CDC is actively crushing the rights of millions of naturally immune individuals in this country if they do not get the vaccine on the assumption they can transmit the virus. But despite clear proof the vaccinated spread the virus, the CDC lifts restrictions on the vaccinated?! That is dystopian.
The facts about natural immunity are simple. Every single peer reviewed study has found that the naturally immune have far greater than 99% protection from having COVID-19, and this immunity does not wane. In contrast, the COVID-19 vaccine provides, at best, 95% protection and this immunity wanes rapidly. I am no mathematician, but a constant 99% seems preferable to a 95% that quickly drops. And, while the vaccinated readily transmit the virus, not so for the naturally immune.
The lesson yet again is not that health authorities should never make mistakes. They will. It happens. The lesson is that civil and individual rights should never be contingent upon a medical procedure. Everyone, the naturally immune or otherwise, who wants to get vaccinated and boosted should be free to do so. But nobody should be coerced by the government to partake in any medical procedure.
FOIA Request

FOIA Response

Pakistan reaches ‘complete ceasefire’ with local Taliban faction
RT | November 8, 2021
Pakistan’s government has agreed a total ceasefire with the banned Tehreek-i-Taliban Pakistan (TTP) group, Information Fawad Chaudhry has announced, noting that talks leading to the move were facilitated by authorities in Kabul.
Speaking on Monday, Chaudhry told reporters that “a complete ceasefire” agreement has been reached and further talks were taking place to ensure a lasting peace. “The talks will focus on state sovereignty, national security, peace, social and economic stability in the areas concerned,” he said, according to local media.
The minister described the move as a “positive development” and said that it would help achieve peace after a long period of conflict, adding that the Taliban, which now rules over Afghanistan, facilitated the talks.
In October, Prime Minister Imran Khan told Turkey’s TRT World that some factions of the TTP were looking for reconciliation and were speaking with the government. “There are different groups that form the TTP and some of them want to talk to our government for peace. So, we are in talks with them. It’s a reconciliation process,” Khan stated.
It had previously been suggested by Pakistan’s President Arif Alvi that a conditional amnesty for TTP members could be granted if they surrendered their weapons, accepted the state constitution, and refrained from any criminal activity.
Reuters, citing sources, reported on Saturday that the TTP had requested certain prisoners be released as a prerequisite for peace talks.
Despite being weakened by a 2014 Pakistani military campaign which drove the TTP out of its stronghold in North Waziristan, the group still has an estimated 4,000-5,000 fighters, many based across the border in Afghanistan, and has been continually involved in bloody incidents.
The TTP is an ideological twin to the Afghan Taliban and wishes to establish its interpretation of Sharia – a hard-line form of Islamic governance – in Pakistan.
100% of Covid-19 Vaccine Deaths were caused by just 5% of the batches produced: Official Government data
THE EXPOSÉ • OCTOBER 31, 2021
An investigation of data found in the USA’s Vaccine Adverse Event Reporting System (VAERS) has revealed that extremely high numbers of adverse reactions and deaths have been reported against specific lot numbers of the Covid-19 vaccines several times, meaning deadly batches of the experimental injections have now been identified.
But what’s perhaps more concerning is that the “deadly” lots were distributed widely across the United States whilst other “benign” lots were sent to just a few locations.
The data used in the investigation was pulled from the publicly accessible VAERS database which can be viewed here. The Vaccine Adverse Event Reporting System (VAERS) is a United States programme for vaccine safety, co-managed by the U.S. Centers for Disease Control and Prevention (CDC) and the Food and Drug Administration (FDA).
The programme collects information via reports made by doctors, nurses, and patients about adverse events (possible harmful side effects) that occur after administration of vaccines to ascertain whether the risk–benefit ratio is high enough to justify continued use of any particular vaccine.
The reports pulled from the database were ones that had been submitted up to October 15th 2021 and they included all adverse reactions reported against the Pfizer and Moderna mRNA Covid-19 injections, as well as all adverse reactions reported against the influenza vaccines; which were used to generate a control dataset .

The VAERS database showed a total of 1,608 adverse event reports against the flu vaccines alongside 15 deaths and 73 hospitalisations. The total count of lot numbers returned was 494.
The ‘lot number’ is a specific string of numbers and letters that tracks a specific batch of vaccine from production and into a persons arm and it is usually found on a vaccine label or accompanying packaging.

The above chart shows the number of adverse event report made to VAERS against the influenza vaccines sorted by the lot number of vaccine that was administered prior to the adverse event.
Except for a few spikes the number of adverse events per lot number was generally the same, with no more than 26 reports being made against a single lot number of influenza vaccine.

The above charts shows the count of lots by number of reports of adverse reactions per lot for the influenza vaccines. It shows that 33% of the lots (165 / 494) only had a single adverse reaction report made against them, whilst just 0.6% of the lots (3 / 494) had at least 20 adverse reaction reports made against them.

The above chart shows how many times a specific lot number was identified in an adverse reaction report of which the person had died following vaccination against the Flu. Ninety-seven-percent of the lots (480 / 494) were associated with zero deaths, whilst 13 lots were associated with a single death and 1 lot was associated with 2 deaths.

The above chart shows the number of states within the USA a specific log number of the influenza vaccine was distributed to.
The VAERS data shows that 44% of the lots (219 / 494) were sent to just a single state within the USA, whilst a further 17% (86 / 494) were sent to 2 states, 10% (50 / 494) were sent to 3 states, 5% (24 / 494) were sent to 4 states, 3% (17 / 494) were sent to 5 states, 2% (11 / 494) were sent to 6 states, and just 0.4 (2 / 494) were sent to 12 states within the USA.
All of the above data was then used as a control dataset to compare against VAERS data for the Pfizer and Moderna mRNA Covid-19 vaccines.

The VAERS database showed a total of 171,463 adverse event reports against the Pfizer Covid-19 vaccine alongside 2,828 deaths and 14,262 hospitalisations. The total count of lot numbers returned was 4,522.
This data alone shows that there have been 106 times as many adverse reactions, 189 times as many deaths, and 195 times as many hospitalisations due to the Pfizer Covid-19 jab than there have been due to all other influenza vaccines combined.

The above chart shows the number of adverse event reports made to VAERS against the Pfizer Covid-19 vaccine sorted by the lot number of vaccine that was administered prior to the adverse event. We do not have reliable information about standard lot size, but news articles indicate an average lot size of 1000 vials (approx. 6000 doses).
The highest number of adverse event reports made to VAERS against a single lot number of the influenza vaccine was 26. Which makes it all the more shocking to discover that the highest number of adverse event reports made to VAERS against a single lot number of the Pfizer Covid-19 vaccine up to October 15th 2021 was 3,563, and this isn’t an anomaly.
Thousands of adverse event reports have been made against a single lot number of the Pfizer Covid-19 vaccine numerous times, and unfortunately the Moderna Covid-19 vaccine hasn’t fared any better.

The VAERS database showed a total of 188,998 adverse event reports against the Moderna Covid-19 vaccine alongside 2,603 deaths and 10,225 hospitalisations. The total count of lot numbers returned was 5,510.
This data alone shows that there have been 118 times as many adverse reactions, 174 times as many deaths, and 140 times as many hospitalisations due to the Moderna Covid-19 jab than there have been due to all other influenza vaccines combined.

The above chart shows the number of adverse event reports made to VAERS against the Moderna Covid-19 vaccine sorted by the lot number of vaccine that was administered prior to the adverse event, and it shows that the Moderna jab fared even worse than the Pfizer jab in this department with the highest number of adverse event reports against a single lot number of Moderna Covid-19 vaccine totalling a staggering 4,967.

The above chart shows the count of lots against the range of adverse events reported per lot of Pfizer Covid-19 vaccine. The data reveals that 2,908 lots (64%) had just a single adverse event report made against them, whilst 2 specific lots had over 3000 adverse event reports made against them.
Shockingly we can also see from the data that 30 lots of Pfizer vaccine had between 1,000 and 1,499 adverse event reports per lot, another 20 lots had between 1,500 and 1,999 adverse event reports per lot, and another 23 lots had between 2,000 and 2,499 adverse event reports per lot.
This suggests that there were a small quantity of dangerous batches of the Pfizer Covid-19 vaccine and a large quantity of seemingly harmless (at least in the short term) batches of the Pfizer Covid-19 vaccine.

But the investigation of VAERS data also revealed that reported deaths due to the Pfizer vaccine were again only associated with certain batches of the jab. The chart above shows that 96% of the lots of Pfizer vaccine had zero death reports made against them. Meaning the 2,828 reported deaths were associated with just 4% of the lots of Pfizer vaccine.
Five lot numbers were associated with 61-80 deaths each, a further 5 lot numbers were associated with 81-100 deaths each, and just 2 separate lot numbers were associated with over 100 deaths each.

The same can be seen for the Moderna Covid-19 vaccine. Ninety-five-percent of the lots of Moderna vaccine had zero death reports made against them. Meaning the 2,603 deaths were associated with just 5% of the lots of Moderna vaccine.
Thirteen lot numbers were associated with 41-60 deaths each, 2 lot numbers were associated with 61-80 deaths each and 1 lot number was associated with 81-100 deaths.
The investigation of VAERS data also found that specific batches of the pfizer and Moderna Covid-19 vaccines which were distributed to between 13 and 50 states across the USA had an unusually high number of adverse event reports and deaths compared to lots that were distributed to 12 states or less across the USA

As you can see from the above table 4,289 different lots of Pfizer vaccine were distributed to 12 states or less across the USA, recording 9,141 adverse event reports against them alongside 99 deaths and 657 hospitalisations. This equates to an average of 2 adverse event reports per lot and 0 deaths and hospitalisations.
However, a further 130 different lots of Pfizer vaccine were distributed to between 13-50 states across the USA, recording 166,170 adverse event reports, 2,799 deaths, and 14,155 hospitalisations. This equates to an average of 1,278 adverse event reports per lot number, alongside 22 deaths and 109 hospitalisations.
This data therefore shows that each lot from the 130 different lot numbers of Pfizer Covid-19 vaccine distributed to more than 13 states, harmed on average 639 times more people, hospitalised on average 109 times more people, and killed on average 22 times more people.

The above chart on the left shows the number of adverse event reports by lot number sent to 13 or more states across the USA. This chart has identified the actual lot numbers of Pfizer vaccine that have caused the most harm in the USA. The most harmful of which is lot number ‘EK9231’; causing over 3,500 adverse event reports.

The above chart on the left shows the number of deaths reported as adverse reactions to the Pfizer vaccine by lot number sent to 13+ states across the USA. This chart has identified the actual lot numbers of Pfizer vaccine that have caused the most deaths in the USA. The deadliest of which is lot number ‘EN6201’ causing almost 120 deaths.

The above chart on the left shows the number of adverse event reports against the Moderna vaccine by lot number sent to 13 or more states across the USA. This chart has identified the actual lot numbers of Moderna vaccine that have caused the most harm in the USA. The most harmful of which is lot number ‘039K20A’; causing over 4,000 adverse event reports.
The second most harmful batch of Moderna vaccine was assigned lot number ‘041L20A’, and media reports show that it was actually recalled by the Orange County Healthcare Agency in January 2021 following reports of allergic reactions.


The above chart on the left shows the number of deaths reported as adverse reactions to the Moderna vaccine by lot number sent to 13+ states across the USA. This chart has identified the actual lot numbers of Moderna vaccine that have caused the most deaths in the USA. The deadliest of which is lot number ‘039K20A’ causing almost 100 deaths.
Conclusion
This investigation of VAERS data reveals several concerning findings which warrant further investigation, but it also leads to questions of why authorities within the USA which are supposed to monitor the safety of the Covid-19 vaccines have not discovered this themselves.
The data clearly shows that the Covid-19 vaccination campaign has been significantly more harmful and deadly than the influenza vaccination campaign. This fact alone begs the question as to how the FDA advisory committee could possibly vote Seventeen to Zero in favour of approving the Pfizer vaccine for use in children aged 5 to 11.
One voting member of the Food and Drug Administration (FDA) advisory committee admitted that it will not be fully known whether Pfizer’s vaccine is safe for 5 to 11-year-old children, until it begins being administered.
Dr Eric Rubin of Harvard University said – “We’re never going to learn how safe the vaccine is unless we start giving it, and that’s just the way it goes”.
But the investigation of VAERS has also identified the specific batches of Pfizer and Moderna vaccine that have caused the most harm across the USA, which leads to other extremely serious questions requiring urgent answers.
Why is it that certain batches of the vaccine have proven to be more harmful than others?
Why is it that certain batches of Covid-19 vaccine have proven to be deadlier than others?
Why is it that the most harmful and deadly Covid-19 vaccines were distributed across the entire USA, whilst the least harmful and deadly were only ever distributed to a few states? Was this done on purpose?
Could this just be a quality control issue?
A Pfizer whistleblower from a Kansas manufacturing facility did after all reveal that “People are being made to sign off on things that normally they wouldn’t, and then they wonder why their own employees won’t take it”.
Featured Video
Matt Bracken: Hezbollah Re-Arming With Massive Help From Iran
or go to
Aletho News Archives – Video-Images
From the Archives
Examples of hate speech by Israel against Palestine
1. “There is a huge gap between us (Jews) and our enemies, not just in ability but in morality, culture, sanctity of life, and conscience. They are our neighbors here, but it seems as if at a distance of a few hundred meters away, there are people who do not belong to our continent, to our world, but actually belong to a different galaxy.” Israeli president Moshe Katsav. The Jerusalem Post, May 10, 2001
2. “The Palestinians are like crocodiles, the more you give them meat, they want more”…. Ehud Barak, Prime Minister of Israel at the time – August 28, 2000. Reported in the Jerusalem Post, August 30, 2000
3. ” [The Palestinians are] beasts walking on two legs.” Menahim Begin, speech to the Knesset, quoted in Amnon Kapeliouk, “Begin and the Beasts”. New Statesman, 25 June 1982.
4. “The Palestinians” would be crushed like grasshoppers … heads smashed against the boulders and walls.” Isreali Prime Minister (at the time) in a speech to Jewish settlers New York Times April 1, 1988
5. “When we have settled the land, all the Arabs will be able to do about it will be to scurry around like drugged cockroaches in a bottle.” Raphael Eitan, Chief of Staff of the Israeli Defence Forces, New York Times, 14 April 1983.
6. “How can we return the occupied territories? There is nobody to return them to.” Golda Maier, March 8, 1969.
… Continue
Blog Roll
 Aletho News
- Voters Don’t Want the Old GOP
- Former US officials who resigned over Gaza urge 2028 presidential candidates to reject architects of Biden-era policy
- Wired for War Crimes: Israeli spy-tech firm targeted Starlink users – researchers
- There is cautious optimism about ending the Ukraine war
- Here are the Bills Pushing Forward Authoritarian Control in Canada
- The accession of Ukraine could signal the collapse of the EU
- Italy puts Ukraine weapons package on hold – media
- US kills 5 in Pacific as unproven drug smuggling claims persist
- Iran Respects International Law, US & Israel are Rogue States
- Russia Helping Build a New Middle East /Trita Parsi
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!

