We spoke to Dr Mike Yeadon about his views on the experimental Covid-19 vaccines, the medicine regulators approving them and his fears for the future.
From the outset, Dr. Yeadon said “I’m well aware of the global crimes against humanity being perpetrated against a large proportion of the worlds population.
“I feel great fear, but I’m not deterred from giving expert testimony to multiple groups of able lawyers like Rocco Galati in Canada and Reiner Fuellmich in Germany.
“I have absolutely no doubt that we are in the presence of evil (not a determination I’ve ever made before in a 40-year research career) and dangerous products.
“In the U.K., it’s abundantly clear that the authorities are bent on a course which will result in administering ‘vaccines’ to as many of the population as they can. This is madness, because even if these agents were legitimate, protection is needed only by those at notably elevated risk of death from the virus. In those people, there might even be an argument that the risks are worth bearing. And there definitely are risks which are what I call ‘mechanistic’: inbuilt in the way they work.
“But all the other people, those in good health and younger than 60 years, perhaps a little older, they don’t perish from the virus. In this large group, it’s wholly unethical to administer something novel and for which the potential for unwanted effects after a few months is completely uncharacterized.
“In no other era would it be wise to do what is stated as the intention.
“Since I know this with certainty, and I know those driving it know this too, we have to enquire: What is their motive?
“While I don’t know, I have strong theoretical answers, only one of which relates to money and that motive doesn’t work, because the same quantum can be arrived at by doubling the unit cost and giving the agent to half as many people. Dilemma solved. So it’s something else. Appreciating that, by entire population, it is also intended that minor children and eventually babies are to be included in the net, and that’s what I interpret to be an evil act.
“There is no medical rationale for it. Knowing as I do that the design of these ‘vaccines’ results, in the expression in the bodies of recipients, expression of the spike protein, which has adverse biological effects of its own which, in some people, are harmful (initiating blood coagulation and activating the immune ‘complement system’), I’m determined to point out that those not at risk from this virus should not be exposed to the risk of unwanted effects from these agents.”
The Israel Supreme Court decision last week cancelling COVID flight restrictions said: “In the future, any new restrictions on travel into or out of Israel need, in legal terms, a comprehensive, factual, data-based foundation.”
“The most likely duration of immunity to a respiratory virus like SARS CoV-2 is multiple years. Why do I say that? We actually have the data for a virus that swept through parts of the world seventeen years ago called SARS, and remember SARS CoV-2 is 80% similar to SARS, so I think that’s the best comparison that anyone can provide.
“The evidence is clear: These very clever cellular immunologists studied all the people they could get hold of who had survived SARS 17 years ago. They took a blood sample, and they tested whether they responded or not to the original SARS and they all did; they all had perfectly normal, robust T cell memory. They were actually also protected against SARS CoV-2, because they’re so similar; it’s cross immunity.
“So, I would say the best data that exists is that immunity should be robust for at least 17 years. I think it’s entirely possible that it is lifelong. The style of the responses of these people’s T cells were the same as if you’ve been vaccinated and then you come back years later to see if that immunity has been retained. So I think the evidence is really strong that the duration of immunity will be multiple years, and possibly lifelong.”
In other words, previous exposure to SARS – that is, a variant similar to SARS CoV-2 – bestowed SARS CoV-2 immunity.
The Israel government cites new variants to justify lockdowns, flight closures, restrictions, and Green Passport issuance. Given the Supreme Court verdict, do you think it may be possible to preempt future government measures with accurate information about variants, immunity, herd immunity, etc. that could be provided to thelawyers who will be challenging those future measures?
Yeadon: “What I outlined in relation to immunity to SARS is precisely what we’re seeing with SARS-CoV-2.The study is from one of the best labs in their field.” So, theoretically, people could test their T-cell immunity by measuring the responses of cells in a small sample of their blood. There are such tests, they are not “high throughput” and they are likely to cost a few hundred USD each on scale. But not thousands. The test I’m aware of is not yet commercially available, but research only in U.K.
“However, I expect the company could be induced to provide test kits “for research” on scale, subject to an agreement. If you were to arrange to test a few thousand non vaccinated Israelis, it may be a double edged sword. Based on other countries experiences, 30-50% of people had prior immunity & additionally around 25% have been infected & are now immune.
“Personally, I wouldn’t want to deal with the authorities on their own terms: that you’re suspected as a source of infection until proven otherwise. You shouldn’t need to be proving you’re not a health risk to others. Those without symptoms are never a health threat to others. And in any case, once those who are concerned about the virus are vaccinated, there is just no argument for anyone else needing to be vaccinated.”
My understanding of a “leaky vaccine” is that it only lessens symptoms in the vaccinated, but does not stop transmission; it therefore allows the spread of what then becomes a more deadly virus.
For example, in China they deliberately use leaky Avian Flu vaccines to quickly cull flocks of chicken, because the unvaccinated die within three days. In Marek’s Disease, from which they needed to save all the chickens, the only solution was to vaccinate 100% of the flock, because all unvaccinated were at high risk of death. So how a leaky vax is utilized is intention-driven, that is, it is possible that the intent can be to cause great harm to the unvaccinated.
Stronger strains usually would not propagate through a population because they kill the host too rapidly, but if the vaccinated experience only less-serious disease, then they spread these strains to the unvaccinated who contract serious disease and die.
Do you agree with this assessment? Furthermore, do you agree that if the unvaccinated become the susceptible ones, the only way forward is HCQ prophylaxis for those who haven’t already had COVID-19?
Would the Zelenko Protocol work against these stronger strains if this is the case? And if many already have the aforementioned previous “17-year SARS immunity”, would that then not protect from any super-variant?
“I think the Gerrt Vanden Bossche story is highly suspect. There is no evidence at all that vaccination is leading or will lead to ‘dangerous variants’. I am worried that it’s some kind of trick.
“As a general rule, variants form very often, routinely, and tend to become less dangerous & more infectious over time, as it comes into equilibrium with its human host. Variants generally don’t become more dangerous.
“No variant differs from the original sequence by more than 0.3%. In other words, all variants are at least 99.7% identical to the Wuhan sequence.
“It’s a fiction, and an evil one at that, that variants are likely to “escape immunity.”
“Not only is it intrinsically unlikely – because this degree of similarity of variants means zero chance that an immune person (whether from natural infection or from vaccination) will be made ill by a variant – but it’s empirically supported by high-quality research.
“The research I refer to shows that people recovering from infection or who have been vaccinated ALL have a wide range of immune cells which recognize ALL the variants.
“This paper shows WHY the extensive molecular recognition by the immune system makes the tiny changes in variants irrelevant.
“I cannot say strongly enough: The stories around variants and need for top up vaccines are FALSE. I am concerned there is a very malign reason behind all this. It is certainly not backed by the best ways to look at immunity. The claims always lack substance when examined, and utilize various tricks, like manipulating conditions for testing the effectiveness of antibodies. Antibodies are probably rather unimportant in host protection against this virus. There have been a few ‘natural experiments’, people who unfortunately cannot make antibodies, yet are able quite successfully to repel this virus. They definitely are better off with antibodies than without. I mention these rare patients because they show that antibodies are not essential to host immunity, so some contrived test in a lab of antibodies and engineered variant viruses do NOT justify need for top up vaccines.
“The only people who might remain vulnerable and need prophylaxis or treatment are those who are elderly and/or ill and do not wish to receive a vaccine (as is their right).
“The good news is that there are multiple choices available: hydroxychloroquine, ivermectin, budesonide (inhaled steroid used in asthmatics), and of course oral Vitamin D, zinc, azithromycin etc. These reduce the severity to such an extent that this virus did not need to become a public health crisis.”
Do you feel the MHRA does a good job regulating ‘big pharma’? In what ways does ‘big pharma’ get around the regulator? Do you feel they did so for the mRNA jab?
“Until recently, I had high regard for global medicines regulators. When I was in Pfizer, and later CEO of a biotech I founded (Ziarco, later acquired by Novartis), we interacted respectfully with FDA, EMA, and the MHRA.
Always good quality interactions.
“Recently, I noticed that the Bill & Melinda Gates Foundation (BMGF) had made a grant to the Medicines and Healthcare products Regulatory Agency (MHRA)! Can that ever be appropriate? They’re funded by public money. They should never accept money from a private body.
“So here is an example where the U.K. regulator has a conflict of interest.” The European Medicines Agency failed to require certain things as disclosed in the ‘hack’ of their files while reviewing the Pfizer vaccine.
“You can find examples on Reiner Fuellmich’s “Corona Committee” online.
“So I no longer believe the regulators are capable of protecting us. ‘Approval’ is therefore meaningless.
“Dr. Wolfgang Wodarg and I petitioned the EMA Dec 1, 2020 on the genetic vaccines. They ignored us.
“Recently, we wrote privately to them, warning of blood clots, they ignored us. When we went public with our letter, we were completely censored. Days later, more than ten countries paused use of a vaccine citing blood clots.
“I think the big money of pharma plus cash from BMGF creates the environment where saying no just isn’t an option for the regulator.
“I must return to the issue of ‘top up vaccines’ (booster shots) and it is this whole narrative which I fear will he exploited and used to gain unparalleled power over us.
“PLEASE warn every person not to go near top up vaccines. There is absolutely no need to them. As there’s no need for them, yet they’re being made in pharma, and regulators have stood aside (no safety testing), I can only deduce they will be used for nefarious purposes.
“For example, if someone wished to harm or kill a significant proportion of the worlds population over the next few years, the systems being put in place right now will enable it.
“It’s my considered view that it is entirely possible that this will be used for massive-scale depopulation.”
Back in January I wrote an article about four randomized controlled trials of ivermectin as a treatment for covid-19 that had at that time released their results to the public. Each of those four trials had promising results, but each was also too small individually to show any meaningful impact on the hard outcomes we really care about, like death. When I meta-analyzed them together however, the results suddenly appeared very impressive. Here’s what that meta-analysis looked like:
It showed a massive 78% reduction in mortality in patients treated with covid-19. Mortality is the hardest of hard end points, which means it’s the hardest for researchers to manipulate and therefore the least open to bias. Either someone’s dead, or they’re alive. End of story.
You would have thought that this strong overall signal of benefit in the midst of a pandemic would have mobilized the powers that be to arrange multiple large randomized trials to confirm these results as quickly as possible, and that the major medical journals would be falling over each other to be the first to publish these studies.
That hasn’t happened.
Rather the opposite, in fact. South Africa has even gone so far as to ban doctors from using ivermectin on covid-19 patients. And as far as I can tell, most of the discussion about ivermectin in mainstream media (and in the medical press) has centred not around its relative merits, but more around how its proponents are clearly deluded tin foil hat wearing crazies who are using social media to manipulate the masses.
In spite of this, trial results have continued to appear. That means we should now be able to conclude with even greater certainty whether or not ivermectin is effective against covid-19. Since there are so many of these trials popping up now, I’ve decided to limit the discussion here only to the ones I’ve been able to find that had at least 150 participants, and that compared ivermectin to placebo (although I’ll add even the smaller trials I’ve found in to the updated meta-analysis at the end).
As before, it appears that rich western countries have very little interest in studying ivermectin as a treatment for covid. The three new trials that had at least 150 participants and compared ivermectin with placebo were conducted in Colombia, Iran, and Argentina. We’ll go through each in turn.
The Colombian trial (Lopez-Medina et al.) was published in JAMA (the Journal of the American Medical Association) in March. There is one thing that is rather odd with this study, and that is that the study authors were receiving payments from Sanofi-Pasteur, Glaxo-Smith-Kline, Janssen, Merck, and Gilead while conducting the study. Gilead makes remdesivir. Merck is developing two expensive new drugs to treat covid-19. Janssen, Glaxo-Smith-Kline, and Sanofi-Pasteur are all developers of covid vaccines. In other words, the authors of the study were receiving funding from companies that own drugs that are direct competitors to ivermectin. One might call this a conflict of interest, and wonder whether the goal of the study was to show a lack of benefit. It’s definitely a little bit suspicious.
Anyway, let’s get to what the researchers actually did. This was a double-blind randomized controlled trial that recruited patients with mildly symptomatic covid-19 who had experienced symptom onset less than 7 days earlier. Potential participants were identified through a statewide database of people with positive PCR-tests. By “mildly symptomatic” the researchers meant people who had at least one symptom but who did not require high-flow oxygen at the time of recruitment in to the trial.
Participants in the treatment group received 300 ug/kg body weight of ivermectin every day for five days, while participants in the placebo group received an identical placebo. 300 ug/kg works out to 21 mg for an average 70 kg adult, which is quite high, especially when you consider that the dose was given daily for five days. For an average person, this would work out to a total dose of 105 mg. The other ivermectin trials have mostly given around 12 mg per day for one or two days, for a total dose of 12 to 24 mg (which has been considered enough because ivermectin has a long half-life in the body). Why this study gave such a high dose is unclear. However, it shouldn’t be a problem. Ivermectin is a very safe drug, and studies have been done where people have been given ten times the recommended dose without any noticeable increase in adverse events.
The stated goal of the study was to see if ivermectin resulted in more rapid symptom resolution than placebo. So participants were contacted by telephone every three days after inclusion in the study, up to day 21, and asked about what symptoms they were experiencing.
398 patients were included in the study. The median age of the participants was 37 years, and they were overall very healthy. 79% had no known co-morbidities. This is a shame. It means that this study is yet another one of those many studies that will not be able to show a meaningful effect on hard end points like hospitalization and death. It is a bit strange that studies keep being done on young healthy people who are at virtually zero risk from covid-19, rather than on the multi-morbid elderly, who are the ones we actually need an effective treatment for.
Anyway, let’s get to the results.
In the group treated with ivermectin, the average time from inclusion in the study to becoming completely symptom free was 10 days. In the placebo group that number was 12 days. So, the ivermectin treated patients recovered on average two days faster. However, the difference was not statistically significant, so the result could easily be due to chance. At 21 days after inclusion in the study, 82% had recovered fully in the ivermectin group, as compared to 79% in the placebo group. Again, the small difference was not statistically significant.
In terms of the hard end points that matter more, there were zero deaths in the ivermectin group and there was one death in the placebo group. 2% of participants in the ivermectin group required “escalation of care” (hospitalization if they were outside the hospital at the start of the study, or oxygen therapy if they were in hospital at the start of the study) as compared with 5% in the placebo group. None of these differences was statistically significant. But that doesn’t mean they weren’t real. Like I wrote earlier, the fact that this was a study of healthy young people meant that, even if a meaningful difference does exist in risk of dying of covid, or of ending up in hospital, this study was never going to find it.
So, what can we conclude?
Ivermectin does not meaningfully shorten duration of symptoms in healthy young people. That’s about all we can say from this study. Considering the conflicts of interest of the authors, my guess is that this was the goal of the study all along: Gather together a number of young healthy people that is too small for there to be any chance of a statistically significant benefit, and then get the result you want. The media will sell the result as “study shows ivermectin doesn’t work” (which they dutifully did).
It is interesting that there were signals of benefit for all the parameters the researchers looked at (resolution of symptoms, escalation of care, death), but that the relatively small number and good health status of the participants meant that there was little chance of any of the results reaching statistical significance.
Let’s move on to the next study, which is currently available as a pre-print on Research Square (Niaee et al.). It was randomized, double-blind, and placebo-controlled, and carried out at five different hospitals in Iran. It was funded by an Iranian university.
In order to be included in the trial, participants had to be over the age of 18 and admitted to hospital because of a covid-19 infection (which was defined as symptoms suggestive of covid plus either a CT scan typical of covid infection or a positive PCR test).
150 participants were randomized to either placebo (30 people) or varying doses of ivermectin (120 people). The fact that they chose to make the placebo group so small is a problem, because it makes it very hard to detect any differences even if they do exist, by making the statistical certainty of the results in the placebo group very low.
The participants were on average 56 years old and the average oxygen saturation before initiation of treatment was 89% (normal is more than 95%), so this was a pretty sick group. Unfortunately no information is provided on how far along people were in the disease course when they started receiving ivermectin. It stands to reason that the drug is more likely to work if given ten days after symptom onset than when given twenty days after symptom onset, since death usually happens around day 21. If you, for example, wanted to design a trial to fail, you could start treating people at a time point when there is no time for the drug you’re testing to have a chance work, so it would have been nice to know at what time point treatment started in this trial.
So, what were the results?
20% of the participants in the placebo group died (6 out of 30 people). 3% of the participants in the various ivermectin groups died (4 out of 120 people). That is an 85% reduction in the relative risk of death, which is huge.
So, in spite of the fact that the placebo group was so small, it was still possible to see a big difference in mortality. Admittedly, this is a pre-print (i.e. it hasn’t been peer-reviewed yet), and the absolute numbers of deaths are small, so there is some scope for random chance to have created these results (maybe people in the placebo group were just very unlucky!). However, the study appears to have followed all the steps expected for a high quality trial. It was carried out at multiple different hospitals, it used randomization and a control group that received a placebo, and it was double-blinded. And death is a very hard end point that is not particularly open to bias. So unless the researchers have falsified their data, then this study constitutes reasonably good evidence that ivermectin is highly effective when given to patients hospitalized with covid-19. That’s great, because it would mean that the drug can be given quite late in the disease course and still show benefit.
Let’s move on to the third trial (Chahla et al.), which is currently available as a pre-print on MedRxiv. It was carried out in Argentina, and funded by the Argentinean government. Like the first trial we discussed, this was a study of people with mild disease. It literally boggles my mind that so many researchers choose to study people with mild disease instead of studying those with more severe disease. Especially when you consider that these studies are all so small. A study of people with mild disease needs to be very large to find a statistically significant effect, since most people with covid do well regardless. The risk of false negative results is thus enormous. If you’re going to do a small-ish study, and you want to have a reasonable chance of producing results that reach statistical significance, it would make much more sense to do it on sick hospitalized patients.
The study was randomized, but it wasn’t blinded, and there was no placebo. In other words, the intervention group received ivermectin (24 mg per day), while the control group didn’t receive anything. This is a bad bad thing. It means that any non-hard outcomes produced by the study are really quite worthless, since there is so much scope for the placebo effect and other confounding factors to mess up the results. For hard outcomes, in particular death, it should be less of a problem (although we wouldn’t expect any deaths in such a small study of mostly healthy people with mild disease anyway).
The study included people over the age of 18 with symptoms suggestive of covid-19 and a positive PCR test. The average age of the participants was 40 years, and most had no underlying health issues. A total of 172 people were recruited in to the study.
The researchers chose to look at how quickly people became free of symptoms as their primary endpoint. This is enormously problematic, since the study, as already mentioned, wasn’t blinded and there was no placebo. Any difference between the groups could easily be explained by the placebo effect and by biases towards treatment benefit among the researchers.
Anyway, the study found that 49% in the treatment group were free of symptoms at five to nine days after the beginning of treatment, compared with 81% in the control group. However, the lack of blinding means that this result is worthless. The methodology is just too flawed.
No data is provided on the number of people who died in each group. Since it isn’t reported, I think it’s safe to assume that there were no deaths in either group. Nor is any data provided on the number of hospitalizations in each group.
So, what does this study tell us?
Absolutely nothing at all. What a waste of time and money.
Let’s move on and update our meta-analysis. The reason we need to do a meta-analysis here is that none of the trials of ivermectin is large enough on its own to provide a definitive answer as to whether it is a useful treatment for covid-19 or not. For those who haven’t heard of meta-analyses before, basically what you do is just take the results from all different studies in existence that fulfill your pre-selected criteria, and then put them together, so as a to create a single large “meta”-study. This allows you to produce results that have a much higher level of statistical significance. It is particularly useful in a situation where all the individual trials you have to work with are statistically underpowered (have too few participants), as is the case here.
In this new meta-analysis, I’ve included every double-blind randomized placebo-controlled trial I could find of ivermectin as a treatment for covid. Using only double-blind placebo-controlled trials means that only the highest quality studies are included in this meta-analysis, which minimizes the risk of biases messing up the results as far as possible. In order to be included, a study also had to provide mortality data, since the goal of the meta-analysis is to see if there is any difference in mortality.
I was able to identify seven trials that fulfilled these criteria, with a total of 1,327 participants. Here’s what the meta-analysis shows:
What we see is a 62% reduction in the relative risk of dying among covid patients treated with ivermectin. That would mean that ivermectin prevents roughly three out of five covid deaths. The reduction is statistically significant (p-value 0,004). In other words, the weight of evidence supporting ivermectin continues to pile up. It is now far stronger than the evidence that led to widespred use of remdesivir earlier in the pandemic, and the effect is much larger and more important (remdesivir was only ever shown to marginally decrease length of hospital stay, it was never shown to have any effect on risk of dying).
I understand why pharmaceutical companies don’t like ivermectin. It’s a cheap generic drug. Even Merck, the company that invented ivermectin, is doing it’s best to destroy the drug’s reputation at the moment. This can only be explained by the fact that Merck is currently developing two expensive new covid drugs, and doesn’t want an off-patent drug, which it can no longer make any profit from, competing with them.
The only reason I can think to understand why the broader medical establishment, however, is still so anti-ivermectin is that these studies have all been done outside the rich west. Apparently doctors and scientists outside North America and Western Europe can’t be trusted, unless they’re saying things that are in line with our pre-conceived notions.
Researchers at McMaster university are currently organizing a large trial of ivermectin as a treatment for covid-19, funded by the Bill and Melinda Gates foundation. That trial is expected to enroll over 3,000 people, so it should be definitive. It’s going to be very interesting to see what it shows when the results finally get published.
You first heard of ‘too big to fail’ banks in 2008 when the global economic collapse destroyed lives and businesses and few, if any fraudster bankers went to jail.
Don’t be surprised to learn that ‘too big to fail‘ also applies to those Big Pharma entities in cahoots with corrupt politicians. This short video explains how Pfizer, conspiring with bent regulators, uses shell companies to get away with their vaccine crimes.
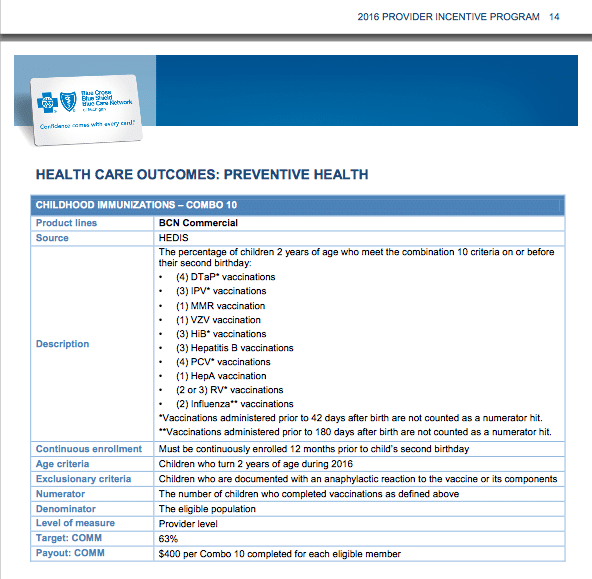
Here is a perfect example of the tactics that Big Pharma uses to incentivize doctors to push vaccines on the public. Insurance company Blue Cross Blue Shield (BCBS) pays pediatricians $400 for EACH fully vaccinated child under the age of 2. This means that for every 100 vaccinated patients, the doctor gets a $40,000 bonus!
Moreover, it is now very difficult to find a pediatrician who will accept a family who doesn’t vaccinate. Even parents who partially vaccinate or follow a different schedule have a hard time finding a doctor. Here’s why: doctors have to vaccinate a certain percentage of their patients or they don’t get their bonus. BCBS says doctors need to vaccinate 63% of their patients to get the payout.
BCBS outlines the incentive program for vaccinating babies in the BCBS doctor incentives booklet. Below is an image of the childhood immunization incentives page.
The program specifies that patients under the age of 2 must receive 24 inoculations for the doctor to receive the $400 per-patient payout. Notice the list includes the flu vaccine, even though evidence suggests that the flu vaccine actually weakens the immune system long-term. Furthermore, during the 2012-2013 flu season, the flu vaccine’s effectiveness was found to be just 56 percent across all age groups reviewed by the CDC.
Exorbitant Payouts for Vaccinating Babies
So how much money can a doctor make by pushing vaccines on trusting parents? Here’s the breakdown:
The average American pediatrician has 1546 patients, though some pediatricians see many more. The vast majority of those patients are very young, perhaps because children transition to a family physician or stop visiting the doctor at all as they grow up. As they table above explains, Blue Cross Blue Shield pays pediatricians $400 per fully vaccinated child. If your pediatrician has just 100 fully-vaccinated patients turning 2 this year, that’s $40,000. Yes, Blue Cross Blue Shield pays your doctor a $40,000 bonus for fully vaccinating 100 patients under the age of 2. If your doctor manages to fully vaccinate 200 patients, that bonus jumps to $80,000. (source: CongitiveTruths.com)
Doctors Receive Bribes for More Than Vaccinations
The complete BCBS doctor incentives booklet was posted by CognitiveTruths.comhere.
The booklet shows that payouts aren’t available just for vaccines. Doctors receive bonuses for making sure that patients “adhere to their prescribed drug therapy.” This falls under BCBS category of “disease management” and includes statins, drugs for hypertension, and oral diabetes medications. Doctors also receive bonuses for helping patients manage depression… but only if they do so using drugs.
These types of practices by the medical establishment give rise to many questions. First, are doctors more concerned about earning their bonus than about children’s health? That would explain why so many doctors are no longer taking families that do not vaccinate. Further, do doctors even care if the one-size-fits-all approach to vaccination is safe?
Finally, if doctors receive payouts for disease management, then why would they want to cure their patients? This approach definitely illustrates the biggest problem of our medical establishment. Let’s face it, the establishment is creating long-term customers instead of curing patients.
You don’t think things are going to go back to normal on the 21st June 2021 do you? The evidence is mounting to the contrary and the latest piece of the puzzle has cost the British tax-payer £320 million.
Previous pieces of the puzzle have come in the form of a document produced for the UK Government entitled ‘Summary of further modelling of easing of restrictions – Roadmap Step 2’, and a contract currently out for tender for the employment of ‘Covid Marshals’.
The former declares that a third wave is inevitable and that it will be the fault of children and those who refuse the experimental Covid-19 vaccines. Whilst the latter confirms that Covid Marshals will be employed from the 1st July 2021 until the end of January 2022 at the earliest, to the tune of £3 million of tax-payers money.
The latest evidence that things will not be returning to normal on the 21st June 2021 comes in the form of a contract which has been awarded to a single company, costing the British tax-payer £320 million. The contract has a start date of 1st April 2021 and is due to run until the 31st March 2022. It’s stated purpose? “The provision of Media buying services for COVID 19 campaigns.”
The closing date for applications was 12am on the 31st March 2021 and the contract was awarded to ‘OMD Group Limited’. The company is based in London and has a financial director named ‘BELL, Ronald James‘ who has been with the company since the 1st November 2017. But we can also see that there have been three new appointees to the board on the 22nd February 2021. These include FENTON, Laura Claire who has been appointed as CEO. PANESAR, Ravinder who has been appointed as a financial director. And STURGEON, Natalie who has been appointed as CEO.
The three new appointees have certainly struck gold rather quick. We wonder if these people have any ties or links to any members of Boris Johnson’s current Cabinet? Track record would suggest so.
The Government has already spent hundreds of millions of tax payers money since March 2020 to advertise the fact that there is a pandemic and now plan to carry on the tradition for at least another year. The question is, if there was really a deadly pandemic would authorities need to advertise it?
The answer of course lies in the fact that this has never been about a virus, and has always been about control. This £320 million contract is to fund propaganda and maintain the level of fear that they have created in a large amount of the UK population.
The contract also explains why the mainstream media have remained largely silent and toed the line at all times in regards to the narrative being portrayed by the UK Government and their circle of scientific advisors. It would cost them millions of pounds in advertising fees if they refused to do so.
Think things will go back to normal on the 21st June 2021? Think again. This won’t end until we all say it does.
A doctor from the Philippines strongly defended the use of ivermectin for preventing and treating COVID-19, pointing to “80 clinical studies” which support his arguments, and alluding to “bias” and conflicts of interest, which have led medical bodies to be reluctant about promoting the drug.
Appearing on Philippine television channel ABS–CBN, Dr. Benigno Agbayani answered a range of questions about the efficacy and safety of the drug, as well as the peculiar reticence to recommend it for treating COVID-19.
Agbayani, the president of Concerned Doctors and Citizens of the Philippines, revealed that since last year, he had spent over five hours a day studying scientific literature on all things pertaining to COVID-19, including the non-effectiveness of lockdowns. “I think I’ve read more than anyone on COVID-19,” he stated.
However, Agbayani did not spend long defending his medical credentials, but instead advocated the use of ivermectin by referring to the wealth of scientific studies with which he was by now very familiar. He already prescribed ivermectin to over 300 of his own patients, but despite the success he has experienced so far, Agbayani stated that he looks “at the success rate of studies, rather than my personal experience, because that’s where I base my recommendations.”
“As much as anecdotal [pieces of evidence] are good, and we have many, I really prefer that we stick to the science,” he said. “People are trying to scare us from taking ivermectin. It’s one of the safest drugs in the world.”
Mentioning a study from September 2020, Agbayani stated that ivermectin had been shown to actually block “the receptor sites of the virus onto our cells, therefore blocking it from ever getting to the cell.”
“You have over 26, as of today, randomized control trials showing effectiveness, even as high as 89% for prevention, and as high as 80% for treatment. So I think regardless of what the other groups are doing, you have so much science behind it, I do not see why we have to be so concerned.”
Some studies mentioned ivermectin in conjunction with accompanying treatments, but Agbayani noted that even with this, it was possible to prove the effectiveness of ivermectin on its own. Pointing to the evidence found by Dr. Tess Lawrie, Agbayani explained that the drugs accompanying ivermectin in the studies were there, “but not all the time,” and that they “have already been proven not to work, so if you have two drugs given with ivermectin, and one drug doesn’t work, then you have to conclude that it must be ivermectin,” which produces the result.
He alluded to the peculiar antagonism which has been levied against ivermectin, noting how scepticism regarding studies promoting ivermectin is not mirrored with other drugs: “[T]he same thing can be said of every drug that we tried. Even people who are taking remdesevir, they also try other drugs, and yet you don’t question that.”
Continuing, he noted that “most” of the drugs accompanying ivermectin in the trials were “not even anti-virus [drugs], most of them are supportive of your immune systems.”
“There are 80 clinical studies [about the use of ivermectin]. If the 80 clinical studies show positive response, and maybe about 2% only showing no response to ivermectin, in clinical studies, of the doses that we give, I think that should be enough proof that it works.”
Drawing once more on the scientific data, Agbayani promoted ivermectin both as a prophylactic, and as a treatment once infected with COVID-19. Conclusions drawn from “at least 12 clinical studies,” of which 3 were randomized, controlled trials, revealed “an 89% rate of preventing COVID-19.”
Global Reluctance Regarding Ivermectin
Yet despite this, medical bodies have been consistently reluctant to promote the use of ivermectin, with Big Tech even weighing in and deleting videos which defended the drug. Thanks to the efforts of the Front Line Covid-19 Critical Care Alliance (FLCCC), the U.S. National Institutes of Health (NIH) upgraded their recommendation for the “miraculous” drug ivermectin, making it an option for use in treating COVID-19 within the United States, but only since January.
Agbayani suggested two reasons for the global reticence regarding the drug. Dealing first with the NIH, he suggested that “the NIH, the U.S. I mean, just needs to update their data. I think the last time they gave an update was February. They said it could be useful, it may not be useful.”
But he also mentioned that there was some deliberate avoidance at properly promoting ivermectin, commenting on how the World Health Organization’s March 3 recommendation of the drug did not include preventative use, but “only mentioned treatment and for severe cases. For severe cases and early treatment.”
“They did not include prophylaxis, because I think they’re afraid to recommend it, that’s why they did not make a comment,” he continued. “If you look at the way they studied it, they did include so many other studies … there seems to be a bias in those recommendations and we feel that they do not want to look at certain studies preferentially, and this was observed even before this recent announcement.”
“There is some kind of bias going on that we’d like to question. This is the time in our history when we should look at conflicts of interest.”
Such a conflict of interest could exist in the vaccine company Merck, Agbayani added, in answer to why the company even issued a statement advising against the use of ivermectin for COVID, despite having developed it some 30 years prior. This was an “excellent example of conflict of interest,” stated Agbayani.
“Merck is coming out with a new drug for the early treatment of COVID-19. How can Merck make money out of ivermectin, if the patents already expired in 1996, so even if it tries that, I don’t think they’ll make money at all, when so many other companies are making ivermectin. So they have to put their mouth on their research expenses on their new drug.”
Despite Merck joining other vaccine companies in pushing out speedily developed new drugs, ivermectin was still being side-lined, although it has been “used for 25 years,” said Agbayani. Even taking a dose, “ten times” the NIH daily recommended amount, would “have no [side] effect.”
“Compare that to other drugs that we are now using that are fairly new, where you are getting so many reports of side effects. So it’s really amazing that people still say it’s an unsafe drug when it’s been used for 25 years, over 3.7 billion doses have been given.”
Dr. Agbayani is by no means alone in his promotion of ivermectin for treating and preventing COVID-19.
Back in December, intensive care specialist Dr. Pierre Kory, a founding member of the FLCCC, delivered an impassioned address to the Senate Homeland Security Committee, defending the “miraculous effectiveness of ivermectin,” and stating that it “basically obliterates transmission of this virus.”
“It literally destroys the virus in most people within 48 hours,” agreed fellow panelist Dr. Jean-Jacques Rajter, whose peer-reviewed study found 60% fewer deaths among patients given the drug.
In fact, the efficacy of ivermectin with regard to COVID-19 was already hinted at in April 2020, when researchers in Australia pointed to a dramatic effect the drug had on the virus. “We showed that a single dose of Ivermectin could kill COVID-19 in a petri dish within 48 hours, indicating potent antiviral activity,” stated Dr. David Jans, a professor of biochemistry and molecular biology at Monash University in Melbourne.
Even after just 24 hours, “there was a really significant reduction” in the virus, added Dr. Kylie Wagstaff, a senior research fellow in biochemistry and molecular biology at Monash University.
A nuclear waste storage tank at a defunct plutonium reactor in Washington state has sprung a leak, the Department of Energy said, as local officials warn the aging vessel will emit 1,300 gallons of chemicals over the next year.
The leaking tank, located at the Hanford site in southeast Washington, just 8 miles west of the Columbia River, was announced on Thursday by the Energy Department. A breach in the 75-year-old storage reservoir was suspected more than a year ago but only confirmed recently, one of several decrepit tanks at the facility.
“It’s a serious matter whenever a Hanford tank leaks its radioactive and dangerous chemical waste,” the state’s ecology director, Laura Watson, said in a statement, adding that that officials do not believe the breach poses “increased risk to workers or the public,” though it does contribute to “the ongoing environmental threat at Hanford.”
“This leak is adding to the estimated one million gallons of tank waste already in the soil across the Hanford site. This highlights the critical need for resources to address Hanford’s aging tanks, which will continue to fail and leak over time.”
While the problematic tank, designated B-109, is only the second officially confirmed leak at Hanford, (the first was detected in 2013), many of the site’s 149 storage tanks are suspected to have issues, with the Washington Ecology Department estimating that more than 200,000 gallons of waste have escaped from the “B Farm” alone, where B-109 is located. Across the whole Hanford facility, they believe 1 million gallons have poured from compromised tanks.
With B-109 leaking an estimated 3.5 gallons each day, or 1,300 gallons per year, the concerns are compounded by the tank’s close proximity to the water table, sitting just over 200 feet above, as well as the Columbia River.
A formal leak assessment was launched last year after the tank’s levels were found to be dropping, and though a breach was discovered, local officials’ hands remain tied under an agreement governing clean-up operations at Hanford. Environmental agencies can only take “immediate action” in response to a leak if it is deemed “necessary to abate an imminent and substantial endangerment to public health or welfare or the environment.” For now, the state, as well as federal agencies, have assessed no immediate danger from B-109, despite the confirmed leak.
“Contamination in this area is not new and mitigation actions have been in place for decades to protect workers, the public and the environment,” Energy Department spokesman Geoff Tyree told the Associated Press, adding “There is no increased health or safety risk to the Hanford workforce or the public.”
Hanford has seen a years-long, multi-billion-dollar clean-up effort due to its ailing equipment, which itself has become controversial. In 2019, the federal government sued arms dealer Lockheed Martin, which was awarded a $3.2 billion contract in the clean-up project alongside another private company, alleging it defrauded American taxpayers with illegal kickback payments.
The site’s management has also come under fire in recent years, with workers accused of deliberately dumping toxic waste into the environment in 2017.
The Hanford facility has a rich history stretching back to the days of the Manhattan Project, becoming the site for the world’s first large-scale plutonium production reactor. Plutonium manufactured there was used in the first nuclear bomb test at the Trinity site, as well as in Fat Man, the bomb dropped on Nagasaki, Japan in the waning days of World War II.
The B-109 tank came online in 1946, running for 30 years before it was shut down, while the entire facility was shuttered in 1987, leaving behind 53 million gallons of waste. Since then, local authorities have worked to stabilize the remaining storage vessels, but problems keep piling up, as thousands of gallons of hazardous materials continue to flow into the soil unabated.
As much of the world rushes to receive a lightly-tested pharmaceutical product, we thought it was high time to look again at the (very) big business of medicine. Leemon McHenry, PhD, guides us to the fraudulent core of ghostwritten studies, captured legislators, revolving-door regulatory agencies, pay-to-play medical journals, and the “key opinion leaders” who lend their academic credentials to giant corporations… for a price.
With every stage in the process seemingly structured for corruption, we can only wonder along with Professor McHenry: “Who’s looking out for scientific integrity?”
By the time you finish this episode of Perspectives, you might just roll down your sleeve for a rethink.
The Interviewee:Leemon McHenry PhD is a bioethicist and Emeritus Professor of Philosophy at California State University, Northridge, in the United States. He has taught philosophy at the University of Edinburgh, Old Dominion University, Davidson College, Central Michigan University, Wittenberg University and Loyola Marymount University, and has held visiting research positions at Johns Hopkins University, UCLA and at the Institute for Advanced Studies in the Humanities in the University of Edinburgh. His research interests center on medical ethics, metaphysics, and philosophy of science.
The Interviewer: John Kirby is the director of FOUR DIED TRYING, a feature documentary and series on the major assassinations of the 1960s and their calamitous impact on the country. To join the struggle for justice for Dr. King, Malcolm X, and John and Robert Kennedy.
Follow Journeyman Pictures on youtube or visit their website for more of their award-winning factual content.
Watch more episodes of Perspectives on the Pandemic here:
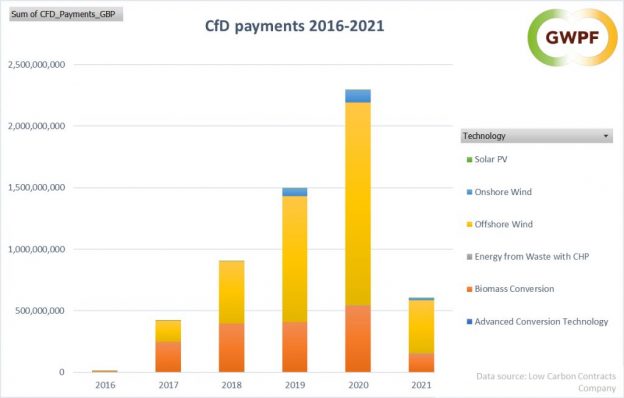
GWPF research has shown that just six offshore windfarms are now sharing £1.6 billion pounds in subsidies between them every year. Three receive annual subsidies of over a quarter of a billion pounds each year. On a single day in April last year, Hornsea 1 received a subsidy payment of nearly £1.5 million pounds.
The level of subsidy is sufficient to cover the construction cost of these windfarms in just six or seven years, meaning that future payments will represent almost pure profit for the operators.
The cost of the Contracts for Difference regime is accelerating, and rose by £0.7 billion last year alone, reaching £2.3 billion in 2020. Consumers are already paying out £6 billion under the Renewables Obligation and another £1 billion under the Capacity Market.
Direct subsidies therefore amount to an annual payment from each household of £350, a sum that is rising by at least £25 per year.
There are further bills to pay too, because windfarms are causing destabilisation of the electricity grid. The cost of the Balancing Mechanism, which deals with grid imbalances, is rising rapidly, costing each household £65 per year, a figure that is rising at a rate of £20 per year.
And the consumer is having to pay for upgrades to the electricity grid too.
Lord Lawson, GWPF director, said:
We are in the middle of an economic crisis and consumers are hit with astronomical costs for unreliable wind energy. These multi-billion subsidies are not only a massive transfer of wealth from the poor to the rich, but are damaging the UK economy as a whole. This madness has to stop.”
Dr Benny Peiser said:
The level of handouts is an obscenity. Every time a new windfarm comes on stream, the consumer is hit with a double whammy – a relentless increase in annual subsidy payments to windfarm operators and an annual bill for fixing the damage that is done to grid stability. This can’t be kept hidden for much longer. The chickens are coming home to roost very soon, and there will be a big political price to pay”.
A few days ago, Vimeo deleted our Documentary Feature “trustWHO”, directed by Lilian Franck, from their platform, stating that they do not support “Videos that depict or encourage self-harm, falsely claim that mass tragedies are hoaxes, or perpetuate false or misleading claims about vaccine safety.” This claim about our documentary is both misleading and false. “trustWHO” has been thoroughly researched for 7 years; it has been fact-checked and approved by lawyers, experts in the medical field and even by key executives of the WHO itself. The documentary simply investigates how efficiency and transparency of the World Health Organization are undermined by both corporate influences and a lack of public funding. It is a journalistic investigation based on facts – and far from what Vimeo makes it out to be.
This is our full statement on the matter, presented by Robert Cibis (Filmmaker, Co-author and producer of “trustWHO”).
Watch this brief statement and selected excerpts from the film:
When the United States government’s Food and Drug Administration earlier this week called for temporarily halting the giving of Johnson & Johnson’s experimental coronavirus vaccine shots because of the developing of blood clots in people who have received the shots, I asked if we were seeing an example of regulatory favoritism for the new mRNA technology shots over more traditional vaccine shots such as the Johnson & Johnson shots. The question arises because the US government is still encouraging everyone to take experimental mRNA “vaccines” from Moderna and Pfizer-BioNTech regarding which there are also many reports of injury and death.
While a variety or injuries and deaths have been reported after people have taken experimental coronavirus vaccine shots developed respectively by the three companies, if you focus in on just blood clot problems, those problems appear to arise after Moderna and Pfizer-BioNTech experimental coronavirus shots as well as after Johnson & Johnson shots.
Megan Redshaw wrote Friday at the Children’s Health Defense website regarding adverse events reported to the Vaccine Adverse Event Reporting System (VAERS) related to the blood clots in people who had taken any one of the three companies’ experimental vaccines:
Children’s Health Defense queried the VAERS data for a series of adverse events associated with the formation of clotting disorders and other related conditions. VAERS yielded a total of 795 reports for all three vaccines from Dec. 14, 2020, through April 8.Of the 795 cases reported, there were 400 reports attributed to Pfizer, 337 reports with Moderna and 56 reports with J&J — far more than the eight J&J cases under investigation, including the two additional cases added Wednesday.
As The Defender reported today, although the J&J and AstraZeneca COVID vaccines have been under the microscope for their potential to cause blood clots, mounting evidence suggests the Pfizer and Moderna vaccines also cause clots and related blood disorders. U.S. regulatory officials were alerted to the problem as far back as December 2020.
So why the different treatment for the Moderna and Pfizer-BioNTech shots?
BLM New York wants an investigation into ‘trained Marxist’ Black Lives Matter co-founder Patrisse Cullors buying four new homes, but given the movement’s history of hypocrisy and grift, why is anyone even remotely surprised?
It would be nice to have a pleasant surprise when it comes to politics. Maybe have some good news to share, but sadly today is not that day. Though I imagine there are members of Black Lives Matter who are having a worse day than I am. Especially given the revelation that their co-founder spent $3.2 million on real estate, and the head of their New York branch is calling for an investigation following her home purchases.
Now, while I’m certainly no fan of BLM’s Marxist messaging, I can sympathize that it must be upsetting to learn that there is a monumental grifter within the movement. But, on the other hand, shouldn’t Black Lives Matter have a much better grasp of when there are grifters within their movement? Especially considering their history?
Take Shaun King, for example. Since he began within the movement, there have been many questions raised about the money that he is raising for families and other such causes. Goldie Taylor of the Daily Beast wrote an article about these issues all the way back in 2015. Questions were also raised by Wesley Lowery of the Washington Post about money raised for Tamir Rice’s family. As events unfolded, there were often stories cropping up that the difficulties were caused by incompetence on King’s part. Then there was the failed launch of the North Star, where an attempt to relaunch Frederick Douglass’ abolitionist newspaper as a media network fell flat on its face. On top of all of this, King actually being a black man has been called into question by his birth certificate and prior police reports.
Another figure to look at would be DeRay Mckesson. To his credit, Mckesson has largely kept to protesting and activism. However, he did attempt to use his position within Black Lives Matter to get into an actual elected position when he tried to run for mayor of Baltimore in 2016. His attempt was an utter failure. He only finished with 3,445 votes, placing 6th in the Democratic primary.
It goes without saying that whenever a movement like Black Lives Matter comes up, there will be people who don’t look at it like any sort of movement for actual change. If you expect there to be true believers, you can bet your bottom dollar that there will be people who don’t really care, or only care to a certain degree. So when you hear about Patrisse Cullors spending all of that money on real estate, it’s rather obvious where their true motivations lie. The self-described “trained Marxist” certainly saw the light of capitalism once she realized she could have a lot more zeros in her bank account.
If time has taught America anything, it’s that the self-sacrificing leaders of civil rights movements simply don’t exist anymore. All that people see is outrage, and opportunity to make some dough. In the case of Black Lives Matter, it’s no different. If there is one irony to all of this, it’s that the co-founder of the movement decided to invest in real estate. You know, the thing that Donald Trump got rich on.
Micah Curtis is a game and tech journalist from the US. Aside from writing for RT, he hosts the podcast Micah and The Hatman, and is an independent comic book writer.
By F. William Engdahl – New Eastern Outlook – 11.04.2022
Amid the ongoing global inflation crisis, NATO heads of state and mainstream media repeat a mantra that high energy prices are a direct result of Putin’s actions in Ukraine since end of February. The reality is that it is the western sanctions that are responsible. Those sanctions including cutting SWIFT interbank access for key Russian banks and some of the most severe sanctions ever imposed, are hardly having an impact on the military actions in Ukraine. What many overlook is the fact that they are increasingly impacting the economies of the West, especially the EU and USA. A closer look at the state of the global supply of diesel fuel is alarming. But Western sanctions planners at the US Treasury and the EU know fully well what they are doing. And it bodes ill for the world economy.
While most of us rarely think about diesel fuel as anything other than a pollutant, in fact it is essential to the entire world economy in a way few energy sources are. The director general of Fuels Europe, part of the European Petroleum Refiners Association, stated recently, “… there is a clear link between diesel and GDP, because almost everything that goes into and out of a factory goes using diesel.” … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.