The MSM’s cancer ‘cure’ stories are bio-firm hype, not hope
By Guy Hatchard | TCW Defending Freedom | October 26, 2022
GLOBALISED mainstream media equates not just with a uniform, poorly-informed world, but a manipulated world.
In Britain, the Times runs a story entitled: After centuries of cut, burn and poison, could a jab cure cancer? by Tom Whipple. Eleven thousand miles away in New Zealand, the same story appears in Stuff newspaper.
This is one of those ‘isn’t it wonderful?’ reassuring stories that unfortunately don’t look quite so rosy after close scrutiny, but like bad pennies are turning up everywhere. On the surface informative and exciting, underneath sadly lacking in that investigative depth we were expecting – and certainly over-hyped.
This particular story would not be out of place in a glossy brochure seeking investment funds for BioNTech. According to the Times article, RNA vaccine technology is rather like buying a piece of furniture from Ikea. Each person could very soon have their own personalised cancer vaccine off the shelf. What could possibly go wrong?
The tremendously hopeful note that the story strikes is based on a lot of over-simplified theory and the success (???) of the Pfizer Covid vaccine co-developed with BioNTech. It sounds reassuringly easy to design mRNA vaccines that rush to your aid and eliminate those nasty cancer cells.
Ugur Sahin and Ozlem Tureci, founders of BioNTech, are pictured in white coats, and are quoted promising: ‘We stimulate the immune system, do something magic, and the tumour disappears.’
Heady stuff, but the cited evidence is less than thin. A decorated cancer researcher who was diagnosed with pancreatic cancer in 2007, then tried all his innovative ideas out on himself, and died in 2011. In 2020, 16 patients with pancreatic cancer were treated by BioNTech. Eighteen months later, eight have died and eight are cancer-free after 18 months. The details are sadly lacking.
What stage were they at and how does that compare with their expected prognosis? The missing piece of the jigsaw is the article’s lack of scrutiny of the safety of BioNTech’s only commercialised mRNA vaccine product – the Pfizer Covid vaccine.
If you want to ask questions and also seek answers, you will need to turn to a completely different kind of journalism. Igor Chudov is a mathematician – like the Times author – but he writes on Substack and is therefore not constrained by any editorial policy or any no-go areas dictated by the newspaper owners, their advertisers, or subtly imposed government guidelines.
Chudov has published a very different cancer story, headlined: Cancer rates are Increasing and may get much worse. Wiped out immune systems take time to manifest.
According to the article, we are seeing the first ripple of a coming storm of cancer deaths. Chudov reports the work of the Ethical Skeptic (another Substack researcher) whose analysis of figures from the Centers for Disease Control and Prevention – the public health agency of the US – has shown that the rate of US cancer deaths accelerated in 2021 and 2022, coinciding with the rollout of the Pfizer/BioNTech mRNA Covid vaccine and other biotech vaccines.
It is the effect size that is surprising – 9 sigma. What does this mean? Well perhaps you can remember from your school maths lessons that for a Bell curve, two-thirds of data points lie within one standard deviation of the mean, that is known as 1 sigma. Ninety-five per cent lie within two standard deviations (2 sigma) and 99.7 per cent lie within 3 sigma.
I’m going to translate for you what the observed 9 sigma deviation from the prior pattern of cancer deaths probably implies in very simple layman terms:
1. A hugely statistically surprising number of people already infected with cancer have suffered a rapid progression of their condition to death. Covid vaccination reduced their likely longevity.
2. Some people who previously had no evidence of cancer, and possibly no lifetime expectation of cancer, are becoming ill and dying in the weeks and months following Covid vaccination. And it is not due to Covid infection – it didn’t happen in 2020.
Read Chudov’s article. It is a long read, but well worth the effort. In addition to the US data, he looks at the official UK cancer mortality data, which shows a similar increase. He also quotes another Substack author, A Midwestern Doctor, who analyses and references in detail what it is about mRNA vaccines that causes cancer. The approach is investigative, as we should expect it.
There are concerning issues that Whipple, author of the fawning Times article, chooses not to address. He failed to discuss questions that constitute the normal substance of scientific debate, but his piece was beamed around the world.
We expect the Times to ask questions, but it is not doing so. It has quietly rolled over and followed the biotech PR line. It is not alone – the mainstream media are collectively failing the sniff test.
We are being manipulated. If you want real journalism, it is flourishing elsewhere. GLOBE (the Campaign for Global Legislation Outlawing Biotechnology Experimentation) and other independents are asking vital questions that few are prepared to countenance.
Biden’s Bivalent Booster Blunder
Vinay Prasad’s Observations and Thoughts | October 26, 2022
The Biden administration has made a fool of themselves with their bivalent vaccine roll out. Pretty much all decisions were errors, and very likely these will hurt them politically. The only way for Biden to save himself from his terrible Covid policy is to fire all his advisors and rehire good ones. Let’s review the facts:
The Biden administration granted emergency use authorization to Pfizer and Moderna for a bivalent booster that targeted Wuhan and BA45. That vaccine received EUA based on mouse data (8-10 mice). There were no human data at the time of approval. (Please don’t confuse the BA4/5 with BA1 bivalent)
Since then, both companies have press released results, but do not specificify the numeric values of antibodies generated in people. No one has clinical data– i.e. is there a reduction in hospitalization? Severe disease? And if so, we don’t know which people (how old) have a further reduction in severe disease or hospitalization from this vaccine.
We also know breakthrough can occur. Rochelle Walensky herself received the vaccine and then had COVID one month later. Ironically, this is probably the peak vaccine efficacy (peak Ab). I don’t know what the vaccine effectiveness is, and neither does she, but my guess is it isn’t terrific.
The Biden administration said that we didn’t have time to wait for clinical trials in people. But each passing day reveals that is a lie. The uptake of this vaccine is abysmal. No one wants it. If no one was going to get it then why not take the time to run the proper studies?
A recent pre-print has shown that the bivalent booster is not better at generating BA45 antibodies than getting the old booster one more time. This is the failure of not generating human trial data.
You could have sorted this out pre-market. *Let’s be clear, these are not clinical data (living longer/better) but without better antibodies, clinical endpoints seem unlikely to be met*

Many universities are now requiring this vaccine for 20-year-old college students who have had three prior doses and Omicron. I think you have to be dropped on your head to actually believe a 20-year-old man in good health who’s gotten three doses and just had Omicron will derive any benefit from this bivalent booster. I have never met even one doctor who thinks that that is true. And yet that is the position of the Biden administration.
They are so hellbent on earning Pfizer money– I mean vaccinating people who just had covid —that they are willing to ignore the mountain of data that suggests that’s not what you should be spending your energy on.
More than a year ago, Marion Gruber and Philip Krause the number one and number two at the US FDA vaccine branch resigned, citing White House pressure to approve boosters for all ages. Their published remarks suggest that they wanted to do it only for the elderly and vulnerable. Their message was repeatedly ignored as the Biden administration rammed booster after booster through the US food and drug administration for ultra low risk populations.
They have actually said a 5-year-old who has had three doses and had covid should get this booster. It’s insane.
Their entire vaccine policy seems to be interested in giving Pfizer and Moderna a perpetual market share for a yearly vaccine. But seems to have no interest in generating credible randomized control trial evidence to inform the public. As such, they fail the American people.
I am concerned that after this White House stint: Ashish Jha, Rochelle Walensky, Vivek Murthy, and Peter Marks (post FDA) will work for or consult for Pfizer and Moderna. That would be devastating.
American people obviously do not want to receive a vaccine every year with non-trivial adverse events without knowing that it gives them some benefit. Benefit to third parties cannot be had because it cannot stop transmission.
Some misguided policy makers argue that even a small reduction in transmission is meaningful. That’s nonsense. The problem is that you can get COVID every single day of your life from now until the end of your life. Even changing the probability modestly won’t change the outcome. Because the probability you will get COVID is one over time. Think of it this way:
You can play Russian roulette with one bullet or three bullets. I would much rather play with one bullet, if I had to. But if you have to play a thousand times in a row, we all know how that game ends.
That’s COVID 19. It’s not going anywhere. You’re going to have to play over and over and over again. And that means you’re all going to get COVID. So the only question is how many doses minimize severe disease? And who needs that to be minimized?
Today in the governor’s debate of New York state, only the Republican candidate was opposed to children’s mandates. It’s amazing that the Democrats are clinging to a failed vaccine policy. Their covid-19 policy is going to lead to catastrophic losses.
They need to fire all their advisors and start new. That’s the only way to fix the situation.
‘Criminal Neglect’: CDC Knew COVID Vaccine Could Cause Myocarditis in Young Males Months Before Telling the Public
By Suzanne Burdick, Ph.D. | The Defender | October 25, 2022
Two months after COVID-19 vaccines were rolled out to the U.S. public, a statistically significant vaccine safety signal for myocarditis in males ages 8 to 21 appeared in the Centers for Disease Control’s (CDC) Vaccine Adverse Event Reporting System (VAERS) — but CDC officials waited another three months before alerting the public, according to a new study.
The study, “Delayed Vigilance: A Comment on Myocarditis in Association with the COVID-19 Injections,” by Karl Jablonowski, Ph.D., and Brian Hooker, Ph.D., P.E., was published on Oct. 17 in the International Journal of Vaccine Theory, Practice, and Research.
In an interview with The Defender, Hooker, chief scientific officer for Children’s Health Defense, said:
“This important paper shows that a strong, statistically significant vaccine adverse event ‘signal’ for myocarditis in males 8 to 21 years of age was seen on the VAERS database as early as Feb. 19, 2021, just two months after the release of the COVID-19 vaccine to the U.S. public.
“Instead of sounding the alarm regarding this signal, CDC officials buried the connection between COVID-19 vaccination and myocarditis until May 27, 2021. By this date, over 50% of the eligible U.S. population had received at least one mRNA COVID-19 vaccine.
“Withholding this type of information is criminal.”
According to researchers at the National Organization for Rare Disorders, myocarditis can result from infections or may result directly from a toxic effect such as a toxin or a virus. “More commonly the myocarditis is a result of the body’s immune reaction to the initial heart damage,” researchers said.
Severe myocarditis can permanently damage the heart muscle, possibly causing heart failure.
In their study, Jablonowski and Hooker recorded and analyzed the increasing incidence of myocarditis as it progressively became a statistically significant “signal” in VAERS, the primary government-funded system for reporting adverse vaccine reactions in the U.S.
“It [myocarditis] became a discernible measure of harm over time, and here we show when it became statistically significant in the week of February 19, 2021,” the authors explained.
Only two months later, the VAERS data from the week of April 23, 2021, showed that the discerned level of myocarditis in young men following COVID-19 vaccination had increased to an extreme statistical level.
Generally, p-values less than .05 are considered to be statistically significant — meaning the observed result cannot reasonably be attributed to chance — and p-values less than .01 are considered to be very statistically significant.
By the week of April 23, 2021, Jablonowski and Hooker saw a p-value of less than 0.0001 (p<0.0001).
“At that p-level, a contrast as great as the one observed in the VAERS data would be expected to occur fewer than one time in 10,000 similar experimental drug trials,” they said.
“That statistic was obtained when 43.78% of the U.S. population had received at least one [COVID-19] injection — 31.20% had received all of those injections available to them or pressed upon them, and 12.58% had received one or more of the COVID-19 injections but not all of them.”
Despite this safety signal, the U.S. Food and Drug Administration on May 10, 2021, expanded the Emergency Use Authorization of the Pfizer-BioNTech COVID-19 Vaccine to individuals as young as 12 years old, and the CDC’s Advisory Committee on Immunization Practices voted to recommend that all that persons age 12 or older get the vaccine.
Around the same time, the CDC’s V-safe post-vaccination data collection tool began accepting entries from adolescents ages 12-15 years. A few weeks later, the CDC finally acknowledged publicly that there may be an association between mRNA COVID-19 vaccination and myocarditis.
“On May 27, 2021, the CDC published on their website ‘Myocarditis and Pericarditis following mRNA COVID-19 Vaccination,’ (an announcement that is no longer available at the time of this writing; however, see Das et al., 2021),” the authors said.
“However, the important point we want to underscore here is that the general public was apparently coming to the realization of the particular life-threatening dangers of myocarditis at a time after 50.56% of the U.S. population had already received one or more up to the limit of all available COVID-19 injections — 42.25% had received the complete series of shots and 8.31% had received some but not all of them.”
“Why the irreversible delay in vigilance?” they asked.
The CDC’s choice — “whether by intention or neglect of the unfolding evidence” — to not warn the U.S. public of possible widespread harm from the mRNA COVID-19 until May 27, 2021, “when 50.56% of the U.S. population had already been injected, some of them multiple times” could be characterized as “criminal neglect.”
Jablonowski and Hooker concluded:
“From February 19, 2021, the signal in VAERS data was already loud and clear after only 14.23% of the U.S. population had been administered at least one of the injections. Subtracting that group from the 50.56% who had taken the risks associated with the shots by May 27, left 36.33% of the U.S. population (or roughly 120 million people) in the dark about the known adverse outcomes, including the irreversible damage of myocarditis, associated with the COVID-19 injections.”
VAERS data show 24,371 reports of myocarditis and pericarditis between Dec. 14, 2020, and Oct. 14, 2022. Of those cases, 1,333 reports occurred among 12- to 17-year-olds, 47 reports occurred among 5- to 11-year-olds and 5 reports occurred among 6-month-olds to 5-year-olds.
The CDC uses a narrowed case definition of “myocarditis” that excludes cases of cardiac arrest, ischemic strokes and deaths due to heart problems that occur before one has the chance to go to the emergency department.
While reports submitted to VAERS require further investigation before a causal relationship can be confirmed, the system has been shown to report only 1% of actual vaccine adverse events.
Suzanne Burdick, Ph.D., is a reporter and researcher for The Defender based in Fairfield, Iowa. She holds a Ph.D. in Communication Studies from the University of Texas at Austin (2021), and a master’s degree in communication and leadership from Gonzaga University (2015). Her scholarship has been published in Health Communication.
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Pfizer will Charge Two Billion Dollars per Pound of Covid mRNA Nanoparticles
This is a 12,370% Markup
By Igor Chudov | October 23, 2022
We all know that Pfizer likes to “move at the speed of science”.
Nowhere is the “speed of science” more pronounced, than in raising prices for its products. Pfizer used to charge its only customer in the United States — the Federal Government – $19.50 per dose.
Now Pfizer decided to diversify and sell its Covid vaccine through health insurance companies. It plans to charge $130 per dose. Mind you, each dose costs $1.18 to produce.
The business plan here, of course, is to keep as many vaccine mandates as possible and have health insurers cover the cost of increasingly frequent vaccinations, child vaccinations etc.
For example, right now the CDC recommends getting the bivalent booster two months after a previous booster.
People ages 12 years and older: A 2-dose primary series and 1 bivalent mRNA booster dose (Moderna or Pfizer-BioNTech) is recommended. The primary series doses are separated by 3–8 weeks and the bivalent mRNA booster dose is administered at least 2 months after completion of the primary series (for people who have not received any booster doses), or at least 2 months after the last monovalent booster dose.
If you think that two months is too frequent, consider that CDC’s Rochelle Walensky was bivalent-boosted only a MONTH ago, and is now suffering from Covid — the same variant she was boosted for. Ms. Walensky is, of course, vaxxed to the max and is thankful for all the shots she received:

The Price
Most of each dose of Pfizer’s “Covid vaccine” is cheap stuff like water, polyethylene glycol, and other chemicals. The actual active ingredient is the mRNA nanoparticles, and those are given at 30 micrograms per dose.
Do the math:
Price Per gram = 130/.000030 = $4,333,333
So Pfizer is selling us their gene juice for over $4,333,333 per gram.
A pound (454 grams) of Pfizer’s mRNA nanoparticles would cost TWO BILLION DOLLARS.
The cost of making that two-billion-dollar pound of mRNA juice is under one percent of the price.
A pretty good deal for Pfizer, right?
Thank God I have a free immune system!
Not enough people vaccinated – Biden
Samizdat | October 25, 2022
US President Joe Biden received his fifth Covid-19 vaccine dose on Tuesday, and urged Americans to do the same. While the president is pushing for a yearly vaccine schedule, less than 10% of the eligible population has gotten the latest omicron-specific shot.
“Get vaccinated,” Biden said at a White House event. “It’s incredibly effective, but the truth is, not enough people are getting it. We’ve got to change that so we all can have a safe and healthy holiday season.”
Biden, who caught a recurring case of Covid-19 earlier this summer despite having received a total of four vaccine doses at the time, then rolled up his sleeve and received his fifth dose – this time of Pfizer’s omicron-specific bivalent booster – on camera.
The president said that the coronavirus vaccine is “just like the flu shot,” and added that “for most Americans, one Covid shot each year will be all that they need.”
However, uptake for the latest round of booster shots has been slow. Fewer than 20 million people have taken the updated formulation, or just 8.5% of the eligible population, according to data from the Centers for Disease Control and Prevention (CDC).
Meanwhile, the state of Florida has recommended against mRNA booster shots for children under 18 and males under 39, citing the low risk posed by Covid-19 to children and the elevated risk of cardiac arrest in young vaccinated men. Several European countries have issued similar recommendations in recent months, but the CDC still recommends that children as young as five receive bivalent boosters, and has recommended that Covid-19 vaccines be added to children’s routine immunization schedules.
Throughout the Covid-19 pandemic, Biden combined an intense public messaging campaign with legal mandates for federal workers and contractors in a bid to up the US’ vaccination rate. While some municipalities also drafted their own mandates, legal challenges followed. In New York City on Tuesday, the Staten Island Supreme Court ordered the city to lift its mandate and rehire all employees fired for non-compliance with full back pay.
COVID19 vaccination
DR. MALCOLM KENDRICK | OCTOBER 25, 2022
I have been somewhat quiet recently. I have started about ten blogs, then got bogged down …. possibly blogged down? Then stopped, and started again, then tore it all up – metaphorically.
The problem is that I have been looking at COVID19 vaccination.
There is much to say, maybe too much. However, one treads a very fine line here. I liken it to walking along a cliffside, in the dark. At any point you can make a small mis-step and plummet to your doom. Or, perhaps it is more like being in the trenches in World War I, knowing that at any point, a sniper could pick you off.
Yes, it is true that WordPress doesn’t seem to care much what anyone writes. Good for them, I say. So, I can write pretty much whatever I want. But the rest of the world watches, waiting for the slightest mistake. At which point you shall be denounced, then silenced, in all other outlets. If this happens, the vast majority of people stop listening to you. ‘Oh him, he’s one of those anti-vaxx nutters. Don’t listen to a word he says.’
Yes, I know there is a large community out there who do not follow the mainstream narrative. Those who know there are – or certainly may be – some significant issues with the COVID19 vaccines. In particular the mRNA vaccines. Speaking to them is easy, gaining their support is easy. They cheer you on.
However, there is no real point in reaching out to them, enjoyable though it may be. It is preaching to the converted. The people that I would really like to get at are those who firmly and absolutely believe that mRNA vaccines are highly effective, absolutely safe, and that everyone should be happy to be vaccinated. Along with their children.
The people who are also very critical of those who do not get vaccinated [I have had three doses, but I shall not be having a fourth, unless things change dramatically].
How do you reach these people? How can you even begin to get them listening to anything you have to say?
To give one example of the problem of starting a discussion. I posted a link in a discussion forum on the Doctors.net website (a website that can only be accessed by UK registered doctors). This link discussed some issues with vaccines. It didn’t seem, to me, to be hyper-critical.
However, I got a message from the moderators informing me that if I attached links to any information critical of vaccines, again, they would remove me from the site. This was my final warning. No discussion.
More recently, the post below was published on the same site. It was in response to a twitter comment which followed an interview with Dr Aseem Malhotra:
‘This is a disgraceful interview with this self-publicising charlatan and hypocrite. He says that “until proven otherwise, it is likely that Covid mRNA vaccines played a significant or primary role in all unexplained heart attacks, strokes, cardiac arrhythmias, & heart failure since 2021”.
That is so grossly irresponsible and untrue It staggers me to think he can be allowed to say this and remain a registered medical practitioner.’
The post I have duplicated here was published by a doctor who works, full-time, for a pharmaceutical company. Something he, surprisingly, failed to mention as a potential conflict of interest. Others piled on in support of him. Many of them agreeing that Aseem Malhotra should be flung off the GMC register forthwith – which would render him unable to work as a doctor.
I suggested that, perhaps it would be better to engage Dr Malhotra in debate, rather than attacking him as a charlatan. At which point I was attacked. In my opinion, if you find yourself being attacked for suggesting that it would be a good idea to have a debate, it is not difficult to work out which way the wind is blowing.
I have discussed vaccination at my local sports club. At which point, almost everyone takes on that silent, arms crossed look, if you mention you have some concerns about vaccines.
They don’t debate the issue, because they can’t, because they don’t know anything other than what they have been told by mainstream media. But it is clear that some of them now see me as a bloody anti-vaxxer. Even if I say nothing more than, ‘I have some concerns.’
Yes, to ask for debate, or to dare express some concerns, is to be labelled an anti-vaxxer.
This is a very high barrier to overcome. I have tried irony. ‘Oh yes, I am absolutely one hundred per cent in favour of COVID19 vaccines. I think everyone should have them four times a year. Pregnant women, children from the moment they are born. No exceptions at all. Yes, these mRNA vaccines have been fully tested. It is clear that they are one hundred per cent safe and one hundred per cent effective. Yup, I cannot see any problems with them at all.’
Response. You are taking the mickey and you are an anti-vaxxer. I claim my prize.
I have also tried saying absolutely nothing at all. I still got accused of being an anti-vaxxer because I did not enthusiasticly agree with criticising someone who was believed to be an anti-vaxxer.
Maybe I should just attend this meeting ‘The New Frontier of RNA Nanotherapeutic. Monday, October 24, 2022 8:30 a.m. – 5 p.m. Hybrid Conference’:
‘The RNA vaccines against COVID-19 mark the beginning of a technological revolution that will transform the way we treat disease and restore health. “The New Frontier of RNA Nanotherapeutics” presented by the George and Angelina Kostas Research Center for Cardiovascular Nanomedicine, will feature a discussion on the events that led to the RNA vaccine breakthrough and preview emerging RNA Nanotherapeutics. Advances in the design of RNA constructs to improve stability and translational efficiency will be presented along with the leading-edge developments in nanomedicine to improve delivery and tissue specificity. The potential of nanotechnology-enabled RNA therapeutics to enhance health is virtually limitless.’
Any doubts I have will evaporate …. maybe.
Anyway. The answer as to … how can I even start a discussion on mRNA vaccines without being shot, falling of the edge of cliff, or being silenced, continues to elude me. Farewell enlightenment. Hello dark ages.
Science, to me, is debate. Science is attacking ideas from all directions. No exceptions. Those ideas which cannot be destroyed may turn out to be correct. But, if an idea is considered sacrosanct, with anyone questioning it condemned as an unbeliever, then we do not have science. We have religion. So yes, in my opinion, vaccines, and vaccination, have become a religious belief. No evidence needed.
Scary. Anyway. If anyone has any good ideas about how a debate can even get started, without descending into anger and accusation … please let me know. It seems beyond me. The end.
Potsdam Climate Institute Scientists Criticized: “Scouring For Most Alarmist Stories”
By Die kalte Sonne | October 22, 2022
Björn Stevens is the director of the Max Planck Institute (MPI) for Meteorology in Hamburg and an expert on clouds. In the Zeit (behind paywall), Stevens expresses criticism of colleagues, primarily at the Potsdam Institute for Climate Impact Research PIK. The Oldenburger Online Zeitung has taken up the interview and quotes indirectly from it.
Among other things, these had warned of the disappearance of all clouds due to global warming. ‘That’s nonsense,’ Stevens said. The scenario is wrong, he said. ‘It’s based on a paper from our institute taken out of context and on a second paper that has numerous flaws.’
The dramatic behavior of the climate in that simulation is based on a gross simplification of clouds that has nothing to do with reality, he said. You can’t get rid of clouds that easily, said Stevens, whose research group simulates clouds in climate models and on whose expertise in cloud issues the world climate report relies heavily. Why his colleagues claimed otherwise, he said, is a question for them to answer. ‘I can only admire the way colleagues there scour the literature for the most alarmist stories.’”
But the blasphemy goes even further.
‘But the tipping points that my colleague Hans Joachim Schellnhuber and others at PIK emphasize are based on their private, much weaker definition. They reinterpret tipping points to include less abrupt or even reversible climate changes. With this new definition, they find tipping points everywhere. Then it’s permanent alarm.’”
Translation by No Tricks Zone
FLORIDA SURGEON GENERAL ON COVID VAX MANDATE
The Highwire with Del Bigtree | October 20, 2022
Florida Surgeon General, Dr. Joseph Ladapo, minces no words regarding his State’s stance on Covid Vaccine Mandates, after a CDC committee voted unanimously to recommend Covid vaccines for kids older than 6 months.
A Tale of Two Pills: Media bias in reporting Ivermectin and ensitrelvir
By Guy Gin | Making (Covid) Waves in Japan | October 21, 2022
Last month, Japanese pharma company Kowa put out a press release of the results of its 1030-person double-blind randomised control trial (RCT) of Ivermectin conducted at 54 institutions in Japan and 2 in Thailand.
Here’s how the results were reported in The Japan Times.

Not effective, you hear! I mean, look at the photo. You don’t get Ivermectin from a pharmacy; you get it from a farmer. Anyway, on to the trial.
A clinical trial was unable to prove the efficacy of the antiparasitic medicine ivermectin against coronavirus variants, according to Japanese drugmaker Kowa Co., which has indicated that it will no longer seek approval for the drug as a COVID-19 treatment.
So this means that not only has IVM not been widely used in Japan (despite what many people outside Japan think) but probably never will be. So what happened? Did the people who took the anti-vaxers’ favourite veterinary medicine all get sick?
In the trial, 1,030 patients with mild COVID-19 were orally administered the drug daily for three days and then compared to others given a placebo.
Ivermectin was found to be safe and few people given the drug developed severe symptoms, Kowa said. But both the group given the drug and the one administered a placebo saw improvements in symptoms, meaning the trial did not show the drug’s efficacy over the placebo as a COVID-19 treatment.
So the reason Kowa was “unable to prove the efficacy” wasn’t because IVM is “not effective”; it was because almost everyone in the placebo group got better quickly too. According to Kowa’s press release, “Both intervention and placebo arms showed milder symptoms around 4 days after the start of administration” and “There were no deaths and hardly any severe cases.”
Although Kowa hasn’t released the full trial details or results, the 0% mortality rate among the 500+ participants in the placebo arm suggests they were mostly at very low risk of severe disease. So the results don’t show IVM was ineffective; they show no medication was necessary for these participants to prevent symptoms worsening or for them to recover quickly.
This a not a new issue in studies on early treatments. Yale epidemiologist Harvey Risch noted the same thing in RCTs showing non-significant effects for another “controversial” drug, hydroxychloroquine.
The RCT studies proclaimed supposedly as definitively showing no benefit of HCQ use in outpatients have all involved almost entirely low-risk subjects with virtually no hospitalization or mortality events and are uninformative and irrelevant for bearing upon these risks according to HCQ use in high-risk outpatients.
When tested on larger numbers of people for mortality benefit, IVM often performs a bit better.

Next, let’s compare how the JT reported Kowa’s IVM trial press release with how Reuters reported Shionogi’s press release for its 1821-person RCT of its anti-Covid drug ensitrelvir.

Japan’s Shionogi & Co Ltd said on Wednesday its oral treatment for COVID-19 demonstrated a significant reduction in symptoms compared with a placebo in a Phase III trial in Asia.
The drug, a protease inhibitor known as ensitrelvir, met its primary endpoint in a trial conducted among predominantly vaccinated patients with mild to moderate cases of COVID-19, the company said in a statement.
A significant reduction in symptoms! So how many people were kept out of the ICU? Well, the Reuters article didn’t clarify what the main result was, so here it is from Shionogi’s press release.
the median time to resolution of the five COVID-19 symptoms [stuffy or runny nose, sore throat, cough, feeling hot or feverish, and low energy or tiredness] was significantly reduced in those treated with the low dose of ensitrelvir (the dose level submitted for approval in Japan) compared to placebo: 167.9 hours versus 192.2 hours, a statistically significant difference of 24 hours (p=0.04).
Yep, ensitrelvir cleared runny noses 1 day quicker than a placebo. So the media reporting of Shionogi’s results wasn’t dishonest, but it wasn’t exactly candid.
Similar to in Kowa’s IVM trial, no deaths were reported among the 900+ placebo recipients in Shionogi’s trial, which again suggests they were very low risk. So these results give us no idea about whether ensitrelvir will prevent the progression to severe disease in high-risk immunocompromised people, which is what actually matters.
Shionogi also reported that no serious adverse events occurred in the intervention arm. But one problem with not trialing a medication on the type of high-risk people who will actually need it is that the trial probably won’t pick up major safety signals that become clear later.

But as El Gato Malo has said, pharma doesn’t make mistakes in trial design; it makes choices.

Safety Reporting of COVID-19 Vaccine Induced Myocarditis Just Seeing the Tip of the Iceberg
By Dr. Peter McCullough & John Leake | Courageous Discourse | October 18, 2022
In 2021 the US CDC and FDA warned America and the world that the mRNA COVID-19 vaccines could result in heart inflammation or myocarditis.[i] This is a medical problem that has occurred in the past not related to vaccines but at a low rate ~4 per million population per year as reported by Arola, et al, from Finland. In general, ~90% of cases occur in men and ~10% in women.[ii]
The principles of management include stopping all forms of exercise since that can be a driver of the development of heart failure and a trigger for sudden death. In cases where there is a progression to heart failure, cardiac biopsy is commonly performed to establish or rule out a diagnosis of giant cell myocarditis which has a markedly worse prognosis than the other forms (parvovirus, etc).
COVID-19 vaccination has been thrust on the world with such vehemence that there has been a hesitancy among physicians and hospitals to spontaneously report cases to the regulatory agencies. The vast majority of physicians took COVID-19 vaccines themselves and may be having trouble coming to personal grips with the threat of heart damage and other risks of vaccination. In 2021 as spontaneous reports came into agencies that predominately young men were developing myocarditis with COVID-19 vaccination, a pattern emerged: 1) highest risk group was males age 18-24 with a skewed distribution and a long tail that extended to men in their seventies, 2) ~90% of required hospitalization, 3) risk was explosive after the second injection, 4) death directly due to myocarditis was confirmed by autopsy.
In the biological licensing agreement letters to Pfizer and Moderna, the US FDA requested prospective cohort studies of myocarditis which call for measurement of blood tests, ECG, and cardiac imaging before injections and at timepoints afterwards to detect the real rate of heart damage and to ascertain how much of the problem could be asymptomatic and potentially present a future risk of sudden death in an unsuspecting patient. Both companies were not forthcoming, so the answer came from Mansanguan et al, from the Bhumibol Adulyadej Hospital, Bangkok, Thailand.[iii] Adolescents age 13-18 were studied in a prospective cohort manner just after the second injection of the Pfizer vaccine and 7/301 (23,256/million) developed myocarditis using a clinical definition based on blood tests, ECG, and cardiac imaging.
Data from multiple sources suggest the condition can be subclinical in about half, meaning neither the patient nor the parents bring it to clinical attention. Patone et al have recently reported on 100 fatal cases of vaccine-induced myocarditis in the UK, and such papers are expected to continue with larger numbers as the medical community begins to fully recognize cause and effect.[iv] Thus spontaneous reporting to agencies represents the tip of a very large iceberg.
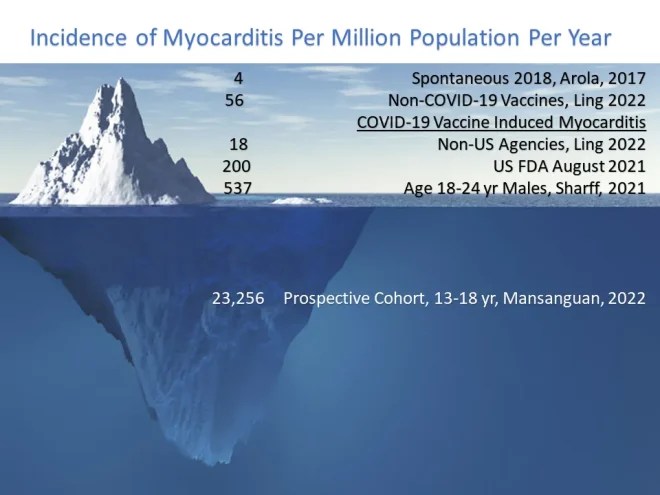
If the estimate Mansanguan study is confirmed or anywhere close to ~25,000/million, that means a million young Americans could have sustained heart damage from COVID-19 vaccination and some of them will be at risk for cardiac arrest and future heart failure. These data suggest we should not be surprised by rising rates of sudden death in young persons with sports and during daily life including sleep.
There can be no more urgent need to halt vaccination and commit a substantial research effort into screening, detection, prognosis, and management of COVID-19 vaccine induced myocarditis. The stakes are high—an entire generation is at risk.
COVID Vaccines and Organ Transplants: Are Healthcare Providers Ignoring Safety Signals?

The Defender | October 24, 2022
Since its experimental beginnings in the mid-1950s, organ transplantation has evolved into what the medical community now casually refers to as a “standard-of-care” procedure, albeit one with still substantial failure rates.
For example, though kidneys top the list of transplanted organs, 14% to 21% of kidney transplants fail within five years, and 15% of kidney transplant candidates are awaiting a repeat procedure.
Recent studies identified a new concern related to the failure of transplanted kidneys and other organs: COVID-19 vaccination.
In one study, published in September in Transplant Infectious Disease, researchers cataloged acute organ rejection within a week or two of COVID-19 vaccination in five individuals who had received kidney, liver or heart transplants six to 18 months earlier.
In August, Japanese researchers reported rejection of corneal grafts in COVID-19 vaccine recipients, occurring from one day to six weeks post-vaccination.
The events caught the Japanese authors’ attention because corneal grafts ordinarily have a high success rate due to the cornea’s status as an organ with immune privilege.
Noting literature that documents transplant rejection in association with other vaccines such as influenza, hepatitis B, tetanus and yellow fever, the Japanese authors expressed worry about what “the projected societal shift towards a more frequent vaccination schedule” portends for transplant recipients.
Concerns about the impact of COVID-19 jabs on people with existing transplants are important, but another pressing-yet-unaddressed question lurks in the shadows: What happens if an unvaccinated person receives a transplanted organ from someone who got one or more COVID-19 jabs?
A record year
Although transplantation experienced a brief lull in the early days of the pandemic, by 2021, the U.S. saw a record-setting number of transplants performed — more than 40,000 kidneys, hearts, livers and other organs.
Although supply is never adequate to meet demand, transplant centers were able to achieve their 2021 milestone in part because of a 10% increase over 2020 in the number of “deceased organ donors” (as opposed to living donors), with 45 of 57 organ procurement organizations setting “all-time records for donors recovered in a single year.”
The surge in organ donation from deceased donors represents a decade-long trend, with “the rising number of deaths of young people due to the ongoing opioid epidemic” hypothesized to be a contributing factor prior to 2021. Still, in prior years, the increase averaged only 5%.
Thrilled with the increased availability of organs, transplant organizations have displayed no curiosity about whether fatalities linked to the rollout of experimental COVID-19 vaccines may be eclipsing or even replacing organs sourced from opioid-related deaths — even though there was a 30% increase (over 2020) in organ donation from individuals who died of cardiorespiratory failure, and a 15% increase in organs from deceased 50- to 64-year-olds.
The COVID-19 vaccine rollout has been linked to 2021’s explosive rise in all-cause mortality in the working-age population, including unprecedented heart-related fatalities in younger adult COVID-19 vaccine recipients.
Traffic fatalities are a key pipeline for organ donation, so transplant centers also benefited from the 16-year high in traffic-related deaths in 2021.
Some observers believe these could be linked to COVID-19-vaccine-related loss of consciousness behind the wheel.
Damaged organs?
According to the United Network for Organ Sharing (UNOS), transplant rejection “is when the organ recipient’s immune system recognizes the donor organ as foreign and attempts to eliminate it.”
Rejection begins as an acute phenomenon but may proceed to the gradual loss of organ function defined as chronic rejection.
UNOS says, “Some degree of rejection occurs with every transplant,” which is why immunosuppressive medications, often for life, are a sine qua non following transplantation.
In August, the independent group of doctors and scientists known as Doctors for COVID Ethics outlined disturbing evidence from autopsies of persons deceased after COVID-19 vaccination about what is happening to the organs of mRNA vaccine recipients — organs potentially being offered to transplant recipients.
They noted that mRNA vaccines “travel throughout the body and accumulate in various organs” where they “induce long-lasting expression of the SARS-CoV-2 spike protein” that in turn induces autoimmune-like inflammation — and the vaccine-induced inflammation “can cause grave organ damage, especially in vessels, sometimes with deadly outcome.”
Citing evidence from Pfizer’s animal experiments, they also underscored the particularly rapid accumulation of mRNA vaccine in the liver, and concluded that blood vessels, at the very least, “will be exposed and affected in every organ and in every tissue.”
Other researchers have highlighted “the possibility of subclinical organ dysfunction in vaccinated recipients.”
No transplant for you
Ironically, transplant programs commonly recommend that would-be organ recipients get “up-to-date” on a slew of vaccines — “typically hepatitis A and B, tetanus [diphtheria, pertussis, tetanus], pneumococcus, measles, human papillomavirus, influenza, and others dependent on geography and age.”
Given the manufacturer-documented potential for vaccines to cause organ-damaging adverse events, this advice was already questionable — but then many transplant centers made matters worse by adding stringent requirements for COVID-19 vaccination.
Even though researchers very quickly established that the immunosuppressive drugs taken by transplant recipients guarantee a “significantly blunt[ed]” COVID-19 vaccine response, prominent healthcare systems like Boston’s Brigham and Women’s Hospital and Colorado’s UCHealth did not hesitate to coldly remove the unvaccinated from their transplant waiting lists.
The American Society of Transplant Surgeons’ COVID-19 Strike Force recommends COVID-19 vaccination not just for all transplant candidates but also for recipients, their family members and live donors.
They virtuously claim that decisions to deny transplants to the unvaccinated are based on a desire to “avoid futile transplants and wasting organs that could benefit other candidates.”
A University of Chicago physician who asserted a “legal right to discriminate against candidates who refuse the COVID-19 vaccine” nevertheless squeamishly labeled the discrimination “too severe,” asking, “one must ask how far the [transplant] community will go” and wondering, “will they mandate multiple boosters”?
Big bucks
Although organ transplantation is shrouded in noble lifesaving verbiage, it is also a major profit center for modern medicine.
Global projections for 2021-2028 suggest the combined organ and tissue transplantation market will double in size, going from $7.24 billion to $14.67 billion — and those figures do not take into account a thriving black market for trafficked organs.
Market analysts expect the growth to be fueled both by demand factors — such as the growing incidence of chronic diseases that cause “catastrophic damage to tissue and organs” — and increased supply — including a rise in celebrity-driven organ donation pledges.
Because access to organs remains the key barrier to transplantation, there has also been a push in recent years to allow donation from “suboptimal” or “extended criteria” donors — for example, the elderly, individuals with fatty liver disease, donors with malignancies or viral hepatitis or donations “after cardiac death.”
Will COVID-19-vaccine-contaminated organs become just another category of “suboptimal” donation?
Recent studies of COVID-19 vaccine recipients’ blood suggest that worries about a contaminated blood supply likely also extend to the organ supply and could place transplant recipients’ lives at risk.
Unfortunately, when problems arise, they will probably be chalked up to ordinary transplant rejection, with no one the wiser about the insidious role of newfangled COVID-19 or future mRNA vaccines.
This article was originally published by The Defender — Children’s Health Defense’s News & Views Website under Creative Commons license CC BY-NC-ND 4.0. Please consider subscribing to The Defender or donating to Children’s Health Defense.
Featured Video

Thomas Fazi: NATO’s Hybrid Warfare – Deception & Permanent War
or go to
Aletho News Archives – Video-Images
Book Review
The Zeolite Book — First Edition, 2026, Paperback
The volcanic mineral medicine will not patent — for the toxic burden medicine will not name
Lies are Unbekoming – October 30, 2026
 Zeolite is old. It is in Roman concrete that has held for two thousand years. It’s in the water filters of ancient cisterns. It’s in the stomachs of Pacific livestock whose keepers knew, somehow, that this grey crumbling rock made the animals healthier. It’s in Soviet clinical protocols from the 1960s. It’s in the standard emergency response to the Chernobyl explosion.
In 1986, after the Chernobyl reactor failure, the Soviet Union manufactured and distributed natural zeolite at industrial scale — for soil remediation, for livestock feed, for human consumption, for the cleanup itself. Karl Hecht, who had been director of the Institute for Experimental and Clinical Pathophysiology at the Charité of Humboldt University Berlin, spent the six decades after that building the clinical research base — on silicon’s role in human health, on zeolite’s clinical safety, on its applications in ageing. In 2018, Pavelić and colleagues published a comprehensive clinical safety review of natural clinoptilolite in Frontiers in Pharmacology. In 2019, Mastinu analysed its binding affinities. In the Western medical literature, these works sit largely uncited.
What has not been treated at book length, until now, is how a volcanic mineral with six decades of Soviet clinical work behind it, two major peer-reviewed Western reviews, and ongoing clinical use across the former Eastern Bloc, remains almost entirely absent from Western medical practice — and what the toxic burden it’s meant to address actually is.
The Zeolite Book gathers the Soviet clinical record, the Western peer-reviewed studies, three contemporary practitioner voices, and three serious counterviews into one honest treatment. That’s why the book runs to seven appendices. 288 pages, four parts, three practitioner voices, three counterviews, seven appendices. The honest treatment is the argument.
Blog Roll
 Aletho News
- UAE security forces tortured, killed journalist for opposing Israel normalization: Report
- They Compared the Spice to the Drug. The Spice Won — Again. (Part 2)
- Thomas Fazi: NATO’s Hybrid Warfare – Deception & Permanent War
- Wrong, AP and NPR: Europe’s 50,000 Heat Deaths Are a Computer-Model Estimate, Not a Real Body Count
- Questioning Your Doctor Is Now Considered A Psychological Problem (Seriously)
- London tourism expo promotes Israeli agency linked to theft of Palestinian land
- Dockworkers launch global strike against Israeli and US military shipments
- Europe facing gas price shock – Gazprom chief
- Ukraine continues recruiting people with disabilities
- Weaponized Journalism: 2021 Sayer Ji Interview with NPR
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!

