German Supreme Court rules mandatory vaccination is constitutionally justified
The Naked Emperor’s Newsletter | May 19, 2022
Judges in Germany’s top court clearly haven’t looked at the data produced in multiple countries, showing the vaccinated being more likely to catch coronavirus.
In a press release today, the court announced that a case, challenging the obligation to provide evidence of vaccination, had been unsuccessful. The complainants said that the mandates violated their fundamental rights.
Whilst the initial vaccine mandate for all adults was rejected earlier in the year, it was still implemented for healthcare workers in March. This meant that all healthcare workers had to provide proof of full vaccination, recovery from COVID-19 or a small number of medical exemptions. If employees did not provide proof, the health department was to be notified immediately and the individual banned from entering the workplace.
One of the reasons for the case being unsuccessful, given in the judgment, was that interference with the right to physical integrity is constitutionally justified. Basically, the protection of vulnerable people is more important than an individual’s fundamental right.
The judgement admits that COVID-19 is mild for most people but can be fatal for the elderly and vulnerable who also don’t respond well to vaccination. They say that at the time the law was passed, a clear scientific majority assumed that vaccinated and recovered people were less likely to become infected and therefore transmit the virus. It was also assumed that vaccinated people were less infectious and for a shorter amount of time. According to the judgement, expert third parties largely agree that vaccine effectiveness will continue to exist, albeit at a reduced level.
Comically, the judgement states that there is no justification for compulsory vaccination enforced by the state but instead the decision should be down to the individual – they can choose to either give up their previous job or consent to the impairment of their physical integrity. Why thank you, Master, for providing me with two terrible choices. But, every cloud and all that, I suppose it is better than being pinned down and vaccinated. Well, until you can’t pay your rent or buy food for your children and have to steal a cardboard box to sleep on in the street.
Fortunately, the judges concluded that it is ok to breach an individual’s fundamental rights because serious side effects or serious consequences induced by the administration of the vaccine are very rare. And, in any case, they are continuously monitoring and evaluating them. They say that the very low probability of serious consequences of vaccination contrasts with the significantly higher probability of damage to vulnerable people.
They conclude, that the further development of the pandemic, after the law was passed, has not changed anything. Nor have any new developments or better insights.
So there you have it. An individual’s rights can be overhauled if a majority of experts conclude you are a danger to a small group of people. Whilst I can understand and appreciate the need to protect the elderly and vulnerable, this shouldn’t be used as a pretext to remove people’s basic rights.
The majority of health care workers want to protect the elderly and vulnerable, that’s why they do the jobs they do. If they are ill or test positive, they aren’t going to deliberately go and infect someone who is likely to die from Covid – they aren’t pyschos (unlike some of the individual’s making these laws).
Furthermore, the science clearly doesn’t back up what they are saying. You are more likely to catch Covid if you are vaccinated and your viral load is similar, if not the same. There may be evidence showing that you are not as infectious for as long but there also may be evidence showing you can have Covid but aren’t testing positive.
Health Minister Karl Lauterbach welcomed the ruling saying that “the state is obliged to protect vulnerable groups”. He is now off for a meeting with other G7 ministers, despite being in contact with the US health secretary, a day before testing positive for Covid. Rules for thee, not for me.
Clearly, the battle to retain one’s basic rights is still not over in many parts of the world. And if it isn’t completely squashed now, you can be sure it will return everywhere with a vengeance, come the winter.
From the heart of the Covid establishment, the truth about asymptomatic spread
By Hector Drummond | TCW Defending Freedom | May 19, 2022
AN important study into Covid-19 has got very little traction, despite coming from the Covid industry’s favourite university, Imperial College London.
This is likely to be because the study totally destroys the industry’s assumptions about asymptomatic spread.
The other institutions involved in this study are the Vaccine Taskforce and Department of Health and Social Care (DHSC), hVIVO (part of Open Orphan plc), and the Royal Free London NHS Foundation Trust. In other words, this study was conducted by the heart of the Covid establishment.
What did they find? Well, forget all you were told about it taking five to six days to develop Covid symptoms, which was always an unwarranted claim whose main purpose was to imprison whole populations. Even if that had been true, it wouldn’t have provided the justification for the Great Jailing that governments across the world sprang on their people. But it’s not true anyway: ‘Researchers found that symptoms start to develop very fast, on average about two days after contact with the virus.’
In fact, it was less than two days – it was 42 hours.
What’s more (and the Imperial press release makes little of this) the amount of detectable virus in the throat and nose in that 42 hours is small. It’s only after symptoms start that the virus levels really crank up. For the first day there’s pretty much nothing; on the second day levels start to rise, but to nowhere near the levels they reach on subsequent days, after symptoms have appeared.
We can see this by looking at some graphs from the paper (from Fig. 2 – the first graph shows levels in the nose by day, the second shows the levels in the throat).


https://www.nature.com/articles/s41591-022-01780-9
As the study says, ‘viral shedding begins within 2 days of exposure’.
Bear in mind also that coughing and sneezing send out vastly far more virus particles than breathing. (For the in-depth details, see chapter 3 of my book The Face Mask Cult.) But if you do not have symptoms, you will not be sneezing or coughing. So even if in the last few hours of your pre-symptomatic period your viral load starts to build up in your nose and throat, you aren’t going to be sending that out into the world in any great amount, because you are pre-symptomatic, and so by definition you aren’t coughing and sneezing.
Remember how you were told at the start of spring 2020 that Covid-19 was a unique virus, different from every virus in history, in that it spread wildly from asymptomatic people, which apparently no virus had ever done before, at least not in anything like the way Covid did? Even normally sober writers such as Matt Ridley spread this melodramatic idea, despite the fact that at the time it had little more credibility than your average urban myth. Asymptomatic spread was the basis for locking everyone up – everyone, not just those with symptoms – but it has turned out to be a chimera.
And of course the enforced quarantine periods not only had to be long, they had to be repeated, over and over, because you could never tell if someone was infected and their breath was spreading Covid across whole suburbs and workplaces and factories, even if that person had just come out of a long enforced quarantine a few days ago after a close contact tested positive, and even if that person felt completely fine. They might still have caught Covid for real since they left quarantine, and even now are killing grandmothers by the dozen as they eat their lunch with their friends. Better lock them up again. And everyone else.
Such was the damage inflicted upon society by the asymptomatic hysteria. In theory it could have gone on for ever; the only things that stopped it doing so were, firstly, the public gradually starting to realise that their lives were being ruined for an overhyped threat, and, secondly, the embarrassing lack of solid evidence to show that asymptomatic spread played much of a role in Covid dissemination (or that Covid was unique in regard to the extent of asymptomatic spread).
So there isn’t any point at all in worrying about catching Covid from someone with no symptoms. There also isn’t any point in symptomless people testing themselves all the time. Or ever. Getting Covid from someone who isn’t showing any signs of it will not happen very often, so the social damage caused by requiring people who aren’t ill to take a test vastly outweighs the benefits of testing them (especially when we consider that the benefits of testing are basically nil anyway – billions of tests have done nothing to prevent Covid remorselessly spreading across the world).
In other words, these results tell us (although this was already clear) to stop testing, stop quarantining and stop worrying about getting Covid from people who aren’t sick. And that means shutting down the whole Covid-industrial complex. The world was trashed for nothing.
I should note that the study does say ‘our data clearly show that SARS-CoV-2 viral shedding occurs at high levels irrespective of symptom severity, thus explaining the high transmissibility of this infection and emphasising that symptom severity cannot be considered a surrogate for transmission risk in this disease’.
This may seem to go against what I have said so far, but it doesn’t, as it applies to the period after symptoms have started, not the period before. It is true that once you have symptoms, there is little correlation between the severity of those symptoms and the amount of viral shedding, as Figs. 4e and 4f in the paper show. (‘Viral shedding’, I should note, refers to the amount of virus found in the nose and throat – it doesn’t refer to the amount of virus being ‘sent out’ by the infected person into the surrounding world.) So someone who has very severe symptoms may not have any more virions in their nose and throat than someone who has mild symptoms.
In the two-day pre-symptomatic period, however, it remains the case that there are only low levels of viral load in the nose and throat, as we saw from the graphs above.
Another significant finding from the study was that it took very little virus to infect someone: ‘Participants were exposed to the lowest possible dose of virus found to cause infection, roughly equivalent to the amount found in a single droplet of nasal fluid when participants were at their most infectious.’
This also means that facemask use is particularly pointless. At best masks can reduce the amount of virions breathed in and out by about 10-15 per cent but if it takes very little to infect a person this will achieve nothing. If someone is breathing out 15,000 virions every ten minutes, reducing that to between 13,500 and 14,000 won’t help.
Of course, the study and the Imperial press release didn’t tell you this. All it said about facemasks was that the study emphasised the importance of wearing them over the nose as well as the mouth, because the nose contained higher peak levels of the virus than in the mouth.
Also, as expected, none of the healthy young people in the study developed anything other than mild-to-moderate cold-like symptoms. None of them ended up in a bad way. As we already knew two years ago, this is a disease which does not threaten the vast majority of young people.
For two years now sceptics like me have been telling people to throw away their tests, and to stop isolating healthy people, and to stop worrying whether the people around you in the restaurant are going to kill you, as the scientific evidence doesn’t support this. If you didn’t believe us then, perhaps you will now.
A Primer on the WHO, the Treaty, and its Plans for Pandemic Preparedness
By David Bell | Brownstone Institute | May 19, 2022
The World Health Organization (WHO), whose constitution defines health as ‘a state of physical, mental and social well-being, not merely the absence of disease or infirmity,’ has recently orchestrated remarkable reversals in human rights, poverty reduction, education, and physical, mental and social health indices in the name of responding to the Covid-19 pandemic.
WHO proposes to expand the mechanisms that enabled this response, diverting unprecedented resources to addressing what in terms of history and disease are rare and relatively low-impact events. This will greatly benefit those who also did well from the Covid-19 outbreak, but has different implications for the rest of us. To address it calmly and rationally, we need to understand it.
Building a new pandemic industry
The World Health Organization (WHO) and its Member States, in concert with other international institutions, is proposing, and currently negotiating, two instruments to address pandemics and widely manage aspects of global public health. Both will significantly expand the international bureaucracy that has grown over the past decade to prepare for, or respond to, pandemics, with particular emphasis on development and use of vaccines.
This bureaucracy would be answerable to the WHO, an organization that in turn is increasingly answerable, through funding and political influence, from private individuals, corporations and the large authoritarian States.
These proposed rules and structures, if adopted, would fundamentally change international public health, moving the center of gravity from common endemic diseases to relatively rare outbreaks of new pathogens, and building an industry around it that will potentially be self-perpetuating.
In the process, it will increase external involvement in areas of decision-making that in most constitutional democracies are the purview of elected governments answerable to their population.
WHO does not clearly define the terms ‘pandemic’ and ‘public health emergency’ that these new agreements, intended to have power under international law, seek to address. Implementation will depend on the opinion of individuals – the Director General (DG) of the WHO, Regional Directors and an advisory committee that they can choose to follow or ignore.
As a ‘pandemic’ in WHO parlance does not include a requirement of severity but simply broad spread – a property common to respiratory viruses – this leaves a lot of room for the DG to proclaim emergencies and set the wheels in motion to repeat the sort of pandemic responses we have seen trialed in the past 2 years.
Responses that have been unprecedented in their removal of basic peace-time human rights, and that the WHO, Unicef and other United Nations (UN) agencies have acknowledged to cause widespread harm.
This has potential to be a boon for Big Pharma and their investors who have done so well out of the last two years, concentrating private wealth whilst increasing national indebtedness and reversing prior progress on poverty reduction.
However, it is not something that has just appeared, and is not going to make us slaves before the month is out. If we are to address this issue and restore societal sanity and balance in public health, we need to understand what we are dealing with.
Proposed International Health Regulations (IHR) amendments
The IHR amendments, proposed by the United States, build on the existing IHR that were introduced in 2005 and are binding under international law. While many are unaware of their existence, the IHR already enables the WHO DG to declare public health emergencies of international concern, and thereby recommend measures to isolate countries and restrict movement of people. The draft amendments include proposals to:
- Establish an ‘emergency committee’ to assess health threats and outbreaks and recommend responses.
- Establish a ‘Country review mechanism’ to assess compliance of countries with various recommendations / requirements of WHO regarding pandemic preparedness, including surveillance and reporting measures. This appears to be modeled on the UN’s human rights country review mechanism. Countries would then be issued with requirements to be addressed to bring them into compliance where their internal programs are considered inadequate, on the request of another State party (country).
- Expand the power of the WHO DG to declare pandemics and health emergencies, and therefore recommend border closures, interruption and removal of rights to travel and potentially internal ‘lockdown’ requirements and send teams of WHO personnel to countries to investigate outbreaks, irrespective of the findings of the emergency committee and without consent of the country where the instance is recorded.
- Reduce the usual review period for countries to internally discuss and opt out of such mechanisms to just 6 months (rather than 18 months for the original IHR), and then implement them after a 6-month notice period.
- Empower Regional Directors, of which there are 6, to declare regional ‘public health emergencies,’ irrespective of a decision by the DG.
These amendments will be discussed and voted on at the World Health Assembly on May 22-28, 2022. They only require a simple majority of countries present to come into law, consistent with Article 60 of the WHO constitution. For clarity, this means countries such as Niue, with 1,300 people, have an equal weight on the voting floor as India, with 1.3 billion people. Countries must then signal intent to opt out of the new amendments within 6 months.
Once approved by the WHA, these measures will become legally binding. There will be heavy pressure applied to governments to comply with the dictates of the WHO DG and the unelected bureaucrats that comprise the organization, and thereby also the external actors who are influential in WHO decision-making processes.
Proposed WHO pandemic ‘treaty’
The WHO proposes a new ‘instrument’ to allow it to manage pandemics, with force of a convention under international law. This has been formally discussed within WHO since early 2021, and a special session of the WHA in November 2021 recommended it go to a review process, with a draft to be presented to the World Health Assembly meeting in Q2 2023.
This proposed treaty would give WHO powers to:
- Investigate epidemics within countries,
- Recommend or even require border closures,
- Potentially recommend travel restrictions on individuals,
- Impose measures recommended by the WHO which, based on Covid-19 experience, may include ‘lockdowns,’ prevention of employment, disruption of family life and internal travel, and mandated masks and vaccination,
- Involve non-state actors (e.g., private corporations) in data gathering and predictive modeling to influence and guide pandemic responses; and in implementing, including providing commodities for, the response;
- Impose censorship through control of, or restrictions on, information the WHO considers to be ‘mis-information’ or ‘dis-information’, which may include criticism of the measures WHO imposes.
Notably, it envisions the setting up of a large entity within WHO to support permanent staff whose purpose is to undertake and enforce the above measures. This sounds very similar to the ‘GERM’ entity proposed recently by Mr Bill Gates, a wealthy US software developer with major pharmaceutical investments, who is the second largest funder of the WHO and one of a number of ‘billionaires’ who have greatly increased personal wealth during the Covid-19 response.
The proposed treaty would prioritize vertical structures and pharmaceutical approaches to pandemics, reflecting approaches by Gavi and CEPI, two organizations set up in the past decade in parallel to the WHO. It would create another bureaucratic structure on pandemics, not answerable directly to any taxpayer base, but imposing further support, reporting and compliance requirements.
Process, acceptance and implementation
These two mechanisms for increasing direct WHO control of pandemics have strong backing from private sector funders of the WHO, and from many national governments, starting with Western governments who adopted Covid draconian measures. To come into practice they must be adopted by the WHA and then be agreed, or ratified, by national governments.
The proposed IHR amendments modify an existing mechanism. A simple majority of States present at the WHA voting against them at the May 2022 meeting would also reject them, but this appears unlikely. To prevent their application, sufficient individual countries will need to signal non-acceptance or reservations after the coming WHA and WHO DG’s notice of adoption, so probably before the end of November 2022.
With regard to the proposed treaty, a two-thirds majority at the 2023 WHA will be required for its adoption, after which it will be subject to national ratification by processes which vary according to national norms and constitutions.
Funding for the large increase in bureaucracy proposed to support both mechanisms will be necessary – this may be partially diverted from other disease areas but will almost certainly require new, regular funding. Other mechanisms in parallel are already being discussed, with the World Bank also proposed as the home for a similar bureaucracy to manage pandemic preparedness, and the G20 mulling their own mechanism.
It is unclear whether these would be tied into the WHO’s proposed treaty and IHR mechanisms or be presented as a ‘rival’ approach. The G20 task force of the WB and WHO suggest a $10.5 billion additional annual budget for pandemic preparedness is required. With such potential financing on offer, and the promise of building powerful institutions around this pandemic preparedness agenda, there is going to be much enthusiasm and momentum, not least from institutional staff and the global health community in general, who will sense lucrative employment and grant opportunities.
While all this depends on money being available, a refusal of countries to fund may not be sufficient to prevent it, as there is considerable private and corporate interest in the treaty and related proposals. The same entities that benefited heavily financially from the Covid-19 response will also stand to benefit from an increased frequency of similar responses.
Whilst pandemics are historically rare, the existence of a large bureaucracy dependent on their declaration and response, coupled with the clear gains to be made by influential funders of the WHO, raise a strong risk that the bar to declaring emergencies, and imposing human rights restrictions on States, will be far lower than before.
Independent States are not however directly subject to the WHO, and adopting these amendments and treaties will not automatically allow the WHO to send teams across borders. Treaties must be ratified according to national processes and constitutions. If accepted by the WHA, it will however be difficult for individual States to avoid compliance unless they are particularly influential on the WHO itself.
International financial agencies, such as the IMF and World Bank, can also exert considerable pressure on non-complying States, potentially tying loans to implementation and commodity purchase as the World Bank has done for the COVID-19 response.
The IHR amendments also allow measures to be taken such as interrupting international travel that can be economically very harmful to small States, irrespective of the State providing permission. Powerful States that are highly influential on the DG election may also in practice be subject to different levels of implementation than smaller ones.
There seem to be at least two feasible scenarios for preventing the adoption of the two new mechanisms.
Firstly, the populations in democratic donor States, who have most to lose in terms of autonomy, sovereignty and human rights and whose taxes will predominantly fund these institutions, can stimulate open debate leading to decisions of national governments to reject the treaty at the WHA, and/or otherwise refuse to ratify.
Secondly, large blocs of countries could refuse to ratify or subsequently comply, making the treaty and IHR amendments unworkable. The latter is conceivable if, for instance, African nations perceive all this as a form of neo-colonialism that needs to be fought in the name of independence.
Some background on pandemic risk, and the WHO.
What is the risk of pandemics?
WHO records 5 pandemics in the past 120 years:
- The Spanish Flu (1918-19), killed 20-509 million people. Most died due to secondary bacterial infection, as this was before availability of any modern antibiotics.
- The 1957-58 influenza outbreaks that killed about 1.1 million people each
- The 1968-69 influenza outbreak that also killed about 1.1 million
- Swine Flu in 2009-10 killed about 120,000 to 230,000.
- Lastly, COVID-19 (2020-22) is recorded by WHO as contributing to the death of several million, but most in old age with other severe comorbidities, so actual figures are difficult to assess. As this indicates.
Pandemics have therefore been rare – once per generation. For context, cancer kills many more people each year in Western countries than Covid-19 at its height, tuberculosis kills 1.6 million people every year (much younger than Covid-19) and malaria kills over half a million children annually (barely affected by COVID-19).
However, as pandemics are very loosely defined by WHO, it Is not unreasonable to assume that a large bureaucracy dependent on pandemics to justify its own existence, and heavily invested in surveillance for new strains of virus, will find reason to declare far more pandemics in the future.
Pandemic response
COVID-19 is the first pandemic in which mass lockdowns, including border closures, workplace closures and prolonged school closures, have been used on a large scale. It is worth remembering that 1969 is remembered for the Woodstock music festival more than the ‘Hong Kong flu,’ a pandemic that targeted young people more than Covid-19. Human rights and economic health did not suffer such declines in any of these prior events.
These new approaches used in the Covid-19 response have resulted in wide disruption of supply lines and healthcare access, increases in early marriage / enslavement of women, mass loss of education of children, and increases in current financial inequality and educational (so future) inequality. Many low-income countries have increased debt and undergone recession, which will reduce future life expectancy, while child deaths have increased, including from former priority diseases such as malaria.
What is WHO, and who owns or runs it?
The WHO (the World Health Organization) was set up in the late 1940s, to coordinate health standards and data sharing internationally, including support for the response to pandemics. It is the main health agency of the United Nations Organization (UN). It provides some support for low-income country health systems where local technical expertise is lacking.
It has country offices in most countries, 6 regional offices, and a global office in Geneva. It is a hierarchical organization, with the Director General (DG) at its head. It has a few thousand staff (depending on definition) and a budget of roughly $3.5 billion a year.
The WHO is controlled in theory by the member nations (most UN members, and a couple of others), on a one country-one vote basis through the World Health Assembly, that usually meets annually. As example, India, with 1.3 billion people, has the same power on the voting floor as Nuie, with 1,300 people. The WHA elects the DG through a 4-yearly vote that is often heavily accompanied by lobbying by major countries.
WHO funding was originally nearly all derived from member countries, who contributed to the ‘core’ budget. WHO would then decide on priorities for expenditure, guided by the WHA. In the past 2 decades, there has been a significant change in funding:
- A rapid increase in private funding, from individuals and corporations. Some is direct, some indirect through parallel international health organizations (Gavi, Cepi) that are heavily privately funded. The second largest contributor to the WHO budget is now a private couple in the United States heavily invested in the international pharmaceutical sector and in software / digitization services.
- The budget has moved from mainly core funding, to mainly ‘directed’ funding, in which the funder specifies the area in which the funding can be used, and sometimes the actual activities to be undertaken. The WHO therefore becomes a conduit for their funds to undertake their intended activities. Both country private funders heavily use this directed approach.
The WHO therefore retains under overall control of an assembly of countries, but day-to-day priorities are increasingly directed by single countries and private interests. Former strong rules on conflict of interest regarding private sector involvement are less externally obvious now, with WHO working more closely with private and corporate sector entities.
Reference documents:
- WHO constitution: https://apps.who.int/gb/bd/PDF/bd47/EN/constitution-en.pdf?ua=1
- IHR 2005: https://www.who.int/publications/i/item/9789241580410
- WHO IHR proposed amendments: https://apps.who.int/gb/ebwha/pdf_files/WHA75/A75_18-en.pdf
- EU and proposed WHO treaty: https://www.consilium.europa.eu/en/policies/coronavirus/pandemic-treaty/
- WHO WHA Nov 21 Special Session draft report: https://apps.who.int/gb/wgpr/pdf_files/wgpr5/A_WGPR5_2-en.pdf
- WHO (EURO) influenza pandemic definition: https://www.euro.who.int/en/health-topics/communicable-diseases/influenza/pandemic-influenza
- WHO ‘zero draft’ of proposed pandemic treaty: https://apps.who.int/gb/wgpr/pdf_files/wgpr9/A_WGPR9_3-en.pdf
- Review of WHO pandemic definitions: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3127275/
- Unicef on harms from public health response:
- https://data.unicef.org/covid-19-and-children/
- IFF harms from public health response: https://www.globalfinancingfacility.org/emerging-data-estimates-each-covid-19-death-more-two-women-and-children-have-lost-their-lives-result
- BIS on health impact of economic harms https://www.bis.org/publ/work910.htm
- On G20 and World Bank mechanisms: https://g20.org/wp-content/uploads/2022/02/G20-FHTF-Financing-Gaps-for-PPR-WHOWB-Feb-10_Final.pdf
- WHO pandemic guidelines (includes previous pandemic list): https://apps.who.int/iris/bitstream/handle/10665/329438/9789241516839-eng.pdf
- Background on evolution of the WHO: https://www.pandata.org/who-and-covid-19-re-establishing-colonialism-in-public-health/
David Bell is a public health physician based in the United States. After working in internal medicine and public health in Australia and the UK, he worked in the World Health Organization (WHO), as Programme Head for malaria and febrile diseases at the Foundation for Innovative New Diagnostics (FIND) in Geneva, and as Director of Global Health Technologies at Intellectual Ventures Global Good Fund in Bellevue, USA. He consults in biotech and global health. MBBS, MTH, PhD, FAFPHM, FRCP
WHO Stealth Coup to Dictate Global Health Agenda of Gates, Big Pharma
By F. William Engdahl – New Eastern Outlook – 18.05.2022
Acting on an initiative from the Biden Administration, by November 2022, conveniently at the onset of the next flu season in the northern hemisphere, the World Health Organization, barring a miracle, will impose an unprecedented top-down control over the national health regulations and measures of the entire planet. In what amounts to a stealth coup d’etat, WHO will get draconian new powers to override national sovereignty in 194 UN member countries, and to dictate their health measures with force of international law. It is sometimes referred to as the WHO Pandemic Treaty but it is far more. Worse, most of the WHO budget comes from private vaccine-tied foundations like the Gates Foundation or from Big Pharma, a massive conflict of interest.
Draconian New WHO Powers
Doing something with stealth means doing it in a secretive or concealed manner, to prevent it being widely known and possibly opposed. This applies to the proposal given by the Biden Administration to the Geneva WHO in January 18, 2022 according to official WHO documents. The WHO hid the details of the US “amendments” for almost three months, until 12 April, just a month before the relevant body of the WHO meets to approve the radical measures. Moreover, rather than the previous 18 month waiting time to become treaty in international law, only 6 months are used this time. This is a bum’s rush. The US proposal is backed by every EU country and in total 47 countries ensuring almost certain passage.
The proposals, officially titled, “Strengthening WHO preparedness for and response to health emergencies: Proposal for amendments to the International Health Regulations,” were submitted by Assistant Secretary for Global Affairs (OGA) in the US Department of Health and Human Services, Loyce Pace, as “amendments” to a previously ratified 2005 WHO International Health Regulations treaty. The WHO defines that 2005 treaty thus: “the International Health Regulations (2005) (IHR) provide an overarching legal framework that defines countries’ rights and obligations in handling public health events and emergenciesthat have the potential to cross borders. The IHR are an instrument of international law that is legally-binding on 196 countries, including the 194 WHO Member States.” (emphasis added).
Ms Pace came to the Biden Administration from heading the Global Health Council, whose members include the most corrupt names in Big Pharma including Pfizer, Lilly, Merck, J&J, Abbott, Bill Gates-funded AVAC, to name a few. Her proposals for the radical transformation of WHO “pandemic” and epidemic powers, could easily have been written by Gates and Big Pharma.
Before we look at what the Loyce Pace “amendments” will do to empower the transformation of WHO into a global health dictatorship with unprecedented powers to overrule judgments of any national governments, one stealthy legal issue must be noted. By disguising a complete change in the 2005 WHO treaty powers as mere “amendments” to a ratified treaty, WHO claims, along with the Biden Administration, that the approval of the amendments requires no new ratification debate by member governments. This is stealth. With no national debate by elected representatives, the unelected WHO will become a global superpower over life and death in the future. Washington and WHO have deliberately restricted the process of public participation to ram this through.
A De Facto New Law
As required, the WHO finally published the US “amendments.” It shows the deletions and as well the new additions. What the Biden Administration changes do is to transform a previously advisory role for the WHO to national governments on not only pandemic responses but also everything tied to national “health,” with an entirely new power to override national health agencies if the WHO Director General, now Tedros Adhanom, determines. The US Biden Administration and WHO have colluded to create an entirely new treaty which will shift all health decisions from a national or local level to Geneva, Switzerland and WHO.
Typical of the Washington amendments to the existing WHO Treaty is Article 9. The US change is to insert WHO “shall” and delete “may”: “If the State Party does not accept the offer of collaboration within 48 hours, WHO shall may…,. In the same article now deleted is “offer of collaboration by WHO, taking into account the views of the State Party concerned…” The views or judgment of say, Germany or India, or USA health authorities become irrelevant. WHO will be able to override national experts and dictate as international law its mandates for any and all future pandemics as well as even epidemics or even local health issues.
Moreover in the new proposed Article 12 on “Determination of a public health emergency of international concern, public health emergency of regional concern, or intermediate health alert,” WHO head–now Tedros in his new 5-year term–alone can decide to declare an emergency, even without agreement of the member state. The WHO head will then consult his relevant WHO “Emergency Committee” on Polio, Ebola, Bird Flu, COVID or whatever they declare to be a problem. In short this is a global dictatorship over citizen health by one of the most corrupt health bodies in the world. The members of a given WHO Emergency Committee are chosen under opaque procedures and typically, as in the current one on polio, many members are tied to the various Gates Foundation fronts like GAVI or CEPI. Yet the selection process is entirely opaque and internal to WHO.
Among other powers the new Pandemic Treaty will give Tedros and WHO the power to mandate vaccine passports and COVID jabs worldwide. They are working on the creation of a global vaccine passport/digital identity program. Under the new “Pandemic Treaty”, when people are harmed by the WHO’s health policies, there’s no accountability. The WHO has diplomatic immunity.
Former WHO senior employee and whistleblower, Astrid Stuckelberger, now a scientist at the Institute of Global Health of the Faculty of Medicine of the University of Geneva, noted, “if the new Pandemic Treaty is adopted by member states, “this means that the WHO’s Constitution (as per Article 9) will take precedence over each country’s constitution during natural disasters or pandemics. In other words, the WHO will be dictating to other countries, no longer making recommendations.”
Who is WHO?
The Director General of WHO would have the ultimate power under the new rules, to determine for example if say, Brazil or Germany or USA must impose a Shanghai-style pandemic lockdown or any other measures it decides. This is not good. Especially when the head of WHO, Tedros, from the Tigray region of Ethiopia, is a former member of the Politburo of the designated terrorist (then by Washington) Marxist organization, the Tigray People’s Liberation Front. He holds no medical degree, the first in WHO director-general history without such. He has a PhD in Community Health, definitely a vague field, hardly medical qualification for a global health czar. Among his published scientific papers are titles such as “The effects of dams on malaria transmission in Tigray Region.” He reportedly got his WHO job in 2017 via backing from Bill Gates, the largest private donor to WHO.
As Ethiopia Minister of Health in the Tigray-led dictatorship, Tedros was involved in a scandalous coverup of three major cholera outbreaks in the country in 2006, 2009 and 2011. An investigative report published by the Society for Disaster Medicine and Public Health found that during one major cholera outbreak, “Despite laboratory identification of V cholerae as the cause of the acute watery diarrhea (AWD), the Government of Ethiopia (Tedros) decided not to declare a “cholera outbreak” for fear of economic repercussions resulting from trade embargos and decreased tourism. Further, the government, in disregard of International Health Regulations (WHO), continually refused to declare a cholera epidemic and largely declined international assistance.”
As Ethiopian Health and later Foreign Minister Tedros was accused of systematic ethnic cleansing against rival tribes in the country, especially Amharas, denying opposition supporters World Bank and other food aid, as well as nepotism, diversion of international funds for hospital construction into political support for his minority party. Ironically this is the opposite of the new WHO law Tedros backs today. On 22 September 2021 Merkel’s Germany proposed Tedros for a further term without opposition.
WHO, Gates, GERM
A hint of what’s in store under the new rules was given by WHO’s largest donor (including his GAVI), the self-appointed “Globalist Everything Czar”, Bill Gates. On his April 22 blog entry, Gates proposes something amusingly with the acronym GERM — Global Epidemic Response and Mobilization—team. It would have a “permanent organization of experts who are fully paid and prepared to mount a coordinated response to a dangerous outbreak at any time.” He says his model is the Hollywood movie, Outbreak. “The team’s disease monitoring experts would look for potential outbreaks. Once it spots one, GERM should have the ability to declare an outbreak…” It would be coordinated by, of course, Tedros’ WHO: “The work would be coordinated by the WHO, the only group that can give it global credibility.”
A dystopian notion of what could take place is the ongoing fake “Avian Flu” epidemic, H5N1, that is causing tens of millions of chickens to be terminated worldwide if even one chick tests positive for the disease. The test is the same fraudulent PCR test used to detect COVID-19. Recently, Dr Robert Redfield, Trump’s head of CDC, gave an interview where he “predicted” that Bird Flu will jump to humans and be highly fatal in the coming “Great Pandemic,” for which COVID-19 was a mere warm-up. Redfield declared in a March 2022 interview, “I think we have to recognize – I’ve always said that I think the COVID pandemic was a wakeup call. I don’t believe it’s the great pandemic. I believe the great pandemic is still in the future, and that’s going to be a bird flu pandemic for man. It’s gonna have significant mortality in the 10-50% range. It’s gonna be trouble.” Under the new WHO dictatorial powers, WHO could declare a health emergency on such a fraud regardless of contrary evidence.
American Airlines Captain Robert Snow speaks out about his vaccine injury
Steve Kirsch | May 14, 2022
Ever wonder why so many flights are delayed or canceled? A lot of it is due to injuries caused by the vaccine mandates.
Today, there are many pilots who are vaccine injured and not saying anything, endangering the public.
Here’s what happened to one vaccine injured pilot who now has to retire because he’s unable to fly anymore.
He speaks freely, right after being released from the hospital.
And no, the CEO of American Airlines, working just 10 minutes away didn’t call or come visit him. That’s the way they treat “family” at American Airlines.
Other articles about the vaccine and pilots
I wonder if the vaccine is causing all these incidents. I’m told they are safe and effective. But that’s not what the data says.
THREE KILLED, AS PLANE CRASHES INTO MEXICAN SUPERMARKET
PLANE CRASHES ONTO A STREET IN SAN DIEGO
PILOT SUFFERS MID-AIR HEART ATTACK
CO-PILOT LANDS PLANE AFTER PILOT HAS HEART ATTACK:
TRAFFIC CONTROL HELPS PASSENGER LAND PLANE, AFTER PILOT HAS HEART ATTACK
Conspiracies about conspiracy theories
A little trip down memory lane
el gato malo – bad cattitude – may 16, 2022
My goodness, these “conspiracy theorists” certainly do have vivid imaginations, don’t they?
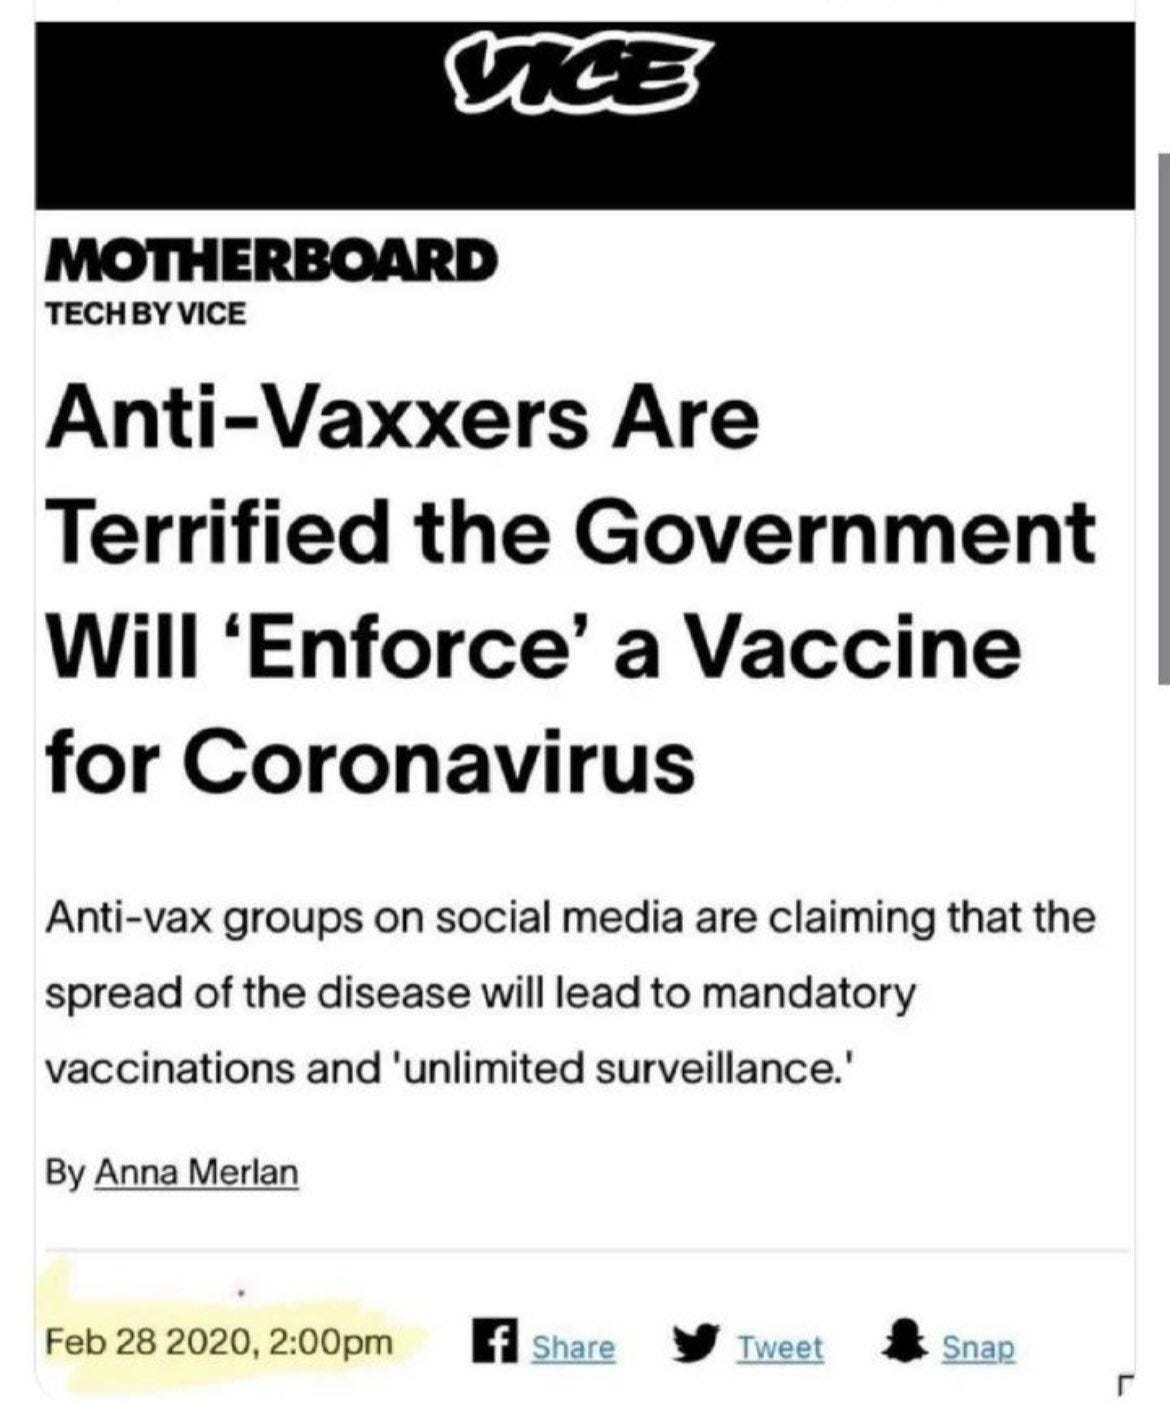
i mean, that would be terribly divisive, counter to rights, and directly antagonistic to people who just want bodily autonomy. can you even imagine public officials doing something like that?
pretty far fetched…

or health bodies using disease to engage in surveillance?
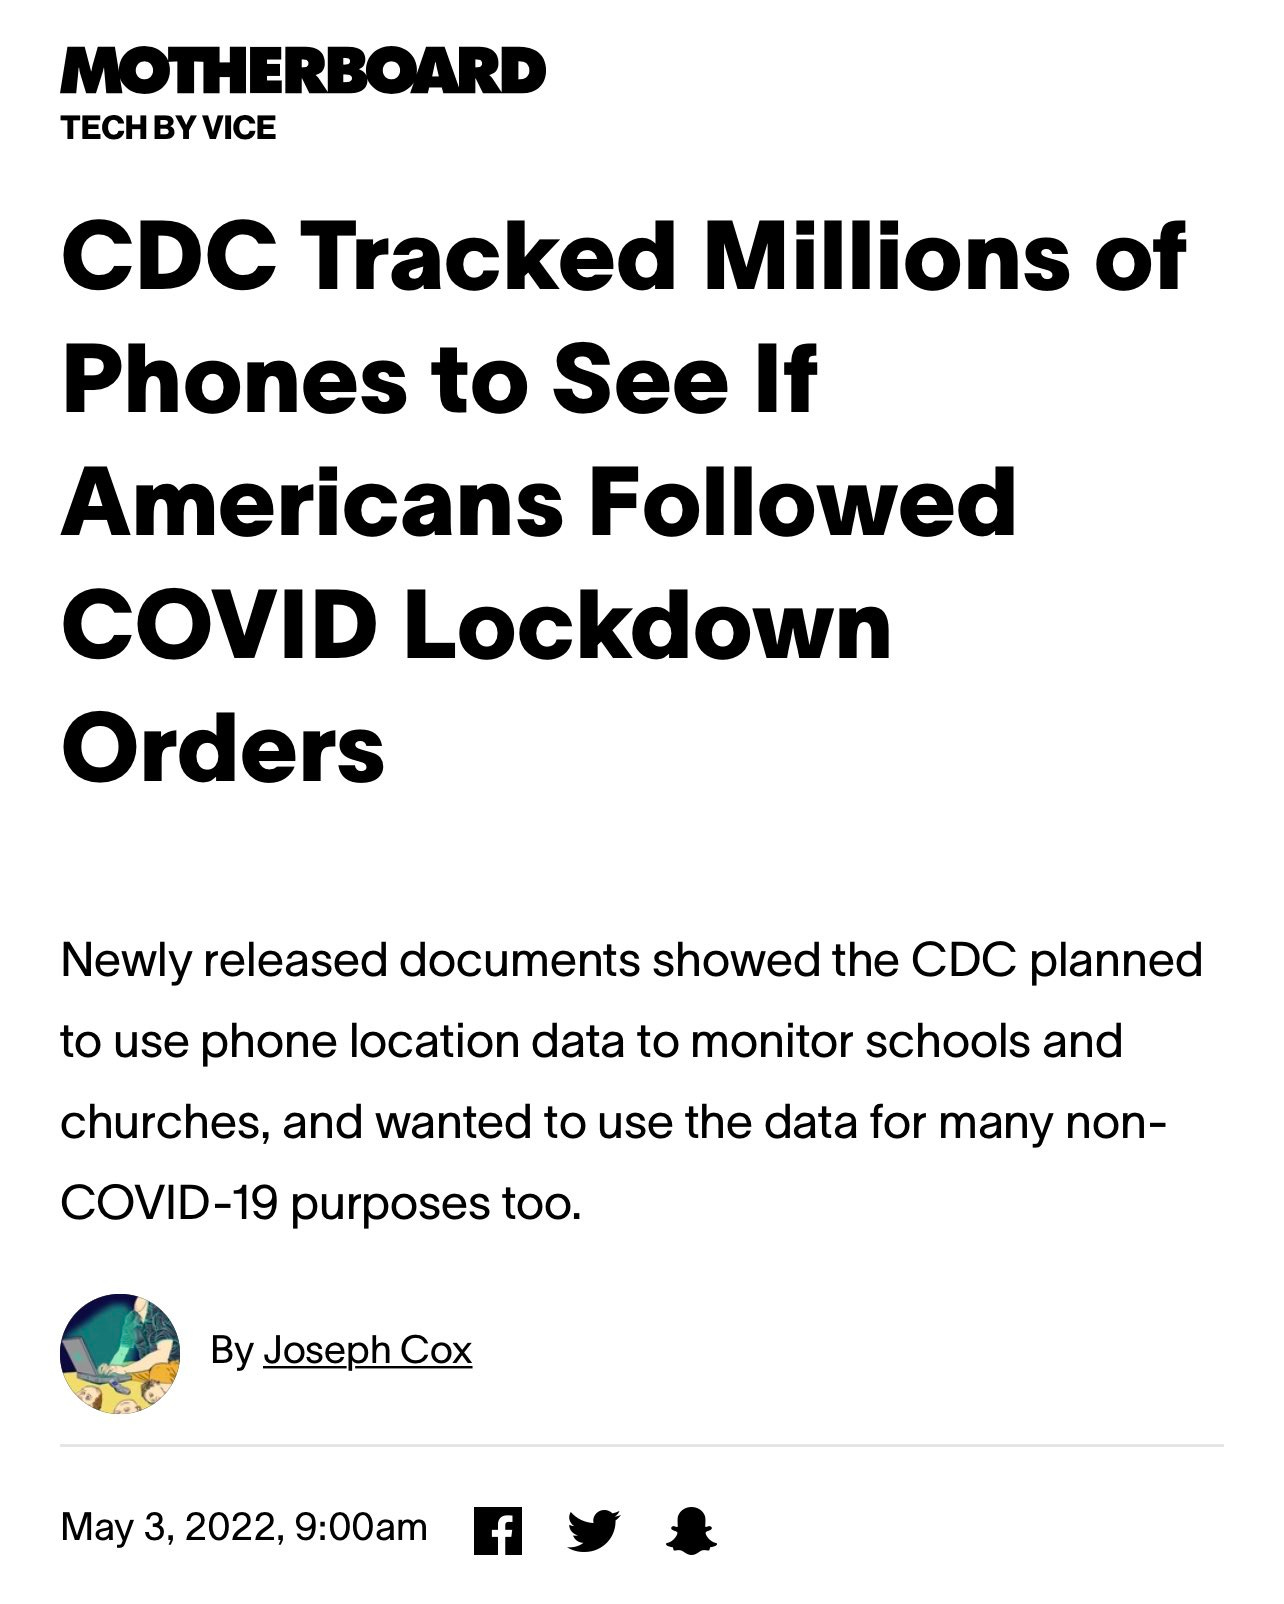
or governments seeking to do the same and mitigate privacy altogether?
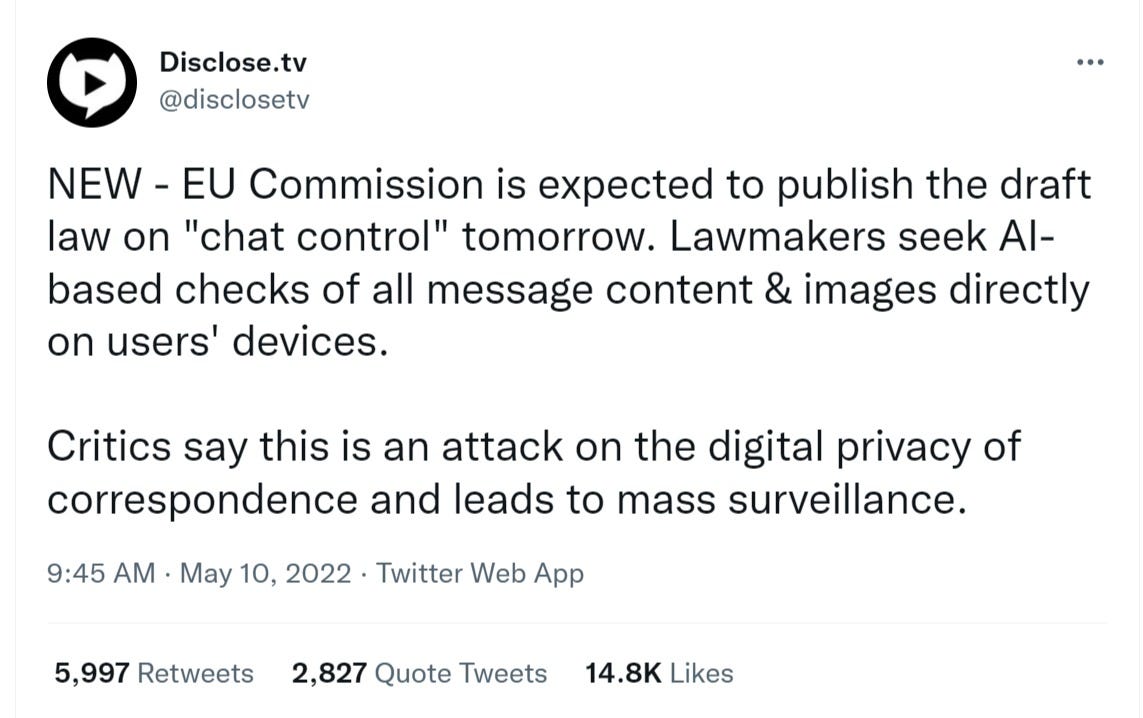
i mean, that’s just silly!
what next, some wild eyed claims that they want universal digital ID?

that they have been quietly rolling out the standards for

and making international and inescapable?

i mean, what will these prolific conspiracy boffins think up next, some sort of state run digital currencies to link to this new ID and surveillance state?
i mean, who would even suggest something like that?

federalreserve.gov/cbdc-faqs.htm
and anyhow, what’s the worst that could happen?

i mean, they told us this is all benign, right?

and it’s not like they ever lied to us before! (or if they did, i’m sure it was for our own good…)

and it’s not like they are seeking to give this power to deeply compromised and captured transnational agencies with no accountability whatsoever and grant them authority over citizens who had no say in the matter…

“The Biggest Global Power Grab We Have Seen in Our Lifetimes”: How Serious is the Threat From the WHO Pandemic Treaty?
so let’s all take a breath. i’m sure you’re just overwrought and imagining things.
there are no conspiracies.
no one is out to get you, least of all some shadowy davos cabal.
and come on, if they were really trying to do this to you, i’m sure they would not just come right out and tell you in some sort of james bond villain megalomaniacal monologue.
i mean, this is real life. no one actually does that…
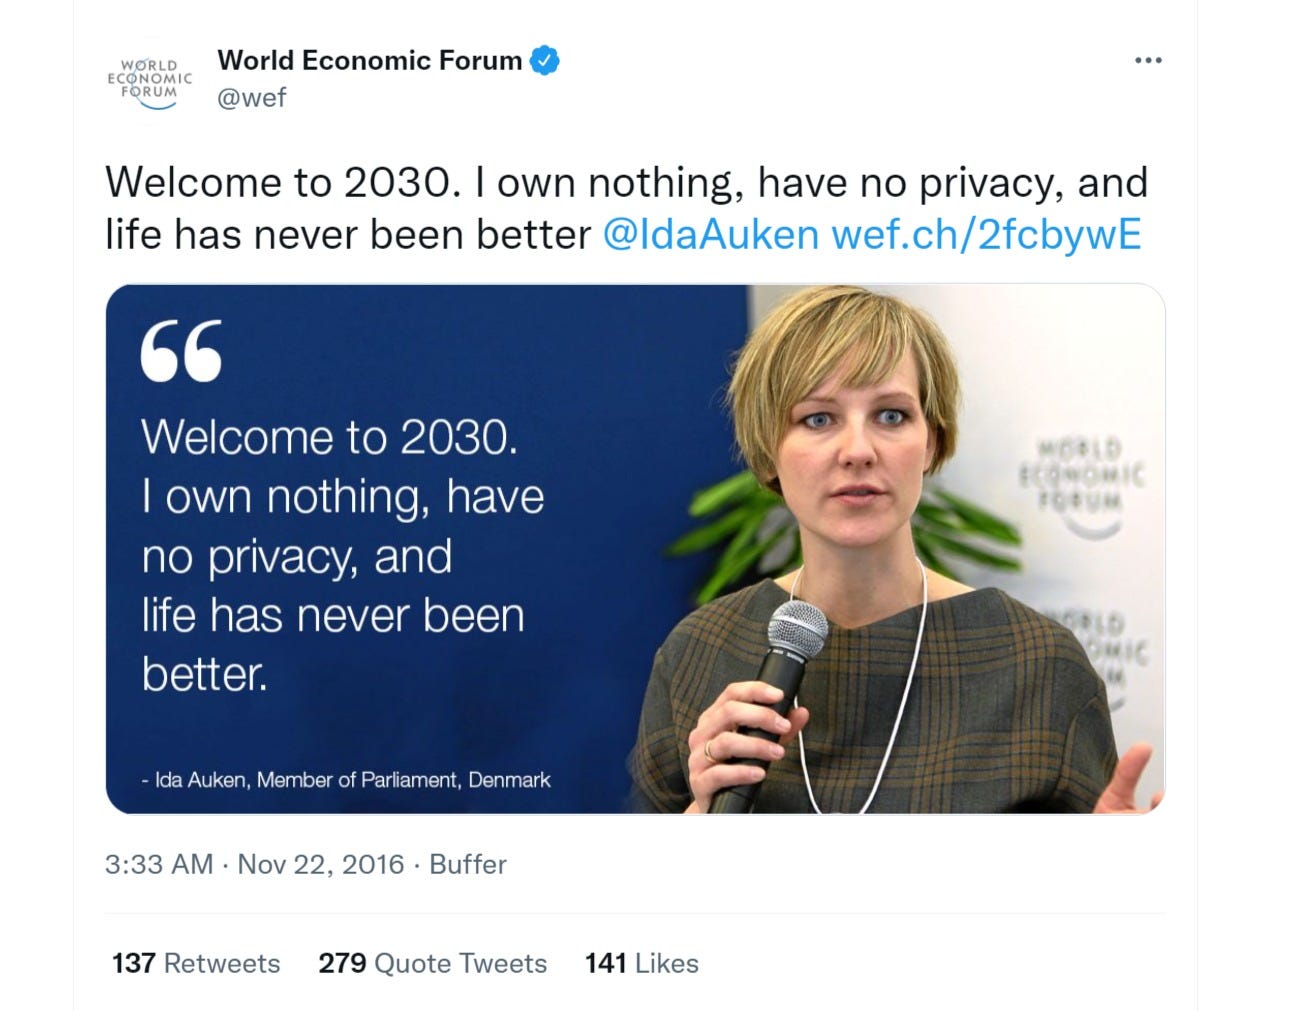
and hey, i’m sure they’ll probably manage to keep those first 2 promises.
watch out for that third one though.
i have some real doubts about it it…
Data From Iceland and Australia Confirm: Vaccine Effectiveness Is Overstated
By Noah Carl | The Daily Sceptic | May 16, 2022
Back in March, I wrote a post noting that excess mortality data from Europe and Israel were hard to reconcile with claims of 95% vaccine effectiveness against death. However, I also noted that some countries data were consistent with very high vaccine effectiveness against death.
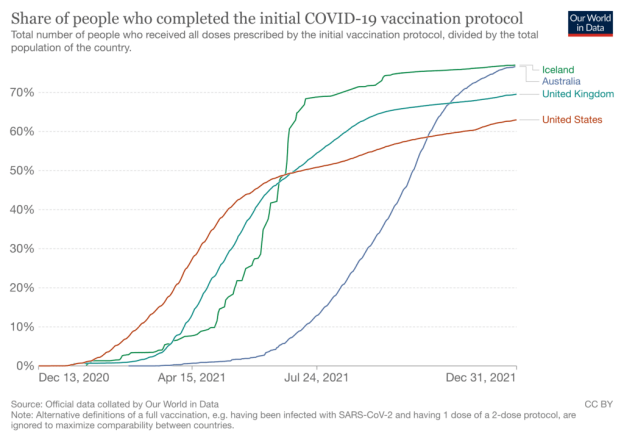
The two examples I gave were Australia and Iceland – both countries with very high vaccination rates. By the end of 2021, each country had double-vaccinated 77% of its population, compared to only 70% in the U.K. and only 63% in the U.S. (see below).
At the time I wrote the post, Iceland had only seen a minor uptick in excess mortality, while Australia had not seen any at all – despite both countries experiencing major outbreaks in the winter/spring of 2022. If countries like Germany, the Netherlands and Israel had seen deadly post-vaccination waves, why hadn’t Iceland and Australia? That was the puzzle.
It appears that ‘puzzle’ is now solved – we just needed to wait for more data. The latest figures from Iceland and Australia show sizeable upticks in excess mortality. First, let’s look at Iceland:
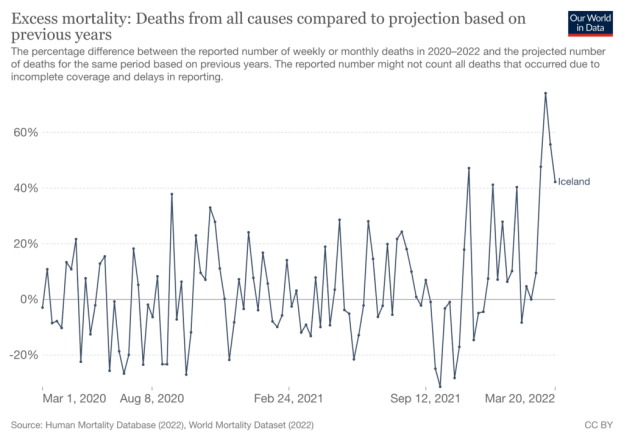
After bouncing around the zero mark for the first two years of the pandemic, excess mortality jumped to 74% in the first week of March. And it has now been above zero for eleven of the last thirteen weeks. Next, let’s consider Australia:
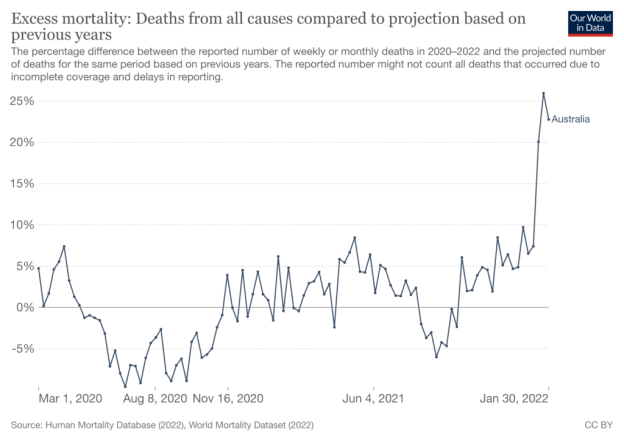
Over the first two years of the pandemic, excess morality averaged roughly zero – dipping lower in the summer and rising higher in the winter. Yet since the start of October, it has been consistently positive, jumping to 26% in the third week of January.
It should be noted: these upticks in excess mortality are not as large as those seen in European countries during 2020 and 2021.
However, they indicate that even very high vaccination rates are not sufficient to prevent mortality from rising when there’s a major outbreak. And they cast further doubt on claims that the vaccines are 95% effective against death. If they were 95% effective against death, excess mortality should hardly have risen at all in Iceland and Australia.
Given that 77% of the entire population was double vaccinated before the latest outbreaks began (and that’s the entire population, not just over 16s), you’d have to believe that excess mortality would have been many, manty times higher in the absence of vaccination to rescue the claim of 95% effectiveness against death.
What’s probably true instead is that the vaccines do reduce mortality from Covid – but not by 95%.
Investigation Launched After ‘Mystery’ Surge in Deaths of Newborn Babies
By Paul Joseph Watson | Summit News | May 16, 2022
Health authorities in Scotland have launched an investigation after a mystery surge in deaths of newborn babies, the second time the phenomenon has been recorded in the space of six months.
A report by the Herald newspaper highlights the “very unusual” spike in deaths of babies, with the alarm being raised after 18 infants died within four weeks of birth in March.
That same control limit was also breached in September last year, when 21 neonatal deaths were reported, the first time this had occurred since records began.
“The neonatal mortality rate was 5.1 per 1,000 live births in September and 4.6 per 1,000 in March, against an average of 1.49 per 1000 in 2019,” reports the newspaper.
Public Health Scotland (PHS) said the deaths could not have been down to chance, while the cause behind the previous spike in September also “remained a mystery.”
The report notes that vaccination uptake has increased in expectant mothers and that COVID infections during pregnancy are associated with a higher chance of premature birth, but found no “direct link” between COVID surges and the deaths.
PHS Scotland says COVID infections “did not appear to have played a role” in the September spate of deaths.
Edinburgh University’s Dr. Sarah Stock said, “The numbers are really troubling,” but admitted she didn’t know the cause of the deaths.
The vaccine cajolers, Part 4: Rewriting history
This is the fourth instalment of Paula Jardine’s six-part investigation into the planning behind ensuring vaccine acceptance and countering vaccine ‘hesitancy’. You can read Part 1, published on Wednesday, here, Part 2, published on Thursday, here, and Part 3, published yesterday, here.
TCW Defending Freedom – May 14, 2022
WHEN Unicef launched the Child Survival Revolution in 1983, it openly acknowledged that infectious childhood diseases in industrialised countries had ceased to be a serious threat before vaccines were introduced, thanks primarily to improvements in sanitation and nutrition.
Later, something resembling a bait and switch took place in traditionally accepted scientific thinking on this empirical observation. The US Centers for Disease Control (CDC) now brands the central role played by improved sanitation and nutrition an anti-vaccination myth, and largely credits vaccines for the reduction in disease burden instead. This amounts to a misrepresentation, an untrue statement of a material fact that is being used to inflate the past performance of vaccines. It would count as unlawful mis-selling in other commercial contexts.
The World Health Organisation (WHO) says: ‘Immunisation is a global health and development success story, saving millions of lives every year.’ It puts the number of lives saved annually at between 3.5million and 5million.
Yet, perversely, universal vaccination may be masking health and mortality problems that arise from the vaccines as, by definition, there’s no control group for comparison. Igor Chudov analysed the 2021 statistics from Florida: ‘What I found is that in 2021, parents of newborns in Florida were much more “vaccine hesitant”, for reasons obvious to my readers, and therefore childhood vaccinations decreased from 93.4 per cent previously to only 79.3 per cent in 2021. During the same time, “all cause” infant mortality under one year of age in Florida also DECREASED by 8.93 per cent.’ (his emphasis)
Chudov’s findings chime with those of Australian physician Dr Archie Kalokerinos who investigated a doubling of the infant mortality rate in Aborigine communities in the 1970s on behalf of the Northern Territories government. He discovered the death rate rose after they began vaccinating malnourished Aborigine children. In some communities, every second child was injured or died.
A 2016 meta-analysis of studies into the DTP vaccine, against diphtheria, tetanus and pertussis (whooping cough) found it increases female mortality rates. Court cases in the US in the 1970s linked it with Sudden Infant Death Syndrome. The CDC calls this association ‘one myth that won’t seem to go away’. Disturbingly in this context, the extent of DTP vaccination coverage is a metric used to monitor access to primary health care and is used by the vaccine alliance GAVI as an equity measure.
A 2021 vaccination impact study led by Professor Neil Ferguson of Imperial College London made the great claim that vaccine campaigns in low and middle income countries had saved a total of 23million children’s lives over the past two decades, and projected that this figure will increase to 37million by 2030. But as with any honest cost-benefit analysis, Ferguson’s estimates need to be offset against another statistic. GAVI itself acknowledges that vaccination campaigns had, until a decade ago, negligently added to the chronic infectious disease burden in the developing world: ‘In 2000, roughly 39 per cent of all healthcare-related injections administered globally were delivered with reused disposable or inadequately sterilised syringes, which resulted in an estimated 23 million people infected annually with hepatitis B, hepatitis C and human immunodeficiency virus (HIV).’
It took a decade to reduce these incidental infections to near zero by using disposable syringes.
The official line from the WHO is that people have become complacent: vaccines are such a successful intervention that the public have forgotten how serious and how deadly the diseases were. To keep people compliant with national immunisation schedules and hit WHO vaccination coverage targets, practitioners are told to tell parents ‘better safe than sorry’.
The example that is used to generate sufficient anxiety or fear is measles, a highly transmissible virus which remains a leading cause of death in parts of Africa and Asia. The CDC insists that getting the vaccine is safer than getting the disease yet provides no statistics to illustrate the relative risk.
According to the UK-based Vaccine Knowledge Project, ‘in high income regions of the world such as Western Europe, measles causes death in about 1 in 5,000 cases, but as many as 1 in 100 will die in the poorest regions of the world. Worldwide, measles is still a major cause of death, especially among children in resource-poor countries.’ One US-based website aimed at public health students and practitioners ignores the nuance, putting the risk of death from measles at 1 in 500 while selectively setting it against a one in a million chance of an allergic reaction to the MMR and ignoring the risk of all the other potential adverse reactions on the US government’s official table of measles vaccine injuries.
A measles mortality map produced by the US government in 1890, seventy years before the vaccine was introduced and before the improvements in sanitation, water quality and nutrition occurred, shows geographical differences in death rates that indicate other underlying factors contributing to measles deaths. The greatest of these risk factors was shown to be malnutrition, as the body’s demand for vitamin A increases in response to a measles infection. Likewise people whose diets are lacking in animal protein, vitamin A’s primary dietary source, are at the greatest risk of death or serious complications.
In countries where malnutrition is a problem, the antibody response to measles vaccines can be boosted by giving vitamin A supplements. Protein malnutrition is amongst the leading causes of death in many places where measles mortality remains high.
Featured Video

Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
or go to
Aletho News Archives – Video-Images
New Book
Trans agenda is ‘normalization of sadism’ – US author

RT | September 23, 2026
The US Democratic Party has embraced a transgender agenda that amounts to “the normalization of sadism,” author A.J. Rice has said, warning that radical trans policies would return if the party is allowed to regain power.
Speaking to RT’s America First host Scotty Nell Hughes about his new book, ‘The Curse of the Bearded Lady: How the Trans Mafia Whacked American Sanity’, Rice argued that activists have gained significant influence in schools, medicine, and corporate America while people who questioned the agenda have faced pressure to stay silent.
The author described the “trans mafia” as the sprawling network of people and institutions that have helped the movement gain influence. He singled out parts of academia, wealthy backers, and corporations, and stated that providers of transition-related treatment also have a financial incentive to keep young people in their care indefinitely.
Rice argued that the consequences of these policies ultimately fall on children who are being drawn toward gender-affirming medical treatments and on girls who are expected to share locker rooms or compete in sports with biological males.
He noted that while voters rejected the Democrats’ approach to gender in 2024, the party, which has been “captured by madness,” has since only doubled down and is seeking what is effectively “the normalization of sadism.” … Full report
Blog Roll
 Aletho News
- German chemicals giant reveals details of downsizing
- Refaat Al-Areer Was The Canary In The Coal Mine In Israel’s War On The Truth
- Israeli election committee bars candidate from Knesset race over Gaza war opposition
- French-Lebanese man files war crimes complaint over Israeli attacks
- Mahan Air Flight Lands in China Despite US Threat against Iranian Airlines
- US eyes $10bn fund to rebuild war-battered Gulf infrastructure
- Trump meets Rodríguez near Maduro’s prison as Venezuela’s oil flows to US
- Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
- Iran FM meets with US envoy on UN meeting’s sidelines at American side’s insistence: Report
- Qatar PM calls for Gulf security framework with Iran, says war must be ‘wake-up call’
- If Americans Knew
- Caught on Tape: AIPAC CEO Boasted of Controlling Trump’s National Security Officials
- Why Hamas Attacked Israel in October 2023 – Israeli professor Ilan Papé
- They see them, then kill them: Israeli quadcopters track, deliberately target civilians in Gaza
- Winter could turn Gaza’s treacherous, war-damaged buildings into deathtraps
- Majority of Democratic Voters Want to Prosecute Both Biden and Trump Administration Officials Over Gaza
- As Gaza languishes, world leaders gather at the UN – Daily Update
- Sanctions are collective punishment: immoral and self-defeating
- Phosphorus Munitions Fired by Israel Burn Groves, Orchards in Southern Lebanon
- Israel Carries Out New Ceasefire Violations Across Gaza
- AI – Emphasis on the ‘I’: Israel Is Funding AI Chatbot Propaganda
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

