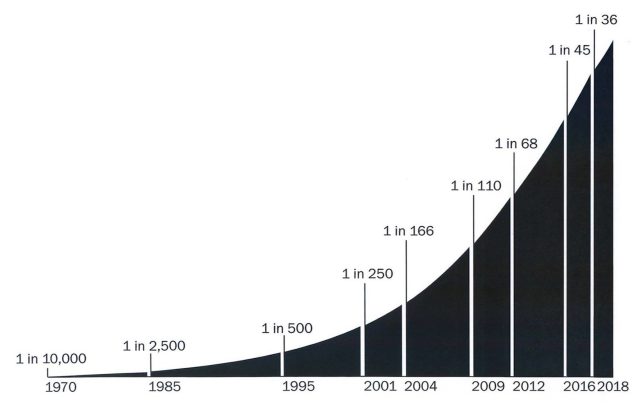
Autism is an epidemic and a pandemic by any reasonable definition of those words. J.B. Handley in, How to End the Autism Epidemic, produced the best chart showing the growth in autism prevalence in the U.S. over the last 50 years:
Increase in Autism Prevalence in the U.S. 1970 to 2017
Source: Handley (2018).
Darold Treffert at Winnebago State Hospital in Wisconsin was one of the first people to attempt to measure autism in the general population. His study, published in Archives of General Psychiatry in 1970, showed an autism rate of less than 1 in 10,000 children.
Then, sometime around 1987, the autism rate in the United States began to skyrocket. By 2017, the autism rate in the U.S. was 1 in 36 kids (Zablotsky et al., 2017). So the U.S. has experienced a 277-fold increase in autism prevalence in the last 50 years.
In some places and populations the rates are even higher: in Tom’s River, NJ, the state’s largest suburban school district, 1 in 14 eight-year-olds is on the autism spectrum; in Newark, NJ, 1 in 10 Black boys is on the spectrum (forthcoming).
The United States is in the midst of a genocide.
Genetic theories of autism never made much sense because “there is no such thing as a genetic epidemic” — the human genome just does not change that fast. An early twin study by Susan Folstein and Michael Rutter at the Institute of Psychiatry in London in 1977 suggested a strong genetic component to autism. More recent scholarship shows that this was likely overstated; the study only had 21 twin pairs and did not effectively control for environmental factors (twins usually grow up in the same family and are thus likely exposed to the same toxicants).
As the autism rate exploded throughout the U.S., the state of California hired eleven of the best geneticists in the country to examine the role of genes in autism. They concluded that genetics explains at most 38% of autism cases and in two places they explained that this was likely an overestimate (Hallmayer et al., 2011). Whatever is driving the surge in autism prevalence, it is not primarily genetics.
Well perhaps the increase in autism prevalence is just the result of better awareness (and what’s called “diagnostic expansion and substitution”)? That theory of the case does not check out either. The state of California funded two multimillion dollar studies to examine sharply rising prevalence in the state and whether it was the result of social factors. The first study was led by pediatric epidemiologist Robert S. Byrd at UC Davis who directed a team of investigators at UC Davis and UCLA. The investigators concluded that, “The observed increase in autism cases cannot be explained by a loosening in the criteria used to make the diagnosis” and “children served by the State’s Regional Centers are largely native born and there has been no major migration of children into California that would explain the increase in autism” (Byrd et al., 2002).
The state of California revisited this question in 2009 with a study led by the top environmental epidemiologist in the state — Irva Hertz-Picciotto at the UC Davis Mind Institute. This study concluded that changes in diagnostic criteria, the inclusion of milder cases, and earlier age at diagnosis explain about a quarter to a third of the total increase in autism (Hertz-Picciotto & Delwiche, 2009). In a subsequent interview with Scientific American, Hertz-Picciotto explained that these three factors “don’t get us close” to explaining the sharp rise in autism over that time period and she urged the scientific community to take a closer look at environmental factors (Cone, 2009).
There are now seven good ‘societal cost of autism’ studies (Jarbrink and Knapp, 2001; Ganz, 2007; Knapp et al., 2009; Buescher et al., 2014; Leigh & Du, 2015; Cakir et al., 2020; Blaxill, Rogers, & Nevison, 2021). They all show that the U.S. and much of the developed world is heading for economic and social collapse as a result of surging autism costs.
Autism increases poverty and inequality. Lifetime care costs for autism range from $1.4 to $2.4 million. Mothers of kids with autism earn 35% less than mothers of kids with other health limitations and 56% less than mothers of kids with no health limitations (Buescher et al., 2014).
In 2015, autism cost the U.S. an estimated $268 billion a year in direct costs & lost productivity; given current rates of increase, autism costs will reach $1 trillion a year (3.6% of GDP) by 2025 (Leigh & Du, 2015). As a point of comparison, the U.S. Defense Department budget is “just” 3.1% of GDP.
All of the more recent studies show autism costs surpassing $1 trillion a year in the near future. There is no plan by any level of government to raise revenue to meet these costs or prevent autism to mitigate these costs. Elected officials are frozen like a deer in the headlights.
In the last decade, three groups of top epidemiologists have published consensus statements declaring that neurodevelopmental disabilities including autism are caused by toxicants in the environment (The Collaborative on Health and the Environment, 2008; Mount Sinai Hospital, 2010; Project TENDR, 2016).
This is good news because it means that autism is likely preventable. The bad news is that the leading mainstream toxicologists do not want to lose their jobs so they generally avoid mentioning pharmaceutical products (even though these products appear to have an outsized impact). Parents groups have made up for the cowardice of mainstream toxicology by funding their own research.
We have fairly good data that five classes of toxicants increase autism risk:
- Mercury from coal fired power plants and diesel trucks;
- Plastics;
- Pesticides & herbicides;
- EMF/RFR; and
- Pharmaceuticals (Tylenol, SSRIs, & vaccines).
Taking each toxicant in turn…
For every 1,000 pounds of environmentally released mercury, there was a 61% increase in the rate of autism (Palmer, 2006). For every 10 miles closer a family lives to a coal fired power plant the autism risk increases by 1.4% (Palmer, 2009).
Plastics: Children with autism had significantly increased levels of 3 endocrine disruptors (two phthalates — MEHP & DEHP, & BPA) in blood samples as compared with healthy controls (Kardas, 2016).
Pesticides & herbicides: Increased use of RoundUp is strongly correlated (r = 0.989) with the rising prevalence of autism (Swanson, 2014). Organophosphates increase autism risk 60 – 100%; chlorpyrifos increase risk 78% – 163%; pyrethroids increase risk 78% (Shelton et al., 2014).
9 studies show an association between acetaminophen (Tylenol) use & adverse neurodevelopmental outcomes (Bauer et al., 2018). Avella-Garcia (2016) & Liew et al. (2016) found that males exposed to Tylenol in utero have significantly elevated risk of autism.
8 studies show a statistically significant association between selective serotonin reuptake inhibitor (SSRI) use in pregnant women and subsequent autism in their children (see meta-analysis in Kaplan et al., 2016). Doctors who prescribe SSRIs to pregnant women are committing malpractice.
Unfortunately, in the debate over toxicants that increase autism risk, all roads lead back to vaccines. At least 5 studies show a statistically significant association between vaccines & autism (Gallagher & Goodman, 2008 & 2010; Thomas & Margulis, 2016; Mawson et al., 2017a & 2017b).
Dr. Paul Thomas is the most successful doctor in the world at preventing autism. Data from his practice show:
If zero vaccines, autism rate = 1 in 715;
If alternative vaccine schedule, autism rate = 1 in 440;
If CDC vaccine schedule, autism rate = 1 in 36.
That study had large sample size (3,344 children), access to medical files, and good researchers working on it. But look closely. His alternative vaccine schedule reduces autism risk by more than 1200%. However even an alternative vaccine schedule increases autism risk by 160% versus no vaccines at all.
And all of those other toxicants that I described above that have been shown to increase autism risk? Those are the 1 in the 715 cases when the parent does not vaccinate at all. Autism appears mostly be a story of iatrogenic injury from vaccines.
This is not a surprise. Thousands of parents have been telling us for years that their children regressed into autism following vaccinations. Ethylmercury is a known neurotoxin and is still in 7 different vaccines (Thomas & Margulis, 2016, p. 14).
Aluminum is a known neurotoxin (Grandjean & Landrigan, 2014) and is used in a majority of vaccines. “The dose makes the poison” paradigm has collapsed in recent years and now we know that many toxicants have no safe dose.
In a sane world, all of this would be seen as good news. In a sane world the CDC, EPA, NIH and every major newspaper would rush out to Portland, Oregon to examine whether the data from Dr. Paul’s practice (and other studies) are correct. But we live in an insane world…
To date, the CDC, EPA, NIH, the federal government, and all state governments have ignored Dr. Paul’s work. None of the top 10 major newspapers in the U.S. have reviewed his book, The Vaccine Friendly, plan even though it is a bestseller on Amazon. In fact the Oregon Medical Board was so incensed by Dr. Paul’s success in preventing autism that they pulled his medical license briefly in 2021 (he has since been reinstated).
All of this information is public and available to anyone with an internet connection and a library card. By 1999 it was clear that vaccines that contained mercury were a problem (see Kirby, 2005). By the early 2000s it was clear that the problems with vaccines went well beyond mercury. Government had a choice to make: come clean or double down. And starting with senior scientist Thomas Verstraeten and then William Thompson the CDC decided to just flat out lie, manipulate findings, and destroy data.
The pharmaceutical industry also had a choice to make: improve their products or utilize their extensive capture of media and government to protect their existing toxic products. As everyone now knows, they chose to protect their existing toxic products. But the pharmaceutical industry has an enormous problem on their hands. We know some vaccines (hepatitis B, HPV, flu, DTaP…) cause catastrophic harms. And pockets of unvaccinated people across the country — who are healthier than vaccinated children — are the control group that provides evidence of Pharma’s crimes.
So starting in 2015, with the introduction of SB277 in California, the pharmaceutical industry began a systematic effort to eliminate the unvaccinated control group in all 50 states. They start by removing religious or personal belief exemptions to vaccination. In subsequent years they introduce bills to eliminate all medical exemptions to vaccination (SB 277 in CA in 2019) to get to 100% vaccination rates (even though all scientists will tell you that there are some children who should not be vaccinated because of underlying health conditions). In the Pharma legislative blitzkrieg no one is spared so that there will be no evidence left of the harms from these products. If 100% of children are treated, then there is no background rate of illness and all vaccine injuries just appear “normal”.
These mandatory vaccine bills are racketeering and crimes against humanity. With the introduction of coronavirus vaccines in late 2020, the situation has gotten much worse. Pharma now aims to vaccinate 100% of adults as well as 100% of kids and the results thus far have been catastrophic.
So here’s where things stand. The vaccine paradigm has collapsed (and no, mRNA, DNA, and adenovirus vector vaccines are not going to save it). Pharma has piles of cash and extensive capture of the media, academia, and government. So they have the ability to do just about whatever they want. Fearing prosecution and seeking immense profits, Pharma has abandoned any pretense of science, consent, or health and pushed all in to set up a totalitarian state that will serve their interests.
But Pharma has harmed so many people — first with the childhood schedule and now with coronavirus vaccines — that there are now millions of people who have seen vaccine injury first-hand and are now fighting back with everything they’ve got. Variously referred to as the medical freedom movement, the health choice movement, and/or the personal sovereignty movement, these brave citizens are taking on the most powerful industry in the world and fighting to save our country from Pharma fascism. The fighting is so fierce because the stakes are enormous. We are fighting to preserve human life as we know it from the most predatory and corrupt industry in the world.
To learn more about the toxicants associated with autism, read The Political Economy of Autism. To learn more about the battle to save our country and the world from Pharma totalitarianism, please subscribe to my Substack.
January 24, 2022
Posted by aletho |
Economics, Science and Pseudo-Science, Timeless or most popular, War Crimes | United States |
Leave a comment
This Week in the New Normal is our weekly chart of the progress of autocracy, authoritarianism and economic restructuring around the world.
1. “ANTI-VAXXERS ARE JOINING RACIST MILITIAS”
We’ve covered the increasing demonisation of the “anti-vaxxers” regularly for over a year now. Ever since Joe Biden announced his new “domestic terrorism bill”, it was obvious that “Anti-vaxxers” were going to be re-branded as some kind of violent threat to democracy (and they were).
Now it’s happening in the UK too, with a story being published warning that “anti-vaxxers” are becoming more militant and there are fears they will “evolve towards US-style militias”, according to the Guardian.
The article references nameless “counter terrorism” officials and anonymous “Whitehall sources”, who warn that…
Latest intelligence assessments describe the anti-vaxxer movement as ostensibly a conveyor belt, delivering fresh recruits to extremist groups, including racially and ethnically motivated violent extremist organisations.
So there you have it, being anti-Covid “vaccines” is a gateway protest. Before you know it you’ll be shaving your head and sieg hieling all over the place.
Absolutely pathetic propaganda, and hopefully not an early warning sign of legislation to come.
2. “WHAT IF DEMOCRACY AND CLIMATE MITIGATION ARE INCOMPATIBLE?”
OK, this is from two weeks ago, but it’s too important to skip. The title says it all, Foreign Policy is genuinely wondering if climate change is too much of a threat to let democracy stand in the way of fighting it.
It’s a long read, soaked to the bone in double-talk and built on some very shaky assumptions, but there’s some good material on there…
Democracy works by compromise, but climate change is precisely the type of problem that seems not to allow for it. As the clock on those climate timelines continues to tick, this structural mismatch is becoming increasingly exposed. And as a result, those concerned by climate change—some already with political power, others grasping for it—are now searching for, and finding, new ways of closing the gap between politics and science, by any means necessary.
It warns in the opening section, before concluding…
… democracy, in its current form, is not necessarily the path to a solution. It might, instead, be part of the problem.
It’s not hard to see where this is going. We warned, several times, that we would be moving on from Covid to climate, and that “climate lockdowns” were a very real possibility. This kind of talk is setting the groundwork for that movement.
3. ‘MORE PEOPLE IS THE LAST THING THIS PLANET NEEDS’
Another from the Guardian, this time interviewing all the hip and happening young men who are “getting vasectomies to save the world”
It’s about the climate. Again.
Apparently, there are already too many people (that’s not true, but whatever), and so young men are getting the snip. Bravely preventing placing the burden of climate catastrophe onto the next generation… by making sure there isn’t one.
One of the (anonymous, and therefore potentially made-up) interviewees went right out cut his balls off the week Donald Trump was elected. That’ll show ’em.
But wait… It’s not just about climate, it’s also about feminism.
Specifically, it’s about correcting the “gender imbalance” traditionally associated with birth control:
Vasectomies address the gender imbalance that still accompanies the choice and practice of birth control. They come with less risk than more invasive and less reliable methods of female contraception, including sterilisation and the coil.
They are genuinely arguing that making yourself sterile forever is less risky and less invasive than having a completely 100% reversible IUD inserted.
Then they start bemoaning that vasectomies can be “hard to come by, especially for younger, childless men“. NHS GPs are apparently reticent to simply sterilise perfectly healthy young men for no good reason:
While there are no laws on the age at which men in the UK can get a vasectomy, the NHS advises that they may be more likely to be accepted if they are older than 30 and have children. “Your GP can refuse to carry out the procedure … if they don’t believe it’s in your best interests,”
Not only that, but the NHS has cut funding to for vasectomies, and perhaps as a result of this, vasectomy numbers are down nationwide. The Guardian want us to think this is a bad thing, but considering the UK’s birth rate has been falling for decades, it might not be.
Nevertheless, there is hope that “world vasectomy day”, and its links to the fight against climate change, will help “burnish” the vasectomy’s progressive image.
The story ends with inspiring words from one of the voluntarily snipped…
“A lot of people are happy to point and say: ‘That’s wrong,’ or film it on their phone… I look at the world and say: ‘That’s not right; I’m going to try to do something about it.’”
A wonderful attitude. I hope he can pass that wisdom on to his children and his children’s children.
… oh, wait.
BONUS: (NEW) HELLHOLE OF THE WEEK
Not Australia this time, well done guys.
This time it’s New Zealand, where Prime Minister Jacinda Ardern has just put in place strict new rules to “combat” the spread of Omicron.
Starting today, the whole of the country will move into the red on New Zealand’s “traffic light” system, meaning mandatory masks, lockdowns for the unvaccinated and an increased self-isolation period of 24 days.
How many cases prompted this decision? Nine.
Nine Covid cases in Motueka are confirmed to have the Omicron variant, prompting the decision, Ardern said.
Australia has been pretty aggressive in the game of “anything you can do, I can do worse” they have going with both New Zealand and Canada, so expect a move from them sometime this week.
IT’S NOT ALL BAD…
Yesterday marked 2022’s first “Worldwide Freedom Rally”, with marches taking place all over the world, from London to Bern, to Vancouver to Warsaw to Liverpool to Genoa.
Bilbao, Graz, Brisbane. The list goes on and on and on.
Huge crowds turned out in Toronto… Stockholm… and Sydney.
In London NHS staff threw down their uniforms in front of Downing Street.
These are the people who they want to classify as domestic terrorists and militias.
Also, someone also sent us this sign, which is our new favourite:

All told a pretty hectic week for the new normal crowd, and we didn’t even mention that the world’s ten richest men have doubled their fortunes during the pandemic or the Fed’s report on a digital dollar.
January 23, 2022
Posted by aletho |
Civil Liberties, Environmentalism, Fake News, Mainstream Media, Warmongering, Malthusian Ideology, Phony Scarcity, Science and Pseudo-Science | The Guardian, UK |
Leave a comment
THE NHS vaccine mandate should be cancelled to prevent staff shortages, the Royal College of GPs has said, as thousands took to the streets across England to protest against the policy. The BBC reported:
‘NHS workers who oppose the Government’s mandatory vaccination policy have staged a protest in central London.
‘Demonstrations were also held in other cities across England including Manchester, Birmingham and Leeds.
‘Martin Marshall, Chairman of the Royal College of GPs, said compulsory vaccination for health professionals in England was “not the right way forward”.
He said the vast majority of staff were vaccinated but some 70,000 to 80,000 were not and they accounted for 10 per cent of staff at some hospital or GP surgeries.
If unvaccinated staff were taken out of frontline roles by April 1st there would be “massive consequences” for the NHS, he told BBC Radio 4’s Today programme.
‘He said a delay would allow time for booster jabs and a “sensible conversation” about whether vaccines should be mandatory at all.
‘Danny Mortimer, deputy chief executive of the NHS Confederation, said some frontline staff would have to leave their roles if they choose not to be vaccinated.
‘He said: “This will reduce frontline NHS staff numbers even further and lead to more gaps in capacity at a time of intense pressure and patient demand.”
‘In London, demonstrators marched from Regents Park to the BBC headquarters in Portland Place in a peaceful protest against mandating vaccines for health workers.’
Update:
The Telegraph and Daily Mail report that mandatory vaccines for NHS staff could now be pushed back by six months, following these nationwide protests over the requirement and amid demands by Tory backbenchers to drop the rule entirely.
January 23, 2022
Posted by aletho |
Civil Liberties, Science and Pseudo-Science, Solidarity and Activism | COVID-19 Vaccine, UK |
Leave a comment

The time has come to terminate the pandemic state of emergency. It is time to end the controls, the closures, the restrictions, the plexiglass, the stickers, the exhortations, the panic-mongering, the distancing announcements, the ubiquitous commercials, the forced masking, the vaccine mandates.
We don’t mean that the virus is gone – omicron is still spreading wildly, and the virus may circulate forever. But with a normal focus on protecting the vulnerable, we can treat the virus as a medical rather than a social matter and manage it in ordinary ways. A declared emergency needs continuous justification, and that is now lacking.
Over the last six weeks in the US, the delta variant strain – the most recent aggressive version of the infection – has according to CDC been declining in both the proportion of infections (60% on December 18 to 0.5% on January 15) and the number of daily infected people (95,000 to 2,100). During the next two weeks, delta will decline to the point that it essentially disappears like the strains before it.
Omicron is mild enough that most people, even many high-risk people, can adequately cope with the infection. Omicron infection is no more severe than seasonal flu, and generally less so. A large portion of the vulnerable population in the developed world is already vaccinated and protected against severe disease. We have learned much about the utility of inexpensive supplements like Vitamin D to reduce disease risk, and there is a host of good therapeutics available to prevent hospitalization and death should a vulnerable patient become infected. And for younger people, the risk of severe disease – already low before omicron – is minuscule.
Even in places with strict lockdown measures, there are hundreds of thousands of newly registered omicron cases daily and countless unregistered positives from home testing. Measures like mandatory masking and distancing have had negligible or at most small effects on transmission. Large-scale population quarantines only delay the inevitable. Vaccination and boosters have not halted omicron disease spread; heavily vaccinated nations like Israel and Australia have more daily cases per capita than any place on earth at the moment. This wave will run its course despite all of the emergency measures.
Until omicron, recovery from Covid provided substantial protection against subsequent infection. While the omicron variant can reinfect patients recovered from infection by previous strains, such reinfection tends to produce mild disease. Future variants, whether evolved from omicron or not, are unlikely to evade the immunity provided by omicron infection for a long while. With the universal spread of omicron worldwide, new strains will likely have more difficulty finding a hospitable environment because of the protection provided to the population by omicron’s widespread natural immunity.
It is true that – despite emergency measures — hospitalization counts and Covid-associated mortality have risen. Since mortality tends to trail symptomatic infection by about 3-4 weeks, we are still seeing the delta strain’s remaining effects and the waning of vaccine immunity against serious outcomes at 6-8 months after vaccination. These cases should decline over time as delta finally says goodbye. It is too late to alter their course with lockdowns (if that were ever possible).
Given that omicron, with its mild infection, is running its course to the end, there is no justification for maintaining emergency status. The lockdowns, personnel firings and shortages and school disruptions have done at least as much damage to the population’s health and welfare as the virus.
The state of emergency is not justified now, and it cannot be justified by fears of a hypothetical recurrence of some more severe infection at some unknown point in the future. If such a severe new variant were to occur – and it seems unlikely from omicron – then that would be the time to discuss a declaration of emergency.
Americans have sacrificed enough of their human rights and of their livelihoods for two years in the service of protecting the general public health. Omicron is circulating but it is not an emergency. The emergency is over. The current emergency declaration must be canceled. It is time.
Authors
Harvey Risch
Harvey Risch is Professor of Epidemiology in the Department of Epidemiology and Public Health at the Yale School of Public Health and Yale School of Medicine. Dr. Risch received his MD degree from the University of California San Diego and PhD from the University of Chicago. After serving as a postdoctoral fellow in epidemiology at the University of Washington, Dr. Risch was a faculty member in epidemiology and biostatistics at the University of Toronto before coming to Yale.
Jayanta Bhattacharya
Jay Bhattacharya, Senior Scholar of Brownstone Institute, is a Professor of Medicine at Stanford University. He is a research associate at the National Bureau of Economics Research, a senior fellow at the Stanford Institute for Economic Policy Research, and at the Stanford Freeman Spogli Institute.
Paul Elias Alexander
Dr Alexander holds a PhD. He has experience in epidemiology and in the teaching clinical epidemiology, evidence-based medicine, and research methodology. Dr Alexander is a former Assistant Professor at McMaster University in evidence-based medicine and research methods; former COVID Pandemic evidence-synthesis consultant advisor to WHO-PAHO Washington, DC (2020) and former senior advisor to COVID Pandemic policy in Health and Human Services (HHS) Washington, DC (A Secretary), US government; worked/appointed in 2008 at WHO as a regional specialist/epidemiologist in Europe’s Regional office Denmark, worked for the government of Canada as an epidemiologist for 12 years, appointed as the Canadian in-field epidemiologist (2002-2004) as part of an international CIDA funded, Health Canada executed project on TB/HIV co-infection and MDR-TB control (involving India, Pakistan, Nepal, Sri Lanka, Bangladesh, Bhutan, Maldives, Afghanistan, posted to Kathmandu); employed from 2017 to 2019 at Infectious Diseases Society of America (IDSA) Virginia USA as the evidence synthesis meta-analysis systematic review guideline development trainer; currently a COVID-19 consultant researcher in the US-C19 research group.
January 23, 2022
Posted by aletho |
Civil Liberties, Economics, Science and Pseudo-Science | Covid-19, COVID-19 Vaccine, Human rights |
Leave a comment
Defending Australian Open Champion Novak Djokovic was deported from Australia, the day before commencement of 2022 tournament play. He entered the country on a visa including a medical exemption based on recent Covid infection. Due to public outry over “special treatment,” his visa was revoked upon arrival in the country, only to be reinstated by a court. It was later revoked by an immigration minister, whose decision was upheld by another court, sending Djokovic packing — potentially for three years.
This draconian act puts Djokovic at a serious disadvantage in his Grand Slam rivalry with Rafael Nadal, who is competing in Australia this year after vocally supporting vaccines. Both champions, along with Roger Federer, currently hold 20 Grand Slam titles. Djokovic was favored to be the first to reach 21, but his decision to remain unvaccinated leaves Nadal alone with that opportunity for now. (Federer is out recovering from surgery.)
Djokovic was technically deported for not being vaccinated, but the decision lacks even a superficial “health and safety” justification. Djokovic already had Covid twice, once in early 2020 and again in December 2021. At the time of his deportation, he had been in Australia for ten days, and tested negative. He’s as healthy as a human being can be — you don’t earn “GOAT’ status in the difficult sport of tennis any other way.
Further proof that Djokovic poses no disease threat to anyone is the fact that this tournament was safely played in January 2021, before vaccines were available for any player or guest. Even if Djokovic had taken the vaccine, he’d be no “safer” in terms of his ability to transmit the virus, as the 100,000 daily cases in highly-vaccinated Australia attest.
Even the government that deported Djokovic didn’t try very hard to frame its decision as the elimination of a health threat. Rather, it stated that Novak could become an “icon of free choice” if allowed to stay. Ironically, he will undoubtedly become that now that he’s made the supreme sacrifice of forfeiting his chance to play in order to openly oppose mandatory vaccination.
It’s not a good look for the Covid Regime if an avowed “anti-vaxxer” dominates the sport. The world audience might start thinking about the relative health status of “unvaccinated” people, particularly since athletes have been experiencing heart trouble all over the world — several already at the Australian Open practice courts.
As it stands, Millions of Australians and others who have already taken the vaccine applaud the government’s decision. They can’t get the vaccine out of their bodies, so the next best thing is to make sure that everyone else has to put themselves into the same spot.
Nevermind the precedent it sets to allow a government to force people to choose between their health and their career. Such Sophie’s choices are normal these days.
The Regime would not have minded Djokovic playing in an unvaccinated state so long as he publicly expressed support for mandatory universal vaccination. He could have easily done this — a hero in Serbia, the wealthy star could have tapped any number of doctors to provide fake certification of vaccination. But that would have violated his principles.
In 2010, an “unwell” Djokovic was collapsing at tournaments, unable to complete strenuous matches. A doctor witnessing his condition on TV got in touch with the athlete, recommending that he eliminate gluten, dairy and processed sugar from his diet. Novak thought it sounded strange but agreed to try, and it’s hard to argue with his results. His 2011 season was one of the best in men’s tennis history. On his new fuel, he was unstoppable. He ended the season with an unbelievable 10–1 record against Nadal and Federer, and compiled a 41-match winning streak.
This experience changed not only the tennis player. It fundamentally changed the man, as Djokovic explains in his book “Serve to Win”:
When it’s not being cared for, your body will send you signals: fatigue, insomnia, cramps, flus, colds, allergies. When that happens, will you ask yourself the questions that matter? Will you answer honestly and with an open mind?
Open-minded people radiate positive energy. Closed-minded people radiate negativity. Eastern medicine teaches you to align mind, body, and soul. If you have positive feelings in your mind — love, joy, happiness — they affect your body… But a lot of people, especially closed-minded people, are led by fear. That and anger are the most negative energies we have. What are closed-minded people afraid of? It could be many things: Fear that they are wrong, fear that someone might have a better way, fear that something has to change. Fear limits your ability to live your life.
Some people at the top feed off of negativity. The way I see it, pharmaceutical and food companies want people to feel fear. They want people to be sick. How many TV ads are for fast foods and medicines? And what’s at the root of those messages? We’ll make you feel better with our products. But even deeper down: We’ll make you fear that you don’t have enough of the things we say you need. It’s crazy — even when you’re completely healthy, they say you need [products] to stay that way.
Here’s a pattern I’d rather embrace: good food, exercise, openness, positive energy, great results. I’ve been living that pattern for several years now. It works better than the alternative.
Djokovic rejects Big food, Big Ag, Big Chemical, and Big Pharma. He doesn’t need them. His practices allow him to be healthy without any of their products — in fact, he’s achieved an elite level of health by actively avoiding their products.
There is no greater threat to the bottom line of these companies than people like Novak Djokovic. He is not scared, he is not anxious, so he can’t be manipulated or sold an easy fix. He can see the path to health takes hard work, and he’s willing to put it in. When they tell him that he can’t be healthy without a vaccine, he laughs in their faces. They can send him packing, but they can never take away his integrity and self-worth.
Novak Djokovic doesn’t want to lie to the public, making it appear as if he agrees with The System’s “path to health.” If he did that, he would get to play his tournament, but he would have millions of lives on his conscience. He’d rather give up his career’s crowning achievement in order to stand in truth. To send people the message: you CAN reject this tyranny. You do NOT have to comply. You can SAY NO, and you will be okay.
It’s easier for him, yes, with his millions of dollars. Healthcare workers on a middle-class salary will have a harder go of it. Military members faced with dishonorable discharge absent vaccination have it worse. But Djokovic has made it easier, at least, for everyone to publicly reject vaccination. If Novak openly rejects this vaccine, they can too, without shame. His very public deportation will hopefully get many people thinking about his approach to health, which if widely understood and adopted, will finally burn the Covid Regime to the ground — once and for all.
Stacey Rudin is an attorney and writer in New Jersey, USA.
January 22, 2022
Posted by aletho |
Book Review, Science and Pseudo-Science, Timeless or most popular | Australian, Covid-19, COVID-19 Vaccine, Human rights |
Leave a comment
Near the top of the results of a Google search for “climate change” was a story in The Atlantic, titled “Lumber Prices Are off the Rails Again. Blame Climate.” This is false. The evidence shows supply chain disruptions are responsible for higher lumber prices.
The article claims that recent high lumber prices and volatility are due to climate change severely impacting the lumber supply coming from Canada.
“When it comes to lumber, climate change has manifested itself in extreme volatility, lack of supply, and a paradigm shift in how lumber markets have behaved for decades. Lumber prices are the second highest they’ve ever been, today, this moment—ever. And it was precipitated by mudslides, which was precipitated by burning, which was precipitated by beetle kill. There’s an infrastructure story in there. There’s a climate story.”
While it is true that lumber prices are currently abnormally high, as shown by this screenshot of a five-year trend from the NASDAQ report on lumber (LUM), climate change is not to blame.
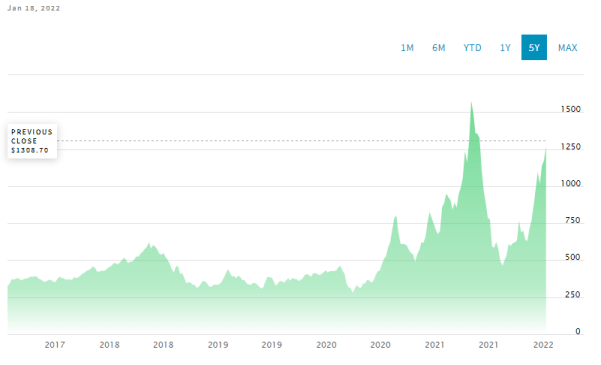
The recent spike in lumber prices is due to the post-pandemic supply chain and shipping bottlenecks. The already climbing prices were exacerbated by the destruction of infrastructure like roads and rail lines in British Columbia and the North-Western United States due to heavy rainfall that struck the region this winter. Parts of major highways like British Columbia Highway 1 were closed for repairs or debris clearing after the flooding and associated mud slides.
This atmospheric river event that carried rain to the West this winter is not an unprecedented climate event, but is instead a weather event. Climate Realism discusses the difference between weather events and climate change here and here, for example.
A recent Climate Realism article showed the claim that the recent atmospheric river event spanning the Pacific Northwest was caused by climate change was false. In the article, Cliff Mass, Ph.D., of the University of Washington, cited rainfall data proving the recent weather event was not sign of climate change. Mass analyzed the rainfall data from Bellingham and Clearbrook Washington, which goes back more than a hundred years, and found no evidence to support the claim that there has been an increase in heavy rainfall.
“There is NO HINT of a trend towards more extreme precipitation at either of these sites.” Dr. Mass said.
Atmospheric rivers have occurred in the region many times throughout history, and have been much more severe in the decades prior to the Industrial Revolution, as described by meteorologist Anthony Watts:
“The highest rainfall ever in California during recorded history likely occurred in January 1862, during the “Great Flood”. This was an atmospheric river event like we are experiencing now, but lasted several days, dumping 24.63 inches of rain in San Francisco, 66 inches in Los Angeles, leaving downtown Sacramento underwater.”
Strong weather events always have been, and always will be potential causes of infrastructure damage and supply-chain disruptions. The potential for localized natural disasters should be factored into infrastructure plans. Corporate media outlets like The Atlantic are wrong to blame climate change every time the skies open.
January 22, 2022
Posted by aletho |
Fake News, Mainstream Media, Warmongering, Science and Pseudo-Science | Canada, The Atlantic, United States |
Leave a comment
Researchers rally against solar geoengineering as a method of fighting ‘climate change’
An international group of scientists and experts wants all nations to sign a pact banning public funding and deployment of solar geoengineering, as well as outdoor experiments revolving around ways to ‘dim the sun.’
“Solar geoengineering at planetary scale is not governable in a globally inclusive and just manner within the current international political system,” the researchers wrote in an open letter published in the Wiley Interdisciplinary Reviews: Climate Change journal this week.
The concept of solar geoengineering aims to lower temperatures on Earth by using modern technology to reduce the incoming sunlight. The proposals include the spraying of aerosols into the stratosphere to stop the spread of solar energy. Some see this as a potential response to global warming.
But the authors of the letter warned about “uncertainties” surrounding the effects of such technologies on weather, agriculture, and the supply of food and water.
The letter argued that the world’s poorest nations will be left highly vulnerable unless powerful countries place the technology of such planetary scale under international control.
“The current world order seems unfit to reach such far-reaching agreements on fair and effective political control over solar geoengineering deployment.”
Proposals to study solar geoengineering were most recently floated by the media amid COP26, a major UN climate change summit in Scotland in November of last year.
In March, the US National Academies of Sciences, Engineering, and Medicine (NASEM) released a report recommending an investment of $100-$200 million in solar geoengineering research over five years as part of crafting “a robust portfolio of climate mitigation and adaptation policies.” NASEM argued that outdoor experiments that involve releasing substances into the atmosphere must be limited and subjected to strict regulation.
NASEM emphasized that solar geoengineering should not be a substitute for reducing greenhouse gas emissions.
January 22, 2022
Posted by aletho |
Malthusian Ideology, Phony Scarcity, Science and Pseudo-Science | COP26, United States |
Leave a comment

Two important papers have recently been published that question the extent to which humans are causing global warming by burning fossil fuel and releasing carbon dioxide into the atmosphere. The works will of course be ignored by mainstream media outlets, but they represent further evidence that a more nuanced view of human-caused or anthropogenic warming is gaining traction among scientists, tired of working within the political constraints of ‘settled’ science.
In a paper to be published next month in the journal Health Physics, three physics professors led by Kenneth Skrable from the University of Massachusetts examine the atmospheric trail left by CO2 isotopes and conclude that the amount of CO2 released by fossil fuel burning between 1750 and 2018 was “much too low to be the cause of global warming”.
Three carbon isotopes are found in the atmosphere, 12C, 13C and 14C. The latter is produced by cosmic rays and is in a constant state of activity but the other two are contained in the gas entering the atmosphere. The carbon in living matter has a slightly higher proportion of 12C. Although only about 4% of CO2 entering the atmosphere every year is produced by human activity, it is said very slightly to alter the balance of the other atmospheric isotopes. As a result it is often used as ‘proof’ that rising CO2 levels are primarily the result of fossil fuel burning.
But the Massachusetts team found that claims of the dominance of anthropogenic fossil fuel in the isotope record have involved the ‘misuse’ of 12C and 13C statistics to validate such suggestions. They conclude that the assumption that the increase in atmospheric CO2 is dominated by or equal to the anthropogenic component is “not settled science”.
Furthermore, they go on to state: “Unsupported conclusions of the dominance of the anthropogenic fossil component of CO2 and concerns of its effect on climate change and global warming have severe potential societal implications that press the need for very costly remedial actions that may be misdirected, presently unnecessary, and ineffective in curbing global warming.”
The “remedial” net zero political agenda is driven by the unproven hypothesis that humans are causing catastrophic heating and climate breakdown by using once-living plant and animal matter and releasing CO2 into the atmosphere. But there is little or no correlation between temperature and CO2 levels on a current, historical or geological timescale. Recent global warming, which replaced the global cooling scare of the 1970s, ran out of steam almost two decades ago. Green activists keep the doomsday tales going by highlighting natural bad weather, quoting massaged surface temperatures (don’t mention the far more accurate and cooler satellite data) and citing increasingly fanciful forecasts from the hottest ticket in town – the Always Goes Wrong Climate Model Show.
The unproven science hypothesis that humans cause most or all climate change is now under increasing attack on a number of fronts in scientific circles. Professor Happer of Princeton University has suggested that CO2 becomes “saturated” once it reaches a certain level, since it reflects heat back to Earth only within certain bands of the infrared spectrum. Under this hypothesis, which was given some credence by former Obama Administration Energy Under-secretary Steve Koonin in his book Unsettled, CO2 becomes “saturated” once it reaches a certain level, with most of the Sun’s heat that is going to be trapped having already been radiated back to Earth.
Ascribing all climate change to just one cause – the burning of fossil fuel – is given short shrift by recent work published by the German physicist Dr. Frank Stefani. In a paper published last year, the researcher at the Helmholtz Zentrum Dresden-Rossendorf dismisses the “illusionary claims of an overwhelming scientific consensus”. He cautions it is essential to support such settled conclusions, “before embarking on drastic, perilous and perhaps misguided plans for global action”.
Much of Dr. Stefani’s research looks at the effect of solar influences and geomagnetic forces on the planet. He suggests that the Sun accounts for between 30-70% of recent planetary warming. He further suggests that it is likely that solar activity will continue its two decade decline – at the end of the 20th century it was likely at its highest level for 8,000 years – and geomagnetic activity as measured by the aa-index will fall. In Dr. Stefani’s work, he uses the aa-index as a proxy for solar activity. So far as CO2 is concerned, he argues that even if there is an annual rise of 2.5 parts per million into the atmosphere, this will lead to only “a mild additional temperature rise” of less than 1°C by 2100. Other scenarios could result in flatter temperature curves “in which the heating effect of increasing CO2 is widely compensated by the cooling effect of a decreasing aa-index”.
There are countless factors that influence the climate in the short, medium and long term. Dr. Stefani concludes his work by noting that the huge “Milankovitch drivers” [changes in the Earth’s axis and orbit] will eventually “cool down mankind’s hubris of being able to significantly influence the terrestrial climate (in whatever direction)”.
January 22, 2022
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular |
Leave a comment
Shortly after World World Two, The Rockefeller Foundation set forth on a quest to bring about a transformation of world agriculture. They did this, in part, by “socially engineering” the scientific culture to not only accept but promote the use of GMO foods and dangerous biotechnologies. And now, they are at it again.
This new attempted policy change is outlined in a document titled “The True Cost of Food: Measuring What Matters to Transform the U.S. Food System”. In the report, mention is made of both the Covid-19 crisis and the climate crisis, claiming that now is the opportunity we’ve been waiting for to effect “transformative change” in food production.
The report is the result of a collaboration between the Rockefeller Foundation, various academics from leading universities, the World Wildlife Fund and the True Price Foundation. Leading the analysis were members of “True Price”, a Dutch company that describes itself as a “social enterprise with the mission to realize sustainable products that are affordable to all by enabling consumers to see and voluntarily pay the true price of products they buy”.
Leading the True Price team is Michel Scholte, an alumnus of the World Economic Forum Global Shapers Network, Adrian de Groot Ruiz, also a former WEF “Global Shaper” and Herman Mulder, former Director-General at ABN AMRO, one of the world’s leading agribusiness banks!
The intended goal of the report is to uncover the “true cost” of food in the US, which is claimed to be at least $3.2 trillion per year, three times more than than $1.1 trillion that Americans spend annually on food.
Included in this “cost analysis” are things like diet-related diseases, air pollution, greenhouse gas emissions and reduced biodiversity – all reasonable concerns. However, to understand the true agenda at play, one must read past the flowery language and popular buzzwords. As noted by author and researcher, William Engdahl:
“The message is that the current American food production is to blame and that radical and costly changes are urgently needed. The difficulty in reading the report is that the language is deliberately vague and deceptive. For example one of the most damaging components of American agriculture since the 1990s has been the wholesale introduction of GMO crops—especially soybeans, corn and cotton and the highly carcinogenic Monsanto-Bayer Roundup with glyphosate. The Rockefeller report omits their direct role in fostering that devastation by their creating and promoting Monsanto and GMO for decades, knowing it was destructive.”
As Engdahl makes clear, such a report detracts attention away from the fact that most of the “costs” associated with the food industry can be traced directly to the Rockefellers themselves and their role in creating the current industrialized food chain that has not only wrought destruction on global agriculture but contributed to the explosion of chronic disease. The adverse health effects caused by the introduction of GMO crops into modern farming and the subsequent lack of safety testing cannot be overstated. This will be detailed in part 2.
Following the classic problem-reaction-solution model, the report makes mention of the impact of Covid-19 on the current food supply chain, stating that the food system needs to become more resilient.
“Food insecurity has skyrocketed during the pandemic, with more than 54 million Americans (one in six Americans), of which over 18 million are children, facing uncertainty around their next meal.”
This is ironic considering that these issues are a direct result of political decisions to institute draconian lockdowns and other nonscientific policies, NOT a virus or a disease called “Covid-19”. And lest we forget the 2012 Rockefeller publication, “Scenarios for the Future of Technology and International Development” (p.18, “Lockstep”) describes many aspects of the Covid-19 drama in haunting detail.
According to the Rockefeller report, the way to construct a more resilient food supply chain is by increasing corporate involvement through a focus on industrialization and technological innovation. However, these are the very same measures that caused many of the issues being outlined.
For example, the report makes mention of “soil health” as a primary concern. However, it is precisely the widespread implementation of modern farming techniques (which involve the use of artificial fertilizers and the spraying of pesticides) – advocated for by the Rockefellers – that has depleted the soil of its nutrients in the first place.
Unsurprisingly the report makes no mention of agroecology or other regenerative methods of natural farming that seek to harness, maintain and enhance biological and ecological processes in agricultural production.
The FAO (Food and Agriculture Organization of the United Nations) describes agroecology as an approach to farming that:
“Favours the use of natural processes, limits the use of external inputs, promotes closed cycles with minimal negative externalities and stresses the importance of local knowledge and participatory processes that develop knowledge and practice through experience, as well as scientific methods, and the need to address social inequalities”.
According to Indian environmental activist, Dr. Vandana Shiva (emphasis added):
“Agroecology, which encompasses common ecological principles – organic farming, permaculture, biodynamic farming, natural farming regenerative agriculture, among many others – has been recognized as the most effective sustainable and equitable method of farming which also addresses the challenges of feeding the world in an era of climate crises.”
Back to the Rockefeller report… Which claims that one of the fundamental shifts required across the current food system is an acceleration in the development of new tools to reduce greenhouse gas emissions. As stated in the report, “this includes new financial markets related to natural capital including carbon, water, soil nitrogen and biodiversity”.
It is not stated how these new financial markets will be constructed, but this seems like a reference to the recent Rockefeller/Wallstreet-backed creation of a new asset class called a Natural Asset Company. NACs are specialized corporations “that hold the rights to the ecosystem services produced on a given chunk of land, services like carbon sequestration or clean water”.
Journalist and researcher Whitney Webb explains the true motives behind the creation of NACs in no uncertain terms:
“The ultimate goal of NACs is not sustainability or conservation – it is the financialization of nature, i.e. turning nature into a commodity that can be used to keep the current, corrupt Wall Street economy booming under the guise of protecting the environment and preventing its further degradation.”
Another method of reducing GHG emissions, according to the Rockefeller/Gates/WEF initiative, is by introducing plant-based, meat-free alternatives. Once again, the threat of “Covid-19” is subtly exploited to highlight the importance of this transition.
“[meat] processing plants that continued to operate became transmission sites for the disease. Reports show approximately 300,000 excess cases of Covid-19 due to proximity to a livestock plant and approximately 5,000 deaths happened among workers in meat processing facilities.”
Here it’s worth noting that the President of the Rockefeller Foundation, Rajiv Shah, is the former Director of Agricultural Development at the Gates Foundation and that Bill Gates is personally invested in Impossible Foods, Memphis Meats and Beyond Meats – companies that produce synthetic meat and dairy products from plants, using laboratory techniques including gene editing.
In Gates’ 2021 book “How to Avoid a Climate Disaster” he advocates for the replacement of beef with fake meat. In a recent interview with MIT technology review, he said that people’s behaviors should change for them to learn to like fake meat, and if that doesn’t work, appropriate regulations should be put in place.
This agricultural transformation advocated for by Gates, the Rockefellers and the WEF, one that seeks to increase industrialization, patentable crops and the consumption of lab-grown “meat”, stems in part, from the mechanical mind and its reductionist theory of food.
The “reductionist” view of food tells us that food is digested in the body where it’s broken down into its constituent parts, sent to different areas of the body and, ultimately, used as “fuel” for the body to burn. Much emphasis is put on the caloric content of food, rather than its nutritional value or its other medicinal properties/benefits. This view stems from our scientific establishment which views the body as nothing more than a complex “machine”.
Furthermore, as is evident, the transhumanists seek to alter our perception of food from something that is grown naturally in the earth beneath our feet to something that is synthetically engineered in laboratories. Companies like Beyond Meat and Impossible Burger have raised millions of dollars, promoting their concoctions on the basis of claims that “Lab-grown meat will replicate the taste and consistency of traditional meat”.
If taste alone doesn’t hook people in, they play the “climate change” card, touting the consumption of fake meat as “necessary” for us to avoid an environmental disaster. Ironically, research indicates that the production of lab-cultured meat could require more energy than the preparation of regular meat. Adding to this irony is the fact that Gates, who lives in a 66,000-square-foot mansion and travels in a private jet, is himself a carbon super-emitter.
In 2019, the USDA and FDA announced a regulatory framework for lab-grown meat, a move that elated the fake-meat industry. Why would synthetic meat producers be happy about this? Kelsey Piper, in an article for Vox, gives us the answer:
“… consumer confidence is absolutely critical. If people don’t believe that cell-based meat products are safe, regulated, and healthy, then they’ll stick with slaughtered meat”.
In other words, no matter how fraudulent, an “FDA Approved” badge constitutes an irreplaceable marketing tool. For example, data indicate that Covid-19 vaccination rates increased after the vaccines were given full FDA approval.
With a regulatory framework in place, startups are working to build out the technological infrastructure that will allow for the production of lab-grown meat at scale. The next step in this “transhumanist tiptoe” will be “food” created using nanotechnology. As stated by author and researcher Aaron Franz,
“Nanotech could take the atoms from an otherwise useless source and turn it into something useful. You could turn dirt directly into food with nanotech.”[1]
Related to this is the developing science of “molecular manufacturing”, which may be defined as “the hypothetical future use of reprogrammable nanoscale ‘assemblers’ to build products atom by atom”.
Franz explains the transhumanist mindset behind the development of such a technology:
“Molecular manufacturing is hailed by transhumanists as a way to conquer scarcity. In a scarcity-free world people would be able to concentrate on things other than survival.”[1]
However, a quick search through the scientific literature indicates that the use of molecular manufacturing in food production goes far beyond alleviating “scarcity” and may have more to do with altering the structure and function of the body itself. For example, a 2015 review paper states that (emphasis added):
“The potential benefits of utilizing nanomaterials in food are improved bioavailability, antimicrobial effects, enhanced sensory acceptance and targeted delivery of bioactive compounds.”
Another review published in the American Journal of Food Technology makes mention of “nanotechnology-based biosensors” for the detection of food-borne pathogens. Shades of the DARPA/NIH brainchild, Profusa, and their research into developing an injectable biosensor that can “detect future pandemics”.
Once again, “public acceptance” is cited as a major hurdle to the introduction of food created using nanotechnology, and therefore one can reasonably predict to see further regulatory frameworks created specifically for such products.
FOOD AS INFORMATION
Despite the reductionist, body-as-a-machine doctrine expounded by the transhumanists, new research argues that food is a form of information and that this information interacts directly with our genetic infrastructure, effecting epigenetic changes by turning on and off various genes – “You are what you eat”, as the old adage goes.
“Epigenetics” refers to the science of how cells control gene activity without changing the DNA sequence. Our food and our environment are two important factors that drive epigenetic changes. One of the primary epigenetic mechanisms is DNA methylation – a process that regulates gene expression by altering protein activity and/or inhibiting the binding of transcription factors.
Abnormal DNA methylation is observed in cancer patients and as researchers note, “Dietary nutrient intake and bioactive food components are essential environmental factors that may influence DNA methylation”. The discovery of epigenetics revealed the profound importance of food intake on disease risk and phenotypic expression.
But DNA methylation is not the only mechanism by which food interacts with our DNA. All food, whether of plant or animal origin, contains non-coding RNA that can survive digestion to affect profound changes in the expression of our genes. These RNAs are shuttled in virus-sized (!) “microvesicles” (also called “exosomes”). A groundbreaking study published in 2011 found that exogenous plant micro RNAs could regulate gene expression changes in humans.
These findings may extend the role of exosomes to that of interspecies communication, thereby highlighting the significance of food as a source of information transfer, affecting the body on a nutritional, energetic and genetic level.
Another source of information comes from the microbes that accompany most plant foods. The “microbiome” as it’s termed refers to the collective microbial (fungal, bacterial, etc) content of our body, much of which is found in the gut. Recent discoveries have illuminated the importance of the microbiome and its role in nearly every chronic disease from depression to cardiovascular disease.
Beneficial microbes help to regulate bowel pH, produce vitamins, maintain mucosal integrity, regulate immune function, reduce inflammation, and ferment complex carbohydrates that are normally inaccessible to human digestion.
Microbes represent a profound “store” of information, relayed to us through the food we eat. Fermented foods (such as kimchi) are thus irreplaceable sources of beneficial bacteria that help to promote optimal bowel conditions, reduce disease risk and restore balance to a microbiome decimated by overly processed foods, glyphosates and other toxins common to modern-day life.
Understanding food as more than merely a source of energy allows us to comprehend the magnitude of the agenda that seeks to promote the consumption of genetically modified, synthetically produced, test-tube mulch cooked-up in corporate laboratories. With this firmly in mind, we are now prepared to dive into the history of GMOs and modern “agribusiness”, with an emphasis on highlighting the role of the Rockefellers and other wealthy elite actors.
To be continued…
REFERENCES
[1] Franz, A. Revolve: Man’s Scientific Rise to Godhood. Franz Productions. 2011.
Ryan Matters is a writer and free thinker from South Africa. After a life-changing period of illness, he began to question mainstream medicine, science and the true meaning of what it is to be alive. Some of his writings can be found at newbraveworld.org, you can also follow him on Gab.
January 22, 2022
Posted by aletho |
Environmentalism, Malthusian Ideology, Phony Scarcity, Progressive Hypocrite, Science and Pseudo-Science, Timeless or most popular | Gates Foundation, Rockefeller Foundation, WEF |
Leave a comment
I’ve been getting frequent requests for at least the last six months to write about the Novavax covid vaccine. I’ve been resisting, mainly because it’s seemed uncertain whether it would ever actually be approved in the western world. Now that it’s been approved for use in the EU, however, that has changed, and I figure that I can put it off no longer.
I guess the reason so many people are excited about the Novavax vaccine is that it uses a traditional technology that’s been used many times previously, rather than the new-fangled technologies used in the mRNA and adenovector vaccines that have up to now been all that’s available in the US and EU. To many people, that apparently makes it feel inherently safer.
The Novavax vaccine consists of two parts: the Sars-Cov-2 spike protein and an adjuvant (a substance that causes the immune system to realize that a dangerous foreign entity is present, and which thus activates an immune response to the spike protein). So, rather than injecting genetic blueprints in to the body that get cells to make the viral spike protein themselves (as is the case with the four previously approved vaccines), the spike protein is injected directly.
The first country to approve the Novavax vaccine was Indonesia, which approved it for use in November. That means that there is no even slightly long term real world follow-up data available yet. All we have is the preliminary results from the randomized trials. That means we still have no idea about rare side-effects, and won’t for months. Several million people had already received the AstraZeneca vaccine before authorities realized it could cause serious blood clotting disorders, and millions had also received the Moderna and Pfizer vaccines before it became clear that they can cause myocarditis. With that cautionary point having been made, let’s take a look at what the preliminary results from the randomized trials show.
The first trial results concerning the Novavax vaccine appeared in the New England Journal of Medicine in May. 4,387 people in South Africa were randomized to receive either the vaccine or a saline placebo. The trial was conducted during the final months of 2020, when the beta variant was dominant in South Africa. Like the earlier covid vaccine trials, the objective of the study was to understand the ability of the vaccine to prevent symptomatic disease, which was defined as symptoms suggestive of covid-19 plus a positive covid test.
The average age of the participants was 32 years and chronic conditions were rare, so this was a group at low risk of severe disease. When this fact is combined with the relatively small total number of participants (for a vaccine trial), there was no possibility that the study was going to say anything useful about the ability of the vaccine to prevent severe disease. So this was really a trial looking at the ability of the Novavax vaccine to prevent the common cold in healthy young people.
Let’s look at the results.
As with the earlier published vaccine trials, data on efficacy was only provided two months out from receipt of the vaccine. At the two month mark, 15 people in the vaccine group had developed symptomatic covid-19, as compared with 29 people in the placebo group. This gives a relative risk reduction of 49% against the beta variant at two months post vaccination, which is disappointing. It’s below the 50% risk reduction that regulators have set as the minimum level required for them to approve a vaccine.
It’s even more disappointing when you consider that efficacy against symptomatic infection likely peaks at two months out from vaccination, and then drops rapidly – that is the pattern that’s been seen with all the other approved covid vaccines, and it’s very likely that the same is true for this vaccine.
Furthermore, the beta variant is long gone. The other approved vaccines appear to have little to no ability to prevent infection from the currently dominant omicron variant (although they do still seem to reduce the risk of severe disease to a large extent). Here in Sweden you are currently just as likely to get covid regardless of whether you’ve been vaccinated or not, but you’re still far less likely to end up in an ICU due to severe covid if you’ve been vaccinated. There’s no reason to assume that this vaccine is any different.
Let’s move on and look at safety. Safety data was only provided for a sub-set of patients, and for the first 35 days out from receipt of the first vaccine dose. What little there was though, was somewhat discouraging, with twice as many adverse events requiring medical attention in the group receiving the vaccine as in the group receiving the placebo (13 vs 6), and twice as many serious adverse events in the group receiving the vaccine (2 vs 1). To be fair though, the small absolute numbers make it impossible to draw any conclusions about safety based on this limited data. So we’ll wait to pass judgement.
Let’s move on to the second trial, which was published in the New England Journal of Medicine in September. This was a much larger trial than the first, with 15,187 people in the UK who were randomized to either the Novavax vaccine or a saline placebo. Like the earlier study, it was looking at the ability of the vaccine to prevent symptomatic disease. The study ran from late 2020 to early 2021, during a time when the alpha variant was dominant, so the results of the study apply primarily to that variant. 45% of the participants had at least one risk factor that would predispose them to severe disease, and the average age was 56 years.
Ok, so what were the results?
Among participants who received two doses of the vaccine, there were 96 covid infections in the placebo group, but only 10 in the vaccine group during the three month period after receipt of the second dose. This gives an efficacy during the first few months of 90%, similar to what was found in the Moderna and Pfizer vaccine trials. One person ended up being hospitalized for covid-19 in the placebo group, while no-one was hospitalized in the vaccine group – so unfortunately there again weren’t enough hospitalizations to be able to say anything about the ability of the vaccine to prevent severe disease (although it’s pretty clear from this study that even for a relatively high risk group, the overall risk of hospitalization due to covid is low – of 96 people in the placebo group who got covid, only one required hospitalization).
Let’s turn to safety. Safety data is only provided for the period from receipt of the first dose to 28 days out from receipt of the second dose, so we don’t learn anything about the longer term, but at least for that shorter period, there was no signal of serious harm. There were 44 serious adverse events in the vaccine group, and 44 serious adverse events in the placebo group. One person in the vaccine group developed myocarditis three days after receipt of the second dose, which suggests that the Novavax vaccine might cause myocarditis, just like the Pfizer and Moderna vaccines do.
Let’s turn to the final trial, which was published in the New England Journal of Medicine in December. It was carried out in the United States and Mexico during the first half of 2021. Just as with the previous trial, the results apply primarily to the alpha variant. 29,949 participants were randomized to either the Novavax vaccine or a saline placebo. Like the other two trials, the purpose was to see if the vaccine prevented symptomatic disease, again defined as symptoms suggestive of covid-19 plus a positive PCR test. The median age of the participants was 47 years, and 52% had an underlying condition that would predispose them to more severe disease if infected with covid-19.
So, what were the results?
At 70 days out from receipt of the second dose, 0.8% of participants in the placebo group had developed covid-19, compared with only 0.1% in the vaccine group. This gives a relative risk reduction of 90%, a result that is identical to that seen in the previous trial. Unfortunately, no information is provided on hospitalizations, which I assume means that not one of the 29,949 people included in the study was hospitalized for covid-19, so, just as with the earlier trials, it’s impossible to tell if the vaccine results in any meaningful reduction in hospitalizations.
At 28 days post receipt of the seond dose, 0.9% of participants in the vaccine group had suffered a serious adverse event, compared with 1.0% of participants in the placebo group. That is encouraging.
Ok, let’s wrap up. what can we conclude about the Novavax vaccine after looking at the results of these three trials?
First, we can conclude that it effectively protected people from symptomatic covid due to the alpha variant at two-three months post vaccination (which of course tells us nothing about how effective the vaccine is after six months or a year). That information is now mostly of historical interest, since alpha is long gone and we’re living in the era of omicron. If the Novavax vaccine is similar to the four previously approved vaccines, then it’s likely useless at preventing infection due to omicron.
Second, it’s impossible to conclude from these trials whether the Novavax vaccine results in any reduction in risk of hospitalization due to covid, for the simple reason that not enough people ended up being hospitalized. Having said that, my guess would be that it probably does protect against hospitalization and need for ICU treatment, just as the other approved vaccines do. At its heart, it’s doing the same thing as they are – generating an immune response to the spike protein found on the original Wuhan covid variant, and the overall trial results are very similar to the trial results for the Moderna and Pfizer vaccines.
The overall safety data suggests that the vaccine is pretty safe, with serious adverse events being balanced between the vaccine group and the placebo group. Rare side-effects are however not detectable in randomized trials with a few tens of thousands of participants. For that longer term follow-up with much larger numbers of people is necessary. So it’s currently impossible to know whether the Novavax vaccine can cause myocarditis, like the mRNA vaccines, or blood clotting disorders, like the adenovector virus vaccines, or some other type of rare adverse event entirely. It’s therefore impossible to say at the present point in time whether it will turn out to be more safe, or less safe, or equivalent to the already approved vaccines.
January 22, 2022
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | Covid-19, COVID-19 Vaccine |
Leave a comment
Letter to Mr William Wragg, MP
18th January 2022
Mr William Wragg, MP
Chair of the Public Administration & Constitutional Affairs Committee (PACAC)
Dear Mr Wragg,
Re: Ethical concerns arising from the Government’s use of covert psychological ‘nudges’ in their COVID-19 communications strategy
We are writing to you as a group of psychological specialists and health professionals to highlight our major ethical concerns about the deployment of covert behavioural-science techniques (commonly referred to as ‘nudges’) in the Government’s COVID-19 communications strategy. Our view is that the use of these behavioural strategies – which often operate below people’s conscious awareness and frequently rely on inflating emotional distress to change behaviour – raises profound moral questions. In light of these pressing concerns we respectfully request that, in your role as chair of the Public Administration & Constitutional Affairs Committee (PACAC), you instigate a comprehensive inquiry into the acceptability of using these strategies on the British people as a means of promoting compliance with public health directives.
Background
The appetite for using covert psychological strategies as a means of changing people’s behaviour was boosted by the emergence of the ‘Behavioural Insights Team’ (BIT) in 2010 as ‘the world’s first government institution dedicated to the application of behavioural science to policy’ (1). The membership of BIT rapidly expanded (2) from a seven-person unit embedded in the UK Government to a ‘social purpose company’ operating in many countries across the world. A comprehensive account of the psychological techniques recommended by the BIT is provided in the Institute of Government document, MINDSPACE: Influencing behaviour through public policy (3), where the authors claim that their strategies can achieve ‘low cost, low pain ways of nudging citizens … into new ways of acting by going with the grain of how we think and act’.
Since its inception in 2010, the BIT has been led by Professor David Halpern who is currently the team’s chief executive. Professor Halpern and two other members of the BIT also currently sit on the Scientific Pandemic Insights Group on Behaviours (SPI-B) (4), a subgroup of SAGE that advises the Government on its COVID-19 communications strategy. Most of the other members of the SPI-B are prominent British psychologists who have expertise in the deployment of behavioural-science ‘nudge’ techniques.
It is important to emphasise that the use of behavioural science in this way represents a radical departure from the traditional methods – legislation, information provision, rational argument – used by governments to influence the behaviour of their citizens. By contrast, many of the ‘nudges’ delivered by the BIT are – to various degrees – acting upon us automatically, below the level of conscious thought and reason.
The ‘nudges’ of concern
The BIT and the SPI-B have encouraged the deployment of many techniques from behavioural science within the Government’s COVID-19 communications. However, there are three ‘nudges’ which have evoked most of our alarm: the exploitation of fear (inflating perceived threat levels), shame (conflating compliance with virtue) and peer pressure (portraying non-compliers as a deviant minority) – or “affect”, “ego” and “norms”, to use the language of the MINDSPACE document.
AFFECT/FEAR
Aware that a frightened population is a compliant one, a strategic decision was made to inflate the fear levels of all the British people. The minutes of the SPI-B meeting (5) dated the 22nd March 2020 stated, ‘The perceived level of personal threat needs to be increased among those who are complacent’ by ‘using hard-hitting emotional messaging’. Subsequently, in tandem with a subservient mainstream media, the collective efforts of the BIT and the SPI-B have inflicted a prolonged and concerted scare campaign upon the British public. The methods used have included:
- Daily statistics displayed without context: the macabre mono focus on showing the number of COVID-19 deaths without mention of mortality from other causes or the fact that, under normal circumstances, around 1600 people die each day in the UK.
- Recurrent footage of dying patients: images of the acutely unwell in Intensive Care Units.
- Scary slogans: for example, ‘IF YOU GO OUT YOU CAN SPREAD IT, PEOPLE WILL DIE’, typically accompanied by frightening images of emergency personnel in masks and visors.
EGO/SHAME
We all strive to maintain a positive view of ourselves. Utilising this human tendency, behavioural scientists have recommended messaging that equates virtue with adherence to the Covid-19 restrictions and subsequent vaccination campaign. Consequently, following the rules preserves the integrity of our egos while any deviation evokes shame. Examples of these nudges in action include:
- Slogans that shame the non-compliant: for example, ‘STAY HOME, PROTECT THE NHS, SAVE LIVES’.
- TV advertisements: actors tell us, ‘I wear a face covering to protect my mates’ and ‘I make space to protect you’.
- Clap for Carers: the pre-orchestrated weekly ritual, purportedly to show appreciation for NHS staff.
- Ministers telling students not to ‘kill your gran’.
- Shame–evoking adverts: close-up images of acutely unwell hospital patients with the voice-over, ‘Can you look them in the eyes and tell them you’re doing all you can to stop the spread of coronavirus?’
NORMS/PEER PRESSURE
Awareness of the prevalent views and behaviour of our fellow citizens can pressurise us to conform and knowledge of being in a deviant minority is a source of discomfort. The Government has repeatedly encouraged peer pressure throughout the COVID-19 crisis to gain the public’s compliance with their escalating restrictions, an approach that – at higher levels of intensity – can morph into scapegoating. The most straightforward example is how, during interviews with the media, ministers have often resorted to telling us that the vast majority of people are ‘obeying the rules’ or that almost all of us are conforming. However, in order to enhance and sustain normative pressure, people need to be able to instantly distinguish the rule breakers from the rule followers; the visibility of face coverings provides this immediate differentiation. The switch to the mandating of masks in community settings in summer 2020, without the emergence of new and robust evidence that they reduce viral transmission, strongly suggests that the mask requirement was introduced primarily as a compliance device to harness normative pressure.
Ethical questions
Compared to a government’s typical tools of persuasion, the covert psychological strategies (outlined above) differ in both their nature and subconscious mode of action. Consequently, we believe there are three main areas of ethical concern associated with their use: problems with the methods per se; problems with the lack of consent; and problems with the goals to which they are applied.
First, it is highly questionable whether a civilised society should knowingly increase the emotional discomfort of its citizens as a means of gaining their compliance. Government scientists deploying fear, shame and scapegoating to change minds is an ethically dubious practice that in some respects resembles the tactics used by totalitarian regimes such as China, where the state inflicts pain on a subset of its population in an attempt to eliminate beliefs and behaviour they perceive to be deviant.
Another ethical issue associated with these covert psychological techniques relates to their unintended consequences. Shaming and scapegoating have emboldened some people to harass those unable or unwilling to wear a face covering. More disturbingly, the inflated fear levels will have significantly contributed to the many thousands of excess non-COVID deaths (6) that have occurred in people’s homes, the strategically-increased anxieties discouraging many from seeking help for other illnesses. Furthermore, a lot of older people, rendered housebound by fear, may have died prematurely from loneliness (7). Those already suffering with obsessive-compulsive problems about contamination, and patients with severe health anxieties, will have had their anguish exacerbated by the campaign of fear. Even now, when all the vulnerable groups have been offered vaccination, many of our citizens remain tormented by ‘COVID-19 Anxiety Syndrome’ (8), characterised by a disabling combination of fear and maladaptive coping strategies.
Second, a recipient’s consent prior to the delivery of a medical or psychological intervention is a fundamental requirement of a civilised society. Professor David Halpern (the BIT Chief Executive and prominent member of SPI-B) explicitly recognised the significant ethical dilemmas arising from the use of influencing strategies that impact subconsciously on the country’s citizens. The MINDSPACE document (9) – of which Professor Halpern is a co-author – states that, ‘Policymakers wishing to use these tools … need the approval of the public to do so’ (p74). More recently, in Professor Halpern’s book, Inside the Nudge Unit, he is even more emphatic about the importance of consent: ‘If Governments … wish to use behavioural insights, they must seek and maintain the permission of the public. Ultimately, you – the public, the citizen – need to decide what the objectives, and limits, of nudging and empirical testing should be’ (p375).
As far as we are aware, no attempt has yet been made to obtain the public’s permission to use covert psychological strategies.
Third, the perceived legitimacy of using subconscious ‘nudges’ to influence people may also depend upon the behavioural goals that are being pursued. It may be that a higher proportion of the general public would be comfortable with the government resorting to subconscious nudges to reduce violent crime as compared to the purpose of imposing unprecedented and non-evidenced public-health restrictions. Would British citizens have agreed to the furtive deployment of fear, shame and peer pressure as a way of levering compliance with lockdowns, mask mandates and vaccination? Maybe they should be asked before the Government considers any future imposition of these techniques.
The position of the British Psychological Society
The British Psychological Society (BPS) is the leading professional body for psychologists in the UK. According to their website (10), a central role of the BPS is, ‘To promote excellence and ethical practice in the science, education and application of the discipline’. [Our emphasis]. Mindful of their important position as the guardian of ethical psychological practice, on the 6th January 2021 46 psychologists and therapists (including many of the signatories of the present letter) wrote to the BPS (11) raising the ethical questions outlined above.
A month later, on the 5th February 2021, a reply (12) was received from Dr Debra Malpass (Director of Knowledge and Insight at the BPS) which failed to directly address our ethical concerns and was, in our view, evasive and disingenuous. Dr Malpass’s response included questioning whether the strategies deployed by Government psychologists were actually covert, stating that the role of specific psychologists had not been evidenced, and expressing how ‘incredibly proud’ the BPS was about the ‘fantastic work done by psychologists throughout the pandemic’.
Dissatisfied with this initial reaction, we contacted the BPS again to question whether our expressed concerns had actually been considered by their ethics committee. We received a brief reply from Dr Malpass on the 16th February 2021 informing us that our initial letter would be considered at their next BPS Ethics Committee on the 1st March; we understood this to be an admission that the covert psychological strategies recommended by psychologists had yet to be scrutinised in regards to their ethical acceptability.
By 12th March, and not having received any further communication from the BPS, we prompted them again. On the 23rd March a message was received from Dr Roger Paxton (Chair of the BPS Ethics Committee) apologising that ‘owing to a very full agenda and an oversight’ no discussion about our concerns had taken place but that they would be included on the agenda of their June meeting.
On the 30th June, and not having received any further communication from the BPS, we prompted them again. On the 1st July we received a response (13) from Dr Paxton, comprising three paragraphs, informing us that the issues we raised had been considered and that their ethics committee had endorsed all previous BPS responses. In this communication, Dr Paxton acknowledged that he had received a large number of recent emails raising the same issues, but rejected our ethical concerns arguing that the strategies referred to were ‘indirect’ rather than covert, the application of psychology in this instance fell outside the realm of individual health decisions (so informed consent was not an issue), levels of fear within the general population were proportionate to the objective risk posed by the virus, and the psychologists’ role in the pandemic response demonstrated ‘social responsibility and the competent and responsible employment of psychological expertise’.
We believe the BPS responses to our ethical concerns about the deployment of covert psychological strategies throughout the COVID-19 pandemic have been defensive and disingenuous. Also we believe the BPS is impeded by a major conflict of interest on this issue in that several members of the SPI-B are also influential figures within the BPS. As such, the impartiality of the BPS in addressing the ethical issues we raised is highly questionable.
Finally, it is worth noting that serious concerns about the Government’s use of behavioural science have previously been raised in relation to other spheres of government activity. An All Parliamentary Group Report (APGR) (14) analysing the recommendations of the Morse Report (15) (a Treasury-commissioned review into the Loan Charge, published in December 2019) found that the distress evoked in those people targeted by behavioural insights may, in some instances, have led to victims taking their own lives. In the words of the APGR:
‘HMRC continue to apply pressure to taxpayers by using 30 behavioural insights in communications, something that has been cited in one of the seven known suicides of people facing the Loan Charge’.
In further recognition of the suffering and anguish associated with these ‘nudge’ techniques, the APGR recommends:
‘An independent assessment and suspension of HMRC’s use of behavioural psychology/behavioural insights in light of the ongoing suicide risk to those impacted by the Loan Charge’.
Clearly, a truly independent and comprehensive evaluation of the ethics of deploying psychological ‘nudges’ on the British people – during public health campaigns and in other areas of government – is now urgently required. We respectfully ask the PACAC to consider performing this important role.
Co-Signatories
Psychology/therapy/mental health
- Dr Gary Sidley (M.Sc., ClinPsy, PhD) Retired Consultant Clinical Psychologist
- Ms Jen Ayling (UKCP registered counsellor) Psychotherapeutic Counsellor
- Dr Faye Bellanca (DClinPsy) Clinical Psychologist
- Dr Christian Buckland ((PsychD) Psychotherapist
- Alison Burnard (Dip Gestalt Therapy) Gestalt Psychotherapist
- Daran Campbell (PG Dip Counselling) Substance Misuse Practitioner
- Dr Tom Carnwath (FRCPsych, FRCGP) Consultant Psychiatrist
- Dr Maria Castro Romero (DClinPsy) Senior Lecturer in Clinical Psychology
- Gillian England (PG Dip Cognitive Behavioural Psychotherapy) Cognitive Behavioural Therapist
- Dr Elizabeth English (M.Phil, DPhil) Mindfulness Teacher & Trauma Therapist
- Mr Patrick Fagan (M.Sc.) Chief Scientific Officer, Capuchin Behavioural Science
- Dr Tracey Grant Lee (DClinPsy) Chartered Clinical Psychologist
- Andy Halewood (Advanced M.Sc. in Counselling Psychology) Chartered Psychologist
- Sue Parker Hall (CTA, MSc, PGCE) Psychotherapist
- Andrew D Harry (RPP PTP) NLP Master Practitioner
- Mrs Nicole Harvey (B.Sc, Pg Dip) Mental Health Practitioner/CBT Therapist
- Ms Julie A Horsley (Advanced Diploma in Counselling) Counsellor/Therapist
- Dr Richard House (MA, Ph.D, C.Psych. AFBPsS) former Senior Lecturer in Psychology
- Emma Kenny (MA Counselling, Advanced Diploma Counselling) Media Psychologist & Psychological Therapist
- Rachel Maisey (MA, PGCE, PgDip Counselling) Integrative Counsellor
- Jane Margerison (PG Dip Integrative Psychotherapy, RMN) Psychotherapist
- Kate Morrissey (Advanced Diploma in Counselling, MA Social Work) Counsellor
- Lucy Padina (Diploma in Psychology, Advanced Diploma in the Management of Psychological Trauma) Independent Consultant & Registered Social Worker
- Carolyn Polunin (M.Sc.) Integrative Psychotherapist
- Dr Livia Pontes (DClinPsy) Clinical Psychologist
- Dr Kate Porter (DClinPsy) Clinical Psychologist
- Ian Price (M.Sc. Organisational Behaviour) Business Psychologist
- Dr Bruce Scott (B.Sc., PhD) Psychoanalyst
- Professor David Seedhouse (PhD) Honorary Professor of Deliberative Practice
- Deborah Short (MA Gestalt Psychotherapy) Psychotherapist
- Ms Deborah Sharples (B.A. [Hons] Social Work) Mental Health Social Worker
- Susan Sidley (RMN) Retired Psychiatric Nurse
- Dr Angela Smith (DClinPsy, PhD) Psychology Lead
- Dr Helen Startup (DClinPsy, PhD) Consultant Clinical Psychologist
- Dr Dov Stein (MA, MB, BCh, BAO DCH Dobs) Consultant Psychiatrist & Psychotherapist
- Dr Zenobia Storah (DClinPsy) Child & Adolescent Clinical Psychologist
- Professor Ellen Townsend (PhD) Professor of Psychology
- Sarah Waters (BA, Dip Counselling & Therapy) Psychotherapist
- Dr Alice Welham (MA, DClinPsy, PhD) Clinical Psychologist
- Dr Damian Wilde (DClinPsy) Highly Specialist Clinical Psychologist
Other health professionals
- Mr John Collis (PGCert in Advanced Practice, BSc [Hons] Nursing, BA [Hons] Retired Nurse Practitioner
- James Cook (Bachelor of Nursing [Hons], Master of Public Health [MPH]) Registered Nurse
- Dr Clare Craig (BM, BCh, FRCPath) Consultant Pathologist
- Dr David Critchley (BSc, PhD) Clinical Pharmacologist
- Roisin Dargan-Peel (MA) Former Registered General Nurse, Midwife & Health Visitor
- Mr Paul Goss (MCSP, HCPC, KCMT) Clinical Director & Chartered Physiotherapist
- Dr Ros Jones (MD, FRCPCH) Retired Consultant Paediatrician
- Mrs Alison Langthorne (RGN) Staff Nurse
- Jenna Leith (RGN) Advanced Nurse Practitioner
- Dr Sam McBride (MB, BCh, MRCP, FRCP, FRCEM) Clinical Gerontologist
- Mrs Julie Noble (M.Sc, RN) Senior Forensic Nurse Examiner & Advanced Practitioner
- Mrs Christine Mary Proctor (RGN) Former Registered General Nurse
- Dr Annabel Smart (MBBS, BSc, DFSRH) Retired General Practitioner
- Nat Stephenson (B.Sc Audiology) Paediatric Audiologist
- Dr Helen Westwood (MBChB, MRCGP, DCH, DRCOG) General Practitioner
January 22, 2022
Posted by aletho |
Civil Liberties, Science and Pseudo-Science, Timeless or most popular | Covid-19, Human rights, UK |
Leave a comment
Now Backed by More Than 17,000 Doctors and Medical Scientists Around the World
Following Dr. Robert Malone’s appearance on The Joe Rogan Experience, more physicians and medical scientists have joined with their colleagues from around the world in signing the Physicians Declaration. Now with more than 17,000 signatures confirmed through a rigorous validation process, these physicians and scientists are represented by Dr. Malone as he speaks at the march to Defeat the Mandates on Sunday, January 23 in Washington, D.C.
The over 17,000 signers to the declaration have reached consensus on three foundational principles:
- Healthy children should not be subject to forced vaccination: they face negligible risk from covid, but face potential permanent, irreversible risk to their health if vaccinated, including heart, brain, reproductive and immune system damage.
- Natural Immunity Denial has prolonged the pandemic and needlessly restricted the lives of Covid-recovered people. Masks, lockdowns, and other restrictions have caused great harm especially to children and delayed the virus’ transition to endemic status.
- Health agencies and institutions must cease interfering with the physician-patient relationship. Policymakers are directly responsible for hundreds of thousands of deaths, as a result of institutional interference and blocking treatments proven to cure at a near 100% rate when administered early.
Led by Dr. Malone and staying loyal to the Hippocratic oath, the declaration’s signers have resisted financial inducements, threats, unprecedented censorship, and reputational attacks to remain committed first to patient health and well-being. After 23 months of research, millions of patients treated, hundreds of clinical trials performed and scientific data shared, and after demonstrating and documenting their success in combating COVID-19, the 17,000+ physicians and medical scientists who signed the declaration support the core principles Dr. Malone and many other doctors have been speaking out about since late last year.
The 17,000+ signatures of the declaration are authentic and must pass a screening process before being officially identified as signing the declaration. Signatories are required to supply their affiliation and a link to their medical organization, facility, or profile. Nurses, non-MD practitioners and non-medical scientists are removed from the list signatories, as are duplicate entries and “bot” emails. The emails of the signatories have been separately and repeatedly tested and verified by a 3rd-party provider.
As the number of signatures to the declaration continues to rise, we have published a select group of world famous, highly credentialed physicians and scientists who authored the declaration. Many other doctors who have spoken out against the corruption, censorship and hypocrisy by authorities have been threatened, fired, censured, lied about, intimidated, and harassed – all while saving patients’ lives daily. Never has the public been forced to become lab rats, for a vaccine 5 years away from adequate testing, violating basic principles of informed consent. Moreover, the medical and scientific evidence on the efficacy and safety of the COVID- 19 vaccine do not support mandating its use for anyone, especially healthy children.
January 23 March on Washington
The over 17,000 signers of the declaration will be represented on Sunday, January 23, when Dr. Malone stands with fellow doctors and scientists on stage in Washington DC, as part of the Defeat the Mandates march Sunday, January 23, 2022. At the Lincoln Memorial, they will be joined by a wide range of featured guests for a series of inspiring talks and musical performances. Join us!
About the Global COVID Summit
Global Covid Summit is the product of an international alliance of doctors and scientists, committed to speaking truth to power about Covid pandemic research and treatment.
Thousands have died from Covid as a result of being denied life-saving early treatment. The Declaration is a battle cry from physicians who are daily fighting for the right to treat their patients, and the right of patients to receive those treatments – without fear of interference, retribution or censorship by government, pharmacies, pharmaceutical corporations, and big tech. We demand that these groups step aside and honor the sanctity and integrity of the patient- physician relationship, the fundamental maxim “First Do No Harm”, and the freedom of patients and physicians to make informed medical decisions. Lives depend on it. More information here: https://globalCovidSummit.org
An events page is available to alert you to upcoming Summits and other events, most prominent of which is the January 23 March on Washington, an “American Homecoming” to protest overreaching medical mandates.
But you can also view some amazing video from past summits including Florida and San Juan, Puerto Rico. Please spread the word about this site – it’s important!
Remember – if you are a physician, nurse, medical scientist or medical care professional, please wear a white coat to the march (or carry it). Let’s all work to make this march peaceful in solidarity for all those marching around the world.
January 22, 2022
Posted by aletho |
Science and Pseudo-Science, Solidarity and Activism | Covid-19, COVID-19 Vaccine, United States |
Leave a comment

 Aletho News

