Medical evidence strongly justifies a proactive approach for using vitamin D
There seems to be an endless refusal by the public health establishment to fight the pandemic with the best science-based tools. Instead, they keep pushing vaccines.
Great German research provides unequivocal medical evidence that the government should be strongly advocating two actions: 1. Take vitamin D supplements and 2. Have your blood tested for vitamin D.
The title for this October 2021 journal article says it all: “COVID-19 Mortality Risk Correlates Inversely with Vitamin D3 Status, and a Mortality Rate Close to Zero Could Theoretically Be Achieved at 50 ng/mL 25(OH)D3: Results of a Systematic Review and Meta-Analysis.” [25(OH)D3 refers to metabolite of the vitamin in blood]
In other words, there is clear evidence that the lower your vitamin D level the greater your risk of dying from COVID infection. Moreover, the data clearly show that you need a blood level of at least 50 ng/mL.
Odds are, however, that very, very few people have been tested for their vitamin D level. This is a situation where waiting for testing is not the prudent approach. Vitamin D pills are pretty cheap and it is perfectly safe to take a healthy daily dose to maintain a good immune system. I take 4,000 IUs twice daily.
Here are a number of highlights from this research and other sources; the discussion is aimed at informing people with information not provided by Big Media, Big Government and Big Pharma.
Vitamin D is an accurate predictor of COVID infection. Its deficiency is just as significant, and perhaps more so, than more commonly discussed underlying medical conditions, including obesity.
To be clear, there is a level of vitamin D for an effective strategy at the personal and population level to prevent or mitigate new surges and outbreaks of COVID that are related to reduced vaccine effectiveness and new variants.
In the German study, fifteen other studies were cited that showed low vitamin D levels were related to cases of severe COVID infection, and seven studies that found positive results from treating ill patients with the vitamin.
The German study noted: “The finding that most SARS-CoV-2 patients admitted to hospitals have vitamin D3 blood levels that are too low is unquestioned even by opponents of vitamin D supplementation.” The German study “followed 1,601 hospitalized patients, 784 who had their vitamin D levels measured within a day after admission and 817 whose vitamin D levels were known before infection. And the researchers also analyzed the long-term average vitamin D3 levels documented for 19 countries. The observed median vitamin D value over all collected study cohorts was 23.2 ng/mL, which is clearly too low to work effectively against COVID.”
Why does this vitamin work so well? The German study explained: A main cause of a severe reaction from COVID results from a “cytokine storm.” This refers to the body’s immune system releasing too many toxic cytokines as part of the inflammatory response to the virus. Vitamin D is a main regulator of those cells. A low level of the vitamin means a greater risk for a cytokine storm. This is especially pertinent for lung problems from COVID.
Other studies
On a par with the German study was an important US medical article from May 2021: Vitamin D and Its Potential Benefit for the COVID-19 Pandemic. It noted: “Experimental studies have shown that vitamin D exerts several actions that are thought to be protective against coronavirus disease (COVID-19) infectivity and severity. … There are a growing number of data connecting COVID-19 infectivity and severity with vitamin D status, suggesting a potential benefit of vitamin D supplementation for primary prevention or as an adjunctive treatment of COVID-19. … there is no downside to increasing vitamin D intake and having sensible sunlight exposure to maintain serum 25-hydroxyvitamin D at a level of least 30 ng/mL and preferably 40 to 60 ng/mL to minimize the risk of COVID-19 infection and its severity.” This confirms the German study and its finding of a critical vitamin level of 50 ng/mL.
Daniel Horowitz has made this correct observation about vitamin D supplementation: “An endless stream of academic research demonstrates that not only would such an approach have worked much better than the vaccines, but rather than coming with sundry known and unknown negative side effects.“
There are now 142 studies vouching for the near-perfect correlation between higher vitamin D levels and better outcomes in COVID patients.
From Israel came work that showed 25% of hospitalized COVID patients with vitamin D deficiency died compared to just 3% among those without a deficiency. And those with a deficiency were 14 times more likely to end up with a severe or critical condition.
Also from Israel, data on 1,176 patients with COVID infection admitted to the Galilee Medical Center, 253 had vitamin D levels on record and half were vitamin D-deficient. This was the conclusion: “Among hospitalized COVID-19 patients, pre-infection deficiency of vitamin D was associated with increased disease severity and mortality.”
Several studies have come from the University of Chicago. One found that a vitamin D deficiency (less than 20 ng/ml) may raise the risk of testing positive for COVID-19, actually a 7.2% chance of testing positive for the virus. And that more than 80% of patients diagnosed with COVID-19 were vitamin D deficient. And Black individuals who had levels of 30 to 40 ng/ml had a 2.64 times higher risk of testing positive for COVID-19 than people with levels of 40 ng/ml or greater.
On the good news side is a new study from Turkish researchers. They focused on getting people’s levels over 30 ng/mL with supplements. At that level there was success compared to people without supplementation. This was true even if they had comorbidities. They were able to achieve that blood level within two weeks. Those with no comorbidities and no vitamin D treatment had 1.9-fold increased risk of having hospitalization longer than 8 days compared with cases with both comorbidities and vitamin D treatment.
Another option
Some people may have absorption problems. The solution is to use the active form of D – either calcifediol or calcitriol – to raise their levels more quickly. This bypasses the liver’s metabolic process very effectively. Studies have shown that people hospitalized with low levels but given the active form of D did not progress to the ICU. Places that sell vitamin D often sell the concentrated active form.
I have a supply of cholecalciferol pills that provide 50,000 IUs, compared to ordinary D pills typically with 2,000 IUs. A reasonable use of the high concentration pills is in the event of coming down with a serious COVID infection. This may be a sensible strategy for those who do not know what their level is or have not taken the normal pills for some period. It can take months to raise a very low level to above the critical level the German study found necessary for the best protection.
Deficiency
Aside from dealing with COVID, two pertinent questions are: Is there an optimal level of vitamin D and are Americans deficient in it? For the first, this has been said: “While blood levels of 30 ng/mL or higher are considered normal, the optimal blood level of vitamin D has not yet been established.” From the Cleveland Clinic is this: “Normal vitamin D levels are usually between 20-80 NG/ML. If supplementation is recommended, remember to take it with a meal and on a full stomach to help absorption. Unfortunately, about 42% of the US population is vitamin D deficient with some populations having even higher levels of deficiency.”
A Mayo Clinic study said this: “Vitamin D deficiency is more common than previously thought. The Centers for Disease Control and Prevention has reported that the percentage of adults achieving vitamin D sufficiency as defined by 25(OH)D of at least 30 ng/mL has declined from about 60% in 1988-1994 to approximately 30% in 2001-2004 in whites and from about 10% to approximately 5% in African Americans during this same time. Furthermore, more people have been found to be severely deficient in vitamin D [ <10 ng/mL]. Even when using a conservative definition of vitamin D deficiency, many patients routinely encountered in clinical practice will be deficient in vitamin D.”
Clearly, personal deficiency can only be determined by a blood test that prudent people will request their doctors to order for a lab test.
Conclusions
Seeing vitamin D as crucial to surviving COVID is supported by solid medical research. There is good data to support a desired level of 50 ng/mL. Whether a person has this level requires a blood test for the vitamin, not something that most physicians normally call for when ordering blood tests for other reasons.
As the US approaches 800,000 COVID related deaths it is reasonable to believe that perhaps hundreds of thousands of lives could have been saved if the government had strongly supported vitamin D blood testing and supplementation if needed. But in the absence of such a COVID policy, people have good reasons to use D supplements if they are not routinely exposed to sunlight without using sunscreen products.
Many physicians have issued protocols for preventing and treating COVID that include vitamin D supplements. For example, the esteemed Dr. Zelenko uses the following: 5,000 IU 1 time a day for 7 days for low risk patients, and for high risk patients: 10,000 IU once a day for 7 days or 50,000 IU once a day for 1-2 days.
However, continuing its stupidity, NIH maintains that “There is insufficient evidence to recommend either for or against the use of vitamin D for the prevention or treatment of COVID-19.” This too was said: “Vitamin D deficiency (defined as vitamin D ≤20 ng/mL) is common in the United States, particularly among persons of Hispanic ethnicity and Black race. These groups are also overrepresented among cases of COVID-19 in the United States. Vitamin D deficiency is also more common in older patients and patients with obesity and hypertension; these factors have been associated with worse outcomes in patients with COVID-19.” Sounds smart to fight deficiency for avoiding COVID health impacts.
Sadly, we cannot count on the public health establishment to take a science-based, aggressive policy on using vitamin D supplements as an alternative to COVID vaccines or expensive medicines. Its up to individuals to protect their own lives by being well informed and proactive.
December 4, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | Covid-19, Vitamin D |
Leave a comment
Hiding part of the data leads to wrong conclusions
There have been numerous papers published showing how well the vaccines protect people after the second dose. Some of this effect is an illusion. The effect happens as a result of inaccurate measuring and a phenomenon called survivorship bias.
Survivorship bias happens when a group is compared at two time points, but the members of the group change between the time points. It would be like assessing the quality of a swimming school which favours the technique of throwing people into the middle of the ocean, leaving them for a couple of hours and claiming credit for how well the remaining students can swim. After two hours, the only people left would be the ones who could already swim and possibly a few who learnt to swim the hard way! The poor souls who drowned in the interim don’t even make the count. Attributing the remaining people’s swimming ability to the coach who turned up 2 hours later would obviously give a very misleading picture. Pointing out that no-one drowned in later lessons would be equally misleading in determining the success of the ‘teaching technique’.
With covid vaccination there is a two week period after vaccination that is not included in the data. The rationale given for this is that vaccines take a while to induce antibodies and therefore the first two weeks’ data are not relevant. Obviously this is flawed. What if the vaccines have deleterious effects that are visible straightaway, that have nothing to do with antibody production? An example is the high rate of shingles seen after covid vaccination, suggesting there is a problem with viral reactivation. This may explain why Sars-CoV-2 infection rates are actually higher in the vaccinated than in the unvaccinated in the first two weeks after vaccination.
The effect of eliminating the first two weeks is a misleading data bias. If people become infected and are dying during that period, this needs to be included. The possibility that the vaccine itself may exert an effect on infection rate cannot be overlooked and the entire dataset needs to be included in order to accurately assess effectiveness. By only measuring the period after the higher risk of infection (0-14 days) it is possible to be deceived. Any signal would be missed.
Aside from it being nonsensical in terms of individual risk to remove this period of time, there will also be an impact on the wider community. If the vaccine in fact causes a spike in infections during the first two weeks, this will inevitably increase spread and will lead to an increased number of infections in that community during that time. Therefore, the assessment of the impact of the vaccination programme must include not only the effect on the individual, but the impact on the wider community.
This point is of particular relevance for close-knit communities where many are being vaccinated at the same time, such as schools and in particular communities with a high number of vulnerable people such as care homes and hospitals. What we are effectively doing is ‘speeding up’ the wave of infections (and deaths). Ultimately at the end of the viral season, the same number of people died. Because of excluding the earlier deaths (1-14 days), we are misled into thinking that the vaccines were more effective than they actually were. By only looking at the later period and seeing fewer deaths during that time, the illusion was created that lives were saved. This is evident in data from many countries following vaccine roll-out. The graph below showing the UK versus Europe illustrates this point, as the UK was the fastest to roll out the vaccine. The total number of deaths, represented by the area under the curve, was similar to other countries, but is just compressed into a shorter time period.
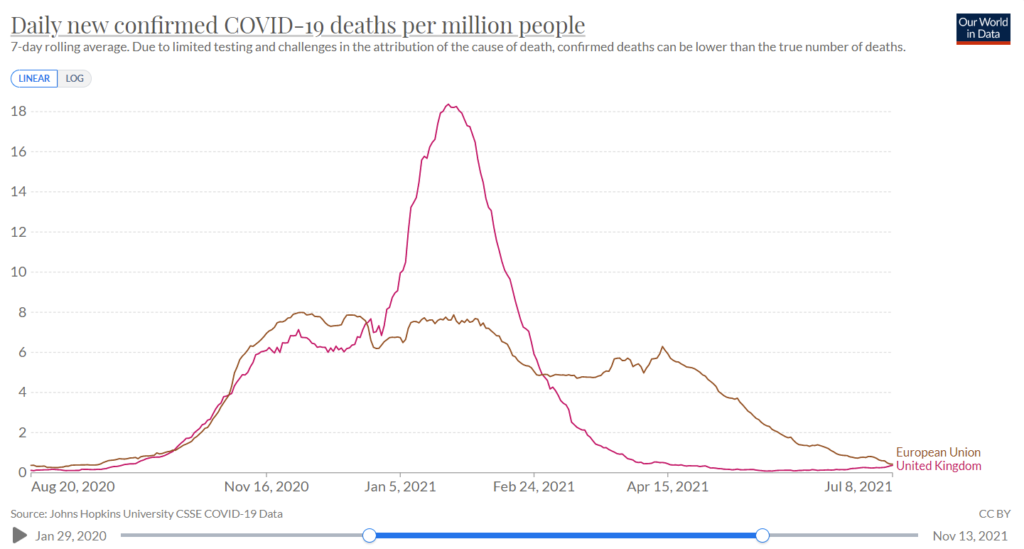
Figure 1: Covid Deaths in winter in UK and the European Union
Let’s now examine some specific examples, e.g. this study of nursing home residents in the United States. The results show that over the course of the study 6.8% of the vaccinated population were infected and 6.8% of the unvaccinated population were infected. However, by deciding that the first 14 days after vaccination should be excluded, the grey area for the vaccinated group is compared to the black and grey area combined for the unvaccinated. Doing so could lead to the claim of 66% vaccine efficacy against infection. The authors of this study were honest enough to share the raw data and did not claim 66% efficacy.
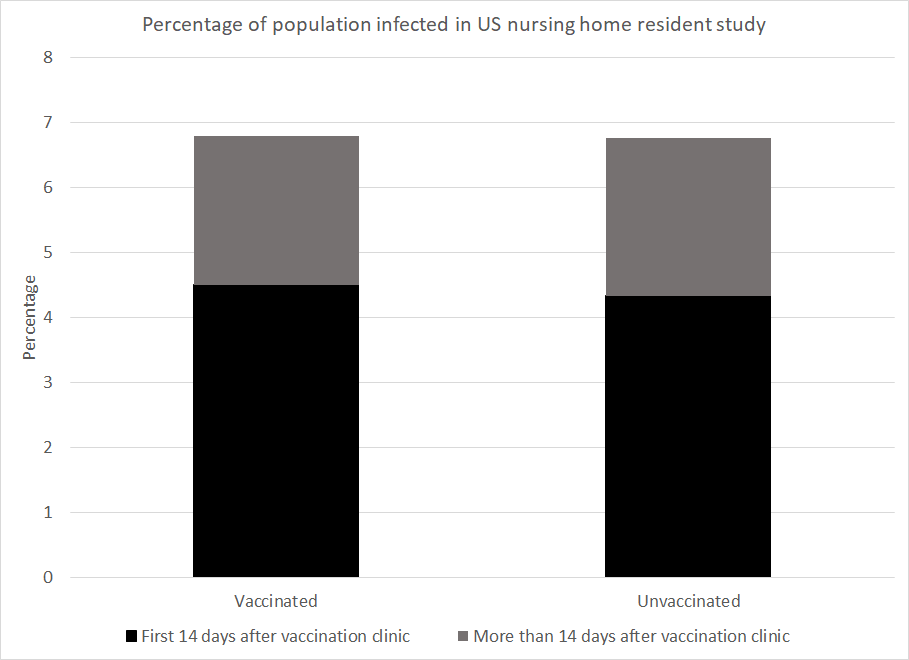
Figure 2: Data from US paper showing the percentage of the nursing home population to be infected by time after the clinic came to their home and by vaccination status
However, numerous studies have relied on this trick to make claims of vaccine efficacy. The most obvious examples of this are the original Pfizer trial study and the AstraZeneca trial.
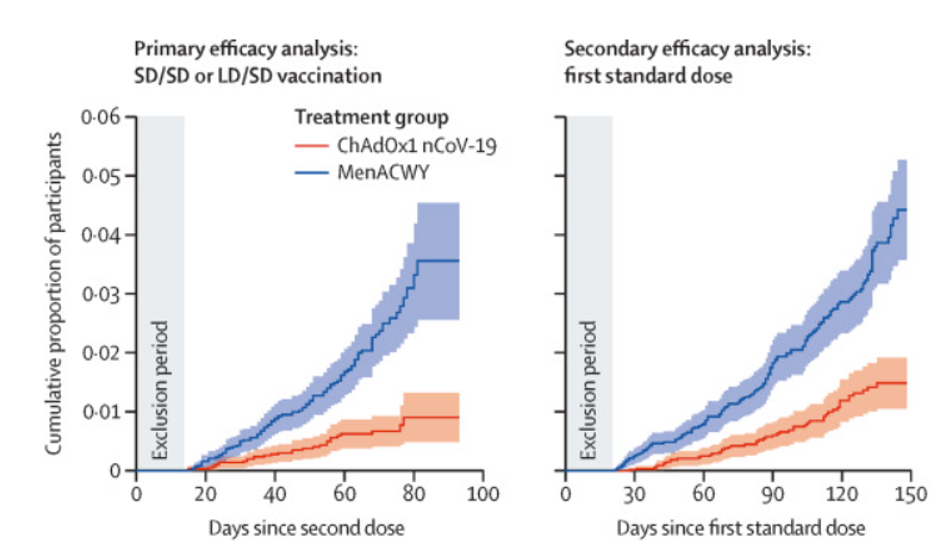
Figure 3: Graph from AstraZeneca trial showing censorship of early period (‘Exclusion Period’)
To take a second example, a Danish paper measured infection numbers in healthcare workers and care home residents. Prior to the beginning of the vaccination programme 4.8% of the healthcare workers had been infected and 3.8% of the care home residents had been. The study ended at the end of the Danish winter wave after 95% of the care home residents had been vaccinated and 28% of the healthcare workers had been. Given the worse position at the start and the lower vaccination rate in healthcare workers you might expect that they were worse off overall. However, the percentage infected by the end of the wave was 7.0% among healthcare workers but 7.7% among care home residents.
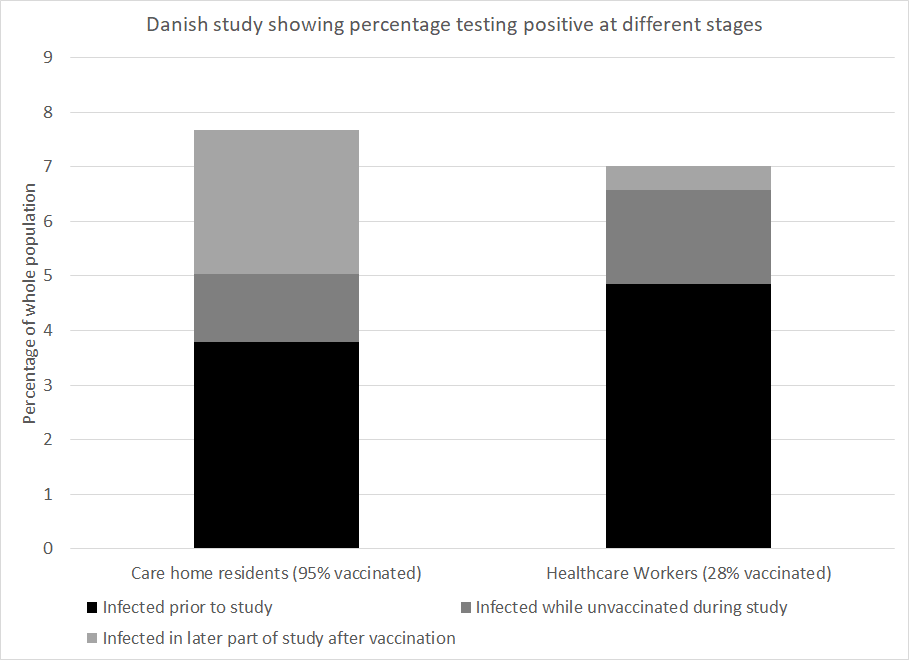
Figure 4: Data from Danish paper showing percentage of population infected among care home residents and healthcare workers
How much of the vaccine efficacy reported in covid research is really a measure of survivorship bias coupled with naturally acquired immunity? This is a critical question. No claim of vaccine efficacy should be made without first addressing this.
December 4, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | Covid-19, COVID-19 Vaccine |
Leave a comment
Looking at the viral evolution of SARS-CoV-2, researchers from the prestigious universities Harvard and MIT have found that the virus not only will continue to mutate and create new variants in the future, but will become resistant to the vaccines as it adapts to humans.
Their study, published December 2, 2021, in the journal Science, shows that the mutations serve as bridges to conferring resistance to neutralizing antibodies. “The severity of the phenotypes we observed in vitro suggest that further evolved variants will more adeptly escape therapeutic antibody neutralization than currently circulating variants of concern, with potential resistance to two-component antibody cocktails,” the study authors wrote.
The scientists urged that “proactively examining the consequences of further viral evolution before the next highly antibody resistant strain emerges is of utmost importance.”
December 4, 2021
Posted by aletho |
Science and Pseudo-Science | Covid-19, COVID-19 Vaccine |
Leave a comment
In my column in the Spectator this week I’ve highlighted an egregious assault on free speech in New Zealand that was brought to my attention by the NZ Free Speech Union, which has issued a statement about it. A distinguished biochemist, Professor Garth Cooper, is being subjected to a disciplinary investigation by the Royal Society of New Zealand that could result in his expulsion. Here’s an extract:
Why is this distinguished scientist at risk of being expelled from New Zealand’s most prestigious academic society? Several months ago he was one of seven signatories to a letter in the New Zealand Listener that took issue with a proposal by a government working group that schools should give the same weight to Maori mythology as they do to science in the classroom. That is, the Maori understanding of the world — that all living things originated with Rangi and Papa, the sky mother and sky god, for instance — should be presented as just as valid as the theories of Galileo, Newton and Darwin.
The authors of the letter, “In Defence of Science“, were careful to say that indigenous knowledge was “critical for the preservation and perpetuation of culture and local practices, and plays key roles in management and policy” and should be taught in New Zealand’s schools. But they drew the line at treating it as on a par with physics, chemistry and biology: “In the discovery of empirical, universal truths, it falls far short of what we can define as science itself.”
In a rational world, this letter would have been regarded as uncontroversial. Surely the argument about whether to teach schoolchildren scientific or religious explanations for the origins of the universe and the ascent of man was settled by the Scopes trial in 1925? Apart from the obvious difficulty of prioritising one religious viewpoint in an ethnically diverse society like New Zealand (what about Christianity, Islam and Hinduism?), there is the problem that Maori schoolchildren, already among the least privileged in the country, will be at an even greater disadvantage if their teachers patronise them by saying there’s no need to learn the rudiments of scientific knowledge. Knowing about Rangi and Papa won’t get you into medical school.
But the moment this letter was published all hell broke loose. The views of the authors, who were all professors at Auckland, were denounced by the Royal Society, the New Zealand Association of Scientists, and the Tertiary Education Union, as well as by their own vice-chancellor, Dawn Freshwater. In a hand-wringing, cry-bullying email to all staff at the university, she said the letter had “caused considerable hurt and dismay among our staff, students and alumni” and said it pointed to ‘major problems with some of our colleagues’.
Two of Professor Cooper’s academic colleagues, Dr Siouxsie Wiles and Dr Shaun Hendy, issued an ‘open letter’ condemning the heretics for causing “untold harm and hurt”. They invited anyone who agreed with them to add their names to the ‘open letter’, and more than 2,000 academics duly obliged. Before long, five members of the Royal Society had complained and a panel was set up to investigate.
Worth reading in full.
If you’re a scholar in the sciences or the humanities and want to defend Professor Cooper you should write to Roger Ridley, the Chief Executive of the Royal Society of New Zealand, at roger.ridley@royalsociety.org.nz. He could use your help.
Stop Press: You can read more about this scandal here.
“Science is helping us battle worldwide crises such as Covid, global warming, carbon pollution, biodiversity loss and environmental degradation” … “Putting science on a pedestal gets us no further in the solution of these crises.”
December 4, 2021
Posted by aletho |
Progressive Hypocrite, Science and Pseudo-Science, Timeless or most popular | New Zealand |
Leave a comment
a trip down memory lane
it was february of 2020, a kinder time. a gentler time.
and the WHO was putting out guidelines to avoid stigmatizing people who got covid…

never forget this.
they knew before 2020 than none of these interventions worked, that their prices were insanely high, and that they should never be undertaken.
they knew the dangers of vilification and polarization.
standing pandemic guidelines vehemently warned against any of this and especially against making pariahs of the infected and cultivating exaggerated fear to drive compliance.
this has NOT been “following the science” is has been the abrogation of a century of evidence based epidemiology and social mores in order to take a devastating and self-serving joy ride with the world’s populace like it was some sort of video game.
and all the health agencies were aware of that.
these were choices.
this was done to you, not for you.
and it was done by people who damn well knew better.
if you learn one thing from this, learn that, because these malefactors and agencies are still around and they are not done with you…
December 4, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | Covid-19, Human rights, WHO |
Leave a comment
There’s a reason heart attacks and blood clots are about to become a LOT more common… but the vaccine has nothing to do with it. Apparently.
Doctors are warning that hundreds of thousands of people in the UK could be at increased risk of heart disease or cardiac events.
Speaking to the Evening Standard, psychological therapist Mark Rayner and vascular surgeon Tahir Hussein said that the UK could see “300,000 new patients with heart issues” in the near future.
What’s to blame? Well, that would be “Post Pandemic Stress Disorder”. A new condition “yet to be recognised”, even though “many experts believe it should be”.
It’s a totally real thing. They didn’t just completely make it up. Don’t be cynical.
You see, all the “pandemic” related anxiety and stress has taken such a toll on the public that doctors are predicting a 5% increase in heart disease, nationwide, and not just in the elderly or infirm.
According to Dr Hussein, he is already seeing…
a big increase in thrombotic-related vascular conditions in my practice. Far younger patients are being admitted and requiring surgical and medical intervention than prior to the pandemic.
Now, some of you demented anti-vaxxers out there might be asking crazy questions like “could this increase in blood clots and heart disease be linked to injecting millions of people with an untested vaccine?”
But that’s absurd. And I told you to stop being cynical.
Yes, fine, in the interests of fairness, we should mention it was recently reported that the Astra Zeneca jab can cause blood clots.
It turns out all the people saying that back in March weren’t just conspiracy theorists spreading misinformation after all. They were totally right. But the clots are only rare, so don’t worry. And they sort of know what causes it now, so future batches might be fine.
And yes, also in the interests of fairness, it’s true that both the Pfizer and Moderna shots can cause heart issues too. Both, according to the CDC, can cause pericarditis and myocarditis, the complications of which include heart attacks, heart failure and strokes.
The UK government has even produced special guidelines for dealing with myocardits, “following Covid19 vaccination”.
But, just like the blood clots, this is very rare. Obviously not so rare you don’t need a special guiding document on how to deal with it, but still very very rare.
… the point is, yes, all the major Covid vaccines are known to have cardiac-related side effects, and yes, some doctors are now predicting a major spike in heart-related health problems, but these are totally unrelated.
Frankly, the very idea this could be a media psy-op designed to do pre-emptive damage control is ridiculous.
Stop. Being. Cynical.
Any connection between heart problems and vaccines is just bad luck or a coincidence. It’s really just the stress.
Don’t ask questions about the vaccine. Don’t decide to not get the vaccine. And certainly don’t worry about what’s in the vaccine. Worrying causes stress which, unlike vaccines, causes heart problems.
Just get the shot. And the second dose. And the booster, every three months. And the updated doses, for the variants.
Just to be safe, get four shots a year, every year, for the rest of your natural life, and/or until you drop dead of a heart attack.
… due to stress.
Don’t be cynical.
December 4, 2021
Posted by aletho |
Fake News, Mainstream Media, Warmongering, Science and Pseudo-Science | COVID-19 Vaccine |
Leave a comment
Courts around the country are striking down vaccine mandates and even Covid restrictions in general. Protests against both have erupted the world over. There is a trend in which major names and faces that imposed lockdowns on the country are resigning from their positions and otherwise dropping out of politics. The Biden administration in general has sunk in the polls. The resistance to the entire regime of command and control that seized the world in March 2020 is growing by the day.
But none of this seems to matter to the dominant Internal portals of Google and YouTube, which Google owns. They occupy the number one and number two spots for global traffic and reach. That’s some serious power over what the majority of people read, see, hear, and believe. It’s true that critically thinking people have already shifted to DuckDuckGo, Rumble, and many other platforms, and their market share is growing, to be sure. But nothing can compare to the 75% market share of YouTube, or the 86% share of search controlled by Google.
Often individual users can develop a distorted sense of that whole based on their own browsing habits. You like Brownstone.org, for example, and you get great information from this site. It is easy to forget that its 4 million users seem nearly invisible compared with the traffic enjoyed by the larger sites. Being on the admin side, it is much easier to observe how a myth spread, for example, by CNN can reach tens of millions of people whereas its refutation on a small site might only reach a few thousand. The myth stands.
For this reason, their Terms of Use seriously matter for culture, politics, intellectual life, and public opinion in general. And Google has just changed its terms as they apply to YouTube. It’s a fair presumption that Google’s search results will reflect these same terms. They pertain directly to the science behind Covid, mitigation policies, and mandates on the vaccines. These new terms go into effect on January 6, 2022 (why that date?). If they are truly enforced, freedom of speech and the ability of the scientific process to operate unimpeded will be severely curtailed.
Under the new rules, you cannot claim “that the pandemic is over.” Which is to say, the pandemic is now declared to last forever. You cannot make “claims that any group or individual has immunity to the virus or cannot transmit the virus,” which means that all the science on naturally acquired immunity can be deleted.
You cannot claim that ”vaccines do not reduce risk of contracting COVID-19,” which directly contradicts the FDA: “The scientific community does not yet know if the Pfizer-BioNTech COVID-19 Vaccine will reduce such transmission.” You cannot post “videos alleging that social distancing and self-isolation are not effective in reducing the spread of the virus” and you cannot claim that “wearing a mask causes oxygen levels to drop to dangerous levels.”
And there is this one: you cannot make claims that “achieving herd immunity through natural infection is safer than vaccinating the population,” even though endemicity is inevitable and the vaccines cannot make a substantial contribution to its achievement due to their inability to protect fully against infection and transmission.
As usual, the long list of Do Nots also includes statements that are patently false and otherwise ridiculous – so much so that it seems not dangerous to permit them! The full list is extremely long and includes many fully open questions that Google/YouTube wants to be declared closed. Some of the Do Nots also include statements that are contradicted by statements from Fauci and Biden, such as the rule that you cannot make “claims that any vaccine is a guaranteed prevention method for COVID-19.” The head of the CDC made exactly this claim!
If these rules are strenuously enforced, millions of videos, interviews, television shows, lectures, press conferences, and scientific presentations will disappear. Maybe tens of millions actually. And all in the name of protecting “science” against its corruption, as if YouTube should be the determinant of what constitutes good science.
Here is what Google says about the consequences of violating the rules:
We may allow content that violates the misinformation policies noted on this page if that content includes additional context in the video, audio, title, or description. This is not a free pass to promote misinformation. Additional context may include countervailing views from local health authorities or medical experts. We may also make exceptions if the purpose of the content is to condemn, dispute, or satirize misinformation that violates our policies. We may also make exceptions for content showing an open public forum, like a protest or public hearing, provided the content does not aim to promote misinformation that violates our policies.
If your content violates this policy, we’ll remove the content and send you an email to let you know. If this is your first time violating our Community Guidelines, you’ll likely get a warning with no penalty to your channel. If it’s not, we may issue a strike against your channel. If you get 3 strikes within 90 days, your channel will be terminated.
An intriguing question for any defender of private enterprise – I am certainly that – is why Google would so willingly turn over its platform to a branch of the state and its medical/policy priorities. It cannot be simply the desire to only say true things because there is plenty that is thoroughly disputable in these rules and much has already been challenged by vast quantities of peer-reviewed studies.
How does it come to be that such a huge business can become fully captured by government? I have friends who say it is the reverse actually, that Google has fully captured government, and is driving forward the agenda of politics. Regardless, it becomes a troubled world in which one can no longer distinguish business from the state, or either from big pharmaceutical companies. The state finds it more advantageous to enlist business in its rights violations than risk the court challenges that come with directly violating the First Amendment. The law restricts states in ways that do not apply to private companies, so the answer for the state seems obvious: use the private sector to achieve state policy priorities, particularly as it pertains to controlling the information to which the public has access.
Others might observe that Google has everything to gain from its investment in lockdown policies and mandates, all the better to keep people glued to their personal computers. Even granting that big tech benefited enormously from lockdowns, that’s an outlook on enterprise that is too cynical for me to believe at this stage. Or maybe I’m naive.
What seems clear is that these censorious moves could seriously erode market share and give rise to new platforms that will eventually compete more directly. But before we get too optimistic about this, the time between now and then is a very long time away, while the change in the scientific culture that this move will enact starts next month.
Here is the full text of Google Terms of Use as it pertains to the most critical issues affecting freedom, free speech, and science in the world today. For your research amusement, you can see via the WaybackMachine how this page has expanded over time from its initial page on May 2, 2020, to today.
COVID-19 medical misinformation policy
The safety of our creators, viewers, and partners is our highest priority. We look to each of you to help us protect this unique and vibrant community. It’s important you understand our Community Guidelines, and the role they play in our shared responsibility to keep YouTube safe. Take the time to carefully read the policy below. You can also check out this page for a full list of our guidelines.
YouTube doesn’t allow content about COVID-19 that poses a serious risk of egregious harm.
YouTube doesn’t allow content that spreads medical misinformation that contradicts local health authorities’ (LHA) or the World Health Organization’s (WHO) medical information about COVID-19. This is limited to content that contradicts WHO or local health authorities’ guidance on:
- Treatment
- Prevention
- Diagnosis
- Transmission
- Social distancing and self isolation guidelines
- The existence of COVID-19
Note: YouTube’s policies on COVID-19 are subject to change in response to changes to global or local health authorities’ guidance on the virus. There may be a delay between new LHA/WHO guidance and policy updates given the frequency with which this guidance changes, and our policies may not cover all LHA/WHO guidance related to COVID-19.
Our COVID-19 policies were first published on May 20, 2020.
What this policy means for you
If you’re posting content
Don’t post content on YouTube if it includes any of the following:
Treatment misinformation:
- Content that encourages the use of home remedies, prayer, or rituals in place of medical treatment such as consulting a doctor or going to the hospital
- Content that claims that there’s a guaranteed cure for COVID-19
- Content that recommends use of Ivermectin or Hydroxychloroquine for the treatment of COVID-19
- Claims that Hydroxychloroquine is an effective treatment for COVID-19
- Categorical claims that Ivermectin is an effective treatment for COVID-19
- Claims that Ivermectin and Hydroxychloroquine are safe to use in the treatment COVID-19
- Other content that discourages people from consulting a medical professional or seeking medical advice
Prevention misinformation: Content that promotes prevention methods that contradict local health authorities or WHO.
- Claims that there is a guaranteed prevention method for COVID-19
- Claims that any medication or vaccination is a guaranteed prevention method for COVID-19
- Content that recommends use of Ivermectin or Hydroxychloroquine for the prevention of COVID-19
- Claims that Ivermectin and Hydroxychloroquine are safe to use in the treatment COVID-19
- Claims that wearing a mask is dangerous or causes negative physical health effects
- Claims that masks do not play a role in preventing the contraction or transmission of COVID-19
- Claims about COVID-19 vaccinations that contradict expert consensus from local health authorities or WHO
- Claims that an approved COVID-19 vaccine will cause death, infertility, miscarriage, autism, or contraction of other infectious diseases
- Claims that an approved COVID-19 vaccine will contain substances that are not on the vaccine ingredient list, such as biological matter from fetuses (e.g. fetal tissue, fetal cell lines) or animal products
- Claims that an approved COVID-19 vaccine will contain substances or devices meant to track or identify those who’ve received it
- Claims that COVID-19 vaccines will make people who receive them magnetic
- Claims that an approved COVID-19 vaccine will alter a person’s genetic makeup
- Claims that COVID-19 vaccines do not reduce risk of contracting COVID-19
- Claims that any vaccine causes contraction of COVID-19
- Claims that a specific population will be required (by any entity except for a government) to take part in vaccine trials or receive the vaccine first
- Content that promotes the use of unapproved or homemade COVID-19 vaccines
- Instructions to counterfeit vaccine certificates, or offers of sale for such documents
Diagnostic misinformation: Content that promotes diagnostic methods that contradict local health authorities or WHO.
- Claims that approved COVID-19 tests are dangerous or cause negative physical health effects
- Claims that approved COVID-19 tests cannot diagnose COVID-19
Transmission misinformation: Content that promotes transmission information that contradicts local health authorities or WHO.
- Content that claims that COVID-19 is not caused by a viral infection
- Content that claims COVID-19 is not contagious
- Content that claims that COVID-19 cannot spread in certain climates or geographies
- Content that claims that any group or individual has immunity to the virus or cannot transmit the virus
Social distancing and self isolation misinformation: Content that disputes the efficacy of local health authorities’ or WHO’s guidance on physical distancing or self-isolation measures to reduce transmission of COVID-19.
Content that denies the existence of COVID-19:
- Denial that COVID-19 exists
- Claims that people have not died or gotten sick from COVID-19
- Claims that the virus no longer exists or that the pandemic is over
- Claims that the symptoms, death rates, or contagiousness of COVID-19 are less severe or equally as severe as the common cold or seasonal flu
- Claims that the symptoms of COVID-19 are never severe
This policy applies to videos, video descriptions, comments, live streams, and any other YouTube product or feature. Keep in mind that this isn’t a complete list. Please note these policies also apply to external links in your content. This can include clickable URLs, verbally directing users to other sites in video, as well as other forms.
Examples
Here are some examples of content that’s not allowed on YouTube:
- Denial that COVID-19 exists
- Claims that people have not died from COVID-19
- Claims that any vaccine is a guaranteed prevention method for COVID-19
- Claims that a specific treatment or medicine is a guaranteed cure for COVID-19
- Claims that hydroxychloroquine saves people from COVID-19
- Promotion of MMS (Miracle Mineral Solution) for the treatment of COVID-19
- Claims that certain people have immunity to COVID-19 due to their race or nationality
- Encouraging taking home remedies instead of getting medical treatment when sick
- Discouraging people from consulting a medical professional if they’re sick
- Content that claims that holding your breath can be used as a diagnostic test for COVID-19
- Videos alleging that if you avoid Asian food, you won’t get the coronavirus
- Videos alleging that setting off fireworks can clean the air of the virus and will prevent the spread of the virus
- Claims that COVID-19 is caused by radiation from 5G networks
- Videos alleging that the COVID-19 test is the cause of the virus
- Claims that countries with hot climates will not experience the spread of the virus
- Videos alleging that social distancing and self-isolation are not effective in reducing the spread of the virus
- Claims that wearing a mask causes oxygen levels to drop to dangerous levels
- Claims that masks cause lung cancer or brain damage
- Claims that wearing a mask gives you COVID-19
- Claims that the COVID-19 vaccine will kill people who receive it
- Claims that the COVID-19 vaccine will be used as a means of population reduction
- Videos claiming that the COVID-19 vaccine will contain fetal tissue
- Claims that the flu vaccine causes contraction of COVID-19
- Claims that COVID-19 vaccines are not effective in preventing the spread of COVID-19
- Claims that the COVID-19 vaccine causes contraction of other infectious diseases or makes people more vulnerable to contraction of other infectious diseases
- Claims that the COVID-19 vaccines contain a microchip or tracking device
- Claims that achieving herd immunity through natural infection is safer than vaccinating the population
- Claims that COVID-19 never causes serious symptoms or hospitalization
- Claims that the death rate from the seasonal flu is higher than the death rate of COVID-19
- Claims that people are immune to the virus based on their race
- Claims that children cannot or do not contract COVID-19
- Claims that there have not been cases or deaths in countries where cases or deaths have been confirmed by local health authorities or the WHO
Educational, documentary, scientific or artistic content
We may allow content that violates the misinformation policies noted on this page if that content includes additional context in the video, audio, title, or description. This is not a free pass to promote misinformation. Additional context may include countervailing views from local health authorities or medical experts. We may also make exceptions if the purpose of the content is to condemn, dispute, or satirize misinformation that violates our policies. We may also make exceptions for content showing an open public forum, like a protest or public hearing, provided the content does not aim to promote misinformation that violates our policies.
What happens if content violates this policy
If your content violates this policy, we’ll remove the content and send you an email to let you know. If this is your first time violating our Community Guidelines, you’ll likely get a warning with no penalty to your channel. If it’s not, we may issue a strike against your channel. If you get 3 strikes within 90 days, your channel will be terminated. You can learn more about our strikes system here.
We may terminate your channel or account for repeated violations of the Community Guidelines or Terms of Service. We may also terminate your channel or account after a single case of severe abuse, or when the channel is dedicated to a policy violation. You can learn more about channel or account terminations here.
Jeffrey A. Tucker is Founder and President of the Brownstone Institute and the author of many thousands of articles in the scholarly and popular press and ten books in 5 languages, most recently Liberty or Lockdown.
December 3, 2021
Posted by aletho |
Full Spectrum Dominance, Science and Pseudo-Science | Google, YouTube |
Leave a comment
I HAVE just been alerted to the Government’s new Myocarditis and pericarditis after Covid 19 vaccination: guidance for healthcare professionals, published four days ago on Monday. It makes chilling reading.
You can read it here.
First, it is a clear admission of that myocarditis is a serious post-vaccine adverse reaction risk. Second, amongst the usual and increasingly implausible disclaimers like ‘it is a rare condition’ and ‘it is usually mild or stable and most patients typically recover fully without medical treatment’, comes the terrifying admission that ‘a high percentage of children admitted to hospital with myocarditis have significant left ventricular fibrosis and no follow-up data is available yet on hospitalised patients.’
So does it recommend halting the vaccine programme for children, given ‘that no follow-up data is available yet on hospitalised patients’?
No.
In complete defiance of any precautionary principle the subtext of this disturbing document is that these are reactions that are expected, not to be alarmed by and to be lived with as an inevitable consequence of the vaccination, giving what should be self-evident advice that though ‘the majority of cases appear to be mild and self-limiting; any acutely ill or unstable patients should be referred to hospital directly’. As though an acutely ill child was not normally treated as an emergency and rushed to hospital.
Furthermore, how they can claim to know at this stage that ‘ the majority of cases are mild and self-limiting’ in the absence of rigorous and systematic follow-up health checks on such children? It beggars belief and betrays an astonishingly cavalier attitude to children.
Even more chilling, if that were possible, is the publication of this document on the very same day that the JCVI decided to recommend second vaccine doses for 12-15s.
The opening few bullet points include these gems:
· Myocarditis – significant left ventricular (LV) fibrosis has been described in a high percentage of children admitted to hospital, with a small percentage of these having non-sustained ventricular tachycardia (VT);
· No follow-up data is available yet on hospitalised patients;
· The long-term consequences of this condition secondary to vaccination are yet unknown, so any screening recommendations need to be balanced against the frequency and severity of the disease with the aim to prevent complications, in particular of myocarditis (arrhythmias, long term myocardial damage or heart failure).
The question is also raised as to why would a GP not refer every child or youth with suspected myocarditis or pericarditis to the paediatric team for a full assessment, especially given this is a vaccine still under emergency use authorisation requiring proper post marketing surveillance? Perhaps the government doesn’t want to find too many cases?
Please, please do anything and everything you can to bring this to the attention of parents.
Some 80 per cent of school children* are estimated to have had Covid already and so have nothing to gain from vaccination, only the potential risk of harm.
*MRC Biostatistics Unit’s statistics on infections and deaths, which are updated once a week using ONS data, estimates that 5.53 million 5-14-year-olds in England have had Covid. This is of a total population of 6,975,037.
December 3, 2021
Posted by aletho |
Science and Pseudo-Science, War Crimes | COVID-19 Vaccine, UK |
Leave a comment
You may think that climate science is complicated and that the scientists who are alarmed about climate change know what they are doing. Well, yes and no. The climate is complicated but scientists have bought into some very silly science.
Happily this is all easy to see with no science involved. Seriously, don’t back away. There is no science coming, especially nothing hard. Happily the world’s top alarmists have provided everything we need in a very simple way. Of course they do not see it because they are committed to alarmism. But I will point it out and you can use your own judgement.
Here goes. Globally, climate alarmism is led by the United Nations. Huge sums of money are at stake but that is not the point here, although it does explain much of what is going on. On the science side alarmism is led by the UN’s Intergovernmental Panel on Climate Change, usually just called the IPCC.
“Intergovernmental” sounds like a word you might learn as a joke. In this case it means that the members of this Panel are most of the world’s national governments. Most or maybe all of these governments pay lip service to climate alarmism.
Every five years or so the IPCC puts out a monster report that claims to be an overview of the latest climate science. In reality they just pick the science that best supports alarmism. This year is one of those years and they outdid themselves. Instead of the usual 1,000 page report it is a whopping 4,000 pages. Of course no one in their right mind will read it, but it sure shows how smart they are, right?
Where it gets useful is that there is a 40 page Summary for Policy Makers, which means for ordinary people. Anyone who votes is a policy maker of sorts. It is here that we find the basic scientific arguments for alarmism and they don’t amount to much.
In fact there are just two arguments for alarmism, which occur as two windows in the very first figure. They are labeled figure 1a and 1b. They are easy to describe so you don’t have to look them up. If you want to see them go here: https://www.ipcc.ch/report/ar6/wg1/.
Figure 1a is called the Hockey Stick by skeptics of alarmism (like me). It claims to be the global average temperatures for the last 2,000 years (like we can know that). It is pretty much a flat line until about 150 years ago and this is the hockey stick handle. Then it suddenly shoots up with big rapid warming from then until now, making the hockey stick blade. Handle flat then blade pointing up.
In short they say there was no global warming until we started it 150 years ago. What makes this silly is that there is lots of evidence for two prior periods of warming that may have been just as warm as today’s. These are so well known that they have names — the medieval warm period (when Vikings farmed Greenland) and the Roman warm period (when civilization flourished).
In between there were really cold spells including the little ice age that ended with the recent warming. In fact our warming may be nothing but the natural end to the little ice age.
There are thousands of research reports on these natural periods of warming and cooling but the IPCC simply ignores them. Alarmism depends on the recent warming being unprecedented. Natural warming disappears. Do not look behind the curtain!
So much for the bogus hockey stick. Figure 1b then zooms in on the recent warming, with a fancy variation on the same disappearing act. This time it is about the computer models of climate change, which is where alarmism comes from. It is these silly computer models that say we are causing dangerous global warming, with worse to come.
Figure 1b shows two computer model outputs. Each line is the global temperature over the last 150 years, when the recent warming occurred. One is supposedly the temperature history as it would have been without human interference, the natural history, and the other is the history with human inputs. Guess what? The natural history has no warming, while the human history shows all the warming that has occurred over the period.
The IPCC says this proves all the warming is caused by us humans. What makes this silly is figure 2, which gives the game away. It is a list of all the things in the models that can cause warming. All are human! There are no natural causes.
This means the models are programmed so that only humans can cause warming. Thus what figure 1b really says is “If we assume that only humans can cause long term warming then we find that the long term warming is caused by humans”. This is called circular reasoning because the conclusion is just a restatement of the assumption. It is truly silly.
What is missing of course is just what was missing In the hockey stick, namely nature. There is actually a great deal of research on possible natural causes for some of the long term warming, maybe even all of it. Keep in mind that the recent warming is very small, just around one degree over 150 years. Small changes in the sun, or the ocean, or even just in the clouds, could easily cause this little bit of global warming.
The IPCC simply ignores all this research, just like it ignored the warm and cold periods in the 2,000 year hockey stick. In fact this extreme alarmist bias dominates government funded climate science, which is most of it.
That is really all there is to alarmist science and it sure is silly! No deep scientific mystery. Just assume that everything that happens is our fault, program the computers that way, and let the computer then predict worse to come. Ignore all the research that says otherwise. Ignore the little ice age and the medieval warm period. Ignore natural change even though it is right in front of us.
Ignoring nature is the silly science of climate alarmism.
Reprinted with added stuff from RANGE magazine, Winter 2021/2022 issue. For more information see http://www.rangemagazine.com
December 3, 2021
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | IPCC |
Leave a comment
WaPo : Less than a week after the new omicron variant of the coronavirus was reported to the World Health Organization, global leaders on Wednesday agreed to start negotiations to create an international agreement to prevent and deal with future pandemics — which some have dubbed a “pandemic treaty.” The special session of the World Health Assembly, only the second ever held by the WHO’s governing body, pledged by consensus to begin work on an agreement, amid a round of applause, after three days of talks. “I welcome the decision you have adopted today, to establish an intergovernmental negotiating body to draft and negotiate a WHO convention, agreement or other international instrument on pandemic prevention, preparedness and response,” WHO Director General Tedros Adhanom Ghebreyesus said. The commitment by countries to negotiate a “global accord” would “help to keep future generations safer from the impacts of pandemics,” he added.
The assembly’s decision will see the creation of an “intergovernmental negotiating body” to draft and negotiate the final convention, which would then need to be adopted by member states. … Tedros said omicron “demonstrates just why the world needs a new accord on pandemics,” and called for a “legally binding” agreement.
#
Marc Morano’s comment: “This will be a virus version of the UN IPCC & Paris climate style pacts. The pandemic ‘crisis’ will become permanent just like the ‘climate crisis.’ Attempts to impose lockdowns for future COVID variants or new viruses may be internationally imposed instead of national, state or local. If you don’t like your governor, mayor or school board, you can vote them out, but if a ‘radical’ WHO ‘pandemic treaty’ that is ‘legally binding’ becomes reality, global mandates may be coming your way and local elections will cease to matter as unelected bureaucrats will be yielding the real power over your life, liberty, and pursuit of happiness. This must be stopped now. Even the Washington Post is calling a ‘pandemic treaty’ a ‘radical’ idea.
Once a ‘pandemic treaty’ is set in place, COVID mandates will become permanent as elite officials fly around the world to discuss how to further crush freedom to wage war on viruses. Just like the UN Intergovernmental Panel on Climate Change, the architects of a ‘pandemic treaty’ will seek more and more power and control and become a self-interested lobbying organization all while doing squat to prevent or mitigate future viruses. A ‘radical’ WHO ‘pandemic treaty’ may be just the ticket for the administrative state to reign in rogue anti-lockdown governors like Ron DeSantis.”
December 3, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science | Human rights, WHO |
Leave a comment
I’ve written about vitamin D as a potential treatment for covid-19 a couple of times before. In September of 2020 I wrote about a Spanish randomized trial that showed a massive reduction in ICU admissions in hospitalized patients treated with 25-hydroxyvitamin D (a part-activated form of vitamin D). However, that study had some major weaknesses – it was completely unblinded and it was small. In other words, although the results were promising, they hardly constituted conclusive proof of a benefit.
Then, in January, I wrote about a much larger double-blind Brazilian trial that failed to show any benefit when hospitalized patients were treated with vitamin D. For many in the mainstream medical community, this study constituted conclusive proof that vitamin D is ineffective as a treatment for covid-19. However, participants in the trial weren’t given vitamin D until late in the disease course, and unlike in the previous Spanish study, they were given regular vitamin D, not the part-activated form used in the Spanish study. Since it takes several days for regular vitamin D to become activated and usable by the body, the study was more or less designed to fail from the start – whether intentionally or unintentionally. There was no realistic chance that it was ever going to show a benefit, even if one exists.
So, when I last wrote about vitamin D, in January, it was still unclear whether it had any role in the treatment of covid-19 or not. Well, has anything changed since then?
Let’s start by taking a look at the observational data. Although the randomized trials of vitamin D have been few and far between, there has been a massive amount of observational data produced. In recent months, two meta-analyses of cohort studies have been published that look at the relationship between vitamin D levels and death, one in the journal Nutrients, and another in the Nutrition Journal. For those who are unaware, a meta-analysis is a pooled study, where you take lots of different studies and pool their results together in to one, in order to get more statistically significant results. And a cohort study is a type of observational study in which you take two or more groups that vary in some specific way, such as in their vitamin D levels, and then follow them over time to see if they have different outcomes.
Interestingly, the two meta-analyses reach the exact opposite conclusions, with one claiming that if we can just get everyone up to 50 ng/ml of vitamin D in the blood stream, then we can literally prevent all covid deaths, while the other says that there is no correlation whatsoever between vitamin D levels and covid mortality.
How is this possible?
Well, the first thing to note is that the two meta-analyses vary in terms of which particular studies they include. The Nutrients study performed its data search in March, while the Nutrition Journal study performed its data search in June. This means that the Nutrition Journal meta-analysis had access to a few extra studies, which weren’t available when the first data search was conducted in March.
But that isn’t the whole explanation. The researchers have also used somewhat different search strategies, which means that each includes some studies that the other lacks. In fact, there is amazingly little overlap between the two meta-analyses in terms of which studies are included. Only two of the seven studies in the Nutrients meta-analysis are included in the Nutrition Journal meta-analysis, and only two of the eleven studies in the Nutrition Journal meta-analysis are included in the Nutrients meta-analysis. No wonder they’re able to reach such divergent results!
This really showcases how easy it is to manipulate meta-analyses so that they show what you want them to show, just by choosing the date on which you extract data and by choosing which specific search terms to use. It’s easy to keep modifying search terms slightly until you get a list that includes the studies you want in, and excludes the studies you want out. Which is why we should always be skeptical of meta-analyses, just as we are with other types of studies.
This explains why we saw a similar phenomenon earlier this year, when half the meta-analyses of ivermectin seemed to show massive benefit and the other half seemed to show no benefit whatsoever.
Meta-analyses are often considered to be the pinnacle of evidence based medicine, but considering how easy they are to game, I think that is wrong. I’d rather have a single large, well done study than a meta-analysis that consists of lots of little studies, even if that meta-analysis includes more participants overall. If all scientists were honest, then meta-analyses would be an excellent tool for determining the truth. But since we know that many scientists aren’t honest, their use is far more limited. At the end of the day we all have to do our own due diligence. The only meta-analyses that I trust fully are the ones I do myself, such as one I did earlier this year on ivermectin.
It is interesting to note though, that the Nutrition Journal study, which came to the conclusion that vitamin D had no effect, actually had results that did suggest benefit. All the included studies showed fewer deaths in the group with a higher vitamin D level, although the results were not able to reach statistical significance overall.
So we have one meta-analysis which shows a large benefit, and one which shows a trend towards benefit. Which is encouraging. Of course, these are observational studies, and so can’t really say anything about cause and effect. People with low vitamin D levels probably spend less time outdoors, which means they’re probably less physically active. And they probably consume a different diet from people with high vitamin D levels. Correlation is not causation, and even if a correlation is seen between vitamin D and death from covid in observational studies, that doesn’t mean it’s the vitamin D that’s preventing the deaths.
So, what we need is good data from randomized trials. As mentioned, the data from randomized trials that existed last time I wrote about vitamin D was limited and mixed, with the Spanish study that gave 25-hydroxyvitamin D showing massive benefit, while the Brazilian study that gave regular inactivated vitamin D showed no benefit whatsoever.
Since then, three new randomized trials have been published, one from India, one from Mexico, and one from Saudi Arabia. Unfortunately, all three were small, with the largest of the three only including 87 patients. Additionally, all three gave regular inactivated vitamin D, not the part-activated form that was found to have an effect in the earlier Spanish study. In other words, the new studies don’t add anything on top of the store of knowledge that we already had in January.
So, we’re actually more or less in the same situation that we were in regarding vitamin D back in January. The observational data suggests that there is a benefit to supplementing with regular vitamin D for prophylaxis, which is in line with a systematic review that was published in the British Medical Journal in the pre-covid era, which found that people with low vitamin D levels who supplement daily with vitamin D reduce the frequency of respiratory infections by half. And the limited randomized trial data that exists suggests that the part-activated 25-hydroxyvitamin D formulation can reduce the risk of bad outcomes if given on admission to hospital. But the evidence is still too weak to draw any firm conclusions.
It’s quite shocking that more data isn’t available to answer this question conclusively at this late stage in the pandemic. I do personally think though, based on the evidence that is available, that it makes sense to take a daily vitamin D supplement. 4,000 IU (100 mcg) is a reasonable dose. It’s safe, it’s cheap, it might well help, and it can’t hurt.
December 3, 2021
Posted by aletho |
Deception, Science and Pseudo-Science, Timeless or most popular | Covid-19, Vitamin D |
Leave a comment
German physician-scientists reported Monday that not a single healthy child between the ages of 5 and 18 died of Covid in Germany in the first 15 months of the epidemic.
Not one.
Even including children and adolescents with preexisting conditions, only six in that age range died, the researchers found. Germany is Europe’s largest country, with more than 80 million people, including about 10 million school-age children and adolescents.
Serious illness was also extremely rare. The odds that a healthy child aged 5-11 would require intensive care for Covid were about 1 in 50,000, the researchers found. For older and younger children, the odds were somewhat higher, about 1 in 8,000.
Another eight infants and toddlers died, including five with preexisting conditions. In all, 14 Germans under 18 died of Covid, about one per month. About 1.5 million German children or adolescents were infected with Sars-Cov-2 between March 2020 and May 2021, the researchers found.
“Overall, the SARS-CoV-2-associated burden of a severe disease course or death in children and adolescents is low,” the researchers reported. “This seems particularly the case for 5-11-year-old children without comorbidities.”
The researchers reported their findings in an 18-page paper published to the medrxiv preprint server on Monday.
The data came from a registry Germany established in March 2020 intended to capture all hospitalizations of people under 18 with Covid. All German children’s hospitals, pediatric infectious disease specialists, and pediatric societies were invited to participate.
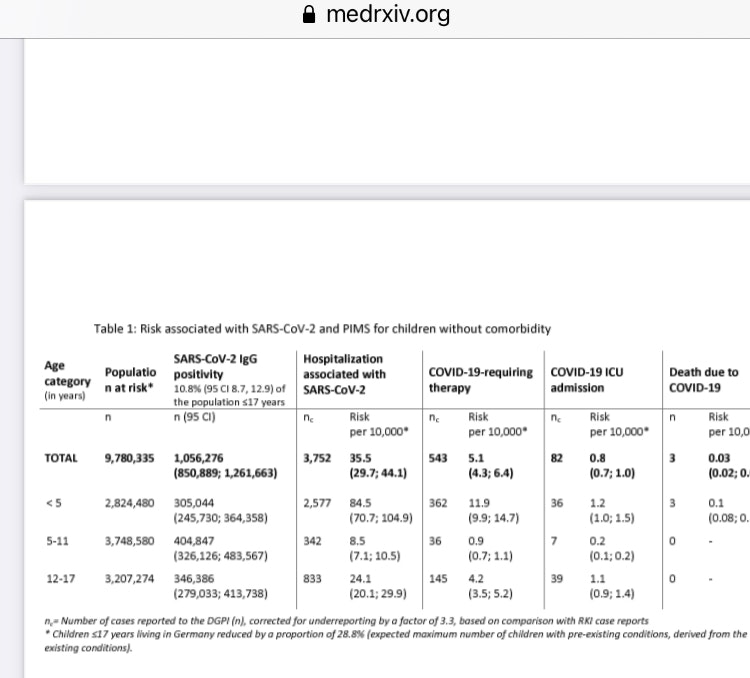
British researchers have posted similar findings, reporting that only six healthy children (including those under 18) out of 12 million died of Covid.
Given the known risks of vaccine-induced myocarditis in young men, the fact that Pfizer tested its mRNA vaccines on barely 3,000 children 5-11 and followed most of them for only weeks after the second dose, the German data again raises the question of how health authorities can possibly justify encouraging children or teenagers to be vaccinated.
But they have.
So parents will have to decide what’s best for their children (at least in those states that bar vaccine fanatics from trying to vaccinate teenagers without parental consent).
December 3, 2021
Posted by aletho |
Civil Liberties, Science and Pseudo-Science | Covid-19, COVID-19 Vaccine, Germany, Human rights |
Leave a comment


 The label for Humira, once the best-selling drug in the world, lists its risks in plain print. One of them, in the label’s own words, is new “autoimmune” disease.


