What is the Number Needed to Vaccinate to prevent a single COVID fatality in kids 5 to 11 based on Pfizer’s EUA application?
And what are the risks that go along with injecting that many kids?
By Toby Rogers | October 31, 2021
Number Needed to Vaccinate (NNTV), the standard policy tool that Pharma, the FDA, & CDC no longer want to talk about
A funny thing happened this afternoon. Not funny as in “haha”. More like funny as in, “ohhhhh that’s how the FDA rigs the process.”
I was reading the CDC’s “Guidance for Health Economics Studies Presented to the Advisory Committee on Immunization Practices (ACIP), 2019 Update” and I realized that the FDA’s woeful risk-benefit analysis in connection with Pfizer’s EUA application to jab children ages 5 to 11 violates many of the principles of the CDC’s Guidance document. The CDC “Guidance” document describes 21 things that every health economics study in connection with vaccines must do and the FDA risk-benefit analysis violated at least half of them.
Today I want to focus on a single factor: the Number Needed to Vaccinate (NNTV). In four separate places the CDC Guidance document mentions the importance of coming up with a Number Needed to Vaccinate (NNTV). I did not recall seeing an NNTV in the FDA risk-benefit document. So I checked the FDA’s risk-benefit analysis again and sure enough, there was no mention of an NNTV.
Because the FDA failed to provide an NNTV, I will attempt to provide it here.
First a little background. The Number Needed to Treat (NNT) in order to prevent a single case, hospitalization, ICU admission, or death, is a standard way to measure the effectiveness of any drug. It’s an important tool because it enables policymakers to evaluate tradeoffs between a new drug, a different existing drug, or doing nothing. In vaccine research the equivalent term is Number Needed to Vaccinate (NNTV, sometimes also written as NNV) in order to prevent a single case, hospitalization, ICU admission, or death (those are 4 different NNTVs that one could calculate).
Pharma HATES talking about NNTV and they hate talking about NNTV even more when it comes to COVID-19 vaccines because the NNTV is so ridiculously high that this vaccine could not pass any honest risk-benefit analysis.
Indeed about a year ago I innocently asked on Twitter what the NNTV is for coronavirus vaccines.

Pharma sent a swarm of trolls in to attack me and Pharma goons published hit pieces on me outside of Twitter to punish me for even asking the question. Of course none of the Pharma trolls provided an estimate of the NNTV for COVID-19 shots. That tells us that we are exactly over the target.
Various health economists have calculated a NNTV for COVID-19 vaccines.
- Ronald Brown, a health economist in Canada, estimated that the NNTV to prevent a single case of coronavirus is from 88 to 142.
- Others have calculated the NNTV to prevent a single case at 256.
- German and Dutch researchers, using a large (500k) data set from a field study in Israel calculated an NNTV between 200 and 700 to prevent one case of COVID-19 for the mRNA shot marketed by Pfizer. They went further and figured out that the “NNTV to prevent one death is between 9,000 and 100,000 (95% confidence interval), with 16,000 as a point estimate.”
You can see why Pharma hates this number so much (I can picture Pharma’s various PR firms sending out an “All hands on deck!” message right now to tell their trolls to attack this article). One would have to inject a lot of people to see any benefit and the more people who are injected the more the potential benefits are offset by the considerable side-effects from the shots.
Furthermore, the NNTV to prevent a single case is not a very meaningful measure because most people, particularly children, recover on their own (or even more quickly with ivermectin if treated early). The numbers that health policy makers should really want to know are the NNTV to prevent a single hospitalization, ICU admission, or death. But with the NNTV to prevent a single case already so high, and with significant adverse events from coronavirus vaccines averaging about 15% nationwide, Pharma and the FDA dare not calculate an NNTV for hospitalizations, ICU, and deaths, because then no one would ever take this product (bye bye $93 billion in annual revenue).
Increased all cause mortality in the Pfizer clinical trial of adults
As Bobby Kennedy noted in personal correspondence with me, Pfizer’s clinical trial in adults showed alarming increases in all cause mortality in the vaccinated :
In Pfizer’s 6 month clinical trial in adults — there was 1 covid death our of 22,000 in the vaccine (“treatment”) group and 2 Covid deaths out of 22,000 in the placebo group (see Table s4). So NNTV = 22,000. The catch is there were 5 heart attack deaths in the vaccine group and only 1 in placebo group. So for every 1 life saved from Covid, the Pfizer vaccine kills 4 from heart attacks. All cause mortality in the 6 month study was 20 in vaccine group and 14 in placebo group. So a 42% all cause mortality increase among the vaccinated. The vaccine loses practically all efficacy after 6 months so they had to curtail the study. They unblinded and offered the vaccine to the placebo group. At that point the rising harm line had long ago intersected the sinking efficacy line.
Former NY Times investigative reporter Alex Berenson also wrote about the bad outcomes for the vaccinated in the Pfizer clinical trial in adults (here). Berenson received a lifetime ban from Twitter for posting Pfizer’s own clinical trial data.
Pfizer learned their lesson with the adult trial and so when they conducted a trial of their mRNA vaccine in children ages 5 to 11 they intentionally made it too small (only 2,300 participants) and too short (only followed up for 2 months) in order to hide harms.
Estimating an NNTV in children ages 5 to 11 using Pfizer’s own clinical trial data
All of the NNTV estimates above are based on data from adults. In kids the NNTV will be even higher (the lower the risk, the higher the NNTV to prevent a single bad outcome). Children ages 5 to 11 are at extremely low risk of death from coronavirus. In a meta-analysis combining data from 5 studies, Stanford researchers Cathrine Axfors and John Ioannidis found a median infection fatality rate (IFR) of 0.0027% in children ages 0-19. In children ages 5 to 11 the IFR is even lower. Depending on the study one looks at, COVID-19 is slightly less dangerous or roughly equivalent to the flu in children.
So how many children would need to be injected with Pharma’s mRNA shot in order to prevent a single hospitalization, ICU admission, or death?
Let’s examine Pfizer’s EUA application and the FDA’s risk-benefit analysis. By Pfizer’s own admission, there were zero hospitalization, ICU admissions, or deaths, in the treatment or control group in their study of 2,300 children ages 5 to 11.
So the Number Needed to Vaccinate in order to prevent a single hospitalization, ICU admission, or death, according to Pfizer’s own data, is infinity. ∞. Not the good kind of infinity as in God or love or time or the universe. This is the bad kind of infinity as in you could vaccinate every child age 5 to 11 in the U.S. and not prevent a single hospitalization, ICU admission, or death from coronavirus according to Pfizer’s own clinical trial data as submitted to the FDA. Of course Pfizer likes this kind of infinity because it means infinite profits. [Technically speaking the result is “undefined” because mathematically one cannot divide by zero, but you get my point.]
Estimating an NNTV and risk-benefit model in children ages 5 to 11 using the limited data that are available
Everyone knows that Pfizer was not even trying to conduct a responsible clinical trial of their mRNA shot in kids ages 5 to 11. Pfizer could have submitted to the FDA a paper napkin with the words “Iz Gud!” written in crayon and the VRBPAC would have approved the shot. They are all in the cartel together and they are all looking forward to their massive payoff/payday.
But let’s not be like Pharma. Instead, let’s attempt to come up with a best guess estimate based on real world data. Over time, others will develop a much more sophisticated estimate (for example, Walach, Klement, & Aukema, 2021 estimated an NNTV for 3 different populations based on “days post dose”). But for our purposes here I think there is a much easier way to come up with a ballpark NNTV estimate for children ages 5 to 11.
Here’s the benefits model:
- As of October 30, 2021, the CDC stated that 170 children ages 5 to 11 have died of COVID-19-related illness since the start of the pandemic. (That represents less than 0.1% of all coronavirus-related deaths nationwide even though children that age make up 8.7% of the U.S. population).
- The Pfizer mRNA shot only “works” for about 6 months (it increases risk in the first month, provides moderate protection in months 2 through 4 and then effectiveness begins to wane, which is why all of the FDA modeling only used a 6 month time-frame). So any modeling would have to be based on vaccine effectiveness in connection with the 57 (170/3) children who might otherwise have died of COVID-related illness during a 6-month period.
- At best, the Pfizer mRNA shot might be 80% effective against hospitalizations and death. That number comes directly from the FDA modeling (p. 32). I am bending over backwards to give Pfizer the benefit of considerable doubt because again, the Pfizer clinical trial showed NO reduction in hospitalizations or death in this age group. So injecting all 28,384,878 children ages 5 to 11 with two doses of Pfizer (which is what the Biden administration wants to do) would save, at most, 45 lives (0.8 effectiveness x 57 fatalities that otherwise would have occurred during that time period = 45).
- So then the NNTV to prevent a single fatality in this age group is 630,775 (28,384,878 / 45). But it’s a two dose regimen so if one wants to calculate the NNTV per injection the number doubles to 1,261,550. It’s literally the worst NNTV in the history of vaccination.
If you inject that many children, you certainly will have lots and lots of serious side effects including disability and death. So let’s look at the risk side of the equation.
Here’s the risk model:
- Because the Pfizer clinical trial has no useable data, I have to immuno-bridge from the nearest age group.
- 31,761,099 people (so just about 10% more people than in the 5 to 11 age bracket) ages 12 to 24 have gotten at least one coronavirus shot.
- The COVID-19 vaccine program has only existed for 10 months and younger people have only had access more recently (children 12 to 15 have had access for five months; since May 10) — so we’re looking at roughly the same observational time period as modeled above.
- During that time, there are 128 reports of fatal side effects following coronavirus mRNA injections in people 12 to 24. (That’s through October 22, 2021. There is a reporting lag though so the actual number of reports that have been filed is surely higher).
- Kirsch, Rose, and Crawford (2021) estimate that VAERS undercounts fatal reactions by a factor of 41 which would put the total fatal side effects in this age-range at 5,248. (Kirsch et al. represents a conservative estimate because others have put the underreporting factor at 100.)
- With potentially deadly side effects including myo- and pericarditis disproportionately impacting youth it is reasonable to think that over time the rate of fatal side effects from mRNA shots in children ages 5 to 11 might be similar to those in ages 12 to 24.
So, to put it simply, the Biden administration plan would kill 5,248 children via Pfizer mRNA shots in order to save 45 children from dying of coronavirus.
For every one child saved by the shot, another 117 would be killed by the shot.
The Pfizer mRNA shot fails any honest risk-benefit analysis in children ages 5 to 11.
Even under the best circumstances, estimating NNTV and modeling risk vs. benefits is fraught. In the current situation, with a new and novel bioengineered virus, where Pfizer’s data are intentionally underpowered to hide harms, and the FDA, CDC, & Biden Administration are doing everything in their power to push dangerous drugs on kids, making good policy decisions is even more difficult.
If the FDA or CDC want to calculate a different NNTV (and explain how they arrived at that number) I’m all ears. But we all know that the FDA refused to calculate an NNTV not because they forgot, but because they knew the number was so high that it would destroy the case for mRNA vaccines in children this age. Your move CDC — your own Guidance document states that you must provide this number.
The Vaccines Cannot Do What Is Asked of Them
eugyppius | November 1, 2021
Increasingly, politicians and medical bureaucrats are entranced by a bizarre pandemic ideology. Like most ideologies, it remains oblivious to evidence and argument, holding that the risk of severe outcomes from Corona infection is far more evenly distributed across the population than it is; and allowing only universal solutions, such as quarantining and vaccinating entire populations. These obtuse views, which just won’t go away, are at the root of our failed and destructive policies. For 20 months now, this pandemic ideology has blinded everyone in charge to the possibility of shielding the vulnerable, leveraging seasonal patterns in infection, and leaving the kids alone. The stratified nature of Corona risk is the key to unravelling the pandemic, and it’s the one thing nobody will recognise.
Success in the pandemic has come to be defined by a series of vague, poorly differentiated statistics, including above all Corona infections, hospitalisations and deaths, and now vaccination rates. In their exclusive focus on these numbers, the press propagate constantly the myth that this is all there is to know about Corona. This impoverished discussion drives bureaucrats and politicians to seek solutions for one vague meaningless metric (Corona ICU admissions) in another vague meaningless metric (vaccination rates). In this way their policies are constructed in a rhetorical world that has very little to do with what is actually happening.
Every day our understanding of what the vaccines can do becomes clearer. It’s not nothing, but it’s much less than we were promised.
Some of our best evidence so far comes from this Swedish retrospective cohort study, which tracks outcomes in 1,684,958 individuals (matched vaccinated and unvaccinated pairs) from 12 January to 4 October 2021. It has been around the block, with an especially good analysis by El Gato Malo, so there’s no point in anything more than a brief review here.
Above all, they find that the vaccines provide temporary protection against infection:

Unfortunately, this protection likely falls below zero – into the zone of negative efficacy – after 7 to 9 months. This is one of multiple lines of evidence confirming that the vaccinated, sooner or later, achieve higher rates of infection than the unvaccinated. According to me, even early vaccine efficacy is likely overstated in studies like these. Probably the vaccinated are always highly vulnerable to infection, but they’re not tested as rigorously and at first their symptoms are so mild as to be nearly unnoticeable. SARS-2 nevertheless lurks among them, mostly undetected, until vaccine protection against overt disease dissipates.
This would explain what happened in Iceland over the summer: A bunch of freshly vaccinated Icelanders went on holiday in the UK, where they promptly picked up SARS-2 and brought the latest Delta update back home with them. In the following weeks, energetic Icelandic testing uncovered rates of infection almost as high in the vaccinated as in the unvaccinated – and this well before we would’ve expected the vaccines to have faded.
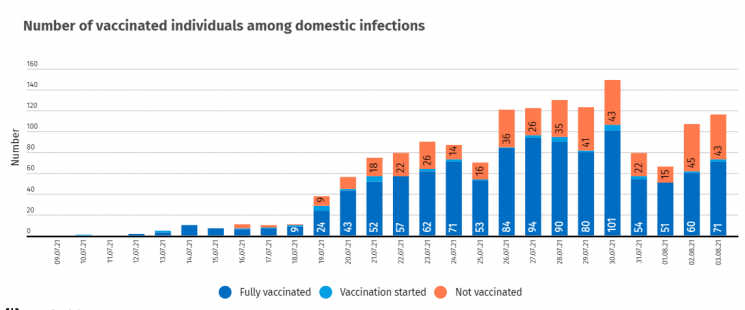
The Swedish study finds that efficacy against severe disease last longer, but also decays substantially in much the same way:
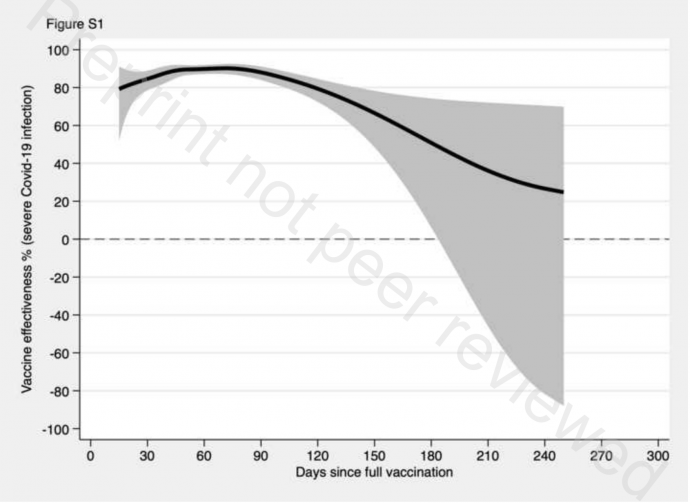
After the 240-day mark, protection against severe outcome is not even at 30%. The decay is most rapid among men, the old and frail, and those with comorbidities – precisely those subpopulations already at greatest risk of severe disease.
So those are the benefits, but as in everything there are also costs – and here they turn out to be substantial.
We’ve already touched on one: The vaccines appear to induce negative efficacy against infection. This probably arises from a combination of minimally symptomatic super-spreading among the vaccinated, the selective pressure that vaccine-elicited antibodies place upon the virus, and the narrow immunity against an obsolete arrangement of the spike protein that the vaccines confer. For a period of several weeks after dose 1 (and likely dose 3), they also make the vaccinated more susceptible to infection, and mass vaccination campaigns have induced case spikes across many countries.
By now it is also clear that the vaccines cause a range of adverse reactions. The best documented is myocarditis in young men, a side effect observed most frequently after dose 2 of the mRNA vaccines. We probably won’t know the true rate of vaccine-induced myocarditis for many years. From excess mortality in younger cohorts and many anecdotal media reports, we can surmise that it is much more common than anybody will admit.
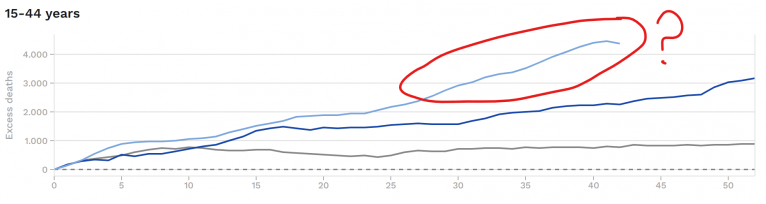
It does not take a Ph.D. in public health to extract a sensible vaccination policy from all this:
1. There is just no question that vaccinating low-risk cohorts (including the recovered) is not only pointless, but also dangerous. These aren’t the people who end up in the hospital dying of Corona anyway. And because the vaccinated sooner or later end up driving transmission, there is only downside and no upside here.
2. All the vaccines are good for, is reducing the likelihood of severe disease among the old and the vulnerable. It follows that only the old and the vulnerable should be vaccinated.
3. In these groups, carefully timed annual vaccinations, like flu shots, might well provide good protection at the height of the winter coronavirus season and limit mortality. Even here, though, you’d have to proceed carefully, to avoid causing case spikes in the newly vaccinated during that brief period where their vulnerability to infection is heightened.
Of course, this is the opposite of what our pandemic ideology permits. Instead, almost all of our governments deploy the vaccines in the most reckless and counterproductive ways possible.
The southern districts of Bavaria are quickly becoming the regions of highest infection in Germany, and Markus Söder, our governor, is demanding a renewed “vaccine push,” including a campaign for booster doses “independently of age,” even obliquely threatening lockdown if we can’t ensure the “safety and stability” of hospitals.
These are exactly the kinds of crackpot universalist solutions that have failed for the past twenty months, and that will do nothing to unburden our healthcare facilities, and very likely end up swamping them with unnecessary patients.
If booster doses are a good idea for anyone – and it’s far from clear they are – it’s frail nursing home residents, most of whose vaccinations are now well past their expiration date, and who are once again beginning to die of SARS-2 just as they did last fall. Vaccinating children and triple vaccinating low-risk adults won’t prevent nursing home deaths, and it will do very little to keep our hospitals “safe,” because the vaccines don’t reduce spread and these people rarely end up in hospital. What is worse, ever newer pushes to vaccinate all hospital personnel and nursing home staff threaten to introduce vaccinated super-spreaders into these sensitive environments. Söder will continue to pound the table demanding ever harsher restrictions for the unvaccinated and more vaccine doses for the already-vaccinated, all while deaths and hospitalisations continue to climb.
Ultimately, the great problem with our vaccine policies, as with our lockdowns, arises from the fact that they don’t work. Because lockdowns and vaccination campaigns are powerless to remove the conditions that brought them about, you can never stop locking down, and you can never stop vaccinating – even as your policies turn out to do worse than nothing.
Blood Clots Associated with Johnson & Johnson COVID Shot
By Dr. Joseph Mercola | November 2, 2021
Researchers at Mayo Clinic have published a study in JAMA showing that there is a 3.5 times higher risk of getting brain blood clots if you take the Astra Zeneca or Johnson & Johnson COVID-19 shots.
Reported incidents of cerebral venous sinus thrombosis (CVST) after the jabs were what instigated a temporary pause in their rollout in April 2021. The researchers used data from the CDC’s Vaccine Adverse Event Reporting System (VAERS) to compare to data compiled in a Minnesota county from 2001 to 2015.
Study authors said women appeared to be more affected than men, although they couldn’t ascertain why. “Most CVST events occurred within 15 days after vaccination, which is likely the highest at-risk period,” they added. ‘The postvaccination CVST rate among females was higher than the prepandemic rate among females. The highest risk was among women aged 30 to 49 years.”
Is it Really True, as Climate Change Activists Claim, That 97% of Scientists Agree With Them?
By Luke Perry • The Daily Sceptic • October 27, 2021
Our Government is imposing draconian limitations on our lifestyles, our economy and our finances in order to achieve net zero carbon emissions to supposedly save the planet from catastrophic anthropogenic global warming (CAGW), now renamed as climate change. Probably one of the most repeated arguments you’ll hear, over and over again, in support of the need to achieve net zero is that “97% of scientists agree CAGW is happening”.
Former President Barack Obama is just one of many who have made this claim: “97% percent of scientists agree: climate change is real, man-made and dangerous.”
So did President Joe Biden’s Special Presidential Envoy for Climate, John Kerry, when he warned of the “crippling consequences” of climate change and that: “97% percent of the world’s scientists tell us this is urgent.”
This claim is widely accepted. Yet, in spite of the damaging effects reaching net zero will have on Western economies, not a single politician or journalist seems to have made the effort to find out where this ‘97%’ figure came from and how accurate it actually is.
Statistical smoke and mirrors?
The main author of the paper which came up with the famous 97% figure was an Australian former web programmer and blogger who later gained a PhD in Philosophy at the School of Psychology, University of Western Australia and then founded what could be seen as a climate alarmist website.
He assembled a group of volunteers as part of a ‘citizen science’ project and tasked them with”‘examining 11,944 climate abstracts from 1991-2011 matching the topics ‘global climate change’ or ‘global warming’”. Note that the volunteers didn’t read the actual scientific papers, they just looked at the abstracts – a summary paragraph or two describing what was in the papers. The volunteers then classed the abstracts into one of seven categories according to their opinions of Anthropogenic Global Warming (AGW):
1. Explicit endorsement of AGW with quantification
2. Explicit endorsement of AGW without quantification
3. Implicit endorsement of AGW
4. No position or Uncertain
5. Implicit rejection of AGW
6. Explicit rejection of AGW without quantification
7. Explicit rejection of AGW with quantification
The reviewers then ‘simplified’ results into four main categories as follows:
Endorse AGW 3,896 32.6% of abstracts
No AGW position 7,930 66.4% of abstracts
Reject AGW 78 0.7% of abstracts
Uncertain on AGW 40 0.3% of abstracts
So, this gave only 32.6% who, the reviewers concluded, endorsed AGW. This was clearly not quite the stunning super-majority of 97% which the study claimed to have identified. Now comes the clever bit. Instead of admitting that just 32.6% of papers (actually just abstracts of papers) endorsed AGW, the group decided to remove all the 7,930 abstracts which didn’t take a position on AGW. Then, hey presto, magic happened. That left just 4,014 abstracts of which 3,896 (97%) supposedly ‘endorsed’ AGW.
But that’s not the end of the magic employed to reach that wondrous 97%. The reviewers decided to lump together three categories of abstracts – Explicit endorsement with quantification; Explicit endorsement without quantification and Implicit Endorsement. But in the paper claiming 97% support for AGW, the reviewers don’t tell us how many papers fitted into each of these three categories. An independent researcher managed to get hold of the original data file and claimed to have found that in 3,896 abstracts which supposedly ‘endorsed’ AGW, just 64 were in the Explicit endorsement with quantification category; 922 were in the Explicit endorsement without quantification; and the vast majority – 2,910 (out of 3,896) – were in the Implicit endorsement of AGW category. Deciding from an abstract of a scientific article that the article ‘implicitly’ supports AGW is a bit like walking down a high street and deciding you know how people will vote based purely on looking at the kind of clothes they wear. To propose this as a serious survey is beyond ludicrous.
Thus, if this independent researcher’s figures are accurate, when you dig down into how the ‘97% of scientists’ figure was actually conjured up, you find that only 986 of 11,944 – that’s just 8.2% – of abstracts actually explicitly said they agreed with the theory of man-made global warming. And that’s clearly not the kind of figure the apocalypse-threatening climate catastrophists would really want to publicise too widely.
So, this ‘97% of scientists’ claim is based on about 11 to 12 volunteers, whose scientific credentials have not (as far as I know) been released and all of whom were probably firm AGW believers, each having to look at around 1,000, often quite obtuse, scientific abstracts. During this review, they decided whether they thought the scientific papers (which they hadn’t read as they had only looked at the abstracts) explicitly or implicitly supported the AGW theory. To claim such an approach is statistically valid is beyond farcical. Given the damage reaching net zero will do to our economies and our lives, it is beyond incredible that not a single politician, mainstream-media journalist or editor seems to have had either the ability or the inclination to expose the more than dubious origins of the almost ubiquitous ‘97% of scientists endorse AGW’ claim.
Tech investor Peter Thiel criticizes “Ministry of Truth” and creation of “fake consensus”
By Cindy Harper | Reclaim The Net | November 2, 2021
During the National Conservatism Conference, held on October 31, tech billionaire Peter Thiel warned against “centralized misinformation” because it creates a “fake consensus.”
Thiel asserted that the centralized misinformation problem is responsible for the silencing of debate on important issues such as inflation of the American economy, COVID-19, and the presence of US troops in Afghanistan.
In his speech, Thiel gave examples of what he described as the “incredible derangement of various forms of thought.” He referenced Stanford’s professor Jay Bhattacharya’s experience. Pictures of the professor were plastered all over the school because he spoke against masks.
He said: “When you have to call things science, you know they aren’t – like climate science or political science,” Epoch reported.
According to Thiel, such excessive dogmatism is the reason for the failed policies by the US government in Afghanistan for more than twenty years.
The PayPal co-founder went on to say that the US is currently experiencing a “runaway, non-transitory inflation” and the “complete bankruptcy of the Fed” because of the inability to tolerate differing ideas and opinions that are unpopular.
“If there’s a misinformation problem, it’s a centralized misinformation problem—and it’s the misinformation coming from the Ministry of Truth,” said Thiel.
FDA approves Pfizer jab for kids, but even they don’t seem sure it’s safe
By Helen Buyniski | RT | November 1, 2021
American children have no choice but to act as experimental test subjects for the Pfizer Covid-19 vaccine to determine the jab’s safety, the Food and Drug Administration has apparently concluded. Good luck, kids!
“We’re never going to learn about how safe the vaccine is unless we start giving it,” editor of the New England Journal of Medicine and Harvard adjunct professor Eric Rubin argued last week, his words buried within the eight-hour barrage of presentations and discussions that swirled around the FDA advisory panel’s approval of the mRNA jab for children aged five to 11.
The FDA followed up on the advisory panel’s 17-0 recommendation with approval, as it typically does, on Friday. If the Centers for Disease Control and Prevention follows suit, some 28 million American children will be quickly served up as fresh-faced fodder for a smaller dose of the Covid-19 vaccine already poised to inject some 100 million American adults. That is, as soon as President Joe Biden is able to whip up a legally-binding demand he can submit to the Occupational Safety and Health Administration.
Friday’s FDA approval means only the CDC stands between American children and a warp-speed rollout of the Pfizer jab. However, the rush to approval doesn’t necessarily mean there are no concerns. A disturbingly large portion of the FDA committee’s members are connected to Pfizer in some way or another, leading vaccine skeptics to cry foul. Meanwhile, a growing portion of the country continues to denounce the mandates in general, insisting everyone should be able to make their own decision regarding whether or not they wish to get injected.
Echoing the newly-reanimated pro-choice slogan, mandate protesters recently swarmed the Brooklyn Bridge declaring ‘My body, my choice’ as New York City employees faced the potential loss of their jobs as firefighters, police officers, sanitation handlers, and corrections officers due to Mayor Bill de Blasio’s insistence that all municipal employees get vaxxed or be relegated to the purgatory of open-ended unpaid leave.
The FDA’s effort to put the cart so far in front of the horse mirrored the words of House Speaker Nancy Pelosi during the congressional tug-of-war over Obamacare in 2010. Faced with a phonebook-sized, dubiously-legal bill unlike anything Congress had passed before and no realistic timeframe to wrangle with the details, Pelosi suggested Congress would have to “pass the bill to find out what’s in it, away from the fog of controversy.”
Since then, legislation by brute force has only grown as the means by which laws are passed in the US, as ever-more-polarized parties refuse to give an inch and betray the appearance of weakness. Allowing the ‘other side’ to be seen as achieving even the slightest victory is unconscionable, and that framework remains in place in the vaccination arena – where it makes less sense than anywhere else.
After all, it was former President Donald Trump’s Operation Warp Speed that brought the world the Pfizer shot, even if the jab itself wasn’t rolled out until shortly (some would say deliberately) after the 2020 election and vaccine mandates have since become a cause celebre of the Democratic Party.
With half the US up in arms about the other half’s supposed refusal to roll up its sleeves and submit to an intensely politicized needle, anyone who hesitates is denounced posthaste in a 21st-century witch hunt – to be fired, if not set on fire; outfitted with the scarlet A for anti-vaxxer, not adulteress; and otherwise chased out of the public square – deplatformed from Twitter, YouTube and Facebook, if not chased physically with pitchforks and torches. Similar divisions have erupted across Europe, and countries like Italy and France have pushed the issue even further, barring the unvaccinated from so much as entering grocery stores to buy food.
While the US study of the Pfizer vaccine’s effects on children five to 11 failed to turn up any deadly side effects, critics argued its population size was too small to be effective for such a purpose. Parents of some jab recipients have observed disturbing symptoms in their offspring in the hours and days following the shots and filmed heartbreaking testimonials describing their downfall from healthy children to pain-wracked perma-patients experiencing near-constant seizures, facial distortions, debilitating heart problems, or other dire health issues.
Another doctor on the FDA committee, Michael Kurilla of the National Institutes of Health, abstained from voting on recommending Pfizer-BioNTech’s vaccine entirely, citing a lack of evidence that all children need the shot, and while Kurilla, an infectious disease and pathology expert, was the only panel member to abstain from voting, he was not the only member to openly express misgivings about doling out the jab to young Americans. His colleague, Dr. Cody Meissner of Tufts University, suggested that it would be an “error” to mandate the jab for children to return to school until there was more hard data.
“We simply don’t know what the side effects are going to be,” he said, acknowledging the shot – like its adult equivalent – probably wouldn’t prevent transmission of the virus. While he was not opposed to administering the shot to certain vulnerable subgroups inside the 5-11 age group, Meissner was concerned approving the shot for everyone in that category would lead to a heavy-handed mandate the likes of which is currently being wielded against American adults.
Children who receive the Pfizer-BioNTech jab may actually get less immunity and face more risk than supplied by getting and recovering from a current strain of Covid-19, Kurilla told the Daily Mail, referring to the Delta variant and other current strains of Covid-19 circulating among the population. “The question really becomes, does this vaccine offer any benefits to them at all?” he asked rhetorically during the FDA committee meeting. He would have voted ‘yes’ if the FDA had merely proposed opening up access to the vaccine to a ‘subset’ of those ages five to 11, but he disagreed with administering it to all children within that age group.
Two other panel members voted to approve despite their misgivings. Meissner argued that a “very small percent of otherwise healthy six-to-11-year-old children…might derive some benefit,” while President and CEO of Meharry Medical College James Hildreth agreed that “vaccinating all of the children…seems a bit much for me,” pointing to the relatively low risk of hospitalization and near-zero risk of death by Covid-19 for children.
Speaking up against the jab, even circumstantially, has become the kiss of death in the medical community, with even medical rock stars like Robert Malone, one of the inventors of mRNA as a drug, cast into the dustbin of history for expressing skepticism that his invention was being incorrectly used to deliver the Covid-19 vaccine.
However, governments worldwide are setting themselves up for civil war as populations are forced to choose one ‘side’ or another. Even many of the vaccinated have acknowledged that the jab should not be forced on anyone, while entire industries like shipping, air travel, defense, and the like grind to a halt as mandates run up against the stubborn will of their employees. Southwest Airlines was allegedly forced to cancel thousands of flights earlier this month, due to a reported mass ‘sickout’ by air traffic controllers unwilling to get vaxxed, though the airline itself has denied this, and rumors of trucker strikes from Australia to America have food sellers panicking at the thought of empty shelves.
As it stands, parents who were willing to submit themselves to experimental shots in the name of convenience and retaining employment may not be so willing to offer up their children as sacrifices to a company once denounced by the US Justice Department as the worst fraudster in the pharmaceutical industry.
Governments that have shown themselves as profoundly untrustworthy throughout the Covid-19 pandemic are unlikely to change their behavior at the last minute, and parents are wise to take care in where they place their trust.
Media Kinda-Sorta Forgets to Mention Doctor’s $2 Million From Pfizer

By Dr. Joseph Mercola | November 02, 2021
A Canadian doctor pushing COVID-19 vaccine shots for children ages 5 years and up who’s been featured in numerous media reports received nearly $2 million in Pfizer funding for vaccine research.
Whether it was intentional or if the media kinda-sorta forgot to mention the conflict, or if they simply didn’t bother doing their own research before using Dr. Jim Kellner as a lead adviser on the COVID shot isn’t clear. But what is clear is that Pfizer has given the University of Calgary professor and pediatrician $1.9 million, with $787,004 of it still being allocated until 2022.
Kellner didn’t attempt to hide his conflict of interest; it’s easily found in his publicly posted curriculum vitae, with the current funding explicitly stated.
Yet, according to True North news, “Kellner’s name turns up over 41 times and appears in numerous videos and articles on the topic of vaccination without any indication of how much money he has received from the vaccine manufacturer Pfizer.”
Useless Green Energy Hitting The Wall
By Francis Menton | Manhattan Contrarian | October 13, 2021
In the field of litigation settlements, people sometimes talk about a “win, win” scenario — a settlement structure where both sides can get some advantage and simultaneously claim victory. By that criterion, what is “green” energy (aka intermittent wind and solar power)? The public pays hundreds of billions of dollars of subsidies to get the things built, and in return it gets: sudden shortages and soaring prices for coal, oil, gas and electricity; and dramatically reduced reliability of the electrical grid, leading to periodic blackouts and risks of many more of same; and despite it all fossil fuel use doesn’t go down. It’s a “lose, lose, lose.”
As the world comes out of the pandemic and the international economy returns to attempting to fulfill normal consumer demand, you can see green energy hitting the wall pretty much everywhere you look. It’s just a question of which data points you want to collect for a day’s entertainment.
The current energy crisis in Europe and Asia is of course getting next to no coverage in the U.S. media. But over at Bloomberg News they have a big story on October 4. That’s Bloomberg News as in Mike Bloomberg — the man with four private jets and at least ten houses who devotes his public life to hectoring you to cut your “carbon footprint.” But now suddenly the Bloomberg News people seem to have figured out that periodic energy crises are an inevitable consequence of increasing reliance on the undependable wind and sun. The headline of the article is “Global Energy Crisis Is the First of Many in the Green Power Era.” The Bloomberg piece itself is behind paywall, but extensive excerpts can be found at Climate Depot, where they call it a “moment of clarity”:
The next several decades could see more periods of energy-driven inflation, fuel shortages and lost economic growth as electricity supplies are left vulnerable to shocks.. . . . The world is living through the first major energy crisis of the clean-power transition. It won’t be the last. . . . Wind and solar power production have soared in the last decade. But both renewable sources are notoriously fickle — available at some times and not at others. And electricity, unlike gas or coal, is difficult to store in meaningful quantities. That’s a problem, because on the electrical grid, supply and demand must be constantly, perfectly balanced. Throw that balance out of whack, and blackouts result.
No kidding.
Meanwhile, the latest place to get hit with blackouts due to an unreliable grid is China. (Previous rounds of blackouts traceable to over-reliance on unreliable wind and/or solar power have hit South Australia in 2016, California in 2020, and Texas in February this year.). From the New York Times, September 27:
Power cuts and even blackouts have slowed or closed factories across China in recent days, adding a new threat to the country’s slowing economy and potentially further snarling global supply chains ahead of the busy Christmas shopping season in the West. The outages have rippled across most of eastern China, where the bulk of the population lives and works.
But didn’t the same New York Times just tell us on October 8 that China is “the world leader” in both solar power and wind power? Somehow, neither of those seems to help when electricity demand suddenly ramps up. Just yesterday the Guardian reported that the recent power chaos is causing China to re-emphasize what they call “energy security,” which the Guardian takes to mean fossil fuels, particularly coal:
China plans to build more coal-fired power plants and has hinted that it will rethink its timetable to slash emissions. . . . In a statement after a meeting of Beijing’s National Energy Commission, the Chinese premier, Li Keqiang, stressed the importance of regular energy supply, after swathes of the country were plunged into darkness by rolling blackouts that hit factories and homes. While China has published plans to reach peak carbon emissions by 2030, the statement hinted that the energy crisis had led the Communist party to rethink the timing of this ambition, with a new “phased timetable and roadmap for peaking carbon emissions”. . . . “Energy security should be the premise on which a modern energy system is built and and the capacity for energy self-supply should be enhanced,” the statement said.
Over in the UK, somebody has now finally taken the time to do a calculation of how much it would cost to provide sufficient battery storage to get the country through an extended (ten day) period of dark and calm in the winter, assuming a grid relying 100% on wind and solar generation. The calculation has been made by Professors Peter Edwards and Peter Dobson of Oxford University, and Gari Owen of Annwvyn Solutions, on behalf of Net Zero Watch, which is a project of the Global Warming Policy Foundation. (Full disclosure: I serve on the board of the American affiliate of this organization.). The answer that Edwards, Dobson and Owen come up with is approximately 3 trillion British pounds. For comparison, UK GDP in 2020 was just under 2 trillion British pounds. And if you look at the Edwards/Dobson/Owen calculation, you will realize that they assume zero loss of energy on the round trip into and out of the batteries. That’s rather a favorable assumption, given that in practice an all-wind-and-solar system would need to store power all the way from the summer to the winter. What percentage of your cell phone’s battery charge is left if you leave the device unplugged on the shelf for six months? But then, it’s all fantasy anyway, so what does it matter?
And finally, the Department of Energy’s Energy Information Agency has just (October 6) come out with its annual International Energy Outlook. This is the sage projection of our wisest gurus of how the production and consumption of energy will change over the three decades from now until 2050. Surely then these guys will show us how the world will achieve the true path to Net Zero carbon emissions within that time frame, if not much sooner.
OK, then, here is the key chart:
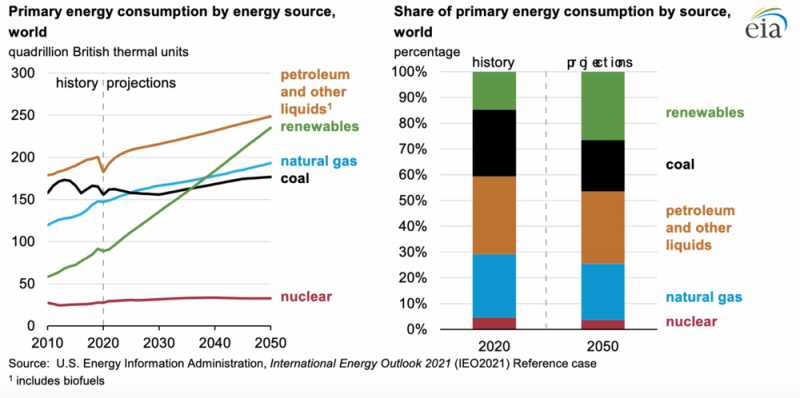
Wait a minute! Could they really be saying that, rather than being on a path to oblivion, all major fossil fuel categories (petroleum, natural gas and coal) will continue to see increased usage right on through 2050, and with no indication that any decline will have begun even then? Yes, that is exactly what they are saying. Indeed the projected increases in consumption of two of those fuels are quite dramatic — up in the range of 50% for natural gas and 40% for petroleum. Yes, so-called “renewables” are projected to increase dramatically; but after thirty years of this, they will still, according to EIA, provide only about 25% of “primary energy consumption,” which is less than petroleum alone, and barely a third of the combined contribution of petroleum, natural gas and coal.
But don’t worry, prices for gasoline and electricity will increase by a multiple, and we’ll have regular blackouts.
Climate change fueled witch hunts… Then and now

By Gregory Wrightstone | CO2 Coalition | October 29, 2021
European witch hunts of the 15th to 17th centuries targeted witches that were thought to be responsible for epidemics and crop failures related to declining temperatures of the Little Ice Age. A belief that evil humans were negatively affecting the climate and weather patterns was the “consensus” opinion of that time. How eerily similar is that notion to the the current oft-repeated mantra that Man’s actions are controlling the climate and leading to catastrophic consequences?

The first extensive European witch hunts coincided with plunging temperatures as the continent transitioned away from the beneficial warmth of the Medieval Warm Period (850 to 1250 AD). Increasing cold that began in the 13th century ushered in nearly five centuries of advancing mountain glaciers and prolonged periods of rainy or cool weather. This time of naturally-driven climate change was accompanied by crop failure, hunger, rising prices, epidemics and mass depopulation.
Large systematic witch hunts began in the 1430s and were advanced later in the century by an Alsatian Dominican friar and papal Inquisitor named Heinrich Kramer. At Kramer’s urging, Pope Innocence VIII issued an encyclical enshrining the persecution and eradication of weather-changing witches through this papal edict. The worst of the Inquisition’s abuses and later systemic witch hunts were, in part, empowered by this decree.
This initial period of cooler temperatures and failing crops continued through the first couple of decades of the 16th century, when a slight warming was accompanied by improvements in harvests. Clearly, the pogrom against the weather-changing witches had been successful!
Unfortunately for the people of the Late Middle Ages, the forty years or so of slight warming gave ground to a more severe bout of cooling. The summer of 1560 brought a return of coldness and wetness that led to severe decline in harvest, crop failure and increases in infant mortality and epidemics. Bear in mind that this was an agrarian subsistence culture, nearly totally dependent on the yearly harvest to survive. One bad harvest could be tolerated, but back-to-back failures would cause horrific consequences, and indeed they did.
 Of course, the people’s misfortunes were attributed to weather-changing witches who had triggered the death-dealing weather, most often in the form of cold, rain, frost and devastating hailstorms. Horrific atrocities were alleged of the witches, including Franconian witches who “confessed” to flying through the air to spread an ointment made of children’s fat in order to cause a killing frost. Across the continent of Europe, from the 15th to the 17th centuries there were likely many tens of thousands of supposed witches burnt at the stake, many of these old women living without husbands on the margins of society.
The worst of the witch hunts occurred during the bitter cold from 1560 to about 1680. The frenzy of killing culminated in the killing of 63 witches in the German territory of Wiesensteig in the year 1563 alone. Across Europe, though, the numbers of witches continued to increase and peaked at more than 500 per year in the mid-1600s. Most were burned at the stake; others were hung.
The end of the witch hunts and killings tie closely to the beginning of our current warming trend at the close of the 17th century. That warming trend started more than 300 years ago and continues in fits and starts to this day.
In the Late Middle Ages, a large segment of the population actually believed that evil people could negatively affect the climate. It appears that we haven’t learned the lessons of the 16th century and the dangers of stirring unfounded fears concerning changes to our climate. Perhaps in the not too distant future we will have the benefit of hindsight and realize that people like Al Gore and Dr. Michael Mann were the Heinrich Kramers of the early 21st century, trying to convince us all that we can control the uncontrollable — the natural cycles of the Sun and Earth that are operating today, just as they have for many millions of years.

Gregory Wrightstone is a geologist and the Executive Director of the CO2 Coalition in Arlington Virginia. He is bestselling author of Inconvenient Facts: The Science that Al Gore doesn’t want you to know.
References:
Pfister (2007) Witch Hunts: Strategies of European Societies in Coping with Exogenous Shocks in the Late Sixteenth and Early Seventeenth Centuries
Behringer (1999) Climatic change and witch-hunting: the impact of the Little Ice Age on mentalities.
Scientist Whose Wife Was Injured by COVID Vaccine Tells FDA: ‘Please Do Not Give This to Kids’
By Megan Redshaw | The Defender | October 27, 2021
The U.S. Food and Drug Administration’s (FDA) advisory committee on Tuesday endorsed Pfizer’s COVID vaccine for children ages 5 to 11, despite strong objections raised during the meeting by multiple scientists and physicians.
Brian Dressen, Ph.D., is one of the scientists who testified during the 8-hour hearing.
Dressen is also the husband of Brianne Dressen, who developed a severe neurological injury during the Utah-based portion of the U.S. AstraZeneca COVID vaccine trial in 2020. After being injured by the first dose, Brianne withdrew from the trial.
During his 3-minute testimony, Dressen, a chemist with an extensive background in researching and assessing the degree of efficacy in new technologies, told the FDA advisory panel Pfizer’s vaccine “failed any reasonable risk-benefit calculus in connection with children.”
Dressen said:
“Your decision is being rushed, based on incomplete data from underpowered trials, insufficient to predict rates of severe and long-lasting adverse reactions. I urge the committee to reject the EUA [Emergency Use Authorization] modification and direct Pfizer to perform trials that will decisively demonstrate that the benefits outweigh the risks for children. I understand firsthand the impact that you will or will not have with the decision you’re going to make today.”
Dressen told the FDA how his wife was severely injured last November by a single dose of a COVID vaccine administered during a clinical trial. He said:
“Because study protocol requires two doses, she was dropped from the trial, and her access to the study app deleted. Her reaction is not described in the recently released clinical trial report — 266 participants are described as having an adverse event leading to discontinuation, with 56 neurological reactions tallied.”
He said he and his wife have since met participants from other vaccination trials — including Pfizer’s trial for 12- to 15-year-olds — who suffered similar reactions and fate.
Dressen said:
“Injured support groups are growing. Memberships number into at least the tens of thousands. We must do better. Those injured in a trial are a critical piece of vaccine safety data. They are being tossed aside and forgotten. The FDA has known first-hand about her case and thousands of others. The FDA has also stated that their own systems are not identifying this issue and that VAERS is not designed to identify any multi-symptom signals. The system is broken.”
Dressen said his family’s lives have changed forever. “The clinical trials are not appropriately evaluating the data,” he said. “The FDA, Centers for Disease Control and Prevention (CDC) and the drug companies continue to deflect the persistent and repeated cries for help and acknowledgment, leaving the injured as collateral damage.”
He added:
“Until we appropriately care for those already injured, acknowledge the full scope of injuries that are happening to adults, please do not give this to kids. You have a very clear responsibility to appropriately assess the risks and benefits to these vaccines. It is obvious that isn’t happening.
“The suffering of thousands continues to repeatedly fall on deaf ears at the FDA. Each of you hold a significant responsibility today and know that without a doubt, when you approve this for the 5 to 11-year-old’s, you are signing innocent kids and uninformed parents to a fate that will undoubtedly rob some of them of their life.”
In an interview with KUTV on Tuesday, Brianne said her kids will not receive a COVID-19 vaccine if approved. “I will react to the vaccine regardless of the brand, and so if my kids have this same genetic makeup, there is the high potential now that the same thing could happen to them,” she said.
Since his wife’s injury — diagnosed by doctors at the National Institutes of Health — the Dressens have met with other trial participants and families with children who also believe they were injured by the COVID vaccines. They formed a support group and website called, C19 Vax Reactions, to share their stories of vaccine injuries.
On June 26, Sen. Ron Johnson (R-Wis.) held a news conference to discuss adverse reactions related to the COVID vaccines — giving individuals, including Brianne, who have been “repeatedly ignored” by the medical community a platform to share their stories.
According to KUTV, the group continues to push the FDA and CDC for answers and help. Largely ignored, they reached out to Utah Senator Mike Lee, who wrote a letter to the CDC and FDA on their behalf.
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
© 2021 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Featured Video

Death Spikes & Rising Cancer In Our Youth Explained
or go to
Aletho News Archives – Video-Images
From the Archives
Politicians lie
By Mazin Qumsiyeh | Popular Resistance | August 18, 2013
There is no way to say this truth nicely: Politicians lie. That includes Japanese, American, Egyptian, Israeli, and Palestinian politicians! Is there something more common sense than that? Yet, so many citizens around the world believe their own politicians or wistfully acknowledge lies but think it is part of the job needed to run things. They believe even when politicians contradict themselves blatantly. This phenomenon is rather remarkable. It is a dissonance and disconnect from reality that many seem oblivious to. It is very dangerous because it can lead to accepting rationales for going to war. These can be deadly wars that lead to millions of lives lost as happened in what was called World War 1 and WW2. Even when incredible and declassified evidence abound, politicians continue to lie and old mythologies refuse to die. Here are just a few of the countless lies told to us over the past few decades… continue
Blog Roll
 Aletho News
- Iraqi resistance group vows to stage airport sit-ins over Iran aerial blockade
- Turkish parliament to review Saudi-Pakistan defense pact next month
- DEATH SPIKES & RISING CANCER IN OUR YOUTH EXPLAINED
- Iran offers Trump deal before US election
- Merz regime wants ‘secret police’ – opposition
- Israeli settlers terrorize West Bank Palestinians with state-provided drones: Report
- They see them, then kill them: Israeli quadcopters track, deliberately target civilians in Gaza
- Debunked: Trump’s egregious UNGA claims on war against Iran crumble under scrutiny
- Europe was part of the infrastructure of US aggression against Iran: Deputy FM
- New evidence on the Bucha Massacre
- If Americans Knew
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- In UN Speech, Iran’s President Displays Pictures of Children Killed by US, Brings Attention to Israel’s Nuclear Arsenal
- Israel displaces hundreds of Palestinians amid wave of demolitions in West Bank
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years


