Israeli control of the Pentagon goes back to 2002.
Pentagon insider and senior enlisted leader of nearly three decades standing, Command Chief Master Sergeant, Retired, Dennis Fritz describes what he saw in the Pentagon leading up to the Iraq War: Each cabinet official had an individual who they would talk to in Israel to keep them posted on what we were doing…
Israeli control of the Pentagon🇺🇸 goes back to 2002
'During the Bush Administration in the run-up to the Iraq War, each cabinet official had an individual who they would talk to in Israel to keep them posted on what we were doing…
As American military forces arrived in Afghanistan, they began building a network of bases to rule the entire nation. This repeated the mistakes of the Vietnam war. Each base required clean water, electricity, security, and frequent resupply, which required guarding bridges, road mine clearing, weekly supply convoys, and helicopter runs. This was expensive, required much manpower, left forces dispersed, provided ample targets for the enemy, and alienated the population with frequent “search and destroy” patrols that caused much death and destruction. Employing this failed strategy in Afghanistan was more difficult as the rugged terrain limited airpower while numerous caves provided the enemy with great hiding locations. In some areas, it was not practical to establish military outposts on good defensive terrain since mountaintops lacked road access and a local water supply. Nevertheless, American Generals insisted on military outposts everywhere, no matter the vulnerability of the base.
American combat forces should have remained mostly out of sight as a reserve force to protect large cities and dispatch units to rural areas only when a large enemy force converged to attack local forces. American aid should have focused on improving the economic infrastructure and local militia forces in a long-term, passive effort that would minimize manpower requirements, causalities, and costs.
I dedicate this article to all women invited to mammography screening and those who love them because the public has consistently been lied to, for over 40 years. In invitations to screening, women have been told that by detecting cancers early, screening saves lives and leads to less invasive surgery.1,2 I shall demonstrate that all three statements are wrong.
Women are still being told these lies, by professional associations, screening advocates, screening researchers, cancer charities, and national boards of health.3-5 The American Cancer Society declares in a headline that “Mammography Saves Lives”4 and claims, with no references, that results from many decades of research clearly show that women who have regular mammograms are less likely to need aggressive treatments like surgery to remove the entire breast (mastectomy).5
Screening Does Not Save Lives
In the randomised trials of mammography screening, the risk ratio for overall mortality after 13 years of follow-up was 0.99 (95% confidence interval 0.93 to 1.03) for those trials with adequate randomisation.6 The estimate happened to be the same for the other trials, some of which were so poorly randomised that the average age in the two compared groups was not the same, which makes an analysis of overall mortality unreliable.
For two of the three adequately randomised trials, those from Canada and the UK, there are follow-up data after 25 and 23 years, respectively.7,8 The risk ratio for overall mortality was 1.01 (95% confidence interval 0.98 to 1.03) for all three trials (both with a fixed effect and a random effects model, Comprehensive Meta Analysis Version 3.0). In the table, the year means the year the trial started:
This is a very strong result as it is derived from a total of 25,046 deaths. We can therefore say with great confidence that mammography screening does not save lives.
If we restrict the analysis to the two trials with a very long follow-up, the result is the same, a risk ratio of 1.01 (0.99 to 1.04).
Breast Cancer Mortality Is a Seriously Flawed Outcome
It will surprise most people to learn that we cannot trust what has been reported in the randomised trials about the effect of screening on breast cancer mortality but this is an objective fact.6
A minority of the women who died were autopsied, and in several trials, cause of death was not assessed blindly.6 I have documented that assessment of cause of death was seriously biased.6,9 If we include all trials in the analysis, we would expect to see the greatest reduction in breast cancer mortality in those trials that were most effective in lowering the rate of node-positive cancers (cancers that had metastasised) in the screened group.
This was indeed the case, but the regression line was in the wrong place. It predicts that a screening effectiveness of zero (i.e. the rate of node-positive cancers is the same in the screened groups as in the control groups) results in a 16% reduction in breast cancer mortality (95% confidence interval 9% to 23% reduction).6,9 This can only happen if there is bias, and further analyses showed that assessment of cause of death and of the number of cancers in advanced stages were both biased in favour of screening.
Systematic reviews that include all the trials, also the poorly randomised ones, have reported that mammography screening reduces breast cancer mortality by 16-19%.6,10 As this estimate is of the same size as the bias in the regression analysis, this suggests that screening does not lower breast cancer mortality.
Another reason why breast cancer mortality is a flawed outcome is that screening leads to overdiagnosis, which is the detection of cancers and precursors to cancer (carcinoma in situ), which would not have come to the attention of the woman in her remaining lifetime and therefore would not have become a problem without screening. Since it is not possible to distinguish between harmless cancers and dangerous ones, they are all treated, and radiotherapy and chemotherapy given to women who are healthy increase their mortality.6
If we take into account the cardiac and lung cancer deaths caused by the type of radiotherapy used when the screening trials were carried out and generously assume that screening reduces breast cancer mortality by 20% and results in only 20% overdiagnosis of healthy women, then there is no mortality benefit from screening.11
Finally, it is noteworthy that the most unreliable trials were those that reported the greatest reductions in breast cancer mortality.6 The difference in the effect estimates between the adequately randomised trials and the poorly conducted trials was statistically significant, both after 7 and 14 years of follow-up (P = 0.005 and P = 0.02, respectively).12
Total Cancer Mortality
Since misclassification of cause of death often concerns deaths from other cancers,6 total cancer mortality is a less biased outcome than breast cancer mortality.
Some trialists have not reported what the total cancer mortality was but we have data from the three adequately randomised trials.6,8 There was no effect of screening on total cancer mortality, including breast cancer, risk ratio 1.00, 95% confidence interval 0.96 to 1.04. There were two different age groups in the Canadian trial, 40-49 (a) and 50-59 years (b):
Since total cancer mortality is less biased than breast cancer mortality, it is of interest to see what the expected cancer mortality (including breast cancer mortality) would have been if the reported reduction in breast cancer mortality of 29% after 7 years in the poorly randomised trials6 were true.
It would have been a risk ratio of 0.95, which is significantly lower (P = 0.02)6 than what was actually found. This provides further evidence that assessment of cause of death was biased in favour of screening.
Breast Cancer Is Not Detected Early but Very Late
If we assume that the observed doubling times in longitudinal tumour studies are constant from initiation till the tumour becomes detectable, the average woman has harboured the cancer for 21 years before it acquires a size of 10 mm and becomes detectable on a mammogram.13
Given this large time span, it is misleading to call it “early detection” also because the effect of screening is trivial, namely to advance the diagnosis by less than a year.13
Yet all authorities repeat this mantra. As it is impossible that everyone working with cancer is unaware of the basics of tumour biology, we can draw the conclusion that the public all over the world is being misinformed. This is fraud because it is deliberate and because women think “early detection” will save their lives.
I once asked a famous tumour biologist, Keld Danø, during a coffee break at an international meeting, whether he agreed with me that it was impossible to lower breast cancer mortality by 30% with screening, based on our knowledge of tumour biology.14 He agreed. When I asked why people like him didn’t participate in the scientific debate, he didn’t reply and it is not difficult to imagine why. It is not wise to point out that your colleagues are wrong when you are on the receiving end of major funds from a cancer charity that touts screening.
The women suffer while everyone else prospers.
The earliest cell changes, carcinoma in situ, are not detected unless the women get a mammogram. In our systematic review of countries with organised screening programmes, we found an overdiagnosis of 35% for invasive cancer and 52% when we included carcinoma in situ.15
Although less than half of carcinoma in situ cases progress to invasive cancer,16,17 the women are nevertheless routinely treated with surgery, drugs, and radiotherapy.
The deep irony is that the surgery is often mastectomy because the cell changes may be diffusely spread in the breast, and sometimes even in both breasts. In New South Wales, one-third of women with carcinoma in situ had a mastectomy,18 and in the UK, carcinoma in situ was more often treated by mastectomy than invasive cancer,19 and the number of women treated by mastectomy almost doubled from 1998 to 2008.20
This brings us to the third big falsehood in the propaganda about mammography screening.
Screening Does Not Decrease but Increases Mastectomies
Because of the substantial overdiagnosis of invasive cancer and carcinoma in situ, and because screening only advances detection of invasive cancers slightly,13 it is inevitable that screening increases mastectomies.
In the randomised trials of screening, we found 31% more mastectomies in the screened groups than in the control groups.6
Denmark is a unique country to study this in practice as we had a period of 17 years (1991-2007) where only about 20% of potentially eligible women were invited to screening because some counties did not have screening.21 When screening starts, more breast cancer diagnoses than usual will be made and there will be more mastectomies. However, as can be seen on the graphs, the huge increases in mastectomies are not compensated by a drop in mastectomies later where there was a similar decline in mastectomies in non-screened areas as in screened areas:22
Moreover, as the next graph shows, there is no compensatory drop in old age groups:22
Yet women are told that screening leads to less invasive surgery, with fewer mastectomies. This is disinformation in the extreme.
The most commonly used trick used to disinform the women about this issue is to report percentages instead of numbers.3 Imagine a town with a certain level of crime. You divide the crimes into serious and less serious ones. Over a period of time, the rate of serious crime increases by 20% and the rate of less serious crime by 40%. This is a development for the worse. But although more people are exposed to serious crime and more people are exposed to less serious crime as well, a trickster would say that, as there are now relatively fewer cases of serious crime, the situation has improved.
It is deplorable that people who know better – screening researchers, cancer charities, national boards of health, etc – have lied to the public this way3 and still do, in direct contrast to logic and the scientific evidence.
The Final Layers of Dishonesty
The mammography screening area is riddled with dishonesty. So much that I needed to write a whole book detailing all the elaborate ways in which researchers and others had made it look like the Emperor was dressed when in fact he was naked.3
The deception is total because it always continued after I had pointed out in letters to the editor what the researchers had done wrong, and to which they responded.3,14 They therefore cannot claim they didn’t know that they continued to manipulate the data and to deceive the public.
Three of the most dishonest and most prolific authors are László Tabár, Stephen Duffy, and Robert Smith. Over many years, they aggressively attacked my extensive research on mammography screening but never with convincing arguments3,14 – they excel at ad hominem arguments.
László Tabár was the primary investigator for the Swedish Two-County study, an early trial that reported a huge effect of screening, a 31% reduction in breast cancer mortality.23 This trial was instrumental for introducing screening. However, there are so many serious discrepancies in numbers, and some of the findings are so implausible and incompatible with reported tumour characteristics, that it looks like scientific misconduct.3,6,24-27 Tabár has made a fortune on mammography screening and has a habit of threatening with litigation whenever anyone gets too close to his secrets.3,14,23
One would not think that Stephen Duffy is a professor of statistics because he has bent the data beyond belief and beyond what is appropriate in many creative and obscure ways.3,6,14 Robert Smith was once the Director of Cancer Screening at the American Cancer Society.
This triumvirate reported a 63% reduction in breast cancer mortality in an observational study.28 I pointed out some of the problems with their study,29 but in their reply,30 they compared women who attended screening with women who didn’t, although it is clear from their own paper that they were aware that such comparisons are seriously misleading.
These authors claimed, based on the Two-County study data, that they had found a “statistically significant 13% reduction in mortality in association with an invitation to screening.”31,32 This is plain wrong and totally impossible. Even if screening was 100% effective and prevented all deaths from breast cancer, it could not reduce total mortality by 13%.
They furthermore predicted that when a screening programme had been running for some time, one could expect a reduction of 3-4% in total mortality.31 This is also impossible unless screening prevents all breast cancer deaths. The lifetime risk of dying from breast cancer is 2.5-3%,33 and it was 3-4% in many countries before screening was introduced.
I dryly remarked in my book that if they continued their line of research for other diseases, they may find the recipe for eternal life.3 I also noted that the problem with lying is that
sooner or later people usually contradict themselves, which they did in relation to a study they had published in The Lancet.3
A common way of duping the readers is to say that early detection of breast cancer “reduces mortality”34 without specifying what kind of mortality this is, which makes the reader believe that screening saves lives.
The most common error in the screening literature could be that people falsely translate a recorded effect on mortality from a cancer into an effect on all-cause mortality. We see claims everywhere that common cancer screening tests save lives but a systematic review of the randomised trials found that the only screening test with a significant lifetime gain was sigmoidoscopy. It extended life by 110 days on average, and as the 95% confidence interval went from 0 to 274 days, this result was on the verge of not being statistically significant.35
Another common trick is to use hypothetical statements when we have certain knowledge. For example, authors may write – even in our most esteemed medical journals – that overdetection “may” occur for invasive cancers and that it “may” cause harm through unnecessary labelling and treatment of patients who, without screening, “might” never have been diagnosed.34 These are not hypothetical possibilities; they are inevitable consequences of screening.
Final Remarks
Starting in 2000, I have published numerous scientific articles, letters to the editor, newspaper articles, and two books about mammography screening that do not leave a shred of doubt that this intervention is very harmful.37
Even though I know that no one will ever be convicted, I consider it a crime that women have been systematically lured into believing that screening is good for them. According to the principles for informed consent, people must be fully informed about the most important benefits and harms of interventions they are offered, but this ethical requirement has been brutally ignored. To such a degree that in many countries, women receive an “invitation” to mammography screening with a pre-allotted time for a mammogram they never asked about.1 This makes them believe it is very important that they show up and puts pressure on them to cancel the appointment if they don’t want a mammogram taken. If they refuse, they are often subjected to highly coercive and paternalistic follow-up letters.
Here are some examples of the deeply unethical practice:1
“We have reserved a time… If the time is very inconvenient, we ask you to contact the mammography screening centre as soon as possible;” “I am concerned that you have not yet responded to our recent invitation for a screening mammogram;” “If you would like to avoid participation, we ask you to fill out a form. You obtain this form by calling the breast-diagnostic centre;” “During the past two years, over 340,000 Queensland women have benefited from taking part in the BreastScreen Queensland Programme,” “You can take a positive step to decrease your own risk, and help us achieve our goal, by deciding to take part.”
What matters is to ensure a high uptake, “our goal,” not that the women understand what they are being subjected to.
I advise women in all countries to not go to mammography screening and to do nothing if they are “invited,” which my wife did. She had no obligation to decline an “invitation” with a pre-allotted time she never asked for, and the letter made her angry.
Screening is harmful in many other ways than those I have mentioned here, e.g. between one quarter and one half, depending on the country, of all women attending screening repeatedly will experience at least one false positive result, which can be distressful for several years.36 It therefore constitutes another tremendous harm.6,14
As I have explained elsewhere,38 the Cochrane Collaboration refused to allow us to update our Cochrane review on mammography screening last year, even though I had updated it three times before and the update was only about adding more deaths to two of the trials.
Absurdly, the ”Sign-Off Editor” noted that our review might create a potentially damaging firestorm of misinformation and we were accused of having pre-conceived ideas about no benefit of screening “rather than considering it may actually have benefit not detected.” We were also forbidden to use the term overdiagnosis even though this is standard and appears in other Cochrane reviews of cancer screening, including our own.6,12
When I first published the Cochrane review, in 2001, there was a huge scandal39 because Cochrane forbade us from publishing our data on the most important harms of screening, overdiagnosis, and overtreatment.3 This should have made the Cochrane leaders handle our update professionally, but they preferred to support the prevailing dogma about screening rather than telling the women the truth.
Only one question remains: Which country will be the first to show a little sanity and respect for the science and abandon screening?
Dr. Peter Gøtzsche co-founded the Cochrane Collaboration, once considered the world’s preeminent independent medical research organization. In 2010 Gøtzsche was named Professor of Clinical Research Design and Analysis at the University of Copenhagen. Gøtzsche has published over 100 papers in the “big five” medical journals (JAMA, Lancet, New England Journal of Medicine, British Medical Journal, and Annals of Internal Medicine). Gøtzsche has also authored books on medical issues including Deadly Medicines and Organized Crime.
Public health policy should rest on solid, transparent evidence — not slogans, not marketing and not selective readings of scientific reviews, biochemist Lucija Tomljenović, Ph.D., said recently.
In a wide-ranging interview on the “Slobodni Podcast,” Tomljenović challenged the evidence base for HPV vaccination programs.
She told host Andrija Klarić that safety and efficacy claims are unsubstantiated, and the benefits of the vaccine do not outweigh the risks.
The widely circulated claim that the HPV vaccine dramatically reduces cervical cancer risk — by as much as 80% if administered before age 16 — collapses under closer examination.
Tomljenović has published more than a dozen papers on the HPV vaccine. She was also an expert witness in litigation against Merck, maker of the Gardasil HPV vaccine. In that role, she presented a systematic critique of the claims that the HPV vaccine prevents cancer.
She also delivered an overview of the science on the adverse events associated with the shot, and she presented evidence that Merck manipulated regulators and legislators to grow the market for its vaccine.
Claims that HPV vaccine reduces cancer risk based on flawed Cochrane reviews
However, systematic reviews are only as reliable as the studies they include, she said.
According to Tomljenović’s analysis of the 300-plus-page review, the majority of epidemiological studies cited to show the vaccine’s effects — including its ability to stop invasive cervical cancer — had serious or critical risk of bias, according to the ratings of Cochrane’s own reviewers.
A systematic review is a “study of studies,” a high-level research method that reviews, synthesizes and critically appraises the available body of evidence for a given disease or health topic in a standardized and systematic way.
Risk-of-bias assessments in those reviews evaluate whether methodological flaws — in design, analysis or reporting — are likely to invalidate results. A “serious” or “critical” rating signals substantial flaws that make conclusions highly questionable.
Yet despite this, Tomljenović said the Cochrane review concluded there was “moderate certainty evidence” that HPV vaccines reduce cervical cancer incidence.
She said that when the studies included in a systematic review are predominantly rated as low quality by the reviewers themselves, it is not justified to conclude the studies provide “moderate certainty evidence” for any outcome.
“Garbage in equals garbage out,” she said.
“If the majority of your studies are of such poor quality — by your own assessment — you cannot claim moderate certainty evidence,” she says. “That is just misinformation.”
Cervical cancer rates were in decline before HPV vaccine introduced
If HPV vaccination dramatically reduces cervical cancer, it follows that there would be a clear population-level decline of the disease following widespread vaccination.
Tomljenović presented national cervical cancer statistics from the U.K., Australia, and the U.S. showing that cervical cancer rates had been declining — and in some age groups were already near zero — before HPV vaccines were introduced into immunization schedules.
“The rate of cervical cancers in the U.K. have been rapidly declining and they have reached their lowest point long before HPV vaccines were introduced,” she said.
In Australia, despite very high vaccination rates, she said there has been no corresponding dramatic improvement when it comes to cancer rates.
She shared those statistics in her presentation slides. “You want me to believe something,” she says. “Show me the data.”
Clinical trials didn’t test for cancer prevention
Health officials and vaccine makers claim the HPV vaccine prevents cancer. However, neither the clinical trials nor the studies included in the Cochrane reviews actually studied whether the vaccines prevented cancer.
However, CIN2 lesions often resolve without becoming cancerous.
Even if one assumed that CIN2 was a valid surrogate, Gardasil 9 demonstrated roughly 60% efficacy against CIN2 or worse over 3.5 years in those trials, Tomljenović said.
This can’t logically translate into claims of 90% lifetime cervical cancer prevention — especially when cervical cancer develops over decades and trials followed participants for only about three years.
“High efficacy against lower-grade precancerous lesions does not necessarily translate to high vaccine efficacy against … cervical cancer,” she said.
Tomljenović said her conclusion is shared by several independent research groups, including a group of German physicians and a group led by Dr. Peter Gøtzsche, writing in peer-reviewed literature.
HPV vaccines associated with many serious side effects
Tomljenović said that many known adverse events associated with the HPV vaccines are not disclosed in official vaccine product information.
Those side effects, which are documented in case reports and adverse event reporting systems, include cardiac arrhythmias, neurological conditions such as acute hemorrhagic encephalomyelitis, autonomic nervous system disorders, chronic fatigue syndrome, premature ovarian failure, and permanent disability.
Other studies have identified similar adverse events.
The National Vaccine Injury Compensation Program has also recognized serious adverse events. For example, a judge awarded compensation to the family of Christina Tarsell, a young woman who died following Gardasil vaccination.
Tomljenović said serious and life-threatening injuries may be rare, but people should be properly informed about the risks.
Financial interests, not science, driving vaccine policy
Tomljenović said she does not dismiss research purely based on funding sources. However, when methodological weaknesses align with extensive pharmaceutical lobbying and financial relationships, legitimate concerns arise that financial interests rather than evidence-based science are driving vaccine policy.
A 2012 article in the American Journal of Public Health documented Merck’s role in drafting and promoting legislation that mandated the HPV vaccine for school attendance in the U.S.
The researchers found that Merck served as “an information resource, lobbying legislators, drafting legislation, mobilizing female legislators and physician organizations, conducting consumer marketing campaigns, and filling gaps in access to the vaccine.”
She also said there is a “revolving door” between Merck and regulatory agencies. Dr. Julie Gerberding, former director of the Centers for Disease Control and Prevention, became president of Merck’s vaccine division when she left the agency.
During her tenure at Merck, she accumulated over $100 million in personal wealth.
Tomljenović also invoked the Vioxx scandal — another Merck product later withdrawn from the market after killing tens or hundreds of thousands of people — as a cautionary tale about regulatory failures.
Researchers have suggested that Merck pushed Gardasil to compensate for its financial losses from Vioxx.
Pap screenings are the best way to prevent cervical cancer
Tomljenović concluded that regular Pap screenings remain a proven, risk-free alternative to HPV vaccination for cervical cancer prevention.
She said that “exposing healthy children to long-term, unpredictable and incompletely understood vaccine risks for no proven substantial benefits … is utterly unscientific, unreasonable, immoral and plain reckless.”
Pap screenings, she argues, carry no risk of autoimmune complications or neurological injury and have already driven substantial declines in mortality.
Dinosaur GenXers like me recall that after the fall of the Berlin Wall, the foreign policy set was busy asking how the United States would cash its forthcoming “peace dividend,” whether NATO would fold up shop having achieved its ostensible purpose, and maybe whether we were entering “the end of history”? How short-sighted. Instead, the pace of war-fighting from the 1950s (the original “peace dividend”), to the 1990s increased by a multitude of twelve. See my chart below.
Overall, the United States has engaged in 481 total military engagements since 1798—287 of them since 1989 (60% of total). We’re only six years into the 2020s and it’s already at 34 and on pace to hit ~57 by decade’s end, which would make it the second-busiest decade in U.S. history behind the 1990s. U.S. servicemen have fought in 102 countries For those keeping score, here’s a list of more than 110 military conflicts since 1989:
January 1989, Libya: Two U.S. Navy F-14s shot down two Libyan jet fighters over the Mediterranean after the Libyan planes showed hostile intent.
May 1989, Panama: President George H.W. Bush deployed ~1,900 troops to Panama after General Manuel Noriega disregarded the results of the Panamanian election.
September 1989, Colombia/Bolivia/Peru: The United States sent military advisers and Special Forces teams to Colombia, Bolivia, and Peru to help combat drug producers and traffickers.
December 1989, Philippines: U.S. fighter planes from Clark Air Base helped the Corazon Aquino government repel a coup attempt, and one hundred marines were sent to protect the U.S. embassy in Manila.
December 1989, Panama: President George H.W. Bush ordered a full-scale military invasion of Panama to protect American citizens and bring General Manuel Noriega to justice; all forces withdrew by February 1990.
August 1990, Liberia: A reinforced rifle company was sent to secure the U.S. embassy in Monrovia and helicopters evacuated U.S. citizens from Liberia.
August 1990, Saudi Arabia: President George H.W. Bush ordered a massive forward deployment of U.S. forces to the Persian Gulf to defend Saudi Arabia after Iraq’s invasion of Kuwait.
January 1991, Iraq/Kuwait: U.S. forces commenced combat operations against Iraqi forces in Iraq and Kuwait under a United Nations coalition; combat was suspended on February 28, 1991.
May 1991, Iraq: U.S. forces entered northern Iraq to provide emergency relief to Kurdish populations facing Iraqi government repression.
September 1991, Zaire: U.S. Air Force transports carried Belgian and French troops into the region and evacuated American citizens after widespread looting and rioting in Kinshasa.
May 1992, Sierra Leone: U.S. military planes evacuated Americans from Sierra Leone after a military coup overthrew the government.
August 1992, Kuwait: The United States began military exercises in Kuwait following Iraqi refusal to recognize its new United Nations-drawn border and cooperate with U.N. weapons inspectors.
September 1992, Iraq: President George H.W. Bush ordered U.S. participation in enforcing a no-fly zone over southern Iraq and aerial reconnaissance to monitor Iraqi cease-fire compliance.
December 1992, Somalia: President George H.W. Bush deployed U.S. forces to Somalia as part of an American-led United Nations task force to address a crisis the Security Council deemed a threat to international peace.
January 1993, Iraq: U.S. aircraft shot down an Iraqi plane in the no-fly zone, and coalition forces attacked missile bases in southern Iraq in multiple strikes through mid-January.
January 1993, Iraq: President Bill Clinton continued the Bush policy on Iraq, with U.S. aircraft firing at Iraqi targets after sensing radar or anti-aircraft threats directed at them.
February 1993, Bosnia: The United States began airdropping relief supplies to Muslims surrounded by Serbian forces in Bosnia.
April 1993, Bosnia: U.S. forces joined a NATO operation to enforce a United Nations ban on unauthorized military flights over Bosnia-Herzegovina.
April-May 1993, Iraq: U.S. planes bombed or fired missiles at Iraqi anti-aircraft sites that had tracked U.S. aircraft enforcing the no-fly zones.
June 1993, Somalia: The U.S. Quick Reaction Force participated in military action against a Somali factional leader who attacked United Nations forces, with continued air and ground operations through the following months.
June 1993, Iraq: U.S. naval forces launched cruise missiles against Iraqi Intelligence headquarters in Baghdad in retaliation for an alleged assassination attempt on former President George H.W. Bush.
July-August 1993, Iraq: U.S. aircraft fired missiles at Iraqi anti-aircraft sites and bombed an Iraqi missile battery displaying hostile intent.
July 1993, Macedonia: 350 U.S. soldiers deployed to the Former Yugoslav Republic of Macedonia as part of a United Nations force to maintain stability in the former Yugoslavia.
October 1993, Haiti: U.S. ships began enforcing a United Nations embargo against Haiti.
February 1994, Bosnia: The United States expanded its participation in United Nations and NATO efforts in former Yugoslavia, with sixty aircraft available for NATO missions.
March 1994, Bosnia: U.S. planes patrolling the no-fly zone shot down four Serbian Galeb planes.
April 1994, Bosnia: U.S. warplanes under NATO command fired on Bosnian Serb forces shelling the United Nations safe city of Gorazde.
April 1994, Rwanda: Combat-equipped U.S. forces deployed to Burundi to conduct potential evacuation of American citizens from Rwanda amid widespread fighting.
April 1994, Haiti: U.S. naval forces continued enforcing the United Nations embargo around Haiti, having boarded 712 vessels since October 1993.
August 1994, Bosnia: U.S. aircraft under NATO attacked Bosnian Serb heavy weapons in the Sarajevo exclusion zone at the request of United Nations forces.
September 1994, Haiti: President Bill Clinton deployed 1,500 troops to Haiti to restore democracy, later increasing to 20,000.
November 1994, Bosnia: U.S. combat aircraft under NATO attacked Serb bases used to assault the Bosnian town of Bihac.
March 1995, Somalia: 1,800 combat-equipped U.S. forces deployed to Mogadishu to assist in withdrawing United Nations forces from Somalia.
May 1995, Bosnia: U.S. fighter aircraft continued enforcing the no-fly zone over Bosnia, with ~500 troops deployed in the Former Yugoslav Republic of Macedonia as part of United Nations peacekeeping.
September 1995, Bosnia: U.S. aircraft participated in major NATO air strikes against Bosnian Serb forces threatening United Nations safe areas, flying roughly three hundred sorties on the first day alone.
December 1995, Bosnia: President Bill Clinton ordered ~20,000 U.S. troops to Bosnia as part of NATO’s Implementation Force to enforce the Dayton peace agreement, with ~12,000 more in support roles across the region.
April 1996, Liberia: U.S. military forces evacuated American and third-country nationals from Liberia after security deteriorated, and responded to attacks on the embassy compound.
May 1996, Central African Republic: U.S. forces deployed to Bangui to evacuate American citizens and government employees and secure the U.S. embassy.
December 1996, Bosnia: President Bill Clinton authorized ~8,500 U.S. troops to participate in NATO’s Stabilization Force (SFOR) follow-on force in Bosnia to deter resumption of hostilities.
March 1997, Albania: U.S. forces evacuated government employees and citizens from Tirana, Albania, and enhanced embassy security amid civil unrest.
March 1997, Congo/Gabon: A standby evacuation force deployed to Congo and Gabon to provide security for Americans and prepare for possible evacuation from Zaire.
May 1997, Sierra Leone: U.S. military personnel deployed to Freetown to evacuate U.S. government employees and citizens.
July 1997, Cambodia: ~550 U.S. military personnel deployed to Thailand for possible emergency evacuation of American citizens from Cambodia during civil conflict.
June 1998, Guinea-Bissau: A standby evacuation force deployed to Senegal to evacuate Americans from Guinea-Bissau after an army mutiny endangered the U.S. embassy.
August 1998, Kenya/Tanzania: U.S. military personnel deployed to Nairobi and Dar es Salaam to provide disaster assistance and enhanced security after terrorist bombings of both U.S. embassies.
August 1998, Albania: Two hundred marines and ten Navy SEALs deployed to the U.S. embassy in Tirana to enhance security against reported threats.
August 1998, Afghanistan/Sudan: President Bill Clinton authorized airstrikes against Osama bin Laden’s camps in Afghanistan and facilities in Sudan in response to the embassy bombings in Kenya and Tanzania.
September 1998, Liberia: Thirty U.S. military personnel deployed to augment embassy security in Monrovia and provide evacuation capability amid political instability.
December 1998, Iraq: The United States and United Kingdom conducted Operation Desert Fox, a bombing campaign against Iraqi facilities deemed capable of producing weapons of mass destruction (WMDs) and other military targets.
1998-2001, Iraq: American and coalition forces conducted ongoing military operations against the Iraqi air defense system in response to threats against aircraft enforcing the northern and southern no-fly zones.
March 1999, Yugoslavia: U.S. forces, in coalition with NATO, commenced air strikes against Yugoslavia in response to its campaign of violence and repression against ethnic Albanians in Kosovo.
April 1999, Albania: President Bill Clinton ordered ~2,500 additional troops and heavy weapons to Albania to enhance NATO’s air operations against Yugoslavia.
May 1999, Yugoslavia: Additional U.S. aircraft and several thousand more personnel deployed to support NATO’s ongoing operations against Yugoslavia.
June 1999, Kosovo: ~7,000 U.S. troops deployed as part of the ~50,000-member NATO-led security force (KFOR) in Kosovo after the end of the air campaign.
October 1999, East Timor: U.S. military forces deployed to support a United Nations multinational force aimed at restoring peace to East Timor, including the USS Belleau Wood and marines.
October 2000, Yemen: After a terrorist attack on the USS Cole in Aden, U.S. military security and disaster response personnel deployed to secure the ship and respond to the incident.
September 2001, Global: Following the 9/11 attacks, President George W. Bush ordered combat-equipped forces to multiple nations in the Central and Pacific Command areas to prevent and deter terrorism.
October 2001, Afghanistan: U.S. forces began combat operations against al-Qaida and the Taliban in direct response to the September 11 attacks.
September 2002, Cote d’Ivoire: U.S. military personnel entered Cote d’Ivoire to evacuate American citizens and third-country nationals from the city of Bouake during a rebellion.
2002, Philippines: ~600 combat-equipped U.S. personnel deployed to the Philippines to train, advise, and assist Filipino forces in enhancing counterterrorism capabilities.
2002, Georgia/Yemen: U.S. combat-equipped forces deployed to Georgia and Yemen to help enhance the counterterrorism capabilities of their armed forces.
March 2003, Iraq: President George W. Bush directed U.S. forces to commence combat operations against Iraq on March 19 as part of a coalition to disarm Iraq, launching a war whose duration was unknown at the time.
June 2003, Liberia/Mauritania: Roughly thirty-five combat-equipped troops deployed to Monrovia to augment embassy security and enable possible evacuation, with additional forces sent to Mauritania.
August 2003, Liberia: ~4,350 combat-equipped U.S. personnel entered Liberian waters to support United Nations and West African efforts to restore order in Liberia.
2003-ongoing, Djibouti: American combat-equipped and support forces deployed to Djibouti to enhance counterterrorism capabilities and support operations against international terrorists in the Horn of Africa.
February 2004, Haiti: Roughly fifty-five combat-equipped troops deployed to Port-au-Prince to augment embassy security during an armed rebellion.
March 2004, Haiti: Roughly two hundred additional combat-equipped troops deployed to Haiti to prepare for a United Nations Multinational Interim Force, eventually growing to ~1,800 personnel.
2004-2005, Iraq: The United States maintained over 135,000 troops in Iraq as part of the Multinational Force, rising to ~160,000 by late 2005.
July 2006, Lebanon: Combat-equipped helicopters and military personnel deployed to Beirut to evacuate American citizens and designated personnel during the security crisis.
2007-ongoing, Somalia: The U.S. military took direct action against members of al-Qaida and al-Shabaab engaged in planning terrorist attacks against the United States.
2007-2011, Afghanistan: U.S. forces grew from ~25,900 to a peak of ~99,000, pursuing al-Qaida and Taliban fighters as part of both ISAF and separate U.S. operations.
2009-ongoing, Yemen: The U.S. military worked with the Yemeni government to eliminate the threat from al-Qaida in the Arabian Peninsula (AQAP), resulting in direct action against operatives and senior leaders.
March 2011, Libya: U.S. military forces launched strikes against Libyan air defenses and military targets to enforce a United Nations-authorized no-fly zone and protect civilians from Gaddafi’s forces.
April-October 2011, Libya: After transferring lead to NATO, U.S. support continued with intelligence, logistics, and unmanned aerial vehicle strikes against defined targets until the mission ended in October.
October 2011, Central Africa: Roughly one hundred combat-equipped U.S. forces deployed to Uganda, South Sudan, the Central African Republic, and the Democratic Republic of the Congo (DRC) to advise regional forces working to remove Lord’s Resistance Army (LRA) leader Joseph Kony.
January 2012, Somalia: U.S. Special Operations Forces conducted a rescue operation in Somalia, freeing kidnapped American Jessica Buchanan and Danish national Poul Hagen Thisted.
September 2012, Libya/Yemen: Combat-equipped security forces deployed to Libya and Yemen after the attack on the U.S. diplomatic post in Benghazi that killed Ambassador Christopher Stevens and three other Americans.
February 2013, Niger: Roughly one hundred U.S. military personnel deployed to Niger with weapons for force protection to support intelligence collection and share intelligence with French forces operating in Mali.
April-June 2013, Jordan: Up to seven hundred combat-equipped U.S. troops deployed to Jordan for training exercises and remained at the request of the Jordanian government amid the Syrian Civil War.
December 2013, South Sudan: U.S. forces evacuated embassy personnel from Juba, and a follow-on evacuation mission near Bor was curtailed after the aircraft came under fire.
June 2014, Iraq: President Obama deployed 300 military advisers to Iraq to assess and counter the threat from ISIL, with subsequent deployments growing to over 5,200 by late 2014.
August 2014, Ukraine: A dozen U.S. troops from European Command deployed to Kiev to help investigate the downing of Malaysian airliner MH17 that killed 298 people.
August 2014, Poland: Six hundred soldiers deployed to Poland as part of Operation Atlantic Resolve to reassure NATO allies in response to Russia’s intervention in Ukraine.
October 2015, Cameroon: Roughly three hundred U.S. military personnel deployed to Cameroon to conduct airborne ISR operations against the Islamist militant group Boko Haram.
June-September 2016, Iraq: An additional 1,160 U.S. troops deployed to Iraq to assist in the fight against ISIL, including preparation for the offensive to retake Mosul.
July 2016, South Sudan: Up to two hundred combat-equipped U.S. forces prepositioned in Uganda and deployed to protect the U.S. embassy after deadly fighting erupted in Juba.
October 2016, Yemen: U.S. forces conducted missile strikes on Houthi-controlled radar facilities in Yemen after threats to U.S. naval vessels, destroying the targets.
January 2017, Europe: 3,500 soldiers with tanks and heavy equipment from the 4th Infantry Division deployed to Poland, marking the start of continuous armored brigade rotations in Europe.
March 2017, Syria: Roughly four hundred Marines and Army rangers deployed to Syria to assist in the fight against the Islamic State.
October 2017, Niger: Four U.S. servicemembers were killed and two wounded during an advise-and-assist mission in Niger when their patrol was ambushed.
December 2017, Iraq/Syria: The Pentagon reported 5,200 U.S. troops in Iraq and 2,000 in Syria, with numbers trending down as the fight against ISIS progressed.
April 2018, Syria: President Donald Trump directed American, French, and British forces to strike Syrian chemical weapons research, development, and production facilities.
February 2018, Afghanistan: The U.S. Army’s first Security Force Assistance Brigade deployed to Afghanistan to train and advise Afghan National Security Forces.
September 2019, Saudi Arabia: Roughly two hundred U.S. support personnel with Patriot batteries and Sentinel radars deployed to augment air and missile defenses after attacks on Saudi oil facilities.
May-June 2019, Middle East: The United States deployed ~14,000 additional forces to the CENTCOM area, including carrier strike groups, Patriot batteries, and additional troops in response to escalating tensions with Iran.
December 2019, Baghdad: Roughly one hundred marines deployed to reinforce security at the U.S. embassy after it was attacked, followed by ~750 troops from the 82nd Airborne as an Immediate Response Force.
January 2020, Kuwait: An additional 2,800 troops from the 82nd Airborne deployed to Kuwait, bringing the total rapid deployment to ~3,500 in response to the Baghdad embassy attack and regional tensions.
February 2020, Africa: The U.S. Army’s 1st Security Force Assistance Brigade deployed to Africa to train and assist African forces and better compete with Russia and China.
2019-2020, Syria: After President Donald Trump announced a full withdrawal from Syria in December 2018, the United States reversed course and maintained roughly four hundred troops in the country.
February 2022, Romania/Poland/Germany: Roughly three thousand troops deployed to Romania, Poland, and Germany as Russia built up forces on Ukraine’s border, eventually growing to over 100,000 U.S. personnel across Europe.
March-September 2022, Europe: Successive waves of additional forces deployed across Europe including aerial refueling, air support, logistics, and combat units in response to Russia’s invasion of Ukraine.
May 2022, Somalia: President Joe Biden authorized a small, persistent U.S. military presence in Somalia to advise and assist local forces, reversing the prior episodic deployment model.
June 2022, Europe: President Joe Biden announced long-term force posture increases across Europe including additional destroyers in Spain, F-35s in the United Kingdom, a rotational brigade in Romania, and a permanent corps headquarters in Poland.
April 2023, Sudan: U.S. forces evacuated roughly one hundred American personnel from the U.S. Embassy in Khartoum amid armed conflict, coordinating with allies including Djibouti, Ethiopia, and Saudi Arabia.
October 2023–February 2024, Iraq/Syria: Iran-backed militias attacked American bases over sixty times; the United States conducted retaliatory strikes on IRGC-linked facilities in eastern Syria and Iraq.
November 2023–ongoing, Red Sea/Yemen: Houthi rebels began attacking commercial shipping and U.S. naval vessels; the United states launched Operation Prosperity Guardian (a multinational naval coalition) in December 2023.
January 2024–January 2025, Yemen: Operation Poseidon Archer—United States and United Kingdom conducted sustained air and cruise missile strikes against Houthi targets, totaling 774 airstrike events.
April 2024, Israel/Iran defense: U.S. forces helped defend Israel during Iran’s first direct missile/drone attack.
November 2024, Israel/Iran defense: United States again assisted Israel defending against a second Iranian attack.
March–May 2025, Yemen: Operation Rough Rider—Trump escalated strikes significantly against Houthi bases, radar, air defenses, and launch sites. Ceasefire brokered by Oman in May.
June 2025, Iran: U.S. forces struck Iranian nuclear sites and defended Israel during a third Iran-Israel conflict.
September 2025–ongoing, Caribbean/Pacific: U.S. military began striking alleged drug trafficking boats using MQ-9 Reapers and AC-130 gunships—over thirty-two strikes killing over 115 people as of December 2025. USS Gerald R. Ford redeployed to Caribbean for Operation Southern Spear.
December 2025, Nigeria: U.S. bombed ISIS targets in Sokoto state in coordination with the Nigerian government.
Late 2025, Venezuela: Escalating maximum pressure campaign culminating in the reported capture of Maduro in January 2026.
January–February 2026, Middle East buildup: Largest U.S. military buildup in the Middle East since the 2003 Iraq invasion.
February 28, 2026, Iran: Operation Epic Fury launched — joint American-Israeli strikes hitting 1,700+ targets in seventy-two hours, targeting nuclear facilities, missile sites, navy, and regime leadership. Forty-eight senior Iranian leaders killed. Seven U.S. service members killed in retaliatory strikes.
Iran’s Foreign Ministry spokesman has condemned an attack by the United States and Israel on a historic site of Isfahan, saying the strike constitutes a crime against cultural heritage.
In a message posted on the social media platform X on Tuesday, Esmaeil Baghaei said the attack caused serious damage to the historic Chehel Sotoun Palace, a renowned museum-palace located near the famous Naqsh-e Jahan Square.
“After hitting Golestan Palace in Tehran, the US and Israel damaged another cultural heritage site of outstanding universal significance in the city of Isfahan: Chehel Sotoun Palace, a @UNESCO World Heritage site within Naqsh-e Jahan Square,” he wrote.
Baghaei described Chehel Sotoun as a masterpiece of the Safavid era, emphasizing that the site is not only part of Iran’s cultural and civilizational heritage but also a cultural treasure belonging to all humanity.
He said the US and Israel were deliberately targeting the historic heart of Isfahan, damaging Chehel Sotoun and putting invaluable historical artifacts of Iran’s civilization at risk.
“The world cannot remain silent while the aggressors’ brutal crimes threaten the shared heritage of humankind.”
The remarks come as the US-Israeli aggression against Iran, which started on February 28, has damaged some historical sites in the country, including those inscribed on the UNESCO World Heritage list.
Tehran’s Golestan Palace was severely damaged as a result of rockets and an explosion wave in Arg Square in the buffer zone.
During many years of contacts with Iran, the IAEA has never found grounds to refuse negotiations on Iranian nuclear program, Russian Foreign Ministry Spokeswoman Maria Zakharova said.
“Throughout all these years, there has not been a single instance where the IAEA stated that there is a reason to confirm a claim or accusation against Iran,” Zakharova noted.
While the issue was “handled politically” and there were public and behind-the-scenes intrigues, not a single report, speech or fact-based document from the agency contained any accusations against Iran, she added.
The IAEA never stated Iran had a nuclear bomb, only noting the fact of uranium enrichment, Russian Foreign Minister Sergey Lavrov said on March 5. The Iranians started boosting the enrichment process only after the US withdrew from the agreements on Iran’s nuclear program, he added.
There is a rising tide of claims from apologists for the crimes of Zionism that they have been misunderstood. Palestinians might be indigenous to Palestine, but the Jews definitely are. What is called the ‘Israel-Palestine’ conflict, they say, is competition over the same small piece of land by two rival groups of indigenous people. But are the Jews indigenous to the Levant? And what are the consequences of the argument?
In fact, most of the power structure of the Zionist state is dominated by Ashkenazi Jews who have no ancestral link to Palestine. Overall despite very significant financial and infrastructural contributions from Western European countries (especially the US, UK and France, for example via the Rothschild family), Eastern European Ashkenazim have been at the centre of the Zionist power structure since the early years of the 20th Century.
Ukraine and the origins of Zionism
For example most members of the Jewish National Council in Palestine prior to the founding of the Zionist state in 1948 were Ukrainian. As is well known key leaders of the Zionist movement hailed from Ukraine. Many, but not all, Ukrainian Zionists were close to the Ukrainian nationalist movement.
For example, the far right Revisionist Zionist Vladimir Yevgenyevich Jabotinsky (later renamed Ze’ev Jabotinsky) was himself a direct descendant of Ukrainian Jewish settlers in Odessa. He famously consorted with the leader of the Ukrainian nationalists, Symon Petliura, a proto-Nazi responsible for pogroms against the Jews and others. As the Polish political scientist and Zionist, Shlomo Avineri has written, “throughout his life”, Jabotinsky “harbored an affinity for Ukrainian nationalism despite its shades of anti-Semitism”.
Arguably Zionism and Ukrainian nationalism share certain commonalities, which perhaps helps to contextualise the Zionist regime’s ongoing support for Zelensky today. As early as January 2022, “Israel” began planning to transfer Ukrainian Jews to become colonists in the land of the Palestinians. “Israel’s” Ministry of Aliyah and Immigrant Absorption proclaimed: “We call on the Jews of Ukraine to immigrate to Israel – your home.” But of course, it is not their home.
Another Zionist colonist from Ukraine, was Golda Mabovitch (later known as Golda Meir), who was Prime Minister of the Zionist entity from 1969-1974. She once claimed ‘I’m a Palestinian’ but also denied that the Palestinian people ever existed.
Eastern European origins of the Zionist leaders
All in all, seven of the fourteen Zionist Prime Ministers, so far, came directly from Russia, Poland, Ukraine or Belarus. The other seven were children of parents from modern Ukraine and/or Belarus (Ariel Sharon, Ehud Olmert, Yitzhak Rabin), Lithuania (Ehud Barak), Poland (Benjamin Netanyahu) Hungary/Romania (Yair Lapid) or Poland, and America (Naftali Bennet). All presidents of the Zionist entity, bar three, came directly or indirectly from Poland, Russia, Belarus, Ukraine, or in one case Austria.
The obsession with proving that the Jews, all the Jews, are indigenous to Palestine flies in the face of the overwhelming evidence of the settler colonial nature of Zionism and the fact that most of those in charge originate in Eastern Europe.
Even the Zionist paper Haaretz has published an article claiming that the argument that Jews are indigenous to Palestine ‘swims in fascist waters’.
The fantasy of the ‘decolonised Judean’
The term ‘decolonized Judean’ is used by Zionists, often white European settlers, to describe themselves. But is there any remnant of the original ‘Jewish people’ which inhabited the Levant two millennia ago amongst the two major groups of Jews in the world today?
The dominant group, massively over-represented at all levels of the power structure in what is called ‘Israel’ today are Ashkenazi Jews. They are conventionally said to be the “Jews of France, Germany, and Eastern Europe and their descendants.” The adjective “Ashkenazic” is said to be “derived from the Hebrew word ‘Ashkenaz,’ which is used to refer to Germany.”
Recent research in linguistics and genetics shows that the ‘Rhineland hypothesis’ which suggests that Ashkenazim come originally from the Levant and that Yiddish originates in Germany is unable to explain the genetic, linguistic and cultural data now available. It suggests instead an Iranian-Turkish-Slavic origin for Ashkenazi Jews and a Slavic origin for Yiddish.
A killer detail in the argument is the existence along the ancient Silk Road trade route, in northeastern Turkey, of four primeval villages whose names resemble “Ashkenaz:” such as İşkenaz. Ashkenazi Jews, then, appear to have no historical connection to the original Jews of Palestine.
The Arab Jews
The Sephardi Jews, are the second main group of Jews in the world. The standard vision is that they are the Jews of ‘Spain, Portugal, North Africa and the Middle East and their descendants’. The adjective “Sephardic” is said to be derived from the Hebrew word “Sepharad,” which refers to Spain. So-called ‘Sephardim’ are increasingly populous and according to some accounts now make up a majority of Jews in occupied Palestine. But they also face a well known pattern of discrimination by the white European Ashkenazi Jews.
When they arrived in occupied Palestine – mostly after 1948 – these Sephardic Jews often spoke a kind of Arabic and were sometimes referred to as ‘Arab Jews’. This was a threat to Zionism which made sure to discourage their use of Arabic and assiduously worked to “de-racialise” them. As Lital Levy notes: “These were indigenous communities… whose unique syncretic cultures have since been completely expunged as a result of emigration… to Israel, where they were subjected to a systematic program of deracination and resocialisation”.
Some left Zionist or anti Zionist groups try to present the Sephardim as a benighted ethnic minority. But, if the aim is to wean Sephardim away from ultra-Zionism, this is a strategy doomed to failure. Once they became settler colonists and their connections with the Arabs were severed, their primary loyalty came to be with the Zionist project. But, this cannot erase the fact that the “Sephardim” are Arab Jews as is widely accepted in the humanities and social science research literature. Even more pointedly linguistic and genetic research shows that contrary to the idea that they are so-called indigenous Jews of the Levant, in fact they are predominantly descended primarily from North African Berbers and Arabs.
The truth is that Ashkenazi Jews come mostly from Eastern Europe, with origins in the Caucasus, Turkey and Iran. Sephardim, are mostly of Arab and Berber origins. They are ‘Arab Jews’ with perhaps as little connection to Palestine as the Ashkenazim. There is, in other words, no unitary ‘Jewish people’ with any historically continuous claim to the land of Palestine.
What do the US Congress, Nicolás Maduro, the riots in Iran, Jeffrey Epstein, and the destruction of Syria have in common? Zionism and Israel have been at the forefront of genocide, foreign interference, honey traps, false flags, and other repugnant schemes since before 1948 – albeit obfuscated for decades by the mainstream media. However, the latest genocide in Gaza has lifted the veil from Israeli heinous crimes and transgressions. This article highlights some of the most significant Zionist operations in the world apart from the Gaza genocide.
Epstein & the Maxwells
Jeffrey Epstein and Ghislaine Maxwell ran one of the most notorious sex trafficking and pedophilia rings in the world. Their clientele: elite politicians, royalty, entrepreneurs, celebrities, and scientists from the world over.
A disgraced Jewish media tycoon and politician, Robert Maxwell, was an ardent supporter of Israel. His biographers narrate in their book “Robert Maxwell, Israel’s Superspy” that he was recruited by Israeli intelligence in the 1960s and that he began buying Israeli tech companies for Mossad. He also owned many pro-Israel newspapers and became a UK member of parliament, citing Henry Kissinger as one of his closest friends. After his death, his lavish funeral was attended by Israeli elites, “including no fewer than six living heads of Israeli intelligence organizations.” Israeli Prime Minister Yitzhak Shamir eulogized him in the following words: “Robert Maxwell has done more for Israel than can today be said.”
Years later, Robert’s daughter, Ghislaine, and Epstein would become partners in crime and infamy. While Ghislaine and Epstein were partaking in child sex and human trafficking, it is also alleged that some of their mega-influential friends were also engaging in the same lascivious activities. This influential network and the Epstein files have become a thorn in the US president’s side, who was previously close to the child sex offender. While Trump’s disinclination towards releasing the Epstein files was palpable, the Epstein Files Transparency Act forced the administration’s hand, and it released 33,000 pages in September-December 2025 and over 3 million pages in January 2026 – files that mention Bill Gates, Trump, Les Wexner, Bill Clinton, Stephen Hawking, Noam Chomsky, etc.
These documents also showcase Epstein’s own Mossad ties. The files illuminate via an FBI report that a confidential informant was “convinced that Epstein was a co-opted Mossad agent”. The report claimed that Epstein was a spy. Moreover, his relationship with Ehud Barak, former Israeli prime minister, has also been enlightening, as not only did the duo meet frequently, but Epstein acted like a “superconnector” for Barak, where he linked the latter to Steve Bannon, Sultan Ahmad Bin Sulayem, Woody Allen, and many others. Epstein and Barak met around 30 times between 2013 and 2017. Apart from this, the recent tranche illuminated Epstein’s generous donations to the Friends of the Israeli Defense Forces (FIDF) as well as the Jewish National Fund (JNF), gifting $25,000 and $15,000 to the groups, respectively.
Even before this recent tranche of Epstein files was released, many have alluded to the same Zionist/Mossad connections. For example, Ari-Ben Menashe, a former senior executive for Israel’s Directorate of Military Intelligence, stated in an interview that “I believe the Americans are sort of trapped by the Israelis. Jefferey Epstein is one of their tools to trap them.”
In the same interview, he asserted that Trump is scared of the Israelis because of what they might say against him vis-à-vis women and finances.
In another interview with Narativ, he claimed that he was introduced to Epstein by Robert Maxwell himself in the mid-1980s. Furthermore, he narrated that he met Epstein and Ghislaine Maxwell in the 1980s and that they were both working with Israeli intelligence at that time.
Moreover, Miami Herald investigative reporter Julie K. Brown, author of “Perversion of Justice: The Jeffrey Epstein Story,” stated in a Times of Israel interview that “It’s not beyond the realm of possibility that Epstein had connections to the [Israeli intelligence community].”
Epstein was charged with child trafficking for the first time in 2005, but he served only 13 months in a non-prosecution deal whose architect was Alex Acosta, then a federal prosecutor.
A White House Staffer claimed that Acosta said, “I was told Epstein ‘belonged to intelligence’ and to leave it alone.”
It is understood that Ghislaine Maxwell “lured most of the girls for Epstein’s abuse with promises of easy money, modelling careers, and educational assistance.” Talking to MintPress, a former US intelligence official revealed that Epstein was financed via illicit means so he could compromise/blackmail political targets. This makes the Epstein scandal perhaps one of the most expansive and consequential blackmail operations in history. Even the controversial way Epstein died before his trial, with evidence suggesting it might not have been a suicide, is enough to raise further suspicions.
The Greater Israel project
Israel has never fully declared its borders. Based on Biblical traditions, some Zionists contend that Israel has a birthright to not only the current land it occupies but also the Gaza Strip, the West Bank, parts of Syria, Egypt, and Lebanon.
This ignominious philosophy, while resonant in Netanyahu’s far-right regime, finds its inception long before Israel existed, with Theodor Herzl writing in his diaries that Israel should run “from the Brook of Egypt to the Euphrates”.
The Greater Israel project is an inveterate part of the state’s DNA – in Netanyahu’s Likud party, this concept was enshrined in the founding charter, saying “between the [Mediterranean] Sea and the Jordan [River] there will only be Israeli sovereignty”. Irridentists in Netanyahu’s government, such as Bezalel Smotrich, gleefully assert that Israel’s borders should include Damascus, Syria’s capital. In perpetual fashion to romance Israel at Palestine’s expense, Mike Huckabee, the American Ambassador to Israel, controversially remarked recently that if Israel takes all of the Middle East, “it would be fine”.
The Greater Israel ideology is not as fantastical as one thinks when one considers the historic and contemporary dismantling of the Middle East and beyond. For the countries deemed not as dangerous, a softer approach is used via peace treaties (see Jordan and Egypt) or the Abraham Accords (UAE, Sudan, and so on) – at least for now. Countries such as Syria, Lebanon, Iran, and Iraq, on the other hand, are treated belligerently. Vis-à-vis Iraq, the seminal work “The Israel Lobby & US Foreign Policy” by John Mershaimer and Stephen Walt highlights that “…the [Iraq] war was motivated in good part by a desire to make Israel more secure.” At that time, former PM Netanyahu testified in front of Congress that toppling Saddam would have positive reverberations across the region. Ariel Sharon, then the prime minister of Israel, had provided significant amounts of intelligence to the US regarding Iraq’s WMDs, which later turned out to be false. Furthermore, AIPAC and Washington’s pro-Israel neocons also pushed Bush to invade Iraq – a move that led to the deaths of hundreds of thousands of Iraqis. This exemplifies America’s perennial vassalage to Israel.
The bombardment of Syrian military infrastructure, as well as Israeli troops entering Syria and creating a buffer zone post-Bashaar is also a significant step towards the stated Greater Israel goal. In fact, the country has occupied hundreds of square kilometers since Bashar’s ouster, has taken over the Syrian side of Mount Hermon, and has constructed military bases in key towns in the Quneitra and Daraa governorates. This is on top of Israel’s 1967 annexation of Syria’s Golan Heights. The Israel Air Force is also acting with impunity, with Syria’s foreign minister claiming that the country has suffered 1,000 Israeli airstrikes since Dec 2024.
Presently in Lebanon, the Israeli government is not only regularly and illegally bombarding the country but has also taken over some Lebanese strategic hilltops. There was even a case where an extremist Israeli settler group crossed the border into Southern Lebanon and “called for expansion under the banner of so-called Greater Israel”. IDF soldiers have also been seen wearing a Greater Israel map on their uniforms, which has since gone viral.
When it comes to the West Bank and Gaza, Israeli settler groups have been chipping away slowly yet steadily patroned and emboldened by the country’s most far-right government ever. For example, recently, Israel’s cabinet approved measures allowing Jewish Israelis to purchase land in the West Bank. Finance Minister Smotrich shamelessly avowed that “We will continue to kill the idea of a Palestinian state”, while Israeli Defense Minister Israel Katz detailed that “We are anchoring settlement as an inseparable part of Israel’s government policy”. The latter also said the IDF will “never leave” Gaza and settlements will be built in the north. Therefore, if one is still incognizant of this perverse Greater Israel philosophy, it should be transparent by now that it is no longer a fringe belief but a present-day reality.
The Iranian Riots, the 12-day & Current War
Most analysts agree that the Iranian protests began due to economic frailty, inflation, and lack of water resources, however the riots that ensued, in which even Mosques and Shrines were burnt, were markedly anomalous and have raised questions about outside intervention. Knowing Mossad’s near-monolithic infiltration in Iran (as witnessed historically and recently), it would not be far-fetched to say that the protests-turned-riots were exploited by the agency.
One huge smoking gun was Mike Pompeo, the former CIA director and Secretary of State, tweeting during the protests, “Happy New Year to every Iranian in the streets. Also to every Mossad agent walking beside them”.
Oddly enough, this tweet came days after a Mossad-linked account tweeted to Iranian protesters, “Go out together into the streets. The time has come. We are with you. Not only from a distance and verbally. We are with you in the field”. This was a rare and shocking admission from the agency that it was active inside Iran.
Tweets aside, Mossad’s entrenchment in the country was characterized by how it operated during the 12-day Israel-Iran war in 2025. During the war that Israel started, “the Mossad was at the forefront of Israel’s assassination of nine out of 13 top Iranian military officials and around a dozen Iranian nuclear scientists”. Furthermore, the Mossad admitted that it not only utilized human spies but also drones in Operation Rising Lion. In fact, the agency released footage showing Mossad agents in Iran assembling drones and missiles – a drone base was even set up inside Iran. Israel’s military killed 436 Iranian civilians in the war (compared to Iran’s 28) and also eliminated many of Iran’s military and government leadership in the 12 days.
Coming to the ongoing war waged by the US-Israel nexus, this too is a part of the Greater Israel project. Israel and US bombings have killed over 1000 civilians in just a few days of fighting (at the time of writing this), which includes 183 children – most of the children passed away in the Minab School strike. They have also assassinated Iran’s Supreme Leader and members of his family. The casualties are increasing rapidly as the war rages on, and hundreds of thousands of Iranians have been displaced. Iran has retaliated by attacking US military bases in the region, as well as Israel, and at least 16 countries have become involved in this conflict due to Zionist aggression. Marco Rubio admitted that Israel forced their hand in attacking Iran; however, due to the backlash, he backtracked on this. Israel has also started intensifying its attacks in Lebanon and is razing its cities. The IDF has killed around 102 civilians, and its actions have caused the displacement of a hundred thousand Lebanese.
Venezuela & Maduro
Why did Netanyahu celebrate the capture of President Maduro? Why did Mike Huckabee imply in an interview that the Venezuelan regime change operation was a massive victory for Israel? On the surface, it appeared that the US’s motive for the capture of Venezuela’s president was to counter drug trafficking or to satiate its gluttony for oil, but digging deeper reveals Israel as a key motivator.
Since 2009, Venezuela, then under Hugo Chavez, severed relations with Israel due to the 2008-09 Gaza War. Venezuela had then become closer to Palestine, being the first country in the Americas to recognize it. Diplomatic and economic relations also thrived with Iran and with Hezbollah. Pro-Israel US think tanks, from the Foundation for Defense of Democracies to the Atlantic Council, have touted that Hezbollah and Hamas’ alliance with Caracas poses a direct threat to the US.
Therefore, Maduro was simply a victim of extending Chavez’s pro-Palestine and anti-Zionist foreign policy.
So in taking down Maduro, a key Iranian and Hezbollah ally/satellite was severely undermined – at least from Tel Aviv’s standpoint. This becomes more apparent when viewed not as an isolated incident but as a panoptic Zionist framework of weakening the global pro-Palestinian and Iranian network: see the Syrian regime change, bombardment of the Houthis, the elimination of Hezbollah’s top leadership, and Iranian protests etcetera.
The US and Israel will obviously be looking to set up a pro-Israel regime now. The main opposition leader in Venezuela, Maria Corina Machado, might be one candidate. She recently met Donald Trump and gifted her own Nobel Peace Prize to him. Many legislators in the US back her to be the next president, although Trump has not endorsed her so far. She, however, has stated that she would relocate Venezuela’s embassy to Tel Aviv and that “Certainly, Venezuela will be Israel’s closest ally in Latin America”. Whether she is backed as the successor or someone else, there is no way the US will allow a continuation of the pro-Palestinian foreign policy Venezuela adopted. This stratagem also falls poignantly into Israel’s Issac Accords – the Latin American version of the Abraham Accords, which the pro-Zionist president of Argentina, Javier Milei, launched alongside Israel. Greg Pence, in his article, aptly writes, “Israel is no longer merely a regional ally but has become the benchmark for defining threats in U.S. foreign policy”. Venezuela was the latest fatality of a bellicose, hyper-Israel-centric US foreign policy.
The Future
This list was certainly not exhaustive. It is missing the recent Somaliland recognition issue; the use of Israeli-made spyware such as Pegasus; Mossad and CIA support for Baloch separatists in Pakistan and much more. The conspiracy theorists were right about a few things: The elites are rapists, child abusers, and human traffickers; The Middle East’s destabilization is by design – not circumstantial; Genocides and regime changes are pardonable when the ones committing them are the ones ruling over us. The controlled media has kept the world benighted and ignorant of the truth. All these repulsive facts point towards one devil: Zionism.
So, what happens next? The voracious Zionists in their so-called rectitude will not cease until they fulfil their prophecy of building the Third Temple, expanding their borders, welcoming their Messiah, removing the Palestinians, and prevailing over non-Jews.
Almost all the Gulf states, including the UAE, Kuwait, Qatar, Bahrain, Iraq, Saudi Arabia, and Jordan, that host American military bases or troops, have been targeted by Iran in the latest military confrontation between the Islamic Republic and the US and Israel.
The current war between arch-foes Iran and Israel and its all-weather friend, the US, has laid bare the hollow security assurances that the Gulf nations have been assured of for decades, retired Colonel Rajeev Agarwal, a West Asia expert and a Senior Research Consultant at the New Delhi-based think tank, the Chintan Research Foundation, told Sputnik.
“It was under this illusion that a large number of Gulf countries had agreed to not only buy very expensive American weapon platforms but also host American military bases in the region,” he said.
The story of American security guarantees goes back to the period of 1979-80, soon after the Iranian revolution, when most countries in the region felt threatened by the Islamic regime in Iran.
At his 1980 State of the Union Address, in reaction to the 1979 Iranian revolution, then-US President Jimmy Carter had assured the region, stating, “An attempt by any outside force to gain control of the Persian Gulf region will be regarded as an assault on the vital interests of the United States of America, and such an assault will be repelled by any means necessary, including military force”.
The failure of the US to protect its military bases and the host Gulf countries is, therefore, a major embarrassment for the US, the Indian Army veteran underscored.
“The fact that Iranian missiles have caused large-scale damage, including the Fifth Fleet HQ and the Naval base in Bahrain as well as military bases in Kuwait, Doha, UAE, Jordan, etc., is proof. In fact, on the night of 1-2 March, the US base in Ebril, Iraq, which is basically a huge ammunition depot, was targeted and completely destroyed,” Agarwal highlighted.
Strikes into the Gulf countries are proof that the security guarantees offered by the US are ineffective and that the Gulf countries cannot rely on American security assurances for their safety in the future, he added.
In fact, the strikes into Doha, Qatar, lay bare the iron-clad security guarantees that the US had assured Qatar after Israel had fired missiles into Doha in September 2025, targeting the Hamas leadership, the defence commentator stressed.
“As regards Iran’s ability to strike into the Gulf nations, all the US bases are well within the reach of Iranian missiles and drones. Despite a large number of missiles getting intercepted, a fair number do escape the Air and Missile Defence Shield to reach their targets. The strikes by drones and missiles in Gulf countries were also a part of the pre-determined military strategy of Iran,” Agarwal noted.
It had, in fact, announced it well before the start of the conflict that, in case of a war started by Israel and the US, all American bases and assets in the region would be considered legitimate military targets and that would bear the brunt of Iran’s punitive response. Iran had also informed the neighbouring Gulf countries that such strikes would not be aimed at targeting their sovereignty and that would be restricted to US, Israeli and Western targets, he pointed out.
There is no doubt that this is the biggest eye-opener for the region on the illusion of a security umbrella by the US. There were previous instances too, though isolated in nature, where the Gulf nations felt betrayed but were convinced that the American security guarantees were still vital for their collective security, the strategic affairs pundit reckoned.
“This war is a lesson not only for the Gulf countries but also for any other nation wanting to secure its national security exclusively through external players. And the lesson is ‘National security cannot be bought’. Integral and organic security systems are vital to ensure a nation’s security. Once this war is over, the region will have to seriously review its security architecture and come up with solutions that are more inclusive and collaborative in nature,” Agarwal concluded.
Iran has an “inalienable right” to enrich uranium for civilian use, Iran’s foreign minister, Abbas Araghchi, told the U.S. delegation with frustration in the final round of talks before the bombs started to fall on Iran.
And the United States has an “inalienable right” to stop you, Trump’s special envoy Steve Witkoff answered with hubris.
Araghchi is right; Witkoff is wrong. Though the U.S. and its partners have presented the public with a war that was caused by Iran’s refusal to compromise on its civilian nuclear program, as a signatory to the Nuclear Non-Proliferation Treaty, Iran has “the inalienable right to a civilian program that uses nuclear energy for peaceful purposes.”
That Iran was enriching uranium for peaceful purposes has been verified by the multiple consecutive International Atomic Energy Agency (IAEA) reports that followed the JCPOA nuclear agreement with Iran and by the 2022 U.S. Department of Defense Nuclear Posture Review and, most recently, by the 2025 U.S. Annual Threat Assessment.
Despite their “inalienable right,” Iran made the major concession of negotiating significant limitations on its nuclear program that could have met U.S. redlines. Instead, the negotiations were interrupted by bombs falling on Iran in an attack that was neither necessitated by the immediate need to defend against an attack nor sanctioned by the Security Council. Negotiations on Iran’s legal nuclear program were answered by an illegal war.
Though the United States seems to have been willing to negotiate if negotiation meant Iran capitulating to its demands, they seem to have been unwilling to negotiate, not only on guarantees against a nuclear weapons program, but on the demand that Iran give up its enrichment program entirely. It was the American demand that Iran could not enrich uranium to any level for the next ten years that finally triggered Araghchi’s frustrated cry that Iran has the “inalienable right” to enrich uranium for civilian use.
Iran offered the Americans a compromise that could have been received by the U.S. as, what former Iranian nuclear negotiator and Ambassador Seyed Hossein Mousavian called in an email correspondence, “a historical JCPOA PLUS deal.” But Washington said no.
There were reportedly three areas in which Iran was unwilling to sufficiently capitulate to American demands. The first was zero enrichment. The U.S. demanded no enrichment for the next ten years. Axios reports that, in its place, the “U.S. offered Iran free nuclear fuel for a civilian nuclear program.” When Iran refused, the U.S. said it was “a big tell.”
Had the U.S. sent diplomats with a historical understanding of the issue they were negotiating, they would have known that there were other interpretations. Iran has always made clear that they would not accept a situation like the one offered because of bitter historical experience.
On more than one occasion in the past, when Iran relied on others to provide its enriched uranium, the U.S. exercised its power to block it and deprive Iran of enriched uranium. When Iran began its nuclear program, they were only enriching uranium to the 3.5% required by its power reactors to produce energy. For the 19.5% enriched uranium needed for medical isotopes for imaging and treating cancer and kidney disease, Iran relied on an agreement with Argentina to supply it. When the uranium was used up, Iran requested that the IAEA help it purchase more under that body’s supervision, which Iran has the right to do as a signatory to the NPT. But the United States and Europe put up roadblocks and prevented the purchase.
Two decades later, Iran again agreed in principle to a nuclear fuel swap that would send their low enriched uranium out of country to be returned as 19.5% enriched uranium for medical use. But it was a trick. The U.S. wanted all Iran’s uranium to be sent out at once before any uranium would be sent back much later. The U.S. was trying to empty Iran of its uranium. When Iran offered a counterproposal of sending out smaller batches of low enriched uranium while receiving simultaneous small batches of uranium for medicinal use, the U.S. ignored the offer and the deal died.
When, one more time, Brazil and Turkey tried to broker a deal with similar simultaneous swaps, Iran agreed, but the U.S. ignored it and reprimanded Brazil and Turkey. On another occasion, when Iran turned to France for enriched uranium, the U.S. pressured them not to provide it.
Iran has learned that relying on others to provide enriched uranium leaves them vulnerable to the United States cutting them off and leaving them with none. Hence the vow that Iran would never again yield their right to enrich their own uranium for civilian purposes.
But Iran was willing to negotiate a deal that would ensure that there could never be a path for that low enriched uranium to become the highly enriched 85% uranium needed for a nuclear weapon. They offered layered options. Mousavian catalogued them for me:
“Iran had accepted coercion verification by the IAEA, to resolve all technical ambiguities, zero stockpile, dilute high-level enrichment, reduce enrichment level to below 5%, suspend the enrichment for some years and even to go for a regional consortium.”
There were three options on the table. In the first, Iran was willing to put itself under maximum inspections, to convert its stockpile of 60% enriched uranium, and cap its enrichment at the 3.67% needed for a civilian energy program.
In the second, Iran was willing to limit their role in the enrichment cycle by becoming a member of a nuclear enrichment consortium. The consortium could include Saudi Arabia, the United Arab Emirates, and perhaps others. Enrichment would be capped at the 3.67% required for civilian use and monitored by the IAEA. Most importantly, a consortium would allow Iran to enrich uranium but deny it access to the full enrichment process by distributing various roles in the process across different member states.
There are also reports that Iran proposed suspending enrichment for three to five years and then joining the regional consortium.
In the most recent, according to Oman’s foreign minister, Badr Albusaidi, who was mediating the most recent talks between Iran and the United States, Iran “agreed not to stockpile excess nuclear material that could be used to build a bomb.” Since Iran would use all of its low enriched uranium for civilian purposes, leaving none to stockpile for any further use, that would ensure “that Iran will never ever have the nuclear material that will create a bomb.” Albusaidi clarified that that meant “there would be zero accumulation, zero stockpiling and full verification… by the IAEA.”
The pathway to a bomb was closed and a deal was “within our reach” when the bombs fell on Iran.
The other two areas of Iranian intransigence were over their program of military national defense. The United States insisted that Iran negotiate on its short and intermediate range ballistic missile program, but Iran refused. “We cannot continue to live in a world where these people not only possess missiles but the ability to make 100 of them a month,” an American official toldAxios. Iran’s missiles are crucial to its national defense and possessing them is entirely legal. Every nation has a defense program, and at least thirty-one, including some that are potentially hostile to Iran, include ballistic missiles in that program, including the U.S. and several of its allies and partners, including Bahrain, Saudi Arabia, Egypt, the United Arab Emirates, the United Kingdom, France, Greece, Israel, Poland, Romania, Turkey, and Ukraine. There is no legal argument for compelling Iran to end its missile program and no legal reason to go to war to force them to do so.
The final reason was Iran’s refusal to address its network of proxies. Stripping Iran of its ballistic missiles and its partners is stripping Iran of any ability to defend itself. And, again, there is nothing illegal in Iran supporting regional partners. And they are not the only one, asthe training and financing of the Mujahideen-e-Khalq (MEK), a dissident Iranian opposition group, shows, to support proxy forces.
“A peace deal is within our reach if we just allow diplomacy the space it needs to get there,” the Omani foreign minister said. But the United States did not allow the diplomatic space and opted, instead, for a war that violates the United Nations charter and hastens the death of international law.
The Man Who Lost a Foot Before Anyone Told Him the Truth
Morgan Nolte, a board-certified clinical specialist in geriatric physical therapy, walked into an apartment to evaluate a patient with a history of diabetes and multiple amputations. Several toes gone. One foot removed entirely. She began the standard medication reconciliation—reviewing every drug the patient was taking—and stopped.
“Where’s your diabetes medications? You have amputations, you have a history of diabetes, you’re not taking any medications. Let me check your blood sugar, because it’s probably raging high.”
“I don’t need them anymore,” he said. “I got off of them.”
He had changed his diet. Started eating low carb. Reversed his diabetes.
What motivated him to finally make that change? “I didn’t want them to take my other foot, because then I couldn’t live independently anymore.”
The system had taken his toes. Taken his foot. Failed him completely. Only then, facing the loss of the second foot—and with it, his independence—did he discover what no one had told him: the disease was reversible all along.
A Last Ray of Hope
Nolte describes another patient. A woman, morbidly obese, bedbound for ten months. She had sold assets to qualify for Medicaid, to get the care she needed. The physical therapy order read, literally, “as a last ray of hope.” The woman had wounds, skin breakdown, vision loss from diabetes. She couldn’t get up. Couldn’t go to the bathroom. Couldn’t do anything anymore. She wasn’t old.
And she was taking massive doses of insulin.
When Nolte visited, she observed the household. Potato chips. Spaghetti. The woman’s husband had consulted a nutritionist, who told him to switch to whole wheat pasta.
“Let’s pump the body with some glucose,” Nolte reflected, “and then let’s add more insulin to get rid of that glucose. But that’s making the problem of insulin resistance even worse.”
The word Nolte uses for this: heartbreaking.
It’s why she left traditional practice.
What Causes Insulin Resistance?
Type 2 diabetes is defined as a disease of insulin resistance. The cells resist insulin’s signal to absorb glucose from the blood. Blood sugar rises. The standard treatment: give insulin to force the glucose into the cells.
The logic seems sound until you ask a question that medical training apparently discourages: What causes insulin resistance in the first place?
Jason Fung, a nephrologist and researcher, poses an analogy. When antibiotics are first introduced, they work brilliantly. With time and steady use, bacteria become resistant. The drugs lose effectiveness. The body’s response to persistent exposure is adaptation—resistance. This principle is universal in biology. Resistance requires two conditions: high levels of the stimulus, and persistence of those high levels.
Antibiotics cause antibiotic resistance. Viruses cause viral resistance. Drugs cause drug tolerance.
Insulin causes insulin resistance.
This is not speculation. Insulinomas are rare tumors that continuously secrete abnormally large amounts of insulin. Patients with these tumors develop insulin resistance in lockstep with their rising insulin levels. Remove the tumor surgically, and the insulin resistance reverses.
Experimentally, constant infusion of insulin into healthy, non-diabetic volunteers induces insulin resistance within days—a 20 to 40 percent drop in insulin sensitivity. Young, lean, healthy men can be made insulin resistant simply by giving them insulin.
When type 2 diabetics are started on intensive insulin therapy, their average dosage climbs steadily. In one study, patients went from zero to 100 units daily over six months. Blood glucose control improved. But the more insulin they took, the more insulin resistant they became. The underlying disease worsened even as the surface marker—blood glucose—looked better.
Ben Bikman, a metabolic researcher, frames it starkly: “Giving a type 2 diabetic insulin is like giving an alcoholic another glass of wine. We’re giving them more of the very thing that caused the problem.”
The Vicious Cycle
The vicious cycle operates like this: A patient is prescribed insulin for high blood sugar. The insulin forces glucose into cells that are already overfull. The patient gains weight—commonly 20 to 30 pounds. Weight gain worsens insulin resistance. Blood sugar rises again. The doctor increases the insulin dose. More weight gain. More resistance. More insulin.
Fung describes patients confronting their doctors: “You gave me this insulin. I gained 30 pounds, and then you gave me more insulin. How is that making me better?”
It’s not.
Fung uses the image of an overfilled balloon. You keep forcing more air into a balloon that’s already stretched to capacity. It takes more and more pressure to add anything. Eventually something gives. But the standard treatment keeps pumping.
Gary Taubes documents a particularly graphic case in his research on insulin’s effects. A woman developed type 1 diabetes at seventeen. For the next forty-seven years, she injected insulin into the same two sites on her thighs. The result: cantaloupe-sized masses of fat on each thigh—visible proof of insulin’s direct fattening effect on tissue, independent of diet or calories consumed.
A 2008 study in the New England Journal of Medicine found that type 2 diabetics on intensive insulin therapy gained an average of eight pounds. Nearly one in three gained more than twenty pounds in three and a half years.
The treatment makes patients fatter. Fatter patients become more diabetic. More diabetic patients need more treatment.
Chronic and Progressive
Fung practiced nephrology for ten years, following orthodox protocols for his diabetic patients. When he looked back at the results, he realized he had not helped them much. He had made them fatter, sicker, and more reliant on drugs.
This confronted him with a choice that confronts every physician working within this system. If the treatment isn’t working—if patients are getting worse—there are two possible explanations. Either the treatment is wrong, or the disease is simply like this: chronic and progressive, inevitably worsening no matter what you do.
Doctors, Fung observes, don’t want to blame themselves. So the profession chose the second explanation. Type 2 diabetes was declared a chronic, progressive disease. The treatment was correct; the disease was just incurable.
“The doctor said, well, the treatment is correct because the blood glucose is fine. Therefore, this must be just the way the disease is—chronic and progressive. Not understanding that their entire treatment paradigm was quite incorrect.”
This framing persists despite obvious counter-evidence. Everyone in medicine knows that if a type 2 diabetic loses significant weight, their diabetes usually improves dramatically or disappears entirely. The disease is observably reversible. The profession declared it irreversible anyway.
Fung identifies two “big lies” in diabetes treatment. The first: that type 2 diabetes is chronic and progressive and cannot be cured. The second: that lowering blood sugar is the primary goal. The actual disease is not high blood sugar—that’s a symptom. The disease is too much glucose in the body and too much insulin trying to manage it. Lowering blood sugar with more insulin just moves the glucose from the blood into the tissues, where it continues to cause damage. The trash isn’t thrown out; it’s hidden under the bed.
Twenty Years On, Off in a Month
The reversal evidence is not subtle. Fung conducted a case series with three patients who had been on insulin for twenty years. They implemented 24-hour fasting three days per week. Within one month, all three were off all their insulin.
Twenty years on the drug. Off in a month.
Nolte reports clients getting off blood pressure medications they’d taken for years within a couple of months. Cholesterol medications. Blood sugar medications. “Happens all the time,” she says. “All the time.”
The man with the amputated foot reversed his diabetes after losing multiple toes and an entire foot to a treatment paradigm that never addressed the underlying cause. His remaining independence depended on figuring out what his doctors hadn’t told him.
Tim Noakes, the South African scientist, puts the absurdity plainly: The medical profession has never encouraged people with lactose intolerance to consume milk, or people with gluten intolerance to eat wheat, or alcoholics to keep drinking. “Yet somehow this common-sense rule seemingly does not apply to the treatment of diabetes.” Patients who cannot properly metabolize carbohydrates are told to eat carbohydrates and inject insulin to manage the consequences.
We fuel the fire with carbohydrates and try to put it out with insulin. The fire grows.
The New Standard of Care
In 2023, the American Diabetes Association updated its standards of care. For patients 65 and older with few other health problems, an A1C of 7 to 7.5 is now acceptable.
An A1C over 5.6 indicates prediabetes. Over 6.5 indicates diabetes.
The new standard of care is diabetes.
As populations get sicker, the definition of sickness is adjusted. The threshold for concern rises to meet the worsening baseline. Physicians become desensitized to illness. One of Nolte’s members lost 50 pounds, eliminated her blood pressure medication, resolved her joint pain. At a church function, someone asked if she was sick—she looked so thin. “I’ve actually never been healthier,” she said.
We are becoming desensitized to what healthy bodies look like. We are becoming accustomed to people who are overweight, on multiple medications, progressing through a disease they were told could not be stopped.
She has seen a physician refuse to order a fasting insulin test, writing back: “I reached out to some colleagues in endocrinology and they said they only check insulin for a type 2 diabetic. You’re only prediabetic, so we’re not going to do that. And you can’t really reverse insulin resistance anyway.”
The patient needed a new doctor. But most doctors learned the same curriculum.
The Endpoint
The woman bedbound for ten months, covered in wounds, losing her vision, taking massive amounts of insulin while eating spaghetti—she represents the endpoint of a treatment logic that inverts cause and effect. The system identified high blood sugar as the enemy. It deployed a weapon that causes weight gain, which worsens insulin resistance, which raises blood sugar, which requires more of the weapon. Then it declared the resulting devastation proof that the disease was always going to progress this way.
The man who reversed his diabetes after losing a foot did so by removing carbohydrates from his diet—by stopping the influx of glucose that insulin was trying to manage. He addressed the cause. The insulin had been addressing the symptom while worsening the cause.
Prescribing insulin for type 2 diabetes is putting gasoline on a fire. Patients see this. “You gave me this insulin, I gained 30 pounds, and then you gave me more insulin.” They experience the paradox in their own bodies. But the institution that created the paradox cannot acknowledge it without acknowledging decades of harm.
So the disease remains chronic and progressive. The patients remain blamed for their failure to comply. And the treatment that worsens the condition remains the standard of care.
References
Books:
Taubes, Gary. Good Calories, Bad Calories: Fats, Carbs, and the Controversial Science of Diet and Health. Anchor Books, 2008.
Taubes, Gary. Why We Get Fat: And What to Do About It. Anchor Books, 2011.
Noakes, Tim. Lore of Nutrition: Challenging Conventional Dietary Beliefs. Penguin Random House South Africa, 2017.
Noakes, Tim, et al. Diabetes Unpacked: Just Science and Sense. No Sugar Coating. Columbus Publishing, 2017.
Fung, Jason. The Diabetes Code: Prevent and Reverse Type 2 Diabetes Naturally. Greystone Books, 2018.
Bikman, Benjamin. Why We Get Sick: The Hidden Epidemic at the Root of Most Chronic Disease—and How to Fight It. BenBella Books, 2020.
Interviews and Presentations:
Fung, Jason. “Get Rid of Diabetes Once and for All.” The Jesse Chappus Show, September 2022.
Nolte, Morgan. “How to ELIMINATE Insulin Resistance Once and for All (COMMON Early Signs).” The Jesse Chappus Show, December 2024.
Bikman, Ben. “If You DO THIS Your Insulin Resistance Will Be Normal FAST!” The Jesse Chappus Show.
When the House of Commons was debating how much to increase the time limit for detention without trial the question of torture came up. Officially this was limited to the nice considerations of whether it was all right to send people to places where torture is used and whether Britain can use information collected by the use of torture in other countries. This discussion gave an impression of democratic Britain as the home of civilised behaviour where the very idea of torture is repugnant to our legislators – unlike, say, the US with its secret CIA jails… In reality, the British state has a long history of using and developing a whole range of torture techniques. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.
 • Osama Bin Laden WAS NOT Responsible for 9/11
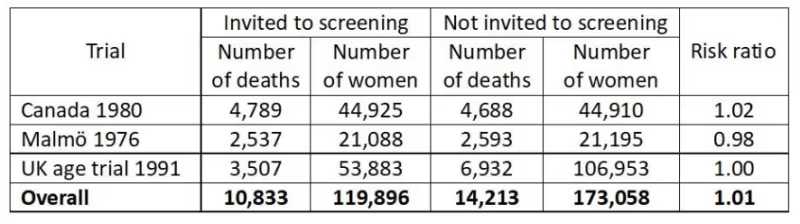
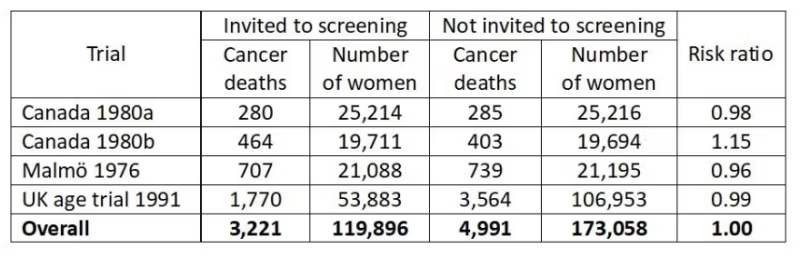
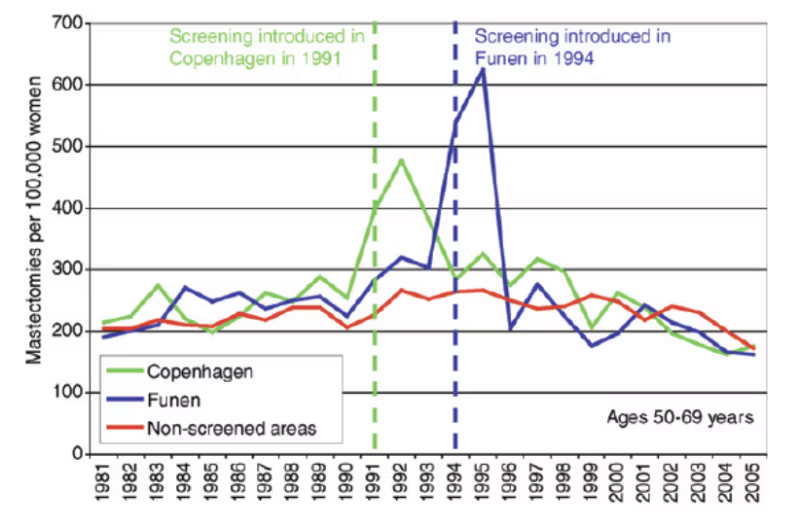
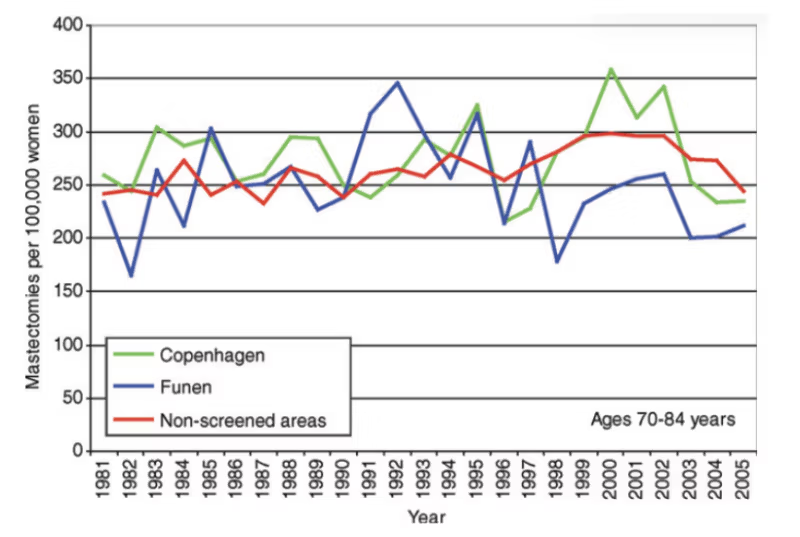



 During many years of contacts with Iran, the IAEA has never found grounds to refuse negotiations on Iranian nuclear program, Russian Foreign Ministry Spokeswoman Maria Zakharova said.

 Aletho News
 Aletho News
