HART vs SAGE
HART Pathology Lead Dr John Lee appeared on Good Morning Britain this week alongside Professor Susan Michie who sits on SAGE and the Scientific Pandemic Insights Group on Behaviours (SPI-B).
Dr Lee noted the lack of evidence for asymptomatic spread of SARS-CoV-2 and also pointed out the absence of diverse scientific discussion in the media. Susanna Reid denied this, stating that the other side was being heard on social media and in the papers. However, these avenues are not the same as trusted mainstream TV programmes and the void of diverse thinking here has no doubt hampered the public’s understanding of ‘the science’.
Reid went on to say that ‘we know from the evidence that lockdown does work’. This is simply not true. Increasingly, the body of evidence points to the exact opposite as can be seen here and in dozens of published peer-reviewed papers, in stark contrast to the absence of evidence demonstrating significant benefits from lockdown when examining the real-world (as opposed to modelled) evidence. In addition, these models neglect to adequately assess the collateral harms.
Reid highlighted the figure of 126,000 COVID-19 deaths. However, there is a serious issue with excess, mainly non-Covid deaths at home which have reached over 50,000 in total. Here in the UK this figure currently sits at roughly 1,000 people each week. Perhaps many of these people would not have been put off seeking medical treatment had Michie, and her behavioural science colleagues, not terrified them into ‘staying at home’. A review of these covert, ethically questionable, psychological strategies was recently published by a member of HART here.
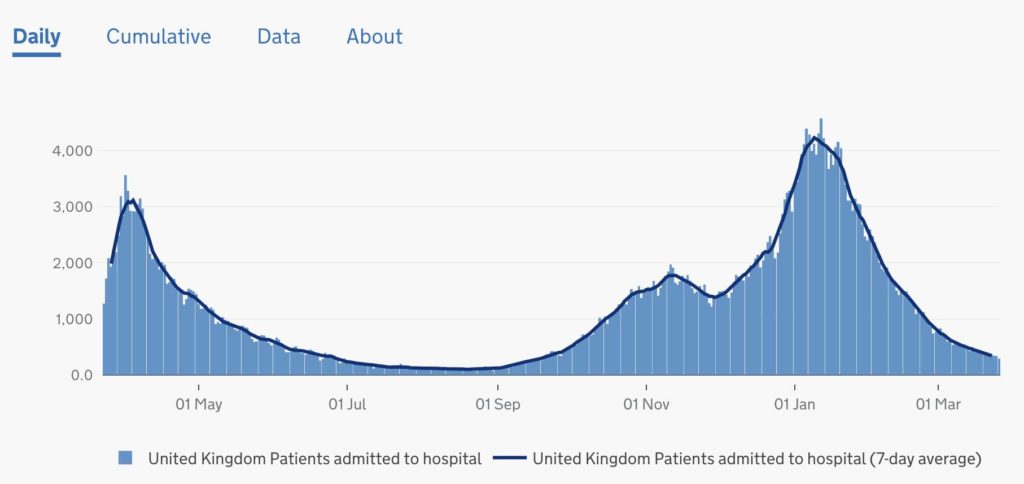
Michie also talked about mutant variants and how many people it is or is not ‘safe’ to interact with. It is a shame that these questions were addressed to a psychologist, rather than to a pathologist with medical training. No mention was made of the inevitable seasonal decline of the virus and Michie mentioned several thousand new cases a day, neglecting to outline how these figures relate to hospital statistics (currently at September levels).
Patients admitted to hospital in the UK
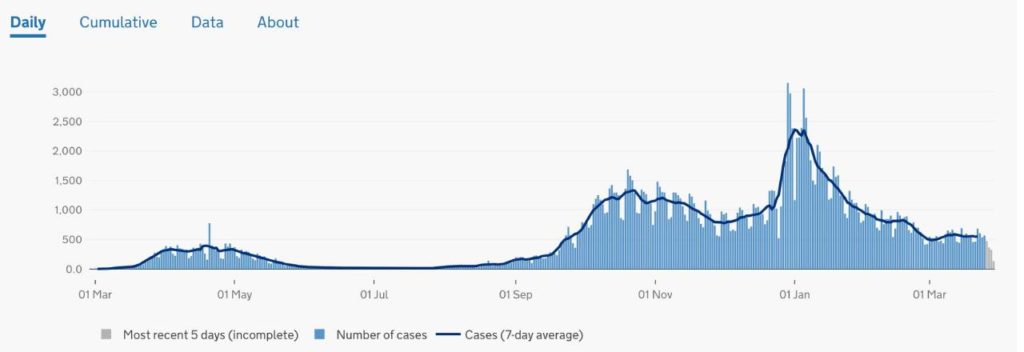
In fact, we know from numerous studies that there will be a significant number of post infectious positives at this stage with patients admitted to hospital for other reasons, incidentally testing positive. In the community, the expected surge in cases in the secondary school population has not materialised and the results of testing show that there is no active SARS-CoV-2 in that population. Overall, there is minimal evidence of residual coronavirus in the community. Mitchie went on to say cases are rising in Scotland. Again, this simply is not true.
Cases in Scotland
Michie then described the possibility of exponential growth if we remove measures too quickly, which shows a misunderstanding of the current immunity status of the population. With so many now having antibodies through natural infection or vaccination, it seems highly unlikely that this virus could now spread in an epidemic fashion. A transition into an endemic phase, as with seasonal flu in which there may be localised outbreaks, mainly in specific institutionalised settings, is much more likely.
The problems with Michie’s thesis are underpinned by the false assumption that asymptomatic spread is a major driver of transmission. There is no robust evidence for this phenomenon, and it would go against decades of understanding of respiratory viruses and how they are transmitted. By continuing to disseminate this questionable hypothesis to the British public, she is continuing to spread unnecessary fear. A far more balanced approach would be to focus on:
1. The viral season rapidly waning
2. The huge percentages of vaccinated people & those with acquired or innate immunity
3. The fact that children are not a significant driver of the disease
4. The fact that clinical symptoms are the driver of transmission of respiratory viruses
We need to stop ‘acting like we’ve got it’ and start living what is left of our finite lives.
Data not dates
It was reported this week that the weekly COVID-19-related death toll has fallen to the lowest rate since October. However, in a scenario of ever-decreasing death rates and diminishing prevalence of the virus, a comparison to the COVID mortality rate at the beginning of the winter wave seems somewhat arbitrary and of no relevance to the current situation. Once deaths reach minimal levels, this indicates that cases must have been minimal 18 days earlier.
A far more sensible metric for comparison would be the current test positivity rate. Since 21 March the PCR positivity rate has been only 2.1% i.e. only 1% higher than the baseline positivity rate we saw in summer. Including all testing, only 0.43% of 1.2 million tests were positive on 29 March. To put this in perspective, 9,957 people tested negative out of every 10,000 tests done. Remaining locked down under these circumstances indicates that the Government has adopted a “Zero Covid” strategy, despite their own admission of the futility and harm that would be caused by attempting this policy. Patrick Vallance himself said: “I think the chance of eradication, true eradication – ie zero – are in themselves close to zero.”
Tracking the success of the vaccine and maintaining confidence Last week, Sir Christopher Chope MP and William Wragg MP raised important questions in the House of Commons regarding COVID-19 deaths following coronavirus vaccination. Health Secretary Matt Hancock responded ‘I think we do have it’. Hancock also referred to the SIREN study but this only covers healthcare workers and therefore does not provide the complete information required for monitoring adverse effects, safety and efficacy. HART would urge active data capture, including a simple vaccine history taken at every unscheduled attendance at a hospital.
We must not forget that these are experimental vaccines, without full regulatory approval but issued under emergency waivers. It would be concerning in the extreme if data were not being collected or if the level of scrutiny of vaccine effects was not sufficient. The availability and rapid access to this data is vital in maintaining the public’s confidence in the vaccination programme.
US states continuing to open up Governors across the US are continuing to open up their states and remove COVID-19 restrictions. Earlier this month, Mississippi and Texas both announced the end of business restrictions and mask mandates, while North Dakota went a step further and implemented legislation to make mask mandates illegal. In Florida, Governor DeSantis is to forbid vaccine passports with an executive order.
In Texas, COVID-19 cases and hospitalisations carry on their downward trajectory despite their removal of measures being described variously as: “absolutely reckless” by California Governor Gavin Newsom, “it just is inexplicable why you would want to pull back now” by Dr Fauci and “neanderthal thinking” by President Joe Biden.
Essential viewing Nick Hudson, co-founder of the international group Pandemics ~ Data & Analytics (PANDA), has given a keynote address at the inaugural BizNews Investment Conference in South Africa. In his speech, Hudson gives a comprehensive overview of the COVID-19 pandemic and explores how instead of helping to slow the spread of the virus, lockdowns have led to infant mortality, poverty, starvation, joblessness and a major upsurge of psychological disorders. Well worth taking 30 minutes to watch in full, here. This video is currently being viewed by several thousand people per hour.
24 March 2021
There is no emergency COVID-19 cases are low and all-cause deaths are now back to normal pre-pandemic rates and falling. All vulnerable groups have been offered a vaccination. There are no longer any justifiable or ethical reasons for prolonging Covid-related statutory ‘emergency powers’.
It is anticipated that all phase 1 priority groups (approximately 32 million people) will have been offered a vaccine by 15 April, a group accounting for 99% of the deaths last spring. This will be an amazing achievement. The virus is now endemic and will circulate at very low levels this summer and is then likely to join the range of respiratory viruses circulating each winter. Talk of continuing social distancing and masks for several years is therefore unnecessary and unhelpful. We urgently need to reduce fear and increase hope as we recover from this crisis.
It is vital that we harness the benefits of the rapid vaccine rollout by acknowledging we are no longer in an emergency. We can and must reopen society. Government and SAGE will need to undo the negative messaging, after a year in restrictions many people will still be fearful to pick up their lives again. News that a £2m Government contract has just been awarded for a COVID Public Information Campaign over the next two years is concerning. The repeal of the coronavirus emergency legislation would give a very positive message of confidence and hope to the British public. Therefore, HART continues to urge all MPs to vote against the renewal of the Coronavirus Act this week in Parliament.
No evidence of SARS-CoV-2 in schools HART predicted 24,000 false positive results in children in the first week of mass testing based on 4 million children being tested twice. In the week of 4 March, only 2.7 million tests were carried out on secondary school children and 0.05% of them were positive. Our previous prediction was based on the estimated false positive rate for the adult population of 0.3%. Testing of university students prior to Christmas showed a very low false positive rate of at or below 0.06% including Newcastle, Hull, Exeter and Birmingham. Testing among school children is demonstrating a similar rate. The good news is that these numbers are so low that no-one can be left in any doubt that they represent only false positive results and that there is no SARS-CoV-2 at present in the secondary school population. The ONS estimated that there would be SARS-CoV-2 in 0.4% (1 in 250) 12-24 year olds, so this is another instance of failed testing with PCR. With no virus in schools, there is now no justification for the mask mandate or mass testing.
Is mask wearing benign? This week, Dr Mary Ramsay from Public Health England told the BBC that face coverings were a ‘lower level restriction’ that ‘people can live with’ and they should continue to be worn ‘for a few years’. Her words are similar to those used by politicians to justify the introduction of the mask mandate in summer 2020, when it was portrayed as an extra layer of protection, a precautionary measure, a nothing-to-lose restriction.
While there is no evidence that masks significantly reduce transmission when worn routinely in real-world settings, there is recognition that they may constitute an infection hazard, particularly when used incorrectly. Masks potentially cause physical harms, while the social and psychological cost of concealing our faces from other people is considerable. Face coverings impair all forms of communication and human connection, make lip-reading impossible for the deaf and constitute a gross impediment to children’s social development.
A highly visible reminder that danger is supposedly all around, face coverings are fuelling widespread, irrational fear at a time when the current viral threat is very low and the vulnerable have been vaccinated. As we look to re-activate the economy and reopen our society, this mask-induced fear will act as a major obstacle. HART believes the Government should now lift the mandate and allow people to decide for themselves whether to wear one. It is time to trust the public with their own personal risk-based decision making.
The futility of border closures Summer holidays are in doubt again, with the news that a £5,000 fine will come into force for anyone trying to travel abroad without a ‘reasonable excuse’. Matt Hancock has said the restrictions are to ‘guard against’ new variants that might put the vaccine rollout at risk. Professor Neil Ferguson was also quoted as saying we ‘should be planning on summer holidays in the UK not overseas’. Closing international borders to keep out ‘foreign mutants’ of an already endemic virus is neither useful nor possible. It is worth noting that mutant variants from abroad pose no extra threat compared with any homegrown variants and are likely to have very similar sequences. Mutant variants, emerging overseas or domestically, are an inevitable biological reality once a virus is in the population, as is the case in the UK. The virus will mutate slowly over time, irrespective of borders.
Mandatory vaccination for care home workers The news that the government is considering making COVID-19 vaccination a legal requirement for all care workers is concerning and against international law. This would create a precedent of eroding informed consent, and is difficult to justify when the vulnerable population have themselves already been offered at least one dose of vaccine, especially in the light of Scottish data that suggests the Oxford-AstraZeneca vaccine reduces risk of hospitalisation by up to 94%. If this is case, would it be better to prioritise second doses for all vulnerable groups, thus rendering the vaccination of our younger, healthy population unnecessary?
And some good news… The number of patients admitted per day to intensive care units is now close to normal, pre-pandemic levels for the time of year. It appears we are well beyond the risk of overwhelming the NHS – further highlighting that now is the time to lift restrictions and allow the NHS to begin rapidly addressing the backlog of postponed appointments and operations. There is no sign of a virus resurgence in American states such as Florida and Texas which have lifted restrictions.
The country of Nicaragua never instituted a lockdown, never required masks, and yet crushed the Corona virus? Major protests in Germany, Switzerland, and the UK as people are saying ‘no’ to more lockdowns.
—————-
Support Truth in Media by visiting our sponsors:
Pulse Cellular: Use code “TRUTH” for 10% every plan for life. https://truthinmedia.com/phone
The newly revised Employment Standards Act in Ontario now states that an employer can layoff an employee without pay for failing to prove that the employee has received a Covid-19(84) vaccine. Meanwhile vaccine passports are becoming a big brother nightmare reality as the world shifts into a digital realm where your every move will be tracked, traced and databased all in the name of keeping you safe from Covid-19(84). In this video Dan Dicks of Press For Truth gives a Covid-19(84) update about new Draconian measures in Ontario when it comes to safety in the work place and also “vaccine passports” that are coming down the pike for everyone in the near future!
If you’re old fashioned like we are and prefer to keep it old school, we also accept cash, cheques, equipment and words of encouragement! You can send us those things here:
Dan Dicks P.O. Box 1521 Squamish BC V8B 0B1
With reports that President Joe Biden’s administration is planning for imposing a vaccine passport mandate in America, expect to see in the media a deluge of vaccine passport propaganda. What will that propaganda look like? A template illustrating several elements you can expect to see in the propaganda push was provided several weeks ago in a CNN interview.
In the first week of March, host Fareed Zakaria and his guest Arthur Caplan provided at CNN a textbook example of how to present vaccine passport propaganda to the American people. Let’s look at some of the major elements of the propaganda template as demonstrated by Zakaria and Caplan.
1) Include some short expression that the idea of vaccine passports can be troubling, but make sure to only bring this up superficially. This is accomplished in the CNN segment by starting with a clip from a short scene from the movie Casablanca. In the clip, a policeman asks to see a man’s “papers,” the man says he does not have them, and the policeman responds, “in that case we’ll have to ask you to come along.” Not shown is the remainder of the scene in which the accosted man, after presenting apparently expired papers, attempts to flee only to be gunned down. Not showing the full scene demonstrates the care demanded in the propaganda to not allow any depiction of potential dire consequences from imposing vaccine passports.
2) Frame the imposing of a vaccine passport mandate as something that is both inevitable and threatens only minimal, if any, harm. Zakaria accomplishes this task with the first sentence he utters to begin the media segment. Zakaria states: “From Casablanca to today, a demand to produce personal documents can be uncomfortable, but, post-pandemic, it’s something we’ll all likely have to get more and more comfortable with.” Masterfully, Zakaria, in addition to minimizing the problems with passports as just causing discomfort, asserts that even that discomfort with time will disappear, suggesting objecting to vaccine passports is just an irrational or silly reaction.
3) Bring on a guest who, despite his description making him sound like someone who would be looking out for the interests of people concerned about vaccine passports, pretty much says that vaccine passports are the best thing since sliced bread. In the CNN interview the guest performing this role is Arthur Caplan, who Zakaria introduces as a “medical ethicist” and “professor at NYU.” A medical ethicist will surely provide some warning about dangers from vaccine passports, right? Yes, in many cases. But, Caplan is not that sort of medical ethicists. He is the one picked to be interviewed in a media segment designed to promote acceptance of vaccine passports.
4) Reiterate that vaccine passports are inevitable, and that people should support them. Zakaria hits the nail on the head with this, presenting this first question to his guest: “So explain why you think, basically, that this is the future and we should be comfortable with it.”
5) Declare that vaccine passports must be imposed on the American people because of coronavirus. Caplan accomplishes this task in his first words in the media segment. He states: “Well, I’m sure that the future holds vaccine passports for us, partly to protect against the spread of Covid.” Of course, as coronavirus has turned out not to be a major danger to most people, imposing a vaccine passport mandate to counter it makes no more sense than doing it to counter any other of many diseases. But, this is not a topic to be brought up when selling people on vaccine passports. Fearmongering, no matter how ridiculously unjustified, is the name of the game. This is the fraudulent message people are encouraged to act on without much critical thought: Coronavirus is gonna kill us all unless we take the shots and show our papers!
6) Say that mandating vaccine passports is really no big deal because of some other supposedly very similar restriction to which some people are already subjected. Caplan states: “And, you know, it’s not a new idea, we have it for yellow fever; there are about more than a dozen countries that say you can’t come in if you haven’t been vaccinated against yellow fever, and many others require you to show proof of vaccination if you transit through those countries.” Are the yellow fever-related requirements justified? Caplan does not say more than that, because these somewhat similar restrictions exist someplace, the mandating of vaccine passports in America is fine. That’s medical ethicist reasoning? Anyway, the yellow fever stuff, because most Americans have no experience with or knowledge of it, is a fine example for the propaganda. Few watchers of the segment will have any basis for questioning the current practice that is used to justify the new desired mandate. One big difference, though, jumps out on further consideration. Caplan explains that the yellow fever requirements apply for just coming to several countries. In contrast, Zakaria early in the interview says the vaccine passports that will, he claims, inevitably be imposed on Americans will be required for people “to get on an airplane, to go to a concert, or to go back to work.” The vaccine passport mandate is, thus, much more troublesome for most Americans than yellow-fever-related requirements for entry into a few countries that most Americans never visit. But, the point is to quickly present the example as if it provides conclusive support no matter how far that representation is from the truth.
7) Dismiss as insignificant people’s concerns about being required, in order to go about their daily activities, to present a vaccine passport and to take a vaccine, or, really, an experimental coronavirus vaccine that is not even a vaccine under the normal meaning of the term. Assert instead that the only danger to freedom could be something theoretical that could be additionally required in the future. Here is how Zakaria puts it in a question to Caplan: “What about the concerns that many people have about privacy, about the privacy of their health data, that, you know, is there a slippery slope here — ‘OK, I’m comfortable telling you whether or not I have Covid, but does that mean it becomes OK to ask about other things?’” Of course, many people are justifiably wary of being pressured to take the shots and then having their mandated vaccine passport used to track them as they go about their daily activities. That is why this media segment and others like it are being presented, after all.
8) Dismiss any concern that vaccine passports can in fact harm freedom. Instead, describe people as benefiting from and gaining freedom by their being mandated to take experimental coronavirus vaccines and present vaccination passports in order to go about their daily activities. Oh yeah, and keep quiet about all the mass surveillance facilitated by a vaccine passport program, the vaccinations-based caste system resulting from the mandate that will make people who do not take the shots suffer, and how the vaccine passport program can be expanded to advance many additional types of control over people. Here is how Caplan puts it: “With a Covid certification, you’re going to gain freedom, you’re going to gain mobility, and I’m going to suggest that you’re probably going to be able to get certain jobs.” Talk about turning things on their head. The mandate really means that people who do not comply will be barred from the mobility they already have and fired from their jobs. Freedom is supported by rejecting the mandate, not by supporting it.
9) Insist that the vaccine passport mandate is fine because it will be applied equally to all people. This is something Zakaria and Caplan spend a long time talking about in the CNN segment. Come on guys, something bad does not become good because it is applied to the maximum number of people, irrespective of their race, sex, or whatever. We are dealing with a mandate here, not giving everyone a serving of his favorite dessert.
10) Declare that a vaccine passport mandate helps encourage people to take the shots. (Unlike the other nine elements of the vaccine passport mandate propaganda template, this one is likely true. Threats can yield compliance. Still, the threats could deter some people from taking the experimental coronavirus vaccine shots. It sure makes you wonder about shots’ supposed safety when an extreme, and unprecedented, act of force is employed to ensure people take the shots.) States Caplan in the interview: “It also gives you an incentive to overcome vaccine hesitancy. Some people are not sure still whether they want to do the vaccine, but if you promise them more mobility, more ability to get a job, more ability to get travel, that’s a very powerful incentive to actually achieve fuller vaccination.” What Caplan is really talking about is coercion. He is saying that people who would otherwise refuse taking the shots will be forced to do so by the vaccine passport mandate severely restricting their activities and even depriving them of the ability to earn an income so long as they do not give in to the demand they take the shots. All this authoritarianism is dressed up in deceptive language. “Vaccine hesitancy” is substituted for “vaccine refusal” to disguise that the vaccine passport mandate is about stopping people from exercising free choice. “Incentive” is substituted for “coercive technique.”
Watch Zakaria and Caplan’s interview here:
Hopefully, many people will see through the deception and be able to prevent the implementation of the vaccine passport mandate Zakaria, Caplan, and others are promoting in the media.
(01:18) [Animation]: “How do mRNA COVID 19 Vaccines work?” by Medical Sciences Animations
(02:59) ANTIBODY-DEPENDENT ENHANCEMENT (ADE)/pathogenic priming in single-stranded RNA virus vaccines – after vaccination, recipients infected worse when challenged with wild virus than non-vaccinated
(09:08) ADE in ferrets Journal of Virology – Immunization with Modified Vaccinia Virus Ankara-Based Recombinant Vaccine agains SARS is Associated with Enhanced Hepatitis in Ferrets https://jvi.asm.org/content/78/22/12672
Dr. Richard Urso has treated 300,000+ patients, performed 30,000+ surgeries and successfully treated 250+ patients with Covid-19. Join us for part 4, as he discusses also discusses conflicts of interest within the FDA, CDC and NIH in our exclusive Jan. 22, 2021 interview:
DISCLAIMER Bright Light News does not provide medical advice and is intended for informational purposes only. It is not a substitute for professional medical advice, diagnosis or treatment. Never ignore professional medical advice in seeking treatment because of something you have read or seen from Bright Light News. If you think you may have a medical emergency, immediately call your doctor or dial 911.
Dr. Paul Marik Discusses Ivermectin and Vitamin D. Wikipedia tells us Dr Marik is “a professor of medicine and serves as Chief, Division of Pulmonary and Critical Care Medicine at Eastern Virginia Medical School. He is known for the vitamin C sepsis cocktail, which is under active multicenter clinical trial.”
Marik was lead author of a journal article on the efficacy of ivermectin as a COVID-19 treatment, which had been provisionally accepted for publication by a Frontiers Media journal in early 2021, but which was subsequently rejected on account of what the publisher said were “a series of strong, unsupported claims based on studies with insufficient statistical significance” meaning that the article did “not offer an objective [or] balanced scientific contribution to the evaluation of ivermectin as a potential treatment for COVID-19”.
Geert Vanden Bossche has made a splash by coming out against the current COVID-19 vaccinations — but is he genuine, or revealing the next leg of the agenda? Either way, his explicit warning about the enhanced risk of zoonotic spread is worth discussing.
11. Signs and symptoms to determine if a patient presenting in primary care or hospital outpatient settings has COVID‐19: https://www.cochranelibrary.com/cdsr/…
The volcanic mineral medicine will not patent — for the toxic burden medicine will not name
Lies are Unbekoming – October 30, 2026
Zeolite is old. It is in Roman concrete that has held for two thousand years. It’s in the water filters of ancient cisterns. It’s in the stomachs of Pacific livestock whose keepers knew, somehow, that this grey crumbling rock made the animals healthier. It’s in Soviet clinical protocols from the 1960s. It’s in the standard emergency response to the Chernobyl explosion.
In 1986, after the Chernobyl reactor failure, the Soviet Union manufactured and distributed natural zeolite at industrial scale — for soil remediation, for livestock feed, for human consumption, for the cleanup itself. Karl Hecht, who had been director of the Institute for Experimental and Clinical Pathophysiology at the Charité of Humboldt University Berlin, spent the six decades after that building the clinical research base — on silicon’s role in human health, on zeolite’s clinical safety, on its applications in ageing. In 2018, Pavelić and colleagues published a comprehensive clinical safety review of natural clinoptilolite in Frontiers in Pharmacology. In 2019, Mastinu analysed its binding affinities. In the Western medical literature, these works sit largely uncited.
What has not been treated at book length, until now, is how a volcanic mineral with six decades of Soviet clinical work behind it, two major peer-reviewed Western reviews, and ongoing clinical use across the former Eastern Bloc, remains almost entirely absent from Western medical practice — and what the toxic burden it’s meant to address actually is.
The Zeolite Book gathers the Soviet clinical record, the Western peer-reviewed studies, three contemporary practitioner voices, and three serious counterviews into one honest treatment. That’s why the book runs to seven appendices. 288 pages, four parts, three practitioner voices, three counterviews, seven appendices. The honest treatment is the argument.
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.


 Zeolite is old. It is in Roman concrete that has held for two thousand years. It’s in the water filters of ancient cisterns. It’s in the stomachs of Pacific livestock whose keepers knew, somehow, that this grey crumbling rock made the animals healthier. It’s in Soviet clinical protocols from the 1960s. It’s in the standard emergency response to the Chernobyl explosion.


