Dr. Peter McCullough is under fire from the American Board of Internal Medicine (A.B.I.M.), who is threatening his medical license for “providing false and inaccurate information to patients”. Senator Ron Johnson has responded with a call for A.B.I.M. and Dr. McCullough to participate in an open hearing on Capitol Hill, and put it all on the table of public record.
Justin and Hailey Bieber, have both suffered recent health unusual health scares for young, healthy people. Were these conditions caused by the Covid shot? Del takes a look at the evidence.
Sharp chest pains. Myocarditis and pericarditis. Heart attacks. Strokes and subsequent blindness.
These are just some of the many COVID-19 vaccine-related adverse events reported by commercial airline pilots and by a growing number of advocacy groups representing aviation industry workers.
According to these individuals and groups, the number of pilots speaking out about their vaccine injuries is dwarfed by the number of pilots who are still flying despite experiencing concerning symptoms — but not speaking out because of what they describe as a culture of intimidation within the aviation industry.
These individuals fear they will lose their jobs and livelihoods in retaliation if they reveal their symptoms or go public with their stories, sources told The Defender.
Still, a growing number of pilots are coming forward.
Last month, The Defender published the accounts of several pilots — and of the widow of a pilot who died from a vaccine-related adverse event.
Since then, more pilots have shared their stories, including one who is currently flying for a commercial airline.
A growing number of advocacy organizations, representing workers across the aviation industry and in several countries, are joining these pilots in speaking out.
Meanwhile, pilots in Canada and the Netherlands recently reported significant legal victories in separate vaccine-related cases.
More pilots come forward, speak to The Defender
Steven Hornsby, a 52-year-old pilot with a legacy passenger airline company, was once an active weightlifter and cyclist, biking 10-26 miles every other day.
He is also a veteran of the U.S. Marine Corps and Operation Enduring Freedom. Per FAA requirements, he passed 24 medical exams in the past 12 years, including 12 electrocardiograms (ECGs).
Hornsby told The Defender, “I’ve never had any cardiovascular issues in my life, nor have I ever had any major health issues … I eat healthy and live what I believe to be a balanced lifestyle.”
Hornsby, however, is not flying today because, he said, he was “coerced … to get the COVID-19 vaccine,” and his employer “made it very clear that all employees would be required to get it and that medical/religious exemptions would be very difficult to get.”
Hornsby’s difficulties began after receiving the second dose of the Pfizer COVID-19 vaccine.
“After my second shot, I initially had zero issues, with little more than light fatigue on day two, Hornsby said. “The 12th day, however, was the culmination of the vaccine and the continuous stress I was adding to my heart from rigorous exercise.”
As he was driving with family, Hornsby said he felt sharp chest pains, “pain radiating through my left arm, and my heart rate spiked as if beating in my neck.”
Hornsby said it took several different diagnoses from doctors and medical practitioners to make a connection between his health issues and the vaccine.
A nurse at an urgent care facility first told him his symptoms did not correlate to a heart attack and were most likely unrelated to the vaccine. Later, at a hospital emergency room, he was again told his symptoms were not likely to be related to the vaccine.
“At that point,” Hornsby said, “I was indignant. Why would a healthcare provider dismiss that perspective? This was my eye-opening reality that a major cover-up was in play.”
Hornsby was ultimately diagnosed with elevated blood pressure but was told he had not suffered a heart attack. Doctors advised him to follow up with a cardiologist, and told him they would not report his case to the Vaccine Adverse Event Reporting System (VAERS).
Hornsby said his cardiologist, after performing blood work, told him his heart was healthy, and though the doctor didn’t dismiss the possibility that his heart issues were connected to the vaccine, he told him the symptoms were “most likely from stress or a musculoskeletal problem.”
“I had to stop trying to force my perceived diagnosis — bias against the vaccine — and listen to the professionals,” Hornsby said, adding “I needed to be patient,” even after a union doctor also dismissed Hornsby’s concerns that his symptoms were related to the vaccine.
Hornsby continued experiencing “intermittent pains,” despite taking home remedies such as tea and supplements to calm his heart rate, which he said were helpful.
It was only in December 2021, when his medical certification was due for renewal, that his aeromedical examiner (AME) advised him to wear a Holter monitor (a type of portable ECG) for one week to monitor his heart.
“That is when I discovered that I had arrhythmia issues, heart palpitations and [an] irregular heart rate, which was occurring almost exclusively at night,” said Hornsby. “I reported back to my AME, who then told me I was grounded and that I should go find a good cardiologist and get healthy.”
“My heart was inflamed,” said Hornsby. “After an echocardiogram, it showed my heart mildly dilated with fluid behind my heart.”
Hornsby said he’s “doing much better,” but he’s still not flying. He’s disappointed with the dismissive manner in which several doctors addressed his concerns.
“Had doctors been willing to view my case — and I suspect others — with an open mind, this could have been diagnosed much, much earlier,” he said. “Looking back, had my heart not been healthy, I would have surely died from cardiac arrest like you’re seeing in young athletes.”
Hornsby said he believes other pilots with similar symptoms are still flying.
“I suspect there are many pilots flying around with minor and perhaps major issues,” Hornsby said. “The vaccine is/was experimental and for good cause. No one knows the long-term effects.”
He added:
“How many years have been shaved from my life? Will I develop scar tissue in my heart? Will I get cancer as a result? Has this trash degraded my immune system? Only God knows.”
Pilot injured by Moderna shot: ‘I have a family to feed’
In fact, The Defender interviewed another pilot — currently flying for a commercial airline in the U.S. — who is experiencing such health difficulties.
The pilot, who spoke to The Defender on condition of anonymity, said:
“I was experiencing chest pain, usually at night, almost like somebody had their hand around my heart and was squeezing.
“Generally, [the pain] would subside during the day, but … would appear occasionally out of nowhere and I would need to lie down.
“It would manifest as pain, but also like something was lodged deep in my esophagus, like I had a piece of food or air that was pressing upon my chest area.”
According to the pilot, his symptoms “began about a week after the second Moderna vaccination.”
He said the airline he works for threatened to terminate anyone who didn’t get the vaccine. “I have a family to feed, so I was left with little choice.”
He said he is “on reserve” and not flying often. While his symptoms have recently subsided, he felt that “looking into further treatment would result in an answer that would be unfavorable to my medical [certification].”
He added:
“In the back of my mind though, the thought of what it could mean for my future health is there.
“The current situation I am faced with is that supporting a family is what is most important to me. Fear of loss of my pilot medical [certification] after being mandated to get this vaccine is the path I am currently on.”
Terminated after 19 years for refusing COVID shot, former Australian pilot advocates for others
Australia, like Canada, has a government-level vaccine mandate for airline crew and airport workers. In Australia, this mandate went into effect on Nov. 15, 2021.
Glen Waters is a former captain with Virgin Australia who is now a spokesman for a group of employees from the same airline.
Waters, who had held the rank of captain for 19 years before being terminated by Virgin Australia for refusing the vaccine, spoke to The Defender on behalf of several pilots who are suffering from vaccine injuries.
According to Waters, “none of the pilots suffering from injuries are prepared to talk” because “the company is actively trying to terminate anyone reporting vaccine injury.”
Waters said employees whose health issues are characterized as “unrelated” to the vaccine are being treated by Virgin Australia “as you would expect a company to care for its employees.”
Waters stated “there are several reasons injured pilots will not come forward,” including:
“There is a stigma attached to anti-vaccine sentiment in any form.
There is a reluctance on the part of the medical community to get involved with possible vaccine injuries.
Vaccine makers will actively fight against injury claims.
Insurance companies have distanced themselves from claims involving the vaccine.
Pilots don’t want to lose their medical certifications, jobs or careers.
Waters said of approximately 900 pilots flying with Virgin Australia, he is aware of nine who are no longer flying because of medical complications that could be linked to the vaccine.
“No doubt there are many more who are continuing to fly with troubling symptoms,” he said.
These symptoms, according to Waters, most commonly include myocarditis and pericarditis. Some symptoms, however, are even more serious.
Waters told The Defender :
“We have one captain [who had] a stroke and went blind, and another had a heart attack and fell down the boarding stairs after landing.
“There have been complaints of constant headaches and numerous reports of chest pains and shortness of breath.
“A number of cabin crew have reported pins and needles in their limbs, almost like electric shocks that persist for hours at a time.
“I have heard [about cases of] tinnitus, vertigo and brain fog, including temporary blindness, in several crew. Disrupted menstrual cycles are reported frequently, perhaps affecting dozens [of employees].”
However, according to Waters, perhaps due to the work environment, not all pilots are comfortable in stating openly that there may be a connection between their health difficulties and the vaccines.
“I’m only aware of three who say the symptoms started within an hour of the vaccine, one within seven days,” he said.
“The stroke and heart attack victims are not attributing their medical event to the vaccine as far as I am aware. Neither [did] the captain who died of a sudden onset of cancer early this year.”
Some employees may not understand their symptoms might be related to the vaccine, Waters said. “Many of the early warning signs — persistent headaches, chest pains, breathlessness — are not recognized by aircrew as possible adverse reactions,” Waters said.
“The heart attacks and strokes are occurring in otherwise fit and healthy individuals. They are sudden and are a real risk to flight safety.”
Waters explained that Australia’s Civil Aviation Safety Authority, similar to other such bodies globally, has “a 1% rule” for pilots: If they have a medical condition “that presents a greater than 1% chance of resulting in an incapacitation event within the next 12 months, then they are considered medically unfit to fly.”
In light of this, according to Waters, “numerous aviation doctors, including Lt. Col.Theresa Long and Lt. Col. Peter Chambers, have recommended tests that will help determine the real risk to pilots.”
These include the D-dimer test for blood-clotting conditions, a complete blood count, post-vaccination ECG analysis, a cardiac MRI and others.
As pilots speak out, there are some legal victories
Despite what numerous pilots call a hostile environment in the aviation industry toward claims of vaccine injury, a recent series of legal decisions were in pilots’ favor and more legal actions are in progress.
A judge at the Amsterdam Court of Appeals in the Netherlands on June 2 ruled in favor of the Dutch Airline Pilots Association, in a case that challenged vaccine mandates introduced by Dutch airline KLM for new pilots.
“It is considered that requesting and demanding a vaccination against corona constitutes an unjustified infringement of the fundamental rights of the candidate pilots.
“After all, the decision whether or not to have yourself vaccinated is something that belongs pre-eminently to this private sphere.
“Requiring the candidate pilot to be vaccinated and to give a positive answer to that question about vaccination status, therefore, violates this. KLM thus leaves no choice to candidate pilots who want to join KLM.”
Per the June 2 ruling, KLM is prohibited from requesting or collecting such information from candidate pilots, or rejecting candidates on the basis of their vaccination status, under penalty of €100,000 (approximately $105,000) per violation.
Following the ruling, the Dutch Pilots Association issued a statement, remarking:
“The [association] endorses the government’s position that vaccination is important, but that compulsory vaccination by the employer is not permitted.
“We were of the opinion that KLM did not comply with this and, moreover, violated our agreements about this, without there being any operational necessity.”
In Canada, the federal government on June 14 announced most travel-related vaccine mandates would be lifted as of June 20.
Responding to this announcement, in a statement sent to The Defender, Free to Fly credited those who opposed the mandates, stating:
“This dark season helps reinforce an important maxim; true change only comes about through tenacity, courage, and the relentless pursuit of truth by principled men and women.
“Across our nation, many Canadians refused to give up on freedom and fought for our fragile democracy. We feel no ‘gratitude’ towards an emboldened state for ceasing to violate God-given freedoms.
“We must never forget our recent travails, and cannot be lulled into complacency, certainly with Trudeau’s government openly threatening reinstatement of mandates with any ‘new variant’.
“We will continue to pursue them, insisting on uncompromising standards in our industry and the assurance we never again go down this road of medical segregation.”
In another recent development, Canadian pilot Ross Wightman became just one of a small number of people who have received compensation from Canada’s Vaccine Injury Support Program.
Wightman was diagnosed with Guillain-Barré Syndrome, a rare condition that affects the nervous system and may cause muscle weakness, paralysis or even death.
He developed the condition within days of receiving his first and only dose of the COVID-19 vaccine. For the past year, Wightman has been unable to work, as he has substantially limited mobility in his arms and legs.
Global Aviation Advocacy Coalition pens open letter to aviation industry
In an open letter to the aviation industry, the GAA raised serious allegations regarding industry vaccine mandates, which the GAA said resulted in a growing number of vaccine-injured pilots who are unable to fly and who may never do so again — and an increasing number of pilots who continue to fly while experiencing potentially serious symptoms.
The GAA said it is in communication with pilots at the following U.S.-based airlines: Alaska, American, Delta, Frontier, JetBlue, Southwest, Spirit and United, and 12 major air carriers in Australia, Canada, France, Germany and the Netherlands.
According to the GAA’s open letter, the organization and the scientists and doctors it works with “are hearing daily from vaccine-injured airline pilots” about conditions including “cardiovascular issues, blood clots [and] neurological and auditory issues.”
The injured pilots are experiencing a broad spectrum of symptoms, “ranging up to death,” the GAA wrote, adding the symptoms “at least correlate to receiving COVID-19 vaccinations.”
The GAA wrote that in many instances, these conditions are serious enough that “pilots have lost medical certification and may not recover the same,” while others “are continuing to pilot aircraft while carrying symptoms that should be declared and investigated, creating a human factors hazard of unprecedented breadth,” and “a landscape which should greatly concern airlines and the traveling public.”
Pilots continue to fly despite experiencing such symptoms, said the GAA, because those “who report their injury face possible loss of licensing, income, and career while receiving little to no support from their unions, and a prosecutorial invective from employing airlines.”
The GAA said many pilots were reluctant to receive the COVID-19 vaccine and opposed mandates:
“Pilots are trained to be careful analysts of their environment, recognizing risks and actively mitigating. For many, their training and differential risk analysis led to concerns and negative conclusions regarding the compatibility of COVID-19 vaccination with health and flight safety.
“Not only did many pilots disagree with arbitrary requirements embodied in vaccination mandates, but they also saw risks in the unanswered questions and unjustified speed and pressure behind the vaccine rollouts. They lobbied their airlines and politicians, recommending caution and opposing mandates.”
However, stated the GAA, for many pilots, it was a choice between vaccination and job loss:
“Once airlines mandated vaccination, many pilots steadfastly refused based on risk and were subsequently put on unpaid leave or outright terminated.
“Principled professionals were forced out of aviation and the industry lost hundreds of thousands of hours of experience. Now, the global airline industry is heading into a dire staffing crisis.
“Thousands of other pilots were coerced into vaccination to provide for their families. This has taken a toll on their mental health.”
For the GAA, blame lies with the mandates — and more broadly, with the airlines, regulators and unions:
“ … there appears to be no evidence of aviation regulators, airlines or unions having performed any of their own due diligence into COVID-19 vaccines and the impact on pilot health or performance.
“This is at complete odds with existing aviation medical standards. Questions exist around competence and possible negligence.
“Failure to address this potential medical watershed will make the airlines and unions complicit in a culture shift that has rocked the aviation mantra of ‘safety first, always.’”
The GAA called on civil aviation authorities such as the Federal Aviation Administration, Transport Canada, UK Civil Aviation Authority, the European Union Aviation Safety Agency and Australia’s Civil Aviation Safety Authority to begin fulfilling their regulatory obligations.
“The crisis in pilot health must be publicly addressed by airlines and representing unions to restore flight safety to what we once knew,” their letter stated.
GAA called for:
“Where it exists, mandated COVID-19 vaccination for aviation workers must be discontinued.
A permissive environment for self-reporting needs to be reemphasized by regulators and airlines.
Thorough and objective aviation medical screenings of pilots and cabin crew need to be a high priority. These must be backed by the regulator and should focus on high prevalence harms which are now showing up in the general public and in our flight crews.
Airlines and regulators hold data about sickness and medical certificate suspension, including symptoms and causal reasons. This data should be analysed by independent third parties to establish or rule out COVID-19 vaccination as a possible cause.”
Free to Fly pursues legal action against Canadian authorities, airline
Canada-based Free to Fly represents close to 3,000 aviation professionals, according to its director, Greg Hill, who spoke to The Defender.
These professionals include pilots, flight attendants, air traffic controllers, maintenance workers and customer service representatives.
According to Hill, industry workers have reported a wide range of health issues, including “generalized chest pains, myocarditis, enlarged heart, blood clots, hearing loss, partial paralysis, lymph issues [and] broad autoimmune dysfunction.”
Some of the injured pilots are “high-end athletes” who experienced a “major decrease in their performance capacity.”
“We’ve had some inexplicable deaths at unreasonably young ages,” Hill said, and “an increase in in-flight diversions with one of our airlines in particular.”
While Hill left open the possibility that at least some of these incidents weren’t vaccine-related, he said that Canadian authorities show “an unwillingness to do a proper investigation.”
“Transport Canada, the airline industry, the airlines and the unions have been uniformly silent on the matter,” Hill said.
Indeed, Hill said the aviation industry, regulators and unions in Canada have not been responsive to outreach from Free to Fly.
Referring to a document, prepared in conjunction with the Canadian COVID Care Alliance, that said flight crew pilots were most at risk of vaccine-related adverse effects due to their work environment, Hill said:
“We gave this to the two largest pilot unions in the country, the Air Canada Pilots Association and ALPA, the Airline Pilots Association … they have refused to respond to it.
“We also sent it to management at two of our largest airlines … they also have refused to even respond to it. And this was raising very explicitly the risks that these medical professionals felt needed, at the very least, to be investigated.
“And as yet, we’ve had nothing but silence formally as far as a response from these groups, as far as adverse events, vaccine injuries.”
The document provides: information on a union’s obligation to its members; a differential risk analysis of COVID-19 versus the vaccines; an analysis of natural versus vaccine-induced immunity; an analysis of adverse reactions to the vaccines and particular risks faced by flight crews; a list of alternate treatment options for COVID-19; and a discussion of informed consent and coercion.
According to Hill, the policy is “no jab, no job” for pilots and aviation professionals in Canada, unless they are granted religious or medical exemptions.
But, said Hill, even in the rare instance when an exemption is granted, those employees nevertheless have found themselves out of work, due to airline practices that Hill described as extortionate.
Hill told The Defender :
“If you’re not willing to take the jab and you can’t be accommodated with a religious or medical exemption, then you are either on unpaid leave or outright terminated. Some of our pilots have already been terminated.
“The vast, vast majority of these accommodations were outright denied … some of the stories of people that were denied medical accommodations are truly shocking, the same on the religious aspect.
“The handful that were approved … are simply another round of extortion. Some of them were denied, then they were approved retroactively … essentially they were approved, but then it didn’t change anything … you continue your unpaid leave, but you’re allowed your benefits.”
Similar to claims made in an open letter hand-delivered to the U.S. Federal Aviation Administration (FAA) and major U.S. air carriers in December 2021, Free to Fly also alleged a violation of existing aviation regulations, this time in Canada.
According to Hill:
“There was, at one point, on the Transport Canada website, this was July 2021, a line that specifically said it remains a general position of Transport Canada … that participation in medical trials is not considered compatible with aviation medical certification.
“A number of us were asking questions … and saying, ‘Well, what’s up with this?’ And the answer was these [vaccines] are approved. And we said, ‘No, they’re not fully approved, they’re approved under interim order.’”
Hill said if you read that interim order, it was quite laughable. It basically said, ‘We’ll roll these vaccines out and we’ll gather data. Right now we feel that they’re okay and we’ll continue to assess as we continue to jab people,’ which just seems insane.
“So we asked these explicit questions, got no suitable answers,” Hill said. “And the week following … they simply memory-holed it, they removed that line and it’s no longer on the website. That was their response.”
Hill also described a culture of intimidation in Canada among pilots and flight crews, resulting in a reluctance to come forward with vaccine injury claims:
“Unless the individuals involved are willing to speak to it, I can’t say … every pilot that’s currently still employed … is living in fear of speaking explicitly, certainly in any public forum … for fear of the retribution that has been rolled out against those of us who no longer have work because we refuse to go down this road and insisted upon medical freedom and in doing a proper analysis of what we’re up against here.”
This has not stopped Free To Fly from pursuing legal action in Canada. According to Hill, in Canada, “… you can’t seek private representation against your company. You have to do it through your union. And when the unions decide to not engage, you’re left between a rock and a hard place.”
Hill added:
“ … if you read through the case law precedent over the past year or two in Canada, the courts have very, very much chosen a side. And the concern is within an English common law system, if we continue to litigate, litigate and lose and lose and lose, you create precedent that makes it harder and harder to dig your way out.
“Unfortunately, in this country, the law is downstream of politics. It’s heavily influenced by it, certainly in my opinion. And politics, of course, is downstream of culture. So unless you impact culture and impact the broader narrative, it’s very difficult to see legal solutions.”
Free to Fly on June 6 sent a letter to Canada’s minister of transport, co-signed by the GAA, containing “important, detailed questions regarding COVID-19 vaccines and flight safety,” according to Hill.
As of this writing, the minister has not responded.
Hill said:
“It’s just mind-boggling … we’ve literally stood the [aviation industry’s] safety culture on its head, and that’s the greatest concern to us.
“It’s not an interest in a desire for conflict. I long for the world before this became an all-consuming role, where we’re pushing to try and get ourselves back to a sense of normalcy and proper risk assessment and risk mitigation, which is what pilots are really dedicated to.
“So that’s all we want: that ability to look at this properly and analyze it properly … aviation medical screenings focusing on some of the high prevalence harms that we’ve seen, that we’re hearing about … these screenings need to be backed by the [Canadian] regulator who, in our opinion, has not done their job properly over the past couple of years.”
As far as suspensions, Hill said, pilots who are off and on have not been able to get their medical [certification] back. And these need to be analyzed by independent third parties.
Some pilots and aviation professionals, in addition to speaking out, are joining advocacy groups.
For instance, Hornsby and the pilot quoted in this story who opted to remain anonymous, have joined USFF, according to its co-founder, Josh Yoder, as are the pilots and air traffic controllers who previously shared their stories with The Defender.
USFF has recently begun filing a series of lawsuits against airlines and federal agencies in response to the vaccine mandates and their aftermath.
Ultimately, though, the public — not just pilots and aviation professionals — must also speak out, according to Hill.
“Whether it’s Canada, the United States, Australia, the United Kingdom, etc., we’d like to see the public as a whole rising up and speaking out publicly about these issues, asking why the regulators haven’t done proper risk assessments in regards to where we’re at with these jabs.”
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
Sen. Rand Paul (R-Ky.) blasted NIAID Director Anthony Fauci for promoting booster jabs for children despite refusing to provide data proving their effectiveness, or their necessity.
The tense exchange happened during a Senate Health Committee hearing Thursday, where CDC Director Rochelle Walensky, Fauci and others hoped to procure more funding for the federal pandemic response.
“Dr. Fauci, the government recommends everybody take a booster over age five,” Sen. Paul told Fauci, who was interviewed via Zoom. “Are you aware of any studies that show reduction in hospitalization, or death for children who take a booster?”
“Right now, there’s not enough data that has been accumulated, Senator Paul, to indicate that that’s the case,” Fauci responded.
“So there are no studies – and Americans should all know this – there are no studies on children showing a reduction in hospitalization or death with taking a booster,” Sen. Paul summarized.
Paul went on to hypothetically ask if booster jabs produce antibodies, wouldn’t a never-ending litany of jabs make sense?
“If I give you 10, or if I give a patient 10 mRNA vaccines, and they make protein each time, or they make antibody each time, is that proof that we should give 10 boosters?” Paul asked.
“No. I think that is somewhat of an absurd exaggeration,” Fauci responded.
Sen. Paul shot back that the only data the Committee’s seen shows possible antibody effectiveness and only in older populations with risk factors, but “for younger folks there’s not.”
“But here’s the other thing,” Paul continued, “There are some risk factors for the vaccine… So the risk of myocarditis with a second dose for adolescent boys 12 to 24 is about 80 in a million. This is both from the CDC and from the Israeli study.”
“So, there is risk, and there are risks, and you’re telling everybody in America just blindly go out there, because we made antibodies… So, it is not an absurd corollary to say, ‘If you have 10.’ In fact, you probably make antibodies if you get a hundred boosters. All right? That’s not science, that’s conjecture and we should not be making public policy on it.”
Elsewhere during Thursday’s questioning, Paul asked Fauci if he personally “ever received a royalty payment from a company that you later oversaw money going to that company?”
“I don’t know as a fact, but I doubt it,” Fauci replied.
Paul went on to point out the “NIH continues to refuse to voluntarily divulge the names of scientists who receive royalties, and from which companies, over the period of time from 2010 to 2016.”
“Can you tell me if anyone on the vaccine approval committee’s ever received money from the people who make vaccines?” Paul asked.
“People who receive royalties are not required to divulge them even on their financial statement according to the Bayh–Dole Act,” Fauci shot back, clearly incensed.
“It’s all redacted and you can’t get any information on the 1,800 scientists who received royalties,” Paul concluded, as he was cut off by the Committee chair.
The exchange comes just one day after it was reported Fauci contracted coronavirus, despite being vaccinated and double-boosted.
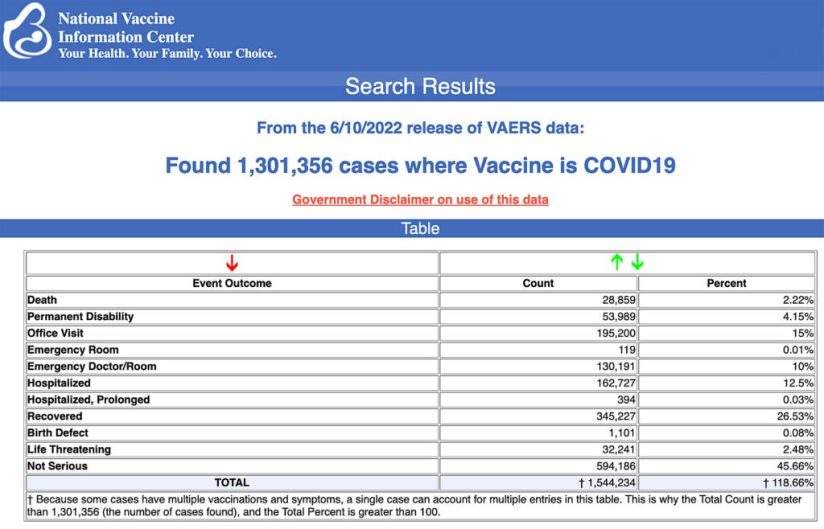
The Centers for Disease Control and Prevention (CDC) today released new data showing a total of 1,301,356 reports of adverse events following COVID-19 vaccines were submitted between Dec. 14, 2020, and June 10, 2022, to the Vaccine Adverse Event Reporting System (VAERS). That’s an increase of 6,027 adverse events over the previous week.
VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
The data included a total of 28,859 reports of deaths — an increase of 327 over the previous week — and 238,412 serious injuries, including deaths, during the same time period — up 1,645 compared with the previous week.
Of the 28,859 reported deaths, 18,719 cases are attributed to Pfizer’s COVID-19 vaccine, 7,581 cases to Moderna and 2,493 cases to Johnson & Johnson (J&J).
Foreign reports are reports foreign subsidiaries send to U.S. vaccine manufacturers. Under U.S. Food and Drug Administration (FDA) regulations, if a manufacturer is notified of a foreign case report that describes an event that is both serious and does not appear on the product’s labeling, the manufacturer is required to submit the report to VAERS.
Of the 13,293 U.S. deaths reported as of June 10, 16% occurred within 24 hours of vaccination, 20% occurred within 48 hours of vaccination and 59% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 590 million COVID-19 vaccine doses had been administered as of June 10, including 349 million doses of Pfizer, 223 million doses of Moderna and 19 million doses of Johnson & Johnson (J&J).
Every Friday, VAERS publishes vaccine injury reports received as of a specified date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed.
4 reports of myocarditis and pericarditis (heart inflammation).
The CDC uses a narrowed case definition of “myocarditis,” which excludes cases of cardiac arrest, ischemic strokes and deaths due to heart problems that occur before one has the chance to go to the emergency department.
22 reports of myocarditis and pericarditis.
The Defender has noticed over previous weeks that reports of myocarditis and pericarditis have been removed by the CDC from the VAERS system in this age group. No explanation was provided.
62 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 97% of cases attributed to Pfizer’s vaccine.
656 reports of myocarditis and pericarditis with 644 cases attributed to Pfizer’s vaccine.
166 reports of blood clotting disorders with all cases attributed to Pfizer. VAERS reported 167 cases of blood clotting disorders in the 12- to 17-year-old age group last week.
19 cases of postural orthostatic tachycardia syndrome (POTS) with all cases attributed to Pfizer’s vaccine.
U.S. VAERS data from Dec. 14, 2020, to June 10, 2022, for all age groups combined, show:
20% of deaths were related to cardiac disorders.
53% of those who died were male, 42% were female and the remaining death reports did not include the gender of the deceased.
FDA authorizes Pfizer and Moderna COVID vaccines for younger children
Moderna and Pfizer-BioNTech’s COVID-19 vaccines are now authorized for emergency use in infants and young children as young as 6 months, CNN reported.
The FDA on Friday authorized Moderna’s vaccine for use in children 6 months through 17 years and the Pfizer-BioNTech vaccine for children 6 months through 4 years.
The FDA’s Vaccines and Related Biological Products Advisory Committee (VRBPAC) on Wednesday unanimously voted 21-0 to recommend Pfizer and Moderna’s COVID-19 vaccines for infants and young children, stating the totality of the evidence available shows the benefits of the vaccines outweigh the risks of use.
The panel ignored pleas from experts, the vaccine-injured and a congressman representing 17 other lawmakers to halt authorization until questions about the safety and efficacy of COVID-19 vaccines for the nation’s youngest children could be properly addressed.
Pfizer’s three-dose vaccine would cover children 6 months to 5 years old, while Moderna’s two-dose vaccine covers children 6 months to 6 years old.
White House officials said the administration of vaccines for these age groups could start as early as June 21.
CDC advisors hold impromptu meeting to get vaccines for kids rolled out by White House deadline
During a meeting Thursday, the CDC announced it scheduled a special two-day meeting of the Advisory Committee on Immunization Practices (ACIP) Friday to discuss authorization of Pfizer and Moderna’s COVID-19 vaccines for infants and young children.
The meeting to discuss authorization of Moderna’s COVID-19 vaccine for 6- to 17-year-olds is scheduled for June 22 and 23.
The CDC today discussed the safety, immunogenicity and efficacy of the Moderna shot in kids 6 months through 5 years of age and Pfizer’s vaccine in children 6 months through 4 years of age.
“The entire process is set up to rubber-stamp the VRBPAC meetings from yesterday,” said Toby Rogers, Ph.D.
In a CHD.TV live blog, Dr. Liz Mumper, a pediatrician and Children’s Health Defense board member, said Pfizer showed an estimate of 80.3% vaccine efficacy but based it on only 7 cases in the placebo group and 3 in the vaccine group.
“These numbers are ridiculously small — the 80% may not stand” if more kids are included in the numbers, Mumper said.
Mumper also pointed out the shots being considered at today’s meeting were based on the original Wuhan strain that is no longer circulating.
“It is not so important how good a vaccine is at generating antibodies to Wuhan strain,” Mumper said. “[We] need long-term data about the impact of the shot on the number of kids who get COVID in [the] community and have severe or mild [cases].
Mumper said:
“U.S. VAERS data from Dec. 14, 2020, to June 3, 2022, for 6-month-olds to 5-year-olds show 1,658 adverse events, including 63 cases rated as serious and 3 reported deaths.
“The risk of a child dying if they have a diagnosis is 1,086/10,700,00 or 1086/10700000 = 0.00010149532. The risk of any child dying of COVID-19 over this time period is 1,086/73000000 = 0.00001487671.”
“Forty-nine states have already bought vaccines for children in the age groups being debated,” she added. “Seems like a done deal.”
FDA’s vaccine advisors endorse Moderna’s COVID vaccine for kids ages 6 to 17
The FDA’s vaccine advisory panel on Tuesday voted unanimously to recommend Moderna’s COVID-19 vaccine for children ages 6 to 17 after determining the benefits of the vaccine outweigh the risks for use.
VRBPAC voted 22 to 0 to recommend Moderna’s two-dose vaccine for 6- to 11-year-olds at half the strength of the adult version, and 22 to 0 in favor of authorizing the shot for 12- to 17-year-olds at the same strength as adults.
During the public comment session, individuals expressed concern over recommending a vaccine for an age group that has an almost zero risk of experiencing severe illness or death from COVID-19 and has already acquired a high level of natural immunity.
Dr. Tom Shimabukuro, a vaccine safety official at the CDC, said some data suggest a higher risk of myocarditis among people 18 to 39 years old after receiving Moderna’s COVID-19 vaccine, but findings were not consistent across various safety databases and were not statistically significant.
The CDC confirmed 635 cases of myocarditis, or heart inflammation, in the 5-to-17 age group out of almost 55 million doses of the Pfizer-BioNTech vaccine administered. The agency said the condition occurred most often in adolescent boys after receiving their second dose.
Florida only state not to preorder vaccines for young children
Florida is the only state in the nation that did not place an order with the federal government for doses of COVID-19 for young children prior to U.S. health agencies authorizing the vaccines, Politico reported.
The deadline for placing a pre-order was Tuesday and 49 other states met the cutoff date.
The Florida Department of Health (DOH), said in a statement to Politico on Wednesday that it did not pre-order vaccines for kids 5 and under because it doesn’t advise all children get vaccinated.
“States do not need to be involved in the convoluted vaccine distribution process, especially when the federal government has a track record of developing inconsistent and unsustainable COVID-19 policies,” the DOH statement said.
Jeremy Redfern, press secretary for Florida’s DOH, confirmed the department “chose not to participate” in the vaccination program.
“It is also no surprise we chose not to participate in distribution of the COVID-19 vaccine when the department does not recommend it for all children,” Redfern said. “Doctors can order vaccines if they are in need, and there are currently no orders in the department’s ordering system for the COVID-19 vaccine for this age group.”
A few weeks back, at the World Economic Forum (WEF) meeting in Davos, Bill Gates said some surprising things. In the course of a 56-minute panel discussion the vaccine pusher extraordinaire admitted (starting at the 18:22 mark) that the Covid vaccines do not block infection and that the duration of whatever protection they bring to the table is extremely short.
He later talked (starting at 51:00 mark) of the absurdity of implementing any Covid passport program—and one can logically deduce any other measure to segregate the vaccinated from the unvaccinated—when the injections have shown no ability to do the least that one should expect from a vaccine: prevent infection and transmission.
These admissions violently kick the stool out from under the arguments made in favor of the more assaultive and damaging Covid “containment measures” taken in the past two years, many of which are still being pursued with pitiless vigor by public officials, CEOs, and educational “leaders” all around the world.
Are we to believe that Bill Gates had a sudden impulse to undermine all that he used his billions to mercilessly promote over the last two years? And that he was giving all those currently carrying out those plans permission to stand down?
It’s a nice thought. But I don’t believe it to be the case.
No. Bill was simply engaging in one of the more tried and true techniques of elite information management, the limited hangout, or what I prefer to call a drive to “save the frame” of an argument that is quickly taking on water.
Since Bill and many of the people he has paired up with to force the experimental and often harmful vaccines upon the world, effectively own or have donated untold amounts of money to many of the world’s more important media outlets, he knew beforehand that he did not have to worry much about his words being widely circulated.
And so it was. Only relatively small independent news gatherers took any note of what he said.
So who was he addressing his words to and why?
He was speaking to the fellow true believers and providing them with a rhetorical model for handling the loss of faith some among their ranks are having in the face of the vaccines’ abject failure.
The key to understanding the frame game here is the clause Gates uttered right before the “but” with which he introduced his truthful words about the “vaccines” pitiful infection-blocking capabilities and short duration of effectiveness: “The vaccines have saved millions of lives.”
Those familiar with the work of cognitive linguist George Lakoff, or the activities of pollster and so-called political wordsmith Frank Luntz will know what I’m talking about.
What these two men have in common—despite their divergent political allegiances—is their belief in the extraordinary power of rhetorical framing; that is, the tendency of the human brain to subordinate the careful analysis of empirically proven details to the embrace of an overarching cognitive metaphor that appeals to their deeper, if often unstated, cultural and emotional values.
It’s the difference between, for example: “The US invaded Iraq on false pretenses and destroyed it, killing hundreds of thousands of innocent people.” and “In its efforts to bring democracy to Iraq, the US made a number of tragic mistakes.”
The first states a bald empirical truth. The second obfuscates that crude reality and subordinates it to the noble vision, so cherished by Americans when contemplating their role in the world, of a country that is constantly helping people around the world to better their lives.
And with widespread imposition of mental frames like this through the media, “poof!” go all the gory, on-the-ground details, and with them more importantly, the need to actually interrogate what we did and how we might seek to repair the lives we broke.
Going back to Davos, Bill was effectively saying to his minions, “You are on a great moral crusade. We’ve had some small problems along the way, but don’t give up, because the world needs us to continue to be heroic and save more lives.”
And with that cognitive frame in place, any creeping doubts those in the audience might have about what they have done, and their future mission, disappear just like that.
We see the same gambit used when the US government inevitably links the apparent waning of the pandemic to the use of vaccines. Here, for example, is what the CDC said to CNN shortly after lifting requirement that US citizens be tested before returning home from foreign travels:
“The Covid-19 pandemic has now shifted to a new phase, due to the widespread uptake of highly effective Covid-19 vaccines, the availability of effective therapeutics, and the accrual of high rates of vaccine-and infection-induced immunity at the population level in the United States. Each of these measures has contributed to lower risk of severe disease and death across the United States.”
It’s no accident that the first factor adduced to explain the onset of happier days, the one that sets the frame for all that follows, is the “widespread uptake of highly effective Covid-19 vaccines.”
The goal here— as it was in the case of Gates at Davos—is to preserve, in the face of abundant empirical evidence to the contrary, the frame that presents the forced administration of vaccines as the great slayer of the pandemic and gifter of our vanquished freedoms, and to turn that suggestion into an established fact through constant repetition.
But, of course, neither Gates’s claim about the vaccines saving “millions of lives” nor the CDCs’ assertion that “widespread vaccine uptake” was the key reason for ending the pandemic are established facts. Far from it. Indeed, there are no scientific studies that I know of capable of authenticating either claim. But that’s just the point.
The elites that deign to rob us of our bodily sovereignty and so much more in the name of Covid, or whatever other “mortal health threat” that they choose to publicize next through their carpet-bomber control of most media, have all done their homework on the frame game and carefully tailor their communications to fit with its imperatives.
Unfortunately, most citizens are still not clued in to how it operates in their lives. Verbal details such as the ones cited above matter because they play an enormous role in establishing and maintaining what the now sadly tarnished Chomsky once brilliantly called the field of “thinkable thought” in our public discussions.
To open up that field we need to smash their frames. But to smash those frames we first need to admit they exist, and where we can go to find them.
Thomas Harrington, Senior Scholar at the Brownstone Institute, is an essayist and Professor Emeritus of Hispanic Studies at Trinity College in Hartford (USA) where he taught for 24 years. He specializes in Iberian movements of national identity Contemporary Catalan culture. His writings are at Thomassharrington.com.
Or maybe there weren’t any deaths at all, and the fact-checkers have debunked all of that.
It doesn’t matter. Forget it. There’s no point even considering what may or may not have caused the blood clots that may or may not have happened in the past.
The point is, in the future, they will be caused by the hot weather.
It is in the best interest of all parties to have transparency in these issues in order to restore public trust in the medical community and reduce vaccine hesitancy which are key goals of the CDC and FDA.
“We do have a problem with vaccine uptake that is very serious in the United States and anything we can do to get people more comfortable to be able to accept these potentially life-saving medical products is something that we feel we are compelled to do,” said Dr. Peter Marks, director of the Center for Biologics Evaluation and Research.
There are two things Dr. Marks can do to achieve his goal:
He can have an open discussion with the people who he alleges are the main spreaders of “misinformation.”
He can open an official FDA investigation into allegations of fraud in the Pfizer trial and produce a written report responding to each allegation.
Dr. Marks, like every other public health official, will not do #1. I understand why he won’t: the data isn’t supportive of the government narrative so he’d lose the debate very badly. This is why nobody at the FDA, CDC, or NIH will talk to any of my colleagues. In ignoring us, he is acting in a way inconsistent with what is expected which was outlined by UCSF Professor Vinay Prasad in this op-ed published 2 years ago, Scientists who express different views on Covid-19 should be heard, not demonized
But #2 is critically important. If there is fraud/ willful misconduct, the liability protection is removed. If the FDA is truly working for the people, these allegations must be investigated.
In order to help facilitate option #2, I personally am aware of over a dozen fraud allegations that should be investigated. This is not a complete list. There are dozens of articles like this one that highlight irregularities in the data that need to be investigated.
My suggestion is that, in addition to the allegations in this article, the FDA should solicit a list of irregularities via an open public process to ensure that all of the key allegations are considered and investigated in order to restore trust in the system. Why would they not want to do that?
Here is only a partial list:
Pfizer admitted in a US court proceeding that there was fraud and the FDA knew about it. An admission in a court like this of fraud is surely grounds for an investigation. Watch this 2 minute video where attorney Robert Barnes describes what happened in his federal court case against Pfizer. Read this article for more: Pfizer admits to COVID vaccine clinical trial fraud in federal court.
13-year old Maddie de Garay developed paralysis less than 24 hours after she was vaccinated. I know Maddie. I know her parents. Today, Maddie is confined to a wheelchair. She was perfectly healthy before she received the vaccine. Less than 24 hours after her second dose, she couldn’t walk off the school bus. Why were her symptoms reported to the FDA in the 12-15 trial results as “functional abdominal pain”? See FDA Buries Data on Seriously Injured Child in Pfizer’s Covid-19 Clinical Trial. I notified acting FDA Commissioner Janet Woodcock on Friday, June 25, 2021 6:21 AM. She promised me the FDA would investigate the fraud. To this day (Jun 14, 2022), the family was never contacted by anyone. I know the FDA is busy, but why has nobody reached out in the year since Commissioner Woodcock promised to investigate? If one child out of 1,000 ends up paralyzed for life, shouldn’t this be something the FDA should be concerned about?
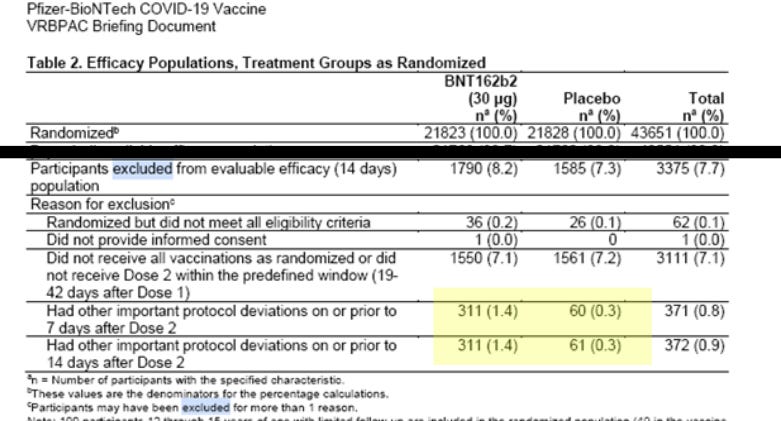
There were 5 times as many exclusions in the treatment arm as in the placebo arm of the trial. It is statistically impossible for such an imbalanced number of exclusions to have happened by chance. It appears to be a deliberate culling of patients with adverse events which is not allowed. If it wasn’t a deliberate culling, then how do you explain such large numbers? The amount of the discrepancy is greater than the entire effect size of the trial. This is from page 18 of the December 10, 2020 VRBPAC meeting document:
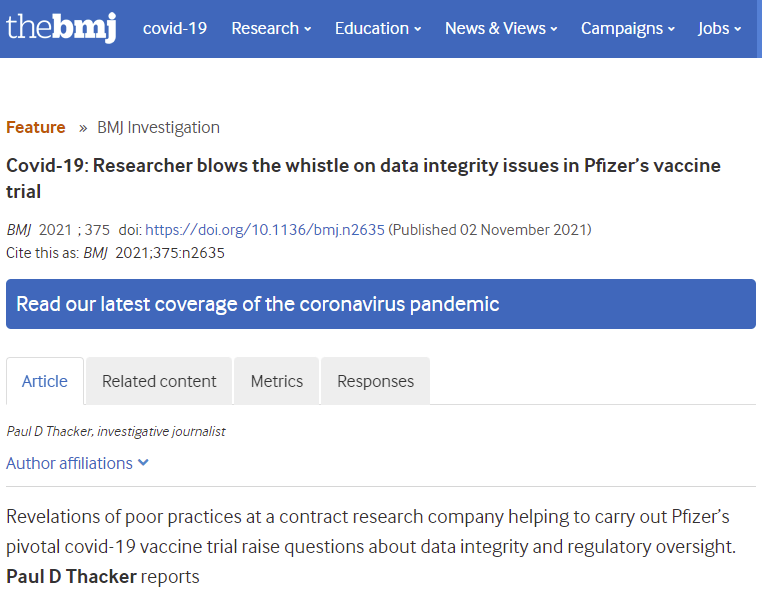
Why were the allegations of data integrity documented by the BMJ never investigated by the FDA? This is published in a major medical journal yet there was no follow up from the FDA at all. I just talked to Brook Jackson on the phone. She now has 20 lawyers on his whistleblower case. Pfizer was able to get the judge in her case to stay discovery for 6 months so an FDA investigation is the only way to compel discovery. I asked her if anyone at the FDA ever contacted her about her allegations and she said nobody ever called to talk to her. Instead, on the very same day that she emailed the FDA about what happened, she was fired. She emailed the FDA about the issues at 9am on September 25, 2020 and she was fired from her job at Ventavia at 3pm. This suggests that the FDA tipped off Pfizer who notified Ventavia. There was no other way Pfizer could have known: Brook only contacted the FDA. Period. The FDA needs to find out who at that FDA tipped off Pfizer, and then who at Pfizer told Ventavia to fire Brook instead of investigating the allegations. There has to be a chain of custody here. We deserve to know what actions the FDA is going to take against that employee who notified Pfizer. Or to notify the public that this is the proper behavior by FDA employees receiving whistleblower complaints is to take actions to get the whistleblower fired. We need to understand how the leadership of the FDA feels about what happened and whether they intend to get to the bottom of it or simply ignore it.
BMJ article documenting irregularities in the Pfizer trial. The whistleblower was fired 6 hours after notifying the FDA which must have leaked the information for Pfizer.
There were more deaths in the treatment arm than in the placebo arm. How does the FDA know for certain that the people who died in the treatment arm did not die as a result of the drug? Did they ever look at the data from Pfizer on this? If so, what convinced them the deaths were not related? Can we see the written report which certified this? Pfizer says the deaths were unrelated, but we are never told how they determined this. Were the same tests done as Dr. Walter Lang did (see this video and also this article) and that Dr. Bhakdi and Dr. Burkhardt did? Dr. Peter Schirmacher also discovered that at least 30% to 40% of the deaths shortly after vaccination were likely caused by the vaccine. Schirmacher’s family’s life was then threatened if Schirmacher said anything more publicly. Did Pfizer use the same methodology as Dr. Schirmacher, Bhakdi, Burkhardt, and Lang? Why did Schirmacher, Bhakdi, Burkhart, and Lang all find a huge rate of causality but Pfizer found nothing. They cannot both be right. How will the FDA resolve the discrepancy and assure the public they found the truth?
A report Pfizer filed with the FDA entitled “Summary Basis for Regulatory Action” contains the following statements which are in conflict with data in the VAERS system which is reporting unprecedented increases in adverse events. There are more adverse and serious adverse events reported for the COVID vaccines than for all vaccines combined over the past 32 years. Therefore, the VAERS data and this report simply cannot both be true. The FDA needs to find out which is giving inaccurate data and correct the problem:
The documents released by Pfizer show a large number of discrepancies that are impossible to explain if the trial was executed as stated. Can you investigate all the discrepancies pointed out in articles such as this and this?
Why isSudden Adult Death Syndrome only affecting people who have been vaccinated with the COVID vaccines? Is there a counter-example?
Why are athletes dying at 22X the normal rate? And why is this only happening after the vaccines rolled out?
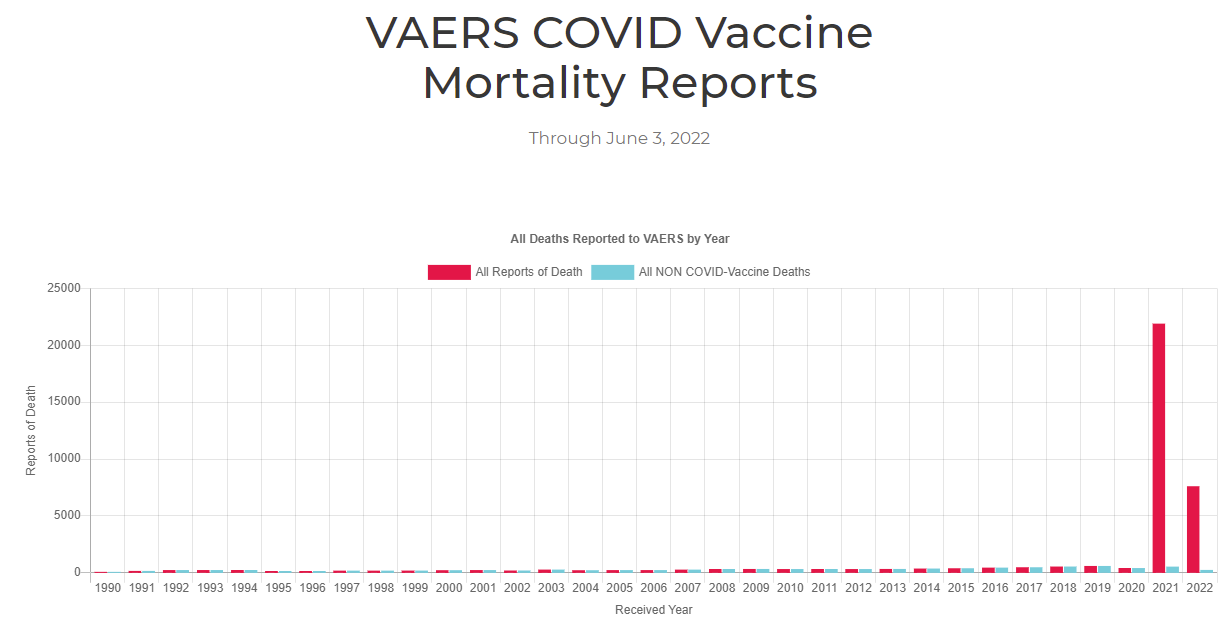
Why are there more deaths reported associated with the COVID vaccines in VAERS than for all vaccines combined in the 32 year history of the VAERS system? It isn’t over-reporting because the deaths for all other vaccines for all years is still completely normal as you can see from this chart:
Mortality chart from OpenVAERS shows that the death reports are elevated only for the COVID vaccines and not for any other vaccines in the entire history of the VAERS system
Shouldn’t the FDA and CDC call for a protective order to prevent retribution by state medical boards against physicians who are reporting adverse events and death following vaccination on social media? Clearly, the CDC and FDA are extremely safety conscious and would want to know about these incidents? So why not make a statement encouraging licensed MDs to speak out?
Why is the public not permitted to see the assessments made of the 13,225 US deaths reported in the VAERS system that were determined to be not linked to the COVID vaccines?
Dr. John Su at the CDC appears to be a co-conspirator with Pfizer to hide the safety data. Whenever he presents, he never mentions that the VAERS data should be multiplied by the appropriate under-reporting factor (URF). This allows the vaccines to look 100 times safer than they actually are. He knows he shouldn’t be doing this, but this hasn’t inhibited his actions at all. The FDA and CDC refuse to acknowledge what the VAERS URF is for these vaccines and they stonewall newspaper reporters who ask about it. How is that being transparent?
Anecdotal data from physicians. There is simply too much anecdotal data from formerly pro-vax physicians who report patients who are previously healthy become “unhealthy” (new disease, existing disease reoccurs, or cognitive decline, or menstrual issues) shortly after being vaccinated. How can that be if the rates are the same before and after the vaccine?
I am back after a disruptive week, flight cancelled, tech stolen etc.
The bonus about having limited access to the internet is that by the time I started to write about a news article I was reading, it had been removed. Normally I wouldn’t have noticed but my sporadic typing meant going back and forth to the article over a number of days.
I was going to write about the study in the article but instead I will preserve the original article itself which was published on MSN.com
*UPDATE – As I type the actual study has been removed as well*
Severe COVID-19 ‘Rare’ In Unvaccinated People, Survey Reveals
A survey has found that people who did not get the vaccine had a lower rate of suffering severe COVID-19 amid the pandemic.
The survey uploaded to the preprint server ResearchGate presented data from more than 18,500 respondents from the “Control Group” project with more than 300,000 overall participants. An analysis revealed that compared to those who got jabbed, unvaccinated people reported fewer hospitalizations.
The international survey also found that the unvaccinated people from more than 175 countries were more likely to self-care to prevent and manage COVID-19 infection. They used natural products like vitamin D, vitamin C, zinc, quercetin, and drugs, such as ivermectin and hydroxychloroquine.
Many participants experienced discrimination for refusing the administration of “genetic vaccines” and struggled with mental health burdens due to the stigma in the mostly “vaccinated” society.
The participants admitted to avoiding vaccines due to their preference for natural medicine interventions and skepticism of pharmaceutical interventions. They also voiced distrust of government information and fear of the possible adverse effects of the vaccines in the long run.
The survey was conducted from September 2021 through February 2022. During the period, participants experienced mild to moderate COVID-19 infection and were infrequently hospitalized.
A number of female participants suffered menstrual and bleeding abnormalities, prompting the researchers who analyzed the data to surmise that the issues might have been caused by spike protein exposure and shedding, as per The Epoch Times.
Data collected from the survey were analyzed and interpreted by an independent, international team of scientists led by Robert Verkerk, Ph.D., the founder and executive and scientific director of Alliance for Natural Health International.
The link to the original article is here but as you can see this just diverts back to the home page.
Wayback Machine seems to be empty but fortunately Google has cached it for now.
The study itself can be read on ResearchGate. (Update – this has now been removed). However, this one is still available on the Wayback Machine.
It used data from a UK citizen-led cooperative called the Control Group Cooperative (CGC). This was formed in July 2021 “to represent the interests of individuals and families around the world who have chosen to not receive COVID-19 ‘vaccine’. Among the aims of the CGC is to evaluate long-term health outcomes among the COVID-19 vaccine-free, as well as linking its members to country support networks and online community groups. Participants who join the ‘control group’ may obtain an ID card (Fig. 1), in the relevant language. The card includes the statement that the individual is part of a SARS-CoV-2 Control Group and “must not be vaccinated”. Many members have reported that these ID cards have been successful in allowing travel, preventing forced vaccination (vaccination without informed consent) or avoiding the loss of liberties, such as access to venues otherwise limited to COVID-19-vaccinated individuals.”
There were around 300,000 members of the CGC which were predominantly from Europe (40.2%) with 25% from North America and 27% from Oceania. Approximately 18,500 were part of the survey on which the study was based.
The study was independent to the CGC and looked at the first five months of survey data. By using data from this group there is an obvious bias but interesting to see the results nevertheless.
Findings included the fact that the unvaccinated did not place a disproportionate burden on health systems. In fact only 0.4% of the cohort were hospitalised with COVID-19 which compared with 0.6% for the US population as a whole.
Reasons for individuals not wanting to be vaccinated was an almost equal five way split between preferring natural medication (16.8%), distrust of pharmaceutical intervention (16.4%), distrust of government information (16.4%), poor/limited trial study data (16.3%) and fear of long-term adverse reactions (15.4%).
Almost 75% of respondents, who had COVID-19, engaged in self-care using vitamins (such as D and C), minerals (zinc), quercetin, as well as ivermectin and hydroxychloroquine. The amount of people using dietary supplements was highest in the USA with 71% of respondents but still relatively high at 60-65% in the rest of the Western world.
A surprising finding was that there were common reports of menstrual disturbances and bleeding abnormalities in the unvaccinated female cohort. The authors suggest a number of reasons this may have occurred, including: COVID-19, pandemic lifestyle changes, shedding exposure or chronic stress.
Around 40% of respondents reported mental health problems due to the psychological stress of the pandemic. It is suggested that “the mental health burden may be associated more to the human response to the pandemic, rather than psychological, fear-based reactions to any threat posed by the SARS-CoV-2 virus itself. This includes discrimination in the workplace, by peers or by family members, as well as victimisation by states (governments/health authorities) owing to ‘unvaccinated’ status.
Much of this disproportionate and discriminatory treatment is likely the result of widespread misunderstandings about, and over-stated benefits of, COVID-19 ‘vaccines’, false claims over societal risks posed by the unvaccinated, media and state propaganda and coercion to ensure high rates of COVID-19 vaccination, institutional mandates, and the desire for in-group identity as explained by social identity theory (Scheepers and Derks, 2016).”
As I said above, the study is clearly biased. However, there is some interesting data to look at (which public health authorities have largely hidden or not collected) and so this study should not be disappeared. It should remain to be dissected and analysed and if others decide the findings are nonsense, it is for them to argue the reasons why.
Investigative Journalist with a popular Substack, Igor Chudov, explains his recent discoveries comparing the dramatic difference in Covid-19 death rates in both Portugal and South Africa, and what could be the cause.
Immune Dysfunction Expert, James Neuenschwander, joins Del to talk about the critical effect lockdowns and masking has had on our immune systems, particularly those of young people. Is there a direct link between the lack of exposure to germs and viruses in recent years and the current spike in deadly outbreaks of hepatitis and RSV?
The state government of Florida is standing up against the effort to indiscriminately inject experimental coronavirus “vaccine” shots into children four years old and younger. And, as reported Wednesday by Christopher O’Donnell and Ian Hodgson at the Tampa Bay Times, Florida is the only state to make this decision, every other state government having pre-ordered the shots from the United States government in anticipation of the granting of US regulatory approval.
Good for Florida. It is making the right choice in refusing to be a pusher for these shots promoted relentlessly by a collaboration of big business, big media, and big government.
In May of last year I wrote about the need for state and local governments to refuse to participate in the then new rollout of experimental coronavirus shots to 12 to 15 years old children. I concluded my comments on the matter with the following statement after addressing dangers of the shots and the very minimal risk coronavirus tends to pose for children:
It is one thing to stand aside as parents choose to have their children injected with experimental shots that carry significant known health risks and unknown potential negative consequences. It is another to actively encourage the giving of such shots through participating in their promotion and distribution. At some point, shouldn’t state and local governments admit that the risk and rewards related to shots are so out of whack that their taking part in pushing the shot-giving is a clear menace? Being presented with the opportunity to give experimental coronavirus vaccine shots to 12 to 15 years old children seems like a good time to declare ‘no more.’
A statement from the Florida Department of Health, reprinted at Fox 13 TV of Tampa Bay, makes clear that the state government’s decision not to preorder the shots was its way of saying “no more” based on the state having come to its own independent decision that the shots are not the safe and effective wonder for all young children that many people in government and the media proclaim them to be. Here is that statement from the Florida Department of Health:
The Florida Department of Health (Department) has made it clear to the federal government that states do not need to be involved in the convoluted vaccine distribution process, especially when the federal government has a track record of developing inconsistent and unsustainable COVID-19 policies.
It is also no surprise we chose not to participate in the distribution of the COVID-19 vaccine when the Department does not recommend it for all children. Doctors can order vaccines if they are in need, and there are currently no orders in the department’s ordering system for the COVID-19 vaccine for this age group.
The local television news report also provided these cogent comments regarding the decision from Joseph Ladapo, the state’s surgeon general:
‘We expect to have good data that the benefits outweigh the risks of any therapies or treatments before we recommend those therapies or treatments to Floridians. That is not going to change. I don’t think that is particularly radical. I think it’s very sensible,’ said Ladapo. ‘From what I have seen, there is just insufficient data to inform benefits and risk in children. I think that’s very unequivocal.’
Bravo to Florida and its surgeon general, about whom I wrote positively upon his appointment to the position in September.
Hopefully, we will see more state and local governments looking critically at the new shady approval of experimental coronavirus shots for young children and declaring their refusal to participate as well.
On June 8th 2022, I sent the following email to several reporters and one editor at al.com, which is the largest news organisation in my state of Alabama. I encourage other Daily Sceptic readers to send the same type of email to the major news organisations in their cities or states.
I don’t expect this news organisation to follow-up on my story suggestions and answer any of my questions, although I would be happy to be proven wrong. My main purpose is to create a record that shows that these reporters and editors are aware of many data points which strongly suggest that Covid vaccines are not ‘safe and effective’ (or necessary for children), and confirm that these ‘watchdog’ journalists will not share these types of stories with their readers. Nor will they pursue their own investigations that might corroborate (or impeach) these findings.
If enough readers participate in this similar experiment, this collective evidence (and the non-responses to our ‘story suggestions’) might provide strong evidence that the mainstream media are conspiring (or at least capitulating) in the cover-up of information that would debunk or challenge many elements of the alleged ‘settled science’ about Covid vaccines. In the opinion of this correspondent, such a finding – suggesting an obvious bias and censorship – would itself constitute an alarming and disturbing scandal.
Note: Story links and excerpts (several from the Daily Sceptic) are provided below this post.
Dear [journalists who routinely write Covid stories and an editor]:
I write to bring to your attention six articles that strongly suggest that Covid vaccines are not “safe and effective” nor necessary for many people. See story links below.
My real purpose in writing is to encourage al.com to do its own reporting to see if your reporters can confirm that the trends depicted in this quantifiable data are, perhaps, also being seen in Alabama.
Specifically:
Are Alabama ambulance companies responding to more calls from individuals suffering health emergencies related to cardiac events than they did prior to widespread Covid vaccination?
Are life insurance companies doing business in Alabama reporting more excess deaths in policy holders since vaccines became widespread, especially in the ages 18 to 64? What are these numbers?
Are funeral homes in Alabama performing more funerals and cremations compared to time periods before Covid vaccines had been widely administered?
Are doctors seeing more complications in vaccinated patients?
Do vaccinated Alabamians now comprise the greatest percentage of PCR-confirmed Covid cases? Are the percentage of vaccinated patients being treated in hospitals now higher than the unvaccinated cohort (as appears to be the case in the U.K., whose data are much more comprehensive and transparent)? Are the percentages of deaths in older age groups (60 plus) now higher among the vaccinated class (as is also the case in the U.K. and other countries)?
How many Alabama children under the age of 18 without serious pre-existing medical conditions have died from Covid in the past 27 months (this would be the mortality figure for ‘healthy’ children)? How many healthy Alabama children died from Covid in the first 12 months of the pandemic? Is death from Covid actually one of the ‘top eight’ or ‘top 10 causes of death of Alabama children in a given year (as has been quoted by public health officials and officials at pediatrician groups)? What are the top 10 annual killers of Alabama children with the number of annual deaths per year?
If I wrote a 1,000-word article, listing several of the ‘accepted Covid narratives’ that I believe are false or dubious and why I believe they are, would you publish this piece?
I’ve come to believe that journalism or independent investigations that would challenge key parts of the ‘Covid narrative’ is not allowed at mainstream news organisations. Can you provide examples from your own reporting that would debunk or refute this theory? Is al.com going to follow up on these articles with your own reporting? If not, why not? Have reporters been told that certain Covid stories cannot be reported? Which al.com journalists have written any story that challenges or questions key parts of the CDC’s ‘settled science’?
Virology Journal has published a letter from a cardiovascular surgeon, Kenji Yamamoto, setting out the case for ceasing all Covid vaccine booster programmes on safety grounds, calling Covid vaccines a “major risk factor for infections in critically ill patients”. His own cardiovascular surgery department at Okamura Memorial Hospital, Japan, has seen numerous complications in vaccinated patients, including some deaths, he says.
The National Health Service has confirmed in response to a freedom of information request that ambulance call-outs relating to immediate care required for a debilitating condition affecting the heart nearly doubled in the whole of 2021 and are still on the rise further in 2022. But the most concerning published figures show that they have also doubled among people under the age of 30.
We are seeing, right now, the highest death rates we have seen in the history of this business – not just at OneAmerica,” the company’s CEO Scott Davison said during an online news conference this week. “The data is consistent across every player in that business.” …
Davison said the increase in deaths represents “huge, huge numbers,” and that’s it’s not elderly people who are dying, but “primarily working-age people 18 to 64” … “Just to give you an idea of how bad that is, a three-sigma or a one-in-200-year catastrophe would be 10% increase over pre-pandemic,” he said. “So 40% is just unheard of.
On Wednesday, Dowd noted that funeral home company Carriage Services saw a 28% increase in September 2021 vs. 2020, and a 13% increase in August vs. the same period. Funerals and cremations are up 12% and 13% respectively on the quarter.
Already evident in previous weeks is that for all but the youngest group, the vaccinated were getting infected at higher rates than the unvaccinated … In several age groups, it would appear the double vaccinated are infected at four to five time the rate of the unvaccinated …
Looking at double (not triple) vaccinated, it appears they have higher rates of hospitalisation for all ages over 60, and comparable rates for ages 18-59.
In this case, the rate of death of the unboosted fully vaccinated is basically twice as high for the over 70 year olds.
Only six of the 25 Covid deaths in the U.K. in the first 12 month of the pandemic occurred among children without pre-existing serious medical conditions … This represents a mortality risk to ‘healthy’ children of approximately 0.0001%.
Perhaps a sign of the times, Ontario has finally taken a step forward by ending its schizophrenic daily reports on COVID.
Indeed, it wasn’t so long ago that Premier Doug Ford was making daily appearances to warn those in the province of the dangers of COVID and to push getting vaccinated. However, just weeks after the Freedom Convoy protest began its cross-country trip to Ottawa, Ford made noticeable changes to his rhetoric, saying it was time to get back to normal.
However, while it’s undoubtedly a good sign the Ford government doesn’t feel the need to provide daily reports on COVID anymore, the decision isn’t without caveat, as the province will continue providing COVID data weekly.
“As of June 16, all COVID-19 datasets will be updated weekly on Thursdays by 2 pm,” the Ontario Data Catalogue reads.
This policy change comes only five days after Ontario ended nearly all remaining mask requirements, including those that applied to public transit.
Besides returning to normal, another motivation for moving away from daily COVID reports on vaccination status, cases, hospitalizations, and deaths may be due to what recent data has shown.
As previously reported by The Counter Signal, the per capita case rate, hospitalization rate, and death rate by vaccination status all show that the vaccine makes almost no difference.
Moreover, those who have received a booster dose appear to be the worst off, having the highest rates of infection, hospitalization, and death per capita of any vaccination group, both in the province and Canada.
This reality completely shatters the ongoing mainstream narrative regarding the necessity of continued vaccination, with natural immunity appearing to be more than adequate — if not better — at preventing transmission and severe illness.
Either way, Ontarians and Canadians more generally might not be done with COVID quite yet, as both the federal and provincial governments have indicated that they’re more than willing to bring restrictions and mandates back in the Fall during flu season.
By Stephen KINZER | Responsible Statecraft | November 17, 2026
The following is an excerpt from Stephen Kinzer’s new book: Boiling Point: How America Brought War to Ukraine (Henry Holt and Company, November 2026)
Huddled beside an airstrip in southern Germany, a handful of anti-Communist warriors prepared to fire the first shots of the Cold War. A CIA officer from the Munich Operations Base was in charge. The Hungarian crewmen he had recruited stood nearby in flight suits. With them were two Ukrainian exiles who had volunteered to parachute into their homeland. They were code-named Apostle 1 and Apostle 2. Each carried forged identity papers, a miniature radio transmitter, a pistol, a machine gun, hand grenades, a purse full of gold coins, and a poison pill to be taken in case of capture. An unmarked C-47 transport plane was waiting.
The CIA officer overseeing this operation, a twenty-six-year-old Yale graduate named Stephen Tanner, watched the plane take off and disappear into the night. It flew over East Germany and Poland, then crossed into Soviet airspace. As it approached the Ukrainian city of Lviv, a cargo bay swung open. The two Ukrainians jumped into the darkness. Their mission was to link up with partisan fighters, seize territory, and establish a clandestine base through which the CIA could send them weapons.
That flight, on September 5, 1949, was the first American act of covert war in Ukraine. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.