On Friday, the FDA released its risk benefit assessment of Moderna’s Emergency Use Authorization (EUA) application to inject mRNA into kids 0 to 17 years old. I’ve been reading it for the past two days and here are the things that stood out to me.
I. Introduction, a shell game to hide the bad data
The risk benefit document for Moderna is 190 pages single-spaced. It was released two business days before the June 14-15 VRBPAC meeting. A similar risk benefit assessment for Pfizer’s EUA application for kids under 5 will be released tomorrow (just 24 hours before the meeting). This guarantees that NONE of the members of the VRBPAC will have read either of these documents prior to the meeting — which is exactly what the cartel wants.
One of the ways that Moderna and the FDA rig the game is by adding endless layers of complexity to hide how bad the data really is. This should have been four separate documents — Moderna in adolescents 12 to 17, Moderna in kids 6 to 11, Moderna in kids 2 to 5, and Moderna in kids 6 months to 23 months. Looked at individually, the shot fails in each of these four age groups. But by lumping them together it creates noise that makes it difficult to understand what’s going on.
Another really pernicious thing that Moderna does is to further subdivide these populations into eight different subpopulations (Randomization Set, Full Analysis Set, Immunogenicity Subset, Per-protocol Immunogenicity Subset, Per-protocol Set for Efficacy, Modified Intent-to-treat Set, MITT1 Set, Safety Set, Solicited Safety Set).
See what they did there? The public just wants to know — does the product work and what are the side effects? By dividing the data into eight subcategories involving four different age groups now you have to wade through 32 different tables to try to make sense of what happened in the clinical trial.
They do something similar with the adverse events by dividing it across five tables x four age groups = 20 adverse event tables in all.
Subdividing the data in this way also allows Moderna to eliminate or hide data that it does not like. This is what people call “massaging the data” and it is unethical and a violation of scientific norms. We’ll return to this topic below.
II. No actual health benefits so Moderna/FDA use the immunobridging trick
The risks of Covid-19 are so low in the childhood population that there were ZERO severe cases of Covid-19 in either the treatment or the control group.
Therefore, the number needed to vaccinate, to prevent a single severe case of Covid-19 in the childhood population is infinity. (Technically it’s undefined because you cannot divide by zero, but you take my point). The FDA and CDC guidance documents for how to write a risk benefit assessment state that one must provide a number needed to treat, the absolute risk reduction, and the relative risk reduction. Moderna just skipped all that because the cartel makes its own rules.
Moderna is in a race against natural immunity. But natural immunity has already won because 74.2% of kids had natural immunity by February — so by now the number is probably closer to 100%. The God-given immune system in kids has already done its part to stop the pandemic and now the FDA wants to mess that up to enrich the cartel and keep the pandemic going forever.
So how does Moderna/FDA claim that this shot was “effective”? They use an unethical statistical trick called “immunobridging.”
It makes me mad that I even have to explain it because it’s such junk science. But we all need to know exactly how the FDA rigged the process so that we can explain to the jury at Nuremberg 2 why these monsters should be convicted so here goes:
Remember, the Moderna shots produced NO reductions in severe outcomes because the risk of Covid-19 in this age group is infinitesimally small (see studies: here, here, here, and here). So Moderna ignored the actual health outcomes and switched to looking at antibodies in the blood. In the process, they engaged in two egregious sleights of hand:
First, Moderna claims that the sample size for each of the four subgroups of children is about 3,000. But when it came to looking at antibodies in the blood, Moderna threw out about 90% of the sample and only looked at the bloodwork of about 300 kids in each age group. No explanation was given for the criteria they used to exclude 90% of the sample from their analysis. We know that up to 30% of kids have no antibody response at all to Covid-19 shots so perhaps they actually started with a much larger sample and then threw out the data that showed no effect from the shot?
The second sleight of hand is that “no placebo recipients were included in the Immunogenicity Subset” (p. 26). Do you realize how huge this is? This is no longer an RCT at all — they did not include the bloodwork from anyone in the placebo group. So the study cannot rule out the possibility that the increase in antibody levels was not from the vaccine at all but could have been from natural immunity. Just astonishing.
After these sleights of hand, Moderna then compares the antibody levels in the blood of about 10% of the children against the antibody levels in a sample of about 300 adults ages 18 to 25 enrolled in a previous clinical trial. If the antibody levels are similar (which they are), Moderna claims, ‘And therefore it will prevent disease in the future in kids!’
A few problems with that claim:
The Moderna study only measured antibody levels two months after the second dose — the time period when the antibody levels are at their peak (what Berenson calls “the happy valley”). But real world experience with these vaccines shows that any efficacy quickly wanes to zero by six months and then goes NEGATIVE after that.
The second problem, and this is unresolvable and instantly disqualifying for Moderna, is that at the April 6, 2022, meeting of the FDA’s “expert advisory committee” one member after another acknowledged that there are no “correlates of protection” for these vaccines. What that means in plain English is that you cannot use antibodies (or B-cells, T-cells, or any other proxy) to predict whether someone is immune or not.
Eric Rubin, who serves on that committee and is also the editor of the NEJM stated it bluntly, “We know what kind of antibody response can be generated, we just don’t know if it works.” You can watch it yourself on video:
The third problem is that the Moderna study was completed back in mid-2021 — when the original Wuhan and Alpha strains were prevalent. Since then, the Omicron variant has entirely replaced the original strains and real world data show that both Moderna and Pfizer shots are not effective against the Omicron variant. So in spite of all of the chicanery (discarding 90% of the sample, immunobridging, claiming correlates of protection that are not valid) Moderna cannot show any evidence that this shot will be effective against SARS-CoV-2 as it exists now.
III. It’s all harms
Let’s talk about harms from this shot (and remember, it’s all harms in this population because the shot made no difference on real world health outcomes). And there, things get really weird really fast.
The median study follow-up duration was just 53 days after dose 2. After that they wiped out the control group. Here’s how they justified it:
Following authorization of an alternative COVID-19 vaccine for this age group on May 10, 2021, participants in the study were permitted to unblind to study treatment. Crossover vaccination with mRNA-1273 of participants initially randomized to placebo began in October 2021. (p. 26)
For each age category, Moderna spreads the adverse events across 5 different tables to increase the noise to hide the signal. But the bottom line is that the adverse events are off the charts.
In the adolescent population 99.2% of vaccine recipients reported at least one adverse reaction after any injection with 25.3% reporting a reaction that was Grade 3 or higher. (p. 54).
Holy sh*t those numbers are high. Grade 3 means: unable to return to work or school the next day because the person is so sick.
A different FDA staffer must have written the summary statements for the other three age groups because they don’t say it this plainly but the adverse event rates are similar across all of the children.
This adverse event data is so high it’s disqualifying.
But then things get even weirder — the adverse event rates in the placebo group were also very high in many, but not all, categories. Moderna used this to say, ‘well yes, the adverse event rate in the treatment group was higher than anything anyone has ever seen before but the rates were also somewhat high in the placebo group and so therefore nothing-to-see-here(TM).’
My strong suspicion in that Moderna rigged the placebo. Why wouldn’t they — the FDA has no regulations concerning the contents of placebos (see Golomb 1995 and Golomb et al. 2010). The dirty little secret of the vaccine program is that manufacturers almost always use rigged placebos to create an artificially high “background rate” to hide adverse events. The brilliant quant Jessica Rose made a similar observation yesterday in her analysis of the FDA risk benefit document:
I still have a very strong suspicion that these ‘placebos’ are not saline and rather empty LNPs. [Lipid nanoparticles — the delivery vehicle that Moderna uses to get mRNA into the cell. An “empty LNP” would be the nanoparticles without the mRNA antigen.]
I’m almost certain this is what Moderna did. In the 2- through 5-year-old age group 37.5% of placebo recipients reported unsolicited adverse events as compared with 40% of vaccine recipients (see p. 139). A number that high in the placebo group would have been impossible if Moderna had used an inert saline placebo.
IV. The way that the FDA rigged the myocarditis data is absolutely sinister
I know that this article is already long but I need to flag one more essential point.
FDA review of the Moderna mRNA shot in adolescents has been held up for a year because the Moderna shot causes myocarditis in this age group — particularly in boys.
So I was curious to see how the FDA would attempt to get around this. And it’s all right there on pages 19 and 20. It’s one of the most chilling things I’ve ever read. The FDA’s argument goes like this:
‘Yes, by spring and summer of 2021 there were already seven high quality studies from around the world showing that mRNA shots increase myocarditis risk. By fall of 2021, the reports continued to come in from the U.K., Europe, Canada, and Nordic countries showing a 2x to 7x increased risk of myocarditis from mRNA shots. Yes, the CDC’s own study of the Vaccine Safety Datalink showed a 2x higher risk of myocarditis from Moderna shots. By May of 2022, we have additional studies from the U.K., Denmark, several Nordic countries, Italy, and France showing a 3x to 7x increased risk of myocarditis from the Moderna shot.’
In all, the FDA cited TWENTY-SIX STUDIES showing that mRNA shots in general, and Moderna in particular, increase the risk of myocarditis.
‘But not to worry!’ the FDA announces in the 4th paragraph in this section. The FDA, CDC, and Kaiser Permanente put their fixers on the case in February and March of this year and made the safety signal shrink down to a more manageable 7% to 50% increased risk of myocarditis and even those results were massaged to make sure that they were not statistically significant, so, nothing-to-see-here(TM). It was the same fixers who they always use — Tom Shimabukuro and John Su — whose entire job is making vaccine safety signals disappear. Those guys are absolutely going to hell.
‘So that’s that,’ the FDA announces. ‘Just ignore those 26 high quality studies from around the world showing an increased risk of myocarditis. Our fixers laundered the data for Moderna so we’re all good.’
V. What is to be done
Children’s Health Defense just launched an excellent 1-click call to action that I highly encourage you to do (and please share it with all of your friends).
Up until Monday night (June 13) at 11:59 p.m. eastern time you can officially register your profound displeasure with the FDA by submitting a formal comment (here) — look for the blue Comment button in the upper left corner of the website. 129,397 comments have already been received — let’s see if we can get that number above 140,000.
If you want to write to public health political appointees, FDA staff, and VRBPAC members, all of their email addresses are here:
Please be polite but let them know that they absolutely must vote NO on the EUA applications from Moderna and Pfizer.
VI. Conclusion
The FDA risk benefit document in connection with the Moderna mRNA shot in kids is dishonest. The public health establishment has abandoned science, logic, reason, rationality, empathy, health, and medicine. The FDA is more than happy to sacrificechildren in order to ingratiate themselves further with the cartel. The proposal to expand the Moderna EUA to kids 0 to 17 is a crime against humanity.
We are absolutely going to win this fight, either in the short term or in the long term. These shots will eventually be withdrawn from the market because they do not work and they cause catastrophic harms. The members of the Vaccines and Related Biological Products Advisory Committee can save themselves a lot of misery (and additional criminal charges at Nuremberg 2.0) by rejecting these applications from Moderna and Pfizer this week.
A growing number of young healthy adults are mysteriously dying. Watch Jefferey Jaxen and Del try to make sense of, what is now being called, “Sudden Adult Death Syndrome” (SADS).
The Vaccine Injury Compensation Program (VICP) is overwhelmed and understaffed with the amount of injury claims being filed from the Covid-19 Vaccines. The program is now on life support and is on the verge of collapse.
The CDC has walked back it’s initial recommendation to mask for Monkeypox, which triggered a firestorm of criticism from the medical and scientific communities.
COVID vaccine mandates are necessary because the protected need to be protected from the unprotected by forcing the unprotected to use the protection that didn’t protect the protected.
Then the only thing that can prevent the vaccinated from being more at risk of COVID infections is getting boosters every few months.
But the boosters can damage your immunity, as noted by Marco Cavaleri, one of the top officials at the European Medicines Agency who, according to Bloomberg,
“warned that frequent Covid-19 booster shots could adversely affect the immune response and may not be feasible. Repeat booster doses every four months could eventually weaken the immune response…”
Scientists are probably working on a solution for the “too many boosters” problem, but have not succeeded yet.
Meanwhile, “trust the science,” and “trust the experts.” I am sure they will come up with something.
Last week Serena Wylde reported for TCW on the lawsuit that the whistleblower Brook Jackson has filed against Pfizer which she feared would be thrown out. Today she updates us on the case.
IT TAKES a special type of person to stay the course as a whistleblower. Dismissal from employment, vilification and isolation are just a few of the prices to pay. But Brook Jackson, the clinical trial regional director who has been battling against Pfizer since 2020 to bring facts to light, is not bowing to intimidation.
Having brought a case against the corporate goliath in January 2021 under the False Claims Act, Jackson was under a gagging order, and her lawyers warned her not to break it as ‘the government would come after her’. But break it she did when in September of 2021 she sent copious amounts of evidence to the British Medical Journal. At this point her attorneys from Berg and Androphy withdrew from the case, leaving her without counsel.
In February of this year the case was finally unsealed and, as reported here last week, Pfizer has filed a motion to have it thrown out. Its argument is essentially that the purchasing party – the US government – of its contract to supply 100million doses of injections in exchange for $1.9billion of US taxpayers’ money, tacitly agreed to the use of fraudulent data. Under this tortuous reasoning, it would appear to be relying on an interpretation that, as both contracting parties were complicit in the sham clinical trials, no breach of contract has occurred.
Some time back we learnt that the Covid-19 injection manufacturers had been granted immunity by governments against civil damages for injury and deaths caused by their products.
But what about criminal responsibility?
An important question must surely be how the law defines intent when it comes to inflicting harm? If a medical practitioner administers an inappropriate and toxic drug to a patient knowing it has the potential to cause harm, including death, is not a resulting fatality classed as a homicide?
As one physician-scientist explained during Republican Senator Ron Johnson’s Expert Panel Discussion on Covid-19 vaccine injuries, held on November 2, 2021, ‘Pfizer don’t do science. They do business. And the Food and Drug Administration know and enable this.’
All eyes are now on the judge, who has granted discovery about any issue related to Pfizer’s motion to dismiss the case. Jackson’s lawyer, Robert Barnes of Barnes Law LLP, says: ‘This is probably the biggest whistleblower False Claims Act case in the history of the United States.’
There is an interview with Robert Barnes at the end of the article which you can see here.
One of the many things that continues to baffle me about the public response to all things Covid, is that the number of people demanding answers to the following questions is pitifully and inexplicably low:
Who was behind the creation of SARS-CoV-2?
Why were they making it?
How and why did it get unleashed on the world?
These questions should unite both those who believe with their whole heart that Lockdowns were necessary and saved lives, and those like me who believe they were utterly futile on their own terms, and have caused untold destruction. They should unite both those who believe that masks were necessary and saved lives, and those like me who believe them to have been utterly futile on their own terms, and a destructive dehumanising force designed to perpetuate fear. They should unite both those who think that the so-called vaccines were safe and effective, and those who believe these blood-clotting, immune-suppressing, gene-editing injections to have been useless on their own terms, and the cause of mass casualties, which will one day be found to have killed millions upon millions of people over the course of several years.
All of us should be demanding who was behind this, why they were doing it, and how it came to be unleashed on humanity. For the fact is that a cytotoxic Spike Protein, with HIV Gp120 inserts which infect and destroy immune cells, was created in a laboratory and added to a coronavirus in gain-of-function research. Why are people not interested in who did this to them and why? Why are they not interested in who was behind something that was used to basically mess up their lives, and the entire planet, for the last two years, and long into the future.
If this were a movie, everybody would be waiting with baited breath for the super villains — Fauci, Daszak, Baric, Gates, Schwab to name but five — to face the reckoning. And yet crickets. It’s a bit like if Hitler had survived in 1945 and the Jews and other people groups who suffered under his murderous regime shrugged their shoulders and said, “We need to move on. When’s my next holiday coming?” To those who think the comparison is ludicrous, I would point out that the official number of deaths from the lab-created, souped up coronavirus now exceeds the number 6 million — an infamous historical number — and I would add to it that the number of deaths from Phase 2 of the operation will, in the end, dwarf that number many times over.
What do I mean Phase 2 of the operation? I mean the fiendishly clever plan to inject billions of people around the world with a totally new, experimental product which would cause their bodies to produce the same gain-of-function Spike Protein, replete with the HIV Gp120 insert, by the billions, for an unknown amount of time. The entire point of Phase 1 — the release of the lab-created SARS-CoV-2 — was to create the fear that would lead to these injections. Does anybody seriously still believe these products were an improvised, off-the-cuff response to that virus? If so, perhaps they’d care to explain how all four major manufacturers of these products (Pfizer, AstraZeneca, Moderna, Johnson and Johnson) all just happened to choose the same cytotoxic Spike Protein as the part of the virus that the human body would produce? As Mike Yeadon, former Pfizer VP for Allergy and Respiratory Research has pointed out, it is the most dangerous part of the virus, as well as that which mutates the most quickly, making it the most unsuitable part to use in a vaccine. And yet four companies did just that. Perhaps they’d also care to explain Moderna’s confidentiality agreement with the National Institute of Allergy and Infectious Diseases (NIAID) to ‘transfer mRNA coronavirus vaccine candidates’ in December 2019. There is no doubt at all that Covid-19 was known about long before you and I ever got to hear about it, as this mention of it in the US Department of Defense database in November 2019, in a contract connected to one of those harmless and benevolent Ukrainian biolabs, clearly shows. There is, therefore, no doubt that the manufacturers of the bioweapon masquerading as a vaccine knew about it and were on it well before it was a thing for the rest of us.
These so-called vaccines, which were never safe nor effective, have already killed or maimed millions around the world. But the real damage is only just beginning. Not only do they train the body to produce antibodies to fight a non-existent enemy — the long-departed original SARS-CoV-2 Spike Protein, which is a bit like the 21st Century British Army training to fight a battalion in Hitler’s Wehrmacht — but even more crucially, they infect and kill crucial T-cells. Which is why the ‘vaccinated’ keep getting Covid reinfections — their immune systems have been left defenseless, and with each recurring bout it becomes increasingly depleted.
Which brings us on to Phase 3. Whilst Phase 1 was about freaking people out with a virus that was dangerous to very few (albeit eminently treatable), and Phase 2 was about injecting people with the poison shot masquerading as the solution, Phase 3 is — I believe — all about covering up the effects of the depleted immune systems of millions of people, to ensure that most people continue to ask no questions and many of them ‘go gentle into that good night’. How? By the release of another lab-created, gain-of-function pathogen, which will be used to explain away the ‘mysterious’ deaths of people with crippled immune systems. If Phase 1 and 2 were fiendishly clever, this is from the pit of Gehenna itself.
Alarmingly, there is a probability that such a pathogen has indeed been released, although it is still too early to know if this is what a grinning William Gates III described as ‘the next one’. Much like the Event 201 simulation in October 2019, which just happened to simulate a global coronavirus pandemic, at the March 2021 Munich Security Conference a ‘Tabletop Exercise’ was conducted entitled, ‘Strengthening Global Systems to Prevent and Respond to High-Consequence Biological Threats.’ Here’s the blurb:
“The exercise scenario portrayed a deadly, global pandemic involving an unusual strain of monkeypox virus that emerged in the fictional nation of Brinia and spread globally over 18 months. Ultimately, the exercise scenario revealed that the initial outbreak was caused by a terrorist attack using a pathogen engineered in a laboratory with inadequate biosafety and biosecurity provisions and weak oversight. By the end of the exercise, the fictional pandemic resulted in more than three billion cases and 270 million fatalities worldwide.”
I’m genuinely unsure at this point whether Monkeypox is Phase 3. I’ve heard many say that it would be impossible to create the same level of fear as with Covid, but I’m not so sure. The 2021 Tabletop Exercise had 270 million deaths by the end of 2023, and I have this horrible feeling that a new lab-created pathogen, unleashed on a world where millions have just had their immune systems horribly damaged, could send many to untimely deaths. I pray not; I fear so.
‘Being “led by the science” is turning out to be an unmitigated disaster, yet it will be “the science” — or Government-approved science — which will be proposed as the saviour. To stop such situations occurring again, we will be told that we must avail ourselves of more technology, more monitoring, more checks, more vaccines, more controls. … Personally, I’d rather trust myself into the hands of the Living God than surrender to the Bill Gatesian Social Distancing Medical Despotism of compulsory vaccines, certifications and health apps that is starting to take shape around us.’
I wish people had listened to the few of us who pleaded with them back then not to fall for the lies of the criminals who were foisting this upon us. Perhaps we could have halted it in its tracks.
Adverse Reactions for Novel Covid-19 Vaccines More Numerous Than for Similar Products by Factor of Between 10 and 169
BATH, UK — A new report prepared by the World Council for Health (WCH) has confirmed that data on adverse drug reactions from the experimental Covid-19 vaccines exist in an amount sufficient for the recall of similar products in the past.
The report was prepared to determine whether sufficient pharmacovigilance data exist on official and public databases (WHO VigiAccess, CDC VAERS, EudraVigilance, and UK Yellow Card Scheme) to establish a safety signal on the novel Covid-19 injections.
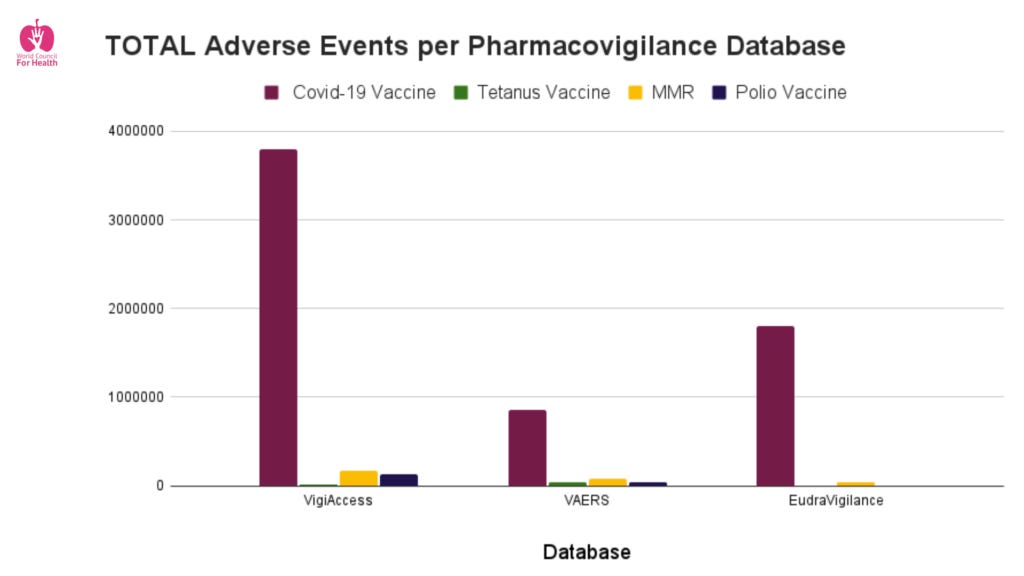
On all databases, it was found that adverse drug reaction (ADR) reports linked to Covid-19 injections are more numerous than other similar products by a factor of between 10 and 169 (see graph below). Many of the ADR reports are serious in nature and there exists sufficient evidence of associated harm on these databases to indicate a product recall.
Total Adverse Events per Pharamacovigilance Database
In total, more than 40,000 deaths are linked to the novel Covid-19 vaccines in the official databases analysed.
In addition, the WCH pharmacovigilance report found that several thousand adverse drug reactions on official databases are related to the use of the experimental Covid-19 vaccines among young boys and girls for whom the vaccine had not been approved at the time.
The purpose of pharmacovigilance databases is to provide a signal of safety, and not to prove causality. To ensure that harms are detected in time, suspicion that an event is linked to the administration of the medicine is enough to register an event. “There is no need to prove that the medicine caused the adverse reaction, just the suspicion is good enough,” Dr. June Raine, head of the UK’s Medicines and Healthcare products Regulatory Agency, said in 2006. When sufficient pharmacovigilance data show a signal of harm, administration of the product should be ceased, the product recalled, and the safety signal investigated.
It should also be noted that such systems of passive surveillance result in significantly fewer ADR reports than active surveillance reporting. As a result, the actual number of adverse events that occurred in temporal relation to Covid-19 injections is likely to be much higher than revealed by the available official data.
In December 2021, World Council for Health called on regulators and governments around the world to immediately cease use of all experimental Covid-19 injections.
Dr. Tess Lawrie, co-founder of the World Council for Health, calls for people to come together to raise awareness of vaccine injury so that those harmed can get the help they deserve. “It is concerning that a grassroots organisation has had to do this work and point out that none of these experimental vaccines are safe according to publicly available official data. Why have the regulators not done their job and protected us?“
When the JCVI considered covid vaccines for children in July 2021, they stated, “JCVI is of the view that the health benefits of universal vaccination in children and young people below the age of 18 years do not outweigh the potential risks”. Even in September 2021, they still said, “A precautionary approach was agreed given the very low risk of serious disease in those aged 12 to 15 years without an underlying health condition that puts them at increased risk.” As HART bulletin readers will know, the Chief Medical Officers eventually recommended the vaccine for 12-15s, in the vain hope of reducing school closures, which of course could have been achieved by simply stopping routine testing of asymptomatic school children and the sending home of healthy contacts.
Roll on to February 2022, when a ‘non-urgent offer’ was made of Pfizer vaccine for 5-11-year-olds, JCVI stated, “This advice on the offer of vaccination to 5 to 11-year olds who are not in a clinical risk group is considered by JCVI as a one-off pandemic response programme. As the COVID-19 pandemic moves further towards endemicity in the UK, JCVI will review whether, in the longer term, an offer of vaccination to this, and other paediatric age groups, continues to be advised.”
If any of our readers has seen this review, we would be pleased to know, as it might help us clarify the surprising appearance of Covid-19 on the NHS routine immunisation programme. Placing an unlicenced preparation onto the routine schedule is unprecedented. It raises serious questions of the legality, given the conditional authorisation was predicated on there being an emergency. It is also of course a subtle way of making parents think this vaccine is just run-of-the-mill. The current low uptake (53% of 12-15s and a mere 8.5% of 5-11s) suggests that at present, parents are well aware that covid-19 vaccines are not the same as other vaccines, either in terms of the risk of the disease for children or in terms of drug safety. They will also be well aware that lots of their triple vaccinated adult friends and family, have been catching covid regardless.
Not content with slipping this drug into the schedule under cover of the 4-day Jubilee holiday, the Local Government Association has been pushing behavioural psychology techniques to increase vaccine uptake in the young. Their opening gambit is, “Younger generations are more likely to be vaccine hesitant partly because they perceive themselves to be at lower risk of developing a severe form of COVID-19”. Surely, this is not a ‘perception’, it is a ‘fact’, which should surely have been viewed as a blessing, rather than an annoyance.
It gets worse: “Highlight the pro-social benefits of vaccination
Behavioural Insight: Emphasising the pro-social benefits of vaccination is particularly effective among young people. Prosocial benefits include achieving herd immunity and protecting others, especially those that are vulnerable and cannot get vaccinated. Combining both informational and emotional content can be effective.” Another one for the fact checkers – the JCVI say, “the benefits to the wider population are highly uncertain.”
And worse: “Highlight social norms about vaccination
Behavioural Insight: Highlighting that there are growing intentions to get vaccinated, that most people are getting vaccinated and that they approve doing so, can effectively encourage vaccine take up. Since young people tend to be more susceptible to peer influence, it is likely that social norms can be particularly effective when targeting this group.
Potential application: Emphasise Social norms in communications targeted towards young people. Make vaccination visible to other young people by setting up vaccination centres in university campuses or schools. Launch an ‘I will get vaccinated’-pledge on social media.”
And faintly ridiculous: “Second vaccine jab compliance
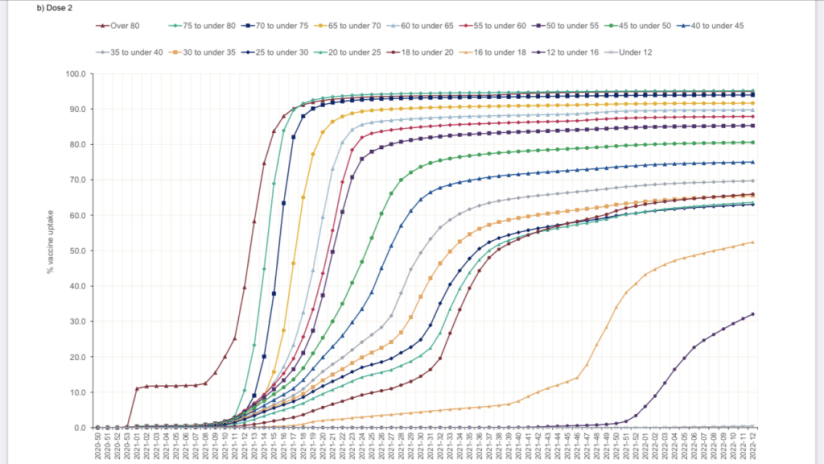
Ensuring residents take their second vaccine dose could be a challenge with which councils can support PHE and the NHS. This could be especially the case if news on vaccine efficacy and new strains undermines the perceived value of the second jab.” Again, the use of the word ‘perceived’ implies that the ‘news’ on vaccine efficacy and new strains is somehow irrelevant to informed consent. No wonder the powers that be don’t want people to see this graph from week 13 of 2022, dropped from the more recent weekly vaccine reports.
The vaccinators are in summer hibernation, but very soon they’ll be with us again, hawking a novel set of wares. The media blitz will start anew and the medical bureaucrats will return to forcing superfluous and potentially harmful medical interventions on millions of people who don’t need them. One day, all of this will be recognised for the absurd hypochondriac panic that it is, but no few people will be hurt, and at least a few will die, before we get there. What follows are some thoughts I have about how to approach especially older acquaintances, who will be at ground zero of the coming propaganda campaign, and who probably don’t need a fifth dose of the magical miraculous mRNA elixir.
First, some notes on normie psychology:
You have to understand that they think the vaccines are the best things ever. They believe Pfizer and Moderna have almost singlehandedly turned the whole pandemic around and given them their lives back. If ever a doubt should creep into their minds about that, they will fall back to believing that being vaccinated is the right pro-social thing to do, and that not being vaccinated is evil, selfish and stupid. It is the unvaccinated who are responsible for variants, who spread Corona and who are prolonging the pandemic. Normies have The Science on their side, and they take great comfort in buying into and espousing the mythology that has been sold to them. This is how sophisticated propaganda and information management works. Contradictory information will make them extremely uncomfortable, and they’ll look for any reason at all not to believe it. If you cause them too much discomfort, they’ll get angry, tune you out, and put you in the antivaxxer bin, where you can be safely ignored.
It’s going to be very hard to win ground here, and your goal shouldn’t be total victory. You just want to get them to think for themselves, consider their own experiences as valid and real information about the world, and break out of the limited vaccinator-cult patterns of thought long enough to ponder how many boosters they really want to put up with.
The most important thing is to present a relaxed, jovial scepticism on key points. The goal is not to argue, but to challenge in an oblique, casual way, while giving as much as you take. Unless we’re talking about somebody who absolutely trusts you and is earnestly seeking your opinion, you shouldn’t be scheduling in-depth conversations or sitting down for a serious talk. You want to raise questions and plant little seeds of doubt, before they ever realise what is happening, and then you want to fade away before they notice that you’re encouraging them to have heretical thoughts.
I. Pharma is losing the game so they are throwing the chess board across the room
The NY Times published a vile piece of fascist Pharma propaganda today. Berenson flagged the online version of the article yesterday. As you know, I have been yelling about the FDA’s Orwellian “Future Framework” for weeks because it’s literally the worst idea in the history of public health.
It turns out that it’s even worse than I thought.
Pharma has already begun a PR offensive to get it across the line and Sharon LaFraniere of the NY Times was eager to do their bidding.
Here’s what’s happening. The mRNA shots are not working against SARS-CoV-2. Everyone knows this. So Moderna and Pfizer are racing to reformulate these shots. The reformulated shots are not working either. Just last week Moderna was touting a bivalent shot that combined Alpha + Beta, but now, apparently, they’ve abandoned that approach. The NY Times article hypes a Moderna shot targeting earlier Omicron variants (it does not say, but perhaps BA.2 and BA.2.12.1?). However evidence from South Africa shows that BA.4 and BA.5 are outcompeting the earlier Omicron variants and the reformulated Moderna shot probably won’t work against the new strains (the virus evolved for a reason — to evade vaccines).
So what are predatory pharmaceutical companies and their feckless government enablers supposed to do!? Abandon clinical trials altogether!
Here’s how the NY Times describes this scheme:
… many experts worry that the virus is evolving so quickly that it is outpacing the ability to modify vaccines, at least as long as the United States relies on human clinical trials for results.
See, it’s not that coronavirus vaccine have failed over and over again (even though they have). It’s that This Wily Virus(TM) is just evolving so quickly that we could not possibly allow human clinical trials of coronavirus vaccines ever again. The only way to beat This Wily Virus(TM) at this point is to abandon science.
Of course it gets worse. The NY Times elaborates:
The problem is that Moderna and Pfizer — the maker of the other main coronavirus vaccine in the United States — do not have enough time now to run more human clinical trials and still manufacture shots before the fall, when the Biden administration is hoping to be able to offer an updated vaccine to counter what public health experts predict will be a winter surge.
See, it’s not that rapacious pharmaceutical companies want to suck all wealth out of the world and put it into their own pockets while setting up a 1,000 year Pharma Reich. No, no, no, silly. It’s just that they “do not have enough time” to do actual science anymore so they are just going to skip all that. Don’t you worry your little head about it.
Furthermore, only a conspiracy theorist would believe that the FDA has abandoned all of its statutory responsibilities to protect public health in order to prostitute themselves to Pharma. The Correct Understanding(TM) is that the FDA is being forced by circumstances outside their control to abandon science. This is not a problem because the cartel is truth, the cartel has always been truth, and since the cartel has decided to abandon science altogether then that’s the new science.
Henceforth, quite literally, the peasants will be forced every six months to inject whatever they are told, with no questions asked, and “they will be [required by law to be] happy about it”.
Instead of human clinical trials the FDA will rely on a few test tube and mouse studies. In the article, Fauci describes this as, “alternative pathways of decision.” That guy just oozes totalitarianism at this point.
So if the “Future Framework” is approved on June 28 the new rules will be: a pharmaceutical company can claim that some new injection creates antibodies in a test tube or mouse (that no one else can see or audit). Done! Ship it and inject it! That’s it. Even though the FDA admits that there are no “correlates of protection.”
In the replies to my earlier articles about the Future Framework some astute readers have pointed out that the FDA has already abandoned human trials when it comes to Covid-19 shots in kids. None of the Moderna or Pfizer clinical trials in kids showed any real world health benefit at all. So they switched to looking at antibodies in the blood and use this tortured mental gymnastics called “immunobridging” to conjure up hypothetical future benefits that never materialize in the real world. Abandoning even the pretense of human trials and moving to test tubes and mice is the obvious next step in this complete abandonment of science.
When people say “I Believe The Science(TM)” what they really mean is “I Support The Genocide.” That’s what’s happening. The FDA has not done science in two years, probably much longer than that.
There is no left and right in politics anymore. Just, the FDA Pharma Fascist Party where members are expected to participate in self-genocide for “the good of society” (read: the profits of the cartel)
vs.
the Rebel Alliance where we practice actual science, critical thinking, logic, and reason, and work every day to protect human health and dignity.
Any politician who wants the 18 million votes of single-issue medical freedom voters in November needs to know that there must be hearings, arrests, and trials of the bureaucrats at FDA, CDC, NIAID, HHS, and NIH who did this to us.
II. What is to be done?
In the meantime, here are the email addresses for all of the public health political appointees, FDA staff, and VRBPAC members who have a say in connection with the “Future Framework”. Please contact them to urge them to reject this nonsense (proposed subject line and email text below — or share your own personal story).
Subject line: The “Future Framework” is the WORST idea in the history of public health. Please vote NO.
1. No Covid-19 shots for kids that failed clinical trials. According to the journal Nature Medicine, children and young people have a 99.995% recovery rate. According to the CDC, the overwhelming majority of children already have natural immunity. The harms from Covid-19 shots in kids are catastrophic.
2. The FDA and CDC must pivot to therapeutics. About twenty off-the-shelf treatments are more effective than vaccines (if used for prophylaxis or early intervention). Get these safe and effective medicines to people who need them and let doctors be doctors again and treat patients based on their own best clinical judgment.
3. Any reformulated Covid-19 shots MUST go through proper HUMAN clinical trials and FDA review. That means:
• large (50,000+ person) double-blind randomized controlled trials with inert saline placebos conducted by an independent third party;
• safety and efficacy studies for two years prior to any application; monitor the treatment and control group for the rest of their lives to record non-specific effects;
• must provide sterilizing immunity with greater than 90% efficacy and less than 0.1% Grade 3 Adverse Events; and
• proper monitoring for carcinogenesis, mutagenesis, and impairment of fertility.
III. The FDA has opened the formal comment portal for the “Future Framework”
If you prefer the official route, you can lodge a formal comment with the FDA by following the instructions (here). Enter docket number FDA-2022-N-0905 at https://www.regulations.gov by June 22 to tell the FDA what you think of their proposed plan to abandon clinical trials for Covid-19 shots in perpetuity.
The Biden administration today said it made available 10 million doses of COVID-19 vaccines for children under age 5 to states and healthcare workers with “millions more available in the coming weeks.”
The White House unveiled its “Operational Plan” for vaccinating the youngest age group — one week before advisors to the U.S. Food and Drug Administration (FDA) are scheduled to meet to decide whether to grant Emergency Use Authorization for the Pfizer-BioNTech and Moderna pediatric vaccines for babies as young as 6 months old.
According to the White House:
“If FDA authorizes and [Centers for Disease Control and Prevention (CDC)] recommends one or both of the COVID-19 vaccines for this age group, it would be a historic milestone in the nation’s fight against the virus — and would mean nearly every American is eligible for the protection that vaccination provides.”
Children under 5 could begin receiving the vaccines as early as “the week of June 20th — with the program ramping up over time as more doses are delivered and more appointments become available,” the White House said.
Senior administration officials told The New York Times orders for the vaccines from states “have been somewhat tepid so far.”
Of the 5 million doses offered last week — prior to today’s announcement — 58% of the available Pfizer vaccines were ordered, and “roughly a third” of the available Moderna vaccines had been ordered.
The vaccines, paid for by the U.S. government, are being made available to pediatricians’ offices, community health centers, rural health clinics, children’s hospitals, public health clinics, local pharmacies and other community-based organizations.
The administration said it “will remain laser-focused on equity and making sure that we reach those hardest-hit and most at-risk communities.”
The plan includes working with programs such as Head Start and the Women, Infants, and Children, or WIC, Program in addition to Medicaid, the Children’s Health Insurance Program, known as CHIP, and Latino, Black and Native American community programs.
The White House also will focus on parents, especially moms:
“‘What to Expect,’ a platform of over 20 million moms, will author a blog series featuring doctors and other trusted experts answering questions about pediatric COVID-19 vaccines, and how moms, expecting moms, and all parents can get the information they need to get themselves and their children vaccinated; author new articles dispelling myths about the COVID-19 vaccine and children; and create and amplify new What to Expect social media content, reaching moms where they are and fighting vaccine misinformation across all platforms.”
Critics question need, raise safety, efficacy concerns
Many experts have questioned the need to vaccine young children in part because the virus poses little-to-no serious risk to them and in part because, according to the CDC, the majority of children have already had, and recovered from the virus.
Dr. Marty Makary last week told Fox News the COVID-19 vaccines do “not make sense” for most kids.
Makary, a physician and public health researcher at Johns Hopkins Bloomberg School of Public Health, said:
“If you look at the fact that 75% of kids had COVID as of a CDC study back in February and Omicron has been ubiquitous since then, 80 to 90 plus percent of kids have already had COVID. So we’re talking about immunizing those who are already immune for a lot of people. That just does not make sense.
Others, including Dr. Michelle Perro, a pediatrician, have warned about the risks associated with the vaccine, and evidence the vaccines provide weak protection, especially as they were designed for the original Wuhan strain which has been supplanted by a wave of new strains.
In a letter submitted Wednesday to the FDA, 18 members of Congress addressed a number of concerns about the vaccines.
They asked the agency to, “Please list the medical emergencies of children 0 to 4 years old that enables the FDA to approve the COVID vaccine for children using its EUA.”
In all, the Congress members demanded answers to 19 questions and requested a response before next week’s meeting.
Commenting on today’s announcement by the White House and on its timing — a week before FDA scientists meet to review data on the vaccines — Children’s Health Defense (CHD) Chairman and Chief Legal Counsel Robert F. Kennedy, Jr. called on parents and physicians “now more than ever” to “step into the breach to protect our babies from our government.”
Kennedy said the COVID-19 countermeasures, including the vaccines, were “never about science or public health.”
He added:
“Now they have departed from common sense and into naked cruelty and barbarism. By recommending an unapproved, experimental, zero-liability and high-risk medical intervention for an illness that poses zero statistical danger to that age group, the White House has made itself the enemy of America’s children.
“The Pharma gods have demanded child sacrifice and the high priests of public health have offered a generation of infants. Now more than ever, parents and physicians must step into the breach to protect our babies from our government.”
Kennedy and CHD in February delivered a letter to top public health officials and the FDA’s Vaccines and Related Biological Products Advisory Committee urging them to reject Pfizer’s application for EUA of its COVID vaccine for children 6 months through 4 years of age.
According to the letter:
“We are writing to put you on notice that should you recommend this pediatric EUA vaccine to children under five years old, CHD is poised to take legal action against you.
“CHD will seek to hold you accountable for recklessly endangering this population with a product that has little, no, or even negative net efficacy but which may put them, without warning, at risk of many adverse health consequences, including heart damage, stroke and other thrombotic events and reproductive harms.”
The FDA was originally scheduled to meet Feb. 15 to review Pfizer’s EUA application for COVID-19 vaccines for children 6 months to 5 years old, but postponed the meeting citing insufficient data. Pfizer resubmitted its application June 1.
Moderna submitted its application for the vaccine for children 6 months to age 6 on April 28, after changing its efficacy claims to meet FDA guidelines.
The World Health Organization (WHO), and the growing pandemic preparedness industry sponsoring it, has faced considerable challenges in maintaining support for its COVID-19 response. It has addressed this difficult situation with simple and uniform messaging. The compliance thus achieved by the WHO has been vital to achieving a successful concentration of wealth, benefitting not just its major sponsors, but also the army of global health staff who have remained obedient throughout.
Threatening this progress, a skeptical minority within the public sphere have been using evidence and rational argument to undermine the pandemic industry’s potential. As the pandemic preparedness and response narrative is poorly defensible on rational criteria, such criticism and opposition must be dealt with and dismissed by other means. This is being achieved through the creation of a dogma around mass COVID-19 vaccination sufficiently separated from reality as to render the normal processes of debate irrelevant. If the gap between pandemic messaging and reality can be kept sufficiently wide, few passengers can step off, and this lucrative gravy train becomes unstoppable.
Small lies can be argued against, big lies become matters of faith
The development and mass deployment of vaccines has been a key component of the COVID-19 response, underpinning much of the transfer of wealth from lower-income people and countries to large Pharma, their investors and the global health workforce they sponsor. Against a background of rapidly increasing global poverty, this unprecedented increase in wealth has in turn raised the potential for unprecedented funding to global health institutions – the mostly Western-based industry that fills offices and drains aid budgets in Europe and North America. A significant cognitive decoupling has been necessary across this sector to achieve sufficient uniformity of voice and purpose, as the institutions involved were ostensibly intended to improve the health and uphold the rights of those less financially fortunate. To achieve success, staff of the WHO and other international organizations therefore had to be enabled to signal virtuous intent while acting in concert for corporate gain.
Vaccines traditionally protect the vaccinated against a target pathogen and humans tend to develop good immunity after respiratory virus infections. These two realities create an urgent problem for the pandemic preparedness industry, as the increased financing set to expand their reach is dependent on successfully convincing the world that these truths are indeed fallacies. Thus, to sell COVAX, the WHO’s financing facility for mass COVID-19 vaccination and the model for future pandemic responses, it was vital for the WHO to ensure that the obvious nonsensical nature of the programme would be ignored. This required coordination and adherence to a single simple message, repeated incessantly to stifle external opinion; a slogan so ridiculous that it becomes inarguable. In other words, it required propaganda.
It is essential to focus people on simplistic slogans if the aim is to suppress their tendency for independent thought and to make any venture in that direction a cause of stress. If people can see their respected authority figures standing behind a statement that is otherwise obviously false, it becomes easier to accept that the false must be true than to stand alone against authority and the crowd. Once one’s colleagues are on-board, the Asch conformity phenomenon kicks in – if everyone else is saying ‘X’, then it surely must be ‘X’, even if it looks like ‘Y’. If a health programme flies in the face of all existing medical knowledge, it must therefore be supported by a sufficiently strong dogma to negate evidence-based arguments. It is a testament to the power of group-think, loyalty to sponsors and the allure of money that this has, thus far, been brilliantly achieved.
COVAX – Selling the golden goose
“No one is safe, until everyone is safe”, the WHO’s COVAX motto, fulfills all the above criteria.
Most people want to be safe – and to achieve industry aims, the public must be convinced that others, not just themselves, are the key to their personal safety. They must support the blame or coercion being applied to these others. But the brilliance of ‘No one is safe, until everyone is safe’ is not just in its appeal to self-preservation and its divisiveness, but in its simple stupidity.
1) For the slogan to be true, the vaccine must be transmission-blocking only. It must not protect the vaccinated individual. Otherwise, their safety will not be dependent on the vaccination of others. However, the WHO and its partners also claim that “COVID-19 vaccines provide strong protection against serious illness, hospitalization and death”. Therefore, in promoting its ‘No one is safe’ slogan, WHO staff must collectively proclaim a falsehood. This builds loyalty and cohesion, as a lie is more easily maintained within a like-minded group.
2) To be ‘safe’ from a virus, one must either be intrinsically at very low risk (as most people are to most viruses) or gain immunity.
‘Intrinsic low risk’ created a huge problem for the mass-vaccination narrative early in the COVID-19 outbreak, as data from China showed the very strong skew of severe COVID-19 towards old age, and association with certain comorbidities. Most people are clearly at minimal risk. This had to be suppressed to enable mass-vaccination – all must consider themselves at risk. Public health agencies and their corporate backers even proclaimed impending catastrophe for the people of sub-Saharan Africa, more than half of whom are under 20 years of age. The use of age-based disease metrics, standard for disease-burden assessments up to 2019, were put aside and ‘COVID-19’ mortality reported as raw mortality numbers only.
Immunity presents a problem, as it is both the pathway through which vaccines work, and the way we naturally gain protection. Immunity makes us safe, but natural immunity is useless to investors. While a safe vaccine would be preferable to a dangerous virus, once infection has occurred the gain from vaccination is minimal. This poses an immediate threat to profits and share price. The response to this dilemma included one of history’s more ludicrous statements from a global institution, when the WHO modified its herd immunity definition to only recognize immunity resulting from pharmaceutical intervention. This is nonsense to anyone with even a rudimentary understanding of immunology, and of course the WHO’s staff have at least rudimentary knowledge.
Inevitably, SARS-CoV-2 has continued spreading, including from the vaccinated. Based on serology from Africa,India and the USA, and the highly transmissible Omicron variant, we can now be confident that nearly all the world’s population have post-infection immunity. It is no biological surprise that immunity gained from a respiratory tract infection with whole virus reduces disease severity more effectively than injection with spike-protein or its mRNA precursors. Claiming that mass vaccination still has public health relevance in these populations requires both abandonment of logic, and a willingness to dispense with decades of prior scientific learning. It requires acceptance of dogma.
A final component of the COVAX strategy, to lock-in celebrity support and enable those promoting the vaccine to still feel virtuous, is ‘vaccine equity’. People in rich countries are having boosters whilst many of the ‘global poor’ still await their first doses. The lack of benefit to be obtained from these doses, and the requirement of coercion to attain high coverage, are irrelevant – inequity in vaccine distribution simply has to be ‘bad’. Whilst pushing more boosters on high income markets, the same Pharma companies can look good by demanding vaccine equity, advocating for the ‘disadvantaged’. In reality this diverts resources from areas of greater need, thereby killing more children, but such fine print will never make the front pages. Commodity equity expands markets and provides returns, while health equity does not. Fear of being vilified as anti-equity helps keep skeptics quiet.
Bolting down the golden goose
Science, including public health, were previously held to be based on processes of logic, based on an acceptance that aspects of our world are grounded in discoverable truth. This concept is a threat to COVAX and the wider pandemic preparedness narrative. It is a threat to the return on investment of the pandemic industry’s sponsors. Greed is a stronger driver than truth, and it must be allowed to run free if society is to be truly reset in favor of those who wish to concentrate and control its wealth.
Despite its massive internal contradictions, disproportionate cost, coercion, and requirement for its promoters to live obvious lies, COVAX and the entire mass-vaccination paradigm has created a strong model for the success of the wider pandemic preparedness project. If truth in public health can be so readily dispensed with, and those working in the field so willingly corralled, the potential for milking the public’s trust and desire for safety presents unprecedented potential for profit. As this wealth accumulates, it supports the continuing advocacy and manipulation required to keep its adherents loyal. This creates a self-perpetuating cycle – we can expect to see more outbreaks, health emergencies and pandemics declared, more vaccines rolled out, and more wealth concentrated as a result. An unstoppable cycle burying truth under a growing fog of fear and falsehood.
That, at least, is the plan. The eventual outcome will depend on whether truth, human rights, equality and trust were ever fundamental to maintaining societal cohesion and peace. If they were, then let us hope the chaos that follows their abandonment is somehow contained. For now, business is business, and the golden goose, bolted down in a hall of lies, will keep on laying.
Members of Congress today demanded answers from Dr. Robert M. Califf, commissioner of the U.S. Food and Drug Administration (FDA), as the agency reviews Emergency Use Authorization (EUA) for COVID-19 shots in children age 5 and under.
The FDA’s Vaccines and Related Biological Products Advisory Committee (VRBPAC) is meeting on four separate occasions in June to discuss additional EUAs that would provide cradle-to-grave COVID-19 shots — and to consider a “Future Framework” that will permanently lower the bar for safety and efficacy, according to Toby Rogers, Ph.D.
A letter signed by Sen. Ted Cruz (R-Texas), Rep. Bill Posey (R-Fla.) and 16 other members of Congress today asked Commissioner Califf 19 questions about the safety of COVID-19 vaccines for young children.
The questions focused on the youngest children (6 months to 5 years) due to the Congress members’ concerns about what they called the FDA’s “one-size-fits-all” approach to the vaccines.
“The data show that the risks of serious adverse outcomes for COVID for children five and under is very low and as such the standard for evaluating EUA interventions must be very high,” the letter states.
“We believe it is prudent and necessary that the FDA provide answers to a number of questions before approving EUA vaccines for children under age 5, including more than 70% of whom are already seropositive for COVID-19.”
The VRBPAC meetings began Tuesday. The meeting schedule is:
June 7 — EUA for Novavax’s COVID-19 shot for adults.
June 14 — Amendment to Moderna’s EUA to include primary series to children and adolescents 6 through 17 years of age.
June 15 — Amendment to Moderna’s EUA to include primary series for children 6 months to 5 years and amendment to Pfizer’s EUA to include the primary series to children 6 months through 4 years of age.
June 28 — Proposed “Future Framework” for COVID-19 shots.
The Congress members’ letter presses the FDA to address unanswered questions regarding the risks and benefits of administering COVID-19 vaccines to children.
They ask the FDA to explain, among many other things:
What the cardiac risk factor is for children who receive EUA COVID-19 vaccines.
When the FDA and the Centers for Disease Control and Prevention (CDC) will provide the public with more details on children’s serious adverse outcomes from COVID-19 infections.
If it is possible that administering the vaccines in young children could predispose them to increased risk from future novel COVID-19 variants.
How many children ages 5 and under with and without pre-existing medical conditions have died from COVID-19 or its variants.
Finally, the letter asks Commissioner Califf to “please list the medical emergencies [among] children 0 to 4 years old that enables the FDA to approve the COVID vaccine for children using its EUA.”
Children’s Health Defense calls for action
Mary Holland, Children’s Health Defense (CHD) president and general counsel, called the FDA’s Future Framework proposal “quite possibly the worst idea in the history of public health.”
Children under 18 with no comorbidities have virtually no risk of death from COVID-19, according to a November 2021 study published in Nature.
A July 2021 preprint paper found children have a 99.995% recovery rate, and the vast majority of children have minimal symptoms.
The Naturestudy described how children between 3 and 11 years of age mount effective, robust and sustained immune responses to COVID-19.
The CDC’s own data show that at least 75.2% of children ages 0 to 11 and 74.2% of adolescents ages 12 to 17 already have superior natural immunity.
There is no clinically significant health benefit from the mRNA vaccines, according to Moderna. Reporting on its Phase 2/3 KidCOVE study, the company said, “the absence of any severe disease, hospitalization or death in the study precludes the assessment of vaccine efficacy against these endpoints.”
Preliminary data showed the shots were only about 44% effective at preventing symptomatic infection in children 6 months to 2 years old, and 37% effective in children ages 2 to 5 — both below the 50% level that regulators generally called the minimum level for EUA approval in 2020.
In New York, officials observed that Pfizer’s efficacy against Omicron plummeted from 68% to 12% after 7 weeks in children ages 5 to 11.
“These shots are dangerous and carry very real risks,” Holland said.
Studies show vaccinated children face a substantial risk of myocarditis. Moderna’s EUA application, originally filed in June 2021, has already been held up because of a clear safety signal for myocarditis, which prompted a number of European countries to prohibit its use in young people.
Additionally, the Vaccine Adverse Events Reporting System or VAERS has more than 48,500 reports of adverse events in children, including 112 deaths (as of May 27), and a growing number of reports of encephalopathies, clotting issues, diabetes and neurological problems in children following COVID-19 shots.
NEW YORK — For nearly two decades, one of the most overlooked and little known arrests made in the aftermath of the September 11 attacks was that of the so-called “High Fivers,” or the “Dancing Israelis.” However, new information released by the FBI on May 7 has brought fresh scrutiny to the possibility that the “Dancing Israelis,” at least two of whom were known Mossad operatives, had prior knowledge of the attacks on the World Trade Center. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.