Covid vaccines more likely to put you in hospital than keep you out: BMJ editor’s analysis of Pfizer and Moderna trial data
BY WILL JONES | THE DAILY SCEPTIC | JUNE 22, 2022
A new paper by BMJ Editor Dr. Peter Doshi and colleagues has analysed data from the Pfizer and Moderna Covid vaccine trials and found that the vaccines are more likely to put you in hospital with a serious adverse event than keep you out by protecting you from Covid.
The pre-print (not yet peer-reviewed) focuses on serious adverse events highlighted in a WHO-endorsed “priority list of potential adverse events relevant to COVID-19 vaccines”. The authors evaluated these serious adverse events of special interest as they were observed in “phase III randomised trials of mRNA COVID-19 vaccines”.
A serious adverse event was defined as per the trial protocols as an adverse event that results in any of the following conditions:
- death;
- life-threatening at the time of the event;
- inpatient hospitalisation or prolongation of existing hospitalisation;
- persistent or significant disability/incapacity;
- a congenital anomaly/birth defect;
- medically important event, based on medical judgement.
Dr. Doshi and colleagues found that the Pfizer and Moderna mRNA COVID-19 vaccines were associated with an increased risk of serious adverse events of special interest of 10.1 events per 10,000 vaccinated for Pfizer and 15.1 per 10,000 for Moderna (95% CI -0.4 to 20.6 and -3.6 to 33.8, respectively). When combined, the mRNA vaccines were associated with a risk increase of serious adverse events of special interest of 12.5 per 10,000 vaccinated (95% CI 2.1 to 22.9).
The authors note that this level of increased risk post-vaccine is greater than the risk reduction for COVID-19 hospitalisation in both Pfizer and Moderna trials, which was 2.3 per 10,000 participants for Pfizer and 6.4 per 10,000 for Moderna. This indicates that the Pfizer vaccine results in a net increase in serious adverse events of 7.8 per 10,000 vaccinated and the Moderna vaccine of 8.7 per 10,000 vaccinated.
Addressing the difference between their findings and those of the FDA when it approved the vaccines, the authors note that the FDA’s analysis of serious adverse events “included thousands of additional participants with very little follow-up, of which the large majority had only received one dose”. The FDA also counted people affected rather than individual events, despite there being twice as many individuals in the vaccine group than the placebo group who experienced multiple serious adverse events.
The authors wonder where the U.S. Government’s own studies of adverse events are. They note that in July 2021 the FDA reported detecting four potential adverse events of interest following Pfizer vaccination – pulmonary embolism, acute myocardial infarction, immune thrombocytopenia and disseminated intravascular coagulation – and stated it would further investigate the findings. However, no update has yet appeared.
They also note that “while CDC published a protocol in early 2021 for using proportional reporting ratios for signal detection in the VAERS database, the agency has not yet reported such a study”.
Their results are compatible, they point out, with a recent pre-print analysis of COVID-19 vaccine trials by Benn et al., which found “no evidence of a reduction in overall mortality in the mRNA vaccine trials”, with 31 deaths in the vaccine arms versus 30 deaths in the placebo arms (3% increase; 95% CI 0.63 to 1.71).
Noting that their study is limited by the fact that the raw data from COVID-19 vaccine clinical trials are not publicly available, they stress that “given the global public health implications, there is an urgency to make all COVID-19 trial data public, particularly regarding serious adverse events, without any further delay”.
They conclude that there is a need for formal harm-benefit analyses for Covid vaccines, taking into account the different levels of risk of serious Covid and adverse events that exist between demographic groups. Ideally, this would be based on individual participant data, they add, though such data remain frustratingly unavailable.
Biden predicts ‘second pandemic’

Samizdat – June 22, 2022
The US needs more money to plan for “the second pandemic,” President Joe Biden said during a press briefing on Tuesday, as he praised his government’s efforts to ensure children under five can get Covid-19 vaccines.
Biden also hailed as “a very historic milestone” that the US has become the first country in the world to offer “safe and effective” Covid-19 vaccines for children as young as six months old.
When asked about how long the administration could keep up the new vaccine campaign, Biden suggested that the current budget would be enough to “get through at least this year” but stressed that “we do need more money.”
He went on to insist that he needed even more money for an unspecified “second pandemic.” “We need more money to plan for the second pandemic. There’s going to be another pandemic,” the president warned, without going into detail about what this new wave might entail.
Biden also took the opportunity to take a swipe at his predecessor, implying that Donald Trump’s lack of preparation increased the impact of the Covid pandemic. “We have to think ahead. That’s not something the last outfit did very well and that’s something we’ve been doing fairly well. That’s why we need the money,” surmised Biden.
Some health experts and agencies such as the World Health Organization have also warned of the likelihood of future pandemics. The WHO had previously announced that it plans to confirm a global pandemic treaty at the 2024 World Health Assembly, which it hopes will help “set out the objectives and fundamental principles in order to structure the necessary collective action to fight pandemics.”
The agreement, which heavily focuses on increased surveillance, vaccinations and “restoring trust in the international health system,” would legally bind its members under international law, superseding regulations of individual countries in an effort to get all nations to act as one in the face of a future outbreak.
If you don’t want to have a Covid vaccine, get a job enforcing vaccine mandates.
The Naked Emperor’s Newsletter | June 21, 2022
Last week the Centers for Medicare & Medicaid Services (CMS) quietly sent round a memo exempting officials from vaccine mandates. Why is this so hypocritical? Well, because the officials they were exempting from the vaccine mandate were officials hired to enforce the very same vaccine mandate.
So it seems the easiest way to get around the vaccine mandate is to get a job enforcing the vaccine mandate.
I’ve probably said vaccine mandate a few too many times now, so here is the memo itself.

The Biden administration first announced the mandates back in August 2021, stating that healthcare and nursing home staff must be COVID-19 vaccinated or lose funding. After legal challenges, different deadlines were imposed with the final deadline occurring on 21 March 2022.
Vaccine mandate deadlines encouraged/forced (take your pick) employees to get vaccinated with uptake rising from 63% to 88% in a number of months. Doctors, nurses and staff who still decided that vaccination was not for them, lost their jobs.
In February, the CMS warned state survey agencies that they must enforce all federal health and safety requirements or lose federal financial support. Although it didn’t explicitly say so, this was widely recognised as a warning to Florida and other states that had said they would not enforce vaccine mandates. Furthermore, the CMS said they would bring in outside surveyors if states did not comply with their directives.
CMS surveyors were given the role of evaluating whether healthcare workers were complying with federal vaccine mandates. They stated that staff vaccination under 100% would constitute non-compliance. However, the extremely reasonable CMS (sarcasm) said that any facility with over 80% of its staff vaccinated would be given 60 days to reach 100% without further action being taken.
Brian Harrison, state representative of Texas and former chief of staff for the Department of Health and Human Services under the Trump administration, said in an interview with Newsmax “This shows that the Biden administration is truly authoritarian and these mandates never had anything to do with public health in the first place, but sadly and tragically, they had much more to do with giving the federal government more control over our lives. These mandates must end.”
Harrison thinks that after the CMS enforced the mandates on its own surveyors, they were unable to live under the same rules. “They couldn’t take it. So instead of taking down the mandate, which would have been the normal common sense solution, they just exempted their own government contractors instead of all the Americans.”
Rules for thee, not for me.
Trudeau wasted over $100 million on expired vaccines
The Counter Signal | June 21, 2022
The 13.6 million expired AstraZeneca vaccines that Trudeau donated to foreign countries is estimated to have cost Canadian taxpayers over $100 million.
As per a report from the National Post, “According to a document tabled in the House of Commons last week, the government disposed of roughly 1.2 million doses of Moderna vaccines that expired either in mid-March or mid-April this year.”
“But that wastage is just a drop in the bucket compared to the nearly 13.6 million doses of AstraZeneca vaccines that the government donated to other countries last year and that sat in the manufacturer’s warehouses until they expired, according to new data provided to the National Post by Health Canada.”
According to the Financial Times, doses of AstraZeneca were priced at roughly $3 to $4 per dose when mass-produced, and governments secured orders of the COVID vaccine.
But this is inaccurate in the case of Canada. Trudeau managed to bungle the deal and secured 20 million doses at more than double that price.
“The only cost per dose revealed so far was released by accident when the price for the AstraZeneca-Oxford vaccine was accidentally left in an email included in a package of documents released to the health committee. That email said Canada would pay $8.18 per dose of AstraZeneca, which would amount to $163 million for the 20 million doses ordered,” the CBC reported in June 2021, just a month before Trudeau announced he’d be donating most AstraZeneca vaccines to foreign countries.
At $8.18 per dose of AstraZeneca, that means that the Trudeau government is estimated to have spent a whopping $111,248,000 on vaccines that were never needed or even wanted, as COVAX was flooded by other countries similarly pawning off their unwanted AstraZeneca vaccines after it was found to cause blood clots.
Indeed, the original agreement was to send even more AstraZeneca vaccines to COVAX that would expire — a total of 17.7 million.
And that’s just for AstraZeneca. Both the Moderna and Pfizer vaccines — for which Canada paid a premium — were even more expensive, and many of these are also either already expired or will expire soon.
However, even this is just the tip of the iceberg regarding how much Trudeau sent to COVAX.
In July 2021, the Trudeau government donated an additional $10 million to COVAX, which was on top of a $440 million in prior donations.
Overall, had the PM had better foresight or financial planning, hundreds of millions of dollars could have been saved throughout the pandemic.
Canada threatens to bring back vaccine passports

By Ken Macon | Reclaim The Net | June 21, 2022
Canada may not have seen the last of the mandatory COVID-19 vaccine passports. Proposed restrictions could even be harsher than before, likely to require three to four inoculations in order to travel.
It’s worth noting that the mandate is not set in stone, but the government is preparing for the possibility of introducing the measures in the Fall. Health Minister Jean-Yves Duclos made the announcement during a press conference. The vaccine passport mandate for federal employees and other travelers might be over for now, but Duclos made it clear that it’s likely to return this fall.
In addition to officially denouncing passport mandates, Duclos took the opportunity to explain some changes in wording regarding vaccine requirements. Canada will no longer refer to people who have had all of their vaccinations as “fully vaccinated.” Instead, the language in any official documents will read “up-to-date.” This is because the government says three doses are no longer enough for many people, with some people being told to get four or even five doses.
These changes came after Dr. Theresa Tam, the chief public health officer, told reporters that several studies had just been completed.
Initially, according to the report, two doses of a vaccine would allegedly give a person 50 to 80 percent protection; however, that number falls to just 20 percent against Omicron and newer variations of the coronavirus.
Canada’s goal is now to convince people to get their third and fourth doses and restricting civil liberties has been a controversial way of forcing that over the last couple of years. Over 90 percent of Canadian adults have two doses, but less than 60% have received their booster.
The Conservative Party of Quebec has already started fighting back against the possibility of a third dose being required for a vaccine passport. For them, it’s a personal choice that shouldn’t be mandated. Many in Canada are ready to put the last few years behind them.
The Covid vaccine paper on declining sperm counts is even worse than it seems at first
By Alex Berenson | Unreported Truths | June 20, 2022
On Friday, the journal Andrology published a peer-reviewed paper showing large decreases in sperm counts among men after the second dose of Pfizer’s mRNA Covid jab.
Based on counts from men who donated sperm to three fertility clinics in Israel, this finding is devastating – medically and politically.
It cuts to the heart of the hottest button question of all about the mRNA shots, whether they have hidden fertility risks. That issue has simmered since early 2021, following my reporting that data showed the shots had caused excess miscarriages in rats – and other reports showing that measurable amounts of vaccine reached the ovaries and testes in tests in rats.
Ever since, media “fact-checkers” and public health authorities have dismissed and mocked the concerns and anyone who raises them:
—
Now – after a half-billion men have received mRNA shots – the skeptics appear to be right. Again. The Israeli paper offers hard evidence that the vaccines may present a systemic risk to men’s sperm counts. What was a conspiracy theory is now just a theory. AGAIN.
The paper raises questions about mechanism of action that must be answered immediately. And on top of the myocarditis risk, the finding is more evidence that encouraging – much less forcing – men under 40 to take the mRNA vaccines was a catastrophic mistake.
—
However, the authors qualified their findings by reporting that after five months, sperm levels recovered. Thus the decreases were only temporary, they wrote.
Put aside the fact that a five-month decrease hardly qualifies as temporary for someone trying to start a family – or compared to a “vaccine” that loses effectiveness against Omicron within weeks or months.
As other writers have pointed out, the actual data in the paper do not really support the argument that sperm levels returned to normal after five months. In fact, by some measures, levels continued to decline.
Rather than acknowledging this fact, the authors offered the best possible spin on their data, while at the same time publishing the figures themselves near the end of the paper so that other researchers could see the reality for themselves.
This tactic is now commonplace among researchers putting out data that might raise concerns about the mRNA shots. It is likely a response to the overwhelming political pressure to hide the deepening crisis around the safety and efficacy of shots that governments have given to over a billion people worldwide.
Below is the crucial chart, which shows that “total motile count” – the number of sperm in the ejaculated semen – plunged 22 percent three to five months after the second shot (T2) and barely recovered during the final count (T3), when it was still 19 percent below the pre-shot level.
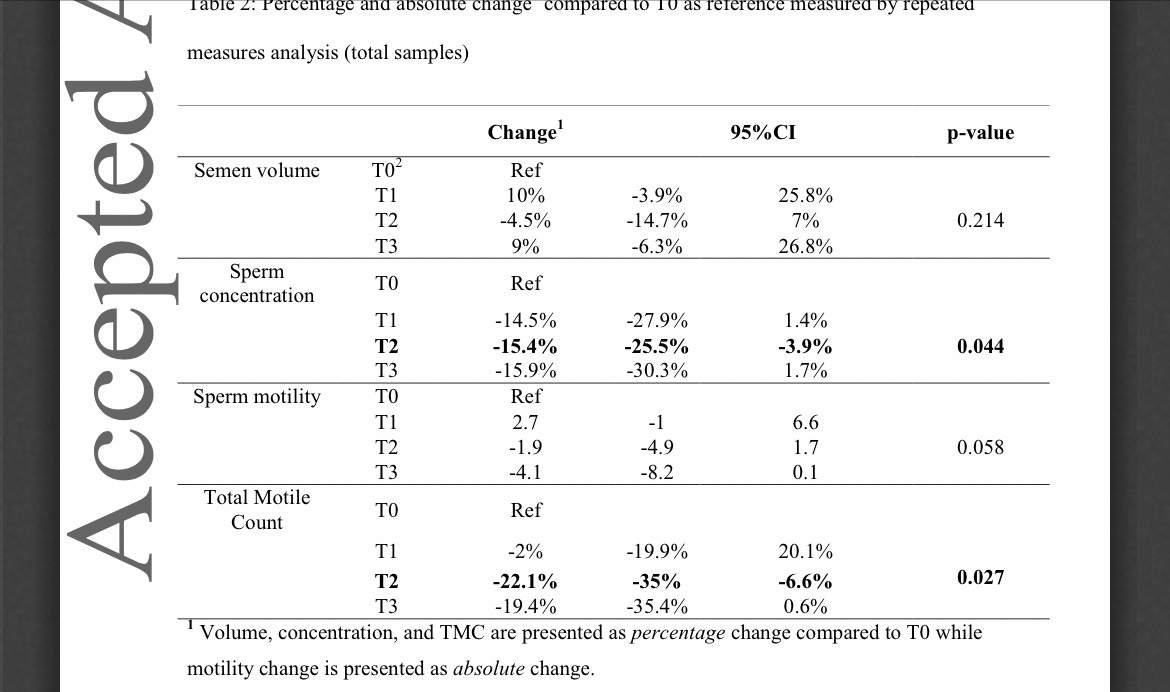
SOURCE
Even more importantly, the fall in sperm counts CANNOT be blamed on short- or even medium-term inflammation as mRNA-generated spike proteins causes our immune cells to ramp up the systemic production of anti-spike antibodies. If that were the case, one would expect to see a short term decrease in sperm count that reverses over time. Instead, total sperm counts are unaffected shortly after the mRNA shots, then decrease months later and hardly recover.
To play down this unpleasant reality, the researchers instead focused on the fact that median rather than average counts did recover after five months. (The median is the numerical midpoint of a series; If a series goes 1, 2, 3, 4, 20, the median will be 3, but the average will be 30 divided by 5, or 6.)
Both the median and the average can be valuable statistics. Using the median rather than the average will hide extreme outliers. In this case, the fact that the average fell much more than the median is a sign that some of the men probably had near-zero sperm counts in both the second and third time periods – and that fact is arguably more important than the median change.
All of which is to say that this data cannot be easily explained away and should not be ignored, as badly as the media would like to do so. The fall in sperm counts is part of an emerging and increasingly dark picture about the long-term health impacts of the mRNA shots – and should all by itself convince parents not to risk exposing their children to these powerful biotechnologies.
Punishing Dissident Physicians
CA Assembly Bill 2098 would muzzle physicians and severely punish those who challenge covid public health measures
By Aaron Kheriaty, MD | Human Flourishing | June 21, 2022
I will be heading to Sacramento next Monday to testify at a Senate committee hearing on California Assembly Bill 2098. The bill, sponsored by Senator Pan—who has been in Pharma’s back pocket for years and the source of much legislative health policy mischief in my home state—would give the medical board the authority to punish any physicians who challenge the safety and efficacy of covid vaccines. This bill is advanced even as evidence continues to emerge of safety problems with the mRNA shots, including a study this week showing the vaccines lower sperm counts in men:

But this proposed measure seeks to enshrine in law “scientific” conclusions which are highly dubious:

All three of these statements are demonstrably false: (a) The death count figures cited are grossly overestimated by hospitals failing to distinguish dying from covid vs. dying with covid and the financial incentives from the Centers for Medicare and Medicaid Services (CMS) to overestimate covid deaths; (b) the efficacy of vaccines has declined with time and new variants, so the statistic cited here is no longer true of the vaccines against omicron; (c) the CDC has consistently failed to follow-up on serious safety signals, apart from myocarditis, and the post-marketing surveillance data acquired from our FOIA request showed serious safety issues in the first three months of vaccine rollout.
If this bill passes, any physician who raises these or other inconvenient scientific facts or study findings could be disciplined by the medical board, as the text of the bill explains:
It shall constitute unprofessional conduct for a physician and surgeon to disseminate misinformation or disinformation related to COVID-19, including false or misleading information regarding the nature and risks of the virus, its prevention and treatment; and the development, safety, and effectiveness of COVID-19 vaccines.
The supposed scientific “facts” mentioned in the bill make it clear just what information will be considered “misinformation” under this law. This bill will spell the end of scientific integrity and medical freedom in California. I worry that if it passes, other states could follow suit. As I have said before, California is the tip of the spear:
Here is the text of a letter I submitted last week to the committee where the bill is currently being reviewed:
13 June 2022
To: California Legislators and Committee Members
RE: AB 2098: Physicians and Surgeons: Unprofessional Conduct – OPPOSE
As a licensed physician in California I strongly oppose the proposed California bill AB 2098 and urge you to vote no and oppose as well.
Advances in science and medicine typically occur when doctors and scientists challenge conventional thinking or settled opinion. This is the very nature of scientific progress. Fixating any current medical consensus as “unchallengeable” by physicians will stifle medical and scientific advances and give undue authority to a few gatekeepers who act as guardians of the consensus. As I testified in January at a U.S. Senate panel on Covid policy: “The scientific method suffered [during the pandemic] from a repressive academic and social climate of censorship and silencing of competing perspectives. This projected the false appearance of a scientific consensus—a ‘consensus’ often strongly influenced by economic and political interests.”
One need only look at the last two years to see how frequently public health recommendations and consensus thinking about Covid changed from one month to the next with the advent of new information. It was frontline ICU physicians who discovered and spoke out about bad outcomes when patients were prematurely placed on ventilators. This shifted the consensus in the direction of avoiding ventilation as much as possible. Likewise, it was frontline physicians who discovered that placing covid patients face-down in the prone position while they were ventilated could improve outcomes, challenging another consensus. Both of these advances came by way of challenging the way things were currently being done. Other physicians challenged the early consensus, which did not recommend the use of steroids to treat Covid. Eventually, this dissenting opinion gained ground and now represents conventional thinking: corticosteroids for critically ill covid patients are now standard care. Many other examples regarding guidelines on masks, social distancing, and other Covid policies could be cited here.
Allowing the free interchange among competing perspectives is absolutely necessary for scientific and medical progress. Good science is characterized by conjecture and refutation, lively deliberation, often fierce debate, and always openness to new data. The censorship of free speech in AB 2098 spells not only the demise of civil liberties and constitutional rights, but the end of the scientific enterprise when it comes to dealing with Covid in CA.
Patients will not trust physicians if they believe their physician has been muzzled by the law and cannot speak his or her mind honestly. Patients want to know that if they ask their physician a question, including a question about Covid, they will get their doctor’s honest opinion—regardless of whether they follow that opinion, seek a second opinion, or whatever. Patients will not trust physicians if they know their doctor is simply parroting a consensus judgment that he may or may not agree with or endorse.
This bill will not help us to deal with Covid more effectively. Doctors will be punished for practicing medicine according to their best judgment. Informed consent, the foundation of good medical ethics, will be seriously compromised, and the trust necessary for the doctor-patient relationship will be shattered. I strongly urge you and your fellow lawmakers must oppose AB 2098. It will harm not only physicians and medical institutions in California, but even more concerningly, it will harm patients.
Sincerely,
Aaron Kheriaty, MD
Here is a link to information from The Unity Project on what you can do to oppose this bill—especially important if you happen to live in California. Please spread the word.
Dr. Clare Craig from the HART group explains the clinical trial used to justify vaccinating kids
Steve Kirsch | June 19, 2022
The HART group is a group of highly respected independent doctors and scientists. My friend, Professor Norman Fenton, is a member of this group.
In this 4 minute video, Dr. Clare Craig, co-chair of the HART group, explains the clinical trial that was used to justify vaccinating our kids. She was appalled.
The only conclusion you can draw after watching this video is that the people running the FDA, CDC and the members of the outside committees approving these vaccines are either completely incompetent or totally bought off.
Everyone should watch this video. It should be required viewing for any parent who is considering vaccinating their child.
Here is the report Pfizer submitted to the FDA referenced in her video. You can see the numbers on page 39 (look in the column headings for the N= numbers).
Wake up, everyone!

By Paul Weston | TCW Defending Freedom | June 21, 2022
AFTER two years of Covid-19 insanity, the West has several new crises to deal with. Rampant inflation, coming food shortages and fuel shortages, monkeypox, a mystifying confusion about XX and XY chromosomes and a strange war in Ukraine which appears to be a proxy war between nuclear armed America and nuclear armed Russia.
I say a strange war because no one seems remotely interested in stopping it, no matter that it could lead to Armageddon. I think this is because Putin can be blamed for some of the deliberately engineered crises we are currently experiencing, so don’t expect it to end soon. Our armchair warrior political class seems more than happy to supply weapons to prolong the inevitable and are valiantly prepared to fight to the last surviving Ukrainian.
I feel as though we no longer exist as human beings in the eyes of our overlords. We are now just cattle being herded toward a dystopian future by a small number of immensely powerful individuals and global organisations who make no secret of the future they wish to build for us. This global coup d’état is driven by lies and corruption at every level of our national and international institutions. Nothing we have been told over the last couple of years is true.
For example, over the last thirty years in England and Wales an average 1.2 per cent of the population died every year, the vast majority of them old and ill. In 2020, the year of the alleged Covid-19 killer pandemic, just 1 per cent of the population died, and again the vast majority were old and ill. Yet despite experiencing a lower-than-average death rate, a Covid-19 emergency was declared which saw the biggest power grab by the state over the lives of its citizens since the dictatorships of Lenin, Hitler and Mao.
The most chilling aspect of this totalitarian takeover is that Western countries acted in unified lockstep as they tore up every tried and trusted historical public health protocol related to airborne viruses and replaced them with a tyranny that had no basis in medical or scientific reality.
People who recognised what was happening publicly protested and were met with state enforced paramilitary brutality never previously seen in the West. In Australia rubber bullets were used against peaceful protesters. In Canada, Justin Trudeau invoked the War Measures Act to beat, jail and pauperise peaceful protesters who preferred to live their lives according to the Nuremberg Code rather than Trudeau’s Mengele Code. In New Zealand huge posters of a beaming Jacinda Ardern were ruthlessly displayed on advertising hoardings across the country.
The biggest issues I can see in all this criminal insanity are two-fold. Firstly, our ruling class now know they can do whatever they want to us if they terrorise us sufficiently, as in carry out acts of genuine terrorism against their own citizens to achieve a political ambition. Secondly, we now know exactly what they want to do to us because they meet up in Davos every year and shamelessly talk about it in very loud voices.
Their power is immense, and for the first time in history they have the ability to build a revolutionary new society without having to carry out violent street revolutions. All they need is electronic data and digital IDs linked to a government-controlled central bank digital currency, which all Western governments are currently implementing. Covid-19, mass vaccinations and digital Covid passes – please don’t think they have been consigned to history – were a necessary pre-condition of course if a Digi-Tyranny could ever become a reality.
Western governments are also working on legislation to both silence dissent on social media and stifle physical public protest. New Ministries of Truth are being formed which will disappear and memory-hole any written and spoken words our ruling class considers to be misinformation or disinformation. This is Orwell’s 1984 and it is happening before our very eyes.
Who are the people/organisations enacting this totalitarian Western coup d’état? Well, it is primarily the World Economic Forum, the United Nations, the World Health Organisation, the World Bank, the International Monetary Fund, the EU, Big Tech social media, the pharmaceutical industry, the entire Western political class and three gargantuan financial institutions called BlackRock, Vanguard and State Street, along with a handful of monumentally wealthy billionaires including Soros and Gates.
The concerted power and wealth held by the above has completely corrupted politics, science, journalism, the judiciary, academia and medicine. There are still some brave souls from those professions who risk their careers by speaking out, but you will never see them via the mainstream media or the biggest social media platforms. Those we are allowed to see are bought and paid for propagandists who tell us nothing other than the revolutionary line.
I am fifty-eight years old now. I was born a long time after World War Two and my entire life – up until 2020 at least – was one of unimaginable ease and freedom compared to most humans who have ever lived. But the freedom I enjoyed is over now. Our future could be very grim indeed. Another pandemic will soon be coming our way and I suspect this one will be necessarily much more lethal than the last.
Also coming our way are ever rising interest rates to counter the deliberately engineered inflation. If these interest rates hit double figures, every average earning mortgage holder will lose their house. The manufacture of petrol and diesel cars will soon be phased out and extortionate taxes will be introduced to keep older ones on the road. Air travel for the masses is not part of the New World Order’s Green Agenda, nor is heating our homes with oil or gas.
They have told us what they want. A smaller population. A lower carbon footprint. A digital ID surveillance/social credit state capable of bending us to their dictatorial will. No more meat, just bugs; lots and lots of delicious bugs. The apparatchiks of the Green New World Order will still have their private jets, their beachside mansions, their haunches of venison and their champagne whilst we will own nothing, which I rather suspect will fail to induce delirious happiness whatever Herr Schwab might purportedly believe.
Can they achieve their publicly oft-stated agenda? Yes, they simply have to continue doing what they are already doing, although it will need to be substantially ramped up, hence my belief another pandemic is on the cards. In America they have the problem of gun ownership in the hands of ordinary citizens, so I think we will see huge efforts – by means more foul than fair – to urgently rectify this problematic issue for the New World Order.
Is it all doom and gloom? Not really. They have shown their hand and despite their seemingly limitless power and wealth there are only a few thousand of them whilst there are billions of us. I see our future as one of only two credible possibilities: freedom for us and jail for them, or slavery for us and even bigger yachts, private jets and sizzling steaks for them. It is up to us in other words. The very first thing the average person needs do is wake up. Before it is too late.
The Latest Tragedy: Sudden Adult Death Syndrome

By Dr. Joseph Mercola | June 20, 2022
In recent weeks, media outlets around the world have started highlighting a medical phenomenon called “sudden adult death syndrome,” or SADS, in what appears to be a clear effort to obscure the reality of COVID jab deaths.
SADS is also short for “sudden arrhythmic death syndrome,”1 which was first identified in 1977. Underlying factors for SADS (both the sudden adult death and sudden arrhythmic versions) include undiagnosed myocarditis, inflammatory conditions and other conditions that cause irregularities in the electrical system of the heart, thereby triggering cardiac arrest.2,3,4 While SADS has been known to occur before, what’s new is the prevalence of this previously rare event.
Historical Prevalence of SADS
According to the British Heart Association, there are about 500 cases of SADS in the U.K. each year.5 The British Office for National Statistics, on the other hand, show far fewer cases.6 The ONS lists a total of 128 cases of SADS (all age groups, whether listed as cardiac-related or unknown) in 2016, 77 cases in 2017, 70 in 2018, 107 in 2019 and 139 cases in 2020.
While data on SADS incidence for 2021 and 2022 are hard to come by, incidence has apparently risen sufficiently enough to cause concern in some countries. Before the pandemic, SADS was the acronym for sudden arrhythmia death syndrome, which was rare and with scant research on it except to mention that it accounted for about 30% of unexpected cardiac deaths among young people.7
But today, it’s no longer rare and SADS is virtually on steroids as the numbers of sudden deaths in young adults pile up around the world. The numbers are so concerning that in Australia, for example, the Melbourne Baker Heart and Diabetes Institute is setting up a new SADS registry “to gain more information” about the phenomenon.8,9
According to a spokesperson, there are approximately 750 SADS cases per year in Australia. In the U.S., the average annual death toll from SADS is said to be around 4,000.10
Since the rollout of the COVID jabs, the news has been chockful of reports of young, healthy and often athletic people dying “for no reason” and doctors claim to be “baffled” by it. Doctors and scientists in Australia are even urging everyone under the age of 40 to get their hearts checked, even if they’re healthy and fit.11
Any thinking person, on the other hand, can clearly see the correlation between the shots, which are now well-known for their ability to cause heart inflammation, and the rise in sudden death among young and healthy people.
Hundreds of Athletes Have Collapsed and Died Post-Jab
Among athletes, sudden death incidence has historically ranged between 1 in 40,000 and 1 in 80,000.12 An analysis13 of deaths among competitive athletes between 1980 and 2006 in the U.S. identified a total of 1,866 cases where an athlete either collapsed from cardiac arrest and/or died suddenly. That’s 1,866 cases occurring over a span of 27 years, giving us an annual average of 69 in the U.S.
Data14 compiled by the International Olympic Committee show 1,101 sudden deaths in athletes under age 35 between 1966 and 2004, giving us an average annual rate of 29 sudden deaths, across all sports. Meanwhile, between March 2021 and March 2022 alone — a single year — at least 769 athletes have suffered cardiac arrest, collapse, and/or have died on the field, worldwide.15
Good Sciencing, which is keeping a running total of athletic deaths post-jab puts the current number of cardiac arrests at 1,090 and total deaths at 715.16 Several dozen more are pending confirmation that the athlete had in fact received the shot.
Among EU FIFA (football/soccer ball) athletes, sudden death increased by 420% in 2021.17 Historically, about five soccer players have died while playing the game each year. Between January and mid-November 2021, 21 FIFA players died from sudden death.
COVID Jab Clearly Associated With Heart Injury
An opinion piece in Frontiers in Sports and Active Living, published in April 2022, highlights the correlation between COVID jab-induced heart inflammation and sudden cardiac death in athletes:18
“Increased COVID-related SCD [sudden cardiac death] appears to be due, at least in part, to a recent history of infection and/or vaccination that induces inflammatory and immune impairment that injures the heart.
An unhealthy lifestyle that may include poor diet or overtraining may likely be a contributing factor. The seeming increased incidence of myocarditis and pericarditis during COVID-19 and in the post-vaccination period, and SCD, poses a serious risk to not only athletes but all others and is a cause for alarm.
As the population ages and the popularity of running, cycling, and other endurance sports increases, the burden of SCD risk can potentially grow as well. A strong focus on both health and fitness should be a loud and clear public health message.”
The Signal That Cannot Be Silenced
In a June 13, 2022, Substack article, Dr. Pierre Kory also commented on this latest effort to explain away COVID jab deaths:19
“I recently posted a deeply referenced compilation20 of evidence detailing the historic humanitarian catastrophe that has slowly unfolded within most advanced health economies across the world. Caused by a global mass vaccination campaign led by the Pharma masters of BMGF/WHO/CDC that illogically (but profitably) targeted a rapidly mutating coronavirus.
They did it with what turned out to be the most toxic protein used therapeutically in the history of medicine. In vials mixed with lipid nano-particles, polyethylene glycol and who knows what else.
I cited studies and reports showing massive increases in cardiovascular deaths and neurologic (and other) disabilities amongst working age adults, beginning in 2021 only.
A disturbing signal screaming from the original clinical trials data,21 VAERS data,22 life insurance data,23 disability data,24 reports of cardiac arrests of professional athletes,25 rises in ambulance calls for cardiac arrests in pre-heart attack age young people,26 and the massive increases in illnesses and data manipulations27 in Department of Defense databases.
As these events become more and more recognized by the average citizen (and occasional journalist), a new pathetic ‘Disinformation Campaign’ was launched in response trying to blame all the young people dying as simply a need for increased awareness of the rare condition called Sudden Adult Death Syndrome (SADS), rather than examples of the legions dying from the vaccines.
The fact checkers also came out in support of this narrative, branding anyone who thinks the vaccines are the cause of SADS as a conspiracy theorist …
What is nauseating is the tone of purported good intention within these articles, informing folks that if you are related to someone young who died suddenly you should go see a cardiologist to make sure you don’t have an abnormal EKG.
After it turns out normal, they will assuredly tell you to get vaccinated, an absurdity atop a mountain of absurdities caused by our bio-medical-media industrial complex over the past 2+ years.”
Diseases ‘Suppressed by COVID’ Make Comebacks
Media are also trying to write off increases of other diseases as something other than COVID jab-related. “Diseases Suppressed During COVID Are Coming Back in New and Peculiar Ways,” CNBC reported June 10, 2022.28
The article goes on to discuss how viruses other than SARS-CoV-2 are now “rearing their heads in new and unusual ways.” Influenza, respiratory syncytial virus (RSV), adenovirus, tuberculosis and monkeypox have all “spiked and exhibited strange behaviors in recent months,” CNBC notes.
No mention is made, however, of the fact that the COVID jab has been linked to vaccine-acquired immunodeficiency (lowered immune function), rendering you more susceptible to infections and chronic diseases of all kinds, including autoimmune diseases.29 MIT research scientist Stephanie Seneff explains the mechanisms for this in “COVID Vaccines and Neurodegenerative Disease.”
The COVID jab has also been shown to activate latent viruses, including hepatitis C,30 cytomegalovirus,31 varicella-zoster32 and herpes viruses.33 Not surprisingly, Moderna is now working on a new vaccine for “latent cytomegalovirus prevention.”34
This is yet another case of a drug company creating a “remedy” against a health problem their own product was responsible for creating in the first place. CNBC, meanwhile, cites “health experts” who attribute lowered immunity to COVID lockdowns, mask wearing and missed childhood vaccinations.35
Amputations of arms, legs, fingers and toes — consequences of post-jab blood clots — are also being written off as something else.36 In this case, media are blaming it on high cholesterol,37 totally ignoring the fact that high cholesterol has been prevalent for decades, and only now are people losing their extremities in shocking numbers.
Spikes in blood clots and strokes, meanwhile, are being blamed on smoking, pregnancy and contraceptives,38 even though blood clots and strokes are among the most common side effects of the COVID jab. Most ridiculous of all, however, is the claim that a “newly-discovered, highly reactive” chemical in the earth’s atmosphere is suspected of triggering heart disease.39
To anyone with half a brain, it’s clear that government authorities and media are doing everything they can to shift blame away from what is the most obvious culprit, namely the COVID shots.
All the diseases and conditions they’re now blaming on everything from cholesterol to mysterious atmospheric chemicals are known side effects of the jab. The elephant in the room is so gigantic, you can’t even get around it anymore. It’s pressing us against the walls.
Nursing Reports From the Frontlines
In his June 13, 2022, Substack article,40 Kory also shares insider information from a senior ICU and ER nurse who suffered blood clotting injuries, spontaneous unstoppable bleeding and cervical lymph node enlargement following her second Pfizer dose.
She filed a report with the Vaccine Adverse Event Reporting System (VAERS), which has since vanished. The batch numbers for the shots she received were associated with bad neurological responses and clotting. She also lost her hematologist-oncologist to vaccine injury.
While only in his early 40s, he’s now too injured to practice. “He was a ‘true believer’ and in denial until it was him who was the injured patient,” she told Kory.
The major cancer hospital where she works now have caseloads “in the thousands,” she says, whereas before the average caseload was between 250 and 400 in any given quarter. They don’t even have enough beds or infusion space to treat them all, and radiation treatments are backlogged.
All kinds of cancers are showing up — brain, lymph, stomach, pancreas, blood and even EYE cancers, “especially in younger people recently vaxxed.” Strokes are also “way up” in people with no risk factors or comorbidities. In an email to Kory, she wrote:41
“Ask me anything. I’ll tell you inside scoop from the floors and suites. This has to stop. They need to admit the fraud and crime and STOP. The liability must be lifted, mandates ended. They KNOW NOW and many KNEW THEN.
Don’t know if you’ll even read this, but I follow all of you on substack and Twitter — those not banned yet! — and read ALL the data. I’ve been a lab rat myself from an issue from a car accident years back — I know the process. So much fraud.”
In a follow-up email, the unnamed nurse continued:
“Lost 4 practitioners to serious side effects of ‘strongly encouraged’ boosters. 2 hospitalized, one in MICU … All in early 30s to mid-40s. They had no need for boosters … All had COVID previous, N antibodies fully measurable.”
Cardiac Anomalies Abound
Her colleagues in the cardiac unit also report “many anomalies … that never existed before,” including massive thrombi that fill the entire artery. Some embalmers have documented this never-before-seen phenomenon.42 They also can barely keep up with the unprecedented number of cardiac arrests. Kory writes:43
“She told me … that on some night shifts, nurse teams are seeing more cardiac arrests in a single shift than ever before and in unprecedented younger age patients.
On some shifts, they have had so many that the ‘crash carts’ are rolled straight from one arrest to another because pharmacy, especially on night shifts, are not able to re-stock fast enough. This situation has happened maybe once in my whole career, when two arrests happened on the same floor or unit within a short time period.”
And, while medical staff still are not speaking out publicly, the reality of the situation appears to be dawning inside the hospital walls, in private conversations between staff. Even there, however, nurses speak in code for fear of reprisal, referring to COVID jab injuries only as “that issue.”
The nurse pointed out that, now, the vaccination status is clearly marked at the top of the first screen of the patient’s medical record when the shot is suspected or known to be related to the patient’s “mysterious” or “complex” problem. Perhaps this is a sign that the dissociation from reality may be slowly breaking. I sure hope so.
Sources and References
- 1, 5 BHF.org.uk SADS
- 2 Cleveland Clinic Sudden Cardiac Arrest
- 3 BMJ Heart 2006;92:316-320
- 4 Heart May 2007; 93(5): 547-548
- 6 ONS.gov.uk SADS 2016-2020
- 7 Hong Kong Medical Journal 2019
- 8, 10 Euro News Weekly June 8, 2022
- 9, 11 Daily Mail Australia June 8, 2022
- 12 Methodist Debakey Cardiovasclar Journal April-June 2016; 12(2): 76-80
- 13 Circulation February 16, 2009; 119: 1085-1092
- 14 European Journal of Cardiovascular Prevention and Rehabilitation December 2006; 13(6): 859-875
- 15 OAN April 10, 2022
- 16, 25 Good Sciencing Athlete Deaths
- 17 Americas Frontline Doctors November 18, 2021
- 18 Frontiers in Sports and Active Living April 12, 2022
- 19, 40, 41, 43 Pierre Kory’s Medical Musings Substack June 13, 2022
- 20 Pierre Kory’s Medical Musings Substack June 6, 2022
- 21 Trends in Internal Medicine 2021; 1(1): 1-6
- 22 Science, Public Health Policy and the Law October 2021; 3: 100-129
- 23 Center Square January 1, 2022
- 24 FRED Population with Disability
- 26 Scientific Reports 2022; 12 Article Number 6978
- 27 The Blaze January 26, 2022
- 28, 35 CNBC June 10, 2022
- 29 Clinical Immunology May 2021; 226: 108721
- 30 Int Med Case Rep J. 2021; 14: 573-576
- 31 Front. Immunol. January 18, 2022
- 32 SAGE Open Medical Case Reports February 26, 2022
- 33 J Med Virol September 2021; 93(9): 5231-5232
- 34 Contagion Live May 12, 2022
- 36 The COVID Blog June 10, 2022
- 37 The US Sun May 22, 2022
- 38 New York Post May 31, 2022
- 39 Daily Mail May 27, 2022
- 42 Steve Kirsch Substack February 12, 2022
The CDC says “severe reactions” to the COVID vaccines are rare. That’s not what we found.

Don’t let the title fool you. The survey was created on June 17 and was executed by Pollfish on Jun 18.
By Steve Kirsch | June 20, 2022
A new poll of Americans shows that it’s likely that over 10M Americans were injured by the vaccine. This may explain why there are staffing shortages everywhere, from pilots to pharmacists.
The CDC has always maintained that severe reactions to the COVID vaccines are rare. Since I became a ‘misinformation’ spreader over a year ago, I’ve never believed that.
Yesterday, VSRF engaged the services of a professional polling company (Pollfish) to survey 500 people who were selected entirely at random.
The results were shocking, but they were consistent with the VAERS data which has been “lit up” since January 2021 telling us “the COVID vaccines are the most unsafe vaccines in human history.”
Now we have independent confirmation that the safety signals in VAERS were accurate, just like we’ve always said.
The numbers in this poll are absolutely shocking and there is no way to spin this as a positive.
This article includes the full Pollfish report as well as the individual response data so that anyone can analyze it themselves.
Key results from the poll
The poll was about the COVID vaccine exclusively, not about other vaccines. Stratified responses are age normalized to the US since the respondents who answered didn’t match the overall US demographics.
Doing some rudimentary estimates from the data (rather than stratifying by age which would be more accurate but more time consuming):
- 20% of the respondents reported they were vaccine injured
- The 20% number is remarkable because there was no pre-screening question and only 77.3% of Americans received at least one dose. That means that if you were vaccinated there is a 26% chance that you were injured (computed as 20.46/77.3). Wow.
- 30% of the households have a vaccine injured person
- 45% of the extended families have a vaccine injured person
- In 87% of the cases where there was a vaccine injury, there was either a doctor visit(s) or hospital stay(s) or both.
- 54% of the injured are still impacted today.
- 45% of the vaccine injured said it would shorten their lifespan
- 41% of the injured are unable to hold a job.
- Only 17% said their injury was a minor annoyance.
Putting these results into perspective
If you took the vaccine there is a 26% chance of injury as noted above. We also know that 45% of the injured said it would shorten their lifespan. This means that we are shortening the lifespan of 12% of the people who opt for the jab (since .26*.45=.117).
Shortening the lifespan of 12% of the people who take the vaccine seems like a very high price to pay for a virus that can be easily treated with a near 100% success rate with repurposed drugs.
For example, my friends George Fareed and Brian Tyson now have treated over 12,000 COVID patients using a combination of repurposed drugs and supplements without a single hospitalization or death if they were treated within 5 days of first symptoms. They even have a top-selling book on Amazon with rave reviews. Despite all of that, the FDA, CDC, and NIH continue to ignore them. They can’t get anyone to return their calls. They’ve had their protocol since the very beginning of the pandemic in March 2020 (it’s evolved over time).
It is stunning that the FDA approves the vaccines for our kids under 5 based on the COVID case statistics from just 10 children (7 placebo and 3 in the treatment arm), yet Fareed and Tyson who have treated over 12,000 patients can’t get a return phone call.
We are basically spending billions of dollars to seriously injure over 10 million Americans and kill hundreds of thousands. In the process, we did not reduce COVID, but made the problem worse with nonsensical interventions when all we ever needed was some simple advice:
- If you are sick stay home
- If you test positive, start a proven early treatment protocol ASAP such as the Fareed-Tyson protocol
We never needed the vaccine, masks (which make the problem worse), lockdowns, mandates, social distancing, or new drugs. All we had to do was follow the two simple steps above. It was never more complicated than that.
The data
Here are the full poll results and a spreadsheet with each individual response so you can do you own analysis:
Comparison with the rates of COVID vaccine injury that nurses report among their peers
Does a 12% injury rate seem high to you? That would be 30M people.
You may change your mind when you watch this video where I interview 7 nurses who were willing to speak out publicly and reveal the rate of vaccine injury among their peers.
Note: There are audio and video drop outs on the call. Use the cursor button to skip over this. I’ve reported these issues to Riverside.fm… their product feels like a beta test. Also, the preview has 8 nurses but there were only 7 in the call. Can you spot the duplicate?
Watch the video.
The rates averaged over 10% with some nurses seeing injury rates among their peers exceeding 40%. Sorry this is so hard to watch with the audio drop outs, but this is the best I have for this interview.
Jessica Rose’s take
She just sent me an email:
Steve, this is excellent. And aligns with my perceptions from the data.
Dr. Pierre Kory’s take
I sent him an email with all the data with a Subject line: Re: WHOA!!! this poll will BLOW YOUR MIND
Pierre quickly wrote back:
Wow is right. Those numbers are beyond disturbing, I have been calling this vaccine escapade a humanitarian catastrophe.. and this is what that looks like.
Comparison with VAERS
OpenVAERS shows 831,800 injuries reported domestically. But non-lethal injuries typically are under reported by a factor of 100 or more as we showed in the analysis of the disability data (where the under reporting factor was 128).
100*831K = 80M vaccine injured.
This makes our survey estimate of 30M look quite conservative.
However, if we take the raw, unadjusted numbers of our survey, 30% of all respondents over 18 were vaccine injured. Since there are 258M people over 18 in the US, we get 77M estimated vaccine injured, eerily close to the VAERS estimate.
So maybe VAERS isn’t such a bad estimator after all.
Validation by the government of Israel
Our final validation point is the proactive poll done by the government of Israel to assess vaccine side effects. This article describes that study. Among the highlights:
- About 25% of people with pre-existing auto-immune disorders, depression or anxiety reported a worsening of their symptoms following the booster.
- 4.5% of respondents reported neurological problems
- 17% reported shaking
So our 20% rate of injury isn’t all that far off what the Israeli government found.
What vaccine injury looks like
Many people never recognize vaccine injury because they don’t know what it looks like.
For example, as I am writing this article, I received the following message from one of my subscribers:
So my mom’s very dear friend called me tonight to tell me that her cancer came back. She was diagnosed over 20 years ago and has been cancer-free. I asked her did you get boosted she said yes, I already knew she was vaccinated. She said don’t start asking me these questions. What does that have to do with anything? They now found Cancer all over her uterus and it’s now spreading to her body. You think it’s from the vaccine? She was perfectly fine all these years before getting vaccinated. It makes me so sad she will probably end up dying.
I hear these stories all the time of a new cancer or a cancer that was under control suddenly coming back with a vengeance. These aren’t coincidences. While for any individual case it may be difficult to determine a cause, in aggregate we are seeing rates of cancer post vaccine that are unprecedented.
This is why Dr. Ryan Cole said, “Since January 1, in the laboratory, I’m seeing a 20 times increase of endometrial cancers over what I see on an annual basis.”
It’s amusing to me that when you search for that quote in Google, you only get articles debunking the claim whereas if you search in DuckDuckGo, you get articles with the original quote. This is pretty sad because Dr. Cole is highly respected among his peers for telling the truth. It’s a pity we never get a chance to have a fair debate with people who claim we are spreading misinformation.
And the personal stories
A lot of people tell me they know hundreds of people and none are vaccine injured.
Perhaps.
Or perhaps 95% of the vaccine injured don’t speak out about their vaccine injury.
It feels like for every person who sees nothing, I hear from people with the opposite experience:
I have so many of my relatives, neighbors and acquaintances succumb to this poison. Just yesterday a 30 year old acquaintance died of sudden heart attack. My aunt is suffering from autoimmune mediated arthritis after she got her 2nd Pfizer shot. A neighbor died after receiving the first dose of Sinovac Vaccine. A relative died after receiving 2nd dose of SinoVac… So many to list!!
Replicating the poll
The out-of-pocket cost for the poll is $500. Anyone could replicate it.
I’m sure fact checkers will spend $50,000 to replicate it 100 times until they get the results that match their narrative, and then publish that.
We didn’t do that. We’ve never asked this set of questions ever before. The questions weren’t “gamed” to elicit a specific response. We put together the questions we wanted, we ran the poll, and we published the results.
But the poll is affordable enough that if you don’t believe me, you can replicate it yourself.
Summary
The COVID vaccines are the most dangerous vaccines in human history. There are systemic flaws in the medical system that cause doctors to fail to recognize the evidence in plain sight. But that doesn’t change the reality. The COVID vaccines have killed hundreds of thousands of people and severely injured millions more. Since there is a safe, inexpensive alternative (early treatment protocols) with near 100% efficacy in reducing hospitalization and death, the vaccines should be immediately halted for all age groups. That would be the right thing to do.
But admitting they made a mistake would be an embarrassment to the medical community, government agencies, and Congress. So they will continue to look the other way and find ways to discredit the evidence and the brave people who are speaking out. They will continue to avoid any accountability by agreeing to an open debate. And in the meantime, millions more will be disabled, and hundreds of thousands will die prematurely.
Doctors and nurses know what is going on, but will not speak out as a group because they will lose their jobs and ability to practice medicine. So they keep their heads down.
The other doctors are so blue-pilled, they actually still believe the CDC. When Pfizer presents safety and efficacy data that is appalling to anyone with a working brain, they simply look at the vote count of the outside committees (unanimously approved) and never bother to learn more about what just happened. They won’t even watch this 4 minute video that explains just how bad the trial data was.
When we discovered that there wasn’t a single death from COVID-19 in the entire state of Massachusetts in both 2020 and 2021 in age 5 to 11, did that change anything? Of course not. COVID is an emergency because it might kill kids in the future and you can never be too careful when it comes to saving kids lives. But when large numbers of kids are killed by the vaccine, we simply look the other way. That’s not an emergency; it doesn’t even exist. Their odd causes of death are ignored.
My survey won’t change anything, even if it is replicated over and over. It will just add more evidence to the public record that the medical community is causing great harm and completely incapable of seeing the truth. They will not allow themselves to be held accountable in an open discussion— ever.
The American people won’t change their minds until the doctors change their minds. And the doctors are so well trained to respect the medical authorities like the FDA, CDC, and NIH and/or sufficiently afraid of the repercussions of speaking out, that nothing will change anytime soon.
The truth always comes out sooner or later. The later it comes out, the greater the damage will be to all these institutions that people once trusted.
The other thing I know is that the scale of this deception is unprecedented. When this unravels, which I have no doubt that it will, it will destroy our trust in:
- the medical community
- the HHS government agencies: CDC, FDA, NIH
- the mainstream media
- Congress
- State and local government officials
- CEOs who imposed vaccine mandates
- local health officials
- Mainstream social networks
- Fact checkers
- The Gates Foundation
- Bill Gates
- The Rockefeller Foundation
- the drug companies
- the courts
- clinical trials
- medical journals
- … and more…
This survey is just one more nail in the coffin of the “safe and effective” narrative. Nothing more.
Pfizer vaccine effects on total motile count in sperm donors
israeli study shows persistent effects
by el gato malo – bad cattitude – june 19, 2022
one of the great early misapprehensions about mRNA vaccines is that they would not have widespread, systematic effects, instead remaining relatively localized. this was rapidly debunked and early studies showed widespread penetration of organs with a particular and perhaps unfortunate preference for concentration in ovaries and testes. (this was discovered early in japan, then denied vehemently by armies of “fact checkers” only to wind up proven in pfizer’s own documents gained through FOIA and lawsuit.)
these mRNA drugs are broadly systemic and concentrate in (amongst others) reproductive organs and effects on menstrual cycles are widely documented.
in light of this quite worrying fact (especially with a compound carrying high CG enrichment relative to high virus and the attendant risks thereof) it has been surprising to me that there have not been more studies on this topic.
but a few are starting to emerge. this israeli study was published 2 days ago:

and the results are, well, nuts. (sorry)
there was strong a priori reason to suspect effects, especially in light of the higher and more persistent prevalence of vaccine induced S proteins vs natural infection and the CG enrichment issued mentioned above.
Over the first pandemic months, there was insufficient data regarding the possible impact of Covid-19 on human reproduction. Yet, it was clear it employs the Angiotensin-Converting Enzyme 2 (ACE2) receptor for cellular entry 3, 4. Various testicular cells including Leydig, Sertoli, spermatogonia and spermatozoa express ACE2 and related proteases resulting with viral fusion 5, 6. Cytokine storm-induced dysfunction, autophagy regulation and damaged blood-testis barrier were also suggested as possible pathogenic mechanism for testicular damage 7. Clinical reports of orchitis, supported by histological findings, further emphasized testicular involvement 8, 9. Therefore, detrimental impact on both spermatogenesis and testosterone production 10 seem an obvious outcome they evaluated donors from 3 sperm banks over a longitudinal period commencing before pfizer vaccine and following up after.
the study was performed and followed up according to the following timeline around vaccination.
- T0 = pre vaxx baseline
- T1 = 15-45 days post
- T2 = 75-120 days post
- T3 = 150+ days post
and from this, substantial effects on sperm concentration and overall motile count were discovered.
the authors draw a set of conclusions from this:
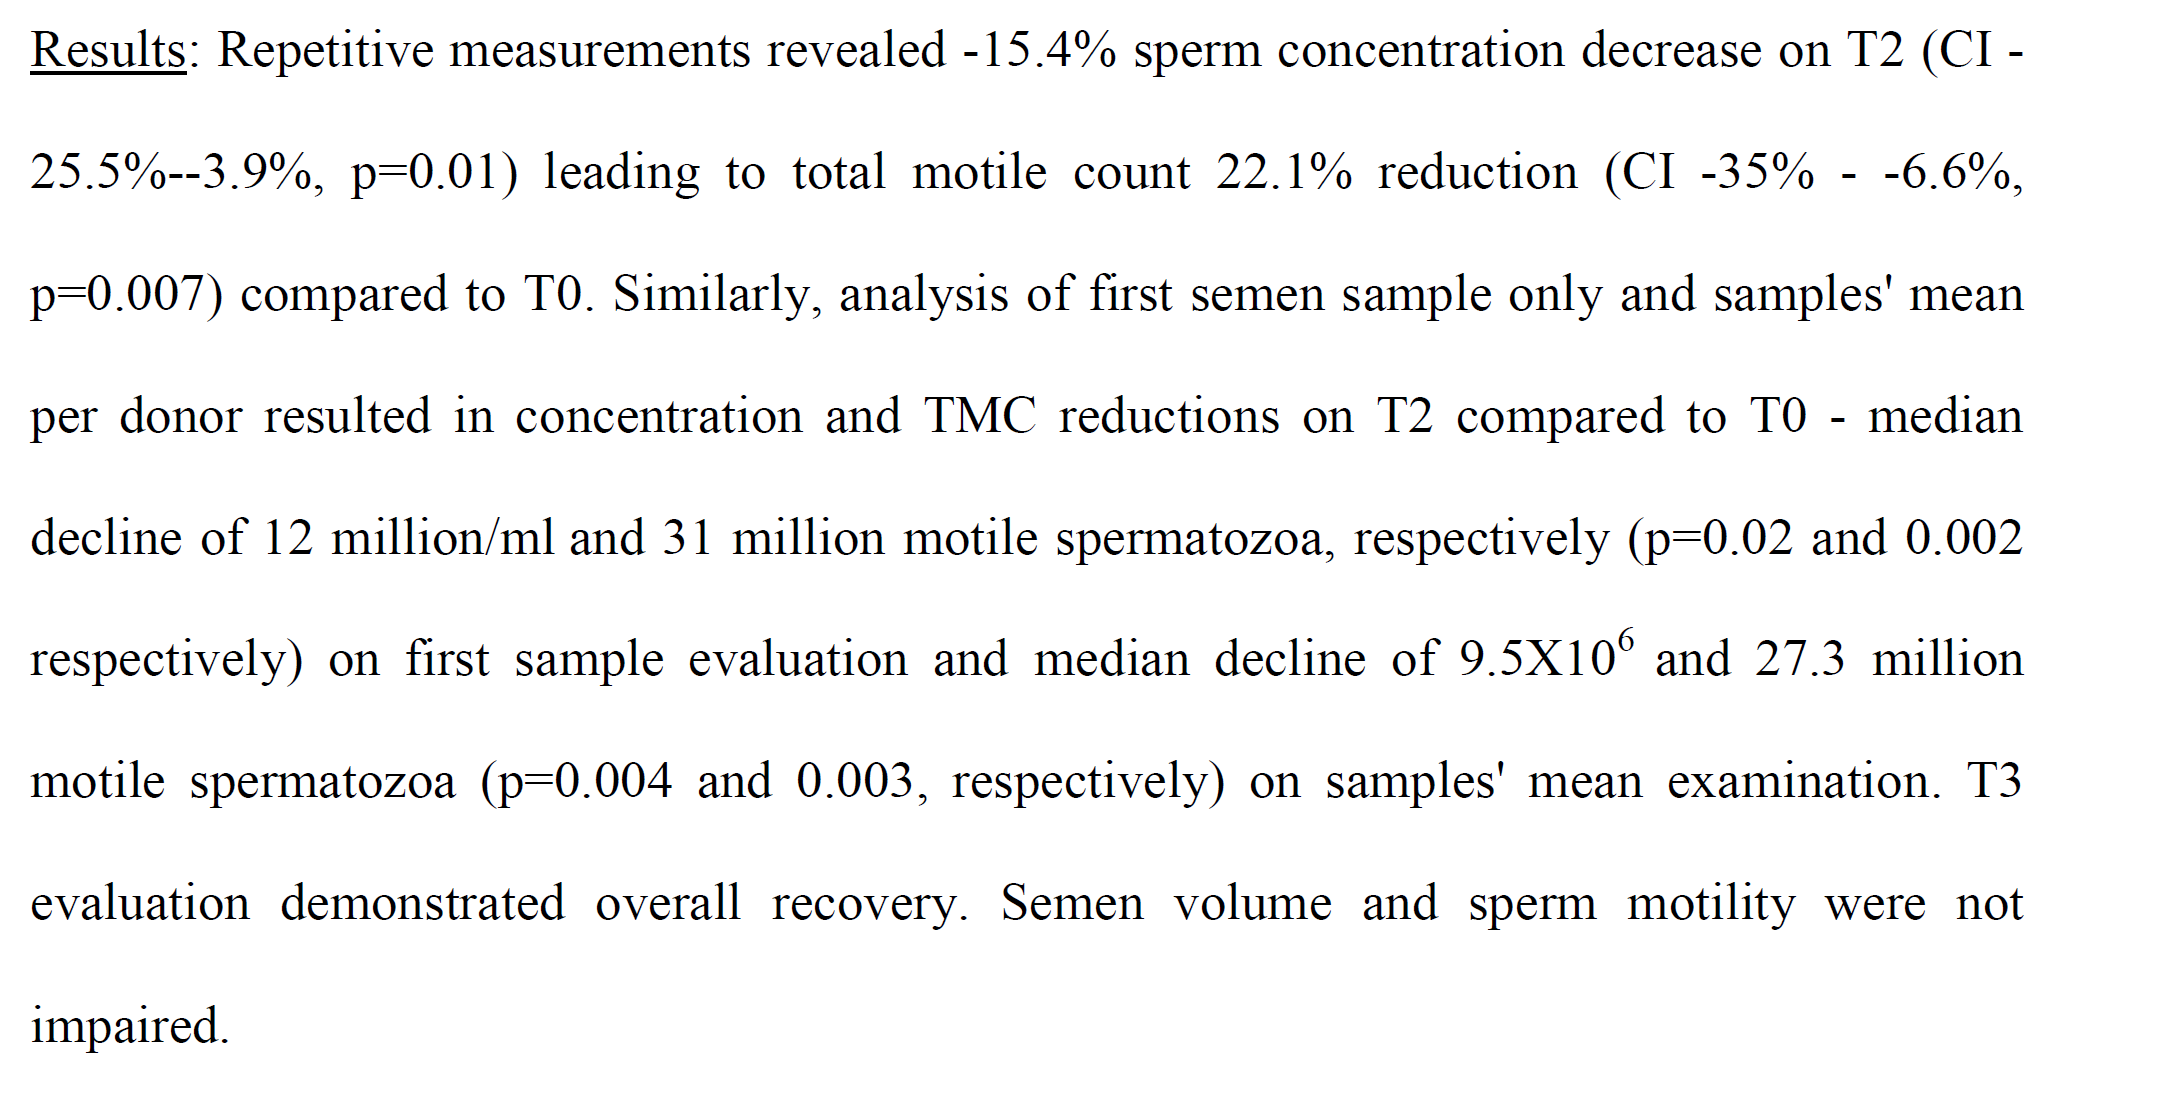
and from this state:
Conclusions: Systemic immune response after BNT162b2 vaccine is a reasonable cause for transient semen concentration and TMC decline. Long-term prognosis remains good
but i am left wondering about these claims and fear they may provide an example of the sort of “nerf or refute your own findings in the abstract so that we can publish this without massive controversy” behavior that has become all too common in medical and scientific journals who withhold peer review from those whose findings look too worrying if stated plainly. (but that will often let such data out if buried deep in supplements and appendixes)
this is why you should always read these data repositories. because they often tell quite a different tale than the abstract.
here’s table two from this same study. notice anything?
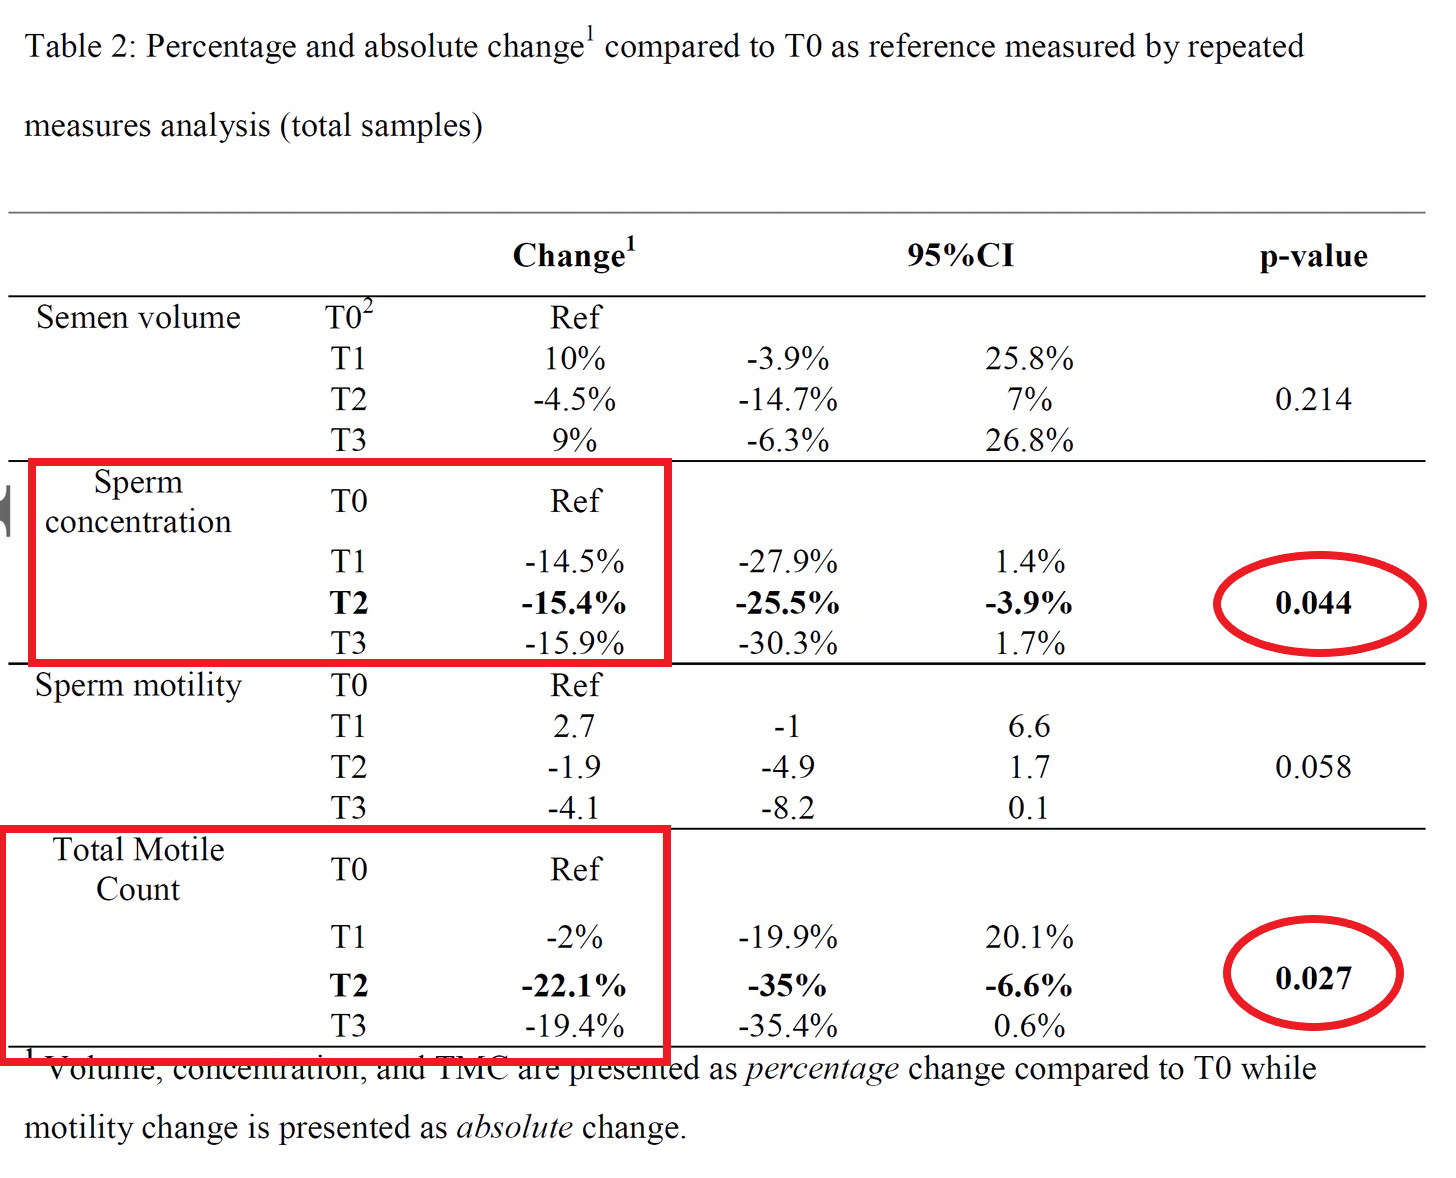
i’m struggling to see how one could call this “recovery.”
post day 150, sperm concentration was -15.9% vs baseline, lower even than in the 75-120 day period. average time post vaxx for T3 collection was 174 +/- 26.8 days so we’re talking about 6 months post vaxx with NO recovery in sperm concentration.
total motile count was slightly recovered from T2, but was still down 19.4% vs baseline, seeming to make up somewhat in volume what is lost in concentration.
both results were statistically significant at a 95% confidence interval.
there is a greater than 97% chance that the TMC figure is real and not random.
those are not odds you want to buck.
this raises some serious concerns for a number of reasons:
- obviously, this is a significant and unforeseen impact not only missed in the rush-job drug trials, but that the drug makers assured us was basically impossible and spent the better part of a year vehemently denying.
- this effect looks durable to at least 6 months and from this data, we really do not know when or even if (or to what extent) it will attenuate.
- the role of boosters here is not known, but there is every reason to expect they will have similar effects and either extend or possibly worsen this effect. that seems like a study that should be being performed immediately.
- even if this condition does moderate and TMC return to prior levels over time, that timescale looks quite long. it’s certainly more than 6 months. this would seem to imply low motile counts could be near constant in a regimen of annual or bi-annual boosters.
when you rush vaccines to market, especially vaccines using an entirely new and poorly understood modality that has never before been approved or even used in humans, you’re going to get all manner of nasty surprises and this looks to be yet another.
and clearly, it was missed. this was not even mentioned as a possibility in any FDA proceedings of which i am aware.
and THAT is why vaccine development generally takes place over 5-10 years, not 5-7 months.
best i can tell, we cannot even yet rule out that these effects are permanent.
and, of course, we have zero idea what they might do to pre-adolescents and possible impacts on their healthy sexual development and ultimate fertility.
and yet the US is bucking the trend in most of europe and approving this drugs for not just the young and healthy but for kids from 6mo-5 yr. this feels reckless.
we have little idea what this may be doing to ovaries and eggs either as these are much more difficult and invasive to study (and will likely need to be assessed by autopsy). this is another analysis that desperately needs to take place because unlike sperm, eggs to not replenish, so if you damage them, that’s that.
add to this effects on normal development and it could take decades to see what happened.
people have historically trusted vaccines because they underwent serious, long term testing before being pushed wide. assessment was measured in decades, not months and even a tiny number of adverse events would pull them off the market.
to trade upon that trust while abandoning all the safeguards that enabled it is bad science and worse public health policy.
how many more examples of unforeseen outcomes must we endure before this simple truth is accepted?
Featured Video

How Many More Gulf States Get Dragged Into Trump’s Iran War?
or go to
Aletho News Archives – Video-Images
Book Excerpt
How CIA used Ukraine as a platform for covert war against Russia
By Stephen KINZER | Responsible Statecraft | November 17, 2026
The following is an excerpt from Stephen Kinzer’s new book: Boiling Point: How America Brought War to Ukraine (Henry Holt and Company, November 2026)
Huddled beside an airstrip in southern Germany, a handful of anti-Communist warriors prepared to fire the first shots of the Cold War. A CIA officer from the Munich Operations Base was in charge. The Hungarian crewmen he had recruited stood nearby in flight suits. With them were two Ukrainian exiles who had volunteered to parachute into their homeland. They were code-named Apostle 1 and Apostle 2. Each carried forged identity papers, a miniature radio transmitter, a pistol, a machine gun, hand grenades, a purse full of gold coins, and a poison pill to be taken in case of capture. An unmarked C-47 transport plane was waiting.
The CIA officer overseeing this operation, a twenty-six-year-old Yale graduate named Stephen Tanner, watched the plane take off and disappear into the night. It flew over East Germany and Poland, then crossed into Soviet airspace. As it approached the Ukrainian city of Lviv, a cargo bay swung open. The two Ukrainians jumped into the darkness. Their mission was to link up with partisan fighters, seize territory, and establish a clandestine base through which the CIA could send them weapons.
That flight, on September 5, 1949, was the first American act of covert war in Ukraine. … continue
Blog Roll
 Aletho News
- Iran rejects unlimited IAEA inspections amid continued military threats
- A Bridge Too Far
- David Barnea in the Bundestag – Mossad as a model for Germany’s Intelligence Services?
- Rome blasts Kiev after Italian lawmakers added to ‘kill list’
- Another €45 bn down the drain: Why the EU is desperate to waste more cash on Zelensky
- In Europe, Anxiety Is Mounting—EU Unity Is Cracking at Every Seam
- How CIA used Ukraine as a platform for covert war against Russia
- European Commission proposes new loan for Kiev
- How Many More Gulf States Get Dragged Into Trump’s Iran War? | Matt Bracken
- US-Iran escalation: The side effects and benefits of low intensity war
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- Argentina’s Perito Moreno Glacier Joins Antarctica and Arctic In Defying Doomsday Melt Claims
- New Study: Barents Sea Temperatures Were Warmer And Sea Ice Less Extensive In The 1700s Than Today
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor

