Lawmakers reject amendment to prevent monitoring of unvaccinated
By Christina Maas | Reclaim The Net | April 12, 2022
All Democrats in the House Judiciary Committee voted against an amendment that could have protected the unvaccinated from being tracked.
The Domestic Terrorism Prevention Act of 2021 gives federal agencies like the FBI, DOJ, and DHS the authority to “analyze and monitor” activities of domestic terrorism and “take steps to prevent domestic terrorism.”
The current administration’s program for tackling domestic terrorism includes monitoring the spread of misinformation and conspiracy theories online.
In February, the DHS released a memo that pays attention to those who claim election fraud in 2020’s presidential race and those who spread “misinformation” about COVID-19.
“There is widespread online proliferation of false or misleading narratives regarding unsubstantiated widespread election fraud and COVID-19,” the DHS memo read.
“Grievances associated with these themes inspired violent extremist attacks during 2021.”
“COVID-19 mitigation measures – particularly COVID-19 vaccine and mask mandates – have been used by domestic violent extremists to justify violence since 2020 and could continue to inspire these extremists to target government, healthcare, and academic institutions that they associate with those measures.”
Following the release of the memo, Republican Rep. Andy Biggs proposed an amendment to the act to protect unvaccinated Americans from being tracked.
“None of the funds authorized to be appropriated in this Act shall be used to monitor, analyze, investigate or prosecute any individual solely because that individual declined the administration of a vaccine to COVID-19 or expressed opposition to such administration,” Biggs’ proposed amendment read.
According to a tweet by Republican Rep. Thomas Massie, every Democrat in the House Judiciary Committee voted against the proposed amendment.
“Due to a troubling DHS bulletin, @RepAndyBiggsAZ offered an amendment to prevent the targeting of Americans due to their views on COVID vax,” Massie wrote.
“Every Dem. voted against his amdt!”
Putting Big Pharma on Trial in the COVID-19 Era, Part 4
The Hypocrisy of “Misinformation”
By Rebecca Strong · February 16, 2022
I find it interesting that “misinformation” has become such a pervasive term lately, but more alarmingly, that it’s become an excuse for blatant censorship on social media and in journalism. It’s impossible not to wonder what’s driving this movement to control the narrative. In a world where we still very clearly don’t have all the answers, why shouldn’t we be open to exploring all the possibilities? And while we’re on the subject, what about all of the COVID-related untruths that have been spread by our leaders and officials? Why should they get a free pass?
Fauci, President Biden, and the CDC’s Rochelle Walensky all promised us with total confidence the vaccine would prevent us from getting or spreading COVID, something we now know is a myth. (In fact, the CDC recently had to change its very definition of “vaccine ” to promise “protection” from a disease rather than “immunity”— an important distinction). At one point, the New York State Department of Health (NYS DOH) and former Governor Andrew Cuomo prepared a social media campaign with misleading messaging that the vaccine was “approved by the FDA” and “went through the same rigorous approval process that all vaccines go through,” when in reality the FDA only authorized the vaccines under an EUA, and the vaccines were still undergoing clinical trials. While the NYS DOH eventually responded to pressures to remove these false claims, a few weeks later the Department posted on Facebook that “no serious side effects related to the vaccines have been reported,” when in actuality, roughly 16,000 reports of adverse events and over 3,000 reports of serious adverse events related to a COVID-19 vaccination had been reported in the first two months of use.
One would think we’d hold the people in power to the same level of accountability — if not more — than an average citizen. So, in the interest of avoiding hypocrisy, should we “cancel” all these experts and leaders for their “misinformation,” too?
Vaccine-hesitant people have been fired from their jobs, refused from restaurants, denied the right to travel and see their families, banned from social media channels, and blatantly shamed and villainized in the media. Some have even lost custody of their children. These people are frequently labeled “anti-vax,” which is misleading given that many (like the NBA’s Jonathan Isaac) have made it repeatedly clear they are not against all vaccines, but simply making a personal choice not to get this one. (As such, I’ll suggest switching to a more accurate label: “pro-choice.”) Fauci has repeatedly said federally mandating the vaccine would not be “appropriate” or “enforceable” and doing so would be “encroaching upon a person’s freedom to make their own choice.” So it’s remarkable that still, some individual employers and U.S. states, like my beloved Massachusetts, have taken it upon themselves to enforce some of these mandates, anyway. Meanwhile, a Feb. 7 bulletin posted by the U.S. Department of Homeland Security indicates that if you spread information that undermines public trust in a government institution (like the CDC or FDA), you could be considered a terrorist. In case you were wondering about the current state of free speech.
The definition of institutional oppression is “the systematic mistreatment of people within a social identity group, supported and enforced by the society and its institutions, solely based on the person’s membership in the social identity group.” It is defined as occurring when established laws and practices “systematically reflect and produce inequities based on one’s membership in targeted social identity groups.” Sound familiar?
As you continue to watch the persecution of the unvaccinated unfold, remember this. Historically, when society has oppressed a particular group of people whether due to their gender, race, social class, religious beliefs, or sexuality, it’s always been because they pose some kind of threat to the status quo. The same is true for today’s unvaccinated. Since we know the vaccine doesn’t prevent the spread of COVID, however, this much is clear: the unvaccinated don’t pose a threat to the health and safety of their fellow citizens — but rather, to the bottom line of powerful pharmaceutical giants and the many global organizations they finance. And with more than $100 billion on the line in 2021 alone, I can understand the motivation to silence them.
The unvaccinated have been called selfish. Stupid. Fauci has said it’s “almost inexplicable” that they are still resisting. But is it? What if these people aren’t crazy or uncaring, but rather have — unsurprisingly so — lost their faith in the agencies that are supposed to protect them? Can you blame them?
Citizens are being bullied into getting a vaccine that was created, evaluated, and authorized in under a year, with no access to the bulk of the safety data for said vaccine, and no rights whatsoever to pursue legal action if they experience adverse effects from it. What these people need right now is to know they can depend on their fellow citizens to respect their choices, not fuel the segregation by launching a full-fledged witch hunt. Instead, for some inexplicable reason I imagine stems from fear, many continue rallying around big pharma rather than each other. A 2022 Heartland Institute and Rasmussen Reports survey of Democratic voters found that 59% of respondents support a government policy requiring unvaccinated individuals to remain confined in their home at all times, 55% support handing a fine to anyone who won’t get the vaccine, and 48% think the government should flat out imprison people who publicly question the efficacy of the vaccines on social media, TV, or online in digital publications. Even Orwell couldn’t make this stuff up.

Photo credit: DJ Paine on Unsplash
Let me be very clear. While there are a lot of bad actors out there — there are also a lot of well-meaning people in the science and medical industries, too. I’m lucky enough to know some of them. There are doctors who fend off pharma reps’ influence and take an extremely cautious approach to prescribing. Medical journal authors who fiercely pursue transparency and truth — as is evident in “The Influence of Money on Medical Science,” a report by the first female editor of JAMA. Pharmacists, like Dan Schneider, who refuse to fill prescriptions they deem risky or irresponsible. Whistleblowers, like Graham and Jackson, who tenaciously call attention to safety issues for pharma products in the approval pipeline. And I’m certain there are many people in the pharmaceutical industry, like Panara and my grandfather, who pursued this field with the goal of helping others, not just earning a six- or seven-figure salary. We need more of these people. Sadly, it seems they are outliers who exist in a corrupt, deep-rooted system of quid-pro-quo relationships. They can only do so much.
I’m not here to tell you whether or not you should get the vaccine or booster doses. What you put in your body is not for me — or anyone else — to decide. It’s not a simple choice, but rather one that may depend on your physical condition, medical history, age, religious beliefs, and level of risk tolerance. My grandfather passed away in 2008, and lately, I find myself missing him more than ever, wishing I could talk to him about the pandemic and hear what he makes of all this madness. I don’t really know how he’d feel about the COVID vaccine, or whether he would have gotten it or encouraged me to. What I do know is that he’d listen to my concerns, and he’d carefully consider them. He would remind me my feelings are valid. His eyes would light up and he’d grin with amusement as I fervidly expressed my frustration. He’d tell me to keep pushing forward, digging deeper, asking questions. In his endearing Bronx accent, he used to always say: “go get ‘em, kid.” If I stop typing for a moment and listen hard enough, I can almost hear him saying it now.
People keep saying “trust the science.” But when trust is broken, it must be earned back. And as long as our legislative system, public health agencies, physicians, and research journals keep accepting pharmaceutical money (with strings attached) — and our justice system keeps letting these companies off the hook when their negligence causes harm, there’s no reason for big pharma to change. They’re holding the bag, and money is power.
I have a dream that one day, we’ll live in a world where we are armed with all the thorough, unbiased data necessary to make informed decisions about our health. Alas, we’re not even close. What that means is that it’s up to you to educate yourself as much as possible, and remain ever-vigilant in evaluating information before forming an opinion. You can start by reading clinical trials yourself, rather than relying on the media to translate them for you. Scroll to the bottom of every single study to the “conflicts of interest” section and find out who funded it. Look at how many subjects were involved. Confirm whether or not blinding was used to eliminate bias. You may also choose to follow Public Citizen’s Health Research Group’s rule whenever possible: that means avoiding a new drug until five years after an FDA approval (not an EUA, an actual approval) — when there’s enough data on the long-term safety and effectiveness to establish that the benefits outweigh the risks. When it comes to the news, you can seek out independent, nonprofit outlets, which are less likely to be biased due to pharma funding. And most importantly, when it appears an organization is making concerted efforts to conceal information from you — like the FDA recently did with the COVID vaccine — it’s time to ask yourself: why? What are they trying to hide?
In the 2019 film “Dark Waters” — which is based on the true story of one of the greatest corporate cover-ups in American history — Mark Ruffalo as attorney Rob Bilott says: “The system is rigged. They want us to think it’ll protect us, but that’s a lie. We protect us. We do. Nobody else. Not the companies. Not the scientists. Not the government. Us.”
Words to live by.
Report on the FDA’s 4/6/22 Advisory Committee (VRBPAC) meeting on the selection of future boosters
While the committee got nowhere on the choice of next boosters, there were a few very important reveals
By Meryl Nass, MD | April 10, 2022
Authorizing vaccine for the 6 months to 5 year old group was never mentioned. Can it be that FDA is finally grappling with the awful data, the longterm risks of vaccination, and will turn away from unleashing these vaccines on our youngest kids? Or is there simply too much money at stake, too many promised school mandates, too many done deals behind closed doors?
Important takeaways
1. Many members and presenters agreed that antibody levels (aka titers) are not a valid measure of immunity (they are not a correlate of protection, and there is currently NOTHING measurable in the blood that is considered a valid reflection of immunity). This admission is HUGE, as it reveals that neutralizing antibody titers can no longer be used to authorize or approve COVID vaccines.
2. Therefore the only way to determine vaccine effectiveness is a clinical trial.
3. No one at the meeting (nearly 30 people) ventured a guess as to what strain might cause the next COVID wave. All seemed to agree there would be another wave, but this was just a guess. However, without a variant you can’t make a vaccine and you can’t conduct a clinical trial to see if the vaccine works. And you can’t possibly do this by June, to make vaccine available for the fall, when FDA and the VRBPAC expect it will be needed.
4. Dr. Peter Marks, the director of the FDA’s vaccine division, CBER, admitted that the 4th booster dose authorized last week was a “stopgap measure”– in other words, he claims it was to kick the waning vaccine efficacy can down the road.
5. Claims were repeatedly made that vaccine still protects against severe outcomes and death, but FDA’s lead scientist for this presentation, Doran Fink, admitted that efficacy is also waning for severe outcomes. I’ll say it is.
6. NO data was presented at all regarding strain choice/prediction of what to use as the antigen(s) for a newer vaccine. It was as if everyone just got the idea to begin thinking about this yesterday.
7. It appeared that neither CDC, FDA nor the VRBPAC advisors wanted to take any initiative or responsibility in figuring out what kind of a vaccine comes next (with the exception of Dr. Kim, who did show initiative about prescribing a way forward). I am not sure any of them wanted to find a way forward.
8. Was everyone dancing around the strain/variant choice because in fact no one really wants a newer vaccine, or because no one wanted to be responsible for picking a loser? I could not tell whether this was a deliberate slow-roll as a means of squeezing out of the COVID vaccine disaster, or whether we were watching an agency and advisors who are highly risk-averse but have no problems with the vaccines.
9. The Public Comments from about 1:30 pm to 2:30 pm (about 5 hours into the meeting) were evidence of outstanding work by independent scientists and heart-rending testimonies by the vaccine injured. There were only 2 people who favored vaccines in the group, one a top Moderna scientist (Dr. Rita Das) who did not actually belong there… had FDA begged Moderna to find someone to speak in favor of boosters?
10. The word transparency was used a lot. Which was peculiar since FDA’s COVID vaccine data, deliberations and decisions have been anything but transparent. Even the reason for today’s meeting is murky.
The link below is to my live blog of the all day meeting.
https://live.childrenshealthdefense.org/admin/fda-advisory-committee/fullscreen-chat
———————-
Of course, what the FDA needs to say, no doubt in some slowly unrolling, self-serving fashion, is that:
- The mRNA platform was the best we could do under the circumstances, but it didn’t actually work out that well.
- Coronaviruses are mutating or lab-tating too quickly to be able to vaccinate effectively against them.
- While we still have contracts for 5 or 10 doses per person, we are going to cancel them and try early treatments.
What they won’t way is that these vaccines sickened many thousands, or millions, and the US will now establish clinics to evaluate and treat the injured Americans who did what their government asked of them, cover their medical expenses and pay them disability.
PS. When the Japanese found that the HPV vaccines caused similar severe injuries, about 8 or 10 years ago, clinics were established to take care of the injured.
What’s Next for Federal Employee Shot Mandate
Liberty Counsel | April 8, 2022
The Fifth U.S. Circuit Court of Appeals ruled 2-1 yesterday to overturn the January injunction issued by a federal judge in Texas that blocked Joe Biden’s shot mandate that required all federal employees to receive the COVID shot or face termination.
Biden announced last September that more than 3.5 million federal workers were required to undergo vaccination, with no option to get regularly tested instead, unless they secured approved medical or religious exemptions.
Feds for Medical Freedom, which represents more than 700 border patrol agents, pilots, diplomats, firefighters, contractors, and other Americans, filed a lawsuit against the Biden administration on December 21, 2021, seeking preliminary and permanent injunctive relief from “enforcing or implementing the Federal Employee Mandate and the Contractor Mandate.”
In Feds for Medical Freedom v. Biden, U.S. District Court Judge Jeffrey Vincent Brown previously granted a preliminary injunction and wrote that the mandate would pose a substantial threat of irreparable harm over the “liberty interests of employees who must choose between violating a mandate of doubtful validity or consenting to an unwanted medical procedure that cannot be undone.”
Yesterday, the Court of Appeals said that Judge Brown did not have jurisdiction to block the mandate. The appeals court ruled that the parties failed to exhaust administrative remedies because they did not raise their claims through the Civil Service Reform Act of 1978. Federal workers facing adverse actions may appeal to an entity called the Merit Systems Protection Board, which decides whether the worker was properly disciplined. If the worker prevails, the board can order an agency to reinstate the worker or undertake other measures. The Court of Appeals noted that federal employees can then appeal to the District of Columbia Court of Appeals.
This case did not raise the Religious Freedom Restoration Act (RFRA), which does not require the exhaustion of administrative remedies and which allows litigation in any federal court. Liberty Counsel’s case involving federal employees, Federal Civilian Contractor Employer v. Carnahan, does raise RFRA. RFRA provides a powerful remedy and protection for federal employees who object to the COVID shots based on their religious beliefs. In fact, the mandate itself acknowledges that federal employees may request a religious accommodation from the shots.
Now Feds for Medical Freedom can ask the full Court of Appeals to review the matter and also request the Supreme Court to intervene. The case is far from over.
Liberty Counsel Founder and Chairman Mat Staver said, “This court decision by no means ends the case for federal employees. The case has a long way to go. While the Court of Appeals dodged the legal issues of the federal employee mandate, federal employees have a clear right to religious accommodation under the Religious Freedom Restoration Act. The mandate even acknowledges the fact that federal employees have religious free exercise rights. Under the mandate, and in accordance with the federal law, employees have the right to religious accommodation from the COVID shots.”
Vaccinated Have Up To SIX Times the Infection Rate of Unvaccinated, NZ Government Data Show
By Amanuensis | The Daily Sceptic | April 9, 2022
New Zealand is a fascinating country – amazing geography, likeable population, and, unlike its neighbour Australia, most of its wildlife isn’t planning on killing you at the slightest opportunity. It is also fascinating with respect to Covid because its population has a very high vaccination rate across all age groups (well, down to five), but up until recently there has been negligible natural immunity to Covid. Because of these two factors, New Zealand was always going to be of interest as soon as Covid arrived properly, if only to see how its vaccination efforts had protected its population.
For those who missed it, since the end of last year New Zealand has had a succession of Covid waves. These started small, but in the most recent wave, taking place during February and March, infection rates were enormous – if we had these infection rates in the U.K. we’d have peaked at approximately 350,000 cases per day (rather than around 200,000). What’s more, it looks like New Zealand exceeded its testing capacity during that wave, suggesting that peak infections were probably even higher. It is relevant to note that during February and March, New Zealand had over 90% of all the cases it has ever had and most of the rest occurred in January – prior to 2022 New Zealand reported very few Covid infections.
So much for the Covid vaccines protecting against infection – but what do the data look like in detail?
Cases
New Zealand is somewhat helpful in that it does publish daily cases, hospitalisations and deaths by vaccine status; somewhat because it doesn’t allow easy access to anything other than the current day’s report. Thankfully, the Wayback Machine ensures that at least some web pages aren’t forever lost to history. These data were collated for dates since mid February 2022 and smoothed with a seven-day moving average to create a time series of Covid cases by vaccine status.
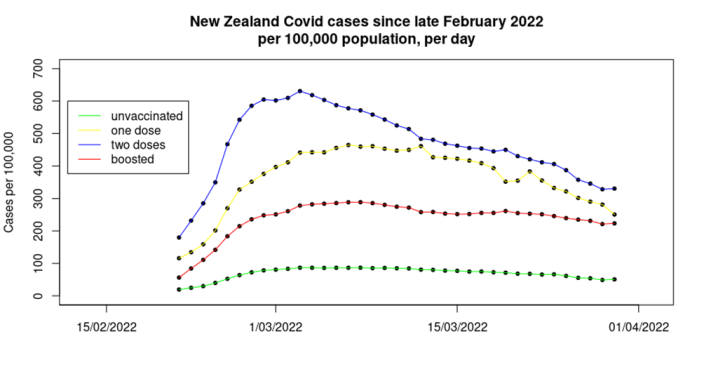
The first time the above graph popped up on my computer screen I had to go and double check all the data sources – and then I triple checked them. The data shown on the graph are notable for several reasons:
- Firstly the obvious one – during the most recent Covid wave there was a much lower infection rate in the unvaccinated, compared with those that had been given one, two or three doses of vaccine. What’s more, this isn’t a small effect – over the period shown approximately:
- 10% of the triple vaccinated in New Zealand were infected.
- 14% of the single vaccinated were infected.
- An astounding 18% of the double vaccinated were infected.
- Yet only 3% of the unvaccinated appear to have been infected.
- The order of the effect is unexpected – for some time in the U.K. the highest case rates have been found in the triple vaccinated, with case rates in the single and double jabbed much lower. In New Zealand the highest rates are seen in the double vaccinated.
- The data for cases in the double dosed appear to have an earlier peak than seen in the data for the unvaccinated, single jabbed and triple jabbed.
- The fall from peak cases to the most recent data point is also interesting. Case rates in the unvaccinated, single dosed and the double dosed have all fallen approximately 45% since their respective peaks, however, case rates in the triple vaccinated have only fallen approximately 20% since their peak. This is rather concerning, as it suggests that we might find that the boosted population maintain a viral reservoir for Covid, ensuring that case rates take much longer to fall to trivial levels and hindering attempts to get society back to a post-Covid normal.
The infections data from New Zealand allow us to estimate the vaccine effectiveness for the Covid vaccines in the absence of natural immunity.
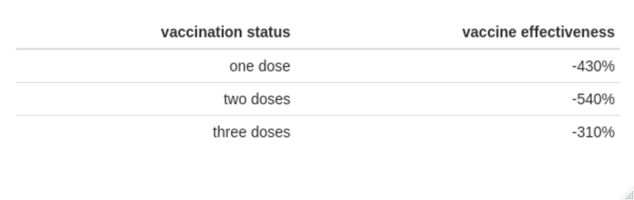
Unadjusted estimates of vaccine effectiveness against infection as at end of March 2022
These data are in contrast to recent data from the U.K., which show one and two doses of vaccine to have a VE of minus-50% to minus-100%, and the booster to have a VE of around minus-300%. While this sounds counterintuitive, it is possible that we’re seeing a complex interplay between a waning of the impact of the vaccine and the impact of additional vaccine doses:
- The U.K. vaccinated early, allowing for the impact of those early vaccine doses to have waned significantly for those choosing not to top-up their ‘protection’.
- The Covid vaccines appear to have a period of approximately two to three months where their impact on the immune system is different than in later periods; this is possibly due to the creation of short-lived IgA (mucosal) antibodies. In the U.K., booster vaccinations were given in autumn 2021, and thus most individuals will have been beyond this period when the Omicron variant’s first wave appeared in December.
In New Zealand, the timescales are very different: those given the booster dose will still be in the two-three month period where short-lived immune responses dominate; those given two doses will be in the proposed period of maximal vaccine negative impact; while those that chose not to accept the offer of a second vaccine dose will be in the period where vaccine effects are waning.
There’s one more point to add for cases in New Zealand, and it relates to the U.K. For months, the UKHSA has been telling us that one possible reason for us seeing far fewer cases in the unvaccinated compared with the vaccinated is because the unvaccinated have natural immunity following high infection rates previously (presumably because the unvaccinated are reckless and didn’t follow lockdown rules – I imagine that they also ride motorcycles too quickly, set off fireworks indoors and play with matches while filling up the car). These data from New Zealand, which at the time had very few individuals previously infected with Covid, show lower case rates in the unvaccinated without any significant levels of natural immunity, contradicting the claim of the UKHSA and eliminating one of its reasons for ignoring the alarming data.
Hospitalisations
Analysis of the hospitalisations data offered by the New Zealand authorities is made complex by there being no stratification of the hospitalisations by age group, and the lack of complete vaccinations data by age. However, U.K. data show that in recent weeks approximately 95% of hospitalisations were in those aged over 60; assuming that this will also hold true for the New Zealand population allows us to offer a indicative analysis of the likely impact for that age group of the vaccines on hospitalisations in the country.
The analysis is also hindered by the data on vaccine coverage for those aged over 60 not differentiating between those that have had only one dose of vaccine and those that are unvaccinated. This might in isolation from other data appear to be ‘sensible’ – after all, the single dosed have the ‘least protection’ as well as ‘the longest time for protection to wane’. However, the data shown in the previous section suggest that the unvaccinated and those having taken a single dose of vaccine are in no way comparable, and that considering them as a single group could lead to misleading conclusions. Nevertheless, that’s the hand that’s been dealt for us.
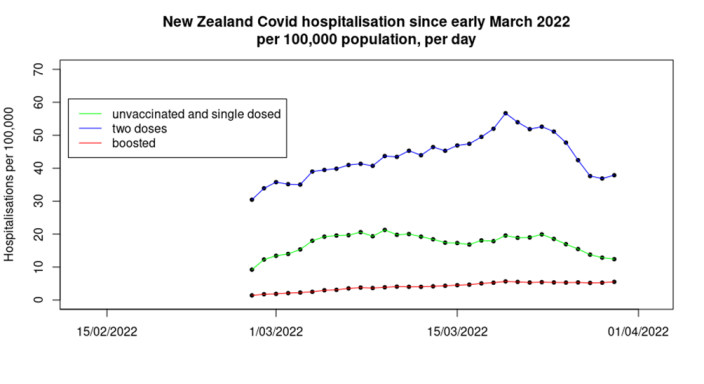
The data are somewhat surprising. While those given a booster dose of vaccine seem to have lower levels of hospitalisations than found in the group containing the unvaccinated and those given only one dose of vaccine – as might be expected – the double dosed have significantly higher hospitalisation rates.
Also interesting is the trend in the data:
- Hospitalisations in the unvaccinated/single-dosed appear to peak earliest – we have also seen this effect in U.K. data, usually in the form of dire warnings early in each Covid wave that the only people being hospitalised are the unvaccinated, only for the warnings to go quiet later in the Covid wave when the data move in the opposite direction.
- Hospitalisations in those given two doses of vaccine appear to peak towards the end of the period shown.
- Hospitalisations in the boosted population appear to show little signs of slowing down, let alone reducing, over the period in question. Note also that this group saw a fourfold increase over the time period shown, whereas the double dose and single-dose/unvaccinated group both saw a 25% increase, albeit with an intermediate period with higher hospitalisation rates.
It was not possible to properly disentangle the hospitalisations data for the unvaccinated, but the data suggest that in aggregate those having taken two or three doses of vaccine (when the two groups are put together) have approximately 45% lower risk of hospitalisation than the unvaccinated/single-dosed. It is worth noting that in the U.K. data we see higher hospitalisation rates in the single vaccinated in those aged over 60, compared with the unvaccinated. It is possible that the same pattern is found in New Zealand, only ‘covered up’ by the co-mingling of the data. If this is the case then the apparent protection offered by the vaccine in the two or three dose individuals will be somewhat lower than 45%.
Deaths
The mortality data from New Zealand are also complicated because the health authorities lump together into one group all the unvaccinated and those having taken a single dose of vaccine. Beyond that complication, deaths data can be tricky to analyse, because there are such huge differences in death rates from (or with) Covid by age. Fortunately, the mortality data offered by the New Zealand authorities do include deaths by age group, which allows a finer analysis than was possible with the infections and hospitalisations data.
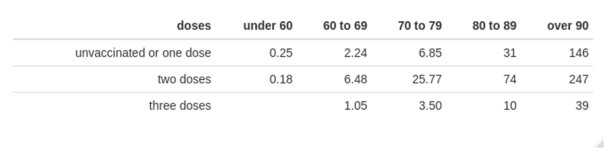
Covid mortality per 100,000 per week, by vaccination status and age
The above table suggests that while those given three doses of vaccine have a decreased risk of death from (or with) Covid compared with the mortality rate in the strange group called ‘unvaccinated or one dose’, the risk of death is greatest in those given two doses of vaccine.
However, it is possible that New Zealand’s data have a similar pattern to that seen in the U.K. (and elsewhere), where dose effects are complicated by the health of those given each vaccine, namely that those closest to death were spared a dose of vaccine, and thus concentrated deaths into the very small number left in the prior dose group. A comparison of the data for ‘unvaccinated or one dose’ with ‘two or three doses’ suggests that the vaccines do still protect against death, but only to a very low degree in younger age groups.
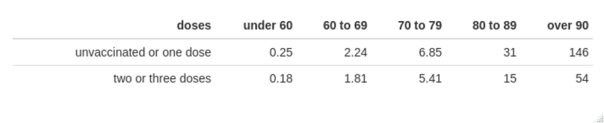
Covid mortality per 100,000 per week, by vaccination status and age
The data above support the use of vaccination to protect against death from (or with) Covid for those aged over 80. On the other hand, the mortality rate in those aged under 60 is very low, and the estimated vaccine effectiveness in protecting against death for those aged under 80 is only approximately 30% – once again, the real-world vaccine effectiveness estimate is rather low. It is also of note that these rather poor figures for the protection offered by the vaccines against mortality come from a country that started vaccination rather late (summer 2021) and where most of the population were only given their booster doses two to three months ago. These data suggest that the vaccines simply do not offer substantive protection against death for newer Covid variants, rather than it simply being a case of waning vaccine protection.
It is also important to note that the data on the benefits of the vaccine in protecting against death shown above should be treated with caution:
- Data on deaths in the unvaccinated and those given a single dose of vaccine are co-mingled; the New Zealand hospitalisation data suggest that death rates might be greater in the single-jabbed.
- The vaccinated appear to have significant increased risk of catching Covid, which contributes to overall risk of serious disease and death.
- These calculations do not include any consideration of the risk of side-effects and complications following vaccination.
Overall mortality
One other aspect of the data coming from New Zealand that is of interest relating to Covid is excess mortality. These data are of interest because New Zealand managed to keep itself more-or-less clear of Covid until the last few months of 2021, and even then case numbers were very low until 2022, with the result that Covid deaths were negligible prior to 2022. With that in mind, its excess death data between the start of 2020 and the end of 2021 are very interesting.
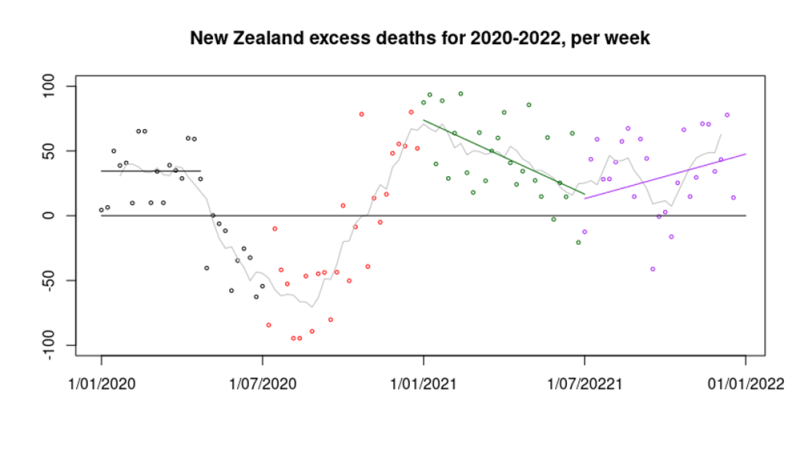
Many countries around the world had a peak in excess deaths in the first quarter of 2020, followed by a significant reduction in deaths into mid 2020. There has been speculation that this pattern was seen because Covid infections in early 2020 killed the most vulnerable, leaving a period in which there were fewer people left to die. However, New Zealand also has this pattern of excess deaths in the first half of 2020 (black data points in the graph above) without Covid infections, suggesting that the reduction in deaths seen in mid 2020 were a result of lockdown. The reason for the excess deaths in New Zealand in the first quarter of 2020 are not at all clear.
Most countries then saw an increase in deaths towards the end of 2020; this has been explained by a resurgence in Covid cases. However, New Zealand saw a similar pattern without Covid infections (red data points). It is possible that this increase was caused by the impact of the reduced healthcare provision during the extreme lockdown – though there are no data to support this supposition. There are reports that the New Zealand healthcare system experienced its busiest summer (January and February) on record with hospitals across the country reaching ‘crisis point’ and several emergency departments at capacity. The cause of this healthcare pressure is unclear, however.
Perhaps the most interesting data in the graph above are seen in 2021. During the first half of 2021 excess deaths slowly reduced from the high seen at the start of 2021 (green data points), perhaps a result of healthcare provision returning to normal. However, around mid-year the trend reversed and excess deaths started to climb again (purple data points). Again, it must be pointed out that there were very few Covid cases in New Zealand at this time, and negligible deaths. Just about the only unusual things occurring in the country at that time were a lack of international travel, restrictions in day-to-day activities for the population and an enormous mass vaccination campaign using novel, under-tested vaccines.
During 2020-2022, there were approximately 2,000 excess deaths in New Zealand, a significant number in a country with a population of five million. We don’t know the proportion that occurred because of lockdown, vaccines or something else; all that we do know is that they weren’t a result of Covid.
Note on data analysis methods. Infection, hospitalisation and mortality data were obtained from the New Zealand Ministry for Health (using Wayback Machine for historical data). Vaccination data were also obtained from the NZ Ministry for Health. Population data were obtained from Stats.govt.nz. Vaccination data were offset by seven days for the infections analysis to account for the Ministry for Health’s definition of vaccine status at infection. An additional seven days offset was applied for hospitalisation, and 14 days for death, to account for the typical timescales of disease progression.
Amanuensis is an ex-academic and senior Government scientist. He blogs at Bartram’s Folly.
Cardiac Disorders Account for 20% of 1.2 Million Injuries Reported After COVID Vaccines, VAERS Data Show
By Megan Redshaw | The Defender | April 8, 2022
The Centers for Disease Control and Prevention (CDC) today released new data showing a total of 1,217,333 reports of adverse events following COVID vaccines were submitted between Dec. 14, 2020, and April 1, 2022, to the Vaccine Adverse Event Reporting System (VAERS). VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
The data included a total of 26,699 reports of deaths — an increase of 303 over the previous week — and 217,301 of serious injuries, including deaths, during the same time period — up 2,780 compared with the previous week.
Excluding “foreign reports” to VAERS, 803,613 adverse events, including 12,304 deaths and 79,094 serious injuries, were reported in the U.S. between Dec. 14, 2020, and April 1, 2022.
Foreign reports are reports foreign subsidiaries send to U.S. vaccine manufacturers. Under U.S. Food and Drug Administration (FDA) regulations, if a manufacturer is notified of a foreign case report that describes an event that is both serious and does not appear on the product’s labeling, the manufacturer is required to submit the report to VAERS.
Of the 12,304 U.S. deaths reported as of April 1, 17% occurred within 24 hours of vaccination, 21% occurred within 48 hours of vaccination and 59% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 561 million COVID vaccine doses had been administered as of April 1, including 331 million doses of Pfizer, 211 million doses of Moderna and 19 million doses of Johnson & Johnson (J&J).

Every Friday, VAERS publishes vaccine injury reports received as of a specified date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed.
Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
U.S. VAERS data from Dec. 14, 2020, to April 1, 2022, for 5- to 11-year-olds show:
- 10,157 adverse events, including 239 rated as serious and 5 reported deaths.
The most recent death involves a 7-year-old boy (VAERS I.D. 2152560) from Washington who died 13 days after receiving his first dose of Pfizer’s COVID vaccine when he went into shock and suffered cardiac arrest. He was unable to be resuscitated and died in the emergency department. - 17 reports of myocarditis and pericarditis (heart inflammation).
The CDC uses a narrowed case definition of “myocarditis,” which excludes cases of cardiac arrest, ischemic strokes and deaths due to heart problems that occur before one has the chance to go to the emergency department. - 38 reports of blood clotting disorders.
U.S. VAERS data from Dec. 14, 2020, to April 1, 2022, for 12- to 17-year-olds show:
- 30,954 adverse events, including 1,778 rated as serious and 44 reported deaths.
The most recent death reported to VAERS involves a 15-year-old girl (VAERS I.D. 2201554) from South Dakota who developed COVID despite receiving two doses of the Pfizer/BioNTech. She received her first dose of Pfizer on July 30, 2021, and her second dose on August 20, 2021. She presented to the ER on January 15, 2022, with abdominal pain, tested positive for COVID, was put on a ventilator and subsequently passed away. - 68 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases attributed to Pfizer’s vaccine.
- 650 reports of myocarditis and pericarditis, with 638 cases attributed to Pfizer’s vaccine.
- 165 reports of blood clotting disorders, with all cases attributed to Pfizer.
U.S. VAERS data from Dec. 14, 2020, to April 1, 2022, for all age groups combined, show:
- 20% of deaths were related to cardiac disorders.
- 54% of those who died were male, 41% were female and the remaining death reports did not include the gender of the deceased.
- The average age of death was 73.
- As of April 1, 5,370 pregnant women reported adverse events related to COVID vaccines, including 1,693 reports of miscarriage or premature birth.
- Of the 3,642 cases of Bell’s Palsy reported, 51% were attributed to Pfizer vaccinations, 40% to Moderna and 8% to J&J.
- 878 reports of Guillain-Barré syndrome, with 42% of cases attributed to Pfizer, 30% to Moderna and 28% to J&J.
- 2,377 reports of anaphylaxis where the reaction was life-threatening, required treatment or resulted in death.
- 1,666 reports of myocardial infarction.
- 13,738 reports of blood-clotting disorders in the U.S. Of those, 6,145 reports were attributed to Pfizer, 4,899 reports to Moderna and 2,651 reports to J&J.
- 4,099 cases of myocarditis and pericarditis with 2,517 cases attributed to Pfizer, 1,391 cases to Moderna and 180 cases to J&J’s COVID vaccine.
The British are now officially hiding Covid vaccine data
… and they are lying about the reason why
By Alex Berenson | April 7, 2022
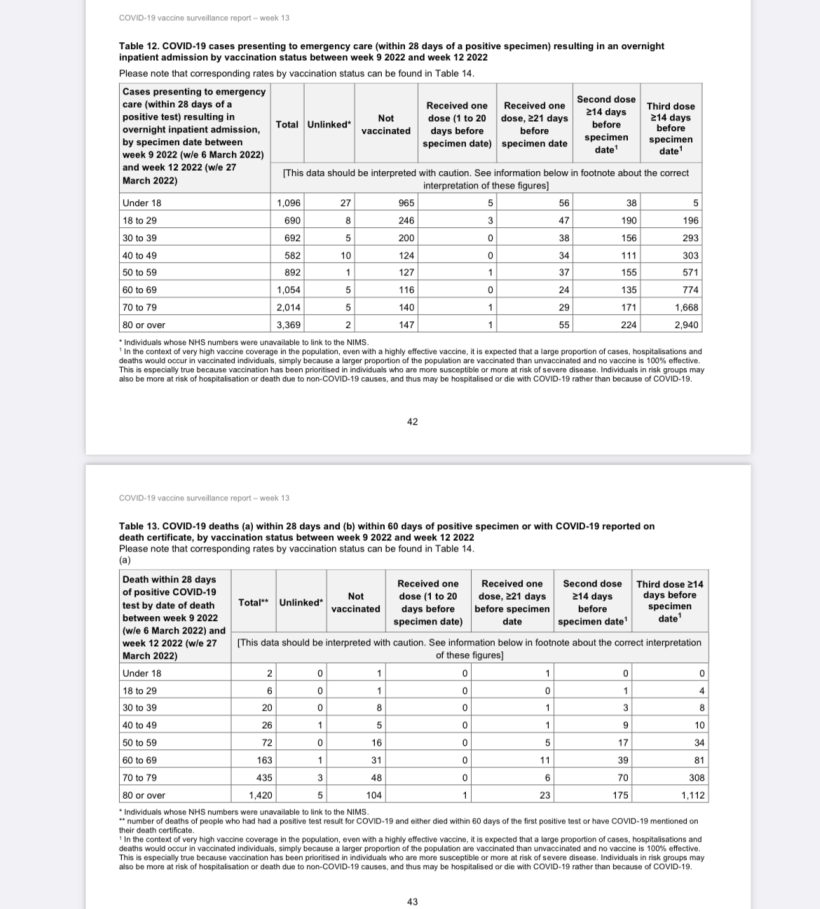
Until last week, the British government offered the best source of raw data on the efficacy of the Covid vaccines. Each Thursday, the UK Health Security Agency reported the number of new infections, hospitalizations, and deaths by vaccine status.
Since last fall, and especially since the Omicron variant hit, the reports have presented an increasingly dismal picture of vaccine efficacy. Last week’s report showed that in March, nearly 90 percent of adults hospitalized for Covid were vaccinated. And OVER 90 percent of deaths were in the vaccinated:
The importance of these reports is hard to overstate.
They were the single best source of raw data about how well the Covid vaccines were or were not working anywhere in the world. It was a long-running sequential series with clearly defined rules from a large country with high vaccine coverage.
Plus, because the British have national health insurance, the government could determine with near-certainty who had been vaccinated. As you can see, fewer than 1 percent of the people in the reports are called “unlinked” – meaning their vaccine status was undetermined.
AS OF THIS WEEK’S REPORT THE BRITISH GOVERNMENT IS NO LONGER PROVIDING THESE CHARTS.
The British government is offering the nonsensical excuse that it can no longer provide the figures because it has ended free universal testing for Covid: Such changes in testing policies affect the ability to robustly monitor COVID-19 cases by vaccination status, therefore, from the week 14 report onwards this section of the report will no longer be published.
The British government is lying.
Even if the end of free testing somehow affected its ability to provide “robust” data about infections, it would make no difference to the hospitalization or death figures, which are far more important. Unless Covid patients are going to be hospitalized anonymously, the Health Security Agency will still be able to match their names (and the names on death certificates) against vaccination records.
In fact the British government would be derelict not to continue to collect the data, and it surely will. But the public will no longer see it.
Why?
One reason and one reason only. Ever since I mentioned the existence of these reports to Joe Rogan in October, they have become an embarrassment. They are impossible to spin, and the clearest possible signal of vaccine failure.
But hiding the numbers won’t make the vaccines work better. It will just make people less likely to believe anything else public health authorities tell them about Covid and the vaccines – if that’s even possible at this point.
Increase in heart attacks since June in both England and Scotland
The Naked Emperor’s Newsletter | April 7, 2022
In my recent article on heart attacks in youngsters I focussed on the Scottish data. I have since looked at the English data and it follows a similar pattern.
The UK Health Security Agency (UKHSA) produce a weekly Ambulance Syndromic Surveillance System Bulletin for England. Page 8 looks at Cardiac or respiratory arrest, specifically the daily number of cardiac or respiratory arrest ambulance service calls.
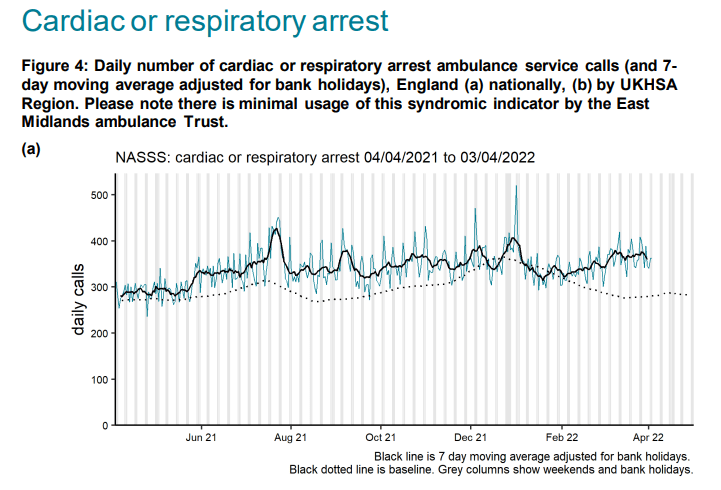
Similar to the Scottish data, during mid 2021 the 7 day average closely followed the black dotted baseline. However, from June it began to rise and stayed higher than average until December. Since February 2022 it has taken off again and is currently much higher than the baseline.
This is data for all ages and as we saw with the Scottish data, when broken down by age, the figures were much worse for the younger age groups. It would be interesting to see this English data also broken down by age.
Three discoveries that should make you think twice, or thrice about COVID vaccinations
By Meryl Nass, MD | April 7, 2022
I don’t write enough about the adverse events from COVID vaccines. The reason is that I like to be accurate, but most of the data on vaccine side effects is hidden from us. So while I have pointed out the many databases that FDA and CDC have available and are supposed to be using to assess vaccine safety, only 1 is publicly available: VAERS. Officially, it is the joint FDA-CDC Vaccine Adverse Event Reporting System. Steve Kirsch and Jessica Rose have done the best job analyzing the VAERS data, so I suggest you go to their substacks and read what they have to say.
Both FDA and CDC each have about ten other databases that taxpayers pay for, but most of them we never hear about. Here are the FDA databases:

Below, then-head of Immunizations at CDC, Dr. Nancy Messonier, told the public about the databases that would be used to assess COVID vaccines’ safety just before the rollout, on December 10, 2020.

Both agencies provided the public with promises of what these vaccine safety databases could provide. The databases FDA rents include more than 100 million Americans, for example. But since the rollout, the federal agencies have been almost silent on what they reveal.
However, yesterday I came across 3 very important items about COVID vaccine safety that I had not seen mentioned until now. Each one is an important, though limited, piece of the COVID vaccine safety puzzle–but together, they give you a very good idea of what we are all dealing with as we traverse this data desert, touching small bits of the elephant like the blind men, but never being able to grasp the picture in its entirety.
Item 1 was posted on the FDA website on July 12, 2021 with no fanfare. It revealed that yes, FDA was using its Medicare beneficiary database to look for potential vaccine adverse reactions, and it found four related to Pfizer’s vaccine, which is the most widely used COVID vaccine. FDA writes:
FDA has routinely been using screening methods to monitor the safety of COVID-19 vaccines and to evaluate potential adverse events of interest (AEI) related to these vaccines. One of these methods, called near real-time surveillance, detected four potential AEIs in the Medicare healthcare claims database of persons aged 65 years and older who had received the Pfizer/BioNTech COVID-19 vaccine. The four potential AEI are pulmonary embolism, acute myocardial infarction, immune thrombocytopenia, and disseminated intravascular coagulation. The screening methods have not identified these AEI after vaccination in persons 65 years and older who received the two other authorized COVID-19 vaccines…
These events have not been identified as safety concerns or signals in the CDC Vaccine Safety Datalink (VSD) or the Veterans Administration (VA) Healthcare data systems screening methods. The Vaccine Adverse Event Reporting System (VAERS), another government monitoring system, also has not identified any association between any COVID-19 vaccine and these AEI.
FDA continues to closely monitor the safety of the COVID-19 vaccines and will further investigate these findings by conducting more rigorous epidemiological studies. FDA will share further updates and information with the public as they become available.
If the vaccine caused blood clots and bleeding, as is suspected, these are exactly four diagnoses I would expect to see indicating vaccine injuries. The claim that FDA has not seen them in its other databases, including VAERS, is curious, because people who independently study VAERS have in fact reported higher rates of myocardial infarctions and pulmonary emboli.
Six weeks after FDA posted about these very serious warning signs, FDA issued a full, unrestricted license for Pfizer’s vaccine, the very one they were warning about. The FDA website where the above information is posted has never been updated, and FDA has not revealed what the last 8 months of “more rigorous epidemiological studies” show.
Item 2 is an academic paper published by the CDC in its own, non peer reviewed journal, the Morbidity and Mortality Weekly Report. It was written by CDC scientists with researchers at various sites that participate in a CDC-funded data collection on COVID.
The paper concludes that while myocarditis is known to occur after COVID vaccinations, it is more common after getting the disease COVID. This is an unusual claim, since myocarditis rates as high as 1 in 2000 males aged 18-24 have been reported after the second Covid shot, and no one has claimed that such rates apply after getting the disease.
So what did CDC do? It chose to examine this issue using a database that admittedly misattributed most vaccinations! CDC has access to everyone’s vaccination data and could easily have have used an accurate dataset, but chose not to. Instead, CDC admitted in the paper’s fine print that while 82% of Americans over age 5 have reportedly received at least one COVID vaccine, in the 15 million person dataset it used, only 28% were recorded as vaccinated. The only reasonable interpretation is that a large number of vaccinated individuals were incorrectly assigned to the unvaccinated category. It seems a case could be made that this is scientific fraud.
Item 3 came from the Pfizer documents that were released on April 1. Huge thanks to all the volunteers who have been digging through these documents to piece together the truth about the vaccines. Huge thanks also to the scientists and attorneys who had to file suit and win in court to force FDA to release them.
This information, I think, could be a gamechanger. It turns out that Pfizer had to hire 600 new full-time employees simply to process the adverse event reports that were coming in regarding vaccine injuries and deaths: 600 new hires in the first 2 1/2 months of the vaccine rollout. And Pfizer further said it planned to hire another 1800. Eighteen hundred more! Just to manage the paperwork resulting from its vaccine-caused carnage.
FDA knew. But FDA wanted it buttoned up for 75 years. CDC knew also, since the reports of deaths to VAERS for COVID vaccines exceed all death reports for the past 30 years, for all other vaccines, put together. Both agencies hid what they knew. CDC even played tricks with data to mislead us. Pfizer knew. DHHS must have known.
There is no Public Health without public honesty. Our public health agencies have become public trickery agencies. Why should anyone believe anything they say now? Why would anyone do what they recommend?
Featured Video

When Israel Is Mighty
or go to
Aletho News Archives – Video-Images
From the Archives
US murdering 1 million Iraqis is democracy, Iran giving yogurt to Iraq is “domination”
By Ali Salaam | American Herald Tribune | July 31, 2017
The New York Times, owned by the Zionist Jewish supremacist Ochs-Sulzberger family, has no problem with Iraqi suffering as long as Iran is not the one behind it.
The Iraq War was a genocide of the Iraqi people by Zionist supremacists in the Bush administration. Over 1 million innocent people were killed based on a lie. American soldiers died in an Israeli war and now an average of 22 soldiers commit suicide every day because their consciences cannot cope with the fact they committed crimes in an illegal war that served no purpose other than to benefit Israel, not America.
Benjamin Netanyahu, Prime Minister of the Zionist regime, once said “We are benefiting from one thing, and that is the attack on the Twin Towers and Pentagon, and the American struggle in Iraq.”
Paul Wolfowitz had his sights on Iraq since his time in the first Bush administration. Former Israeli official and Bush administration official Richard Perle had his eyes on Iraq since at least his authorship of the Clean Break white paper. The Zionist regime had their eyes on Iraq since the 1980s when strategist Oded Yinon wrote his white paper in support of dividing the Arab-Muslim world along ethnic and sectarian lines. The global Zionist lobby has had their eyes on Iraq since Theodor Herzl stated that Eretz Israel’s true borders go from the Nile River in Egypt to the Euphrates River in Iraq. … continue
Blog Roll
 Aletho News
- MEP blasts ‘Euro-Gestapo’ for lecturing Russia on democracy
- Syria May Send Troops to Saudi Arabia Amid War with Ansar Allah
- UK whines about losing billions to ‘Putin tax’
- Baghaei to Rubio: Distorted narratives cannot erase US record of broken commitments
- Houthis Don’t Have to Conquer Saudi Arabia to Make It Pay
- MOE: Nearly 22,000 Students and Education Workers Killed
- Guterres in Islamabad: Genocide, cowardice, and the cage of Imran Khan
- Johnson, Marandi say Yemen holds upper hand over Saudi Arabia
- False flags won’t save aggressors, Iran FM spokesman says
- The Makkah Pact Enters Into Force: The End of American Dominance or Its New Form?
- If Americans Knew
- Israel puts Gaza’s sick, injured, newborn in peril – Daily Update
- Report claimed Mark Levin used by Israeli government to influence Trump
- Over 2,000 Gazans have died awaiting medical evacuation amid Israel’s continued siege
- How a U.S. Diplomat Suppressed and Altered Reports Critical of Israel
- 5 Palestinians Die from Israeli Strikes in Gaza as Relentless Attacks Continue
- Report: Ceasefire Slows Killing but Leaves Devastation Intact
- Country Music Singer Zach Bryan Breaks Attendance Record at Robert Kraft’s Gillette Stadium While Wearing ‘Free Palestine’ Shirt for Second Night in a Row
- Three years of death and devastation: Israel’s war on Gaza in pictures
- Why Hamas believed the status quo was more dangerous than its 7 October gamble
- Debunking Israel’s latest list of ‘terrorist’ journalists in Gaza
- No Tricks Zone
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative

