The scandalous absence of child vaccine damage information
By Kathy Gyngell | TCW Defending Freedom | April 19, 2022
We have repeatedly referred at TCW to the studied silence of the mainstream media regarding the damage and fatalities associated with the Covid vaccines despite reported reactions (which may be only 10 per cent of the total), now standing at 1,480,307, and nearing the one and half million mark. Fatalities, too, continue their inexorable rise, a further sixteen deaths reported since the end of March, their total now 2,087. For full reports of vaccine adverse effects and events including 352 pages of specific reaction listings, see here.
What is worse, perhaps, than the MSM’s general state of denial is their unconcern about the shocking paucity of the child adverse reaction data published by the Medicines and Health products Regulatory Authority (MHRA). Yet under-18s have been actively encouraged to have the vaccine since the end of July 2021 in the absence of any long-term safety data and despite clear indications that younger ‘fertile’ age cohorts were proving more vulnerable in multiple respects to the vaccine. However no special monitoring system for children has been set up, or none that has been reported. Unlike its Yellow Card reporting involving adults, the MHRA does not break down the child numbers into specific adverse events, as though children were of less importance. As a result we have no way of knowing whether the reports relate to any major, life-changing side-effects such as Guillain-Barré syndrome (muscle weakness caused by the immune system attacking the body’s nerves) or Bell’s palsy (a type of facial paralysis) or to other serious side-effects reported by adults including seizures, nervous system disorders, deep vein thrombosis, menstrual disorders, and eye and ear disorders including blindness and deafness.
With the extension of the vaccine rollout to young children aged between five and 11 since the beginning of April, we have decided it is high time to highlight what is known and not known, what is reported and not reported, about the risk to children of this experimental gene therapy.
Nearly 3.5 million children (3,413,500) have already been injected, with a total dosage (1st, 2nd & boosters) of 5,626,100 jabs, and a total number of 3,735 adverse reaction Yellow Card reports. Data published by the MHRA on Thursday April 14 details:
· Pfizer – 3,400,000 children (1st doses) plus 2,000,000 second doses & 200,000 boosters resulting in 3,424 Yellow Cards
· AZ – 11,600 children (1st doses) plus 8,700 second doses & ‘extremely limited boosters’ resulting in 263 Yellow Cards – Reporting rate 1-in-44
Note: 1,500 doses (1,000 children – 1st doses) removed from last two weeks reporting
· Moderna – 1,900 children (1st doses) and 1,400 second doses and 2,500 boosters resulting in 24 Yellow Cards
Note: 200 children (1st doses) removed from last two weeks reporting
· Brand unspecified – 24 Yellow Cards
Unaccountably it appears that the number of 1st doses (1,000 for AZ and 200 for Moderna) and 2nd doses (500 for AZ) recorded has decreased since two weeks ago. Hence 1,200 children recorded as vaccinated two weeks ago are now missing. No explanation has been given for this. I understand that the MHRA is now on holiday for two weeks so we are unlikely to get any clarity on this until May.
Note too that AstraZeneca which is not recommended for under 18s appears to have been continued. MHRA reports to April 6 2022 show that 11,600 children (up from 11,496 last October) have received one or more doses of AstraZeneca, resulting in an increased Yellow Card adverse event reporting rate of 1 in 44 children (up from 1 in 49 last October). This, shockingly, is counter to the government’s own official guidance and evidence which has been available for patients and healthcare professionals, most recently updated on January 26 2022:
‘COVID-19 Vaccine AstraZeneca is not recommended for children aged below 18 years. No data are currently available on the use of COVID-19 Vaccine AstraZeneca in children and adolescents younger than 18 years of age.’ Yet the most recent MHRA publication says:
‘The safety and efficacy of COVID-19 Vaccine AstraZeneca in children and adolescents (aged <18 years old) have not yet been established. No data are available.’
So why and to which children were these doses given? To vulnerable children prior to the main rollout? And why second or booster doses? Furthermore, whoever they are, are the 263 adversely impacted children receiving adequate care and support? Are the other children who received the AZ vaccine being checked?
Myo/pericardial effects in children
The only specific adverse effects data that has been published for children is 73 cases of myocarditis and pericarditis (inflammation of the heart) in under-18s. This is worrying not least because of the rising and unexplained death toll in young men reported elsewhere in these pages, but also because it is now well-established that the likelihood of this reaction in young men is higher than their risk of myocarditis from Covid infection; a risk which the NHS has warned as being especially the case ‘in young men under the age of 40‘.
Other adverse effects
This still leaves the bulk of 3,735 Yellow Card Reports up to this week for under-18s uncategorised. Yet MHRA themselves state that ‘the experience reported in under-18s is similar to that identified in the general population’. If we take them at their word, extrapolating from the data published on suspected adverse effects in the adult population, children and young people, are experiencing a selection of the following:
· Lymph node pain and swelling
· Heart palpitations and fluttering
· Fever, chills, fatigue and malaise
· Ear pain, tinnitus and vertigo
· Nausea, vomiting and allergies
· Eye pain, swelling and photophobia
· Blurred vision and visual impairment
· Diarrhoea, abdominal pain and distension
· Lip, mouth and facial swelling
· Pain in arm, chest, bones and jaw
· Anaphylaxis
· Respiratory infection, influenza and herpes
· Joint and muscle pain, swelling and stiffness
· Muscle spasms and twitching
· Balance disorders and arthralgia
· Fainting and dizziness
· Facial palsy, headaches and migraines
· Skin sensations, burning and numbness
· Seizures and tremors
· Anxiety, depression and insomnia
· Confusion and disorientation
· Kidney pain and hair loss
· Breast pain and menstrual disorders
· Breathlessness, wheezing and coughing
· Sweating, blisters, rashes and itching
· Haemorrhages (all types) and nosebleeds
· Embolisms and thrombosis
Given the lack of information published as to the adverse effects experienced by the 3.4 million children injected thus far, we have to ask whether their consent was truly informed? The answer has to be no, it was not.
Worryingly there are a number of potential barriers to reporting adverse effects in children. These include:
· Child or parental failure to recognise symptoms as vaccine-related
· Fear of parents of not being believed or thought to be anti-vax or of ‘making a fuss’
· Lack of understanding of potential longer-term issues
· Healthcare professionals’ lack of awareness of vaccine adverse effects
· Young people not seeking help and support especially if they took the vaccine decision themselves
· Yellow Card system awareness and accessibility
Furthermore, if the 3,735 Yellow Card Reports for under 18s is less than 10 per cent of actual figures as the MHRA indicates may be the case, in the absence of long-term safety data, how can the child vaccine rollout possibly be justified, deemed safe or ethical? Why was post vaccine monitoring not insisted on?
This weekend the Sunday Times reported a scandal that Jeremy Hunt, the former Health Secretary, claimed to be worse than thalidomide. He was not however addressing the reckless child Covid vaccine rollout but a deeply shocking investigation into child deformities caused by an epilepsy drug still being given to pregnant women that should have been stopped years ago. Hunt said that while it was ‘never comfortable’ for governments to acknowledge such injustices, the state had a moral duty to the families. ‘It’s time the British state faced up to its responsibilities,’ he said. ‘Just as we eventually did to victims of the thalidomide scandal.’
These are words we need to hear him speak about the Covid vaccines.
I pray that he and this newspaper, which tenaciously and courageously fought for the victims of thalidomide, will not stay blind to the scandal that is happening on their watch; or let years go by before they retrospectively struggle to examine the multiplicity of harms, some of which we may not know till they reach maturity, that children have been needlessly subjected to by the experimental Covid vaccines.
Few Doctors Telling Truth About COVID Vaccines
By Joel S. Hirschhorn | April 19, 2022
Nearly all physicians work for corporations that require them to take COVID vaccine shots. Most will be reluctant to tell their patients about their vaccine doubts. Also, most do not have the time to study the medical literature about the many negative aspects of the vaccines. Now comes a survey with some interesting findings.
Levels of vaccine hesitancy among physicians seem higher than expected, with 1 in 10 primary care doctors not believing that vaccines are safe, according to a new survey.
Among 625 physicians, 10.1% did not agree that vaccines were safe; 9.3% did not agree that vaccines were effective; and 8.3% did not agree that they were important, Timothy Callaghan, PhD, of Texas A&M School of Public Health in College Station, and colleagues reported online in Vaccine.
The high proportion of hesitancy among primary care doctors “was certainly a surprise for us,” Callaghan said. “We thought it might be a very small proportion of physicians who hold hesitancy about vaccines given that we have lots of evidence of the safety and effectiveness of vaccines. [Talk about bias!] However, once we dug into the data, we found that concerns about vaccines in general were far more widespread in the physician population than we might have expected.”
Confidence in vaccines among physicians was still higher than in the general public, as were rates of COVID-19 vaccination, with only 5.2% still unvaccinated at the end of the survey in May 2021. But high levels of vaccine uptake among doctors could have more to do with employer regulations or perceived risks of their workplace environment, Callaghan said.
The research project was inspired by Callaghan’s own experience with one of his doctors who was not vaccinated and tried to dissuade Callaghan from COVID vaccination. Few of us have had that experience!
“It wasn’t my primary care physician, but another one of my doctors realized that I studied issues related to vaccine hesitancy, and over the course of multiple visits, tried to convince me that COVID-19 vaccines weren’t safe and weren’t worth it,” Callaghan said. “It made me question whether this was a one-off, or if we have an actual issue on our hands.”
Callaghan and colleagues conducted their survey from May 14 to May 25, 2021 among 625 physicians in family medicine, internal medicine, or general practice. They were asked how strongly they agreed with questions about safety, effectiveness, and importance of vaccines, among other factors.
Only 67.4% strongly agreed that vaccines are safe, just 75% strongly agreed they are effective, and only 76% strongly agreed they’re important, the researchers found. Good, but not good enough.
“As surprised as we were about the 1-in-10 piece, we were equally if not more surprised by the proportion of physicians strongly agreeing that vaccines in general are safe,” Callaghan said, anticipating that it would have been far higher. Guess there are doctors who see the truth.
In further analyses, Callaghan and colleagues found that higher levels of political conservatism were negatively and significantly associated with agreeing that vaccines are safe. In other words, the more conservative docs saw the truth. They also found those who had COVID-19 were significantly less likely to believe that vaccines are safe.
The team saw similar results for belief in vaccine effectiveness: physicians who were more liberal were more likely to strongly agree that vaccines are effective compared with those who were more conservative.
“Conservatives (in the public) with vaccine hesitancy, served by physicians who share their political views, may therefore miss out on opportunities to be presented with information about the benefits of vaccination; especially in rural areas where both hesitancy and self-identification with right-leaning political views are particularly high,” the researchers wrote. More pro-vaccine bias.
While political affiliation did appear to play some role in beliefs, Callaghan noted a wider problem that might be at play. “There’s not that much training on vaccines and vaccinology … in medical school,” he said. “Most medical students aren’t exposed to in-depth discussions of virology to have those strong opinions.”
“And given the clouded information environment that surrounded COVID-19 in particular, and increasingly, vaccines in general, it remains possible that [physicians] are just relying on what they’re hearing in the news and the misinformation that’s out there, as opposed to best scientific evidence,” he said. The bigger truth is that most docs do not spend time examining medical research data.
The survey also asked specifically about confidence in COVID-19 vaccines and found physician confidence split by vaccine type. While 68.7% were very confident in the safety of the Moderna vaccine and 72.7% were very confident in the safety of the Pfizer vaccine, only 32.1% were very confident in the safety of the Johnson & Johnson vaccine.
Dr. Joel S. Hirschhorn, author of Pandemic Blunder and many articles and podcasts on the pandemic, worked on health issues for decades, and his Pandemic Blunder Newsletter is on Substack. As a full professor at the University of Wisconsin, Madison, he directed a medical research program between the colleges of engineering and medicine. As a senior official at the Congressional Office of Technology Assessment and the National Governors Association, he directed major studies on health-related subjects; he testified at over 50 US Senate and House hearings and authored hundreds of articles and op-ed articles in major newspapers. He has served as an executive volunteer at a major hospital for more than 10 years. He is a member of the Association of American Physicians and Surgeons, and America’s Frontline Doctors.
COVID Vaccine Mandate for Pilots Violates Federal Law, Puts Passengers at Risk, Citizen Group Warns
By Michael Nevradakis, Ph.D. | The Defender | April 18, 2022
The Federal Aviation Administration’s (FAA) COVID-19 vaccine mandate for pilots violates federal regulations and places pilots and passengers at risk, according to a letter from the California-based Advocates for Citizens’ Rights.
The letter, only recently made public, was hand-delivered in December 2021 to then-director of the FAA, U.S. Department of Transportation, U.S. Department of Justice (DOJ), and CEOs and legal counsel of major U.S. air carriers (American Airlines, Alaska Airlines, Delta Airlines, Southwest Airlines and United Airlines).
It includes data showing pilots across the aviation industry — including commercial, military and general aviation pilots — face increased health risks from the vaccines due to the unique nature of their profession.
The letter also states that a significant number of vaccine injuries and adverse effects involving pilots have been recorded, and in some instances have forced pilots to stop flying.
The letter claims:
- Federal regulations that prohibit pilots who have received non-FDA-approved medical products, such as COVID vaccines, from flying are being violated.
- Vaccinated pilots potentially are flying with abnormal health conditions that may be exacerbated by flying at high altitudes. These include heart damage and blood clotting, which could lead to stroke or cardiac arrest.
- Some pilots have suffered death and serious injury following COVID vaccination.
- The federal government is aware of the issues associated with the vaccines, based on complaints filed with government agencies.
- The health risks to pilots from the vaccines may lead to a catastrophic event such as a plane crash, with multiple fatalities and significant legal and monetary liabilities for the government, insurers and airlines.
The letter was co-signed by a series of prominent figures, including:
- Robert F. Kennedy, Jr., chairman and chief legal counsel of Children’s Health Defense (CHD)
- Mary Holland, CHD general counsel
- Reiner Fuellmich, attorney and co-founder of the People’s Court of Public Opinion, which launched an international grand jury investigating COVID-related restrictions and mandates
- Several other doctors, medical practitioners and lawyers.
In an interview with The Defender, Advocates for Citizens’ Rights attorney Leigh Taylor Dundas, lead signatory of the letter, said products authorized under Emergency Use Authorization (EUA) are not fully approved by the FDA, and under EUA rules cannot be mandated.
“Our government has a long history, even with approvals and releases of products … of getting it wrong,” Dundas said. “Witness thalidomide, DDT, all sorts of things like that.”
“As a former environmental attorney and now staunch defender of basic human rights and civil liberties … I get contacted a fair amount by concerned individuals from all walks of life,” Dundas said.
“I was aware from things I had been hearing at conferences … that the inoculation was presenting severe and sometimes fatal issues to those who took it.”
Dundas said:
“I became aware that certain military personnel who were high-ranking surgeons within the U.S. armed forces were not just anecdotally becoming aware that pilots were having severe incidents of injury, but also that statistically that was being borne out by way of the database.
“At the same time, I was becoming aware of similar incidents in the civilian pilot population. So the combination of the two made me sort of pull the string and try to determine if not only was the vaccination causing an increase generally of disease and fatalities among those who took it, but if perhaps [these adverse reactions were] due to the unique combination of pilots being at altitude for long periods of time.”
Dundas said it appeared from the anecdotal, subjective data she was hearing and raw statistical data coming out of the DOD databases that these military doctors had access to — that the pilots were uniquely likely to be suffering ill effects from the vaccines.
Significant health risks for pilots
The letter, along with the accompanying documentation, references numerous instances of adverse reactions sustained by pilots and other health risks they face as a result of the COVID vaccines.
The letter quotes flight surgeon and aerospace medicine specialist Dr. Theresa Long and cardiologist Dr. Peter McCullough, a cardiology consultant for the FAA.
Long and McCullough, who signed the letter, said:
- “The risk of ‘post-vaccination myocarditis [is] not trivial.’
- “The ‘aviation population is comprised of individuals with demographics that the [U.S. Centers for Disease Control and Prevention (CDC)] and FDA established (on June 25, 2021) was at greatest risk for developing post-vaccination induced myocarditis.’”
Cody Flint, also a signatory of the letter, described his experience. Flint, based in Cleveland, Mississippi, is an agricultural pilot with 10,000 hours of flight time. He testified at a Nov. 2, 2021 U.S. Senate hearing on COVID vaccine injuries about the adverse effects he sustained.
Portions of Flint’s testimony were quoted in the letter, including:
“I have been very healthy my whole life, with no underlying conditions.
“I received my first dose of the Pfizer COVID vaccine on Feb. 1 [2021]. Within 30 minutes, I developed a severe stabbing headache, which later became a burning sensation in the back of my neck.
“Two days after vaccination, I got in my airplane to do a job that would only take a few hours. Immediately after taking off, I knew that something was not right with me. I was starting to develop tunnel vision, and my headache was getting worse.
“Approximately two hours into flying, I pulled my airplane up to turn around and felt an extreme burst of pressure in my ears. Instantly, I was nearly blacked out, dizzy, disoriented, nauseous and shaking uncontrollably. By the grace of God, I was able to land my plane without incident – although I do not remember doing this.
“My initial diagnosis of vertigo and severe panic attacks – although I’ve never had a history of either of these – was later replaced with left and right peri-lymphatic fistulas, Eustachian tube dysfunction and elevated intracranial pressure due to brain swelling.
“My condition continued to decline, and my doctors told me that only an adverse reaction to the vaccine or a major head trauma could have caused this much spontaneous damage.
“I’ve had six spinal taps over eight months to monitor my intracranial pressure, and two surgeries, eight weeks apart, to repair the fistulas. I have missed nearly an entire year of my life … I don’t know if I’ll ever be able to fly again.
“… the FDA, CDC, and NIH [National Institutes of Health] refuse to acknowledge that real lives are being absolutely destroyed by this vaccine.”
The letter also refers to the case of American Airlines pilot Wilburn Wolfe, who suffered a major seizure following his COVID vaccination. Wolfe died, though not while he was on duty.
It also cites the case of a Canadian flight in December 2021 that was forced to divert back to the airport shortly after takeoff because the pilot, who was recently vaccinated, passed out.
In other testimony from the November 2021 Senate proceedings, Long said the U.S. military was aware of the risks to its pilots, but chose to proceed with its vaccine mandate for service members.
Long said:
“Last May [2021], I attended the Senior Preventative Leadership Program for the Army. When we were given an opportunity to ask the senior leaders questions, I simply asked: ‘So we skipped two years of Phase 2 trials, and three years of Phase 3 trials? We only lost 12 active-duty soldiers to COVID — yet we’re going to risk the health of the entire fighting force, on a vaccine we only had two months of safety data on?’
“The response was: ‘You’re damn right, Colonel. And you’re going to get every soldier you can to take the vaccine so I can get enough data points to determine if the vaccine is safe.’”
Long said numerous soldiers told her about “threats and intimidation” they faced to get the vaccines that were still under the EUA. She said the Army Public Health Command was “not tracking, tracing or monitoring adverse events.”
Additional testimony from Long, cited in the letter, concerned military pilots she treated for vaccine injuries:
“I saw five patients in clinic, two of which presented with chest pain, days to weeks after vaccination, and were subsequently diagnosed with pericarditis …
“The third pilot had been vaccinated and felt like he was drunk, chronically fatigued within 24 hours after vaccination, [stating] he drank a lot of coffee to ‘try and wake himself up’, and continued to fly, until he realized the problem wasn’t going away.
“After I reported to my command my concerns that — in one morning — I’d had to ground 3 out of 3 pilots due to vaccine injuries, the next day my patients were canceled, my charts were pulled for review and I was told that I would not be seeing acute patients anymore, just healthy pilots there for their flight physical.”
The letter referenced 10 reports from the Vaccine Adverse Event Reporting System (VAERS) involving pilots who sustained severe injuries and side effects following the COVID vaccine. According to the letter, these 10 examples are a mere sample of the total number of injuries reported by pilots.
These injuries and symptoms included:
- Heart attacks
- Atrial fibrillation
- Pericarditis
- Brain swelling
- Elevated intracranial pressure affecting the spinal cord and brain stem
- Sub-arachnoid hemorrhages (brain bleeding)
- Blindness
Statements from the VAERS reports include descriptions of vaccine injuries reported by pilots.
One report (VAERS ID: 1026783-1) stated:
“The physician determined … I had an allergic reaction to the Pfizer COVID vaccine [that] severely increased the pressure in my spinal cord and brain stem. That pressure causes my vision problems and ultimately ruptured my left inner ear, breaking off several crystals in the process. I cannot fly with this condition.”
Another pilot stated (VAERS ID: 1743012-1):
“Symptoms began almost immediately [post-vaccination] as constant dizziness, body aches, overall weakness. Two months later I woke up with chest pain and difficulty breathing … I was diagnosed with inflammation of the heart cavity and pulmonary arteries … I was later diagnosed with vasculitis, specifically aortitis.
“I was completely healthy prior to the vaccination and there is not a single member of my family with any of the listed conditions … [I am] awaiting a medical evaluation … to determine if I’m allowed to remain on flying status and in the military.”
Another report (VAERS ID: 1768479-1) submitted by a pilot described the following:
“[The] morning following injection, I experienced extreme dizziness and brain discomfort. Dizziness was bad enough to make walking difficult and even created motion sickness … heights of about 10 feet give bad vertigo.
“I am a pilot and aircraft mechanic and this creates an issue working on jets … brain fog is also long-lasting still [sic] and makes mental clarity difficult, which was never an issue until the day after the shot.
“My heart has created irregular heart rhythms, I have physical stress and tire easily and my muscles will shake and twitch after minimal effort … my cognitive skills seem to have diminished from the lasting brain fog.”
Another pilot reported (VAERS ID: 1358033-1): “2 days after second shot, blood clot in left arm. Hit while walking in my home. Could not lift my arm. 5 days later heart attack. Pilot with EKG yearly. Last EKG less than one month from [sic] my heart attack on April 29, 2021.”
And one pilot reported (VAERS ID: 1376453-1): “Severe vertigo experienced for four days and counting … as a professional helicopter pilot, I cannot perform my job with these symptoms.”
In one report (VAERS ID: 1702509-1), submitted by a doctor, a pilot who was also a triathlete experienced pericarditis, chest pressure and irregular heartbeat after vaccination, with pain that “radiated to [the] jaw and neck,” “pressure in the chest” and difficulty walking, despite no prior heart problems.
Another report (VAERS ID: 1245452-1) submitted by a doctor described how a 37-year-old pilot who received the Moderna vaccine, and who had no prior medical history of heart conditions, sustained atrial fibrillation and a decrease in thyroid hormones, leading to him being kept off duty.
In one case (VAERS ID: 1388581-1), a doctor who is also a commercial airline pilot reported “subarachnoid hemorrhage” and “associated nausea, vomiting and photophobia.” According to the VAERS report, the doctor “remains off work pending FAA evaluation.”
This sampling of reports from VAERS is likely only the tip of the iceberg, according to Dundas, who said:
“It’s known that there’s a 1% reporting rate to VAERS, that there’s 99% underreporting. So if you looked at what was already in there, within a few months of this [vaccine] being rolled out and mandated to the pilots, you rapidly did the math … and realized that we are absolutely destroying the health of our pilots.”
The military’s own database, Defense Medical Epidemiological Database, found similar instances of injuries, Dundas said:
“When you looked at the data that these high-ranking U.S. military doctors were seeing, what you rapidly realized is that in all of the years prior to 2021, for the five years preceding that point in time, the total cumulative number of incidents of disease and injury in this database were 1.7 million every single year.
“Then, in January 2021, the U.S. military decided to essentially mandate that their service members take the vaccine, and it was fortuitous that they did it in January; [this] made for a very clean cut in terms of analyzing the data set.
“Within the first nine months [of 2021], the total number of incidents of disease and injury in the U.S. armed forces jumped from a very stable baseline of 1.7 million per year … to almost 22 million … and the year wasn’t even over. That was just the first three quarters of 2021.
“[These were] injuries where military pilots were walking off of flight vehicles, clutching their chests, complaining of chest pain. The military refused to take that seriously and ordered the doctors who would normally be sending these soldiers for cardiac MRIs and EKGs to basically write it off as anxiety or some such [condition].”
Josh Yoder, a pilot with a major commercial airline, Army combat veteran and former flight medic, co-founded the U.S. Freedom Flyers (USFF), an organization opposing vaccine mandates for pilots.
In an interview with The Defender, Yoder said vaccine injuries among airline crews are “extremely common” and are being “actively covered up” by airline companies and the FAA.
Yoder told The Defender :
“U.S. Freedom Flyers receives almost daily communication from airline pilots who are flying with symptoms such as chest pain and neurological conditions post-vaccination. Most of them are afraid to come forward and seek medical attention for fear of losing their flight medicals.
“USFF has documented cases of blood clots, strokes, cardiac arrest, unconsciousness and sudden death among airline professionals which have been medically linked to the COVID-19 vaccinations.”
FAA ‘betting the farm’ a major catastrophe won’t occur
Dundas told The Defender the FAA is aware of these risks associated with the vaccines but is sweeping the problem under the rug.
She said the agency may be hoping “redundancy” in the cockpits of commercial airliners — meaning that two pilots are jointly in charge of flying the aircraft — will be enough to stave off a potential disaster.
“Where that analysis breaks down is during takeoff or landing,” Dundas said, “because during takeoff and landing, you’re not on autopilot. You’ve got both pilots fully engaged, but one of the pilots actively has his hands on the joystick and the controls.”
She added:
“If you’re 300 feet or 1,000 feet above, coming in for a landing … you’ve now got a massive gross muscle unit seizure as [the pilot’s] hand is on the yoke, that’s going to dip a wing and you’re going to have an entire plane full of people cartwheeling down the runway … probably with a mass fatality event at the end of the line.
“Even if you’re betting the farm, as I believe the FAA right now is, because they don’t have a choice, the water is already under the bridge on pilot redundancy. All it takes is bad timing for one of these events to occur on takeoff or landing. And you’ve got an unrecoverable airplane, [a] fatal crash, which the Department of Justice frowns upon.”
Yoder, also addressing this risk, said:
“Pilot redundancy is a critical component to aviation safety. The topic of adverse vaccine reaction and pilot redundancy is a complex one that requires in-depth analysis which the FAA has never studied.
“Critical phases of flight such as take-off or landing pose the greatest risk to passengers, should that be the moment a pilot experiences known side effects of these inoculations, such as blood clots, stroke, cardiac arrest or sudden death, which could lead to an unrecoverable event.”
FAA, airline industry violating federal regulations
In addition to numerous documented instances of pilots sustaining significant injuries and side effects — or even dying — as a result of the COVID vaccines, the letter also indicates the vaccination itself, let alone the vaccine mandates, may be in violation of federal regulations.
Specifically, the letter accuses the FAA, and the aviation industry, of:
“ … putting both pilots and the general public at risk of death and/or serious injury by operating in contravention of Title 14 of the Code of Federal Regulations, §61.53, and related guidance which together operate to disallow medical clearance of pilots who have injected or ingested non-FDA approved products — like the COVID-19 inoculation.”
The letter goes on to clarify this clause in the federal regulations prohibits aviation medical examiners from issuing medical clearances to pilots who use non-approved medical treatments, such as those that are being administered under an EUA instead of full FDA approval, and new medications fully approved by the FDA less than 12 months prior, stating that the FDA:
“ … generally requires at least one year of post-marketing experience with a new drug before consideration for aeromedical certification purposes.
“This observation period allows time for uncommon, but aeromedically significant, adverse effects to manifest themselves…”
The letter further quotes the federal regulations as stipulating:
“[N]o person who holds a medical certificate issued under part 67 of this chapter may act as pilot in command, or in any other capacity as a required pilot flight crewmember, while that person … [is] receiving treatment for a medical condition that results in the person being unable to meet the requirements for the medical certificate necessary for the pilot operation.”
As stated in the letter:
“[P]ut simply, any pilot flying right now who has been vaccinated in the United States has almost certainly NOT [emphasis original] received an FDA-approved vaccine …
“And even were such pilots to have received an FDA-approved vaccine, under relevant federal regulations, the pilots should still not be flying for 12 more months …
“The reason for this cannot be overstated: history and common sense evince that significant time must elapse post-FDA approval to ensure that new medical products do not end up causing adverse effects (as did Thalidomide and glyphosate).
“This is particularly true when the individuals who are receiving such new, experimental medical products are spending significant amounts of time at high altitude, and are in control of large vehicles carrying hundreds of other passengers, who could all die or be severely injured should the operator suffer an adverse health event.”
As previously reported by The Defender, and as outlined in the letter, none of the COVID vaccines currently available and being administered in the U.S. have received full FDA approval.
“We’ve got the FAA, a federal regulatory body, that is charged with protecting the safety of the flying public, as well as pilot safety, ignoring their own rule and the guidance on it,” Dundas said.
“Here, we’ve got an inoculation that is wholly unapproved, at least in the U.S., and yet we’ve got major carriers … who are not just ignoring this rule, but mandating their pilots to take this. And we’re seeing hellacious, horrifying results,” she added.
Dundas said the letter clearly warns the government and airlines of the legal and financial liabilities they would face should an airline disaster occur that is traced back to an adverse vaccine-related event suffered by a pilot — especially as it would be on the record that these entities have been made aware of such a risk.
As legal precedent, she cited a $2.5 billion fine levied by the DOJ in January 2021 against Boeing for “fraud conspiracy” involving safety issues with the 737 Max airplane, stemming from Boeing’s concealment from regulators of potential safety issues involving that model of aircraft.
The settlement included payments to the families of passengers who were killed in crashes involving the 737 Max.
Dundas likened the vaccine injury data involving pilots to the internal 1977 Ford Motor Company “smoking gun” memo that revealed the company was aware of safety issues with the Pinto model of automobiles but considered it more cost-effective to pay off future victims than to issue a recall and rectify the problem.
“Essentially what I was doing with the way I crafted the letter was … I was putting all the players in the industry, the regulator, the airline companies and the insurers for the companies, on notice that you probably have a problem here based on the numbers [of adverse vaccine events affecting pilots] that we are seeing,” Dundas said.
The letter provides an estimate of the likely amount of compensation that would result from a hypothetical accident if it could be traced back to an issue the airlines and regulators were aware of: $2 million to $3 million per person.
This amount, according to Dundas, would be “separate from punitive [actions], from fines assessed by the DOJ.”
Did letter cause FAA director to resign?
In February, then-FAA director Steve Dickson suddenly announced his resignation, effective March 2022, claiming it was “time to go home” to his family.
Dickson, however, had previously faced controversy. For instance, during his confirmation as FAA director, allegations arose that during his previous tenure overseeing the pilots of Delta Air Lines, a Delta pilot was grounded in 2016 after she raised concerns regarding the airline’s approach to managing safety risk.
According to Yoder, the real reasons for his resignation may have had less to do with a desire to spend more time with his family and more to do with the hand-delivered letter he received in December 2021.
“Dickson’s resignation came on the heels of the tremendous pressure being applied to the agency via Leigh Dundas’ FAA letter, along with back-channel communication and media attention from [the] U.S. Freedom Flyers,” Yoder said.
Dickson’s promotion of unapproved experimental vaccines for pilots, which violates the FAA’s own guidance, caused a dangerous situation for not only pilots but also the flying public, Yoder said.
“Documented cases of pilots experiencing severe adverse reactions in flight accrue daily, thanks to an inept response from the FAA,” he said. “Internal reports from FAA employees reveal a scandal-ridden agency which needs to be destroyed and rebuilt from the ground up.”
“The FAA’s primary charter is safety and they have failed miserably by approving experimental vaccines for pilots with zero long-term safety studies.”
According to Yoder, the FAA, even following Dickson’s resignation, does not appear to have taken concrete actions in response to the letter.
“Rather than being proactive, the FAA and the airlines have chosen to ignore a prominent passenger safety issue,” Yoder said.
“Historically, it’s taken a fatal crash or series of near misses to execute change within the agency. Fundamental change to safety policy within the FAA is typically written in blood,” he said.
According to Dundas, a recent spate of widespread flight cancellations and protracted delays in late 2021 and up to the present — frequently blamed by airlines on such factors as poor weather — are in fact connected to pilot action in relation to the vaccine mandates, for two reasons: opposition to the mandates, and an abundance of caution by pilots who call in sick at the first sign of any symptoms of illness:
“I think it’s twofold, and I think you’re seeing two things and they’re very logical,” Dundas said, noting that pilots, along with certain other transportation employees, are technically not allowed to go on strike without first exhausting their collective bargaining remedies. That’s the federal law that’s been in existence for decades.
“But this is a cat of a different color,” Dundas said. “You are mandating, against other federal law … an inoculation that you’re not allowed to mandate, and it’s likely unconstitutional.”
“So you have a lot of sectors in transportation that are really not happy saying get the jab, get the jab or your job is going goodbye,” she said.
Dundas added:
“What you saw … were segments of these transportation sectors saying, ‘you know what, we operate heavy machinery and we are required as well by rule and law in many cases to not operate these large pieces of equipment if we are remotely under the weather.’
“So, I think you saw a convergence of two variables. I think you saw pilots who were unhappy at being made to work in unsafe working conditions … in conjunction with a pilot population that was getting now not just the first shot, but the second shot and/or the third shot and a cumulative consequence and concatenation of adverse health events.
“[T]hey [the pilots] are, in many cases, highly educated, caring human beings, [who] wake up in the morning and go, ‘You know what, I’m not 100%, I’m not fit to fly, I’m going to call out sick because I don’t want to take other people down with me if I’m about to have a stroke.’”
Dundas said a recent flight of hers from Salt Lake City was delayed for almost a full day following an adverse event affecting one of the flight attendants scheduled to work on that flight.
Dundas also cited conversations with pilots who told her “they wanted no part of the mandate.”
According to Dundas, the reasons for their opposition were described in the following terms:
“[W]e see our colleagues dying and or stroking out or having cardiovascular events that they are not recovering from.
“And so, we quit rather than sacrifice our health or possibly our lives. And now we’re flying charters [private aviation] where [COVID vaccination] is not a mandate, it’s not required.”
Letter calls on FAA, airlines to take immediate action
The letter from Advocates for Citizens’ Rights calls for immediate action by federal authorities and air carriers, including:
- Medically flagging all vaccinated pilots.
- Adaptation, on the part of the FAA, of a screening program requiring all vaccinated pilots to undergo medical recertification, including D-Dimer, Troponin, and EKG tests, as well as cardiac MRIs, with medical clearance issued to vaccinated pilots only if they present “a clean bill of health on ALL [emphasis added] tests.”
- Medically decertifying and grounding any pilot who fails one or more of the aforementioned tests, or who otherwise displays symptoms of possible blood clotting issues or myocarditis; re-testing these pilots at six-week intervals until they return to a medically acceptable condition.
- Allowing commercial aircraft to be operated only by pilots who can show a clean medical examination undertaken a minimum of five days after each COVID vaccination and booster shot, stating that “the current FAA wait time of two (2) days is insufficient to detect a significant number of blood clotting and myocarditis cases (which are manifesting more than 47 hours post-inoculation).”
- Immediate investigation, on the part of the FAA, of all commercial air carriers and all insurance companies providing coverage to commercial airlines, regarding the application of federal do-not-fly regulations.
- Creation, by the FAA, of “a database to track pilot adverse events in a manner similar to VAERS,” stating the likelihood that “medical adverse events post-vaccination in pilot populations are occurring at greater rates than have been tracked or monitored in either civilian or military populations …”
“[A]ny in-house counsel, any CEO, any insurance company number-cruncher, any airline regulator who reads this [letter] is going to be nothing if not clear about the fact that … there is a problem brewing,” Dundas said.
“Right now, they have completely abandoned their duty to both the pilot population and the American flying population by allowing carriers to mandate a non-FDA-approved medical intervention, in violation of their own regulations and guidance,” she added.
Yoder expressed his unease with the current level of safety of air travel as a result of the vaccine mandate for pilots, stating that passengers are taking a risk by flying.
“Every time a passenger flies with a fully vaccinated crew, they are accepting a predictable risk that their pilots have been injected with an inoculation which has known side effects of blood clots, strokes, myocarditis, all of which can lead to cardiac arrest, incapacitation and sudden death,” he said.
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
MIT’s Dean of Science responds to me: She’s NOT interested in looking at the vax safety data!
She has intellectual curiosity in all areas of science… except the vaccines

Steve Kirsch with MIT Dean of Science Nergis Mavalvala taken April 15, 2022 at MIT breakfast in Palo Alto
By Steve Kirsch | April 15, 2022
Summary
The Dean of Science at MIT believes open discussion to resolve differences of scientific opinion should be encouraged. That’s the good news.
However, when I asked her whether she would publicly call for such a discussion for the vaccines, her answer was “No.” That’s the bad news.
I also asked her if I could show her data that would change her mind. Her answer was, “No.”
This is an important issue; it is an issue that affects the health of every MIT student, staff, and faculty member. She knows that there are two legitimate sides of this issue because she knows that at least one MIT faculty member agrees with me that the COVID vaccines are dangerous. Yet open discussion on this is forbidden at MIT. They simply are not interested in hearing from anyone with any credentials (such as my colleagues) who is able to challenge their policies.
Dean Mavalvala should be actively facilitating the resolution of this important issue by calling for an open discussion. Instead, she is stonewalling and hoping it will go away. She’s wrong. It won’t.
My meeting with Dean Mavalvala
I was able to speak personally to the Dean of Science at MIT today thanks to an MIT breakfast scheduled 10 minutes from my home.
As you can see from the photo above, she’s fully bought into the mainstream narrative that masks work even though the science says they don’t work at all (and it isn’t even a close call). So I didn’t think my conversation would go that well. I was right.
I started off asking her why nobody at MIT would sponsor my talk. She said that the faculty sponsor must be both familiar with and supportive of the body of work.
OK, so that’s actually a reasonable response. No objection from me.
She also knew that Professor Retsef Levi had agreed to sponsor my talk on the MIT campus. But it wasn’t MIT who located Professor Levi. I was the one who found Professor Levi. He subscribes to my Substack and saw my frustration and reached out to me.
Professor Levi is a hero… one of the few (perhaps only) MIT faculty members who independently looked at the data and came to the same (obvious) conclusion that the vaccines were bad news. All of his attempts to persuade other MIT faculty members to look at the underlying data were unsuccessful. So now I don’t feel so bad. It’s not just me. People just don’t like to be shown they are wrong…especially on something that is life threatening.
I asked Dean how I could convince her that the MIT policies on the vaccine and masking were wrong. She replied that science advances through peer-reviewed research.
I said sure, but that process has been corrupted. She agreed with that but said that’s the way it is.
She was not interested in looking at any data that would challenge her beliefs that the vaccines are safe and effective
Next, I asked if I could meet with her to share the data showing the vaccines are unsafe. She said she was not interested in that because that isn’t her field.
That’s interesting because right after our conversation, she gave a talk about how she is fascinated by all areas of science and loves her job as Dean since she gets to learn about all the cool stuff going on at MIT.
Yet she is not interested in seeing data that challenges her beliefs that affect everyone at MIT, and that has likely caused injury and perhaps death of MIT students, staff, and faculty members. So her intellectual curiosity basically stops at the point that I challenge her strongly held beliefs.
I said that it is really important that there should be an OPEN discussion between the different points of view on the vaccine. She agreed.
She then gave her talk.
After the talk, I asked her if she would “walk the talk.” Specifically, would she publicly call out the “experts” who refuse to be challenged to have an open discussion with those who have differing views?
Her answer was “no” she wouldn’t call for this because she thinks the vaccines are safe.
I pressed her on this. I believe that her role as Dean of Science at MIT includes championing science in public policy. When public policy is based on bad science, all our science leaders should be speaking out about that. At that very instant, she and her handlers insisted that “she had to leave” before she could answer my question.
So I then sent her the following email offering to finish the conversation.
Dean Mavalvala,
I’m sorry you were rushed at the end and we didn’t have time to continue our conversation.
This is important to resolve as we believe that over 100,000 Americans have been killed by the vaccine and we have 10 different ways to show that. If we are right, the vaccines should be immediately stopped and not mandated at MIT.
I would like to finish our conversation on a zoom call. It would take less than 5 minutes.
I think you have a responsibility to call for the right thing which is an open discussion between the two sides. You agreed this was the right thing to do before your speech.
This isn’t going to be resolved by “peer reviewed science” since that process has been corrupted (which you acknowledged). Also, resolution of differences through publication of peer reviewed studies is a laborious, time consuming process that has been corrupted.
It’s important to have the disagreements over the vaccine resolved ASAP as a huge number of Americans refuse to be vaccinated. Are they justified? It’s a matter of great public concern.
Open discussions are a faster, more efficient way to resolve such differences. This is especially important when we are in a state of emergency.
For example, in less than 2 hours, we were able to resolve all of our issues with the Bangladesh mask study due to the interactive nature of the discussion. In just 2 hours, it became clear to any objective viewer that the study failed to show masks worked. This would have taken years to resolve via peer review since there would be conflicting papers.
In addition, science is supposed to encourage resolution of differences through discussion and debate rather than censorship.
I note that the scientists who disagree with the mainstream narrative WANT an open discussion/debate on the key issues.
Yet those who claim the vaccines are safe and effective WANT censorship and REFUSE to be held accountable.
For example, this happened in Canada where 3 top Canadian scientists asked for a discussion with Canada’s health authorities. The authorities did not show up at the table. They sent no one. How do we resolve our differences when the other side is afraid to show up at the table?
As Dean of Science at MIT you should be speaking out publicly against the censorship of scientists because you should be a defender of Science. Similarly, I believe you should call for those who promote the mainstream narrative on vaccine safety to accept challenges from legitimate qualified scientists. You could say this is not your role, but the fact is that no other prominent person is stepping up to the plate to do this. As a defender of science, it is your responsibility to step in and make things right, don’t you think? If not, who will?
-steve
I will let you know if I hear back. Don’t hold your breath.
If you know anyone at MIT, be sure to share this article with them.
More Than 1 Million COVID Vaccine Injuries, Nearly 27,000 Deaths Reported to VAERS: CDC Data
By Megan Redshaw | The Defender | April 15, 2022
The Centers for Disease Control and Prevention (CDC) today released new data showing a total of 1,226,314 reports of adverse events following COVID vaccines were submitted between Dec. 14, 2020, and April 8, 2022, to the Vaccine Adverse Event Reporting System (VAERS). VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
The data included a total of 26,976 reports of deaths — an increase of 277 over the previous week — and 219,865 serious injuries, including deaths, during the same time period — up 2,564 compared with the previous week.
Excluding “foreign reports” to VAERS, 805,921 adverse events, including 12,471 deaths and 79,811 serious injuries, were reported in the U.S. between Dec. 14, 2020, and April 8, 2022.
Foreign reports are reports foreign subsidiaries send to U.S. vaccine manufacturers. Under U.S. Food and Drug Administration (FDA) regulations, if a manufacturer is notified of a foreign case report that describes an event that is both serious and does not appear on the product’s labeling, the manufacturer is required to submit the report to VAERS.
Of the 12,471 U.S. deaths reported as of April 8, 17% occurred within 24 hours of vaccination, 21% occurred within 48 hours of vaccination and 59% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 564 million COVID vaccine doses had been administered as of April 8, including 334 million doses of Pfizer, 212 million doses of Moderna and 19 million doses of Johnson & Johnson (J&J).
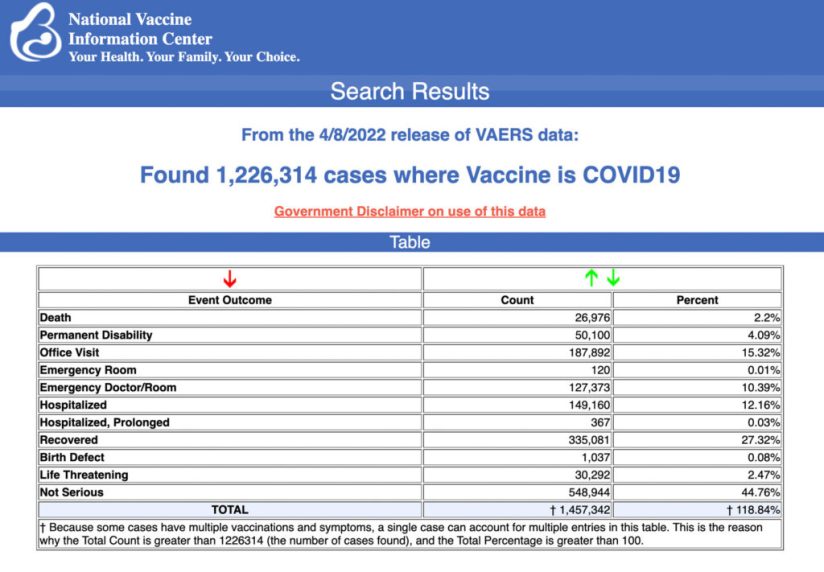
Every Friday, VAERS publishes vaccine injury reports received as of a specified date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed.
Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
U.S. VAERS data from Dec. 14, 2020, to April 8, 2022, for 5- to 11-year-olds show:
- 10,216 adverse events, including 242 rated as serious and 5 reported deaths.
- 18 reports of myocarditis and pericarditis (heart inflammation).
The CDC uses a narrowed case definition of “myocarditis,” which excludes cases of cardiac arrest, ischemic strokes and deaths due to heart problems that occur before one has the chance to go to the emergency department. - 39 reports of blood clotting disorders.
U.S. VAERS data from Dec. 14, 2020, to April 8, 2022, for 12- to 17-year-olds show:
- 31,048 adverse events, including 1,792 rated as serious and 44 reported deaths.
- 67 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases attributed to Pfizer’s vaccine.
- 651 reports of myocarditis and pericarditis, with 639 cases attributed to Pfizer’s vaccine.
- 166 reports of blood clotting disorders, with all cases attributed to Pfizer.
U.S. VAERS data from Dec. 14, 2020, to April 8, 2022, for all age groups combined, show:
- 20% of deaths were related to cardiac disorders.
- 54% of those who died were male, 41% were female and the remaining death reports did not include the gender of the deceased.
- The average age of death was 73.
- As of April 8, 5,404 pregnant women reported adverse events related to COVID vaccines, including 1,6936 reports of miscarriage or premature birth.
- Of the 3,647 cases of Bell’s Palsy reported, 51% were attributed to Pfizer vaccinations, 40% to Moderna and 8% to J&J.
- 860 reports of Guillain-Barré syndrome, with 42% of cases attributed to Pfizer, 30% to Moderna and 28% to J&J.
- 2,373 reports of anaphylaxis where the reaction was life-threatening, required treatment or resulted in death.
- 1,671 reports of myocardial infarction.
- 13,755 reports of blood-clotting disorders in the U.S. Of those, 6,169 reports were attributed to Pfizer, 4,911 reports to Moderna and 2,654 reports to J&J.
- 4,124 cases of myocarditis and pericarditis with 2,531 cases attributed to Pfizer, 1,402 cases to Moderna and 181 cases to J&J’s COVID vaccine.
Woman develops fatal brain disease after second Moderna dose
Carol Beauchine died from sporadic Creutzfeldt-Jakob Disease (CJD), a rapidly evolving, fatal degenerative brain disorder she developed after her second dose of Moderna’s COVID vaccine.
In an exclusive interview with The Defender, Carol’s son, Jeffrey Beauchine, said it was excruciating to watch his 70-year-old mother — who was healthy until she got the vaccine — die from a disease he believes the vaccine caused.
Beauchine said Carol received her first dose of Moderna on Feb. 16, 2021, and didn’t report any complaints. After getting the second dose on March 17, Carol immediately said she “felt different.” She developed numbness that spread throughout the entire left side of her body, blindness and hearing loss. She lost the ability to walk and communicate, and her brain degenerated until she passed away on Aug. 2, 2021 — just five months after receiving her second dose of Moderna.
The family submitted a report to VAERS, but the CDC has not followed up on Carol’s death. The Defender has received numerous reports of people who died from sporadic CJD after receiving a COVID vaccine — all women who were between the ages of 60 and 70, including Cheryl Cohen and Jennifer Deason Sprague.
Biden administration extends COVID public health emergency needed to keep vaccines under EUA
The Biden administration on Wednesday extended the COVID public health emergency, now two years old, for an additional 90 days — allowing vaccines and other drugs to remain under Emergency Use Authorization (EUA). Keeping COVID vaccines and other countermeasures under EUA shields pharmaceutical companies from liability for the harms caused by their products.
According to Reuters, a public health emergency was initially announced in January 2020, when the COVID pandemic began. It has been renewed each quarter since and was due to expire on April 16.
The Department of Health and Human Services (HHS) said in a statement it was extending the public health emergency and will give states 60 days’ notice prior to termination or expiration. This may be the last time HHS Secretary Xavier Becerra extends it, according to policy experts.
Pfizer to seek authorization from FDA for COVID booster shot for kids 5 to 11 years old
Pfizer and BioNTech Thursday said they plan to apply for EUA of a COVID booster dose for healthy 5- to 11-year-olds based on the results of a small study that has not been published or analyzed by independent experts.
Pfizer said in a press release the third dose of its vaccine produced significant protection against the Omicron variant in children 5 to 11 in a small Phase 2/3 clinical trial. The study was based on data from only 140 children 5 through 11 years old who received a booster dose six months after the second dose of Pfizer-BioNTech’s COVID vaccine as part of the primary series.
Pfizer claimed a closer look at 30 children showed a 36-fold increase in virus-fighting antibodies — levels high enough to fight the Omicron variant, and that a third dose was “well tolerated with no new safety signals observed.”
Although Pfizer said more than 10,000 children under the age of 12 have participated in clinical trials investigating Pfizer’s COVID vaccine, only 140 were selected for the study forming the basis for the company’s EUA request.
CDC launches internal review over failed COVID response
The CDC announced Monday it was launching a month-long comprehensive agency-wide review following widespread criticism of the agency’s response to the COVID pandemic.
The agency plans to evaluate its structure, systems and processes, CDC Director Dr. Rochelle Walensky told staff in an email obtained by The Washington Post. Walensky said the goal of the review is to “modernize” the agency and “to position CDC, and the public health community, for greatest success in the future.”
The review will be conducted by Jim Mcrae, associate administrator for primary healthcare at the Health Resources and Services Administration (HRSA). The HRSA and the CDC are part of the Department of Health and Human Services.
Last month, the CDC’s decision to remove from its data tracker website tens of thousands of deaths linked to COVID — including nearly a quarter of the deaths the agency said had occurred among children — eroded public trust in the CDC’s handling of case counts.
Children’s Health Defense asks anyone who has experienced an adverse reaction, to any vaccine, to file a report following these three steps.
6 Double Standards Public Health Officials Used to Justify COVID Vaccines
Madhava Setty, M.D. | The Defender | April 13, 2022
We are not only in an epidemiological crisis, we also are in an epistemological crisis. How do we know what we know? What differentiates opinion from a justified belief?
For nearly two years, the public has been inundated by a sophisticated messaging campaign that urges us to “trust the science.”
But how can a non-scientist know what the science is really saying?
Legacy media sources offer us an easy solution: “Trust us.”
Legions of so-called “independent” fact-checking sites that serve to eliminate any wayward thinking keep those with a modicum of skepticism in line.
“Research” has been redefined to mean browsing Wikipedia citations.
Rather than being considered for their merit, dissenting opinions are more easily dismissed as misinformation by labeling their source as untrustworthy.
How do we know these sources are untrustworthy? They must be if they offer a dissenting opinion!
This form of circular reasoning is the central axiom of all dogmatic systems of thought. Breaking the spell of dogmatic thinking is not easy, but it is possible.
In this article I describe six examples of double standards medical authorities have used to create the illusion their COVID-19 narrative is logical and sensible.
This illusion has been used with devastating effect to raise vaccine compliance.
Rather than citing scientific publications or expert opinions that conflict with our medical authorities’ narrative — information that will be categorically dismissed because it appears on The Defender — I will instead demonstrate how, from the beginning, the official narrative has been inconsistent, hypocritical and/or contradictory.
1. COVID deaths are ‘presumed,’ but vaccine deaths must be ‘proven’
As of April 8, VAERS included 26,699 reports of deaths following COVID vaccines.
The Centers for Disease Control and Prevention (CDC) officially acknowledges only nine of these.
In order to establish causality, the CDC requires autopsies to rule out any possible etiology of death before the agency will place culpability on the vaccine.
But the CDC uses a very different standard when it comes to identifying people who died from COVID.
The 986,000 COVID deaths reported by the CDC here are, as footnote [1] indicates, “Deaths with confirmed or presumed [emphasis added] COVID-19.”
If a person dies with a positive PCR test or is presumed to have COVID, the CDC will count that as COVID-19 death.
Note that in the CDC’s definition, a COVID fatality does not mean the person died from the disease, only with the disease.
Why is an autopsy required to establish a COVID vaccine death but not to establish a COVID death?
Conversely, why is recent exposure to SARS-CoV-2 prior to a death sufficient to establish causality — but recent exposure to a vaccine considered coincidental?
2. CDC uses VAERS data to investigate myocarditis yet claims VAERS data on vaccine deaths is unreliable
On June 23, 2021, the CDC’s Advisory Committee on Immunization Practices met to assess the risk of peri/myocarditis following COVID vaccination, especially in young males.
This was the key slide in this presentation:
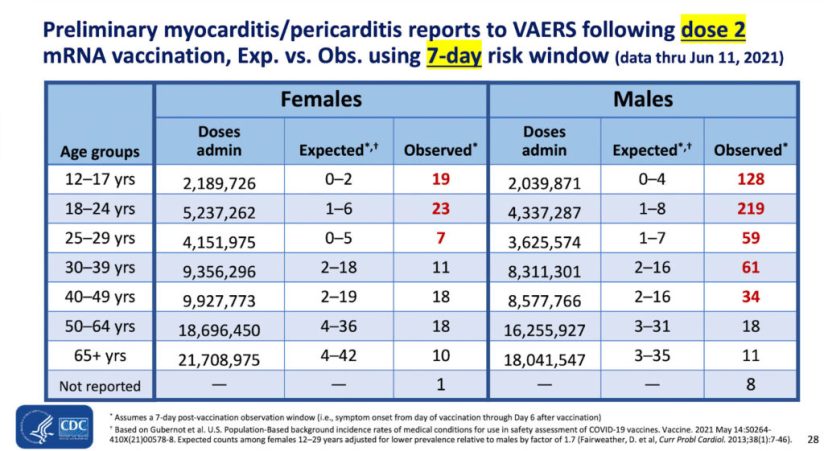
The observed risk of myocarditis is 219 in about 4.3 million second doses of COVID vaccine in males 18 to 24 years old.
The CDC is fine with using VAERS data to assess risk of myocarditis following vaccination — yet the agency rejects all but nine of the 26,699 reports of deaths following the vaccines.
Why does the CDC trust the peri/myocarditis data in VAERS but not the data on deaths?
One reason may be because the onset of myocarditis symptoms is closely tied to the time of vaccination.
In other words, because this condition closely follows inoculation the two events are highly correlated and suggestive of causation.
For example, here is another slide from the same presentation:
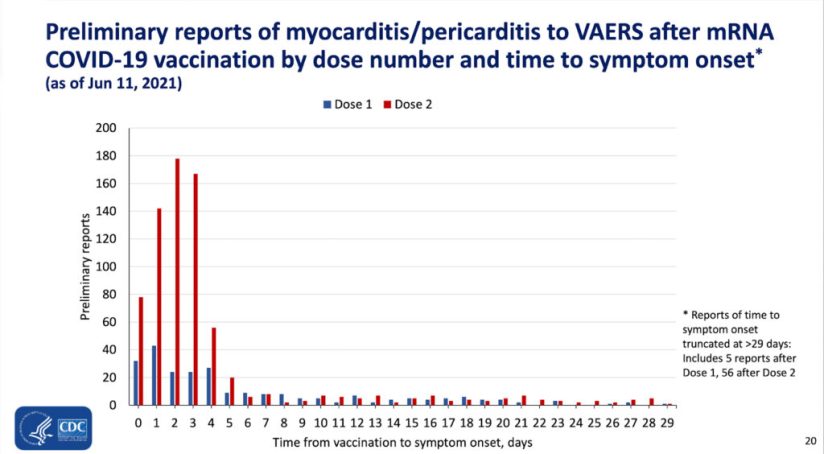
The majority of cases of vaccine-induced peri/myocarditis suffered symptoms within the first few days after injection. As explained above, this is highly suggestive of a causative effect of the vaccine.
A recent study in The Lancet included a similar graph, taken directly from VAERS, on deaths following vaccination:
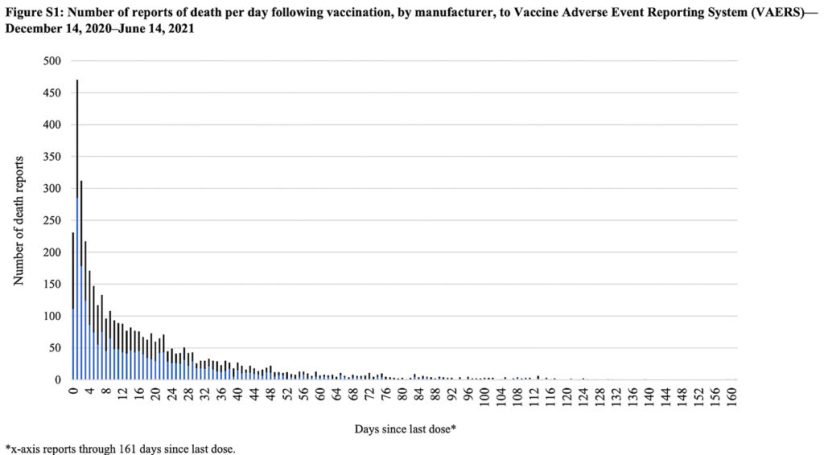
Once again, the event (death) closely follows vaccination in the majority of cases.
As we regard the two graphs above we should acknowledge that the temporal relationship between the injection and the adverse event is suggestive of causation but does not stand as proof of such.
However, it is also important to note that if the vaccination caused the deaths, that is exactly what the plot would look like.
It should be clear that the CDC has no justification for dismissing VAERS deaths if the agency is willing to accept reports of myo/pericarditis from the very same reporting system.
3. CDC pushes ‘relative risk’ for determining vaccine efficacy, but uses ‘absolute risk’ to downplay risk of adverse events
In Pfizer’s Phase 3 trial, nine times more placebo recipients developed severe COVID than those vaccinated during the short period of observation. This constitutes a relative risk reduction of 90%.
This seemed an encouraging finding and was used as a major talking point to compel the public to accept this experimental therapy despite the absence of any long-term data.
However, the risk of a trial participant contracting severe COVID (Table S5) was 1 in 21,314 (0.0047%) if they were vaccinated.
If they received the placebo, the risk was still only 9 in 21,259 (0.0423%).
The vaccine reduced the absolute risk of contracting severe disease by 0.038%.
Mainstream media and the CDC never mentioned the minuscule reduction in absolute risk of contracting severe COVID by getting inoculated.
Moreover, with 0.6% of vaccine recipients in the trial suffering a serious vaccine injury (one that results in death, medical or surgical intervention, hospitalization or an impending threat to life), approximately 16 serious adverse events will result for every serious case of COVID prevented by vaccination.
However, when it comes to risk of myo/pericarditis, the CDC states, “Myocarditis and pericarditis have rarely been reported, especially in adolescents and young adult males within several days after COVID-19 vaccination.”
The CDC further states, “While absolute risk remains small, the risk for myocarditis is higher for males ages 12 to 39 years…”
In other words, the risk of adverse events is being considered in absolute terms, not relative.
The CDC presentation slide above (Table 1) indicates the relative risk of contracting myo/pericarditis in males 18 to 24 is 27 to more than 200 times higher than expected in (unvaccinated) young men that age.
When assuaging the public’s fear around vaccine-induced myocarditis, the CDC finds it useful to cite absolute risk — yet when promoting the efficacy of the vaccine, the CDC emphasizes relative risks.
This double standard has been quietly and masterfully employed to reduce vaccine hesitancy and encourage compliance.
4. FDA requires randomized control studies for early treatment medications — but not for boosters
The CDC reports that as of April 8, 98.3 million Americans had received a COVID booster.
On March 29, the U.S. Food and Drug Administration (FDA) authorized a second booster for the immunocompromised and adults over age 50.
These authorizations were made not because of solid evidence the boosters are effective but rather to remedy the fact that the primary vaccine series has been widely shown to have waning efficacy within a few months.
As reported by The Defender, Dr. Peter Marks, director of the FDA’s vaccine division, Center for Biologics Evaluation and Research, admitted the fourth booster dose approved last week was a “stopgap measure” — in other words, a temporary measure to be implemented until a proper solution may be found in the future.
Despite the lack of solid evidence, the FDA continues to recommend and authorize boosters.
Yet when it comes to early treatment options, the agency holds medicines — including those the agency has already licensed and approved for other uses — to a different standard.
In this CNN interview from August 2021, Dr. Anthony Fauci, head of the National Institute of Allergy and Infectious Diseases, warns people not to take ivermectin for COVID because “there is no clinical evidence that this works.”
With regard to hydroxychloroquine, Fauci said, “We know that every single good study — and by good study, I mean randomized control study in which the data are firm and believable — has s shown that hydroxychloroquine is not effective in the treatment of Covid-19”, as reported by the BBC on July 29, 2020.
Where, then, are the randomized control studies in which the data are firm and believable that show boosters are effective at preventing COVID?
There aren’t any. None have been done.
As of today, the FDA still refuses to authorize the use of ivermectin and hydroxychloroquine to treat COVID despite hundreds of studies that demonstrate significant benefits (ivermectin, hydroxychloroquine) in prevention as well as early and late treatment.
The double standard here is blatant. There are no randomized control studies that show boosters are effective in preventing COVID.
Nevertheless, these experimental therapies have the FDA’s blessing while inexpensive, highly effective safe and proven medicines are ignored despite the enormous evidence that supports their use.
5. FDA uses immunobridging to justify Pfizer shots for young kids, but rejects antibodies as indicative of immune protection from COVID
Immunobridging is a method of inferring a vaccine’s effectiveness in preventing disease by assessing its ability to elicit an immune response through the measurement of biochemical markers, typically antibody levels.
The FDA asserts the presence of SARS-COV-2 antibodies is not necessarily indicative of immune protection from COVID.
Moreover, the FDA’s Vaccine and Related Biologics Product Advisory Committee reached a consensus last week that antibody levels cannot be used as a correlate for vaccine effectiveness.
Their decision is consistent with the CDC’s executive summary of a science brief released on October 29, 2021:
“Data are presently insufficient to determine an antibody titer threshold that indicates when an individual is protected from infection.”
Nevertheless, the FDA used immunobridging as a means to justify authorization of the Pfizer vaccine to children ages 5 to 11, as explained in The Defender here and here.
Because there were no deaths or serious cases of COVID in the pediatric trial, the FDA chose to reject its own position (and that of its advisory committee) regarding antibody titers as a correlate for vaccine efficacy.
6. Causation must be proven for vaccine injuries, but correlation suffices for proving vaccine efficacy
When it comes to vaccine injuries the public is often reminded that correlation does not equal causation.
In other words, just because an injury was preceded by inoculation doesn’t mean the vaccine caused the injury.
But what constitutes causation in medicine? A mechanism of action needs to be identified and pathological studies must confirm this mechanism while eliminating other potential causative factors. Causation can be proven only on a case-by-case basis.
Proving causation requires an enormous burden of proof in medicine.
For example, does smoking cause lung cancer? The answer is yes, it can. That doesn’t mean that it will.
However, when it comes to the benefit of medical intervention, such as a vaccine, causation does not have to be established. Correlation suffices.
In the COVID vaccine trials, fewer vaccinated people contracted COVID than unvaccinated ones. Yet there were those who received the vaccine who contracted the disease anyway.
To be fair, this is how all new medical interventions are evaluated. The benefit doesn’t have to be caused by the vaccine in the strictest sense, there just has to be a correlation between vaccination and a relative protective effect.
The more often this happens, the more confident we can be that the outcome wasn’t simply a coincidence.
Likewise, when it comes to assessing the harm of medical intervention, the most sensible outcome to consider is mortality. After all, what would be the point of introducing a vaccine that prevented some deaths while causing more?
Nevertheless, this is, in fact, what we have done with the Pfizer product. The interim results from the Phase 3 trial demonstrated that all-cause mortality in the vaccinated cohort was higher than in the placebo.
This glaring problem gets brushed aside because there were two deaths from COVID in the placebo arm versus just one in the vaccinated cohort, allowing the vaccine manufacturer to claim a 50% efficacy in preventing this outcome.
However, if we attribute a protective benefit to the vaccine in preventing this one fatality, we must also conclude that the vaccine was responsible for the extra death when considering mortality from all causes.
Doing otherwise would be applying yet another double standard.
How the pandemic could have played out differently
To summarize how devastating the use of these double standards in crafting the “safe and effective” narrative was, let’s look at how different the situation would be if we had adopted the opposite standard:
- There would have been an extremely low number of deaths from COVID. Very few, if any, autopsies have definitively confirmed that a fatality was caused by SARS-CoV-2. If confirmation by autopsy is the standard, there have been essentially zero deaths from COVID during the pandemic.
On the other hand, if we presume the deaths registered in VAERS are in fact vaccine-induced fatalities — similar to how the CDC presumed many deaths from COVID — we can affirm there have been more than 26,000 vaccine deaths. - Using absolute risk reduction as a measure of efficacy, vaccines would have been widely rejected as ineffective, providing only a 0.038% risk reduction for contracting severe COVID.
- Ivermectin and hydroxychloroquine would have been readily available for people who got COVID. And for those who got the vaccine but got COVID anyway, these medicines would have been a great alternative to boosters, which wouldn’t have been approved due to the lack of a single randomized control study proving they work.
- No children between the ages of 5 and 11 would have received this risky, experimental vaccine as it wouldn’t have been authorized for this age group — because Pfizer’s pediatric trials did not demonstrate any meaningful outcomes in children ages 5 to 11.
- The Pfizer vaccine would no longer be in use because interim data demonstrated that all-cause mortality is higher in the vaccinated.
Madhava Setty, M.D. is senior science editor for The Defender.
Real James Bond villains wear cardigans
Bill Gates, the WEF, and the WHO are not done with us. It’s time we were done with them.
el gato malo – bad cattitude – april 13, 2022
in history as in literature, a special place of contempt is held for the grand vizier, the guy behind the throne, the power behind the power. it’s a position of great influence but zero accountability, especially if you can subvert the ruler you puppet past the point of being able to scapegoat you.
buying or leading a politician and getting goodies is a process as old as politics, probably older as it was likely the reason the first politician was elected in the first place…
but the truly discerning james bond villain level vizier, well, they just go right ahead and buy their own NGO’s. that’s how you take over the world. space lasers and earthquake machines may be cool, but real conquest usually banal.
get to about the 1 minute mark in this video where you can hear bill speak about talking to donald trump in the white house.

trump asks about looking into some of the ill effects of vaccines.
gates tells him “that’s a dead end, that would be a bad thing, don’t do that.”
this is not a man giving well intentioned advice.
this is a man covering up a crime committed in the service of crony capitalism.
the gates foundation has a longstanding relationship with vaccines that is more than a little sketchy. they were pushing oral polio vaccines in africa LONG after they were known to be unsafe and had actually become the leading cause of polio in the world.
“The Gates Foundation is a leading funder of oral polio vaccination in Africa and around the world, having dedicated nearly $4 billion to such efforts by the end of 2018. As discussed in Forbes in May 2019, Gates has “personally [driven] the development” of new oral polio vaccines and plays a “strategic role beyond funding.”
the US uses ONLY injected IPV polio vaccines. both the US and the EU discontinued use of orals because of side effects including actually causing polio.
A year ago, news outlets briefly shone a light on the fact (a fact that makes public health officials squirm) that oral polio vaccines are causing polio outbreaks. With reports streaming in throughout 2019 regarding the circulation of vaccine-derived polioviruses in numerous African and Asian countries, a CDC virologist confessed, “We have now created more new emergences of the virus than we have stopped.”
… there were 400 recorded cases of vaccine-derived polio in more than 20 countries worldwide.
(author’s note: that’s ~3X the total of all natural polio cases worldwide and of those, only 29 occurred outside of pakistan and 100% of those were in afghanistan. this vaccines caused multiples more polio than the virus itself)
This week, the same story is making the same headlines, with the WHO’s shamefaced announcement that the oral polio vaccine is responsible for an alarming polio outbreak in Sudan—“linked to an ongoing vaccine-sparked epidemic in Chad”—with parallel outbreaks in a dozen other African countries. In fact, between August 2019 and August 2020, there were 400 recorded cases of vaccine-derived polio in more than 20 countries worldwide. Ironically, WHO disclosed this “setback” barely a week after it declared the African continent to be free of wild poliovirus—which has not been seen in Africa since 2016. While African epidemiologists cheerily claim that these outbreaks can “be brought under control with further immunization,” and Sudan prepares to launch a mass polio vaccination campaign, WHO is warning that “the risk of further spread of the vaccine-derived polio across central Africa and the Horn of Africa” is high.
but gates kept pushing them in africa anyway, probably because so many of his pals owned the production and that’s what the gates foundation does. that’s what all these guys do. big business and billionaires are not friends of free markets. they want sure things and it’s cheaper to twist and break arms and buy mandated markets than to compete on a fair playing field.
i have (on excellent, direct authority from a personal friend who i trust implicitly and who spoke directly to the folks involved) the following story about the gates foundation in india:
gates himself came in to speak with the health ministers. he offered them a vaccine for a disease they already had one for. they told him, “no thank you, we already have that one covered.” he told them “well, you need to switch to this vaccine or there will be no gates foundation investment for india.” the one he wanted them to switch to was owned by a “friend of his.” this story was relayed by extremely liberal folks who literally run vaccine programs in india. they heard this conversation directly and have no reason to lie. they were horrified. it was a pay to play stick up. (they still declined)
this is not the sort of conflict of interest that’s helpful in a guy telling the president not to look into vaccine issues. it also stands testament to his morality and inclination. bill gates is as amoral as he is rich. always has been. much of microsoft was stolen from his less machiavellian partners.
i’m presuming this interview above and the discussion with trump were pre-covid because it’s never mentioned and had this been post covid, i find it hard to believe that it would not have been, but it seems more apropos now that ever. obviously, the conflicts of interest certainly did not stop back then and vaccine ill effects are looking like quite the hot topic just now.
and gates is, as ever, right smack in the middle of the dirtiest, most profitable part of it.
it was september 2019. SARSCOV-2 was still not really on the radar. according to many, there was not even an outbreak yet.
that same month, billy made a large investment in a company called bioNtech to allegedly pursue HIV and tuberculosis vaccines. if memory serves, he bought about 1/3 of the company which was entirely preclinical in infectious diseases at the time. they were mostly a phase 1-2 oncology company. this looks like a sweetheart valuation.
obviously, this became a very big deal in a very big hurry. it was their mRNA payload that was licensed by pfizer for their vaccine, a product that went on to be the most profitable drug per unit time in human history. (and possibly the most profitable altogether) bioNtech minted money.
lots of things about this investment have long smelled fishier than a sushi bar dumpster.
but then a funny thing happened with a now vexingly familiar cast of characters.

(read more HERE)
even months later in january 2020, folks like osterholm were still buying the “no signs of human to human transmission” line.
yet somehow, 4 months earlier (and who knows when the due diligence started. might have been 6 or more), gates was putting his money right on the one obscure square that would pay out 100 to one. at a company with near zero footprint in infectious disease. for a virus no one was focused on. whose genetic code would not (allegedly) be initially characterized for 4 more months.
then, in the same odd, sudden miracle that got moderna the NIH science they licensed for their vaccine, bioNtech also had a product and pfizer jumped to license it.
alone, having a wargame for the war that had, unbeknownst to most, already started, might raise eyebrows, but it might also be a coincidence.
but when the folks coming to that wargame have been making big bets on the kinds of weapons that that precise (and only that precise) sort of war would use, well, one might start to sharpen the points on one’s pointy questions.
just what was informing what here?
this idea that “mRNA is magic and you can develop a vaccine in weeks” is complete nonsense. it’s never been true and the rest of the mRNA vaccine timelines stand testament to it. no other vaxx has been forthcoming.
this HAD to have been in the works for a significant period beforehand.
the fix appears to have been deeply in here. somebody was getting some VERY early looks at some tech to vaccinate against a virus no one else even had a copy of. the awareness not just of the pathogen, but the way to code for its spike protein and the impending pandemic seems to have been loose in certain circles long before the rest of us were told.
the NIH seeded moderna. i still do not have confirmation on where bioNtech got theirs, but i have a hunch and it rhymes with “silly plates” and that this might explain the sweetheart deal.
there is really only one story that makes sense to me here on covid origins, and that story is this:
NIH funded eco health alliance run by daszak and in cahoots with folks like baric colored outside the lines with fauci’s grant money. they, in collaboration with the wuhan institute of virology hotwired the hell out of covid viruses from bats engaging in gain of function work WAY outside of safe limits. this was not a weapon. it was work on inoculation. that was daszak’s longstanding focus. we’ll probably never know what happened in wuhan, but the breadcrumbs here are AWFULLY provocative and the sudden appearance of 2 mRNA vaccines, one with the NIH folks that funded EHA at the WIV, one with bioNtech, looks like an offshoot of it. (lots of detail HERE and HERE on the breadcrumbs)
wrapped up in this from the very beginning were load of the WEF gang (who had just run an oddly timely pandemic wargame for a disease an awful lot like covid) and the WHO.
billy gates is neck deep in both, a charter member of the cool kids crony capitalist table at davos and a top funding source for the WHO, donating more than 10% of its budget. it’s clearly a great investment for him as it poops golden eggs in terms of early information and hard sell opportunities for poor countries. it’s a seat at every table that makes you look like a philanthropist while in reality being a lead pipe wielding coercive corporatist.
gates is not a good guy.
he’s a sociopathic nerd with the most unsavory of associates.
and he knows how to play the crony capitalist game with the absolute best of them. the gates foundation has become a barely veiled international influence organization masquerading as a charity.
between gates and china, the WHO will dance to whatever song the two play. and oh, how they will dance.
remember this gem? (i do)

this was a big part of what got the out of control abandonment of 100 years of science based pandemic guidelines rolling.
“hey, let’s throw all the science, data, and history out the window and copy a terrifying authoritarian regime with a human rights record that would make myanmar blush!”
yeah, well, we all remember how THAT worked out…
but this is government. it’s worse than government, it’s trans-national organizational government. these are the people who invented “failing up” where the bigger your screw ups, the higher you get promoted. (if you doubt me, look at who runs the IMF and the world bank some time…)
and so, despite having cheer led for nothing uty pseudoscience, failure, and human ruin, the current plan being put forward is, wait for it, “hey, let’s give the WHO massive, unaccountable globalist powers!”
of course, this was clearly the plan all along if you were paying attention.

note the direct parrot of the WEF “build back better” taking point.
this gang sees every crisis as a chance to try to grab control of the world. and they are at it again.
In a consensus decision aimed at protecting the world from future infectious diseases crises, the World Health Assembly today agreed to kickstart a global process to draft and negotiate a convention, agreement or other international instrument under the Constitution of the World Health Organization to strengthen pandemic prevention, preparedness and response.
Dr Tedros Adhanom Ghebreyesus, WHO Director-General, said the decision by the World Health Assembly was historic in nature, vital in its mission, and represented a once-in-a-generation opportunity to strengthen the global health architecture to protect and promote the well-being of all people.
“The COVID-19 pandemic has shone a light on the many flaws in the global system to protect people from pandemics: the most vulnerable people going without vaccines; health workers without needed equipment to perform their life-saving work; and ‘me-first’ approaches that stymie the global solidarity needed to deal with a global threat,” Dr Tedros said.
they will also force licensing, break patents, and drive health policy at the highest levels.
but here’s the full blown worst of it:

The World Health Organization (WHO) has contracted German-based Deutsche Telekom subsidiary T-Systems to develop a global vaccine passport system, with plans to link every person on the planet to a QR code digital ID.
Indeed, despite the minuscule threat posed by new variants and dubious-at-best vaccine efficacy, the WHO is adamant that a global QR code-based vaccine passport system is vital for all future health emergencies, not just COVID.
“COVID-19 affects everyone. Countries will therefore only emerge from the pandemic together. Vaccination certificates that are tamper-proof and digitally verifiable build trust. WHO is therefore supporting member states in building national and regional trust networks and verification technology,” says unit head of the WHO’s Department of Digital Health and Innovation Garrett Mehl.
“The WHO’s gateway service also serves as a bridge between regional systems. It can also be used as part of future vaccination campaigns and home-based records.”
got that? this one is going to be digitally verifiable and global. nowhere to run, nowhere to hide, universal, mandatory, trans-national, and administered by an agency completely unaccountable to you and beholden to proven kleptocrats, authoritarians, and crony corporatists. they are basically a subsidiary of china and gates inc.
they will not get any better or more honest next time.
we’re talking about taking one of the most corrupt, captured, and incompetent agencies in the history of bureaucratic bloviation and giving them the keys to the world crisis machine and to an electronic health passport that will be your right to travel and work and eat out and shop and who knows what else. this is the cornerstone of an international social credit system. wait until they add your ESG score and your carbon footprint.
giving this team universal chicken little rights and direct links at highest levels to public policy is bad enough. letting them enable fine grained access into permission to have anything resembling a life will have you eating bugs and tweeting what you’re told faster than you can say #grasshoppers #yummy!
they promised you that in the future you’d have no privacy and own nothing and that you’d been happy.
guess which two promises they’re going to keep?
and government will fall all over themselves to help and to outsource the imposition of the infinite personal tracking and permissioning they have so long salivated over under the pretext of pandemic preparedness. (oops, look, another trojan framing of subjugating masquerading as safety. told you these were EVERYWHERE…)
this is not going to be acceptable or even tolerable.
this group should be disbanded, not granted greater remit.
and they are not done, because the power behind these thrones is ever hungry.
you might be thinking “wow, that was awful” but they are all thinking “wow, that was surprisingly easy. i wonder what we could do if we had some time to get set up beforehand and really run the table?”
these are not good people.
they do not have noble aims nor your best interests at heart.
they are a global aristocracy of surpassing ruthlessness telling scare stories so they can mandate alleged solutions.
they tell you it’s about saving you.
it isn’t.
read the fine print.
follow the money.

the super rich do not like to guess. they do not like to be surprised by trends. it is far more certain and therefore more profitable to force you to buy that which they are selling. the public health grift and the climate grift are all one grift: use government and trans-government to frighten and force people into buying the needless products that you’re going to produce for them.
small investors talk their book. titanic investors force you to buy it.
- if it’s a vaccine, mandate it and bar all useful therapeutics from market.
- if it’s a windmill, kill nuclear and inflict absurdist carbon taxes.
- never let any of it be properly assessed.
- use fear to drive compliance and compliance to drive mandate.
they will sell you your own collar and leash and demand your gratitude for having done so.
and if you don’t wake up pretty soon, they’re going to get it from you. by force. and you will be powerless to stop it.
the confluence of a global health passport and central bank digital currencies is an extinction level event for personal liberty and privacy.
and make no mistake: gates wants it. the WEF wants it. and most western governments want it.
but they also know that you do not want it. so they need a pretext and a plan and a pile of boring, technocratic yammering to hide it behind. they learned from last time. they saw the cracks we squirmed through and how we got away. and they do not plan to let it happen again. the next one will be air tight. they’ll have the WHO ready to both be able to declare a global emergency and impose ready made verified global digital ID using that fear as a pretext.
if you let them get these pieces into place, you are NOT going to like the endgame.
this has reached the email length limit. check the substack page for an addendum.
Featured Video

When Israel Is Mighty
or go to
Aletho News Archives – Video-Images
From the Archives
US murdering 1 million Iraqis is democracy, Iran giving yogurt to Iraq is “domination”
By Ali Salaam | American Herald Tribune | July 31, 2017
The New York Times, owned by the Zionist Jewish supremacist Ochs-Sulzberger family, has no problem with Iraqi suffering as long as Iran is not the one behind it.
The Iraq War was a genocide of the Iraqi people by Zionist supremacists in the Bush administration. Over 1 million innocent people were killed based on a lie. American soldiers died in an Israeli war and now an average of 22 soldiers commit suicide every day because their consciences cannot cope with the fact they committed crimes in an illegal war that served no purpose other than to benefit Israel, not America.
Benjamin Netanyahu, Prime Minister of the Zionist regime, once said “We are benefiting from one thing, and that is the attack on the Twin Towers and Pentagon, and the American struggle in Iraq.”
Paul Wolfowitz had his sights on Iraq since his time in the first Bush administration. Former Israeli official and Bush administration official Richard Perle had his eyes on Iraq since at least his authorship of the Clean Break white paper. The Zionist regime had their eyes on Iraq since the 1980s when strategist Oded Yinon wrote his white paper in support of dividing the Arab-Muslim world along ethnic and sectarian lines. The global Zionist lobby has had their eyes on Iraq since Theodor Herzl stated that Eretz Israel’s true borders go from the Nile River in Egypt to the Euphrates River in Iraq. … continue
Blog Roll
 Aletho News
- MEP blasts ‘Euro-Gestapo’ for lecturing Russia on democracy
- Syria May Send Troops to Saudi Arabia Amid War with Ansar Allah
- UK whines about losing billions to ‘Putin tax’
- Baghaei to Rubio: Distorted narratives cannot erase US record of broken commitments
- Houthis Don’t Have to Conquer Saudi Arabia to Make It Pay
- MOE: Nearly 22,000 Students and Education Workers Killed
- Guterres in Islamabad: Genocide, cowardice, and the cage of Imran Khan
- Johnson, Marandi say Yemen holds upper hand over Saudi Arabia
- False flags won’t save aggressors, Iran FM spokesman says
- The Makkah Pact Enters Into Force: The End of American Dominance or Its New Form?
- If Americans Knew
- Report claimed Mark Levin used by Israeli government to influence Trump
- Over 2,000 Gazans have died awaiting medical evacuation amid Israel’s continued siege
- How a U.S. Diplomat Suppressed and Altered Reports Critical of Israel
- 5 Palestinians Die from Israeli Strikes in Gaza as Relentless Attacks Continue
- Report: Ceasefire Slows Killing but Leaves Devastation Intact
- Country Music Singer Zach Bryan Breaks Attendance Record at Robert Kraft’s Gillette Stadium While Wearing ‘Free Palestine’ Shirt for Second Night in a Row
- Three years of death and devastation: Israel’s war on Gaza in pictures
- Why Hamas believed the status quo was more dangerous than its 7 October gamble
- Debunking Israel’s latest list of ‘terrorist’ journalists in Gaza
- In Gaza, focus is on survival, “every step is a struggle” – Daily Update
- No Tricks Zone
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative

