Denmark Suspends COVID Vaccine Campaign, EU Set to End Mass Testing
By Michael Nevradakis, Ph.D. | The Defender | April 27, 2022
Denmark on Tuesday became the first country to suspend its national COVID-19 vaccine campaign after health officials said the pandemic is under control there.
Bolette Soborg, director of the Danish Health Authority’s department of infectious diseases, on Tuesday said Denmark is “winding down” the mass vaccination program, and that invitations for vaccinations would no longer be issued after May 15.
“We plan to reopen the vaccination programme in the autumn,” Soborg said, adding: “This will be preceded by a thorough professional assessment of who and when to vaccinate and with which vaccines.”
Public health authorities cited several factors contributing to the decision to end the national vaccination campaign. These include a decline in the number of new reported infections, stabilized hospitalization rates and an overall high level of vaccination.
This decision comes just a few months after Denmark eliminated all COVID-19-related restrictions, becoming the first European Union (EU) member state to do so.
On February 1, the country dropped restrictions ranging from vaccine passports to mask mandates. Public health authorities at the time said COVID-19 was no longer considered a critical threat to public health.
Despite a “surge” in reported infections in Denmark, attributed to the Omicron variant, health authorities said these cases are not placing a heavy burden on the country’s health system.
Denmark’s health authorities are the first to explicitly state that future COVID-19 vaccination drives will be targeted, rather than universal.
EU set to announce ‘post-emergency’ phase of pandemic, Fauci says U.S. out of ‘pandemic phase’
Denmark’s decision comes as several other countries appear to be walking back mass-scale COVID-19 vaccination and related public health initiatives.
In an interview Tuesday on PBS NewsHour, Dr. Anthony Fauci said, “We [the United States] are certainly right now in this country out of the pandemic phase.”
However, when asked whether there will be an end to the COVID-19 pandemic, he said that’s “an unanswerable question.”
In the U.K., the country’s Health Security agency this week announced it is slashing its staff by almost half, and reducing its COVID-19 budget by nearly 90% compared to 2021 levels.
And the European Commission — the executive branch of the EU — is reportedly preparing to announce the EU has entered a new “post-emergency phase” of the COVID-19 pandemic, Reuters reported today, citing a draft document the news agency said it reviewed.
Despite there being no official statements yet from EU officials, according to Reuters, the draft document, prepared by EU Health Commissioner Stella Kyriakides, states:
“This Communication puts forward an approach for the management of the pandemic in the coming months, moving from emergency to a more sustainable model.”
In practical terms, this would mean an end to mass COVID-19 testing, already shut down in several EU countries.
This approach contrasts with China’s “zero-COVID” policies — which have resulted in mass testing and a renewed wave of mass lockdowns.
In a possible reflection of the EU’s new policy direction — and its stark differentiation from China’s COVID policies — Greek health minister Thanos Plevris said recently “we are entering the phase of co-existing with COVID … we don’t believe in the zero-COVID policy, like in China.”
According to Reuters, the EU’s draft document is non-binding on member-states and states that “COVID-19 is here to stay,” with a likely emergence of new variants and “surges,” necessitating that “vigilance and preparedness remain essential.”
The document asks EU governments to be ready to re-enact emergency measures if deemed necessary, though the nature of these “emergency measures” does not appear to be specified.
However, the draft document does address the introduction of more sophisticated means of detecting outbreaks of — and the spread of — COVID-19, highlighting that “[t]argeted diagnostic testing should be put into place.”
Such “targeted” testing would focus on “priority groups,” such as people close to outbreaks, those at risk of developing severe COVID-19 symptoms and medical staff who are in regular contact with vulnerable populations.
The draft document also suggests surveillance and tracking of COVID-19 infections should be adapted and targeted, focusing more on genomic sequencing and less on the mass reporting of “cases.”
This new surveillance system would amount to one that, according to Reuters, is “similar to that used to monitor seasonal flu, in which a limited number of selected healthcare providers collect and share relevant data.”
As reportedly stated by the document, “[t]he objective of surveillance should no longer be based on the identification and reporting of all cases, but rather on obtaining reliable estimates of the intensity of community transmission, of the impact of severe disease and on vaccine effectiveness.”
However, unlike Denmark’s approach, the document states that vaccines remain essential, with a recommendation that EU member states consider enacting strategies to bolster vaccination levels among children age 5 and up prior to the start of the new school year.
Some EU member states, such as Greece, have strongly hinted wide-scale COVID-19 vaccinations and restrictions may resume in September.
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
New Zealand Used Selective Science and Force to Drive High Vaccination Rates
By J.R. Bruning | Brownstone Institute | April 26, 2022
We expect that knowledge produced and applied in a health emergency will produce information that is protective of health. But it is increasingly apparent that over the last two years New Zealand’s Ardern government has designed policy, regulation, and information to coercively steward citizens to accept a drug under provisional consent.
Strict lockdowns were promised to end when 90% of the population was vaccinated. This was unprecedented: policy endpoints required population-level uptake of novel technology, no matter whether the individual was at risk or not.
In addition, data production was contracted by the department intent on a 90% vaccination rate. For decades governments have promoted ‘evidence-based science’ as the gold standard for public reasoning and risk deliberation. What we saw was internally produced and contracted science that focused on case rates, while (inconvenient) information in the published scientific literature on vaccine risk, waning and breakthrough was ignored.
This produced a tightly controlled scope of knowledge production that then failed to adhere to long-established democratic and public health principles. Responsible risk governance requires that governments must be responsive to data that indicates a technology is not as effective or is possibly more harmful than estimated, – for a democratic government’s primary role is the protection and safety of all citizens. Technology must not be valorized, and uncertainty set aside, in order to achieve policy ends.
Universal Vaccination Assumed from April 2021
New Zealand’s Unite Against Covid-19 ‘elimination’ strategy was confirmed in the first quarter of 2020. Policy, propaganda and legislation predominantly centred around the case, or infection rate, rather than the fatality rate as the measure of risk.
Even though the clinical trials did not demonstrate that the vaccine prevented transmission and infection, the Government promoted ‘the jab’ as a way to protect families in the Unite Against Covid-19 campaign. Persistent reporting of case rates fostered a perpetual state of fear and uncertainty among the population, who perceived infection from the SARS-CoV-2 virus to be something more like Ebola.
The Ardern government’s intention for the entire population to get the mRNA vaccine was declared through the signing of a supply agreement. This intention was then embedded in policy and regulation via the Traffic Light system, designed to nudge the population over 12 into compliance.
It was known by July 2021 that the vaccine waned and was leaky. Breakthrough infections were relatively common and for many. The clinical trials remain incomplete, lacking long-term safety data. The trials did not demonstrate that the vaccine prevented hospitalization and death.
However, in April 2022 in New Zealand, mandatory vaccinations remain compulsory for border workers, and workers in health and disability; corrections; defence; Fire and Emergency New Zealand (FENZ) and Police. These professions must be vaccinated and have received a booster vaccination against COVID-19.
At ‘Traffic Light Orange’ Kiwis ‘must wear a face mask’ in retail businesses, on shared and public transport, in government facilities and when visiting a healthcare service. This is despite the fact that Omicron ripped through New Zealand in February.
In the first week back at school and university after the summer holidays –the obedient mask-wearing young friends of my kids, including my son, from Otago and Canterbury down on the South Island up to the capital Wellington and Auckland – were locked down with Omicron in their first weeks back at university. No evaluation of Omicron and mask efficacy has been provided by the state.
The Risk Modellers
Government policy processes have persistently excluded uncomfortable knowledge that suggested uncertainty or risk. First, the policy accompanying and justifying Covid-19 legislation and Orders, and modelling by the contracted institution Te Pūnaha Matatini (TPM) contained narrow reasoning central to the state’s claims, locking in the narrative that infection was the predicator of risk, modelling wave after wave of infection.
Second, policy supporting the legislation excluded consideration of age-stratified risk and failed to address common principles of infectious disease management embedded in the New Zealand Health Act. Third, reviews of the scientific literature that could publicly identify and communicate risk relating to vaccine-related harm and issues relating to efficacy simply never occurred.
The gaps are considerable. The Government’s Covid-19 Unite campaign failed to communicate age-stratified risk of hospitalization and death as the pandemic evolved. New evidence on infection fatality rates were not reported to the public. In modelling papers, TPM used old infection fatality rate statistics that overestimated death rates.
The potential for the vaccine to wane or for breakthrough infection to occur was ignored in a major policy paper focussed on elimination and by the modellers at TPM. The role of natural infection in producing a broader, and protective structural response, assisting populations to shift to herd immunity status was downplayed. While herd immunity was recognized, testing and data modelling was undertaken to identify naturally derived herd immunity in the population. Later modelling exclusively associated herd immunity with vaccination.
Perhaps the problems addressed here are not surprising, when most modelling was undertaken outside of New Zealand’s public health institutions. Instead, number-crunching was carried out by data analysts, mathematicians affiliated with TPM, with scarce few infectious disease epidemiologists trained in public health ethics participating. And of course, the science and data modelling were directly funded by the government departments and Ministries dedicated to over 90% vaccine compliance.
Global vaccination policies ignored the fact that infection-related risk always centered on the aged and infirm and those with complex multimorbid conditions. Disconcertingly, the clinical trial data had conceded that vaccine efficacy remained uncertain for the most at-risk of harm from Covid-19 – the immunocompromised, autoimmune and people who were frail, and those with inflammatory conditions (see p.115). In addition, as coronaviruses readily mutate, it was highly probable the vaccine would have a short shelf life.
Early Treatments Sidelined
Governments are entrusted with an overarching obligation to protect health – this includes putting populations directly at risk through bad policy. There was always a role for safe, established drugs with a long history of safe use that had undergone complete testing before launching onto the market.
Early treatments could have been integrated as a major tool to prevent hospitalisation and death. Early treatments avoid the dilemma of mutating variants while acting to protect at-risk groups whose immune systems might not be as responsive to a vaccine.
Conventionally doctors are at liberty to repurpose drugs for their patients, such as antivirals with a long history of safe use. However, in July 2021, the government locked in approved drugs for treatment.
From at least October, New Zealand doctors were instructed to ‘not use any other antiviral outside of a clinical trial’ while Medsafe warned against use of the safe antiviral Ivermectin for a respiratory virus. Yet the clinical guidelines were intended as last resort medicine for the hospitalized, rather than designed as protective nor preventative at home therapies.
These directives have fractured the practice of informed consent, which forms the basis of trust in the doctor-patient relationships. Even the New Zealand Medical Council, the organisation that grants licences to practice medicine, declared that there was ‘no place for anti-vaccination messages in professional practice.’ These actions may unwittingly undermine trust in vaccines and the doctor-patient relationship for years to come.
The implications of silencing doctors, some who have had their medical licenses suspended, when observed alongside the above-mentioned data gaps, are extraordinary.
Ethical questions continue to be sidelined. The principle of proportionality, embedded in the 1956 Health Act, has been effectively dropped. Proportionality, which allows for individual risk, is a core consideration in public health. Medicine is a technology, and the space where biology meets technology – including medicine – is never constant, and requires value-based judgement. Risk management of a medical intervention for a pregnant woman, young person or child requires significantly different deliberation to a 75-year-old.
Democratically Unaccountable Legislation
Since January 2020, a tsunami of rights-limiting has been rolled out purposefully and consistently. There was scant citizen consultation with public input limited to a few short days in most cases. The unprecedented barrage of rules and orders released by the Ardern government entrenched requirements for almost everybody to get the mRNA vaccine.
By mid-2021 – before most mandates – the scientific literature was revealing that the vaccine waned; that breakthrough infection occurred and that there was extensive evidence that it produced a wide range of side effects, and even death. This knowledge should have invalidated any workforce vaccine mandate, but instead by October, the state doubled down and locked in mandates and regulations that would legally and socially coerce most of the population over 12 into accepting the shot.
It’s probable that the mountain of legislation produced over the last two years never fulfilled democratic norms of accountability and transparency. For science in a pandemic to be harnessed to serve the public interest, the institutions that set those terms of reference must be guided by principles that protect health.
The failure of government agencies to draw on peer-reviewed scientific literature while prioritizing internal modelling is clear from tracking the literature stored online with the relevant agencies. Most compellingly, it is documented in the policy supplied in support of the unprecedented quantity of law-making.
It appears that from late 2019, institutional interests anticipated that there would be hesitancy around vaccine safety. Yet there was no public forum. Instead, groups who sought to question the safety of the novel mRNA vaccine remained outside ‘accredited’ media, possibly due to the chilling effect of unprecedented Covid-19 funding and advertising boosts which effectively captured mainstream media.
That the New Zealand state mandated not-at-risk people accept a novel technology, creating rules (as nudge policies) that limited economic and social life for the non-vaccinated when there was early evidence the vaccine was leaky and potentially harmful, will take years to unpick. As mandates continue, injured groups continue to face barriers to justice following vaccine injury and death.
Ultimately, practices such as this raise nagging doubts concerning the state’s capacity to honor broader obligations to protect health and the public interest in future emergency situations. New Zealand’s response to the Covid-19 pandemic serves as a case study – a precedent, for future health emergencies.
A deeper dive on this discussion can be found in the paper, Covid-19 Emergency Powers and on Rumble. The paper is offered to assist academic and legal experts, citizens and communities to consider use of policy and science by the Ardern Government from 2020-2022. I question the potential for the New Zealand state to navigate future pandemics, and future techno-controversies, in the public interest.
J.R. Bruning is a consultant sociologist (B.Bus.Agribusiness; MA Sociology) based in New Zealand. Her work explores governance cultures, policy and the production of scientific and technical knowledge. Her Master’s thesis explored the ways science policy creates barriers to funding, stymying scientists’ efforts to explore upstream drivers of harm. Bruning is a trustee of Physicians & Scientists for Global Responsibility (PSGR.org.nz). Papers and writing can be found at TalkingRisk.NZ and at JRBruning.Substack.com and at Talking Risk on Rumble.
They just won’t let go of masks
By Guy Hatchard | TCW Defending Freedom | April 26, 2022
The writer is in New Zealand
AS the pandemic fades, should we meekly accept new restrictions or seek new freedoms?
An article in the New Zealand autumn 2022 AA Directions magazine advises that ‘masks are going to be part of our day-to-day lives for the foreseeable future’, and teaches us how to recognise whether someone is smiling behind their mask.
Yesterday in Stuff, science columnist Dr Siouxsie Wiles finally gets around to admitting that ‘you can’t rely on mRNA vaccines’. Her answer? Be stricter about mask wearing.
Dr Wiles, a British microbiologist who received the 2021 New Zealander of the Year Award for pandemic science communication, cites a new study which she says supports continuing use of masks at gatherings. Click on the link (most people don’t) and you arrive at a study that involves theoretical modelling rather than verified effects.
Mask studies (of which there are many) have not demonstrated large reductions in Covid transmission. They tend to be very technical in nature and focus on the comparative viral loads found in nasal and mask swabs. These measurements can be connected to Covid transmission only via theoretical modelling.
Back in the real world, the near universal combination of vaccination and mask wearing to date in New Zealand has not stopped Omicron transmission.
A study published in ClinMed entitled ‘Adverse Effects of Prolonged Mask Use among Healthcare Professionals during Covid-19’surveyed 343 healthcare professionals in New York City hospitals obliged to wear masks throughout most of their working day. They reported: headaches (71 per cent), skin breakdown (50 per cent), and impaired cognition (24 per cent). Yes, you did read that right, one quarter of medical professionals wearing masks suffer decreased intellectual capacity.
Even costly N95 masks do not stop the passage of air around them essentially negating their purpose and prompting the observation that it is like trying to stop mosquitos with chicken wire. Surgical masks or their equivalent are mainly required in hospitals and dirty environments such as sawmills or building sites to protect the wearer from inhaling human tissue or large particulates.
So will Dr Wiles advise us next week to wear a full deep-sea diving suit? In the crazy world of the new subnormal apparently nothing absurd can be ruled out.
Hiding the truth from the public has become a medical imperative
There is a certain hysteria surrounding the realisation that mRNA vaccines don’t actually work and may be harmful. When my kids were growing up we used to read an amusing book to them, Lies My Mother Told Me. How many lies have we been told? Too many.
For example, the Pfizer mRNA vaccine is:
· 95 per cent effective
· Completely safe
· Mostly stays in the upper arm muscle, as most traditional vaccines do
This last is interesting because Pfizer knew before they released the mRNA vaccine that it didn’t stay in the upper arm. They had completed an animal study which suggested that most of the mRNA vaccine spread throughout the body instead of staying at the injection site. The lipid nanoparticles (LNP), which encase the mRNA and help to breach cell walls are highly mobile and ensure that the mRNA spreads rapidly to all the organ systems in the body. If you want the full story see this article by clinical immunologist Dr Byram Bridle.
If we had known this, we would have realised early on that adverse reactions such as liver and kidney damage, strokes, cardiac events, neurological conditions and sudden-onset cancers were not unrelated to vaccination, as many victims were assured at the time by the NZ Ministry of Health, GPs and hospital staff.
Medical professionals assessing the causal connections between mRNA vaccination and subsequent adverse events were relying upon their prior knowledge about traditional vaccines. They thought they knew that vaccine ingredients mostly stayed at the injection site and eventually appeared in lymph nodes as they were cleaned up by the immune system. Pfizer neglected to tell them this was not the case. In fact Pfizer didn’t seem to inform anybody: the damning data was hidden in an obscure study buried in the requirements of the various national regulatory processes supposedly scrutinising safety. Anyone sounding the alarm seemed to be cancelled by the media and relegated to the ranks of conspiracy theorists.
Now that we have some hard NZ data showing that the protective effect of mRNA vaccination is a myth, there appears to be a rush on the part of seasoned and highly decorated Covid science communicators like Dr Siouxsie Wiles, member of the NZ Order of Merit, to throw us a lifeline. We may not actually choose to be saved. We might instead get on with our own lives and make the best of what opportunities we can discover for ourselves. At least we will be rowing our own boat, not sinking in the good ship misinformation.
When will these vaccine zealots wake up to the truth?
By Guy Hatchard | TCW Defending Freedom | April 24, 2022
WE should not understate the naivety of the government, media and scientists during the pandemic. The tabloid-style stories of severe Covid outcomes, the authoritative voice of Dr Anthony Fauci (who has financial conflicts of interest), the allure of the word vaccine, and the exaggerated death toll in foreign lands all combined into a convincing call for immediate and coercive action. Yet behind the stories, the highly profitable pharmaceutical PR system was running at full steam playing on the fear factor. New Zealand fell head over heels in love. Love knows no reason and that was certainly the case here.
New Zealand is a long way from the rest of the world. We have a tradition of proud independence and self-sufficiency, but we rolled over and played Follow the Leader. No one in a position of influence struck a note of caution, especially not our Prime Minister. We instituted the largest public borrowing programme in our history and spent it on a US mega corporation with a poor safety record and a history of punitive malpractice judgments. The government instituted saturation advertising of vaccine safety and efficacy, and then followed up with mandates, sackings and social exclusion. Our media shouted down those few asking questions.
Times, however, have changed. The respected and conservative Wall Street Journal (WSJ) has aired concerns about poor regulatory decisions at the US Food and Drug Agency (FDA) over booster shots. It joins a growing international chorus of highly qualified and influential voices.
On April 3, in an opinion piece entitled ‘FDA Shuts Out Its Own Experts in Authorising Another Vaccine Booster’, Dr Marty Makary, a surgeon and public policy researcher at Johns Hopkins University School of Medicine, wrote: ‘The FDA last week authorised Americans over 50 to get a fourth Covid vaccine dose. Some of the FDA’s own experts disagreed, but the agency simply ignored them.’
Eric Rubin, editor-in-chief of the New England Journal of Medicine (arguably the world’s most influential medical journal) and a member of the FDA advisory committee on vaccines told CNN last month: ‘I haven’t seen enough data to determine whether anyone needs a fourth dose.’
Dr Cody Meissner, also a member of the FDA vaccine advisory committee and chief of paediatric infectious diseases at Tufts Children’s Hospital in Boston, agreed: ‘The fourth dose is an unanswered question for people with a normal immune system.’
A third member of the committee, Dr Paul Offit of the Children’s Hospital of Philadelphia, went further. He told the Atlantic magazine that he advised his 20-something son to forgo the first booster.
Two top FDA officials, Marion Gruber, Director of the FDA Office of Vaccine Research and Review and her deputy Paul Krause, quit the FDA in September last year complaining of undue pressure to authorise boosters and a lack of data to support their use.
Unbelievably, the US Centers for Disease Control (CDC) rubber-stamped the FDA decision to approve a second booster without even convening its panel of external independent vaccine experts.
The WSJ article described the effect of boosters as fleeting, mild and short-lived. It sounded a note of alarm saying that neither the CDC nor the US National Institutes of Health (NIH) had made a priority of studying vaccine complications. Moreover their VAERS data collection and analysis process is incomplete and inadequate. In other words, the safety investigation to date of adverse effects of mRNA vaccination is incomplete and potentially misleading.
The central question raised by the WSJ opinion piece is, why wouldn’t the US regulators wish to undertake accurate and complete investigation of adverse effects of mRNA vaccination? Have pharmaceutical interests been able to influence decision-making at the FDA to their own commercial advantage at the expense of safety considerations?
The British Medical Journal agrees. On March 16 it published an article which said: ‘Evidence-based medicine has been corrupted by corporate interests, failed regulation and commercialisation of academia.’
The lessons are obvious. We have stifled debate and slavishly followed FDA advice. Now there is a need for revaluation and debate. We have travelled a long way down a one-way street, but it appears to be a dead end. The triumphant articles published about a survey of vaccine-resistant people born in Dunedin was a low point in uncritical mainstream media publishing. We have to regain an objective voice.
A paper published on April 5 in the New England Journal of Medicine found that any measurable protective effect of the fourth inoculation (which in any case, it found, is very small in absolute terms) disappeared after just eight weeks. Moreover a paper in the Lancet on April 8 admitted that boosters carry a risk of additional side-effects. Both these papers, however, skirted the obvious safety questions in favour of weak praise for vaccine orthodoxy.
In contrast the WSJ article asked the important question: ‘Who is actually getting serious about measuring the extent of adverse events, rather than continuing to urge uncritical acceptance of a largely ineffective vaccine?’
So far New Zealand media have steered clear of such questions. Dr Ashley Bloomfield, chief executive of the country’s Health Ministry, has refused to institute mandatory reporting of adverse events following mRNA Covid vaccination and he has excelled at denying vaccine exemptions to those injured by the first shot. Silence is no longer tenable, although in actuality it never was. Questions have to be asked. No ifs or buts. Overseas media outlets of the thinking kind are waking up.
If we can’t face debating rationally with our critics, we are drifting on to the rocks of ignorance and prejudice.
Time for us to wake up.
NEW DATA SHOWS TROUBLING TREND IN VACCINATED
The Highwire with Del Bigtree | April 21, 2022
The Highwire with Del Bigtree | April 21, 2022
Elon Musk’s attempt to buy the social media giant Twitter has sent shockwaves through the mainstream media. Why are they so threatened by free speech?
ELON MUSK BUYING TWITTER
You’ve probably heard that billionaire Tesla-founder Elon Musk is putting together a financial package to become the sole proprietor of Twitter. Having already purchased 10% of the social media giant’s shares, Musk turned down a seat on the board of directors and decided to just buy the whole place.
To be clear, we don’t much like Musk and trust him less. The whole story is likely just another non-issue for people to squabble over.
… that said, you’d have to be made of stone not to take some bitter pleasure in watching the squirming of “liberal” pundits who are suddenly having their own sophistry turned against them.
Remember how those of us concerned about corporate censorship have always been told that “private companies can do what they want” and “if you don’t like, go make your own platform”? Well, apparently those arguments no longer apply.
In fact, according to Robert Reich in the Guardian, “going to another platform” is not an option. Funny that.
Mehdi Hasan rants about Musk’s “problematic free speech escapade” in his latest show, setting up a strawman so large he could burn it and guarantee a bountiful harvest.
The Conversation hosts an article that argues allowing everyone equal room to express themselves is actually bad for free speech because it doesn’t protect “the vulnerable” from harassment.
But the prize for the most-revealing reaction goes to Max Boot of the Washington Post, who said on twitter:
It’s delightful. From the refusal to acknowledge that the paper he works for was only just recently purchased by Jeff Bezos, the second richest man in the world, to the coy euphemism for censorship, all good stuff.
But why is all this happening? And where is it all going?
There are a few ways this could go. For one, the government might step in and stop Musk from buying the company. Protecting social media from becoming a “monopoly”, scoring some points with the “left” for “standing up to billionaires”, and setting a precedent for state interference in private business.
It could be that Musk does buy twitter, and scraps any limitations in line with his “free speech absolutist” claims… but then nation-states will be “forced” to make new rules limiting speech since “irresponsible tech companies refuse to act to stop hate speech” or something along those lines.
Whatever happens, its easy to see how this could further the war on free speech, one way or another. Or maybe nothing will happen at all, and it’s just fun and games.
How to lie with statistics – Vaccine efficacy edition
The Naked Emperor’s Newsletter | April 23, 2022
Just a quick post to show another method of how to increase vaccine efficacy. This time looking at data from Switzerland and Liechtenstein (S&L).
By mid December 2021, S&L were at the peak of their third wave. It was ok though because 67% of the country had been fully vaccinated, 17% with a booster. 32% of selfish people had still not been vaccinated however.
As the vaccines stop people from going to hospital this would show up in the stats.
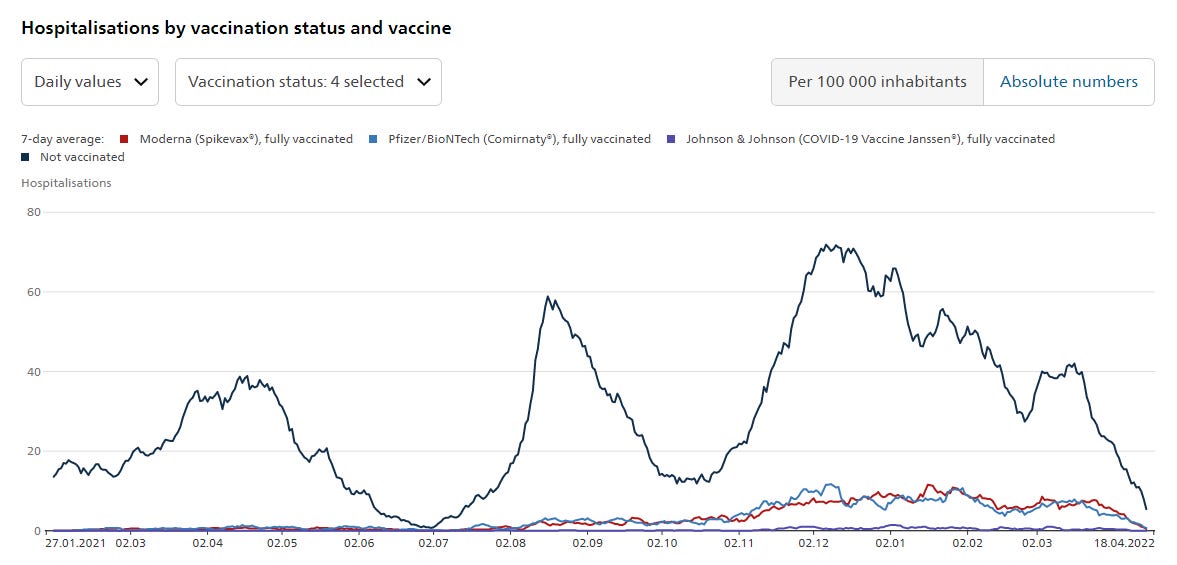
Yes, as predicted, there was a slight increase in hospitalisations for fully vaccinated citizens (Moderna – red line, Pfizer – light blue line) but a massive spike in hospitalisations for those pesky unvaccinated (dark blue line).
Job done, vaccine efficacy proven.
But hold on a second, there is another category. “Vaccine unknown, fully vaccinated”. Let’s add this to the graph.
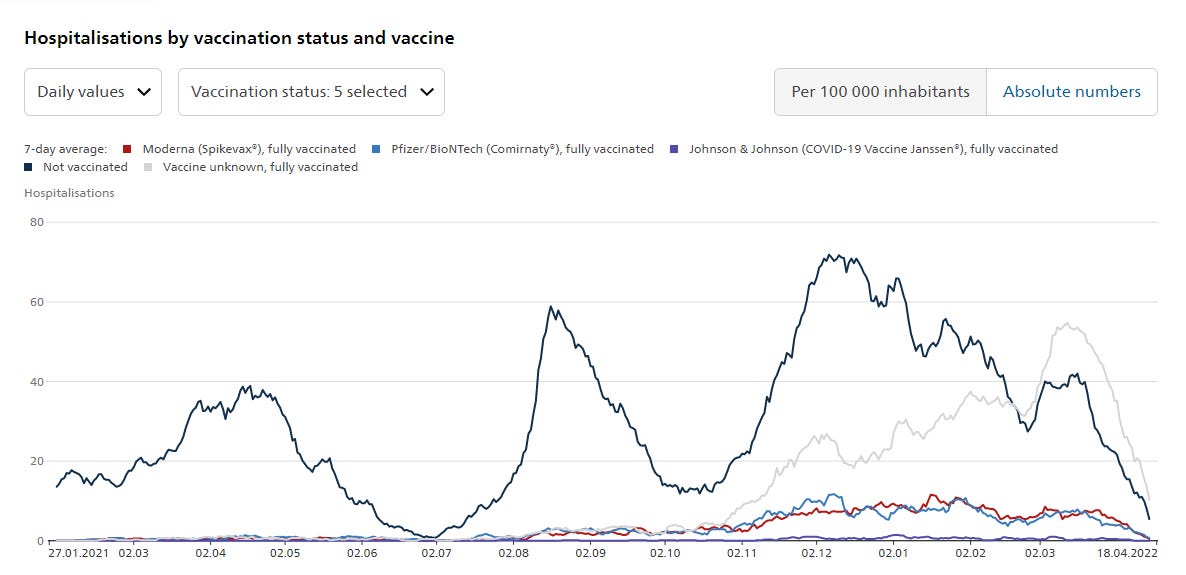
They don’t really want you to see this line so have made it a faint grey colour. However much they would like to pretend it wasn’t there, it is. And it shows a lot of fully vaccinated people going to hospital, and continuing to go to hospital, until March 2022, well after the peak for unvaccinated individuals.
Lot’s of fully vaccinated people going into hospital who have forgotten which vaccines they had. Did they forget or were they too ill? Is this an admin issue or are these people who had a combination of vaccines and so couldn’t be put in one category?
Either way, this grey lined category shifts a lot of people out of the Pfizer and Moderna vaccinated categories. It makes vaccine efficacy look much better than it actually is by saying only this many Pfizer or Moderna vaccinees were hospitalised.
Another great example of how to lie with statistics.
EU commission sued over Covid-19 vaccine secrecy
Samizdat | April 23, 2022
Five Green MEPs are suing the European Commission over its ultra-secretive vaccine contracts, arguing that the heavily redacted versions released by the EC “made it impossible to understand the content of the agreements,” in a statement published Friday.
“Secrecy is a breeding ground for distrust and skepticism, and it has no place in public agreements with pharmaceutical companies,” Margrete Auken, a Danish MEP involved in the suit, declared, adding that “the European Commission’s refusal to provide transparency on its vaccine contracts affects the public’s confidence in the EU’s ability to obtain the best possible outcome for its citizens.”
The MEPs are demanding the details of the contracts the EC signed with vaccine-makers BioNTech, Pfizer, Moderna, AstraZeneca, Johnson & Johnson, and Novavax, including price per dose, advance payments, conditions for vaccine donations, liability, and indemnification matters.
“Purchases made with public money should come with public information, definitely in matters of health,” Dutch MEP and party to the lawsuit Kim van Sparrentak said in the group’s statement, noting that “confidentiality under the guise of trade secrets only fuels uncertainty and fear.”
In addition to Auken and van Sparrentak, the MEPs signing on to the suit are Tilly Metz (Luxembourg), Jutta Paulus (Germany), and Michele Rivasi (France), the chair of the parliament’s committee on Covid-19.
The lawsuit, filed in the European Court of Justice in Luxembourg, comes as EC President Ursula von der Leyen revealed that every EU member state would be required to adopt EU Digital Covid Certificates, a digital health passport issued to those with proof of vaccination, a negative PCR test, or proof of recovery from Covid-19. While the validity period for such certificates was due to lapse at the end of June, the EC is not only renewing it another year, but making it mandatory for all 27 EU countries from July 1. Only 15 are currently using it, according to von der Leyen.
The move comes despite many EU states winding down their Covid-19 restrictions, moving away from some of the stricter measures imposed in the first 18 months of the pandemic. Germany, which had initially sought to require all citizens over the age of 60 to receive a Covid-19 vaccine, has been forced to axe those plans after they were voted down in the Bundestag, though the country’s health minister has warned that the government may reimpose mask mandates, as he expects infections to increase in the fall.
In response to the lawsuit, the EC has insisted it cannot reveal the contracts it signed with the vaccine-makers back in 2020, claiming “the commission is in the business of respecting contracts.” At the time, EU lawmakers who wanted to see the contracts were prohibited from taking notes and forced to sign non-disclosure agreements.
Much of the world seemed to be headed for mandatory Covid-19 vaccination six months ago. However, the realization that despite their manufacturers’ initial promises, the vaccines were no magic bullet – not only incapable of stopping the spread, but incapable of preventing further infection – has cooled public fervor for mandates. Health concerns and complaints of discrimination against the unvaccinated have also contributed to the backlash. However, the manufacturers, as well as most officials, continue to insist that the vaccines are “safe and effective.”
Berlin Senate tries to hush dramatic increase in heart complaints and strokes in 2021
Free West Media | April 20, 2022
The Berlin SPD member of parliament Robert Schaddach inquired in March with a parliamentary question to the Senate’s internal administration about the development of relevant fire brigade incidents that suggest the suspicion of vaccination consequences. Schaddach said: “The aim of the question is to determine the development of the Berlin fire brigade’s deployment figures with regard to heart complaints and strokes over the past four years.”
The answer of the senate administration gives cause for concern. Under the headings of “Heart Complaints/Implanted Defibrillator” and “Chest Pain/Other Chest Complaints”, the number of logged deployments in 2021 increased by 31 percent to a total of 43,806 deployments compared to the averages from 2018/2019. Similarly, the number of logged deployments under the keywords “Stroke/Transient Ischaemic (TIA) Attack” increased by 27 percent to a total of 13,096 deployments compared to the averages from 2018/2019.
However, the Berlin Senate Administration does not want to comment on this development. It writes evasively in its response of April 7: “Changes in the frequency of use of the main complaint protocols ‘Heart complaints/Implanted defibrillator’ as well as ‘Chest pain/Other complaints in the chest’ within the framework of the standardised emergency call query may be related to more intensive protocol use, the classification of symptoms, the further development of quality management, but also changes in the number of emergency rescue deployments, for example due to population growth or demographic change.”
While the Berlin Senate administration is trying to keep the information out of the public eye, its response was received with all the more interest by the Feuerwehrgemeinschaft Berlin, an association of several hundred firefighters critical of vaccination. A spokesperson for the association explained: “Such rates of increase need to be explained.” He also said it was striking that the highest rates of increase are occurring precisely in the age groups that are not commonly understood to be vulnerable groups.
It is now necessary to “examine whether there is a causal connection here with the vaccination side effects caused by the Corona vaccine, which have increasingly come into the media spotlight”, according to the fire brigade community. It therefore “urges the management of the Berlin fire brigade to initiate a scientific and open-ended investigation of a possible connection in cooperation with the experts of the Robert Koch Institute (RKI) and the Paul Ehrlich Institute (PEI)”.
Until meaningful results are available, the “facility-based vaccination obligation”, which is still in force, must be suspended.
As jabbed athletes collapse, the authorities look the other way
By Guy Hatchard | TCW Defending Freedom | April 21, 2022
THROUGHOUT 2021, attempts were made to debunk persistent reports that an unusual number of athletes were suffering cardiac events which might be related to mRNA Covid vaccination. The main theme of these fact-checking efforts was denial – athletes were not at risk and cardiac events were not happening.
In 2022 this dialogue is evolving because the numbers are growing and harder to ignore. According to an investigative report by OAN, a pro-Trump online US news site, 769 athletes suffered sudden health events between March 2021 and March 2022 with an average age of 23 years. In February, 15 top tennis players were unable to complete their matches in the Miami Open tournament.
Of necessity in the face of mounting numbers of injury reports, the fact-checking dialogue has hesitated on the brink, but on February 1 this year, the Washington Post still labelled stories of adverse effects of mRNA vaccines on athletes FALSE. Its story relied heavily on a discussion of the Danish footballer Christian Eriksen, who suffered a cardiac arrest on June 12 2021 just before half time in a match against Finland. The circulation of the apparently false story that Eriksen had been vaccinated was attributed by the Washington Post to a shady far-Right group in Austria seeking to influence their upcoming election.
 Dig deeper and the story gets more murky. Few if any of the participants in this argument on both sides have verified hard facts to hand. The Washington Post, which had probably realised by February that it was quite possible that an unusual number of athletes were unexpectedly falling to the ground, decided to finish its article by asserting that the sporting collapses must be down to Covid, not Covid vaccination. Again no hard facts about actual athletes, just a polarised muck-throwing event.
As a scientist I realise that what is lacking here is reliable data. Why is it lacking? Here is the nub – the authorities are so sure they are right about the safety of vaccines that they are refusing to collect data. New Zealand has refused to institute mandatory reporting of adverse events following mRNA vaccination and other countries are in the same boat. We don’t have a lot of data to go on because it is not being collected. Sporting bodies are not counting either, or perhaps they have lost count or looked the other way.
Delving into the world of psychology, I find this unsettling. Why wouldn’t we collect data? Why aren’t we allowed to ask questions? Why isn’t the Ministry of Health counting and publishing up-to-date medical data on the frequency of cardiac and thrombotic events of all types?
There are stories in the popular press (actually not so popular these days) reporting recent excess cardiac events as due to ‘holiday heart syndrome’ or the need for young people ‘to avoid strenuous exercise’. Neither of these had been a thing until 2021. Why hasn’t the MoH quashed these speculative sallies into obfuscation by publishing data? You tell me.
The finger-pointing gets worse. One particular ‘whack-an-antivaxxer’ sport recently originated at Otago Medical School in New Zealand. A popular digest of a study of 1,000 people born in Dunedin in 1972 was reprinted in leading publications around the world. The article implied that anti-vaxxers suffered from sexual abuse, maltreatment, deprivation or neglect, or having an alcoholic parent as they were growing up. They were also described as low educational achievers likely to suffer from mental illness.
I am a little sceptical by nature, so I noticed that the reports were based on an article in a publication called The Conversation, which has received support during the pandemic from the Bill and Melinda Gates Foundation. The Conversation describes itself as both devoted to academic rigour and seeking to explain science to the general public. Curiously its article about the Dunedin survey contained only one quantitative piece of information – 13 per cent of the respondents were vaccine resistant. No other quantitative information was provided to support the extreme characterisation of the vaccine hesitant in the article.
I tracked down the actual study entitled ‘Deep-seated psychological histories of COVID-19 vaccine hesitance and resistance’. Seven of the ten authors were based in the USA. One of the authors disclosed that he is funded by the US Centers for Disease Control and Prevention.
The survey completed in April 2021 actually found that 13 per cent of the respondents were vaccine resistant and 12 per cent were vaccine hesitant. So fully 25 per cent of the respondents were vaccine hesitant to varying degrees.
I then rapidly came across an old friend used to distort information: absolute differences versus relative differences.
Of those willing to vaccinate (note the word used is willing, not necessarily keen), 62 per cent had at least one Adverse Childhood Event (ACE). Of those hesitant or resistant to vaccination 73 per cent had at least one ACE. The difference between 62 and 73 per cent is not large in absolute terms.
Based on this small difference, Professor Richie Poulton, a Dunedin-based co-author of the study, was quoted in the Otago Daily Times as saying about the vaccine hesitant and resistant responders:
‘The childhood experiences of those surveyed ranged from sexual abuse, parental neglect, poverty, to isolation and lack of achievement in school. They covered the whole suite of difficulties you can think of that might impinge on a person’s good development. Their personality became very stress reactive – they saw danger or threat where there essentially was none.’
Now you probably did percentages at school, so do you think Professor Poulton’s comments accurately reflect the difference between 62 per cent and 73 per cent exposures to at least one ACE? Because I certainly don’t. A significant percentage of both groups experienced ACEs growing up, but they had different opinions about vaccination.
Wouldn’t it be more productive to ask: why do we have such a high rate of ACEs in New Zealand? Is our mental health service under-funded? Is our education system failing us? Is support for families sufficient?
I went further down the pages examining results of a battery of ‘questionnaires’. I found that although there were measurable differences between the two groups: ‘vaccine willing’ and ‘vaccine hesitant and resistant’, their average scores were well within the standard deviation of the mean standardised score for each test.
This means most of those responding to the survey were relatively average people. The vaccine hesitant and resistant were being falsely characterised as ill-educated social deviants. This sounds like victim blaming. So much for the academic rigour and capacity to explain science to which The Conversation proudly aspires.
Were the media comments about the study an unsupported and false attempt to discredit the unvaccinated and categorise them as outcasts and misfits without the necessary intelligence to think for themselves? The small differences between the two groups were insufficient to justify this black-and-white condemnation widely shared around the world’s media.
There were some differences in educational attainment. Some 35 per cent of the vaccine willing had a BA degree or higher, while 15 per cent of the vaccine hesitant or resistant had a BA or higher. However the Dunedin results may be misleading regarding the influence of education. A study in the USA found that people with a PhD were more likely to be vaccine hesitant, implying that a decision not to vaccinate may possibly be encouraged by the development of high level critical thinking.
In the mainstream media articles, Professor Poulton pleaded with us to feel pity for the unvaccinated, because of their supposed difficult childhood (which was in fact not so different from that of the vaccinated). Was he simply lowering our opinion of the unvaccinated by playing upon stereotypes? Subtly hammering home the current mainstream media messaging that only Right-wing extremists and selfish antisocials remain unvaccinated.
Did he realise that the unvaccinated are legitimately concerned about the vaccinated because they have been unwittingly exposed to serious but as yet unquantified medical risk?
As I am aware that Covid mRNA vaccine adverse events are running at 30-50 times higher than any previous vaccine, I would ask different questions of the data:
- Were those willing to be vaccinated being misled by the inadequate content of their education?
- Do prior adverse experiences provide good reason to be more cautious in future?
The Immunisation Advisory Centre at the respected University of Auckland (incidentally partly funded by pro-vaccine interests) reassuringly says:
‘Confirmed cases of myocarditis are rare. More than 80 per cent of reported cases of myocarditis following mRNA Covid vaccination have recovered quickly with rest and commonly used oral anti-inflammatory medications such as ibuprofen.’
Are you reassured by this, or have you looked at the Medsafe adverse event data where 18,000 mRNA vaccine recipients reported chest pain and shortness of breath – symptoms admitted by the Immunisation Advisory Centre to be indicative of myocarditis?
Have you concluded, like me, that as many as 80 per cent of cases of myocarditis among the vaccinated remain unreported and untreated? A ticking time bomb, of which professional athletes represent only the tip of the iceberg.
The question is, how long are our health authorities going to continue to look the other way and refuse to start counting accurately, appropriately, and retrospectively?
CDC Weighs ‘Upgrades’ to COVID Vaccines as Booster Strategy Fails
By James Lyons-Weiler | PopularRationalism | April 21, 2022
According to CNN, CDC’s Advisory Committee on Immunization Practices (ACIP) continue to “mull over” what’s next for Covid-19 boosters, and indeed are even considering what the “upgrades” Covid-19 vaccines. There are indications that they know that “entirely different vaccine formulations could be needed”.
Currently, additional booster doses are recommended only for certain people with weakened immune systems and adults 50 and older.
CDC quoted Dr. Sara Oliver, one of CDC’s epidemic intelligence service officers with the Division of Viral Diseases, who provided a robust soundbite:
“Policy around future doses require continued evaluation of Covid-19 epidemiology and vaccine effectiveness, including the impact of both time and variants, and the ability of doses to improve this protection.”
The specifics CNN cited Oliver as seeing CDC needing to take into account include recent case counts, hospitalization rates, and vaccine effectiveness in the US, and also – shocking – including whether it’s waning over time. They also cited that she thought CDC should weigh “the impacts of circulating coronavirus variants”.
We know vaccine effectiveness is unacceptably low – and given Dr. Fantini’s results may actually be negative, indicating disease enhancement.
Oliver stated that the evolution of the virus will be an important consideration for considering “platforms” for future COVID-19 vaccinations.
It’s not hard to read between the lines here. Readers of PopularRationalism already know that the mRNA vaccines have proven to be worse than a dismal failure. This is CDC putting the word out that a second round of vaccine development is expected, and is about the closest we’ll ever see to CDC admitting the vaccination program has flopped.
And it’s surprising to see ACIP being focused on future “effectiveness”. Clearly, if newly formulated vaccines are proposed, they will be a square one in terms of the regulatory stage of development, and we should be seeing data on efficacy, which is a measure of a vaccine’s ability to reduce transmission in a prospective randomized clinical trial, not effectiveness, which is measured using real-world data.
As the real-world data on COVID-19 vaccine effectiveness came in, it was quite bad, so the net was lowered from “preventing transmission” and “reducing new infections” to “producing an antibody response”.
So far, according to USASpending.Gov, the US has now spent over 3.63 trillion dollars in its response to COVID-19. According to the US Center for Economic Studies, the US suffered record-smashing loss of -9.5% of its GDP in 2020, and over 30% shrinkage in economic growth.
Nevertheless, both Pfizer and Moderna are taking a stab at vaccines meant to be available against Omicron, but it is doubted whether the variant will be around long enough to even be targeted by the new vaccines. Pfizer is hoping for a vaccine that will remain effective for more than a year, while Moderna’s non-peer-reviewed preprint containing data from their internal study of the efficacy of their bivalent vaccine was cited by CDC with the careful caveat that the preprint had “not been peer-reviewed or published in a professional journal.”
In the heyday of the pandemic, Pfizer and Moderna could get away with sending FDA assurances that they would share data mentioned in press releases once the FDA gave EUA or full-out approval. Now that the fog of the pandemic has lifted, it seems that the standard practice of labeling press releases, such as Moderna’s recent one on their bivalent vaccine as “Forward Looking Statements” is in place, so I suspect Moderna, Pfizer and the SEC got my memos.
Due to evidence of lack of efficacy and need, FDA, Pfizer and Moderna have delayed further consideration of COVID-19 vaccines for young children until June, according to Politico (SeekingAlpha, Politico).
Unfortunately, the companies are still communicating “success” as equivalent with “antibody response” when we all know (or at least my immunology students know that they really should be measuring and reporting memory B-cell responses and the degree of match between the antibodies produced by B-cells upon reinfection and whatever variant or variants have taken over after Omicron is a distant memory.
CDC also shared that Kaiser Permanente – which profits from vaccine sales – was in the driver’s seat of the CDC’s ACIP committee, with Dr. Matthew Daley, ACIP Vaccine Working Group Chairperson and senior investigator at the Kaiser Permanente Institute for Health Research issuing “marching orders” to the rest of ACIP to be “be more proactive than reactive” on the future of Covid-19 vaccinations.
This article is just a reminder to those who need it that #ParentsAreWatching, and that #ScientistsAreWatching, too.
Rhode Island bill plans to DOUBLE tax for parents of unvaccinated children
By Kit Knightly | OffGuardian | April 21, 2022
A bill recently placed before the Rhode Island legislature contains clauses that would make Covid vaccination mandatory for everyone over the age of 16, and double state income tax for all parents who refused to inject their children with Covid the experimental Covid “vaccines”.
The bill, titled “HEALTH AND SAFETY- IMMUNIZATION AGAINST COVID-19 ACT” and introduced by State Senator Samuel Bell lays out in S1 (a) and (b):
(a) Every person of at least sixteen (16) years of age who is eligible for immunization against COVID-19 and who resides in the State of Rhode Island, works in the State of Rhode Island, or pays personal income taxes to the State of Rhode Island pursuant to chapter 30 of title 44 shall be required to be immunized against COVID-19.
(b) Every resident of Rhode Island eligible for immunization against COVID-19 who is under sixteen (16) years of age or under guardianship shall be required to be immunized against COVID-19, with the responsibility for ensuring compliance falling on all parents or guardians with medical consent powers pursuant to § 23-4.6-1.
And then details stringent financial penalties in S1(e) [emphasis added]:
Any person who violates this chapter shall be required to pay a monthly civil penalty of fifty dollars ($50.00) and shall owe TWICE THE AMOUNT OF PERSONAL INCOME TAXES as would otherwise be assessed pursuant to chapter 30 of title 44.
This is by far most punitive “anti-vaxxer” legislation we’ve seen (so far). Even if it does not pass, it shows us that the Covid agenda is still very real, and they are not even close to done trying to bully people into compliance.
You can download the whole bill here.
Featured Video

When Israel Is Mighty
or go to
Aletho News Archives – Video-Images
From the Archives
US murdering 1 million Iraqis is democracy, Iran giving yogurt to Iraq is “domination”
By Ali Salaam | American Herald Tribune | July 31, 2017
The New York Times, owned by the Zionist Jewish supremacist Ochs-Sulzberger family, has no problem with Iraqi suffering as long as Iran is not the one behind it.
The Iraq War was a genocide of the Iraqi people by Zionist supremacists in the Bush administration. Over 1 million innocent people were killed based on a lie. American soldiers died in an Israeli war and now an average of 22 soldiers commit suicide every day because their consciences cannot cope with the fact they committed crimes in an illegal war that served no purpose other than to benefit Israel, not America.
Benjamin Netanyahu, Prime Minister of the Zionist regime, once said “We are benefiting from one thing, and that is the attack on the Twin Towers and Pentagon, and the American struggle in Iraq.”
Paul Wolfowitz had his sights on Iraq since his time in the first Bush administration. Former Israeli official and Bush administration official Richard Perle had his eyes on Iraq since at least his authorship of the Clean Break white paper. The Zionist regime had their eyes on Iraq since the 1980s when strategist Oded Yinon wrote his white paper in support of dividing the Arab-Muslim world along ethnic and sectarian lines. The global Zionist lobby has had their eyes on Iraq since Theodor Herzl stated that Eretz Israel’s true borders go from the Nile River in Egypt to the Euphrates River in Iraq. … continue
Blog Roll
 Aletho News
- MEP blasts ‘Euro-Gestapo’ for lecturing Russia on democracy
- Syria May Send Troops to Saudi Arabia Amid War with Ansar Allah
- UK whines about losing billions to ‘Putin tax’
- Baghaei to Rubio: Distorted narratives cannot erase US record of broken commitments
- Houthis Don’t Have to Conquer Saudi Arabia to Make It Pay
- MOE: Nearly 22,000 Students and Education Workers Killed
- Guterres in Islamabad: Genocide, cowardice, and the cage of Imran Khan
- Johnson, Marandi say Yemen holds upper hand over Saudi Arabia
- False flags won’t save aggressors, Iran FM spokesman says
- The Makkah Pact Enters Into Force: The End of American Dominance or Its New Form?
- If Americans Knew
- Report claimed Mark Levin used by Israeli government to influence Trump
- Over 2,000 Gazans have died awaiting medical evacuation amid Israel’s continued siege
- How a U.S. Diplomat Suppressed and Altered Reports Critical of Israel
- 5 Palestinians Die from Israeli Strikes in Gaza as Relentless Attacks Continue
- Report: Ceasefire Slows Killing but Leaves Devastation Intact
- Country Music Singer Zach Bryan Breaks Attendance Record at Robert Kraft’s Gillette Stadium While Wearing ‘Free Palestine’ Shirt for Second Night in a Row
- Three years of death and devastation: Israel’s war on Gaza in pictures
- Why Hamas believed the status quo was more dangerous than its 7 October gamble
- Debunking Israel’s latest list of ‘terrorist’ journalists in Gaza
- In Gaza, focus is on survival, “every step is a struggle” – Daily Update
- No Tricks Zone
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative

