Pfizer hired about 600 additional full-time employees to process adverse event reports during the three months following the Emergency Use Authorization (EUA) of its COVID-19 vaccine, newly released documents reveal.
According to the documents, Pfizer said, “More are joining each month with an expected total of more than 1,800 additional resources by the end of June 2021.”
The information was contained in a 10,000-page document cache released April 1 by the U.S. Food and Drug Administration (FDA) and made public as part of a court-ordered disclosure schedule stemming from an expedited Freedom of Information Act (FOIA) request.
The latest revelations appeared in a document, “Cumulative analysis of post-authorization adverse event reports” of the Pfizer-BioNTech vaccine, highlighting such adverse events identified through Feb. 28, 2021.
The document was previously released in November 2021, but was partially redacted. The redactions included the number of employees Pfizer hired and/or was planning to hire.
According to the unredacted document released April 1:
“Pfizer has also taken a multiple actions [sic] to help alleviate the large increase of adverse event reports. This includes significant technology enhancements, and process and workflow solutions, as well as increasing the number of data entry and case processing colleagues.
“To date, Pfizer has onboarded approximately 600 additional full-time employees (FTEs).
“More are joining each month with an expected total of more than 1,800 additional resources by the end of June 2021.”
The unredacted version also revealed the number of Pfizer-BioNTech vaccine doses shipped worldwide between December 2020 and February 2021:
“It is estimated that approximately 126,212,580 doses of BNT162b2 [the Pfizer EUA vaccine] were shipped worldwide from the receipt of the first temporary authorisation for emergency supply on 01 December 2020 through 28 February 2021.”
The number of shipped doses previously was redacted.
Remarking upon this newly revealed information, Brian Hooker, chief scientific officer of Children’s Health Defense, told The Defender :
“The rollout of the Pfizer vaccine has led to an unprecedented number of adverse events reported — 158,000 adverse events in the first two-plus months of the rollout means that the rate of reported AE [adverse events] was approximately 1:1000, with many of the AEs graded as serious. This is based on a denominator of 125,000,000 vaccines distributed.
“It is no wonder that an army of 1,800 individuals was needed to process all of the information.”
Hooker noted the total number (1,205,755) of COVID vaccine adverse events reported to the Vaccine Adverse Event Reporting System between Dec. 14, 2020 and March 25, 2022, now eclipses the total number (930,952) of adverse events reported in the 32-year history of the database.
Dr. Madhava Setty, a board-certified anesthesiologist and senior science editor for The Defender, previously reported on the same Pfizer document, before the unredacted version was released.
“In that piece, I alluded to Pfizer’s admission that they needed more staff to process all of the adverse events being reported to them,” Setty said.
“It seems this document has now been updated. 600 FTEs [full-time employees]! … I wonder how many extra people the CDC [U.S. Centers for Disease Control and Protection] has hired? Given how they are operating, I would say zero.”
Pfizer downplayed adverse reactions in request for full FDA license
The April 1 document release also included “request for priority review” — the documentation Pfizer in May 2021 submitted to the FDA for full licensure of its Comirnaty COVID vaccine.
In this document, Pfizer described its vaccine as fulfilling an “unmet medical need,” claiming:
“Mass immunization with a safe and effective vaccine against COVID-19 can dramatically alter the trajectory of the pandemic.
“According to policy briefing by the Institute for Health Metrics and Evaluation published on 31 March 2021, COVID-19 remains a leading cause of death in the US with up to 100,000 additional deaths projected in the US between March and July 2021, many of which can likely be prevented with COVID-19 vaccination.”
Pfizer expressed “concerns” about lifting COVID-related measures, such as lockdowns, on the basis that the lifting of such restrictions would “counteract the impacts of this vaccination effort.”
The document states:
“Vaccination against COVID-19 began with EUA/conditional approvals in December 2020, in a phased rollout defined by national/regional guidance.
- “However, there continue to be concerning trends that may counteract the impacts of this vaccination effort, including:
- “[L]imitations in access to obtaining a vaccine due to infrastructure challenges (ie, clinic and appointment capacity and systems)
- “[I]ncreasing viral transmission fueled by relaxed compliance with mitigations as the pandemic surpasses the 1-year mark (ie, masks, physical distancing, limiting travel)
- “[I]ncreasing circulation of emerging variants of concern (which are currently driving continued spread of viral infection in Europe despite extensive mitigation mandates).”
Pfizer justified its request for full licensure of its COVID vaccine on the following basis:
“A vaccine program must be implemented expediently and rapidly expanded to have a significant impact on the pandemic course.
“Licensure of BNT162b2 is likely to enhance vaccine uptake by facilitating supply of vaccine from Pfizer/BioNTech directly to pharmacies and healthcare providers/facilities.
“The greatest impact of BNT162b2 licensure may be direct supply to healthcare providers who serve vulnerable populations such as elderly patients and those who live in rural and underserved communities (ie, individuals who might be unable to navigate the challenges of securing vaccine access using the systems in place for EUA).
“Expansion of vaccine via licensure would ultimately improve the prospect of achieving population herd immunity to bring the pandemic under control.”
The same document glossed over the adverse effects for which the company previously admitted it hired a significant number of new employees to process, claiming:
“Based on Phase 1 data from the FIH Study BNT162-01, BNT162b1 and BNT162b2 [various vaccines tested during the trial period] were safe and well-tolerated in healthy adults 18 to 55 years of age, with no unanticipated safety findings.
“Phase 2/3 safety data were generally concordant with safety data in Phase 1 of the study, both overall and with regard to younger and older participants.”
This is despite hard figures regarding adverse reactions provided later in the document:
“Through 28 February 2021 (data lock point aligned with Pharmacovigilance Plan), there were a total of 42,086 case reports (25,379 medically confirmed and 16,707 non-medically confirmed) containing 158,893 events. Cases were received from 63 countries.
“Consistent with what was seen in Phase 2/3 of Study C4591001, most reported AEs were in System Organ Classes (SOCs) with reactogenicity events: general disorders and administration site conditions (51,335), nervous system disorders (25,957), musculoskeletal and connective tissue disorders (17,283), and gastrointestinal disorders (14,096).
“Post-authorization data have also informed the addition of adverse drug reactions (ADRs) related to the experience of reactogenicity to the product labeling.”
Release of Pfizer vaccine documents still in progress
Many of the documents released as part of the April 1 tranche appear to include more mundane information and data related to the Pfizer COVID vaccine trials.
These documents include:
- Peer-reviewed scientific articles funded by Pfizer-BioNTech, titled “Phase 1/2 Study of COVID-19 RNA Vaccine” (August 2020) and “Safety and Immunogenicity of Two RANA-Based Covid-19 Vaccine Candidates,” published in the New England Journal of Medicine in October 2020.These studies supported “further evaluation of this mRNA vaccine candidate” despite the apparent appearance of serious adverse effects in one of the 12 participants receiving 30 μg and 100 μg doses of the BNT162b1 candidate vaccine during the trial phase. This, however, does not appear to have been the final vaccine formulation that ultimately received an EUA.
- A questionnaire that vaccine trial participants were required to complete, along with a study book displaying the information to be collected from those participating.
- Documents outlining the randomization scheme used for identifying vaccine trial participants and those who received doses of the vaccine or a placebo.
- Documents listing anonymized demographic characteristics of vaccine trial participants.
- An anonymized listing of important protocol deviations.
- Consent forms that vaccine trial participants were asked to complete, as well as other related documents submitted by Pfizer for Institutional Review Board (IRB) approval, and information regarding institutions participating in the IRB process.
- Clinical study approval forms.
- Audit certificates for vaccine trial locations.
The next set of documents — an expected 80,000 pages — is scheduled to be released on or before May 1.
Michael Nevradakis, Ph.D., is an independent journalist and researcher based in Athens, Greece.
April 6, 2022
Posted by aletho |
Deception, Science and Pseudo-Science | CDC, COVID-19 Vaccine |
Leave a comment
Del catches up with ICAN Lead Attorney, Aaron Siri, Esq, on the recent legal win against Washington D.C., putting the kibosh on the outrageous law which allowed minors to get vaccinated without parental consent.
April 5, 2022
Posted by aletho |
Civil Liberties, Corruption, Deception, Science and Pseudo-Science, Timeless or most popular, Video | CDC, COVID-19 Vaccine, United States |
Leave a comment
The Highwire with Del Bigtree | March 31, 2022
Former British broadcasting executive, Mark Sharman, recently spoke out about the incredible failures of the media during Covid by warning journalists not to question the official government line in their reporting.
From the legislative arena to big business, Covid restrictions seem to be in their final day. Businesses have begun re-hiring unvaccinated workers, airline CEOs are calling for an end to Biden’s federal mask mandate, and legislators are working to prevent mandates from ever happening again.
April 4, 2022
Posted by aletho |
Civil Liberties, Full Spectrum Dominance, Mainstream Media, Warmongering, Science and Pseudo-Science, Timeless or most popular, Video | Covid-19, COVID-19 Vaccine, Human rights, UK, United States |
Leave a comment

Covid vaccine myocarditis: the catecholamine hypothesis (Cadegiani)
A Brazilian investigator may have identified the mechanism driving mRNA vaccine myocarditis. And the US CDC finally acknowledges the strongly increased risk in young males.
What is causing vaccine myocarditis?
What is causing post-vaccination myocarditis, and why does it affect primarily young adults, especially young males and athletes? It has been speculated that in young males, muscle blood flow may be higher, which may cause higher biodistribution of vaccine mRNA or spike protein. The mRNA or spike protein may then be absorbed by the heart muscle and cause inflammation.
But Brazilian investigator Flavio Cadegiani, who previously looked into the role of androgens (male sexual hormones) in covid, recently proposed a new and highly intriguing theory: Based on autopsy findings, Cadegiani noted that post-vaccination myocarditis appears to be very similar not to typical myocarditis (e.g. viral myocarditis), but rather to adrenergic myocarditis or catecholamine-mediated stress cardiomyopathy (i.e. heart muscle injury caused by catecholamines).
Catecholamines are a group of hormones that include, most notably, dopamine, adrenaline and noradrenaline. These hormones drive the “fight-or-flight response”, and their concentration is highest in young adults, especially in young males and athletes. Cadegiani notes that the adrenal glands (located on top of the kidneys) are amongst the tissues with highest production of spike protein from mRNA covid vaccines, which can cause local inflammation and may lead to a “catecholamine storm”, which is known to have a toxic stress effect on heart muscle cells.
Prior to covid mRNA vaccinations, this type of heart injury was seen almost exclusively in patients with a rare tumor of the adrenal gland (called pheo-chromo-cytoma). Cadegiani suspects that mRNA vaccination is more likely to affect adrenal glands than a mild coronavirus infection, especially in young and healthy adults.
Cadegiani (February 2022): Catecholamines are the key trigger of mRNA SARS-CoV-2 and mRNA COVID-19 vaccine-induced myocarditis and sudden deaths. (ResearchGate)
New CDC study on myocarditis
In a newly published study covering data from 40 US health care systems and about 15 million people, the US CDC purports to show that “the risk for cardiac complications was significantly higher after SARS-CoV-2 infection than after mRNA COVID-19 vaccination for both males and females in all age groups”, which “supports the continued use of recommended mRNA COVID-19 vaccines among all eligible persons aged ≥5 years.”
But the actual data provided by the CDC tells a very different story.
First, the US CDC confirms that among males aged 12 to 17, the rate of diagnosed myocarditis or pericarditis after the second vaccine dose is 1 in 4,500 to 1 in 2,700, and in males aged 18 to 29, the rate is 1 in 15,000 to 1 in 6,600.
These values are significantly higher than anything previously acknowledged by the CDC, but they still only include cases diagnosed by a doctor or in a hospital. If undiagnosed and unrecognized (subclinical) cases of myocarditis and pericarditis are taken into acccount, the rate will likely reach about 1 in 1,000 in young males. Even an undiagnosed case of myocarditis can turn out to be fatal, as the many recent cases of athletes with sudden cardiac arrest have shown.
However, the CDC argues that the risk of diagnosed myocarditis and pericarditis is still higher after SARS-CoV-2 infection, viz. 1 in 2,000 to 1 in 1,500 in males aged 12 to 17, and 1 in 1,800 to 1 in 1,000 in males aged 18 to 29. But previous studies, both in the US and in Europe, have already shown that the incidence of myocarditis remained normal or even below average during major covid waves in 2020 and early 2021 and only increased during vaccination campaigns in 2021 (see chart below).
So what did the CDC get wrong? It’s a classic mistake (or trick): while the CDC speaks of “SARS-CoV-2 infections”, they in fact only captured positive tests and only within the health care system (i.e. at a doctor’s office or in a hospital). SARS-CoV-2 infections were not captured “if testing occurred in homes, schools, community sites, or pharmacies”, or, one may add, if no testing at all occurred. Thus, the CDC captured only a fraction of actual infections (perhaps 10% or even less), and they likely captured only the most severe infections (i.e. young adults who visited a doctor or a hospital).
(In a somewhat related development, the CDC recently reduced US child covid deaths by 25%, as these deaths, while testing positive, had nothing at all to do with covid.)
But the CDC made another basic mistake: not only is the risk of myocarditis/pericarditis after vaccination in young males higher than after infection (as already shown by several other studies), but vaccination doesn’t prevent infection, either, and there is still no evidence that vaccination reduces the risk of post-infection myocarditis in young adults. In other words, the risk after vaccination simply increases the already existing risk after infection.
To make matters even worse, the CDC study considered only the first two doses of covid vaccination, whereas some US colleges and universities have already mandated a third dose for their students, adding even more risk. In fact, a booster dose may well increase the total risk of myocarditis and pericarditis to more than 1 in 1,000 in otherwise perfectly healthy young males. And as a recently published cardiac MRI study has shown, heart abnormalities in adolescents with mRNA vaccine myopericarditis may persist for at least several months.
In conclusion, the forced covid vaccination of young and healthy adults and children may constitute the largest medical scandal, or medical crime, in modern history. Based on the currently available evidence, covid vaccination is only appropriate in people at significant risk of severe acute covid.
CDC (April 2022): Cardiac Complications After SARS-CoV-2 Infection and mRNA COVID-19 Vaccination (CDC/MMWR)
Figure: Myocarditis and Covid Vaccination in the Western US

Myocarditis and Covid Vaccination in the Western US (JAMA )
April 4, 2022
Posted by aletho |
Deception, Science and Pseudo-Science, War Crimes | CDC, Covid-19, COVID-19 Vaccine, United States |
Leave a comment
While Germany’s Health Minister Karl Lauterbach continues to insist the mRNA technology vaccines are “more or less free of side effects”, German commentary site achgut.com here reports how vaccine injuries have exploded across Germany.
Waiting list grows to 800
The site reports “the Marburg University Hospital has set up a special outpatient clinic for patients with side effects after the Corona vaccination, and the waiting list has grown to about 800 patients.”
Recently a number of doctors have been warning about the risks of the vaccines at achgut.com: Dr. Gunter Frank, Dr. Jochen Ziegler and Dr. Andreas Zimmermann.
“Virtually overrun” by patients
Dr. Jochen Ziegler wrote Germany could have “a real socio-medical emergency” that would also even result in “a fundamental crisis of confidence in the state and its institutions”.
Slowly, and ever so hesitantly, the first major media outlets like Austrian Servus TV and Germany’s ARD plusminus, have reported on vaccine side effects. Most recently the Berliner Zeitung reported on physician Erich Freisleben, whose practice is virtually “overrun” by patients with vaccination side effects.
Potentially 1 million affected
According to Achgut.com, Dr. Freisleben “estimates the cases of severe vaccine side effects at three percent. That would affect a projected one million people in Germany alone.”
According to Freisleben: “I’ve seen maybe five or six side effects with vaccines before in 35 years of practicing medicine. For the novel vaccines, I have now counted 96. That’s out of proportion.”
Ignoring history
Achgut.com comments that “we are dealing here with a completely new vaccination technology” and: “We do not yet know what the new mRNA vaccines will do to our immune system.”
Freisleben warns against compulsory vaccination and that a “softening of the Basic Law would mean not having understood the lessons of history.”
“Compulsory vaccination would open the door wide to abuse,” the Berlin physician adds.
April 3, 2022
Posted by aletho |
Civil Liberties, War Crimes | COVID-19 Vaccine, Germany, Human rights |
Leave a comment
Moderna last week said it will seek Emergency Use Authorization (EUA) for its COVID-19 pediatric vaccine, after announcing its two-dose regimen reduced cases of symptomatic disease by 43.7% in children 6 months to 2 years old and by 35.7% in children ages 2 to 6.
The company said its Phase 2/3 KidCOVE study of its mRNA-1273 in children “successfully met its primary endpoint.”
However, as Politico reported Wednesday, and as experts told The Defender, some doctors and scientists question whether Moderna’s clinical trial data will be sufficient for the U.S. Food and Drug Administration (FDA) to grant EUA for the vaccine.
Experts cited the trials’ low efficacy rates, small sample size and reliance on a research workaround called immunobridging as weaknesses that could hinder Moderna’s case.
“Given the other data that surrounds it, I don’t know that it’s a slam dunk that the FDA will move forward in terms of releasing it for emergency use,” Peter Hotez, professor of pediatrics and molecular virology and microbiology at the Baylor College of Medicine, told Politico.
“We’re still learning about the relationship between virus-neutralizing antibodies and effectiveness,” Hotez said, adding the FDA might need to raise its standards.
Experts also raised questions about the risk-benefit ratio of the COVID vaccines for an age group with a statistically insignificant risk of severe illness.
The FDA recently tabled Pfizer’s petition for EUA of its pediatric vaccine for infants and children 6 months to age 5, citing insufficient data on a third dose for children 2 to 4 years old.
Small trials hide injuries, experts say
Moderna’s trial was designed to analyze the safety, immunogenicity and tolerability of two vaccine doses in healthy children who were administered two 25-microgram doses 28 days apart, according to Clinical Trials Arena.
The sample size was small. Approximately 6,700 children were enrolled in the trial’s 6-and-under age group, including about 4,200 children between the ages of 2 and 6 and 2,500 children between 6 months and 2 years.
The trial also encompassed children in the 6- to 12-year-old age group, bringing the total to nearly 11,700 children.
According to Dr. James Campbell, professor of pediatrics and physician-scientist at the Center for Vaccine Development and Global Health at the University of Maryland School of Medicine, adult vaccine trials typically look at larger sample sizes.
Campbell, who tackled dosage studies for children for the Moderna study, said, “Instead of having 30,000 to 45,000 people — half who get the vaccine and half the placebo — we’re enrolling more like a few thousand in each of these age groups.”
Toby Rogers, Ph.D., an expert in statistics and how they relate to vaccine trials, told The Defender that 6,700 participants makes for an undersized trial.
“Researchers would call this ‘intentionally undersized to hide harms,’” Rogers said. “And this is a standard trick that pharmaceutical companies do.”
For the Moderna study, there were about 3,350 participants each in the treatment and placebo groups. An adverse event such as myocarditis might happen one out of 5,000 times, Rogers said.
“If you have only 3,300 in the treatment group, you are unlikely to see that particular harm in the clinical trial,” he said. “And, if you do see it in the treatment group, the company has ways to kick that person out of the trial.”
Rogers added:
“Say you experience myocarditis and you call the hospital at midnight and get in the car and go to the hospital, you get kicked out of the trial because you are breaking their protocols. They want you to call their doctors and not the hospital. They do that pretty regularly.”
In context, trials for the polio vaccine had a million participants.
“And now we have trials that are coming in with just a few thousand participants. It’s bad faith. This is just the tip of a large iceberg,” Rogers said.
Moderna trials show vaccine fails to meet FDA 50% efficacy standard for EUA products
Moderna’s claim that two shots of its vaccine reduced cases of symptomatic disease by 43.7% in children 6 months to 2 years old and by 35.7% in children ages 2 to 6 means the vaccine falls below the FDA’s 50% efficacy threshold for EUA products.
“No one would argue that 40 percent protection is great,” Dr. Chandy John, a pediatrician at Indiana University, told The Atlantic.
According to Politico, Moderna officials said the regimen met a metric called immunobridging, meaning the pediatric doses produced the same immune response that’s been seen in young adults.
Bridging studies are used in lieu of duplicating large-scale efficacy trials. Researchers extrapolate efficacy results from one population to predict drug efficacy in another population, according to Bernard Fritzell in a paper published in Developing Biological Standards.
In practice, using immunobridging means that pediatric vaccine researchers looked at an older group from a previous trial, who received a different dose of a vaccine with different ingredients, and decided what level of antibodies in that group were enough to ward off COVID.
They then looked at the younger children’s group to see how many of those participants had that same level of antibodies — a process that is not predictive of an individual’s ability to fight off infections, Rogers said.
Rogers added:
“So moving forward, into this mythical future, we predict that this many kids with antibodies will be protected. If this was a legitimate way to do science, you’d never have to do clinical trials in kids, because you could just immunobridge from any population under the sun whenever you wanted to. If you get a clinical trial with zero effect, you are going to finesse it with immunobridging.”
Dr. Meryl Nass, an internal medicine physician with expertise in anthrax and bioterrorism and member of the Children’s Health Defense (CHD) scientific advisory committee, also criticized the practice.
“The term ‘immunobridging’ is simply a fancy way of saying we are going to use antibody titers instead of actual cases of disease prevented as our benchmark,” Nass told The Defender.
“And we will compare the antibody level in one age group to that in another, and if they are comparable, we will say the vaccine works in the new age group,” Nass said.
Nass said the FDA began accepting surrogate markers of efficacy in vaccines years ago for vaccines intended for rare conditions in which there were not sufficient cases to determine actual efficacy in the real world.
Nass said:
“This is simply not the case with COVID. There is plenty of COVID going around. For Moderna to claim the FDA should authorize its vaccine in babies and preschool children because the vaccine led to high antibody levels, when its real-world efficacy (and only against mild symptoms) was only 40% is a bad joke.
“The efficacy level tells you that antibody levels are a poor surrogate for efficacy and should therefore be ignored. Other parts of the immune system contribute to immunity besides neutralizing antibodies.”
Dr. Elizabeth Mumper, pediatrician, CEO of The RIMLAND Center and member of CHD scientific advisory committee, echoed Nass’ concerns.
“Emergency Use Authorization typically demands a 50% threshold of efficacy for approval,” said Mumper.
“Here, Moderna tries to get around their less-than-50% efficacy results by using a concept called immunobridging, meaning to show that children develop the same immune antibody response as young adults,” Mumper said.
“However, there are problems with assuming antibody response numbers correlate with clinical outcomes.”
Moderna also admitted its study was unable to assess the vaccine’s efficacy against severe disease, hospitalization or death for ages 6 and younger, as participants’ infections were mild or moderate.
The only adverse events the study reported were fevers — 15% of children had fevers higher than 100.4 degrees and 1 in 500 experienced a fever higher than 104 degrees.
Moderna did not disclose if any of the children who participated required hospitalization as a result of the fevers. It did reveal that adverse reactions were more frequently reported after the second dose.
Trials’ short duration, plus evolving variants raise questions
Critics also cited the study’s short duration, though Moderna said it will continue to monitor its participants for 12 months.
“Long-term adverse effects of the vaccine remain an open question,” said Stephanie Seneff, Ph.D., senior research scientist at MIT’s Computer Science and Artificial Intelligence Laboratory.
“Are we prepared to booster children every three or four months, since the protection from the vaccine is short-lived?” Seneff asked.
The Omicron variation affected the Moderna’s efficacy rates in children, an outcome the company claimed was “as expected.”
But the fact that the virus continues to mutate at a fast rate and the fact that kids 6 and younger are at low risk from COVID makes the vaccine’s use in healthy children questionable, Hamid A. Merchant, subject leader in pharmacy at the University of Huddersfield, UK, said in the Journal of Pharmaceutical Policy and Practice.
Merchant said:
“Currently deployed COVID vaccines were designed using the variant that was prevalent in early 2020 and the virus has significantly mutated since then; the breakthrough cases from [the] recent Omicron outbreak is a good example of the rapidly evolving nature of this virus.”
Research in the UK indicates more than 85% of children ages 5 to 11 years have already contracted COVID and have acquired natural immunity, Merchant added.
Kids at low risk of severe disease
Politico reported that even though the 5-and-under age group was more likely to be hospitalized for Omicron, children in this age group account for only 0.1% of the deaths from COVID and 3% of COVID cases in the U.S., according to CDC’s own data.
“According to data from most countries, practically no children under the age of 5 have died from COVID,” Nass said. “In the UK and Wales, over two years of the pandemic, only one child without comorbidities (a chronic illness) died from COVID.”
Nass added:
“While CDC claims over 1,000 children have died with COVID, CDC responded to a FOIA request from Informed Consent Action Network that it does not collect and analyze data on healthy children who have died from COVID in the U.S.
“This is hard to believe, but since the New York Times revealed that CDC hides the bulk of the data it collects on COVID, in part to avoid providing tinder to ‘antivaxxers’ regarding poor vaccine efficacy, it may be that CDC did in fact choose not to look at such data.”
A Johns Hopkins’ study that monitored 48,000 children under 18 who were diagnosed with COVID showed there were zero deaths in those without comorbidities. Another study in Nature came to much the same conclusion.
“Infants and toddlers do surprisingly well with Omicron,” Mumper said, adding:
“We know they have fewer ACE2 receptors in their noses, which may be protective. We know they have cross-protection from other infant viruses. We know the jab-generated B cell-specific spike protein antibody response is a very specifically targeted response, and not as broad as the natural symphony of well-orchestrated immune responses children usually mount.”
Rogers this week wrote the harms from COVID vaccines are catastrophic, and benefits are questionable:
“There are now 44,975 [Vaccine Adverse Event Reporting System] reports of adverse events in children following Covid shots, a few of which led to deaths. These reports likely understate harms by a factor of 41 to 100.”
Nass also called out the issue of risk versus benefit for the young age group:
“If we are vaccinating kids to protect grandma, which a Moderna official suggested, it should be noted that that is not considered ethical under U.S. law. You cannot vaccinate kids, and have them take a risk for a marginal benefit to themselves because you are hoping to provide a great benefit to adults.”
Apparently, the majority of parents agree. The Hill reported only 25% of children ages 5 to 11 are vaccinated, even though the FDA authorized vaccines for their age group last October.
“I hope the FDA holds Moderna’s feet to the fire and demands very robust results,” Mumper said.
“The basic concept is: First do no harm. If a baby’s background risk with COVID is not significantly changed by an mRNA jab, then the shot is not justified. If the jab just prevents mild to moderate infections, is it necessary or desirable?”
April 2, 2022
Posted by aletho |
Science and Pseudo-Science | COVID-19 Vaccine, United States |
Leave a comment
EVEN IF THOSE MESSAGES CONTRADICT INDEPENDENT RESEARCH ON WHAT IS BEST FOR PATIENTS
Australia’s march toward medical authoritarianism continues.
Doctors are now being told they could face discipline for saying anything that contradicts “public health messaging,” even if what they are saying is “evidence-based.”
They may even face investigations for “authoring papers” that health authorities do not like.
Unfortunately, I am not exaggerating.
Like all physicians, Australian doctors can face disciplinary investigations for medical errors or other problems. In Australia, those investigations are called “notifications,” a nicely Orwellian euphemism. Ahpra, the Australian Health Practitioner Regulatory Agency, oversees them.
On Feb. 28, a big Australian medical insurer warned physicians that to avoid Aphra notifications, they needed to “be very careful” not to contradict “public health messaging” in social media comments.
But the warning – although first mentioning social media – went even further. It also warned against “authoring papers” that contradicted the authorities’ favored views.
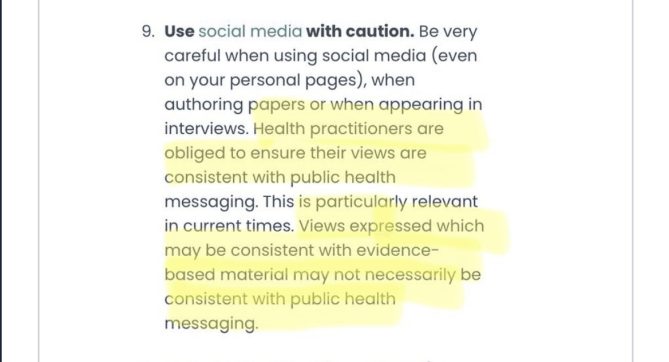
Further, even “views… consistent with evidence-based material” could lead to problems if they contradicted “public health messaging.”
The warning came from the Medical Indemnity Protection Society, which provides professional insurance coverage for doctors. Although these insurers do not speak officially for government agencies, doctors effectively cannot practice without professional insurance, so their pronouncements are powerful.

In other words, only a very brave physician in Australia would consider offering advice that’s not “consistent with public health messaging” anytime soon.
No worries, though, the public health authorities know best!
April 2, 2022
Posted by aletho |
Civil Liberties, Science and Pseudo-Science | Australia, Covid-19, COVID-19 Vaccine, Human rights |
Leave a comment
Two Australian Senators raised some serious vaccine issues during a recent debate in their parliament. As has been the case with questions raised by other parliamentarians from around the world, these speeches were made to an empty room. Fortunately, they are recorded for the world to listen too.
The first speech is by Malcolm Roberts, Senator for Queensland. He raised the issue of documented evidence and victim testimony of vaccine injuries which are hidden behind anonymous government data. The Senator says that the very least we can do for the victims is to say their names and he precedes to recall accounts of various individuals who have died after being vaccinated.
Senator Roberts says the Australian regulators have been bullying medical practitioners not to report or talk about vaccine harms. Furthermore, he claims 98% of the 800 vaccine deaths, reported by physicians, have been erased without autopsy or consideration of medical data.
He says data recently revealed in US court papers shows vaccine harm was apparent in the Pfizer clinical trials. This information should have resulted in the refusal of the application for provisional use. No data was provided on individuals in the trials and no independent analysis of the fundamental issues surrounding novel mRNA vaccines was conducted in Australia. Instead, the Secretary just took Pfizer, AstraZeneca and Moderna’s word for it.
The Senator goes on to list the fines that these same pharmaceutical companies have been issued with (for criminal behaviour) over the years. AstraZeneca had a US $355 million fine for fraud and US $550 million fine for making unfounded efficacy claims. Pfizer had a US $430 million fine for unfounded claims about efficacy and a US $2.3 billion fine for unfounded claims about efficacy and for paying kickbacks.
Indemnities have been made against any damage caused by the vaccines which he calls deceit and criminal incompetence. Some of the Australian political parties have accepted $1 million each from the pharmaceutical companies in this election cycle alone. Billions more are being set aside in the Australian budget to continue the pharmaceutical companies’ COVID-19 gravy train.
Senator Roberts says mention should be made to the decision to ban safe, fully approved and widely accepted alternatives to COVID-19 vaccines, including hydroxychloroquine, Ivermectin, vitamins, minerals, natural antivirals, healthy eating and lifestyles. This ban was taken to ensure the fastest and widest-possible adoption of the vaccines and the vaccines approval was funded by the same pharmaceutical companies that produce them.
He thinks the Australian Bureau of Statistics is culpable in this scandal and cover-up. It’s annual budget is $400 million but the most recent mortality data is from November 2021. The most recent breakdown of mortality by cause and age is from 2020 as is the most recent data on live births. Birth data used to be available six weeks after so he asks are they hiding miscarriages?
The Senator says peer reviewed and soon to be published data is to be released from outside the government which must require the secretary to cancel the provisional approval of the vaccines.
He recaps the extent to which we have been misled:
- Freedom of information documents show there has been a failure to assess the reproductive toxicology of the vaccines;
- Documents indicate a failure to assess the impact of micro RNA sequences and related molecular genetic issues on the human body;
- Peer-reviewed and published in-vitro research shows gene based vaccine generated spike proteins can migrate into human cell nuclei to disrupt DNA repair mechanisms;
- Vaccine derived RNA can be reverse transcribed leading to possible integration into the human genome, which is denied based on what the pharmaceutical companies say.
- Internal Pfizer data indicate they accepted 1,272 different adverse vaccine events, including paralysis and death. German and US insurance actuarial data suggests the Australian database of adverse events notifications is under reporting by nine fold. Documents show there are two databases, an official one and one for the public meaning vaccine injury is likely to be significantly higher than reported.
He reports on German pathologists describing pathological aggregates of spike proteins and lymphocyte infiltrations in inflamed organs in autopsies related to deaths post vaccination. Whistle-blowers to the British Medical Journal provide reports on inadequacies, irregularities and possible fraudulent practises in the Pfizer vaccine trials.
Too frequent vaccines for respiratory viruses runs the risk of desensitising the immune response to the virus and lead to hypo immunity, a worse illness than without the immunisation. He says repeated vaccination is doing more harm than good.
The Senator concluded by asking a question to all those who have gone along with the deceit, “how the hell do you expect to get away with it? We’re not going to let you get away with it, we won’t let you get away with it. We’re coming for you. We have the stamina to hound you down and we damn well will.”
The next speech was by Senator Gerard Rennick, another representative from Queensland.
He says, to date, government figures show there have been over 116,000 reported, suspected adverse events to the vaccines in Australia. This is more than all other drugs put together since 1971 and the number is still climbing. Is it any wonder the Australian health system is struggling?
Most of these cases are prepared by medical professionals and almost every one has ticked the box indicating that they suspect the injury was caused by the vaccine. Anyone who has failed to speak up is destroying the lives of so many Australian people.
March 31, 2022
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular, Video, War Crimes | AstraZeneca, Australia, COVID-19 Vaccine, Moderna, Pfizer |
Leave a comment
Yesterday morning, celebrity doctor Sara Kayat appeared on GB News to defend the UK government’s decision to “offer” coronavirus vaccinations to children between the ages of 5 and 11.
In standing up for the policy, Dr Kayat made the following statement:
It’s important we remind parents that the [Joint Committee on Vaccination and Immunization] have looked into all of the data, they’ve told us the benefits far outweigh the risks. The risks are extremely low, and the risks of Covid much higher.”
Is this true?
Let’s take the statements in reverse order.
Are the “risks of Covid much higher than the risks of the vaccine?”
They have literally no way of knowing.
But since Covid’s survival rate for children is something like 99.9998%, does it even really matter?
Do the benefits of the vaccine “far outweigh its risks”?
Again, they have literally no way of knowing.
But since the vaccine manufacturers:
- openly acknowledge in their supply contracts that their product may have unknown side effects,
- have demanded legal immunity to protect themselves from being sued should their vaccine cause harm,
- and released a document listing 9 pages of over 1200 “adverse events of special interest”, which they defend by saying there “may not be a causal relationship”
… they are at least aware that there might be some risks.
And finally, have the JCVI really looked into “all the data”?
Absolutely not, because they don’t have all of the data.
None of the covid vaccines were subject to usual tests due to the covid “emergency”, the few studies that were done were highly flawed, and since the vaccines have only existed for about 18 months there has been literally no time to do any kind of research on the possible long term side effects of the vaccine.
In short, they don’t have “all the data”. They don’t have most of the data. They have almost no data, except that your child has 499,999 out of 500,000 chance of surviving “Covid”.
Do you want to risk giving your child an untested vaccine to mitigate a one in five-hundred-thousand chance?
March 31, 2022
Posted by aletho |
Deception, Fake News, Mainstream Media, Warmongering, Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine |
Leave a comment
While other universities are scrapping vaccine passport requirements, the Ontario-based University of Waterloo has fired 49 members of staff for not showing a vaccine passport.
As reported by CTV, this came as the province of Ontario announced it would be dropping all COVID-19 measures.
“We have an obligation under the Health and Safety Act to protect our employees, and the employees have the obligation to comply,” said Nick Manning, vice president of university relations.
“All of those who weren’t able to be compliant after progressive measures faced the ultimate result of termination.”
The university terminated the staff members, yet it had announced it would be dropping its vaccine mandate on May 1.
Other schools in the province, including the University of Toronto, Wilfrid Laurier University, Ryerson University, and the University of Guelph, have announced that those who had been suspended over their vaccine status will resume work.
March 30, 2022
Posted by aletho |
Civil Liberties | Canada, COVID-19 Vaccine, Human rights |
Leave a comment
The end of the Covid-19 pandemic is being declared by most countries in the world at almost the precise 2nd anniversary to the day of the entire world shutting down voluntarily for “two weeks to flatten the curve.” Mask and vaccine mandates, along with vaccination passports, are dropping all over the world.
But if you thought that the end of the pandemic meant a return to normal life, you would be wrong. In the blink of an eye, we have seamlessly transitioned our attention from a pandemic enemy to the new Tsarist enemy in our global village. But have no fear, Sheriff Zelenskyy and his elite, woke allies in the West are going to save us from Vladimir Putin. And if you’re not on Team Ukraine, then you know, like whatever.
If this sounds kind of unbelievable to you, it’s because it is. It is astonishing to watch world leaders’ flourishing rhetoric on Ukraine, an unfathomable itch for war (see Nancy “I’d like to take out those tanks” Pelosi) and positioning the war between Russia and Ukraine as the barometer of our civilizational survival.
It has been particularly puzzling and stupefying over the past week to have seen that Canadian Prime Minister Trudeau is in Europe now, taking photos with armed Ukrainians and pontificating about freedom, democracy and tolerance. Ukrainian President Zelenskyy addressed the Canadian Parliament to a full house not seen at any point during two years of coronavirus and Justin Trudeau marveled at his stance against authoritarianism.
All around the world, meaningless gestures of antipathy toward Russia are proliferating on social media. Russian vodka is poured out. The National Mustard Museum has banned Russian Mustard (there is a mustard museum, who knew??), Russian orchestra conductors are getting fired and medical clinics in Germany are denying care to Russians. And in the most Canadian rebuke ever, the alleged inventors of poutine in Quebec, Canada have renamed their creation so as not to give credit to Putin.
Meanwhile, back at home, unvaccinated Canadians including my own severely disabled son are still not allowed to board a plane or train within Canada or to leave Canada. Truckers’ bank accounts and crypto wallets are still frozen, their trucks destroyed and persons targeted by the Canadian government for supporting the truckers will be ‘marked for life’ by Canadian banks.
Provincial Covid passports and mask mandates have been rescinded from coast to coast across Canada, yet Trudeau still holds six million unvaccinated Canadians hostage in their own country. Similar to many places in America, Canadians’ freedom is still subject to capricious, mean-spirited, abusive and nonsensical regulations that have no public health justification or scientific evidence.
Should freedom not begin at home? For how much longer will this federal cognitive dissonance be sustainable?
Hopefully, the absurdity and punitive nature of the travel regulations will come to an end in Canada soon. If not, there are several court challenges being simultaneously mounted by civil rights groups and individuals challenging the legality and constitutionality of the restrictions. But that will be a slow process of winding through the courts.
American lawmakers also see this issue as a problem. A group of Republican lawmakers is proposing legislation that will open up the border completely to Canadians. If that happens, Trudeau will have no choice but to follow suit.
Peace talks, or at least ceasefire talks are underway between Russia and Ukraine. No such ideological ceasefire, talks or dialogue of any kind are occurring in Canada between political factions or between leaders and their psychologically, financially and emotionally wounded populace. The coronavirus measures enacted in Canada have created a highly divisive country, torn apart along public health lines.
The pandemic left a highly fractured, wounded populace in its wake in Canada, US, and most places in the world. We are desperately in need of displays of unity, kindness and healing among themselves and above all, from their leadership.
Unfortunately for now, Canadians will continue to be fed a steady diet of the importance of democracy and the dangers of authoritarianism from the Canadian Prime Minister who enacted the current iteration of Canada’s War Measures Act to dislodge peaceful protesters from their capital city. It is hard not to conclude that it may in fact take a change of government to redemocratize the Dominion of Canada.
Invocations of freedom and sanctifying democracy must begin at home.
March 29, 2022
Posted by aletho |
Civil Liberties, Progressive Hypocrite, Timeless or most popular | Canada, COVID-19 Vaccine, Human rights |
Leave a comment
The Centers for Disease Control and Prevention (CDC) today released new data showing a total of 1,195,396 reports of adverse events following COVID-19 vaccines were submitted between Dec. 14, 2020, and March 18, 2022, to the Vaccine Adverse Event Reporting System (VAERS). VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
The data included a total of 26,059 reports of deaths — an increase of 418 over the previous week — and 211,584 reports of serious injuries, including deaths, during the same time period — up 3,375 compared with the previous week.
Excluding “foreign reports” to VAERS, 795,783 adverse events, including 11,943 deaths and 77,404 serious injuries, were reported in the U.S. between Dec. 14, 2020, and March 18, 2022.
Foreign reports are reports foreign subsidiaries send to U.S. vaccine manufacturers. Under U.S. Food and Drug Administration (FDA) regulations, if a manufacturer is notified of a foreign case report that describes an event that is both serious and does not appear on the product’s labeling, the manufacturer is required to submit the report to VAERS.
Of the 11,943 U.S. deaths reported as of March 18, 17% occurred within 24 hours of vaccination, 21% occurred within 48 hours of vaccination and 59% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 558 million COVID vaccine doses had been administered as of March 18, including 329 million doses of Pfizer, 210 million doses of Moderna and 19 million doses of Johnson & Johnson (J&J).
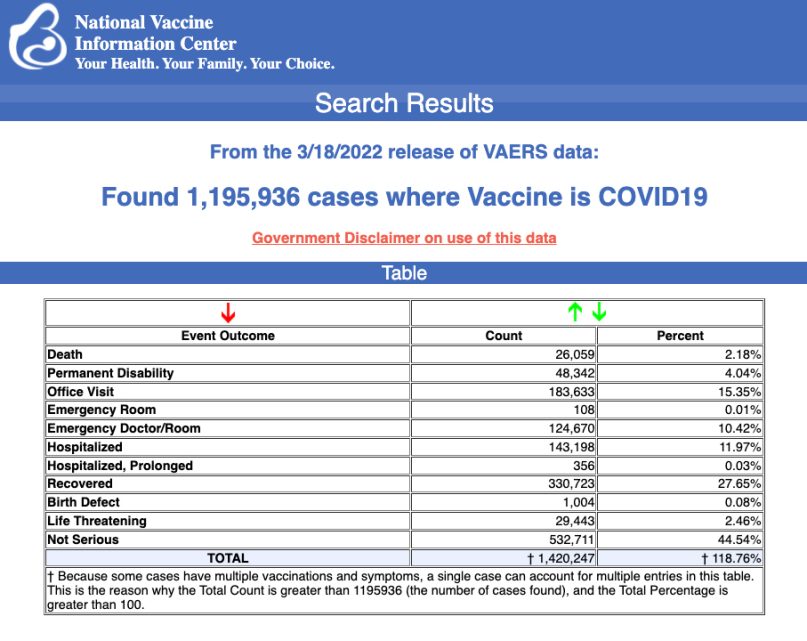
Every Friday, VAERS publishes vaccine injury reports received as of a specified date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed.
Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
U.S. VAERS data from Dec. 14, 2020, to March 18, 2022, for 5- to 11-year-olds show:
- 9,463 adverse events, including 228 rated as serious and 5 reported deaths.The most recent death involves a 7-year-old boy (VAERS I.D. 2152560) from Washington who died 13 days after receiving his first dose of Pfizer’s COVID vaccine when he went into shock and suffered cardiac arrest. He was unable to be resuscitated and died in the emergency department.
U.S. VAERS data from Dec. 14, 2020, to March 18, 2022, for 12- to 17-year-olds show:
“Sudden suicide one week after the vaccine. Patient was a perfectly happy child. After the vaccine, he became much more tired and achy and lost interest in doing his sports. One week later, without any warning, he hung himself.”
- 68 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases attributed to Pfizer’s vaccine.
- 648 reports of myocarditis and pericarditis, with 636 cases attributed to Pfizer’s vaccine.
- 163 reports of blood clotting disorders, with all cases attributed to Pfizer.
U.S. VAERS data from Dec. 14, 2020, to March 18, 2022, for all age groups combined, show:
- 20% of deaths were related to cardiac disorders.
- 54% of those who died were male, 41% were female and the remaining death reports did not include the gender of the deceased.
- The average age of death was 72.7.
- As of March 18, 5,294 pregnant women reported adverse events related to COVID vaccines, including 1,679 reports of miscarriage or premature birth.
- Of the 3,621 cases of Bell’s Palsy reported, 51% were attributed to Pfizer vaccinations, 40% to Moderna and 8% to J&J.
- 869 reports of Guillain-Barré syndrome, with 41% of cases attributed to Pfizer, 30% to Moderna and 28% to J&J.
- 2,371 reports of anaphylaxis where the reaction was life-threatening, required treatment or resulted in death.
- 1,647 reports of myocardial infarction.
- 13,602 reports of blood-clotting disorders in the U.S. Of those, 6,077 reports were attributed to Pfizer, 4,848 reports to Moderna and 2,633 reports to J&J.
- 4,070 cases of myocarditis and pericarditis with 2,502 cases attributed to Pfizer, 1,381 cases to Moderna and 177 cases to J&J’s COVID vaccine.
Mother calls for more vaccine studies after 12-year-old experiences severe pericarditis
An Australian mother is calling for long-term studies on mRNA COVID vaccines and better advice for parents after her 12-year-old son was hospitalized for pericarditis just hours after getting the Moderna shot.
The mother, referred to in the media only as “Nat,” vaccinated her son despite being hesitant about the long-term health risks because she believed she was doing the right thing. But within seven hours of being vaccinated, her son was unable to sit or lie down without severe chest pain and complained of breathing difficulties.
ER doctors confirmed Nat’s son had pericarditis, a condition characterized by inflammation of the membrane around the heart.
Nat said she was angry because she was hesitant about giving him the vaccine, but still chose to vaccinate him anyway. Now, she wants the federal government to present better information to parents on the risks of COVID vaccines to help them make a more informed choice on whether to immunize their children.
CDC removes tens of thousands of deaths ‘accidentally’ attributed to COVID
The CDC on March 15 removed from its data tracker website tens of thousands of deaths attributed to COVID, including nearly a quarter of the deaths attributed to children. The CDC said it made adjustments to the mortality data because its website’s algorithm was “accidentally counting deaths that were not COVID-19-related.”
Prior to the adjustment on March 15, the CDC reported 851,000 COVID deaths, including 1,755 pediatric deaths. After the change, COVID-related deaths dropped to 780,000.
The change resulted in the removal of 72,277 deaths previously reported across 26 states, including 416 pediatric deaths — a reduction of 24% to 1,341, the agency said.
According to The Guardian, the error arose from two questions the CDC asks states when they report COVID fatalities. One data field asks if a person died “from illness/complications of illness,” and the field next to it asks for the date of death.
When the answer is “yes,” then the date of death has to be provided. But if a respondent included the date of death but put “no” or “unknown” in the other field, the CDC’s system assumed the answer was an error and switched the answer to “yes.” This resulted in an overcount of COVID deaths in the demographic breakdown.
The agency said once it discovered the problem, it corrected it, but it is unknown how long inaccurate COVID deaths were reported.
The CDC’s COVID statistics, used to justify which age groups should receive vaccines, were used by U.S. health agencies to support the authorization of Pfizer’s COVID vaccine for children 5 to 11 years old.
Moderna to request authorization of COVID vaccine for kids 5 to 11
Moderna on March 23 announced plans to request Emergency Use Authorization (EUA) for its pediatric COVID vaccine, citing preliminary data showing the two-dose regimen was safe for children under age 6, but may not be effective at reducing severe COVID.
The company released partial results from its two pediatric clinical trials in 6,900 children showing the mRNA shots were only about 44% effective at preventing symptomatic infection in children 6 months to 2 years old, and only 37% effective in children aged 2 to 5.
FDA guidelines for EUA products stipulate the product must show 50% efficacy.
The company said the majority of COVID cases observed were mild and no severe disease, hospitalizations or deaths were reported among any of the children who participated in the trial, making it impossible to detect the vaccine’s protective effect against the worst outcomes.
Moderna did not report details on types of side effects except for data on children who experienced fevers. The company said about 15% of children had fevers higher than 100.4 degrees, and 1 in 500 experienced a fever higher than 104 degrees.
However, data show the vaccine may not be effective at reducing severe COVID in children, who make up only a small percentage of SARS-CoV-2 infections — most of which are asymptomatic and mild.
4th COVID shot offers little protection against infection
A small study conducted by Researchers at Sheba Medical Center in Israel found efficacy of a fourth dose of Pfizer and Moderna COVID vaccines resulted in only marginal protection from SARS-CoV-2 infection.
According to the study, published in the New England Journal of Medicine, a fourth Pfizer dose showed 30% efficacy in preventing infection and Moderna’s fourth dose showed only 11%.
The study’s authors said a fourth dose provided “moderate protection against symptomatic infection” (Pfizer = 43%; Moderna = 31%), with symptomatic infection defined as a fever lasting either more or less than 48 hours. Other systemic symptoms included fatigue, myalgia, and headache.
However, these efficacy numbers fall short of the required 50% threshold required by the FDA for EUA products in the U.S.
About 25.2% of fourth dose recipients experienced moderate-to-severe local reactions and 6.5% had moderate-to-severe systemic reactions to a second booster, while the majority of all COVID cases in participants were asymptomatic or had negligible symptoms.
Children’s Health Defense asks anyone who has experienced an adverse reaction, to any vaccine, to file a report following these three steps.
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
March 27, 2022
Posted by aletho |
Aletho News | COVID-19 Vaccine, United States |
Leave a comment


