CDC Adds Over 2000 Deaths Associated with COVID-19 Shots in One Week & 917 Unborn Baby Deaths
By Brian Shilhavy | Health Impact News | July 9, 2021
The U.S. CDC released more data today in their Vaccine Adverse Event Reporting System (VAERS), a U.S. Government funded database that tracks injuries and deaths caused by vaccines, and they added more than 2000 deaths following COVID-19 shots over what they reported last week.
Last week they were reporting 6,985 deaths, and this week that number jumped up to 9,048.
This is by far the largest increase of recorded deaths in one week since they started reporting deaths following COVID-19 shots.
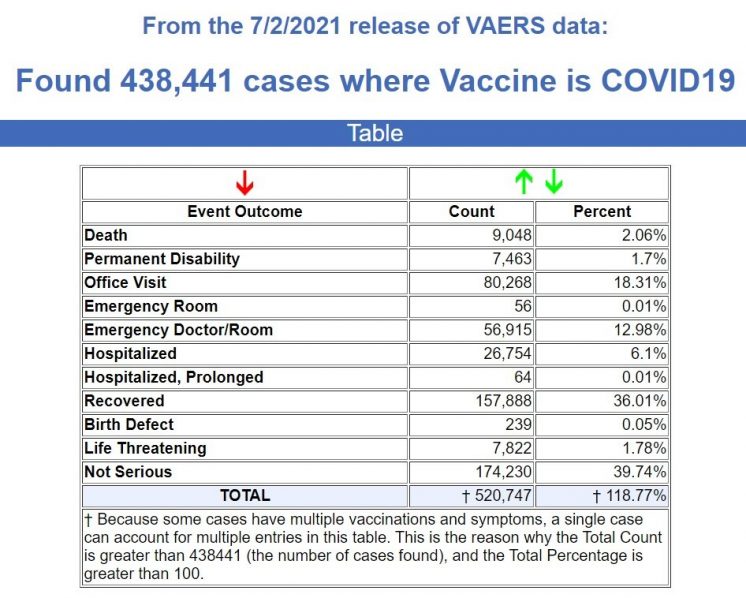
Source
Besides the 9,048 deaths, there are 7,463 permanent disabilities, 56,971 Emergency Room visits, 26,818 Hospitalizations, and 7,822 Life Threatening injuries following the COVID-19 injections.
And yet, none of this government data will be reported in any corporate media news broadcast, and those who try to post it on the Big Tech social media sites will be flagged for “fake news” by the “fact checkers.”
These are not even the true numbers, as the CDC selectively chooses what to release to the public each week, and of course many deaths and injuries go unreported because the public is conditioned to believe that none of these deaths and injuries have anything to do with the COVID-19 shots.
To put this into perspective, there are now 30% more deaths recorded in 7 months since the launch of the COVID-19 shots in December of 2020, than during the entire 31-year history of VAERS recording deaths following vaccines since it started in 1990.
1990 to November 2020: 6,145 deaths following ALL VACCINES. (Source.)
December 2020 to July 2, 2021: 9,048 deaths from COVID-19 shots only. (Source.)
Deaths of Unborn Babies Much Higher than Originally Thought
Last week we reported 622 deaths of unborn children when the pregnant mother received a COVID-19 injection. Using the same search parameters, that number increased to 803 cases this week. (Source.)
However, deaths recorded in the age group of 12-15 have not really increased yet according to the data that the CDC is releasing, so I began to look at the deaths in the “unknown” age group to see if there were some there. I did find a couple, but what I also found was that there were other “symptoms” that the VAERS data uses that do NOT include the term “abortion” when reporting deaths of unborn children in pregnant mothers who took the shots.
So I noted those symptoms, such as “Foetal death, Premature baby death, Stillbirth,” etc., and the deaths increased from 803 to 917. (Source.) And it is very possible I am still missing some, not to mention the ones that never get reported, or if they are reported, are not released by the CDC.
Of the 9,048 deaths the CDC recorded, 3,073 of those deaths are listed as age “unknown.” (Source.)
Trying a few different searches among this “unknown” age group, I did find a 13-year-old boy who died, and a curious entry of an 11-year-old girl who died and where the “family who got vaccinated died along with their dog due to have been being exposed to the members who got vaccinated.”
VAERS ID: 1440065 – Write-up: died three days after Covid vaccination; Autopsy showed enlarged heart and fluid surrounding the heart; Autopsy showed enlarged heart and fluid surrounding the heart; This is a spontaneous report from a contactable consumer or other non-health care professional in response to mail sent regarding the confirmation of below mentioned query. A 13-year-old male patient received second dose of bnt162b2 (PFIZER-BIONTECH COVID-19 mRNA VACCINE, Formulation: Solution for injection, Batch/Lot number and Expiration date not reported) via an unspecified route of administration in an unspecified anatomical location on an unspecified date as single dose for COVID-19 immunisation. The patient medical history and concomitant medications were not reported. The patient previously received first dose of bnt162b2 (PFIZER-BIONTECH COVID-19 mRNA VACCINE, Formulation: Solution for injection, Batch/Lot number and Expiration date not reported) via an unspecified route of administration in an unspecified anatomical location on an unspecified date as single dose for COVID-19 immunisation. On an unspecified date, the patient after receiving his second Covid vaccine from Pfizer died three days later. The patient underwent lab tests and procedures which included autopsy: enlarged heart and fluid surrounding the heart caused by the Covid vaccination. The outcome of the events was fatal. No follow-up attempts are possible; information about lot/batch number cannot be obtained.; Reported Cause(s) of Death: enlarged heart and fluid surrounding the heart.
VAERS ID: 1320319 – Write-up: Girl”s family who got vaccinated died along with their dog due to have been being exposed to the members who got vaccinated; 11 year old, pre-period, girls family who got vaccinated; This is a spontaneous report from a contactable consumer. A 11-years-old patient of an unspecified gender received BNT162B2 (PFIZER-BIONTECH COVID-19 VACCINE), via an unspecified route of administration on an unspecified date (Batch/Lot number was not reported) as single dose for covid-19 immunisation. The patient medical history and concomitant medications were not reported. The reporter reported that 11 year old, pre-period, girls family who got vaccinated died along with their dog due to have been being exposed to the members who got vaccinated. The patient died on an unspecified date. It was not reported if an autopsy was performed. The lot/batch number has been requested; Reported Cause(s) of Death: Girl”s family who got vaccinated died along with their dog due to have been being exposed to the members who got vaccinated.

18-year-old Camilla Canepa died in Italy following the AstraZeneca COVID-19 shot
Neurosurgeon Who Operated on 18-year-old Girl: “I had never seen a brain reduced in those conditions by a thrombosis so extensive and so serious”.
On June 15th this year we published the story of Camilla Canepa, the 18-year-old Italian woman who developed blood clots and was dead two weeks after experimental AstraZeneca shot. The full story was originally published on The COVID Blog.
Her death shocked the community where she lived so much, that a criminal investigation was started, and Italy changed its policy on the AstraZeneca COVID-19 shot limiting it to only people over the age of 60.
The neurosurgeon who operated on her brain has since spoken out, and English translations of what he stated have been circulating through the alternative media this week.
I found an original source from Italy that reported this, and here is the translation, courtesy of DeepL.
The death of Camilla Canepa has shocked the whole of Italy, so much so that after the death of the 18-year-old girl from Sestri Levante as a result of thrombosis emerged a few days after the administration of the vaccine AstraZeneca the Ministry of Health has decided to ban the product against Covid to those under 60 years.
Waiting for the autopsy on the body of the young woman that will be carried out on Tuesday, to speak to La Stampa is Gianluigi Zona, director of the neurosurgical and neurotraumatology clinic of the San Martino Hospital in Genoa: “I had never seen a brain reduced in those conditions by a thrombosis so extensive and so serious”.
“Reasoning in retrospect – explains the doctor on the controversy for the lack of immediate intervention on Camilla – it’s all easy and everyone is a world champion, the last doctor who comes to see a patient is always the smartest.
I can’t judge what could have been picked up already in the first CT scan, it never arrived at San Martino. Normally, if there are no clues that lead to assume something serious is going on, no doctor in the emergency room prescribes a CT scan with contrast or other tests.”
The situation was immediately serious once the operation began: “All the venous sinuses were blocked by thrombi, a scenario that I had never seen in many years of this profession. You have to imagine the venous sinus as the river in the middle of a valley in which several streams converge.
If you build a dam in the middle of the river, the river swells and at that point the tributaries cannot discharge, with the result that the upstream pressure rises. In front of the picture I saw in the head of that girl, it is clear that – concludes the head physician – we are facing something not normal”. (Source.)
Life Will Be Very Different For The Have Jabs & The Have Nots
By Richie Allen | July 10, 2021
The Times newspaper is claiming this morning, that vaccine passports or covid certificates will be a condition of entry to pubs nightclubs and restaurants this Autumn. The paper reports:
Entertainment venues in England would be forced to make customers use so-called vaccination passports from autumn, to prove that they had either had both doses or a negative test the day before.
Recent figures have shown a reduction in the take-up of vaccines with first doses halving in two weeks. Fewer than 100,000 a day are being given out on average for the first time since April.
The government will justify the draconian measure by claiming that it is necessary to prevent a fourth wave of coronavirus overwhelming the NHS this Winter.
Government ministers have told The Times that by mid-September all over-18’s will have had the chance to be double jabbed. According to The Times :
Another government figure added: “If we can show real benefits of getting vaccinated in terms of everyday life then it could be quite a useful tool.”
I did call this early last year, before anyone had ever heard of a vaccine passport. I said that in the very near future people would need to prove that they were safe in order to travel or to socialise.
When vaccine minister Nadhim Zahawi said that the UK wasn’t “the sort of country to introduce such measures,” I said he was lying. It’s open tyranny now. Yet there will be very little outrage and lots of compliance.
This isn’t a dystopian novel. It’s life now. Your government is telling you that unless you submit yourself for regular injections and constant testing, you cannot leave the country and are forbidden to socialise.
Life will be very different for the have jabs and the have nots. If I thought that they would leave the have nots alone, I could live with it. But they won’t. The coercion will continue. They will not accept that we won’t surrender to the jab.
The question is, how far will they go?
Israel’s Flu/Covid Mass-Jabbing Problem
By Stephen Lendman | July 6, 2021
Israel is one of the world’s most extensively jabbed nation for flu/covid protection — not gotten, despite false claims otherwise.
Through mid-year, over 80% of its adult population got one or more flu/covid jabs, nearly 60% overall.
Last April while still prime minister, Netanyahu called Israeli mass-jabbing “enormously successful (sic)” — ignoring its harm to health, its deadly consequences to show up in the months and years ahead.
Israel’s foreign ministry spokesman Lior Haiat defied reality by calling flu/covid mass-jabbing “the solution” to the viral illness (sic).
Yet late last month, outbreaks began increasing — in summer when decreasing should be more likely.
On June 27, head of Israel’s health ministry, Chezy Levy, resigned.
Roni Numa replaced him as a Bennett regime flu/covid czar.
Nachman Ash was appointed new health ministry head.
What Netanyahu falsely called the world’s first country to “beat” flu/covid has a renewed viral illness outbreak problem on its hands.
Bennett falsely attributed increased outbreaks to what he called a “national weak point (at) Ben-Gurion airport,” adding:
“(I)n coordination with the transportation minister, the health minister and the interior minister, we decided to appoint a special director to handle transitions and prevent the entry of this virus and future variants and viruses from around the world into Israel.”
Everyone arriving in Israel from abroad who’s not jabbed or recovered from flu/covid is now quarantined until set free.
According to Bennett, his regime’s flu/covid policy is “maximum protection for Israeli citizens (sic), with minimum harm (sic) to routine and the economy in Israel; masks instead of restrictions (sic), (and toxic Pfizer mRNA jabs) instead of lockdowns.”
The above ignores that up to half of flu/covid outbreaks occurred in Israelis already jabbed.
On Tuesday, Israel’s health ministry reported a 50% increase in Monday outbreaks from the previous day, the highest number since March 30.
A 42% total of outbreaks occurred in flu/covid jabbed Israelis.
Falsely blaming them on the highly publicized Delta scariant ignores that it’s no more hazardous than other strains.
Yet Israel’s health ministry attributed over 90% of new outbreaks to what it falsely called the “highly contagious delta variant (sic).”
The health ministry also admitted that the efficacy of Pfizer’s mRNA drug is far removed from what Netanyahu called “enormously successful (sic).”
High-outbreak areas in the country are now labeled red, orange or yellow zones.
Despite mass-jabbing responsibility for increased outbreaks, the Bennett regime’s health ministry may call for a third one and new restrictions.
Flu/covid season runs from October through May when outbreaks are highest.
With large numbers of people jabbed for protection from the viral illness not gotten in the West, Israel and elsewhere, perhaps record numbers of outbreaks will occur from early this fall until year year’s warm weather season.
A Final Comment
According to the pro-Western, pro-toxic flu/covid mass-jabbing, pro-inflicting maximum harm on maximum numbers of people WHO, it’s too soon to resume normal activities (sic).
On Monday, the agency’s so-called top emergency expert Mike Ryan warned about increased outbreaks ahead.
“It’s not like this thing has gone away. It isn’t over,” he said — perhaps with the Delta scariant in mind that’s all about mind-manipulating refusniks to get theirs.
Indeed, flu/covid outbreaks are never over. They’ve showed up annually for time immemorial.
They will ahead during the 2021/22 flu-renamed covid season and others to follow.
Should people who have recovered from COVID take a vaccine?
By Marc Girardot | Trial Site News | July 6, 2021
Epidemiology1 , immunology2 and the clinical data3 all say a clear “No!”.
There is no good reason to vaccinate the recovered.
________________________________________________________________________
A British friend, recovered from COVID, decided to get vaccinated despite being naturally immune. This is the email he recently sent me:
“Marc I suffered a mild stroke on Wednesday 8 days after taking the Astrazeneca 2nd dose. Since I am a marathon runner I am a very ‘rare case’. I don’t smoke, have high blood pressure, high cholesterol, family history or come into any of the risk categories for blood clots…
You did warn me against taking the second dose and I wished I’d heeded your advice. I’ve taken a totally unnecessary risk with my life and I bitterly regret doing it.”
Contrary to most, Tony was informed; he had been told about the power of natural immunity, about the long—if not lifelong—duration of immunity, of the risk inherent to any medical procedure (Yes, vaccination is a medical procedure!), as well as of the rising levels of adverse events. He admitted he hadn’t imagined it could happen to him…
Though it is hard to assess precisely the actual severity and breadth of vaccine-related adverse events, it is very clear that vaccination against COVID-19 isn’t as harmless4 as pharmaceutical companies, mainstream media, academia, health authorities and the medical community have been saying. And, in contrast to high risk individuals who are still susceptible, recovered people have no real benefit to balance the additional risks of vaccination.
2021 Adverse Events Reporting
| VAERS US | EUROVIGILANCE EUROPE | YELLOW CARDS UK | |
| Date | 18/06/2021 | 04/06/2021 | 16/06/2021 |
| Fully Vaccinated (Mn) | 148.46 | 137.44 | 30.68 |
| Deaths | 6,136 | 4,572 | 1,356 |
| Incidents | 387,288 | 316,925 | 73,944 |
| Death per 100,000 | 4.1 | 3.3 | 4.4 |
For over a year, mainstream media, health authorities as well as many “experts” have been downplaying the power of the immune system, dismissing natural immunity5 and proclaiming that immunity to COVID-19 was short-lived6. Simultaneously, vaccines have been portrayed as the silver bullet to this crisis, an incidental procedure with no risk whatsoever. The data shows a different picture and many are coming forward7 8, to challenge the official narrative. We will demonstrate that the official narrative is a dangerous fallacy.
The human immune system is one of the most sophisticated achievements of evolution. The survival of our species has depended on it for millenia. Today, we still very much rely on it. For the record, 99% of people infected with SARS-CoV-2 recover without treatment. Only 1% of SARS-CoV-2 patients, who did not receive early home-based treatment, end up hospitalized9. In other words, the immune system overwhelmingly protects. Even vaccines are entirely dependent on the immune system: vaccines essentially teach our immune systems what viral markers to be prepared for, they are not cures per se. Without a functional immune system, there can be no effective vaccine10.
On the waning immunity fallacy
Once recovered, the immune response recedes, notably via a decrease in antibodies. It is not only natural; it is indispensable to restore the body to a normal, balanced state. Just as a permanent state of fever is harmful, a high number of targetless antibodies or T-cells constantly circulating throughout the body could create serious complications, such as autoimmune diseases11. Taking an evolutionary perspective, only those whose antibody and T-cell count waned post-infection survived. So, a decreasing number of antibodies and T-cells is reassuring, even healthy.
Antibody Levels during infection and post infection

Redline= antibodies – Blue-line= Memory B cells | Credit: Nature
But this decrease in T-cells and antibodies doesn’t mean that immunity is lost . It means the immune system has adapted to the new situation, and is now just on sentinel mode: Memory B- and T-cells, circulating in the blood and resident12 in tissues, act as vigilant13 and effective sentinels for decades:
- survivors of the Spanish Flu epidemic were tested for their immunity to the 1918 influenza virus 90 years later –14,15 and still demonstrated immunity;
- people who had recovered from the 2003 SARS infection demonstrated robust T-Cell responses seventeen years later16.
- the wide-spread prevalence of high cross-immunity17,18,19— gained from past common cold infections—further demonstrates the resilience of natural immunity for coronaviruses.
Indeed, all recent studies show that specific anti-SARS-CoV-2 immunity remains effective20,21,22,23, possibly for a lifetime24. Our immune system is a modular platform, it can combine in an infinite number of ways to address a multitude of threats in a variety of contexts. As such it is neutral to the viral threats it faces. In other words, there is absolutely no reason to believe that those recovered from Covid-19 would lose their immunity over the years, or even the decades25 to come.
On the reinfection fallacy
You might have also heard of people becoming reinfected by SARS-CoV-2. Indeed, immunity, natural or vaccine-induced, isn’t the impenetrable shield described by many. Essentially harmless and asymptomatic reinfections do take place. That is, in fact, the very mechanism by which adaptive immunity is triggered.
However, symptomatic reinfections are very rare26,27. Like an army that adapts its response to the size and the progression of its enemy forces, adaptive immunity provides a specific, rapid and resource-optimized response. As such reinfections are mostly asymptomatic28 and recovered patients are protected from severe disease.
In fact, innocuous reinfections can play a positive public health role by acting as continuous immune updates29 for the population. They can help form a seamless and progressive adaptation to emerging variants and strains. And indeed a recent study showed that couples with children were more frequently asymptomatic than couples without, most likely because children act as natural and harmless immunisation vehicles. The most likely reason why high density countries mostly have very low death tolls is that they have asymptomatic reinfections that regularly and widely update the population’s immunity.
On the variant fallacy
As demonstrated by the low numbers of symptomatic reinfections mentioned above, and also by multiple studies31,32, variants have thus far not escaped acquired immunity. Just as Americans can speak and interact seamlessly in England, unhindered by a few word variants33, natural immunity is unhindered by variants, possibly more so than vaccine-induced immunity. There is ample evidence of the sophistication and breadth of the human immune system, and it is clear that a few minor gene changes in the virus cannot evade its arsenal .
Across the world34, multiple studies demonstrate high levels of pre-existing cross-reactive T-cells35 and antibodies to SARS-CoV-2. In other words, many were already largely immune via other coronaviruses. This is the most likely explanation for the unexpectedly high level of asymptomatic infections during the pandemic. More importantly, this demonstrates that even with large genetic differences, prior immunity to related coronaviruses is sufficient to avoid severe COVID-19. Therefore, it is quite evident that variants are of no concern to the recovered population.
On the vaccine better-than-natural-immunity fallacy
You might have heard people stating that vaccines provide better protection than natural immunity. That is an interesting way of bending reality. How can a vaccine be more effective at immunisation than the disease it is trying to mimic?
Theoretically, there are several reasons explaining why natural immunity is better than vaccine-induced immunity:
- Fewer immune targets: mRNA/DNA vaccines present only a fraction of the virus genetic code (5-10%). For example, they don’t utilize the ORF1 highly immunogenic epitopes36. Therefore, the immune system recruits a smaller number of T-cells by tapping into a narrower repertoire and consequently mounts a less effective response37. The logic: Imagine you lose a number of key players for a football tournament, you might still win, but it will be harder.
- Longer immune trigger time: The smaller number of epitope targets also means that the alarm to the immune system will be delayed. This is a key driver of success in the COVID-19 battle. The wider the target repertoire, the faster the encounter between dendritic cells and identifiable antigens.
The logic: Like a party you go to, you can start partying much faster when you have ten friends there than when you have only one. They are just easier to find. - Inappropriate delivery location: The intramuscular delivery of current vaccines unfortunately doesn’t mimic viral penetration and propagation at all. Coronaviruses don’t enter the body via muscles. They do so via the respiratory tract, often infecting cell-to-cell. Contrary to muscle-delivered vaccines, natural immunity places a strong sentinel force of memory resident cells at the portals of entry38 and shuts the body entrance to the virus preemptively. From an evolutionary standpoint, this makes perfect sense.
The logic: it’s much easier to stop an army coming through a narrow gorge than on the beaches of Normandy.
Recent research confirms this logic. One comparative study39 in Israel found the protection from severe disease to be 96·4% for Covid-19 recovered individuals but 94.4% for vaccinated ones, and concluded “Our results question the need to vaccinate previously-infected individuals.” Another reference comparative study40 by a team at New York University highlighted a faster, wider and more impactful humoral and cytotoxic reaction in recovered immunity versus vaccine-induced.
There is ample evidence that vaccinating people recovered from COVID-19 doesn’t bring any benefit. It quite possibly does the opposite, because of the risk of building tolerance to elements of the virus43 translating into reduced immune potency.
On the vaccine innocuity fallacy
Without denigrating the incredible contribution of vaccines to modern medicine and public health, one needs to acknowledge that vaccines are a medical procedure. As such, vaccines should never be considered lightly. They are neither neutral, nor trivial, all the more so when they are injected into billions of people.
By their very nature, vaccines tinker with the sophisticated balance of one’s immune system. That in itself demands respecting rigid safety protocols. Though we have made considerable progress in our understanding of immunology, we are still very far from understanding its intricacies and subtleties, especially when it comes to novel mRNA and DNA technologies. Because of the risk of anaphylactic44 shock, auto-immune diseases, unforeseen interactions, design flaws, deficient quality protocols, over-dosage, and so on, vaccines have traditionally been strictly regulated.
History teaches us to be watchful45 with vaccines, from the botched inactivation of polio vaccines that ended infecting 40,000 kids46 with polio in 1955, to the 1976 swine flu vaccine47 which caused 450 to develop Guillain-Barré syndrome, to the more recent vaccine-induced outbreak of polio in Sudan48. The recent rejection49 by Brazilian health authorities of the Bharat’s Covaxin is a clear reminder of how rigorous and independent our health authorities need to be if vaccines are to promote, not hinder, public health.
Map of Vaccine Symptoms
316,925 reports (date: 06/20/21)
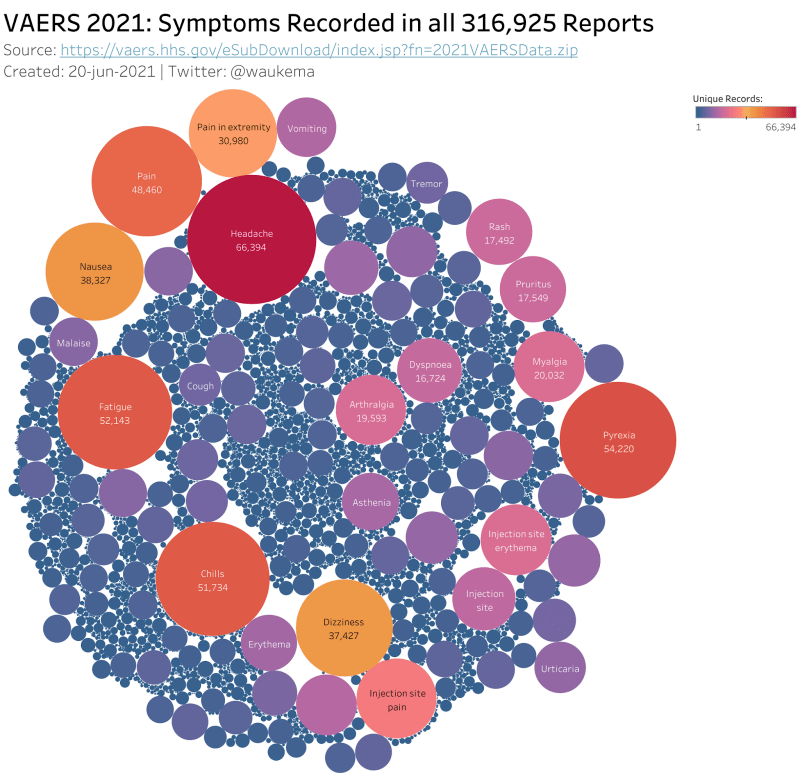
credit: Wouter Aukema – source: CDC
After 6 months of vaccination and a year of research, a number of red flags should be alerting the would-be vaccinated and health authorities:
- Wandering nanoparticles: The lipid nanoparticles, the carriers of the mRNA, were supposed to remain in the muscle, but ended up broadly distributed throughout the body50, notably in the ovaries51, the liver52 and possibly the bone marrow.
- Anaphylactic PEG: A number of concerns had been raised regarding the novel use of PEG adjuvant53. Notably, prior research had raised the risk of cardiac anaphylaxis at second injection54.
- Sensitive locations: ACE-2 receptors susceptible to binding to the spike protein are highly expressed in blood vessel lining cells of highly sensitive areas, such as the brain, the heart, the lungs, the liver and both male and female reproductive systems.
- Toxic circulating spikes: The spike proteins induced by mRNA/DNA vaccines have been shown to be pathogenic55,56,57,58 and highly inflammatory59, notably because of the similarity of a spike sequence to that of Staphylococcal Enterotoxin B60. It has also been found to be directly causing blood clots through platelet activation61,62. One researcher said, “Our findings show that the SARS-CoV-2 spike protein causes lung injury even without the presence of an intact virus”.
- BBB disruption – A recent study highlights the risk of disruption of the blood-brain barrier63, a fundamental filter mechanism to protect the brain64,65. The spike protein has also been found to cross the BBB and create inflammation in the brain,.
- High adverse events: Even though most likely under-reported66, the overall number of serious adverse events versus other traditional vaccines remains very high. The 6,000+ deaths67 seen [in the US] in six months exceed all the vaccine-related deaths in 30 years. This is quite disquieting, and tends to confirm the aforementioned red flags..
- Children more at risk: The Covid-19 vaccines seem to be more harmful to children and teens, notably with a growing number of myocarditis68,69 events. The fact that vaccine doses are not adjusted for body weight is notably a cause for concern given the discovery of circulating nanoparticles and spike toxicity.
These are essentially just the short-term effects of these novel vaccines. There is no long-term clinical data regarding the implications of these vaccines, notably regarding autoreactive antibodies (antibodies that target one’s own body creating autoimmune diseases).
To conclude, we question why anyone healthy and recovered from COVID-19 would want or be advised to take any risk—even the most remote—in getting vaccinated given that:
- those who have recovered from COVID-19 enjoy robust immunity,
- natural immunity duration is decades-long, probably lifelong,
- natural immunity effectiveness is better than vaccine-induced,
- variants are not an immunological concern, presenting no risk of immune escape,
- vaccines are medical interventions which should never be taken lightly, especially when still experimental,
- there is no benefit for COVID-19 recovered and
- COVID-19 vaccines are obviously not as safe as stated initially by the manufacturers.
- The 2021 seasonal peak in Europe started down on January 22 when only 0.13% of the population was fully vaccinated.
- “Comprehensive analysis of T cell immunodominance and immunoprevalence of SARS-CoV-2 epitopes in COVID-19 cases” by Alessandro Sette et al, Cell, February 2021
- “No point vaccinating those who’ve had COVID-19: Findings of Cleveland Clinic study” by Dr. Sanchari Sinha Dutta, June 2021
- “Pfizer-BioNTech vaccine is “likely” responsible for deaths of some elderly patients, Norwegian review finds” by Ingrid Torjesen, British Medical Journal, May 2021
- “Why COVID-19 Vaccines Offer Better Protection Than Infection” by Brian W. Simpson, John Hopkins School Of Public Health Expert Insights, May 2021
- “Study Finds People Have Short-Lived Immunity to Seasonal Coronaviruses” by Dr. Francis Collins, CDC’s Director Blog, September 2020
- “Are Covid Vaccines Riskier Than Advertised? There are concerning trends on blood clots and low platelets, not that the authorities will tell you” by Joseph A. Ladapo and Harvey A. Risch, The Wall Street Journal, June 2021
- “Why we petitioned the FDA to refrain from fully approving any covid-19 vaccine this year” by Peter Doshi et al, The British Medical Journal Opinion, June 2021
- “Phase 3 trial shows REGEN-COV™ (casirivimab with imdevimab) …” show 4.1% of at risk Placebo (non treated) patients are hospitalized, or 1% of the general population
- “Coronavirus vaccines may not work in some people. It’s because of their underlying conditions.” by Ariana E. Cha, The Washington Post, May 2021
- “Determinants and outcomes of accelerated arteriosclerosis: Major impact of circulating antibodies” by Alexandre Loupy, Circulation Research, June 2015
- “Peripheral and lung resident memory T cell responses against SARS-CoV-2” by Meritxell Genescà et al, Nature, May 2021
- “Tissue-Resident Memory T Cells and Fixed Immune Surveillance in Nonlymphoid Organs” by Francis R. Carbone, Journal of Immunology, July 2015
- “Flu survivors still immune after 90 years” by Ed Yong, National Geographic
- “Neutralizing antibodies derived from the B cells of 1918 influenza pandemic survivors” by James E. Crowe Jr., Nature
- “SARS-CoV-2-specific T cell immunity in cases of COVID-19 and SARS, and uninfected controls” by Le Bert et al, Nature, July 2020
- “Targets of T Cell Responses to SARS-CoV-2 Coronavirus in Humans with COVID-19 Disease and Unexposed Individuals” by A.Sette et al, Cell, June 2020
- “A majority of uninfected adults show pre-existing antibody reactivity against SARS-CoV-2” by Pascal M. Lavoie et al, JCI Insight, March 2021
- “Cross-reactive antibody immunity against SARS-CoV-2 in children and adults” by Todd Bradley et al, Nature, May 2021
- “Robust SARS-CoV-2-specific T cell immunity is maintained at 6 months following primary infection” by Paul Moss, Nature Immunology, May 2021
- “Naturally enhanced neutralizing breadth against SARS-CoV-2 one year after infection” by Michel C. Nussenzweig, Nature, June 2021
- “A long-term perspective on immunity to COVID” by ” by A.Radbruch & H-D.Chang
- “SARS-CoV-2 natural antibody response persists up to 12 months in a nationwide study from the Faroe Islands” by Peter Garred et al, 2021
- “SARS-CoV-2 infection induces long-lived bone marrow plasma cells in humans” by Ali H. Ellebedy et al, Nature, May 2021
- “Immunity to the Coronavirus May Last Years, New Data Hint” by Apoorva Mandavilli, New York Times, November 2020
- “Prior SARS-CoV-2 infection is associated with protection against symptomatic reinfection” by Christopher J.A. Duncan, Journal of Infection, December 2020
- “What we know about covid-19 reinfection so far” by Chris Stokel-Walker, British Medical Journal, January 2021
- “Antibody Status and Incidence of SARS-CoV-2 Infection in Health Care Workers” by Thomas G. Ritter, et al, New England Journal of Medicine, December 2020
- “Development of potency, breadth and resilience to viral escape mutations in SARS-CoV-2 neutralizing antibodies” by Paul D. Bieniasz et al, March 2021
- Get article on
- “Comprehensive analysis of T cell immunodominance and immunoprevalence of SARS-CoV-2 epitopes in COVID-19 cases” by A.Tarke et al… – Cell – 16-02-2021
- “Landscape of epitopes targeted by T cells in 852 individuals recovered from COVID-19: Meta-analysis, immunoprevalence, and web platform” by Matthew R. McKay et al, Cell, May 2021
- “How Broad is Covid Immunity?” by M.Yeadon/M.Girardot, Panda, March 2021
- Countries: Canada, Ecuador, Gabon, Germany, India, Singapore, Sweden, UK, USA, Tanzania, Zambia
- “Cross-reactive CD4+ T cells enhance SARS-CoV-2 immune responses upon infection and vaccination” by Claudia Giesecke-Thiel, April 2021
- “Profiling SARS-CoV-2 HLA-I peptidome reveals T cell epitopes from out-of-frame ORFs” by Pardis C. Sabeti, Cell, June 2021
- “The landscape of antibody binding in SARS-CoV-2 infection” by Irene M. Ong et al, PLOS biology, June 2021
- “Adaptive immunity to SARS-CoV-2 and COVID-19” by Alessandro Sette & Shane Crotty, Cell, January 2021 – page 866
- “Protection of previous SARS-CoV-2 infection is similar to that of BNT162b2 vaccine protection: A three-month nationwide experience from Israel” by Amit Hupper et al, April 2021
- “Discrete Immune Response Signature to SARS-CoV-2 mRNA Vaccination Versus Infection” by Sergei Koralov, Cell, May 2021
- “We observe striking expansion of circulating plasmablasts in COVID-19 patients relative to healthy volunteers”
- “In COVID-19 (recovered) patients, we observed an expansion of cytotoxic populations and a dramatically elevated cytotoxic signature in NK cells, CD4 and CD8 T cells, and γδ T cells.”
- “Differential Effects of the Second SARS-CoV-2 mRNA Vaccine Dose on T Cell Immunity in Naïve and COVID-19 Recovered Individuals” by Jordi Ochando et al, Cell, March 2021
- “Suspicions grow that nanoparticles in Pfizer’s COVID-19 vaccine trigger rare allergic reactions” by Jop de Vrieze, Science, December 2020
- “Historical Vaccine Safety Concerns”, CDC
- “The Cutter Incident: How America’s First Polio Vaccine Led to a Growing Vaccine Crisis” by Michael Fitzpatrick, Journal of the Royal Society of Medicine, 2006
- “The Public Health Legacy of the 1976 Swine Flu Outbreak” by Rebecca Kreston, 2013
- “UN says new polio outbreak in Sudan caused by oral vaccine” by Maria Cheng, Associated Press, September 2020
- “Anvisa denies certificate of good practice to Bharat Biotech, which produces Covaxin” by Enzô Machida and Murillo Ferrari, CNN, March 2021
- “Organ bio distribution study undertaken by the Japanese regulator”
- “Potential adverse effects of nanoparticles on the reproductive system”by Shao LQ, DovePress, September 2018
- “Synthetic Lipid Nanoparticles Targeting Steroid Organs” by Bertrand Tavitian, The Journal of Nuclear Medicine, 2013
- “PEGylated liposomes: immunological responses” by Tatsuhiro Ishida et al, Science and Technology of Advanced Materials Vol 20, 20219
- “Pseudo-anaphylaxis to Polyethylene Glycol (PEG)-Coated Liposomes: Roles of Anti-PEG IgM and Complement Activation in a Porcine Model of Human Infusion Reactions” by János Szebeni et al, ACS Nano, 2019
- “Superantigenic character of an insert unique to SARS-CoV-2 spike supported by skewed TCR repertoire in patients with hyperinflammation” by Ivet Bahar et al, PNAS, October 2020
- “SARS-CoV-2 spike protein induces inflammation via TLR2-dependent activation of the NF-κB pathway” by Hasan Zaki et al, March 2021
- “SARS-CoV-2 Spike Protein Impairs Endothelial Function via Downregulation of ACE 2” by John Y-J. Shyy, Circulation Reseacrh, MArch 2021
- “Single intratracheal exposure to SARS-CoV-2 S1 spike protein induces acute lung injury in K18-hACE2 transgenic mice” by Pavel Solopov et al, The FASEB Journal, May 2021
- “SARS-CoV-2 spike protein interacts with and activates TLR4” by Fuping You et al, December 2020
- “Bacterial Toxins—Staphylococcal Enterotoxin” by Bettina C. Fries & Avanish K. Varshney
- “A prothrombotic thrombocytopenic disorder resembling heparin-induced thrombocytopenia following coronavirus-19 vaccination” by Sabine Eichinger et al, The New England Journal of Medicine, April 2020
- “Acquired Thrombotic Thrombocytopenic Purpura: a rare disease associated Acquired with BNT162b2 vaccine” by Dorit Blickstein et al, Journal of Thrombosis and Haemostatis, June 2021
- “The SARS-CoV-2 spike protein alters barrier function in 2D static and 3D microfluidic in-vitro models of the human blood–brain barrier” by Sergio H. Ramirez, Neurobiology of Disease, December 2020
- “The S1 protein of SARS-CoV-2 crosses the blood–brain barrier in mice” by William A. Banks et al, NAture Neuroscience, December 2020
- “Guillain-Barré syndrome following ChAdOx1-S/nCoV-19 vaccine” by Boby Varkey Maramattom et al, June 2021
- “Underreporting of Side Effects to VAERS” by Vincent Iannelli, Vaxopedia, September 2017
- Open VAERS data
- “The C.D.C. is investigating nearly 800 cases of rare heart problems following immunization.” by Apoorva Mandavilli, New York Times, June 11, 2021
- “Israel reports link between rare cases of heart inflammation and COVID-19 vaccination in young men” by Gretchen Vogel & Jennifer Couzin-Frankel, Science, June 2021
French City Fair Drops Covid Measures In Victory For People Power!
By Richie Allen | July 7, 2021
On Friday last, the historic city of Tours in France opened its annual fair. It’s normally a very big deal. This year is even more special as the fair celebrates its centenary. However, organisers and traders were shocked on Friday, when hardly anyone turned up.
Attendees and staff were told that they would need a “sanitary pass” to attend. To get a pass, a visitor or worker needed to show proof of vaccination or take a PCR test at the entrance. Throughout Friday, the fair was a ghost town and only 4 per cent of the staff had shown up.
Panic ensued. Traders, having spent thousands of euros for their pitches started screaming bloody murder. Others started buying and selling products among themselves. It was grim. Punters were walking away in their thousands. No-one wanted anything to do with the PCR tests piled high at the entrances.
At the 11th hour, the city backed down and all restrictions were lifted. The traders had been bombarding the local authority all day with texts and emails, threatening retribution if the sanitary pass wasn’t kicked to the kerb.
The city blinked and the fair was mobbed over the rest of the weekend. The PCR tests are still rotting at the entrances. The people of Tours stood up.
Vive La France! That’s the way it’s done. That’s people power. The French never let you down. Let it be a lesson to the businesses of the UK and Ireland.
We are sick to the back teeth of this scamdemic. We want our lives back. We want to frequent shops, theaters, cafés, cinemas, bars and restaurants again. We’ll fill your tills.
Just remember, whether we have been jabbed or not is none of your business. Same goes for face muzzles. The ball is now firmly in your court. I can’t wait to see you again.
Featured Video

Seyed M. Marandi: US-Iran War Inevitable: Kuwait and Bahrain May Fall
or go to
Aletho News Archives – Video-Images
From the Archives
Oil and the Israel Lobby
Reknowned economist M. Shahid Alam offers this excellent critique of Noam Chomsky’s defective analysis of the relative influence of Oil versus the Israel lobby over US foreign policy: … continue
Blog Roll
 Aletho News
- ICC ignored ‘very well-documented’ NATO crimes – ex-Libyan minister
- SNSC secretary dismisses US response to Iran’s conditions as ‘inadequate’
- Sanaa says Taiz roads open, secure for residents, warns Saudi forces
- Iraqi resistance group urges Saudi leadership to admit defeat, lift Yemen siege
- Trump’s Retreat: How Al-Aqsa Flood Took Down the US Empire
- Israel’s Military Actions in Lebanon Grossly Violate International Law — Lavrov
- Seyed M. Marandi: US-Iran War Inevitable: Kuwait and Bahrain May Fall
- Leaders Condemn Ansarallah Attack on Saudi Arabia While Ignoring Illegal War Against Yemen
- Leaked: Britain’s Covert Iraqi Psyops Network
- Yemeni Armed Forces Warn Airlines Against Using Saudi Airports, Exempt Mecca and Medina
- If Americans Knew
- How Israel Conquered the Latin American Right
- Agents search Rep. Omar’s Washington home in criminal probe as she vows she won’t ‘be silenced’
- “The Rule Was: ‘Shoot Everyone You See'”
- Israel goes ballistic over Nobel Laureate Navi Pillay
- U.S. May Join Yet Another Middle Eastern War — TCN
- Yellow Line moves again as Israel closes in on trapped Gazans – Daily Update
- Israeli Attacks Kill Seven Palestinians in Gaza Including Six-year-old Girl
- Gaza: Ceasefire Anniversary Marks Year of Failed Promises
- The American Conservative: Mike Huckabee Should Resign
- A C-Section in Shackles: A Palestinian Woman’s Harrowing Birth in Israeli Detention
- No Tricks Zone
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI

