US chief medical officer Anthony Fauci’s net worth surged to $12.6 million in 2021, nearly twice the $7.6 million it had been in 2019, watchdog group OpenTheBooks revealed on Friday, citing financial disclosures it obtained from Fauci’s employer, the National Institutes of Health.
Already the highest-paid employee in the federal government before the pandemic as director of the National Institutes for Allergies and Infectious Diseases, Fauci pulled down a salary of $456,000 in 2021 and $480,000 in 2022. However, that paycheck represents just a fraction of the money he made while his Covid-19 policies helped push the US economy into a recession.
The disclosures show multiple trusts, retirement accounts, and other financial assets, all of which seem to have appreciated in value during the pandemic even as much of the real economy suffered. Book royalties and the $1 million Dan David Prize from Israel, as well as appearances and speaking fees, round out Fauci’s Covid-19 windfall. When OpenTheBooks asked the NIH to see all royalties paid to the doctor, however, the document they received – which would have shown exactly how much Fauci was financially benefiting from drugs and other patents – was reportedly heavily redacted.
“While Dr. Fauci has been a government bureaucrat for more than 55 years, his household net worth skyrocketed during the pandemic,” OpenTheBooks CEO Adam Andrzejewski told Fox News, attributing the doctor’s wealth spurt to “career-end salary spiking, lucrative cash prizes awarded by nonprofit organizations around the world, and an ever-larger investment portfolio.”
Fauci has been criticized throughout the pandemic for allegedly profiting off the pricey antiviral medication remdesivir, which he proclaimed the standard for treating Covid-19 despite lackluster clinical trial results and having been against the initial advice of the World Health Organization.
Fauci appears to dislike discussing his finances in public, having been caught on a hot mic describing Republican Senator Roger Marshall as a “moron” for merely asking to see what were supposed to be publicly available documents. The Kansas senator, who is also a doctor, asked to see Fauci’s financials during a January hearing only for the NIAID chief to insist they were already public – a statement that was not true at the time. OpenTheBooks sued for access in January and only recently received the documents it posted on Friday.
Following the hearing, Marshall introduced the FAUCI Act (Financial Accountability for Uniquely Compensated Individuals) to require that government employees’ financial disclosures be publicly accessible on the Office of Government Ethics website.
The German government has ordered 100 million doses of BA.1 and BA.4/5 bivalent vaccines at a cost of 2.5 billion Euros, and almost nobody wants them. An amusing Welt article chronicles the scenes unfolding at our deserted regional vaccination centres, which for some reason are still open:
Michael Hubmann did not expect that so few would come. Only 85 people had themselves vaccinated against Covid-19 on Thursday in Fürth in Middle Franconia, a district with 120,000 inhabitants. “We’ve tried to make it as easy as possible for people,” says Hubmann, a paediatrician who coordinates the vaccination campaign. He explains that vaccinations were offered simultaneously in two shopping centres, a bus, a home for the elderly and in a former shop in the pedestrian zone. “Yet hardly anyone wanted to have the fourth dose.”
The medical bureaucrats are baffled, just baffled:
“Unfortunately, interest in the fourth dose has been pretty low so far,” says Markus Beier, Chairman of the German Association of General Practitioners. At the same time, he says it’s important that people over 60 and those with previous illnesses in particular protect themselves with a further dose. “There is uncertainty among the population as to what further vaccinations will achieve. But they still strengthen protection against severe outcome.”
Meanwhile, vast quantities of vaccine are expiring. At the end of August alone, 3.9 million doses of Moderna and another 700,000 doses of Novavax had to be binned.
The chart above tells the whole sordid story of our recent experiment with mass vaccination. Demand for this snake oil was highest in the beginning, before anybody had any direct experience with it; and in the Fall, when the government tied it to specific social privileges. As overt vaccinator coercion has faded and millions of people have tried these doubtful elixirs for themselves, demand has all but evaporated. This is the ultimate vindication for all those who have been saying that the vaccines are lousy overhyped pharmaceutical products with a bad side-effect profile. A safe and effective product would only gain momentum with the population. It took less than two years for these to wear out their welcome.
GlaxoSmithKline (GSK), which is not a manufacturer of a Covid vaccine and thus did not benefit from Covid vaccine sales, recently announced second quarter 2022 results that surpassed expectations. This has enabled an upward adjustment in the profit forecast for the full year 2022. The Telegraph reported that GSK shares are up 44% from last spring.
Sales of GSK’s shingles vaccine, Shingrix, was the main driver of growth. Shingrix sales more than doubled in the second quarter, being April to June 2022, pushing up total GSK sales by 13%.
Shingrix is a relatively new shingles vaccine that my doctor tells me is considered an improvement on Zostervax, the traditional shingles vaccine. However, Shingrix is not cheap. A two dose course in Hong Kong costs £600, in the U.K. £440 and in the U.S. around $300. Allowing for distributor and retail margins, I estimate that GSK’s income would be about one third of the retail price. Let’s assume therefore that GSK earns £150 per two dose course on a worldwide average basis.
According to GSK, sales of Shingrix doubled to £731M, an increase of £366M in one fiscal quarter. At £150 per course, this equates to an unexpected increase in sales and thus vaccine recipients in one fiscal quarter of 2.4 million from the expected quarterly run rate.
When asked the reason for this surprising jump in Shingrix sales, GSK’s CEO stated: “It comes after countries started to shift their focus away from Covid towards other jab campaigns.”
Nobody seems to have questioned this statement. In the period in question, April to June 2022, Covid vaccine programmes were still highly active and indeed many programmes across the world were on to their third or fourth booster.
Though extremely painful, shingles is not life threatening and generally affects people over 50. It affects persons who have previously had chickenpox, often in their childhood, and is triggered mainly by overwork, lack of sleep or similar stress-related reasons. Shingles attacks the nervous system, especially nerve endings, and hence is often intensely painful.
Vaccination against shingles is not routinely given to all over-50s in most countries. Despite this, according to GSK, in the middle of a continuing Covid campaign, countries opted to shift their focus to vaccinating against shingles?
Is this likely? If indeed there was a shift to more usual vaccination programmes, would vaccination against shingles have been prioritised? Additionally, given the cost of this vaccine, and weighing up the public benefit, would most countries or patients really switch to Shingrix from the much cheaper Zostervax?
All of this seems unlikely. So what has driven a 50% increase in sales of a very expensive vaccine not part of the usual standard vaccination programme?
Further, taking the USA as an example, the ratio of Shingrix to Zostervax sales is 50-50. In most other countries, Shingrix has less than 50% of the market. If 2.4 million people in one quarter had the Shingrix vaccine, how many more had Zostervax? It is not inconceivable that some 5 million more people than usual were vaccinated against shingles in one quarter.
Can this really be explained by countries restarting their normal vaccination programmes, and for no particular reason adding a shingles vaccines into the standard mix?
I may have the answer. In my 50s I twice had shingles. I can vouch for how painful it is. Since then I have had the traditional shingles vaccine jab every few years and had been shingles free for 15 years. I have also consciously improved how I manage my business travel and lifestyle to reduce travel stress and tiredness, which had been the previous drivers in my case.
In March and April 2021 I had my first and second Pfizer Covid jabs. On the day following the second jab I developed a chickenpox like rash and started to experience nerve pain. As I am something of a shingles veteran, I immediately thought “I am getting shingles!” And this is, indeed, what developed quite badly over the next few days.
I rang my doctor who said, “It can’t be shingles, you are vaccinated.” However, after examining me the next day he agreed I was right. I asked what had brought this on? Could it be the Covid jabs? He replied: “I cannot explain why, but it is not likely to be connected to the Covid jab. Just unfortunate timing.”
My doctor then prescribed the usual medication for shingles and it cleared up in a week or so (for some it can take many weeks). My doctor then suggested I spend £600 having the new and better Shingrix vaccine, “as obviously your body is now immune to the traditional vaccine”. In his defence, this was very early days for assessing vaccine side-effects.
I decided I would not spend £600. Instead, I set about researching on the internet.
Since then it has transpired that shingles is a recognised reaction to the Pfizer vaccine in older people. Shingles is an inflammation of the nerves and nerve endings. The mRNA vaccines are now known to affect the nervous system in a number of different ways. It appears that triggering shingles is one of them (or else it is a result of a temporary depression of the immune system, as some have suggested).
Significantly, my doctor has confirmed he has now had other patients who contracted shingles after Covid vaccination. Most took up his £600 offer of Shingrix. It does not take much to imagine what a multiplier effect such advice and take-up across the world would have on the sales of Shingrix and the profits of GSK.
Something must be happening across the world for sales of an existing single product to double in a quarter by 2.4 million. In the absence of any other new factors, one can conclude that the drive in sales must have been due to one side-effect of the Covid vaccines. Equally one can imagine the booster effect for the makers of Zostervax too.
Whilst not all pharmaceutical companies have produced enormously profitable Covid vaccines, the emerging medical toll, side-effects and general aftermath of these vaccines and lockdowns is only just emerging. I suspect all pharmaceutical companies will now share in a second Covid profits bonanza driven by medications prescribed to deal with the collective aftermath of Covid. GSK has lit the way.
On September 8, I wrote about California Governor Gavin Newsom having AB 2098 — legislation that “tells the state’s medical boards to punish doctors who challenge the coronavirus orthodoxy” — on his desk for him to either veto or sign into law. The punishment the state medical boards could impose under the legislation includes revoking doctors’ medical licenses.
Here is an update. On Friday, Newsom signed into law this bill directing the prosecution of an attack on free speech, medical freedom, and the pursuit of better health.
The coronavirus orthodoxy, or party line, the legislation seeks to protect has repeatedly been wrong — from promoting “social distancing” and mask wearing that have not been shown to provide a net benefit in countering coronavirus to advocating that everyone take the “safe and effective” coronavirus “vaccine” shots that turned out to be both exceedingly dangerous and ineffective. The coronavirus orthodoxy also demanded that much of the economy and social interactions be shut down for an extended period of time in a supposed effort to reduce the spread of the not-very-threatening-to-most-people coronavirus. In short, the coronavirus orthodoxy is an enemy of wellbeing.
Newsom’s decision to sign AB 2098 into law is not surprising given that he has been one of the governors most adamant in imposing a coronavirus crackdown.
Kim Iverson, a TV journalist formerly at The Hill and now streaming her own show on YouTube, has been one of the most honest and courageous voices during the pandemic. She is the rare journalist today who is willing to follow the evidence wherever it may lead. I sat down with her this morning for an interview about California’s latest attempt to suppress the free speech of physicians and undermine the doctor patient relationship. Assembly Bill 2098, which I have posted about previously—see Punishing Dissident Physicians and The Censorship of Medicine—is set to become law unless the governor vetoes it today.
I also had a wide-ranging two-part conversation with Dr. Drew Pinsky on his podcast recently, where we discussed my new book, The New Abnormal: The Rise of the Biomedical Security State. It’s available on the Apple Podcasts (link to Part 1 and Part 2), or your other favorite podcast app.
You can pre-order the book here and it will ship in one month…
Ron Johnson, the only Federal politician that has publicly called out the deep corruption behind the failed U.S COVID response, is helping protect doctors.
Senator Ron Johnson and I just published an Op-Ed Monday on the Fox News site, the 3rd most visited news site on the internet, with almost one billion visits per month.
As some are probably aware, California’s Legislature just passed an obscenity of a bill titled “AB 2098” which calls for the state’s medical board to revoke the license of any physician who expresses an opinion “contradicted by contemporary scientific consensus to the standard of care.” I am not even sure what that means but holy cow, they just literally started to outlaw opinions.
Not sure which genius came up with that bill but to pretend there is a “scientific consensus” on a novel disease and a novel gene therapy is absurd. That is not how science works. Medicine is (was?) constantly trying to increase its knowledge base throughout history. In fact, one of the core responsibilities of a physician is not just to care for a patient as their “primary consideration” but also to add knowledge to the discipline and to teach it to others. Here is another responsibility articulated in the Hippocratic Oath written around the 4th century BC: Neither will I administer a poison to anybody when asked to do so, nor will I suggest such a course. Whoa. Hippocrates was warning us 24 centuries ago about the situation of being asked to administer poisons. Wow.
Anyway, what is medical consensus – is it state-wide, national or international? I am sure there are more than a couple of California doctors (or maybe not) whose opinions conflict with the captured Federal health agencies but are instead supported by academies of scientists and health agencies in other countries. Or even states like Tennessee that made ivermectin legally available over the counter to its citizens!
Denmark long ago restricted any person under 30 from getting the Moderna “vaccine.” In the US we now give it to toddlers. I repeat, in the U.S, we now give it to toddlers. If I object to injecting toddlers with Moderna, using the same “science” that Denmarks authorities are using, am I then a misinformationist that should not be allowed to practice medicine? What would happen to me if I go even further and espouse Denmark’s latest guidance which is to not recommend COVID mRNA vaccination to any low risk individual under 50? I guess the California State Department of Health guidance would trump that of Denmark’s. Watch out Denmark, here I come!
The scariest part of that legislation to me is that it reflects a complete ignorance of decades of evidence demonstrating that our Federal Health Agencies are under regulatory capture by the Pharmaceutical Industry. Just look at all the shenanigans the PFDA (the P is not a typo) pulled to sell the most vaccines. The below policies were all written by the Pharmaceutical Industry and issued by the PFDA, yet California doctors who know this and try to warn their patients in order to protect them from the evils of that industry could lose their license. Remember these two brilliant scientific standards?
(I paraphrase from memory)
Testing is no longer indicated for those who have received COVID mRNA vaccination (luckily this one didn’t last very long).
Testing for antibodies to assess prior exposure to COVID is not recommended prior to administering COVID mRNA vaccination.
They literally tried to avoid gathering data that would prove the vaccines were ineffective. Then they literally established that natural immunity should be ignored. With no data to support those “standards.” One of the greatest absurdities in the history of medicine was the fact that the entire health system started vaccinating people right after they recovered from COVID. They didn’t even wait for the variant to change first. But, if you publicly express a difference of opinion with this expert approach to managing an infectious disease, your livelihood could be taken away from you. Seriously? What is happening in America? This is absolutely terrifying stuff. Fantods ripple up and down my spine as I contemplate the very high possibility that such an absurd bill could start spreading across the country, trampling on the very Constitution it is supposedly supported by.
Further, in order to establish a “true” consensus and/or standard of care guideline it has been estimated to require numerous studies over an average of 17 years. So, am I not allowed to voice an opinion until 17 years of studies pass? In a novel pandemic in which insights and data accumulate rapidly? What if I am an expert way ahead of the curve based on research I am doing and/or the ever evolving data and insights I gain from treating patients with this novel disease. Should I be quiet for 17 years until such a time when my insights and expertise are more widely established and accepted?
How will our silence ever get us to that consensus? How will my patients fare during that time? Stay home, wait until your lips turn blue because I am not allowed to have an opinion or practice in treating you if it differs from either non-treatment or giving pathetic Paxlovid, a drug which has one mechanism of action identical to that of just one of ivermectin’s many mechanisms. This is exhausting.
And should I ignore the decades of examples of corruption of the medical sciences via its journals and research funding? The vehicles that have propagated guidelines on any number of fraudulent medications (SSRI’s, statins, Xygris, Oxycontin, Vioxx, Bextra, Avandia and many more). Should I be silent until those frauds are more widely exposed?
Think about all the doctors who saved their patients from those frauds despite being propagated as “medical consensus” at the time? A free and open scientific debate, championing those voices without conflicts of interest is what is needed. Instead this bill will silence those without conflicts while further amplifying the media megaphone of vaccine manufacturer CEO’s. These are dark dark times.
And why are we suddenly displacing the time honored protections of medical malpractice – where the consequences of harming a patient was borne by the physician if they adopted an idea or practice which hurt a patient. That has kept doctors in line for decades. But now, prior to any idea or practice I espouse actually resulting in harm, my opinion would be silenced or else I lose my license to practice. This is an obscenity. This would disappear care practices that would help patients far more frequently than it would care practices that harm patients.
This bill will lead to even more morbidity and mortality, not only in COVID, but in other diseases as well. Pharma already controls the medical journals and Federal Health agencies. But they don’t control independent physician’s opinions and voices. Well, at least they didn’t until now.
Good luck California, I fear for you. No-one from the medical field will be able to warn you of the continued rampages of a documented criminal industry.
Our Op-Ed is here, but I think I already covered most of it. Enjoy, although it ain’t fun.
Michel Goldman, M.D., Ph.D., professor of immunology and pharmacotherapy at the Université libre de Bruxelles in Belgium, suspects his third dose of Pfizer’s COVID-19 vaccine may have sent his cancer into overdrive.
But he told The Atlantic he wants discussion of the COVID-19 vaccine to be transparent — so he went public about his suspicion that the Pfizer booster shot he received on Sept. 22, 2021, may have induced rapid progression of his angioimmunoblastic T-cell lymphoma (AITL), a type of lymphoma he’d been diagnosed with before he got the booster shot.
After his diagnosis, Goldman said he rushed to get the booster shot, believing he would need it more than most people because once he started chemotherapy, his immune system would be compromised.
But after receiving the shot, Goldman’s follow-up CT scan showed something unexpected: Within only a few days, his cancer had grown so fast that cancerous points were lighting up all over his scan.
“It looked like someone had set off fireworks inside Michel’s body,” The Atlantic reported.
Goldman and his brother, Serge Goldman, a fellow scientist and head of nuclear medicine at the teaching hospital of the Université libre de Bruxelles, suspected Goldman’s COVID-19 booster shot may have triggered the rapid proliferation of cancerous growth in his body.
The initial CT scan had been “a bit disturbing,” Serge Goldman told The Atlantic, because it showed an asymmetrical cluster of cancerous nodes around Goldman’s left armpit, where Michel’s first two doses of vaccine had been delivered.
The CT scan done after Michel’s third dose showed the cancer’s asymmetry had flipped and was clustered by his right armpit, where he received the third shot.
The brothers knew it could be a mere coincidence, but they thought it was important to investigate the possibility that the vaccine might be behind the clustering — because it could mean other people with certain forms of cancer might be at risk of a COVID-19 vaccine causing their cancer to progress more rapidly.
So on Nov. 25, 2021, the brothers — who had written prior papers together — and other colleagues published a case report in which they described Michel Goldman’s experience and urged the scientific community to study the phenomenon to see if it occurred in patients diagnosed with AITL.
“Since nucleoside-modified mRNA vaccines strongly activate T follicular helper cells, it is important to explore the possible impact of approved SARS-CoV-2 mRNA vaccines on neoplasms affecting this cell type,” the authors wrote.
The brothers said the case study “suggests that vaccination with the [Pfizer-BioNTech] BNT162b2 mRNA vaccine might induce rapid progression of AITL.”
They noted, however, that it would be “premature” to extrapolate the findings from Michel Goldman’s case to other patients with the same kind of cancer and that “dedicated studies are needed.”
Going public was ‘the right thing to do’
Michel Goldman’s case study added to the scientific literature that aims to understand the relationships between mRNA vaccines and the functioning of helper T-cells.
For instance, previous researchers have noted mRNA vaccines rev up helper T-cells, which may explain why Michel Goldman’s AILT went into overdrive following his third booster shot.
“Perhaps the shots gave such a jolt to his helper T cells that they went berserk,” The Atlantic reported. “If they were prone to forming tumors, or if they were already cancerous, then overstimulation could have made the problem even worse.”
Research involving body scans of some people who get mRNA vaccines — including cancer patients — shows heightened activity in the lymph nodes near the armpit on the side where the shot was received.
In February 2018, a team of researchers at Columbia University’s Institute for Cancer Genetics published a study using mice with a pair of gene mutations — the same two mutations found in Michel Goldman’s tumor — showing that the mutations predispose T-cells to go rogue.
The study also showed that when the mice were injected with red blood cells from sheep — as an experimental stand-in for invading microbes — the mice developed the same subtype of lymphoma Michel Goldman had.
Michel Goldman previously headed a $2 billion European endeavor to accelerate the research of new medicines and in December 2020, he publicly spoke out in support of the safety of mRNA vaccines — the technology used in both the Pfizer and Moderna COVID-19 vaccines.
At that time, he said the highest risk — especially for vulnerable people — is not to be vaccinated and that his main concern about mRNA vaccination was that people might use the possible side effects as an argument against getting the vaccine.
Michel Goldman doesn’t regret going public with his case, even though it presented challenging evidence regarding the safety of mRNA vaccines for individuals such as himself.
“I’m still convinced it was the right thing to do,” he told The Atlantic.
He remains adamant that COVID-19 vaccines are useful for the vast majority of people, but he is unsure whether he himself will get another booster dose.
“I don’t know what I will do,” he said.
Suzanne Burdick, Ph.D., is a reporter and researcher for The Defender based in Fairfield, Iowa. She holds a Ph.D. in Communication Studies from the University of Texas at Austin (2021), and a master’s degree in communication and leadership from Gonzaga University (2015). Her scholarship has been published in Health Communication. She has taught at various academic institutions in the United States and is fluent in Spanish.
My recent post about scientists finding mRNA nanoparticles containing Covid vaccine genetic code, in the breast milk of vaccinated mothers, and mentioning an infant documented to have died thereof, got quite a bit of traction online.
Today, I want to look at a study from a year ago that purported to NOT find mRNA nanoparticles in breast milk. We will see why exactly the team having Bill Gates and CDC-sponsored researchers, could not find what the independent scientists could find a year later!
I decided to compare the two studies (one that found mRNA in breast milk and the other that did not) very closely and compare their methodologies using the “Modern Discontent” method.
Modern Discontent has a great post about his method, but he mostly is saying “pay close attention and understand the whole f… thing”, which is basically what I usually do with something interesting and important anyway. He posted his method three days ago, and I had my substack for a while longer. So, I intuitively used many of his approaches, but he laid them out very systematically and clearly. His article is extremely useful for all people writing about biomedical science, so take a look:
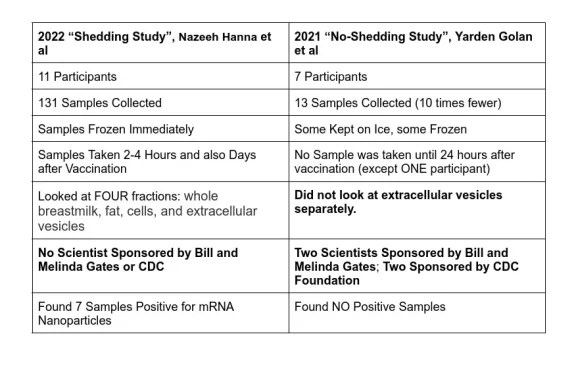
At first sight, both studies, which I will call the 2022 shedding study (which I discussed two days ago) and the 2021 no-shedding study, superficially appear to be similarly designed. They took several lactating women and tested their milk. One study found shedding, while the other did not. Upon a closer look, the differences between these studies turned out to be extremely important!
Here’s a summary of their differences:
You can see that the study that found mRNA lipid nanoparticle shedding, was done more thoroughly. The shedding study had:
More participants (11 vs 7)
More milk samples were taken (131 vs 13!)
Samples better preserved (frozen immediately)
Samples were taken at varied moments post-vaccination including within mere hours, and also days
Looked at very important Extracellular Vesicles
As a result of being more thorough and covering more cases, the shedding study found actual shedding! Surprise!
What if the women in the shedding study, getting the same vaccines, were analyzed using the poorer methodology of the no-shedding study?
I took the chart from the shedding study showing five women with milk samples positive for mRNA nanoparticles. I crossed out samples that WOULD NOT BE DETECTED, if the no-shedding study methodology was applied to the samples of the shedding study:
You can see that if the researchers in the shedding study used the crippled methodology of the no-shedding study, they would detect only two positive samples, instead of seven.
The methodology of the no-shedding study would miss all extracellular vesicle (EV) samples because they did not look at EVs. That is shown in the column on the right that is entirely crossed out.
The no-shedding study would also miss the 1 hour and three-hour samples because they did not take those samples (save for just ONE woman who happened not to be positive).
As a result, had the less thorough no-shedding study methodology been applied to the shedding study, only 2 positive samples, instead of 7, would be detected!
Since the actual no-shedding study collected only 13 samples and not 131 samples and used deficient methodology, no wonder they missed all positive instances!
It is as if the no-shedding study was intentionally designed not to find anything. Hmmm…
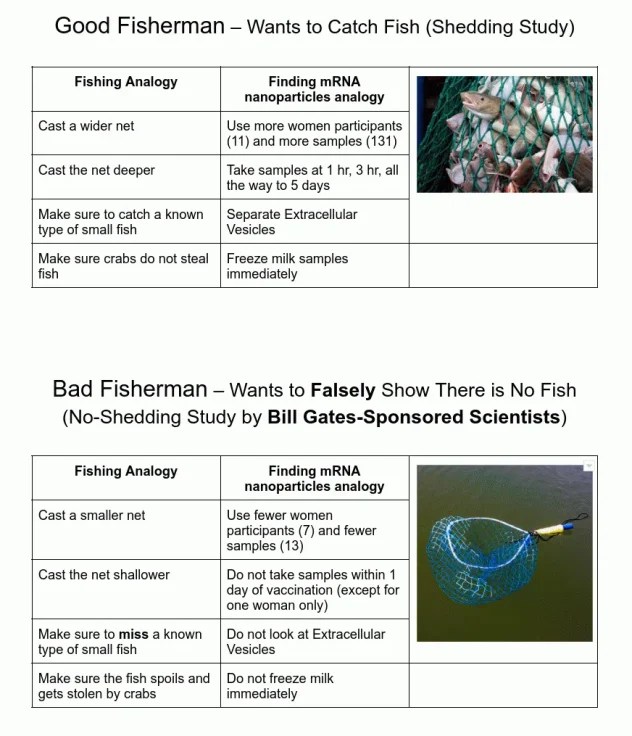
Fishing Analogy
Let me give an analogy that many will understand — fishing using fishing nets.
Let’s say that a good fisherman (the shedding study) was asked to do his best job fishing to see if a particular lake has fish (mRNA nanoparticles). A bad fisherman, on the contrary, would be asked to design his fishing expedition to not catch any fish, so as to falsely prove that the lake has no fish. What would they do? This infographic shows the difference:
What’s up with Bill Gates and the CDC?
By pure coincidence, the study that did not find mRNA nanoparticles in breast milk (the no-shedding study), had key scientists sponsored by the Bill and Melinda Gates Foundation. They also received money from the CDC. You can see that Prof. Gaw and Dr. Flaherman were key participants, making the most important decisions and analyses!
Did these sponsorships influence the authors’ approach to designing the experiment? We cannot know this. We can only wonder.
As my beleaguered teaching colleagues and I try to get our school communities into the swing of things once again this new academic year, I find myself to be merely, powerlessly wishing that no more grotesque permutations of the Covid Madness return for a third consecutive winter. ‘Home-learning’ in particular was, of course, disastrous for children in a myriad of ways. On a purely practical level, it was fairly tricky for the teachers too, so I do believe that most of the profession hopes to avoid the insidious perfidy of forced absences or outright closures. Granted, I would prefer my colleagues to be motivated in these desires by an understanding of the abhorrent, casual neglect of children’s fundamental needs over which we were forced to preside for two years. But I’ll have to be content if the Department for Education will just let us stay open.
Belatedly, conventional wisdom has it that Covid doesn’t tend to seriously affect the school-aged population. Perhaps if the undistorted version of that truism was more widely accepted – that Covid doesn’t tend to seriously affect the healthy population – some teachers (and their unions) might find that their selfish and flawed but unending clamour for ‘more to be done’ lost its sympathisers.
It’s been a typically warm and sunny September thus far, but a small number of our students remain curiously attached to their face-coverings, sporting them lesson in, lesson out, as I look on aghast but unable to order their removal. The so-called harmless, cost-free non-pharmaceutical intervention continues to wreak its harms.
For those of us who have, by now, long fought Covid restrictions, it might feel like a further, renewed battle this Autumn to see off the prospect of the Return of the Madness. After all the hammer-blows of Spring 2020, we ordered our thoughts, picked our battles, identified our sacrifices, practised our polemics, marshalled our arguments and, eventually, took to the fray. For many of us with little or no previous experience in politicking, we may even have learnt some tricks about the art of discourse and debate along the way.
I am not referring here to my professional life of course. In my professional life I am – quite rightly – not permitted to express my personal or political ideologies or opinions to students. No good and proper teacher would dream of doing so – unless of course you suddenly, naively found that your beliefs fell in line with the government propaganda of the day. If you happened to support the mantra “Hands, Face, Space”, you could plaster it across every TV screen and vacant stretch of wall in the whole place. If you were minded to promote social distancing, or face coverings, or bubbles, or ‘don’t kill granny’, or healthy 12 year-olds giving their own consent to being tested for Covid before entering the building, or any other similar paean to the dreaded virus – exhort it from the corridors, folks! If you were an Assistant Head, you might even have the surprising chutzpah to lead a series of science-themed assemblies (to 1,200 impressionable young minds) in which you vaingloriously celebrated the disingenuous and risible proposition that Professor Sarah Gilbert’s AstraZeneca vaccine “saved 2 billion lives”.
No – when I refer to my endeavouring anew to muster awareness of the risk of restrictions this winter, I’m talking about in my personal life, away from school.
There is a danger for those of us who have resisted the mainstream Covid narrative for two-and-a-half years that we forget quite how completely and devastatingly uninterested the compliant majority are in our version of events. Many may have shifted their positions slightly, faced with ever more piles of evidence (from their own preferred sources) of the damage needlessly done. Surely, it would be hard to find someone who would embrace it all quite so gleefully all over again.
But the big arguments are not won; the wider population are still just not listening. Family members try to gently talk us down; friends tactlessly avoid the subject altogether or just silently disappear from view; some colleagues regard me warily and with increasing wryness as a bit of a crank. They all seem to manage to tell themselves that none of it really affects them and, with a special kind of inward-looking perspective, I suppose they can make that be true.
So we keep talking and waiting and wondering where the socially palatable prima facie evidence to incontrovertibly back us up and help us definitively put a stop to all this might come from. I continue to posit theories, based on my understanding of basic principles of human decency and common sense. Anecdotes, ideas and experiences should be part of our arguments and, after all, when that single piece of elusive, critical, confirmatory data lands – why should anybody ever believe what any expert says these days anyway?
Some older adults – I overhear them in crowded cafes – are delightedly and obediently getting in line for their fifth (count ‘em!) Covid jab, and some disconcerting individuals in the High Street and park remain devotedly wedded to their face-covering. They don’t seem one bit ashamed or embarrassed by the many peculiar and ridiculous things their Government forced them to do for a good while there. Is that just it for them? Over and Out, Shut Up, Move On. Are these things, this history, these awful, ungodly consequences we’re all living with, just a permanent feature of the rest of their lives, no questions asked?
There are certainly those who seemed to revel in the whole drama of it all, those who still reel performatively, sanctimoniously backwards in doorways when you dare to step near; those who complied without thought and still appear blissfully ignorant of any possibility of error or mishap or downside and who probably watch too much TV; those who spewed the new terminologies of their epoch with uneasy, faltering confidence: ‘flatten the curve’, ‘viral load’, ‘third wave’, and – my personal favourite – ‘asymptomatic’.
Is it possible that this merry, obstinate lot are the very same people who seem in recent times also to be lurching emptily but enthusiastically from one cause to another? ‘Stay Safe everyone!’ ‘Respect this virus!’, bang a kitchen pan and ‘Save the NHS!’, erect a flag and ‘Stand with Ukraine!’, buy some frozen Chicken Kievs, close everything when it’s hot and etcetera and blah, ad infinitum.
Could it be that the common thread which connects all the headline-followers, the unquestioning, the frighteningly readily compliant, is a lack of something raw, true, local, deep and meaningful in their lives? Might there be a link between the modern world’s malaise, the tragic lack of connection and community, and a very public hankering after connection and community? You don’t know your neighbour, you’re not invested in your town, you couldn’t possibly overcome the awkwardness involved in helping the elderly lady down the road – why not get your phone out instead to prove how good you are at Joining In and Helping Out?
If people don’t have a potentially perilous stake in something close, precious and valuable, or anything at all to believe in which reaches them viscerally, it seems as though they might just keep scrambling around, somewhat manically and pathetically, for Another Good Cause to get behind.
And if I’m right about all of that, then the solution to the real Covid problem lies with people and professionals who don’t know they’ve got a problem.
Get a life. Get a community. Get some meaning. And do not force a single school kid to stay at home again this year.
The Lancet recently released its long-awaited COVID-19 commission report. The report well reflects the current state of public health science and addresses the business needs of the Lancet. It may have been naïve to expect further, but health is an important area and should be taken more seriously.
The level of obfuscation of evidence, misrepresentation of prior knowledge, and disregard for diversity of scientific evidence and opinion does not reflect well on either Lancet or the commission itself.
The Lancet in context
Medicine and public health are particularly dependent on truth and transparency, as the lives and health of people cannot be entrusted to dogma and superstition. Clear and open debate is fundamental to minimizing mistakes, which can kill, and to building the trust that patients and populations need to follow guidance (as they must ultimately be the decision-makers). These two related disciplines are also increasingly lucrative for practitioners and for the companies supplying the wares they employ. These forces inevitably pull in different directions.
Private companies making these wares, such as those in the pharmaceutical industry, have a responsibility to maximize profits for their shareholders. This means encouraging more people to use their tests or drugs, rather than putting people in states of health where they do not need them (either good health, or death).
This is not an extreme position, it is a simple truth – it is how this industry is structured. If there is a wonder drug in a lab somewhere that resolves all metabolic disease with a single dose, and it is easy to manufacture and copy, then the Pharma industry would collapse. Pharma has a duty to build a market, not heal.
Transparency and truth, on the other hand, could mean admitting certain highly profitable drugs are not needed or even dangerous; that an alternative safe and cheap drug, previously available for other purposes, will be more cost-effective and lower risk.
We cannot expect private companies to state this, as it will damage or destroy their income (their business). If they do not try to block a repurposed drug that puts their own investments at risk, they would be betraying their investors. What they should do, for their investors, is overemphasize the advantage of their own product, maximize the desire of people to use them, and run public campaigns to ensure this situation is prolonged as far as possible. This is what any for-profit business does – it is their job. It is not unexpected.
We have long relied on medical journals to act as a conduit for information from researchers to medical practitioners and the public. This is a plausible model if journals are independent and the staff and owners of the journal promote truth above politics or company profit.
This was once the case; the Lancet, a subject of this article, was once family-owned and that could hold to the values of Thomas Wakley and his descendants, standing against medical authorities up to 1921. It has since been owned by other for-profit companies, now a subsidiary of a larger Dutch-based publishing conglomerate, ‘Elsevier.’
Elsevier in turn is owned by RELX group (back in London), a large company with a typical list of major institutional investors including BlackRock (and so its major owner Vanguard), Morgan Stanley and Bank of America – the same list as major pharmaceutical and biotech corporations whose products Lancet publishes on.
The above does not tell us there is intentional wrong or malfeasance, just intrinsic conflicts of interest of the type journals such as Lancet are supposed to guard against. Lancet’s ultimate ownership has a duty to shareholders to use their portfolio of assets to maximize return; on this measure alone Lancet should favor certain pharmaceutical companies. The only thing that could stand in the way is lack of competence by the owners, or a moral code that rates investors below integrity.
In this context, Lancet’s track record over COVID-19 has been checkered. In February 2020 it published a major letter on COVID-19 origins that ignored major conflicts of interest in which nearly all authors were implicated in the alternative lab origin hypothesis. It published clearly fraudulent data on hydroxychloroquine that were significant in halting early treatment studies.
A lack of early effective treatment was necessary to secure Pharma profits for later COVID-19 medications and vaccines. The later exposure of the fraud was subsequently described by The Guardian and was one of the biggest retractions in modern history.
In 2022 Lancet published a weakly-evidencedopinion advocating medical fascism; dividing and restricting people based on compliance with pharmaceutical interventions. Lancet’s top leadership has remained unchanged throughout. This is relevant context for understanding the report of the Lancet ‘commission’ on COVID-19.
The Lancet COVID-19 Commission’s Report
In mid-2020 Lancet recruited people from various aspects of public life to review various aspects of the COVID-19 outbreak. This ‘commission’ (a somewhat grand name for a privately-convened group from a private for-profit business) was headed by economist Jeffrey Sachs, who preceded the recent release of the report by publicly discussing conclusions on the potential source of SARS-CoV-2, highlighting the probability of a laboratory origin as opposed to direct animal-human spread.
This part of the commission’s investigation had been halted early when Sachs discovered that several panel members had undisclosed conflicts of interest amounting to receipt of funding to conduct the very laboratory gain-of-function research widely suspected of promoting rapid human spread. Some had been authors of the earlier Lancet origins letter.
The Executive Summary provides a foretaste of the quality of work to come, noting IHME estimates of “17·2 million estimated deaths from COVID-19,” a “staggering death toll” as the commission notes, particularly staggering as it is higher than the WHO estimates for total excess deaths throughout the pandemic period. These WHO estimates include all deaths caused by lockdowns and those where virus detection was incidental. It is an implausible figure, even ignoring the lack of context here (nearly all in late old age, and with severe comorbidities).
Ironically, the commission reports in its main text over 2.1 million excess deaths from malaria, tuberculosis and HIV arising from the COVID-19 response in 2020 alone. However, this is a misunderstanding by commission members of WHO’s actual estimates – WHO does report significant excess 2020 deaths from these diseases but not this many – though many more will accumulate through subsequent years.
Reflecting the lack of inclusiveness of the commission itself, the report recommends censorship of the alternate approaches, considering “failure to combat systematic disinformation” to be a contributor to severity. The commission then inadvertently provides an example of disinformation in its characterization of the Great Barrington Declaration, misrepresenting it as calling for “uncontrolled spread of the virus.”
This, based on the declaration itself, must be a lie, as the commission must not have read the declaration within the two years they had available. Did they not consider it pertinent to question those who wrote it or (over 900,000) signed it? Whether the declaration was correct or not, it reflected prior WHO evidence-based policy. Ignoring this is simply untenable for a serious inquiry.
The overall findings of the commission are extremely disappointing from the point of view of science, public health, and simple honesty. Its apparent lack of familiarity with prior public health norms and practice, including that of the World Health Organization (WHO), may have been genuine, or may be contrived to emphasize a narrative it was intended to support. Given Lancet’s COVID-19 track record and business imperatives, the latter would not be entirely unexpected, but it is disappointing to see adults in positions of influence producing a document of this nature.
Summary of key findings
The Report helpfully provides a three page ‘Key Findings’ section. While missing aspects of the main body such as the euphemism “prosocial behaviour” to denote social exclusion, and extolling the “logic” of the completely illogical WHO slogan for mass COVID-19 vaccination, “No one is safe until everyone is safe,” it generally captures the main thrust of the whole text. Reading the rest is however recommended to understand how modern public health thinking has so clearly gone off the rails.
The key findings are stepped through here. Anyone with a public health background is encouraged to refute the concerns raised, as many of the commission’s assertions appear to involve common traps that seem inexcusable for public health professionals. They hang heavily on a failure to grasp three fundamentals of COVID-19 and public health:
Public health interventions are about risk and benefit. Interventions have positive and negative impacts. Recommendations therefore cannot be given without considering the potential harms they may cause in the short and long term, weighing these against perceived benefits.
COVID-19 mortality is highly skewed towards very old age, and heavily associated with comorbidities. Therefore it is imperative to consider COVID-19 disease burden relative to other diseases in terms of life-years lost, not raw mortality (from or with) COVID-19.
Prolonged lockdowns, workplace and school closures were not part of prior policy, or were partially recommended only in far more severe outbreaks. This is not implying the interventions were good or bad, it is just a fact that they defied public health norms and prior evidence. They were recommended against due to the harm they potentially cause. This lands most heavily, as WHO notes, on low income people and populations.
Highlights of the commission’s key findings:
“WHO acted too cautiously and too slowly on several important matters: … declare a public health emergency… restrict travel … endorse the use of facemasks…”
The commission seems unaware of the prior WHO pandemic influenza guideline. It is not among their 499 references. WHO specifically warned against restricting travel in this guideline, also noting that evidence on facemasks is “weak.” Travel restrictions can be significantly harmful to economies – cutting tourism income alone in low-income countries can increase mortality through poverty. The report fails to mention costs that extending these response measures would impose. Where lockdown costs are mentioned at all, it is in the context of costs of ‘failure’ to implement earlier or heavier, never in terms of weighing harm avoided against that caused. Ignoring relative costs, including the long-term health costs of increased poverty from longer lockdowns, is anathema to good public health policy.
Metanalysesof randomized control trials of community masking do not show significant benefit, and trials during COVID-19 show similarresults. At a minimum, WHO was therefore evidence-based when recommending against community-masking – the organization is yet to provide evidence to back its later endorsement of their widespread use. The Lancet commission appears to be specifically recommending against the use of evidence-based approaches.
“… most governments around the world were too slow to acknowledge its importance and act with urgency in response….”
Most people live in low and middle income countries with low COVID-19 mortality and far higher burdens from other infectious disease, which occur in far younger people. This statement therefore seems strangely Western-centric. If they had known earlier, what would countries have actually done? (if earlier implementation of poverty-inducing responses, then for how long?)
The commission appears unaware of serological evidence of spread prior to January 2020, in some cases backed by PCR. This would negate any benefit from this recommendation, even ignoring the harms.
Citing the Western Pacific Region as an example of ‘lockdowns working’ similarly makes little sense, as comparisons elsewhere (e.g. Europe) did not show significant benefit, while in crowded slum areas they are clearly pointless. Evidence of early wide transmission (e.g Japan) indicates that low mortality was due to other factors.
“Epidemic control was seriously hindered by substantial public opposition to routine public health and social measures, such as the wearing of properly fitting face masks and getting vaccinated.”
This statement is ignorant or disingenuous. If the commission members have experience in public health, they know that quarantine of healthy people, prolonged ‘distancing’ and workplace closures were never used at scale before, and that widespread lockdowns were not ‘routine public health and social measures.’ If they did not know this, they had two years to find out. The world, including Lancet, knew by March 2020 that COVID-19 overwhelmingly targets the elderly and has little impact on healthy working-age adults.
The vaccines do not significantly reduce overall transmission – heavily vaccinated countries continue to show high transmission – so to suggest low vaccination hindered epidemic control is a vacuous statement. It may seem intuitive (e.g. it occurs with some other vaccines) but the commission had 18 months to observe COVID-19 mass vaccination.
“Public policies have also failed to draw upon the behavioural and social sciences.”
This is an extraordinary statement to use regarding COVID-19. Many Western governments have openly employed behavioral psychology in an unprecedented way in the COVID-19 outbreak. No public health campaign has ever gained such media attention or had such uniform suppression of non-official messaging from media outlets. It is strange to see a statement so removed from reality.
“Heavily burdened groups include essential workers, who are already disproportionately concentrated in more vulnerable minority and low-income communities.”
This appears to be a nod to compassion for vulnerable populations. It is true that certain groups did suffer higher rates of severe COVID-19, though these are highly correlated with rates of comorbidities (obesity in Western countries is unfortunately associated with poverty, and poverty with certain ethnic groups).
However, the burden was overwhelmingly on the elderly – to a rate several thousand times that in young people. It is the response that burdened these groups most clearly and the report does mention inequity-driving school closures, but this appears forgotten elsewhere in an apparent blind support for faster and harder lockdowns.
“In low income and middle-income countries (LMICs)… better outcomes were seen when previous experiences with outbreaks and epidemics were built upon, and when community-based resources—notably community health workers—were used to support screening and contact tracing, capacity and trust-building within communities.”
This claim appears false. Sub-Saharan African countries did well irrespective of prior experience, with a relative exception of South Africa where obesity is more prevalent and there is a higher proportion of old people. Tanzania instituted very few COVID-19 specific measures but has similar outcomes. More than half the sub-Saharan population is less than 20 years of age, an age-group with extremely low mortality in the West. Actual spread in Africa, confirmed by WHO, has been very high.
“… the support for vaccine production in LMICs, for use in those countries, has come at a great cost in terms of inequitable access to vaccines.”
Nearly all people in low and middle income countries (except perhaps China) will by now haveimmunity. Post-infection immunity is equal or more effective to vaccine-induced immunity. Therefore, mass vaccination of a whole population with COVID-19 vaccines that don’t significantly reduce transmission cannot plausibly provide much benefit, whilst resource diversion is harmful. This statement is therefore devoid of public health sense.
“Economic recovery depends on sustaining high rates of vaccination coverage …”
Economic recovery depends on removing impediments to a functioning economy (lockdown measures). Vaccinating immune people with a vaccine that does not stop transmission cannot help to ‘reopen’ an economy. This statement parrots official mass-vaccination messaging elsewhere, but Lancet’s commission had an opportunity to promote logic and evidence-based policy.
“The sustainable development process has been set back by several years, with a deep underfinancing of investments needed to achieve the Sustainable Development Goals.”
This is indeed clear. Poverty is worse, malnutrition is worse, and preventable disease burdens are higher. Women’s rights are greatly reduced across much of the world, and school attendance has been denied to hundreds of millions of children, entrenching future poverty. Acknowledging this is important, but it also calls into question much of the remainder of the report. Recommendations that acknowledge these mass harms which are concentrated on populations with lowest COVID-19 risk, but go on to recommend more of the interventions that caused them, do not seem well considered.
The remainder of the key findings recommend policies of mass vaccination ‘to protect populations,’ more money for the World Health Organization, and more money internationally for supporters of the growing pandemic agenda. This plays to Lancet’s gallery, but does not consider the harms of resource diversion, the actual very low mortality from pandemics over the last 100 years, or the heterogeneity of human populations and of risk to disease.
If vaccines worked in reducing mortality (for all-cause mortality (the Pfizer and Moderna randomized controlled trials have not shown this to date), if vaccination was confined to highly vulnerable groups where benefit is most likely, and if the trillions of dollars spent on lockdown compensation, mass testing and mass vaccination had been spent on chronic and endemic disease burdens and poverty mitigation, does the Commission really believe more people would have died and outcomes been worse?
A travesty of public health and science
The commission members appear convinced that lockdowns and mass vaccination were a net benefit, but It also appears that in two years of consultation they have not considered the alternative. The loss of decades of progress on infectious disease, human rights, and poverty reduction caused by lockdowns has not been given sufficient pause for thought.
A virus that mainly targets people over 75 years of age was addressed with a public health response that targets the children and the economically productive, cementing long-term poverty and inequity. They support this approach, but consider it should have been instituted earlier, and was lifted too soon.
After emphasizing mandatory and restrictive measures throughout, and misrepresenting or ignoring alternative approaches, the report ends on a note that it should perhaps have started with. “We note the timeliness of recommitting to the Universal Declaration of Human Rights, the UN’s moral charter, as we celebrate its 75th anniversary in 2023.”
This declaration includes rights to work, travel, socialize, and express opinions freely including, specifically, through any media. A quick read of the WHO’s charter would also have helped – health includes social and mental well-being (and physical well-being beyond a single disease). The report is void of such thinking – a travesty of both human rights and public health.
The report could well have been written based on slogans from WHO, Gavi and CEPI (whom the Lancet recommends should receive more money), from Pharma companies (on whose support Lancet is heavily directly or indirectly reliant) and from the World Economic Forum (who seem everywhere these days).
Some will have hoped for careful and considered thought, wide consultation, and a strong evidence base. It seems the corporate world may no longer have time for such indulgence. This is, in the end, a rich person’s club, seeking increased taxpayer funding for their favorite project. They are doing this in the name of public health.
It was reasonable to have hoped for better. What would Thomas Wakley have thought?
David Bell, Senior Scholar at Brownstone Institute, is a public health physician and biotech consultant in global health. He is the former Program Head for malaria and febrile diseases at the Foundation for Innovative New Diagnostics (FIND) in Geneva, Switzerland.
September 12, 2022, President Biden signed the “Executive Order on Advancing Biotechnology and Biomanufacturing Innovation for a Sustainable, Safe and Secure American Bioeconomy.”1
Specified in that order is the development of genetic engineering technologies and techniques “to be able to write circuitry for cells and predictably program biology in the same way in which we write software and program computers,” as well as genetic technologies to “unlock the power of biological data” using “computing tools and artificial intelligence.”
Additionally, “obstacles for commercialization” will be reduced “so that innovative technologies and products can reach markets faster.” What we have here is, in a nutshell, the creation of a fast-tracked mRNA pipeline.
When, in June 2022, the U.S. Food and Drug Administration quietly implemented a “Future Framework” scheme2 to deliver reformulated COVID boosters without additional testing, I predicted that this “no testing required” formula would spread beyond COVID shots. And, according to this executive order, that’s exactly what’s about to happen.
In early September 2022, the FDA also put out medically false and misleading COVID booster campaign messages that prove we’ve officially entered the era of transhumanism:
“It’s time to install that update! #UpdateYourAntibodies with a new #COVID19 booster.”3 “Don’t be shocked! You can now #RechargeYourImmunity with an updated #COVID19 booster.”4
Is This the Death Knell to Allopathic Medicine?
Historically, gene therapies have had to jump through extra hoops, which is why so few exist on the market. As of 2021, there were 20 gene therapies commercially available.5 The world’s first gene therapy trial didn’t begin until 1990, so this is still a very new field.
The entire gene therapy field actually collapsed overnight in 1999, when a teenage trial participant died from side effects. An FDA investigation concluded research had moved too fast and that safety “had not been put first.”6 Progress, thanks to increased caution, slowed from there on.
Such caution is now being thrown to the wind, and it’s not difficult to predict there will be disastrous ramifications. Millions will die from poorly tested gene therapies and, eventually, medical research and allopathic medicine will both cease to exist, as survivors vow to have nothing to do with that murderous cabal ever again.
The only way they might be able to keep going is if they are in control of people’s brain function and/or able to force drugs under threat of death, or worse — neither of which is impossible at this point, shockingly enough. In the meantime, we’re looking at a cornucopia of mRNA shots coming our way.
mRNA Flu Shots Are in the Works
Not surprisingly, mRNA flu shots are in the works.7 While we probably won’t see mRNA flu shots during the 2022/2023 winter season, there’s every reason to expect they’ll be rolled out next year.
September 14, 2022, Pfizer initiated a Phase 3 study, which will test a quadrivalent mRNA-based flu shot on 25,000 American adults.8 Pfizer is also exploring mRNA technology that uses self-amplifying RNA (saRNA), for potential use in the future.9
Moderna began its Phase 3 mRNA flu jab trial in early June 2022.10 It’s also working on mRNA shots for respiratory syncytial virus (RSV) and cytomegalovirus (CMV), which is in the herpes family, as well as a SARS-CoV-2-influenza combination shot. Ultimately, Moderna wants to create an annual mRNA shot that covers all of the top 10 viruses that result in hospitalizations each year.11
Its current flu jab candidate, mRNA-1010, encodes for the hemagglutinin (HA) glycoproteins of four different influenza strains, including influenza A/H1N1, A/H3N2, influenza B/Yamagata and B/Victoria. According to Moderna:12
“HA is a major influenza surface glycoprotein that is considered an important target to generate broad protection against influenza and is the primary target of currently available influenza vaccines.”
Over the past three years, I’ve written several articles exploring the transhumanist agenda, which all these mRNA shots and genetic technologies are part and parcel of. Basically, the goal of the transhumanist movement is to transcend biology through technology, and to meld human biology with technology and artificial intelligence.
In September 2020, I posted a video with Dr. Carrie Madej (above), in which she suggested we were standing at the crossroads of transhumanism, thanks to the fast approaching release of mRNA COVID-19 shots.
Since these shots are designed to manipulate your biology, they have the potential to also alter the biology of the entire human race. Nearly two years later, we still don’t know the extent to which they might be doing that, yet more fast-tracked and untested gene therapies are on the way.
One reason why it’s important to know for certain whether synthetic RNA ends up creating permanent changes in the genome is because synthetic genes are patented. If they cause permanent changes, humans will contain patented genes, and that brings up very serious questions, seeing how patents have owners, and owners have patent rights.
US Defense Department Aims to Create Human Cyborgs
The hydrogel used to preserve the mRNA can also contain nanobots to create a bioelectric interface capable of connecting to a smartphone or other interface. Novel technologies that measure biological data, such as blood sugar, are based on this. Such technologies will, of course, have immediate ramifications for our privacy.
Who will collect and have access to all this data? Who will be responsible for protecting it? How will it be used? Also, if your cellphone can receive information from your body, what information can your body receive from it, or other sources? Could transmissions affect your mood? Your behavior? Your physical function? Your thoughts or memories?
So far, it doesn’t appear as though the COVID shots have these kinds of capabilities built in, but we do know for a fact that militaries around the world are exploring and working toward such capabilities. In fact, it’s an arms race in its own right.
In his September 14, 2022, Substack article,13 “Human Cyborgs Are Just the Beginning,” Dr. Robert Malone reviewed several of those plans. Certain report titles alone tell the story, such as the U.S. Department of Defense (DOD) Biotechnologies for Health and Human Performance Council’s report,14 “Cyborg Soldier 2050: Human/Machine Fusion and the Implications for the Future of the DOD.” It doesn’t leave a whole lot to the imagination, does it? According to the assessment abstract:
“The primary objective of this effort was to forecast and evaluate the military implications of machines that are physically integrated with the human body to augment and enhance human performance over the next 30 years.
This report summarizes this assessment and findings; identifies four potential military-use cases for new technologies in this area; and assesses their impact upon the DOD organizational structure, warfighter doctrine and tactics, and interoperability with U.S. allies and civil society.”
Human augmentation technologies deemed technically feasible by 2050 at the latest include ocular enhancements to improve sight and situational awareness, optogenetic bodysuit to restore or improve muscular strength and control, auditory enhancements, and neural enhancement of the brain for two-way data transfers and brain-to-brain communication.
Changing What It Means To Be Human
In “The Plan to Turn You Into a Genetically Edited Cyborg,” I covered another shockingly dystopian report by the U.K. Ministry of Defense and the German Bundeswehr Office for Defense Planning, published in May 2021.
That report, “Human Augmentation — The Dawn of a New Paradigm, a Strategic Implications Project,”15 reviews the scientific goals of the U.K. and German defense ministries, and they basically mirror that of the U.S. DOD. On page 12 of the report, the concept of the human body as a platform is described, and how various parts of the human platform can be augmented. For example:
Physical performance such as strength, dexterity, speed and endurance can be enhanced, as well as physical senses. One example given is gene editing for enhanced sight
Psychological performance such as cognition, emotion and motivation can be influenced to activate and direct desired behavior. Examples of cognitive augmentation include improving memory, attention, alertness, creativity, understanding, decision-making, intelligence and vigilance
Social performance — “The ability to perceive oneself as part of a group and the readiness to act as part of the team” — can be influenced. Communication skills, collaboration and trust are also included here
They list several different ways to influence the physical, psychological and social performance of the “human platform,” including genetics (germ line and somatic modification), synthetic biology, invasive (internal) and noninvasive (external) brain interfaces, passive and powered exoskeletons, drugs and nano technology, neurostimulation, augmented reality technologies such as external holograms or glasses with built-in artificial intelligence, and sensory augmentation technologies such as external sensors or implants.
As noted in this report, “Human augmentation has the potential to … change the meaning of what it means to be a human.” This is precisely what Klaus Schwab, founder and executive chairman of the World Economic Forum (WEF), has stated is the goal of The Fourth Industrial Revolution.16
WEF has been at the center of global affairs for more than 40 years, and if you take the time to dive into WEF’s Fourth Industrial Revolution material, you realize that it’s all about transhumanism. It’s about the merger of man and machine.
This is a dystopian future that WEF and its global allies are actively trying to implement, whether humanity at large agrees with it or not. Importantly, the “Human Augmentation” report readily admits that human augmentation can “directly enhance behavior.”
And, if you think these reports are just brain fodder for geeks in uniforms, think again. The U.K. Defense and Security Accelerator (DASA) is currently, right now, accepting proposals for human augmentation technologies such as those listed above.17 Grants of 70,000 euros ($74,000), will be given to proposals that can provide proof of concept.
We’re Already Being Programmed to Accept Transhumanism
Both the DOD’s “Cyborg Soldier” report and the British/German “Human Augmentation” reports discuss the fact that human augmentation will inevitably widen already existing disparities, inequalities and inequities, and therefore, “efforts should be undertaken to reverse negative cultural narratives of enhancement technologies.”18
In other words, don’t let people come to the conclusion that human cyborgs are a bad idea, because at worst that might prevent their development, and at best, it’ll pitch regular people against the augmented elite, making their efforts to rule the plebs more difficult.
As noted by Malone, “Once again, we are being played before we even know what the playing field looks like.”19
Disturbingly, considering how nontransparent governments have been so far, it’s not inconceivable that technologies capable of influencing thoughts and behaviors would be used on populations without informing anyone, which makes the list of potential risks one takes with each new mRNA injection even longer than it already is.
But we don’t need to be genetically reengineered or have nanobots introduced into our brains to be at risk of outside manipulation. That’s already happening through noninvasive means.
Control Capabilities Go Far Beyond Orwell’s ‘1984’ Vision
In a November 2019 interview with CNN,20 history professor Yuval Noah Harari, a Klaus Schwab disciple, stated that humans are already “hackable,” meaning the technology exists by which a company or government can know you better than you know yourself, and this knowledge can be used for both good and ill.
According to Harari, the available capabilities already go far beyond Orwell’s “1984” authoritarian vision, and it’s only going to become more powerful from here.
He predicted that algorithms will increasingly be used to make decisions that historically have been made by humans, either yourself or someone else, including whether or not you’ll be hired for a particular job, whether you’ll be granted a loan, what scholastic curriculum you will follow and even whom you will marry.
To learn more about the larger issues of transhumanism and the race to merge man with machine and artificial intelligence, check out the Truthstream Media video below.
For example, there are even ongoing attempts to upload the human mind into the cloud, ultimately creating a form of “digital hive mind” where everyone communicates via “Wi-Fi telepathy.” This, despite the fact we still do not fully understand what “the mind” actually is, or where it’s located.
Final Thoughts
I don’t know what it will take to prevent the dystopian post-human world envisioned by Schwab and his technocratic minions, but I suspect education would be a cornerstone of such an endeavor. In order for there to be a resistance, enough people need to be aware of what the plan is, and where we’re actually being led with all these novel therapies and inventions.
In the shorter term, it’s crucial to realize that the fast-tracking of “genetic engineering technologies and techniques to be able to write circuitry for cells and predictably program biology in the same way in which we write software and program computers” means they’re going to cut corners. Loads of them.
Testing is basically going to be done on the population at large, just as they’ve done with the COVID jabs. The results of such experimentation are relatively predictable. People will be seriously injured and many will die. So, think long and hard before you agree to take any of these forthcoming gene therapies.
NEW YORK — For nearly two decades, one of the most overlooked and little known arrests made in the aftermath of the September 11 attacks was that of the so-called “High Fivers,” or the “Dancing Israelis.” However, new information released by the FBI on May 7 has brought fresh scrutiny to the possibility that the “Dancing Israelis,” at least two of whom were known Mossad operatives, had prior knowledge of the attacks on the World Trade Center. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.









 Aletho News

