A worldwide call for data transparency: Show us the data!
By Steve Kirsch | February 3, 2023
We could end the debate on COVID vaccine safety instantly. All we need is the death-vax record data. But today, that data is being concealed by the health authorities in every jurisdiction. Here’s why.
A simple database of death-vax records should be made publicly available by the CDC and other health authorities worldwide.
The death-vax records can be analyzed in seconds using a variety of totally objective methods to show whether the COVID vaccines have increased or decreased all-cause mortality in each age range.
No medical records, cause of death, etc. are required or needed. Just the age, date of death, and dates of vaccination are all that is required for each death since the start of the COVID vaccination program.
The death-vax data has been collected, but it has never been made publicly available anywhere in the world. There is no PII or HIPAA violation by disclosing the records.
There is absolutely no excuse for this data not to be made PUBLICLY available now.
Because kids are most at risk, universities in particular should be demanding data transparency of the death-vax records.
It is immoral and unethical for universities to mandate COVID vaccines if the health authorities refuse to show us the death-vax database records that would justify their use.
The death-vax data consists of one record for each death since Dec 14, 2020 to the present with these columns:
- Age
- Date of death
- Date of each COVID vaccine administered (blank if unvaccinated)
That’s it.
Does that sound like too much to ask for?
Optional:
- Manufacturer of each dose (blank if unvaccinated)
- State (e.g., California)
In the US, the death data is already collected by the CDC for the entire country. The immunization data is available from each state.
The CDC could quickly collect this information, do the database join, remove the PII fields, and make this database publicly available.
This would reveal to the entire world whether the vaccines are safe or not. Instantly. No more debates.
No medical records are required. No judgment is required. The analysis is all based on mathematics and the law of large numbers. If the vaccines are saving lives, we’ll know it. If the vaccines are killing people, we’ll know it.
EVERYONE should be demanding to see the death-vax record-level data. It can be easily compiled. It is dispositive. We’d know instantly whether the vaccines are safe or not. No more arguments. No more debates. No more censorship. One and done.
Yet, nobody in the mainstream infectious disease or epidemiology community seems to care about seeing this data. Nobody is calling for it. Why is that? Are they afraid of being proven they are wrong?
If the vaccine is so safe, they should be shouting for the release of this data from the rooftops because nearly 80% of the public is no longer drinking the Kool-Aid:
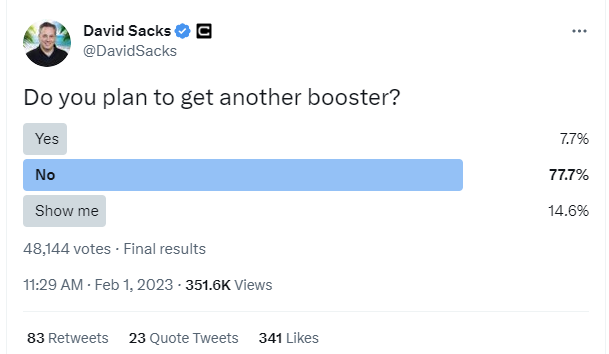
But the authorities are remaining silent and keeping the data under wraps. That can only mean one thing: the data is horrible and they know it. That’s why they are hiding it from public view.
That’s not just a hunch. I did my own data collection and analysis. Even after adjusting for the bias of the reporters (by restricting the analysis to just parents and grandparents of the reporter), the signal of harm was huge.
Science used to be about data and what the data shows. Sadly, today, science is about what the CDC says, even if there is no data in support of the recommendation whatsoever.
The most stunning example of this is the “six foot rule.” Did you know that it was entirely fabricated out of thin air? From Presidential Takedown page 49:

What is even more stunning is that the CDC has never admitted this publicly. This is evidence that they are a corrupt organization and the corruption goes to the very top of the organization.
We now have over two years worth of death and vaccination data for people who died after getting a COVID shot, yet nobody wants to see the record level data tied to the vaccination dates?!?!
Let me be perfectly clear:
This is an abject failure of the entire medical community for not demanding to see this data.
In the US, hundreds of millions of people participated in a massive clinical trial and have data to share with people. At least 500,000 of the participants paid the ultimate price: they sacrificed their lives to send a message to America about the vaccines. It is extremely disrespectful to these people to ignore their death data and not share it with the public. Why are we not allowing these people to share their data?
Do you think if we could ask those people right before they died, “Do you want to let others know what killed you?” Do you think they would all say, “No! Don’t let anyone know. Please keep it a secret!”?
John Beaudoin and I have been calling for the death data to be set free and made public. We have been ignored.
Why aren’t any of these organizations calling for data transparency here so we can learn the truth?
- The mainstream medical community
- Heads of state throughout the world
- The CDC
- The FDA
- The White House
- Congress
- The mainstream media
- Public health authorities
- Any doctor or nurse who recommends the jab to patients
- Universities who mandate the vaccines for students, staff, or faculty
- Any organization that supports COVID vaccines for their members, employees, or visitors
The data exists in VSD as well. But the CDC won’t allow anyone to see it.
The data exists in every state health department. But you can’t FOIA it because it requires a join to avoid PII problems and FOIA requests are not allowed if they generate effort like that. So FOIA requests won’t work.
It’s time for everyone to demand that our health authorities “Show us the data!”
We should all refuse to comply until they produce it.
Who could ever forget the classic “Show me the money!” scene from the movie Jerry Maguire?
In the same way Tom Cruise said passionately “Show me the money,” everyone all over the world should be equally passionate with their doctors and healthcare authorities and demand: “Show me the DATA” before we agree to comply with their requests/demands regarding vaccination.
Check out this video from True North entitled “Show us the data and evidence” that described the civil disobedience in Canada:
Business owners and local politicians are pushing back against the government’s lockdown measures. Their ask of the government is simple – if you’re going to shut us down, show us the data and evidence.
The data that we have shows that the biggest harm is being done to kids.
Therefore, the biggest urgency is to put pressure on any school or university that recommends or requires the COVID vaccines to drop it immediately
Please ask the university president or head of school at any school your child attends to contact the CDC and let them know that if the CDC doesn’t make the death-vax record level data publicly available with the next 30 days, that the school will suspend their COVID vaccination policies until such time as this data is produced and scientists can analyze it. That is the only ethical thing to do.
You can refer to my article in your email.
The public health authorities have been voluntarily keeping the data secret for two years now. That data would end the debate. We should not let them continue to get away with it.
Is the FDA “doubling down” on a failed strategy?
By Maryanne Demasi, PhD | January 30, 2023
Last Thursday, the FDA convened its Vaccines and Related Biological Products Advisory Committee (VRBPAC) to discuss the future of covid vaccines.
The panel voted 21 to 0 in favour of moving towards a more simplified vaccine schedule – an annual shot which would be updated as new variants emerge – much like the annual flu shot.
Despite the unanimous vote, VRBPAC members did raise concerns about knowledge gaps and questioned the need to boost everyone, as well as the futility of chasing rapidly mutating viruses.
But it all fizzled out quickly, and the FDA promised to reconvene in May or June to discuss the data further.
That said, I had some interesting observations of my own.
We are three years into the pandemic, and the FDA has still not established a “correlate of protection” for the vaccines.
Eight covid-19 vaccine emergency use authorisations (EUAs)* have been granted, based on their ability to induce “neutralising antibodies,” a surrogate marker of protection.
The idea is, the more antibodies you produce, the better you are protected.
Except, neutralising antibodies do not predict the degree to which someone is protected from infection… and the FDA knows it.
Ofer Levy, VRBPAC member and Professor of Paediatrics at Boston Children’s Hospital first voiced his concern at the April 6, 2022 meeting.
“We’re at risk of doubling down on a failed strategy,” said Levy as the committee discussed a framework for offering annual covid shots for Americans.
“Where is the federal effort to coordinate all of that to develop a public repository around the correlate of protection, and to make sure we have the best available data for the immunogenicity when we make those decisions?”
The FDA’s top vaccine official, Peter Marks, agreed with Levy.
“There is not a clear, perfect, immune correlate of protection” admitted Marks, “We’re using poor man’s immune correlates of protection here — or poor person’s immune correlates of protection with antibody levels.”
In Dec 2022, Peter Marks reiterated these concerns in an article published in JAMA. He and his co-authors wrote:
“Therefore, unless correlates of protection that are strongly associated with duration of protection against COVID-19 can be identified, it is likely that rather than relying on immunobridging to infer vaccine effectiveness, large randomized clinical trials similar to the initial trials of the currently authorized or licensed vaccines for COVID-19 will be required to ascertain the effectiveness of these new vaccines.”
But fast forward to this latest meeting, and it becomes clear that we’re all still in the dark.
We have no correlate of protection, the FDA is relying heavily on real world studies (confounded data) and the agency still has not demanded any randomised controlled trials to show the bivalent booster can reduce severe disease or hospitalisations.
It’s no wonder doctors are coming out in droves, refusing to have any more covid shots until the FDA demands better studies.
“I don’t think we can say with credibility what the objective benefits are for someone like me to take an additional dose, nor what the rate of any rare but important side effects would be,” tweeted Todd Lee, a physician certified in Infectious Diseases and General Internal Medicine in Quebec, Canada.
Similarly, Vinay Prasad, haematologist-oncologist at the University of California San Francisco vowed not to take any more shots until there were data from randomised controlled trials.
“I took at least 1 dose against my will. It was unethical and scientifically bankrupt. I am not done with that error. No more,” he tweeted.
As part of its post-marketing requirements, Pfizer is legally obligated to conduct a study involving people aged 16 to 30 to look at rates of subclinical myocarditis (i.e. underlying damage to the heart muscle without causing symptoms).
The final report was due 31 Dec 2022, but that deadline lapsed, and the FDA said nothing. There was no mention of the study, neither in the briefing notes ahead of the VRBPAC meeting, or during the meeting.
I asked the FDA directly for access to Pfizer’s study, but the agency said in an email, “You may submit a FOIA request for this information, or if you would like it more quickly, you can reach out to the manufacturer directly.”
Pfizer did not respond to my request, and the FDA refused to confirm whether it had even received Pfizer’s study, before abruptly ending our communication.
Jessica Adams, an expert in drug regulatory affairs pointed out on twitter that the FDA had quietly changed the due date for the study from 31 Dec 2022 to 30 June 2023.

So, now as it stands, millions of young people will receive boosters, mandated or not, without knowing if the vaccine is causing subclinical myocarditis.
FDA still working from home
Finally, the meeting was again held online because the majority of FDA employees are still working from home.
Since all federal employees have been mandated to take the covid-19 vaccine to “protect themselves and those around them,” why aren’t they conducting face-to-face meetings?
“FDA leaders are in a bubble. How much longer will the FDA (18,000-employees) continue to work remotely? It’s mid-day on a weekday and the parking lot is essentially empty” tweeted Marty Makary, surgeon and public policy researcher at Johns Hopkins University.
“The FDA was telling the rest of America to get vaccinated, mask up and go back to work, but the FDA mysteriously did not follow its own advice,” said David Gortler, drug safety expert and former senior advisor to the FDA commissioner.
Well, it’s as though the FDA heard the cries.
Today, the FDA announced that “staff will be transitioning to a hybrid workplace.” This transition will enable face-to-face formal meetings between FDA and industry to resume within weeks.
*FDA issued eight EUAs based on neutralising antibodies (immunobridging studies) – an unproven correlate of protection.
- Pfizer EUA – 6 months to 4 year olds
- Pfizer EUA – 5 to 11 year olds
- Pfizer EUA – 12 to 15 year olds
- Pfizer EUA booster #1
- Pfizer EUA booster #2
- Moderna EUA – 6 months to 17 year olds
- Moderna EUA – booster #1
- Moderna EUA – booster #2
Vitamin D Cuts COVID-19 Risk of Death in Half, New Study Finds. So Why Isn’t it Recommended?

BY WILL JONES | THE DAILY SCEPTIC | FEBRUARY 3, 2023
Vitamin D cuts the risk of death from COVID-19 by 51% and the risk of ICU admission by 72%, a meta-analysis of randomised controlled trials has found. The new study, published in Pharmaceuticals, is titled “Protective Effect of Vitamin D Supplementation on COVID-19-Related Intensive Care Hospitalisation and Mortality: Definitive Evidence from Meta-Analysis and Trial Sequential Analysis”. Here’s the abstract, summarising the study’s method and results.
Background: The COVID-19 pandemic represents one of the world’s most important challenges for global public healthcare. Various studies have found an association between severe vitamin D deficiency and COVID-19-related outcomes. Vitamin D plays a crucial role in immune function and inflammation. Recent data have suggested a protective role of vitamin D in COVID-19-related health outcomes. The purpose of this meta-analysis and trial sequential analysis (TSA) was to better explain the strength of the association between the protective role of vitamin D supplementation and the risk of mortality and admission to intensive care units (ICUs) in patients with COVID-19.
Methods: We searched four databases on September 20th 2022. Two reviewers screened the randomised clinical trials (RCTs) and assessed the risk of bias, independently and in duplicate. The pre-specified outcomes of interest were mortality and ICU admission.
Results: We identified 78 bibliographic citations. After the reviewers’ screening, only five RCTs were found to be suitable for our analysis. We performed meta-analyses and then TSAs. Vitamin D administration results in a decreased risk of death and ICU admission (standardised mean difference (95% CI): 0.49 (0.34–0.72) and 0.28 (0.20–0.39), respectively). The TSA of the protective role of vitamin D and ICU admission showed that, since the pooling of the studies reached a definite sample size, the positive association is conclusive. The TSA of the protective role of vitamin D in mortality risk showed that the z-curve was inside the alpha boundaries, indicating that the positive results need further studies.
Discussion: The results of the meta-analyses and respective TSAs suggest a definitive association between the protective role of vitamin D and ICU hospitalisation.
Despite these highly positive results, the latest official guidelines from NICE still state that vitamin D is not recommended for the prevention of COVID-19. (NICE also doesn’t recommend the use of ivermectin or budesonide.) Yet remdesivir is recommended despite the WHO finding little or no effect. Will NICE now update its guidelines? I wouldn’t count on it.
Dr. John Campbell discusses the new study in a recent video, arguing the evidence on vitamin D is now conclusive and wondering why adequate vitamin D supplementation is not being officially promoted in the U.K. The fact that the MHRA is 86% industry-funded may have something to do with it, he suggests.
Returning to COVID19

By Dr. Malcolm Kendrick | January 31, 2023
With the resignation of Jacinda Ardern, my thoughts were dragged back to Covid once more. Jacinda, as Prime Minster of New Zealand was the ultimate lockdown enforcer. She was feted round the world for her iron will, but I was not a fan, to put it mildly. Whenever I heard her speak, it brought to mind one of my most favourite quotes:
‘Of all tyrannies, a tyranny sincerely exercised for the good of its victims may be the most oppressive. It would be better to live under robber barons than under omnipotent moral busybodies. The robber baron’s cruelty may sometimes sleep, his cupidity may at some point be satiated; but those who torment us for our own good will torment us without end for they do so with the approval of their own conscience.’ C.S. Lewis
At one point she actually said the following:
“We will continue to be your single source of truth” “Unless you hear it from us, it is not the truth.’
If I ruled the world, anyone who said, that, or anything remotely like that, would be taken as far as possible from any position of power, never to be allowed anywhere near it again. Ever.
Yet, there are still many who believe her to have been a great and caring leader. She certainly hugged a lot of people with that well rehearsed pained/caring expression on her face.
Enough of that particular woman. But it got me thinking about lockdowns again and the whole worldwide madness of Covid. This was a time of such blundering idiocy that I find increasingly difficult to believe it ever happened. A bad dream.
‘The sky is falling, the sky is falling…’ Cue, everyone running about in panic. People, allegedly, dropping dead on the streets. Mortuaries, allegedly, overflowing. Freezer lorries, allegedly, stacked with dead bodies. Bring out your dead!
I worked with doctors who strode around the wards in positive pressure protective gear. There were GPs who simply refused to visit elderly residents in nursing homes. On my patch this was all GPs and all nursing homes. Meanwhile I happily visited away with a mask stuck to the top of my head.
During the Covid pandemic I travelled far past angry, to reach a point of utter weariness. Instead of becoming outraged by the latest rubbish that was being pronounced, I very nearly washed my hands of it. However, after learning of Jacinda’s resignation I roused myself to have another look at what actually did happen. Or to be more specific, what was the impact of Covid on overall mortality. The only outcome that really matters.
Rid your mind of the numbers claimed to have died of Covid. The, never to be clarified distinction between those who died ‘of’ or ‘with’ Covid. Or those who read an article on Covid and then, overwhelmed with fear, stepped out in front of a bus. Thus, becoming a Covid related… associated, something, anything to do with Covid, death.
Over time the Covid figures became so ridiculous and unreliable as to become meaningless. I should know, I wrote some of the death certificates myself. Let me think… ‘She died of COVID, she died of COVID not. Eeny, meeny, miney mo…’
I am not saying that Covid did not kill a large number of people. But the fact that deaths from influenza disappeared completely for two years tells me all I need to know. ‘Roll up, roll up, Ladies and Gentlemen, to see the amazing lady influenza disappear before your very eyes.’ An astonishing trick, all the way from La La Land. ‘You expect me to believe that? Ho, ho, ho, very funny…. Oh, sorry, you actually do.’
Anyway, to clear my internal database of horribly unreliable figures, I went back to look at my favourite graphs on EuroMOMO. This website looks at overall mortality, and only overall mortality. Their data comes from countries who do know how to record deaths, honestly. Unlike some others, who shall be nameless … China.
However, the main reason to focus on EuroMOMO is that overall mortality is something you cannot fake. About the only thing you can do to manipulate the figures is hold back data for a month or two – which has been done, but not to any great degree. So, without further ado, let us move onto EuroMOMO. Below is a recent graph. I have deliberately removed most of the information you need to know what it is showing. I wanted people to avoid jumping to conclusions … that they might then find it difficult row back from.

I found myself examining this graph idly and thought. Imagine if you had no idea what you were looking at here. What would you think? It’s a squiggly line, yes. Very good, gold star. What else?
To give you a bit more detail. This is a graph of overall mortality, across a large number of European countries. All of those who provide data to the EuroMOMO database anyway. Norway, the ultimate European lockdown champion, has mysteriously disappeared from the database. Maybe they shall return …. I have begun to see everything as a conspiracy nowadays.
The graph itself begins in January 2017 and finishes in January 2023. As you can see (if not terribly clearly) there are two wavy dotted lines. These lines rise up in the winter, and then fall back down in the summer. Something seen every year. This is because, every year, more people die in the winter than in the summer.
Everyone thinks they know the reason for this winter summer effect, but I am not so sure they do. But that is an enormously complicated topic for another time.
The lower, dotted lines represent the ‘average’ mortality you would expect to see [with upper and lower ‘normal’ limits] year on year. Above those wavy dotted lines sits a solid spikey line. This represents the actual number of deaths that occurred. Not just from Covid, but from everything.
This does raise an immediate question. If we keep seeing more deaths than we would expect in the winter, year on year, then the ‘average’ number of deaths should rise? Thus, the wavy dotted lines ought to be going up and up, in the winter. But they don’t.
I am not entirely sure why this is not the case. But it is a statistical question of such mind-boggling complexity that I am, frankly, unable to answer it. I have looked into it, but I was scared off by the sheer scale and difficulty of the mathematics involved. Too many equations for my poor wee brain.
Anyway, this graph starts in the winter of 2017 and ends about now. The vertical lines are drawn at midnight on Dec 31st each year. Which means that we have almost exactly six years of data. Excellent data, not manipulated in any way. I say this because, whilst the diagnosis of ‘Covid death’ may be disputed, the diagnosis of death cannot.
What stands out? Well, there was a very sharp peak of deaths in early 2020. This, as you have probably worked out, was when Covid first hit. I find it fascinating that it was so transient. It came, it went… gone. For a bit anyway.

Was the precipitous fall due to strict lockdowns? Some will doubtless argue this. However, we all locked down again in autumn 2020 and the death rate went up, and stayed up, for about six months. Until, that is, January came along, and it all settled down again. Which follows pretty much the pattern of 2017, 2108 and 2019. And the pattern of all pandemics. They come, and they go. Some a little earlier, some a little later.
What else do you see – now that we are all pretty much fully vaccinated? I think another thing that stands out is the sudden and sharp rise in mortality in November 2022. Which is virtually identical to the spike in 2020. Strange?
However, to my mind, the thing that shouts most loudly about this graph is that the years of Covid pandemic panic really do not look that much different from the previous three years. Half close your eyes, and there is almost nothing to see. The Covid peaks were a little higher, and a little longer – maybe.
If you knew nothing about the Covid pandemic I don’t think you would exclaim. ‘My God, look at these vast waves of death in 2020, 2021. What amazing, never seen before thing, happened here?’ Yes, first spike of early 2020 was certainly sharp, and unusual, but it was short. And very little different to the spike at the end of 2022. As for the rest?
Now, I would like to turn your attention to Germany. The most populous country in Europe. Here it is even more clear that the years of the Covid pandemic are not remotely unusual. If I had removed the calendar years off this graph, you would be hard pressed to spot the Covid pandemic. In truth, you would be more than hard pressed. You couldn’t.

The 2018 influenza spike was equally dramatic to Covid peak of 2021, if not more so. [You may have noticed that there was no peak in 2020] In addition, at the end of 2022, we have the highest peak of all. Future historians might well look at this graph and ask. ‘Tell me, why did the world go mad in 2020, and remain mad through 2021? Why did everyone lockdown in March 2020, and then do nothing whatsoever in December 2022?’
It almost goes without saying that, had we locked down again in November 2022, it would have been claimed that lockdown saved us all. Look at how quickly it came, then went. Well, they could have claimed it. But we didn’t lock down again, did we? In direct contrast to Germany. What of the people living in Luxembourg?

Luxembourg is surrounded by Belgium France and Germany. People move freely from one to the other, always have done, and still do. The ‘deadly’ Covid pandemic raged all around them. Here, absolutely nothing happened. Mind you, they also seem to have been unaffected by influenza.
Whilst the Germans were dying in large numbers in 2018, the Luxembourgians carried on serenely, not an extra death to be seen. Why? Discuss. [It seems that most/all countries unaffected by Covid, were also unaffected by earlier flu epidemics].
I know some of you may be thinking that Germany is much bigger than Luxembourg so … so what? If you are going to see an effect on mortality, you are more likely to see it happen, more dramatically, and rapidly, in a country with fewer people.
I should explain that the figures on the left axis, on the German and Luxembourg graphs (unlike the first one), do not represent total deaths, they are the ‘Z score’. That is, the deviation from the mean.
The upper dotted line represents a Z score of five. That means, five standard deviations above the mean. It has been decreed that if you hit more than five standard deviations above the mean, for any length of time, this is a signal that ‘something bad’ is happening. The alarm starts goes off, and epidemiologists run around bumping into each other. ‘The sky is falling… etc.’
If you use the Z score it makes no difference how large the population is. It has been specifically designed to make it possible to compare changes in overall mortality, in populations of very different sizes. I feel the need here to make it clear that Luxembourg is not that small. It has more than twice the population of Iceland, for example.
Enough of the maths already.
So, deep breath, and trying to bring all these random thoughts together. What does EuroMOMO tell us? It tells us that Covid was a bit worse than a bad flu season, with 2018 being a good reference point. [There have been far worse flu epidemics than 2018, and I am not talking about 1918/19].
What EuroMOMO makes most clear, at least to me, is that Covid was not, repeat not, a pandemic of unique power, and destructiveness. It could have never remotely justified the drastic actions that were taken to combat it.
Belatedly, this is becoming recognised, as has the damage associated with lockdowns. Here is the abstract of an article from 2022. A bit dry, but worth a read. ‘Are Lockdowns Effective in Managing Pandemics?’
‘The present coronavirus crisis caused a major worldwide disruption which has not been experienced for decades. The lockdown-based crisis management was implemented by nearly all the countries, and studies confirming lockdown effectiveness can be found alongside the studies questioning it.
In this work, we performed a narrative review of the works studying the above effectiveness, as well as the historic experience of previous pandemics and risk-benefit analysis based on the connection of health and wealth. Our aim was to learn lessons and analyze ways to improve the management of similar events in the future.
The comparative analysis of different countries showed that the assumption of lockdowns’ effectiveness cannot be supported by evidence—neither regarding the present COVID-19 pandemic, nor regarding the 1918–1920 Spanish Flu and other less-severe pandemics in the past.
The price tag of lockdowns in terms of public health is high: by using the known connection between health and wealth, we estimate that lockdowns may claim 20 times more life years than they save. It is suggested therefore that a thorough cost-benefit analysis should be performed before imposing any lockdown for either COVID-19 or any future pandemic.’ 1
In the face of such evidence, the argument for lockdown seems to be transforming into a somewhat pathetic whinge. ‘We didn’t know. It’s all very well people saying we shouldn’t have locked down now. We didn’t hear you saying it at the time. We were just following The Science, don’t blame us. Better safe than sorry. Don’t blame us … I think you’re being very nasty to us.’
This, of course, is nonsense. There were plenty of scientists arguing against lockdown at the time. However, they were all ruthlessly censored, attacked, and silenced. Experts such as Prof. John Ioannidis, Prof. Karol Sikora, Prof. Sunetra Gupta, Prof. Carl Heneghan. These last two UK professors argued very strenuously against lockdowns. They were ignored, then vilified. Here from an article written in January 2021:
‘… Sunetra Gupta. She’s been getting flak from the mob for months but it reached a crescendo yesterday when she was on the Today programme. Why is the BBC giving space to a nutter, people asked? She isn’t a nutter, of course. She’s an infectious disease epidemiologist at Oxford University. But she bristles against the COVID consensus and that makes her a bad person, virtually a witch, in the eyes of the zealous protectors of COVID orthodoxy. Professor Gupta has written about the barrage of abuse she receives via email. ‘Evil’, they call her.’
‘… her chief crime, judging from the hysterical commentary about her, is that she is critical of harsh lockdowns. She is a founder of the Great Barrington Declaration, which proposes that instead of locking down the whole of society we should shield the elderly and the vulnerable while allowing other people to carry on pretty much as normal. It is this perfectly legitimate discussion of a social and political question — the question of lockdown — that has earned Gupta the most ire.’ 2
I would like to point out that I was arguing against lockdown, right from the very beginning. Yes, I do enjoy saying, ‘I told you so’ from time to time. It is one of the few satisfactions I get in life nowadays. Here is a section from a blog I wrote in March 2020. Once again, right from the start:
‘… However, there is also a health downside associated with our current approach. Many people are also going to suffer and die, because of the actions we are currently taking. On the BBC, a man with cancer was being interviewed. Due to the shutdown, his operation is being put back by several months – at least. Others with cancer will not be getting treatment. The level of worry and anxiety will be massive.
Hip replacements are also being postponed and other, hugely beneficial interventions are not being done. Those with heart disease and diabetes will not be treated. Elderly people, with no support, may simply die of starvation in their own homes. Jobs will be lost, companies are going bust, suicides will go up. Psychosocial stress will be immense.
In my role, working in Out of Hours, we are being asked to watch out for abuse in the home. Because we know that children will now be more at risk, trapped in their houses. Also, partners will suffer greater physical abuse, stuck in the home, unable to get out. Not much fun.
Which means that we are certainly not looking at a zero-sum game here, where every case of COVID prevented, or treated, is one less death. There is a health cost.
There is also the impact of economic damage, which can be immense. I studied what happened in Russia, following the breakup of the Soviet Union, and the economic and social chaos that ensued. There was a massive spike in premature deaths.
In men, life expectancy fell by almost seven years, over a two to three-year period. A seven-year loss of life expectancy in seventy million men, is forty-nine million QALYs worth. It is certainly a far greater health disaster than COVID can possibly create…’ 3
And lo, the damage is coming to pass. Maybe not so many people dying of starvation as I predicted, at least not in the West. In poorer countries, however …
Another terrible thing that happened during lockdown was the vilification of anyone who dared question the official narrative. Yet almost everything they predicted has come true. Have the likes of Professor Gupta been forgiven and welcomed back into the fold? Have a wild guess on that one.
What of those who deliberately whipped up the panic and led the dreadful behavioural psychology teams. They quite deliberately frothed the population into a state of terror. What of those, whose ridiculous models kicked the whole damned thing off? The Professor Neil Fergusons of this land? Yes, you.
These people are all still comfortably ensconced, advising away. Their positions fully secure. In the UK they were mostly given knighthoods, damehoods, and other shiny gongs to impress their friends with. This, I find hard to swallow.
More worrying is that there will never be an honest review on the pandemic. Why, because so many people in positions of power would be seriously threatened by it. Which means that any such review will end up as a completely bland whitewash. ‘In general the actions taken were reasonable, and in a situation where so much was unknown, it was better to try and protect the public … blah, blah.’ Case closed.
The reality is that these lockdowns were a complete disaster. A complete disaster. The fact that we will never have a proper debate about them, means that we will learn nothing from what happened. This, in turn, means that another disaster is on the way. Those who should be listened to will be attacked, silenced and censored, again.
Those who got it all horribly wrong last time will be handed even greater powers … next time. The reason why lockdowns did not work, they will argue, is because they were not strict enough, or long enough. We need proper lockdowns next time. You have been warned. Cast your eyes over China.
I will leave you with the conclusion of the paper ‘Are lockdowns effective in managing pandemics?’
- Neither previous pandemics nor COVID19 provide clear evidence that lockdowns help to prevent death in pandemic
- Lockdowns are associated with a considerable human cost. Even if somewhat effective in preventing COVID19 death, they probably cause far more extensive (an order of magnitude or more) loss of life
- A thorough risk-benefit analysis must be performed before imposing any lockdown in future.
Which can probably be summed in in the words: Primum non nocere. First, do no harm.
The central guiding principle of medicine that was hurled out of the window in March 2020 by people who seem not to exhibit a scrap of humility, or humanity. Nor apology.
1: https://www.ncbi.nlm.nih.gov/pmc/articles/PMC9368251/
2: https://www.spectator.co.uk/article/the-censorious-war-on-lockdown-sceptics/
3: https://drmalcolmkendrick.org/2020/03/29/a-health-economic-perspective-on-covid-19/
Congressman Thomas Massie Obliterates Vaxx Mandate Against Healthcare Workers
By J.D. Rucker • The Liberty Daily • February 1, 2023
The House of Representatives is very different than it was a year ago. Back then, any notion of ending vaccine mandates was shuffled into a memory hole. Anyone who opposed them was dismissed as an anti-vaxxer. Today, we may be seeing progress. Finally.
On Tuesday, Congressman Thomas Massie gave a speech explaining the reasons the vaccine mandate against healthcare workers must end.
“I rise in support of this resolution because it would facilitate the passage of HR 497, the Freedom for Healthcare Workers Act,” he said. “What does that bill do? It ends the unscientific, illogical, immoral, unconstitutional, unethical vaccine mandate on healthcare workers that is predicated on lies.”
He listed the five predicates for the mandate that turned out to be lies:
- The vaccine prevents spread
- The vaccines don’t cause any harm
- The mandates are scientific
- Natural immunity should be ignored
- Nobody’s liable for the damage the mandate can cause
As he put it, “We’re living under medical malpractice martial law right now under the PREP Act and the EUAs.”
He concluded by dropping the ultimate truth bomb. “This is the epitome of hypocrisy. Nobody in this room was mandated to take a vaccine, and we’re voting on whether we’re going to force people who want to take care of people whether they have to take the vaccine.”
Drink it, snort it, smoke it – the vaccine juggernaut rumbles on
By Roger Watson | TCW Defending Freedom | January 28, 2023
More good news on vaccine, folks. First, you may be required to take only one Covid-19 shot per year, and if all goes well you will not even have to do that. You will be able to drink or even inhale your vaccine. No more painful injections, just a quick slurp or a snort and the job’s a good ’un. That’s you safe from the deadly virus for another year.
We could even make it fun. Why not hold Covid-19 vaccine parties? A selection of flavours in shot glasses (they don’t call them shot glasses for no reason) or add your vaccine to a vape and puff away until your immune system is primed.
I glean all this garbage from Global Health Now, the daily newsletter from the Johns Hopkins Bloomberg School of Public Health. The first story concerns how the Food and Drug Administration (FDA) in the United States is considering ‘simplifying the Covid vaccination schedule, allowing most people to get the currently available booster, regardless of how many doses they had received before that’. This means that if you are boosted up to the eyeballs or have never had one before and suddenly made the incomprehensible decision to start now, then Bob’s your uncle; roll up your sleeves.
Please note that nothing has changed; there is no new vaccine and no new threat. The FDA is just making an arbitrary decision to change the schedule. Clearly the aim is to get more people to accept the vaccination. But it is also clear that they are making this stuff up as they go along. They have no further evidence that the vaccines will work any better this way.
The information that is available to them is the abundant and accumulating evidence of vaccine harms which, incredibly, the Medicines and Healthcare products Regulatory Agency (MRHA) in the United Kingdom admits can be serious while insisting that the vaccines are safe. If truth is the first casualty of war – it certainly died early in the Covid-19 madness – logic is not far behind it. The MRHA is willing to trade off serious vaccine side effects against minimal protection from a virus which is virtually harmless to the vast majority of people. Perhaps the FDA is trying to reduce the number of boosters it says people will need in the hope that vaccine injuries will go away. Alternatively, it may be keen to accelerate the rollout before the general population wakes up to the fact that they are being conned, if they are lucky, and killed if they are not.
The potential for a drinkable/snortable/inhalable vaccine comes courtesy of US Speciality Formulations, a company which has produced the QYNDR vaccine. If QYNDR is a bit of a consonant-rich mouthful, then be informed that the official pronunciation if ‘KINDER’. And the advent of QYNDR is closer than you think. Phase 1 trials have already been completed in New Zealand (where else?) and all that is required is more funding to proceed with further trials. Apparently, it is very difficult to formulate a vaccine that survives the vicissitudes of the digestive tract.
And why do we need these vaccines? Well, according to US Speciality Formulations: ‘Covid-19 is still here and deadly.’ Also, I imagine that the inventors and investors envisage that this will make them shedloads of money. It clearly pays to perpetuate the Covid-19 narrative and to pepper it with as much panic as possible.
At some point in the panic-demic, the vaccine rollout became a juggernaut. Large and hard to stop. With the widespread and obvious extent to which people are gullible, government and drug manufacturers are willing to lie, health professionals are willing to stay silent and there are bucks to be made, it is unlikely that the juggernaut will be halted any time soon.
Who knows what’s next? Perhaps they will develop a vaccine that one can stick up one’s bottom. Whether or not they do, I strongly advise them that is what they can do with the present products.
Featured Video

Seyed M. Marandi: Toward Total War in the Middle East
or go to
Aletho News Archives – Video-Images
From the Archives
The Geopolitics behind the War in Yemen (I)
By Mahdi Darius NAZEMROAYA | Strategic Culture Foundation | 30.03.2015
The United States and the Kingdom of Saudi Arabia became very uneasy when the Yemenese or Yemenite movement of the Houthi or Ansarallah (meaning the supporters of God in Arabic) gained control of Yemen’s capital, Sanaa/Sana, in September 2014. The US-supported Yemenite President Abd-Rabbuh Manṣour Al-Hadi was humiliatingly forced to share power with the Houthis and the coalition of northern Yemenese tribes that had helped them enter Sana. Al-Hadi declared that negotiations for a Yemeni national unity government would take place and his allies the US and Saudi Arabia tried to use a new national dialogue and mediated talks to co-opt and pacify the Houthis.
The truth has been turned on its head about the war in Yemen. The war and ousting of President Abd-Rabbuh Manṣour Al-Hadi in Yemen are not the results of «Houthi coup» in Yemen. It is the opposite. Al-Hadi was ousted, because with Saudi and US support he tried to backtrack on the power sharing agreements he had made and return Yemen to authoritarian rule. The ousting of President Al-Hadi by the Houthis and their political allies was an unexpected reaction to the takeover Al-Hadi was planning with Washington and the House of Saudi. … continue
Blog Roll
 Aletho News
- Israeli lobby seeks to bind US fate to ‘Israel’: Araghchi
- Pakistan-Iran talks secure LNG shipment to Islamabad through Hormuz
- Black Sea grain crisis puts global wheat supplies under pressure
- IRGC air defenses destroy another US MQ-1 drone over Strait of Hormuz
- Imran Khan’s entire immediate family detained in Pakistan ahead of mass protest demanding his release
- EU nation detains former presidential frontrunner
- Leaked: Britain’s Sham Conviction Of Hashim Thaci
- Seyed M. Marandi: U.S. Strike Imminent – Toward Total War in the Middle East
- Russia Voted Under Fire. Washington Is Loading the Tankers.
- 12 Things Your Oncologist Was Trained Not to Tell You
- If Americans Knew
- Israeli Attacks in Gaza Kill at Least Seven Palestinians Over Three Days, including Woman and Child
- Trump’s militarization of Washington DC as he pursues Israel’s war against Iran
- Why Israel Fears This Searing New Documentary
- Huckabee aide solicited cash gifts from Israelis
- This isn’t sci-fi, AI is already killing people
- ‘The Most Brutal Thing’: Investigation Reveals Execution of Elderly Woman in Rafah
- Inside Israel’s ‘soft’ ethnic cleansing plan for Gaza through the eyes of its victims
- New online database tracks pro-Israel political donations in the United States
- Israeli president pardons soldier convicted for killing wounded Palestinian
- Singer Ed Sheeran says his ‘heart broken’ by Gaza devastation, addresses Macklemore controversy
- No Tricks Zone
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years
- Fear Of Debate: Alarmist German Climate Scientist Calls On Mainstream Media To Discredit Skeptic Voices
 Aletho News
