Every third Dutch farm to be closed down or expropriated!
Free West Media | July 6, 2022
CO 2 hysteria was so yesterday. In the Netherlands there’s now a nitrogen alarm. Ironically, at a time when the specter of food shortages and hunger is looming, the “Green Deal” of the all-powerful, misanthropic EU has prompted Commissioner Frans Timmermans to demand that ten percent of agricultural land be set aside across Europe.
In order to help this madness prevail, a Dutch “nitrogen problem” has been invented. On this basis, they want to force the livestock farmers – who are named as the main culprits – to give up their businesses. The Dutch “Minister for the Environment and Nitrogen”, Christianne van der Wal, announced that 30 percent of livestock farmers would have to give up their farms. Those affected now have the choice to give up their farms voluntarily and leave, or to pledge never to practice their profession again – only then would they be compensated. Those who do not comply face expropriation by the state. The aim is to reduce nitrogen emissions by up to 95 percent by 2030.
The Netherlands is the world’s fifth-largest exporter of food, exceeded only by the United States, Germany, the United Kingdom, and China, according to World Bank statistics.
So for at least a third of farmers it is a matter of survival. No wonder, then, that the protest is huge. For weeks, the angry farmers have been blocking roads and marching in front of government buildings to make their displeasure visible. Among other things, the access roads to some supermarkets were blocked. It was also announced that the access roads to the international airport in Amsterdam would be closed.
A few days ago farmers broke through a police barrier with their tractors and sprayed the minister’s house with liquid manure – symbolically the right thing to do because nitrogen is a building block for biological life on earth, the most abundant element in the atmosphere. It needs carbon, hydrogen, oxygen, lightning and bacteria, to provide “reactive” nitrogen. Fertilizer is just the workaround. Unbelievably, the Rutte government is targeting the manure people!
The mainstream media tried to sweep the issue under the carpet as tens of thousands of farmers took to the streets for days to demonstrate against EU regulations and government plans that would ruin Dutch agriculture. The police announced tougher action against the demonstrators, which, however, will probably only result in further escalation.
In Stroe alone, 30,000 farmers from all over the Netherlands came together to demonstrate against the government’s plans. In concrete terms, these plans stipulate that nitrogen emissions must be greatly reduced following a ruling by the highest court. In natural areas, the value is to be reduced by 12 to 95 percent, depending on the area category. According to government figures, this could mean the end for about a third of Dutch livestock farms, but it is much higher, farmers say.
The police meanwhile speak of a “threatening and unacceptable situation”. According to polls, about 45 percent of the Dutch population back the protests. In October, it was still 38 percent.
Shooting at protesters
The police fired shots at a farmers’ protest in Heerenveen on Tuesday evening. According to Facebook group Verzet Friesland, 16-year-old Jouke was shot at by police as he drove off with his tractor.
“The media are shouting that he drove into them, but it is very clear on camera that that was not the case. He just wanted to drive home.” Police opened fired on Jouke. Fortunately he was not injured, but the bullet missed him by two centimetres.
“The photos that are circulating show that the bullet(s) hit the cab of the tractor and missed Jouke by a hair. There was no shooting at tyres or in the air. It is by sheer luck that the police and the ministry responsible do not have a fatality on their conscience,” said lawyer Sietske Bergsma. Dozens of farmers tell the same story of police brutality.
Dutch anti-globalists are praying that this protest be the straw that break the Rutte camel’s back.
‘Why the Rush for Toddler Vaccines?’ Asks Wall Street Journal Editorial Board Member
By Susan C. Olmstead | The Defender | July 5, 2022
A Wall Street Journal (WSJ) editorial board member Monday called into question the motives behind the U.S. Food and Drug Administration’s (FDA) decision to extend Emergency Use Authorization of Pfizer and Moderna’s COVID-19 vaccines to toddlers and infants as young as 6 months old, writing that the decision was motivated by politics and pressure rather than science.
In her WSJ opinion piece — “Why the Rush for Toddler Vaccines?” — Allysia Finley wrote:
“The FDA standard for approving vaccines in otherwise healthy people, especially children, is supposed to be higher than for drugs that treat the sick.
“But the FDA conspicuously lowered its standards to approve COVID vaccines for toddlers. Why?”
Finley started her piece with a quote from President Biden, which praised the FDA’s recommendation: “This is a very historic milestone. The United States is now the first country in the world to offer safe and effective COVID-19 vaccines for children as young as six months old.”
She responded, writing, “In fact, we don’t know if the vaccines are safe and effective.”
She continued:
“The rushed FDA action was based on extremely weak evidence. It’s one thing to show regulatory flexibility during an emergency. But for children, Covid isn’t an emergency.
“The FDA bent its standards to an unusual degree and brushed aside troubling evidence that warrants more investigation.”
“Mr. Biden’s hypocrisy is hard to stomach,” she wrote, listing many reasons for caution in vaccinating young children against COVID-19, including:
- Children are at low risk of dying from COVID-19: Only 209 kids between 6 months and 4 years old have died from COVID-19 — about 0.02% of all virus deaths in the U.S. About half as many toddlers were hospitalized with COVID-19 between October 2020 and September 2021 as were hospitalized with the flu during the previous winter.
- The two children in Pfizer’s trial who got sickest with COVID-19 also tested positive for other viruses. It’s possible that many hospitalizations attributed to COVID-19 this winter were instigated or exacerbated by other viruses.
- The FDA authorized vaccines for toddlers based on a comparison of the antibodies they generated to the original Wuhan variant with those in young adults who had received two doses. But two doses offer little if any protection against Omicron infection in adults, and even protection against hospitalization is only around 40% to 60%.
- Vaccinated toddlers in Pfizer’s trial were more likely to get severely ill with COVID-19 than those who received a placebo. Most children who developed multiple infections during the trial were vaccinated.
“FDA granted the Pfizer and Moderna vaccines for toddlers an emergency-use authorization allowing the agency to expedite access for products that ‘prevent serious or life-threatening diseases or conditions,’” wrote Finley.
“While adult COVID vaccines clearly met this standard in late 2020, the toddler vaccines don’t.”
As to why the FDA “rushed” and “bent its standards,” Finley suggested, “perhaps [the FDA] felt pressure from the White House as well as anxious parents.”
White House COVID-19 response coordinator Ashish Jha repeatedly told parents that he expected vaccines for toddlers would be available in June, she wrote.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Vaxsplainers
German state media “debunks” eugyppius

eugyppius – July 6, 2022
I’m happy to report that my remarks on lower case rates in lesser-vaccinated East Germany, after being recycled by BILD, are now the subject of a long state media debunking in Tagesschau.
Why Are Case Rates Lower in the East? ask “science” reporter Anna Behrend and official state media “fact-finder” Pascal Siggelkow.
The nationwide seven-day incidence in Germany has been on the rise again for several weeks now. Health Minister Karl Lauterbach has already spoken of a summer Corona wave. But a look at the developments reveals that there are huge differences between the federal states:
While the incidences in Lower Saxony and Schleswig-Holstein have already passed the threshold of 900, the numbers in Thuringia and Saxony are still under 400. In general, it’s remarkable that all the East German states – with the exception of Mecklenburg-Vorpommern – are significantly below the national average incidence of of 687.7. And this is despite the fact that Saxony, Brandenburg and Thuringia have some of the poorest vaccination rates. In conspiracy-theory circles, people are already fantasising about “negative efficacy”, especially with regard to booster vaccinations, saying that the figures amount to proof that the vaccines are ineffective. But is there really a causal connection between the vaccination rate and the incidence?
Before they get into that, Siggelkow and Behrend light the incense and cycle through the familiar vaccinator nostrums. “Vaccination protects against severe outcomes and death,” even though the rise of Omicron has led to a great many “breakthrough infections.” Mysterious “studies,” which are never further characterised, are said to show “that vaccinated people … are slightly less contagious,” although they have to concede that “there isn’t enough data to conclude this decisively.”
Then, when they’re reasonably sure most people have stopped reading, comes an uncomfortable admission. Case incidences, the cornerstone of Tagesschau Corona reporting since 2020, are of, uh, “limited significance”:
If the vaccination rate … is not the decisive factor … how is it that the number of new infections in the East is comparatively low right now? First of all, it must be said that the current infection figures are only of limited significance. “One must always also consider that incidences are calculated on the basis of reported laboratory results,” says [virologist Johannes] Knobloch. As before, only positive PCR tests count in the RKI statistics. Willingness to be tested and the accessibility of PCR tests therefore have a very large influence on the measured incidence. … “The number of unreported cases is probably higher than in all previous phases of the pandemic.”
According to experts, the incidence continues to indicate whether the wave of infection is rising or falling. Caution is advised, however, when making regional comparisons, as the testing strategies and also the number of tests differ greatly across states. Fewer tests mean that fewer infections are detected. A high proportion of positive tests … indicates a high number of unreported cases …
Ah, so they just have super high positivity rates in the East then? That’s the explanation?
Ha no:
But it’s not the case that Eastern states have uniquely high positive rates compared to the others. So different testing patterns alone cannot explain the current low incidence there either.
It wasn’t that long ago that all manner of respectable journalists, especially those working for Pravda operations like Tagesschau, wrote long think pieces on the “global menace” of “vaccine scepticism,” complete with histrionics about the lower vaccination rates in Eastern Europe causing “much higher infection figures.” Lazy Googling yields many typical items, such as this piece from MDR in November, lamenting that the “incidence among unvaccinated in Sachsen-Anhalt is significantly higher than among the vaccinated.” This at a time when the vaccinated were exempt from most testing, while many unvaccinated had to submit to daily antigen tests before they could even go to work.
Now that these games no longer favour the vaccinated, though, we’re allowed to wonder about things like positivity rates. These certainly matter, but – unbeknownst to our crack fact-checking team – they’ve become totally meaningless in the era of lateral flow testing, as a plurality of PCR tests in Germany are conducted to confirm a positive antigen result, and nobody has any idea what the true rate of testing might be.
Frustrated on this front, Siggelkow and Behrend look for other signs that infections might really be higher in the East, even though the official incidence is lower there. More and more, you have the feeling of a desperate grasping after straws:
If the true incidence were in fact higher, you would expect to see this in ICU admissions …
Yet the proportion of Covid patients in ICU is currently not conspicuously high in the East compared to the rest of Germany.
Foiled again!
So were most people in the low-incidence states already infected and now immune? Those who become infected with the coronavirus usually form antibodies against it. How long and how well these antibodies protect against a new infection with the virus has not yet been conclusively researched.
However, if we assume that there is at least some protection for a while, one conceivable reason for the low incidence in some states would be that more people have already come into contact with the virus there and are therefore less likely to be infected now.
… It’s not known precisely how much of the population in which states has already recovered from infection. If you take the number of new infections … since the beginning of the year as a rough approximation of the circulation of Omicron, you find no confirmation of the assumption that the population of the East has had greater contact with the virus. …
How confusing. Do Tagesschau no longer stand by their dire proclamations, uttered just this past winter, that lower vaccination rates were to be blame for higher infections in the East? Is their position now that the East never saw higher rates of infection at all, even though the vaccines definitely protect against infection? Also too, why have we abandoned so soon our thesis that the incidence is of “limited significance,” can only tell us when cases are going up or down, and says nothing about how many cases there actually are? I thought regional comparisons of case numbers were bad?
Way down at the bottom, when Behrend and Siggelkow are triply sure nobody is reading anymore, they toss out the possibility that cases might indeed be lower in the East – not because of the vaccines, but because the new Omicron variants haven’t gotten there yet:
One reason the nationwide incidences are rising so sharply in the first place is the Omicron subtypes BA.4 and BA.5, which experts consider more contagious than the previously known “sister variants.” BA.5 is now dominant … It’s of course possible that some states are more affected by the new variants than others, where these variants have not yet arrived.
If BA.5 infects the vaccinated preferentially, and vaccination rates vary substantially across regions, there will be many places where BA.5 never quite seems to have arrived. Perhaps aware of this close brush with crimethink, our braintrust wraps things up with some cleansing mantras:
What is certain, though, is that there is no scientifically sound reason to assume that a high vaccination rate could be partly responsible for a high incidence. On the contrary: Scientific data show instead that people infected with Omicron are less likely to infect others than the unvaccinated.
Every conspiracy theory must first be ignored, then denied, and finally debunked, before it becomes true.
‘We Need to Be Allowed to Ask Questions,’ Says Canadian Prof Suspended for Questioning COVID Shots for Kids

By Julie Comber, Ph.D. | The Defender | July 5, 2022
A Canadian university professor suspended for comments he made during a December 2021 conference about COVID-19 vaccines in an interview this week with The Defender called for “openness, critical thinking and to stop believing what we are being told is the truth.”
“We need to be allowed to question again,” said Patrick Provost, Ph.D., an infectious and immune diseases researcher who learned June 13 that Laval University in Quebec City was suspending him for eight weeks without pay.
Laval University also suspended Nicolas Derome, Ph.D., a professor in the university’s biology department, for concerns he raised in November 2021 about Quebec’s campaign to vaccinate 5— to 11-year-olds.
In his interview with The Defender, Provost also discussed an article he wrote questioning COVID-19 policies, published June 22 on the Québecor media platform, then retracted a day later.
For the article, Provost used Quebec’s publicly available data to raise questions about the province’s management of the pandemic. The province of Quebec is home to about 8.5 million people, the second-most populous province in Canada.
“I was so happy when I found out my article was going to be published,” Provost told The Defender, “I really thought it would be a game-changer in the public debate about COVID-19 [in Quebec]. That finally, based on official public data, we could start to discuss the situation.”
However, by the next day, June 23, Québecor had removed Provost’s article from all of its websites.
Sébastien Ménard, publisher and editor-in-chief of the Journal de Québec, one of Québecor’s publications, tweeted (in French):
“Although we encourage debating ideas, we have decided to remove this letter [by Dr. Provost] from our websites. After verification, some of the elements it contained were inaccurate or could mislead the public, which we cannot support.”
Commenting on the retraction, Provost said:
“I’m really worried about the direction we are heading, about our democracy. Why hide the truth? These numbers are real, this was just my analysis of them. Maybe it’s a disturbing truth.”
Libre Média, a new Quebec-based independent media website, on June 24 published Provost’s article so it is still publicly available.
Libre Média prefaced the article with a note that it was publishing Provost’s article in full, “in accordance with its mission to protect freedom of the press.”
Criticism of COVID vaccines for young children led to suspension
Two days after Québecor removed his article, Provost went public with the news that Laval notified him on June 13 that the university was suspending him, effective June 14.
Provost filed a grievance through his union, the Union of Laval University Professors.
According to Provost, he sent an email to all his colleagues at Laval University last December, in which he urged them to engage in debates on COVID-19 vaccination and public health measures, because he felt public debate had been lacking.
In the email, he gave the example of a lecture he had given at a conference on Dec. 7, 2021, in which he criticized Quebec’s campaign to vaccinate 5- to 11-year-old children against COVID-19.
The conference was organized by Réinfo Covid Québec, a Quebec collective of caregivers, doctors and citizens “gathered around an idea: the need for a fair and proportionate health policy in Quebec and elsewhere in the world.”
“As a result of this, a professor from the faculty of medicine filed a complaint against me in January, outraged that I was raising questions,” Provost told The Defender. “In particular, that I said the risks of adverse effects [of Pfizer’s mRNA shot] outweighed the benefits for children.”
Provost said his suspension didn’t factor into Québecor’s decision this week to censor his article, as he had not made the news of his suspension public before the article was removed.
COVID mortality rate ‘greatly overestimated’ data show
In his article, Provost noted that the vaccine mandates for travel within Canada and for federal public servants had been suspended two days before, on June 20.
However, mandates could be reimposed, so Provost invited readers to consider a true portrait of the impact of COVID-19 in Quebec, based on the province’s own publicly available data.
As of June 19, when Provost accessed the cumulative data online, there were 15,462 deaths related to COVID-19 (Chart 2.1) out of a total of 1,077,256 confirmed cases of COVID-19 (Chart 1.1), for a calculated mortality rate of 1.44%.
Provost wrote:
“This mortality rate is greatly overestimated, mainly (i) by including, in the numerator, deaths with, and not because of, COVID-19, which were apparently as numerous, and (ii) by excluding, in the denominator, cases of asymptomatic or unreported infections, which were several times higher than the reported symptomatic infections.”
Provost then turned to official figures from the Institut de la statistique du Québec and the Institut national de santé publique du Québec (INSPQ), and made these five observations based on the data:
- There was no excess all-cause mortality since the beginning of the COVID-19 pandemic, except for people age 70 and over during the first wave (April to June 2020) and in January 2022, shortly after the lockdowns and curfews were imposed, which was also when the third vaccine doses were offered.
- More than 90% of people age 70 or older who died with or from COVID-19 had two or more pre-existing medical conditions (Table 2.2).
- 69.2% of the people who died were over the age of 80 (Figure 2.3), thus the average age of people who died with or from COVID-19 was beyond their life expectancy at birth.
- The number of deaths (Table 2.1) compared to the number of cases (Table 1.1) is 0.07% in people with no pre-existing conditions, 6 times higher in people with one pre-existing medical condition (0.4%), and 98 times higher in people with two or more pre-existing conditions (6 .9%), according to data last updated on May 2.
- Between 0 and 5 people under the age of 40 (with less than one pre-existing medical condition) have died in Quebec since the start of the pandemic (Table 2.2).
According to Provost, early on in the pandemic, the analysis of official government data showed two of the main risk factors for complications and death from COVID-19: “advanced age and the number of pre-existing medical conditions, in particular, obesity.”
“The threat of COVID-19 was very real,” wrote Provost, “but was it of the magnitude that we have been told?”
According to the public data available on the sites of INSPQ and of Quebec Data Partnership, from April 1, 2020, to March 31, 2021, there were 20,616 hospitalizations due to COVID-19 out of a total of 986,607 hospitalizations — so approximately 2.1% of hospitalizations were a result of COVID-19 infections.
At the worst point in the crisis, COVID-19 hospitalizations peaked at 5.9% of the total.
Given the above data, Provost asked if the public health measures taken were justified. He raised a series of questions, including:
- Did the data support imposing such severe and comprehensive health measures, rather than targeted ones that would protect those most at risk?
- Did the data justify not considering the collateral effects of restrictive health measures?
- Did the data justify preventing physicians from making individualized risk versus benefit assessments of a medical intervention (COVID-19 vaccination) with their patients?
Provost also asked if the data justified overriding the right of individuals to consent, in a free and informed manner, to an injection that is still experimental.
He questioned mass vaccination of the entire population for a disease that particularly affects the very old and sick, and of imposing vaccination on young people and workers.
Quebec used vaccine passports, and Provost asked if the data justified restricting the right to access public places and hindering the freedom of movement by train or plane of people who were not “adequately” vaccinated, “even though the shots do not prevent infection or transmission.”
With respect to governance, Provost said the government assumed power by self-proclaiming and perpetuating a state of health emergency and certain measures beyond the emergency period.
He noted that professionals and academics were muzzled if they were critical of health measures, through pressure from their professional organizations or their institutions, under penalty of losing their jobs.
He also pointed out that the polarized and polarizing media coverage sowed fear, anxiety and division, and that citizens were encouraged to discriminate against people who were not vaccinated against COVID-19.
As part of the remedy to what he viewed to be heavy-handed public health measures, Provost stressed the “importance of depoliticizing decisions that infringe on individual rights and freedoms by establishing, for example, by a Council of Scholars that is independent from the government, so that these decisions are based on science and are made more quickly.”
Provost closed his article by calling for a review of the management of the pandemic:
“An assessment of the management of this crisis, which has revealed the limits, even the flaws, of our system and our democratic life, is essential.
“We owe it to too many seniors whom we have failed to protect, as well as to those whose rights and freedoms have been violated for too long.”
Dozens of messages of support
Provost told the Defender that in the hours before his article was pulled, one idea was to have another professor write a rebuttal to his article.
But instead, Quebecor’s news sites simply deleted the article.
On Monday, Joel Monzée wrote an article in Libre Média about the censorship of Provost’s article and its implications for science. “Science is only science because it questions itself,” Monzée wrote.
Monzée said that with respect to the COVID-19 pandemic, “It is blithely claimed that there is a scientific consensus. However, this only exists because certain academic personalities seem to have enough influence over their colleagues to curb any questioning of the consensus, at least in public.”
Monzée asked, if there were inaccuracies in Provost’s article, then why not address them with a counter-analysis?
Provost is the supervisor of four Ph.D. students whose work has been affected by his suspension.
“Because of my suspension, I cannot go on the campus, enter the Research center or talk to them,” Provost said. “They are essentially left alone. They are collateral damage.”
Provost said that though the situation was difficult, in the past few days he had received dozens of messages of support, and also observed that a growing number of citizens “have a thirst for truth and openness.”
Provost told The Defender, “I would like to raise awareness about how our society is evolving, it’s not in a good direction. It is getting to the point where private interests will be directing our country, we will just be servants.”
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Ukraine Crisis Highlights Concerns About Whether OPCW Still Has Any Global Relevance, Observers Say
Samizdat | July 6, 2022
The executive council of the Organization for the Prohibition of Chemical Weapons (OPCW) kicked off its hundredth session at The Hague on Tuesday. Last month, the global watchdog assured that it was “monitoring the situation” in Ukraine closely as far as the potential use of chemical weapons is concerned.
The OPCW’s lack of a coherent, objective and fair-minded response to recent crises centered around Syria and Russia demonstrates its politicization and domination by Western interests, and the longer the watchdog stays out of Ukraine, the better, former diplomats, geopolitical observers, and international legal experts have told Sputnik.
“In Ukraine the OPCW has fortunately not been pressed into action. This, I suspect, is because the US is satisfied with the situation as it is, with no need for the US itself to be drawn in, as would no doubt be the case if a chemical attack was fabricated,” Peter Ford, Britain’s former ambassador to Syria, said.
The veteran diplomat, who warned the British government against the folly of the 2003 invasion of Iraq, and stressed that Western powers’ campaign to topple the Syrian government in the 2010s could open a “Pandora’s box” of endless crises, said the Syria case demonstrated clearly that the OPCW is no longer an independent, impartial agency.
“The Syria crisis proved without a shadow of a doubt that the Western powers have bent the OPCW to their own will, destroying in the process the organization’s credibility, probably irretrievably. This is a tragedy for world peace,” Ford stressed, referring to documented OPCW efforts to censor and smear agency whistleblowers who revealed that the watchdog’s report on the April 2018 chemical attack in Douma, Syria was doctored to implicate the Assad government.
In Ukraine, Ford fears, the international community can now only depend on “self-interested restraint on the part of the Pentagon in controlling its proxies rather than the deterrent power of a genuinely impartial international watchdog.”
Chemical Weapons Danger in Ukraine
Since the escalation of the crisis in Ukraine in February, Russia has sent the OPCW and its technical secretariat over two dozen notes warning of possible staged provocations by Ukrainian forces or radical nationalists involving chemical weapons. Last month, the agency assured the international community that it was “closely monitoring the situation in Ukraine” for chemical weapons use.
On Wednesday, Russian military indicated that it had information on plans by Kiev to stage a provocation in the Donetsk People’s Republic using chlorine gas to accuse Moscow on indiscriminate attacks targeting chemically hazardous objects.
Alessandro Bruno, a Toronto-based geopolitical analyst and political observer at Lombardi Letter, says that while the OPCW’s official mission and goals are “certainly worth pursuing,” the problem is the watchdog’s control by Western interests seeking to obfuscate the truth and objectivity in favor of politicized objectives.
“They seem to have targeted only specific sides in specific wars to suit specific aims, which typically are those of Western powers. There have been many efforts to manipulate these organizations by the dominant powers, particularly in the West,” Bruno said.
The scholar recalled instances of claims by the US and its allies about Russia’s use of chemical weapons, from the allegation that Russia poisoned pro-Western Ukrainian presidential candidate Viktor Yushchenko in the mid-2000s, to the 2018 Novichok scandal in Britain, which “many thoughtful journalists have debunked,” to the Alexei Navalny “poisoning” saga of 2020, which doctors treating the opposition vlogger have debunked.
“Yet the accusations of chemical weapons that Russia used have persisted, even though they defied all logic. That’s the biggest issue with these organizations. They must be more neutral. Their headquarters must be in more neutral locations, because the fact that many of these organizations operate from Western capitals makes them more prone to Western media misinformation,” Bruno said.
The geopolitical analyst still fears that the West could use the pretext of ‘Russian chemical weapons use’ in Ukraine “to get more directly involved into the conflict and potentially trigger a much wider physical war.”
“So far, I think, some of the powers came to understand that making an accusation like that in this conflict would be riskier than the accusations they made in Syria and Iraq, Navalny and Yushchenko and so on, that this would have much bigger implications, that this would blow back against the West,” Bruno stressed.
Tool of US Interests
Christopher C. Black, an international criminal and human rights lawyer with 20 years of experience covering war crimes and international relations, echoed Bruno’s sentiments about the OPCW’s noble stated aims and their stark contrast with the body’s actual history, which “shows that [the watchdog] acts to serve the interests of the United States and its NATO and other allies.”
“We saw strong evidence of this when the USA tried to get rid of the Director General Jose Bustani of Brazil in 2002, when the United States was preparing its invasion of Iraq and John Bolton went to The Hague and threatened his family if he did not resign,” Black recalled, pointing to Bustani’s 2018 interview with The Intercept in which the former OPCW chief detailed the threats made against his children living in the United States.
“In August 2020, it was revealed through leaks from Austrian government sources that the OPCW and British claims that Novichok had been found in the blood of the Skripals allegedly poisoned in the UK were false, that in fact no such agent had been found in their blood at all. But the findings were suppressed and a false report issued to back the UK claims,” the lawyer added. “Similar results were seen regarding the alleged poisoning of Mr. Navalny. We can quickly understand what goes on behind the scenes at the OPCW,” Black said.
Black finds it unlikely that the chemical weapons watchdog will change “without a change in the balance of power in the world,” which is taking place, but whose effects on international organizations will be slow to appear.
In Ukraine, the lawyer fears, “We cannot expect any objective consideration of Kiev regime or NATO claims of Russia using chemical weapons in Ukraine for the reasons stated above, despite the fact that Russia has not used them, does not use them and will not use them. To the contrary we have a situation in which Kiev and NATO forces keep making false claims while themselves preparing chemical weapons attacks to be staged as false flag attacks to be blamed on Russia and when Russia asks the OPCW to investigate this, Russia is met with silence,” he said.
How OPCW Can Regain Credibility
Dr. Alfred De Zayas, a lawyer, writer and former independent expert on international order with the United Nations, similarly doubts the OPCW’s ability to reform in its current itteration, saying the agency “has long been instrumentalized to pursue the geopolitical interests of Western powers.”
The international legal expert is confident that agencies like the OPCW, the International Criminal Court and the Human Rights Council can regain their credibility by demonstrating impartiality. “This is possible if the BRICS countries become more vocal and more visible on the international scene. There is no reason why African, Asian and Latin American countries should dance to the tune of the ‘Washington consensus’,” De Zayas stressed.
In Ukraine, the OPCW’s assurance about “monitoring the situation” carries only a “purely propagandistic value,” and is “intended to charge and convict Russia even before there is any evidence of violations of the Chemical Weapons Convention,” the observer believes.
“If the OPCW investigates not only potential Russian war crimes, but also expands its investigation to potential chemical weapons violations and war crimes by Ukrainian forces and by foreign mercenaries, including US, UK, French, Georgian and others, then the OPCW might regain some credibility. That, however, would be ‘out of character’. It is not unlike the ICC, which in the eyes of many observers in the US, Canada, UK, France, Germany, Switzerland – has lost its little credibility and will have no authority unless and until it indicts Western politicians and bureaucrats including Tony Blair, George W. Bush, Paul Wolfowitz, Victoria Nuland, Barack Obama (the king of the drones), Donald Trump, Nikolas Sarkozy, etc.,” De Zayas concluded.
Two and 3-year-old kids with seizures is “the new normal”
I’m getting multiple reports from nurse friends about 2 and 3 year-olds having seizures. It is only happening to vaccinated kids, and symptoms start 2 to 5 days after the COVID jab.
By Steve Kirsch | July 4, 2022
Doctors are mystified by a rash of seizures, rashes, etc. happening to 2 and 3-year-old kids.
The only thing these kids have in common is that they were given the COVID vaccine just days earlier (two to five days earlier).
The doctors cannot figure out what is causing the seizures (since it couldn’t be the vaccine since those are safe and effective). The medical staff is not permitted to talk about the cases to the press or on social media or they will be fired.
One nurse posted something to the effect of “how is this legal????” I had to paraphrase to protect the poster.
This is why you are hearing these reports from me. They can’t fire me.
There is nothing on the mainstream media about this since the nurses and doctors aren’t allowed to talk about it.
This will all come out some day, but for now, everyone is keeping quiet about it and the doctors are instructed to convince the parents that it isn’t vaccine related and that they are the only ones having the problem.
Because that’s how science works.
Financial Times Censors Criticism of Vaccine Article
BY TOBY YOUNG | THE DAILY SCEPTIC | JULY 5, 2022
Earlier today, the Financial Times removed a comment from a reader calling himself ‘Mykonos Mike’ underneath an article about why COVID-19 infection and vaccination are only partially effective – and, in some cases, completely ineffective after a certain period of time has passed – when it comes to reducing a person’s likelihood of becoming re-infected, infecting others, and ending up with a severe bout of the disease. The reason given for removing the comment, in spite of the fact that it was the most liked and commented on, was “violating our community guidelines”, although, needless to say, no more detail was provided.
In light of this, we thought it was only right to republish Mykonos Mike’s comment in full.
Is this the long winded drivel to explain how people who have taken four doses of a 95% effective vaccine can get infected multiple times? The science in the pandemic has been so wrong it entered fairy tale wonderland story telling level, almost from the beginning. This is volume 15 of series four of the story. I’ll provide a spoiler – nobody cares anymore. And the decisions made in relation to this virus were ineffective and have created massive social and economic problems that will last decades. Time to start calling it as it is FT, the media are hugely complicit in this nonsense. Governments, scientists, health authorities and pharmaceutical companies need to answer very direct questions.
You can read the FT article Mike is commenting on here. Here’s an excerpt.
A surge in COVID-19 hospital admissions driven by the BA.5 subvariant of Omicron, accompanied by the inability of vaccines to prevent reinfection, has prompted health policymakers to rethink their approach to boosters.
U.S. regulators last week recommended changing the design of vaccines to produce a new booster targeting Omicron — the first change to the make-up of shots since their introduction in late 2020. Research into immune imprinting, whereby exposure to the virus via either infection or vaccination determines an individual’s level of protection, is now driving the debate over the make-up of COVID-19 vaccines.
Immunologists say that, more than two years into the coronavirus pandemic, people have acquired very different types of immunity to the SARS-CoV-2 virus, depending on which strain or combination of strains they have been exposed to — leading to big differences in COVID-19 outcomes between individuals and countries.
“The effect is more nuanced than ‘more times you have it, less protection you get’,” said Professor Danny Altmann of Imperial College London, who is investigating the phenomenon with colleagues. “It’s more helpful to consider it as progressive fine-tuning of a huge repertoire. Sometimes this will be beneficial for the next wave, sometimes not.” …
A study of 700 U.K. healthcare workers by the Imperial team, published last month in the journal Science, found that Omicron infection had little or no beneficial effect of boosting any part of the immune system — antibodies, B-cells or T-cells — among people who had been imprinted with earlier SARS-CoV-2 variants.
The Daily Sceptic has addressed the claims being made about this study and the supposed loss of natural immunity with Omicron here.
Will Pfizer Be Charged for Mislabeling Vaccine Side Effects?
By Dr. Joseph Mercola | July 5, 2022
As the U.S. Food and Drug Administration continues to release Pfizer’s clinical trial documentation,1 we’re finding more and more evidence that very little has been done on the up-and-up, and the COVID jab trials may be among the most fraudulent in medical history.
Can All Serious Adverse Effects Be Written Off?
Importantly, Pfizer classified almost all severe adverse events that occurred during its Phase 3 trials as unrelated to the injection. As reported by The Defender, June 21, 2022:2
“The latest release by the U.S. Food and Drug Administration (FDA) of Pfizer-BioNTech COVID-19 vaccine documents reveals numerous instances of participants who sustained severe adverse events during Phase 3 trials. Some of these participants withdrew from the trials, some were dropped and some died.
The 80,000-page document cache includes an extensive set of Case Report Forms (CRFs) from Pfizer Phase 3 trials conducted at various locations in the U.S., in addition to other documentation pertaining to participants in Pfizer-BioNTech vaccine trials in the U.S. and worldwide …
The CRFs included in this month’s documents contain often vague explanations of the specific symptoms experienced by the trial participants. They also reveal a trend of classifying almost all adverse events — and in particular severe adverse events (SAEs) — as being ‘not related’ to the vaccine.”
The Defender article includes 11 examples3 of trial participants who experienced severe adverse effects that were classified as “unrelated” to the experimental gene transfer technology they’d received just days or weeks earlier.
A 2,566-page document4 catalogues the serious adverse events and six deaths that occurred during the trial. These events were all classified as “toxicity level 4,” which is the most serious, yet none of them were deemed related to the injection.
This simply isn’t believable. It’s completely unrealistic, especially when serious events occur in multiple participants. A handful of examples of Level 4 adverse events listed in this document — all of which were written off as “not related” to the mRNA injection — include:5
- Acute respiratory failure
- Cardiac arrest
- Brain abscess
- Adrenal carcinoma (adrenal cancer)
- Chronic myeloid leukemia (blood and bone marrow cancer)
The six deaths reported were listed as being caused by arteriosclerosis, cardiac arrest, hemorrhagic stroke and myocardial infarction.6 Many participants also dropped out or were excluded from the trial due to serious side effects involving the heart, cardiovascular system, cancer, stroke, hemorrhage and neurological impacts.
Examples of Level 3 Adverse Events
Most Level 3 adverse events were also dismissed as unrelated to the shot. As reported by The Defender, only a “small number” were listed as being related to the injection. Examples of Level 3 side effects include:7
- Deafness/hearing loss
- Tachycardia (disruption of the normal electrical impulses that control your heart rate — the very problem that underlies most cases of “sudden adult death syndrome” or SADS)
- Ventricular arrhythmia (abnormal heart rhythm that makes the lower chambers twitch rather than pump — another underlying cause of SADS)
- Neutropenia (low neutrophil level in your blood; neutrophils are a type of white blood cell made by your bone marrow that fight infections by destroying viruses and bacteria)
- Vertigo
45% Experienced One or More Adverse Events
Another document8 that raises suspicions of bias is one admitting that “40% to 45% of participants who received BNT162b1 and BNT162b2 across age groups and across dose levels reported one or more AEs [adverse events] from Dose 1 through 28 days (i.e., 1 month) after Dose 2.”
BNT162b2 was the candidate injection that went on to receive Emergency Use Authorization (EUA) from the FDA. Among those who got the highest dose (30 micrograms) of BNT162b2, 50% of younger participants 25% in the older age group reported one or more adverse events.
The most common adverse events were nervous system disorders, followed by musculoskeletal and connective tissue disorders. Yet despite high rates of side effects across dose levels, this document also insists that “most AEs were considered by the investigator as not related to study intervention.”
During the open-label period of the study, 12,006 participants were followed for a minimum of six months, and among those, 28.8% reported at least one adverse event at some point during that follow-up, and 2.1% reported one or more severe adverse events.
Incidence Rate in Treatment Group FAR Higher Than Placebo
As reported by The Defender :9
“The review provides data for participants from dose 3 … to the data cutoff date. The severe adverse event incidence rate (IR) was 6.0 per 100 PY (patient-years), with specific conditions reported including pulmonary embolisms, thrombosis, urticaria, a cerebrovascular accident and COVID-19 pneumonia.
Here, the review adds that the IR for original placebo participants who had at least 1 life-threatening AE from Dose 3 to the data cutoff date was 0.5 per 100 PY.
Only one such life-threatening event, an instance of anaphylactoid reaction, was considered to be related to the vaccination. Other life-threatening, serious adverse events included cardio-respiratory arrest, gastrointestinal necrosis, deep vein thrombosis and pulmonary embolism …
Notably, according to the review, ‘all … events of facial paralysis were considered by the investigator as related to study intervention.” [Editor’s note: these specifically refer to events that occurred during the open-label follow-up period when BNT162b2 Dose 3 or Dose 4 was offered to both placebo and initial treatment groups.]
Young Children Have Extremely Low Risk of Death From COVID
In the end, we all know what happened. Despite all the evidence to the contrary, Pfizer concluded the shot was safe and effective for everyone and the FDA went along with it. The vaccine manufacturers and the FDA have decided it isn’t even worth invoking the precautionary principle for the very youngest of children, which is nothing short of reprehensible, criminal maleficence.
In mid-June 2022, against strong objections from physicians, scientists and researchers, the FDA’s vaccine advisory panel — the Vaccines and Related Biological Products Advisory Committee (VRBPAC) — unanimously agreed to grant EUA to both Pfizer’s and Moderna’s COVID shots for infants and young children.10,11
Pfizer’s EUA is for a three-dose regimen (3-microgram shots) for children 6 months to 5 years old, while Moderna’s EUA is for a two-dose regimen (25-microgram shots) for children 6 months to 6 years.
According to the U.S. Centers for Disease Control and Prevention,12 an estimated 75% of American children ages birth to 11 already have some level of immunity, having been exposed to one of the several variants that have come into circulation over the past two-plus years.
This immunity level alone makes EUA for COVID shots questionable. CDC data also prove young children have a very low risk of hospitalization and death from COVID, which makes the EUAs even more questionable.
Data13 published in mid-March 2022 suggest babies and young children under the age of 4 have had a peak hospitalization rate for COVID of 14.5 per 100,000. That peak occurred after Omicron became predominant. The hospitalization rate for the Delta variant in this age group was 2.9 per 100,000.
In all, since March 2020, a total of 2,562 infants and young children (6 months to 4 years) have been hospitalized WITH COVID. Of those, 2,068 had COVID listed as the primary reason for admission (84.7% of the total), and only 624 required ICU admission.
The median length of hospital stay was 1.5 days (range: one to three days). Of the 2,562 children with suspected COVID infection, 16 of them (0.6%) died in the hospital. Death certificate data push that number a bit higher. The Vaccine Reaction notes,14 “According to death certificate data,15 202 deaths have been attributed to COVID-19 among children 6 months to 4 years of age through May 11, 2022.”
While any death is tragic, it’s worth noting that 923 (35.8%) of the children hospitalized with suspected COVID also had one or more underlying medical conditions.16 We don’t know for sure, but it’s quite possible that those who died with a COVID diagnosis actually died from whatever underlying condition was present or had brought them to the hospital in the first place.
What I’m trying to say is that 16 to 202 deaths over two-plus years aren’t cause for panic, and that’s true even if COVID was the primary cause of those deaths. The likelihood of your child getting injured by the mRNA shot is undoubtedly significantly greater than their risk of dying from COVID.
Jab More Likely to Put You in the Hospital Than Keep You Out
The same is true for adults, by the way. A June 2022 analysis17,18 of Pfizer and Moderna trial data found the shots are more likely to put you in the hospital than keep you out of it. As reported by The Daily Sceptic :19
“A new paper20 by BMJ Editor Dr. Peter Doshi and colleagues has analyzed data from the Pfizer and Moderna COVID vaccine trials and found that the vaccines are more likely to put you in hospital with a serious adverse event than keep you out by protecting you from COVID.
The pre-print (not yet peer-reviewed) focuses on serious adverse events highlighted in a WHO-endorsed ‘priority list21 of potential adverse events relevant to COVID-19 vaccines.’ The authors evaluated these serious adverse events of special interest as observed in ‘phase III randomized trials of mRNA COVID-19 vaccines’ …
Dr. Doshi and colleagues found that the Pfizer and Moderna mRNA COVID-19 vaccines were associated with an increased risk of serious adverse events of special interest of 10.1 events per 10,000 vaccinated for Pfizer and 15.1 events per 10,000 vaccinated for Moderna …
When combined, the mRNA vaccines were associated with a risk increase of serious adverse events of special interest of 12.5 per 10,000 vaccinated … The authors note that this level of increased risk post-vaccine is greater than the risk reduction for COVID-19 hospitalization in both Pfizer and Moderna trials, which was 2.3 per 10,000 participants for Pfizer and 6.4 per 10,000 for Moderna.
This means that on this measure, the Pfizer vaccine results in a net increase in serious adverse events of 7.8 per 10,000 vaccinated and the Moderna vaccine of 8.7 per 10,000 vaccinated.”
Doshi’s team wasn’t the first to reanalyze Pfizer’s trial data. The Canadian COVID Care Alliance has also published a clear and easy-to-read summary22 of the Pfizer trial results, and the many questions raised by it. As noted by Dr. Robert Malone:23
“The bottom line is that the Pfizer Phase 3 trial which was used by NIAID [the National Institutes of Allergy and Infectious Diseases], FDA and CDC to justify the emergency use authorization is pretty much a junk clinical trial which was inappropriately halted long before it even got close to meeting the intended follow up period, did not provide a sufficiently long follow up analysis of vaccination-associated adverse events, and in which the control group was intentionally eliminated.
This resulted in basically erasing any opportunity to ever get to the bottom of what the major true risks of the Pfizer mRNA inoculations were. In terms of more minor risks, the study was not powered (not big enough) to evaluate those.”
FDA and CDC Have Neglected Important Duties
Doshi and his coauthors also note the FDA also watered down results by including “thousands of additional participants with very little follow-up, of which the large majority had only received one dose.”
They then further diluted the appearance of risk by counting only the number of people affected rather than counting the total number of individual adverse events. This makes a big difference, as twice as many people in the treatment group reported multiple serious adverse events, as compared to the placebo group.
The FDA and CDC have both also failed to produce promised follow-up investigations. In July 2021, now a full year ago, the FDA said it would investigate four “potential adverse events of interest following Pfizer vaccination,” namely pulmonary embolism, acute myocardial infarction, immune thrombocytopenia and disseminated intravascular coagulation, but to date, no update has been issued.
Similarly, in early 2021, the CDC published a protocol on how to use proportional reporting ratios to detect signals in the U.S. Vaccine Adverse Event Reporting System (VAERS), but no study or report showing what that protocol might have found has ever been published.
As it turns out, the CDC hasn’t been looking for safety signals in VAERS — not with the proportional ratios protocol or any other. So, while they’ve publicly claimed they haven’t seen any signals of concern, the reason they haven’t seen any signals is very simple: They never looked at the data!24
That’s how ridiculous things are now. When a drug company or health agency claims they haven’t found a problem, you actually have to ask them, “where, when, how and how often did you look?” But of course, virtually no one would ever ask such questions because they would assume these agencies are competent, which of course is a false assumption.
Their Fraudulent Behavior Could Be Their Undoing
As you probably know, the makers of the COVID shots are indemnified against legal liability for any injuries and all deaths stemming from their products. No one is able to sue them for damages.
The only way to hold them responsible is to prove they’ve committed fraud. This would remove their liability immunity. As detailed at the beginning of the article, their consciously choosing to miscategorize adverse events during the initial trials and concealing the harms should be a slam dunk to convict them of fraud.
But there is also another fact they concealed: There’s evidence showing they knew the mRNA doesn’t stay in the injection site but, rather, distributes throughout the body,25 and this too could be a smoking gun that proves fraud. If convicted of fraud, Pfizer, Moderna and Janssen would likely face liabilities in the trillions of dollars in damages.
When I exposed Merck’s Vioxx scandal in 1999 in this newsletter, before they even released their drug on the market, I thought that was huge. Their drug killed more than 60,000 people, and they could have been liable for $25 billion in damages, but their clever lawyers reduced it to $5 billion.
Well, that catastrophe is a drop in the bucket compared to the COVID scam, which has likely killed between 600,000 and 750,000 Americans, disabled as many as 5 million, and injured an estimated 30 million Americans in one way or another.26,27 That’s just the estimated toll in the U.S., so you can imagine what the global numbers might be. It’s a catastrophe of unprecedented proportions. A June 2022 survey by Steve Kirsch also found:28
- 6.6% of COVID jabbed respondents suffered heart injury (about 10 million Americans, based on the national vaccination rate)
- 6.3% had to be hospitalized for their side effects (another 10 million Americans)
- 9.2% of those who took the jab had to seek medical help for their injury, which translated over the whole country would be about 18 million doctor’s visits
- People who got the shot were more likely to die from COVID than the unvaccinated
- 2.63% of the responders had lost someone in their household to COVID infection, and 2.03% had lost someone in their household to the COVID jab
Expect Depopulation
Whether intentional or not, mounting evidence now indicates the COVID-19 injections will result in depopulation through premature death and adverse effects on fertility in women and men alike. I’ve previously discussed the risk of pregnancy loss and infertility in women who get the shot, as the mRNA has an affinity for accumulating in the ovaries29 (as well as the adrenals, liver and bone marrow).
Research30,31 from Israel now also reveals the shot deteriorates sperm count and sperm motility in men for about three months. Considering the multidose mRNA shots are recommended at three-month intervals, you can see how this can really decimate a man’s prospects of fathering a child.
Fertility has been on a steady decline for decades in most parts of the world,32 but the worldwide COVID jab campaign may massively speed that up. Germany recently released data showing a 10% decline in birth rate during the first quarter of 2022.33

Other countries are also seeing a drop in birth rate, nine months after the start of the mass vaccination campaign against COVID. Between January and April 2022, Switzerland’s birth rate was 15% lower than expected, the U.K.’s was down by 10% and Taiwan’s was down 20%.34
What punishment could possibly be appropriate for company heads and health agency leaders responsible for causing massive depopulation worldwide through products that were based on fraudulent science and fictional claims? I doubt if there’s enough money in the world to set that right.
Future Trials To Be Skipped Altogether
As if matters weren’t already beyond horrible, the FDA is considering allowing manufacturers to reformulate their COVID injections in perpetuity without conducting any additional clinical trials!35 In other words, they’d allow drug companies to change the mRNA and/or other ingredients without any safety or efficacy testing whatsoever. As reported by Toby Rogers, Ph.D., in a June 27, 2022, article in The Defender :36
“FDA released a briefing document37 in connection with this scheme to end science as we know it in connection with future COVID-19 shots … The briefing document is 18 pages of text, 1.5 line spacing, with just 19 references — 9 of which are pre-prints or from the CDC’s in-house newsletter Morbidity and Mortality Weekly Report (MMWR) which means they are not peer-reviewed.
Any true believer in The Narrative(TM) could have written this in a few hours. To base the entire future of COVID-19 shots on this glorified undergrad term paper is madness …
The core argument of the briefing document is hilarious (or rather, it would be hilarious if it was not a plan to permanently institutionalize genocide and hide the evidence). In several places the FDA argues (colloquialisms mine):
1. These COVID-19 shots work great … Boosters too, total home run, the Israelis even have 10-weeks of data showing that they might help old people. What more evidence could you want?
2. Okay, well, it depends on what you mean by ‘work.’ These shots do not stop infection, transmission, hospitalization, or death, even though that’s why we licensed them. Any protection wears off fairly quickly, but It’s Not Our Fault(TM) because This Wily Virus(TM) mutates too fast and no one told us that it would ever mutate.
3. So these shots must be reformulated but we cannot possibly ask Lord Pharma to do proper clinical trials ever again because we already know that these shots work great (see point #1)!”
In short, the FDA argues that since there are time constraints, evaluation of effectiveness must rely on “measures other than actual health outcomes.” In other words, whether the shots actually lower your risk of severe illness, hospitalization and death will have no bearing.
The only measure they’ll take into account is whether or not the jab triggers a rise in antibody levels, which has never been proven to be beneficial. If anything, the increase in COVID antibodies actually increases your risk of infection. This also means that as long as antibody levels are through the roof, the death rate could be just about anything, because it’s not part of the safety equation.
Faith in Magic Has Officially Replaced Science
As noted by Rogers,38 “The ‘Future Framework’ is a plan to base the entire COVID-19 vaccine program on magical thinking rather than science.” Indeed, Dr. Deborah Birx recently confirmed that the whole vaccine push has been based in faith in magic.39
June 23, 2022, Birx answered questions from the House Select Subcommittee on the Coronavirus Crisis. Rep. Jim Jordan, R-Ohio, asked whether the government was lying or guessing when they stated that vaccinated individuals couldn’t catch or spread COVID. At first, she claimed she didn’t know, but when pressed, she replied, “I think it was hope that the vaccine would work in that way.”40
So, the government issued mandates and made unequivocal, absolute statements that were not allowed to be questioned because they HOPED the shots would work a certain way — all while insisting they were the ones following and trusting the science and anyone who questioned their logic was a dangerous nut job. Let that sink in. Hope is literally the diametrical opposite of science.
It’s an Insiders’ Plot
As explained by Rogers, the same old players are behind this brazen attempt to eliminate the need for clinical trials: CDC staffers, academics who are in the pockets of Bill Gates and the NIAID, the drug companies themselves and the World Health Organization. Rogers writes:41
“I did not understand until just yesterday (as I started to write this article) that this entire ‘Future Framework’ is actually coming from the WHO. The Bill & Melinda Gates Foundation is the biggest voluntary contributor to the WHO. So Gates is likely directing the play.
Gates requires that WHO use the McKinsey consulting firm so this is probably a McKinsey operation (and McKinsey also works for Pharma so this is a huge conflict of interest). As Naomi Wolf points out, the involvement of the WHO also raises troubling questions about the influence of the Chinese Communist Party over this process.
As far back as January, the WHO/Gates/McKinsey junta realized that these shots were terrible and so they decided to use that as an opportunity to seize even more power and control.
The WHO set up a Technical Advisory Group on COVID-19 Vaccine Composition (TAG-CO-VAC) to implement these Orwellian ‘Future Frameworks’ across the developed world to lower manufacturing costs for Pharma and avoid bothersome health data that might hurt profits. All the messaging we have seen from the FDA and leaked to the press was initially developed and released by TAG-CO-VAC.”
No doubt, we live in unprecedented, precarious times. Logic, reason, science and sanity itself has been tossed aside by those who claim the right to make decisions for all mankind. If the FDA goes forward with this “Future Framework” scheme, the only safe assumption is that COVID shots will become more and more dangerous.
Worse, we can expect other vaccines and drugs to be allowed on the market without clinical trials as well. It truly could change the science of medicine as we know it.
Of course the WHO also wants to seize control over health care worldwide, which would eliminate medical rights everywhere. It’s a nightmare scenario with no end in sight as of yet. All we can do is continue to push back, to inform ourselves, to speak out, share facts and data, and refuse to comply with unscientific recommendations based on little more than hope in fabricated conclusions.
Sources and References
- 1 PHMPT.org Pfizer Documents Released by FDA
- 2, 3, 5, 6, 7, 9 The Defender June 21, 2022
- 4 PHMPT.org 16.2.7.1 Adverse Events Legend
- 8 PHMPT.org 2.5 Clinical Overview for BNT162b2
- 10 The Defender June 15, 2022
- 11, 14 The Vaccine Reaction June 21, 2022
- 12 CDC MMWR April 29, 2022; 71(17): 606-608
- 13, 16 CDC MMWR March 18, 2022; 71(11): 429-436
- 15 FDA. Briefing Document on EUA amendment request for Pfizer-BioNTech COVID-19 vaccine for use in children 6 months […]. VRBPAC Meeting June 15, 2022
- 17, 20 SSRN June 23, 2022
- 18, 23 Robert Malone Substack June 22, 2022
- 19 The Daily Sceptic June 22, 2022
- 21 SPEAC October 26, 2021
- 22 Canadian COVID Care Alliance, More Harm Than Good
- 24 Jackanapes Substack June 16, 2022
- 25, 29 Paul Alexander Substack June 27, 2022
- 26 the New American June 27, 2022
- 27, 28 Steve Kirsch Substack June 25, 2022
- 30 Andrology June 17, 2022 DOI: 10.111/andr.13209
- 31 Expose June 26, 2022
- 32 Bloomberg June 21, 2022
- 33 Twitter Jikkyleaks June 26, 2022
- 34 SWPRS June 2022
- 35, 36, 38, 41 The Defender June 27, 2022
- 37 FDA Briefing Document June 28, 2022
- 39, 40 Daily Caller June 23, 2022
Twitter censors story of British mother who died after reaction to Covid vaccine

By Didi Rankovic | Reclaim The Net | July 4, 2022
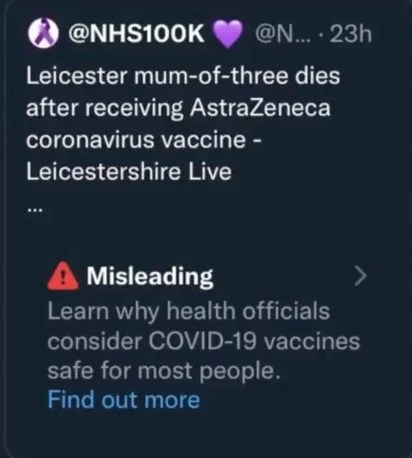
Three children in the UK were left without a mother after she died from a massive stroke determined to be caused by blood clots that formed after she received the AstraZeneca coronavirus vaccine, but Twitter is labeling conversations about this information taking place on the platform as “misinformation.”
Previously healthy Lucy Taberer, whose youngest is a five-year-old boy, succumbed to the consequences of the Covid shot 22 days after she was vaccinated. At first, the 47-year-old experienced mild side-effects, described in reports as common, to then develop a bruise, skin rash, and pain that the doctors at first dismissed as being caused by kidney stones.
In the end, it turned out that the victim’s reaction to the vaccine had been to develop blood clots that proved to be fatal.
Her death certificate reads that Taberer died of cerebral venous sinus thrombosis and vaccine-associated thrombosis with thrombocytopenia.
Local media, including Leicester Mercury, reported about it, and Taberer’s step daughter tweeted a link to the story, but was quickly shut down by Twitter, which labeled the post as “misleading.”
To add insult to injury, she was advised to click another link, provided by Twitter’s “fact-checkers,” that would “explain” why health officials think Covid vaccines are safe “for most people.”
Since the tweet about the woman’s death did not claim the vaccines were unsafe for most people, it remains unclear what logic drives Twitter’s censorship around the topic, other than the desire to stop any mention of the jabs in a negative context, whether true or false.
GB News reported on this, wondering if it wasn’t enough for a child to deal with the loss, but also “have to be insulted in their grief if they mention it on the internet.”
Host Mark Steyn noted that three guests who regularly appear on his show were among those awarded compensation after the UK government last week admitted Covid vaccines in some cases can be deadly. All three lost their loved ones to the vaccine.
But, he noted, social media have been slow (or not interested) in catching up, even as governments are starting to pay out compensation.
Our latest polls show twice as many people died from the vaccine as from COVID
These are third party polls. We don’t control the recipients. The people making the assessments of vaccine deaths are almost all people who took the shot.
By Steve Kirsch | July 3, 2022
Here are the last two external polls we ran:
Both show that the vaccine killed nearly twice as many people as COVID did.
The survey recipients are a broad cross-section of America and were selected by Pollfish.
For the Jun 30 poll, the numbers were 45 killed by the vaccine [Q16] vs. 23 killed by the COVID virus [Q18] and for the Jul 2 poll, the numbers were 38 [Q22] and 18 [Q24], respectively.
If the vaccines are safe and effective, how can they explain these poll results? This is objective poll data of the American people.
These are great polls to run past your blue-pill friends and have them explain it to you since they are the expert and you don’t know anything.
I predict silence from the medical community, the mainstream media, Congress, and the government agencies. Not even 60 Minutes is going to touch this data with a ten foot pole. Nobody will. They will just ignore it just as they have for my earlier polls.
Next step for us: run it against 5,000 people.
Warning: many people will die because of these COVID injections, many healthy children WILL die due to these shots…
“FDA, CDC, NIH, Moderna, & Pfizer secretly told me this”
By Dr. Paul Alexander | June 30, 2022
They said, follow the $CIENCE. Fauci said he is the $CIENCE.
I have been trying to warn. I have written on this here in stack. I try again.
Everything you have been told by government, by CDC, by NIH, by Fauci, by Birx, by Bourla, by Pfizer, by all your government officials, were lies, distortions, exaggerations, meant to mislead you. All pure lies on everything about lockdowns and these failed COVID gene injections. All, every single part was a lie. A deception. This entire COVID pandemic, was a lie! Yes, we had an emergency, but everything done to us the last over 2 years was a fraud hoax, a lie. Every single COVID policy failed. Canada, US, UK, everywhere.
The entire lockdown lunacy failed! All school closures failed, just killed children. Everything was a lie! They knew it would never work but knew one thing, that you as people, as the population, crazily thought, that they as health officials and medical doctors, wanted to do good by them and they could ‘trust’ you. You would do them no harm.
Little did they know. Little did we know the corruptible malfeasants we were dealing with. I include many medical doctors in this.
Trump was right when he early on said it was hoax. He did not mean the virus was a fraud or hoax. He meant the repose. The response was, and he saw what the deepstate and media, and CDC and NIH and Fauci and Birx were doing to him. But he could not stop them. He could, he could have, but he was weak. He then did the unthinkable. He allowed Fauci and Birx to lead a crazy lockdown lunatic policy that harmed and killed thousands of Americans. None of it worked! Not one!
You will come to learn, that 2.5 years of your life was taken away, for a lie! A greed, power drunk lie! By sick malfeasant people. Their motives. That must all be investigated and if it is shown they did this deliberately and caused deaths, we jail them all! Yes, 2.5 years lost to these malfeasants. The COVID injection is a failed ineffective dangerous injection.
I am no anti-vaxxer, but I am against these injections.
I was told by these officials (FDA, CDC, NIH, Moderna, & Pfizer), in confidential secret discussions, that in about 6 to 6.5 years from roll-out, in those who take the injections, they feared mass auto-immune disease and deaths, they feared viral immune escape and very problematic variants, and they anticipated constant deaths from the injections but a major number of deaths to emerge. I could not even understand exactly what they did for it was so haphazard, but these were officials. And they wanted to talk to me. To tell me ‘their truths’.
They said based on all they knew, that the COVID injections could never work, especially the mRNA platform. It never worked in the animal model and was pathological. They told me that in about 6 to 6.5 years, there will be a surge in deaths in persons who take the injections (then about 1 year ago). This was their projection. They advised me they nor their families will never (especially their children) take any of the COVID injections.
The key is the injection works for some people and I argue we do not know how long and what the effects are and this is what I was told. But you understand that too. You cannot take a 15 year process and boil it down to a few months and declare it is safe. They were never safety tested to exclude harms and deaths longer term. We do not know exactly what is coming. But it certainly does not work for a whole bunch of people. Look around, you know people who have been harmed by these injections and died. Do you not? Something is very wrong with these injections. Very wrong and they just will not stop.
I am being open with you to inform you. I am sick and tired, years now, of the lies and fraud and disaster put out by the media, the alphabet health agencies etc. You trusted your public health officials, you think ‘they care about you’, well, they never cared about you, your family, or the truth. It is to them about the $CIENCE.
I think I shared prior that my office was on the 6th floor of the HHS building in DC, Operation warp speed and Moderna were stationed on the 7th floor. FDA, CDC etc. have sub-satellite offices at HHS. At least when I was there and Hahn, Redfield etc. came there daily after congress or White House to see their staff, various persons, persons in various offices.
These people I talked with, came to me out of anger and fear too, they knew who I was and wanted to tell me their stories and how worried they were for the population, and fearful for their lives and own careers as to the COVID injections (and other issues). If they spoke out openly so had to talk secretly.
They were very very dismayed and angered and worried as to why the agencies they worked for e.g. FDA and NIH and CDC etc. and the pharmaceuticals were not properly regulating and conducting the proper safety studies, proper durations of follow-up. They felt the COVID injection program was a pure disaster and should be stopped back then. This is 6 months or so before roll-out. They felt no healthy children should ever be given the very injections they were working on. They were that concerned.
I want to be clear again, based on all I know today, based on what I was told, many many children will die due to these injections. Healthy children will die, not ‘if’, but ‘will die. Healthy children, healthy people, normal people never needed and do not need these injections. I have told you before that (strong research and scholarship by Geert) we will be in a pandemic for 100 years if we continue these injections. It is the COVID injection itself that is driving the variants and these CDC, NIH, Moderna, and Pfizer officials are malfeasants IMO who are continuing this. There is no sound justification. These malfeasants know that they are vaccinating with the Wuhan strain (legacy strain) that has been gone many months now and omicron dominates. The vaccinal antibodies are to the original Wuhan strain and will not hit the omicron spike antigen (original antigenic sin (OAS)).
It is the COVID injection (and consequent non-neutralizing antibodies pressuring the spike antigen) that is causing the vaccinated to become infected, hospitalized, and die. The data is clear. Massive antibody-dependent enhancement, some refer to this as antibody mediated viral enhancement. Some pathogenic priming. All IMO the very same. The recall antibodies are to something that does not exist today. The key is to reduce viral pressure, infectious pressure on the population, so that the sub-optimal injections have less virus to put under pressure. We have effective chemoprophylaxis, we can do this. We have early treatment. This can worked effectively and this can thus help reduce viral transmission. At the same time, the best step is to stop these filed injections.
I want all of these people investigated in proper public and legal inquiries, and if it is shown they did wrong, in proper inquiries, I want them arrested. I want all who made policy decisions that costed lives, to be jailed! All their monies taken!
Dr. Rogers looked at the FDA June 28th meeting and his takeaway is bang on and what we have been saying here for near a year now here:
‘‘Yesterday, the FDA’s Vaccines and Related Biological Products Advisory Committee approved a bivalent Covid-19 shot with the Wuhan strain and the Omicron variant.
The vote was:
19 yes.
2 no.
A few thoughts:
The Wuhan strain is no longer in circulation. So they are vaccinating against a strain that no longer exists.
The Omicron variant that they are going to put into this shot is Omicron BA.4/BA.5:
1. By the time it gets to market in the fall, Omicron BA.4/BA.5 will likely no longer be in circulation.
2. There is no efficacy data whatsoever on vaccines against Omicron BA.4/5.
3. There is no safety data whatsoever on vaccines against Omicron BA.4/5.
4. They do not intend to gather any efficacy or safety data between now and when these shots will be released in the fall:
At the meeting, the manufacturers (Moderna, Pfizer, and Novavax) were asked what their production timelines are… and they said out loud, “So long as we don’t have to provide any clinical data, we’ll have them ready by fall.”
Dr. Rogers is a smart guy.
His work:
Featured Video

HE SAVED LIVES. NOW HE FACES PRISON.
or go to
Aletho News Archives – Video-Images
From the Archives
NATO Sanctions and the Coming Global Diesel Fuel Disaster
By F. William Engdahl – New Eastern Outlook – 11.04.2022
Amid the ongoing global inflation crisis, NATO heads of state and mainstream media repeat a mantra that high energy prices are a direct result of Putin’s actions in Ukraine since end of February. The reality is that it is the western sanctions that are responsible. Those sanctions including cutting SWIFT interbank access for key Russian banks and some of the most severe sanctions ever imposed, are hardly having an impact on the military actions in Ukraine. What many overlook is the fact that they are increasingly impacting the economies of the West, especially the EU and USA. A closer look at the state of the global supply of diesel fuel is alarming. But Western sanctions planners at the US Treasury and the EU know fully well what they are doing. And it bodes ill for the world economy.
While most of us rarely think about diesel fuel as anything other than a pollutant, in fact it is essential to the entire world economy in a way few energy sources are. The director general of Fuels Europe, part of the European Petroleum Refiners Association, stated recently, “… there is a clear link between diesel and GDP, because almost everything that goes into and out of a factory goes using diesel.” … continue
Blog Roll
 Aletho News
- Trump meets Rodríguez near Maduro’s prison as Venezuela’s oil flows to US
- Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
- Iran FM meets with US envoy on UN meeting’s sidelines at American side’s insistence: Report
- Qatar PM calls for Gulf security framework with Iran, says war must be ‘wake-up call’
- China condemns US extortion of Iranian airlines, rejects Washington’s ‘illegal’ sanctions threats
- Italy to move military personnel from Taif base after missile strike
- Finland’s Stubb tells European leaders to calm down
- Defeating Russia on battlefield impossible – Fico
- Finland’s Gender Clinic Reversal
- Massachusetts Wants Mental Health Visits, Why Does Government Use ‘Health’ to Enter Our Homes & Families?
- If Americans Knew
- Sanctions are collective punishment: immoral and self-defeating
- Phosphorus Munitions Fired by Israel Burn Groves, Orchards in Southern Lebanon
- Israel Carries Out New Ceasefire Violations Across Gaza
- AI – Emphasis on the ‘I’: Israel Is Funding AI Chatbot Propaganda
- Israel Blocking Hundreds of Wheelchairs for Injured Children From Entering Gaza
- Israel Is Expanding and Upgrading Compounds for Palestinian Militias in Gaza
- The Palestinian-American Residents of This West Bank Town Are Wondering: Where Is Trump?
- Gaza desperately needs tents, wheelchairs, fuel… and everything else (Israel blocks it all) – Daily Update
- Israeli Attacks in Gaza Kill at Least Seven Palestinians Over Three Days, including Woman and Child
- Trump’s militarization of Washington DC as he pursues Israel’s war against Iran
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

