How the Medical Establishment Covers Up the Harms of Adding Fluoride to Drinking Water
By Robert Carnaghan | The Daily Sceptic | April 1, 2022
 The addition of a fluoride, such as hexafluorosilicic acid or disodium hexafluorosilicate, to public water supplies has been recommended in a joint statement by the four Chief Medical Officers of the U.K. The Government’s Health and Care Bill, which has reached its final stages in Parliament, includes a small section to facilitate water fluoridation, which is now expected to be spread throughout the U.K.
Although water is already fluoridated in a few parts of the U.K. (mainly Birmingham), for nearly forty years no new schemes have been implemented since local opposition has managed to defeat them all. The Government is now determined to impose its wishes.
A recent press release said that “higher levels of fluoride are associated with improved dental health outcomes”, and that the “Health and Care Bill will cut bureaucracy and make it simpler to expand water fluoridation schemes”. The Bill’s explanatory notes state: “Research shows that water fluoridation is an effective public health intervention to improve oral health for both children and adults and reduces oral health inequalities.”
For about 70 years it has been claimed that fluoridation reduces dental decay, and that it is safe. Although there is abundant evidence showing that in fact it is neither effective nor safe, the proponents of fluoridation have long had the advantage of far greater funding than that available to sceptics.
Trials of fluoridation started in 1945 in the U.S. and Canada but, before any had been completed, and without any comprehensive health studies, fluoridation was endorsed as safe and effective by the U.S. Public Health Service. The American Dental and Medical Associations soon added their approval, as later did their equivalents in the U.K.
The original trials were studied by Dr. Philip Sutton in Australia who graduated with honours in Dental Science. Asked to examine them, he found they were of low quality, full of errors and omissions.
In Austria, Rudolf Ziegelbecker also studied the original fluoridation trials and found they did not show what had been claimed. Professor Erich Naumann, Director of the German Federal Health Office, said of him: “Your results have been accepted everywhere in Germany with the greatest interest and have increased the grave doubts against drinking water fluoridation.” Prof. Naumann added: “It is regrettable that the existing data on water fluoridation had not been examined earlier using mathematical-statistical methods. Otherwise the myth of drinking water fluoridation would have already dissolved into air long ago.”
In the U.K., pilot schemes started in the mid-1950s in four areas, all of which sooner or later abandoned the practice: Andover (1955-58), part of Anglesey (1955-92), Kilmarnock (1956-62), and Watford (1956-89). In 1957, Dr. Geoffrey Dobbs wrote in New Scientist that they “are now officially described as demonstrations of the benefits of fluoridation, not experiments, so the results are a foregone conclusion” and their purpose quite openly “promotional”. He added that the studies would gain enormously in value if those responsible were willing to submit them to impartial scientific assessment.
When the UK pilot studies started, it was officially stated that they should include “full medical and dental examinations at all ages”, but no medical examinations were done, and neither short-term nor long-term possible harms were explored. This lack of concern continues, with a general failure in fluoridated countries to monitor fluoride exposure or side effects.
In 2000, a major report by the Centre for Reviews and Dissemination at the University of York concluded that, despite many studies over 50 years, “We were unable to discover any reliable good-quality evidence in the fluoridation literature world-wide”. Even among the 26 better studies on fluoridation and tooth decay, not one was evaluated as “high quality, with bias unlikely”.
In 2015, a Cochrane review added: “There is very little contemporary evidence, meeting the review’s inclusion criteria, that has evaluated the effectiveness of water fluoridation for the prevention of caries.”
When Israel ended fluoridation in 2014-15, partly because of health concerns, its Ministry of Health pointed out that WHO data indicated no significant difference in the level of tooth decay between countries that fluoridate and those that do not fluoridate.
A trial in Hastings in New Zealand was apparently so successful that it was widely reported as a classic case of the benefit of fluoridation, with tooth decay reduced by at least half. However, when New Zealand passed freedom-of-information legislation, two university researchers were able to access the original records, which revealed that the published results were fraudulent. One of those involved in running the trials was asked for an explanation but he did not even try to justify the published results.
Not only is there a great absence of good quality evidence that fluoridation significantly reduces tooth decay, there has, especially in recent years, been growing evidence that it is harmful.
In 2006, a major report by the U.S. National Research Council said that fluoride exposure is plausibly associated with neurotoxicity, gastrointestinal problems, endocrine problems and other ailments. It was also unable to rule out an increased risk of cancer and of Down’s syndrome in children.
In 2017, a team of experts in Chile, supported by the Medical College of Chile, concluded that fluoridation is ineffectual and harmful.
Fluoride occurs naturally in a few water supplies, but so does arsenic. A recent study from Sweden shows an increased prevalence of hip fracture in post-menopausal women associated with long-term exposure to natural fluoride at levels in water in the same range as used in some parts of the U.K. for artificial fluoridation.
About half a century passed before the declassification of hundreds of U.S. Government documents provided clues to the real reason for fluoridation. Much meticulous research by an award-winning investigative journalist, Christopher Bryson, resulted in his thoroughly documented book, The Fluoride Deception, showing beyond doubt the extensive fraud involved.
Bryson’s research revealed the strong connection between fluoridation and the Manhattan Project to create the first atomic bombs. Huge amounts of fluorine were used to extract the isotope of uranium needed. Workers suffered hundreds of chemical injuries, mostly from the gas uranium hexafluoride.
In 1943 and 1944, farmers reported workers made ill, crops blighted and livestock injured, with some cows so crippled they could not stand. When the war was over, farmers in New Jersey sued DuPont and the Manhattan Project for fluoride damage. In response the Government mobilised officials and scientists to defeat the farmers.
In 1946, the United States had begun full-scale production of atomic bombs, and the New Jersey farmers’ legal action was seen as a threat, because of the potential for enormous damages and a public relations problem, with more trouble likely if they won. The farmers’ legal action was blocked by the Government’s refusal to reveal how much hydrogen fluoride DuPont had vented into the atmosphere.
Dr. Harold Hodge defended the nuclear programme against the legal threat from farmers. He had the idea of calming the public’s fears by talking about the usefulness of fluorine in tooth health. In January 1944, a secret conference on fluoride metabolism took place in New York. Organised by President Roosevelt’s science adviser, James Conant, documents from it are among the first that connect the atomic bomb programme to water fluoridation and to the Public Health Service.
Manhattan Project scientists were ordered to help the contractors. They also played a prominent role in the fluoridation of the public water supply in Newburgh, New York, an experiment that began in May 1945. In 1947 the U.S. Atomic Energy Commission took over from the Manhattan Project.
Dr. Harold Hodge, the Project’s senior wartime toxicologist, became the leading promoter of fluoridation. He announced it was so safe that it would take a massive dose of fluoride to cause harm. (Some 25 years later, in 1979, he quietly admitted in an obscure paper that he had been wrong.)
A Committee to Protect Our Children’s Teeth was formed, with powerful links to U.S. military-industrial interests and their determined effort to escape liability for fluoride pollution. The aim was to transform the public image of fluoride from that of a dangerous pollutant to a beneficial prophylactic medicine.
This aim was achieved with the help of Edward Bernays, an expert in the use of psychological techniques to achieve “manipulation of the organised habits and opinions of the masses” and “the engineering of consent”. Bernays advised the avoidance of debate: fluoridation was to be presented as indisputably beneficial; only the ignorant could object to it.
Reviews of Bryson’s book included one in the scientific journal Nature, noting that he “raises the stakes by reporting a great deal of relevant and often alarming research”, and describing the book as “thought-provoking and worthwhile”.
Publishers Weekly wrote: “Bryson marshals an impressive amount of research to demonstrate fluoride’s harmfulness, the ties between leading fluoride researchers and the corporations who funded and benefited from their research, and what he says is the duplicity with which fluoridation was sold to the people.”
Chemical & Engineering News stated: “We are left with compelling evidence that powerful interests with high financial stakes have colluded to prematurely close honest discussion and investigation into fluoride toxicity.”
Bryson found that, while the American Dental Association had previously opposed fluoridation, it changed its tune after receiving a large donation from an industrialist with a stake in the commercial use of fluoride.
A study of workers at a chemical company in Cleveland was used to promote the idea that fluoride reduces tooth decay. It said workers exposed to fluoride had fewer cavities than those not exposed to it. The report helped to shift public opinion. The secret version of the report, discovered decades later, stated that most of the men had few or no teeth, and that corrosion affected such teeth as they had.
As early as 1951 a confidential gathering of State Dental Directors in the U.S. was advised by Dr. Frank Bull, “We have told the public it works, so we can’t go back on that”. If it was difficult then, it must be very difficult now for prestigious dental and medical organisations to admit that the assurances of effectiveness and safety they have given for so long were at best mistaken and at worst fraudulent.
Among the various methods used to suppress adverse evidence and dissent have been mocking, silencing, sacking and denigration of scientists who threatened the official story. One of the earliest to suffer was Dr. George Waldbott, an eminent U.S. physician who was viciously maligned after reporting fifty cases of people made ill by fluoridated water, as established by double-blind tests.
Dr. John Colquhoun, a former supporter of fluoridation in New Zealand, was Chief Dental Officer for Auckland when he discovered and reported that fluoride was damaging children’s teeth. This was not what the authorities wanted to hear and he was sacked.
Dr. William Marcus was Senior Science Adviser in the Office of Drinking Water in the Environmental Protection Agency. He was sacked when he warned that research by the famous Battelle Institute showed that some forms of cancer could be caused by fluoride.
Dr. Phyllis Mullenix was the Chief Toxicologist at the prestigious Forsyth Dental Center, who discovered that fluoride is a neurotoxin that can adversely affect the brain. Following publication of her peer-reviewed study, U.S. Government pressure resulted in her being sacked and the institute’s toxicology department closed.
Often those whose research gave results unfavourable to fluoridation found that medical journals were hostile. Dr. Albert Schatz was a co-discoverer of streptomycin, the first effective drug for tuberculosis. When he found that infants in Chile had much higher death rates in fluoridated areas he sent a report in 1965 to the editor of the Journal of the American Dental Association who returned it unread.
The reluctance of many medical journals to publish adverse findings on fluoride resulted in the foundation of the International Society for Fluoride Research and its quarterly journal Fluoride. However, MEDLINE, the bibliographic database published by the U.S. National Library of Medicine, declined to index the peer-reviewed journal’s contents.
Dr. Richard Foulkes chaired a committee that recommended fluoridation in British Columbia. Later, a friend urged him to do his own research, after which he changed his mind and said: “My initial belief was based on information given to me by those in authority rather than on the basis of my examination of the facts.”
Dr. Hardy Limeback was Head of Preventive Dentistry at the University of Toronto when in 1999 he apologised for having promoted fluoridation. “I did not realise the toxicity of fluoride,” he said. “I had taken the word of the public health dentists, the public health physicians, the USPHS, the USCDC, the ADA, the CDA that fluoride was safe and effective without actually investigating it myself”.
It used to be claimed that fluoride works on the teeth from within and therefore that pregnant mothers should take fluoride for the sake of unborn children’s teeth. Now it is said that fluoride’s main effect is from the outside (topical, not systemic). Therefore, there is no need to imbibe it.
Water fluoridation is a blunderbuss that hits far more than the intended target. About a third to a half of fluoride that is ingested remains in the body where it accumulates, not only in the teeth and bones but also in the kidneys, pineal gland and the cardiovascular system. Kidney patients are particularly at risk from fluoridation.
The dose of fluoride a person gets in water is haphazard since people consume widely differing amounts. Bottle-fed babies get very much more fluoride than breast-fed ones, and the American Dental Association conceded in 2006, with little publicity, that “using water that has no or low levels of fluoride” should be considered when preparing formula milk for infants. However, neither an ordinary water filter nor boiling can remove fluoride.
Recent research also finds that fluoride damages children’s brains. For example, studies show a loss of IQ and increased symptoms of ADHD in offspring when pregnant women are exposed to fluoride at doses commonly experienced in fluoridated communities in Canada.
Leading scientists concerned about fluoride’s toxicity, and willing to speak out, include Dr. Philippe Grandjean (Harvard University: “Fluoride is causing a greater overall loss of IQ points today than lead, arsenic or mercury”); Dr. Kathleen Thiessen (“The principal hazard at issue from exposure to fluoridation chemicals is IQ loss”); Professor David Bellinger (Harvard Medical School: “It’s actually very similar to the effect size that’s seen with childhood exposure to lead”); Professor Bruce Lanphear (“Fluoride exposure during early brain development diminishes the intellectual abilities in young children”); and Dr. Howard Hu (“Fluoride is a developmental neurotoxicant at levels of exposure seen in the general population in water-fluoridated communities”).
No less important is the fact that fluoridation is treatment without consent. People without the resources needed to obtain alternative supplies of water for drinking and cooking are chemically treated, in effect compulsorily.
For more information see Fluoride Free Alliance U.K., Fluoride Action Network and Stop Fluoridation U.K.
FDA Weighing Moderna Vax for Kids 6 and Under, But Experts Say Trials Inadequate
The Defender | April 1, 2022
Moderna last week said it will seek Emergency Use Authorization (EUA) for its COVID-19 pediatric vaccine, after announcing its two-dose regimen reduced cases of symptomatic disease by 43.7% in children 6 months to 2 years old and by 35.7% in children ages 2 to 6.
The company said its Phase 2/3 KidCOVE study of its mRNA-1273 in children “successfully met its primary endpoint.”
However, as Politico reported Wednesday, and as experts told The Defender, some doctors and scientists question whether Moderna’s clinical trial data will be sufficient for the U.S. Food and Drug Administration (FDA) to grant EUA for the vaccine.
Experts cited the trials’ low efficacy rates, small sample size and reliance on a research workaround called immunobridging as weaknesses that could hinder Moderna’s case.
“Given the other data that surrounds it, I don’t know that it’s a slam dunk that the FDA will move forward in terms of releasing it for emergency use,” Peter Hotez, professor of pediatrics and molecular virology and microbiology at the Baylor College of Medicine, told Politico.
“We’re still learning about the relationship between virus-neutralizing antibodies and effectiveness,” Hotez said, adding the FDA might need to raise its standards.
Experts also raised questions about the risk-benefit ratio of the COVID vaccines for an age group with a statistically insignificant risk of severe illness.
The FDA recently tabled Pfizer’s petition for EUA of its pediatric vaccine for infants and children 6 months to age 5, citing insufficient data on a third dose for children 2 to 4 years old.
Small trials hide injuries, experts say
Moderna’s trial was designed to analyze the safety, immunogenicity and tolerability of two vaccine doses in healthy children who were administered two 25-microgram doses 28 days apart, according to Clinical Trials Arena.
The sample size was small. Approximately 6,700 children were enrolled in the trial’s 6-and-under age group, including about 4,200 children between the ages of 2 and 6 and 2,500 children between 6 months and 2 years.
The trial also encompassed children in the 6- to 12-year-old age group, bringing the total to nearly 11,700 children.
According to Dr. James Campbell, professor of pediatrics and physician-scientist at the Center for Vaccine Development and Global Health at the University of Maryland School of Medicine, adult vaccine trials typically look at larger sample sizes.
Campbell, who tackled dosage studies for children for the Moderna study, said, “Instead of having 30,000 to 45,000 people — half who get the vaccine and half the placebo — we’re enrolling more like a few thousand in each of these age groups.”
Toby Rogers, Ph.D., an expert in statistics and how they relate to vaccine trials, told The Defender that 6,700 participants makes for an undersized trial.
“Researchers would call this ‘intentionally undersized to hide harms,’” Rogers said. “And this is a standard trick that pharmaceutical companies do.”
For the Moderna study, there were about 3,350 participants each in the treatment and placebo groups. An adverse event such as myocarditis might happen one out of 5,000 times, Rogers said.
“If you have only 3,300 in the treatment group, you are unlikely to see that particular harm in the clinical trial,” he said. “And, if you do see it in the treatment group, the company has ways to kick that person out of the trial.”
Rogers added:
“Say you experience myocarditis and you call the hospital at midnight and get in the car and go to the hospital, you get kicked out of the trial because you are breaking their protocols. They want you to call their doctors and not the hospital. They do that pretty regularly.”
In context, trials for the polio vaccine had a million participants.
“And now we have trials that are coming in with just a few thousand participants. It’s bad faith. This is just the tip of a large iceberg,” Rogers said.
Moderna trials show vaccine fails to meet FDA 50% efficacy standard for EUA products
Moderna’s claim that two shots of its vaccine reduced cases of symptomatic disease by 43.7% in children 6 months to 2 years old and by 35.7% in children ages 2 to 6 means the vaccine falls below the FDA’s 50% efficacy threshold for EUA products.
“No one would argue that 40 percent protection is great,” Dr. Chandy John, a pediatrician at Indiana University, told The Atlantic.
According to Politico, Moderna officials said the regimen met a metric called immunobridging, meaning the pediatric doses produced the same immune response that’s been seen in young adults.
Bridging studies are used in lieu of duplicating large-scale efficacy trials. Researchers extrapolate efficacy results from one population to predict drug efficacy in another population, according to Bernard Fritzell in a paper published in Developing Biological Standards.
In practice, using immunobridging means that pediatric vaccine researchers looked at an older group from a previous trial, who received a different dose of a vaccine with different ingredients, and decided what level of antibodies in that group were enough to ward off COVID.
They then looked at the younger children’s group to see how many of those participants had that same level of antibodies — a process that is not predictive of an individual’s ability to fight off infections, Rogers said.
Rogers added:
“So moving forward, into this mythical future, we predict that this many kids with antibodies will be protected. If this was a legitimate way to do science, you’d never have to do clinical trials in kids, because you could just immunobridge from any population under the sun whenever you wanted to. If you get a clinical trial with zero effect, you are going to finesse it with immunobridging.”
Dr. Meryl Nass, an internal medicine physician with expertise in anthrax and bioterrorism and member of the Children’s Health Defense (CHD) scientific advisory committee, also criticized the practice.
“The term ‘immunobridging’ is simply a fancy way of saying we are going to use antibody titers instead of actual cases of disease prevented as our benchmark,” Nass told The Defender.
“And we will compare the antibody level in one age group to that in another, and if they are comparable, we will say the vaccine works in the new age group,” Nass said.
Nass said the FDA began accepting surrogate markers of efficacy in vaccines years ago for vaccines intended for rare conditions in which there were not sufficient cases to determine actual efficacy in the real world.
Nass said:
“This is simply not the case with COVID. There is plenty of COVID going around. For Moderna to claim the FDA should authorize its vaccine in babies and preschool children because the vaccine led to high antibody levels, when its real-world efficacy (and only against mild symptoms) was only 40% is a bad joke.
“The efficacy level tells you that antibody levels are a poor surrogate for efficacy and should therefore be ignored. Other parts of the immune system contribute to immunity besides neutralizing antibodies.”
Dr. Elizabeth Mumper, pediatrician, CEO of The RIMLAND Center and member of CHD scientific advisory committee, echoed Nass’ concerns.
“Emergency Use Authorization typically demands a 50% threshold of efficacy for approval,” said Mumper.
“Here, Moderna tries to get around their less-than-50% efficacy results by using a concept called immunobridging, meaning to show that children develop the same immune antibody response as young adults,” Mumper said.
“However, there are problems with assuming antibody response numbers correlate with clinical outcomes.”
Moderna also admitted its study was unable to assess the vaccine’s efficacy against severe disease, hospitalization or death for ages 6 and younger, as participants’ infections were mild or moderate.
The only adverse events the study reported were fevers — 15% of children had fevers higher than 100.4 degrees and 1 in 500 experienced a fever higher than 104 degrees.
Moderna did not disclose if any of the children who participated required hospitalization as a result of the fevers. It did reveal that adverse reactions were more frequently reported after the second dose.
Trials’ short duration, plus evolving variants raise questions
Critics also cited the study’s short duration, though Moderna said it will continue to monitor its participants for 12 months.
“Long-term adverse effects of the vaccine remain an open question,” said Stephanie Seneff, Ph.D., senior research scientist at MIT’s Computer Science and Artificial Intelligence Laboratory.
“Are we prepared to booster children every three or four months, since the protection from the vaccine is short-lived?” Seneff asked.
The Omicron variation affected the Moderna’s efficacy rates in children, an outcome the company claimed was “as expected.”
But the fact that the virus continues to mutate at a fast rate and the fact that kids 6 and younger are at low risk from COVID makes the vaccine’s use in healthy children questionable, Hamid A. Merchant, subject leader in pharmacy at the University of Huddersfield, UK, said in the Journal of Pharmaceutical Policy and Practice.
Merchant said:
“Currently deployed COVID vaccines were designed using the variant that was prevalent in early 2020 and the virus has significantly mutated since then; the breakthrough cases from [the] recent Omicron outbreak is a good example of the rapidly evolving nature of this virus.”
Research in the UK indicates more than 85% of children ages 5 to 11 years have already contracted COVID and have acquired natural immunity, Merchant added.
Kids at low risk of severe disease
Politico reported that even though the 5-and-under age group was more likely to be hospitalized for Omicron, children in this age group account for only 0.1% of the deaths from COVID and 3% of COVID cases in the U.S., according to CDC’s own data.
“According to data from most countries, practically no children under the age of 5 have died from COVID,” Nass said. “In the UK and Wales, over two years of the pandemic, only one child without comorbidities (a chronic illness) died from COVID.”
Nass added:
“While CDC claims over 1,000 children have died with COVID, CDC responded to a FOIA request from Informed Consent Action Network that it does not collect and analyze data on healthy children who have died from COVID in the U.S.
“This is hard to believe, but since the New York Times revealed that CDC hides the bulk of the data it collects on COVID, in part to avoid providing tinder to ‘antivaxxers’ regarding poor vaccine efficacy, it may be that CDC did in fact choose not to look at such data.”
A Johns Hopkins’ study that monitored 48,000 children under 18 who were diagnosed with COVID showed there were zero deaths in those without comorbidities. Another study in Nature came to much the same conclusion.
“Infants and toddlers do surprisingly well with Omicron,” Mumper said, adding:
“We know they have fewer ACE2 receptors in their noses, which may be protective. We know they have cross-protection from other infant viruses. We know the jab-generated B cell-specific spike protein antibody response is a very specifically targeted response, and not as broad as the natural symphony of well-orchestrated immune responses children usually mount.”
Rogers this week wrote the harms from COVID vaccines are catastrophic, and benefits are questionable:
“There are now 44,975 [Vaccine Adverse Event Reporting System] reports of adverse events in children following Covid shots, a few of which led to deaths. These reports likely understate harms by a factor of 41 to 100.”
Nass also called out the issue of risk versus benefit for the young age group:
“If we are vaccinating kids to protect grandma, which a Moderna official suggested, it should be noted that that is not considered ethical under U.S. law. You cannot vaccinate kids, and have them take a risk for a marginal benefit to themselves because you are hoping to provide a great benefit to adults.”
Apparently, the majority of parents agree. The Hill reported only 25% of children ages 5 to 11 are vaccinated, even though the FDA authorized vaccines for their age group last October.
“I hope the FDA holds Moderna’s feet to the fire and demands very robust results,” Mumper said.
“The basic concept is: First do no harm. If a baby’s background risk with COVID is not significantly changed by an mRNA jab, then the shot is not justified. If the jab just prevents mild to moderate infections, is it necessary or desirable?”
In Australia, doctors are now being warned they “are obliged to” follow public health messages
EVEN IF THOSE MESSAGES CONTRADICT INDEPENDENT RESEARCH ON WHAT IS BEST FOR PATIENTS
By Alex Berenson | Unreported Truths | April 2, 2022
Australia’s march toward medical authoritarianism continues.
Doctors are now being told they could face discipline for saying anything that contradicts “public health messaging,” even if what they are saying is “evidence-based.”
They may even face investigations for “authoring papers” that health authorities do not like.
Unfortunately, I am not exaggerating.
Like all physicians, Australian doctors can face disciplinary investigations for medical errors or other problems. In Australia, those investigations are called “notifications,” a nicely Orwellian euphemism. Ahpra, the Australian Health Practitioner Regulatory Agency, oversees them.
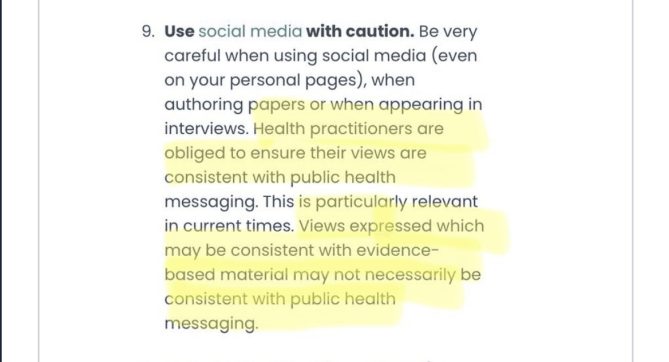
On Feb. 28, a big Australian medical insurer warned physicians that to avoid Aphra notifications, they needed to “be very careful” not to contradict “public health messaging” in social media comments.
But the warning – although first mentioning social media – went even further. It also warned against “authoring papers” that contradicted the authorities’ favored views.
SOURCE
Further, even “views… consistent with evidence-based material” could lead to problems if they contradicted “public health messaging.”
The warning came from the Medical Indemnity Protection Society, which provides professional insurance coverage for doctors. Although these insurers do not speak officially for government agencies, doctors effectively cannot practice without professional insurance, so their pronouncements are powerful.

In other words, only a very brave physician in Australia would consider offering advice that’s not “consistent with public health messaging” anytime soon.
No worries, though, the public health authorities know best!
The Remarkably Surprising Results of Ending Mask Mandates
A number of states have recently lifted mask mandates after months or years of forced masking – so what’s happened afterwards?
By Ian Miller | March 31, 2022
During the pandemic, an endlessly repeated phrase from experts, media members, politicians and social media pundits has been that it’s “too soon” to lift restrictions.
It’s important to deconstruct the intentions encapsulated in that phrase, because it’s remarkably pernicious.
The implication of the infuriating phrase, “it’s too soon to lift restrictions,” is that restrictions were proven to have had a demonstrable impact on the spread of COVID, which is entirely inaccurate. It also implies that restrictions should be considered necessary or valuable for a virus which will likely infect everyone on earth, possibly multiple times throughout their lifetime.
There’s also the unspoken assumption that restrictions are imposed at no cost; that masking kids in schools, for example, has little to no downside with significant benefits.
The “evidence” used by health officials to justify continued mask mandates has consistently been unbelievably flawed and thoroughly debunked.
We’ve seen the results of masking across the general population and in specific populations:
By pretending that mask mandates ever had any evidentiary basis, that the “benefits” will always outweigh the harms, while ignoring the inescapable reality that COVID will infect essentially everyone regardless of policy, the phrase that it’s “too soon” is profoundly ignorant and extremely disturbing.
Even now, as the Los Angeles City Council voted to end the vaccine requirement for many businesses, they have already set the stage for future mandates:
“I know it feels like we’re out of the woods. It feels like we’re all going back to normal. But there’s new variants and new strains all the time,” he said. “This BA.2 (variant) is spreading and we really don’t know what the variant a month from now or two months are.”
Martinez responded last week by saying, “I agree with you on that,” and noted that the City Council would have to revisit the vaccination mandates “as we learn to live with this pandemic unfortunately.”
Of course, Martinez ignores the unequivocal, inarguable fact that the vaccine mandates and passports in Los Angeles he’s advocated for had zero impact whatsoever on the rate of spread.
NY Times Latest to Mislead Public on New Ivermectin Study
The NEJM study chose a much lower dose, 400mcg per day for only three days, less than half the total dose that has been shown to be effective
By Madhava Setty, M.D. | The Defender | March 31, 2022
The New York Times on Wednesday sent an email blast to subscribers with the subject line: “Breaking News: Ivermectin failed as a Covid treatment, a large clinical trial found.”
The Times was referring to a study I wrote about, that same day, for The Defender.
My article called out the Wall Street Journal for its March 18 reporting on the same study — before the study was even published — for its failure to provide an accurate, critical assessment of the study.
The study in question — “Effect of Early Treatment with Ivermectin among Patients with Covid-19” — was officially published Wednesday in the New England Journal of Medicine (NEJM).
In it the authors concluded:
“Treatment with ivermectin did not result in a lower incidence of medical admission to a hospital due to progression of Covid-19 or of prolonged emergency department observation among outpatients with an early diagnosis of Covid-19”
The Times did not critique the study itself, but quoted the opinion of Dr. David Boulware, an infectious-disease expert at the University of Minnesota:
“There’s really no sign of any benefit. Now that people can dive into the details and the data, hopefully that will steer the majority of doctors away from ivermectin towards other therapies.”
Yes. Let us dive into the details and the data and see where it “steers” us, shall we?
A closer look at the details
The NEJM study took place in Brazil between March 23 and Aug. 6, 2021.
The study examined 1,358 people who expressed symptoms of COVID-19 at an outpatient care facility (within seven days of symptom onset), had a positive rapid test for the disease and had at least one of these risk factors for severe disease:
- Age over 50
- Hypertension requiring medical therapy
- Diabetes mellitus
- Cardiovascular disease
- Lung disease
- Smoking
- Obesity
- Organ transplantation
- Chronic kidney disease (stage IV) or receipt of dialysis
- Immunosuppressive therapy (receipt of ≥10 mg of prednisone or equivalent daily)
- Diagnosis of cancer within the previous 6 months
- Receipt of chemotherapy for cancer.
Young and healthy individuals were not part of this study.
Both vaccinated and unvaccinated individuals were included in the study. The percentage of vaccinated participants in each group was not specified. Note that by choosing not to identify vaccination status as a confounding variable the authors are implying that vaccines are playing no role in preventing hospitalization.
The 1,358 subjects were divided into two equally sized groups that were relatively well-matched and randomized to receive either a three-day dose of placebo or a three-day course of ivermectin at 400 mcg/kg.
The primary outcome was hospitalization due to COVID-19 within 28 days after randomization or an emergency department visit due to clinical worsening of COVID-19 (defined as the participant remaining under observation for >6 hours) within 28 days after randomization.
How researchers were able to conclude ‘no benefit’ despite signs to the contrary
The study’s authors wrote:
“100 patients (14.7%) in the ivermectin group had a primary-outcome event (composite of hospitalization due to the progression of COVID-19 or an emergency department visit of >6 hours that was due to clinical worsening of COVID-19), as compared with 111 (16.3%) in the placebo group (relative risk, 0.90; 95% Bayesian credible interval, 0.70 to 1.16).”
In other words, a greater percentage of placebo recipients required hospitalization or observation in an emergency department than those who received Ivermectin.
The authors of the study broke it down by subgroups here:
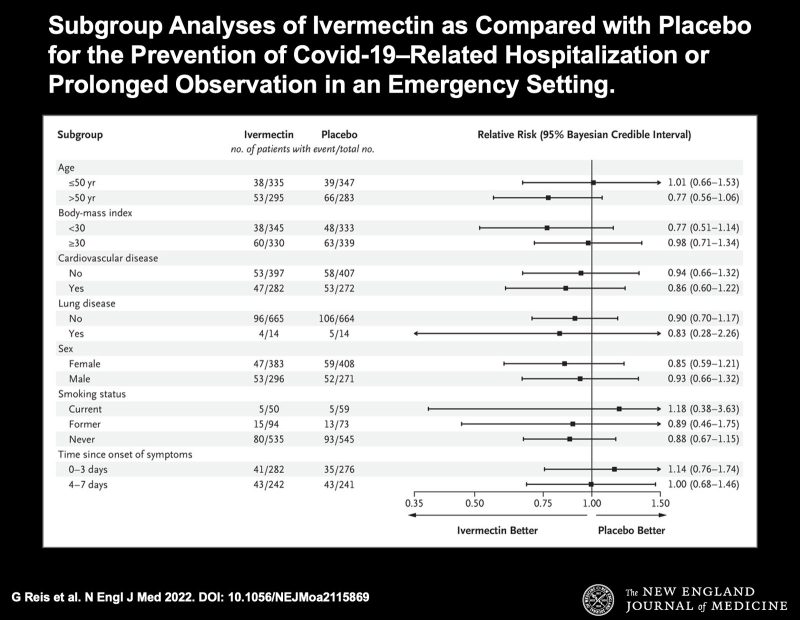
As is demonstrated in nearly every subgroup, the Ivermectin recipients fared better than those who received the placebo.
However, these data were not statistically significant given the size of the study.
This is how the authors were able to conclude there was no benefit to ivermectin use in preventing hospitalization in high-risk patients in their study.
Patients were under-dosed, some didn’t follow instructions
As it stands, the study The New York Times and The Wall Street Journal declared as proof of the uselessness of ivermectin in treating COVID-19 is actually quite promising — contrary to what their headlines told readers.
The dosing protocol advised by the Frontline COVID-19 Critical Care Alliance (FLCCC) includes a five-day course of ivermectin at 600 micrograms per kilogram of body weight for people with risk factors such as those possessed by participants in the study.
Instead, the investigators behind the NEJM study chose a much lower dose, 400mcg per day for only three days. This represents less than half of the total dose that has been shown to be effective in practice.
Furthermore, despite acknowledging that studies have shown some indication that the bioavailability of ivermectin increases when taken with food, especially a fatty meal, participants in the trial were instructed to take the medicine on an empty stomach.
In other words, the patients were significantly under-dosed — and yet a positive effect of the drug was emerging, though not statistically significant given the size of the study.
Also of note, the investigators chose to include emergency room visits with hospitalizations for COVID. Clearly, six hours of observation in an ER is a significantly different outcome than a hospitalization that may last a night or much longer.
When excluding the ER visits from the primary outcome and examining only hospitalizations, the ivermectin cohort had even less risk of an outcome, i.e. the relative risk was 0.84 vs 0.9 when ER visits and hospitalization were grouped together.
Perhaps the most glaring deficiency of the study is the low number of placebo recipients who actually followed the study’s protocol:
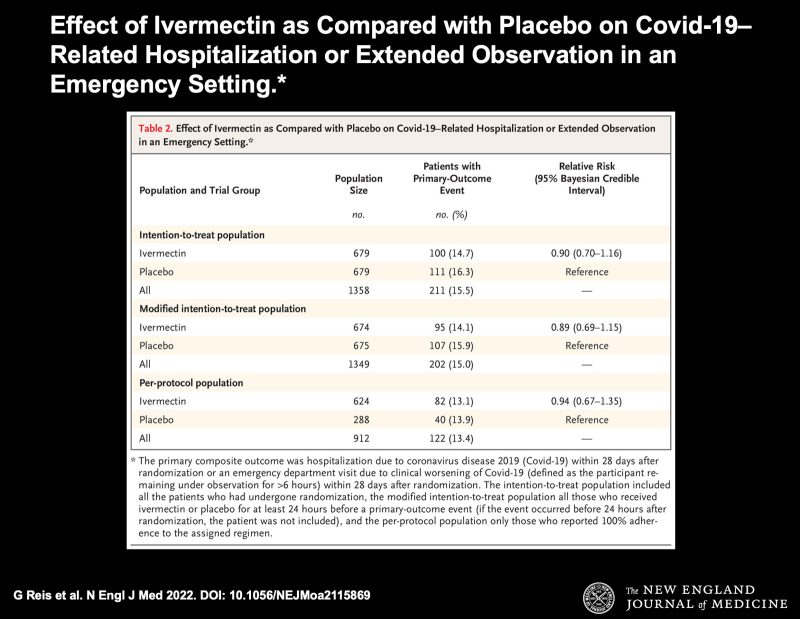
Only 288 of 679 participants randomized to receiving the placebo reported 100% adherence to the study protocol. Nearly 400 didn’t.
Why not? We asked Dr. Meryl Nass, an internist and member of the Children’s Health Defense scientific advisory committee.
Nass told The Defender :
“Presumably they knew the difference between ivermectin and placebo, and the placebo subjects went out and bought ivermectin or something else … but whatever they did, they didn’t bother with the pills they were given.
“So, it was not actually a double-blinded trial. Yet the 391 people who didn’t take the placebo but did something else were included in two of the three calculations of ivermectin efficacy anyway.”
So, was this the definitive answer proclaimed by mainstream sources? Nass thinks otherwise:
“I would say that instead, it was a failed trial due to the 391 placebo recipients who admitted they did not follow protocol versus the 55 in the ivermectin arm.”
More questions than answers
Rather than pounding the final nail in the coffin around ivermectin’s utility in treating COVID, the NEJM study raises more questions.
- What would the effect have been if a higher dose shown to be effective were administered?
- What would be the benefit of this medicine in patients with no risk factors?
- How statistically significant would the results have been if more participants were enrolled?
- Why weren’t more participants enrolled as the study progressed given the emerging benefit of the drug and the absence of adverse events?
- Why did the investigators define a primary outcome with such different real-world implications (ER visits vs hospitalizations)?
- With less than 50% of the placebo arm adhering to the study protocol, why were their outcomes included in the analysis?
- What effect did vaccination status have on outcome? If this is the primary means endorsed to prevent hospitalization, why wasn’t vaccination status mentioned as a confounder?
- Did the investigators choose to limit the study as it became clear that an Ivermectin benefit would be too big to ignore?
Given these obvious issues with the study, it is becoming even more clear where the real story is: Neither The Wall Street Journal or The New York Times are willing to pursue startling details around how corporate interests are corrupting scientific opinion as reported here.
Instead, these iconic journals chose to report on a scientific study on or prior to the day of publication using misleading headlines backed up by flimsy investigations conducted by journalists with no capacity to dissect the analysis or data.
Here’s a bigger question: Are they incompetent, or complicit, too?
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
The Guardian Rewrites the Facts
By Will Jones | The Daily Sceptic | March 31, 2022
The Guardian has been running a series to mark the second anniversary of the first U.K. lockdown called “Rewriting COVID-19”, billed as examining the “narratives and received wisdom of the first two years of the pandemic”. It aims to ask “experts what we’ve got wrong and how to move forward”.
“Rewriting COVID-19” seems an apt title, with one contribution, from anthropologist Devi Sridhar, criticised for literally rewriting the history of the pandemic by claiming she only advocated Zero Covid before the vaccines arrived, when she is on record promoting it subsequently.
Despite the Guardian saying the series is about asking “experts”, it begins with a scurrilous piece by science journalist Debora MacKenzie, proclaiming, “False narratives about Covid left us with millions of deaths.” Criticising lockdown scepticism as “libertarian” (boo, hiss!), MacKenzie argues: “Infectious disease is always profoundly collective, whether or not leaders find that ideologically congenial… The many people whose age or medical condition makes them more likely to die if [infected], or who have suppressed immunity – perhaps only because they need an arthritis drug – cannot take ‘personal responsibility’ for avoiding Covid if they must return to the office, surrounded by maskless people exercising their ‘individual freedom’ to exhale asymptomatic Omicron.” According to Ms. MacKenzie, then, we must all change the way we live forever in case we inadvertently infect others with our asymptomatic bugs. But don’t worry, if we all wear masks then no one will get infected!
One expert who has contributed is Dr. William Hanage, Professor of the Evolution and Epidemiology of Infectious Disease at Harvard University. It’s not a great start, however, when he cites a figure of 160,000 U.K. pandemic deaths, even though the number of excess deaths during the pandemic is more like 133,000 (a figure which includes collateral deaths). He also claims herd immunity has “stubbornly failed to arrive and expel the virus from the population”, despite that being, as he should know, a caricature of what scientists say about herd immunity.
It’s what he says next, however, that puts his dogmatism really on show.
It should be astonishing given these facts, but some stubborn voices have continued to argue that in the autumn of 2020 we should have rushed to remove restrictions on all except those most at risk – who would be somehow saved by untested, implausible means gathered together under the heading of ‘targeted protection’. At that point no vaccines were widely available, and the effective therapies we now have against Covid were pie in the sky. Shockingly, there are now attempts to rehabilitate these ideas in parts of the media. Reaching back to relitigate such already-discredited approaches is nonsense. And worse, it makes reasonable discussions about pandemic management that much harder. Distraction has always been the goal of such revisionism.
It’s a bit rich to criticise focused protection as untested and implausible when the lockdown measures he is promoting are themselves untested – and now that they have been implemented have shown no overall benefit or effectiveness.
Although he implies he wants “reasonable discussions about pandemic management”, he shows no sign himself of pursuing that, as he writes off any scepticism of Covid restrictions as beyond reasonable debate. He implies that relaxing restrictions before vaccines were available was not a “reasonable” position to take as it was “guaranteed to lead to more preventable transmission, more serious illness, more hospitalisations and more deaths”. This is despite it being shown repeatedly that Covid waves rise and fall whether or not restrictions are in place, with Sweden demonstrating this in spring 2020 and Florida – which from autumn 2020 adopted the focused protection approach Professor Hanage rails against – having no worse a winter than those places which locked down hard. Why is a Harvard professor of epidemiology dismissing out of hand the ‘reasonableness’ of the evidence from Florida in the winter of 2020-21?
Professor Hanage states that Omicron BA.2 is mild enough to be “readily handled by the great majority of vaccinated folks” – implying it isn’t readily handled by the great majority of unvaccinated people, which is clearly misleading.
Having found a scientist willing to write meanly and intemperately about those who disagree with him, the series falls back on its science journalists. (To be fair, it also includes a contribution from Professor Danny Altmann of Imperial College London, saying the vaccines are not much cop and seem to cause original antigenic sin – which is surprisingly off-narrative.)
Science journalist Laura Spinney attempts a heroic defence of Zero Covid – though seems to undermine her own argument by conceding that you “need a plan B in case the context changes”. This might seem fatal for the argument, as of course the context always changes (you can’t live in a hermit kingdom forever), but Spinney instead blames the ultimate failure of Zero Covid on “other countries” which “let the virus rip”. If only everyone had done Zero Covid, it would have just gone away.
Reciting the Zero Covid article of faith, “The virus deprives us of liberty; the efforts preserve it,” she insists these “efforts” don’t necessarily mean lockdown, but merely “mass testing plus isolation of the infected, ventilation, masking, distancing” – failing to recognise that such measures, even without stay-at-home orders and business closures, are economically and socially crippling, rendering normal life and many activities unviable or prohibitively unpleasant.
It’s no surprise to find Spinney is no fan of cost-benefit analyses when it comes to pandemics, claiming it is “pointless… to cost elimination, or any other containment strategy”. “How do you measure what it has saved you,” she asks, in a misplaced rhetorical question. “In speculative fiction terms, what’s the counterfactual?” I’d suggest, countries which didn’t do these things, and earlier pandemics where we didn’t panic and overreact, which show clear benefits to keeping calm and carrying on.
At one point she claims that “non-pharmaceutical interventions” “stop transmission completely” – has she been following any of the data or studies these past two years? – and lines up countries which are “abandoning” such restrictions as responsible for the rise of hypothetical “more severe” new variants. Whatever the problem, it’s always the fault of the countries which didn’t impose more severe Zero Covid measures.
Not so much rewriting Covid, then, as rewriting the facts. So much for them being sacred.
Featured Video

Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
or go to
Aletho News Archives – Video-Images
New Book
Trans agenda is ‘normalization of sadism’ – US author

RT | September 23, 2026
The US Democratic Party has embraced a transgender agenda that amounts to “the normalization of sadism,” author A.J. Rice has said, warning that radical trans policies would return if the party is allowed to regain power.
Speaking to RT’s America First host Scotty Nell Hughes about his new book, ‘The Curse of the Bearded Lady: How the Trans Mafia Whacked American Sanity’, Rice argued that activists have gained significant influence in schools, medicine, and corporate America while people who questioned the agenda have faced pressure to stay silent.
The author described the “trans mafia” as the sprawling network of people and institutions that have helped the movement gain influence. He singled out parts of academia, wealthy backers, and corporations, and stated that providers of transition-related treatment also have a financial incentive to keep young people in their care indefinitely.
Rice argued that the consequences of these policies ultimately fall on children who are being drawn toward gender-affirming medical treatments and on girls who are expected to share locker rooms or compete in sports with biological males.
He noted that while voters rejected the Democrats’ approach to gender in 2024, the party, which has been “captured by madness,” has since only doubled down and is seeking what is effectively “the normalization of sadism.” … Full report
Blog Roll
 Aletho News
- ‘We don’t seek permission to defend our country’: Snippets from President Pezeshkian’s UNGA address
- NATO chief wants Europeans to fight American wars [for Israel]
- German chemicals giant reveals details of downsizing
- Refaat Al-Areer Was The Canary In The Coal Mine In Israel’s War On The Truth
- Israeli election committee bars candidate from Knesset race over Gaza war opposition
- French-Lebanese man files war crimes complaint over Israeli attacks
- Mahan Air Flight Lands in China Despite US Threat against Iranian Airlines
- US eyes $10bn fund to rebuild war-battered Gulf infrastructure
- Trump meets Rodríguez near Maduro’s prison as Venezuela’s oil flows to US
- Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

