Increased energy prices could “cause heart attacks and strokes”
In the middle of the cost of living crisis, the press has found yet another reason people might keel over… and it’s still not the vaccine.
By Kit Knightly | OffGuardian | February 5, 2022
Our UK readers will be familiar with the press coverage of the cost of living crisis in this country, as wages continue to fall further and further behind inflation, and the economy reels from the deliberately devastating lockdown, the cost of everything from food to fuel is ever increasing.
People are understandably troubled and anxious, whether or not the energy cost crisis is genuine or manufactured for the sake of profits, the reality is that many people will face the choice of heating their homes or eating enough food over the last two months of winter and into the spring.
This could easily result in people – especially the elderly or disabled – suffering health problems or even death due to the cold or malnutrition. Many of these people will likely become “covid cases” or “covid deaths” once they’re subjected to the totally unreliable tests.
It’s all a perfect little circuit. And it serves the Covid agenda in more ways than one, because it’s just handed the press yet another explanation for heart attacks that haven’t happened yet.
It seems like only a few days ago we ran an article pointing out all the numerous different reasons the press are predicting people will have heart attacks this year… and that’s because it was.
Stress, anxiety, the weather, “long covid” and a plague of undiagnosed aortic stenosis are all predicted to cause thousands upon thousands of heart attacks and strokes in the near future.
And now so is the increased cost of living.
Appearing on Lorraine on ITV yesterday morning, Dr Amir Khan claimed:
… if you can’t afford to heat your home, it actually causes an increased risk of developing heart attacks and strokes because your blood vessels contract to conserve heat, which pushes your blood pressure up, and over time that has an impact on your heart attack risk.”
In future, maybe they should simply run press releases saying “Covid vaccine only thing in world which doesn’t cause a heart attack”
As Neil Oliver pointed out on Twitter…
How the Biomedical State Maintains the ‘All the Experts Agree’ False Consensus

The Daily Bell | February 4, 2022
We’ve previously explored the mind-numbing “experts say” mantra that the corporate media parrots non-stop. Talking heads incessantly implore the peasant class to “respect the science.”
The purpose is to create a mirage of consensus in order to discourage real journalists or normal people from looking into matters themselves. This tactic is pervasive, but nowhere has it been more widely employed than in the COVID era.
Because, if three key facts were permitted to infect the public consciousness, they would inevitably result in mass upheaval of the ruling class that perches on top of society, feeding on it like vultures:
- A.) the original virus almost certainly escaped from a Wuhan lab (if it wasn’t purposely released; let’s not underestimate the hubris of the biomedical state). Worse, that leaky Chinese lab relied on funding from the United States National Institutes of Health (funneled through a “non-profit” called EcoHealth Alliance) to perform dangerous gain-of-function research on bat coronaviruses.
- B.) The vaccines (which are actually mRNA gene therapies) do not work to prevent infection as promised and cause extensive side effects that were covered up in the original trials.
- C.) The “social distancing” lockdown measures – which plunged untold billions worldwide into poverty, death, and despair – were totally ineffective at preventing the spread of the virus: “Shelter-in-place orders had no detectable health benefits.” Imagine the criminality of all the suffering for no good reason.
At every turn, the “experts” got it wrong.
So how does the biomedical establishment maintain the façade of legitimacy?
The biomedical state uses multiple mechanisms to discourage scientists from dissenting from the approved narrative
You’ve heard the talking point ad nauseam: “99% of scientists agree the vaccines are safe and effective.”
First of all, that figure is not vindicated by any actual polling; it’s just an offhand catchphrase.
Second, what happens to scientists who deviate from the “safe and effective” slogan?
- Their message will get censored or distorted (or both)
- Might lose their professional license
- Ostracized by their peers
- If they’re a researcher, they’ll risk wrecking their career and losing critical funding from NIH and pharma corps.
JFK Jr. explains:
“As director of the National Institute of Allergy and Infectious Diseases (NIAID), Dr. Anthony Fauci dispenses $6.1 billion in annual taxpayer-provided funding for scientific research, allowing him to dictate the subject, content, and outcome of scientific health research across the globe. Fauci uses the financial clout at his disposal to wield extraordinary influence over hospitals, universities, journals, and thousands of influential doctors and scientists—whose careers and institutions he has the power to ruin, advance, or reward.”
- You’ll get smeared in the corporate media
Exhibit A:
Epidemiologists at Harvard, Stanford, and Oxford – three of the most highly-regarded mainstream institutes of higher learning in the world – authored the Great Barrington Declaration in October 2020.
The gist of the document (which you can read here) is that a COVID Zero policy (the elimination of the SARS-CoV-2) virus in the population is a pipe dream. The social distancing and lockdown orders had devastating effects on public physical and mental health. Those at risk of severe illness or death from infectious disease should be protected while the non-vulnerable (the vast majority of the population) should resume normal life.
Those rational, science-based propositions should have been aired publicly in a healthy national debate.
But, predictably, open debate is not how Anthony Fauci and Francis Collins, NIH Director, do things. Instead of debating the merits of the Barrington Declaration, Collins sent an email to Fauci on Oct 8 (later leaked) that read:
“This proposal from three fringe epidemiologists… seems to be getting a lot of attention – and even a co-signature from Nobel Prize winner Mike Leavitt and Stanford. There needs to be a quick and devastating published takedown of its premises. I don’t think like that on line yet – is it underway?”
Does that sound like the language of a public health servant doing God’s work to protect the people from a deadly virus – or that of a cynical political operative?
Is coordinating a media hitjob on ideological opponents part of the NIH Director’s job description?
More importantly, though, if they can orchestrate a smear campaign against three “fringe” epidemiologists from Harvard, Stanford, and Oxford, what signal does that send to a run-of-the-mill MD in Wisconsin who might be inclined to ask critical questions?
The message is obvious: “shut your mouth or we’ll come for you.”

They don’t even have to go after everyone. All they need is to bag a few high-profile scalps to set the example.
MSNBC Misinfo: Zeke Emanuel Peddles Fear, Says Unvaxxed Children ‘Likely To Get Serious Case Of Covid’

By Tyler Durden | Zero Hedge | February 5, 2022
Dr Ezekiel Emanuel – former Biden Covid-19 adviser and brother of former Chicago Mayor Rahm Emanuel (and the real ‘Ari Gold’ from Entourage) appeared on MSNBC Wednesday, where he proceeded to peddle the lie that unvaccinated children are ‘likely’ to get a ‘serious’ case of Covid.
“This repeats what we’ve seen in older kids, five and above, where we know the vaccine does protect very well. And there we still have under 50%, I believe, of the children vaccinated, and that’s a serious problem for the country,” Emanuel told host Kristen Welker after she asked about parents’ willingness to vaccinate their children. “Parents have to be more willing – I think they hear some of these rare side effects and think they’re very common.”
“With the omicron variant, kids are either going to get the vaccine or they’re likely to get a serious condition of omicron. Having omicron with the vaccine is almost invariably going to be better and safer for children,” Emanuel added. “I am confused about parents’ attitudes. Five and above seems like a no-brainer. Two to five, I understand some hesitancy. Two and under with the small dose, I think probably a very good idea.”
It’s been widely established that Omicron is a relatively mild strain of Covid – from which children face an extremely low risk.
Another recent study cited by economist Emily Oster also reiterated the extremely low risk young children face of severe COVID-19 outcomes. “What we can say is that based on everything we know, the risks to small children from COVID-19 are extremely small,” she wrote. –Fox News
MSNBC faced harsh criticism over Emanuel’s statement.
The network even tweeted (and then deleted) the easily debunked misinformation, receiving a serious ratio of comments to ‘likes.’
Intentional? Or…
Following the backlash, Emanuel issued a Saturday tweet in which he says he “misspoke.”
Steve’s fact-based COVID-19 hub

By Steve Kirsch | February 2, 2022
Spotify made a press release about their new platform policies which prohibits any information which in their sole opinion may cause offline harm or poses a direct threat to public health. They refer people to their “fact-based” COVID-19 hub for accurate information.
I think their “fact-based” hub is filled with misinformation, so I decided to write my own simplified version that takes just a couple of minutes to read.
Here it is:
- Early treatments using repurposed drugs in a proven protocol are the best way to treat COVID. Treating as soon as symptoms appear is key. Fareed and Tyson have now treated over 10,000 people infected with COVID without any deaths as long as the people arrived early in the disease. The NIH and CDC ignore these treatments. I recommend you choose an early treatment protocol where there have been at least 10,000 COVID patients treated early without a single death (such as the Fareed-Tyson protocol), and start it as soon as you have symptoms.
- The evidence is clear that all of the current COVID vaccines available in the US today are both unsafe and ineffective. They are not suitable for anyone because they are more likely to kill you than to save you. If they don’t kill you, they may permanently damage your immune system or leave you permanently disabled. Avoid these at all costs. After 90 days, it appears that the vaccines have negative efficacy against Omicron, making you up to twice as likely to be infected. This is likely why case rates are so high in highly vaccinated countries. See Incriminating Evidence for details.
- Cloth and surgical masks do not work. There have been just two randomized trials with masks and COVID (Denmark and Bangladesh) and they proved that surgical and cloth masks have no effect. Similarly, N95 masks do not work in practice either. The FAA rules basically require you to wear these masks on planes, mandating a medical intervention that is much more likely to make you sick and has no chance to protect you. See Incriminating Evidence for details.
- If you require PPE that might protect you from COVID, consider a 3M respirator with a P100 filter. Even better is to use a PAPR with your respirator (with a P100 or P3 filter). See this article on masks and respirators for details. These products that protect you do not protect others. The FAA will not allow these devices on a plane.
- Social distancing is not the right way to think about risk reduction. Think instead the 4 D’s: draft, distance, density, duration. Putting yourself in an unventilated small room at close distance to a source for a long duration will maximize your exposure. The 6 foot rule for standing in line is nonsensical since as soon as you enter the airspace of the person in front of you, you will be breathing the virus from people who were standing in that spot hours (to days) ago (depending on the ventilation in the area). There is absolutely nothing magical about 6 feet.
- Mitigation strategies such as testing, masking, isolation, and vaccination are largely ineffective. See this article for a convincing example.
- The best way to treat COVID is to do the opposite of what the CDC and FDA advises. So when they tell you to mask up, get boosted, avoid all repurposed drugs and supplements (including ivermectin, HCQ, fluvoxamine, vitamin D, zinc, aspirin, budesonide, etc), take paxlovid, molnupiravir, and remdesivir, you know what to do.
- There is only significant spread if you have symptoms. For example, in a study in China, they looked at 1,174 close contacts of these asymptomatic individuals and could not find ONE CASE of a person getting COVID from the asymptomatic people. Therefore, testing asymptomatic people is unnecessary because it is a lot of effort for near 0 gain.
- Omicron is very mild compared to Delta. After you recover from an Omicron infection, data shows you will be protected from Delta as well.
- As of December 3, 2021, Omicron had spread to 38 countries, but the WHO couldn’t find anyone who died from Omicron. How is this a national emergency?
- People who get the virus and recover are always better off than a vaccinated patient. Unlike vaccinated people, if a naturally infected patient is ever re-infected, they cannot transmit the virus to others (as far as we know so far).
- Censorship of COVID advice by social media (in particular the hazards of the vaccines and the effectiveness of early treatment protocols) has cost hundreds of thousands of lives.
- None of the health authorities issuing mandates and directives are willing to participate in a recorded scientific discussion with the so-called “misinformation spreaders” such as Robert Malone, Peter McCullough, Robert Kennedy, … Our authorities are afraid of the truth.
- The CDC, FDA, and NIH are all corrupt agencies that have looked the other way at safety signals. There are over 1M adverse events in VAERS and these represent over 40M adverse events in the real world. This is unprecedented, yet the CDC isn’t able to find a safety signal other than a “slightly elevated” risk of myocarditis. Attempts to bring the VAERS data to their attention is futile. They won’t even do a proper calculation of the underreporting factor which is required to do a proper risk-benefit analysis. They ignore the DMED data entirely.
Compare my fact-based COVID-19 hub to Spotify’s and let me know which one you like better.
EU Wants To Keep Vaccine Passports In Place For Another ENTIRE YEAR
By Steve Watson | Summit News | February 4, 2022
The unelected bureaucrat governors of the EU in the European Commission have proposed keeping the bloc’s COVID vaccine passport system in place for another entire year, despite the fact that many member countries are ramping down restrictions.
In a notice on its website, the Commission states “Today the European Commission is proposing to extend the EU Digital COVID Certificate by a year, until 30 June 2023.”
It continues, “The COVID-19 virus continues to be prevalent in Europe and at this stage it is not possible to determine the impact of a possible increase in infections in the second half of 2022 or of the emergence of new variants.”
“Extending the Regulation will ensure that travellers can continue using their EU Digital COVID Certificate when travelling in the EU where Member States maintain certain public health measures,” the statements adds.
It continues, “The Commission is adopting the proposal today to make sure the European Parliament and the Council can conclude the legislative procedure in time before the current Regulation expires.”
The move comes even as several countries, including Denmark, Norway, Italy, Sweden, France, in addition to non-EU countries such as Switzerland and England move to scrap restrictions including the vaccine passes.
The European Commission admits in its statement that it is up to the individual countries whether they carry on using the EU COVID vaccine passport scheme.
“The domestic use of EU Digital COVID Certificates remains a matter for Member States to decide, the statement notes, adding “The EU legislation on the EU Digital COVID Certificate neither prescribes nor prohibits the domestic use of EU Digital COVID Certificate (such as for access to events or restaurants).”
It also notes that “At the same time, where a Member State establishes a system of COVID-19 certificate for domestic purposes, it should continue to ensure that the EU Digital COVID Certificate is also fully accepted for those purposes. Beyond that, the Commission also encourages Member States to align their domestic validity periods with the validity period set at EU level for the purpose of travel.”
As we reported in November, despite vaccine passport schemes and high vaccination rates in many of the countries affected, COVID cases across Europe continued to surge as winter kicked in.
In addition, a recent investigation by experts in Spain concluded that vaccine passports have no significant impact on reducing COVID-19 infection rates.
The findings are similar to evidence found by the UK government that vaccine passports could actually increase Covid rates in the country.
The Spanish study noted that the only positives of such a scheme are that it “warns people that there is still danger from the pandemic and encourages vaccination uptake among the reticent.”
In other words, although vaccine passports have no discernible impact on their stated goal – reducing the spread of COVID-19 – they do succeed in keeping people fearful and compliant.
That conclusion dovetails with a recent admission by French Minister of Health Olivier Véran that the vaccine passports are “a disguised form of vaccination obligation,” but are “more effective.”
Since when was heart trouble ‘non-serious’?
By Guy Hatchard | TCW Defending Freedom | February 4, 2022
New Zealand – The Medsafe report Adverse events following immunisation with COVID-19 vaccines: Safety Report #39 – 31 December 2021 lists 46,000 adverse events reported since the start of the Pfizer vaccine rollout in New Zealand. Historically this is 30 times the rate of adverse effects reported for flu vaccines. More than 50 per cent of these adverse effects are reported by medical professionals and about 40 per cent by affected members of the public via the CARM (Centre for Adverse Reactions Monitoring) website. Prior experience published by Medsafe concludes that only 5 per cent of adverse events are reported to CARM. A total of 8.1million doses have been administered in NZ.
The ten most common adverse events
Some 44,000 of the 46,000 adverse events are dismissed by Medsafe as ‘non-serious’—a number which has been echoed by politicians across the NZ political spectrum and by our Ministry of Health as evidence that the Pfizer vaccine is safe. The ten most common adverse events (all rated as non-serious) are as follows (from Medsafe). The total number of events below is more than 44,000 because many people experienced multiple symptoms.
The Mayo Clinic in USA reported before the pandemic that the risk of developing myocarditis is rare and lists the following concerning symptoms of myocarditis:
Mayo Clinic—Myocarditis Symptoms
If you’re in the early stages of myocarditis, you might have mild symptoms such as chest pain, rapid or irregular heartbeats, or shortness of breath. Some people with early-stage myocarditis don’t have any symptoms. The signs and symptoms of myocarditis vary, depending on the cause of the disease. Common myocarditis signs and symptoms include:
• Chest pain
• Rapid or irregular heartbeat (arrhythmias)
• Shortness of breath, at rest or during activity
• Fluid buildup with swelling of the legs, ankles and feet
• Fatigue
• Other signs and symptoms of a viral infection such as a headache, body aches, joint pain, fever, child dizziness, a sore throat or diarrhea
Sometimes, myocarditis symptoms may be similar to a heart attack. If you are having unexplained chest pain and shortness of breath, seek emergency medical help.
Of the ten most common adverse effects of Covid-19 vaccination reported to CARM in NZ, you can see eight are listed as symptoms of myocarditis by the Mayo Clinic. Given that myocarditis is the most common known severe outcome of Covid-19, why have the eight common vaccine adverse effects also known to be symptoms of myocarditis been characterised as ‘non-serious’? Is this a glaring case of misdiagnosis? If so, why?
NZ GPs and medical personnel had a naive expectation of vaccine safety
The first point to note is that most NZ medical professionals had expectations of vaccine safety based both on years of experience with vaccination programmes and the extensive medical education they had received. They had no prior experience with drugs or vaccines which had not already completed years of testing and safety evaluation. It was for them therefore virtually unthinkablethat the Pfizer vaccine was unsafe. Moreover the Pfizer vaccine trial results had already characterised the common adverse effects as non-serious. For this reason the very common reports of chest discomfort and shortness of breathfollowing Covid-19 vaccination, which according to prior protocols should have led to intensive investigation and treatment, were dismissed as non-serious without investigation and in most cases without reporting to CARM. Perhaps their very common occurrence fostered an attitude of indifference and dismissal which many victims suffered in NZ when they reported such symptoms to their GP or to hospital staff.
Rates of Myocarditis symptoms are higher than realised
The prevalence of a wide range of known myocarditis symptoms is probably indicative of a very high rate of subclinical and mild myocarditis following Pfizer vaccination. The important point to note is that the recommended treatment for mild myocarditis is rest. Most people recover if it is treated early with sufficient prolonged rest. If left untreated, myocarditis can restrict the capacity of the heart to pump blood which can lead to serious cardiac events such as heart attack, stroke, and arrhythmia. It is wrong to undertake vigorous physical activity including sport while suffering from myocarditis. It is clear from this that insufficient precautionary instructions were given to vaccine recipients about the risks they faced and the steps that they needed to take to avoid these risks. This may have contributed to cardiac problems including among some recipients undertaking vigorous physical exercise.
The possible extent of these cardiac events is indicated by multiple reports to voluntary organisations. An important point to note here is that reporting to CARM is not mandatory, a very unfortunate yet unforgivably deliberate omission. Medsafe attempts in its Safety Report #39 (referenced above) to dismiss the significance of adverse events by comparing their rate to population norms. In the absence of mandatory reporting, especially considering that Medsafe knows adverse events are grossly under-reported, all such comparisons are statistically meaningless.
A public information campaign is essential
Belatedly Dr Ashley Bloomfield, Director General of the Ministry of the Health, struck a note of alarm about myocarditis in his December 15 2021 letter to directors of district health boards, but this concern did not alter much the processes being applied. Individuals experiencing myocarditis following their first vaccination are still being denied exemptions. Those suffering strokes and heart attacks are in some if not most cases being denied Accident Compensation Commission (ACC) assistance. There is also a virtual data black-out on rates of cardiac events and hospitalisations and on ACC claims. Anecdotal and whistleblower reports here and overseas suggest these might be high but considering that data collection has been haphazard due to the ‘non-serious’ label, these might be hard to quantify unless the government makes an honest attempt to inform the public of risks and ask people to come forward who are already affected. This is particularly important as many stroke, cardiac and other serious adverse event sufferers have already been emphatically informed by their GP or other medical professionals that their symptoms must be unrelated to the Pfizer vaccination – an egregious form of victim-blaming lacking any scientific basis.
For more information: HatchardReport.com
Stop ‘harmful’ mass testing of children now, demand MPs
TCW Defending Freedom – February 4, 2022
THE cross-party Pandemic Response and Recovery All-Party Parliamentary Group of MPs met this week to hear whether there is a case for the continued mass testing of healthy children by schools and nurseries.
The committee is co-chaired by Conservative MP Esther McVey and Labour MP Graham Stringer. The group examined the pros and cons of testing in schools, and growing concerns about the likely physical and mental health harms caused by constant testing. Their uncompromising conclusion was that the mass testing of healthy children is ‘harmful, invasive and unevidenced’.
Ms McVey told the group something few of the public outside parents are aware of, which is that children are still routinely being asked to take tests, even at primary school, regardless of whether they have symptoms.
Though the threat of school closures has been lifted and the requirement for children to wear masks rescinded, hundreds of thousands of children are still missing schooling, she said, owing to constant testing and the government requirement for healthy children to isolate.
She informed the group that the evidence presented by their experts found no benefits to mass testing and that the children are not drivers of transmission. They have been disrupted, harmed and distressed despite the absence of any robust randomised control trial evidence of the benefits of mass testing them: ‘The evidence we have heard is clear. Testing in schools must stop, especially in the absence of any sort of study on the impact it has on our children’s physical and mental health. Evidence sessions such as this one are so important, to allow us to get a full picture before we make a decision and put our case to the Government.’
Mr Stringer said: ‘We cannot continue to force such an invasive procedure and we have heard today of children as young as two being physically restrained by their parents, put in headlocks or vomiting after the tests. As I have said before, the evidence to impose these sorts of measures must be overwhelming and I’m not aware the evidence exists that testing healthy children is beneficial and will help stop the spread of SAR-CoV-2. Not to mention the eye-watering sums spent on testing which could have been so much better spent on redressing some of the damage already caused to child mental health. Surely the time has come to stop the mass testing of healthy children?’
The group heard from Dr Angela E Raffle, honorary senior lecturer, University of Bristol Medical School Department of Population Health Sciences, Dr Allyson Pollock, clinical professor of public health at the University of Newcastle, child and adolescent clinical psychologist Dr Zenobia Storah, Professor Ellen Townsend, professor of psychology at the University of Nottingham and Mark Ward, a parent who spoke about the traumatic experiences of testing his toddler.
They all argued against the mass testing of healthy children in schools, highlighting the insufficient scientific and clinical evidence and arguing that, far from being of any public health benefit, mass testing causes significant damage to children.
Dr Raffle said: ‘SARS-CoV-2 testing of healthy school children needs to stop. The World Health Organisation cautions against mass symptomless testing because of high costs, lack of evidence on impact, and risk of diverting resources from more important activities. There is no sound evidence that testing children leads to reduction in serious cases of Covid-19. The policy decision in England to introduce school testing appears to have been a political decision, to create the impression of safety, rather than investing in staffing and ventilation which would have made an impact. The tests being used have not been properly evaluated as self-tests or for use in children. Children are low transmitters compared with adults. The net effect of the school testing is harmful because of the trauma of repeated testing and the disruption to children’s lives through repeated exclusion and isolation. Testing is important when done under medical supervision in order to guide decisions about the best way to treat a child who is ill, but the indiscriminate use of tests in children who are well is unjustified.’
Professor Pollock said: ‘Many of the so-called public health measures applied over the last two years have been no more than blanket measures applied with no evidence but with serious consequences, such as mass testing healthy school children. The tests are inappropriate and in the UK we completely ignored the Wilson and Junger 1968 principles of screening. They are not tests of infectiousness so children were and are being isolated unnecessarily. We know from studies that infected children do not spread the virus to others readily, not other children, their families nor their teachers. Now with the milder Omicron variant, many of them will be asymptomatic, so constantly mass testing healthy children is not only a traumatic experience but an appalling waste of time and is something that should only be done if clinically necessary, such as if a child is ill enough to need medical attention.’
Dr Storah described mass testing of healthy children as ‘harmful, invasive and unevidenced’ and ‘nothing short of state-sponsored child abuse’. She said: ‘I have been working with young people throughout the last two years and have seen a steep rise in mental health conditions as a result of measures like testing. These obsessive infection control measures are causing worrying levels of highly anxious behaviour. They maintain and amplify the fear messaging, further exacerbated when children are surrounded by adults, their parents or teachers, also constantly testing. It is utterly extraordinary for a society to treat their young in such an abusive way, to throw decades of understanding about normal child development out of the window without having considered the risk factors. One in six young people now meets the diagnostic criteria for at least one mental health disorder but there is still time to lessen and even reverse the long-term psychological impact this is having on our children. Children and adolescents need to be prioritised and mass testing, like face coverings, must be consigned to the policy bin, once and for all. What is required immediately is a return to normality for all children and all school and extra-curricular environments.’
Professor of Psychology Ellen Townsend told the group: ‘It is unclear what mass testing healthy children is achieving from a Public Health perspective. No studies have been carried out to understand if there are any benefits and no evaluation has been done on the psychological impact of testing – this is a grave and unethical oversight. We must recognise that children are at minimal risk to others but the harms caused to children, the disruption of testing protocols in schools and the resulting absences, are completely disproportionate to the proclaimed benefits of indiscriminate mass testing. The president of the Royal College of Paediatrics and Child Health was quite correct when she said last year that testing in schools was causing unnecessary chaos.’
You can find information about the APPG and its membership here and here.
No question the vaccines increase your susceptibility to COVID. What else do they do?
By Meryl Nass, MD | February 3, 2022

https://www.publichealthscotland.scot/media/11404/22-02-02-covid19-winter_publication_report.pdf
If you live in Scotland, a small country, the government, with its NHS, is like Santa: it knows if you’ve been bad or good. Scotland has 5.5 million residents. Over 5 million of them are listed in Scotland’s report of cases, above. The rest are kids too young for the vaccine. Sadly for Scots, 80% went along with the jab. It didn’t help them. And you can’t dispute these numbers: look at the narrow confidence intervals.
So now we know the jabbed get more COVID. What we suspect is that they also get more heart attacks, strokes, blood clots, autoimmune diseases and myocarditis. Will Scotland release those data, ever?
Different vaccines reveal different side effects
MHRA should release the raw data for public scrutiny
Health Advisory & Recovery Team | February 1, 2022
The MHRA Yellow Card reporting system is designed to provide a signal of possible problems with new drugs based on reports of suspected adverse reactions from qualified medical practitioners. The data collected could be of much more value if more details were published. The MHRA shares such information with the pharmaceutical industry but, despite its role being to protect the public and relying on public funding, this data is not put into the public domain.
To make the most of what information is available the reports on different vaccine types can be compared. Any side effects that are a result of the production of the spike protein itself may be similar between all vaccine types. However, if one vaccine type has a much higher rate of a particular adverse effect than other vaccine types then this is suggestive of a genuine causal relationship. Confounders such as age may account for part of these differences, which is why publishing the raw data is so important.
Data sharing
The Yellow Card scheme is administered by the MHRA, a government body funded, at least in part, by the public. The data for the scheme is collected largely by NHS staff, who are again funded by the public. However, despite public finance being crucial to the generation of Yellow Card data, the MHRA have refused to release the anonymised individual patient data from this scheme for independent analysis (FOI 21/640). The MHRA argue that release of these data would be too onerous, yet paradoxically these same data are passed on to the vaccine manufacturers for analysis as a matter of routine (FOI 21/942). All that the public can access from Yellow Card is a rudimentary summary of the total numbers of adverse events recorded for each vaccine type in particular medical categories.
The MHRA’s attitude to data sharing stands in stark contrast to the situation in the USA, where the VAERS reporting system [2] provides anonymised individual patient data, and the detailed analyses that this allows has been crucial for recognising important safety signals [3] — albeit US Regulators have been slow off the mark in making full use of the data available to them. We note that the MHRA’s refusal to share the information that they hold within the Yellow Card database would not be tolerated in the general science community where access to raw data is now a prerequisite for publication in peer reviewed journals.
Despite the intransigence of the MHRA over the issue of releasing raw data from the Yellow Card scheme to the general public, it is incumbent upon the scientific community to make the maximum use of the data released from the scheme to scrutinise the validity of the conclusions that the MHRA reach in their weekly reports. This is particularly important to achieve because, despite FOI requests to see the scientific analyses on which their conclusions are based, the MHRA have been unable to produce any such reports (FOI 21/942).
Comparing frequency of reports by vaccine type
The weekly data released from the Yellow Card scheme takes the form of the total number of doses of each of the vaccines given, the total number of reports filed for each vaccine type, and the total number of adverse reactions recorded for each of a huge range of medical conditions compiled separately for each of the vaccine types. What insights can we gain from analysis of this information?
A simple question that we can ask is whether the different vaccines elicit the same or different rates of reporting of adverse reactions or number of reactions per report. The answer is clear (Table 1). There is something about a Moderna injection that generates a higher frequency of adverse event reports with less reactions per report than an Astrazeneca vaccination, which in turn generates a higher frequency of reports and more reactions per report than a Pfizer injection. The figures involved are so huge that these differences cannot be due to chance. There is something important happening that needs to be explained.
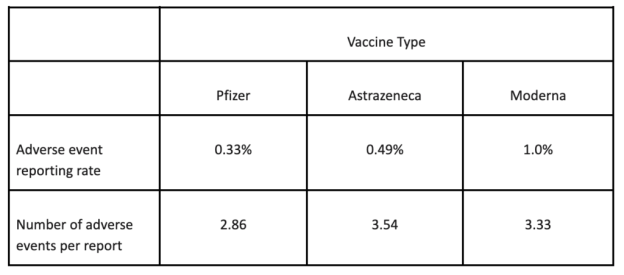
Table 1. Percentage of vaccinations resulting in a Yellow card report, and mean number of adverse events per report for three covid-19 vaccines administered in the UK
Risk of misinterpretation
Unfortunately, however, our interpretation can never be secure. The results we see could be due to the vaccines themselves. Alternatively, they could also be due to some confounding factor like the differences in age profile of the patients who were injected with different vaccine types, or to certain vaccine types being injected predominantly as boosters, or some combination of such factors. Yet distinguishing between alternative explanations is vital. If the effects we see are indeed due predominantly to vaccine type, this would have serious implications for vaccination policy and optimum choice of vaccine for minimising adverse reactions. However, analysis of confounding effects can only be achieved if the raw, anonymised individual patient data from the Yellow Card scheme are released by MHRA.
Comparing type of report by vaccine type
The second type of question that we can address using the Yellow Card data is whether choice of vaccines affects the spectrum of medical conditions recorded as adverse reactions. To answer this question, we can first sum up the number of adverse events elicited by each vaccine under the broad headings Blood & Vascular, Cardiac, Immune, Reproductive & Breast, Respiratory, Skin, Nervous System, Eye, Muscle and Other. A simple test for heterogeneity indicates that the relative frequency with which these classes of adverse reactions occur is highly dependent on the type of vaccine administered (χ2(18) = 29508, P<<0.001). Figure 1 illustrates the percentage by which the observed numbers of adverse reactions differ from the number expected if all vaccines elicited the same spectrum of adverse reactions. It is clear from the figure that departures from expectations are particularly large in the categories Blood & Vascular, Cardiac, Reproductive & Breast, and Skin; the different vaccines are eliciting quite different relative frequencies of adverse reaction in these categories.
For the categories Blood & Vascular, Cardiac, and to a lesser extent Immune and Reproductive & Breast, much higher than expected numbers of adverse reactions are elicited when the mRNA vaccines are administered, and lower than expected numbers of adverse reactions are found when the virus vectored Astrazeneca vaccine is used. Given that the same spike protein is encoded in the mRNA and virus vectored vaccines, this suggests that differences in the observed spectra of adverse reactions may be related to the mode of delivery of the spike encoding nucleic acid sequence in the vaccine. This observation for the Cardiac category is in agreement with a recent case series analysis which found that the risk of myocarditis is greater following sequential doses of mRNA vaccine than sequential doses of the adenovirus vaccine [4]. The role of the mRNA vaccine delivery system itself in eliciting adverse reactions must therefore come under scrutiny.
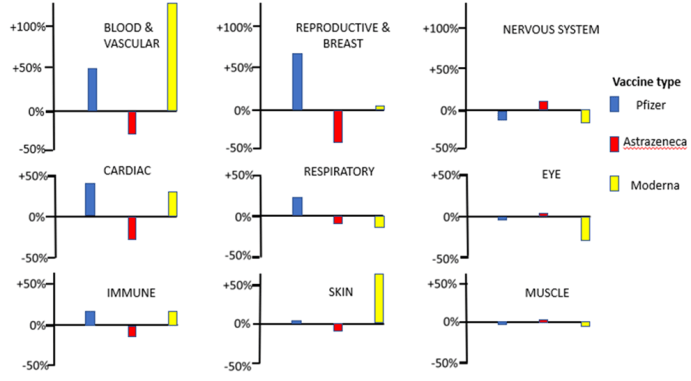
Figure 1. Percentage deviation of observed number of adverse reactions from the number expected if the spectrum of adverse events was the same for all vaccines. Data from nine different categories of adverse events are shown
While this example shows that the Yellow Card data may be helpful for generating ideas and supporting other studies, the inadequacy of the partial information currently released by the MHRA means that our interpretation of such data will always be compromised. Again, we do not possess the means to control for possible confounding factors (age and sex of individual, vaccine dose number etc.) that could contribute to the results observed. Nevertheless, in this example, the sheer size of the apparent effects of vaccine type on the spectrum of adverse effects indicates that a thorough investigation is essential. If the vaccine effect were confirmed, this would have serious real-world implications for the Covid-19 vaccination programme and the safety and health of the UK population.
Conclusion
The data we need to carry out the necessary analysis to maximise the usefulness of the Yellow Card scheme has already been collected at the public expense and is currently held by the MHRA. We call upon the MHRA immediately to release the raw, anonymised, individual patient data from the Yellow Card reporting scheme to enable rigorous scrutiny of Covid-19 vaccine adverse events by doctors, researchers and the public. This echoes the recent call by BMJ editors for immediate release of raw data from trials conducted by vaccine manufacturers [5].
2. https://www.cdc.gov/vaccinesafety/ensuringsafety/monitoring/vaers/index.html
3. https://jessicar.substack.com/p/a-report-on-myocarditis-adverse-events
4. https://www.medrxiv.org/content/10.1101/2021.12.23.21268276v1
5. Doshi P, Godlee F, Abbasi K. Covid-19 vaccines and treatments: we must have raw data, now BMJ 2022; 376 Covid-19 vaccines and treatments: we must have raw data, now | The BMJ
Featured Video

Trita Parsi: Middle East Unraveling — Are We on the Path to World War?
or go to
Aletho News Archives – Video-Images
From the Archives
Why Saudi Ties to 9/11 Mean U.S. Ties to 9/11
By Kevin Ryan | Dig Within | September 27, 2015
Media interest in Saudi Arabian connections to the crimes of 9/11 has centered on calls for the release of the 28 missing pages from the Joint Congressional Inquiry’s report. However, those calls focus on the question of hijacker financing and omit the most interesting links between the 9/11 attacks and Saudi Arabia—links that implicate powerful people in the United States. Here are twenty examples. … continue
Blog Roll
 Aletho News
- Neria Leiter Was A Legitimate Military Target
- Integrity Initiative: UK-funded network framed dissent as Russian disinformation for years
- ‘We don’t seek permission to defend our country’: Snippets from President Pezeshkian’s UNGA address
- NATO chief wants Europeans to fight American wars [for Israel]
- German chemicals giant reveals details of downsizing
- Refaat Al-Areer Was The Canary In The Coal Mine In Israel’s War On The Truth
- Israeli election committee bars candidate from Knesset race over Gaza war opposition
- French-Lebanese man files war crimes complaint over Israeli attacks
- Mahan Air Flight Lands in China Despite US Threat against Iranian Airlines
- US eyes $10bn fund to rebuild war-battered Gulf infrastructure
- If Americans Knew
- Caught on Tape: AIPAC CEO Boasted of Controlling Trump’s National Security Officials
- Why Hamas Attacked Israel in October 2023 – Israeli professor Ilan Pappé
- They see them, then kill them: Israeli quadcopters track, deliberately target civilians in Gaza
- Winter could turn Gaza’s treacherous, war-damaged buildings into deathtraps
- Majority of Democratic Voters Want to Prosecute Both Biden and Trump Administration Officials Over Gaza
- As Gaza languishes, world leaders gather at the UN – Daily Update
- Sanctions are collective punishment: immoral and self-defeating
- Phosphorus Munitions Fired by Israel Burn Groves, Orchards in Southern Lebanon
- Israel Carries Out New Ceasefire Violations Across Gaza
- AI – Emphasis on the ‘I’: Israel Is Funding AI Chatbot Propaganda
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

