The 5 signs you DON’T have “Omicron”… you have a cold & a PCR test
By Kit Knightly | OffGuardian | December 15, 2021
They are determined to make the “Omicron Variant” appear as frightening as possible, that means getting as many cases as possible, which means flipping all the way to the front of the Covid playbook.
Enter “The 5 Signs You May Have Omicron Covid”, an article in the Metro yesterday, and repeated in spirit across dozens of other outlets.
For those of you feeling morbidly curious, here are the five signs of Omicron:
- scratchy throat
- Fatigue
- mild muscle aches
- dry cough
- night sweats
The astute reader will no doubt pick up that these are the symptoms of every single one of the common cold viruses that infect millions of people all over the world every single year.
It’s just the old Simpsons joke about “mild hunger, occasional thirst and tiredness at night”, only they expect us to take it seriously.
The odds are you’ve experienced these symptoms at least once or twice in the last year or so. This does not mean you had Omicron. It does not mean Omicron even exists.
Rather, it’s just a ploy to get you to follow government guidance and, in the words of the article:
“order a free PCR test as soon as possible”.
The government site for ordering PCR tests has already shut down due to millions of requests. We have repeated, ad infinitum, that these tests are scientifically meaningless, and return huge numbers of false positives.
Nevertheless, hundreds of thousands of PCR tests are being done on people with nothing but mild cold symptoms as we speak, and in these nasal swabs lies the incipient “Omicron wave”.
That is why Sajid Javid is going on TV saying he expects cases of Omicron to “dramatically increase” in the run-up to Christmas, because they are going to make it happen.
Then they’ll probably have the Prime Minister announce new restrictions… just after Parliament adjourns for the Christmas break, so they can’t be reviewed or voted on.
It’s the same old trick, again and again and again. Hopefully, people will stop falling for it soon.
Danish Study Confirms That Natural Immunity Protects Better Against Infection Than the Vaccines
By Noah Carl | The Daily Sceptic | December 15, 2021
Last week, I wrote about a second major study finding that natural immunity protects better against infection than the Pfizer vaccine. Both this study and the earlier one were from Israel, and while there’s every reason to believe the results generalise to other populations, it’s always good to have data from multiple countries.
We now have those data in the form of a study published by the Statens Serum Institut in Denmark. I can’t say the report itself is worth reading in full, since it’s written in Danish. But I’ve posted the key figure below. It shows protection against infection for three different groups – adjusting for age, sex, comorbidities, and time of year.
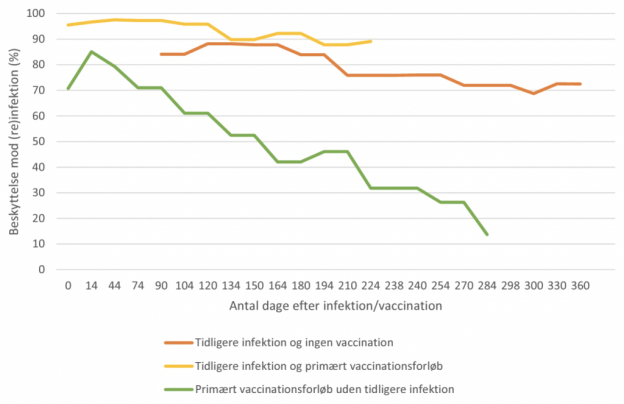
The orange line corresponds to people who’ve been previously infected but not vaccinated; the yellow line to those who’ve been previously infected and vaccinated; and the green line to those who’ve been vaccinated but not previously infected.
The y-axis gives the percentage reduction in the number of infections, compared to those who haven’t been vaccinated or previously infected. For example, a value of 90% means there would be only 10 infections for every 100 in the comparison group. The x-axis gives the number of days since the relevant event.
As you can see, vaccine-induced immunity wanes rapidly, beginning a few weeks after vaccination. And at the five month mark, protection is well below 50%. Natural immunity, by contrast, is robust: a full year after infection, protection is still above 70%.
Consistent with what the two Israeli studies found, hybrid immunity – conferred by the combination of vaccination and previous infection – is slightly better than natural immunity. However, the difference is small compared to that between natural and vaccine-induced immunity.
Evidence for the superiority of natural immunity is now robust. So while those who’ve already had Covid should be perfectly free to get vaccinated, there’s no obvious need for them to do so. The tricky part may be getting this message through to politicians.
32,649 Deaths 3,003,296 Injuries Following COVID Shots in European Database of Adverse Reactions
Young, Previously Healthy People Continue to Die

By Brian Shilhavy | Health Impact News | December 15, 2021
The European Union database of suspected drug reaction reports is EudraVigilance, and they are now reporting 32,649 fatalities, and 3,003,296 injuries, following COVID-19 injections.
A Health Impact News subscriber from Europe reminded us that this database maintained at EudraVigilance is only for countries in Europe who are part of the European Union (EU), which comprises 27 countries.
The total number of countries in Europe is much higher, almost twice as many, numbering around 50. (There are some differences of opinion as to which countries are technically part of Europe.)
So as high as these numbers are, they do NOT reflect all of Europe. The actual number in Europe who are reported dead or injured following COVID-19 shots would be much higher than what we are reporting here.
The EudraVigilance database reports that through December 4, 2021 there are 32,649 deaths and 3,003,296 injuries reported following injections of four experimental COVID-19 shots:
- COVID-19 MRNA VACCINE MODERNA (CX-024414)
- COVID-19 MRNA VACCINE PFIZER-BIONTECH
- COVID-19 VACCINE ASTRAZENECA (CHADOX1 NCOV-19)
- COVID-19 VACCINE JANSSEN (AD26.COV2.S)
From the total of injuries recorded, almost half of them (1,409,643) are serious injuries.
“Seriousness provides information on the suspected undesirable effect; it can be classified as ‘serious’ if it corresponds to a medical occurrence that results in death, is life-threatening, requires inpatient hospitalisation, results in another medically important condition, or prolongation of existing hospitalisation, results in persistent or significant disability or incapacity, or is a congenital anomaly/birth defect.”
A Health Impact News subscriber in Europe ran the reports for each of the four COVID-19 shots we are including here. It is a lot of work to tabulate each reaction with injuries and fatalities, since there is no place on the EudraVigilance system we have found that tabulates all the results.
Since we have started publishing this, others from Europe have also calculated the numbers and confirmed the totals.*
Here is the summary data through December 4, 2021.
Total reactions for the mRNA vaccineTozinameran (code BNT162b2,Comirnaty) from BioNTech/ Pfizer: 15,061 deaths and 1,399,513 injuries to 04/12/2021
- 38,170 Blood and lymphatic system disorders incl. 217 deaths
- 43,454 Cardiac disorders incl. 2,204 deaths
- 404 Congenital, familial and genetic disorders incl. 38 deaths
- 18,886 Ear and labyrinth disorders incl. 10 deaths
- 1,330 Endocrine disorders incl. 5 deaths
- 21,574 Eye disorders incl. 35 deaths
- 115,450 Gastrointestinal disorders incl. 602 deaths
- 354,635 General disorders and administration site conditions incl. 4,251 deaths
- 1,589 Hepatobiliary disorders incl. 78 deaths
- 15,371 Immune system disorders incl. 77 deaths
- 57,255 Infections and infestations incl. 1,605 deaths
- 22,928 Injury, poisoning and procedural complications incl. 261 deaths
- 34,691 Investigations incl. 464 deaths
- 9,568 Metabolism and nutrition disorders incl. 256 deaths
- 172,420 Musculoskeletal and connective tissue disorders incl. 187 deaths
- 1,254 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 122 deaths
- 236,435 Nervous system disorders incl. 1,609 deaths
- 2,000 Pregnancy, puerperium and perinatal conditions incl. 60 deaths
- 215 Product issues incl. 3 deaths
- 25,493 Psychiatric disorders incl. 182 deaths
- 4,981 Renal and urinary disorders incl. 236 deaths
- 49,076 Reproductive system and breast disorders incl. 5 deaths
- 60,177 Respiratory, thoracic and mediastinal disorders incl. 1,664 deaths
- 65,710 Skin and subcutaneous tissue disorders incl. 128 deaths
- 3,007 Social circumstances incl. 19 deaths
- 7,280 Surgical and medical procedures incl. 90 deaths
- 36,160 Vascular disorders incl. 653 deaths
Total reactions for the mRNA vaccine mRNA-1273(CX-024414) from Moderna: 9,084 deaths and 409,189 injuries to 04/12/2021
- 8,678 Blood and lymphatic system disorders incl. 102 deaths
- 13,650 Cardiac disorders incl. 953 deaths
- 166 Congenital, familial and genetic disorders incl. 7 deaths
- 4,940 Ear and labyrinth disorders incl. 4 deaths
- 373 Endocrine disorders incl. 4 deaths
- 5,992 Eye disorders incl. 31 deaths
- 33,407 Gastrointestinal disorders incl. 339 deaths
- 109,178 General disorders and administration site conditions incl. 3,117 deaths
- 673 Hepatobiliary disorders incl. 44 deaths
- 4,054 Immune system disorders incl. 16 deaths
- 15,636 Infections and infestations incl. 849 deaths
- 8,535 Injury, poisoning and procedural complications incl. 172 deaths
- 8,001 Investigations incl. 211 deaths
- 3,893 Metabolism and nutrition disorders incl. 220 deaths
- 49,233 Musculoskeletal and connective tissue disorders incl. 184 deaths
- 568 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 74 deaths
- 68,948 Nervous system disorders incl. 870 deaths
- 754 Pregnancy, puerperium and perinatal conditions incl. 6 deaths
- 82 Product issues incl. 2 deaths
- 7,472 Psychiatric disorders incl. 149 deaths
- 2,398 Renal and urinary disorders incl. 174 deaths
- 8,859 Reproductive system and breast disorders incl. 7 deaths
- 18,183 Respiratory, thoracic and mediastinal disorders incl. 975 deaths
- 21,946 Skin and subcutaneous tissue disorders incl. 82 deaths
- 1,872 Social circumstances incl. 39 deaths
- 1,642 Surgical and medical procedures incl. 115 deaths
- 10,056 Vascular disorders incl. 338 deaths
Total reactions for the vaccine AZD1222/VAXZEVRIA (CHADOX1 NCOV-19) from Oxford/ AstraZeneca: 6,515 deaths and 1,088,775 injuries to 04/12/2021
- 13,292 Blood and lymphatic system disorders incl. 254 deaths
- 19,523 Cardiac disorders incl. 720 deaths
- 203 Congenital familial and genetic disorders incl. 7 deaths
- 12,845 Ear and labyrinth disorders incl. 4 deaths
- 619 Endocrine disorders incl. 4 deaths
- 19,170 Eye disorders incl. 29 deaths
- 103,368 Gastrointestinal disorders incl. 340 deaths
- 286,356 General disorders and administration site conditions incl. 1,544 deaths
- 971 Hepatobiliary disorders incl. 62 deaths
- 4,99 Immune system disorders incl. 30 deaths
- 33,416 Infections and infestations incl. 441 deaths
- 12,583 Injury poisoning and procedural complications incl. 180 deaths
- 23,958 Investigations incl. 159 deaths
- 12,472 Metabolism and nutrition disorders incl. 96 deaths
- 161,308 Musculoskeletal and connective tissue disorders incl. 114 deaths
- 650 Neoplasms benign malignant and unspecified (incl cysts and polyps) incl. 25 deaths
- 223,680 Nervous system disorders incl. 1,007 deaths
- 533 Pregnancy puerperium and perinatal conditions incl. 14 deaths
- 191 Product issues incl. 1 death
- 20,150 Psychiatric disorders incl. 60 deaths
- 4,093 Renal and urinary disorders incl. 63 deaths
- 15,594 Reproductive system and breast disorders incl. 2 deaths
- 38,722 Respiratory thoracic and mediastinal disorders incl. 817 deaths
- 49,877 Skin and subcutaneous tissue disorders incl. 53 deaths
- 1,533 Social circumstances incl. 6 deaths
- 1,499 Surgical and medical procedures incl. 26 deaths
- 27,179 Vascular disorders incl. 457 deaths
Total reactions for the COVID-19 vaccine JANSSEN (AD26.COV2.S) from Johnson & Johnson: 1,989 deaths and 105,819 injuries to 04/12/2021
- 1,029 Blood and lymphatic system disorders incl. 41 deaths
- 1,952 Cardiac disorders incl. 169 deaths
- 36 Congenital, familial and genetic disorders
- 1,080 Ear and labyrinth disorders incl. 2 deaths
- 72 Endocrine disorders incl. 1 death
- 1,415 Eye disorders incl. 7 deaths
- 8,743 Gastrointestinal disorders incl. 80 deaths
- 27,925 General disorders and administration site conditions incl. 533 deaths
- 130 Hepatobiliary disorders incl. 11 deaths
- 473 Immune system disorders incl. 9 deaths
- 4,676 Infections and infestations incl. 157 deaths
- 974 Injury, poisoning and procedural complications incl. 20 deaths
- 4,927 Investigations incl. 111 deaths
- 664 Metabolism and nutrition disorders incl. 50 deaths
- 15,331 Musculoskeletal and connective tissue disorders incl. 45 deaths
- 59 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 4 deaths
- 20,725 Nervous system disorders incl. 219 deaths
- 43 Pregnancy, puerperium and perinatal conditions incl. 1 death
- 32 Product issues
- 1,479 Psychiatric disorders incl. 17 deaths
- 443 Renal and urinary disorders incl. 26 deaths
- 2,249 Reproductive system and breast disorders incl. 6 deaths
- 3,799 Respiratory, thoracic and mediastinal disorders incl. 259 deaths
- 3,241 Skin and subcutaneous tissue disorders incl. 8 deaths
- 337 Social circumstances incl. 4 deaths
- 718 Surgical and medical procedures incl. 58 deaths
- 3,267 Vascular disorders incl. 151 deaths

*These totals are estimates based on reports submitted to EudraVigilance. Totals may be much higher based on percentage of adverse reactions that are reported. Some of these reports may also be reported to the individual country’s adverse reaction databases, such as the U.S. VAERS database and the UK Yellow Card system. The fatalities are grouped by symptoms, and some fatalities may have resulted from multiple symptoms.
RFK Jr. as America’s #1 HIV/AIDS Denier and the Sounds of Media Silence
BY RON UNZ • UNZ REVIEW • DECEMBER 15, 2021
Robert F. Kennedy, Jr.’s book attacking Anthony Fauci and the medical establishment has become a publishing sensation, spending more than a full week as the #1 Amazon bestseller and racking up over 2,600 reviews, 94% of them five-star.
Now after nearly a month of stunned silence, the American media is finally taking belated notice. This morning the Associated Press released a 4,000 word hit-piece harshly attacking the most prominent public figure in America’s much-vilified anti-vaxxing movement.
- How a Kennedy Built an Anti-Vaccine Juggernaut Amid COVID-19
Michelle R. Smith • The Associated Press • December 15, 2021 • 4,000 Words
A great deal of effort had obviously been invested in this attack, and the byline of the named author was shared by five additional AP writers and researchers, underscoring the journalistic resources devoted to damaging the reputation of an individual who has obviously made such powerful enemies. But in reading the article, the phrase that came to my mind was “the Sounds of Silence” or perhaps the famous Sherlockian clue of “the Dog That Didn’t Bark.”
Almost half of the entire book under attack—around 200 pages—is devoted to the presenting and promoting the astonishing claim that everything we have been told about HIV/AIDS for more than 35 years probably amounts to a hoax. As I wrote last week:
Yet according to the information provided in Kennedy’s #1 Amazon bestseller, this well-known and solidly-established picture, which I had never seriously questioned, is almost entirely false and fraudulent, essentially amounting to a medical media hoax. Instead of being responsible for AIDS, the HIV virus is probably harmless and had nothing to do with the disease. But when individuals were found to be infected with HIV, they were subjected to the early, extremely lucrative AIDS drugs, which were actually lethal and often killed them. The earliest AIDS cases had mostly been caused by very heavy use of particular illegal drugs, and the HIV virus had been misdiagnosed as being responsible. But since Fauci and the profit-hungry drug companies soon built enormous empires upon that misdiagnosis, for more than 35 years they have fought very hard to maintain and protect it, exerting all their influence to suppress the truth in the media while destroying the careers of any honest researchers who challenged that fraud. Meanwhile, AIDS in Africa was something entirely different, probably caused mostly by malnutrition or other local conditions.
I found Kennedy’s account as shocking as anything I have ever encountered.
By any reasonable standard, Robert F. Kennedy, Jr. has now established himself as America’s #1 “HIV/AIDS Denier,” and prior to the Covid outbreak, AIDS had probably spent almost four decades as the world’s highest-profile disease, reportedly absorbing some two trillion dollars in research and treatment costs. So for someone to essentially claim that the disease doesn’t actually exist would seem the height of utter lunacy, on a par with Flat Earthism. Yet not a single word of this astonishing situation appears in the long AP article, that attacks Kennedy on almost all other possible grounds, fair or unfair. Did all six of the AP writers and researchers somehow skip over those 200 pages in Kennedy’s bestseller?
That large team of AP journalists seems to have spent at least ten days working on their lengthy article, mining Kennedy’s record for almost everything controversial they could possibly find, even highlighting a photograph that merely shows him standing next to Trump allies Roger Stone and Michael Flynn.

Surely these reporters consulted numerous leading figures in the medical establishment on the HIV/AIDS issue, yet not a single word on that incendiary topic was included in their 4,000 word denunciation.
Although ferocious attacks against Kennedy’s HIV/AIDS claims might naturally have been expected, perhaps certain aspects of the book caused the senior editors of the Associated Press to draw back and decide that discretion on this matter was the better part of valor. As I had explained:
However, the first endorsement on the back cover is from Prof. Luc Montagnier, the medical researcher who won a Nobel Prize for discovering the HIV virus in 1984, and he writes: “Tragically for humanity, there are many, many untruths emanating from Fauci and his minions. RFK Jr. exposes the decades of lies.” Moreover, we are told that as far back as the San Francisco International AIDS Conference of June 1990, Montagnier had publicly declared “the HIV virus is harmless and passive, a benign virus.”
Perhaps this Nobel Laureate endorsed the book for other reasons and perhaps the meaning of his striking 1990 statement has been misconstrued. But surely the opinion of the researcher who won a Nobel Prize for discovering the HIV virus should not be totally ignored in assessing its possible role.
I went on to note:
And he was hardly alone. Kennedy explains that the following year, a top Harvard microbiologist organized a group containing some of the world’s most distinguished virologists and immunologists and they issued a public statement, endorsed by three additional science Nobel Laureates, that raised the same questions:
It is widely believed by the general public that a retrovirus called HIV causes a group of diseases called AIDS. Many biomedical scientists now question this hypothesis. We propose a thorough reappraisal of the existing evidence for and against this hypothesis, to be conducted by a suitable independent group. We further propose that the critical epidemiological studies be designed and undertaken.
As Kennedy tells the story, by that point AIDS researchers and the mainstream media were completely in thrall to the ocean of government funding and pharmaceutical advertising controlled by Fauci and his corporate allies, so these calls by eminent scientists were almost entirely ignored and unreported. According to one journalist, some two trillion dollars has been spent on HIV/AIDS research and treatment over the decades, and with so many research careers and personal livelihoods dependent upon what amounts to an “HIV/AIDS industrial-complex,” few have been willing to critically examine the basic foundations of that empire.
Until a couple of weeks ago, I had never given any thought to questioning AIDS orthodoxy. But discovering the longstanding scientific skepticism of so many knowledgeable experts, including four Nobel Laureates, one of them the actual discoverer of the HIV virus, has completely shifted my perspective. I cannot easily ignore or dismiss the theories Kennedy presents… And in basic fairness to the author, he himself also repeatedly emphasizes that he can “take no position on the relationship between HIV and AIDS” but is simply disturbed that Fauci has successfully used his government funding and media clout to suppress an ongoing and perfectly legitimate scientific debate. According to Kennedy, his book is intended “to give air and daylight to dissenting voices.”
So the total silence of the article does certainly raise certain obvious suspicions. As I previously wrote:
Robert F. Kennedy, Jr. is a top figure in America’s much-vilified anti-vaxx movement and his book is becoming a major element of that cause. His strident attacks against pharmaceutical companies, medical orthodoxy, and Fauci have earned him numerous, powerful enemies. If his AIDS claims were really as ridiculous as they might seem, would they not have already become a lightning rod for attacks against him? Suppose that his anti-vaxx tome had devoted 200 pages to arguing that our world was secretly controlled by invisible 12-foot-tall Reptilians from another dimension. Surely Kennedy’s enemies would have unleashed a huge storm of media ridicule against him for that lunacy, thereby discrediting his critique of vaccination campaigns. Yet instead complete silence has greeted his AIDS claims, raising questions in my mind of whether the medical establishment suspects that it has a great deal to hide and that many of Kennedy’s accusations might be correct.
As an outside observer with no special expertise in these areas of medicine, I was impressed by much of the material that Kennedy marshaled in support of his unorthodox views on vaccines and Covid treatments, but found that the evidence he provided on HIV and AIDS was vastly more comprehensive and persuasive, while being backed by far more authoritative experts. But if as he argues, the truth about HIV and AIDS has been successfully suppressed for decades by the entire medical industry, we must necessarily become very suspicious about other medical claims, including those regarding Covid and vaccinations.
Unless the medical and media establishments swiftly and forthrightly challenges Robert F. Kennedy, Jr. on the issue of HIV/AIDS, any fair-minded observers must necessarily conclude they recognize that he is substantially correct. And if he is correct about AIDS, any shreds of remaining credibility in our public health authorities will surely be destroyed, while the longstanding theories of Berkeley Prof. Peter Duesberg will have been vindicated:
- The chemical bases of the various AIDS epidemics: recreational drugs, anti-viral chemotherapy and malnutrition
Peter Duesberg, Claus Koehnlein, and David Rasnick • Journal of Bioscience • June 2003 • 24,000 Words
So as some have suggested, HIV/AIDS might very well become the Achilles’ Heel of our corrupt and incompetent medical establishment.
New German Chancellor Says There Will Be “No Red Lines” As Regards COVID Restrictions
By Steve Watson | Summit News | December 15, 2021
Angela Merkel’s successor in Germany has declared that there is nothing he won’t do to battle COVID, a stark statement given previous pledges to make compulsory vaccinations legal.
Chancellor Olaf Scholz used his first address to the nation in Germany to push vaccinations, declaring that they are the only way Germany can overcome the pandemic.
Scholz added that there would be “no red lines” in the battle against the current wave of COVID, which he declared to be fueled by unvaccinated citizens.
“We will pull every possible lever,” he continued, adding “It will get better. Yes, we will win the fight against this pandemic with the biggest determination. And, yes, … we will overcome the crisis.”
He added that “our society is not divided,” and referring to people opposed to vaccinations proclaimed “We will not put up with a tiny minority of uninhibited extremists trying to impose their will on our entire society.”
While claiming “We are listening. We are looking for debate,” Scholz stated “There is in Germany today . . . denial of reality, absurd conspiracy stories, wilful disinformation and violent extremism.”
“We will counter this with the means of our democratic constitutional state. Our democracy is a democracy capable of defending itself,” the Chancellor further warned.
On Sunday, Scholz stated that he supports vaccine mandates across Germany, noting that he intends to “vote for compulsory vaccination, because it is legally permissible and morally right.”
Scholz previously said he wants to introduce mandatory coronavirus vaccination for all Germans as early as February, according to sources close to him.
Germany recently recorded its highest COVID death toll for 9 months, despite having mask mandates and stringent rules in many regions that banned the unvaccinated from numerous venues.
The country is preparing to follow the example of Austria by imposing new lockdown measures that will exclusively apply to the unvaccinated.
The Pandemicists Must Be Stopped
The Pandemicists at Work:

This strange and mildly disturbing illustration actually accompanies the article, one of many cases where the NYT betray the sinister undertones of their agenda via accompanying imagery.
eugyppius – December 14, 2021
Corona has vastly expanded the ranks of pandemic planners and public health botherers. Unless something is done, these people will destroy all of society in their radical pursuit of a few viruses.
Just a few words on “Omicron is a Dress Rehearsal for the Next Pandemic”, a New York Times article by Emily Anthes, a science journalist with ties to the World Economic Forum. It’s subtitled “America’s response to the variant highlights both how much progress we have made over the past two years — and how much work remains,” and it’s every inch as awful as you’d imagine.
In the piece, Anthes laments that the United States is “woefully unprepared for the challenges ahead, starting with the most fundamental of tasks: detecting the virus.” She quotes a microbiologist to complain that “We had a delay of one to two months before we were even able to identify the presence of [Omicron] … And by that time, it had already circulated widely between multiple states and from coast to coast.” She wastes many words on the necessity of “Testing, testing, testing”; here, apparently, America still needs vastly more capacity. She and her many scientist informants also want more gene sequencing to detect variants sooner. She’s sure that all of this is absolutely necessary, even though she doesn’t know why:
Scientists are finding more Omicron cases every day, and the variant could soon overtake Delta. What comes next — what we should aim for, even — is less clear. Should we spend the winter trying to stop every infection? Protecting the highest risk people from severe disease and death? Ensuring that hospitals are not overrun?
“One thing that we’ve lacked continuously through the pandemic is a goal,” said Emily Gurley, an epidemiologist at the Johns Hopkins Bloomberg School of Public Health. “We still don’t have that. Certainly, we don’t have that for Omicron.”
No realistic public health goal underpins this diagnostic mania, of course. People who test positive for Corona are sent home to suffer in untreated silence by themselves. Endlessly testing, tracing, sequencing, panicking and closing is, however, a goal in itself for people like Emily Gurley and all the other pandemicists Anthes gleefully quotes, from Eric Topol to Trevor Bedford to Ezekiel J. Emanuel. All of them want the Corona Circus to play on, and after it ends they hope for a sequel sometime soon. Never before have they enjoyed such personal and professional prominence.
Even if by some miracle all of this winds down tomorrow, this whole odious internationally networked enterprise of Virus Astrology, from virologers to sequencers to testers to planners to nudgers to vaccinators, won’t go away. They were a malign influence even before Corona, of course. In 2009, when we suffered under a small fraction of the Pandemicism that burdens us now, they succeeded in causing an international uproar over a mild strain of pandemic influenza. Now their ranks have been vastly expanded, and they are already hoping for the next opportunity to close our schools, lock us up at home and stick us full of needles.
The pandemicists are truly dangerous, and they will grind human civilisation into the dust unless we find some way of putting all of them out of work. They aren’t going to save anybody from the next pandemic; in the event it happens, they’ll just take advantage of the opportunity to expand their ranks still further and make all of our lives worse. And should novel viruses prove slow to materialise in the post-Corona era, they’ll get up to other tricks. Tricks like new and enhanced histrionics over every seasonal influenza outbreak. Tricks like the intentional release of more engineered viral pathogens to keep the grant funding flowing. Tricks like constant lunatic mass vaccination schemes against ever milder viruses. Still other tricks I haven’t considered. The pandemicists have to go.
A huge Israeli study shows natural Covid immunity is far superior to the vaccine-generated kind
By Alex Berenson | December 14, 2021
mRNA vaccine protection from Covid is far weaker than natural immunity and declines very fast, according to a new study of almost 6 million people in Israel.
During the summer Covid wave, more than 140,000 Israelis who had been vaccinated but not received a booster shot became infected with Covid. Put another way, in just two months, about 1 out of every 20 vaccinated Israelis became infected with Sars-Cov-2.
Natural immunity – the protection following infection and recovery – lasts much longer, the study shows.
In fact, people who had already had Covid once had better protection from the virus more than a year later than people who had been vaccinated only three months before.
The gap was even larger in cases of severe infection.
Vaccinated people were more than five times as likely to develop severe infections than people with natural immunity. Only 25 out of roughly 300,000 Israelis with natural immunity developed severe Covid infections in the summer wave – compared to almost 1,400 vaccinated Israelis.
The difference did not result from gaps in age between vaccinated and recovered people. People over 60 benefitted even more from natural immunity relative to vaccination than did younger people.
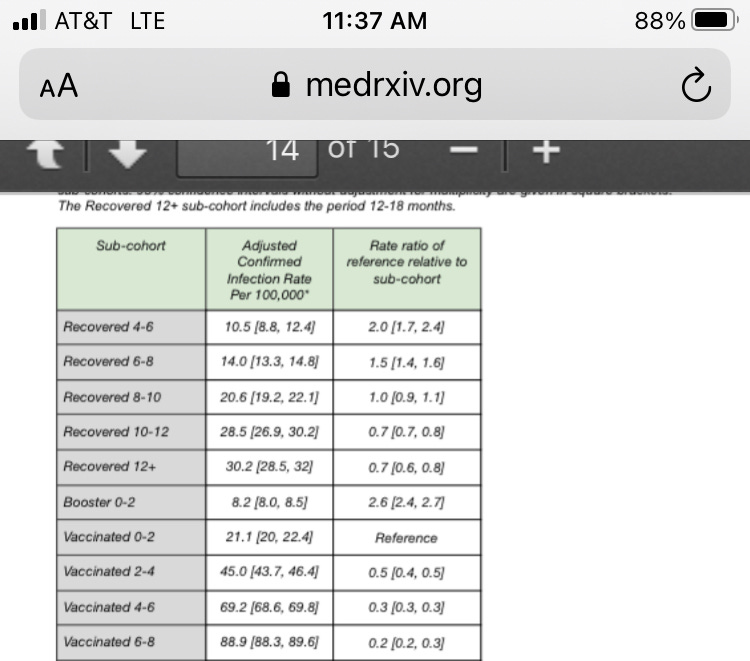
The study also showed that giving people who had natural immunity a vaccine dose did little to lower rates of infection for them, raising the question of why they should ever be vaccinated.
Finally, the study offered a disturbing signal that vaccination may ultimately interfere with the development of lasting immunity in people who are infected after being vaccinated.
A booster shot did lower the risk of infection about to the level of peak protection from natural immunity – but because the study ended in September, it is impossible to know how long that protection may last.
All these findings come out of a database of Covid infections among almost 6 million Israelis in August and September, at the peak of the fourth Covid wave in Israel. The database contains information on essentially every Israeli over age 16 who was fully vaccinated or had previously had a Covid infection.
The paper, “Protection and waning of natural and hybrid COVID-19 immunity,” is currently available as a preprint at:
https://www.medrxiv.org/content/10.1101/2021.12.04.21267114v1.full.pdf
Oddly, the paper’s title does not mention waning of vaccine immunity, although the figures it presents make the severity of the problem clear. Such shyness is common among researchers presenting bad news about Covid vaccines – they will offer the data, but not highlight it.

Israel has exclusively used the Pfizer mRNA vaccine, began mass vaccinations before almost any other country, and has an excellent health care database. As a result, it has among the best information on the effectiveness of the shots. It offers far more complete data than the United States.
The vaccine failure over the summer in Israel – following apparent success in the spring – has presaged a similar pattern across the United States and Europe, and a similar desperate campaign for boosters.
In this paper, the researchers examined infection rates among five different groups of Israelis – those with natural immunity, those who had received boosters, those who were vaccinated but had not received boosters, those with natural immunity who had also received a vaccine, and those who had become infected after being vaccinated.
The researchers specifically excluded unvaccinated Israelis without natural immunity from the comparison because Israel has very few of them and they are “unrepresentative of the overall population.”
In other words, the researchers explicitly denied the validity of the comparison that vaccine advocates make when they compare Covid rates among vaccinated and unvaccinated people in places with high vaccination rates (a point I have been trying to make for months).
The researchers found that the highest rates of infection by far came in people who had been vaccinated at least six months before. They had a nearly 3 percent chance of being infected per month (the researchers present the figure as 89 per 100,000 “person-days.”)
Those people were four times as likely to be infected as newly vaccinated people. They were also seven times as likely to be infected as people who had natural immunity from an infection six to eight months before, and three times as likely as those who had natural immunity from an infection more than year before.
A single vaccination dose in people with natural immunity temporarily produced strong protection, the researchers found. But after six months, the advantage had faded to within the margin of statistical error. In other words, so-called hybrid immunity hardly appeared to exist after six months – natural immunity was once again providing the protection.
Nor did vaccination appear to stop severe disease.
Nearly every case of severe disease in the database – almost 1,400 of the roughly 1,600 cases – came in vaccinated but unboosted people. Boosters did appear to reduce severe disease significantly. Again, though, the study covered less than two months after the booster program began, when boosters should be at peak effectiveness.
Finally, the study showed that people who had been vaccinated and then been infected and recovered were actually more likely to be infected again six months later than those who had only “pure” natural immunity.
That finding, though based on a small number of cases, adds to worrying data that mRNA vaccination may actually wrong-foot our immune systems in the long run and make it harder to build lifelong protection against Covid.
Featured Video

EUROPE FEARS RUSSIA’S NEXT MOVE / Ian Proud
or go to
Aletho News Archives – Video-Images
New Book
New Book: No Autoimmunity The Body Doesn’t Attack Itself
Lies are Unbekoming | September 24, 2026
 The label for Humira, once the best-selling drug in the world, lists its risks in plain print. One of them, in the label’s own words, is new “autoimmune” disease.
A drug prescribed for a condition labelled autoimmune carries a warning that it can cause a condition labelled autoimmune. That contradiction sits in every box, on a folded paper almost nobody reads.
My new book starts there.
No Autoimmunity: The Body Doesn’t Attack Itself
For seventy years, “your body is attacking itself, and we don’t know why” has ended the conversation for people diagnosed with multiple sclerosis, lupus, rheumatoid arthritis, Hashimoto’s, Type 1 diabetes, Crohn’s and psoriasis. More than eighty conditions now carry the autoimmune label. The diagnosis comes with a prescription for life. It almost never comes with a question about cause.
This book asks the question and answers it from the framework’s own records: its drug labels, its journals, its regulatory filings, and its own experiments. … continue
Blog Roll
 Aletho News
- Merz regime wants ‘secret police’ – opposition
- Israeli settlers terrorize West Bank Palestinians with state-provided drones: Report
- They see them, then kill them: Israeli quadcopters track, deliberately target civilians in Gaza
- Debunked: Trump’s egregious UNGA claims on war against Iran crumble under scrutiny
- Europe was part of the infrastructure of US aggression against Iran: Deputy FM
- New evidence on the Bucha Massacre
- Italy and France debunk reports CIA issued ‘Russian drone threat’ warning
- How Russia is Rewiring the Global South
- Britain’s elites want you ready to die for a war they keep imagining
- Inside Ukraine’s propaganda operation targeting Americans
- If Americans Knew
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- In UN Speech, Iran’s President Displays Pictures of Children Killed by US, Brings Attention to Israel’s Nuclear Arsenal
- Israel displaces hundreds of Palestinians amid wave of demolitions in West Bank
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

