Is Vaccine Effectiveness Against Death Mostly a Statistical Illusion?

By Will Jones | The Daily Sceptic | December 12, 2021
One of the big challenges in analysing the data on Covid has been definitions. What is a Covid death, what is a Covid case or infection? What the data appears to say can change radically depending on the definitions adopted.
This has been a particular issue with vaccination, as vaccination status is subject to a variety of conflicting definitions. In particular, when does someone count as vaccinated? Is it as soon as they have the needle in their arm, or do they remain ‘unvaccinated’ after that for a period of time, say seven, 14 or 21 days?
For instance, the recent ICNARC report stated the number of ICU admissions by vaccination status. But it also clarified that ‘unvaccinated’ includes those who received a jab less than 14 days prior to testing positive. This means that some (an unknown number) who were counted as unvaccinated had in fact received a dose.
This may be more than just a minor problem. For one thing, there is now a lot of evidence that people are more vulnerable to infection in the days following their jab, likely due to temporary immune suppression. This means a significant proportion of the vaccinated who are susceptible to infection with the current dominant variant are infected in the immediate post-jab period when in many studies and reports they don’t count as vaccinated. This creates a ‘survivorship bias‘ in the remaining vaccinated group that exaggerates vaccine efficacy. For instance, in a study of the U.S. nursing home population published in NEJM, once the post-jab period was included – when the vaccinated experienced higher incidence than the unvaccinated – the overall proportion of vaccinated and unvaccinated groups testing positive was the same at 6.8%. This makes it essential that all the data is presented, including for past-jab periods, and definitions are clear.
A similar problem occurs with the classification of deaths as vaccinated and unvaccinated. New analysis led by Norman Fenton, Professor in Risk Information Management, and Martin Neil, Professor in Computer Science and Statistics, both at Queen Mary, University of London, has highlighted a strange anomaly in the ONS deaths data that may be indicative of a deeper problem. They noticed that if non-Covid deaths in the unvaccinated were plotted against time over the course of the vaccine rollout then a strange spike appeared during the rollout in which the mortality rate among the unvaccinated shot up to well above the background level. The same thing happened with the non-Covid mortality rate in the single-dosed as second doses were rolled out, and the phenomenon was repeated in each age group as vaccines were administered.
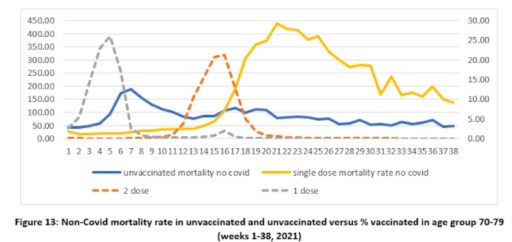
Since there is no obvious reason that vaccination should impact on non-Covid mortality in this way, Prof Fenton, Prof Neil and team argue that this is evidence of a problem in the way the data is recorded or defined. In particular, if it is assumed that the unvaccinated in fact continue to die of non-Covid causes at the background rate and that the additional non-Covid deaths above that are deaths that are actually in the vaccinated but have been misclassified (owing, say, to not counting those who die within 14 days of their jab) then, they argue, a more realistic pattern emerges (see below).
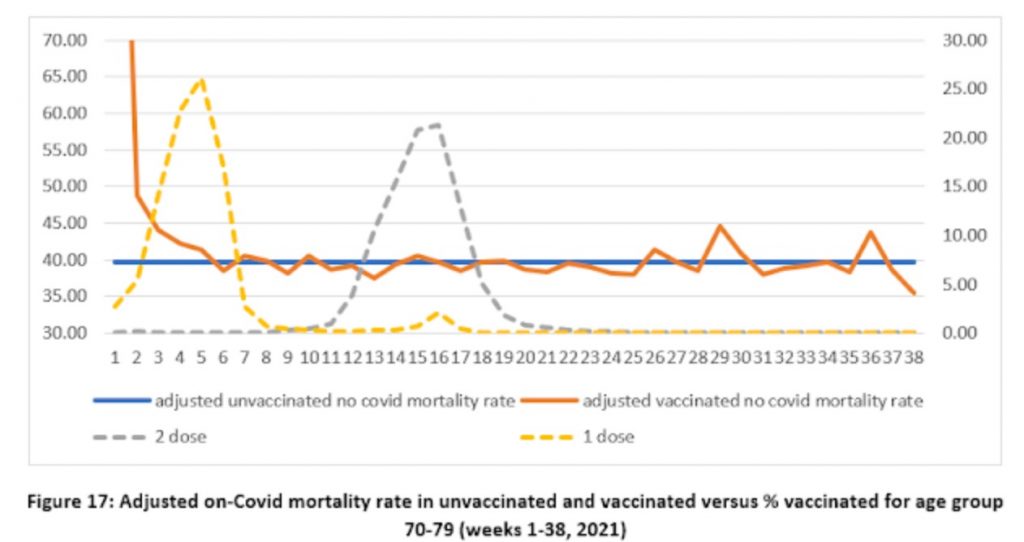
In each age group there is now a spike in non-Covid deaths in the vaccinated right at the start of the rollout, which the team argue makes sense as vaccination was prioritised for the most vulnerable who are more likely to die of any cause. Indeed, it was confusing in the original data that this initial spike was absent and the vaccinated died of non-Covid causes at a lower rate than the unvaccinated despite the most vulnerable being prioritised for vaccination.
The team discovered a different problem when they looked at Covid deaths by vaccination status. Here, the vaccines appear to be highly efficacious, but there is an anomaly that may again be indicative of deeper problems in the data.
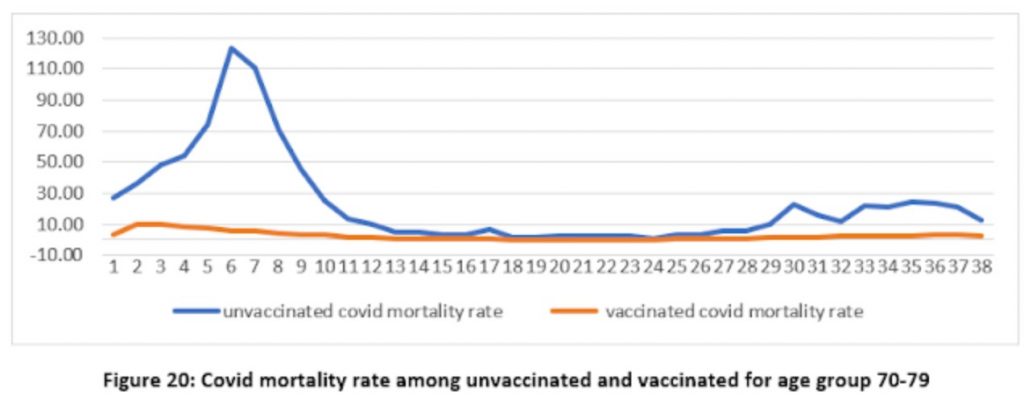
Again a spike appears in the unvaccinated mortality rate where there is none in the vaccinated. Fair enough, you might think, as the vaccines are protecting the vaccinated. However, it’s important to remember that the vaccines are not expected to work until 21 days after the first jab, yet here we have a spike in unvaccinated Covid mortality in the middle of the rollout before most of the vaccines should take effect – referring to figure 17 above we can see that the vaccine rollout in the age group peaked in week five, around the same time as the mortality rate in the unvaccinated peaked (week six), which all seems much too early.
Prof Fenton, Prof Neil and team suggest that the problem here may be in the denominator, that is to say, in how many people are supposed to be in the vaccinated and unvaccinated populations when calculating the mortality rate each week. It’s important to realise that the populations here are changing fast as tens of thousands of people get vaccinated each week. Using the right figure for the right week therefore makes a big difference to the mortality rate reported. Could this anomalous spike in unvaccinated Covid deaths be an artefact of this kind of problem?
Professor Fenton thinks so. He and his team suggest that the problem may be that the relevant denominator or number of people vaccinated for each week is not how many are vaccinated in the week a person dies but in the week they were infected, which is around three weeks earlier on average. What happens if the denominators are shifted by three weeks to allow for this? (Prof Fenton demonstrates the effect of shifting denominators in a short video of a hypothetical example here.)
The effect is remarkable, as shown below (note the change of scale on the y-axis).
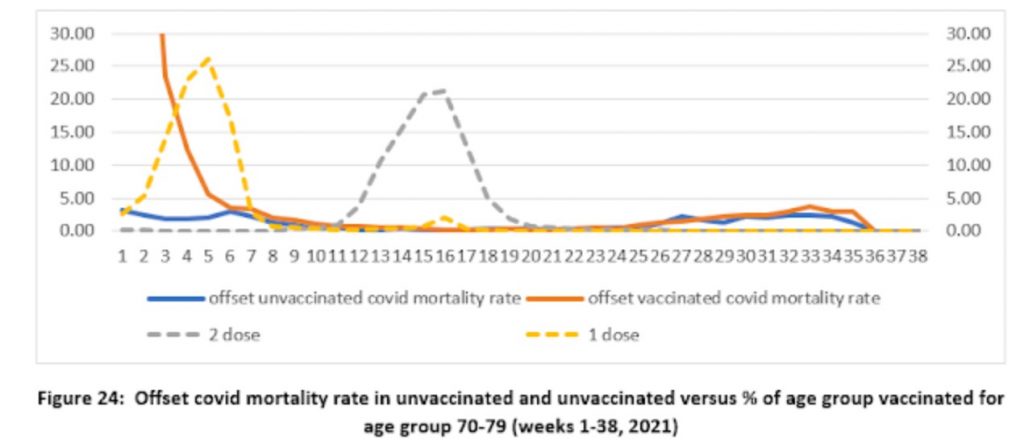
Shifting the population denominator estimates by three weeks means that the number of vaccinated for calculating the vaccinated mortality rate becomes much smaller, making the mortality rate much higher, while the denominator for the unvaccinated becomes much larger, making the mortality rate much lower. This massively reduces the mortality rate in the unvaccinated to low levels – to under five deaths per 100,000 people throughout the period, rather than as many as 125 per 100,000 in week six previously. Instead, a mortality spike appears in the vaccinated at the start of the vaccine rollout (though note that the scale is smaller so it only reaches 30 per 100,000 people), which makes some sense as the vulnerable were prioritised for vaccination and at this point the population of vaccinated was small, so contained a high proportion of vulnerable people. Prof Fenton and team remark that it also tallies with what we know of the increased vulnerability of the recently-vaccinated to infection, as noted above.
The shift in population estimates also greatly reduces the implied effectiveness of the vaccines in the autumn wave, where the lines are now much closer to one another, which is in line with findings from Sweden and elsewhere as vaccine efficacy wanes. Prof Fenton and team suggest that once you take into account the initial spike in the vaccinated, then this new analysis suggests there is “no reliable evidence that the vaccines reduce all-cause mortality”.
So is this what’s going on? There are certainly anomalies that need to be explained, and the analysis by Professor Fenton, Professor Neil and team makes a lot of sense. It deserves to be taken seriously by the ONS and UKHSA.
Stop Press: Watch Prof Fenton discussing his team’s findings with Maajid Nawaz on LBC radio.
The most detailed evidence yet of the devastating damage Covid vaccines can do
By Neville Hodgkinson | TCW Defending Freedom | December 13, 2021
INJECTING millions of people with countless copies of a gene that instructs the body to produce a toxic protein might not seem very sensible. But it was hoped that this approach, the basis of the Covid vaccine, would help minimise damage caused by the protein – the ‘spike’ that the genetically engineered SARS-CoV-2 uses to invade our body cells – when we meet the actual virus.
Last month we reported an American heart specialist’s finding that most of his patients showed biochemical changes signalling increased cardiovascular risk in the weeks following their Covid mRNA jab. Markers for inflammation, cell death and an immune response to coronary artery injury all increased compared with results from a few months previously. The overall results indicated a ‘dramatic’ rise, from 11 per cent to 25 per cent, in the likelihood of a heart attack or similar event occurring some time over the next five years should those changes persist.
The report was presented as an abstract to a meeting of the American Heart Association (AHA), and subsequently published in Circulation, the AHA’s journal. After being made public, an ‘expression of concern’ was added to the abstract, saying there are ‘potential errors’ and it may not be reliable.
There is however every reason to take it seriously – apart from UK researchers reportedly having found similar results, which they are not prepared to publish for fear of losing research money.
Last Friday the most detailed evidence yet of the damage the vaccine can do was presented at an online symposium on Covid science organised by Doctors for Covid Ethics. This is an international group that has long opposed the mass rollout of the Covid jab, arguing in particular that the immune system may attack our own tissues when it detects the presence of the spike protein.
Thousands of deaths have been reported in the wake of the jab, but regulators claim most of these are coincidental, and have neglected detailed investigation of whether or not the vaccine was responsible.
Exactly that kind of investigation was carried out by German pathologist Professor Dr Arne Burkhardt, who has 40 years of experience in the field. He examined the tissues and organs of 15 patients where a post-mortem had been performed, an exceptional opportunity that came about because the bodies were in institutes of legal medicine and institutes of pathology.
There were seven men and eight women aged between 28 and 95. They died between seven days and six months post-injection.
In essence, Burkhardt found internal damage in most of the deceased, caused by a self-destruct process in which immune cells – lymphocytes – had invaded different parts of the body.
In five of the 15 cases, it was concluded that the correlation with the vaccination was very probable; in seven, it was probable; and in two cases it was not clear, but possible. ‘In one case we did not find any of these changes of any significance,’ Burkhardt said.
He presented slides showing how the lymphocytes infiltrated heart muscle in particular, causing inflammation. Resulting lesions were small and easily overlooked, ‘but the destruction of just a few muscle cells may have a devastating effect’, he said. ‘If the inflammatory infiltration is found where the impulse for the contraction of the heart is given, this may lead to heart failure.’
Another finding, also easily missed, was lung damage caused by the lymphocyte invasion, seen in nearly half the cases. Liver, kidney, uterus, brain, thyroid and skin also showed signs of autoimmune damage.
Summarising Burkhardt’s presentation, Canadian microbiologist Professor Dr Michael Palmer said: ‘Anybody with a medical training will see just how devastating the effect of these vaccines can be, at least in those who die after the vaccination . . . we also now know why the authorities were very hesitant to have autopsies performed on such victims.’
Elsewhere, Palmer has argued that even though deaths after vaccination are few compared with the numbers who have received the jab, ‘the total lifetime dose of these messenger RNA vaccines that you can tolerate before you die is limited. We don’t know the exact amount because there is simply not enough experimental data. That’s one of the great scandals of these vaccines, that no proper toxicity studies have been carried out.’
Animal studies have shown clearly that the jab does not just stay at the site of the injection. It circulates widely, such that the spike protein can combine with receptors in many parts of the body, and especially cells that line our blood vessels, causing both clotting and excessive bleeding. Many sudden clusters of deaths (see here and here) have been reported in the immediate wake of the vaccine drives, also observed in athletes.
Burkhardt’s findings, highlighting immune cell infiltration of tissues where the vaccine-induced spike protein has manifested, come in the wake of many warnings of such a mechanism and are supported by various studies suggesting long-term risks. These include:
· US physician Dr Patrick Whelan warned the US Food and Drug Administration a year ago, before the vaccine rollouts, that jabs based on the spike protein may themselves trigger symptoms of severe Covid, including blood clots, brain inflammation and damage to the heart, liver and kidneys. Whelan, a paediatric specialist caring for children with multisystem inflammatory syndrome, urged particular caution over giving the vaccine to children and young adults, as they normally fight off the infection in its early stages. Before any of the vaccines were approved for widespread use in humans, he said, there should be an assessment of the effects on the heart.
· The vaccine includes a modification in the RNA code aimed at synthesising abundant copies of the spike protein – running into trillions of molecules, according to this visual display produced by Dr Charles Hoffe, a Canadian doctor. He says the majority of people who receive the Covid shot ‘are getting blood clots that they have no idea they’re even having.’ The modification, along with a device that protects the RNA mechanism against immediate destruction by the body, may enable the jabs to present a bigger risk in some recipients than natural infection, since this is usually dealt with successfully by a healthy immune system. No one knows exactly how much of the protein is produced by the jab, nor how long it lasts in the body.
· Dr Robert Malone, inventor of the mRNA technology, says ‘multiple peer-reviewed references’ demonstrate that the virus’s spike protein poisons body cells (see for example here), but the vaccine developers have not demonstrated the safety of their version of the protein. Proper evaluation of the risks is still not being carried out, he says.
· Another German pathologist found from autopsies conducted on 40 people who died in the wake of the jab that 30-40 per cent were vaccine-related. Professor Peter Schirmacher believes many such deaths are missed, with doctors attributing them to natural causes.
· American cardiologist and journal editor Dr Peter McCullough has warned that the vaccine can damage heart tissue in ways that go unnoticed at first, but which create scar tissue liable to cause permanent cardiac dysfunction later in life. ‘This will go down as the most dangerous biological medicinal product rollout in human history,’ he says. McCullough has also highlighted an increase in deaths among children in the UK since the NHS began vaccinating teenagers aged 12 and over against Covid.
· An analysis of UK ‘Yellow Card’ adverse reaction data by Dr Tess Lawrie’s Evidence-Based Medicine Consultancy found thousands of reports of blood clotting after the Covid jabs. Almost every vein and artery was affected, and every organ including parts of the brain, lungs, heart, spleen, kidneys, ovaries and liver, ‘with life-threatening and life-changing consequences’. Lawrie urged the UK regulators as long ago as last June to declare the vaccine unsafe for use in humans because of the deaths and adverse reactions being reported.
· A ‘chilling’ acknowledgement of the specific risks of mycocarditis (inflammation of the heart muscle) and pericarditis (swelling in tissue surrounding the heart) following Covid vaccination was issued this month by the UK Health Security Agency. The agency still insists such cases are rare and that most patients recover fully, but evidence such as Burkhardt’s suggests many deaths may go unrecognised as vaccine-related.
It’s a terrible mess, and there is a desperate need for a review of the entire Covid vaccine strategy. UK pathologists, please come to the rescue!
Since Biden’s Injection Order the Rate of Covid Deaths in the US Military Has Quadrupled
Anti-Empire | December 12, 2021
On August 25th Biden ordered that every member of the US military (active, reserve and national guard) must perform a fundamental sacrament of the mind virus cult known as “vaccination”.
A week before the order US military Covid deaths stood at 34.
Presently they stand at 79.
In other words, in the 4 months since the injection order as many US servicemen were deemed to have died with/from Covid as in the entire 17 months before the order was given.
In the entire vaccine-free 2020 fewer than 20 US servicemen died with/from Covid. (24 by March.)
The unvaccinated military of 2020 experienced three times fewer Covid deaths than the heavily injected military of 2021.
Even so at 2 million strong and 79 deaths, a Covid death is still rarer than a lottery win.
The Pentagon says the dead were overwhelmingly “not fully vaccinated,” but the Pentagon also doesn’t consider troops “fully vaccinated” until 14 days after the 2nd dose — that is to say until the initial period of negative vaccine efficiency has ended.
Comirnaty, liability, and how the HHS lies, cheats and steals
By Meryl Nass, MD | December 12, 2021
I checked the Federal Register and there has been no notice that Comirnaty has been added to the National Childhood Vaccine injury Program (NVICP). I confirmed this by checking whether Comirnaty had been added to the childhood schedule, and according to the HRSA, which manages both compensation programs, it has not.
So, if you receive the licensed Comirnaty vaccine, correctly labeled as the brand-name product and not the vaccine being fobbed off as licensed product, and you are injured, you are free to sue the manufacturer for your injury. Could this be why Pfizer wrote, “Pfizer does not plan to produce any product with these new [Comirnaty National Drug Codes] and labels over the next few months while EUA authorized product is still available and being made available for U.S. distribution.”
If, however, you receive the Pfizer-BioNTech vaccine under Emergency Use Authorization, or the Moderna or J and J vaccine, you can’t sue anyone. You have the right to beg HRSA for compensation of lost wages and unpaid medical bills, period. So far, HRSA and the Countermeasures Injury Compensation Program it administers have not paid out one dime for the approximately one million injuries and 20,000 deaths reported to VAERS for any COVID vaccine.
In other words, the federal government (DHHS) has not admitted a single injury was caused by a COVID vaccine. CDC says it has not linked a single death to a COVID vaccine–not even when the patient walked into the vaccination center but got carried out to the morgue. FDA doesn’t know much about myocarditis, Bell’s Palsy, thrombosis, thrombocytopenia, pulmonary emboli, etc. There are no black box warnings on any of the COVID vaccines.
HRSA, FDA, CDC and NIH are all agencies within the federal Department of Health and Human Services. They have all gotten their stories straight. They know nothing and they are just following orders. Heil HHS!
They can’t find a doggone problem in the 20 or so databases they are spending many $millions of your money to “study.”
Want to know the biggest conspiracy in the US right now? It is the HHS.
FDA has access to a bunch of electronic databases it has termed the “BEST” Initiative, and it published a plan to use them to study heart attacks, pulmonary embolism, thrombocytopenia, etc. back in July. Where are the results, FDA? What are you waiting for? (According to CDC, “More than 459 million doses of COVID-19 vaccines were administered in the United States from December 14, 2020, through November 29, 2021.”). It seems clear that we aren’t supposed to be informed of FDA’s findings until everyone possible has been vaccinated, at which point the results will be irrelevant.
In October 2020, FDA’s Steve Anderson told us there were even more databases that would be studied.
On August 23, 2021, FDA announced its databases were inadequate to assess myocarditis, so BioNTech would have to do it for them. Here is what FDA wrote about its inability to use VAERS and its many other databases:
- As noted above, the FDA acknowledges that “We have determined that an analysis of spontaneous postmarketing adverse events reported under section 505(k)(1) of the FDCA [in other words, VAERS–Nass] will not be sufficient to assess known serious risks of myocarditis and pericarditis and identify an unexpected serious risk of subclinical myocarditis.
- Furthermore, the pharmacovigilance system that FDA is required to maintain under section 505(k)(3) of the FDCA [in other words, FDA’s many other databases that cost the taxpayer zillions–Nass] is not sufficient to assess these serious risks.”
NOT SUFFICIENT???
Unsaid, but implied, is that if FDA is incapable of studying thousands of reported cases of myocarditis, it probably cannot study the other serious adverse events that have been reported in conjunction with COVID vaccines.
VAERS has operated for 30 years, collecting reports of vaccine adverse events. It averaged under 100 cases of myocarditis reported yearly until this year. Through November, CDC reports it received 1949 reports of myocarditis and pericarditis, in those under 30. CDC didn’t say what the total number of reports for all ages was.
Somehow, these HHS don’t seem all that concerned that the admitted reporting rate of myocarditis is over 20 times the average during the past 30 years. Why?
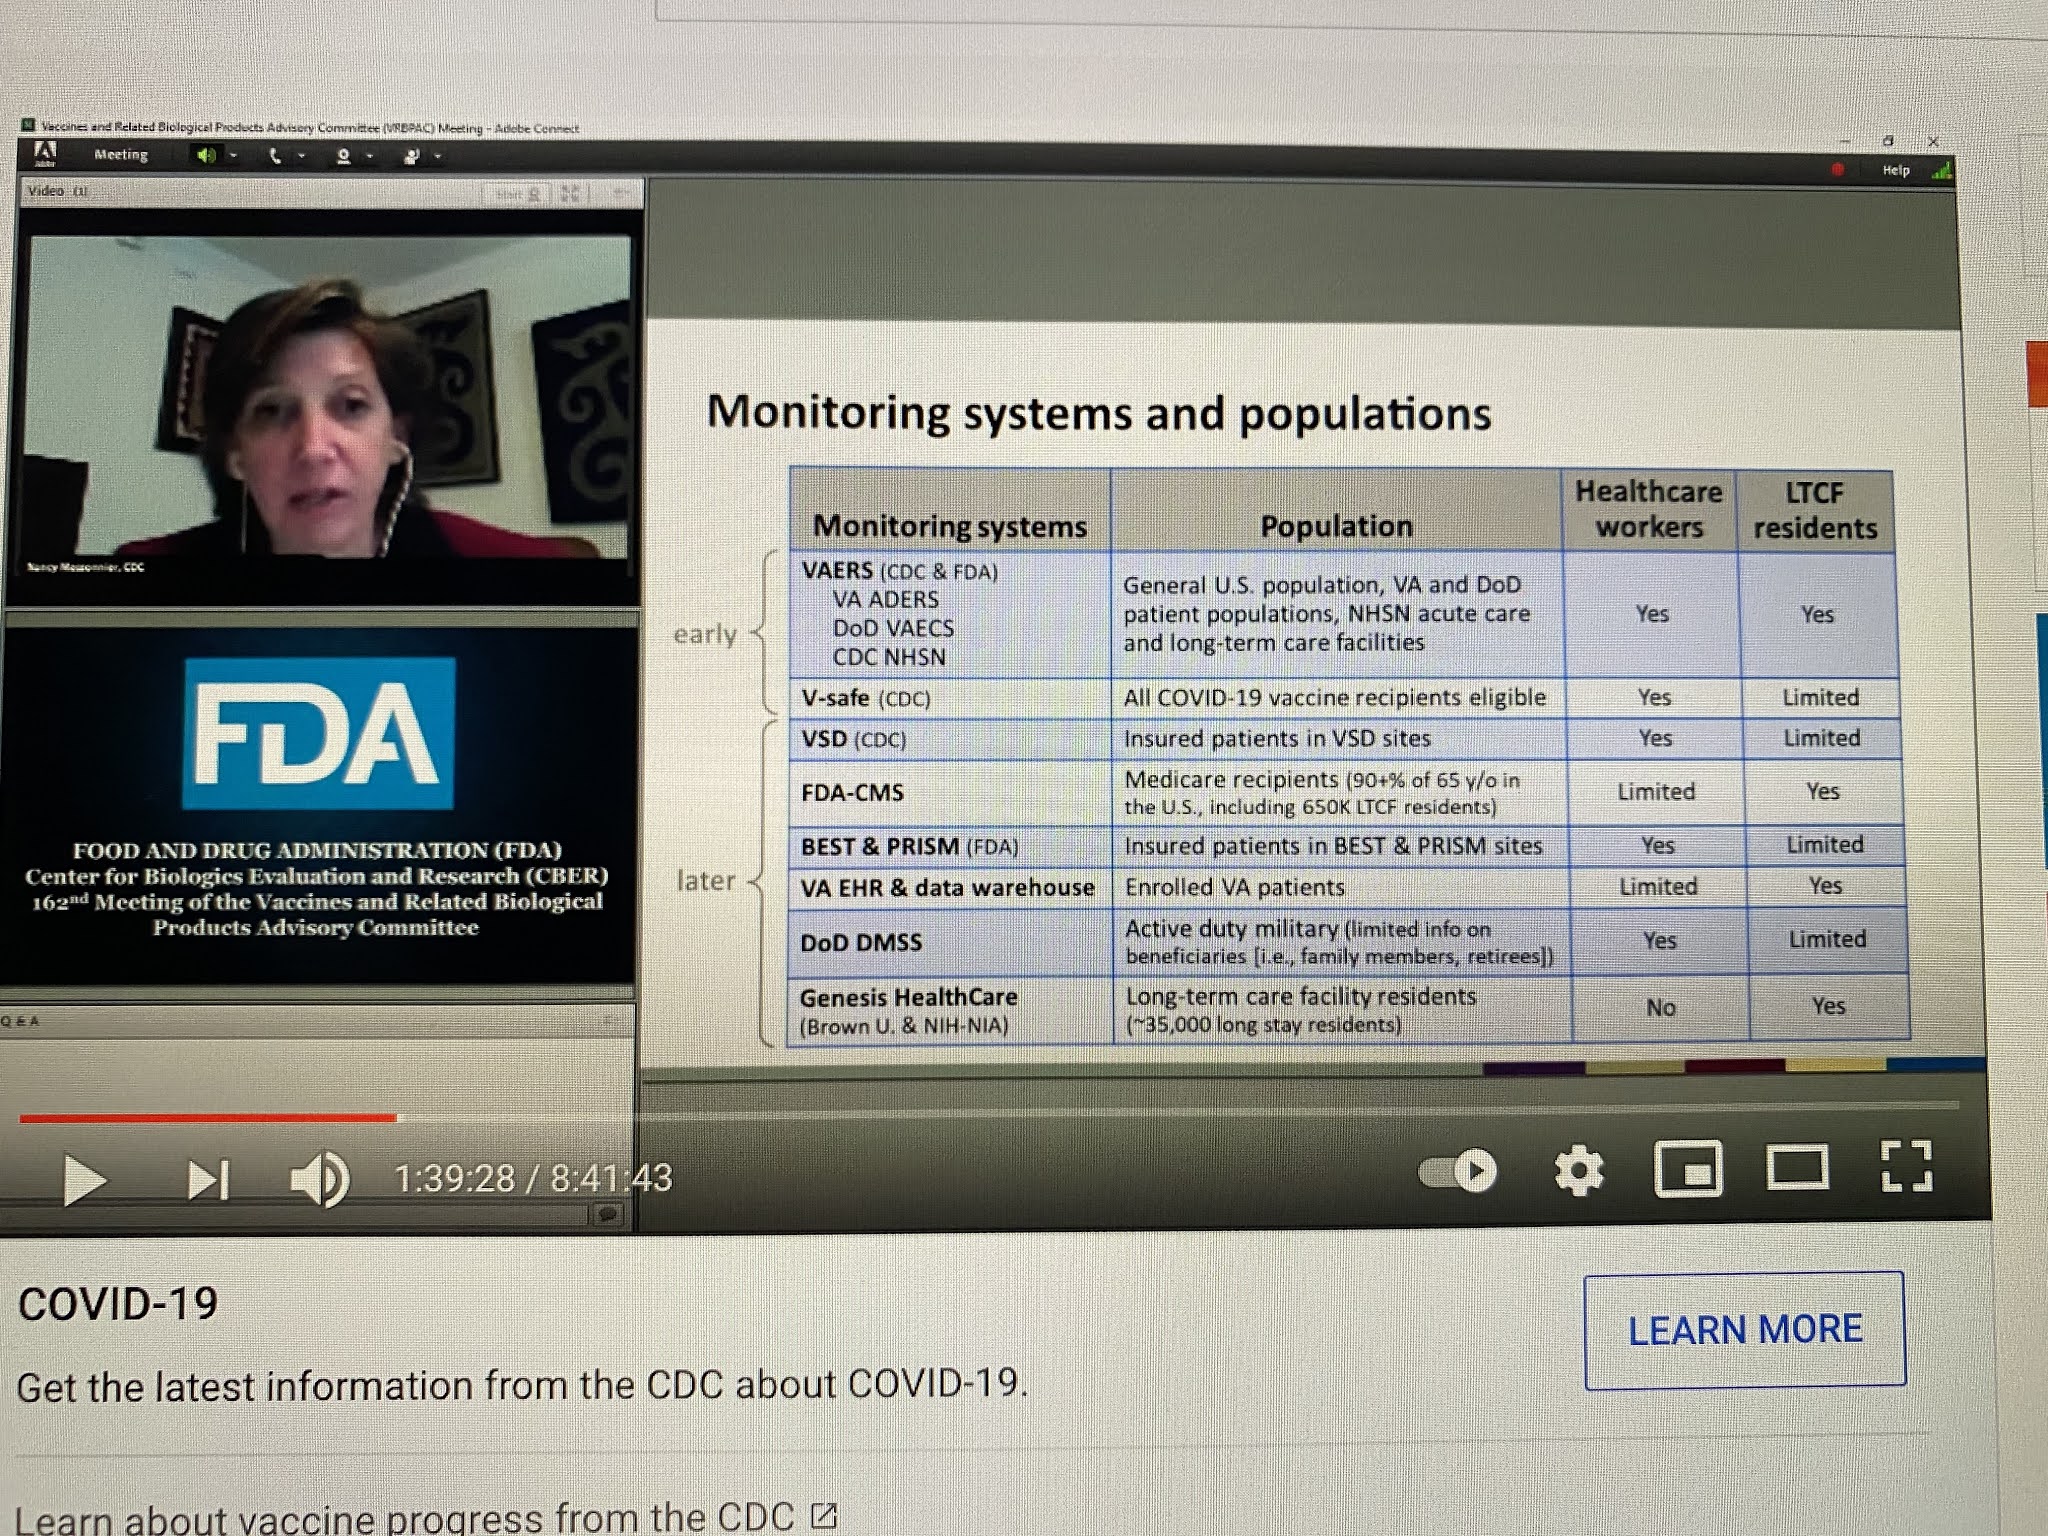
CDC has been even more shady in its analyses of safety as FDA, if that is even possible. Below, Nancy Messonier, then head of Immunizations and Respiratory Diseases at CDC, presented this list of databases that CDC would be using in the evaluation of COVID vaccine safety, on December 10, 2020. Apart from the V-safe (which they stopped talking about last January), VSD (which somehow can’t find any problems, not even myocarditis) and VAERS, all these other databases have been MIA.
NIH, whose job has never been to issue treatment guidelines, but instead to do and fund research, suddenly took over the treatment guidelines for COVID early in 2020. It formed a committee of internal and eternal “experts” to make up the guidelines. How were they chosen? That is not clear, but what is clear is that 16 of these so-called experts had current or recent financial entanglements with Gilead, the maker of remdesivir. NIH and the US Army also owned pieces of remdesivir. A number of other had financial conflicts with Merck. While NIH is the biggest single funder of medical research in the world, I cannot recall seeing a single study it funded on the safety of COVID vaccines. But somehow vaccines are its number one recommendation.
But it is not even clear that the committee is functional. The NIH has been sued to learn whether a vote was even taken by the committee regarding its ivermectin guidelines, which fly in the face of the evidence on ivermectin. How was NIH somehow authorized to issue guidelines in the first place?
Here is what has obviously occurred. All these agencies were told they had to keep quiet on vaccine problems (and perhaps problems of other COVID treatments), and they had to fiddle with their data or their analytic methods, or both, to get the required results. And there was to be NO BAD NEWS, no matter what. And no good news regarding generic treatments.
As we have seen, the so-called scientists and physicians working as bureaucrats in these agencies all caved, sucked it up, did the dirty work, kept their jobs, and betrayed their oaths and the trust of the people of the USA and the world.
Joe Biden spins tornado misinformation
By Gregory Wrightstone | CO2 Coalition | December 12, 2021
President Joe Biden wasted no time in politicizing the recent tornado tragedy that claimed nearly 100 lives in Kentucky, Illinois, Arkansas, Tennessee, and Missouri. Speaking less than 24 hours after the devastation of communities and lives, Biden linked the storms to man-made climate change.
“All I know is that the intensity of the weather across the board has some impacts as a consequence of the warming of the planet and climate change,” Biden said. “The fact is that we all know everything is more intense when the climate is warming. Everything. And obviously it has some impact here.”
Is that really the case? Have violent tornadoes been increasing? The answer to that question is clear, but you won’t find the answer at the agency most responsible for monitoring such things. It appears that the National Oceanic and Atmospheric Administration (NOAA) is playing games with tornado data. In 2017, while researching tornado data, I archived the NOAA site’s page on tornadoes and data. At the time, NOAA specifically warned that pre-Doppler radar records of tornadoes (before 1995) are unreliable:
“One of the main difficulties with tornado records is that a tornado, or evidence of a tornado, must have been observed. Unlike rainfall or temperature, which may be measured by a fixed instrument, tornadoes are short-lived and very unpredictable. A tornado in a largely unoccupied region is not likely to be documented. Many significant tornadoes may not have made it into the historical record since Tornado Alley was very sparsely populated during the early 20th Century.”
Because of this, NOAA recommended (at the time) only using the strongest tornadoes as a measure of pre-Doppler numbers and provided this chart that documented an overall decrease in the number of strong and violent storms that were categorized as >EF 3 (I have added the carbon emissions to the chart).

Figure 1 – Tornadoes: NOAA (2017) NCEI Historical Records and Trends, https://www.ncdc.noaa.gov/climate-information/extreme-events/us-tornado-climatology/trends CO2: Boden 2016 Global Regional and National Fossil-Fuel CO2 Emissions. CDIAC
Accessing the very same link for NOAA today takes one to their latest iteration, which showcases a chart of ALL tornadoes dating back to 1950 and shows a steady and significant rise in the number of tornadoes from 1950 to the late 1990s. Bear in mind, that just a few years ago, NOAA specifically warned against using exactly this data because it would under-count the numbers before 1995.

Figure 2 – Tornadoes: NOAA (2017) NCEI Historical Records and Trends, https://www.ncdc.noaa.gov/climate-information/extreme-events/us-tornado-climatology/trends
Updated data on tornadoes through 2020 is available at ustornadoes.com and showcases just why using pre-Doppler data is misleading. Figure 3 shows the pre-Doppler numbers of tornadoes reported. Importantly, this is not capturing increasing actual numbers of tornadoes that occurred, but rather increased reporting.

Figure 3 – US Pre-Doppler Tornadoes https://www.ustornadoes.com/annual-tornadoes/
Figure 4, below, is a chart of all Doppler-era tornadoes showing no increase at all.

Figure 4 – US pre-Doppler Tornadoes https://www.ustornadoes.com/annual-tornadoes
All of this begs the question: Why would a government agency promote flawed data? The answer is simple: It “confirms” their preconceived notion of increasing severe weather and provides support for alarming claims of ever-increasing death and destruction.
You can be sure that Joe Biden will not be the last to use these deaths and this tornado deception to spread fear and alarm to support their plans to spend trillions of dollars to solve a non-existent climate crisis. The Biden administration should “follow the science” and get to the business of helping the victims and stop spreading misinformation.
Gregory Wrightstone is a geologist, executive director of the CO2 Coalition, Arlington, Va., and author of “Inconvenient Facts: The science that Al Gore doesn’t want you to know.”
Queensland will let essential businesses like grocery stores and pharmacies introduce vaccine passports
By Ken Macon | Reclaim The Net | December 12, 2021
When the state-wide lockdown is lifted, Queensland will allow supermarkets and other businesses providing essential services to implement vaccine passports. The provision could deny those without a vaccine passport easy access to food and other basics.
Queensland will reopen its borders this week. The Health Minister Yvette D’Ath said that once the borders reopen, new health directives will be released, which could be less strict on businesses that have implemented health mandates.
“In the coming days, the Government will issue the guidelines required for business and industry as our border reopens,” she said in a statement.
“This will include information on managing close contacts in the workplace.
“Our objective is to provide an environment where business, particularly essential business, remains open.”
Starting December 17, Queenslanders will be required to show a vaccine passport to enter restaurants, cafes, pubs, bars, clubs, cinemas, theaters, museums, libraries, and stadiums.
The vaccine passport mandate does not apply to businesses providing essential services, like supermarkets, grocery stores, pharmacies, and post offices. However, the Small Business Minister Di Farmer said that essential services can implement vaccine passports if they choose to, especially if they want to continue operations without restrictions.
“The essential services are the things that really remained open during lockdown,” Farmer told 4BC Radio on Wednesday.
“There will also be a range of other businesses who may make the choice just to only have their vaccinated staff and patrons using their business.”
In a press conference on December 9, Farmer explained that every business would be allowed to enforce vaccine passports.
“Any business is able to make that decision, and a lot of them are actually thinking about that very seriously,” she said.
“[When Queensland opens up] you will need to be protected and businesses all over Queensland will be making that decision.
“If a person decides not to be vaccinated, then those are the things that they will take into consideration.”
‘This untested vaccine should never have been released. The truth will out and heads will roll’

By Neville Hodgkinson | TCW Defending Freedom | June 15, 2021
THE Covid vaccine should never have been released to the public because of its experimental nature, and it is giving rise to such serious complications and concerns over future risks that the rollout should be stopped immediately.
So says Dr Roger Hodkinson, a highly experienced retired pathologist who chairs an American biotechnology company which both sells a Covid test and is developing tests for early diagnosis of cancer.
His warning comes as the UK’s regulator is being urged to declare the Covid vaccines ‘unsafe for use in humans’ because of the high number of vaccine-attributed deaths (1,253) and adverse reactions (888,196, with 256,224 individual reports) over the five months to May 26. Hodkinson describes this report, by Dr Tess Lawrie, as ‘a devastating analysis of the whole mess’.
In a hard-hitting interview with former BBC and ITV journalist Anna Brees, Dr Hodkinson says a ‘vast number’ of physicians do not buy into the ‘idiocy’ of the global vaccination campaign, but are reluctant to speak out because they fear for their jobs. Pressure to conform has come from politicians, mass media, and the medical colleges.
You can watch the interview here.
Hodkinson came under intense criticism last year after likening Covid to ‘a bad flu season’ when trying to counter what he called the ‘utterly unfounded public hysteria driven by the media and politicians’.
Brees has also faced censorship for what she calls her ‘citizen journalism’. She was blasted by TV presenter Piers Morgan as a ‘conspiracy-theory-spewing imbecile’ when she challenged his support for last Christmas’s lockdown.
Hodkinson tells her in the new interview: ‘This is not just another news story. This is the biggest story of our times. It’s a tragedy that journalists at large are not following your example.’
He assures her that he is not a lone voice, but part of an international group of doctors who are working to try to end the vaccine rollout, which they regard as a tragic betrayal of medical ethics.
In an appeal directed to politicians, Hodkinson says the evidence of harm from the Covid vaccines ‘is so overwhelming that now is the time for a leader to put his or her standard in the ground and say, “I was wrong. I was led astray by my advisers, who had given me terrible information to act upon”. If you take that brave step, many people will forgive you for honesty, and your star can actually rise for the next election.’
Of the vaccine, he says: ‘This is of course an experimental vaccine. It should never have been released. It was never an emergency which predicated the development of the vaccine. And as with all vaccines, there are complications, which were predictable, with time. But there was never enough time given for the clinical trial, which only lasted 4-6 months.
‘In particular, complications are now coming out which are very disturbing. The latest, over the last few days, starting off in Israel, is the frequency of myocarditis in young adult males. And getting worse the younger they are, in teenagers.
‘Myocarditis is a medical term for inflammation of the heart. It is never mild, as they are describing it – meaning not terribly significant. The heart cells that make up the heart muscles never regenerate. It’s not like the liver, or the kidney, that regenerates. When a heart muscle dies, it’s dead. And it’s never replaced. So muscle cells in the heart will be dying. The number is hard to determine, because the person is still alive.
‘But I can tell you with categorical certainty that myocarditis is totally unpredictable in terms of its long-term consequences. It may only present 20 years later because of the reserve of the heart having been destroyed. We are talking here about cardiac arrhythmias, abnormal heartbeats, heart failure and so on. This is a most worrying development. And it’s exactly the kind of complication that would have come out of a normal clinical trial for a vaccine, which typically takes a number of years.’
Brees commented: ‘There must be thousands of thousands of doctors who completely disagree with you. Or is there something to keep them quiet? Why should we listen to you?’
Hodkinson replied: ‘Let me assure you that the statistics – when the books are written – will be exactly the other way round. I suspect – and it’s impossible to confirm, because of the intimidation that [medical] colleges across the world are putting on individual physicians – including me – there is a vast number of physicians who do not buy into this idiocy. Physicians who are well trained can see through this immediately as so transparently stupid. It’s medical idiocy of the most grotesque degree that’s going on.
‘The bottom line is that this vaccination of everybody should stop immediately.
‘The predicate for all these vaccines was the statement that this was a medical emergency on a most sinister global scale. Well, it never was, by any definition. If you take away that underpinning requirement, if you take away the emergency, there was absolutely no reason for the development of a vaccine that contravened all the normal safeguards for the introduction of something on such a global scale.
‘There’s never, ever, in medical history, been a vaccination programme on this scale, involving billions of people, with the most minor attention to long-term consequences.
‘The story is not yet over. Look, the last time I checked, pregnancy takes nine months. You cannot conceivably check for fertility issues if you are only doing a clinical trial for 4-6 months, that never even included pregnant women other than those that got pregnant during the trial. And there were only 40 of them. There are very serious scientific possibilities here for long-term infertility. The studies have not been done.
‘We do know for a fact that the placenta and the testis have a very heavy expression of the receptor for the spike protein which is being produced in large amounts by the vaccines. We also know that during a SARS epidemic, which was a very similar organism, there were a small number of reports – but it was a small number of people who came down with it – of orchitis, a medical term for inflammation of the testis. So on the male side of fertility, there are serious scientific grounds for worry.
‘On the female side there’s equal concern, because it comes out of the obscure Pfizer submission to the Japanese regulatory authority that the vaccine particles – the tiny lipid nano-particles that are part of the vaccine – locate very heavily in the ovary. This was a rat study, but it still showed, most unexpectedly, heavy localisation of these particles in the ovary. If that is in the literature, it needs to be excluded as a possible long-term complication. And you can’t do that unless you check fertility issues over a number of years.
‘I’m telling you that this is a very serious problem. I don’t mean you, Anna Brees. I mean you, the general public, the politicians, the people driving the bus: GET A GRIP ON YOURSELVES! This is serious medical science. And you’re mucking around with billions of people’s health, for the most tenuous of reasons. And it’s totally and utterly unacceptable.
‘When it comes to injecting this stuff into the arms of children, I call that state-sanctioned child abuse, on the most monstrous scale. It is utterly unacceptable, and it should stop immediately.’
Last week, in an interview with Real America’s Voice, Dr Mike Yeadon, former vice-president for research with the Pfizer drug company, warned that children are 50 times more likely to be killed by the Covid vaccines than by the virus itself. You can watch the interview here.
Brees, who has a 12-year-old child, told Hodkinson that she had seen doctors on the BBC Newsround children’s programme saying the vaccine is safe, and encouraging its use. He said: ‘They are culpable of extreme medical malpractice.*
‘There are two underpinning ethics. First, do no harm – and we are seeing that playing out in spades now, with all these complications. The second one, with respect to vaccination, is informed consent. There is no informed consent, because people are not being told this is UNSAFE. The billboards say one, four-letter word: SAFE. That’s a contortion of medical language. It’s Orwellian.’
In a blistering criticism of medical colleges which act as ‘enforcers’ of vaccination programmes, Hodkinson said: ‘It is medical negligence of the highest order to be agreeing with something the government wants you to do that you know is harmful.’
But, Brees asked, with all the censorship taking place, do they know it’s harmful?
Hodkinson replied: ‘The worst censorship is with physicians. That’s the ultimate resource of trust and reliable information for the public.
‘But the other two sources are being equally censored, in a brutal fashion. The mainstream media is not running anything. [TCW has suggested that one reason for this is the amount of government advertising.] Of course, you don’t bite the hand that feeds you, do you? And social media is censoring everything that is not palatable to Facebook, Twitter, YouTube etc.’
He concluded: ‘I do think the truth will out. There will be books being written as we speak that condemn in the strongest possible terms this entire mad episode in human history. And heads will roll. There will be blood in the gutter. And that is going to happen, in my opinion, very, very soon. Because something so crazy as this, something so gigantically mad, cannot be suppressed.’
Hodkinson believes that when this happens, the medical colleges will be ‘massively changed in terms of how they address their obligations to the public.
‘Politicians, regulatory bodies, media, individual physicians, so many are culpable of the most terrible crime ever committed on humanity. It’s on that scale. It’s absolutely tragic.’
* A complaint about this programme was made by a TCW reader who tweeted the response here.
Stunning data from South Africa suggest Omicron may be the end of Covid (and of Covid vaccines)
By Alex Berenson | Unreported Truths | December 11, 2021
A six-tweet thread from a South African engineer sums up the apparent state of play: Omicron appears more contagious but far milder than earlier strains of Covid.
South African physicians and hospitals have leaned in this direction all along. But now we have close to three weeks of data and they are saying so with increasing certainty. The lag from symptoms to severe disease is about a week. If large numbers of patients were going to progress to hospitalization or intensive care, they almost surely would have done so by now.
Perhaps one more week and we will know for sure, but at this point it would be a stunning reversal if Omicron were NEARLY as dangerous as earlier strains. And the Omicron’s mildness is not because South Africa is highly vaccinated; only about 1 in 4 South Africans is fully vaccinated.
What has not yet been said – and will surely NOT be by the media – is that assuming this data holds, Omicron’s emergence should end any and all vaccination efforts with the mRNA or DNA/AAV vaccines. Their risk profile has been steadily worsening – one has yet coherently explained the synchronized rise in all-cause mortality in highly vaccinated countries. The Netherlands saw all-cause mortality 41 percent above normal (yes, 41 percent) in its most recent week of data. Only one of five of those deaths was Covid related.
Giving these vaccines for a virus that appears to be becoming a cold for most people is horrendously bad public policy. Especially since the vaccines don’t appear to work very well against Omicron in any case.
All that’s left now is to track the mess from the vaccines. Let’s hope it’s temporary.
The end.
SOURCE:
Americans are smartening up about the boosters
By Meryl Nass, MD | December 11, 2021
According to the CDC, as of December 10, 2021:
About 200.7 million people, or 60.5% of the total U.S. population, have been fully vaccinated.*
About 49.9 million additional/booster doses in fully vaccinated people have been reported.“
What does this really mean?
- At least 16% of those who got their first dose of a two shot series decided not to go back for number 2, or perhaps died.
- Less than 25% of those who did become fully vaccinated have gone back for a first booster.
I think a large chunk of the population was sucked into getting the vaccines initially, but a considerable number of them have seen through the vaccine propaganda and realize it is not solving the COVID problem, and is not providing vaccinated individuals much protection.
Perhaps some of them have noticed that Israel is already talking about shot #4. Or they may have heard that if the Omicron strain continues to cause very mild disease, it will serve as as a natural vaccine, inoculating people who get it.
Latest Modelling on Omicron Ignores All Evidence of Lower Severity, Among Numerous Other Problems
By Mike Hearn | The Daily Sceptic | December 11, 2021
Today the Telegraph reported that:
Experts from the London School of Hygiene and Tropical Medicine (LSHTM) predict that a wave of infection caused by Omicron – if no additional restrictions are introduced – could lead to hospital admissions being around twice as high as the previous peak seen in January 2021.
Dr Rosanna Barnard, from LSHTM’s Centre for the Mathematical Modelling of Infectious Diseases, who co-led the research, said the modellers’ most pessimistic scenario suggests that “we may have to endure more stringent restrictions to ensure the NHS is not overwhelmed”.
As we’ve come to expect from LSHTM and epidemiology in general, the model forming the basis for this ‘expert’ claim is unscientific and contains severe problems, making its predictions worthless. Equally expected, the press ignores these issues and indeed gives the impression that they haven’t actually read the underlying paper at all.
The ‘paper’ was uploaded an hour ago as of writing, but I put the word paper in quotes because not only is this document not peer reviewed in any way, it’s not even a single document. Instead, it’s a file that claims it will be continually updated, yet which has no version numbers. This might make it tricky to talk about, as by the time you read this it’s possible the document will have changed. Fortunately, they’re uploading files via GitHub, meaning we can follow any future revisions that are uploaded here.
Errors
The first shortcoming of the ‘paper’ becomes apparent on page 1:
Due to a lack of data, we assume Omicron has the same severity as Delta.
In reality, there is data and so far it indicates that Omicron is much milder than Delta:
Early data from the Steve Biko and Tshwane District Hospital Complex in South Africa’s capital Pretoria, which is at the centre of the outbreak, showed that on December 2nd only nine of the 42 patients on the Covid ward, all of whom were unvaccinated, were being treated for the virus and were in need of oxygen. The remainder of the patients had tested positive but were asymptomatic and being treated for other conditions.
The pattern of milder disease in Pretoria is corroborated by data for the whole of Gauteng province. Eight per cent of Covid-positive hospital patients are being treated in intensive care units, down from 23% throughout the Delta wave, and just 2% are on ventilators, down from 11%.
Financial Times, December 7th
The LSHTM document claims to be accurate as of today, but just ignores the data available so far and replaces it with an assumption; one that lets them argue for more restrictions.
What kind of restrictions? The LSHTM modellers are big fans of mask wearing:
All scenarios considered assume a 7.5% reduction in transmission following the introduction of limited mask-wearing measures by the U.K. Government on November 30th 2021, which we assume lasts until April 30th 2022. This is in keeping with our previous estimates for the impact of increased mask-wearing on transmission.
I was curious how they arrived at this number given the abundant evidence that mask mandates have no impact at all (example one, example two). But no such luck – a reference at the end of the above paragraph points to this document, which doesn’t contain the word “mask” anywhere and “7.5%” likewise cannot be found. I wondered if maybe this was a typo but the claim that the relevant reference supports mask wearing appears several times and the word “mask” isn’t mentioned in references before or after either.
There are many other assumptions of dubious validity in this paper. I don’t have time today to try and list all of them, although maybe someone else wants to have a go. A few that jumped out on a quick read through are:
- An assumption that S gene drop-outs, i.e. cases where a PCR test doesn’t detect the spike protein gene at all, are always Omicron. That doesn’t follow logically given the very high number of mutations and given that theoretically PCR testing is very precise, meaning a missing S gene should be interpreted as “not Covid”. Of course, in reality – as is by now well known – PCR results are routinely presented in a have-cake-and-eat-it way, in which they’re claimed to be both highly precise but also capable of detecting viruses with near arbitrary levels of mutation, depending on what argument the user wishes to support.
- “We use the relationship between mean neutralisation titre and protective efficacy from Khoury et al. (7) to arrive at assumptions for vaccine efficacy against infection with Omicron” – The cited paper was published in May and has nothing to say on the topic of vaccine effectiveness against Omicron, which is advertised as being heavily mutated. Despite not citing any actual measured data on real-world vaccine effectiveness, the modelling team proceeds to make arguments for widespread boosting with a vaccine targeted at the original 2019 Wuhan version of SARS-CoV-2.
- They make scenarios that vary based on unmeasurable variables like “rate of introduction of Omicron”, making their predictions effectively unfalsifiable. Regardless of what happens, they can claim that they projected a scenario that anticipated it, and because such a rate is unknowable, nobody can prove otherwise. Predictions have to be falsifiable to be scientific, but these are not.
- Their conclusion says “These results suggest that the introduction of the Omicron B.1.1.529 variant in England will lead to a substantial increase in SARS-CoV-2 transmission” even though earlier in the ‘paper’ they say they assume anywhere between a 5%-10% lower transmissibility than Delta to 30%-50% higher (page 7), or in other words, they have no idea what the underlying difference in transmissibility is – and that’s assuming this is actually something that can be summed up in a single number to begin with.
Analysis
If you’re new to adversarial reviews of epidemiology papers some of the above points may seem nit-picky, or even made in bad faith. Take the problem of the citation error – does it really matter? Surely, it’s just some sort of obscure copy/paste error or typo? Unfortunately, we cannot simply overlook such failures. The phenomenon of apparently random or outright deceptive citations is one I’ve written about previously. This problem is astoundingly widespread in academia. Most people will assume that a numerical claim by researchers that has a citation must have at least some level of truth to it, but in fact, meta-scientific study has indicated the error rate in citations is as high as 25%. A full quarter of scientific claims pointing to ‘evidence’ turn out when checked to be citing something that doesn’t support their point! This error rate feels roughly in line with my own experiences and that’s why it’s always worth verifying citations for dubious claims.
The reality is that academic output, especially in anything that involves statistical modelling, frequently turns out to not merely be unreliable but leaves the reader with the impression that the authors must have started with a desired conclusion and then worked backwards to try and find sciencey-sounding points to support it. Inconvenient data is claimed not to exist, convenient data is cherry picked, and where no convenient data can be found it’s just conjured into existence. Claims are made and cited but the citations don’t contain supporting evidence, or turn out to be just more assumptions. Every possible outcome is modelled and all but the most alarming are discarded. The scientific method is inconsistently used, at best, and instead scientism rules the day; meanwhile, universities applaud and defend this behaviour to the bitter end. Academia is in serious trouble: huge numbers of researchers just have no standards whatsoever and there are no institutional incentives to care.
Some readers will undoubtably wonder why we’re still bothering to do this kind of analysis given that there’s nothing really new here. On the Daily Sceptic alone we’ve covered these sorts of errors here, here, here, here, here and here – and that’s not even a comprehensive list. So why bother? I think it’s worth continuing to do this kind of work for a couple of reasons:
- Many people who didn’t doubt the science last year have developed newfound doubts this year, but won’t search through the archives to read old articles.
- The continued publication of these sorts of ‘papers’ is itself useful information. It shows that academia doesn’t seem to be capable of self-improvement and despite a long run of prediction failures, nobody within the institutions cares about the collective reputation of professors. The appearance of being scientific is what matters. Actually being scientific, not so much.
Featured Video

EUROPE FEARS RUSSIA’S NEXT MOVE / Ian Proud
or go to
Aletho News Archives – Video-Images
New Book
New Book: No Autoimmunity The Body Doesn’t Attack Itself
Lies are Unbekoming | September 24, 2026
 The label for Humira, once the best-selling drug in the world, lists its risks in plain print. One of them, in the label’s own words, is new “autoimmune” disease.
A drug prescribed for a condition labelled autoimmune carries a warning that it can cause a condition labelled autoimmune. That contradiction sits in every box, on a folded paper almost nobody reads.
My new book starts there.
No Autoimmunity: The Body Doesn’t Attack Itself
For seventy years, “your body is attacking itself, and we don’t know why” has ended the conversation for people diagnosed with multiple sclerosis, lupus, rheumatoid arthritis, Hashimoto’s, Type 1 diabetes, Crohn’s and psoriasis. More than eighty conditions now carry the autoimmune label. The diagnosis comes with a prescription for life. It almost never comes with a question about cause.
This book asks the question and answers it from the framework’s own records: its drug labels, its journals, its regulatory filings, and its own experiments. … continue
Blog Roll
 Aletho News
- Merz regime wants ‘secret police’ – opposition
- Israeli settlers terrorize West Bank Palestinians with state-provided drones: Report
- They see them, then kill them: Israeli quadcopters track, deliberately target civilians in Gaza
- Debunked: Trump’s egregious UNGA claims on war against Iran crumble under scrutiny
- Europe was part of the infrastructure of US aggression against Iran: Deputy FM
- New evidence on the Bucha Massacre
- Italy and France debunk reports CIA issued ‘Russian drone threat’ warning
- How Russia is Rewiring the Global South
- Britain’s elites want you ready to die for a war they keep imagining
- Inside Ukraine’s propaganda operation targeting Americans
- If Americans Knew
- Trump betrayed voters with his campaign lies and prioritized a foreign country once he took office
- Netanyahu calls Israel’s war in Gaza ‘opposite of genocide’ in UN speech to near-empty hall
- Settler Kidnappings: Torture, Sexual Abuse and Terrorisation of Palestinian Abductees as Israel Deepens Annexation of West Bank
- Gaza winter nears as 162,000 tents become unusable, raising fears of humanitarian crisis
- Netanyahu says, “It’s the opposite of genocide”; UN says Gaza economy is world’s ‘most severe crisis on record’ – Daily Update
- Israel’s US-Backed Assault on Gaza Has Created the ‘World’s Most Severe Economic Crisis on Record’: UN
- ‘Protecting U.S. Citizens’… From Israel
- ‘This is where I live now, the back of a truck’: a day in the life of a grandmother in Gaza
- In UN Speech, Iran’s President Displays Pictures of Children Killed by US, Brings Attention to Israel’s Nuclear Arsenal
- Israel displaces hundreds of Palestinians amid wave of demolitions in West Bank
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

