Aletho News

ΑΛΗΘΩΣ

Political Appointee CDC Director Rochelle Walensky Overrides FDA Vaccine Advisory Committee and Authorizes Pfizer Booster Shots

The Last Refuge | September 24, 2021

Centers for Disease Control (CDC) Director Rochelle Walensky has overridden the recommendations of the FDA vaccine advisory committee and authorized booster shots for individuals who took the Pfizer vaccine. The boosters are for anyone who took the Pfizer vaccine six months ago or more, in addition to all those with underlying medical health conditions that make them susceptible to the COVID-19 variants. [CDC Announcement HERE]

Additionally, all healthcare workers and basically all those who were previously designated as “essential workers”, including those in the food supply chain, are authorized to receive the vaccine. According to Joe Biden’s speech that followed the unilateral declaration of the CDC, this decision means, “60 million Americans are now eligible for a booster six months after their second shot. And up to 20 million who will receive their — received their earlier Pfizer shot at least six months ago are eligible today.”

The unilateral booster declaration does not include authorization for Moderna or Johnson and Johnson, only Pfizer. Apparently, the Pfizer lobbying group has deeper pockets and is more politically connected. The Moderna and J&J decision will be made at a later date. “We will also evaluate with similar urgency available data in the coming weeks to swiftly make additional recommendations for other populations or people who got the Moderna or Johnson & Johnson vaccines.” (link)

September 29, 2021 Posted by | Timeless or most popular, War Crimes | , , , | Leave a comment

14 Signs of Vitamin D Deficiency

By Dr. Joseph Mercola | September 27, 2021

Vitamin D is also called the sunshine vitamin since your skin makes vitamin D when exposed to ultraviolet light from the sun.1 Vitamin D performs many functions within the body, including maintaining adequate levels of calcium and phosphate, essential for normal bone mineralization.2

It helps reduce inflammation, which is necessary for the modulation of cell growth and immune function. Vitamin D also affects genes that help regulate cell differentiation and apoptosis.

The main indicator of your vitamin D level is 25-hydroxyvitamin D (25OHD). Data collected from the National Health and Nutrition Examination Survey in 2005-2006 showed a deficiency prevalence of 41.6% in the U.S. population.3 However, as I discuss later in this article, today as many as 80% of people may be deficient in vitamin D.

It’s important to note that how the measurement of insufficiency and deficiency is defined depends on the serum concentrations used. Some researchers use a level of 20 nanograms per milliliter (ng/mL) or 50 nanomoles per liter (nmol/L); the ng/mL is used most frequently in the U.S. and nmol/L is the standard in Europe.

However, GrassrootsHealth Nutrient Research Institute recommends vitamin D serum concentration levels from 40 ng/mL to 60 ng/mL or 100 nmol/L to 150 nmol/L.4 At this level, the number of people who are likely deficient in vitamin D would be significantly higher.

14 Signs You Might Have a Vitamin D Deficiency

During cold and flu season when respiratory illnesses are prevalent, or if you’re immune-compromised and want to build up your natural defenses against other infections, it is essential to maintain healthy levels of vitamin D to help reduce your risk of viral and bacterial illness.5,6 A blood test is the best way to determine your vitamin D levels, but here are some symptoms that may indicate your levels are low:

1.Aching muscles — Nearly half of all adults are affected by muscle pain.7 Researchers believe most of those are deficient in vitamin D. Some studies have suggested that nerves have vitamin D receptors that affect the perception of pain. In one animal model, research demonstrated a vitamin D-deficient diet can induce deep muscle hypersensitivity that was not connected to low levels of calcium.8

2.Painful bones — Vitamin D regulates the level of calcium in your body, necessary to protect bone health.9 Vitamin D deficiency can cause your bones to soften, called osteomalacia. This may be a precursor to osteoporosis.

3.Fatigue — This is a common symptom of a variety of different health conditions, including sleep deprivation. Researchers have found that supplementing cancer patients suffering from fatigue can improve their symptoms.10

In one study11 using 174 adults with fatigue and stable medical conditions, the researchers found 77.2% were deficient in vitamin D. After normalizing their level, the fatigue symptoms improved significantly.

4.Reduced muscle performance — Vitamin D deficiency is as common in athletes as in others. Vitamin D is crucial for muscle development, strength and performance. Older adults taking a vitamin D supplement have a reduced risk of falls and improved muscle performance.12

Correction through oral supplementation or sensible sun exposure may reduce symptoms of stress fractures, musculoskeletal pain and frequent illness. Vitamin D also has a direct effect on muscle performance. In one paper from the Journal of the American Academy of Orthopaedic Surgeons, the author wrote:13

“Higher serum levels of vitamin D are associated with reduced injury rates and improved sports performance. In a subset of the population, vitamin D appears to play a role in muscle strength, injury prevention, and sports performance.”

5.Brain health — Vitamin D is also essential for your brain health. Symptoms of deficiency can include dementia caused by an increase of soluble and insoluble beta-amyloid, a factor in Alzheimer’s disease.14 Research has also found an association with depression15 that may be associated with the function of vitamin D buffering higher levels of calcium in the brain.16

Vitamin D deficiency in pregnant women can increase the risk of autism and schizophrenic-like disorders in the baby.17 One study of people with fibromyalgia found a vitamin D deficiency was more common in those who had anxiety and depression.18 Another looked at vitamin D deficiency in obese subjects and found a relationship between low levels of vitamin D and depression.19

6.Poor sleep — The mechanism linking vitamin D and poor sleep quality has not been identified. But research has found people with low levels of vitamin D have poor quality sleep and a higher risk of sleep disorders.20

7.Sweaty head — Excessive sweating, especially on your head, or a change in your pattern of sweating, can indicate a vitamin D deficiency.21

8.Hair loss — Vitamin D is crucial to the proliferation of keratinocytes and plays an important role in your hair cycle. The vitamin D receptor appears to play a role in the anagen phase of hair growth, leading researchers to conclude, “Treatments that upregulate the vitamin D receptor may be successful in treating hair disorders and are a potential area of further study.”22

9.Slow-healing wounds — Chronic wounds are a major public health challenge.23 In the U.S. 2% of the population is affected by chronic wounds and it is estimated to account for 5.5% of the cost of health care in the U.K. NHS. Vitamin D promotes wound healing and the creation of cathelicidin, a peptide that fights wound infections.24

10.Dizziness — Evidence from animal models suggests that vitamin D is critical in the development of the inner ear,25 which affects balance and coordination. Analysis of people with vestibular neuritis, characterized by vertigo, showed lower serum vitamin D levels than in people without vestibular neuritis.26

11.Heart problems — Clinical studies have shown that vitamin D3 improves circulation and can help improve high blood pressure.27 In one study28 researchers discovered that vitamin D3 also has a significant effect on the endothelial cells that line your cardiovascular system. They found that it helped balance concentrations of nitric oxide and peroxynitrite, which improved endothelial function.

12.Excess weight — How vitamin D affects obesity has not been identified. However, data do show there is a high probability of deficiency in people who are obese.29

13.Recurring infections — There have been multiple epidemiological studies that show vitamin D deficiency can increase the risk of infection and raise the severity, particularly in respiratory tract infections.30 Multiple studies have demonstrated that vitamin D deficiency increases the potential risk for severe disease and mortality, especially in those who are critically ill.31

14.Reduced cognitive function — Data show that vitamin D deficiency increases your risk of dementia twofold32 and raises your risk of impaired cognitive function.33

80% of People With COVID-19 Are Deficient in Vitamin D

Vitamin D plays an important role in the development and severity of many diseases. This is why, from the very beginning of the COVID-19 pandemic, I suspected that optimizing vitamin D levels would significantly lower the incidence of infection and death in the general population.

Since then, mounting evidence has revealed that higher levels of vitamin D may reduce the rate of positive tests, hospitalizations and mortality related to this infection. One study,34 released in late 2020, assessed the serum 25OHD levels of patients hospitalized with COVID-19 to evaluate the influence it might have on the severity of the disease. The researchers found 82.2% of those with COVID-19 were vitamin D deficient (levels lower than 20 ng/mL).

Interestingly, they also found those who were deficient had a greater prevalence of cardiovascular disease, high blood pressure, high iron levels and longer hospital stays. A second study35 found similar results for people who only tested positive for COVID-19.

In another study published in August 2021 in the American Journal of Physiology, Endocrinology and Metabolism, data showed that the vitamin’s metabolites can inhibit replication and expansion of SARS-CoV-2, the virus that causes COVID-19.36,37

It’s important to remember the data showing people who are deficient in vitamin D have a higher risk of severe disease were available long before the COVID-19 pandemic. Yet, information that may suggest the other side of the same coin — namely supplementing with vitamin D — may have a positive effect on disease severity, can come under attack.

So, it isn’t a big leap to understand that if simple and inexpensive solutions, such as supplementation with vitamin D, were to emerge, that, billions of dollars the pharmaceutical companies stand to make by vaccinating the world would be lost.

Unlike the painful reports of vaccine adverse events received by the U.S. Vaccine Adverse Event Reporting System (VAERS),38 supplementing with vitamin D, magnesium and vitamin K2 have been studied for years and found to be “well tolerated.”39,40

Added to which, the studies on vitamin D have demonstrated insufficiency and deficiency are associated with a number of health conditions.

Magnesium and Vitamin K2 Optimize Your Vitamin D3 Supplement

In the past, I’ve written about the importance of taking vitamin K2 MK-7 and magnesium with your vitamin D3 supplement. Both play an important role in your overall health and in the bioavailability and application of vitamin D in your body. If you’re not using magnesium and vitamin K2, you could need nearly 2.5 times more vitamin D, which GrassrootsHealth discovered in its D*action project.41

Over 10,000 individuals provided information about supplement use and overall health status to GrassrootsHealth since they began conducting large-scale population-based nutrient research in 2007.42

That information has led to the recommendation that vitamin D blood levels between 40 ng/ml and 60 ng/ml (100 nmol/L to 150 nmol/L) are safe, effective and lower overall disease incidence and health care costs. As reported by GrassrootsHealth from their data:43

“… 244% more supplemental vitamin D was needed for 50% of the population to achieve 40 ng/ml (100 nmol/L) for those not taking supplemental magnesium or vitamin K2 compared to those who usually took both supplemental magnesium and vitamin K2.”

In practical terms, this means when you take vitamin K2 and magnesium with vitamin D, you need far less vitamin D to achieve a healthy level.

Sources and References

September 29, 2021 Posted by | Science and Pseudo-Science, Timeless or most popular | | Leave a comment

How the Spike Protein Hurts the Heart

By Dr. Joseph Mercola | September 28, 2021

This video from the Front Line doctors White Coat Summit was published in mid-August. In it, pathologist Dr. Ryan Cole succinctly outlines many of the health challenges associated with the experimental genetic therapy injection program. He asks, after thousands of people have died from the injection, where are the autopsies to investigate this investigational program?

In July 2021, the U.S. military published a study in JAMA Cardiology 1 in which they asked the question if myocarditis was a possible adverse event following a jab with mRNA COVID-19 injection. They identified 23 men who were diagnosed with myocarditis within 4 days of getting the shot. They determined that there was a diagnosis of myocarditis after “vaccination in the absence of other identified causes.”2

And yet, despite finding myocarditis in previously healthy individuals following the shot, the writers only recommended vigilance. The heart problems in 23 military men who had signed up to protect the citizens of the U.S., “should not diminish overall confidence in vaccinations during the current pandemic.”3

As of September 3, 2021, the vaccine adverse event reporting system (VAERS)4 had received 675,591 reports of adverse events following vaccination. Of these, there were 14,506 deaths, 6,422 heart attacks and 5,371 cases of pericarditis or myocarditis.

It is important to note that the VAERS has tracked adverse events since 1990. In 2019, there were 605 reports of deaths from all vaccines given. In 2021, there were 14,594 deaths reported in nine months.

Although these numbers are significant, a 2010 Harvard study commissioned by the Department of Health and Human Services revealed data demonstrating the VAERS likely only represents approximately 1% of those who are injured.5

In light of these statistics and knowing the new shot program was experimental, December 18, 2020, the Children’s Health Defense chairman and chief legal counsel, Robert F. Kennedy Jr, requested the Biden Administration consider establishing a “comprehensive, high integrity system to monitor adverse outcomes following vaccination.”6

In early 2020, many clinicians, scientists and other health experts warned that millions of people may experience potentially permanent or long-term injury or death after the shot. Interestingly, it is the call for greater surveillance of vaccine injury that has, in part, generated censorship from social media platforms through AI surveillance of your posts.

Spike Protein Damages Endothelial Cells and Hurts Heart

Dr. J. Patrick Whelan is a pediatric rheumatologist who warned the FDA of the microvascular injury the vaccine may cause to the kidneys, brain, liver and heart before it was released to the public. Whelan specializes in treating children with multisystem inflammatory syndrome (MIS-C), which is associated with coronavirus infections.7

He did not dispute the potential benefit the vaccine might have to arrest the spread of the virus, but instead cautioned that recipients may experience permanent damage to their microvasculature. At the time, his concern was based on data scientists and doctors were reporting after an infection with COVID-19 affected multiple organs beyond the lungs.

In March 2021, a research study was published in the American Heart Association’s journal Circulation.8 However, it is important to note that the study was preprinted online in December 2020,9 before the first vaccine was administered in the U.S.10

This is important, since the study demonstrated that the spike protein associated with SARS-CoV-2 damages endothelial function.11 In other words, before the emergency use authorization jab that injected instructions to create the spike protein was first administered, the CDC, FDA and NIAID were well aware the spike protein was likely causing damage to the endothelial cells lining the circulatory system.

This information was not discussed in the media and not considered by the FDA, and it continues to be buried as government agencies push for 100% vaccination in the U.S. In the study, the researchers created a pseudo-virus12 that contained the spike protein but did not contain the virus. Using an animal model, they showed that the virus was not necessary to create damage and inflammation.13

When the S protein attached to the ACE2 receptor it disrupted signaling to the mitochondria and caused damage and fragmentation. The alterations in mitochondrial function were confirmed as part of the inhibition of ACE2 signaling in the lab.

The results also revealed that the virus could induce endothelial cell inflammation and endotheliitis. The protein reportedly decreased ACE2 levels and impaired nitric oxide bioavailability.14 Co-senior scientist of the study, Uri Manor, explained in a press release from Salk Institute:15

“If you remove the replicating capabilities of the virus, it still has a major damaging effect on the vascular cells, simply by virtue of its ability to bind to this ACE2 receptor, the S protein receptor, now famous thanks to COVID. Further studies with mutant spike proteins will also provide new insight towards the infectivity and severity of mutant SARS CoV-2 viruses.”

Further Study Demonstrates the Effect of the Spike Protein

Then, a second paper16 was published online March 8, 2021, investigated the potential that the spike protein is an inflammagen, or an irritant that can trigger inflammation at the cellular level. The researchers sought to determine if the spike protein was the underlying cause of the hypercoagulation found with a COVID-19 infection.

Mass spectrometry showed the spike protein damaged fibrinogen, prothrombin and complement 3, all compounds used in coagulation. They suggested that the presence of the protein was contributing to hypercoagulation and may result in large microclots that have been observed in plasma samples from patients infected with COVID-19.

Again, science demonstrated that it wasn’t the virus causing endothelial damage that led to organ damage, such as was found in the heart, liver and kidney of COVID-19 patients. Rather, it was the spike protein that was also being injected in a genetic therapy shot program.

A third study published April 27, 2021, again demonstrated in an animal model that exposure to the spike protein alone was enough to induce severe lung damage.17 And yet, there was no move by governmental agencies to slow the distribution of this genetic experiment.

Researchers have continued to study how the spike protein affects the endothelial cells, and ultimately damages the heart muscle. A study published June 2021 in Frontiers in Cardiovascular Medicine18 demonstrated that the spike protein down regulates the expression of junctional proteins found in the arteries. They concluded:

“… these experiments reveal that Spike-induced degradation of endothelial junctional proteins affects endothelial barrier function and is the likely cause of vascular damage observed in COVID-19 affected individuals.”

Even as researchers identify the pathway the spike protein takes to damage the endothelial cells, it is patently ignored by the mainstream media, governmental agencies and many health experts who continue to push the public into vaccinating with a genetic therapy injection that does not effectively keep you from getting the disease or stop you from spreading the disease.

Infection Starts and May Stay in the Lungs

Interestingly, another study19 published in March 2021 questioned if the prevalence of inflammatory heart disease after COVID-19 infection in professional athletes would affect their ability to return to play.

The researchers evaluated 789 professional athletes who had COVID-19 and found no adverse cardiac events in those who underwent cardiac screening. In this group of healthy individuals, it appeared very rare for there to be systemic involvement of the spike protein.

However, in the VAERS reports September 3, 2021, there were a total of 11,793 individuals who suffered heart attack, myocarditis or pericarditis in the nine months that the vaccine had been administered.20 The effect of COVID-19 on the heart is well documented.21

In my interview with Dr. Vladimir Zelenko22 in February 2021, we discussed the treatment of COVID-19 with hydroxychloroquine. At that point, Zelenko had treated 3,000 patients with symptoms of COVID-19 and only three of his high-risk patients had subsequently succumbed to the disease.

While the focus of the interview was on treatment protocols and the use of the antimalarial drug hydroxychloroquine, Zelenko shared an interesting statistic about his protocol. In the early months of COVID-19, Zelenko decided to treat his high-risk patients as early as possible, without waiting for severe symptoms. This turned out to be one key to his significant success.

His understanding of the mechanism behind hydroxychloroquine and zinc led to using the combination alongside azithromycin, to prevent bacterial pneumonia and other bacterial infections common with COVID.

What is interesting are the statistics for Zelenko’s patients with long haul symptoms. Data from the University of Washington in 2021 found 32.7% of outpatients with COVID-19 go on to experience persistent symptoms.23,24 However, Zelenko had treated 3,000 patients and none who received treatment within the first five days went on to develop long-haul symptoms. His data was from the same period as that of the University of Washington.

While he has had patients with persistent symptoms from COVID-19, they sought medical care after the first five days of symptoms, which meant the inflammatory process had advanced. From his experience, and the experience of the patients he treated, early intervention with the protocol nearly eliminated the risk of persistent symptoms.

Long Haul Symptoms May Be Related to Spike Damage

The symptoms that may last for weeks or months after a COVID-19 infection are referred to as long-haul symptoms. For some, this may be the result of vascular damage caused by the spike protein. The CDC25 reports that a combination of the following symptoms without an active COVID infection can appear weeks after the infection and last for months.

  • Brain fog described as difficulty thinking or concentrating
  • Chest pain
  • Cough and difficulty breathing
  • Depression or anxiety
  • Dizziness when first standing
  • Fast beating heart or pounding heart
  • Fatigue
  • Fever
  • Headache
  • Joint or muscle pain
  • Loss of smell or taste
  • Shortness of breath

Scientists now know that the predominant pathophysiology of COVID-19 includes endothelial damage and microvascular injury, stimulation of hyperinflammation and hypercoagulability.26 A review in Physiological Reports27 examined how the capillary damage and inflammation from endotheliitis triggered by COVID-19 could contribute to the persistent symptoms by interfering with tissue oxygenation.

The combined effects of capillary damage in multiple key organs may accelerate hypoxia-related inflammation and lead to long-haul symptoms. Unlike Zelenko’s patients who did not have long-haul symptoms, participants in an online survey published in EClinical Medicine did not fare so well.28

The study revealed data from 3,762 participants with suspected or confirmed COVID-19 in 56 countries. For the majority, it took greater than 35 weeks to recover from all their symptoms. The data showed that people experienced an average of 55.9 symptoms across 9.1 organ systems. The most frequent symptoms six months after infection were cognitive dysfunction, fatigue and post-exertional malaise.

List of Vaccine Side Effects Is Growing

As the list of people reporting adverse events after the vaccine continues to grow, social media platforms are working just as hard to suppress any information about the list of side effects people are experiencing.

In order to tell their stories, people are posting videos, still photos and evidence of their vaccine injury at No More Silence29 and 1000 COVID Stories.30 One example is Sarah Green, a 16-year-old student who is experiencing debilitating symptoms. This is her story as told by her mother:31

“Within a few weeks, she developed a bad stutter and started experiencing uncontrollable head movements. She looked like someone who has Parkinson’s. She had never stuttered or had these tics before.

She was admitted to the hospital where she spent two nights and underwent numerous tests, before being discharged and told that it was a ‘nervous tic,’ and to see a mental health provider.

‘We asked several times if it could be the vaccine and we were ignored, until one doctor told us that he had no idea what it was, but it was ‘absolutely not the vaccine’ and we couldn’t blame everything on that.’

Her parents argued for a referral to see a neurologist, who diagnosed Sarah with Functional Movement Disorder, and told that it was “related to the vaccine, but not vaccine related.” They also said that it was an ‘extremely rare’ side effect, despite having seen several cases of it in their own practice over the past year.

Sarah had ended the last school year with a 4.7 GPA and was enrolled in an Early College program, on track to graduate with an Associates Degree. Given her current physical condition and limitations, she had no choice but to drop her college classes for this upcoming semester.

She has started her regular classes but has found it impossible to look down or write without triggering violent tremors and spasms. Her teacher will be typing her notes for her.

‘I am heartbroken because she has worked so hard and everything has changed for her — and I’m so damn mad! Our whole lives have changed, and for what what? A vaccine that doesn’t even work! My hope is that you, the reader, will be able to make an informed decision when deciding whether you get the vaccine or not. We were not afforded that opportunity.’”

It is crucial to report a vaccine injury or side effect to VAERS, as the data are essential in helping individuals, doctors and researchers make informed decisions. You can make your own report online or using a PDF by going to the Vaccine Adverse Event Reporting System.32 You’ll find more information about adverse events and how vaccines affect your health at the National Vaccine Information Center.33

Sources and References

September 29, 2021 Posted by | Timeless or most popular, Video | , | Leave a comment

Community Masking: Where did ‘The Science’ Come From?

By Noah Carl • The Daily Sceptic • September 28, 2021

Before 2020, evidence for the efficacy of community masking – that is, asking ordinary members of the public to wear cloth or surgical masks when going about their business – was shaky at best.

This evidence was reviewed in detail by Jeffrey Anderson, a former director of the Bureau of Justice Statistics. He notes that:

of the 14 RCTs that have tested the effectiveness of masks in preventing the transmission of respiratory viruses, three suggest, but do not provide any statistically significant evidence in intention-to-treat analysis, that masks might be useful. The other eleven suggest that masks are either useless—whether compared with no masks or because they appear not to add to good hand hygiene alone—or actually counterproductive.

In another piece that’s well worth reading, Professor Steve Templeton provides a list of quotations from what he calls “the BP era” (Before Things Got Political). Each quotation, taken from one or other expert, testifies to the lack of evidence that community masking works against respiratory pathogens.

For example, in a systematic review published early last year, Jingyi Xiao and colleagues “did not find evidence that surgical-type face masks are effective in reducing laboratory-confirmed influenza transmission, either when worn by infected persons… or by persons in the general  community to reduce their susceptibility”.

This is presumably why, at the start of the COVID-19 pandemic, health authorities in both the U.K. and the U.S. advised against community masking.

For example, on 4th March 2020, Chris Whitty told Sky News that “wearing a mask if you don’t have an infection reduces the risk almost not at all”. And as late as 3rd April, Jonathan Van Tam said “there is no evidence that general wearing of face masks… affects the spread of the disease”.

Likewise, in a tweet sent on 27th February, the CDC said that it “does not currently recommend the use of facemasks”. And two days later, the U.S. Surgeon General urged people to “STOP BUYING MASKS” because they are “NOT effective” at preventing the general public from catching coronavirus.

In a video interview from May of 2019, Anthony Fauci actually laughed at the notion of wearing a face mask. The interviewer asks him, “The best way for me to prevent getting an infectious disease… is what? Wearing a mask?” To which Fauci replies, “No, no no… you avoid all the paranoid aspects.”

Yet by the summer of 2020, the health authorities in both countries had done an about-face, and were now recommending face masks to the public. These recommendations subsequently became mandates.

‘The Science,’ in other words, had changed. But what prompted this change? The charitable answer is that new evidence emerged suggesting that community masking does work against SARS-CoV-2. However, this new evidence looks just as shaky – if not shakier – than the pre-Covid evidence.

I suspect that something else happened. Back in the spring of 2020, all Western countries were on the same upward trajectory, with cases doubling every few days. Meanwhile, Japan, Korea, Hong Kong and Singapore had all manged to ‘flatten the curve’, despite eschewing draconian lockdowns.

Commentators were searching around for an explanation, and ‘masks’ seemed like a good one. After all, Western health authorities had advised against masks. Yet many East Asians had been wearing them for years.

If you were on social media at that time, you probably remember seeing a version of this chart, which went viral numerous times:
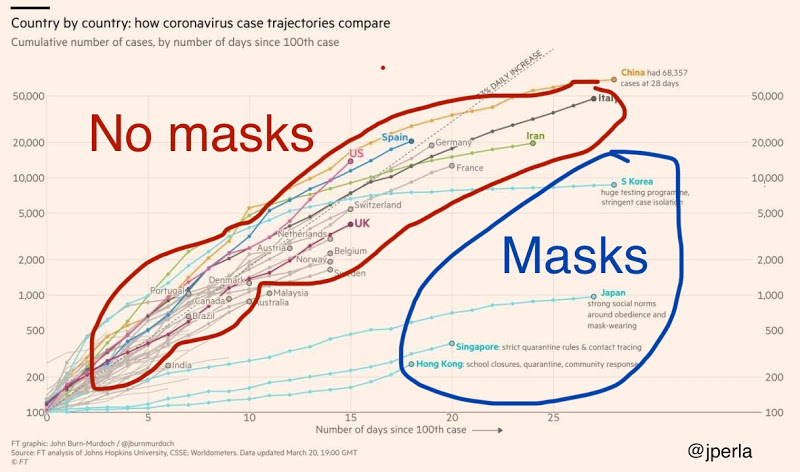
Putting ‘correlation doesn’t equal causation’ aside, it appears to suggest that masks are the crucial factor for bringing COVID under control. Of course, the subsequent imposition of mask mandates in Western countries didn’t forestall large winter outbreaks, which rather undermines the mask theory.

Nonetheless, it seemed plausible enough at the time. And articles began appearing in major news outlets that questioned the West’s reluctance to wear face masks. On social media, commentators asked why we shouldn’t follow the East Asian countries, given their far greater success in handling the pandemic.

I suspect this pressure had more to do with the health authorities’ about-face than any fundamental change in the quality of evidence. It was another case of ‘politician’s logic’. ‘Something must be done; mask-wearing is something; therefore we must do it.’

In a matter of weeks, ‘The science’ went from ‘don’t do X’ to ‘do X’. And yet it took another whole year for the first RCT of community masking to be published. The theory I’ve outlined is speculative, of course. But I don’t see what else can account for such a sudden shift in public health advice.

September 28, 2021 Posted by | Science and Pseudo-Science, Timeless or most popular | | Leave a comment

Nothing They’ve Tried Has Worked: The Story In Four Charts

By Tom Woods | Principia Scientific | September 28, 2021

I send a lot of charts, as you know. But these are especially interesting. What story are the charts below — which cover four different regions of the United States — telling us about the Covid virus?

The dark line represents 2020. The lighter line represents 2021.

I get that the curves are not absolutely identical. But they’re not altogether different, either. The same trajectories are evident in both years, in each chart.

What do these charts mean?

Do they mean that the virus is regional and seasonal, and that despite our feeble interventions it does what it will?

I won’t attempt to draw any sweeping conclusions for you. But look at the charts and make up your own mind.

Meanwhile, much of the public continues to believe the standard story.

Someone inside the Tom Woods Show Elite, my private group for normal people, put it this way: “Most people believe that masks work, that kids are dying in droves due to Covid, and that the vaccines stop the spread. If you go up to people in public at random and ask them basic questions about Covid, they will not know these basic things.”

It reminds me of when 70 percent of Americans thought Saddam Hussein had been responsible for 9/11.

September 28, 2021 Posted by | Science and Pseudo-Science, Timeless or most popular | , | Leave a comment

CASHLESS SOCIETY: PROGRAMMABLE MONEY AND FINANCIAL CONTROL

Computing Forever | September 27, 2021

Source articles:

https://www.independent.ie/news/cars-funerals-and-home-improvements-eu-to-crack-down-on-large-cash-payments-40713482.html

https://archive.is/740Rb#selection-881.0-918.1

https://www.rte.ie/news/coronavirus/2021/0910/1245839-who-vaccine-pandemic/

Support my work here: https://computingforever.com/donate/
Buy How is This a Thing Mugs here: https://teespring.com/stores/computing-forever-store

This video contains the following stock videos and images sourced from pixabay.com:

https://pixabay.com/videos/money-euro-currency-inflation-64212/
https://pixabay.com/videos/money-budget-count-cash-counting-59139/
https://pixabay.com/photos/credit-card-card-credit-2308179/
https://pixabay.com/illustrations/euro-currency-money-finance-coins-6547061/
https://pixabay.com/videos/cash-money-currency-finance-wealth-59134/
https://pixabay.com/videos/map-digital-global-business-45956/
https://pixabay.com/videos/earth-globe-country-africa-asia-1393/
https://pixabay.com/videos/supermarket-cart-market-mall-buy-1735/
https://pixabay.com/videos/network-connect-internet-abstract-45961/
https://pixabay.com/videos/fiber-light-wheat-design-shape-55776/
https://pixabay.com/videos/particles-plexus-network-glowing-27669/
https://pixabay.com/illustrations/australia-oceania-national-flag-1157502/
https://pixabay.com/videos/download/video-2118_source.mp4?attachment
https://pixabay.com/photos/dollars-currency-money-us-dollars-499481/

http://www.computingforever.com

September 28, 2021 Posted by | Civil Liberties, Economics, Timeless or most popular, Video | | Leave a comment

Gagged Australian Nurses Form Whistleblower Group to Expose What’s Really Happening with COVID-19 Vaccine Injuries

By Brian Shilhavy | Health Impact News | September 27, 2021

Reignite Democracy Australia, which was started by journalist Monica Smit, an outspoken critic on authoritarian lockdowns in Australia who was just released from jail on bond last week, has started a group called “Nurses Speak Out” where gagged nurses are speaking out about the truth of what is currently going on inside of hospitals with people suffering from vaccine injuries.

They are posting these stories on their Telegram channel as well.

This is an Anonymous whistleblowing channel for Nurses & Healthcare workers in Australia. We will share verified experiences from frontline workers who see firsthand the damage caused by COVID-19 vaccinations.

These submissions have been vetted by a collective of health professionals. Some details may be omitted, your identity will be protected. AHPRA has gagged, coerced and threatened anyone who comes forward – let’s save some lives.

This channel is dedicated to all frontline workers around the world. This is Australia. This is for you.

Here are some of their stories that have just been published.

Hi,

I’m a community RN on the —— , Qld.

I am seeing and caring for adversely affected clients who have had the vaccines and are quite literally dying. Our palliative care is increasing at an exponential rate, people are getting diagnosed with terminal conditions and dying quickly. We (community nurses) are seeing 2-3 palliative clients per day each, this is a massive increase from 1-2 each per week. Other palliative clients who haven’t been vaxxed, then their families talk them into the vax, die more quickly than expected.

Have noted that those who are vaxxed that their clinically ‘weak’ areas are being exacerbated. Appears to be at 3, 5 then 12 week patterned intervals. Not one of them associate with the C19vax.

Had one man in his 70’s in very stable remission with leukemia for years. Within 3 weeks of having ‘the vaccine’ his white cell count dropped so he had neutropenia. He suddenly developed in 24 hours bilateral cellulitis to both legs up to thighs. 9 weeks later, he is dead.

Those with rheumatoid arthritis who have been jabbed experiencing related consistency of flare ups. Getting all sorts of skin infections for no obvious reasoning. They’re having constant medication reviews and increasing analgesia.

3 x clients with healing venous ulcers, all 3 had the jab, 3 weeks later all developed septicemia all with hard to treat bacteria.

Those with cardiac conditions who were clinically stable on medication for years, suddenly no longer stable. Arrhythmias, unstable blood pressure, syncope, falls, increased hospitalisations.

Cancers: seeing massive increase in skin cancers. They’re growing very quickly and aggressively.

Cognition: clients who have been vaxxed and predisposed to some memory issues, increasing episodic bouts of confusion with accompanying amnesia and increasing STML.

Of my nursing colleagues who have been vaxxed, noticing increasing sick leave being taken.

Sincerely,
Veronica
Community RN

Triage Admin, Emergency Department.

Hi,

I work in Emergency Department as an admin clerk at triage and I can tell you the reason I will not be having this vaccine is that every third or fourth patient is coming in with an adverse reaction.

Some complaining that their heart is beating so hard and is squeezing out of their chest, I’ve seen vision changes, numbness , skin problems , cellulitis young men and women diagnosed with pericarditis myocarditis, clots , tumors even my colleagues have had Bell’s palsy there is so much more.

What amazes me with all this is that no one can see it! Young patients being told it’s just anxiety 😥, nurses at triage rolling their eyes saying things like “can’t they just stay home and take a panadol” !

Then to top it all off our double jabbed nurses at triage test positive to Covid and are admitted and are sick but they are saying “at least I’m vaccinated I could have been a lot worse”, there are 5 unvaccinated clerks at the front desk at triage and we have worked through this pandemic but now we are a danger to the other other staff

UNBELIEVABLE! So we now have received the letter saying no jab no job we’ve got till the 30th 😟 Also would like to add the influx of nursing home patients that are coming in is ridiculous, falls vertigo generally declining quickly after jab, I’m not a medical person but I can see what’s going on it’s very sad 😞

Hi,

I am a Physiotherapist with 40 years of Private Practice experience – Some of the clients I see I have been seeing them and their families for different things for decades.

On Thursday I had four of the jabbed ones in. They all had the same set of symptoms.

Their original injury that I treated them for occasionally — maybe once every few years over the last few decades has returned with a vengeance and is excruciatingly painful. Additionally all four of them had pain all over in ankles, wrists, knees, hips, backs all over… and they all had a severe headache.

They are not relating this to the jab.

I have been seeing this new presentation of pain over the last couple of weeks.

However, on Thursday with them all coming in on the same day with the same symptoms I now KNOW it is a pattern of pain for the jabbed.

This evening I went out with a Nurse friend who is jabbed and she has the same thing happening to her. Neck, arm and wrist pain, swollen feet and foot pain, and she kept saying she felt old, and her body was breaking down… She is 15 years younger than me and could barely walk home from dinner.

These people are my friends and long term clients — it is difficult to watch them suffer.

(Response to #0003)
25/09/2021
Private Practice Physiotherapists

Hi,

We’re also a group of private practice physios of similar vintage and have seen this pattern of presentation in the jabbed ones.

Headaches feature prominently. In addition, we’ve noticed discoloured feet (purple-red), swollen joints (one young patient with Crohn’s disease resorted to a walking stick), swollen and tight calves, recurrence of old injuries as well as new joint aches snd pains.

When dry needling, our acupuncture needles are now “swimming” in tissue because there’s just so much generalised inflammation of the muscles. Patients are reluctant to report these symptoms because they’re doctors have told them “the shots are safe”!

Student Nurse, Rural.

Hi,

I’m a student nurse working in a rural hospital.

I’ve had several people walk into the hospital with flaring pains all over their body, on my last shift there were 9 patients who whispered to me that they were sure that their condition was caused by the COVID vaccine they got but they were afraid to tell the registered nurse for fear of being ostracised. They got the jab because everyone else was getting it rather then making the decision for medical treatment.

I have seen many nurses and doctors laughing about these people in the break room. Calling these patients Anti-vaxers and wishing they could kick them out for the real patients in need. I told my student supervisor and the nurses stopped talking about it when I was on break but I have the feeling they still had those conversations behind my back.

RN. Aged Care, NSW.

Hi,

I am (was) a Registered Nurse in Aged Care in NSW.
I was terminated from my job there over a week ago now for declining the jab.

The facility had a covid clinic where the masses received Pfizer.

On the day as they had left over stock the staff were then offered jabs which many of them didn’t feel comfortable but got because the management where there on the day saying things like “come on just get it, don’t be ridiculous, if you can’t trust the science what can you trust” one staff member declined twice, the third time she was pushed into getting it (all on the same day) I seen this as pure bullying and coercion, she submitted and got the jab.

The next day a resident died (nobody batted an eyelid) within three days post jab another two residents died.

Over the course of the next three weeks we lost in total 6 residents all who had significantly declined overall and not to mention a lot of other residents declining overall and becoming unwell.

The second jab clinic, within the first week, we had five people end up in hospital who then died, shortness of breath, heart issues, others the residence getting rashes not being able to lift their arm up, acting as delirious state, within the next week after that another 5 residents died.

In total within the 3 months roll out of the jab, we had 14 deaths of vaccinated residents.

In a nursing home with 90 residents most of the staff are commenting on how unheard of this amount of death was but when questioned in relation to the jab many were in denial stating it couldn’t be from that.

Over the course of three months watching the staff who had been injected so many staff off on sick leave a few staff members ended up in the hospital one for heart reasons the other one had blistering rashes all over her body she ended up being admitted twice, mass reports of headaches lasting days to weeks, dizziness, just generally reporting to not feeling right since having it. The fear in the eyes of the staff is something I will never forget. Other staff feeling completely deflated as they could lose there jobs and had to submit to the jab, In which some after were crying to me at how much they just felt defeated. I have many things to say in relation to this, I could write a novel.

I know just within the week and a half of not being there they are struggling to fill shifts, which sadly impacts on everyone, residents and staff the only people it doesn’t effect is the management.

I love being a nurse but I just can’t do it in this current situation it no longer aligns with what I believe health to be. It is a sad and devastating time.

RN, Emergency Department. NSW.

I am a Registered Nurse from NSW,

I have a young colleague, also a nurse who did not want the vaccine.

Due to the mandate she got the shots. After her first shot she had searing pain down her arm. Unrelenting pain. After her second shot, she was bedridden for an entire week. She could not sit up straight. She was so sick, unable to move and constant chest pain.

After the week of being bedridden she returned to work with chest pain. She finally has been admitted to hospital with myocarditis.
She is early 20’s. Before the vaccines she was healthy with nil health issues. Now she has cardiac issues and may need medication for the rest of her life.

Each day we are seeing the emergency department full of patients with stroke, Pulmonary embolisms, cardiac arrhythmias, Myocarditis, endocarditis. The increase of strokes is exponentially growing. Patient after patient with PE’s, cardiac issues. Most in previously healthy patients. Doctors are denying connections to the vaccines.

RN, 40years. Palliative Care.
AHPRA Verified ✅

Hi,

I am an RN of 40 years, presently my work is in Palliative care where I have worked for 8.5 years permanently in ——-.

I am seeing patients developing increased effects from Palliative radiation, which is commonly prescribed for reducing various conditions arising from cancers. Our patients are deteriorating more quickly with increasing weaknesses, breathlessness (?PEs) facial droops (Palsy or stroke), neuropathys in hands or feet.

The cancers some only recently diagnosed, seem to have metastisised very rapidly. This needs to be looked into carefully. We as nurses are commenting those going for radiation are very much at risk; a death sentence which hastens their deterioration towards death. As Palliative patients, their downturns are passed as expected, while we see them as alarming.

I have many colleagues took the jab out of sheer fear of losing their job and incomes. Also one other colleague after she recieved her 1st pfizer jab was off work with encephalitis and remains very unwell having diffuculty with headaches and dizzy spells.

I am ordered to leave from September 30th, a job I am passionate about and feel have been valued. While now 61 years old I hoped to continue my work for 5 more years and feeling very sad to be forced to leave.

I think the radiation perhaps is accentuating the vaccinations, namely the graphene components.

Sincerely.

EN. Brisbane, QLD.

Hi, Enrolled Nurse from Brisbane…

I work in Private health, so don’t often get to see initial reason for presentation to emergency, as they are usually transferred from public to us later.

I nursed a man in his 60’s recently that got vaxed…he had a knee replacement 3 months prior (fully healed).

Came in to hospital again due to severe bleeding and needing surgery… post-surgery his knee haemorrhaged quite badly… then got a vacc dressing…ended up nursing him again in a Rehab ward a week later… told me it happened after vaccination but surgeon didn’t report it or link it with vaccine.

Another older lady presented as very disordered after vaccination.. couldn’t walk properly, ended up 2 assist with a FASF… on Lyrica 150 BD for nerve pain… frequently complained of headaches and chronic ear ache.. ended up going home after a long rehab stint..

I won’t be getting the jab so will probably be unemployed in the next month or so… One of our Doctors is very over the draconian crap..his words.. he is fully vaxed and furious we are still wearing masks.

Remedial Massage Therapist, QLD.

Part 1 of 2.

Hello,

I am a Remedial Massage Therapist operating out of Wellness Clinic in an exclusive seaside town in —— Qld, Australia.

Over the past 12months the majority of my regular clients have received both shots of either AZ or Pzizer and I have observed and felt the changes in their bodies. I will also add that not only have the changes happened in their bodies but also their personalities.

Over the past 2 months I have also listened to them telling me of their sudden medical issues that are happening to them. This has been so disturbing for me that I am closing my business and am taking the time to heal myself both physically and mentally.

Their bodies over the past 12months have changed. They have no movement, elasticity anymore. It is like they are turning to lead. I have 3 clients, all retirees and golfers who now have tears in their supraspinatus. This is on their left hand side from swinging the golf club.

(1) One client, male retiree who has been rushed to hospital 4 times last week unable to urine or make bowel release. The Doctors have told him that he has kidney stones. Hmmm… He also had a large burning and itchy rash all over his back. He said it was that painful he had his wife put metho on his back to ease the pain as nothing else was working.

(2) One retired lady advised me that she had a cyst forming behind her knee and when she would have a shower it would burst and the blood that came out was uncontrollable. This happened twice within a couple of weeks. She went to the Doctors he said it was a bakers cyst. She returned saw another Doctor who said it was a BCC. The third time she came to me her leg is now swollen all the way and she is in a lot of pain.

(3) Another lady, a Doctor herself advised that she had an electrical like pain run across her back. She couldn’t quite explain it. Never had anything like it before and now has a sore neck and headaches. I felt her neck and there was a pulsing feeling at the rear. She couldn’t feel it. I went back to that site 2 more times and I could feel it. She couldn’t.

Cont…

Part 2 of 2.

… (4) A retired lady told me she had burning and itching skin on her chest and that she was in a lot of pain. I asked her if I could see it. It covers a large area between her breasts and underneath her bra line. She said it is getting worse each day. It was very red and raw.

(5) Another regular client has markings all through her lower back on the left side. She was unaware. I took a pic and showed her. She said that she had been putting an electric heat pack in that location at night to warm her up. She went to the Doctors and the skin clinic and they didn’t know what it was. She came back to see me 5 weeks later and the markings are still there.
I have attached the pics (redacted) for you to view. and the list goes on..

I have regularly massaged these clients over the past 2-3 years and I find it extremely troubling. These haven’t happened straight after their shots but over the 3, 4 , 5 months following so they are not connecting it to their shots. I am unable to say anything to them as their once friendly personalities have also changed. They are more aggressive and talk at you, not to you and will defend these shots.

The man I mentioned above even said to me that he will be getting the booster shot if and when it comes out next year. When you hear from your clients all day, every client, not 1 or 2 then this is a concern for all people who have had this shot. They are not the same people, on any level anymore. Like I mentioned above this has traumatised me to the point that I am now unable to continue my passion for the foreseeable future and I am now focusing on healing me, physically, mentally and spiritually. Take care everyone and be safe.

Radiographer, Private Practice, Rural.

Hi,

I work as a Sonographer for a private rural practice. We mostly see outpatients but the occasional patient via ED.
I work three days a week and I would say I see at least one patient per shift with an injury directly related to the vaccine. Some examples:
89 yo F haemathrosis to left shoulder at injection site one week post vaccine.
No blood thinners. Healthy

72 yo F (mother in law)
Very healthy, fit. No medical problems.
Profoundly deaf in both ears over a period of days. Had vax 10 months ago. No cause found.

56 yr old M
Testicular ultrasound showed epididymis one week post vax.

Lots of unexplained abdominal pain, headaches, shoulder pain and inability to use arm at injection site.
Hope that’s helpful.
Regards. ——

RN, 39years.

Hi,

I am an RN with almost 40years experience.

We looked after one of the first AZ blood clot patients

Male, 45yo. 8 days post his 1st AZ shot he complained of dreadful stomach pains. Went to ED.

Scans showed a massive blood clot in his bowel.
It took 3-4 days before they could operate, as his Coags were all over the place.

The clot was finally removed along with almost 2 metres of necrotic bowel.

When out of ICU, he came to our ward. A beautiful man, who was black and blue all over with bruising. He was on an anti-coagulant drip, with a drug I’d never heard of (still can’t remember the name).

He was transferred to our Haematology ward, and unsure what happened to him.

Admitted a pt yesterday, who had been in ED for 10 hrs. Quite casually he told me that he couldn’t believe the numbers of young guys coming in with side effects from the vaccine. I asked him how he knew this, and he said he could hear the conversations.
I asked re the side effects and he said chest pains, breathing problems!

Nursed a female pt, fully vaxxed, with pancreatic issues, but she’s had increasing weakness in her legs?? All Neuro tests are NAD. She can no longer weight bear, and has been told it’s because she’d been in ICU and was deconditioned???
I’m not so sure….

Will no doubt lose my job end of October, as no jab for me!😥😥

RN. Emergency Department, Melbourne, VIC.

Hi,

I am an Emergency Department RN based in Melbourne’s east and have similar experiences to the other whistleblowers.

We have young, healthy men in their 20’s-30’s coming in every single day due to chest pain after the vaccine. Pathology is usually fairly normal (Trops and d-Dimer) and doctors write it off as either psychological or unrelated to the vaccine. Even when they admit it’s probably vaccine related, it is never reported. Ever.

I have looked after a young, healthy female who felt coerced in to getting it due to her job in healthcare, who suffered from severe headaches ever since, and nothing seemed to help. She was sent home basically left to hope that it resolves eventually. Doctors did not report it.

Another patient came in with multiple blood blisters, and petechiae on his arms. He was diagnosed with ITP which is a known adverse effect of the Pfizer vaccine. His platelets were literally completely wiped out. Doctors did not think it was linked to the vaccine he had 3 days earlier, and so it was not reported.

If science was being respected, people would be followed up properly, and the cause of the chest pain for example would be getting investigated, but it isnt.

None of these things were discovered during the purportedly thorough and complete clinical trials. None of the patients were made aware of the possibility of these effects, which means they could not give proper informed consent.

Now they want to force us to take it or lose our job? Who knows what other problems will be uncovered in the future?

No risk/reward analysis is being done in regards to age demographics. Many experts are saying young adults have greater risk from the vaccine than the virus. No formal studies have been done that I’m aware of, but I suspect that is true. And it is definitely true for children. The government now wants to vax all children despite their risk of harm from covid being almost zero, and the risk from the vax being comparatively high.

Medical treatment is supposed to have a favourable risk/benefit analysis, and it absolutely does not in this case.

The medical field is about to lose staff who are capable of thinking for themselves and standing up for themselves, and healthcare for patients will be much worse because of it.

RN. Brisbane Hospital, QLD.
AHPRA Verified ✅

Hi there,

I am a nurse at one of the major hospitals in Brisbane. Had my first Pfizer shot back in April – suffering pericarditis, numbness and tingling in both arms, ceased menstruation, elevated insulin levels.

Will not get second.

No Covid at our hospital. Have seen many adverse reactions from Covid vaccine. Mainly block clots, strokes, heart problems.

AIN. Aged Care, NSW.
AHPRA Verified ✅

I work as an AIN (Assistant in Nursing) in aged care in rural NSW.

One of my colleagues in her mid 30s went home sick the day after her second Pfizer shot. She went white and nauseaus and faint. This was in March and she has not been back to work since (its September now). After ages of going to Doctors etc she was diagnosed with myocarditis, she says she can hardly do anything. She was fine and healthy before, slim, physically active and on a good diet. Whenever the other staff talk about it, the narrative goes: oh she must have had something else before that, surely it’s not from the vaccine.

Two residents died within 2-3 weeks after first Astra-Zeneca shots, however were overall in bad condition before.

Residents are not allowed to leave the facility and nobody is allowed to see them except on compassionate grounds (basically if someone becomes really unwell). This causes some of the people to be really mentally unwell. There has not been one Covid Case in our town for the whole course of the pandemic since 2020.

We are told we have a “choice” to either get the flu and covid shot or we can’t work here. Another colleague had 40 years experience in emergency nursing and refused the flu shot, she was subjected to sitting at the door doing covid checks for about six months (even when there was no flu season) until she gave up and resigned. She had never had a flu shot for her entire career.

RN. Clinical Call Handler, COVID Vaccine Adverse Events, VIC.
AHPRA Verified ✅

Hi,

I am a registered nurse in Melbourne with almost 33 years experience.

I currently have a role as a clinical call handler for people that are experiencing side effects from covid vaccines.

The adverse events that have been reported to me are extremely concerning in both the types of reactions and the frequency of them.

Apart from the usual expected side effects of over, pain etc for 1 to 2 days, some of the reactions that have been reported to me multiple times include

*Delayed anaphylactic reactions involving respiratory distress, facial and tongue swelling, usually a rash, but not always , with onset occurring usually around 2 days after vaccine, but has been up to 4 days post vaccine.

* Chest heaviness, stabbing chest pains, palpitations and shortness of breath is reported to me several times a day every day usually in young people (male and female) post Pfizer 1st and 2nd dose.

* Heart palpitations are very commonly reported across all age groups( usually Pfizer)

* ongoing shortness of breath for 6 plus weeks post vaccination with no explanation

* unusual rashes that appear days to weeks after vaccination

* unexplained bruising that appear days to weeks after vaccination with both Pfizer and AZ ( commonly reported extensive bruising on legs)

* swollen, painful varicose veins

* persistent headaches for weeks after vaccination, sometimes severe but usually just annoyingly persistent

* heavy vaginal bleeding in post menopausal women ( mid to late 50’s) and menstrual disruption/ irregularities in younger women

* Blood noses post Pfizer is extremely common

* Burning pain in limbs, in several cases the pain is so severe that the person is unable to walk.

* numbness and tingling in arms and legs is very commonly reported up to 6 weeks post vaccination with both Pfizer and AZ

* leg / foot pain and swelling( symptoms strongly suggestive of DVT however I don’t get to follow up)

* severe vertigo and tinnitus ( Pfizer)

* numbness down one side of face (this is surprisingly common)

* uncontrollable muscle twitching/ spasms

* extreme lethargy that persists for months after vaccine.

* Exacerbation of old injuries such as previously broken or sprained joints flare up or old scars become red and inflamed again.

* older Australians that have had Astrazeneca vaccine and have been ok but then had flu vaccine and have been extremely unwell since. I do believe there is a correlation between the 2 given within weeks of each other that is causing significant health decline in older people.

* people that have had stable auto immune disease but then once vaccinated their symptoms are markedly exacerbated or others with no previous history of immune disorders, I suspect develop an immune disorder post vaccine

I am certain that these vaccines are causing immune, neurological and blood clotting disorders resulting in significant harm to an unacceptably large amount of people.

There is more specific cases that I am aware of but for anominity I will not disclose them here. I am aware of ICU admissions post Pfizer vaccination in 3 different people as well as deaths of elderly nursing home residents within 24 hours of vaccination.

I am both concerned and frustrated that the medical profession is either unaware that these side effects are happening, or in many cases, not prepared to admit that they are in fact a result of the covid vaccines, (often medically gaslighting and putting down to anxiety), leaving these poor affected people desperately seeking help and answers, that in most cases, they probably won’t get either. I have tried to raise this issue on more than one occasion, but it falls on deaf ears.

RN/Critical Care Nurse. Rural, NSW.

Hi,

Love your idea by the way! It’s too hard for us to speak out and keep our jobs 😔

I watched many of my fellow colleagues suffer side effects. I was one of them too! When you talk about it so many stories come out and quite a few of us have ongoing issues to this day.

Within my workplace in a rural Emergency department I find myself as a team leader at times. I have been overwhelmed with patients post vaccination suffering side effect. Some short term such as chest pain amongst 20 -40yr olds to abdominal pain. Then the more serious long term stokes, heart attacks, guillian barre and pulmonary embolism.
For those nurses around me that have not had their vaccination yet, they are terrified!! For us that have had a reaction…..never again!

Very little are reported and knowing how a proper clinical trial is conducted for my many years at university…this roll out is terribly wrong!

I understand COVID can make you quite sick (even if I have never seen it in my nursing career) but I believe this vaccination is no better! We need to go back to the drawing board and admit defeat instead of pushing forward.

The politics running this with no medical knowledge should be ashamed!

RN. Palliative Care Ward, Melbourne. VIC. AHPRA Verified ✅
.

I’m a RN working on a Palliative Care ward in a major Melbourne hospital.
We never had Covid patient as they stay on the acute wards, obviously we need to protect our non-Covid patients.

However we have had a number of patients coming to our ward and subsequently dying with sudden onset of unusual symptoms. Of course no connection has been made to the jab what so ever.

One male 70-something had his second AZ jab and a few days later suddenly collapsed with seizures. He was brought into hospital, ICU, had a number of CT’s, MRI’s and other investigations done, was intubated for a number of weeks. Everytime he was extubated, he was having seizures despite being on high doses of anticonvulsant (anti-seizer medication). The medical team decided he might have Autoimmune encephalitis (=autoimmune brain inflammation) eventhough the EEG and blouds did not confirm this conclusively.

(1). A man in that age group suddenly having an autoimmune disease? Eventually the decision was made to palliate him, which is when he was transferred to our ward. He somehow stabilised on our ward but was bedbound and definetly not like himself. Now here’s the twist. All along in his medical history the diagnoses was documented as “autoimmune encephalitis vs. vaccine injurie post AZ”. At one stage during the weekly meeting I actualy asked if he was going to be a Coroners case, since it’s unclear what his cause of death would be.

I was looked at realy strange, my concern was dismissed, I was told no it’s clear that he suffers from Autoimmune Encephalitis. After that the above comment was removed and his diagnoses remained Autoimmune encephalitis. To me this was a trigger to start looking at each patients history deeper.

(2). Female 65 years old and healthy was transferred to us after she’d suddenly collapsed at home for unknown reasons. ICU, intubated, again seizures from unkown reasons. They had done all the tests available under the sun(whole body MRI, CT, EEG, Autoimmune tests, etc). Medical team unable to find a cause of her severe deterioration. Decision was made to palliate. Transferred to us and then died after a couple of weeks. At least this one was a Coroners, as the cause of death was unclear.

A number of other patients were transferred to us, mostly with some sort of seizure that led to a collapse, or Stroke that led to more strokes and collapses. Sometimes one has to dig a bit to find info of recent vaccination with Covid vaccine!

I am genuenly concerned for every single person that had or will have the jab! Please don’t take it!

Physiotherapist, Private Practice.

Hi.

Thanks for giving us somewhere safe to speak out. I am a physio in private practice and previously contracted to aged care.

I have seen several deaths in aged care facilities in 12-24hours following the vaccination in people who were previously stable. Each time the entire file has been completely removed from the system and any notes by staff related to vaccine were deleted prior to the file being returned.

I actually retained proof of this from the first time I saw it happen as I could not believe what I had seen happen given how strict they are on no modification of record keeping being made in ANY other circumstance. This was not normal protocol when a death occurred in the facilities.

In private practice I have seen and heard of many side effects – similar to all those listed in the other accounts (persistent sharp headaches, increased previous injury flares, auto-immune disorder flares)

Probably the worst 2 were a patient with Parkinsons who I have been seeing for several years and had been symptomatically stable the entire time despite other health challenges. Post second vaccination they had a debilitating increase in freezing episodes and pain through their lower limbs. Their specialist denied this would have any connection to the vaccination so they did not question it any further.

Another client attended an appointment reporting they were completely bedridden for 3 weeks with extreme dizziness, lack of appetite and fatigue post initial vaccine (AZ). They were still breathless and very fatigued on the day they saw me. They are normally very well and active with no history of prior health issues. Again when they contacted the GP regarding the issues following the vaccine they were informed that what they had experienced the equivalent of “mild” symptoms of COVID and that was all to be expected with the vaccine. When I queried if they were going to return for their second dose, they reported they were so afraid as the GP had told them catching COVID would be much worse than what they were currently going through so they definitely needed to ensure they returned for their second dose. 😥😥

RN, Cardiology Ward, Major Hospital.
27/09/2021 AHPRA Verified ✅

Hi,

I work on a busy cardiology ward.

Overall in the medical notes Doctors aren’t connecting the dots and not even considering the jab as a reason for the illness. Whether that is intentional or not I don’t know.

I have seen young adults come onto the ward for cardiac monitoring after collapsing after the jab.

(1). A lady with an autoimmune disease came in with a pericardial effusion after her jab.

(2). One lady had chest pain for weeks after the second astrazeneca dose, she had myocarditis. She was quite sick when she was on the ward, she had fevers, and all of her face was swollen, her eyelids were that swollen she could barely open them and inside her eyes were all glassy.

(3). Another was a young guy, healthy as, post jab had severe cellulitis to one side of his face, his ear was Triple the size.

(4). Another guy in his 20s had his first pfizer and the day after was febrile, and after a TOE was diagnosed with infective endocarditis. He also developed acute kidney injury to the point of needing dialysis. All kidney scans came back normal but still his kidneys were failing. In his notes when he was in ED it was mentioned that this started post jab but then on the ward after being reviewed by multiple specialists (infectious disease, renal, cardiac) not once was the jab mentioned.

What I am finding disturbing in my area is that it’s not even being considered as a potential cause. Even though problems start after the jab.

RN, Community GP Practice, Former Vaccinator. AHPRA Verified ✅

Part 1 of 2..

Hi,

I’m an RN who was working in a GP clinic and guilty of being a covid vaccinator.

I had raised concerns on a number of occassions and could no longer give it when I started to see what was happening. During this time I have seen and heard things which lead me to believe the vaccines are not safe.

I have heard many people saying they were spaced out and dizzy for days.I can’t count how many times I heard “spaced out”. Older people coming back and saying they were off balance and having falls when this hasn’t happened to them before.

Also heard people say loss of bladder control, arthritis flare ups, eczemea and skin rashes, strange blister, out of control diabetes, unhealing wounds and enhanced pain of old injuries. A man reported that he had visual problems and thought he almost went blind for a month but went to the optometrist instead of a dr and he said he had reported it to the report link provided which he said they had “pretty much dismissed it”.

I have sent a man off in the ambulance with anaphylaxis reaction, uncontrollable shaking and tingling around his mouth, unable to walk. I have had 40y old man crying half hr post vaccination saying he didnt feel right, was dizzy, headache, heart palpatations and jitters, he did not believe it was anxiety as they said.

I’ve since realised there was an older man who didnt come back for second jab and I had reported this to the report line. I remember he had walked back into the treatment room the day after his jab and he was anxious, glassy eyed, said he was sick and had been falling over that night. I did his obs and his ecg wasnt right, offered for him to go in ambulance but he declined. He missed his second appointment I wouldn’t be surprised if he died.

I have seen a man with cancer go down hill very quickly after his jab.
I have heard patients tell me there family has told them they have to get the shot or they wont pay for a ventilator. Also a pt tell me that her old neighbour told her he thinks he has killed himself getting the jab and he hasnt been the same since.

Cont…

I have heard of a nurse pressured to get the jab who had diabetes under control is now on insulin. Another nurse I know didn’t want it but said she has brain fog and memory loss and sudden onset of menopause..she also admits to seeing patients at a seperate clinic she works at go down hill since getting the shots.

I have a nurse friend who has 2 family members, 1 with bells palsy and the other with myocarditis. She also knows a fit healthy 30yr old who had a heart attack.

My sisters 60yr old neighbour is in a coma after second shot. Her mother in law keeps passing out and her father in law has been showing aggression.

My brother in law also knows a guy in a coma and somebody else with blood clots in his bowel.
My sister in law had kidney stones the day after her second shot.

Another thing I have noticed is personality changes in patients and people I know or have worked with where a number of them seem to become aggressive, lack empathy and logical sense.

In comparing my findings with other nurses we have all noticed similiar patterns where we agree that comorbidities seem to become worsened and mortality is being sped up.

We are very concerned and worried sick, especially that they want to give these to our children who will be at much greater risk from the jab than the virus.

We disagree with the mandates, we believe the cases of injuries and deaths to be under reported and the jabs are unsafe and unethical and should be ceased immediately.

RN, Major Hospital.
27/09/21 AHPRA Verified ✅

I work on a rehab ward

I know of 3 patients who had a stroke 7-8 days post jab.

(1). 1 Pt with bell’s palsy.

(2). 1 Pt with Guillain-Barré syndrome.

(3). 1 man experienced an unresponsive episode following his 2nd jab. Diagnosed with hypo delirium and pneumonia! 3 weeks in hospital so far and at what financial cost?
Nothing documented in notes. Family told it was nothing to do with the jab.

Also possibly seeing vac shedding too.
Bels palsy, shingles causing encephalitis, lots of falls.

Lots of PE’s, but unsure of vac status.

Interesting that recently the federal gvt was trying to amend the NDIS Act! It would be interesting to see the statistics of new NDIS applications.

And, what happened to influenza?? Vanished?

Reported by REGISTERED NURSE from Regional NSW:

(1). 62 year old with blood clot on lung post AstraZeneca- ICU admission

(2). 35 year old with severe headaches and blood clot on brain- ICU admission 2 weeks- sent home to have MRIs every 2 weeks as followup

(3). 27 Year old Male- Pericarditis following Pfizer

(4). 19 Year old female- cardiac arrest 3 days post pfizer (deceased)
…and many others.

V status not being consistently asked or documented in eMR- medical team not looking to make correlation. Medical team worried about AHPRA and their careers if they speak out.

This is not what we signed up for!

MD. RN. 46years.
27/09/2021. AHPRA Verified ✅
Part 1 of 2.

Hi,

Im an RN of 46 yrs practicing as an acute peri/post operative care nurse.
I no longer practice. The following is an account of a close nursing colleague. She experienced: Pfizer x no1 jab- “headache from hell”.
No 2 pfizer jab- awoke in the night totally paralysed for 4-6 hrs(estimated as time unknown on waking). She could not move a muscle, cough, speak, take a deep breath or nudge her husband to call ambulance until it resolved. Only eyes would open and blink..at one point she wished she would die she felt so terrible.

On return to duty when recovered much later, she reported incident in writing to hear similar affects with 6 other nurses in total at her hospital. Date 2/6/21. Still has not been interviewed face to face as normal protocol, 10 weeks later.

What is going on? We must all ask ourselves and our superiors?
The Hippocratic oath- to do no harm? Are the medicos brain dead? Is it mind control? Surely no one could need the $ that badly. That is only one example…

Cont…

No 2 this is anecdotal from a jab victims daughter-in-law:
An 80 r yr old independant lady, no comorbidities in nursing home. Family expressly forbade- face to face with 2 staff members, her having the jab( I can’t call it a vaccine as it isnt). The army turned up to jab the residents. When they came to this 80 yr old, the residential nurse on duty told the army nurse the said woman was not to have the injection. She ignored the nurse and gave it (az) anyway- that was on a Thursday.

On the Friday the relative came to see her mother in law, having been informed via phone of the misdeed. She found the woman in an unusually hyped up state- as if high on something- unusual for this quiet woman.

On the Saturday, the injected woman asked her nurse to return her to her room as she felt unwell. According to the relative who had been told the following, as she walked down the hallway she collapsed and died instantly. This was day 2 after first az.

The attending physician refused to sign the death certificate as he thought his now deceased patient had NOT died of a cardiac arrest as staff assumed. Deceased was sent to coroner in a large city nearby. The coroner only scanned the body, decided it was heart attack and declined to perform a full post mortem. The lady has since been cremated so no body to exume? We all know what to call such an incident!

Life should never be this cheap!
Enough is enough. This must be stopped.
We all know there is power in numbers. Everyone, seem to be impotent to act on this critical and existential crisis in the making.

In fact this is threatening humanity’s very survival.

Childless Gladys should read these ‘testimonials’. She is some one else’s child too! Unwitting guilt abounds. The people responsible including medico’s, who ignore what they must be re-cognising, cannot plead ” I didn’t know” for too much longer, surely?? Bring on Nuremberg!

M. D. RN

Senior Clinical Nurse Specialist, Metropolitan Hospital, NSW.
27/09/21.

Hi there,
I am a senior Nurse (CNS2) in a metropolitan hospital, NSW.

My usual role is in Cardiology.
My lengthy career is ending this week, after decades in the acute sector.

I have seen many patients both in ED and Cardiology with vaccine SE’s .
These are LARGELY under-recognised, and RARELY reported. I have told relatives to make their own TGA reports as reporting in the acute sector is NOT HAPPENING.

Doctors are RARELY attributing the various conditions to vaccination, but when you take a history it is very easy to join the dots.

Heart attacks (all ages), acute myocarditis / pericarditis, DRASTIC deterioration in EF (ejection fraction – index of heart’s pumping strength), ie worsening in heart failure.

I understand that many are presenting with strokes, and other neurological complications.

Diabetes has been far more unstable in some, and difficult to manage, with very labile BSLs.

I have seen colleagues with gastrointestinal SE, recurrent pneumonias

Many non- injected, including myself have experienced symptoms from spike protein transmission (shedding).

GI pain (severe), headaches, migraines, sleep disturbance.
I have seen bizarre changes in pathology, huge drops in haemaglobin, and derangements in biochemistry (Na, kidney function).

I had a secondment in Aged Care and after the vaccination was rolled out in Facilities, saw MANY acute deteriorations, with increases in death rates above normal
Loss of speech, loss of mobility, chest infections.

My sister in law works in community aged care, and has seen MANY SE as well. Renal Failure, siezures, acute loss of mobility with resultant falls.
Many of the elderly she has cared for and knows well have had their death hastened, or had to move into residential care as they now cannot manage at home.

Thanks for helping us to get our stories out there.

RN, 40 years experience, NSW.
27/09/21. AHPRA Verified ✅

Hello,
I am an RN with over 40 years experience, mostly in the public sector.

I am currently employed on a casual basis.

I received a letter from NSW Health last week stating I “ must have” my first “ vaccination” by the 30th September to continue to work.
If I don’t I will not be able to work for NSW Health and will be placed on unpaid leave.

All of the nurses in my ward( except a pregnant one) acquiesced to the “ vaccine” even though some were
dead against it.

One nurse experienced loss of sensation in both legs below the knees which eventually resolved.
Another staff member( clerical) had a mini stroke and ended up in ED.
Both these episodes were not reported as vaccine injury.

Indeed, one Physician said it definitely is not vaccine related.
I will now be forced not to work as I do not want the “vaccine”.
I believe NSW Health system will be in dire straights after 30th September and beyond as very experienced staff leave.

I am a Registered Nurse working for a large public hospital in Melbourne.

A significant amount of our patients have had the covid vaccine and are presenting to us as transfers from ED, presenting with chest pain, shortness of breath, neurological symptoms , headaches and fevers. These patients are being found to have confirmed mini strokes (TIA), Pulmonary Embolisms, neurological disorders, severe headaches and deranged pathology resulting particularly often in acute kidney injury.

The most concerning of these presentations is the fact that majority of these patients range from 20-70 years old. One female patient in her 30’s presented with a body temperature of 40 degrees and has since been found to have multiple bilateral PE’s.

There has been no documentation or discussion from Doctors linking these patients symptoms with their recent covid vaccination. These patients were healthy and fully functioning people pre vaccination.

We’re also having to palliate patients at a concerning rate due to acute deterioration. Most of these patients are dying from respiratory failure or suffering a massive stroke.

All nurses in my clinical area have now been vaccinated besides myself. Some have told me they were coerced into getting it by management.
I am counting down the days now until I’m fired for not wanting the vaccine.

Our current staffing is awful, I hate to think how bad it will be after October 15th when unvaccinated nurses are mercilessly terminated from employment. I feel for the patients who will fall through the gaps of our already stressed healthcare system.

Registered Midwife, WA.
28/09/2021
AHPRA Verified ✅

Hello, Thank you so much for the work you are doing.

I’m a Registered Midwife in W.A. and until I resigned on Wednesday Sep 21, I had been working at the biggest hospital in the South West region. When RANZCOG and the ACM came out with their guidelines stating the c19 vax was safe for pregnancy, the directive from the hospital was to promote it hard.

At the hospital clinic I know of 2 women that received their first doses and they subsequently lost their babies;

1st dose at 34 weeks and 2 days, fetal death in utero at 36 weeks

1st dose 28+2, fetal death in utero 29 weeks I know of other women in the community under 20 weeks as reported to me by midwives that work with General Practice obstetricians;

1st dose 12+6, miscarriage 13 weeks

1st dose 17 +5, miscarriages 18 weeks

1st dose 12 weeks, miscarriage 12+2

Now, I know correlation does not mean causation, but it certainly should be investigated. Only one of the above cases have been reported. I fear many won’t be and they will be lumped into the 1:4 pregnancy loss statistic.

It’s not something that is asked (vaccine status) when women come to the hospital with a loss, so many may fall through and be missed.

I mentioned it to a doctor and they didn’t see the connection. I’m so sad to leave a job I love, but this isn’t health. This is something entirely different.

Registered Midwife, Small Rural Hospital.
28/09/21. AHPRA Verified ✅

Hi,

I’m a Midwife in a small rural hospital.

We recently admitted a woman who’s baby had unfortunately died in utero and was subsequently stillborn. She was in her third trimester and she’d had her 2nd dose of Pfizer just 3 days before she stopped feeling the baby moving.

When I questioned my manager if this was going to be reported to the TGA she talked to the doctor and he said no, because there was no evidence of the two being linked.

I can’t help but wonder…what if nobody else is reporting events like this either because they all think there is no evidence?

contact us: nursesspeakout@pm.me

September 27, 2021 Posted by | Full Spectrum Dominance, Science and Pseudo-Science, Timeless or most popular | , | Leave a comment

Legitimate resistance: should Hamas and Hezbollah learn from the Taliban?

By Ramzy Baroud | MEMO | September 27, 2021

An urgent task is awaiting us: given the progression of events, we must liberate ourselves quickly from the limits and confines placed on the Afghanistan discourse, which have been imposed by US-centred Western propaganda for over 20 years and counting. For a start, we must not allow the future political discourse on this subject to remain hostage to American priorities: successes, failures and geostrategic interests.

For this to happen, the language itself must be challenged. This is critical if we are to glean valuable lessons from Afghanistan and avoid a repeat of the failure to comprehend the US defeat in Vietnam (1955-1975) in the way it should have been understood, not the way that Washington wanted Americans — in fact, the whole world — to understand. Vietnam was not merely an American “debacle”, and did not only culminate in an American “defeat”. It was also a Vietnamese victory and the triumph of the will of the people over the US imperialist war machine.

In US mainstream media and, to a large extent, academia, the history of the Vietnam War was written almost entirely from an American perspective. Even the anti-war version of that history remained US-centric.

Alas, in the case of Afghanistan, many of us, whether in journalism or academia, wittingly or otherwise, remain committed to the US-based discourse, partly because the primary sources from which our information is gleaned are either American or pro-American. Al-Akhdar Al-Ibrahimi, former UN Peace Envoy to Afghanistan from 1997 to 1999, and again from 2001 to 2004, reminded us recently, in an interview with French newspaper Le Monde, of the importance of using proper language to describe the unfolding events in Afghanistan: “Why [do we] always speak of an American defeat? First of all, this is a victory for the Taliban, which must be attributed to their tactical genius.” (Translated from French)

The answer to his question can be deduced easily from his own words because, to speak of a Taliban victory, is to admit to their “tactical genius”. The admission of such a truth can have far-reaching consequences.

The use of the terms defeat vs. victory is critical because it situates the conversation within two entirely different intellectual frameworks. For example, by insisting on the centrality of the question of the American defeat, whether in Afghanistan or Vietnam, then the focus of the follow-up questions will remain centred on American priorities: Where did the US go wrong? What urgent changes must Washington implement in its foreign policy and military agendas to stave off its Afghanistan shortcomings? And where should the US go from here?

However, if the focus remains centred on the victory of the Afghan resistance — and yes, it was Afghan resistance, not merely that of the Taliban or Pashtun — then the questions that follow would relocate the conversation somewhere else entirely. How did poorly armed fighters manage to defeat the world’s combined great powers? Where should Afghanistan go from here? And what lessons can national liberation movements around the world learn from the Afghan victory?

For the purpose of this article, I am concerned with the Afghan victory, not the American defeat.

The rise and fall of the “terrorist” discourse

The collapse of the Soviet Union in 1991 had a massive impact, not only on the geopolitical map of the world, but also on relevant global political discourses. Like the USSR, the Warsaw Pact and its global alliances began to disintegrate, the US moved quickly into action, asserting its dominance from Panama (1989) to Iraq (1991) and beyond. The American objective was not merely a violent declaration of its triumph in the Cold War, but a message to the rest of the world that the “American century” had begun and that no form of resistance to the US stratagem could be tolerated.

In the Middle East, in particular, the new narrative was on full display, with clear and repeated distinctions between “moderates” and “extremists”, friends and enemies, allies and those marked for “regime change”. According to this new logic, anti-colonial forces that were celebrated as liberation movements for decades fell suddenly into the category of “terrorists”. This definition included Palestinian, Lebanese and other resistance groups, even though they sought liberation from illegal foreign occupation.

Years later, the discourse on terrorism — summed up by George W. Bush’s statement in September 2001, “Either you are with us or you are with the terrorists” — became the yardstick by which the world, according to Washington, was to be judged and divided into freedom-loving nations and terrorist, extremist regimes. The latter category was eventually expanded to include Iraq, Iran and Syria. On 29 January 2002, North Korea was also added to Washington’s so-called “axes of evil”.

Afghanistan, of course, topped the American list of terrorist states, under various pretences: initially it was for harbouring Osama Bin Laden and Al-Qaeda and, later, the mistreatment of women, and so on. Eventually, the Taliban was labelled a “terrorist” group, leading an “insurgency” against the “democratically-elected” Afghan government in Kabul. The past 20 years have been spent in the construction of this false paradigm.

In the absence of any strong voices in the media demanding a US withdrawal and defending the Afghan people’s right to resist foreign occupation, there was a near-complete absence of an alternative political discourse that even attempted to raise the possibility that the Taliban, despite all of their questionable strategies and practices, may, in fact, be a national liberation movement.

The reason we were discouraged from considering such a possibility is the same reason why US-Western-Israeli propaganda insisted on removing any distinction between Daesh (ISIS), Al-Qaeda, the Taliban, Hamas, Hezbollah, Al-Houthis and many other such groups. On the one hand, discussing the particularities of each movement requires real knowledge of the history and formation of each one separately, and the political circumstances through which they continue to operate. This kind of knowledge is simply non-existent in the cliché-ridden, soundbite-driven mainstream media. On the other hand, such understanding is inconvenient, as it complicates the deception and half-truths necessary for the US, Israel and others to depict their military occupations, unlawful military interventions and repeated wars as fundamental to some imagined global “war on terror” and, as some European intellectual circles prefer to dub it, a war on “radical Islam”.

However, unlike Al-Qaeda and Daesh, Hamas, Hezbollah and the Taliban are not trans-border militant groups fighting a global agenda, but national liberation movements which, despite their emphasis on religious discourses, are political actors with specific political objectives confined largely within the borders of their own countries; Palestine, Lebanon and Afghanistan, respectively.

Regarding Hamas, London-based author Daud Abdullah wrote in his book Engaging the World: The Making of Hamas Foreign Policy that: “Hamas sees foreign relations as an integral and important part of its political ideology and liberation strategy. Soon after the Movement emerged, foreign policies were developed to help its leaders and members navigate this tension between idealism and realism. This pragmatism is evident in the fact that Hamas was able to establish relations with the regimes of Muammar Gaddhafi in Libya and Bashar Al-Assad in Syria, both of whom were fiercely opposed to the Muslim Brotherhood.”

It was also Abdullah who became one of the first to draw the parallels between Palestine and Afghanistan as soon as the Taliban declared victory in Kabul. In a recent article in the Middle East Monitor, he wrote, “Palestine and Afghanistan are salient examples. Throughout history, their peoples have witnessed numerous invasions and occupations. After two decades the US has finally run out of stamina. Similarly, they will eventually realise the futility of supporting the Zionist occupation of Palestine.”

Indeed, the lesson of Afghanistan must be studied carefully, especially by resistance movements that are undergoing their own wars of national liberation.

Now that the US has officially ended its military operations in Afghanistan, albeit not by choice, the emphasis on the so-called “war on terror” discourse will certainly begin to fade. What, though, will come next? While another interventionist discourse will certainly fight for prominence in the new American thinking, the discourse of national liberation, based on legitimate resistance, must return to the centre of the conversation.

This is not an argument for or against armed struggle, as this choice falls largely, if not entirely, on nations that are struggling for their own freedom, and should not be subject to the selective, frequently self-serving, ethics of Western moralists and activists. It is worth mentioning that international law does not prohibit people from using whatever means necessary to liberate themselves from the jackboot of foreign occupation. Indeed, myriad UN resolutions recognise the “legitimacy of (oppressed people’s) struggle by all means at their disposal, including armed struggle”. (UN Commission of Human Rights Resolution 1982/16)

Nevertheless, armed struggle without popular, grassroots support often amounts to nothing, for a sustainable armed campaign, like those of Hamas, Hezbollah or the Taliban, requires deep-rooted social and socio-economic support. This proved as true in Vietnam as it did earlier in Algeria (1954-1962), Cuba (1953-1959) and even South Africa, where the history of armed struggle has been largely written out in favour of what is meant to appear as a “peaceful” anti-apartheid struggle and transition of power.

For nearly 30 years, partly as a consequence of the dismantling of the Soviet Union and the seemingly uncontested rise of the American empire, almost any form of armed struggle in national liberation contexts has been depicted as “terrorism”. Moreover, in the post-9/11 US-dominated world, any attempt at arguing otherwise earned any daring intellectual the title of “terrorist sympathiser”.

Twenty years have elapsed since the American invasion of Afghanistan culminated in the defeat, not just of the US but also of the US political discourse on terrorism, resistance and national liberation. The resulting victory of the Taliban will extend well beyond the borders of Afghanistan, breaking the limits imposed on the discussion by western-centric officials, media and academia, namely the urgently needed clear distinction between “terrorism” and national liberation.

The American experiment, using firepower to control the world, and intellectual hegemony to control our understanding of it, has clearly failed. This failure can and must be exploited as an opportunity to revisit urgent questions and to resurrect a long-dormant narrative in favour of anti-colonial, national liberation struggles with the legitimate right — in fact, responsibility — to use all means necessary, including armed struggle, to free nations from the yoke of foreign occupation.

September 27, 2021 Posted by | Book Review, Illegal Occupation, Timeless or most popular | , , , , | Leave a comment

Chromothripsis: Bad news for gene editing

By Claire Robinson | GMWATCH | September 22, 2021

CRISPR gene editing is often presented as a straightforward, precise, and safe procedure. But recent research findings on CRISPR gene editing for gene therapy applications show it can lead to massive damage to chromosomes. The phenomenon is known as chromothripsis.

An article in Nature Biotechnology about the new findings describes chromothripsis as “an extremely damaging form of genomic rearrangement that results from the shattering of individual chromosomes and the subsequent rejoining of the pieces in a haphazard order”.

And now there are signs that the findings are hitting gene editing companies’ stock.

“You cannot make this go away”

The authors of the new study, published in Nature Genetics, conclude that “chromothripsis is a previously unappreciated on-target consequence” of the double-strand breaks in the DNA that CRISPR gene editing is designed to bring about. The fact that the damage occurs “on-target” – at the intended edit site – means that any attempts to target the CRISPR gene editing more precisely will not solve this problem, as pointed out in the Nature Biotechnology article by one of the researchers on the study, David Pellman of the Dana-Farber Cancer Institute and Harvard Medical School. He said, “You cannot make this go away by making the cutting more specific.”

Cancer worries

The major worry with chromothripsis in therapeutic settings is that it can lead to cancer or an inherited disease in any children of the affected patient. It would only take a single cell to be affected by chromothripsis to result in a cancer.

This has implications for animal gene editing, as edited animals could be prone to cancer. But it also spells bad news for plant gene editing, where chromosomal damage would lead to changes in the function of genes that could in turn result in unexpected toxicity or allergenicity, as well as unpredictable effects on wildlife.

Effect “cannot be completely avoided”

While an expert interviewed for the Nature Biotechnology article is upbeat about the ability of the gene editing field to “innovate its way around” this and any other problems that arise from CRISPR processes, the researchers on the original paper seem less convinced.

This is evident from the preprint version of their article, which appeared on BioRxiv before the peer-reviewed version was published in Nature Biotechnology. In the preprint version, the authors bluntly call chromothripsis “a catastrophic mutational process” and warn that it is “an on-target toxicity that may be minimized by cell manipulation protocols or screening but cannot be completely avoided in many genome editing applications”.

However, this wording is absent from the final published version. The original downbeat conclusion on the impossibility of avoiding chromothripsis has been watered down to the bland statement, “As genome editing is implemented in the clinic, the potential for extensive chromosomal rearrangements should be considered and monitored.”

Investors running scared

Others who remain unconvinced that this inherent problem of CRISPR can be solved may include investors in CRISPR-based companies. An article for the investment news outlet Seeking Alpha says that the “new data concerning chromothripsis may affect the long-term outlook of companies such as Crispr Therapeutics”. The stock of these companies (collected in a fund known as ARKG), which was previously surging, suddenly slumped in July this year, the same month that the Nature Biotechnology study was published.

The Seeking Alpha article continues, “The long-term impact on health of gene editing may not be known until around 2040.” It concludes, “Given the uncertain outlook, investors may be wise to re-evaluate their positions in companies employing DNA double strand breaks to edit the genome.”

Seeking Alpha does not go so far as to blame the chromothripsis findings as the sole or main cause of ARKG’s slump, but notes it as “one contributory factor”.

Chromothripsis is just the latest in a long list of unintended CRISPR-induced outcomes that can occur at the intended edit site and thus cannot be avoided by improving CRISPR targeting. In spite of this, policymakers in the UK and the EU persist in echoing industry lobbyists’ narratives that CRISPR gene editing is precise and the outcomes predictable.

September 27, 2021 Posted by | Economics, Science and Pseudo-Science, Timeless or most popular | Leave a comment

WHO Insider Blows Whistle on Gates and GAVI

This article was previously published March 19, 2021, and has been updated with new information.

By Dr. Joseph Mercola | September 24, 2021

OK folks, today you are in for a real treat. We have presented many of the pieces previously, but this will help put them in the proper perspective. That is the phase we are in now. We have the facts, we just need to understand what they mean and interpret them properly.

This is a really important article. It catalyzed my understanding of what the heck is going on. The facts are obvious; the entire response to the global pandemic was facilitated by the World Health Organization. Their recommendations were followed lock-step by virtually every government on Earth.

No one will dispute this fact. The next data point is: Who controls the WHO? Some will dispute this, but the evidence is pretty clear and solid. It is Bill Gates, who became the WHO’s biggest funder when then-President Trump removed U.S. support in 2020.

What does Gates have to benefit from controlling the WHO? How about the best investment he ever made, with many tens of billions of dollars running through his “nonprofit” GAVI Vaccine Alliance? The maniacal suppression and censorship of any inexpensive natural alternative for COVID-19 makes perfect sense now.

These natural therapies, with nebulized hydrogen peroxide, ivermectin and hydroxychloroquine being the best examples, would be serious competition for the vaccines. If everyone knew that these remedies were readily available, highly effective and practically free, who would risk their life for a vaccine? Virtually no one. It all makes perfect sense.

With that framework, enjoy the information our team has compiled that expands on this general concept. Every day we are putting the pieces of the puzzle together, and the more pieces we fit together, the sooner you will see the bigger picture.

WHO Insider Speaks Out

In July 2020, four German attorneys founded the German Corona Extra-Parliamentary Inquiry Committee (Außerparlamentarischer Corona Untersuchungsausschuss1).2,3 In the video above, the founding members, led by Dr. Reiner Fuellmich,4 interviews Astrid Stuckelberger, Ph.D., a WHO insider, about what she discovered about Bill Gates and GAVI, the Vaccine Alliance.

Stuckelberger has served as deputy director of the Swiss national program of aging since the 1990s, and is the president of the WHO-funded Geneva International Network on Ageing.

According to her bio,5 she “is an internationally recognized expert on issues related to evaluating scientific research for policymakers, in particular in health and innovation assessment, pandemic and emergency management training and in optimizing individual and population health and well-being.”

She’s also a published author, with a dozen books to her credit, as well as more than 180 scientific articles, policy papers and governmental and international reports. Stuckelberger points out that much of the research was and still is highly politicized and primarily done to support and justify political decisions.

For the past 20 years, since 2000, she’s been involved with public health at the WHO, and was part of their research ethics committee for four years. In 2009, she got involved with the WHO’s international health regulations.

Stuckelberger points out that the whole purpose of WHO’s international health regulations is to prepare member states to be ready for a pandemic, to be able to not only prevent outbreaks but also respond swiftly when an outbreak occurs. However, the WHO has actually been actively preventing and undermining this pandemic preparedness training.

The Center of Corruption

According to Stuckelberger, Switzerland is at the heart of the corruption, largely thanks to it being the headquarters for GAVI, the Vaccine Alliance, founded by Bill Gates. In 2009, the GAVI Alliance was recognized as an international institution and granted total blanket immunity.6

As explained by Justus Hoffmann, Ph.D., one of the German Corona Extra-Parliamentary Inquiry Committee members, GAVI has “qualified diplomatic immunity,” which is odd, considering the organization has no political power that would warrant diplomatic immunity. Odder still is that GAVI’s immunity clauses go beyond even that of diplomats. GAVI’s immunity covers all aspects of engagement, including criminal business dealings.

“They can do whatever they want,” Stuckelberger says, without repercussions. The police, for example, are barred from conducting an investigation and collecting evidence if GAVI were to be implicated in a criminal investigation. “It’s shocking,” she says. GAVI is also completely tax exempt, which Stuckelberger notes is “very strange.”

Essentially, GAVI is a nongovernmental organization (NGO) that is allowed to operate without paying any taxes, while also having total immunity for anything they do wrong, willfully or otherwise. This is rather unprecedented, and raises a whole host of questions. It’s particularly disturbing in light of evidence Stuckelberger claims to have found showing that GAVI is “directing, as a corporate entity, the WHO.”

Furthermore, documents cited by Stuckelberger show the WHO has assumed what amounts to dictatorial power over the whole world. The director general has the sole power to make decisions — including decisions about which tests or pandemic medications to use — that all member states must then obey.

The Nation-State of Gates

What’s more, Stuckelberger discovered that, in 2017, Gates actually requested to be part of the WHO’s executive board — like a member state — ostensibly because he gives them so much money. Indeed, his funding exceeds that of many individual member states.

Like Stuckelberger says, this is truly incredible — the idea that a single man would have the same power and influence over the WHO as that of an entire nation. It’s a brazen power grab, to say the least. While there’s no evidence that Gates was ever officially granted the status of a member state, one wonders whether he doesn’t have it unofficially.

One thing that raises Stuckelberger’s suspicion is the fact that Swissmedic, the Food and Drug Administration of Switzerland, has entered into a three-way contract agreement with Gates and the WHO. “This is abnormal,” she says.

Essentially, in summary, it appears that when he did not get voted in as a one-man nation state, Gates created three-party contracts with member states and the WHO, essentially placing him on par with the WHO. As mentioned earlier, whatever the director general of the WHO says, goes. They’ve effectively turned global health security into a dictatorship.

The question is, is Gates the real power behind the curtain? Does he tell the director general what to do? When you look back over the past year, it seems Gates has often been the first to announce what the world needs to do to address the pandemic, and then the WHO comes out with an identical message, which is then parroted by world leaders, more or less verbatim.

As noted by Fuellmich, it’s becoming clear that many private-public partnerships have been hijacked by the private side — and they’re immune from liability. “This has got to stop,” he says.

A complete review and overhaul of the United Nations, which established the WHO, is also required as the U.N. has done nothing to prevent or rein in undemocratic and illegal activity. As noted by Fuellmich, we probably need to reconsider whether we even need them.

Changed Definition of Pandemic Allowed Health Dictatorship

In the interview, they also highlight the WHO’s role in setting the stage for a global health dictatorship by changing the definition of “pandemic.” The WHO’s original definition, pre-2009, of a pandemic was:7,8

“… when a new influenza virus appears against which the human population has no immunity, resulting in several, simultaneous epidemics worldwide with enormous numbers of deaths and illness.”

The key portion of that definition is “enormous numbers of deaths and illness.” This definition was changed in the month leading up to the 2009 swine flu pandemic.

The change was a simple but substantial one: They merely removed the severity and high mortality criteria, leaving the definition of a pandemic as “a worldwide epidemic of a disease.”9 This switch in definition is why COVID-19 was and still is promoted as a pandemic.10,11,12

We now have plenty of data showing the lethality of COVID-19 is on par with the seasonal flu.13,14,15,16,17 It may be different in terms of symptoms and complications, but the actual lethality is about the same. Yet we’re told the price we must all pay to keep ourselves and others safe from this virus is the relinquishing of our civil rights and liberties.

In short, by removing the criteria of severe illness causing high morbidity, leaving geographically widespread infection as the only criteria for a pandemic, the WHO and technocratic leaders of the world were able to bamboozle the global population into giving up our lives and livelihoods.

WHO Rewrites Science by Changing Definition of Herd Immunity

The WHO has also radically altered the definition of “herd immunity.” Herd immunity occurs when enough people acquire immunity to an infectious disease such that it can no longer spread widely in the community. When the number susceptible is low enough to prevent epidemic growth, herd immunity is said to have been reached.

Prior to the introduction of vaccines, all herd immunity was achieved via exposure to and recovery from an infectious disease. Eventually, as vaccination became widespread, the concept of herd immunity evolved to include not only the naturally acquired immunity that comes from prior illness, but also the temporary vaccine-acquired immunity that can occur after vaccination.

However, in October 2020, the WHO upended science as we know it, revising this well-established concept in an Orwellian move that totally removes natural infection from the equation.

As late as June 2020, the WHO’s definition of herd immunity, posted on one of their COVID-19 Q&A pages, was in line with the widely-accepted concept that has been the standard for infectious diseases for decades. Here’s what it originally said:18

“Herd immunity is the indirect protection from an infectious disease that happens when a population is immune either through vaccination or immunity developed through previous infection.”

The updated definition of herd immunity, which appeared in October 2020, read as follows:19

“‘Herd immunity’, also known as ‘population immunity’, is a concept used for vaccination, in which a population can be protected from a certain virus if a threshold of vaccination is reached. Herd immunity is achieved by protecting people from a virus, not by exposing them to it.

Vaccines train our immune systems to create proteins that fight disease, known as ‘antibodies’, just as would happen when we are exposed to a disease but — crucially — vaccines work without making us sick.

Vaccinated people are protected from getting the disease in question and passing it on, breaking any chains of transmission. With herd immunity, the vast majority of a population are vaccinated, lowering the overall amount of virus able to spread in the whole population.”

After public — and no doubt embarrassing — backlash, the WHO revised its definition again December 31, 2020, to again include the mention of natural infection, while still emphasizing vaccine-acquired immunity. It now reads:20

“‘Herd immunity’, also known as ‘population immunity,’ is the indirect protection from an infectious disease that happens when a population is immune either through vaccination or immunity developed through previous infection.

WHO supports achieving ‘herd immunity’ through vaccination, not by allowing a disease to spread through any segment of the population, as this would result in unnecessary cases and deaths.

Herd immunity against COVID-19 should be achieved by protecting people through vaccination, not by exposing them to the pathogen that causes the disease.”

WHO’s Recommendation of PCR Test ‘Intentionally Criminal’

Stuckelberger also shocks the Corona Extra-Parliamentary Inquiry Committee by pointing out that twice — December 7, 2020,21,22 and January 13, 202123 — the WHO issued medical alerts for PCR testing, warning that use of high cycle thresholds (CT) will produce high rates of false positives, that the CT value should be reported to the health care provider and that test results be considered in combination with clinical observations, health history and other epidemiological information.

Yet since the beginning of the pandemic, it has pushed PCR testing as the best way to detect and diagnose infection. This, she says, makes it intentionally criminal. The January 13, 202124,25 medical product alert was, incidentally, posted online January 20, 2021, mere hours after Joe Biden’s inauguration as the president of the United States.

In this alert, the WHO stressed that the “CT needed to detect virus is inversely proportional to the patient’s viral load,” and that “Where test results do not correspond with the clinical presentation, a new specimen should be taken and retested.”

It also reminds users that “disease prevalence alters the predictive value of test results,” so that “as disease prevalence decreases, the risk of false positive increases.” The alert goes on to explain:26

“This means that the probability that a person who has a positive result (SARS-CoV-2 detected) is truly infected with SARS-CoV-2 decreases as prevalence decreases, irrespective of the claimed specificity.

Most PCR assays are indicated as an aid for diagnosis, therefore, health care providers must consider any result in combination with timing of sampling, specimen type, assay specifics, clinical observations, patient history, confirmed status of any contacts, and epidemiological information.”

Taking a patient’s symptoms into account and using a scientifically defensible CT count should have been routine practice from the beginning. It just didn’t fit the geopolitical narrative. Since the start of the pandemic, the WHO has recommended using a CT of 45,27,28,29 which guarantees an enormous number of false positives, and therefore “cases.” This alone is how they kept the pandemic fearmongering going.

The scientific consensus has long been that anything over 35 CTs renders the PCR test useless,30,31,32 as the accuracy will be a measly 3%, meaning 97% are false positives.33 By finally recommending lower CTs and more precise criteria for diagnosis, the WHO engineered an assured end to the caseload at a desired time. Coincidentally, the next day, January 21, 2021, President Biden announced he would reinstate the U.S.’ financial support for the WHO.34

Time to Put an End to the Global Health Mafia

The WHO was created as a specialized agency of the U.N., established in 1948 to further international cooperation for improved public health conditions. It was given a broad mandate under its constitution to promote the attainment of “the highest possible level of health” by all peoples.

It is now beyond dispute that the WHO is beyond compromised. Because of its funding — a large portion of which comes from the “one-man nation-state of Gates” — it fails to complete its original mandate. Worse, WHO serves corporate masters and through its dictatorial powers is essentially destroying, not improving, the health of the world.

In June 2010, the Council of Europe Parliamentary Assembly (PACE) issued a report35 on the WHO’s handling of the 2009 pandemic of novel influenza A (H1N1), which included the recommendation to use a fast-tracked vaccine that ended up causing disability and death around the world.

PACE concluded “the handling of the pandemic by the WHO, EU health agencies and national governments led to a waste of large sums of public money, and unjustified scares and fears about the health risks faced by the European public.”36

Specifically, PACE found “overwhelming evidence that the seriousness of the pandemic was vastly overrated by WHO,” and that the drug industry had influenced the organization’s decision-making — a claim echoed by other investigators as well.37,38,39,40,41

The Assembly made a number of recommendations, including greater transparency, better governance of public health, safeguards against undue influence by vested interests, public funding of independent research and, last but not least, for the media to “avoid sensationalism and scaremongering in the public health domain.”42

None of those recommendations were followed and, if anything, the WHO’s mismanagement of public health, thanks to private-public partnerships with NGOs such as GAVI, has only worsened. Other reports, two published in 201543,44 and one in 2017,45 also highlighted the WHO’s failures and lack of appropriate leadership during the 2013 through 2015 Ebola outbreak in West Africa.

While the WHO is recognized as being uniquely suited to carry out key functions necessary in a global pandemic, experts at the London School of Hygiene and Tropical Medicine, and the Harvard Global Health Institute, have pointed out, years ago, that the WHO has eroded so much trust that radical reforms would be required before it can assume an authoritative role.

Yet here we are, still, and no reforms ever took place. Instead, the corruption festered and metastasized, and the WHO turned into a power hub for the technocratic deep state that seeks to assume power and control over all nations.

As noted by Fuellmich, we probably need to take a long hard look at the WHO and the U.N., and decide whether they’re even worth saving. At bare minimum, the disproportionate influence by private vested interests, disguised as NGOs such as GAVI, must be thoroughly investigated and routed out.

Sources and References

September 27, 2021 Posted by | Timeless or most popular, Video | , , , | Leave a comment

UK to begin nation-wide fluoridation of tap water

By Kit Knightly | OffGuardian | September 26, 2021

The British government is expected start adding fluoride to the drinking water all over the country according to a story in the Guardian.

The story focuses on a joint statement the Chief Medical Officers (CMOs) of England, Scotland, Wales and Northern Ireland published on Thursday, which recommends everyone, everywhere should have fluoride added to their water supply.

The report was already praised in a tweet from UK Health Secretary Sajid Javid:

While fluoridation is already in place in some parts of the UK, it has always been considered a matter for local government and currently affects less than 10% of the country.

Proposed changes to the regulations in sections 128-129 of the new Health and Care Bill would centralise this power, taking the decision out of the hands of local councils and handing it to the Health Secretary.

The authors of the report, including England’s CMO Chris Whitty (who we are more than familiar with, thanks to Covid) are not subtle in their attempts to cloak the proposed policy in “progressive” camouflage.

Statistics on tooth decay in children and the working class are trotted out so fluoridation could be sold as both “protecting children” and tackling “entrenched inequality”.

But what is the real risk-reward situation for fluoridated tap water?

Well, the only potential benefit of fluoride is preventing tooth decay. That’s it. (And even then, over-exposure to fluoride can actually damage your teeth through dental fluorosis).

The potential side effects of fluoride toxicity are far more dangerous than needing a root canal.

There is some evidence fluoride could increase the risk of cancer – a 2006 study found an increased risk of osteosarcoma in young boys – but the most serious problem associated with fluoride is developmental neurotoxicity.

In 2012 a study from the Harvard School of Public Health found fluoride exposure is detrimental to the intellectual development of children, with an author of the study saying [emphasis added]:

Fluoride seems to fit in with lead, mercury, and other poisons that cause chemical brain drain. The effect of each toxicant may seem small, but the combined damage on a population scale can be serious, especially because the brain power of the next generation is crucial to all of us.”

These findings were confirmed when the same group conducted a pilot study on the effect of long term fluoridation in Chinese children.

The results found that children raised in areas with widespread water fluoridation had markedly lower average IQs than children from areas with no fluoride in the water:

This pilot study in a community with stable lifetime fluoride exposures supports the notion that fluoride in drinking water may produce developmental neurotoxicity

To sum up: Fluoride in the water could potentially make future generations of people compliant, gullible and stupid.

Or, in other words, it’s the perfect thing to start pumping into the water when you’ve just tried to launch a global coup, and not enough people are falling for it.

September 26, 2021 Posted by | Timeless or most popular | | Leave a comment

What Does It Mean to ‘Trust the Science’?

By Dr. Joseph Mercola | September 24, 2021

In the featured video,1 James Corbett of The Corbett Report explores what it means to “trust the science,” demolishing along the way the notion that science can ever be “settled” and beyond question. This is important, because scientific deception will continue to be used in the biosecurity state being built around us.

What Science Should You Trust?

With increasing frequency, we’re told to “trust the science” and “follow the science.” Yet what science are we supposed to follow? Exactly who’s an expert and who’s not, and who decides which is which? As I’ve been writing about for nearly two years now, there’s plenty of scientific evidence refuting everything we’re being told to accept as “fact.”

This includes the claim that masks protect against viral infection, that lockdowns slow down the spread, that school closures protect children, that there are no effective early treatments for COVID-19, and that the fast-tracked COVID shots are safe, effective and necessary even if you have natural immunity.

Whistleblowers Expose Corruption at the EPA

Corbett starts out by reviewing a recent Intercept story, published in two parts: “Whistleblowers Expose Corruption in EPA Chemical Safety Office,”2 published July 2, 2021, and “Leaked Audio Shows Pressure to Overrule Scientists in ‘Hair-On-Fire’ Cases,”3 published August 4, 2021.

According to four whistleblowers — Elyse Osterweil, Martin Phillips, Sarah Gallagher and William Irwin, all of whom are scientists employed by the U.S. Environmental Protection Agency and hold doctorates in toxicology, chemistry, biochemistry and medicinal chemistry — managers and career staffers in the EPA’s Office of Chemical Safety and Pollution Prevention have tampered with the risk assessments of dozens of chemicals to hide their dangers. According to The Intercept :4

“The whistleblowers, whose jobs involve identifying the potential harms posed by new chemicals, provided The Intercept with detailed evidence of pressure within the agency to minimize or remove evidence of potential adverse effects of the chemicals, including neurological effects, birth defects, and cancer.

On several occasions, information about hazards was deleted from agency assessments without informing or seeking the consent of the scientists who authored them.

Some of these cases led the EPA to withhold critical information from the public about potentially dangerous chemical exposures. In other cases, the removal of the hazard information or the altering of the scientists’ conclusions in reports paved the way for the use of chemicals, which otherwise would not have been allowed on the market.”

At the EPA, Following the Science Is a Punishable Offense

The EPA, according to these whistleblowers, is violating the Toxic Substances Control Act (TSCA), and when staffers actually do follow the science wherever it leads, they are punished.

In a statement to The Intercept and Rep. Ro Khanna, chair of the House Committee on Oversight and Reform, the EPA whistleblowers state that they fear “their actions (or inactions) at the direction of management are resulting in harm to human health and the environment.”

They certainly have cause for concern. For example, one recent study5 warns exposure to organochlorine pesticides and polybrominated diphenyl ethers during pregnancy can cause the chemicals to accumulate in multiple fetal organs and contribute to chronic health problems. This is the first study to demonstrate that toxic chemicals can be present in the fetus even if the mother does not have detectable levels in her blood. As noted by Beyond Pesticides:6

“… studies like these help government and health officials better identify fetal exposure contaminants and subsequent health concerns otherwise missed by current chemical monitoring methods.”

In Part 27 of its report, The Intercept discusses a particular chemical that Irwin had been assessing. He had concerns that the unnamed chemical in question was analogous to bisphenol-A (BPA), a chemical now recognized for its detrimental effects on reproduction, fertility and human hormones.

When he refused to sign off on the chemical as safe, he was removed from the assessment, and the chemical was approved, despite the potential harms he’d uncovered.

So, what scientists should we trust? Scientists like these four whistleblowers? Or “the EPA” as a catchall designation, where corrupt career managers have overruled the scientists doing the actual work and who have the actual science credentials?

Believing (the Wrong) Science Now Proves You’re Racist

As noted by Corbett, this issue is no small matter. Determining what science is “valid” and what’s not has enormous repercussions for society. To illustrate his point, he goes on to review the issue of hormone-disrupting chemicals and their reproductive effects.

Some scientists have sounded the alarm, saying our reproductive capability is so severely impacted by toxic environmental factors that by 2045, all couples will require fertility treatment if they want to conceive. Sperm counts have dropped precipitously ever since the 1970s, and the trend is showing no signs of leveling off.

If true, this signals a true existential emergency, but as has become the norm over the past couple of years, the declining sperm count issue is now being reframed as a racist, “far right” issue. This in and of itself ought to signal that we’ve left science and moved into ideology, but no.

The narrative we’re asked to swallow is the complete opposite: That the scientists who made these discoveries used sham science to fit an ideological narrative rooted in white supremacy. Meanwhile, “the science” offered by nonscientists says there’s no problem here, and that’s that.

Corbett cites a Quillette article by Geoffrey Kabat, “The Sperm Count Culture War,” published mid-June 2021, which states:8

“The latest entry in the sperm count debate comes from a Harvard-MIT research team led by philosophy professors Marion Boulicault and Sarah Richardson.

They recently published a paper in the journal Human Fertility entitled ‘The Future of Sperm Variability for Understanding Global Sperm Count Trends.’ They also published an article in Slate9 summarizing their findings for a lay audience.

While the scientific paper is dense and difficult to navigate, the Slate article gets straight to the point with its title: ‘The Doomsday Sperm Theory Embraced by the Far Right.’

Its subheading elaborates: ‘The idea that male fertility is on the decline is an old myth dressed up as science.’ The authors tell us why they believe the accepted science on declining sperm counts should be rejected:

‘The human species is in grave reproductive danger, according to recent headlines. Some scientists say that sperm counts in men around the world have been plummeting, with Western men approaching total infertility by 2045.

Far-right ‘Great Replacement’ theorists, who fear that people of color are ‘replacing’ the white population, have taken up the research with gusto …

The narrative that white, Western men are in danger of emasculation and disappearance has deep roots in white nationalist discourse. It is tied to a nostalgic cultural myth of a past in which white men held unchallenged power.'”

Human Extinction Concerns Dismissed as Fearmongering

As noted by Kabat, the two philosophy professors “all but ignore the science to focus on what they believe is more important — the ideological framing of the issue in socio-cultural discourse.”

Interestingly, the paper they published is in response to “what is widely considered to be the most definitive research on science of sperm count decline,” Kabat notes, and perhaps that’s why they did it. It’s real science being debunked as “science driven by ideology,” by nonscientists who have an ideological agenda but pretend not to!

Here we have two philosophy professors trying to debunk 50 years of research by some of the most respected researchers in the field — by declaring the whole investigation racist, misogynistic and “overtly white supremacist.” They roundly dismiss concerns about impending global infertility and thus human extinction, stating:10

“What these anxieties have in common with the threat of sperm count decline is the premise that, in an environmentally clean and appropriately-gendered social past, there existed an optimal and natural manifestation of masculinity …

It is all too easy for scientific institutions, with majority-white researchers, to center white people and further these myths, which circulate often unconsciously … The recent sperm count decline research demonstrates how racist, sexist, and Eurocentric ideas can get embedded in the categories that scientists use to analyze data.”

In their paper, Boulicault et.al. offer their own hypothesis to explain and dismiss the decline in sperm count as a natural variation that has no bearing on fertility or health — none of which is accurate or true.

Expertise Matters

The take-home message here is that philosophy professors can depose (or at least attempt to depose) a team of reproductive health scientists who have spent their entire careers looking at this issue, simply by interjecting their own ideology into the mix, all while accusing the actual scientists of ideology-based hype. And here’s how mainstream media covered this clearly insufficient debunking attempt:11

  • Yahoo! News — “Freaking Out About Declining Sperm Count? Don’t, Harvard Researchers Say.”
  • The Telegraph — “Threat of Human Extinction from Falling Sperm Counts Greatly Exaggerated.”
  • Haaretz — “Spermaggedon in the West? Relax, Harvard Has Good News for You.”
  • Vox — “Sperm Counts Are Falling. This Isn’t the Reproductive Apocalypse — Yet.”

Kabat writes:12

“None of the news stories … so much as remarked on the inflammatory rhetoric of the Boulicault paper, which will appear to the fair-minded reader as an activist manifesto masquerading as a scientific hypothesis. Even the New York Times fumbled this. It provided a useful discussion of some of the questions raised by the Harvard study and presented different points of view …

But it treated the study as a serious critique of the sperm count controversy, giving no indication of Boulicault and colleagues’ ideological framing of the issue or that their alternative hypothesis has little to do with science …

It is difficult to explain the deference paid to the Harvard paper by various commentators. Perhaps we are in a time in which even trained scientists are reluctant to call out an uninformed but ideologically fashionable treatment of a high-profile issue.”

Are You Seeing How This Applies to the COVID Narrative?

These stories tell us a lot about our current situation, where ideological gatekeepers are commanding us to “look here, not there.” Actual, reproducible science by bonafide scientists is being dismissed as “ideology masquerading as science,” while fake or flimsy science is being held up as the only science worthy of that designation.

If you chose to trust science that counters the technocratic transhumanist Deep State narrative, well, then you’re labeled a racist, a misogynist, a white supremacist, a domestic terrorist or some other unpleasant and derogatory term, the only purpose of which is to shame and shut you up.

As noted by Corbett, when politicians and health authorities urge us to “trust the science,” they are referring to select agency-branded science, meaning science that has the stamp of approval of the U.S. Food and Drug Administration, the U.S. Centers for Disease Control and Prevention or the World Health Organization, for example.

The assumption we’re supposed to accept is that these organizations aren’t tainted by the kind of corruption we’re now told exists within the EPA — financially driven corruption that sidelines actual scientists, even within those organizations, that may have serious concerns. But regulatory capture is a longstanding problem, and there’s no evidence to suggest it’s been rooted out of the agencies we’re now told to trust without question. As noted by Corbett:

“As ‘The Science’ more and more dictates whether you can step outside your own home, or what kind of experimental interventions you are forced or coerced into putting into your body against your will, I hope you understand that the stakes have been raised to the point where this is not some mere philosophical concern. This is the heart of the biosecurity state that we are being steeped in.”

Sources and References

September 26, 2021 Posted by | Civil Liberties, Corruption, Mainstream Media, Warmongering, Science and Pseudo-Science, Timeless or most popular, Video | | Leave a comment
