Fauci and the Great AIDS Swindle
A Partial Review of Robert F. Kennedy, Jr., THE REAL ANTHONY FAUCI

BY LAURENT GUYÉNOT • UNZ REVIEW • NOVEMBER 27, 2021
Robert F. Kennedy, Jr.’s new book, The Real Anthony Fauci: Bill Gates, Big Pharma, and the Global War on Democracy and Public Health is not the book of a politician seeking attention. It is the book of a man determined to stake his own life in the resistance against the unfolding bio-terrorist assault on humankind by governments captive of the pharmaceutical industry. He is calling for mass insurrection, and his last word is: “I’ll see you on the barricades.” The book begins like this:
I wrote this book to help Americans—and citizens across the globe—understand the historical underpinnings of the bewildering cataclysm that began in 2020. In that single annus horribilis, liberal democracy effectively collapsed worldwide. The very governmental health regulators, social media eminences, and media companies that idealistic populations relied upon as champions of freedom, health, democracy, civil rights, and evidence-based public policy seemed to collectively pivot in a lockstep assault against free speech and personal freedoms. Suddenly, those trusted institutions seemed to be acting in concert to generate fear, promote obedience, discourage critical thinking, and herd seven billion people to march to a single tune, culminating in mass public health experiments with a novel, shoddily tested and improperly licensed technology so risky that manufacturers refused to produce it unless every government on Earth shielded them from liability. … Conscientious objectors who resisted these unwanted, experimental, zero-liability medical interventions faced orchestrated gaslighting, marginalization, and scapegoating. American lives and livelihoods were shattered by a bewildering array of draconian diktats imposed without legislative approval or judicial review, risk assessment, or scientific citation. So-called Emergency Orders closed our businesses, schools and churches, made unprecedented intrusions into privacy, and disrupted our most treasured social and family relationships.
 Kennedy is not a newcomer to this frightening dystopia. “My 40-year career as an environmental and public health advocate,” he writes, “gave me a unique understanding of the corrupting mechanisms of ‘regulatory capture,’ the process by which the regulator becomes beholden to the industry it’s meant to regulate.” From the time he entered the vaccine debate in 2005, he realized that “the pervasive web of deep financial entanglements between Pharma and the government health agencies had put regulatory capture on steroids.” The Centers for Disease Control and Prevention (CDC), for example, owns 57 vaccine patents and spent $4.9 billion in 2019 buying and distributing vaccines. The Food and Drug Administration (FDA) receives 45 percent of its budget from the pharmaceutical industry. The National Institutes of Health (NIH), with its $42 billion budget, owns hundreds of vaccine patents and often profits from the sale of products it supposedly regulates. High-level officials receive yearly emoluments of up to $150,000 in royalty payments on products that they help develop and then usher through the approval process.
Dr. Anthony Fauci, “America’s reigning health commissar,” stands at the summit of that Leviathan. From 1968, he occupied various posts at the National Institute of Allergy and Infectious Diseases (NIAID), a sub-agency of NIH, of which he became director in 1984. With a $417,608 annual salary, he is the highest paid of all federal employees, including the President. “His experiences surviving 50 years as the panjandrum of a key federal bureaucracy, having advised six Presidents, the Pentagon, intelligence agencies, foreign governments, and the WHO, seasoned him exquisitely for a crisis that would allow him to wield power enjoyed by few rulers and no doctor in history.” He has nurtured a complex web of financial entanglements that has transformed the NIH into a subsidiary of Big Pharma. Reaching into the deep pockets of the Clinton and Gates Foundations, he has used his $6 billion annual budget to achieve dominance and control over many agencies, including the World Health Organization (WHO). He can make and break careers, enrich or punish university research centers, and dictate the outcome of scientific research across the globe, consistently prioritizing pharmaceutical industry profits over public health.
Kennedy’s book documents Fauci’s “two-decade strategy of promoting false pandemics as a scheme for promoting novel vaccines,” as well as “his actions to conceal widespread contamination in blood and vaccines, his destructive vendettas against scientists who challenge the Pharma paradigm, [and] his deliberate sabotaging of patent-expired remedies against infectious diseases.”
But of course, Kennedy’s book is not about a man: it is about an irremediably corrupt and predatory system created in the U.S. and exported worldwide. Ultimately, however, the system is built and run by humans, and focusing on its most emblematic representative shows its very soul.
Kennedy’s book puts the current crisis in historical perspective. But it doesn’t tell the story chronologically. It starts with a very long first chapter on the current Covid crisis—a book by itself—, then goes back, from chapter 3, to the 1980s and the search for the AIDS vaccine, the template for today’s pharmaceutical coup. In this review, I will focus on the AIDS episode, because it is the least familiar part of a history covering fifty years, and it helps make sense of what is happening today. It is an incredible story, that I would have had difficulty believing just three years ago, but that our current enslavement now makes utterly credible.
The thirty-year decampment of journalistic scrutiny means that there is still no coherent public narrative chronicling Dr. Fauci’s futile quest for his “inevitable” AIDS vaccine, much less accountability. Industry and government scientists have instead shrouded the scandalous saga in secrecy, subterfuge, and prevarication, obscuring a thousand calamities and a sea of tears deserving its own book. Every meager effort to research the debacle—on Google, PubMed, news sites, and published clinical trial data—yields only shocking new atrocities—a grim, repetitive parade of horribles: heartbreaking tragedies, entrenched institutional arrogance and racism, broken promises, vast expenditures of squandered treasure, and the recurring chicanery of Anthony Fauci, Bob Gallo, and Bill Gates.
Kennedy deserves praise and gratitude for his courage to bring this controversy out into the open, in a clear and well-documented exposé. His book is destined to become a landmark in the struggle for Life and Truth—and in the Kennedy heroic saga. This article reflects only a fraction of what can be learned from its 480 pages packed with data and references. Since page numbers in the kindle edition (recommended for its thousand hyperlinks) differ from those in the printing book, I have dispensed with them.
In the Beginning
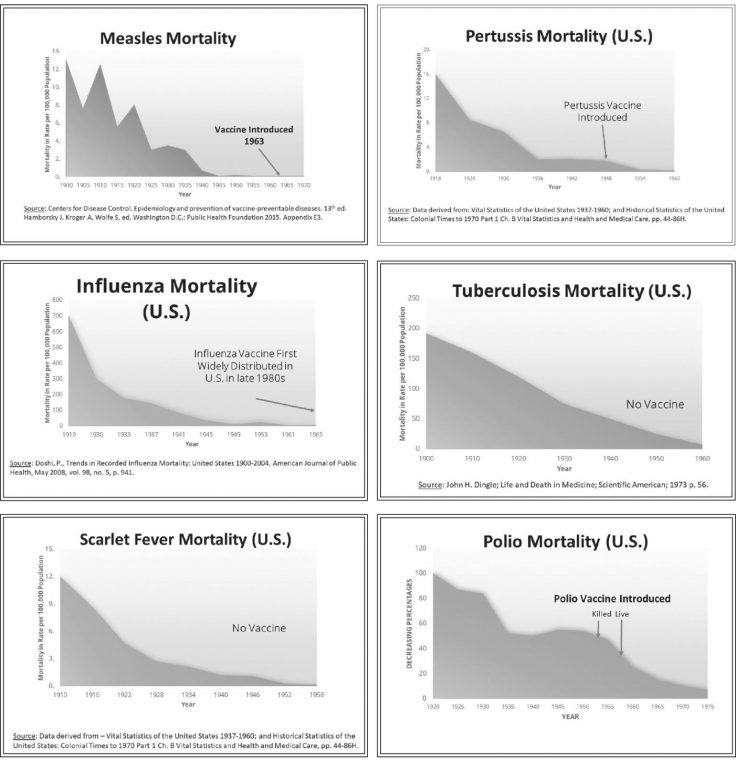
In the first lines of his 2014 book Thimerosal: Let the Science Speak (documenting an astonishing 1,135 percent higher rate of autism among children who took hepatitis B vaccines), Kennedy prudently claimed to be “pro-vaccine” and to “believe that vaccines have saves the lives of hundreds of millions of humans over the past century.” Kennedy makes no such disclaimer in his new book. Rather, he sides with the critics of the popular dogma that vaccines played the key role in abolishing mortal contagious illnesses in North America and Europe, citing a 2000 study by CDC and Johns Hopkins scientists that concluded: “nearly 90 percent of the decline in infectious disease mortality among US children occurred before 1940, when few antibiotics or vaccines were available.” The main causes of the dramatic 74 percent decline in infectious disease mortality in the first half of the twentieth century were improved nutrition and sanitation.
From Kennedy, The Real Anthony Fauci, 2021
This revisionist but objective perspective explains why Fauci and Gates’s obsession with vaccine-preventable diseases has caused negative overall impacts on public health in Africa and Asia, by proportionally reducing assistance streams for nutrition, clean water, transportation, hygiene, and economic development. Gates and Fauci have actually hijacked WHO’s public health agenda away from the projects that are proven to curb infectious diseases, and diverted international aid to wedge open emerging markets for their multinational partners.
To understand their craze for vaccines, Kennedy reminds us of the pioneering influence of the Rockefeller Foundation. In 1911, after the Supreme Court ruled that Standard Oil constituted an “unreasonable monopoly” and splintered it into thirty-four companies, John D. Rockefeller inaugurated what Bill Gates would later call “philanthrocapitalism.” He provided large grants to scientists for synthesizing and patenting chemical versions of the molecules identified in traditional medicine. The Foundation provided almost half of the initial budget for the League of Nations’ Health Organization (LNHO) in 1922, and populated its ranks with its veterans and favorites. It imbued the League with its technocratic philosophy of health, inherited by its successor body, the WHO, in 1948.
The Rockefeller Foundation launched a “public-private partnership” with pharmaceutical companies called the International Health Commission, which first set about inoculating the hapless populations of the colonized tropics with a yellow fever jab. By the time John D. Rockefeller, Jr. disbanded it in 1951, the International Health Commission had spent billions of dollars on tropical disease campaigns in almost 100 countries and colonies. These projects had a hidden agenda, according to a 2017 report, U.S. Philanthrocapitalism and the Global Health Agenda: they allowed the Rockefeller family to open developing world markets for oil, mining, banking and other profitable trades, including pharmaceutical profits that grew tremendously when, in the 1970s:
a wave of new technologies, including PCR and super powerful electron microscopes, had opened windows on teeming new worlds containing millions of species of previously unknown viruses to scientists. … The lure of fame and fortune ignited a chaotic revolution in virology as ambitious young PhDs scrambled to inculpate newly discovered microbes as the cause of old malignancies. … Under this new rubric, every theoretical breakthrough, every find, became potentially the basis for a new generation of drugs.
By the mid-1970s, the CDC was seeking to justify its existence by tracking small outbreaks of rabies. “Drumming up public fear of periodic pandemics was a natural way for NIAID and CDC bureaucrats to keep their agencies relevant. Dr. Fauci’s immediate boss and predecessor as NIAID Director, Richard M. Krause, helped pioneer this new strategy in 1976.” That year the fake swine flu epidemic was concocted. The experimental vaccine was so fraught with problems that the Health and Human Services (HHS) discontinued the jab after vaccinating 49 million Americans. According to news accounts, the incidence of flu was seven times greater among the vaccinated than the unvaccinated. Furthermore, the vaccine caused some 500 cases of the degenerative nerve disease Guillain-Barré Syndrome, 32 deaths, more than 400 paralyzations, and as many as 4,000 other injuries. Injured plaintiffs filed 1,604 lawsuits. By April 1985, the government had paid out $83,233,714 and spent tens of millions of dollars adjudicating and processing those claims.
Another scandal broke in 1983, when a NIH-funded UCLA study found that the DTP vaccine developed by Wyeth—now Pfizer—was killing or causing severe brain injury, including seizures and death, in one in every 300 vaccinated children. While protecting children against diphtheria, tetanus, and pertussis, the DTP vaccine had ruined their immune systems, making them vulnerable to a wide range of other deadly infections.
The resultant lawsuits caused the collapse of insurance markets for vaccines and threatened to bankrupt the industry. Wyeth claimed to be losing $20 in downstream liability for every dollar it earned on vaccine sales, and induced Congress to pass in 1986 the National Childhood Vaccine Injury Act, which shielded vaccine makers from liability. (This incentive for unrestricted greed was strengthened in 2005 when George W. Bush signed into law the Public Readiness and Emergency Preparedness Act).
AIDS and AZT
In 1984, when Fauci became director of NIAID, the AIDS crisis was spiraling out of control. That proved “a redemptive juncture for NIAID and the launch pad for Dr. Fauci’s stellar rise.” In an April 1984 press conference, NIH scientist Robert Gallo linked AIDS to the virus that was soon to be named HIV. Dr. Fauci then moved aggressively to claim jurisdiction for his agency over the National Cancer Institute (NCI), another sub-agency of NIH. “As the nation’s newly appointed AIDS czar, Dr. Fauci was now a gatekeeper for almost all AIDS research … parroting NCI’s vows to cure cancer, Dr. Fauci promised Congress that he would quickly produce drugs and vaccines to banish AIDS.”
At the same time, he was deliberately spreading contagion terror, warning in a 1983 fear-mongering article that “the scope of the syndrome may be enormous”, since “routine close contact, as within a family household, can spread the disease”—despite the fact that AIDS was almost exclusive to intravenous drug users and male homosexuals. A year later, Fauci was forced to concede that health officials had never detected a case of the disease spread through “casual contact.” Nevertheless, Dr. Fauci’s systematic response was “to amplify the widespread panic of dreaded pestilence that would naturally magnify his power, elevate his profile, and expand his influence. Amplifying terror of infectious disease was already an ingrained knee-jerk institutional response at NIAID.”
Having seized control over AIDS research, Fauci captured the new flood of congressional AIDS appropriations flowing to NIH through the lobbying of a newly organized gay community. By 1990, NIAID’s annual AIDS budget reached $3 billion. In the ensuing decades, the federal government spent over half a trillion dollars in the quest for an elusive vaccine that never materialized. Dr. Fauci pumped up taxpayers’ money into nearly 100 vaccine candidates, with no other result than “massive transfers of public lucre to Dr. Fauci’s Pharma partners,” and a sea of tears for millions of unfortunate human guinea pigs.
NIAID’s lack of in-house drug development capacity meant that Fauci had to farm out drug research to a network of so-called “principal investigators” (PIs), academic physicians and researchers controlled by pharmaceutical companies and acting as liaisons, recruiters and spokespersons.
PIs are pharmaceutical industry surrogates who play key roles promoting the pharmaceutical paradigm and functioning as high priests of all its orthodoxies, which they proselytize with missionary zeal. They use their seats on medical boards and chairmanships of university departments to propagate dogma and root out heresy. … They are the credentialed and trusted medical experts who prognosticate on television networks—now helplessly reliant on pharmaceutical ad revenue—to push out Pharma content.
Dr. Fauci’s choice to transfer virtually all of NIAID’s budget to pharmaceutical PIs for drug development was an abdication of the agency’s duty to find the source and eliminate the explosive epidemics of allergic and autoimmune disease that began under his watch around 1989. … NIAID money effectively became a giant subsidy to the blossoming pharmaceutical industry to incubate a pipeline of profitable new drugs targeted to treat the symptoms of those very diseases.
In the late 80s and early 90s, PIs received every year between 4 and 5 billions of dollars from NIH’s budget. But “legalized bribes” from drug companies and royalty payments from drug products often dwarfed their government funding. Celia Farber’s 2006 Harper’s article, “Out of Control: AIDS and the Destruction of Medical Science,” laid bare the culture of squalor, corruption, and vendetta at Fauci’s AIDS Branch, the Division of Acquired Immunodeficiency Syndrome (DAIDS).
Despite his miserable track record at reducing illness over the previous decade, Fauci persuaded President Bill Clinton, in May 1997, to set a new national goal for science. In a speech delivered at Morgan State University, Clinton—perhaps not without cryptic irony— imitated Kennedy’s May 25, 1961 moonshot promise, saying, “Today let us commit ourselves to developing an AIDS vaccine within the next decade.”
A year later, Bill Gates, who had just founded his International Aids Vaccine Initiative (IAVI), sealed a deal with Fauci. “Over the next two decades, that partnership would metastasize to include pharmaceutical companies, military and intelligence planners, and international health agencies all collaborating to promote weaponized pandemics and vaccines and a new brand of corporate imperialism rooted in the ideology of biosecurity.” The story of Gates’ involvement in the vaccine business, of his murderous experiments in Africa and India, and of his rise as the unofficial top sponsor of the WHO (ordering in 2011: “All 193 member states, you must make vaccines a central focus of your health systems”), is told in chapters 9 and 10 of Kennedy’s book.
When Dr. Fauci became head of NIAID, azidothymidine, known as AZT, was the only candidate as an AIDS remedy. AZT is a “DNA chain terminator,” randomly destroying DNA synthesis in reproducing cells. It had been developed in 1964 for cancer, but abandoned as too toxic even for short-term therapy. It was deemed so worthless that it was not even patented. In 1985, Samuel Broder, head of the National Cancer Institute (NCI), claimed having found that AZT killed HIV in test tubes. The British company Burroughs Wellcome then patented it as an AIDS remedy. “Recognizing financial opportunity in the desperate terror of young AIDS patients facing certain death, the drug company set the price at up to $10,000/year per patient—making AZT one of the most expensive drugs in pharmaceutical history. Since Burroughs Wellcome could manufacture AZT for pennies per dose, the company anticipated a bonanza.”
Fauci gave Burroughs Wellcome a monopoly control over the government’s HIV response. But all did not go smoothly. “AZT’s horrendous toxicity hobbled researchers struggling to design study protocols that would make it appear either safe or effective.” Another problem is that community-based doctors were achieving promising results with cheap, off-label therapeutic drugs. Dr. Fauci refused to test any of those repurposed drugs that had no Pharma patrons. When he did put on trial AL721, an antiviral that was far less toxic than AZT, he rigged the studies to fail, and abruptly cancelled Phase 2.
Meanwhile, he accelerated testing of AZT, skipping animal testing and allowing Burroughs Wellcome to proceed directly to human trials. In March 1987, Fauci’s team declared the human trials a success after only four months, and Fauci congratulated himself in front of the press. However, when in July 1987, the official report of Burroughs Wellcome’s Phase 2 trial was published, European scientists complained that raw data showed no benefit in reducing symptoms. FDA conducted its own investigation eighteen months later, but kept its results secret, until investigative journalist John Lauritsen obtained some of them by using the Freedom of Information Act; the documents showed that the Fauci/Burroughs Wellcome research teams had engaged in widespread data tampering. More than half of the AZT patients suffered adverse reactions so deadly that they needed multiple blood transfusions just to keep them alive. Nevertheless, Fauci kept on lying himself to the top of the world, with little scrutiny from mainstream media.
A key and enduring legacy of the AZT battle was Dr. Fauci’s emergence as the alpha wolf of HHS [Health and Human Services]. His enormous budget, and multiplying contacts on Capitol Hill, the White House, and the medical industry, thereafter allowed him to influence or ignore a succession of politically appointed HHS directors and to bully, manipulate, and dominate HHS’s other sister agencies, most notably FDA.
AZT was not the only subject of interest to Fauci. By June 2003, NIH was running 10,906 clinical trials on new antiviral concoctions in some four hundred clinical trials in ninety countries. Some of those trials seemed pulled out of Dickens’ worst nightmares. The Alliance for Human Research Protection (AHRP), a medical industry watchdog organization, has documented that between 1985 and 2005, NIAID conscripted at least 532 infants and children from foster care in New York City as subjects of clinical trials testing experimental AIDS drugs and vaccines. AHRP’s investigation revealed that many of those children were perfectly healthy and may not even have been HIV-infected. Yet 80 of them died. In 2004, journalist Liam Scheff chronicled Dr. Fauci’s secretive experiments on foster children at Incarnation Children’s Center (ICC) in New York City and numerous sister facilities between 1988 and 2002. These disclosures, comments Kennedy, beg many questions:
From what moral wilderness did the monsters who devised and condoned these experiments descend upon our idealistic country? How have they lately come to exercise such tyrannical power over our citizens? What sort of nation are we if we allow them to continue? Most trenchantly, does it not make sense that the malevolent minds, the elastic ethics, the appalling judgment, the arrogance, and savagery that sanctioned the barbaric brutalization of children at the Incarceration Convent House, and the torture of animals for industry profit, could also concoct a moral justification for suppressing lifesaving remedies and prolonging a deadly epidemic? Could these same dark alchemists justify a strategy of prioritizing their $48 billion vaccine project ahead of public health and human life? Did similar hubris—that deadly human impulse to play God—pave the lethal path to Wuhan and fuel the reckless decision to hack the codes of Creation and fabricate diabolical new forms of life—pandemic superbugs—in a ramshackle laboratory with scientists linked to the Chinese military?
Indeed, Kennedy shows in his final chapter, “Germ Games,” that Fauci’s investments in so-called “gain of function” experiments to engineer pandemic superbugs raise “the ironic possibility that Dr. Fauci may have played a role in triggering the global contagion that two US presidents entrusted him to manage.”
Africa is “the venue of choice for companies seeking cooperative government officials, compliant populations, the lowest per-patient enrollment costs, and lax oversight by media and regulatory officials.” In the early 1990s, African dictators rolled out the red carpet for Pharma, cashing in on the lucrative business of farming out their citizens for the booming clinical trial business. And on January 29, 2003, President George W. Bush announced at his State of the Union speech his Emergency Plan for AIDS Relief (PEPFAR), Fauci’s new swindle:
On the continent of Africa, nearly 30 million people have the AIDS virus. … Yet across that continent, only 50,000 AIDS victims—only 50,000—are receiving the medicine they need. … I ask the Congress to commit $15 billion over the next five years, including nearly $10 billion in new money, to turn the tide against AIDS in the most afflicted nations of Africa and the Caribbean.
Does HIV Cause AIDS?
Kennedy’s chapter 5, “The HIV Heresies,” opens up with the following note:
I hesitated to include this chapter because any questioning of the orthodoxy that HIV is the sole cause of AIDS remains an unforgivable—even dangerous—heresy among our reigning medical cartel and its media allies. But one cannot write a complete book about Tony Fauci without touching on the abiding—and fascinating—scientific controversy over what he characterizes as his “greatest accomplishment” and his “life’s work.”
The controversy illustrates how pharmaceutical industries and health agencies, acting in concert, engineer consensus on incomplete or fraudulent theories, and ruthlessly suppress dissent from even the most gifted recognized scientists. “From the outset,” Kennedy insists, “I want to make clear that I take no position on the relationship between HIV and AIDS.” However, there seems little doubt that his basic point is correct:
During the thirty-six years since Dr. Fauci and his colleague, Dr. Robert Gallo, first claimed that HIV is the sole cause of AIDS, no one has been able to point to a study that demonstrates their hypothesis using accepted scientific proofs. … Even today, incoherence, knowledge gaps, contradictions, and inconsistencies continue to bedevil the official dogma.
The success story of the HIV-AIDS dogma shows “many of the tactics Dr. Fauci has pioneered to dodge debate—bedazzling and bamboozling the press into ignoring legitimate inquiry of the credo, and undermining, gaslighting, punishing, bullying, intimidating, marginalizing, vilifying, and muzzling critics.” One of Fauci’s victims was Dr. Peter Duesberg, who in 1987 was still recognized as the world’s most accomplished retrovirologist. Duesberg argues that HIV does not cause AIDS but is essentially a “free rider” common to high-risk populations who suffer immune suppression due to environmental exposures. HIV, he says, is a harmless passenger virus that has almost certainly coexisted in humans for thousands of generations without causing diseases. While HIV may be sexually transmittable, Duesberg claims, AIDS is not.
Duesberg published his views in a groundbreaking 1987 article, then in a 724-page book, Inventing the AIDS Virus. Kennedy finds that “Duesberg’s rationales appear so clean, so elegantly crafted, and so compelling that, in reading them, it seems impossible that the entire [orthodox] hypothesis did not instantly collapse under the smothering weight of relentless logic.” But Fauci and Gallo never attempted to reply to Duesberg. Blaming AIDS on a virus was the gambit that had allowed NIAID to claim the jurisdiction—and cash flow—away from NCI, and Duesberg was severely punished for endangering this.
Dr. Fauci summoned the entire upper clergy of his HIV orthodoxy—and all of its lower acolytes and altar boys—to unleash a storm of fierce retribution on the Berkeley virologist and his followers. … the AIDS establishment, down to its lowliest doctor, publicly reviled Duesberg, NIH defunded him, and academia ostracized and exiled the brilliant Berkeley professor. The scientific press all but banished him. He became radioactive.
Surprisingly, however, Dr. Luc Montagnier, whose discovery of HIV Gallo had in fact stolen—as he admitted in 1991 after years of litigation—, became Duesberg’s most embarrassing convert, declaring at the San Francisco International AIDS Conference in June 1990, that “the HIV virus is harmless and passive, a benign virus.” He added that, according to his findings, HIV becomes dangerous only in the presence of a second organism, a bacteria-like bug called a mycoplasma. Montagnier, in fact, had never claimed that HIV was the only factor in AIDS, and grew increasingly skeptical of that theory. His repeated questioning of the establishment paradigm signaled the beginning of his vilification, for which his Nobel Prize hardly protected him.
Gallo’s “proof” that the cause of AIDS was a virus—as opposed to toxic exposures— provided the critical foundation stone of Dr. Fauci’s career. It allowed Fauci to capture the AIDS program and launch NIAID as the leading federal partner of the drug-production industry. This explains why Fauci never funded any study to explore whether HIV actually caused AIDS, and took vigorous preemptive action against any such study.
Kennedy cites other dissenting voices on AIDS epidemiology. Dr. Shyh-Ching Lo, the Chief Researcher in charge of AIDS programs for the Armed Forces Institute of Pathology, was shocked by Anthony Fauci’s unconventional claim that antibodies, normally the sign of a robust immune response, should, with HIV, be the signal for impending death. Since “HIV tests” do not in reality detect the elusive virus but only antibodies, there seems to be an Orwellian inversion at work. Kennedy also quotes Dr. David Rasnick, a PhD biochemist who has worked for thirty years in the pharmaceutical biotech field:
Fauci’s fundamental conundrum is that he has told everybody to diagnose AIDS based on the presence of HIV antibodies. With every other disease, the presence of antibodies is the signal that the patient has vanquished the disease. With AIDS, Fauci and Gallo, and now Gates, claim it’s a sign you’re about to die. Think about it; if the objective of an AIDS vaccine is to stimulate antibody production, then success would mean that every vaccinated person would also have an AIDS diagnosis. I mean, this is fodder for a comedy bit. It’s like someone gave the Three Stooges an annual billion-dollar budget!
The nature of AIDS—a syndrome, not a disease—is itself subject to questions, since it was made to encompass a galaxy of some thirty separate well-known diseases, all of which occur in individuals who have no HIV infection. “In the hands of Dr. Fauci’s opportunistic PIs, AIDS became an amorphous malady subject to ever-changing definitions, encompassing a multitude of old diseases in hosts who test positive for HIV.” Nobel Laureate Kary Mullis, the inventor of the PCR tests, pointed out that the PCR was capable of finding HIV signals in large segments of the population who suffered no AIDS symptoms. On the other hand, AIDS commonly occurs in people who test HIV negative, as Geoffrey Cowley documented in a 1992 Newsweek article, followed by Steve Heimoff in the Los Angeles Times.
These very inconsistencies were not a problem for Fauci and his standing army of pharmaceutical mercenaries. Quite the opposite: they opened up Africa’s AIDS bonanza. Researchers funded by Fauci, using PCR tests and murky statistical models, declared that up to 30 million Africans were suffering from AIDS, nearly half the adult population in some nations. While in Western nations, AIDS continued to be a disease of drug addicts and homosexual “poppers” (consumers of the amyl nitrite vasodilator providing relaxation of the anal musculature, packaged into the “popper” container patented by Burroughs Wellcome and advertised in the gay press throughout the AIDS epidemic), mysteriously, in Africa, 59 percent of AIDS cases were women, and 85 percent were heterosexuals.
But in the early 1990s, the character of AIDS changed dramatically with the proliferation of AZT. As they started to give AZT to people who were in fact not even sick but simply positive on the HIV test, AIDS started to look increasingly like AZT poisoning. And the death rate climbed precipitously. According to the Duesbergians, the vast majority of “AIDS deaths” after 1987 were actually caused by AZT. The medication that Dr. Fauci was prescribing to treat AIDS patients actually did what the virus could not: it caused AIDS itself. In 1988, the average survival time for patients taking AZT was four months. In 1997, recognizing the lethal effect of AZT, health officials lowered the dose; the average lifespan of AZT patients then rose to twenty-four months. According to Dr. Claus Köhnlein, a German oncologist, “We virtually killed a whole generation of AIDS patients without even noticing it because the symptoms of the AZT intoxication were almost indistinguishable from AIDS.”
Conclusion
In July 2019, Dr. Fauci made a surprise announcement: he finally had a working HIV vaccine, the potential “nail in the coffin” for the epidemic. He conceded that his new vaccine didn’t prevent transmission of AIDS, but predicted that those who took the jab would find that when they did get AIDS, the symptoms would be much reduced. Kennedy comments:
So confident was Dr. Fauci of the media’s slavish credulity that he assumed, correctly, that he’d never need to answer the many questions raised by this feverish gibberish. That entire odd proposition received zero critical press commentary. His success at slapping lipstick on this donkey and selling it to the world as a Thoroughbred may have emboldened his ruse—a year later—of placing similar cosmetics on the COVID vaccines that, likewise, neither prevent disease nor preclude transmission.
By 2019, the AIDS rope started to wear out. Who still cared about AIDS anyway? The “Covid-19 Pandemic” came as the perfect opportunity for a reset and an update in the pharmaceutical racket. As Winston Churchill reportedly said, “Never let a good crisis go to waste”. With complicit corporate media blacking out the scandalous track record of his white-coat mafia, Fauci emerged, again, as the good doctor, the savior.
“Is it fair to blame Dr. Fauci for a crisis that, of course, has many authors?” asks Kennedy. To some extent, it is.
Under Dr. Fauci’s leadership, the allergic, autoimmune, and chronic illnesses which Congress specifically charged NIAID to investigate and prevent, have mushroomed to afflict 54 percent of children, up from 12.8 percent when he took over NIAID in 1984. Dr. Fauci has offered no explanation as to why allergic diseases like asthma, eczema, food allergies, allergic rhinitis, and anaphylaxis suddenly exploded beginning in 1989, five years after he came to power. On its website, NIAID boasts that autoimmune disease is one of the agency’s top priorities. Some 80 autoimmune diseases, including juvenile diabetes and rheumatoid arthritis, Graves’ disease, and Crohn’s disease, which were practically unknown prior to 1984, suddenly became epidemic under his watch. Autism, which many scientists now consider an autoimmune disease, exploded from between 2/10,000 and 4/10,000 Americans when Tony Fauci joined NIAID, to one in thirty-four today. Neurological diseases like ADD/ADHD, speech and sleep disorders, narcolepsy, facial tics, and Tourette’s syndrome have become commonplace in American children. The human, health, and economic costs of chronic disease dwarf the costs of all infectious diseases in the United States. By this decade’s end, obesity, diabetes, and pre-diabetes are on track to debilitate 85 percent of America’s citizens. America is among the ten most over-weight countries on Earth. The health impacts of these epidemics—which fall mainly on the young—eclipse even the most exaggerated health impacts of COVID-19.
Dr. Fauci has done nothing to advance NIAID’s core obligation of researching the causes of chronic allergic and autoimmune diseases that have mushroomed under his tenure. Instead, Fauci has “reshaped NIAID into the leading incubator for new pharmaceutical products, many of which, ironically, profit from the cascading chronic disease pandemic.” Instead of researching the causes of Americans’ failing health, Dr. Fauci funnels the bulk of his $6 billion budget to the research and development of new drugs and vaccines that are largely responsible for weakening our natural immunity. “Of late, he has played a central role in undermining public health and subverting democracy and constitutional governance around the globe and in transitioning our civil governance toward medical totalitarianism.”
I was reminded of Dr. Knock, the central character of Jules Romains’s famous novel Knock or the Triumph of Medicine, written in 1923. Dr. Knock is a shady medical doctor of dubious competence who professes that “health” is an obsolete and unscientific concept, and that all men are sick and need to be informed about it by their doctor. To advance his plan of converting a whole town into permanent patients, he enlists the help of the school teacher and of the pharmacist, who suddenly sees his clientele booming (watch unforgettable moments of Guy Lefranc’s 1951 film adaptation with Louis Jouvet here and here).

Louis Jouvet as Dr. Knock in 1951
To some extent, however, Fauci is himself the product of a civilizational orientation that could only, in the long run, lead to the tyrannical medical technocracy that is now trying to enslave us. Rather than a new Dr. Frankenstein, Fauci is our own monster coming back after us. Kennedy hints at this vast aspect of the question, pointing to the need for deep questioning. The way Americans and Westerners in general have come to view health care has been shaped by the philosophy of the Rockefeller Foundation: “a pill for an ill.” In the debate between the “miasma theory”—that emphasizes preventing disease by fortifying the immune system through nutrition and by reducing exposures to environmental toxins and stresses—versus the “germ theory”—which blames disease on microscopic pathogens—we have unambiguously opted for the latter. We have signed up for an approach to disease that requires to identify the culpable germ and tailor a poison to kill it. The choice was not forced upon us. We have surrendered responsibility for our health to medical experts and insurance brokers.
As Dr. Claus Köhnlein and Torsten Engelbrecht observe in their book Virus Mania (2007) quoted by Kennedy: “The idea that certain microbes—above all fungi, bacteria, and viruses—are our great opponents in battle, causing certain diseases that must be fought with special chemical bombs, has buried itself deep into the collective conscience.” It is a warlike paradigm, perfectly suited for manufacturing consent on the way to dictatorship. As Kennedy wrote in his preface to Dr. Joseph Mercola and Ronni Cummins, The Truth About Covid-19 (2021), “demagogues must weaponize fear to justify their demands for blind obedience.”
Government technocrats, billionaire oligarchs, Big Pharma, Big Data, Big Media, the high-finance robber barons, and the military industrial intelligence apparatus love pandemics for the same reasons they love wars and terrorist attacks. Catastrophic crises create opportunities of convenience to increase both power and wealth.
Laurent Guyénot, PhD, is the author of The Unspoken Kennedy Truth and of a film on the same subject.
What’s the Truth About Covid Vaccines and Heart Attacks?
By Will Jones • The Daily Sceptic • November 27, 2021
A further three football players collapsed during play this week, bringing new interest to the question of what might be the connection between this unusually high number of on-field medical emergencies and the Covid vaccines. Football pundit Trevor Sinclair got into hot water for raising the question on-air, while scientists argued that the disturbing trend is more likely to be a consequence of Covid itself than the vaccines.
Presumably something lies behind the recent rise, which according to some analysts has involved 21 sudden deaths (most heart-related) of FIFA players so far in 2021, compared to around 4.2 in an average year (with a standard deviation of 2.0). Assuming this isn’t a reporting phenomenon, this is an extraordinary spike and highly statistically significant.
The two major unusual factors this year are the presence of SARS-CoV-2 and the Covid vaccination programme. However, only two such deaths were reported in 2020, when Covid was also around, which would seem to lend weight to a vaccine explanation.
The vaccines are known to affect the heart and cardiovascular system in some cases, which is why blood clots and heart inflammation (e.g. myocarditis) are among the side-effects listed and why a number of countries have ceased using some of the vaccines in younger age groups. This means the idea that there could be a link between an unusual spate of heart-related emergencies and the vaccines shouldn’t be dismissed out of hand.
On the other hand, some studies have shown that the risk of developing myocarditis is substantially higher following SARS-CoV-2 infection than vaccination.
A number of scientists have pointed out that insofar as cardiovascular problems arise from the effect of the SARS-CoV-2 spike protein (and there seems to be some agreement that the spike protein is a large part of the causal story here) a bout of SARS-CoV-2 exposes the body to at least as much spike protein as a course of vaccination. Against that, those who suspect that the vaccines are playing a key role say that in fact most SARS-CoV-2 infections are not systemic but remain localised to the respiratory system, so have little impact on the cardiovascular system, whereas vaccination always allows the spike protein to have a systemic impact by gaining easy access to the bloodstream.
This matter would seem to merit much closer and more urgent attention than it appears to be receiving from regulators. It should be straightforward for those with access to the relevant data (most of which unfortunately is not publicly available) to analyse cardiovascular deaths according to vaccination status and prior infection status to see if there are patterns that may be a signal of concern.
An abstract appeared in the leading journal Circulation earlier this month which concluded: “The mRNA vaccines dramatically increase inflammation on the endothelium and T cell infiltration of cardiac muscle and may account for the observations of increased thrombosis, cardiomyopathy, and other vascular events following vaccination.” There was no study to accompany the abstract, however, and it has been heavily criticised by some specialists. Nonetheless, leading NHS Consultant Cardiologist Dr Aseem Malhotra stuck his neck out this week on GB News to reveal that a cardiology researcher colleague found similar results, but was not prepared to publish for fear of the repercussions for his or her career: “They aren’t going to publish their findings, they are concerned about losing research money.”
What are the wider trends in deaths?
Since July, ONS data shows there have been 20,823 excess deaths in England and Wales, with 11,531 involving Covid, leaving 9,292 excess deaths from other causes (if we make the conservative assumption that all Covid deaths are excess deaths).
Analysis of cause of death data for England shows that between July 4th and November 5th 2021 there have been 3,095 excess deaths involving heart failure, of which 854 could be put down to COVID-19, leaving 2,241 from other causes; 4,460 excess deaths involving ischaemic heart diseases, of which 1,413 could be Covid, leaving 3,047 from other causes; 1,307 excess deaths involving cerebrovascular diseases, of which 489 could be Covid, leaving 818 from other causes; and 8,109 excess deaths involving ‘other circulatory diseases’, of which 3,357 could be Covid, leaving 4,752 from other causes. These categories can overlap – a death certificate can mention more than one of them – so the figures can’t simply be added to get a grand total, and the underlying cause could be recorded as something different. Nonetheless, we are talking about thousands of additional cardiovascular deaths since the summer.
Despite this, ONS data shows that deaths where the underlying cause was cardiovascular have been below average in this period. At the same time, deaths where Covid is recorded as the underlying cause account for only a fraction of cardiovascular deaths in the period. So what was the underlying cause of all these excess deaths involving cardiovascular conditions that weren’t Covid either? A query to the ONS came back suggesting that it was down to the significant excess in deaths where the underlying cause was recorded as “symptoms, signs and ill-defined conditions”. In other words, we don’t really know. So according to official data, there have been thousands of excess deaths involving cardiovascular conditions in the past four months, but the underlying cause of many of those deaths is unknown. This would seem to warrant further investigation, and since the vaccines may be implicated, without delay.
31,014 Deaths 2,890,600 Injuries Following COVID Shots in European Database of Adverse Reactions
Young, Previously Healthy People Continue to Die

By Brian Shilhavy | Health Impact News | November 28, 2021
The European Union database of suspected drug reaction reports is EudraVigilance, and they are now reporting 31,014 fatalities, and 2,890,600 injuries, following COVID-19 injections.
A Health Impact News subscriber from Europe reminded us that this database maintained at EudraVigilance is only for countries in Europe who are part of the European Union (EU), which comprises 27 countries.
The total number of countries in Europe is much higher, almost twice as many, numbering around 50. (There are some differences of opinion as to which countries are technically part of Europe.)
So as high as these numbers are, they do NOT reflect all of Europe. The actual number in Europe who are reported dead or injured following COVID-19 shots would be much higher than what we are reporting here.
The EudraVigilance database reports that through November 20, 2021 there are 31,014 deaths and 2,890,600 injuries reported following injections of four experimental COVID-19 shots:
- COVID-19 MRNA VACCINE MODERNA (CX-024414)
- COVID-19 MRNA VACCINE PFIZER-BIONTECH
- COVID-19 VACCINE ASTRAZENECA (CHADOX1 NCOV-19)
- COVID-19 VACCINE JANSSEN (AD26.COV2.S)
From the total of injuries recorded, almost half of them (1,355,192) are serious injuries.
“Seriousness provides information on the suspected undesirable effect; it can be classified as ‘serious’ if it corresponds to a medical occurrence that results in death, is life-threatening, requires inpatient hospitalisation, results in another medically important condition, or prolongation of existing hospitalisation, results in persistent or significant disability or incapacity, or is a congenital anomaly/birth defect.”
A Health Impact News subscriber in Europe ran the reports for each of the four COVID-19 shots we are including here. It is a lot of work to tabulate each reaction with injuries and fatalities, since there is no place on the EudraVigilance system we have found that tabulates all the results.
Since we have started publishing this, others from Europe have also calculated the numbers and confirmed the totals.*
Here is the summary data through November 20, 2021.
Total reactions for the mRNA vaccine Tozinameran (code BNT162b2, Comirnaty) from BioNTech/ Pfizer: 14,526 deaths and 1,323,370 injuries to 20/11/2021
- 35,826 Blood and lymphatic system disorders incl. 207 deaths
- 40,230 Cardiac disorders incl. 2,128 deaths
- 376 Congenital, familial and genetic disorders incl. 33 deaths
- 17,995 Ear and labyrinth disorders incl. 10 deaths
- 1,217 Endocrine disorders incl. 5 deaths
- 20,443 Eye disorders incl. 32 deaths
- 110,658 Gastrointestinal disorders incl. 585 deaths
- 337,450 General disorders and administration site conditions incl. 4,118 deaths
- 1,502 Hepatobiliary disorders incl. 75 deaths
- 14,528 Immune system disorders incl. 76 deaths
- 53,108 Infections and infestations incl. 1561 deaths
- 20,222 Injury, poisoning and procedural complications incl. 240 deaths
- 33,067 Investigations incl. 451 deaths
- 9,103 Metabolism and nutrition disorders incl. 249 deaths
- 164,885 Musculoskeletal and connective tissue disorders incl. 179 deaths
- 1,163 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 114 deaths
- 225,032 Nervous system disorders incl. 1,556 deaths
- 1,851 Pregnancy, puerperium and perinatal conditions incl. 55 deaths
- 206 Product issues incl. 2 deaths
- 24,225 Psychiatric disorders incl. 174 deaths
- 4,667 Renal and urinary disorders incl. 224 deaths
- 43,949 Reproductive system and breast disorders incl. 5 deaths
- 57,013 Respiratory, thoracic and mediastinal disorders incl. 1,617 deaths
- 62,414 Skin and subcutaneous tissue disorders incl. 125 deaths
- 2,765 Social circumstances incl. 19 deaths
- 4,797 Surgical and medical procedures incl. 60 deaths
- 34,678 Vascular disorders incl. 626 deaths
Total reactions for the mRNA vaccine mRNA-1273 (CX-024414) from Moderna: 8,518 deaths and 390,163 injuries to 20/11/2021
- 8,227 Blood and lymphatic system disorders incl. 94 deaths
- 12,657 Cardiac disorders incl. 915 deaths
- 156 Congenital, familial and genetic disorders incl. 6 deaths
- 4,698 Ear and labyrinth disorders incl. 2 deaths
- 348 Endocrine disorders incl. 3 deaths
- 5,731 Eye disorders incl. 29 deaths
- 32,091 Gastrointestinal disorders incl. 326 deaths
- 104,720 General disorders and administration site conditions incl. 2,986 deaths
- 644 Hepatobiliary disorders incl. 40 deaths
- 3,820 Immune system disorders incl. 16 deaths
- 14,668 Infections and infestations incl. 782 deaths
- 8,158 Injury, poisoning and procedural complications incl. 162 deaths
- 7,117 Investigations incl. 143 deaths
- 3,703 Metabolism and nutrition disorders incl. 206 deaths
- 47,355 Musculoskeletal and connective tissue disorders incl. 174 deaths
- 531 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 67 deaths
- 66,320 Nervous system disorders incl. 823 deaths
- 722 Pregnancy, puerperium and perinatal conditions incl. 6 deaths
- 78 Product issues incl. 2 deaths
- 7,100 Psychiatric disorders incl. 142 deaths
- 2,277 Renal and urinary disorders incl. 164 deaths
- 8,061 Reproductive system and breast disorders incl. 7 deaths
- 17,235 Respiratory, thoracic and mediastinal disorders incl. 914 deaths
- 20,963 Skin and subcutaneous tissue disorders incl. 76 deaths
- 1,769 Social circumstances incl. 36 deaths
- 1,374 Surgical and medical procedures incl. 78 deaths
- 9,640 Vascular disorders incl. 319 deaths
Total reactions for the vaccine AZD1222/VAXZEVRIA (CHADOX1 NCOV-19) from Oxford/AstraZeneca: 6,145 deaths and 1,075,335 injuries to 20/11/2021
- 13,124 Blood and lymphatic system disorders incl. 248 deaths
- 19,128 Cardiac disorders incl. 696 deaths
- 195 Congenital familial and genetic disorders incl. 8 deaths
- 12,669 Ear and labyrinth disorders incl. 3 deaths
- 597 Endocrine disorders incl. 4 deaths
- 18,919 Eye disorders incl. 29 deaths
- 102,402 Gastrointestinal disorders incl. 312 deaths
- 283,288 General disorders and administration site conditions incl. 1,469 deaths
- 950 Hepatobiliary disorders incl. 60 deaths
- 4,834 Immune system disorders incl. 29 deaths
- 32,441 Infections and infestations incl. 413 deaths
- 12,358 Injury poisoning and procedural complications incl. 177 deaths
- 23,611 Investigations incl. 150 deaths
- 12,369 Metabolism and nutrition disorders incl. 91 deaths
- 159,668 Musculoskeletal and connective tissue disorders incl. 94 deaths
- 624 Neoplasms benign malignant and unspecified (incl cysts and polyps) incl. 22 deaths
- 221,536 Nervous system disorders incl. 958 deaths
- 521 Pregnancy puerperium and perinatal conditions incl. 12 deaths
- 188 Product issues incl. 1 death
- 19,933 Psychiatric disorders incl. 58 deaths
- 4,031 Renal and urinary disorders incl. 58 deaths
- 15,124 Reproductive system and breast disorders incl. 2 deaths
- 37,980 Respiratory thoracic and mediastinal disorders incl. 735 deaths
- 49,247 Skin and subcutaneous tissue disorders incl. 48 deaths
- 1,498 Social circumstances incl. 6 deaths
- 1,404 Surgical and medical procedures incl. 25 deaths
- 26,696 Vascular disorders incl. 437 deaths
Total reactions for the COVID-19 vaccine JANSSEN (AD26.COV2.S) from Johnson & Johnson: 1,825 deaths and 101,732 injuries to 20/11/2021
- 986 Blood and lymphatic system disorders incl. 40 deaths
- 1,837 Cardiac disorders incl. 155 deaths
- 35 Congenital, familial and genetic disorders
- 1,033 Ear and labyrinth disorders incl. 2 deaths
- 69 Endocrine disorders incl. 1 death
- 1,351 Eye disorders incl. 7 deaths
- 8,500 Gastrointestinal disorders incl. 75 deaths
- 26,871 General disorders and administration site conditions incl. 488 deaths
- 121 Hepatobiliary disorders incl. 11 deaths
- 445 Immune system disorders incl. 9 deaths
- 4,315 Infections and infestations incl. 143 deaths
- 920 Injury, poisoning and procedural complications incl. 18 deaths
- 4,766 Investigations incl. 103 deaths
- 625 Metabolism and nutrition disorders incl. 45 deaths
- 14,897 Musculoskeletal and connective tissue disorders incl. 43 deaths
- 54 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 3 deaths
- 20,097 Nervous system disorders incl. 197 deaths
- 41 Pregnancy, puerperium and perinatal conditions incl. 1 death
- 26 Product issues
- 1,407 Psychiatric disorders incl. 16 deaths
- 417 Renal and urinary disorders incl. 22 deaths
- 2,059 Reproductive system and breast disorders incl. 6 deaths
- 3,617 Respiratory, thoracic and mediastinal disorders incl. 234 deaths
- 3,094 Skin and subcutaneous tissue disorders incl. 8 deaths
- 319 Social circumstances incl. 4 deaths
- 690 Surgical and medical procedures incl. 54 deaths
- 3,140 Vascular disorders incl. 140 deaths
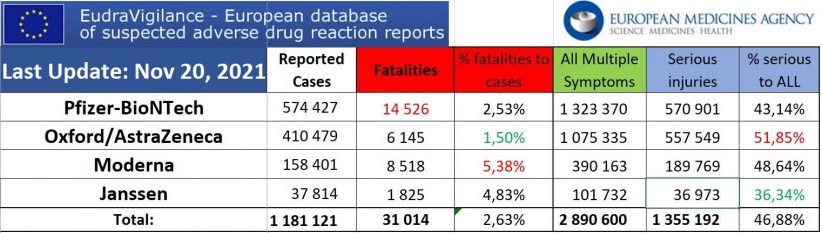
*These totals are estimates based on reports submitted to EudraVigilance. Totals may be much higher based on percentage of adverse reactions that are reported. Some of these reports may also be reported to the individual country’s adverse reaction databases, such as the U.S. VAERS database and the UK Yellow Card system. The fatalities are grouped by symptoms, and some fatalities may have resulted from multiple symptoms.
With Democrat Back in White House, MSNBC Returns to Ignoring U.S.-Backed War in Yemen

By Adam Johnson | The Column | November 24, 2021
A review of MSNBC’s coverage from Nov. 3, 2020 to Nov. 22, 2021 shows MSNBC hasn’t run a single segment on the U.S.-backed war still raging in Yemen.
To the extent MSNBC did cover Yemen’s “civil war” during this time frame it was exclusively to pass along, without skepticism, claims last spring from Democrats that President Biden had “ended U.S. support for the war”—which turned out to not be true in any meaningful sense, a fact evident at the time but not met with any questioning from MSNBC reporters or pundits.
Since then, it’s become increasingly clear little has changed in the status quo. While the U.S. has halted some forms of assistance, like mid-air refueling of aircraft, other forms of vital participation remain, including: green-lighting of weapons transfers, maintaining spare parts for Saudi war planes, sharing some forms of intelligence, and training the Royal Saudi Navy, which is enforcing a catastrophic blockade on Yemen.
And then there is the political cover that the Biden administration is giving the Saudi-led coalition, a vital form of support that noted in September by Annelle R. Sheline and Bruce Riedel at The Brookings Institute—hardly a far-left bastion of anti-imperial polemic:
Biden’s broken promise on Yemen
… Unfortunately, Biden’s approach is fatally flawed. The president stated that he would “end U.S. support for offensive operations in Yemen.” Yet the Saudi-led war on Yemen by definition, is an offensive operation. Saudi Arabia is bombing and blockading another country: Between March 2015 and July 2021, the Saudis conducted a minimum of 23,251 air raids, which killed or injured 18,616 civilians. The Houthis, known formally as Ansarallah, launch missiles in retaliation but if Saudi airstrikes ceased, the Houthis would have little reason to provoke their powerful neighbor. As long as the U.S. materially and rhetorically backs the Saudis’ war of choice, Biden’s assertion that the U.S. would end support for offensive operations is a lie.
The second crucial flaw in Biden’s approach is that he did not call for an immediate end to the Saudi blockade of Yemen. The blockade primarily blocks fuel from entering the Houthi-controlled Hodeida port; the Saudis also prevent the use of Sanaa International Airport. Blockades cannot be defensive: they are offensive operations, and therefore U.S. involvement should have ended following Biden’s declaration in February. The U.S. tacitly cooperated with the blockade by not challenging it, and the U.S. Navy occasionally announces it has intercepted smuggled weapons from Iran, suggesting a more active role than the administration admits. Congress should investigate.
Just this week, the Biden White House and State Department announced the US will be selling another $650 million in weapons to Saudi Arabia, hiding behind the nonsensical talking point that the weapons are “purely defensive.”
There was a time when MSNBC media personalities did act like they cared about what the UN calls the “world’s worst humanitarian disaster,” which has killed almost a quarter of a million people.
MSNBC ignored the war almost completely during the Obama years and early Trump years. But after the Saudi coalition bombed a school bus in August 2018, and Saudi dictator Mohammad bin Salman ordered the killing of Washington Post columnist Jamal Khashoggi in October 2018, they—like much of the U.S. media—finally began reporting on the regime’s human rights abuses. For a while.
MSNBC ran multiple segments on the war in the second half of 2018 when it was considered very much Trump’s war.
- Aug 9 2018 – All in with Chris Hayes: Dozens of children killed in school bus bombing in Yemen
- Aug 10 2018 – Velshi & Ruhle: An airstrike in Yemen struck a school bus, killing children
- Oct 21 2018 – All in with Chris Hayes: 14 Million People On Brink Of Starvation In Yemen
- Nov 15 2018 All in with Chris Hayes: Trump boosts authoritarians, as war rages in Yemen
- Sept 2018 – All in with Chris Hayes: WSJ: Pompeo backed continuing US role in war in Yemen
- Nov 28 2018 – All in with Chris Hayes: Senate advances bill to end support for war in Yemen
- Dec 12 2018: All in with Chris Hayes: Rep. Chris Murphy on what’s at stake with vote on Yemen
- Dec 12 2018 – All in with Chris Hayes: Paul Ryan’s Cowardly Act On Yemen
- Dec 13 2018 – Andrea Mitchell Reports: Bernie Sanders: Congress must determine U.S. involvement in Yemen crisis
- Dec 13 2018 – Ali Velshi: Senate votes to end U.S. support for Saudi-led war in Yemen
After this spasm of concern in late 2018, the coverage largely died out. As I noted in FAIR at the time, when activist pressure to pass a resolution compelling an end to U.S. support for the war was at its most urgent in March 2019, MSNBC ignored the effort altogether. There was a brief aside about Trump’s veto of said Yemen war powers act by Rachel Maddow on April 16, 2019, but it amounted to little more than a passing mention.
The next—and it turns out last—time an actual segment aired on the Yemen war was on Morning Joe in July 2020. This report, by NBC News’ Keir Simmons, did mention the war and the U.S.’s role in it, with a focus on how Covid was killing Yemenis. But since the July 2020 Morning Joe report, there have been no segments aired on MSNBC about the U.S.-backed Saudi bombing of Yemen.
In over 18 months, our nominally progressive cable network has not dedicated a single news report, roundtable debate, or segment to the world’s worst humanitarian disaster, which continues to be aided and armed by the U.S. government. When it was Trump’s war—and the Saudi regime fell out of favor with U.S. elites—their hearts bled. Now that we’re back to business as usual and the war is being armed and supported by a Democratic White House, it’s simply a non-issue.
In February 2021, President Joe Biden announced the U.S. was ending its support for “offensive” operations in Yemen, a deliberately vague and ultimately meaningless distinction that appears to have been designed to confuse progressives into declaring victory and moving on. Much to the White House’s liking, one can assume, the gambit seems to have worked, with MSNBC shelving the issue altogether and treating the U.S.-funded and backed war crime like it was wrapped up and out of our hands.
But it’s far from it. At any time, the Biden administration could cancel a U.S. program that provides maintenance for Saudi warplanes, the same warplanes that are still dropping bombs on civilians, including the recent bombing of a plastics factory in Sana’a. The Biden administration could reject the sale of U.S. air-to-air missiles, which can be used to shoot down airplanes and are one more tool the Saudi-led coalition can use to menace humanitarian workers who want to deliver supplies, or people trying to get their ill loved ones out of the country for treatment. And, it is an extremely low bar, but, at any point, Biden could clarify what is meant by support for “defensive” operations, and disclose the full extent of U.S. participation in the blockade, something he has repeatedly declined to do, even after 16 senators requested more transparency and robust action. These are all things the Biden administration is declining to do, thereby providing material and political support that is contributing to Saudi Arabia’s ability to continue the war.
After his six-month period in 2018 of breathlessly and repeatedly pronouncing the urgency of the issue, Chris Hayes’ show ‘All In’ has not run a segment on Yemen at all since December 2018.
Hayes hasn’t even mentioned the topic on Twitter since Biden took office Jan 20, 2021.
Mehdi Hasan, a consistent, long-time critic of Saudi Arabia and the war prior to joining MSNBC Feb 28 2021, did a segment on his online-only Peacock show after the election on Dec. 3 featuring prominent Yemen war critics Prof. Shireen Al-Adeimi and journalist Spencer Ackerman. In this segment, Hasan suggests in his opening that a Biden presidency would turn a page on the U.S.-Saudi relationship and end the war, neither of which happened (though both of his guests expressed profound skepticism). Also on his Peacock online-only show, he asked questions about continued U.S. support for Saudi Arabia, some quite skeptical, to guests Sen. Chris Murphy (D-Conn.) in April 2021 and Rep. Mark Pocan (D-Wisc.) in May 2021. But none of this was on his main cable show on MSNBC.
Hasan has not done a single segment on the Yemen war for his MSNBC show since his show first aired Feb 28 2021. On March 14 2021, he did ask White House Chief of Staff Ron Klain about the White House going soft on Saudi Arabia in general and in a one “minute rant” from May 2021, Hasan did take about 6 seconds to mention the U.S. selling arms to Saudi Arabia that are used in Yemen.
But this is the full extent of Hasan’s—and thus MSNBC’s—Yemen coverage. It goes without saying that multimillionaire MSNBC personalities Lawrence O’Donnell and Rachel Maddow haven’t done any segments on the war since Biden took office because, in the more than six years since it’s been raging, they haven’t mentioned it at all. To their credit, at least their indifference to the world’s largest humanitarian crisis isn’t motivated by partisan gotchas—they just don’t care in general.
In November 2020, Hasan insisted “we” needed to hold Biden to his promises that he would end US support for the war in Yemen.
Now that it’s been over a year since Biden’s election, and the U.S. is openly backing the Saudi blockade starving Yemenis, selling $650 million weapons to Saudi Arabia just this week, and continues to back SaudiArabia at the UN, perhaps media personalities with large platforms at nominally progressive cable networks should do just that.
New Zealand Doctors Speaking out with Science
NZDSOS – 15/11/2021
‘NZ Doctors Speaking out with Science’ featuring Drs Alison Goodwin, Matt Shelton, and Emanuel Garcia. News Conference 15th November, 2021.
See also:
Lethal Injection; Frontline E.R. Doctor Gives Chilling Account of Unusual Vaccine-Induced Illness
BY MIKE WHITNEY • UNZ REVIEW • NOVEMBER 20, 2021
“Americans are scared to death… People are walking off the job, not because they want to lose their jobs, but they don’t want to die from the vaccine! … They say, ‘Listen, I don’t want to die. That’s the reason I’m not taking the vaccine.’ It’s that clear.” Dr. Peter McCullough
A report in the U.K. Telegraph explains how the Covid-19 vaccine has led to a sharp rise in excess deaths. Here’s an excerpt from the article:
“Nearly 10,000 more people than usual have died in the past four months from non-Covid reasons, as experts called for an urgent government inquiry into whether the deaths were preventable…
Latest figures from the Office for National Statistics showed that England and Wales registered 20,823 more deaths than the five-year average in the past 18 weeks. Only 11,531 deaths involved Covid.” (“Alarm grows as mortuaries fill with thousands of extra non-Covid deaths,” UK Telegraph )
Mortality is rising because more people are dying. And more people are dying because more people have been vaccinated. There’s a link between rising mortality and the Covid-19 vaccine. Naturally, the media wants to shift responsibility for the fatalities to “delayed treatments” and “the lack of preventable care”. But this is just a diversion. The primary cause of death is the injection of a toxic pathogen into the bloodstreams of roughly 70% of the population. That’s what’s causing the clotting, the bleeding, the pulmonary embolisms, the heart attacks, the strokes, and the premature deaths. It’s the vaccine. Here’s more
“Weekly figures for the week ending November 5 showed that there were 1,659 more deaths than would normally be expected at this time of year. Of those, 700 were not caused by Covid.
The excess is likely to grow as more deaths are registered in the coming weeks.
Data from the UK Health Security Agency show there have been thousands more deaths than the five-year average in heart failure, heart disease, circulatory conditions and diabetes since the summer.
The number of deaths in private homes is also 40.9 per cent above the five-year average, with 964 excess deaths recorded in the most recent week, which runs up to November 5.” (“Alarm grows as mortuaries fill with thousands of extra non-Covid deaths“, UK Telegraph )
The sudden surge in mortality is not a meaningless blip on the radar. It’s a red flag indicating a significant break in the five-year trend. Something has gone terribly wrong. Mass vaccination was supposed to reduce the number of cases, hospitalizations and deaths. Instead, the fatalities continue to rise.
Why?
The answer to that question can be found in the data itself. As the author admits, there has been a sharp uptick in heart failure, heart disease, circulatory conditions and strokes. (Diabetes is the outlier) These are precisely the ailments one would expect to see if one had just injected millions of people with a clot-generating biologic that triggers a violent immune response that attacks the inner lining of the blood vessels inflicting severe damage to the body’s critical infrastructure. So, yes, all-cause mortality is up, and it is certain to climb even higher as more people are vaccinated and gradually succumb to the (frequently) delayed effects of a hybrid concoction that is the cornerstone of a malign plan to dramatically reduce global population. Check out this chart followed by a brief comment by diagnostic pathologist, Dr Claire Craig:
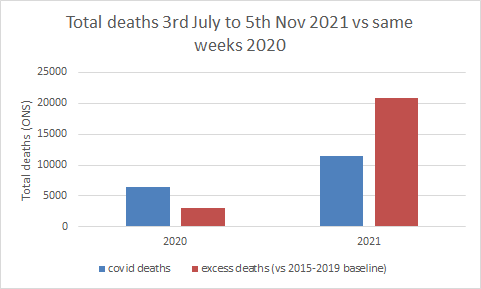
Dr Clare Craig @ClareCraigPath
“Since summer there have been twice as many covid deaths, but seven times as many excess deaths as last year.” (Twitter)
And here’s another blurb from Craig:
“If you start at week 22 and add up all the deaths since for each year, then something very abnormal is happening this year among 15-19 yr old males.”
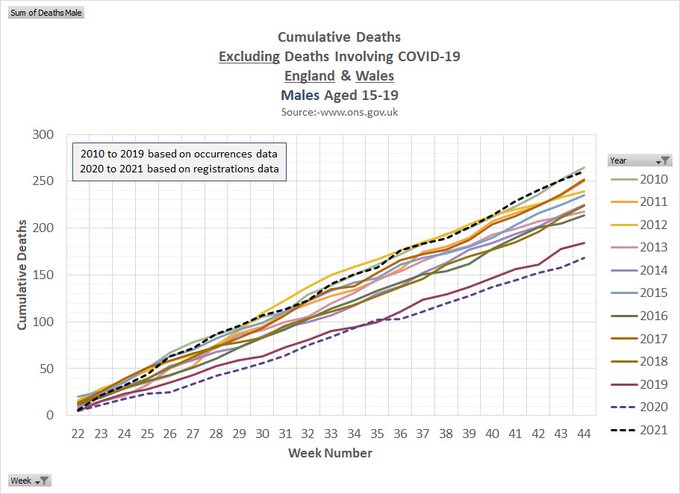
So, not only are more people dying, but the demographic has shifted downwards as younger and younger people are drawn into the vaccine vortex. Simply put, the number of young people dying from vaccine-inflicted cardiac arrest and myocarditis continues to increase with no end in sight.
Not surprisingly, all-cause mortality is higher among the vaccinated than the unvaccinated which, again, makes it easier to trace the problem back to its root, a cytotoxic “poison-death shot” that suppresses the innate immune system, damages vital organs and shaves years off the lives of normal, healthy people.
Perhaps, you’ve seen one of the many short videos of fit, young athletes who suddenly have dropped dead on the field of play or been rushed to hospital shortly after getting injected. If not, here’s a link to two of them. (Athletes collapse following vaccination: See here and here)
According to Israeli Real-Time News, there has been a “500% increase in deaths of players in 2021… Since December, 183 professional athletes and coaches have suddenly collapsed! 108 of them died!”
“500% increase in the deaths” of athletes?!? What are we to make of this?
For starters; the Covid-19 vaccine is not a medication. It is the essential component in the elitist plan for industrial-scale extermination. It is designed to inflict severe physical injury on the people who take it. It’s shocking that people are so deep in denial that they can’t see what’s going on right before their eyes. (Please, watch the video clips of the athletes. These are the fittest people on the planet and, yet, they are being struck down by the mystery substance in the vaccine.) Here’s how South African doctor Shankara Chetty summed it up in a recent video posted on Bitchute:
“The pathogen that is causing all the deaths from the illness is the spike protein. And the spike protein is what the vaccine is supposed to make in your body. … Spike protein is one of the most contrived poisons that man has ever made. And, the aim of this toxin, is to kill billions of people without anyone noticing it. So it is a poison with an agenda.” (“South African Physician Dr. Shankara Chetty Talks about “The Bigger Plan”, Bitchute)
There it is in a nutshell. And Chetty is not alone in linking the vaccine to the agenda of the globalist elites who plan to use the cover of a pandemic to implement their “population management” scheme. Former Pfizer vice president, Mike Yeadon, offered a similar view just days ago on his website. He said:
“We are in the midst of the biggest depopulation program the world has ever seen, where most of humanity are acting as useful idiots to it and to their own demise.”
Indeed, and we have tried to provide as much information as possible on the biologic agent that is being used to pursue this malign agenda, the spike protein. In early reports we passed along the research of Dr. Patrick Whelan who grasped the danger of the spike protein before anyone else. Here’s a brief recap of his analysis from a letter he submitted to the FDA on December 8, 2020:
“I am concerned about the possibility that the new vaccines aimed at creating immunity against the SARS-CoV-2 spike protein have the potential to cause microvascular injury to the brain, heart, liver, and kidneys in a way that does not currently appear to be assessed in safety trials of these potential drugs.
… Meinhardt et al…. show that the spike protein in brain endothelial cells is associated with formation of microthrombi (clots)… In other words, viral proteins appear to cause tissue damage without actively replicating virus…. The Pfizer/BioNTech vaccine (BNT162b2) is composed of an mRNA that produces a membrane-anchored full-length spike protein. The mouse studies suggest that an untruncated form of the S1 protein like this may cause a microvasculopathy in tissues that express much ACE2 receptor.
… it appears that the viral spike protein… is also one of the key agents causing the damage to distant organs that may include the brain, heart, lung, and kidney. Before any of these vaccines are approved for widespread use in humans, it is important to assess in vaccinated subjects the effects of vaccination on the heart…. As important as it is to quickly arrest the spread of the virus by immunizing the population, it would be vastly worse if hundreds of millions of people were to suffer long-lasting or even permanent damage to their brain or heart microvasculature as a result of failing to appreciate in the short-term an unintended effect of full-length spike protein-based vaccines on these other organs. (“FDA shrugs off dire warning about lethal spike protein“, Truth in the Age of Covid)
From the very beginning, government regulators and their allies in the public health establishment have ignored (or censored) the warnings of capable physicians and researchers. They also waved-off career immunologist and vaccinologist, Dr Byram Bridle who was the first in his profession to identify the spike protein as “a specific causative agent of disease”; aka–“a pathogen”. Here’s Bridle:
“‘We have known for a long time that the spike protein is pathogenic… It is a toxin. It can cause damage in our body if it’s in circulation. Now, we have clear-cut evidence that . . . the vaccine itself, plus the protein, gets into blood circulation.’”
Once that happens, the spike protein can combine with receptors on blood platelets and with cells that line our blood vessels. This is why, paradoxically, it can cause both blood clotting and bleeding. ‘And of course the heart is involved, as part of the cardiovascular system… That’s why we’re seeing heart problems. The protein can also cross the blood-brain barrier and cause neurological damage…
‘In short,… we made a big mistake. We didn’t realize it until now. We didn’t realize that by vaccinating people we are inadvertently inoculating them with a toxin.”… (“Vaccine scientist: ‘We’ve made a big mistake’“, TCW Defending Freedom )
Here again, we have a highly-regarded immunologist, with more than 3 decades of experience under his belt, who offered his informed and evidence-based research on an issue that should have been of great interest to the regulators that were making decisions about the long-term safety of the experimental drug they were foisting on millions of people across the country. But there was no interest at all. Despite the fact that the science supported his conclusions, Bridle was viciously attacked, censored, dragged through the mud, and forced to leave his place of employment.
Why?
Because he drew the same conclusions as Dr. Patrick Whelan. There’s really no substantive difference between the two except that Bridle’s comments attracted more attention in the media which made him a greater threat to the “universal vaccination” strategy. That was his real crime; he discovered the truth and made his findings available to the public, basically alerting them to the dangers of the “poison-death shot”. For that he was crushed.
Bridle has since made other claims that should concern anyone whose cancer might be in remission. Here’s what he said in a recent interview:
“What I’ve seen way too much of is people who had cancers that were in remission, or that were being well controlled; their cancers have gone completely out of control after getting this vaccine. And we know the vaccine causes a drop in T-cell numbers, and those T-cells are part of our immune system and they are part of the critical weapons our immune system has to fight off cancer cells; so there’s a potential mechanism there. All I can say, is I’ve had way too many people contact me with these reports for me to feel comfortable. I would say that is my newest major safety concern, and it’s also the one that’s going to be the most under-reported in the adverse data base, because if someone has had cancer before the vaccine, there’s no way public health officials will ever link it to the vaccine.” (“Dr Byram Bridle speaks”, Bitchute, :55 second-mark)
So, the vaccine suppresses the immune system?
Yes, it does, and author Alex Berenson provided evidence of this just recently in an article he posted on Substack. Here’s an excerpt:
“… the British government… admitted today, in its newest vaccine surveillance report, that:
“N antibody levels appear to be lower in people who acquire infection following two doses of vaccination.” (Page 23)
What’s this mean?…
What the British are saying is they are now finding the vaccine interferes with your body’s innate ability after infection to produce antibodies against not just the spike protein but other pieces of the virus…
This means vaccinated people will be far more vulnerable to mutations in the spike protein EVEN AFTER THEY HAVE BEEN INFECTED AND RECOVERED ONCE…
… it probably is still more evidence the vaccines may interfere with the development of robust long-term immunity post-infection.” (“URGENT: Covid vaccines will keep you from acquiring full immunity EVEN IF YOU ARE INFECTED AND RECOVER”, Alex Berenson, Substack)
Berenson’s observations square with research that was compiled earlier in the year by scientists in The Netherlands and Germany who:
“… warned that the … (COVID-19) vaccine induces complex reprogramming of innate immune responses that should be considered in the development and use of mRNA-based vaccines… the research team from Radboud University Medical Center and Erasmus MC in the Netherlands… showed that the vaccine altered the production of inflammatory cytokines by innate immune cells following stimulation with both specific (SARS-CoV-2) and non-specific stimuli.
Following vaccination, innate immune cells had a reduced response to toll-like receptor 4 (TLR4), TLR7 and TLR8 – all ligands that play an important role in the immune response to viral infection…. an unexplored area is whether BNT162b2 vaccination has long-term effects on innate immune responses …
This could be very relevant in COVID-19, in which dysregulated inflammation plays an important role in the pathogenesis and severity of the disease,” writes the team. “Multiple studies have shown that long-term innate immune responses can be either increased (trained immunity) or down-regulated (innate immune tolerance) after certain vaccines or infections.” (Research suggests Pfizer-BioNTech COVID-19 vaccine reprograms innate immune responses, new-medical-net)
Berenson’s finding also align with with cutting-edge research showing that the spike protein greatly “impedes adaptive immunity” by preventing DNA from repairing damaged cells. The paper suggests that the spike protein does in fact “impact on the nucleus of the cell, where we store our DNA, our core genetic material.” Here’s more from Berenson’s breakdown of the paper:
“… our cells have mechanisms to repair their own DNA.
But – at least in the experiments these two scientists ran – the spike protein appeared to interfere with our own DNA repair proteins: “Mechanistically, we found that the spike protein localizes in the nucleus and inhibits DNA damage repair by impeding key DNA repair protein BRCA1 and 53BP1 recruitment to the damage site.”
To be clear, the scientists did NOT prove the spike protein was causing these problems in people, or even animals… Nonetheless, at a time when advanced countries that have high mRNA (and DNA/AAV) vaccination rates are seeing unusually full hospitals and higher-than-normal death rates, they are yet more cause for concern. As the authors explained:
“Our findings reveal a potential molecular mechanism by which the spike protein might impede adaptive immunity and underscore the potential side effects of full-length spike-based vaccines.” (“URGENT: Worrisome paper about the spike protein’s impact on DNA and DNA repair”, Alex Berenson, Substack)
Bottom line: If the vaccine does in fact inhibit the body’s innate immune response, then people are going to get alot sicker from seasonal infections that routinely spread through the population. Their path to recovery will also be alot more difficult.
But rather than belabor the immunity angle, let’s move on to the research of Dr Charles Hoffe who was the first physician to provide hard evidence that the vaccines generate blood clots by triggering an immune response in which the body attacks the thin layer of cells lining the walls of the blood vessels. Hoffe found that 62% of his patients that had been vaccinated tested positive for blood clots on a D-dimer test. Naturally, he was alarmed by what he found, particularly since the vaccine “was causing serious neurological events, and even death. When he raised his concerns with the BC College of Physicians, they immediately implemented a gag order, and reprimanded him in an attempt to intimidate, and silence him.”
Hoffe has been interviewed a number of times and always provides a detailed and riveting account of his findings. In a recent interview, he predicted that some vaccinees suffering from clot-related issues would likely die in just three years. Here’s what he said:
“… once you block off a significant number of blood vessels to your lungs, your heart must pump at a much greater resistance to get the blood through your lungs. That causes a condition called pulmonary artery hypertension, which is high blood pressure in your lungs because so many of the blood vessels in your lungs are blocked. And the terrifying thing about this is that people with pulmonary artery hypertension usually die of right-sided heart failure in three years… And not only is the long-term outlook very grim, but with each successive shot, the damage will add and add and add. It’s going to be cumulative because you are getting more and more damaged capillaries.” (“Shock: Doctor Warns That Majority Of Vaccinated Patients Could HavePermanent Heart Damage, Some May Die Within Three Years”Permanent Heart Damage, Some May Die Within Three Years”, Infowars; Minute 6:10)
Once again, there is no discrepancy between the analysis of Whelan, Bridle and Hoffe. And while the focus of their attention might vary slightly, their conclusions are the same. These experimental injections pose serious risks for anyone who allows himself to be inoculated.
Now check out how similar Hoffe’s analysis is to Dr. Rochagne Kilian who was an Emergency Room physician at the GBHS hospital until she resigned in protest. This is a particularly important video as it describes the “oddball” symptoms and exceedingly rare conditions that are now presenting in emergency rooms everywhere following the mass vaccination of millions of people with the “poison-death shot”. (I transcribed the video myself, so there could be errors.)
Dr Rochagné Kilian – Blows the Whistle on Covid-19 Vaccines and D-Dimer Levels
“What I was seeing in my ER department especially in the last 8 to 9 months is related to the D-Dimer levels. We use D-Dimers specifically related to pulmonary embolisms as well as Deep Vein Thrombosis. D-Dimer detects any thrombosis (clots) in the body but it doesn’t give you a diagnosis it gives you a basis for going further and doing an ultrasound and CT scan to either confirm or deny the presence of a pulmonary embolism or Deep Vein Thrombosis.
The first part of 2020 was probably the slowest ever in the emergency department, but when we went into 2021 and the vaccination rollout started, we ended up seeing an increase in stroke, transient ischemic attacks and stroke like presentations. (There were) definitely significant larger numbers of those people coming in. I ended up doing D-dimer tests on these people and never before in my clinical experience had I seen D-dimers and the amount of people with positive D-dimers higher than 2,000, higher than 3,000 and higher than 5,000. My clinical experience told me a needed to go look for a large clot either in their legs or their lungs. And I ended up doing a CT scan on these people. Most of them, and I will say almost all of them, had negative scans which started making me think that if there was not a significant clot in their lungs, but my D-dimer was so much higher than what I was usually seeing, it might not be concentrated in one clot. But that it is multiple micro-thrombi extended throughout the body, and that is so easy to miss because the CT scan is not going to pick it up.
“These people coming into the ER were all people anywhere from about a week to four months after receiving their 2nd injections. There are certain factors that can influence a D-dimer test that can give you a sense of a higher level than would be expected in the body. That said, the patients I was doing D-Dimer tests on did not have a level of maybe a positive 500 or 400 reading. It was more than 3500, more than 5000 ng/ml. So those are significantly positive without any proof of having a pulmonary embolism. If I was seeing high levels of D-dimer without a definite diagnosis, I needed to ask more questions.
One study said, never ignore extremely elevated D-dimer levels. They are specific for serious illness, including venous thrombosis, sepsis, and/or cancer. Even if sharply elevated D-dimer are a seemingly solitary finding, clinical suspicion of severe underlying disease should be maintained.
There were two conditions that stood out and the first one was disseminated intravascular coagulation also known as DIC. The second one is antiphosphlipid syndrome. Both of these conditions are related to an abnormality in either the initiation or the feedback of the coagulation pathway as well as thrombosis or the thrombosis cycle where clots are being broken down. DIC is a serious sometimes life threatening situation in which the proteins in the blood involved in blood clotting become overactive. It’s a cascade that’s difficult to stop once it’s reached a certain level. There are certain conditions that trigger DIC; significant sepsis, underlying viruses, trauma, major surgery, pregnancy and childbirth. And less common causes toxic drug reaction, blood transfusion reaction, and organ transplants. So there was a connection with intravascular products and a possible DIC.
Most cases of DIC are diagnosed rapidly and suddenly which is the acute presentation. But there are cases where it develops gradually, occurring over a longer period of time. This is known as a chronic form of DIC and I would go as far to say a subacute form of DIC that is very easy to miss. Simultaneous clotting and bleeding can occur with chronic DIC. The bleeding part comes in blood in the urine, headaches and other symptoms associated with brain bleeds, bruising, inflammation of red, small dots on the limbs, bleeding at sites of wounds and mucosal bleeding. which means bleeding out of the gums and nose. I definitely saw an increase in nose bleeds and bleeding from previous wound sites. ulcers, as well as rashes that couldn’t be explained. Blood clotting symptoms and signs were symptoms like chest pains, heart attacks, strokes, TIAs, and headaches either related to bleeding or not. As well as symptoms related to kidney failure, because of the clotting of those smaller blood vessels that go to the kidneys. Antiphosphlipid syndrome is a very similar type of condition. But the basis of the antiphosphlipid syndrome is an autoimmune disorder meaning that the body’s immune system makes proteins–known as antibodies–that mistakenly attacks its own body or tissues. That gives the skin the cascading effect of clotting disorder but it is linked to an autoimmune trigger. Basically, it presented in exactly the same way; high blood pressure which I was seeing alot of; first diagnosis of high blood pressure, heart attacks, strokes, TIAs, heart valve problems, repeated headaches or migraines, vision loss, balance and mobility problems, difficulty concentrating or thinking clearly,
The astute listener would start forming a picture of what we’ve been told about Covid-19, and there are research papers connecting Covid 19 with an underlying vascular disease. One of these was a study called “Covid 19; unraveling the clinical progression of Nature’s Virtually perfect Biological weapon.”
“SARS-Cov-2, presenting as Covid-19 syndrome, was not a respiratory basis, but an underlying vascular basis. which had certain phases of incubation, pulmonary phase, pro inflammatory phase, (which once again comes into a cytotoxic inflammation process) then moves into a protothrombic phase . Covid-19 is a thrombotic disease. implications for prevention, antithrombotic therapy and follow up…
This picture shows us certain risk factors, Homeostatic Abnormalities, as well as clinical outcomes. It indicates increased D-dimer levels. It also mentions Venous Thromboembolism, Myocardial Infarction, and Disseminated Intravascular Coagulation that is connected to postulated mechanisms of coagulathopy as well as parthenogenesis of thrombosis in Covid-19…
I started asking the question, if we are able to detect certain connections between vascular abnormalities and Covid-19, and we based our proposed treatment on the spike protein, which includes the Pfizer and Moderna injections, shouldn’t we be looking for similar side effects or complications from that same injection?
If we are mandating certain treatments, we do need to do the due diligence to make sure what the side effects and complications especially in a time where there has not been long term studies.”And that’s what led me to focusing on D-dimers.” (“Dr Rochagné Kilian – Blows the Whistle on Covid-19 Vaccines and D-Dimer Levels“, Bitchute)
Kilian’s statement should be read over and over again. It is the most detailed description we have of the mysterious and deeply sinister machinations of a laboratory-engineered bioweapon that, in effect, turns the vascular and immune systems against the person who was vaccinated. Disseminated intravascular coagulation and antiphosphlipid syndrome are names that are entirely unknown to the American people, and yet, these freakish conditions are now responsible for a growing number of patients that are experiencing bleeding, clotting, headaches, rashes, bruising, high blood pressure, and inflammation . And– in more extreme cases– chest pains, heart attacks, strokes, heart-valve problems, and brain bleeds. One can only guess how the media will try to cover-up these extraordinarily-rare and potentially life-threatening conditions??
When Kilian asks:
“If we are able to detect certain connections between vascular abnormalities and Covid-19… shouldn’t we be looking for similar side effects or complications from that same injection?”
Bingo! If the spike protein produced by the vaccines, inflicts the same internal damage as Covid-19, then shouldn’t doctors expect to see the same symptoms?
Yes, they should. And if the symptoms are the same, then there’s a good chance that vaccine-induced injuries are being misdiagnosed as Covid-19.
Think about that for a minute. That would be the perfect scenario for the pandemic managers and their billionaire backers who’d love to see the impending mountain of carnage blamed on the waning virus instead of on their own poison-death shot.
And that is the evil-genius of the globalist strategy; to remove the fingerprints from the smoking gun before the investigators even arrive at the scene of the crime.
The amount of planning that must have gone into this scam, is simply breathtaking.

This perverse ban on ivermectin, cheap and proven to work
By Kathy Gyngell | TCW Defending Freedom | November 23, 2021
GIVEN the feared winter resurgence of Covid infection despite, or because of, the government’s mass vaccination programme, the continued ban on ivermectin in this country becomes ever more perverse.
It beggars belief that the British public is still denied access to this proven prophylactic and treatment. If the public health authorities are genuinely worried about pressure on hospitals, why have not the Medicines and Health products Regulatory Agency (MHRA), Public Health England, the NHS and Department of Health all gone flat out over this last year to approve ivermectin with the same zeal they gave emergency authorisation to the limited trialled, novel gene therapy, Covid vaccines?
The answer is widespread misinformation from the top down. Put ‘ivermectin’ into the Google search box and what do you come up with? Topping the list is a warning from the US Food and Drug Administration (FDA) why it should NOT be used to treat or prevent Covid-19. Their reason? It’s as simple as the fact that they have not approved it and, because they have not approved, it cannot be used. Trials are ongoing they say. Maybe some are. But plenty have been completed, as Dr Pierre Kory’s paper (he was the lead author) ‘Review of the Emerging Evidence Demonstrating the Efficacy of Ivermectin in the Prophylaxis and Treatment of Covid-19’, published by the American Journal of Therapeutics earlier this year, made quite clear.
By contrast with this detailed review of the evidence the FDA’s substantive concern appears to rest on random reports of harms deriving from self-medication with ivermectin.
The BBC not to be behindhand entered the fray with its customary selective and biased take on ‘the science’. Its recent report entitled ‘How false science created a Covid ‘miracle’ drug‘ made not even the most minimal of checks on the veracity of their assertions, which are pulled apart here. A letter sent to a programme journalist in response to their request for information (in advance of transmission) by Dr Tess Lawrie, the Director of the British Ivermectin Recommendation Development Group (BIRD), an advocacy group of clinicians and scientists from around the world, setting out the science behind the case for authorising it, was completely ignored. Her letter can be found here.
How the BBC came not to ask how it was that remdesivir – a standard medication for Covid in the UK – was approved on the basis of one study when ivermectin, with 63 studies, of them 31 Randomised Controlled Trials (RCT), 7 meta-analyses, 32 Observational Controlled Trials (OCT), multiple country case studies, expert opinion, patient testimony ALL pointing in favour of the medication, was not, is inexplicable.
This is the news source the public is still told to trust.
A blog posted on BIRD last week asked whether there are indeed any genuine gripes about the quality of the evidence, as the FDA and others suggest?
No, there are not. The author argues it is down to a misinformation campaign based on misleading information produced by high profile public health agencies, like the World Health Organisation, itself a victim of disinformation tactics, that has been ‘perpetrated by a minority of corporations to manipulate and delay government action on matters that would adversely affect their income and profit’. Speculation of course. But every indication points that way.
As reported extensively in TCW Defending Freedom, for example here, the WHO is subject to the huge financial influence of the Bill and Melinda Gates Foundation, the organisation’s second biggest donor. Since one of the BMGF’s long-term interest is in delivering vaccines, why would they show any interest in promoting the use of cheap, old repurposed medications in the treatment and prevention of Covid-19? It’s for the very same reason that ivermectin has proved of so little interest to Big Pharma -it’s hardly the money spinner that indemnified world-wide vaccination is.
Worse perhaps than what these big interests have not done is what they have actively done to discredit ivermectin. The BIRD blog relays an analysis by Dr Kory setting out what the WHO ‘did’ with the ivermectin evidence. He says it:
· Failed to publish a pre-established protocol for data exclusion
· Excluded two ‘quasi-randomised’ controlled trials (RCTs) with lower mortality
· Excluded two RCTs that compared ivermectin to or gave it together with other medications, all reporting lower mortality
· Excluded seven other available ivermectin RCT results
· Excluded all RCTs and observational controlled trials (OCTs) investigating ivermectin in the prevention of Covid-19
· Excluded 13 OCTs, more than 5,500 patients, that showed reductions in mortality
· Excluded numerous published and pre-print epidemiologic studies.
The bottom line, however, remains – if ivermectin is good enough and provenly effective for the more than 20 lower-income countries which do distribute it and also benefit from lower Covid rates, why are the populations of wealthier nations and individuals still being denied?
It’s a point that clearly has bothered the chairman of the Tokyo Medical Association, Dr Haruo Ozaki, who would recommend ivermectin for Covid patients, noting that the parts of Africa that use ivermectin to control parasites have a Covid death rate of just 2.2 per 100,000 population, compared with 13 times that death rate among African countries that do not use ivermectin.
‘I would like,’ said Dr Ozaki, ‘the government to consider treatment at the level of the family doctor’ with the informed consent of the patient. So would we.
Featured Video

No Vote, No Representation, No State: Democracy, Israeli Style
or go to
Aletho News Archives – Video-Images
From the Archives
Sanctions, War and the Policy of Dual Containment
By SASAN FAYAZMANESH | March 17, 2008
It is now nearly three decades since the Unites States adopted the policy of dual containment of Iran and Iraq. While much has been written about the containment of Iraq, there has been very little in-depth analysis of this policy when it comes to Iran. In a book that is going to be released on March 31, 2008, entitled The United States and Iran: Sanctions, Wars and the Policy of Dual Containment (Routledge), I attempt to address this shortcoming by investigating when and why the US policy of containment of Iran came about, how it evolved, and where it stands today.[1] To the extent that Israel has been involved in US policy making, the study will also include the role that Israel has played in the containment of Iran. Also, since the fate of Iran has been inextricably linked to that of Iraq, occasionally the investigation will overlap with the containment of Iraq.
The policy of dual containment of Iran and Iraq originated during the Carter Administration, but it was not until the Clinton Administration that the expression “dual containment” became popular. … continue
Blog Roll
 Aletho News
- No Vote, No Representation, No State: Democracy, Israeli Style
- Zionist Bought Senate Blocks Information About American Citizens Killed By Israel
- While Gaza dominates the UN, these are the people keeping it alive
- New Report: “Scholasticide and Genocide in Gaza: Assessment, Testimonies and Legal Analysis”
- ‘THAAD Delusion’: Iran war exposes US missile shield limits – The Atlantic
- Moscow issues warning to NATO over Russian exclave
- Yes, the Iran war has destroyed Trump’s presidency
- The fallacy of US delusions about Iran’s economic collapse
- Hezbollah denies Syria cell link, warns of Israeli plan to sow discord
- The legacy of US sanctions, war, and occupation in Iraq
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates

