When it comes to COVID, public health officials have consistently downplayed and/or ignored natural immunity.
Yet these public health experts and many doctors and scientists know that no vaccine can confer the type of robust, full, sterilizing and life-long immunity to COVID that natural-exposure immunity confers.
Officials at the Centers for Disease Control and Prevention (CDC) and National Institutes of Health (NIH) know anyone exposed, infected and recovered from SARS-CoV-2 has acquired cellular immunity.
They know how natural immunity works, yet they continue to deceive the public on this issue by falsely insisting vaccines are the only answer to “ending the pandemic.”
The authors of a 2008 study on the 1918 pandemic virus showed how potent and long-lived natural immunity is, and how the immune system generates new antibodies if and when needed (re-exposed).
The researchers wrote:
“A study of the blood of older people who survived the 1918 influenza pandemic reveals that antibodies to the strain have lasted a lifetime and can perhaps be engineered to protect future generations against similar strains … the group collected blood samples from 32 pandemic survivors aged 91 to 101 … the people recruited for the study were 2 to 12 years old in 1918 and many recalled sick family members in their households, which suggests they were directly exposed to the virus … The group found that 100% of the subjects had serum-neutralizing activity against the 1918 virus and 94% showed serologic reactivity to the 1918 hemagglutinin.
“The investigators generated B lymphoblastic cell lines from the peripheral blood mononuclear cells of eight subjects. Transformed cells from the blood of 7 of the 8 donors yielded secreting antibodies that bound the 1918 hemagglutinin.
“ … here we show that of the 32 individuals tested that were born in or before 1915, each showed sero-reactivity with the 1918 virus, nearly 90 years after the pandemic. Seven of the eight donor samples tested had circulating B cells that secreted antibodies that bound the 1918 HA. We isolated B cells from subjects and generated five monoclonal antibodies that showed potent neutralizing activity against 1918 virus from three separate donors. These antibodies also cross-reacted with the genetically similar HA of a 1930 swine H1N1 influenza strain.”
The very same CDC that fights against COVID natural immunity, argues just the opposite when it comes to chickenpox.
Guidance on the CDC website, “Chickenpox Vaccination: What Everyone Should Know,” states: “People 13 years of age and older who have never had chickenpox or received chickenpox vaccine should get two doses, at least 28 days apart.”
In this reasonable guidance, the CDC says you need the chickenpox jab if you “have never had chickenpox.” If you have had it, then you do not need the vaccine.
The CDC goes even further, stating: “You do not need to get the chickenpox vaccine if you have evidence of immunity against the disease.” So if someone has had chickenpox and recovered, and can demonstrate that via a laboratory test, they don’t need the vaccine.
Again, this makes sense. All parents know this, and have for generations. You do not need a vaccine for measles, if you already had measles and cleared the rash and recovered. Natural, beautiful robust immunity, typically lasts for the rest of a person’s life.
The same goes for the CDC’s guidance for the measles, mumps, and rubella vaccine (MMR). The CDC clearly states no MMR vaccine is needed if “You have laboratory confirmation of past infection or had blood tests that show you are immune to measles, mumps, and rubella.”
So, what is different for COVID-19? Is something other than science at play here?
We now have a major crisis as the race is on to vaccinate our 5- to 11-year-old children who bring no risk to the table, with a vaccine that has been shown to be sub-optimal and carrying risks.
We even have one of the FDA advisory committee members, Dr. Eric Rubin, who is also lead editor of the New England Journal of Medicine, stating: “We’re never gonna learn about how safe the vaccine is until we start giving it.”
This is a shocking statement by someone who played a role in the decision-making, and should lead us to examine if Rubin and others on that committee were conflicted in terms of relationships to the vaccine developers.
Rubin further stated: “The data show that the vaccine works and it’s pretty safe … we’re worried about a side effect that we can’t measure yet,” he said, referring to a heart condition called myocarditis.
So then why would Rubin and others agree to expose our children to potential harm from a vaccine for an illness that poses little risk to children, if they have serious concerns and admit they have not and cannot yet measure the safety?
This depth of uncertainty should never exist in any drug or vaccine that the FDA regulates, much less a drug officials propose to administer to 28 million children. Something is very wrong here.
An April 2021 study in the Journal of Infection (April 2021) examined household transmission rates in children and adults. The authors reported there was “no transmission from an index-person < 18 years (child) to a household contact < 18 years (child) (0/7), but 26 transmissions from adult index-cases to household contacts < 18 years (child) (26/71, SAR 0=37).”
These findings add to the stable existing evidence that children are not spreading the virus to children but rather that adults are spreading it to children.
Why vaccinate our children for this mild and typically non-consequential virus when they bring protective innate immunity towards this SARS-VoV-2, other coronaviruses and other respiratory viruses?
Why push to vaccinate our children who may well be immune due to prior exposure (asymptomatic or mild illness) and cross-reactivity/cross-protection? Why not consider assessing their immune status?
Dr. Geert Vanden Bossche writes that children’s innate immunity:
“… normally/ naturally largely protects them and provides a kind of herd immunity in that it dilutes infectious CoV pressure at the level of the population, whereas mass vaccination turns them into shedders of more infectious variants. Children/ youngsters who get the disease mostly develop mild to moderate disease and as a result continue to contribute to herd immunity by developing broad and long-lived immunity.”
Here are six studies that make the case for not vaccinating children:
1. A 2020 Yale University report indicates children and adults display very diverse and different immune system responses to SARS-CoV-2 infection which explains why they have far less illness or mortality from COVID.
According to the study:
“Since the earliest days of the COVID-19 outbreak, scientists have observed that children infected with the virus tend to fare much better than adults … researchers reported that levels of two immune system molecules — interleukin 17A (IL-17A), which helps mobilize immune system response during early infection, and interferon gamma (INF-g), which combats viral replication — were strongly linked to the age of the patients. The younger the patient, the higher the levels of IL-17A and INF-g, the analysis showed… these two molecules are part of the innate immune system, a more primitive, non-specific type of response activated early after infection.”
2. Studies by Ankit B. Patel and Dr. Supinda Bunyavanich show the virus uses the ACE 2 receptor to gain entry to the host cell, and the ACE 2 receptor has limited (less) expression and presence in the nasal epithelium in young children (potentially in upper respiratory airways).
This partly explains why children are less likely to be infected in the first place, or spread it to other children or adults, or even get severely ill. The biological molecular apparatus is simply not there in the nasopharynx of children. By bypassing this natural protection (limited nasal ACE 2 receptors in young children) and entering the shoulder deltoid, this could release vaccine, its mRNA and LNP content (e.g. PEG), and generated spike into the circulation that could then damage the endothelial lining of the blood vessels (vasculature) and cause severe allergic reactions (e.g., here, here, here, here, here).
3. William Briggs reported on the n=542 children who died (0-17 years (crude rate of 0.00007 per 100 and under 1 year old n=132, CDC data) since January 2020 with a diagnosis of COVID linked to their death. This does not indicate whether, as Johns Hopkins’ Dr. Marty Makaryhas been clamoring, the death was “causal or incidental.” That said, from January 2020, 1,043 children 0-17 have died of pneumonia.
Briggs reported:
“There is no good vaccine for pneumonia. But it could be avoided by keeping kids socially distanced from each other — permanently. If one death is “too many,” then you must not allow kids to be within contact of any human being who has a disease that may be passed to them, from which they may acquire pneumonia. They must also not be allowed in any car … in one year, just about 3,091 kids 0-17 died in car crashes (435 from 0-4, 847 from 5-14, and 30% of 6,031 from 15-24). Multiply these 3,000 deaths in cars by about 1.75, since the COVID deaths are over a 21-month period. That makes about 5,250 kids dying in car crashes in the same period — 10 times as many as Covid.”
Briggs concluded: “there exists no justification based on any available evidence for mandatory vaccines for kids.”
4. Weisberg and Farber et al. suggest (and building on research work by Kumar and Faber) that the reason children can more easily neutralize the virus is that their T cells are relatively naïve. They argue that since children’s T cells are mostly untrained, they can thus immunologically respond (optimally differentiate) more rapidly and nimbly to novel viruses such as SARS-CoV-2 for an effective robust response.
5. Research published in August 2021 by J. Loske deepens our understanding of this natural type biological/molecular protection even further by showing that “pre-activated (primed) antiviral innate immunity in the upper airways of children work to control early SARS-CoV-2 infection … the airway immune cells in children are primed for virus sensing…resulting in a stronger early innate antiviral response to SARS-CoV-2 infection than in adults.”
6. When one is vaccinated or becomes infected naturally, this drives the formation, tissue distribution and clonal evolution of B cells, which is key to encoding humoral immune memory.
Research published in May 2021 showed that blood examined from children retrieved prior to COVID-19 pandemic have memory B cells that can bind to SARS-CoV-2, suggestive of the potent role of early childhood exposure to common cold coronaviruses (coronaviruses). This is supported by Mateus et al. who reported on T cell memory to prior coronaviruses that cause the common cold (cross-reactivity/cross-protection).
There is no data or evidence or science to justify any of the COVID-19 injections in children. Can the content of these vaccines cross the blood-brain barrier in children? We don’t know because it wasn’t studied.
There is no proper safety data. The focus rather has to be on early treatment and testing (sero antibody or T-cell) to establish who is a credible candidate for these injections, as it is dangerous to layer inoculation on top of existing COVID-recovered, naturally acquired immunity.
There is no benefit and only potential harm/adverse effects (here, here, here).
Dr. Alexander is considered a global expert on COVID-19 generally and in some areas highly expertised. Dr. Alexander holds masters level study at York University Canada, a masters in epidemiology at University of Toronto, a masters in evidence-based medicine at Oxford and a doctorate in evidence-based medicine and research methods from McMaster University in Canada.
Professor Richard Ennos, a retired Professor of Evolutionary Biology at Edinburgh University, writes:
In Scotland this summer there has been excess mortality for the past 21 weeks with the total excess now exceeding 3,000 deaths. I and others have written to MSPs about the dreadful situation asking for a thorough analysis of what is responsible. In response we have been sent a reply from Anita Morrison, Head of Health and Social Care Analysis and Support, that I reproduce below. Five possible explanations are given, none of which reflect favourably on the Scottish Government’s public health policy. To paraphrase her reply, 45% are due to COVID-19 and the rest are accounted for by one or more of:
COVID-19 deaths that were not recognised.
Unintended consequences of the Scottish Government’s non-clinical response to COVID-19 (masks, social isolation etc.).
Problems with access to the health and social care services (presumably due to Scottish government policy of withdrawing these).
Patients not accessing services that were available (presumably because they were too scared of catching COVID-19 due to Scottish government exaggeration of the risks).
Some other cause that has not been identified.
What follows is my reply to Anita Morrison to point out that her response is a damning indictment of Scottish Government public health policy whose outcome should ultimately be measured by the metric of excess deaths.
FAO: Anita Morrison
Head of Health and Social Care Analysis and Support
Directorate for Covid Public Health
Cc Dr. Gregor Smith, Jason Leitch, Caroline Lamb, Maree Todd MSP, Kevin Stewart MSP, Nicola Sturgeon MSP
28th October 2021
Dear Anita Morrison
Thank you for your response to my letter, originally addressed to Sarah Boyack MSP, concerning the unprecedented rise in excess deaths in Scotland this summer that continues as I write (252 excess deaths above five-year average in the past week 42, 24% higher than normal). It is now indisputable that some major health catastrophe is unfolding in Scotland this summer. It is clearly essential that there is serious scrutiny of the health policies that have been adopted by the Scottish Government that have led to this situation. To help with this I would like to look in some detail at the explanations that you have provided for the incredibly worrying situation, and set out the implications of what you have written.
In your response you have put forward the argument that some 45% of these excess deaths have been caused by Covid. This proposition relies on the assumption that all Covid deaths represent excess deaths, a position that is hard to sustain given that Covid deaths are associated with multiple comorbidities, and therefore are unlikely to be exclusively in addition to deaths that would have occurred anyway from other causes.
Setting aside this difficulty, and assuming that 45% of excess deaths are due to Covid, this indicates that the policies that have been pursued by the Scottish Government have been unsuccessful in controlling deaths from Covid this summer. This is in contrast to the summer of 2020 when there was no such excess of deaths due to Covid or any other cause. This increase in the impact of Covid in Scotland between the summers of 2020 and 2021 is nicely illustrated using National Records of Scotland data from the two years stratified by different age groups.
A simple and compelling explanation for these data is that a policy has been enacted in 2021 that was not enacted in 2020 that has caused a three- to six-fold increase in summer Covid hospitalisations. What could that be?
Let us now turn to the majority of excess deaths that cannot be accounted for by Covid. I will be using the most up to date figures from the National Records of Scotland for the summer period 2021 up to week 42 that indicate 3,028 excess deaths (rather than your figures that extend only to week 40). The National Records of Scotland classify these deaths according to their causes, location and age. This is illustrated below.
Here we see that Covid can actually account for a maximum of only 26% of excess deaths in summer 2021. Significant rises in cancer and circulatory deaths are concerning, but perhaps of greater note is that 44% of excess deaths come under the classification of ‘Other’. They are not the kinds of deaths that are readily classifiable into the normal categories that we expect in Scotland, or they would have been placed in those categories. It is therefore these ‘Other’ deaths, some 44% of the total, that we need to investigate in great detail.
From the other panels in the graph above we can see that these ‘Other’ deaths are occurring at home, implying that they are likely to have been sudden because there has been no hospital admission. Furthermore, these excess deaths are not confined to the oldest age groups, where we expect most deaths, but are extended into the younger age group. Analysis of the timing of this rise in excess death shows that it started in the oldest age group and is initiated sequentially in ever younger age groups (see graph below). This strongly suggests that there is some cause for these excess deaths at home that operates first in the elderly and works its way sequentially down the age groups in Scotland. What could this be?
Now let us look at the non-Covid explanations that you have provided for the dramatic increase in excess deaths in Scotland over the past summer.
Your first explanation is that the summer excess deaths recorded as non-Covid are actually due to Covid, but have not been certified as such. I see that you yourself are not convinced by this explanation given the level of testing that has taken place. However, let us suppose this to be true. In that case the Scottish Government’s public health measures that have been put in place in summer 2021 to prevent Covid have been far worse than those put in place in summer 2020 – indeed they have been disastrous.
Your second explanation is that the non-clinical responses to COVID-19 put in place by the Scottish Government (mask-wearing, social isolation etc.) have had unintended deleterious consequences on public health and have dramatically increased the rates of death in the Scottish population. This is an admission of abject failure of the Scottish Government’s public health response to Covid. Public health policy is all about balancing the benefits and risks of interventions to achieve the lowest possible impact during a health emergency. It is pertinent to remember that no benefit-risk assessment of non-clinical interventions on the physical and mental health of the Scottish population was conducted before these interventions were enforced.
Your third explanation is that there has been a problem with access to health and social care services, and patients have not received the care they required from the NHS. Access to these services over the past 20 months has been under the control of the Scottish Government, so if this explanation is correct, then the Scottish Government is culpable for increasing the death rate in Scotland. Numerous policies have been deliberately pursued to dramatically reduce GP face-to-face consultation, to cancel appointments and operations in hospitals etc., so the evidence to support this, as at least a partial explanation, is overwhelming.
Your fourth explanation is that individuals who are in poor health have not referred themselves to health and social care services as they would at other times. To some extent this would be confounded with Scottish Government policies of restricting health care provision discussed above. However there has also been a concerted and relentless media campaign by the Scottish Government to increase fear in the public, particularly fear of hospitals where they may catch Covid. This has meant that they have not gone for treatment when it was necessary. Whatever the proximal cause of failure to seek medical attention, the ultimate cause and responsibility lies in Scottish Government policy.
Your final explanation for the dramatic rise in excess deaths in summer 2021 is that there is some other cause that has not yet been identified. As noted earlier the phenomenon of excess deaths in the presence of a Covid epidemic was not seen in summer 2020, but is seen in summer 2021. What differs between the two years? The glaringly obvious answer is the rollout of COVID-19 vaccination. There was no COVID-19 vaccination programme in 2020, but there was rollout of Covid vaccinations in a sequential way to increasingly younger age groups in 2021, a pattern that we see in the manifestation of excess deaths. All of the COVID-19 vaccines are novel and experimental with no long-term safety data. They are now associated with a wide range of serious side-effects (blood clotting, myocarditis, Guillain-Barre syndrome) whose likely frequency in the wider population was not assessed in the small-scale phase one and two trials that included only a subset of healthy volunteers. The Yellow Card adverse events reporting system, that capture only a fraction of events, has already recorded over 1,700 deaths in the U.K. population associated with the COVID-19 vaccines. There is therefore a prima facie case for COVID-19 vaccination being a contributing factor to the dramatic rise in summer excess deaths in Scotland in 2021.
I am very grateful for your response to my original letter. It has been extremely helpful in crystalising my thoughts about the causes of the dramatic and continuing rise in excess deaths that we currently see in Scotland. My conclusion is that whatever the true explanation for the phenomenon, it is rooted in the misguided and disastrous public health policies of the Scottish Government. The analysis has moreover highlighted that a significant contributor to the excess death of the Scottish population this summer may be adverse reactions to the COVID-19 vaccines, a factor that apparently has not occurred to either the Scottish Government or yourself. I would be grateful if you would pass on this insight to the Scottish Health minister so that unnecessary suffering and death is not meted out on the adults, and now children of Scotland.
It sounds like a script in a science fiction movie, but it’s not: Emails obtained by The Intercept show that the National Institutes of Health worked together with one of its grantees, EcoHealth, to evade gain-of-function (GOF) research restrictions.
While EcoHealth’s plans for the research “triggered concerns at NIH,” staff went ahead and “adopted language that EcoHealth Alliance crafted” so the work could go on. The Intercept added that none of the featured experiments could have triggered the current pandemic, but the idea of the deceptive move shows what persons in a position of authority at the highest levels will do to circumvent safety rules and regulations.
The violations were serious enough to spark concerns from Jesse Bloom, a virologist at the Fred Hutchinson Cancer Research Center. “The discussions reveal that neither party is taking the risks sufficiently seriously,” Bloom told The Intercept.
Simon Wain-Hobson, a virologist at the Pasteur Institute in Paris, minced no words with his opinion on what happened. “It’s absolutely outrageous,” Wain-Hobson said. “The NIH is bending over backward to help people it’s funded. It isn’t clear that the NIH is protecting the U.S. taxpayer.”
There are “strong grounds” to conclude that Israel’s systematic targeting of journalists working in Palestine and its failure to properly investigate killings of media workers amount to war crimes, a complaint being submitted to the International Criminal Court (ICC) will say.
The International Federation of Journalists (IFJ), working with the Palestinian Journalists’ Syndicate (PJS) and the International Centre of Justice for Palestinians (ICJP), has asked Bindmans and Doughty Street Chambers to submit a complaint to the ICC detailing “the systematic targeting of Palestinian journalists on behalf of four named victims – Ahmed Abu Hussein, Yaser Murtaja, Muath Armaneh, and Nedal Eshtayet – who were killed or maimed by Israeli snipers while covering demonstrations in Gaza. All were wearing clearly marked PRESS vests at the time they were shot.”
“At least 46 journalists have been killed since 2000 and no one has been held to account,” the IFJ said in a statement on its website.
The complaint will also include the “bombing of the Al-Shorouk and Al-Jawhara Towers in Gaza City in May 2021″.
IFJ General Secretary Anthony Bellanger said: “The targeting of journalists and media organisations in Palestine violates the right to life and freedom of expression. These crimes must be fully investigated. This systematic targeting must stop. The journalists and their families deserve justice.”
Would the doctrine of the “Original Antigenic Sin” (OAS) play a heavy role in the existing COVID vaccine strategy — due to the sub-optimal, non-sterilizing, imperfect COVID-19 vaccine?
Experts agree we should never have tried to vaccinate our way out of a pandemic while in a pandemic.
According to the OAS by Dr. Thomas Francis, the initial priming of the immune system (initial exposure to the virus, either in the wild or via a vaccine) gets ‘fixed’ for life. If the initial priming of the immune system is sub-optimal and biased, then that sub-optimal initial priming can effectively derange and bias the immune response long-term, which would guide all future immunological responses.
We should have known that this initial priming, if deranged and wrong, would severely stagger and hobble our immune response for the rest of our lives.
And so, are we setting up our populations — and dangerously, our children — for disaster? With this imperfect and sub-optimal immune priming using COVID vaccines that do not stop infection or transmission in the first place?
The COVID-19 vaccines being administered in the U.S. only reduce symptoms, thus allowing the host to stay alive (an evolutionary future it did not have) while remaining capable of transmitting.
Evidence shows vaccinated persons are indeed susceptible to infection, and as alarmingly, carry as high a viral load as the unvaccinated.
Are we about to rob our children of their most precious gift — a robust, durable, potent natural innate immunity with these imperfect leaky vaccines — an immunity that has always protected them and helps reduce the infectious pressure and helps contribute to population herd immunity? With vaccines that have been shown to be harmful?
I argue we could potentially kill many children with these vaccines because we simply have not done the proper safety tests and studies for the proper duration of follow-up, so as to “exclude harms.”
If we have not conducted the proper studies, how could we justify the safety of these vaccines for our children? To do so is dangerous and reckless, as it deceives the public and parents. It is illogical and irresponsible, and without any credible basis.
We do not know what will happen to our healthy children long-term. This is potentially catastrophic if COVID mass vaccination is allowed in our children.
These public health officials at the U.S. Food and Drug Administration, Centers for Disease Control and Prevention (CDC), National Institutes of Health (NIH), National Institute of Allergy and Infectious Diseases (NIAID) — including Dr. Anthony Fauci and Dr. Rochelle Walensky — have made no valid case as to why our children warrant these vaccines.
Yet they are seeking to vaccinate healthy children with near statistical zero risk — with only the opportunity for harm and no opportunity for benefit.
In addition to the OAS, Read et al also provided us a roadmap to these vaccine and immune system challenges, in their treatise on Marek’s disease in chickens.
In their seminal 2015 PLOS paper, the authors argued some vaccines may boost and enhance the fitness of more virulent strains. They asked a simple question: Could some vaccines drive the evolution of more virulent pathogens?
We say “yes!” This can be explained by natural selection which selects out or culls pathogen strains/variants that are so lethal or “hot” they could kill their hosts if they survive and, thus, inadvertently, kill themselves.
Marek’s disease effect and vaccination may well be at play here with COVID vaccines — moderating symptoms while not stopping infection or transmission, thus posing a danger to the unvaccinated and vaccinated.
We — or at least the virologists and immunologists and vaccine developers — should also have understood the COVID vaccines would drive antibodies against the spike glycoprotein only, while our natural-exposure infection immune response will be broad, robust, durable, long-term — providing immunity against the spike (S) protein, the membrane protein, the nucleocapsid (N) protein, and all the epitopes on the viral ball and all conserved parts of the virus.
No COVID vaccine immunity could be equal to or better than naturally acquired immunity. This should have never even been in question. Assertions otherwise by the CDC, NIH, NIAID or vaccine developers are outright falsehoods and means to deceive the public.
We should have known we could never achieve “zero COVID” as this is a mutable respiratory pathogen. This means, similar to flu and cold viruses, COVID mutates often.
This is what viruses do. They exist to replicate, and the replicating process of their genetic material is unstable and imperfect. Because there are errors in the replication of the genetic material, there will always be mutations.
For example, the original SARS-CoV-2 was the Wuhan strain — now it is the Delta variant. The vaccine for the original strain cannot hit the mutated spike, as the mutations occur on the spike. That’s why we have the immune escape.
So no matter what vaccine you make, you will not be able to vaccinate for the right strain or variant at any time, as the virus would have mutated by the time we vaccinate.
You can never get ahead of a mutating virus with a vaccine.
This is especially true given COVID has an animal reservoir. The virus lives stably in the bat population. Unless we kill off all the bats — and their intermediate hosts, which include civet cats and raccoon dogs and camels — we will always have a “reservoir” for the virus, in animals. Infected animals can in turn infect humans who get close to or interact with them.
This is a very different pathogen and approach than the one taken with smallpox, which did not have an animal reservoir — we only had to remove smallpox from the human population, we didn’t need to worry about it spilling over from other species.
According to Dr. Robert Malone, “The idea that if you have a workplace where everybody’s vaccinated, you’re not going to have virus spread is totally false … a total lie … the vaccinated are actually the “super-spreaders” that everyone was told about in the beginning of the pandemic.”
Malone further states, “if the government isn’t going to disclose what the [vaccine] risks are, and they’re not going to disclose what’s really going on because they think that you can’t handle the news … this is called the noble lie.”
Are we closer to understanding now that vaccinating for COVID under tremendous infectious and vaccine pressure (and ecological pressure) would drive immune escape? That this strategy is indeed a recipe for disaster?
Could COVID-19 vaccines be enhancing the evolution of variants/mutants that are more infectious and capable of spreading much faster and with greater lethality?
Are these COVID-19 vaccines sub-optimally priming the immune system for long-term skewed deranged responding?
Could the use of ‘imperfect’ sub-optimal vaccines enhance the progression of variants that place unvaccinated persons at elevated evolutionary risk of very severe illness, including death? Our children? Is this Marek 2.0?
Where are the safeguards when the proper studies were not done by the vaccine developers, and where is the FDA as the top regulator, in protecting the health and well-being of our children?
Dr. Janet Woodcock, as the head of the FDA, where are you in this? You could not be informed by the science, for there is none to support this grossly reckless and absurd push to vaccinate children.
What is going on here? This certainly is not “about the science.”
I challenge any public health official to sit down with me and my scientific colleagues and explain your science. Debate us. Show us what you are looking at to arrive at these very dangerous statements and decisions.
We may end up killing many children with these vaccines. In fact, not ‘we’, ‘you’ — Fauci and Walensky and Dr. Francis Collins — may end up killing many of our children.
Please stop this insanity, step back and focus on the vulnerable and elderly where there is risk. Leave the children alone!
“If the CDC, NIH, FDA (Walensky, Fauci, Collins, Marks, Woodcock), vaccine developers and all involved in these COVID vaccines, all the television medical experts, all who are absolved thanks to liability protection, if you feel so strongly that these are safe for our children, then do the right thing: Take liability protection off the table. Stand by the vaccine’s safety. Put some skin in the game — for as we speak, only our healthy children are carrying risk and I fear it could be potentially catastrophic for them.
Dr. Alexander is considered a global expert on COVID-19 generally and in some areas highly expertised. Dr. Alexander holds masters level study at York University Canada, a masters in epidemiology at University of Toronto, a masters in evidence-based medicine at Oxford and a doctorate in evidence-based medicine and research methods from McMaster University in Canada.
In my previousarticles I have highlighted how the Government and most of the media are concealing certain facts, altering previously established protocols or manipulating data that has the effect of deceiving the public. I try not to dwell on why. Whatever the reason there is something that needs to be addressed.
Every form of medical treatment has an element of risk and any new development in healthcare is to some degree experimental. Time will and does tell how successful and how risky a particular form of therapy is. The Covid vaccination strategy would be no different in that respect. Yet Government and media have, in their headlong, panic-stricken way resisted all attempts of cautious, sceptical and truly ethical scientific scrutiny. They fail to recognise any form of experimentation, any increased risk profile associated with a novel medical procedure or how time and trialling (of which the public are those undergoing the trials) help establish the safety of a particular procedure.
All this in the day of ‘defensive medicine‘ – a term sometimes used to describe a way of preventing patients from successfully suing their practitioners. But defensive medicine or dentistry can also protect the public if used genuinely for that specific purpose. All you need to do is practise fully informed consent where you are honest with your patient and explain the pros and cons clearly and freely in a way that doesn’t help steer the patient into a decision that is biased, for example by scaring the patient into electing no treatment or falsely reassuring the patient into accepting it. All that has gone out of the window with Covid. Similar safeguards are required for customers of pension and mortgage providers and gambling platforms for example – ‘your capital is at risk’, ‘the value of your investment is at risk’ etc. All these things are done to prevent the harms and scandals that are in the history books.
So by abandoning the safeguards and principles that had successfully been established pre-Covid, what would happen if things turned out not to be what the patient (the majority of the public in this case) were led to believe? What if the treatment they underwent proved to be more harmful than beneficial? This may not be the case with respect to the Covid vaccine, but what if it was?
How could the Government, healthcare profession and media ever come round to admitting possible culpability? What temptation might there be for all these interested parties, who have acted almost in complete unison, to try and avoid the possibility of being exposed for any wrongdoing? They would have so much to lose. They would be disgraced. They would be (rightly) sued. They would lose all trust and credibility. Could such possible malpractice put too high a price on any form of compunction and admission? Have all parties gone down a road that has no exit? Might they never let a form of confession or admission of liability occur? And how?
There needs to be much more public discussion on these questions. It’s the only way in future to protect the public because we have to face the reality that it is time that will and does tell the truth.
It is common knowledge that the British armed forces have been heavily involved in the conflicts of the last decades incited by the United States as they used their troops on a large scale in Iraq and Afghanistan, to name a few. Due to the US and UK military actions in those countries a lot of civilians died and their families and representatives vehemently demand justice for those guilty of war crimes.
Through Resolution 2391 (XXIII) dated November 26, 1968, the UN General Assembly adopted the Convention on the Non-Applicability of Statutory Limitations to War Crimes and Crimes Against Humanity. The rules aimed at protecting the victims of armed conflict, and placing restrictions on the methods and means of warfare, are spelled out in detail in international humanitarian law, which also defines the mechanisms for ensuring compliance with these rules.
However, the US and the UK have recently, and inexcusably, started to think of themselves as outside the scope of these international legal documents that they adopted themselves, and allow them to be ostensibly violated. Moreover, as evidenced by numerous testimony, including those published in Western media outlets, there is the increasing desire to cover up the war crimes that have been committed in recent decades in the Middle East and Afghanistan by US military service personnel, and some of its allies. Besides the efforts to shirk responsibility for the crimes committed through the use of such tactics, it has become increasingly evident that the US and UK military agencies have not properly monitored operations conducted by their combat units.
Thus, not only Arab, but also British media outlets have on multiple occasions reported the evidence that high-ranking British officials with the Ministry of Defense had been covering up the war crimes committed by UK military personnel in Iraq and Afghanistan for years. These outlets have reported on multiple occasions, in particular, about the war crimes involving personnel from elite British special forces, such as the SAS and Black Watch. On top of that, journalistic investigations found hard evidence of the falsification of documents; in these, premeditated killings and torture in Afghanistan and Iraq were dressed up as “Special Ops against terrorists” while inquiry into the committed crimes was stonewalled due to explicit political pressure. In this vein, on instructions of then UK Defense Secretary Michael Fallon all proceeding regarding these matters were dismissed even before they got to court. The investigation by the BBC and the Times reporters has clearly shown that evidence collection and production was prevented due to political reasons.
For example, The Sunday Times has provided evidence regarding the involvement of one British Special Air Service soldier in the killings, as well as the evidence of crimes committed by members of the Black Watch battalion, which is part of the Royal Regiment of Scotland, including beatings, torture, and sexual abuse. These actions alone are enough to be scrutinized in the International Criminal Court.
It is worth pointing out that in order to investigate the complaints lodged by Iraqis about the British military’s actions, an IHAT (Iraq Historic Allegations Team) investigative group was specifically established to examine hundreds of claims made by victims’ relatives. However, in January 2016, swayed by then British Prime Minister David Cameron, the UK Ministry of Defense announced that investigation into 57 criminal cases filed against the British military had been discontinued. Moreover, intentionally trying to downplay criminal acts the UK authorities suspended from legal practice solicitor Phil Shiner that had handed over to IHAT data about more than 1,000 instances of violence by the military. In an all-out attempt to obstruct the investigations concerning offenses committed by the British military, Boris Johnson, the incumbent head of the UK Cabinet, authored the corresponding bill on Overseas Operations allowing for the suspension of investigation.
In 2017, Supreme Court of the United Kingdom ruled that during their presence in Iraq British troops had breached the Geneva Conventions by committing pre-meditated murder, intentionally inflicting severe sufferings or grievous bodily harm, engaging in meaningless and large-scale destruction and appropriation of property (not warranted by military necessity), deliberate attacks on the civilian population as such or on individual civilians not directly involved in hostilities and offending human dignity including engagement in humiliating and degrading treatment.
Nonetheless, the Service Police Legacy Investigations (SPLI) dropped all cases related to UK service members alleged crimes committed between 2003 and 2009 in Iraq. None of 1,291 charges resulted in prosecutions or prison time. Iraqi civilians claims regarding the criminal behavior of British soldiers were considered by the police officers of the Royal Navy and the police of the Royal Air Force who were part of SPLI. As the UK Defense Secretary Ben Wallace stated on October 20 in the House of Commons, the SPLI “officially closed its doors”, and noted that the main problem in the activities of this structure was the “lack of evidence base”, while acknowledging that “some shocking and shameful incidents did happen in Iraq.” “We recognize that there were four convictions of UK military personnel for offences in Iraq including offences of assault and inhuman treatment.”
There is no doubt that such a decision by the SPLI was again clearly driven by the political interests of the current Johnson’s government, which is wary of an uptick in anti-government protests in the country amid growing public discontent with the performance and policies of the British authorities.
It is worth noting that the UK government has a lengthy track record of harboring war criminals for decades. Since 1948, the Malaysians have been unable to seek justice in a case of the Scots guards massacring residents in a village near the town of Batang Kali, where 24 people were killed for no reason. Moreover, these murderers even took memento photo by the victims bodies. However, the British authorities have not brought anyone to justice and have not even bothered to pay compensation to the relatives of those murdered more than 70 years ago…
Such British policies, and, especially efforts of the UK Ministry of Defense regarding the war crimes cover-up raises a lot questions for the UK authorities. As for the UN, International Committee of the Red Cross, International Criminal Court and many other human rights institutions, they have a duty to respond to such crimes despite the attempts by certain British political circles to hush up such criminal activities and shirk responsibility.
Safeway grocery store #1892 in Cortez, Colo., just lost its pharmacy manager because she no longer wants to administer “this poison,” referring to Wuhan coronavirus (Covid-19) “vaccines,” to customers.
According to reports, Nichole Belland took to the store’s intercom to announce that she is leaving her position for good because she can no longer in good conscience continue jabbing people with these “Operation Warp Speed” abominations they are calling “vaccines.”
“This is Nichole Belland, pharmacy manager for Safeway store at 1892 of Cortez,” Belland was heard saying over the intercom to a store full of surprised shoppers.
“I quit, effective immediately, because I will not give this poison to people. Wake up, everybody. This is poison. This is hurting people. I’ve seen it. I’ve seen customers die. Wake up, do not take it.”
If It Came Down To It, Would You Quit Your Job Rather Than Harm Others With Covid Jabs?
Steve Kirsh, the executive director of the COVID-19 Early Treatment Fund (CETF), got the chance to talk with Belland about what prompted her to leave her job in the dramatic way that she did.
It turns out that Belland had not worked at Safeway for several months prior to coming on the loudspeaker to make her announcement. Almost immediately after she was told by her supervisor that she would need to jab people with the “Operation Warp Speed” drugs, she decided to quit.
Belland was told at the time that she would have no choice but to administer the shots on demand, or else be fired from her position. She instead decided to go on temporary personal leave, but that was set to expire on October 15.
“I had tremendous concerns about these shots early on,” Belland says.
Not seeing any other way to get her message across before being forced out of her job, Belland went in on October 14, took her certificates and degrees off the wall, and proceeded to use the intercom to reveal publicly why she was essentially being forced to quit.
Belland says that around 8-10 customers were in front of her at the time when she picked up the intercom microphone and began speaking the truth into it. She had no idea that this brave act would end up going viral, possibly inspiring others who feel similarly to do the same.
Like many, Belland says that she is not necessarily “anti-vaccine.” She is anti-experimental gene therapy, which is technically what covid shots are since they were not developed using the same technologies as existing vaccines.
Prior to quitting, Belland had administered “thousands” of other shots to patients at her pharmacy, where she worked for 12 years after graduating from the University of Minnesota. However, when covid injections came along, it was a different story.
You can watch the full video interview between Kirsh and Belland at Red Voice Media.
“Bravo! Good for her, I would do the same thing if I was in her shoes!” wrote a commenter at Red Voice Media. “No job is more important than your overall health!”
“No job or any action is more important than the realization that you may be directly responsible for the injury or even death of another,” responded another, clarifying the reason why Belland quit.
“Every time a nurse who sticks a needle in someone’s arm who becomes ill or deceased later, and when on learning of their loss, she intentionally continues – is committing a premeditated harmful act to another.”
As the vaccine mandates pile on, we can expect more incidents like this to occur. More of the latest can be found at Pandemic.news.
Anthony Fauci’s National Institutes of Health once experimented on foster children with AIDS, testing experimental drugs on the children while almost always failing to provide an independent advocate to make sure the children remain safe and healthy. This happened throughout the late 1980s and 1990s, and the practice was exposed in 2005.
According to Anthony Fauci’s biography page on the official NIH website, the longest-serving government employee began working for the NIH in 1968. In 1984, Fauci became the Director of NIAID, a position he still holds today.
As Director of NIAID, Fauci oversees research to “prevent, diagnose, and treat infectious and immune-mediated diseases, including HIV/AIDS” according to the website. In 1988, Fauci became the first Director of the Office of AIDS research.
While Fauci was in these roles, it was revealed in 2005, the NIH oversaw the enrollment of thousands of foster children with AIDS into controversial programs that allowed them to receive experimental drugs designed to combat the illness. Some of these children later died, and most were not given independent advocates that were promised.
According to John Soloman, then reporting for the Associated Press, the NIH “promised in writing to provide an independent advocate to safeguard the kids’ well-being as they tested potent AIDS drugs,” however, these advocates failed to materialize for almost every child involved. The subjects – foster children without stable home lives – ranged from infants to late teens.
Solomon wrote that, with a general lack of oversight, “Several studies that enlisted foster children reported that patients suffered side effects such as rashes, vomiting and sharp drops in infection-fighting blood cells, and one reported a ‘disturbing’ higher death rate among children who took higher doses of a drug, records show.” (READ MORE: NIH Quietly Changes Definition Of ‘Gain-Of-Function’ Amid Fauci, Wuhan Lab Scandal Fallout)
“Some foster children died during studies,” reported Solomon after noting that the majority of children appear to not have received an advocate. “State or city agencies said they could find no records that any deaths were directly caused by the experimental treatments,” he noted.
A 2009 articlefromThe New York Times claims that no New York City children “died as a result of the trials” and that children in the city were not selected for the trials based on their race.
Still, the Times found “that the agency had not always followed its own protocols and kept poor records.” The Times also discovered that some of the children died, but those involved with the research asserted the deaths were unrelated to the experimental drugs.
In 2018, only two years before the mainstream media would lionize Fauci via its nonstop coverage of COVID-19, then-82-year-old AIDS activist Larry Kramer described Fauci as “The consummate manipulative bureaucrat who speaks out of too many sides of his mouth.’’ Kramer died in May of 2020.
We also know that Fauci was actively, personally engaged in AIDS research around the time the foster children were being used for experiments. In fact, Fauci told NPR earlier this year that, in the 1980s, he would clandestinely visit gay bath houses, bars, and night clubs with the goal of physically witnessing the transmission of HIV live and in person.
Data released Friday by the Centers for Disease Control and Prevention (CDC) showed that between Dec. 14, 2020, and Oct. 22, 2021, a total of 837,595 adverse events following COVID vaccines were reported to the Vaccine Adverse Event Reporting System (VAERS).
The data included a total of 17,619 reports of deaths — an increase of 491 over the previous week. There were 127,457 reports of serious injuries, including deaths, during the same time period — up 4,624 compared with the previous week.
Of the 8,068 U.S. deaths reported as of Oct. 22, 11% occurred within 24 hours of vaccination, 15% occurred within 48 hours of vaccination and 27% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 411.6 million COVID vaccine doses had been administered as of Oct. 15. This includes: 242 million doses of Pfizer, 154 million doses of Moderna and 15 million doses of Johnson & Johnson (J&J).
The data come directly from reports submitted to VAERS, the primary government-funded system for reporting adverse vaccine reactions in the U.S.
Every Friday, VAERS makes public all vaccine injury reports received as of a specified date, usually about a week prior to the release date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed.
Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
This week’s U.S. data for 12- to 17-year-olds show:
Another recent death includes a 15-year-old male who died six days after receiving his first dose of Pfizer’s COVID vaccine. According to his VAERS report (VAERS I.D. 1764974), the previously healthy teen complained of brief unilateral shoulder pain five days after receiving his COVID vaccine. The next day he played with two friends at a community pond, swung on a rope swing, flipped into the air, and landed in the water feet first. He surfaced, laughed and told his friends “Wow, that hurt!” He then swam toward shore underwater, as was his usual routine, but did not re-emerge.
An autopsy showed no external indication of a head injury, but there was a small subgaleal hemorrhage — a rare, but lethal bleeding disorder — over the left occiput. In addition, the boy had a mildly elevated cardiac mass, increased left ventricular wall thickness and small foci of myocardial inflammation of the lateral wall of the left ventricle with myocyte necrosis consistent with myocardial infarction.
58 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases
attributed to Pfizer’s vaccine.
539 reports of myocarditis and pericarditis (heart inflammation) with 531 cases attributed to Pfizer’s vaccine.
125 reports of blood clotting disorders, with all cases attributed to Pfizer.
This week’s U.S. VAERS data, from Dec. 14, 2020, to Oct. 22, 2021, for all age groups combined, show:
19% of deaths were related to cardiac disorders.
54% of those who died were male, 41% were female and the remaining death reports did not include gender of the deceased.
FDA grants Emergency Use Authorization for Pfizer Vaccine for 5- to 11-year-olds
The U.S. Food and Drug Administration (FDA) today granted Emergency Use Authorization (EUA) for the Pfizer-BioNTech COVID vaccine for children 5 to 11 years old, The Associated Press reported.
The announcement followed Tuesday’s recommendation by the FDA’s vaccine advisory committee that the agency grant Pfizer’s request. The advisory committee vote passed with 17 in support, and one abstention.
“The vaccine was not granted FDA approval, but instead an emergency use authorization. Emergency authorizations are used when the secretary of health and human services has declared a public health emergency to more quickly clear the use of vaccines, treatments, and diagnostic tests. These authorizations lapse when the state of emergency ends. Pfizer’s vaccine was fully approved for those age 16 and older in August, and was previously granted an emergency use authorization for use in adolescents ages 12 to 15.”
The dose for younger children will be one-third the strength given to people 12 and older, with two shots given three weeks apart. Before the shots can be rolled out, the CDC must weigh in with its own recommendations.
Based on CDC data presented during the meeting, among children 5 to <12 years of age, there have been approximately 1.8 million confirmed and reported COVID cases since the beginning of the pandemic, and only 143 COVID-related deaths in the U.S. through Oct. 14.
Pfizer provided safety data on two study cohorts of children ages 5 to 11, both of roughly equal size. The first group was followed for only about two months, the second for only two-and-a-half weeks.
Pfizer said “post-vaccination myocarditis/pericarditis” in participants 5 to <12 years of age will not be studied until after the vaccine is authorized for children.
Pfizer vaccine ‘failed any reasonable risk-benefit calculus in connection with children,’ scientist says Brian Dressen, Ph.D., is one of the scientists who testified Tuesday during the FDA advisory committee’s 8-hour hearing. Dressen is also the husband of Brianne Dressen, who in 2020 developed a severe neurological injury during the Utah-based portion of the U.S. AstraZeneca COVID vaccine.
During his 3-minute testimony, Dressen, a chemist with an extensive background in researching and assessing the degree of efficacy in new technologies, told the FDA advisory panel Pfizer’s vaccine “failed any reasonable risk-benefit calculus in connection with children.”
Dressen said the decision to authorize for 5- to 11-year-olds is being rushed and is based on “incomplete data from underpowered trials, insufficient to predict rates of severe and long-lasting adverse reactions.”
Dressen urged the committee to reject the EUA modification and direct Pfizer to perform trials that decisively demonstrate the benefits outweigh the risks for children.
Dressen’s wife was severely injured last November after receiving her first and only dose of a COVID vaccine administered during a clinical trial.
“Because study protocol requires two doses, she was dropped from the trial, and her access to the study app deleted,” Dressen said. “Her reaction is not described in the recently released clinical trial report — 266 participants are described as having an adverse event leading to discontinuation, with 56 neurological reactions tallied.”
CDC updates guidance allowing immunocompromised to get a fourth COVID shot
Immunocompromised adults who received a third dose of either the Pfizer-BioNTech or Moderna COVID vaccine will become eligible for a fourth booster shot six months after receiving their third dose, according to CDC guidance issued Monday.
“In such situations, people who are moderately and severely immunocompromised may receive a total of four vaccine doses,” with the fourth coming at least six months after the third, the CDC’s new guidelines said.
However, a third dose is now considered part of the primary series, rather than a booster. The earliest that immunocompromised people who received a third mRNA vaccine shot can get a fourth shot as a booster would be February.
The agency said people could select that booster from any of the three COVID vaccines available in the U.S, including J&J, but specified a fourth dose of Moderna’s vaccine should be half the size of a normal dose.
Double-vaccinated can still spread the virus at home
Fully vaccinated people are catching COVID and passing it on to those they live with, warn experts in the UK. A British study published in the Lancet Oct. 29, showed individuals who have had two vaccine doses can be just as infectious as those who have not been jabbed.
Even if they are asymptomatic or have few symptoms, the chance of transmitting the virus to other unvaccinated housemates is about two in five, or 38%. This drops to one in four, or 25%, if housemates are also fully vaccinated.
“By carrying out repeated and frequent sampling from contacts of COVID-19 cases, we found that vaccinated people can contract and pass on an infection within households, including to vaccinated household members,” said Dr. Anika Singanayagam, co-lead author of the study.
“Our findings provide important insights into … why the Delta variant is continuing to cause high COVID-19 case numbers around the world, even in countries with high vaccination rates.
Vaccinated contacts who tested positive for COVID on average received their shots longer ago than those who tested negative, which the authors said was evidence of waning immunity and supported the need for booster shots.
Neil Ferguson, an Imperial epidemiologist, said the transmissibility of Delta meant that it was unlikely Britain would reach herd immunity for long.
“That may happen in the next few weeks: If the epidemic’s current transmission peaks and then starts declining, we have by definition in some sense reached herd immunity, but it is not going to be a permanent thing,” Ferguson told reporters.
16-year-old girl develops severe vulvar ulcers after second Pfizer shot
According to the report, a 16-year-old non-sexually active female presented to the pediatric gynecology clinic with vaginal pain six days after receiving her second dose of Pfizer’s COVID vaccine.
Within 24 hours of receiving the vaccine, the girl developed fever, fatigue, myalgias and “sores” in her vaginal area. Over the next two days, right-sided lesions in her vaginal area coalesced and became more painful. The teen went to the urgent care with a fever of 105 degrees. She was diagnosed with a Bartholin gland abscess.
Despite antibiotic therapy, her symptoms worsened and her lesions were covered in exudate with a necrotic, ring-like border. In the gynecology clinic, the patient’s lesions were exquisitely painful, resulting in difficulty with urination, defecation and walking. She had no respiratory symptoms and no history of COVID exposure.
The report said the findings “were consistent with vulvar aphthous ulcers in association with influenza-like symptoms following Pfizer BioNTech (BNT162b2) COVID-19 vaccination.”
“Our patient had typical clinical features of aphthous ulcer, including an influenza-like prodrome and characteristic dermatologic manifestations which occurred after receiving the Pfizer COVID vaccine,” the authors wrote. According to the report, the girl’s case was submitted to VAERS “due to the temporal relationship with COVID vaccine administration.”
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
In early 2020, as scientists were analyzing the SARS-CoV-2 virus, it was theorized the virulence and infectivity could be explained by gain-of-function research. Months of lab analyses and political arguments ensued over whether the virus was leaked from the lab or developed naturally in the wild.
Despite public outcry and denials from top health experts that the virus was created, the preponderance of the evidence indicates the virus was manipulated in the lab.1 Then, the United States Agency for International Development (USAID), publicly announced October 5, 2021, they would grant Washington State University $125 million “to detect emerging viruses.”2
This is far greater than the $7.4 million Newsweek 3 reported was granted to the NIAID for gain-of-function work on bat coronavirus in Wuhan, China. Dr. Kanta Subbarao is from the Laboratory of Infectious Disease at the National Institute of Allergy and Infectious Diseases (NIAID) at the National Institutes of Health (NIH).4
According to Subbarao, these experiments “are routine virological methods” and “emphasized that such experiments in virology are fundamental to understanding the biology, ecology and pathogenesis of viruses and added that much basic knowledge is still lacking for SARS-CoV and MERS-CoV.”
Historically, the NIH had funded gain-of-function research, but this was paused in October 2014. December 19, 2017, the NIH announced they would lift the funding pause on gain-of-function research and stated:5
“We have a responsibility to ensure that research with infectious agents is conducted responsibly, and that we consider the potential biosafety and biosecurity risks associated with such research.”
As Newsweek reported, the “second phase of the project, beginning that year [2019], included additional surveillance work but also gain-of-function research for the purpose of understanding how bat coronaviruses could mutate to attack humans. The project was run by EcoHealth Alliance, a nonprofit research group, under the direction of president Peter Daszak.”6
After months of public and political debate, argument and division, the U.S. government agency USAID stepped into the spotlight again and awarded millions to a university “to make sure the world is better prepared.”7
University Accepts $125 Million for Gain-of-Function Research
Washington State University published a press release8 October 5, 2021, announcing they had been awarded $125 million from USAID. Called a “cooperative agreement,” the university is heading up a new five-year global project in which they have been asked to9 “… detect and characterize unknown viruses which have the potential to spill over from wildlife and domestic animals to human populations.”
The project will partner with 12 countries throughout Africa, Latin America and Asia. The idea is to carry out animal surveillance within the country’s borders using their facilities. USAID announced the project “to detect unknown viruses with pandemic potential” as part of Discovery & Exploration of Emerging Pathogens Viral Zoonoses (DEEP VZN).10
The organization believes that SARS-CoV-2 has demonstrated how infectious diseases threaten society. This is especially true of viruses that have been manipulated to increase virulence and infectivity in humans.11 The goal of the project is to collect over 800,000 samples over five years from wildlife and then determine the zoonotic potential of these viruses.12
“The project will focus on finding previously unknown pathogens from three viral families that have a large potential for viral spillover from animals to humans: coronaviruses, the family that includes SARS-CoV-2 the virus that causes COVID-19; filoviruses, such as the Ebola virus; and paramyxoviruses which includes the viruses that cause measles and Nipah.”
Ebola virus was first discovered in 1976 and has since led to several deadly outbreaks in African countries. The CDC13 writes that scientists do not know where Ebola virus comes from. However, the virus can spread through direct contact with body fluids and tissues of infected animals.
Nipah was first discovered in 199914 and the first outbreak resulted in 300 human cases and more than 100 deaths. The animal host is believed to be the fruit bat that can spread the disease to animals and humans. The infection also spreads from person to person and can range from mild to severe. Up to 70% of those infected between 1998 and 2018 have died.
The project expects to find between 8,000 a nd 12,000 new viruses, “which researchers will then screen and sequence the genomes of the ones that pose the most risk to animal and human health.”15 In case this sounds familiar, as Breaking Points anchor emphasizes, this has been “code” for gain-of-function research,16 or detecting viruses that have not yet “emerged.”
Documents Reveal Virus Was Manipulated to Increase Virulence
An ongoing Freedom of Information Act litigation brought by The Intercept17 against the NIH resulted in the release of over 900 pages of previously undisclosed documents that detailed the work of EcoHealth Alliance as a subcontractor of gain-of-function research on bat coronavirus through the Wuhan Institute of Virology.
It’s important to note that the moratorium on federal funding of gain-of-function research instituted in 2014 was initiated on the heels of a high-profile lab mishap at the CDC and controversial experiments over deadly bird flu virus that was manipulated to be more contagious.18
Reportedly, the goal was to determine if bird flu could mutate in the wild and start a pandemic. David Relman, a microbiologist from Stanford University, stated the obvious when he said,19 “I don’t think it’s wise or appropriate for us to create large risks that don’t already exist.”
The new documents released under the FOIA request by The Intercept contained previously unpublished proposals by the NIAID and updates to the EcoHealth Alliance’s research. As reported in The Intercept,20
“The documents contain several critical details about the research in Wuhan, including the fact that key experimental work with humanized mice was conducted at a biosafety level 3 lab at Wuhan University Center for Animal Experiment — and not at the Wuhan Institute of Virology, as was previously assumed.
The documents raise additional questions about the theory that the pandemic may have begun in a lab accident, an idea that Daszak has aggressively dismissed.”
According to The Intercept, Richard Ebright, molecular biologist at Rutgers University, also reviewed the documents released in the FOIA. He told The Intercept that the documents contained vital Information about the research being conducted in the Wuhan lab. He wrote:21
“The viruses they constructed were tested for their ability to infect mice that were engineered to display human type receptors on their cell. While they were working on SARS-related coronavirus, they were carrying out a parallel project at the same time on MERS-related coronavirus.”
In other words, the lab was doing parallel research on two types of coronaviruses that were able to infect humanized mice. In a series of posts on Twitter, Ebright goes on to say:22
“The materials further reveal for the first time that one of the resulting novel, laboratory-generated SARS-related coronaviruses — one not been previously disclosed publicly — was more pathogenic to humanized mice than the starting virus from which it was constructed … and thus not only was reasonably anticipated to exhibit enhanced pathogenicity, but, indeed, was *demonstrated* to exhibit enhanced pathogenicity.
The documents make it clear that assertions by the NIH Director, Francis Collins, and the NIAID Director, Anthony Fauci, that the NIH did not support gain-of-function research or potential pandemic pathogen enhancement at WIV are untruthful.”
This new information again questions the origins of COVID-19, which many scientists proposed was from a wet market in China where humans and animals are in close contact. However, bioscience safety experts have long suspected a lab origin. It appears that some in the U.S. government and some scientists have not learned from the gain-of-function research in Wuhan and have brought the problem home to roost.
International Athletes Willfully Exposed to Lab-Leaked Virus
Whether the virus was released intentionally or accidentally is a question for another day. Long before the outbreak, scientists had expressed concerns that these kinds of experiments may end up creating the thing they were reportedly working against. As the Intercept reports,23 in 2014 a grant was awarded to EcoHealth Alliance titled “Understanding the Risk of Bat Coronavirus Emergence.”
Part of the grant money was earmarked to identify and alter bat coronaviruses suspected of being able to infect humans. In the grant the writers acknowledged concerns stating, “Fieldwork involves the highest risk of exposure to SARS or other CoVs, while working in caves with high bat density overhead and the potential for fecal dust to be inhaled.”24
In the USAID announcement, the government agency gives an overview of the goals in one sentence:25 “The Biden-Harris Administration is committed to advancing global health security, international pandemic preparedness and global health resilience.” As a Breaking Points anchor in this video says,26 “So essentially, we have learned nothing.”
August 1, 2021, Rep Michael McCaul, R-Texas, the ranking member of the House Foreign Affairs committee, published an addendum to the investigation into the origins of SARS-CoV-2. The investigation concluded:27
“… the preponderance of evidence suggests SARS-CoV-2 was accidentally released from a Wuhan Institute of Virology laboratory sometime prior to September 12, 2019. The virus, or the viral sequence that was genetically manipulated, was likely collected in a cave in Yunnan province, PRC, between 2012 and 2015.
Researchers at the WIV, officials within the CCP, and potentially American citizens directly engaged in efforts to obfuscate information related to the origins of the virus and to suppress public debate of a possible lab leak.”
By the end of August 2021, the White House released a statement from President Biden essentially calling the intelligence report inconclusive,28 “while this review has concluded, our efforts to understand the origins of this pandemic will not rest.”
Multiple pieces of information led the committee to conclude there was ample evidence to support genetic modification of the coronavirus and there was a cover-up which “likely turned what could have been a local outbreak into a global pandemic.”29 The cover-up involved the 2019 Military Games held October 18, 2019, in Wuhan China.
The report demonstrated that by October 2019, health officials in Wuhan were well aware of an outbreak of infectious disease. The athletes reported that the city appeared to be in lockdown30 while they were there. The games drew over 9,000 athletes from 109 countries. The Chinese government had 236,000 volunteers, 90 hotels, three railroad stations and more than 2,000 drivers available for the athletes.
The report included a quote from a Canadian Armed Forces personnel who participated in the games, which appeared in The Financial Post.31 He was told the lockdown in the city was to make it easier for the participants in the games to get around. Twelve days after arrival in Wuhan, he was sick with fever, chills, vomiting and insomnia.
He reported that on the flight home to Canada, 60 athletes were isolated at the back of the plane for the 12-hour flight with a range of symptoms including coughing and diarrhea. After returning home, the same service member found his family members got ill, which the report finds is:32
“… consistent with both human-to-human transmission of a viral infection and COVID-19. Similar claims about COVID-19 like symptoms have been made by athletes from Germany, France, Italy, and Sweden.”
Funding Gain-of-Function Research Out in the Open
Following the release of The Intercept report and additional grant documentation, some GOP members are calling for Dr. Anthony Fauci to resign while others want him fired from his position on the White House COVID-19 response team.33
U.S. Sen. Rand Paul, R-Ky. has referred Fauci to the Department of Justice for an investigation for possible perjury charges relating to his Congressional testimony in May 202134 and July 2021,35 when he vehemently denied ever having funded gain-of-function research.
Paul specifically asked the DOJ36 to investigate whether Fauci violated 18 U.S. Code § 10012137 — which makes it a federal crime to make “any materially false, fictitious or fraudulent statement or representation” as part of “any investigation or review” conducted by Congress — or any other statute.
How much genetic manipulation and gain-of-function research that occurs as a result of the $125 million grant to the university may not come to light for years. However, it is incumbent on our government to ensure biosafety in the labs doing the research and, for the public, to call for a halt of this type of research that “create[s] large risks that don’t already exist.”38
An FDA vaccine advisory panel on Tuesday voted unanimously 17-0 in favor shooting up kids aged 5-11 with Pfizer’s experimental mRNA injection with panelist Dr Eric Rubin stating, “we’re never going to learn about how safe this vaccine is unless we start giving it.”
The panel voted in favor of experimenting on tens of millions of helpless children with zero long-term data on side effects because 94 children between 5 and 11 have died with COVID-19 (they claimed “of”) and “all have names. All of them had mothers,” to quote the emotional gobbledegook uttered by panelist Patrick S. Moore.
“To me, it seems that it is a hard decision but a clear one,” said Patrick S. Moore, a University of Pittsburgh microbiologist and committee member. He noted that 94 children between 5 and 11 have died of covid-19, and “all have names. All of them had mothers.”
Members of the FDA’s vaccine-advisory panel supported Moderna’s booster dose even though the evidence for it was from a small study and had mixed results.
“It’s more a gut feeling rather than based on really truly serious data,” said Patrick Moore, a member of the committee and a professor of molecular genetics and biochemistry at the University of Pittsburgh School of Medicine. “The data itself is not strong, but it is certainly going in the direction that is supportive of this vote.”
On February 13, 1960, France carried out its first nuclear test in Algeria’s southern Reggane region. According to official statistics, 17 nuclear tests were carried out in total over the next 6 years. The area remains affected, and local scientists say that radioactive contamination has caused genetic mutations and irreversibly changed the region.
There are no official statistics on the number of victims. The only figures can be found in the records kept by the French representative of the local church, which lists 42,000 victims of nuclear tests. Three years ago, the French Ministry of Defense issued a statement, putting the number at 27,000 people. The victims include French soldiers as well as local Algerians who lived in the surrounding areas. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.


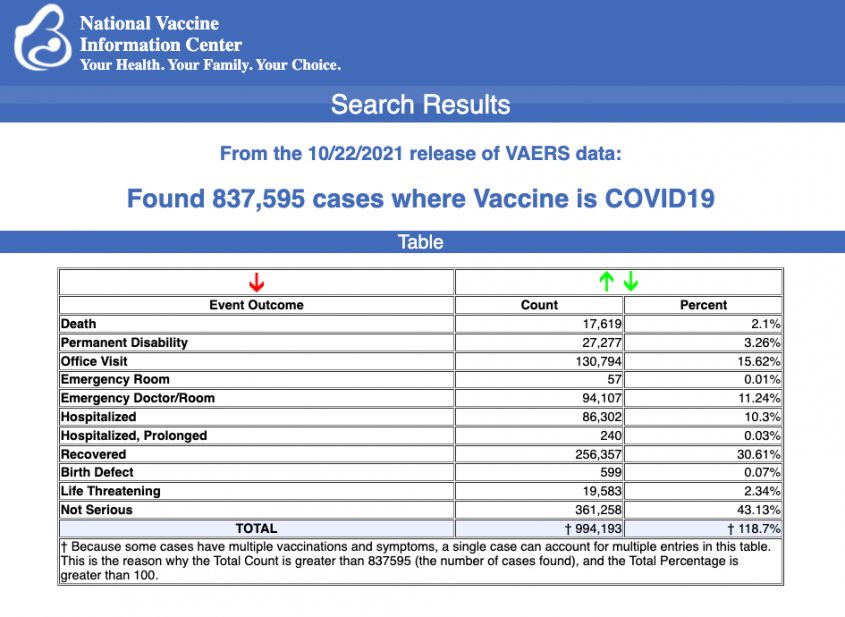
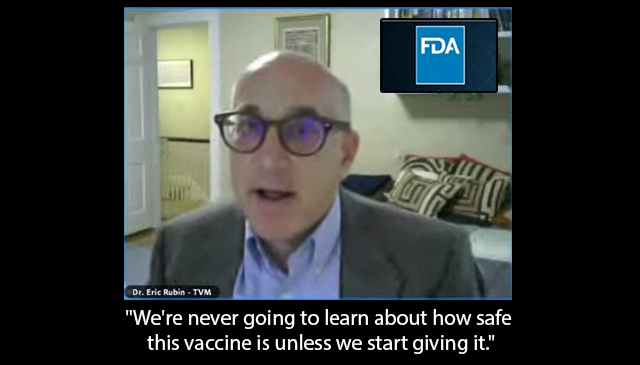

 Aletho News

