Mortality data tells us information about deaths in Australia and is usually released every 6 weeks. For an unexplained reason, the latest data is over 15 weeks overdue.
As Government becomes more and more powerful, anyone who challenges the current policies is smeared and censored. The legacy media happily parrots the propaganda, afraid of losing government funding.
Unreliable, intermittent wind and solar energy will leave Australian families sitting in the dark without coal-fired power to back them. ‘Renewables’ only farm taxpayer money, not energy.
Where to even begin with the FDA’s preposterous risk-benefit analysis of Pfizer’s mRNA COVID-19 “vaccine” in children ages 5 to 11?
Let’s start with my bona fides. I have a year of undergraduate statistics at one of the best liberal arts colleges in America (Swarthmore). I have a year of graduate statistics at the masters program rated #1 for policy analysis (UC Berkeley). And I have a Ph.D. in political economy from one of the top universities in the world (University of Sydney). My research focus is on corruption in the pharmaceutical industry so I’ve read scientific studies in connection with vaccines nearly every day for 5 years. Earlier in my career I worked professionally tearing apart shoddy cost-benefit analyses prepared by corporations that were trying to get tax breaks, contracts, and other concessions from local government. Suffice it to say I’ve thought a lot about risk-benefit analysis and I’m better equipped than most to read one of these documents.
The FDA’s risk-benefit analysis in connection with Pfizer’s Emergency Use Authorization (EUA) application to inject children ages 5 to 11 with their COVID-19 vaccine is one of the shoddiest documents I’ve ever seen.
Let’s take it from the top:
🚩 COVID-19 rates in children ages 5 to 11 are so low that there were ZERO cases of severe COVID-19 and ZERO cases of death from COVID in either the treatment (n= 1,518) or control group (n= 750). So any claims you see in the press about the Pfizer vaccine being “90% effective” in children are meaningless because they are referring to mild cases from which children usually recover quickly (and then have robust broad spectrum immunity). So there is literally no emergency in this population for which one could apply for Emergency Use Authorization. Pfizer’s application should be dead on arrival if the FDA actually followed the science and their own rules. We will return to this topic below.
🚩 Pfizer’s clinical trial in kids was intentionally undersized to hide harms. This is a well known trick of the pharmaceutical industry. The FDA even called them out on it earlier this summer and asked Pfizer to expand the trial and Pfizer just ignored them because they can. (Pfizer fudged it by importing data from a different study but this other study only monitored adverse outcomes for 17 days so if anything the new data polluted rather than clarified outcomes). To put it simply, if the rate of particular adverse outcome in kids as a result of this shot is 1 in 5,000 and the trial only enrolls 1,518 in the treatment group then one is unlikely to spot this particular harm in the clinical trial. Voilà “Safe & Effective(TM)”.
🚩 Pfizer only enrolled “participants 5-11 years of age without evidence of prior SARS-CoV-2 infection.” Does the Pfizer mRNA shot wipe out natural immunity and leave one worse-off than doing nothing as shown in this data from the British government? Pfizer has no idea because children with prior SARS-CoV-2 infection were excluded from this trial. This was by design. Toxic polluters have learned to not ask questions that they do not want the answers to, lest they wind up staring at their own smoking gun in a future court case.
“What the British are saying is they are now finding the vaccine interferes with your body’s innate ability after infection to produce antibodies against not just the spike protein but other pieces of the virus. Specifically, vaccinated people don’t seem to be producing antibodies to the nucleocapsid protein, the shell of the virus, which are a crucial part of the response in unvaccinated people. This means vaccinated people will be far more vulnerable to mutations in the spike protein EVEN AFTER THEY HAVE BEEN INFECTED AND RECOVERED ONCE (or more than once, probably). It also means the virus is likely to select for mutations that go in exactly that direction because those will essentially give it an enormous vulnerable population to infect. And it probably is still more evidence the vaccines may interfere with the development of robust long-term immunity post-infection.”
🚩 Did Pfizer LOSE CONTACT with 4.9% of their clinical trial participants? The FDA risk-benefit document states: “Among Cohort 1 participants, 95.1% had safety follow-up ≥2 months after Dose 2 at the time of the September 6, 2021 data cutoff.” So what happened with those 4.9% who did not have safety follow-up 2 months after Dose 2? Were they in the treatment or control group? We have no idea because Pfizer isn’t saying. Given the small size of the trial, failing to follow up with 4.9% of the participants potentially skews the results.
🚩 The follow up period was intentionally too short. This is another well-know trick of the pharmaceutical industry designed to hide harms. Cohort 1 appears to have been followed for 2 months, cohort 2 was only monitored for adverse events for 17 days. Many harms from vaccines including cancer and autoimmune disorders take much longer to show up. As the old saying goes, “you can have it quick or you can have it done right, but you cannot have both.” Pfizer chose quick.
🚩 The risk-benefit model created by the FDA only looks at one known harm from the Pfizer mRNA shot — myocarditis. But we know that the real world harms from the Pfizer mRNA shot go well beyond myocarditis and include anaphylaxis, Bell’s Palsy, heart attack, thrombocytopenia/ low platelet, permanent disability, shingles, and Guillain-Barré Syndrome (GBS) to name a few. Cancer, diabetes, endocrine disruption, and autoimmune disorders may show up later. But the FDA does not care about any of that because they have a vaccine to sell so they just ignore all of those factors in their model.
🚩 Pfizer intentionally wipes out the control group as soon as they can by vaccinating all of the kids who initially got the placebo. They claim that they are doing this for “ethical reasons”. But everyone knows that Pfizer’s true aim is to wipe out any comparison group so that there can be no long term safety studies. Wiping out the control group is a criminal act and yet Pfizer, Moderna, J&J, and AZ do this as standard practice with the blessing of the FDA/CDC.
🚩 Given all of the above, how on earth did the FDA claim any benefits at all from this shot? You should probably sit down for this part because it’s a doozy! Here’s the key sentence:
Vaccine effectiveness was inferred by immunobridging SARS-CoV-2 50% neutralizing antibody titers (NT50, SARS-CoV-2 mNG microneutralization assay).
Wait, what!? I’ll explain. There were ZERO cases of severe COVID-19 in the clinical trial of children ages 5 to 11. So Pfizer and the FDA just ignored all of the actual health outcomes (they had to, there is no emergency, so the application is moot). INSTEAD Pfizer switched to looking at antibodies in the blood. In general, antibodies are a poor predictor of immunity. And the antibodies in the blood of these 5 to 11 year old children tell us nothing because again, there were zero cases of severe COVID-19 in this study (none in the treatment group, none in the control group). So Pfizer had to get creative! What they came up with is “immuno-bridging”. Pfizer looked at the level of antibodies in the bloodwork of another study, this one involving people 16 to 25 years old, figured out the level of antibodies that seems to be protective in that population, then figured out how many kids ages 5 to 11 had similar levels of antibodies in their blood, and then came up with a number for how many cases, hospitalizations, ICU admissions, and deaths would be prevented by this shot in the 5 to 11 population in the future, based on the antibody levels and health outcomes from the 16 to 25 year old population. If your head hurts from that tortured logic, it should, because such chicanery is unprecedented in a risk-benefit analysis.
So when the FDA uses this tortured logic at the beginning of their briefing document, all of the calculations that stem from this will be flat out wrong. Not just wrong but preposterous and criminally wrong.
The whole ballgame comes down to Table 14 on page 34 of the FDA’s risk-benefit document. And there the red flags come fast and furious.
🚩 The FDA model only assesses the benefits of vaccine protection in a 6-month period after completion of two doses. Furthermore it assumes constant vaccine efficacy during that time period. This is problematic on several counts.
First, reducing mild cases in children is not a desired clinical outcome. As Dr. Geert Vanden Bossche points out, mass vaccination turns kids into shedders of more infectious variants.
“Under no circumstances should young and healthy people be vaccinated as it will only erode their protective innate immunity towards Coronaviruses (CoV) and other respiratory viruses. Their innate immunity normally/ naturally largely protects them and provides a kind of herd immunity in that it dilutes infectious CoV pressure at the level of the population, whereas mass vaccination turns them into shedders of more infectious variants. Children/ youngsters who get the disease mostly develop mild to moderate disease and as a result continue to contribute to herd immunity by developing broad and long-lived immunity. If you are vaccinated and get the disease, you may develop life-long immunity too but why would you take the risk of getting vaccinated, especially when you’re young and healthy? Firstly, there is the risk of potential side effects; secondarily, there is the ever increasing risk that your vaccinal antibodies will no longer be functional while still binding to the virus, thereby increasing the likelihood of ADE or even severe disease….”
Second, we know that vaccine efficacy in the month after the first dose is negative because it suppresses the immune system and it begins to wane after 4 months so all of the FDA’s estimates of vaccine efficacy are inflated.
Third, the harms of myocarditis from these shots will likely unfold over the course of years. Robert Malone, the inventor of mRNA technology notes that the FDA is admitting that children will be injected twice a year forever (hence the six month time frame in the FDA risk-benefit model). But the risks of “adverse events such as cardiomyopathy will be cumulative.” So any model that only looks at a six month time frame is hiding the true adverse event rate.
🚩 The FDA/Pfizer play fast and loose with their estimates of myocarditis. First they estimate “excess” (read: caused by the shot) myocarditis using data from the private “Optum health claim database” instead of the public VAERS system (p. 32). So it’s impossible for the public to verify their claims. Then, when it comes to estimating how many children with vaccine-induced myocarditis will be hospitalized and admitted to the ICU they use the Vaccine Safety Datalink (see page 33). Why switch to a different database for those estimates? Finally, there is no explanation for how they calculated “excess” myocarditis deaths, so they just put 0. Red flag, red flag, red flag.
The FDA estimates that there will be 106 extra myocarditis cases per 1 million double-jabbed children 5-11. There are 28,384,878 children ages 5 to 11 in the U.S. The Biden administration wants to inject Pfizer mRNA shots into all of them and has already purchased enough doses to do just that (even though only 1/3rd of parents want to jab their kids with this shot). So (if the Biden administration has its way) 106 excess myocarditis cases per 1 million x 28.38 million people would be 3,009 excess myocarditis cases post-vaccination if the Pfizer vaccine is approved.
And over the course of several years many of those children will die.
Dr. Anthony Hinton (“Consultant Surgeon with 30 years experience in the NHS”) points out that myocarditis has a 20% fatality rate after 2 years and a 50% fatality rate after 5 years:
Viral myocarditis results in 2 in 10 people dead after 2 years and 5 in 10 after 5 years. It’s not mild. It’s dead heart muscle. https://t.co/ixRmk48rja
So the FDA has it exactly backwards — they want to prevent mild COVID in children which reduces herd immunity and they just flat out lie about the harms from myocarditis.
I’ve taken the liberty to correct the FDA’s Table 14 with actual real world data and extended it over 5 years. It looks like this:
A study by Harvard Pilgrim Healthcare for the U.S. Department of Health and Human Services estimated that VAERS only captured 1% of actual vaccine injuries. Steve Kirsch has done elaborate modeling that puts the Under-Reporting Factor of COVID-19 vaccine deaths at 41 (so multiply the above numbers by 41). And myocarditis is just one of a multitude of possible harms from COVID-19 vaccines. Dr. Jessica Rose recently calculated an Under-Reporting Factor of 31 for all severe adverse events following vaccination.
Conclusion
The Pfizer vaccine fails any honest risk-benefit assessment in connection with its use in children ages 5 to 11. The FDA’s risk-benefit analysis of Pfizer’s mRNA vaccine in children ages 5 to 11 is shoddy. It used tortured logic (that would be rejected by any proper academic journal) in order to reach a predetermined result that is not based in science. The FDA briefing document is a work of fiction and it must be withdrawn immediately. If the FDA continues with this grotesque charade it will cause irreparable harms to children and the FDA leadership will one day be prosecuted for crimes against humanity.
The U.S. Food and Drug Administration’s (FDA) advisory committee today endorsed Pfizer’s COVID vaccine for children ages 5 to 11, despite strong objections raised during the meeting by multiple scientists and physicians.
The vote passed with 17 supporting it and one abstention.
Before the shots can be rolled out, the FDA will have to formally authorize the vaccine, and the Centers for Disease Control and Prevention (CDC) must also weigh in with its own recommendations — but the Biden administration’s announcement last week that it has already ordered 68 million doses of the pediatric vaccine suggests Pfizer’s request will sail through.
According to the FDA website, as of Oct. 25, the agency had received 139,470 comments from the public prior to today’s meeting — a number federal officials described as strikingly high.
As he opened the meeting, Dr. Peter Marks, director of the FDA’s Center for Biologics Evaluation and Research (CBER), said, “I want to acknowledge the fact that there are strong feelings that have clearly been expressed by members of the public both for and against” authorization.
The dose for younger children would be one-third the strength given to people 12 and older, with two shots given three weeks apart.
Based on CDC data presented during the meeting, among children 5 to <12 years of age, there have been approximately 1.8 million confirmed and reported COVID cases since the beginning of the pandemic, and only 143 COVID-related deaths in the U.S. through Oct. 14.
In this same age group, there were 8,622 COVID-related hospitalizations through Sept 18.
“This translates to cumulative incidence rates of approximately 6,000 and 30 per 100,000 for confirmed COVID cases and COVID-related hospitalizations, respectively, among children 5 to <12 years of age,” Pfizer’s application said.
Children with underlying medical conditions, such as asthma, diabetes and obesity, made up two-thirds of severe COVID cases.
Pfizer provided safety data on two study cohorts of children ages 5 to 11, both of roughly equal size. The first group was followed only for about two months, the second for only two-and-a-half weeks.
The two-month cohort included 2,268 children ages 5 to 11. Of the 2,268 children, 1,518 received the vaccine and 750 received a placebo. Each received two shots spaced three weeks apart.
Pfizer’s study found its vaccine was about 91% effective against symptomatic COVID in children, based on 16 cases of COVID in the placebo group and three cases in the vaccinated group over the brief follow-up period.
Most side effects occurred within a couple of days and included pain at the injection site, fatigue, headache, muscle pains and chills, Pfizer said.
According to Pfizer, the number of participants in the current clinical development program was “too small to detect any potential risks of myocarditis associated with vaccination.”
Long-term safety of Pfizer’s COVID-19 vaccine “to evaluate long-term sequelae of post-vaccination myocarditis/pericarditis” in participants 5 to <12 years of age will not be studied until after the vaccine is authorized for children,” Pfizer’s application noted.
Pfizer data insufficient, kids’ risk of vaccine injury greater than COVID risk, experts say
Experts raised concerns over the lack of safety and efficacy data presented by Pfizer for use of its COVID vaccine in younger children, and they pointed to increasing safety signals based on reports to the Vaccine Adverse Event Reporting System (VAERS).
They also questioned the need to vaccinate children — whose risk of dying from COVID is “almost nil” — at all.
According to Dr. Meryl Nass, member of the Children’s Health Defense Scientific Advisory Panel, Pfizer once again did not use all of the children who participated in the trial in their safety study.
“Three thousand children received Pfizer’s COVID vaccine, but only 750 children were selectively included in the company’s safety analysis,” Nass said. “Studies in the 5-11 age group are essentially the same as the 12-15 group — in other words, equally brief and unsatisfying, with inadequate safety data and efficacy data, with no strong support for why this type of immuno-bridging analysis is sufficient.”
Nass said, “All serious adverse events were considered unrelated to the vaccine.”
During the meeting and in its FDA application, Pfizer argued children should be vaccinated to prevent SARS-CoV-2 transmission, yet the company did not assess asymptomatic transmission.
Dr. Ofer Levy, a VRBPAC member, asked for evidence that Pfizer’s vaccine prevents transmission.
Dr. William Gruber, senior vice president of Pfizer Vaccine Clinical Research and Development, said they did not assess whether the vaccine prevents transmission, but said there is evidence the vaccine prevents transmission in adults.
When questioned further, Gruber was unable to cite specific evidence to back his assertion.
Steve Kirsch, founder of the COVID-19 Early Treatment Fund, asked the panel how they could do a risk-benefit analysis with Pfizer’s COVID vaccine if they did not know the CDC’s VAERS under-reporting factor (URF).
Kirsch asked:
“How can you do a risk-benefit of analysis of COVID vaccines if you don’t know the URF? This is extremely, extremely important. You have been assuming it has been one. It is not one. Using a URF of 41, which is calculated using CDC methodology, we find over 300,000 excess deaths in VAERS. If the vaccine didn’t kill these people, what did?”
“How many Americans have to die before you pull the plug?” Kirsch asked.
Kirsch also questioned the panel on why Maddie de Garay’s severe adverse reaction to the Pfizer vaccine, which left her paralyzed, was not reported by the company to the FDA.
Dr. Jessica Rose, viral immunologist and biologist, told the panel EUA of biological agents requires the existence of an emergency and the nonexistence of alternate treatment.
“There is no emergency and COVID-19 is exceedingly treatable,” Rose said.
In a peer-reviewed study co-authored by Rose, myocarditis rates were significantly higher in people 13 to 23 years old within eight weeks of the COVID vaccine rollout.
In 12- to15-year-olds, Rose said, reported cases of myocarditis were 19 times higher than background rates.
“In an act of censorship, this paper has been temporarily removed and it has now been killed without criticism of the work,” Rose said, noting the timing of the removal was strange.
Rose said tens of thousands of reports have been submitted to VAERS for children ages 0 to 18.
Rose explained:
“In this age group, 60 children have died — 23 of them were less than 2 years old. It is disturbing to note that “product administered to patient of inappropriate age was filed 5,510 times in this age group. Two children were inappropriately injected, presumably by a trained medical professional, and subsequently died.”
Dr. Josh Guetzkow, a senior lecturer at the Hebrew University of Jerusalem, said expanding the EUA to children is unnecessary, premature and will do more harm than good.
Guetzkow said there is no emergency for children, especially healthy ones whose risk of severe illness and death is “almost nil.”
Guetzkow said kids with pre-existing conditions and prior COVID infections were not included in Pfizer’s study, so including them in the EUA is negligence.
“Pfizer’s trial is woefully underpowered to detect specific safety concerns, such as myocarditis, just like the adolescent study was, and if they weren’t able to detect an unexpected safety concern there, they wouldn’t be able to here,” Guetzkow said.
Guetzkow said:
“In Pfizer’s study, only .5% of controls were dropped due to important protocol violations, versus 3% in the treatment group. The odds of that happening by chance are 1 in 10,000. This deviation is poorly explained with no ITT analysis. The study is not double-blind and may be subject to bias. Most VSD safety monitoring programs have not reported results, why not wait?”
Guetzkow said, “from CDC reports, we can expect that for every 18 child hospitalizations prevented, at least 43 will end up in the hospital for all causes following vaccination,” yet, the “FDA’s risk-benefit analysis only counts myocarditis hospitalization.”
“Why ignore the V-safe data, and shouldn’t FDA verify Pfizer’s efficacy and immunobridging analysis first?” he asked.
Guetzkow said VAERS shows alarming safety signals, which cannot be attributed to increased vaccination, simulated reporting or COVID infections.
“We calculated the ratio of adverse events reported per million Pfizer vaccinations to reports per million flu vaccinations among teenagers to see what to expect in children. Serious events are reported 51% more often for Pfizer, deaths 47 times, life-threatening conditions 49 times,” Guetzkow said.
Guetzkow asked the panel to look at the data on COVID vaccines compared to flu vaccines. Pointing to the data on reproductive organs, Guetzkow asked, “why would we expect children to take these risks to protect adults?”
There are more than 900 types of adverse events reported after Pfizer vaccination that have never been reported after flu vaccines, including 11 cases of multisystem-inflammatory syndrome (MS-C) that occurred without previous history of COVID infection, Guetzkow said.
He added that if the panel was considering authorizing Pfizer’s COVID vaccine to prevent MS-C — as Pfizer’s application suggested as one of the reasons they should — the panel should reconsider.
During another part of the meeting, Julia Barnes-Weise, director of the Global Healthcare Innovation Alliance Accelerator, said pharmaceutical companies have concerns.
“One of them is, especially for a not-yet-approved vaccine, that they could be held liable for any injury that that vaccine seems to have caused,” Barnes-Weise said.
In a preliminary analysis last week, FDA reviewers said protection would “clearly outweigh” the risk of a very rare side effect in almost all scenarios of the pandemic, PBS News Hour reported.
Children’s Health Defense (CHD) said yesterday it would take legal action against the FDA if it granted EUA for the Pfizer-BioNTech vaccine for children 5- to 11- years old.
In a letter signed by Robert F. Kennedy, Jr., CHD chairman and chief legal counsel, and Nass, Kennedy and Nass wrote:
“CHD will seek to hold you accountable for recklessly endangering this population with a product that has little efficacy but which may put them, without warning, at risk of many adverse health consequences, including heart damage, stroke, and other thrombotic events and reproductive harms.”
Megan Redshaw is a freelance reporter for The Defender. She has a background in political science, a law degree and extensive training in natural health.
The rediscovery of a series of grisly experiments on beagle puppies has galvanized social media users into demanding the arrest of “America’s doctor” Anthony Fauci. But where was everyone when his work was harming humans?
Images of a sad pair of beagle puppies, their heads encased in square cages as they lie hopelessly on a table, have yanked at America’s heartstrings since they were shoved back into the national spotlight by White Coat Waste Project, a group that calls out US government labs for animal cruelty and other misuse (and abuse) of citizens’ money.
Millions of taxpayer dollars were used to essentially torture the puppies to death in labs in and out of the US, according to the organization, which unearthed evidence of the cruelty in the form of over $21 million spent on a total of four experiments – none of which was medically necessary. One involved severing 44 puppies’ vocal cords so that their pained barking and whining wouldn’t bother the scientists; another deliberately infected them with sand flies over the course of 22 months, restricting their movements by locking their heads in boxes so that they could not even swat the insects away as they were being eaten alive.
It’s horrific stuff by any measure, beyond cartoonish levels of evil. Indeed, even Texas Senator Ted Cruz (R) claimed he thought the tweets he’d read about Fauci “literally ‘torturing puppies’” had to be “metaphorical.”
But while the outrage is justified, it’s also old news. One could ask why the masses have turned against Fauci only now, when his National Institute for Allergies and Infectious Diseases has been funding the torture of puppies for years, with one of the horrific experiments dating from 2016. The most recent grant dated from 2020, meaning Fauci’s agency was vivisecting helpless furry animals at the University of Georgia even while he was being worshiped as America’s Doctor™ and posing for photos with other people’s dogs.
Even White Coat Waste Project refers to its own revelations as “Fauci’s other international scandal,” implying knowledge of a better-known episode in the fame-hungry doctor’s life.
One must ask why the popular outrage against Fauci over animal cruelty is not matched by an equal (if not more forceful) outrage over the doctor’s crimes against humanity. From his enthusiastic support of gain-of-function studies to his efforts to sideline a cheap, effective drug that could have saved thousands of lives during the AIDS epidemic in favor of a highly toxic alternative, Fauci’s hands are covered in the blood of humans as well as that of canines.
Indeed, Fauci’s behavior during the Covid-19 outbreak – trashing cheap but effective treatments in favor of expensive alternatives lacking proof of efficacy – eerily mirrors his actions during the early years of AIDS. Thousands of people have died in both cases after Fauci pushed deadly or ineffective medications – most notably the failed cancer drug AZT in the 1980s and the failed Ebola drug remdesivir in the last two years – while safer and more efficacious remedies sat on the shelf.
Discoveries that members of the National Institutes of Health, parent of Fauci’s NIAID, had hefty investments in Gilead, maker of remdesivir, as well as in Moderna, one of the manufacturers of an mRNA vaccine for Covid-19, have only raised more questions about Fauci’s motives during the coronavirus pandemic.
Fauci has also been caught lying repeatedly about his involvement in gain-of-function research aimed at making bat coronaviruses more infectious in humans. Despite his profuse denials of even funding such research in recent months, he previously defended the work by arguing that any knowledge gained from bolstering the infectious potential of such pathogens was “worth the risk” of unleashing a pandemic. Whether or not his NIAID-funded research played a part in the Covid-19 outbreak has not been proven, but Fauci’s furious tap-dancing around any questions regarding the Wuhan lab or gain-of-function research in general does him no favors.
Yet, somehow, none of this elicits anything like the howls of rage coming from dog-lovers on social media. The same outrage-on-demand contingent who demand countries like China and Vietnam stop eating dog meat, signing a petition with one hand while biting into a well-done burger with the other, insist on the closure of “barbaric” wet markets like the one we were told spawned the novel coronavirus in late 2019. This group’s problem is less animal cruelty than being reminded of that cruelty. They’d rather wait until their meat is shrink-wrapped and frozen in a supermarket than pick out the tastiest-looking chicken in the bunch and have it slaughtered then and there.
Ultimately, Fauci being arrested is an endpoint that animal rights activists, human rights activists, and the normally comatose members of Congress – 24 of whom actually signed a letter demanding answers from the once-untouchable Coronavirus Pope – should see eye-to-eye on. But the diminutive doctor must not be permitted to skate on his real crimes – whether it’s pandemic profiteering, bankrolling gain-of-function research in China that was at the time illegal to perform in the US, or allegedly perjuring himself in congressional testimony. Fauci has much to answer for. Dozens of dead puppies are just the tip of the iceberg.
Unfortunately, like other gleeful architects of the Covid-19 police state who’ve been caught in the midst of scandal – former New York Governor Andrew Cuomo, for example – arresting Fauci on the basis of popular rage over dead puppies is likely to close the book on further prosecution, no matter how heinous his “real” crimes.
Just as Cuomo is unlikely to ever be held to account for the thousands of elderly New Yorkers who died because of his nursing-home order to house Covid-positive patients with the helpless elderly, Fauci will be permitted to enjoy his retirement – and big fat pension – in peace. Americans who have lost everything to his mismanagement of the Covid-19 pandemic must not let that happen.
Helen Buyniski is an American journalist and political commentator at RT. Follow her on Telegram
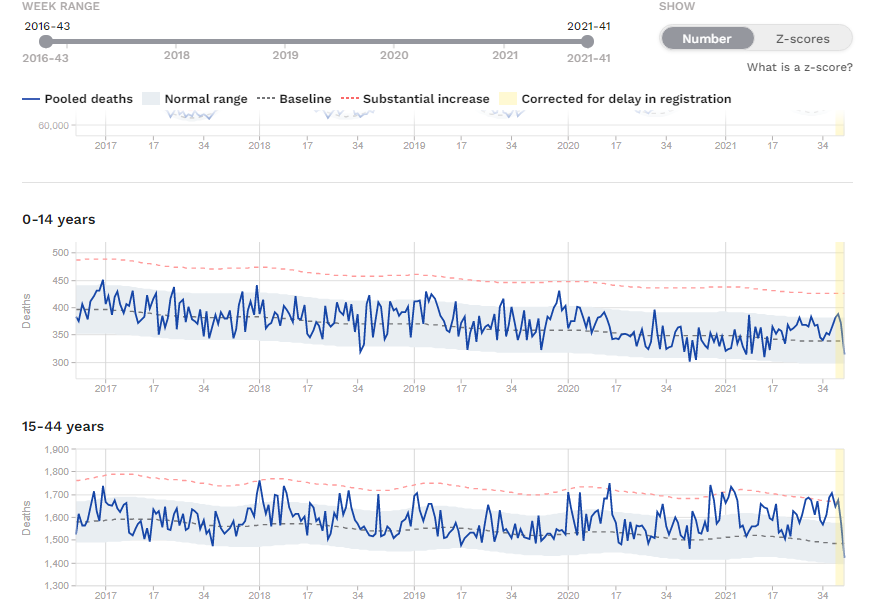
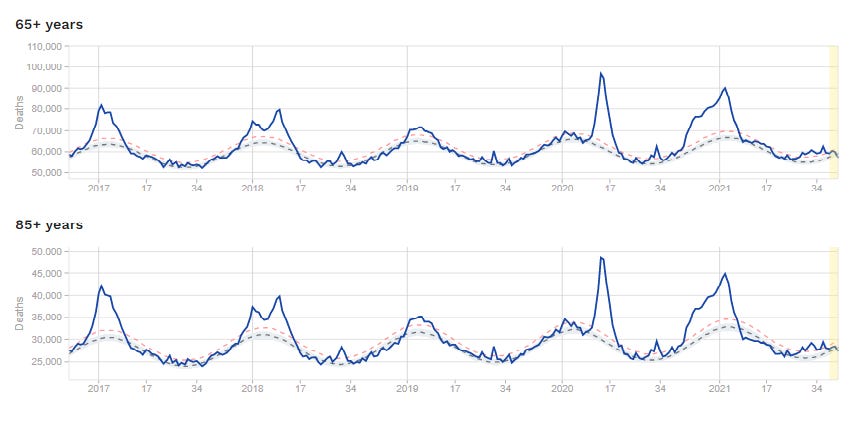
It wouldn’t take much to push a population of such elderly and frail people into a life-threatening situation. Lock them up for months on end. Deny them human contact on pain of arrest and fines they couldn’t hope to pay. Withdraw medical treatment. Quarantine their carers. Terrorise them with propaganda about a civilisation-ending disease. Order them to stay at home and avoid the contact of other people like the plague. Tell them hospitals standing empty are on the verge of being overwhelmed. Turn medical centres into places to fear, the breeding grounds of a deadly new disease. That should be more than enough. It has been more than enough.
To preserve the elderly, the world has used the young – who suffered no pandemic – as a shield.
The young have lost their jobs, their childhoods, their right to breathe air freely, their right to say no to experimental medicine they do not need.
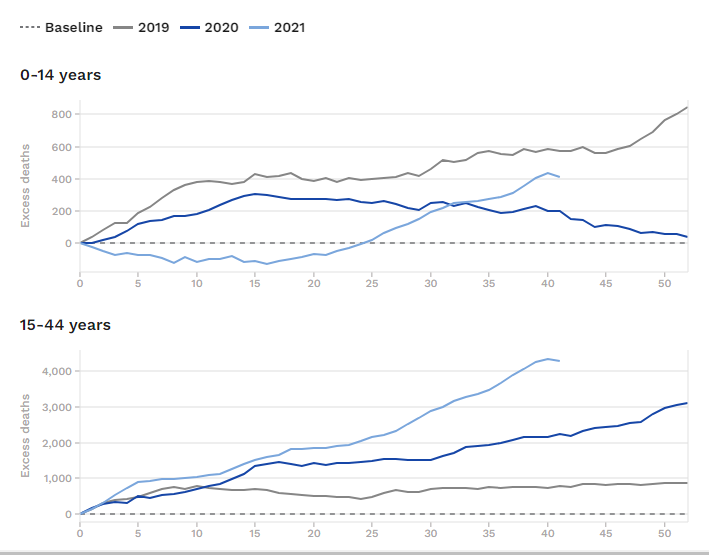
And now they appear to be dying for the elderly too:
Please can somebody explain why deaths are rising so steeply in European youth?
They did not suffer from historically excess death in the middle of the pandemic.
Why are they dying now?
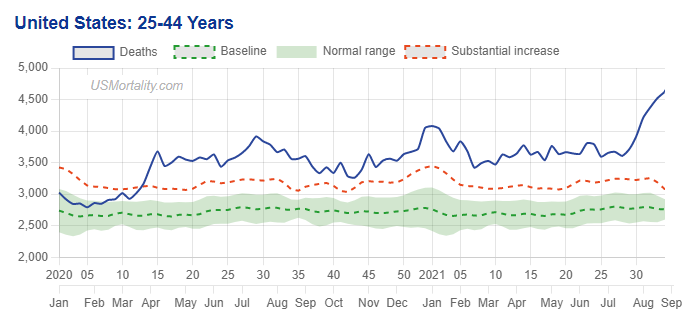
And it is not only them – US young people are suffering the same fate:
PHARMACOVIGILANCE: the practice of monitoring the effects of medical drugs after they have been licensed for use, especially in order to identify and evaluate previously unreported adverse reactions.
Pages 34-35 of the FDA review of Pfizer’s data for the 5-11 year olds provides the pretense of truly caring about identifying and quantifying adverse events from the vaccine. Just look at all the “activities” Pfizer and its partner must do. Well, of course they have to do them, since their clinical trial was so underpowered (not enough subjects) and only ran 2 months for about half the kids and 2.5 weeks for the rest. Duh?
Not only that, but Pfizer presented its data to FDA on October 6, and FDA already had completed its review and written its 39 page report by October 23, 17 days later. Fast work. But then again, we are only talking about the health of 28 million elementary school kids. And millions more overseas whose countries follow FDA advice.
And lest I forget, we are also talking about their education, because it seems they won’t be able to attend school soon, if unjabbed. Gavin Newsome said so. And a bill is being introduced in the District of Columbia for the same purpose.
Clearly, the stakes are pretty low, so a pretend Pfizer clinical trial and a pretend FDA review are good enough, right?
Below is part of FDA’s presentation. What is missing is the most important information, revealed in an Aug 23 letter from FDA. And that is, that the trials FDA demands Pfizer undertake to find out how dangerous its vaccines actually are, will not be reported to FDA until 2024 and 2025–presumably after most of the world’s children have already received 2 or 4 or 6 or 8 doses.
9 PHARMACOVIGILANCE ACTIVITIES
Pfizer submitted a revised Pharmacovigilance Plan (PVP) to monitor safety concerns that could be associated with BNT162b2 in individuals 5-11 years of age. The PVP includes the following safety concerns:
• Important Identified Risks: anaphylaxis, myocarditis, and pericarditis
• Important Potential Risks: Vaccine-associated enhanced disease (VAED), including vaccine-associated enhanced respiratory disease (VAERD).
Pfizer-BioNTech plans to conduct passive and active surveillance to monitor the postauthorization safety for the Pfizer-BioNTech COVID-19 Vaccine, including: 35
• Mandatory reporting by the Sponsor under the EUA for the following events to VAERS within 15 days: SAEs (irrespective of attribution to vaccination); COVID-19 disease resulting in hospitalization or death; multisystem inflammatory syndrome (MIS)
• Adverse event reporting in accordance with regulatory requirements for the licensed vaccine, COMIRNATY
• Additionally, following approval of COMIRNATY, the Sponsor was also asked to submit reports of myocarditis and pericarditis as 15-day reports to VAERS.
• Periodic safety reports containing an aggregate review of safety data including assessment of AEs; vaccine administration errors, whether or not associated with an AE; and newly identified safety concerns.
• Post-authorization observational studies, that would be modified to encompass the evaluation of children 5-11 years of age include active surveillance safety studies using large health insurance claims and/or electronic health record database(s):
– Study C4591009: A non-interventional post-approval safety study of the Pfizer-BioNTech COVID-19 mRNA Vaccine in the United States
Objective: To assess the occurrence of safety events of interest, including myocarditis and pericarditis, in the general U.S. population of all ages, pregnant women, the immunocompromised, and persons with a prior history of COVID-19 within selected data sources participating in the U.S. Sentinel System.
– Study C4591021: Post-conditional approval active surveillance study among individuals in Europe receiving the Pfizer-BioNTech Coronavirus Disease 2019 (COVID-19) Vaccine
Objective: To assess the potential increased risk of AESIs, including myocarditis/pericarditis, after being vaccinated with at least one dose of the PfizerBioNTech COVID-19 Vaccine.
– Study C4591021 Substudy: Substudy to describe the natural history of myocarditis and pericarditis following administration of COMIRNATY
Objective: To describe the natural history of post-vaccination myocarditis/pericarditis, including recovery status, risk factors, and/or identification of serious cardiovascular outcomes within one year of myocarditis/pericarditis diagnosis among individuals vaccinated with BNT162b2 as well as individuals not vaccinated with a COVID-19 vaccine.
– Study C4591036: Prospective cohort study with at least 5 years of follow-up for potential long-term sequelae of myocarditis after vaccination (in collaboration with Pediatric Heart Network [PHN]). Working title: Myocarditis/pericarditis follow-up study within the Pediatric Heart Network
Objective: To characterize the clinical course, risk factors, resolution, long-term sequelae, and quality of life in children and young adults <21 years with acute postvaccine myocarditis/pericarditis. Pfizer-BioNTech also plans to include vaccine effectiveness analyses among individuals 5-11 years of age in Study C4591014 entitled “Pfizer-BioNTech COVID-19 BNT162b2 Vaccine Effectiveness Study Kaiser Permanente Southern California.”
Here come jabs in schools without parental consent.
“Bonnie J. Fraser Henry OBC FRCPC is a Canadian physician who is the Provincial Health Officer for British Columbia, the first woman in this position. Henry is also a clinical associate professor at the University of British Columbia. She was a family doctor and is a specialist in public health and preventive medicine.”
In fact, the politicians have worked on this for years, and enshrined it in legislation, she says.
Looks like you can garner lots of awards when your heart is a stone, Bonnie.
And, like Presidential wannabe Governor Cuomo, she even had time to write a book about her leadership in the pandemic, titled Be Kind, Be Calm, Be Safe. Do these people know what they are, or are they high on their own supply?
Here someone collected her telling the truth about masks last year and flip-flopping later:
A Pakistani taxi driver will leave US detention at Guantanamo Bay after 17 years behind bars. Mistaken for a wanted terrorist, the man suffered horrific torture in American custody, despite never being charged with any crime.
Ahmed Rabbani’s release was announced on Friday by Reprieve, a human rights NGO. Rabbani had been unanimously cleared for release by the prison’s Periodic Review Board, made up of senior officials from six US agencies, including the State Department and Department of Homeland Security.
Rabbani’s journey through the underbelly of the US’ post-9/11 security infrastructure began in Karachi, Pakistan, in 2002. Mistaken for wanted terrorist Hassan Ghul, the taxi driver was arrested by Pakistani authorities outside Ghul’s apartment complex and sold to American personnel in the country.
Information gleaned from an associate of Rabbani arrested on the same day was used to arrest several suspected Al-Qaeda operatives, including a supposed member of Osama Bin Laden’s security detail. However, Rabbani was never charged with any crime, and is not believed to be involved in terrorism.
Nevertheless, he spent more than 545 days after his arrest being tortured in a CIA ‘black site’ in Afghanistan. The torture inflicted there on Rabbani was detailed in the US Senate’s 2014 torture report, and included long periods of being shackled with his hands outstretched over his head, an agonizing position that led Rabbani to try to cut off his own hand to end the pain.
Testimony from multiple detainees held in the same CIA prison describes permanent darkness, cells flooded with excrement and infested with vermin, beatings, sleep deprivation, being buried in simulated graves, being stripped naked and doused with cold water, and being denied bathing facilities for months on end.
According to Reprieve, Rabbani’s interrogators knew that “they had the wrong man,” but tortured him anyway. After more than a year in the CIA facility, Rabbani was transferred to the Guantanamo Bay detention camp on US territory in Cuba. He would spend the next 17 years there, without a charge or trial date.
His case attracted international attention, and in 2018, Rabbani wrote an op-ed published in the Los Angeles Times describing physical and sexual abuse by guards, force-feeding, and repeated hunger strikes to protest the conditions of his imprisonment. At the time of the op-ed, Rabbani said that he was suffering from “stomach problems so acute that I cannot consume hard food without vomiting blood,” and was being denied digestible food.
Conditions in Guantanamo chipped away at Rabbani’s mental health. “There is no morning and no evening,” he wrote. “There is only despair.”
“Ahmed’s clearance is long overdue,” said Reprieve attorney Mark Maher. “For those of us who have supported him, the feeling is one of relief, tempered with sadness for all he has lost… but we won’t celebrate until he is back with his family in Pakistan and able to hug his 19-year-old son for the first time.”
Of the 780 people detained in Guantanamo Bay since the facility opened in 2002, 732 have been transferred elsewhere or released, 38 remain there, and nine have died in custody. President Joe Biden has promised to close the notorious prison before he leaves office, a promise that was made, but not kept, by his former boss Barack Obama.
I find myself in the position that I must use an alias for fear of reprisal. Those days may be quickly coming to an end, as hospitals are denying requests for vaccine exemptions with impunity. I will likely soon be out the door, with nothing to lose. Even if I survive this round, if the “pandemic” continues, it won’t be long before I am shelved like a can of spam.
Doctors need to be called out. From early in the pandemic, it was like a mass hypnosis or forgetfulness of everything we had learned in medical school. Immune system knowledge was shelved and replaced by government dictates. The thought of early outpatient treatment with “off label” drugs that could modulate the immune system was forbidden. We essentially told patients that they had to go home and wait until they were sick enough to be hospitalized, then treatment would begin. Imagine telling all diabetics that there is no metformin, Glucophage, or insulin. Would we really wait until patients are in diabetic ketoacidosis, and then treat them only at the hospital? It is medical malfeasance of a grand scale.
We physicians gave up our training and our reasonable medical thought process. The reasons are multiple. First, it was the easy way out. Second, many of us are employed and fear reprisal. Third, despite what the public thinks, we physicians are not bold leaders, we tend to be sheep, and are afraid of having an entire institution ostracize us or our colleagues to think us crazy.
As we got to the point of vaccine rollout, doctors were not using the scientific method, questioning and challenging prevailing hypotheses. They kept their heads down, closed clinics, converted to telemedicine, and pushed only the jab.
I had conversations with doctors who are supposed experts in virology and immunology denying the lasting immunity of natural infection. Conversations about natural immunity:
“I have antibodies.”
“But they will wane.”
“But I have memory cells.”
Dumbfounded look.
Really, are these the leaders we want?
Other conversations about the safety of vaccines:
“The vaccine is safe.”
“No, we would have shut down any trial in the past after even 100 deaths.”
“This is more serious.”
“But the survival rate is about 99.6%.”
“It’s killing people.”
“So is the vaccine”
“You can’t believe VAERS.”
“It was set up to help protect the public, and if anything, it is underreporting side effects.”
“You’re a conspiracy theorist.”
Or conversations about early treatment
“You must get the vaccine, it is the only “proven” treatment, there are no other treatments.”
“Really, ivermectin has eradicated COVID in India, parts of Mexico, Japan….”
“It is a horse dewormer.”
“It won a Nobel Prize in medicine, is a WHO essential drug, and has been around for decades with a great safety profile.”
“No, only the vaccine works.”
“But it is failing”
“You are a denier and a conspiracy theorist.”
“Sigh….”
Lately, it has been all about getting 100% of the population jabbed. For what reason? I am not sure, and some of the more detailed and investigated theories scare me. I shudder to think. But last year’s heroes are being labeled selfish and villainous for not getting the vaccine. Hospital systems have abandoned their community’s health and ignored early successful outpatient treatment in favor of huge government subsidies for inpatient and ICU treatment. The success of these treatments was not great, but that is another article. Now we have the same hospital systems turning their backs on their own employees. Basically, health providers have a choice, get shot, or get fired. How does that help? Both vaxxed and unvaxxed can spread the virus, so it doesn’t help anyone. It only helps the hospital to get more government money by meeting quotas.
I, for one, will remember that when we faced a real crisis, the hospitals and many physicians chose money and profit over their own community’s best interest. Perhaps it is time for groups of physicians to get back to running their own healthcare clinics and hospitals. We used to have a code of ethics. We used to put patients first. Not anymore.
As for physicians, those who are blindly following the government edicts are culpable in a moral atrocity. Bullying and deriding patients who chose to refrain from this still experimental therapy is an abomination. (You will say it isn’t experimental anymore, to which I would say that just because the government broke its own rules regarding approval, doesn’t make it legal or right). Patients have sincere beliefs for making their choice. Respect their thoughts. Do you yell as much at smokers, drinkers, fornicators, drug abusers, etc? No, I think not. I think you chose to fit in because it gives you a sense of righteousness.
And going so far as to encourage vaccination in children and pregnant women is crazy. There is blood on the hands of any physician who does this. With children, there is no benefit to the vaccine, only harm. They would serve themselves and society better with natural immunity. The vaccine hasn’t been studied on women and their babies. It is pregnancy category X (unknown) but being pushed wholesale on these poor women without proper studies. Shame on you, doctors who are doing this. I certainly have lots to answer for when I meet my maker, but this is on another level.
I beg physicians to get back to basics, remember all the epidemiology and immunology that bored us to tears in school. Investigate the real literature and take a stand. Society needs us to do this. Even if you have been vaccinated, help those who are fighting for their lives. Stand up against this forced vaccine tyranny. Support those who have legitimate reasons for declining the jab. If you don’t stand up now, who will stand up for you when you are faced with your choice of yet another booster or your job.
Yousef A. from Beit Lahiya in the Gaza Strip survived an Israeli airstrike in May 2021 that killed his father and three of his sisters. He is still recovering from his injuries.
Following his death from Covid-19 earlier this week, former US Secretary of State Colin Powell’s legacy will be examined by many people for many different reasons. Some will eulogise him as one of America’s top diplomats and presidential advisers. Many more, I suspect, will remember him as the man who lied for his country again, and again, and again.
One of the Greek sages, Chilon of Sparta, said we should not speak ill of the dead (what is now the Latin aphorism “De mortuis nil nisi bonum dicendum est”), a maxim with which I would generally agree. However, it is precisely because of the dead that I am writing these words.
The dead to which I refer come from many nations around the world; countless men, women and children who left this earth in the absence of mercy, a voice or justice. Millions of others have yet to have any sort of closure or peace due to US militarism, wars, interventions and atrocities over many decades. Powell supported, excused and covered up most of them from Vietnam to the present day.
A memorial service for General Powell will be held at the Washington National Cathedral in the US capital next month. The so-called great and good will eulogise the first African American to serve as chairman of the Joint Chiefs of Staff and US Secretary of State. My own contribution is not for Powell and the mourners, but for the forgotten survivors who will have been propelled back into very dark places at seeing his name in the headlines this week.
To the Iraqi people, Powell was the man who did the dirty work in arguing the case for a war that created more than a million widows and orphans. Estimates of the number of dead in Iraq continue to be amended. It was Powell who stood before the UN on behalf of President George W Bush in February 2003 and spoke with great authority, using photographs to “prove” that Iraq under Saddam Hussein had weapons of mass destruction (WMDs). This was a lie, and he knew it.
A couple of weeks ahead of his speech, some Algerian refugees were arrested for allegedly producing ricin in Wood Green, North London. The British media splashed with the headlines that anti-terror police had uncovered an Al-Qaida cell poised to unleash the deadly poison on an unsuspecting public. The more lurid reports also claimed that the “ricin factory” contained bomb-making equipment. British Prime Minister Tony Blair — another man with a long-distance relationship with the truth — whipped up a frenzy of hysteria claiming that, “This danger is present and real, and with us now.”
Blair was backed up by Powell in his presentation to the UN Security Council; both men were pushing the case for war against Iraq. Powell cited the London “find” gravely as an “Iraq-linked terrorist network”. Despite the fact that the British government’s chemical weapons research facility at Porton Down knew that there was no ricin in Wood Green in early January 2003, Powell went ahead and peddled his lies regardless. Blair and Powell both appear to have ignored the facts. In a nest of vipers, it’s always difficult to separate one snake from another.
Two years later a very different story emerged during the Old Bailey trial of the Algerian refugees: there was no ricin and no sophisticated Al-Qaida plot. Jury foreman Lawrence Archer was so outraged at what emerged during his seven-month odyssey in court that he co-wrote a book with journalist Fiona Bawdon exposing the lies told by Powell backed up by “shamelessly distorted” words from the British government, media and security agencies.
Powell claimed later to regret his performance at the UN. That didn’t help the Algerians, though, who were held in a high-security prison for more than two years until the case against them in their infamous trial by jury collapsed. The US official knew that there was no ricin plot; indeed, that there was no ricin, so what was the white powder in the vial he waved around so dramatically in the Security Council meeting?
To the people of Vietnam, Colin Powell was the soldier who covered up the war crimes carried out in Mỹ Lai by a unit of US troops who slaughtered 500 civilians. Powell admitted in a 1968 memo that there might have been be “isolated cases of mistreatment”, but in August 1971 he eventually told the truth in a sworn affidavit during the war crimes trial of Brigadier General John Donaldson who, it was alleged, had routinely “killed or ordered the killing of, unarmed and unresisting” Vietnamese civilians from his helicopter.
Powell ingratiated himself in 1985 as a senior assistant to US Defence Secretary Caspar Weinberger, when he helped cover up the selling of weapons to Iran so that the Reagan administration could funnel money to the US-backed and funded right-wing Contra counterrevolutionaries in Nicaragua. Weinberger faced five charges related to the so-called Iran-Contra scandal only to be pardoned by President George H.W. Bush before he could be put on trial. It emerged that Powell took part personally in at least one covert weapons sale in exchange for hostages.
He had his finger in many pies in subsequent years which saw the demise of some dictatorships and the rise of others in US military action in Panama, the Philippines, Somalia, Liberia, Bangladesh, Russia, Bosnia, Afghanistan, the Persian Gulf and the Middle East.
To the Palestinians — and myself, I must add — Powell will always be the man who was treacherous and duplicitous towards them. He lied about Israel’s massacre of Palestinians in the Jenin refugee camp in April 2002.
The Israel Defence Forces (IDF) tried desperately to hide one of its many war crimes committed in the occupied West Bank when its soldiers killed at least 52 Palestinians in the refugee camp between 1 and 11 April at the height of the Second (Al-Aqsa) Intifada. Ariel Sharon’s cowardly troops would have made a quick exit but for the dilemma of how to cover up the killing of so many people. It’s a dilemma that focused the minds of those in charge of so-called Operation Defensive Shield.
As I wrote in MEMO last year, “[They] decided to enforce a siege so tight that no one, despite global protests, could get past Israel’s ring of steel; it was a total lockdown and lasted for weeks while the Israeli government did its best to keep journalists and human rights observers away from the Palestinian city…
“The atmosphere was tense and the UN announced that it was planning to launch an investigation into compelling allegations of Israeli war crimes said to have been committed in the refugee camp. The Israelis did what they do well, and mobilised malleable politicians and government advisers to mislead a gullible media and public.”
The then US Secretary of State Powell was brought in to use calm, authoritative tones at a press conference in Jerusalem’s King David Hotel, which Zionist terrorists blew up in 1946, killing 91 people and wounding 41 others. The irony wasn’t lost on the Palestinians and the watching world.
He claimed to have seen “no evidence” of a massacre. In last year’s article I pointed out: “By 23 April Powell was back in Washington briefing senators: ‘Right now, I’ve seen no evidence of mass graves and I’ve seen no evidence that would suggest a massacre took place.’ He wasn’t lying, of course, because he never went to Jenin, so could not have ‘seen’ the evidence even if he had wanted to.”
I was one of the first journalists on the scene, though, and was in the refugee camp in Jenin on the day that the former general presented his less than honest briefing to the world’s media. The anger and frustration I felt listening to his lies was probably nothing compared with the feelings of the Palestinians in Jenin who told me how their mothers, wives, children and other relatives had been killed before their eyes. I remember seeing a group of Palestinian women tearing at the rubble with their bare, bloodied hands trying to find the bodies of loved ones. The stench of death was overwhelming. Moreover, while Powell said that he saw “no evidence” of a massacre, Human Rights Watch disagreed, and said so when it published a hard-hitting report on what happened in Jenin.
The Jacobin online magazine has published a brutally savage obituary of Powell. “There’s Nothing Honourable or Decent About Colin Powell’s Long List of War Crimes” was the headline. I and millions like me couldn’t agree more. He was buried on Friday morning, but as yet there’s no official tombstone. When it is eventually fixed on his grave, it should be very simple: “Here lies Colin Powell – in death as in life”.
On February 13, 1960, France carried out its first nuclear test in Algeria’s southern Reggane region. According to official statistics, 17 nuclear tests were carried out in total over the next 6 years. The area remains affected, and local scientists say that radioactive contamination has caused genetic mutations and irreversibly changed the region.
There are no official statistics on the number of victims. The only figures can be found in the records kept by the French representative of the local church, which lists 42,000 victims of nuclear tests. Three years ago, the French Ministry of Defense issued a statement, putting the number at 27,000 people. The victims include French soldiers as well as local Algerians who lived in the surrounding areas. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.