EU Wants To Keep Vaccine Passports In Place For Another ENTIRE YEAR
By Steve Watson | Summit News | February 4, 2022
The unelected bureaucrat governors of the EU in the European Commission have proposed keeping the bloc’s COVID vaccine passport system in place for another entire year, despite the fact that many member countries are ramping down restrictions.
In a notice on its website, the Commission states “Today the European Commission is proposing to extend the EU Digital COVID Certificate by a year, until 30 June 2023.”
It continues, “The COVID-19 virus continues to be prevalent in Europe and at this stage it is not possible to determine the impact of a possible increase in infections in the second half of 2022 or of the emergence of new variants.”
“Extending the Regulation will ensure that travellers can continue using their EU Digital COVID Certificate when travelling in the EU where Member States maintain certain public health measures,” the statements adds.
It continues, “The Commission is adopting the proposal today to make sure the European Parliament and the Council can conclude the legislative procedure in time before the current Regulation expires.”
The move comes even as several countries, including Denmark, Norway, Italy, Sweden, France, in addition to non-EU countries such as Switzerland and England move to scrap restrictions including the vaccine passes.
The European Commission admits in its statement that it is up to the individual countries whether they carry on using the EU COVID vaccine passport scheme.
“The domestic use of EU Digital COVID Certificates remains a matter for Member States to decide, the statement notes, adding “The EU legislation on the EU Digital COVID Certificate neither prescribes nor prohibits the domestic use of EU Digital COVID Certificate (such as for access to events or restaurants).”
It also notes that “At the same time, where a Member State establishes a system of COVID-19 certificate for domestic purposes, it should continue to ensure that the EU Digital COVID Certificate is also fully accepted for those purposes. Beyond that, the Commission also encourages Member States to align their domestic validity periods with the validity period set at EU level for the purpose of travel.”
As we reported in November, despite vaccine passport schemes and high vaccination rates in many of the countries affected, COVID cases across Europe continued to surge as winter kicked in.
In addition, a recent investigation by experts in Spain concluded that vaccine passports have no significant impact on reducing COVID-19 infection rates.
The findings are similar to evidence found by the UK government that vaccine passports could actually increase Covid rates in the country.
The Spanish study noted that the only positives of such a scheme are that it “warns people that there is still danger from the pandemic and encourages vaccination uptake among the reticent.”
In other words, although vaccine passports have no discernible impact on their stated goal – reducing the spread of COVID-19 – they do succeed in keeping people fearful and compliant.
That conclusion dovetails with a recent admission by French Minister of Health Olivier Véran that the vaccine passports are “a disguised form of vaccination obligation,” but are “more effective.”
Eli Yale Surveillance State
By Stephen Lendman | February 5, 2022
Since seasonal flu was renamed covid over two years ago, medical tyranny became the new abnormal on thousands of US college and university campuses nationwide.
Rights guaranteed by international and US constitutional law no longer apply.
Health and freedom-destroying mandates replaced them.
The higher education experience I enjoyed long ago is gone since medical tyranny took over.
Yalies are enduring some of the worst of what no one should tolerate under virtual surveillance state standards.
A university hotline was established to make “confidential (snitching) reports.”
It largely relates to assuring “compliance with (draconian flu/covid) health and safety standards” that harm and don’t protect.
According to your.yale.edu, it’s to enforce compliance with all things flu/covid to include:
Destruction of normal campus interactions by mandated social distancing.
The same goes for masking.
What Yale calls “personal protective equipment (sic)” risks potentially serious respiratory harm while providing nothing beneficial.
So-called “cleaning and disinfecting standards” are best achieved by old-fashioned soap, water and other good personal hygiene practices.
Yale’s hotline for snitching on non-compliers to any of the above and whatever else relates to flu/covid operates “24 hours a day, seven days a week, every day of the year.”
The Washington Free Beacon (WFB) discussed one example of how Yale’s surveillance state operates.
On a Saturday night at 9:30 PM, a student in what appeared to be a deserted campus library went maskless to relax.
Alone with no one around, there was no reason to wear what’s required by university rules when others are nearby.
Somebody spotted, filmed and reported him.
In response, he got the following Office of the Dean notice, saying:
“The Compact Review Committee (CRC) is reviewing a report that your conduct failed to meet the commitments you agreed to in the Yale Community Compact.”
“The CRC has received the enclosed report from Melanie Boyd, Dean of Student Affairs, Yale College (flu/covid) Health and Safety Leader…”
“You have until (24 hours from this notice to) provide the CRC with any relevant information you would like the Committee to consider in its evaluation.”
“(F)ailure to do so could lead to disciplinary action with the Yale College Executive Committee.”
“The CRC will review the matter and decide whether your conduct poses a risk to the health and safety of yourself or other community members.”
Days after receiving the above notice, he received the following reply:
The so-called CRC “determined that your conduct posed a risk to the health and safety of yourself or other community members (sic).”
“Should you continue to engage in behavior that violates the Yale Community Compact, you will be placed on Public Health Warning and may face more serious outcomes, including the removal of permission to be on campus.”
On the same evening that the reprimanded student went maskless with no one around him in a near-deserted campus library, “1,000 maskless students gathered for Yale’s annual holiday dinner,” the WFB reported.
A video of the event showed the maskless attendees.
Apparently unsnitched on or for whatever other reason(s), no disciplinary actions were reported.
According to what students told the WFB, “rules increasingly feel like overkill.”
Enforcing them is “spotty.”
So far, there’s been no “organized opposition.”
Mass surveillance state Yale discourages it.
What one unnamed student called “a silenced majority (reflects fear of) administrative consequences” for openly addressing what harms health and denies students the full academic experience they deserve.
Other colleges and universities instituted their own surveillance state practices.
Northwestern University with campuses in Evanston, IL and Chicago is one.
Harvard is another. “Speak up,” it urged!
“Simple. Anonymous. 24/7.”
“Keep Harvard a safe place to live, learn and work (sic)” — by making it unsafe and unfit for students, faculty and staff.
By imposing draconian health and freedom-destroying mandates.
At Yale, no official guidelines were published to explain what alleged offenses merit what punitive actions.
The same is likely true on other campuses with draconian rules in place.
Most important is that kill shots and all else flu/covid have nothing to do with protecting and preserving health.
They aim to destroy public health and what remains of fundamental freedoms.
We’ve been lied to and mass deceived for over two years.
For students, academic life as it should be is gone.
For working-age individuals required to be jabbed and masked et al, destroying health and freedom is a condition of employment where these draconian standards were implemented.
The same applies to where free access to other public places are restricted or otherwise impeded.
I mentioned the following once before in an earlier article:
What’s going on reminds me of a comic routine performed on television long ago by famed entertainer/tightwad-impersonating Jack Benny (1894 – 1974).
Approached by a thug impersonator and told “Your money or your life,” Benny responded:
“I’m thinking it over.”
There’s nothing to think over about draconian flu/covid mandates.
It’s crucial to shun what’s designed to destroy health and freedom — on the phony pretext of providing protection not gotten.
Canadian trucker Freedom Convoy embraces GiveSendGo after GoFundMe censorship
By Tom Parker | Reclaim The Net | February 4, 2022
After having their fundraising efforts shut down by GoFundMe, the leaders of the Canadian trucker Freedom Convoy have switched to alternative platforms to fundraise and communicate with their supporters.
The Freedom Convoy, which has been traveling across Canada to protest vaccine mandates, has gained huge traction online and had raised over $10 million on GoFundMe. However, GoFundMe withheld the convoy’s funds twice and said that it’s “collaborating with local law enforcement” before permanently shutting down the campaign and refusing to pass on the millions of dollars that had been raised.
The shutdown of the campaign came days after a Canadian city council member had requested a lawsuit to seize GoFundMe funds raised by the Freedom Convoy.
Following these issues with GoFundMe, the Freedom Convoy launched a campaign on the alternative crowdfunding site GiveSendGo and has already raised tens of thousands of dollars. We have confirmed that this is the official campaign created by Tamara Lich who created the original campaign on GoFundMe.
While GoFundMe has removed multiple fundraisers from its platform, GiveSendGo has championed freedom of speech and platformed many fundraising campaigns that have been restricted by GoFundMe including those raising money for Kyle Rittenhouse and election investigations.
In addition to embracing GoFundMe, the organizers of the Freedom Convoy have also partnered with CloutHub to create a group for communicating with their supporters and set up a campaign page that contains quick links to the group and fundraising page.
“There is no more important movement for freedom across the American continent right now than the Freedom Convoy 2022,” CloutHub CEO Jeff Brain said. “We are proud to support the Canadian truckers and will help support the other trucker movements popping up around the world to fight against unlawful mandates. CloutHub is where the world connects and organizes to take on the issues they care about, including defending liberty and freedom.”
CloutHub, which had direct experience of Big Tech censorship when it was deplatformed by IBM in 2020, offers users an alternative platform that focuses on bringing people together and empowering them to connect and solve issues that they care about. It has also encouraged lawmakers to pursue laws that limit the power of Big Tech.
The GiveSendGo campaign can be found here. The page may be slow as it deals with heavy demand.
‘Freedom Convoys’ gaining steam across Europe
RT | February 4, 2022
Truckers in France are reportedly planning to emulate the Canadian ‘Freedom Convoy’ by mobilizing groups of big rigs to protest vaccine mandates and other Covid-19 restrictions set by Paris. According to a BFM TV report, demonstrators plan to “paralyze” the French capital next week before joining a wider “European convergence” in Brussels.
The outlet reported that a leaflet announcing the ‘Freedom Convoy France’ has been circulated on social media networks, calling on “citizens” to “recover their freedom, their fundamental rights, unconditional access to care, education, and culture, respect for the essential values of our Constitution.” It also noted that the truckers in “Canada [had] paved the way for us.”
After final preparations on Monday and Tuesday, the convoy will set off in three waves from across France – with those furthest from Paris setting off on Wednesday, according to an itinerary on the leaflet. All three waves are expected to reach the national capital Friday evening. On Sunday, the convoy is slated to leave and “join our European friends” in Brussels.
The BFM TV report noted that a Facebook group, called ‘Le convoi de la liberte’, had been created on January 26 and reached nearly 197,000 members. The outlet said the convoy may reinvigorate protests against vaccination passes, which have apparently been flagging [???] in recent weeks.
In addition, the report pointed to a ‘World Freedom Convoy’ group that has been set up on Telegram. This is thought to include demonstrators from Germany, Italy, and Croatia, among others. The Bruzz news outlet in Belgium reported on Thursday that some 40,000 people had joined the group within the past week – with the focus on free speech and the right to make one’s own health choices.
According to Bruzz news, the truck drivers hope to head toward their respective capital cities starting Monday before heading on to Brussels. The outlet noted that it was unclear how many would actually take part, but added that police were monitoring the situation.
Meanwhile, The Guardian reported that a Facebook group of US truckers called ‘Convoy to DC 2022’, who planned to drive to Washington, DC next month, had gained more than 100,000 members before being deleted by Meta. The organizers have reportedly since moved to Telegram, where over 28,000 have joined.

Since when was heart trouble ‘non-serious’?
By Guy Hatchard | TCW Defending Freedom | February 4, 2022
New Zealand – The Medsafe report Adverse events following immunisation with COVID-19 vaccines: Safety Report #39 – 31 December 2021 lists 46,000 adverse events reported since the start of the Pfizer vaccine rollout in New Zealand. Historically this is 30 times the rate of adverse effects reported for flu vaccines. More than 50 per cent of these adverse effects are reported by medical professionals and about 40 per cent by affected members of the public via the CARM (Centre for Adverse Reactions Monitoring) website. Prior experience published by Medsafe concludes that only 5 per cent of adverse events are reported to CARM. A total of 8.1million doses have been administered in NZ.
The ten most common adverse events
Some 44,000 of the 46,000 adverse events are dismissed by Medsafe as ‘non-serious’—a number which has been echoed by politicians across the NZ political spectrum and by our Ministry of Health as evidence that the Pfizer vaccine is safe. The ten most common adverse events (all rated as non-serious) are as follows (from Medsafe). The total number of events below is more than 44,000 because many people experienced multiple symptoms.
The Mayo Clinic in USA reported before the pandemic that the risk of developing myocarditis is rare and lists the following concerning symptoms of myocarditis:
Mayo Clinic—Myocarditis Symptoms
If you’re in the early stages of myocarditis, you might have mild symptoms such as chest pain, rapid or irregular heartbeats, or shortness of breath. Some people with early-stage myocarditis don’t have any symptoms. The signs and symptoms of myocarditis vary, depending on the cause of the disease. Common myocarditis signs and symptoms include:
• Chest pain
• Rapid or irregular heartbeat (arrhythmias)
• Shortness of breath, at rest or during activity
• Fluid buildup with swelling of the legs, ankles and feet
• Fatigue
• Other signs and symptoms of a viral infection such as a headache, body aches, joint pain, fever, child dizziness, a sore throat or diarrhea
Sometimes, myocarditis symptoms may be similar to a heart attack. If you are having unexplained chest pain and shortness of breath, seek emergency medical help.
Of the ten most common adverse effects of Covid-19 vaccination reported to CARM in NZ, you can see eight are listed as symptoms of myocarditis by the Mayo Clinic. Given that myocarditis is the most common known severe outcome of Covid-19, why have the eight common vaccine adverse effects also known to be symptoms of myocarditis been characterised as ‘non-serious’? Is this a glaring case of misdiagnosis? If so, why?
NZ GPs and medical personnel had a naive expectation of vaccine safety
The first point to note is that most NZ medical professionals had expectations of vaccine safety based both on years of experience with vaccination programmes and the extensive medical education they had received. They had no prior experience with drugs or vaccines which had not already completed years of testing and safety evaluation. It was for them therefore virtually unthinkablethat the Pfizer vaccine was unsafe. Moreover the Pfizer vaccine trial results had already characterised the common adverse effects as non-serious. For this reason the very common reports of chest discomfort and shortness of breathfollowing Covid-19 vaccination, which according to prior protocols should have led to intensive investigation and treatment, were dismissed as non-serious without investigation and in most cases without reporting to CARM. Perhaps their very common occurrence fostered an attitude of indifference and dismissal which many victims suffered in NZ when they reported such symptoms to their GP or to hospital staff.
Rates of Myocarditis symptoms are higher than realised
The prevalence of a wide range of known myocarditis symptoms is probably indicative of a very high rate of subclinical and mild myocarditis following Pfizer vaccination. The important point to note is that the recommended treatment for mild myocarditis is rest. Most people recover if it is treated early with sufficient prolonged rest. If left untreated, myocarditis can restrict the capacity of the heart to pump blood which can lead to serious cardiac events such as heart attack, stroke, and arrhythmia. It is wrong to undertake vigorous physical activity including sport while suffering from myocarditis. It is clear from this that insufficient precautionary instructions were given to vaccine recipients about the risks they faced and the steps that they needed to take to avoid these risks. This may have contributed to cardiac problems including among some recipients undertaking vigorous physical exercise.
The possible extent of these cardiac events is indicated by multiple reports to voluntary organisations. An important point to note here is that reporting to CARM is not mandatory, a very unfortunate yet unforgivably deliberate omission. Medsafe attempts in its Safety Report #39 (referenced above) to dismiss the significance of adverse events by comparing their rate to population norms. In the absence of mandatory reporting, especially considering that Medsafe knows adverse events are grossly under-reported, all such comparisons are statistically meaningless.
A public information campaign is essential
Belatedly Dr Ashley Bloomfield, Director General of the Ministry of the Health, struck a note of alarm about myocarditis in his December 15 2021 letter to directors of district health boards, but this concern did not alter much the processes being applied. Individuals experiencing myocarditis following their first vaccination are still being denied exemptions. Those suffering strokes and heart attacks are in some if not most cases being denied Accident Compensation Commission (ACC) assistance. There is also a virtual data black-out on rates of cardiac events and hospitalisations and on ACC claims. Anecdotal and whistleblower reports here and overseas suggest these might be high but considering that data collection has been haphazard due to the ‘non-serious’ label, these might be hard to quantify unless the government makes an honest attempt to inform the public of risks and ask people to come forward who are already affected. This is particularly important as many stroke, cardiac and other serious adverse event sufferers have already been emphatically informed by their GP or other medical professionals that their symptoms must be unrelated to the Pfizer vaccination – an egregious form of victim-blaming lacking any scientific basis.
For more information: HatchardReport.com
38,983 Deaths and 3,530,362 Injuries Following COVID Shots in European Database as Mass Funeral for Children who Died After Pfizer Vaccine Held in Switzerland

By Brian Shilhavy | Health Impact News | February 4, 2022
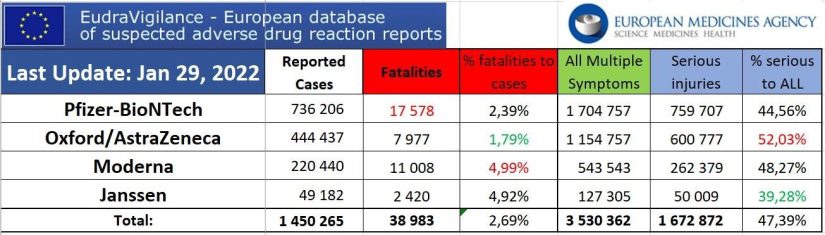
The European (EEA and non-EEA countries) database of suspected drug reaction reports is EudraVigilance, verified by the European Medicines Agency (EMA), and they are now reporting 38,983 fatalities, and 3,530,362 injuries following injections of four experimental COVID-19 shots:
- COVID-19 MRNA VACCINE MODERNA (CX-024414)
- COVID-19 MRNA VACCINE PFIZER-BIONTECH
- COVID-19 VACCINE ASTRAZENECA (CHADOX1 NCOV-19)
- COVID-19 VACCINE JANSSEN (AD26.COV2.S)
From the total of injuries recorded, almost half of them (1,672,872 ) are serious injuries.
“Seriousness provides information on the suspected undesirable effect; it can be classified as ‘serious’ if it corresponds to a medical occurrence that results in death, is life-threatening, requires inpatient hospitalisation, results in another medically important condition, or prolongation of existing hospitalisation, results in persistent or significant disability or incapacity, or is a congenital anomaly/birth defect.”
A Health Impact News subscriber in Europe ran the reports for each of the four COVID-19 shots we are including here. It is a lot of work to tabulate each reaction with injuries and fatalities, since there is no place on the EudraVigilance system we have found that tabulates all the results.
Since we have started publishing this, others from Europe have also calculated the numbers and confirmed the totals.*
Here is the summary data through January 29, 2022.
Total reactions for the mRNA vaccine Tozinameran (code BNT162b2,Comirnaty) from BioNTech/ Pfizer: 17,578 deaths and 1,704,757 injuries to 29/01/2022
- 48,240 Blood and lymphatic system disorders incl. 242 deaths
- 57,541 Cardiac disorders incl. 2,554 deaths
- 522 Congenital, familial and genetic disorders incl. 51 deaths
- 22,590 Ear and labyrinth disorders incl. 11 deaths
- 1,911 Endocrine disorders incl. 6 deaths
- 25,814 Eye disorders incl. 38 deaths
- 133,365 Gastrointestinal disorders incl. 681 deaths
- 422,360 General disorders and administration site conditions incl. 5,024 deaths
- 1,931 Hepatobiliary disorders incl. 90 deaths
- 18,455 Immune system disorders incl. 95 deaths
- 76,443 Infections and infestations incl. 1,878 deaths
- 33,972 Injury, poisoning and procedural complications incl. 331 deaths
- 42,585 Investigations incl. 502 deaths
- 11,344 Metabolism and nutrition disorders incl. 273 deaths
- 201,643 Musculoskeletal and connective tissue disorders incl. 212 deaths
- 1,629 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 153 deaths
- 278,744 Nervous system disorders incl. 1,859 deaths
- 2,513 Pregnancy, puerperium and perinatal conditions incl. 74 deaths
- 251 Product issues incl. 3 deaths
- 30,622 Psychiatric disorders incl. 207 deaths
- 6,150 Renal and urinary disorders incl. 266 deaths
- 68,129 Reproductive system and breast disorders incl. 6 deaths
- 72,531 Respiratory, thoracic and mediastinal disorders incl. 1,884 deaths
- 78,059 Skin and subcutaneous tissue disorders incl. 146 deaths
- 3,871 Social circumstances incl. 22 deaths
- 21,010 Surgical and medical procedures incl. 204 deaths
- 42,532 Vascular disorders incl. 766 deaths
Total reactions for the mRNA vaccine mRNA-1273 (CX-024414) from Moderna: 11,008 deaths and 543,543 injuries to 29/01/2022
- 12,365 Blood and lymphatic system disorders incl. 120 deaths
- 18,287 Cardiac disorders incl. 1,142 deaths
- 190 Congenital, familial and genetic disorders incl. 11 deaths
- 6,310 Ear and labyrinth disorders incl. 8 deaths
- 502 Endocrine disorders incl. 6 deaths
- 7,475 Eye disorders incl. 36 deaths
- 44,340 Gastrointestinal disorders incl. 413 deaths
- 145,153 General disorders and administration site conditions incl. 3,630 deaths
- 793 Hepatobiliary disorders incl. 54 deaths
- 5,370 Immune system disorders incl. 22 deaths
- 23,070 Infections and infestations incl. 1042 deaths
- 10,286 Injury, poisoning and procedural complications incl. 208 deaths
- 12,129 Investigations incl. 393 deaths
- 4,847 Metabolism and nutrition disorders incl. 263 deaths
- 66,358 Musculoskeletal and connective tissue disorders incl. 223 deaths
- 682 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 85 deaths
- 91,230 Nervous system disorders incl. 1,029 deaths
- 907 Pregnancy, puerperium and perinatal conditions incl. 10 deaths
- 98 Product issues incl. 4 deaths
- 9,441 Psychiatric disorders incl. 181 deaths
- 3,030 Renal and urinary disorders incl. 214 deaths
- 12,547 Reproductive system and breast disorders incl. 9 deaths
- 23,251 Respiratory, thoracic and mediastinal disorders incl. 1,162 deaths
- 27,540 Skin and subcutaneous tissue disorders incl. 96 deaths
- 2,239 Social circumstances incl. 45 deaths
- 3,028 Surgical and medical procedures incl. 203 deaths
- 12,075 Vascular disorders incl. 399 deaths
Total reactions for the vaccine AZD1222/VAXZEVRIA (CHADOX1 NCOV-19) from Oxford/ AstraZeneca: 7,977 deaths and 1,154,757 injuries to 29/01/2022
- 13,912 Blood and lymphatic system disorders incl. 278 deaths
- 20,984 Cardiac disorders incl. 830 deaths
- 235 Congenital familial and genetic disorders incl. 8 deaths
- 13,406 Ear and labyrinth disorders incl. 7 deaths
- 692 Endocrine disorders incl. 6 deaths
- 20,086 Eye disorders incl. 32 deaths
- 107,453 Gastrointestinal disorders incl. 434 deaths
- 304,993 General disorders and administration site conditions incl. 1,855 deaths
- 1,039 Hepatobiliary disorders incl. 69 deaths
- 5,409 Immune system disorders incl. 40 deaths
- 42,266 Infections and infestations incl. 620 deaths
- 13,630 Injury poisoning and procedural complications incl. 198 deaths
- 25,681 Investigations incl. 205 deaths
- 13,023 Metabolism and nutrition disorders incl. 126 deaths
- 168,174 Musculoskeletal and connective tissue disorders incl. 165 deaths
- 743 Neoplasms benign malignant and unspecified (incl cysts and polyps) incl. 40 deaths
- 234,117 Nervous system disorders incl. 1,178 deaths
- 635 Pregnancy puerperium and perinatal conditions incl. 20 deaths
- 199 Product issues incl. 1 death
- 21,051 Psychiatric disorders incl. 69 deaths
- 4,338 Renal and urinary disorders incl. 78 deaths
- 16,849 Reproductive system and breast disorders incl. 3 deaths
- 41,401 Respiratory thoracic and mediastinal disorders incl. 1,082 deaths
- 52,064 Skin and subcutaneous tissue disorders incl. 65 deaths
- 1,617 Social circumstances incl. 9 deaths
- 1,973 Surgical and medical procedures incl. 30 deaths
- 28,787 Vascular disorders incl. 529 deaths
Total reactions for the COVID-19 vaccine JANSSEN (AD26.COV2.S) from Johnson & Johnson: 2,420 deaths and 127,305 injuries to 29/01/2022
- 1,229 Blood and lymphatic system disorders incl. 51 deaths
- 2,552 Cardiac disorders incl. 204 deaths
- 40 Congenital, familial and genetic disorders incl. 1 death
- 1,319 Ear and labyrinth disorders incl. 3 deaths
- 105 Endocrine disorders incl. 1 death
- 1,656 Eye disorders incl. 10 deaths
- 9,588 Gastrointestinal disorders incl. 88 deaths
- 34,487 General disorders and administration site conditions incl. 685 deaths
- 153 Hepatobiliary disorders incl. 13 deaths
- 544 Immune system disorders incl. 10 deaths
- 8,521 Infections and infestations incl. 207 deaths
- 1,147 Injury, poisoning and procedural complications incl. 25 deaths
- 6,086 Investigations incl. 131 deaths
- 756 Metabolism and nutrition disorders incl. 60 deaths
- 17,116 Musculoskeletal and connective tissue disorders incl. 55 deaths
- 86 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 8 deaths
- 23,413 Nervous system disorders incl. 245 deaths
- 55 Pregnancy, puerperium and perinatal conditions incl. 1 death
- 30 Product issues
- 1,766 Psychiatric disorders incl. 22 deaths
- 535 Renal and urinary disorders incl. 31 deaths
- 2,941 Reproductive system and breast disorders incl. 6 deaths
- 4,468 Respiratory, thoracic and mediastinal disorders incl. 304 deaths
- 3,760 Skin and subcutaneous tissue disorders incl. 10 deaths
- 409 Social circumstances incl. 4 deaths
- 867 Surgical and medical procedures incl. 74 deaths
- 3,676 Vascular disorders incl. 171 deaths
*These totals are estimates based on reports submitted to EudraVigilance. Totals may be much higher based on percentage of adverse reactions that are reported. Some of these reports may also be reported to the individual country’s adverse reaction databases, such as the U.S. VAERS database and the UK Yellow Card system. The fatalities are grouped by symptoms, and some fatalities may have resulted from multiple symptoms.
On January 29, 2021 a mass funeral protest for children who have died after receiving a Pfizer vaccine was held in Geneva, Switzerland.
Someone recorded the event and made a short video. This is on our Bitchute Channel, and also on our Telegram channel.
Tow Truck Operator refuses to assist authorities at Freedom Convoy
JustinCredibleTV | February 2, 2022
See also:
Alberta towing companies reject requests to supply trucks to RCMP
By Melanie Risdon | Western Standard | February 1, 2022
Authorities searching for tow truck companies to assist in the removal of trucks from Coutts border blockade are coming up empty-handed.
According to local towing companies, requests have come in since Sunday for trucks to assist RCMP should they look to haul away trucks and other vehicles participating in the border blockade.
The Western Standard spoke with a number of tow truck companies in southern Alberta including in Calgary and Lethbridge.
City Wide towing in Calgary said they had tow trucks at the blockade yesterday to help support anyone in need, but confirmed no trucks stayed on scene.
“Our trucks won’t be heading outside of Calgary today,” said a call centre employee at City Wide who did not want to give her name.
“We will be remaining in Calgary to service the surrounding area.”
TnT Towing in Lethbridge is one of the largest towing companies in the area. When contacted, the person who answered the phone said they had no comment but did indicate they had been contacted.
“We don’t know who it was that called, but we don’t want to get involved so we won’t be commenting.”
One smaller towing company in southern Alberta that was approached to supply tow trucks said they are “stuck between a rock and a hard place.”
“We have created relationships in our community and contracts that would be in jeopardy if we participate in any way,” said a worker at the towing company who asked to remain anonymous to avoid any negative response to his company.
“A lot of these smaller companies don’t want to ruin their reputation in the communities they serve so they don’t want to get involved,” he said.
“We have received calls here to supply our trucks, but we’ve also had calls from locals who won’t identify themselves asking if we plan to send trucks. When I told them ‘no’ they said ‘good then we will keep supporting you.’”
The Western Standard spoke with Abe Martens from Xodus Car Transport out of Lethbridge County. Martens’ company focuses on transporting vehicles, but also offers towing services.
“We are here with our trucks at the blockade, but we are participating and are in full support of the truckers,” said Martens. … Full article
No question the vaccines increase your susceptibility to COVID. What else do they do?
By Meryl Nass, MD | February 3, 2022

https://www.publichealthscotland.scot/media/11404/22-02-02-covid19-winter_publication_report.pdf
If you live in Scotland, a small country, the government, with its NHS, is like Santa: it knows if you’ve been bad or good. Scotland has 5.5 million residents. Over 5 million of them are listed in Scotland’s report of cases, above. The rest are kids too young for the vaccine. Sadly for Scots, 80% went along with the jab. It didn’t help them. And you can’t dispute these numbers: look at the narrow confidence intervals.
So now we know the jabbed get more COVID. What we suspect is that they also get more heart attacks, strokes, blood clots, autoimmune diseases and myocarditis. Will Scotland release those data, ever?
Attack of the Transphobic Putin-Nazi Truckers!

By CJ Hopkins | Consent Factory, Inc. | February 4, 2022
They rolled up on Ottawa’s Parliament Hill like one of the plagues in the Book of Revelations, honking their infernal air horns, the grills of their tractors grinning demonically, the sides of their dry vans painted with blasphemies like “FREEDOM TO CHOOSE,” “MANDATE FREEDOM,” “NO VACCINE MANDATES,” and “UNITED AGAINST TYRANNY.”
Yes, that’s right, New Normal Canada has been invaded and now is under siege by hordes of transphobic Putin-Nazi truckers, racist homophobes, anti-Semitic Islamaphobes, and other members of the working classes!
According to the corporate media, these racist, Russia-backed, working-class berserkers are running amok through the streets of Ottawa, waving giant “swastika flags,” defecating on war memorials, sacking multi-million-dollar “soup kitchens,” and eating the food right out of homeless people’s mouths. Rumor has it, a kill-squad of truckers has been prowling the postnatal wards of hospitals, looking for Kuwaiti babies to yank out of their incubators.
I know, this is Canada, so that sounds a little dubious, but this has all been thoroughly fact-checked by the fact checkers at the New Normal Ministry of Truth … you know, the ones that fact-checked Russiagate, and the Attempted Putin-Nazi Insurrection of January 6 at the US Capitol, and the safety and effectiveness of the Covid “vaccines,” and the masks, and the inflated Covid statistics, and the rest of the official Covid narrative.
Or just take it from Prime Minister Justin Trudeau …

Now, this is the actual prime minister of Canada, not just some woke fanatic on Twitter. He was tweeting from his fortified Covid Bunker in an undisclosed location somewhere in the Yukon, or possibly the United States, where he fled as the transphobic Putin-Nazi truckers rolled up outside his office in Ottawa. Trudeau had vowed to stand and fight, but he had no choice but to flee the capital after he mysteriously tested positive for Covid (which also might have been the work of the Russians, possibly the same professional team of weed-smoking, hooker-banging Novichok assassins that got to the Skripals back in 2018).
Russian involvement has not yet been confirmed by the ex-CIA and NSA officials posing as “analysts” on CNN, but according to the CBC, “there’s concern that Russian actors could be continuing to fuel things as the protest grows, and perhaps even instigating it from the outset.”
And, in light of the exposure of Putin’s plot to produce a “very graphic” false-flag video “involving the deployment of corpses” as a pretext to invade the Ukraine and set off nuclear Armageddon, or at least a raft of economic sanctions and DEFCON 1-level bellicose verbiage, it’s possible that the entire “Covid pandemic” was an elaborate Putin-Nazi ruse designed to bring down the Trudeau government, and sabotage the implementation of the New Normal global-segregation system, and the compulsory mRNA “vaccination” of every man, woman, and child on earth, and “democracy,” and transgender rights … or whatever.
But, seriously, this is where we are at the moment. We are in that dangerous, absurdist end-stage of the collapse of a totalitarian system or movement where chaos reigns and anything can happen. The official Covid narrative is rapidly evaporating. More and more people are taking to the streets to demand an end to whole fascist charade … no, not “transphobic white supremacists” or “anti-vax extremists,” or “Russian-backed Nazis,” but working-class people of all colors and creeds, families, with children, all over the world.
The Covidian Cult has lost control. Even hardcore mask-wearing, social-distancing, triple-vaxxed-double-boosted members are defecting. Formerly fanatical New Normal fascists are mass-deleting their 2020 tweets and switching uniforms as fast as they can. No, it isn’t over yet, but the jig is up, and GloboCap knows it. And their functionaries in government know it.
And therein lies the current danger.
There is a narrow window — a month or two, maybe — for governments to declare “victory over the virus” and roll back their segregation systems, mask-wearing mandates, “vaccine” mandates, and the rest of the so-called “Covid restrictions.” Many governments are already doing so, England, Norway, Denmark, Sweden, Switzerland, Finland, Ireland, etc. They have seen which way the wind is blowing, and they are rushing to dismantle the New Normal in their countries before … well, you know, before a convoy of angry truckers arrives at their doors.
If they let that happen, they will find themselves in the unenviable position that Trudeau is now in. The Canadian truckers appear to be serious about staying there until their demands are met, which means Trudeau only has two options: (1) give in to the truckers’ demands, or (2) attempt to remove them by force. There’s already talk about bringing in the military. Imagine what an unholy mess that would be. Odds are, the military would disobey his orders, and, if not, the world would be treated to the spectacle of full-blown New Normal Fascism in action.
Either way, Trudeau is history, as long as the truckers stand their ground. I pray they do not give an inch, and I hope the leaders of other New Normal countries, like Australia, Germany, Austria, Italy, and France, are paying close attention.
Some of my readers will probably remember a previous column in which I wrote:
“This isn’t an abstract argument over ‘the science.’ It is a fight … a political, ideological fight. On one side is democracy, on the other is totalitarianism. Pick a fucking side, and live with it.”
This is it. This is that fight. It is not a protest. It is a game of chicken. A high-stakes game of political chicken. In the end, politics comes down to power. The power to force your will on your adversary. GloboCap has been forcing the New Normal on people around the world for the past two years. What we are witnessing in Canada is the power of the people, the power the people have always had, and which we will always have, when we decide to use it … the power to shut down the whole GloboCap show, city after city if necessary.
So get out there and support the Canadian transphobic Putin-Nazi truckers … or your local transphobic Putin-Nazi truckers. Don’t worry if you don’t have a swastika flag. The agents provocateurs and the official propagandists in the corporate media will take care of that!
#
Different vaccines reveal different side effects
MHRA should release the raw data for public scrutiny
Health Advisory & Recovery Team | February 1, 2022
The MHRA Yellow Card reporting system is designed to provide a signal of possible problems with new drugs based on reports of suspected adverse reactions from qualified medical practitioners. The data collected could be of much more value if more details were published. The MHRA shares such information with the pharmaceutical industry but, despite its role being to protect the public and relying on public funding, this data is not put into the public domain.
To make the most of what information is available the reports on different vaccine types can be compared. Any side effects that are a result of the production of the spike protein itself may be similar between all vaccine types. However, if one vaccine type has a much higher rate of a particular adverse effect than other vaccine types then this is suggestive of a genuine causal relationship. Confounders such as age may account for part of these differences, which is why publishing the raw data is so important.
Data sharing
The Yellow Card scheme is administered by the MHRA, a government body funded, at least in part, by the public. The data for the scheme is collected largely by NHS staff, who are again funded by the public. However, despite public finance being crucial to the generation of Yellow Card data, the MHRA have refused to release the anonymised individual patient data from this scheme for independent analysis (FOI 21/640). The MHRA argue that release of these data would be too onerous, yet paradoxically these same data are passed on to the vaccine manufacturers for analysis as a matter of routine (FOI 21/942). All that the public can access from Yellow Card is a rudimentary summary of the total numbers of adverse events recorded for each vaccine type in particular medical categories.
The MHRA’s attitude to data sharing stands in stark contrast to the situation in the USA, where the VAERS reporting system [2] provides anonymised individual patient data, and the detailed analyses that this allows has been crucial for recognising important safety signals [3] — albeit US Regulators have been slow off the mark in making full use of the data available to them. We note that the MHRA’s refusal to share the information that they hold within the Yellow Card database would not be tolerated in the general science community where access to raw data is now a prerequisite for publication in peer reviewed journals.
Despite the intransigence of the MHRA over the issue of releasing raw data from the Yellow Card scheme to the general public, it is incumbent upon the scientific community to make the maximum use of the data released from the scheme to scrutinise the validity of the conclusions that the MHRA reach in their weekly reports. This is particularly important to achieve because, despite FOI requests to see the scientific analyses on which their conclusions are based, the MHRA have been unable to produce any such reports (FOI 21/942).
Comparing frequency of reports by vaccine type
The weekly data released from the Yellow Card scheme takes the form of the total number of doses of each of the vaccines given, the total number of reports filed for each vaccine type, and the total number of adverse reactions recorded for each of a huge range of medical conditions compiled separately for each of the vaccine types. What insights can we gain from analysis of this information?
A simple question that we can ask is whether the different vaccines elicit the same or different rates of reporting of adverse reactions or number of reactions per report. The answer is clear (Table 1). There is something about a Moderna injection that generates a higher frequency of adverse event reports with less reactions per report than an Astrazeneca vaccination, which in turn generates a higher frequency of reports and more reactions per report than a Pfizer injection. The figures involved are so huge that these differences cannot be due to chance. There is something important happening that needs to be explained.
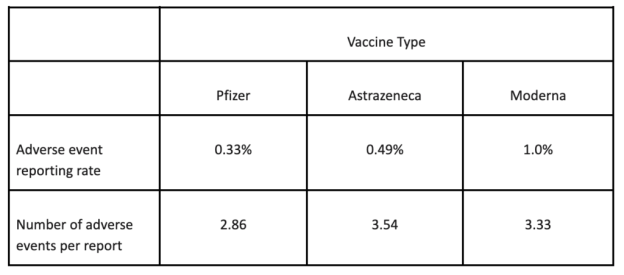
Table 1. Percentage of vaccinations resulting in a Yellow card report, and mean number of adverse events per report for three covid-19 vaccines administered in the UK
Risk of misinterpretation
Unfortunately, however, our interpretation can never be secure. The results we see could be due to the vaccines themselves. Alternatively, they could also be due to some confounding factor like the differences in age profile of the patients who were injected with different vaccine types, or to certain vaccine types being injected predominantly as boosters, or some combination of such factors. Yet distinguishing between alternative explanations is vital. If the effects we see are indeed due predominantly to vaccine type, this would have serious implications for vaccination policy and optimum choice of vaccine for minimising adverse reactions. However, analysis of confounding effects can only be achieved if the raw, anonymised individual patient data from the Yellow Card scheme are released by MHRA.
Comparing type of report by vaccine type
The second type of question that we can address using the Yellow Card data is whether choice of vaccines affects the spectrum of medical conditions recorded as adverse reactions. To answer this question, we can first sum up the number of adverse events elicited by each vaccine under the broad headings Blood & Vascular, Cardiac, Immune, Reproductive & Breast, Respiratory, Skin, Nervous System, Eye, Muscle and Other. A simple test for heterogeneity indicates that the relative frequency with which these classes of adverse reactions occur is highly dependent on the type of vaccine administered (χ2(18) = 29508, P<<0.001). Figure 1 illustrates the percentage by which the observed numbers of adverse reactions differ from the number expected if all vaccines elicited the same spectrum of adverse reactions. It is clear from the figure that departures from expectations are particularly large in the categories Blood & Vascular, Cardiac, Reproductive & Breast, and Skin; the different vaccines are eliciting quite different relative frequencies of adverse reaction in these categories.
For the categories Blood & Vascular, Cardiac, and to a lesser extent Immune and Reproductive & Breast, much higher than expected numbers of adverse reactions are elicited when the mRNA vaccines are administered, and lower than expected numbers of adverse reactions are found when the virus vectored Astrazeneca vaccine is used. Given that the same spike protein is encoded in the mRNA and virus vectored vaccines, this suggests that differences in the observed spectra of adverse reactions may be related to the mode of delivery of the spike encoding nucleic acid sequence in the vaccine. This observation for the Cardiac category is in agreement with a recent case series analysis which found that the risk of myocarditis is greater following sequential doses of mRNA vaccine than sequential doses of the adenovirus vaccine [4]. The role of the mRNA vaccine delivery system itself in eliciting adverse reactions must therefore come under scrutiny.
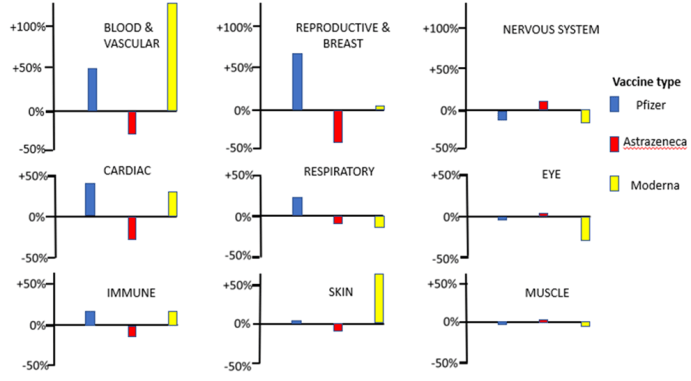
Figure 1. Percentage deviation of observed number of adverse reactions from the number expected if the spectrum of adverse events was the same for all vaccines. Data from nine different categories of adverse events are shown
While this example shows that the Yellow Card data may be helpful for generating ideas and supporting other studies, the inadequacy of the partial information currently released by the MHRA means that our interpretation of such data will always be compromised. Again, we do not possess the means to control for possible confounding factors (age and sex of individual, vaccine dose number etc.) that could contribute to the results observed. Nevertheless, in this example, the sheer size of the apparent effects of vaccine type on the spectrum of adverse effects indicates that a thorough investigation is essential. If the vaccine effect were confirmed, this would have serious real-world implications for the Covid-19 vaccination programme and the safety and health of the UK population.
Conclusion
The data we need to carry out the necessary analysis to maximise the usefulness of the Yellow Card scheme has already been collected at the public expense and is currently held by the MHRA. We call upon the MHRA immediately to release the raw, anonymised, individual patient data from the Yellow Card reporting scheme to enable rigorous scrutiny of Covid-19 vaccine adverse events by doctors, researchers and the public. This echoes the recent call by BMJ editors for immediate release of raw data from trials conducted by vaccine manufacturers [5].
2. https://www.cdc.gov/vaccinesafety/ensuringsafety/monitoring/vaers/index.html
3. https://jessicar.substack.com/p/a-report-on-myocarditis-adverse-events
4. https://www.medrxiv.org/content/10.1101/2021.12.23.21268276v1
5. Doshi P, Godlee F, Abbasi K. Covid-19 vaccines and treatments: we must have raw data, now BMJ 2022; 376 Covid-19 vaccines and treatments: we must have raw data, now | The BMJ
Featured Video

The Search for Truth: Charlie Kirk’s Assassination One Year Later
or go to
Aletho News Archives – Video-Images
From the Archives
The 9/11 “Double-Cross” Conspiracy Theory
BY LAURENT GUYÉNOT • UNZ REVIEW • SEPTEMBER 6, 2022
Is it true that “9/11 was an inside job”? Yes, insofar as Israel is “inside” the U.S. But for the 9/11 truthers who have identified Israel as the main perpetrators, “9/11 was an inside job” is at best a half-truth, and at worst an integral part of the Zionist operation, like a secondary flag sewn as a lining under the false flag of Islamism. Victor Thorn (1963-2017) wrote in his book 9/11 made in Israel: The Plot Against America (2011): “In essence, the ‘9-11 truth movement’ was created prior to Sept. 11, 2001 as a means of suppressing news relating to Israeli complicity. . . . The slogan ‘9-11 was an inside job’ was quite possibly the greatest example of Israeli propaganda ever devised.” In milder terms, it is “controlled opposition”.
A genuine truth movement would have pointed to Israel as the prime suspect from the start. From day one, it was obvious who would benefit. … continue
Blog Roll
 Aletho News
- Europe’s mounting social chaos… chickens coming home to roost for proxy war against Russia
- US-Russia Diesel Deal Becomes Massive Defeat for Ukraine
- Hormuz and the Looming Economic Catastrophe
- Dhubab offensive, media blitz and the rapid unraveling of Saudi-backed coalition’s new gambit
- Putin Conveys to Trump Iran’s Vision on Possible Conflict Resolution – Kremlin
- The Search for Truth: Charlie Kirk’s Assassination One Year Later
- ‘Harsh reality’: Iran says France seeks monopoly on power and intimidation, not peace for all
- When Will This White House Madness End?
- Huckabee aide goes to ‘unusual lengths’ to portray ‘Israel’ positively
- Trump Announces Diesel Supply Deal With Putin Following Phone Call
- If Americans Knew
- Israeli forces kill another child in Gaza – Daily Update
- Gaza ceasefire exists in name only, say more than 100 organizations
- Nearly 2 Million in Gaza Need Urgent Shelter Assistance as Winter Looms: IOM Chief Warns
- Suppressing Palestinian resistance: US charity under fire for AI monitoring of Gaza classrooms
- Thousands Are Held in Israeli Torture Camps. This Is What Happens Inside
- Israel puts Gaza’s sick, injured, newborn in peril – Daily Update
- Report claimed Mark Levin used by Israeli government to influence Trump
- Over 2,000 Gazans have died awaiting medical evacuation amid Israel’s continued siege
- How a U.S. Diplomat Suppressed and Altered Reports Critical of Israel
- 5 Palestinians Die from Israeli Strikes in Gaza as Relentless Attacks Continue
- No Tricks Zone
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative

