The English data on vaccines and mortality, revisited
By Alex Berenson | November 28, 2021
Last Saturday morning I posted a short post with a very simple chart – two lines in all.
One line tracked the number of weekly deaths per 100,000 vaccinated people aged 10-59 in England. The other tracked the number of deaths per 100,000 unvaccinated people in England. The chart showed that vaccinated people in this age group were dying overall at a higher rate than unvaccinated people.
I’m never exactly sure which posts will “land” – gain traction and go viral. This chart landed. Hard. Someone wrote me that it broke the Internet. It didn’t break the Internet, only Kim Kardashian’s ass can break the Internet, but it has rocketed around ever since. It has been seen over 800,000 times on this page alone and many millions more in screenshots and Twitter posts elsewhere.
Clearly, the reason the chart has gained so much attention is that it quickly and simply provides a way for people who are concerned about the vaccines to provide apparent visual proof that they are increasing all-cause mortality – overall death rates.
The chart has also engendered a fierce backlash from the usual fact-checkers and vaccine fanatics who say it is – wait for it – “misinformation.” (To be clear, I didn’t actually create the chart, but I checked the underlying British government report to make sure it accurately represents the report’s figures. It does, as everyone agrees.)
The “fact-checkers” have two primary complaints about the chart.
The first is that the vaccinated and unvaccinated groups are not exactly the same. A smaller percentage of teenagers than fifty-somethings are vaccinated, so the unvaccinated group overall skews somewhat younger than the older group. Since death rates rise with age, that difference may be enough to explain the gap between the two groups.
The second is that overall death rates in people over 60 (who are not covered in the chart) are much higher than those in the 10-59 range and appear to be lower in the vaccinated over the unvaccinated.
Another way to look at the objections: the first is that the chart doesn’t say what it seems to say, because of a hidden flaw in the data. The second is that it would be basically meaningless even if it did, because other more robust datasets contradict it.
—
Part of being on Team Reality is acknowledging reality, and acknowledging when your critics have a factually correct objection. So I want to acknowledge that, like the chart itself, these objections BOTH are valid and factually accurate, viewed individually.
What the fact-checkers and vaccine fanatics appear incapable of understanding is that the two objections effectively cancel each other out – and do nothing to address concerns over the long-term failure of Covid vaccines or their impact on all-cause mortality.
These folks think they are sophisticated thinkers who have blown up apparent evidence that the vaccines are dangerous. In fact, just as they have for the last several months, they are telling themselves what they want to hear instead of listening to what the data are saying – and, increasingly, shouting.
—
They have identified and latched on to ONE complication of using population-level data to judge vaccine effectiveness – the fact that differing rates of uptake by age may make the Covid vaccines seem less effective than they are.
But they – deliberately or out of ignorance – are ignoring another one, one that makes the vaccines seem MORE effective than they are.
The second problem is not a secret to epidemiologists.
It has been quietly discussed for flu vaccines for more than a decade, and I have written about it repeatedly in the last year. The problem is this: the popular belief that sick people are more likely to be vaccinated than healthy people is entirely wrong.
People who receive vaccines are healthier overall than those who do not. They care more about avoiding sickness, and they have the time and energy and money to find their way to a vaccination site. They are not healthier because they get vaccines; they get vaccines because they are healthier.
Older people who receive flu vaccines die – of both the flu and all causes – at much lower rates than unvaccinated people after they receive flu shots. But they also die at much lower rates BEFORE they receive the vaccines. The seminal study demonstrating this relationship is now more than 15 years old; it was published in the International Journal of Epidemiology in April 2006.
“The reductions in risk before influenza season indicate preferential receipt of vaccine by relatively healthy seniors,” the authors wrote.
This paradox helps explain why a huge study of flu vaccines in the United Kingdom showed that increasing vaccination levels in older people did not reduce the number of hospitalizations or deaths from the flu.
The researchers took advantage of the fact that Britain prioritizes people 65 and older for vaccinations and that people are much more likely to get a shot when they are 65 or 66 than 64 or 63. Vaccination levels rose sharply as people turned 65, but the health of the people who received the shots did not improve.

(SOURCE: https://www.acpjournals.org/doi/10.7326/M19-3075?url_ver=Z39.88-2003&rfr_id=ori:rid:crossref.org&rfr_dat=cr_pub%20%200pubmed)
The same pattern is visible in the United States, where a massive increase in the number of flu vaccines in the last generation has made no apparent difference in the number of flu deaths. In fact, in 2005, researchers noted that although vaccinations had risen from 20 percent of elderly people in 1980 to 65 percent in 2001, “unexpectedly, estimates of influenza-related mortality in this age group also increased [emphasis added] during this period.”
In other words, influenza vaccines only seem to work. Any observational estimate that compares death rates in people who have gotten shots to those who have not will be inherently untrustworthy, no matter how hard researchers try to correct for the healthy recipient bias.
—
What is true for flu vaccines appears to be even more true for Covid vaccines.
The relentless vaccination push means that in many countries, more than 90 percent of elderly people are vaccinated. The split is even more stark in countries like England, where 2.44 million people 80 and over have been fully vaccinated, compared to 69,000 who are unvaccinated (and 24,000 who have received the first dose but not the second).
Look at those numbers again.
2,440,000 people in England 80 and over vaccinated. Almost 97 percent of the total number of elderly people.
69,000 80 and over unvaccinated. Less than 3 percent.
These two groups cannot remotely be compared.
How do they differ? I can’t find any hard data, but we know that at least a fraction of the elderly unvaccinated are too ill to be vaccinated. Some are in hospice care. Norway recommended against giving people in hospice the Covid vaccine in January following deaths in terminally ill patients.
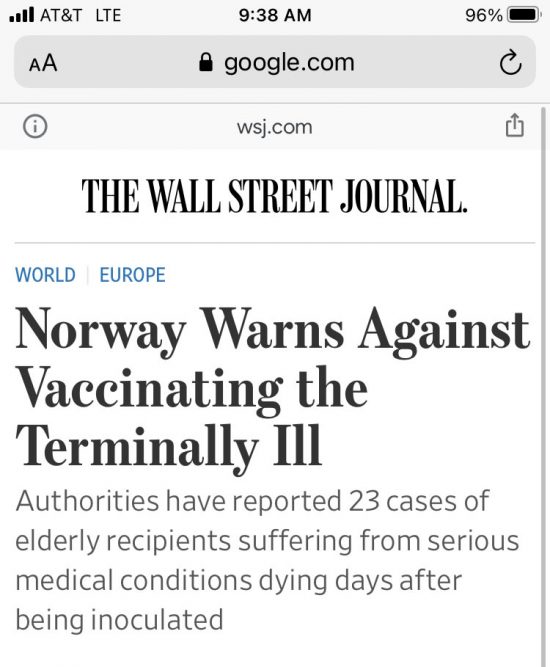
A paper published online in March in the Journal of Pain and Symptom Management noted that “communication from hospice organizations has primarily emphasized the vaccination of hospice staff without the same priority mention for patients” and called for hospices to do more to offer vaccines to patients.
The paper’s title was even starker:
A Shot at Inclusion: Reconsidering Categorical Exclusion of Hospice Patients from COVID Vaccine Allocation.
How many Covid deaths in unvaccinated elderly people are actually “with Covid” deaths in people dying in hospice? Again, we don’t know. But what we know is that even a small number of those deaths will hopelessly bias the relative risk ratio for unvaccinated to vaccinated Covid deaths, because the overall number of unvaccinated people is so small.
As of September, about 30 to 35 unvaccinated English people 80 and over died of or with Covid each week, compared to about 250 fully vaccinated people a week.
So trying to measure vaccine effectiveness by looking at the relative risks of the vaccinated and unvaccinated elderly is impossible. But that is exactly what the health authorities and their servants in the media do when they put out figures that seem to show the risk of death from Covid is much lower in elderly people who have been vaccinated.
They are lying with truthful data, and they (some of them, anyway, though probably not the reporters who are writing the stories) are smart enough to know exactly what they’re doing.
—
Meanwhile, they are ignoring a much more important indicator – trends in both Covid and all-cause mortality are very much going the wrong way in the vaccinated elderly population.
In the last four weeks for which British data are available, roughly coinciding with September, about 1,000 vaccinated English people 80 and over died from Covid and 16,000 from all causes.
Compare those numbers to four weeks in May, when fewer than 70 vaccinated English people 80 and over died from Covid and 13,000 from all causes.
Put another way, overall deaths rose more than 20 percent in the vaccinated elderly from May to September, and Covid deaths 15-fold. And this was not because many more people were vaccinated. The number of vaccinated elderly people rose only about 4 percent from May to September.
Compare that to the mortality trends in unvaccinated English people 80 and over.
About 800 died of all causes in four weeks in May (at the time, there were about 77,000 unvaccinated elderly people, compared to 69,000 in September). Fewer than 20 of those died of Covid.
In September, about 140 unvaccinated elderly people died of Covid – a eight-fold increase compared to the 15-fold increase in the vaccinated.
(All data from the British government:
See tables 3 and 4 in downloaded file.)
But that difference isn’t the striking part.
The striking part is that only 700 unvaccinated elderly English people died OF ALL CAUSES in those four weeks in September – FEWER than back in May. (The trend roughly tracked the overall drop in the elderly unvaccinated population. It appears that about 1 percent of those folks die a month, at least in warmer months.)
This trend is stunning for two reasons.
First, the fact that 100 more unvaccinated elderly people (supposedly) died of Covid in September yet 100 fewer of them died overall strongly suggests that many of those reported deaths are actually with and not from Covid.
Second, per capita all-cause mortality – not just Covid mortality, all-cause mortality – rose close to 20 percent in the very large group of the vaccinated elderly. Some of those extra deaths came from Covid. But most did not.
And though death rates are still somewhat higher in the unvaccinated – as they should be, given the fact that vaccine recipients are healthier – but that fact is far less relevant than the notable rise in the vaccinated.
What’s behind the rise in those deaths in the vaccinated elderly? We don’t know. But we’d better find out. Especially since we are now stuffing boosters into their arms.
—
All of this is somewhat complicated, I’ll admit. The data has lots of confounders and continues to evolve. And trying to explain relative changes in all-cause mortality in the context of healthy vaccine recipient bias using papers about flu vaccine – well, it’s not a soundbite.
Which comes back to the chart from last week.
The chart IS a soundbite.
It is a simple and factually accurate way to say:
Something is wrong. The promises that the health authorities have made over the last 12 months about the vaccines are not coming true. Despite near-complete levels of adult vaccination in Europe, many countries are seeing skyrocketing Covid cases and deaths. And worst of all, all-cause non-Covid mortality is running well above normal in country after country.
Not everyone is going to wade through this article. But everyone can read that chart from last week. It’s not perfect, but it uses real data to raise a crucial issue.
That’s why it landed. And that’s why the vaccine fanatics hate it so much.
What’s the Truth About Covid Vaccines and Heart Attacks?
By Will Jones • The Daily Sceptic • November 27, 2021
A further three football players collapsed during play this week, bringing new interest to the question of what might be the connection between this unusually high number of on-field medical emergencies and the Covid vaccines. Football pundit Trevor Sinclair got into hot water for raising the question on-air, while scientists argued that the disturbing trend is more likely to be a consequence of Covid itself than the vaccines.
Presumably something lies behind the recent rise, which according to some analysts has involved 21 sudden deaths (most heart-related) of FIFA players so far in 2021, compared to around 4.2 in an average year (with a standard deviation of 2.0). Assuming this isn’t a reporting phenomenon, this is an extraordinary spike and highly statistically significant.
The two major unusual factors this year are the presence of SARS-CoV-2 and the Covid vaccination programme. However, only two such deaths were reported in 2020, when Covid was also around, which would seem to lend weight to a vaccine explanation.
The vaccines are known to affect the heart and cardiovascular system in some cases, which is why blood clots and heart inflammation (e.g. myocarditis) are among the side-effects listed and why a number of countries have ceased using some of the vaccines in younger age groups. This means the idea that there could be a link between an unusual spate of heart-related emergencies and the vaccines shouldn’t be dismissed out of hand.
On the other hand, some studies have shown that the risk of developing myocarditis is substantially higher following SARS-CoV-2 infection than vaccination.
A number of scientists have pointed out that insofar as cardiovascular problems arise from the effect of the SARS-CoV-2 spike protein (and there seems to be some agreement that the spike protein is a large part of the causal story here) a bout of SARS-CoV-2 exposes the body to at least as much spike protein as a course of vaccination. Against that, those who suspect that the vaccines are playing a key role say that in fact most SARS-CoV-2 infections are not systemic but remain localised to the respiratory system, so have little impact on the cardiovascular system, whereas vaccination always allows the spike protein to have a systemic impact by gaining easy access to the bloodstream.
This matter would seem to merit much closer and more urgent attention than it appears to be receiving from regulators. It should be straightforward for those with access to the relevant data (most of which unfortunately is not publicly available) to analyse cardiovascular deaths according to vaccination status and prior infection status to see if there are patterns that may be a signal of concern.
An abstract appeared in the leading journal Circulation earlier this month which concluded: “The mRNA vaccines dramatically increase inflammation on the endothelium and T cell infiltration of cardiac muscle and may account for the observations of increased thrombosis, cardiomyopathy, and other vascular events following vaccination.” There was no study to accompany the abstract, however, and it has been heavily criticised by some specialists. Nonetheless, leading NHS Consultant Cardiologist Dr Aseem Malhotra stuck his neck out this week on GB News to reveal that a cardiology researcher colleague found similar results, but was not prepared to publish for fear of the repercussions for his or her career: “They aren’t going to publish their findings, they are concerned about losing research money.”
What are the wider trends in deaths?
Since July, ONS data shows there have been 20,823 excess deaths in England and Wales, with 11,531 involving Covid, leaving 9,292 excess deaths from other causes (if we make the conservative assumption that all Covid deaths are excess deaths).
Analysis of cause of death data for England shows that between July 4th and November 5th 2021 there have been 3,095 excess deaths involving heart failure, of which 854 could be put down to COVID-19, leaving 2,241 from other causes; 4,460 excess deaths involving ischaemic heart diseases, of which 1,413 could be Covid, leaving 3,047 from other causes; 1,307 excess deaths involving cerebrovascular diseases, of which 489 could be Covid, leaving 818 from other causes; and 8,109 excess deaths involving ‘other circulatory diseases’, of which 3,357 could be Covid, leaving 4,752 from other causes. These categories can overlap – a death certificate can mention more than one of them – so the figures can’t simply be added to get a grand total, and the underlying cause could be recorded as something different. Nonetheless, we are talking about thousands of additional cardiovascular deaths since the summer.
Despite this, ONS data shows that deaths where the underlying cause was cardiovascular have been below average in this period. At the same time, deaths where Covid is recorded as the underlying cause account for only a fraction of cardiovascular deaths in the period. So what was the underlying cause of all these excess deaths involving cardiovascular conditions that weren’t Covid either? A query to the ONS came back suggesting that it was down to the significant excess in deaths where the underlying cause was recorded as “symptoms, signs and ill-defined conditions”. In other words, we don’t really know. So according to official data, there have been thousands of excess deaths involving cardiovascular conditions in the past four months, but the underlying cause of many of those deaths is unknown. This would seem to warrant further investigation, and since the vaccines may be implicated, without delay.
31,014 Deaths 2,890,600 Injuries Following COVID Shots in European Database of Adverse Reactions
Young, Previously Healthy People Continue to Die

By Brian Shilhavy | Health Impact News | November 28, 2021
The European Union database of suspected drug reaction reports is EudraVigilance, and they are now reporting 31,014 fatalities, and 2,890,600 injuries, following COVID-19 injections.
A Health Impact News subscriber from Europe reminded us that this database maintained at EudraVigilance is only for countries in Europe who are part of the European Union (EU), which comprises 27 countries.
The total number of countries in Europe is much higher, almost twice as many, numbering around 50. (There are some differences of opinion as to which countries are technically part of Europe.)
So as high as these numbers are, they do NOT reflect all of Europe. The actual number in Europe who are reported dead or injured following COVID-19 shots would be much higher than what we are reporting here.
The EudraVigilance database reports that through November 20, 2021 there are 31,014 deaths and 2,890,600 injuries reported following injections of four experimental COVID-19 shots:
- COVID-19 MRNA VACCINE MODERNA (CX-024414)
- COVID-19 MRNA VACCINE PFIZER-BIONTECH
- COVID-19 VACCINE ASTRAZENECA (CHADOX1 NCOV-19)
- COVID-19 VACCINE JANSSEN (AD26.COV2.S)
From the total of injuries recorded, almost half of them (1,355,192) are serious injuries.
“Seriousness provides information on the suspected undesirable effect; it can be classified as ‘serious’ if it corresponds to a medical occurrence that results in death, is life-threatening, requires inpatient hospitalisation, results in another medically important condition, or prolongation of existing hospitalisation, results in persistent or significant disability or incapacity, or is a congenital anomaly/birth defect.”
A Health Impact News subscriber in Europe ran the reports for each of the four COVID-19 shots we are including here. It is a lot of work to tabulate each reaction with injuries and fatalities, since there is no place on the EudraVigilance system we have found that tabulates all the results.
Since we have started publishing this, others from Europe have also calculated the numbers and confirmed the totals.*
Here is the summary data through November 20, 2021.
Total reactions for the mRNA vaccine Tozinameran (code BNT162b2, Comirnaty) from BioNTech/ Pfizer: 14,526 deaths and 1,323,370 injuries to 20/11/2021
- 35,826 Blood and lymphatic system disorders incl. 207 deaths
- 40,230 Cardiac disorders incl. 2,128 deaths
- 376 Congenital, familial and genetic disorders incl. 33 deaths
- 17,995 Ear and labyrinth disorders incl. 10 deaths
- 1,217 Endocrine disorders incl. 5 deaths
- 20,443 Eye disorders incl. 32 deaths
- 110,658 Gastrointestinal disorders incl. 585 deaths
- 337,450 General disorders and administration site conditions incl. 4,118 deaths
- 1,502 Hepatobiliary disorders incl. 75 deaths
- 14,528 Immune system disorders incl. 76 deaths
- 53,108 Infections and infestations incl. 1561 deaths
- 20,222 Injury, poisoning and procedural complications incl. 240 deaths
- 33,067 Investigations incl. 451 deaths
- 9,103 Metabolism and nutrition disorders incl. 249 deaths
- 164,885 Musculoskeletal and connective tissue disorders incl. 179 deaths
- 1,163 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 114 deaths
- 225,032 Nervous system disorders incl. 1,556 deaths
- 1,851 Pregnancy, puerperium and perinatal conditions incl. 55 deaths
- 206 Product issues incl. 2 deaths
- 24,225 Psychiatric disorders incl. 174 deaths
- 4,667 Renal and urinary disorders incl. 224 deaths
- 43,949 Reproductive system and breast disorders incl. 5 deaths
- 57,013 Respiratory, thoracic and mediastinal disorders incl. 1,617 deaths
- 62,414 Skin and subcutaneous tissue disorders incl. 125 deaths
- 2,765 Social circumstances incl. 19 deaths
- 4,797 Surgical and medical procedures incl. 60 deaths
- 34,678 Vascular disorders incl. 626 deaths
Total reactions for the mRNA vaccine mRNA-1273 (CX-024414) from Moderna: 8,518 deaths and 390,163 injuries to 20/11/2021
- 8,227 Blood and lymphatic system disorders incl. 94 deaths
- 12,657 Cardiac disorders incl. 915 deaths
- 156 Congenital, familial and genetic disorders incl. 6 deaths
- 4,698 Ear and labyrinth disorders incl. 2 deaths
- 348 Endocrine disorders incl. 3 deaths
- 5,731 Eye disorders incl. 29 deaths
- 32,091 Gastrointestinal disorders incl. 326 deaths
- 104,720 General disorders and administration site conditions incl. 2,986 deaths
- 644 Hepatobiliary disorders incl. 40 deaths
- 3,820 Immune system disorders incl. 16 deaths
- 14,668 Infections and infestations incl. 782 deaths
- 8,158 Injury, poisoning and procedural complications incl. 162 deaths
- 7,117 Investigations incl. 143 deaths
- 3,703 Metabolism and nutrition disorders incl. 206 deaths
- 47,355 Musculoskeletal and connective tissue disorders incl. 174 deaths
- 531 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 67 deaths
- 66,320 Nervous system disorders incl. 823 deaths
- 722 Pregnancy, puerperium and perinatal conditions incl. 6 deaths
- 78 Product issues incl. 2 deaths
- 7,100 Psychiatric disorders incl. 142 deaths
- 2,277 Renal and urinary disorders incl. 164 deaths
- 8,061 Reproductive system and breast disorders incl. 7 deaths
- 17,235 Respiratory, thoracic and mediastinal disorders incl. 914 deaths
- 20,963 Skin and subcutaneous tissue disorders incl. 76 deaths
- 1,769 Social circumstances incl. 36 deaths
- 1,374 Surgical and medical procedures incl. 78 deaths
- 9,640 Vascular disorders incl. 319 deaths
Total reactions for the vaccine AZD1222/VAXZEVRIA (CHADOX1 NCOV-19) from Oxford/AstraZeneca: 6,145 deaths and 1,075,335 injuries to 20/11/2021
- 13,124 Blood and lymphatic system disorders incl. 248 deaths
- 19,128 Cardiac disorders incl. 696 deaths
- 195 Congenital familial and genetic disorders incl. 8 deaths
- 12,669 Ear and labyrinth disorders incl. 3 deaths
- 597 Endocrine disorders incl. 4 deaths
- 18,919 Eye disorders incl. 29 deaths
- 102,402 Gastrointestinal disorders incl. 312 deaths
- 283,288 General disorders and administration site conditions incl. 1,469 deaths
- 950 Hepatobiliary disorders incl. 60 deaths
- 4,834 Immune system disorders incl. 29 deaths
- 32,441 Infections and infestations incl. 413 deaths
- 12,358 Injury poisoning and procedural complications incl. 177 deaths
- 23,611 Investigations incl. 150 deaths
- 12,369 Metabolism and nutrition disorders incl. 91 deaths
- 159,668 Musculoskeletal and connective tissue disorders incl. 94 deaths
- 624 Neoplasms benign malignant and unspecified (incl cysts and polyps) incl. 22 deaths
- 221,536 Nervous system disorders incl. 958 deaths
- 521 Pregnancy puerperium and perinatal conditions incl. 12 deaths
- 188 Product issues incl. 1 death
- 19,933 Psychiatric disorders incl. 58 deaths
- 4,031 Renal and urinary disorders incl. 58 deaths
- 15,124 Reproductive system and breast disorders incl. 2 deaths
- 37,980 Respiratory thoracic and mediastinal disorders incl. 735 deaths
- 49,247 Skin and subcutaneous tissue disorders incl. 48 deaths
- 1,498 Social circumstances incl. 6 deaths
- 1,404 Surgical and medical procedures incl. 25 deaths
- 26,696 Vascular disorders incl. 437 deaths
Total reactions for the COVID-19 vaccine JANSSEN (AD26.COV2.S) from Johnson & Johnson: 1,825 deaths and 101,732 injuries to 20/11/2021
- 986 Blood and lymphatic system disorders incl. 40 deaths
- 1,837 Cardiac disorders incl. 155 deaths
- 35 Congenital, familial and genetic disorders
- 1,033 Ear and labyrinth disorders incl. 2 deaths
- 69 Endocrine disorders incl. 1 death
- 1,351 Eye disorders incl. 7 deaths
- 8,500 Gastrointestinal disorders incl. 75 deaths
- 26,871 General disorders and administration site conditions incl. 488 deaths
- 121 Hepatobiliary disorders incl. 11 deaths
- 445 Immune system disorders incl. 9 deaths
- 4,315 Infections and infestations incl. 143 deaths
- 920 Injury, poisoning and procedural complications incl. 18 deaths
- 4,766 Investigations incl. 103 deaths
- 625 Metabolism and nutrition disorders incl. 45 deaths
- 14,897 Musculoskeletal and connective tissue disorders incl. 43 deaths
- 54 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 3 deaths
- 20,097 Nervous system disorders incl. 197 deaths
- 41 Pregnancy, puerperium and perinatal conditions incl. 1 death
- 26 Product issues
- 1,407 Psychiatric disorders incl. 16 deaths
- 417 Renal and urinary disorders incl. 22 deaths
- 2,059 Reproductive system and breast disorders incl. 6 deaths
- 3,617 Respiratory, thoracic and mediastinal disorders incl. 234 deaths
- 3,094 Skin and subcutaneous tissue disorders incl. 8 deaths
- 319 Social circumstances incl. 4 deaths
- 690 Surgical and medical procedures incl. 54 deaths
- 3,140 Vascular disorders incl. 140 deaths
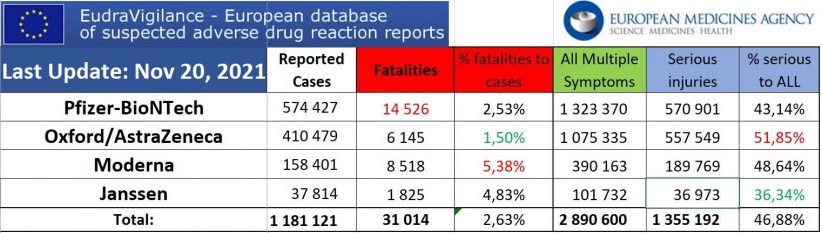
*These totals are estimates based on reports submitted to EudraVigilance. Totals may be much higher based on percentage of adverse reactions that are reported. Some of these reports may also be reported to the individual country’s adverse reaction databases, such as the U.S. VAERS database and the UK Yellow Card system. The fatalities are grouped by symptoms, and some fatalities may have resulted from multiple symptoms.
Higher Infection Rates in Vaccinated Not an Artefact of Wrong Population Data, New Analysis Shows
By Will Jones • The Daily Sceptic • November 26, 2021
Back in October, when the critics rounded on the UKHSA for publishing vaccine data that didn’t fit the narrative, front and centre of their complaints was the claim that they were using poor estimates of the size of the unvaccinated population, and thus underestimating the infection rate in the unvaccinated. Cambridge’s Professor David Speigelhalter didn’t hold back, writing on Twitter that it was “completely unacceptable” for the agency to “put out absurd statistics showing case-rates higher in vaxxed than non-vaxxed” when it is “just an artefact of using hopelessly biased NIMS population estimates”.
To the UKHSA’s credit, while it conceded other points, it never gave in on this one, sticking to its view that the National Immunisation Management System (NIMS) was the “gold standard” for these estimates. It pointed out that ONS population estimates have problems of their own, not least that for some age groups the ONS supposes there to be fewer people in the population than the Government counts as being vaccinated.
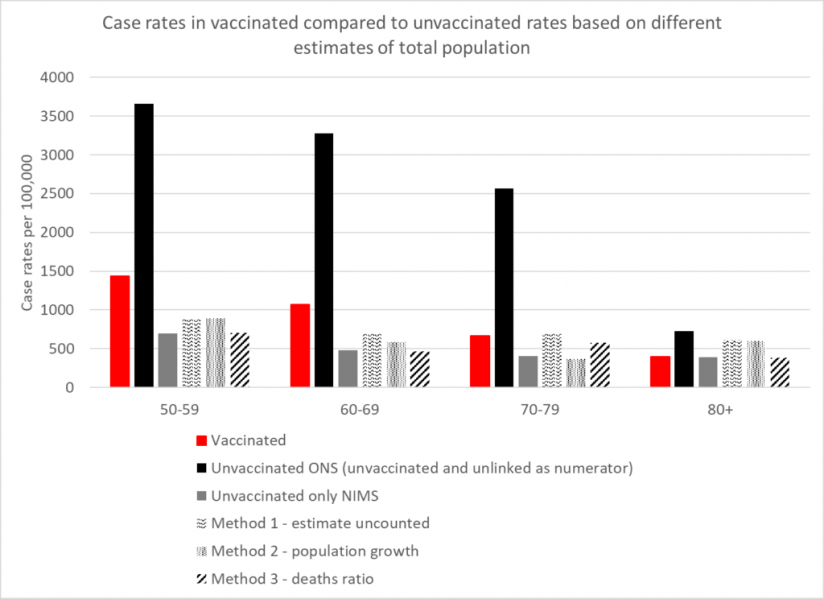
How can we know which estimates are more accurate? A group of experts has applied analytical techniques in order to estimate the size of the unvaccinated population independently of ONS and NIMS figures. Using three different methods, experts from HART found that estimates from all three methods were in broad agreement with the NIMS estimates, whereas the ONS estimate was a much lower outlier.
The first method involves recognising that people not within the NHS database system still catch Covid and still get tested. Assuming these people have the same infection rates per 100,000 people as the unvaccinated, you can calculate how many people there are outside of the database system and add these to the NIMS totals.
The second method involves looking at the rate of growth of people with an NHS number, which has been remarkably steady at around 2.9% per year. If you assume that people who are not yet registered in the NHS will sometimes become sick enough to seek healthcare, and thus a record will be created for them, applying this growth rate to the 2011 ONS population estimates give another figure for the total population.
The third method involves assuming that, in low-Covid weeks, deaths within an age bracket should occur at a similar rate in vaccinated and unvaccinated, allowing the size of the total population to be inferred from the percentage of deaths in the unvaccinated.
The results in terms of reported infection rates according to the five different estimates are depicted in the chart above. They show that the ONS is a clear outlier, its estimates sitting far too low, and NIMS is likely to be much more accurate. The ONS puts the unvaccinated population at around 4.59 million whereas NIMS puts it at 9.92 million, a difference of 5.33 million. That’s a lot of people not to be included in estimates, and suggests, among other things, that the ONS has not adequately estimated the magnitude of illegal immigration into the country.
As well as vindicating the UKHSA in its decision to stick with NIMS over ONS, HART’s analysis also indicates that, contrary to the assertions of Prof Spiegelhalter, the UKHSA data showing infection rates higher in the vaccinated compared to the unvaccinated is not a mere artefact of using the wrong population estimates. There may be other biases in it, but this is not one of them.
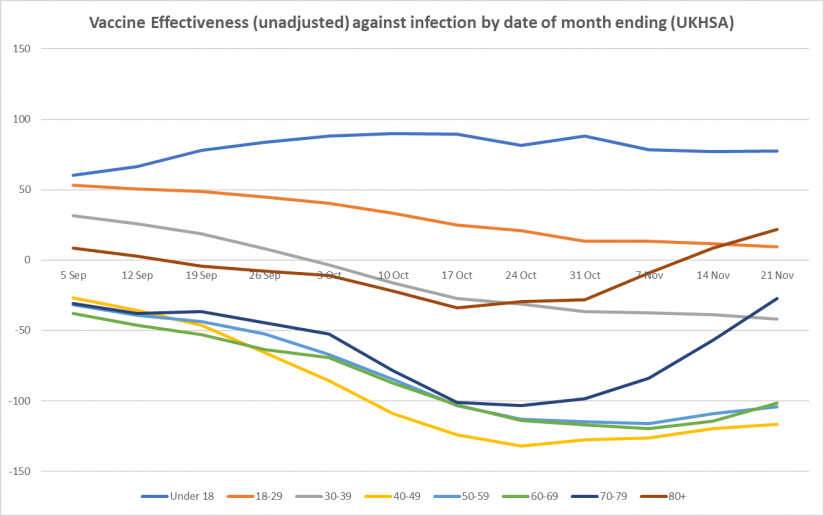
Here is the weekly update on unadjusted vaccine effectiveness based on the raw data in the UKHSA Vaccine Surveillance report. The unadjusted vaccine effectiveness estimates against infection have remained low in all adult age brackets this week, particularly in those aged 40-70, though there is little sign of further decline; in the older age groups (over 40), the recent vaccine effectiveness revival continues, possibly as a result of the third doses. There is also a sign of a rise in vaccine effectiveness against hospitalisation in the over-70s.



more early takes on omicron variant
reports from SA indicate that the virus is VERY mild
el gato malo | bad cattitude | november 28, 2021
aside from all the breathless reporting about “MOAR SPIKE MUTATIONS!!” i have yet to see a single report with any actual clinical evidence that the newly branded omicron variant is anything other than less dangerous than delta was.
it’s just, to steal a wonderful quote “mutational stargazing.”


this makes sense. not only are we continuing to evolve AWAY from an what looks near certain to be a lab engineered virulence optimum, but this is the natural path of viral evolution.
delta was a deeply attenuated version of prior versions. it’s original CFR was around 0.1%. this rose sharply over the summer as vaccine fade hit and this rise affected the vaccinated and the unvaccinated alike, so it appears to be a property of the virus, not of the vaccines. it was also mirrored by all cause mortality and so appears to be a real rise in fatality, not a definitional artifact.
i will still bet dollars to doughnuts that it was the vaccines themselves that, by being leaky but semi-protective, drove this inverted gradient to hotter strains.
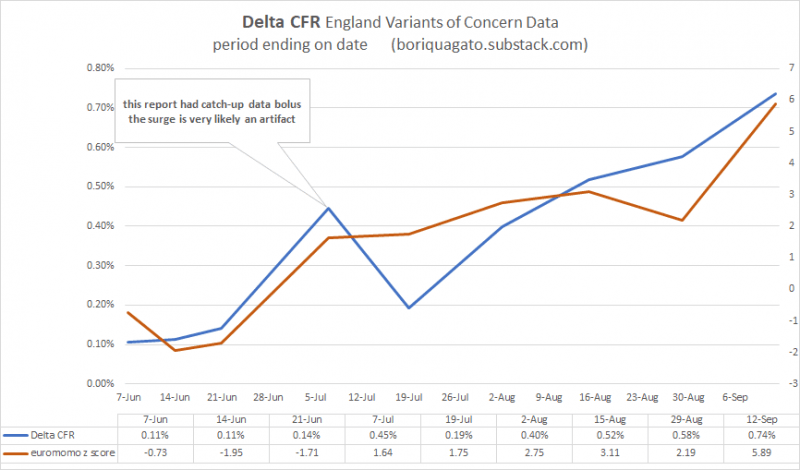
full discussion and data HERE.
a virus “wants” one thing: to spread. make a copy of me and pass it on. that’s the whole ballgame. harming the host and incapacitating them is maladaptive to this goal. mild viruses spread better. asymptomatic viruses spread best of all.
and that looks more and more like the case here. omicron looks milder than delta, especially than the souped up delta strains that emerged over the summer.

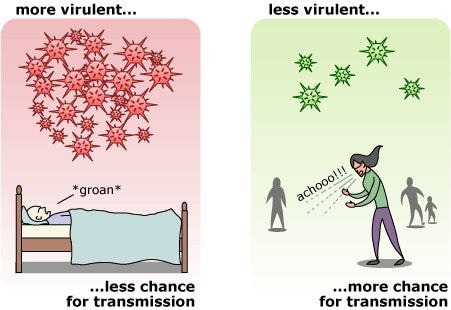
this is good news, not a reason for terror. the ideal outcome would be a virus with no symptoms and infinite spread that would immediately inoculate everyone.

primary symptoms appear to be lethargy. loss of taste and smell is largely absent.
as this virus looks to outcompete delta, but with lower risk, the idea that we want to keep it out seems exactly wrong. this is the variant you want. more spread, considerably less risk, mostly asymptomatic, but will generate the real, sterilizing immunity that the vaccines do not.
this is how pandemics end, not how panics should begin.
watching the west once more lose its collective mind is just pathetic.
based on the early looks, this is not even a chipmunk in the road to swerve around, it’s the shadow of a chimpunk and it’s a less dangerous strain that the one we currently have and another even lower risk bite at the immunity apple.
whether it will follow delta in terms of vaccine mediated evolution toward hotter future strains is anyone’s guess (and certainly possible) but if it is, indeed, destined to do so, then that’s all the more reason to let it spread now.
“we should panic in case it turns out we need to panic” is simply not a basis for public health.
pandemics can and do end themselves and it’s become manifestly obvious that the vaccines developed here and pushed endlessly as panacea are of little to no help in that regard and quite a strong case to be made that they have made it, overall, worse for everyone, including the vaccinated.
boosters, lockdowns, and travel bans are not the way out. the generation of low risk natural herd immunity is.
it is long past time we stopped playing these stupid games.
the prizes we stand to win are not going to get any less stupid this time…
We are mandating a vaccine where there is no scientific evidence that it has ever saved a single life
BMJ notes we will NEVER have the evidence, vaccine makers structured the trials to avoid proving an all-cause mortality benefit since they know it’s negative
By Steve Kirsch | November 27, 2021
If you are are still in doubt as to whether we are being hoodwinked on the safety and efficacy of the COVID vaccines, this Editorial in the BMJ today should remove all doubt. We are being hoodwinked. And it’s not going to get better. Ever. So we are stuck with a vaccine that is being mandated where most people have no fu*&($#ing clue as to whether it works or not.
Why? It’s simple. They know full well from the VAERS data that the vaccine kills far more people than it saves (regardless of age) and they want to make sure you will never find out.
Get it?
Those of us who know how to interpret the safety data from VAERS and other similar systems know full well what is going on, but when we try to warn people, we are being marginalized as spreaders of misinformation. Who’s lying? Well, suffice it to say that no self-proclaimed VAERS expert will agree to a debate.
Note: For those of you upset about the headline, sure, they can argue that the COVID vaccines saved people from dying from COVID. I concede that. But the all-cause mortality (ACM) rate (which nobody is looking at), has always been far greater than the COVID lives saved.
And that my friends is the inconvenient truth.

Canadian landlord says tenants need to show a vaccine passport to live in building
By Christina Maas | Reclaim The Net | November 27, 2021
Strategic Group, a major rental housing provider in Alberta, Canada, announced that all new tenants need to show a vaccine passport to live in its properties. Critics claim the renter’s vaccine mandate sets a dangerous precedent.
“Vaccination of everyone in our community is the only way we are going to get through this pandemic and back to a sense of normalcy,” said Riaz Mamdani, founder and CEO of Strategic Group, in an October 28 press release.
“The safety of our team and our residents is a top priority, so ensuring full vaccination across the board is the least we can do.”
The press release said that “all employees, residents, and prospective residents” have to be vaccinated. Existing tenants will have to show proof of vaccination. Anyone “unable to be vaccinated (i.e., children under the age of 12) is exempt until able to receive the vaccine.”
“These rules apply to all of Strategic Group’s residential communities in Alberta.”
The renter owns more than 100 1 and 2-bedroom units in Edmonton and Calgary.
The Canadian Press reported that the Strategic Group COO Tracey Steman said that the company was “very proud” of the mandatory vaccination policy.
“And we’d like to see other landlords implement the same policy… It will help to end this pandemic,” Steman continued. “We’ve had really good feedback from our tenants.”
According to the company’s CEO, residents inspired the new policy as they were saying that “they value knowing that all their neighbors are vaccinated – they feel even safer in their own homes.”
Eva Chipiuk of the Justice Center for Constitutional Freedoms (JCCF) told LifeSiteNews that Strategic Group’s vaccine mandate for tenants “sets a dangerous precedent in Alberta and in Canada.”
“According to this renter’s policy, you do not deserve a roof over your head unless you have taken an experimental injection,” said Chipiuk.
“Such a policy, utterly unthinkable two years ago, is now frighteningly announced with pride,” she added.
“Under what authority is this policy being made?”
Chipiuk noted that the laws banning smoking indoors were discussed in “government housing.”
“This is not the same. These rental companies are taking the law into their own hands. If we allow this to happen, what will be next and who will find themselves without a place to live?” the lawyer asked.
In an article on The Lawyers Daily, landlord-tenant lawyer Caryma Sa’d explained why it is illegal for landlords to enforce vaccine passport mandates for tenants. Sa’d noted that refusing a potential client because of their vaccination status is discrimination.
Also, “landlords cannot simply make unilateral changes to the terms of the agreement, which would include imposing proof of vaccination as a condition of the tenancy.”
“This would prevent a landlord from attempting to evict a tenant based on vaccination status, unless it can be established that the tenant is substantially interfering with the reasonable enjoyment of others within the unit or otherwise causing serious problems at the residential complex because of their vaccination status,” the lawyer continued.
The president of the Canadian Federation of Apartment Associations John Dickie told the Canadian Press that it was “possible” for some landlords to follow Strategic Group’s lead and implement a vaccine passport mandate, but that was not likely to be “very widespread.”
“We’re not the health police,” said Dickie.
“Rental housing providers realize people need housing. We’re not in the habit of inquiring into people’s political views.”
PROOF: COVID vaccines cause prion diseases
By Steve Kirsch | November 26, 2021
Twitter suspended my account (likely forever since there is no appeal) due to one post on prion diseases. Here’s the information they wanted to make sure you NEVER find out.
Summary
There is no doubt the mRNA vaccines are causing prion diseases. People didn’t have these diseases before the shot and suddenly they develop them after the shot. There is no other explanation for this. None of the “fact checkers” can explain the cause of the excess rates. Prion diseases are incurable and always fatal. You can die as soon as 6 weeks after COVID vaccination (see within 6 weeks and within 6 months examples).
However, Twitter believes this is not true, but they refuse to tell anyone why they think that. Other fact checkers who have checked this out never did a VAERS query and are unable to explain away the “excess” number of reports other than doing a blanket dismissal that everything in VAERS is fraudulent without providing any evidence of that claim (other than one report out of 1.6M reports).
None of the fact checkers will debate on this to set the record straight.
On November 24, 2021 I posted the following message on Twitter:

Twitter suspended my account hours later. There is no appeal available. All content over the last 12 years was removed. All my 75K followers were zeroed. My messages were removed. There was no opportunity to download my content.
The only thing left: that my Twitter ID was @stkirsch.
Twitter refuses to tell us what I said that was misleading?
Twitter won’t tell me that!!! They are deliberately withholding their definitive analysis on this extremely important scientific issue. Why???
I really want to know. Obviously, Twitter fact-checkers (all of whom I presume must have PhD degrees or MD degrees to be able to assess my claims) were able to quickly read all the medical literature and determine without a doubt I made an error and should be terminated for making a mistake. But they won’t tell me the mistake!!
If they want to fight misinformation, why aren’t they posting a link to their research proving me wrong when they terminate the account. They obviously invested hours of time in the research before they terminated me. Why not provide a link to that research so everyone can learn from it including me??
Here’s the evidence for my claim
Back in May 2021 when Professor Byram Bridle was disclosing the FOIA request on the Pfizer vaccine bio-distribution data he mentioned that the spike protein was associated with Lewy body formation which is linked to prion diseases. He expressed concern that the vaccines could cause prion diseases like dementia, Alzheimer’s, and Creutzfeldt-Jakob disease (CJD).
What do you know. He was right. Now we have proof.
Check out these VAERS query results. These searches are over all 30 years of VAERS and all 70+ vaccines. See anything unusual? Yeah, for less than 1 year of the COVID vaccines, the results are off the charts.
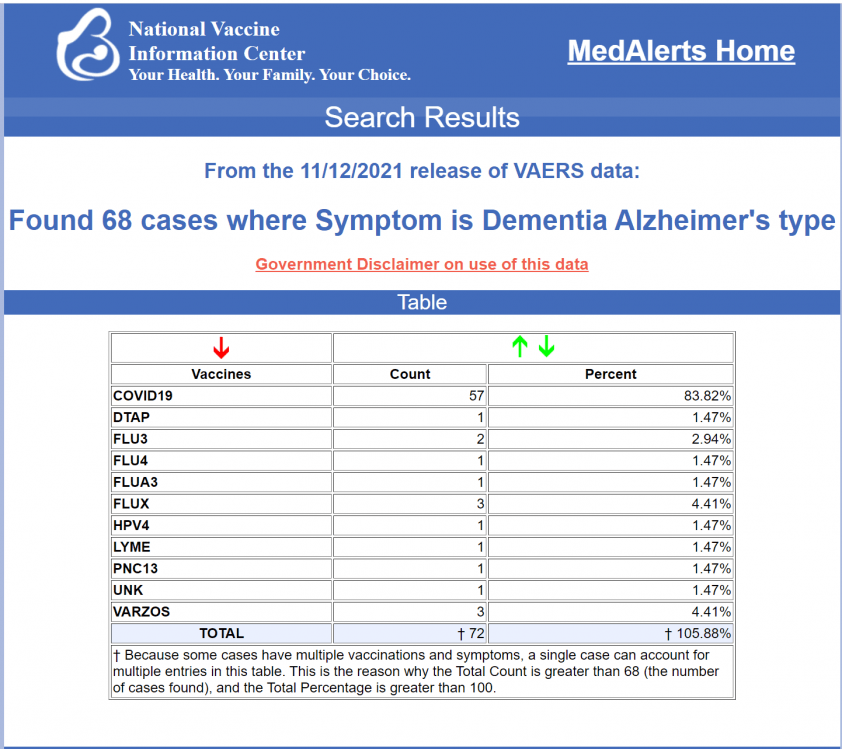
And for CJD which is extremely rare:

Remember, these are 30 year searches for all vaccines. Clearly there are excess reports. And we know VAERS isn’t being “over-reported” this year which I’ve shown many times before (events not caused by the vaccine are reported at rates comparable to other vaccines).
If it wasn’t the COVID vaccines causing this, what was the cause?
Nobody can answer that question, not even the Twitter fact checkers!
For further reading, check out these articles:
- Jessica Rose’s article on COVID vaccines and prion diseases
- Stephanie Seneff’s paper on prion disease and the COVID vaccines
- Bart Classen’s paper linking the vaccines and prion diseases
- SARS-CoV-2 causes brain inflammation and induces Lewy body formation in macaques
- SARS-CoV-2 Prion-Like Domains in Spike Proteins Enable Higher Affinity to ACE2
And compare them to some of the “fact checks” which claim there are no instances in VAERS which as you can see from the queries above (which you can replicate yourself):
You decide who is telling the truth.
And note that the “fact checkers” never did a single VAERS query. Wow. That’s the first place you’d look to prove the claim is false.
Uprising in Guadeloupe

By David Montoute | Fourth World | November 23, 2021
An insurrectional situation has emerged in Guadeloupe. Roads are closed, buildings set on fire, and clashes between demonstrators and security forces are raging. Many Guadeloupeans have decided that, against dictatorship, violence is a legitimate option. It is a violence directed against the so-called ‘health pass’ and against the mandatory vaccination of careworkers imposed upon this overseas territory by Metropolitan France.
In September, France had made it compulsory for all health workers, home carers, transport staff, medical students, firefighters, and all related personnel to have the Covid vaccine. This was accompanied with the requisitioning of all Ivermectin stocks in order to force the deeply unpopular vaccine upon the people of Guadeloupe (as well as neighbouring Martinique). According to French government figures, only 33% of Guadeloupeans are vaccinated (versus 75% in Metropolitan France), with a simiar figure in Martinique.
Tensions rose in October with the arrest of two demonstrators, one of them being Claudine Maraton, the general secretary of the UTS-UGTG (the trade union section of the General Workers Union of Guadeloupe). The UGTG had taken a leading position in the political opposition to the vaccine mandate, a position that the president of the Guadeloupe region also came to echo. As the conflict sharpened, the governing En Marche party’s MP for Guadeloupe began to describe the situation on the island as “quasi-insurrectional”, with opposition to the Covid regulations showing a “weakening state authority” on the island.
The Minister of Health, Olivier Véran seemed to recognise the fragility of France’s position, and decided to push back the deadline for the vaccination mandate to November 15th. But if November 15th marked the end of the ‘health emergency’ measures in most of the overseas territories, in Guadeloupe, it marked the start of an indefinite general strike, launched by a collective of trade union and citizen organisations against the mandatory injection of careworkers and the pass sanitaire. At a press conference at the Palais de la Mutualité in Pointe-à-Pitre, Maïté Hubert M’Toumo, the new General Secretary of the UGTG had already sounded the battle-cry: “From Monday, war is declared!”
“From September, the French state decided to renew hostilities […] all doctors and nurses can receive a notice prohibiting them from working. This means that from Monday, the French state which spoke of war has just declared war on us. The situation is catastrophic. Thousands of workers are affected, whom they want to shamelessly fire, without delay of challenge. We can’t accept that. It’s not possible. The Guadeloupeans are in danger and from the moment war is declared, we are obliged to respond. From Monday, war is declared, there will be nothing that will work, we must organise ourselves so that nothing functions: Monday, Tuesday, Wednesday, Thursday… every day! We have no choice, we must come together, all social and professional classes, all Guadeloupeans. From Monday there will be two camps: the camp of the French state which has decided to defile us and defile all who oppose their plans; and the other side that wants to protect the country in order to live in freedom. The French president said that vaccines are freedom, so freedom is conditioned on a vaccine, a vaccine that is not under control, a vaccine that generates more and more serious side effects. Is this freedom? It’s not possible. So from Monday, war is declared!”

Maïté Hubert M’Toumo
The Departmental Fire and Rescue Service (SDIS), also affected by the mandatory vaccination order, had come to assume a leading role in the protests. As the strike began on the 15th, fights broke out between firefighters and the elite gendarmes, When the gendarmes charged one group, the firefighters responded with jets of water. Other incidents between strikers and police triggered a wave of arrests as the Pointe-à-Pitre prosecutor’s office complained of “repeated threats to a law enforcement officer.” Maïté Hubert M’Toumo denounced the arrests in a public statement, calling them “a serious attack on a fundamental freedom which is the right to strike” and rallying “all members and activists to strengthen the picket lines”. Even as the government sent in hundreds of police and gendarme reinforcements, the strike hardened on the following weekend, with rioting breaking out in Pointe-à-Pitre and across the Island. Several gas stations were closed by protesters, and many motorists raided those that remained open, fearing the strike would impact fuel supplies. As the demonstrations and clashes escalated, shops and pharmacies were torched and looted, while schools, post offices and courts were shut down. Reports surfaced that protestors had broken into an arms depot in the island’s capital, Pointe-à-Pitre, and stolen rifles. Col Jean Pierre, of the gendarmerie at Pointe-à-Pitre, said some of the protesters had fired upon security forces. “We just don’t know how far this will still go,” the city’s mayor, Harry Durimel, told FranceInfo radio.
This weekend, Paris authorities began sending elite police and counterterrorism officers with armoured vehicles to Guadeloupe in a bid to stamp out the uprising. The police reinforcements set about dismantling protesters’ road barricades while the island’s authorities imposed a dusk-to-dawn curfew until Tuesday morning. By Monday the police had arrested at least 38 people charged with looting and smashing shops.
Over the weekend, the main UGTG trade union called for continued protests. Meanwhile, Martinique has followed its neighbour’s example and gone on general strike against the measures dictated by Paris.
The cultural rejection
Guadeloupe – like Martinique – has a deep-rooted history of anti-vaccine sentiment linked to distrust of the Paris government. Political scientist Pamela Obertan, who is helping to organise anti-mandate protests explains that Guadeloupeans “are descendants of slaves, and for us, control over our bodies is really important… The government wants to impose on us a medical experiment. We are still medical experiments.”
For decades, agriculture workers in Guadeloupe and Martinique were exposed to an endocrine-disrupting, carcinogenic pesticide called chlordecone. Around 95% of the population in these two islands is known to register chlordecone in their blood. Studies have linked the pesticide to prostate cancer, and, significantly, Guadeloupe and Martinique have the highest prostate cancer rates in the world. Yet nothing has been done about real health emergencies such as this one. And this goes a long way to explain the distrust towards the metropolis that is felt in the French Antilles. It is this context that has empowered vaccination-refusal, which is now turning into a nationalist and patriotic cause.
Accompanying this development, there is a longstanding usage and trust in folk medicine. As Guadeloupe’s University Hospital director lamented, the vaccine refusniks are “pushing Guadeloupian pharmacology.” From the start of the aggressive push for ”Covid” vaccination, sales of Virapic, a syrup based on the local jackass bitters herb, skyrocketed. This tropical shrub (Neurolaena lobata) is traditionally used for treatment of fever and flu symptoms, wounds and infections, and a variety of parasitic ailments such as malaria, ringworm, and amoebiasis. The plant has found a local champion in pharmacist Henry Joseph, co-founder of the laboratory Phytobokaz. Joseph, claims to have proven the plant’s efficacy against emerging RNA viruses and thus its relevance to ‘Covid-19′.
Whatever comes of such research, the island’s distrust in vaccines is unlikely to abate any time soon. The metropolitan government’s refusal to negotiate, together with the local suppression of data on vaccine deaths will continue to antagonise an already rebellious populace. According to lawyer Maître Ellen Bessis, the University Hospital Center (CHU) of Guadeloupe never declares vaccination status amongst any hospitalisations. This, she says allows them to register vaccinated deaths in Guadeloupe’s hospitals as unvaccinated, which is what she says is happening. Bessis’ claim is based on the extensive testimony of firefighters who, in Guadeloupe, share the job of transporting emergency cases to hospital. As the civil liberties organisation Rester Libre ! says, “If this information were verified, it would be an absolute scandal: a statistical lie designed to hide the dangerousness of the vaccine. It would create a crisis of absolute confidence with the public authorities, and, therefore, all the figures, all the data, could be called into question.”
It is difficult to imagine how the execrable Macron government could possibly backtrack in this conflict, or provide any concessions for Guadeloupe. For to do so would undermine the mandate policy in metropolitan France. Yet the rebellion of the island population can only deepen, as Ellen Bessis affirms.
“We wonder what is going on in the mind of the government!” says Jocelyn Zou, of the fire department’s union. “We Guadeloupeans have a notion of freedom. But they impose compulsory vaccination on us when alternative solutions exist. We have every motivation to fight to the end!”
France to send special forces to Guadeloupe after looting, arson:
RELATED: Martinique and Guadeloupe: Ivermectin stocks are requisitioned to force vaccination
What is happening in Australia’s Aboriginal communities?
OffGuardian | November 26, 2021
The last few days we have heard some alarming reports about how the Northern Territories of Australia are treating their indigenous communities.
Tweets and videos have emerged claiming aboriginal people are being removed from their land and sent to “quarantine centres”, allegedly to protect them from the virus.
Some representatives of the community have sent out videos asking for “international aid”, and claiming Aboriginal communities are being placed under “martial law” and people are being removed from their homes “at gunpoint”
At a protest against the measures, one aboriginal elder was violently arrested by officers witnesses claim were not wearing ID badges.
Another elder, June Mills, posted a video to facebook expressing concern about how difficult it is to get information out of the locked down communities. She says she has heard that the army is “removing people against their will”, ending with the emotive cry “they are killing us!”
Australia has been so rapidly descending into a fascist hellhole that none of this, if true, would be at all surprising. The very fact they have a huge quarantine camp they unironically refer to as “The Centre for National Resilience” should be a massive red flag for everyone.
Michael Gunner, Chief Minister of the Northern Territories, was a caricature of wide-eyed zealotry in a recent press conference. When asked whether vaccine mandates might alienate some people, even those already vaccinated he said:
If you support or give comfort to anybody who argues against the vaccine, you are an anti-vaxxer, I don’t care what your personal vaccination status is.”
The phrase “give comfort too” should alarm people, because it’s only ever used in warlike settings, discussing treason and collusion. “Giving comfort to the enemy“.
In another press conference, Gunner also announced a “hard lockdown” in aboriginal communities, meaning people are not allowed to leave their homes except for medical treatment or if required by law. Adding that people are being “removed” to quarantine centres in military trucks. Not just people diagnosed with “covid”, but “close contacts” too:
Police are going door to door in Aboriginal communities to “intensively engage” with those who do not want the “vaccine”.
All this is being sold in the mainstream as “concern” for communities which could be “extra vulnerable”.
Voices on social media – who are totally real, and not at all shills there to control the narrative – are claiming strict measures are necessary to protect indigenous Australians from Covid, because it would rip through their communities “like syphilis did to the Native Americans”. There is, so far, very little evidence to support this fear-mongering.
However, written statements, allegedly from people detained, are emerging online saying they are being well taken care of, and that “irresponsible” social media posts are “hurting people”.
Amnesty UK issued a press release condemning the moves, but this was swiftly countermanded by Amnesty Australia, and dismissed as “disinformation” in the press and by Michael Gunner as “conspiracy theorising” from “tinfoil hat-wearing tossers”.
Some other Australian states are already building quarantine camps specifically for Aboriginal communities.
South Australia announced a tender for these camps last week, with press coverage underlining they would be only for those people who are “unable to isolate at home”.
Whether genuinely well-intentioned or not, it can certainly be argued this is an example of massive governmental overreach, especially for a virus that is at worst a bad seasonal flu.
It’s a convoluted and complex situation, with the real facts being hard to establish. Whatever the reality, it’s a situation that bears close watching.
Are We Overreacting to Omicron?
BY PAUL ELIAS ALEXANDER | BROWNSTONE INSTITUTE | NOVEMBER 26, 2021
With natural exposure immunity and early outpatient treatment and when combined with no reports of increased lethality, the WHO’s reaction of generating panic toward “Omicron” is causing needless fear and panic. So too with the Biden administration’s newly imposed travel restrictions, which will achieve nothing and will once again disrupt trade and violate human rights.
The WHO has said that the Omicron variant can spread more quickly than other variants. Likely true. The virus is behaving just like how viruses behave. They are mutable and mutate and via Muller’s ratchet, we expect this to be milder and milder mutations and not more lethal ones given the pathogen seeks to infect the host and not arrive at an evolutionary dead-end.
The virus will mutate downward so that it can use the host (us) to propagate itself via our cellular metabolic machinery. The Delta has shown us this: it is very infectious and mostly non-lethal. Especially for children and healthy people. So is the WHO panicking the globe needlessly? Is this Covid-19 February 2020 once again?
The problem with South Africa as is with Australia and New Zealand and even island nations like Trinidad is that it has low natural immunity to SAR-Cov-2. This is because, as we witnessed over the last year and more, if you lock down your society too long and too hard, you deny the nation and population from inching closer to population-level herd immunity. And you have no economy or society from which to reemerge. You devastate your society for a pathogen that is largely harmless to the vast majority of people especially children.
Moreover, governments asked us for two weeks to flatten the curve to help prepare hospitals so that they can tend to surges and other non-Covid illnesses. We as societies gave our governments 2 weeks, not 21 months. They failed to tend to the non-Covid illnesses and we locked down the healthy and well (children and young and middle aged healthy persons) while failing to properly protect the vulnerable and high-risk persons such as the elderly. We failed and it was like killing fields in our nursing homes.
This failure rests on public health messaging and government. Additionally, what did our governments in the US, Canada, UK, Australia etc. do with the tax money for the hospitals and PPE etc.? Hospitals must be prepared by now. Governments have failed! Not the people. The Task Forces have failed, not the people.
These nations thought that they could stay locked down and wait for a vaccine. This is a reasonable view though I was against lockdowns as they would and did cause crushing harms on especially poor persons and children. The problem is there was an opportunity cost because the vaccine we were waiting on was suboptimally developed without the proper safety testing or assessment of effectiveness.
We have data that the Pfizer vaccine loses 40% of antibodies per month, meaning in 3 months post-shot, you have low effective vaccinal immunity. We see it clearly playing out now whereby you got to tamp down spread with the draconian lockdowns, but you did it at the cost of natural immunity. That is the opportunity cost. So we spent on getting the vaccine and it cost us natural immunity and thus herd immunity.
For example, the vaccine has failed to stop infection and spread against Delta. We have research findings by Singanayagam et al. (fully vaccinated individuals with breakthrough infections have peak viral load similar to unvaccinated cases and can efficiently transmit infection in household settings, including to fully vaccinated contacts), by Chau et al. (viral loads of breakthrough Delta variant infection cases in vaccinated nurses were 251 times higher than those of cases infected with prior strains early 2020), and by Riemersma et al. (no difference in viral loads when comparing unvaccinated individuals to those who have vaccine “breakthrough” infections and if vaccinated individuals become infected with the delta variant, they may be sources of SARS-CoV-2 transmission to others) that reveal the vaccines have very suboptimal efficacy.
This situation of the vaccinated being infectious and transmitting the virus has also emerged in seminal nosocomial outbreak papers by Chau et al. (HCWs in Vietnam), the Finland hospital outbreak (spread among HCWs and patients), and the Israel hospital outbreak (spread among HCWs and patients). These studies have also revealed that the PPE and masking were essentially ineffective within the healthcare setting. All of the HCWs were double-vaccinated yet there was extensive spread to themselves and their patients.
In addition, Nordström et al. (vaccine effectiveness of Pfizer against infection waned progressively from 92% day 15-30 to 47% day 121-180, and from day 211 and onwards no effectiveness), Suthar et al. (a substantial waning of antibody responses and T cell immunity to SARS-CoV-2 and its variants, at 6 months following the second immunization), Yahi et al. (with Delta variant, neutralizing antibodies have a decreased affinity for the spike protein, whereas facilitating antibodies display a strikingly increased affinity), Juthani et al. (higher numbers of patients with severe or critical illness in those who received the Pfizer vaccine), Gazit et al. (SARS-CoV-2-naïve vaccinees had a 13-fold increased risk for breakthrough infection with the Delta variant, and substantially elevated risk of symptomatic Covid and hospitalization), and Acharya et al. (no significant difference in cycle threshold values between vaccinated and unvaccinated, asymptomatic and symptomatic groups infected with Delta) collectively reveal the poor efficacy and even negative efficacy of the Covid vaccines. Levine-Tiefenbrun et al. reports that the viral load reduction effectiveness declines with time after vaccination, “significantly decreasing at 3 months after vaccination and effectively vanishing after about 6 months.”
As an example, the Swedish study (retrospective with 842,974 pairs (N=1,684,958) is particularly alarming for it shows that while the vaccine provides temporary protection against infection, the efficacy declines below zero and then to negative efficacy territory at approximately 7 months, underscoring that the vaccinated are highly susceptible to infection and eventually become highly infected (more so than the unvaccinated). A further example emerges from Ireland whereby reporting suggests that the Waterford city district has the State’s highest rate of Covid-19 infections, while the county also boasts the highest rate of vaccination in the Republic (99.7% vaccinated). Reports are that the U.S. Covid-19 deaths for 2021 surpassed the deaths from 2020, leading some to state that “more people have died from COVID-19 in 2021, with most adults vaccinated and nearly all seniors), than in 2020 when nobody was vaccinated.”
Thus these nations that locked down and stayed that way are in a quandary for they do not know what to do now. If you open you will get surges in infection. Where is the money that was to go to hospital preparation? Did governments embezzle and steal and misappropriate the money for the hospitals remain still not prepared?
We have a lot of natural immunity in the US, e.g. near 65-70% of the population. The open states (those that did not lock down too long and too hard and opened quickly) will likely do very well with this Omicron or any new variant. This also is the power of natural immunity.
And we need not forget the potency of the overlooked ‘innate’ immunity with the innate antibodies and innate natural killer cellular compartment. This innate response is particularly potent in children (our first line of defense against pathogens) and is what has spared children from Covid and how children typically stave off pathogens, especially young children still laying down immunological memory.
Moreover, there is no reporting of increased virulence/lethality of this new Omicron variant. As yet this will remain the case based on Delta and prior variants. There are no guarantees but we operate based on risk and all things point to the same for this new variant.
Just because there is a wave in SA does not mean that there will be waves in the US or Israel or other places with greater natural immunity. This was the prize of letting people enjoy day-to-day living. The nations that have ended lockdowns are likely to move past this new variant scare, and be fine. This is more of an overreaction by the WHO and governments and much ado about nothing.
Dr Alexander holds a PhD. He has experience in epidemiology and in the teaching clinical epidemiology, evidence-based medicine, and research methodology. Dr Alexander is a former Assistant Professor at McMaster University in evidence-based medicine and research methods; former COVID Pandemic evidence-synthesis consultant advisor to WHO-PAHO Washington, DC (2020) and former senior advisor to COVID Pandemic policy in Health and Human Services (HHS) Washington, DC (A Secretary), US government; worked/appointed in 2008 at WHO as a regional specialist/epidemiologist in Europe’s Regional office Denmark, worked for the government of Canada as an epidemiologist for 12 years, appointed as the Canadian in-field epidemiologist (2002-2004) as part of an international CIDA funded, Health Canada executed project on TB/HIV co-infection and MDR-TB control (involving India, Pakistan, Nepal, Sri Lanka, Bangladesh, Bhutan, Maldives, Afghanistan, posted to Kathmandu); employed from 2017 to 2019 at Infectious Diseases Society of America (IDSA) Virginia USA as the evidence synthesis meta-analysis systematic review guideline development trainer; currently a COVID-19 consultant researcher in the US-C19 research group
Featured Video

Seyed M. Marandi: US-Iran War Inevitable: Kuwait and Bahrain May Fall
or go to
Aletho News Archives – Video-Images
From the Archives
USS Liberty Massacre: A Pivotal Moment in the Hostile Takeover of America
By Kevin Barrett | Crescent | Dhu al-Qa’dah 24, 1445
In corporate America, hostile takeovers are commonplace. They occur when an aggressor—a larger corporation or rich individuals—seizes control of a smaller corporation without asking permission.
What few recognize is that the United States itself has been subjected to a hostile takeover. Since the aggressor, the illegitimate settler colony known as “Israel,” is much smaller than the US, the takeover has necessarily been surreptitious.
As of June, 2024, Israel’s gradual takeover of the US has become obvious and undeniable—a proverbial “elephant in the living room.” … continue
Blog Roll
 Aletho News
- Seyed M. Marandi: US-Iran War Inevitable: Kuwait and Bahrain May Fall
- Leaders Condemn Ansarallah Attack on Saudi Arabia While Ignoring Illegal War Against Yemen
- Leaked: Britain’s Covert Iraqi Psyops Network
- Yemeni Armed Forces Warn Airlines Against Using Saudi Airports, Exempt Mecca and Medina
- Iran security chief says powers greater than US tried to conquer Iran but ended in ‘dustbin of history’
- Europe’s mounting social chaos… chickens coming home to roost for proxy war against Russia
- US-Russia Diesel Deal Becomes Massive Defeat for Ukraine
- Hormuz and the Looming Economic Catastrophe
- Dhubab offensive, media blitz and the rapid unraveling of Saudi-backed coalition’s new gambit
- Putin Conveys to Trump Iran’s Vision on Possible Conflict Resolution – Kremlin
- If Americans Knew
- Gaza: Ceasefire Anniversary Marks Year of Failed Promises
- The American Conservative: Mike Huckabee Should Resign
- A C-Section in Shackles: A Palestinian Woman’s Harrowing Birth in Israeli Detention
- ‘He’s Desperate’: AIPAC Begins Spending Against Abdul El-Sayed to Boost Mike Rogers:
- Trump, Hormuz, and the Looming Economic Catastrophe
- For three years, Israel has killed a child in Gaza every 71 minutes – Daily Update
- Israeli forces kill another child in Gaza – Daily Update
- Gaza ceasefire exists in name only, say more than 100 organizations
- Nearly 2 Million in Gaza Need Urgent Shelter Assistance as Winter Looms: IOM Chief Warns
- Suppressing Palestinian resistance: US charity under fire for AI monitoring of Gaza classrooms
- No Tricks Zone
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!
- New Study: 50 Years Of The Most Aggressive ‘Net Zero’ Policies Can Only Affect The Global Climate By 0.03°C
- US September “Heat” Was No Record…Many Records Set Decades Ago
- Latest European Green Energy Debacle; Portugal’s Largest Flagship Solar Park Insolvent!
- Green Energy Debacle: German Expert Professor Fritz Vahrenholt Warns Of Severe Economic And Social Consequences
- Two More Paleo Reconstructions Affirm Meters-Higher Sea Levels Across Ireland, Brazil 7000-6000 Years Ago
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI

