When it comes to COVID, public health officials have consistently downplayed and/or ignored natural immunity.
Yet these public health experts and many doctors and scientists know that no vaccine can confer the type of robust, full, sterilizing and life-long immunity to COVID that natural-exposure immunity confers.
Officials at the Centers for Disease Control and Prevention (CDC) and National Institutes of Health (NIH) know anyone exposed, infected and recovered from SARS-CoV-2 has acquired cellular immunity.
They know how natural immunity works, yet they continue to deceive the public on this issue by falsely insisting vaccines are the only answer to “ending the pandemic.”
The authors of a 2008 study on the 1918 pandemic virus showed how potent and long-lived natural immunity is, and how the immune system generates new antibodies if and when needed (re-exposed).
The researchers wrote:
“A study of the blood of older people who survived the 1918 influenza pandemic reveals that antibodies to the strain have lasted a lifetime and can perhaps be engineered to protect future generations against similar strains … the group collected blood samples from 32 pandemic survivors aged 91 to 101 … the people recruited for the study were 2 to 12 years old in 1918 and many recalled sick family members in their households, which suggests they were directly exposed to the virus … The group found that 100% of the subjects had serum-neutralizing activity against the 1918 virus and 94% showed serologic reactivity to the 1918 hemagglutinin.
“The investigators generated B lymphoblastic cell lines from the peripheral blood mononuclear cells of eight subjects. Transformed cells from the blood of 7 of the 8 donors yielded secreting antibodies that bound the 1918 hemagglutinin.
“ … here we show that of the 32 individuals tested that were born in or before 1915, each showed sero-reactivity with the 1918 virus, nearly 90 years after the pandemic. Seven of the eight donor samples tested had circulating B cells that secreted antibodies that bound the 1918 HA. We isolated B cells from subjects and generated five monoclonal antibodies that showed potent neutralizing activity against 1918 virus from three separate donors. These antibodies also cross-reacted with the genetically similar HA of a 1930 swine H1N1 influenza strain.”
The very same CDC that fights against COVID natural immunity, argues just the opposite when it comes to chickenpox.
Guidance on the CDC website, “Chickenpox Vaccination: What Everyone Should Know,” states: “People 13 years of age and older who have never had chickenpox or received chickenpox vaccine should get two doses, at least 28 days apart.”
In this reasonable guidance, the CDC says you need the chickenpox jab if you “have never had chickenpox.” If you have had it, then you do not need the vaccine.
The CDC goes even further, stating: “You do not need to get the chickenpox vaccine if you have evidence of immunity against the disease.” So if someone has had chickenpox and recovered, and can demonstrate that via a laboratory test, they don’t need the vaccine.
Again, this makes sense. All parents know this, and have for generations. You do not need a vaccine for measles, if you already had measles and cleared the rash and recovered. Natural, beautiful robust immunity, typically lasts for the rest of a person’s life.
The same goes for the CDC’s guidance for the measles, mumps, and rubella vaccine (MMR). The CDC clearly states no MMR vaccine is needed if “You have laboratory confirmation of past infection or had blood tests that show you are immune to measles, mumps, and rubella.”
So, what is different for COVID-19? Is something other than science at play here?
We now have a major crisis as the race is on to vaccinate our 5- to 11-year-old children who bring no risk to the table, with a vaccine that has been shown to be sub-optimal and carrying risks.
We even have one of the FDA advisory committee members, Dr. Eric Rubin, who is also lead editor of the New England Journal of Medicine, stating: “We’re never gonna learn about how safe the vaccine is until we start giving it.”
This is a shocking statement by someone who played a role in the decision-making, and should lead us to examine if Rubin and others on that committee were conflicted in terms of relationships to the vaccine developers.
Rubin further stated: “The data show that the vaccine works and it’s pretty safe … we’re worried about a side effect that we can’t measure yet,” he said, referring to a heart condition called myocarditis.
So then why would Rubin and others agree to expose our children to potential harm from a vaccine for an illness that poses little risk to children, if they have serious concerns and admit they have not and cannot yet measure the safety?
This depth of uncertainty should never exist in any drug or vaccine that the FDA regulates, much less a drug officials propose to administer to 28 million children. Something is very wrong here.
An April 2021 study in the Journal of Infection (April 2021) examined household transmission rates in children and adults. The authors reported there was “no transmission from an index-person < 18 years (child) to a household contact < 18 years (child) (0/7), but 26 transmissions from adult index-cases to household contacts < 18 years (child) (26/71, SAR 0=37).”
These findings add to the stable existing evidence that children are not spreading the virus to children but rather that adults are spreading it to children.
Why vaccinate our children for this mild and typically non-consequential virus when they bring protective innate immunity towards this SARS-VoV-2, other coronaviruses and other respiratory viruses?
Why push to vaccinate our children who may well be immune due to prior exposure (asymptomatic or mild illness) and cross-reactivity/cross-protection? Why not consider assessing their immune status?
Dr. Geert Vanden Bossche writes that children’s innate immunity:
“… normally/ naturally largely protects them and provides a kind of herd immunity in that it dilutes infectious CoV pressure at the level of the population, whereas mass vaccination turns them into shedders of more infectious variants. Children/ youngsters who get the disease mostly develop mild to moderate disease and as a result continue to contribute to herd immunity by developing broad and long-lived immunity.”
Here are six studies that make the case for not vaccinating children:
1. A 2020 Yale University report indicates children and adults display very diverse and different immune system responses to SARS-CoV-2 infection which explains why they have far less illness or mortality from COVID.
According to the study:
“Since the earliest days of the COVID-19 outbreak, scientists have observed that children infected with the virus tend to fare much better than adults … researchers reported that levels of two immune system molecules — interleukin 17A (IL-17A), which helps mobilize immune system response during early infection, and interferon gamma (INF-g), which combats viral replication — were strongly linked to the age of the patients. The younger the patient, the higher the levels of IL-17A and INF-g, the analysis showed… these two molecules are part of the innate immune system, a more primitive, non-specific type of response activated early after infection.”
2. Studies by Ankit B. Patel and Dr. Supinda Bunyavanich show the virus uses the ACE 2 receptor to gain entry to the host cell, and the ACE 2 receptor has limited (less) expression and presence in the nasal epithelium in young children (potentially in upper respiratory airways).
This partly explains why children are less likely to be infected in the first place, or spread it to other children or adults, or even get severely ill. The biological molecular apparatus is simply not there in the nasopharynx of children. By bypassing this natural protection (limited nasal ACE 2 receptors in young children) and entering the shoulder deltoid, this could release vaccine, its mRNA and LNP content (e.g. PEG), and generated spike into the circulation that could then damage the endothelial lining of the blood vessels (vasculature) and cause severe allergic reactions (e.g., here, here, here, here, here).
3. William Briggs reported on the n=542 children who died (0-17 years (crude rate of 0.00007 per 100 and under 1 year old n=132, CDC data) since January 2020 with a diagnosis of COVID linked to their death. This does not indicate whether, as Johns Hopkins’ Dr. Marty Makaryhas been clamoring, the death was “causal or incidental.” That said, from January 2020, 1,043 children 0-17 have died of pneumonia.
Briggs reported:
“There is no good vaccine for pneumonia. But it could be avoided by keeping kids socially distanced from each other — permanently. If one death is “too many,” then you must not allow kids to be within contact of any human being who has a disease that may be passed to them, from which they may acquire pneumonia. They must also not be allowed in any car … in one year, just about 3,091 kids 0-17 died in car crashes (435 from 0-4, 847 from 5-14, and 30% of 6,031 from 15-24). Multiply these 3,000 deaths in cars by about 1.75, since the COVID deaths are over a 21-month period. That makes about 5,250 kids dying in car crashes in the same period — 10 times as many as Covid.”
Briggs concluded: “there exists no justification based on any available evidence for mandatory vaccines for kids.”
4. Weisberg and Farber et al. suggest (and building on research work by Kumar and Faber) that the reason children can more easily neutralize the virus is that their T cells are relatively naïve. They argue that since children’s T cells are mostly untrained, they can thus immunologically respond (optimally differentiate) more rapidly and nimbly to novel viruses such as SARS-CoV-2 for an effective robust response.
5. Research published in August 2021 by J. Loske deepens our understanding of this natural type biological/molecular protection even further by showing that “pre-activated (primed) antiviral innate immunity in the upper airways of children work to control early SARS-CoV-2 infection … the airway immune cells in children are primed for virus sensing…resulting in a stronger early innate antiviral response to SARS-CoV-2 infection than in adults.”
6. When one is vaccinated or becomes infected naturally, this drives the formation, tissue distribution and clonal evolution of B cells, which is key to encoding humoral immune memory.
Research published in May 2021 showed that blood examined from children retrieved prior to COVID-19 pandemic have memory B cells that can bind to SARS-CoV-2, suggestive of the potent role of early childhood exposure to common cold coronaviruses (coronaviruses). This is supported by Mateus et al. who reported on T cell memory to prior coronaviruses that cause the common cold (cross-reactivity/cross-protection).
There is no data or evidence or science to justify any of the COVID-19 injections in children. Can the content of these vaccines cross the blood-brain barrier in children? We don’t know because it wasn’t studied.
There is no proper safety data. The focus rather has to be on early treatment and testing (sero antibody or T-cell) to establish who is a credible candidate for these injections, as it is dangerous to layer inoculation on top of existing COVID-recovered, naturally acquired immunity.
There is no benefit and only potential harm/adverse effects (here, here, here).
Dr. Alexander is considered a global expert on COVID-19 generally and in some areas highly expertised. Dr. Alexander holds masters level study at York University Canada, a masters in epidemiology at University of Toronto, a masters in evidence-based medicine at Oxford and a doctorate in evidence-based medicine and research methods from McMaster University in Canada.
Professor Richard Ennos, a retired Professor of Evolutionary Biology at Edinburgh University, writes:
In Scotland this summer there has been excess mortality for the past 21 weeks with the total excess now exceeding 3,000 deaths. I and others have written to MSPs about the dreadful situation asking for a thorough analysis of what is responsible. In response we have been sent a reply from Anita Morrison, Head of Health and Social Care Analysis and Support, that I reproduce below. Five possible explanations are given, none of which reflect favourably on the Scottish Government’s public health policy. To paraphrase her reply, 45% are due to COVID-19 and the rest are accounted for by one or more of:
COVID-19 deaths that were not recognised.
Unintended consequences of the Scottish Government’s non-clinical response to COVID-19 (masks, social isolation etc.).
Problems with access to the health and social care services (presumably due to Scottish government policy of withdrawing these).
Patients not accessing services that were available (presumably because they were too scared of catching COVID-19 due to Scottish government exaggeration of the risks).
Some other cause that has not been identified.
What follows is my reply to Anita Morrison to point out that her response is a damning indictment of Scottish Government public health policy whose outcome should ultimately be measured by the metric of excess deaths.
FAO: Anita Morrison
Head of Health and Social Care Analysis and Support
Directorate for Covid Public Health
Cc Dr. Gregor Smith, Jason Leitch, Caroline Lamb, Maree Todd MSP, Kevin Stewart MSP, Nicola Sturgeon MSP
28th October 2021
Dear Anita Morrison
Thank you for your response to my letter, originally addressed to Sarah Boyack MSP, concerning the unprecedented rise in excess deaths in Scotland this summer that continues as I write (252 excess deaths above five-year average in the past week 42, 24% higher than normal). It is now indisputable that some major health catastrophe is unfolding in Scotland this summer. It is clearly essential that there is serious scrutiny of the health policies that have been adopted by the Scottish Government that have led to this situation. To help with this I would like to look in some detail at the explanations that you have provided for the incredibly worrying situation, and set out the implications of what you have written.
In your response you have put forward the argument that some 45% of these excess deaths have been caused by Covid. This proposition relies on the assumption that all Covid deaths represent excess deaths, a position that is hard to sustain given that Covid deaths are associated with multiple comorbidities, and therefore are unlikely to be exclusively in addition to deaths that would have occurred anyway from other causes.
Setting aside this difficulty, and assuming that 45% of excess deaths are due to Covid, this indicates that the policies that have been pursued by the Scottish Government have been unsuccessful in controlling deaths from Covid this summer. This is in contrast to the summer of 2020 when there was no such excess of deaths due to Covid or any other cause. This increase in the impact of Covid in Scotland between the summers of 2020 and 2021 is nicely illustrated using National Records of Scotland data from the two years stratified by different age groups.
A simple and compelling explanation for these data is that a policy has been enacted in 2021 that was not enacted in 2020 that has caused a three- to six-fold increase in summer Covid hospitalisations. What could that be?
Let us now turn to the majority of excess deaths that cannot be accounted for by Covid. I will be using the most up to date figures from the National Records of Scotland for the summer period 2021 up to week 42 that indicate 3,028 excess deaths (rather than your figures that extend only to week 40). The National Records of Scotland classify these deaths according to their causes, location and age. This is illustrated below.
Here we see that Covid can actually account for a maximum of only 26% of excess deaths in summer 2021. Significant rises in cancer and circulatory deaths are concerning, but perhaps of greater note is that 44% of excess deaths come under the classification of ‘Other’. They are not the kinds of deaths that are readily classifiable into the normal categories that we expect in Scotland, or they would have been placed in those categories. It is therefore these ‘Other’ deaths, some 44% of the total, that we need to investigate in great detail.
From the other panels in the graph above we can see that these ‘Other’ deaths are occurring at home, implying that they are likely to have been sudden because there has been no hospital admission. Furthermore, these excess deaths are not confined to the oldest age groups, where we expect most deaths, but are extended into the younger age group. Analysis of the timing of this rise in excess death shows that it started in the oldest age group and is initiated sequentially in ever younger age groups (see graph below). This strongly suggests that there is some cause for these excess deaths at home that operates first in the elderly and works its way sequentially down the age groups in Scotland. What could this be?
Now let us look at the non-Covid explanations that you have provided for the dramatic increase in excess deaths in Scotland over the past summer.
Your first explanation is that the summer excess deaths recorded as non-Covid are actually due to Covid, but have not been certified as such. I see that you yourself are not convinced by this explanation given the level of testing that has taken place. However, let us suppose this to be true. In that case the Scottish Government’s public health measures that have been put in place in summer 2021 to prevent Covid have been far worse than those put in place in summer 2020 – indeed they have been disastrous.
Your second explanation is that the non-clinical responses to COVID-19 put in place by the Scottish Government (mask-wearing, social isolation etc.) have had unintended deleterious consequences on public health and have dramatically increased the rates of death in the Scottish population. This is an admission of abject failure of the Scottish Government’s public health response to Covid. Public health policy is all about balancing the benefits and risks of interventions to achieve the lowest possible impact during a health emergency. It is pertinent to remember that no benefit-risk assessment of non-clinical interventions on the physical and mental health of the Scottish population was conducted before these interventions were enforced.
Your third explanation is that there has been a problem with access to health and social care services, and patients have not received the care they required from the NHS. Access to these services over the past 20 months has been under the control of the Scottish Government, so if this explanation is correct, then the Scottish Government is culpable for increasing the death rate in Scotland. Numerous policies have been deliberately pursued to dramatically reduce GP face-to-face consultation, to cancel appointments and operations in hospitals etc., so the evidence to support this, as at least a partial explanation, is overwhelming.
Your fourth explanation is that individuals who are in poor health have not referred themselves to health and social care services as they would at other times. To some extent this would be confounded with Scottish Government policies of restricting health care provision discussed above. However there has also been a concerted and relentless media campaign by the Scottish Government to increase fear in the public, particularly fear of hospitals where they may catch Covid. This has meant that they have not gone for treatment when it was necessary. Whatever the proximal cause of failure to seek medical attention, the ultimate cause and responsibility lies in Scottish Government policy.
Your final explanation for the dramatic rise in excess deaths in summer 2021 is that there is some other cause that has not yet been identified. As noted earlier the phenomenon of excess deaths in the presence of a Covid epidemic was not seen in summer 2020, but is seen in summer 2021. What differs between the two years? The glaringly obvious answer is the rollout of COVID-19 vaccination. There was no COVID-19 vaccination programme in 2020, but there was rollout of Covid vaccinations in a sequential way to increasingly younger age groups in 2021, a pattern that we see in the manifestation of excess deaths. All of the COVID-19 vaccines are novel and experimental with no long-term safety data. They are now associated with a wide range of serious side-effects (blood clotting, myocarditis, Guillain-Barre syndrome) whose likely frequency in the wider population was not assessed in the small-scale phase one and two trials that included only a subset of healthy volunteers. The Yellow Card adverse events reporting system, that capture only a fraction of events, has already recorded over 1,700 deaths in the U.K. population associated with the COVID-19 vaccines. There is therefore a prima facie case for COVID-19 vaccination being a contributing factor to the dramatic rise in summer excess deaths in Scotland in 2021.
I am very grateful for your response to my original letter. It has been extremely helpful in crystalising my thoughts about the causes of the dramatic and continuing rise in excess deaths that we currently see in Scotland. My conclusion is that whatever the true explanation for the phenomenon, it is rooted in the misguided and disastrous public health policies of the Scottish Government. The analysis has moreover highlighted that a significant contributor to the excess death of the Scottish population this summer may be adverse reactions to the COVID-19 vaccines, a factor that apparently has not occurred to either the Scottish Government or yourself. I would be grateful if you would pass on this insight to the Scottish Health minister so that unnecessary suffering and death is not meted out on the adults, and now children of Scotland.
The latest two-part episode of CHD.TV’s “Against the Wind” with host Dr. Paul Thomas featured two medical professionals who successfully treated COVID patients without a single fatality.
The guests — Dr. Jim Meehan, an ophthalmologist with advanced medical training in immunology and interventional endocrinology, and Scott Miller, a physician assistant with Miller Family Pediatrics — focused on this question: How do medical professionals transcend the fear of condemnation to save patients from often deadly mainstream treatments?
Thomas opened the segment by describing how, on a recent drive to work, he passed a group of young schoolchildren, all wearing masks and “socially-distanced” by 6 feet. As a father and a pediatrician, “It just felt so wrong,” he said.
“Looking into the eyes of some of these kids, you could just see the lights were gone,” Thomas said.
Meehan shared his evidence-based scientific analysis of why masks are ineffective, unnecessary and harmful.
Meehan also discussed his experience treating COVID patients using available therapies not offered in hospitals, and how his social media posts about COVID treatments were banned.
Of the approximately 4,000 COVID patients Meehan treated, none died. Meehan said his patients came to him early enough for treatment. In the hospital, he successfully treated more than 20 patients who were failing hospital COVID protocols, including a 66-year-old man who had taken two rounds of Remdesivir.
Meehan said shortly after the COVID vaccine rollout, he began recognizing vaccine adverse effects, including miscarriages, vasculitis, inflammatory pathologies and blood clot formations.
Thomas saw a case of myocarditis after vaccines in his pediatric practice.
Meehan said:
“This could have been you. This could have been your child. Your daughter. This could have been your father … These are experimental vaccines. It will be a decade before we know how severe the adverse reactions are going to be. It’s going to be years before we determine that we might lose 10% of the population to antibody-dependent enhancements.”
After Meehan started to see young and college-aged patients with COVID vaccine injuries, he added an emergency declaration to his website. Later he was banned from social media for posting about the danger of spike proteins and how animal studies showed those proteins cross the blood-brain barrier and cause neurological harm.
Meehan said his safety warnings against COVID vaccination apply across the board, but especially pregnant women, children and youth.
“We must not vaccinate children who are statistically at zero risk of dying from COVID-19,” he said, sharing data from a recent Johns Hopkins University analysis that found of the more than 330 COVID deaths in kids under age 25, data suggested most or nearly all appeared to be in kids with a life-threatening, pre-existing condition.
Next, Thomas interviewed Miller (starts at 37:14) who discussed his experience successfully treating approximately 1,400 patients, including a 100-year-old, with unconventional immune-boosting protocols he learned about through research and case studies.
Miller used FDA-approved therapies that were not FDA-approved for treating COVID, which resulted in him losing his medical license.
Miller treats children as well as adults in his practice. He has had none of his pediatric patients die or become hospitalized from COVID.
Miller discussed the research and moral obligation that compelled him to buck the system and advocate for proven treatments that work for COVID. He said:
“I got to a point where it felt so futile telling people one by one, when there are so many people who needed this information, that I just started openly talking about it.”
Covid curves of Sweden and Britain are remarkably similar. Britain’s peaks are slightly higher, as are its cumulative deaths per capita, but in general, the two share the same ups and downs and the same Covid seasons.
This might lead some to conclude that for Covid purposes Sweden and Britain are in the same region and highly comparable, but such comparisons have been outlawed by the Covid fanatics. For some reason, Sweden can for Covid reasons only ever be compared to just three other countries; Norway, Finland, and Denmark, and no others.
Sweden and Britain had outbreaks at exact same time albeit British death peaks were higher
Sweden with its 1,450 deaths per million takes 54th place, the UK with its 2,050 deaths per million takes 27th
That trio indeed had a better Covid outcome (if not a better rights, dignity, and calmness outcome) than Sweden, which supposedly means that if Sweden had locked down as they had it would have likewise experienced similarly low Covid deaths. What is the proof of that? If lockdowns “mitigate” Covid deaths then why wasn’t the UK with its even more Draconian lockdown able to replicate low Norwegian and Finnish numbers? Why wasn’t lockdown UK able to show Sweden “how it’s done” and embarrass her? (Or lockdown world leader Peru for that matter which is instead nonetheless also world’s Covid deaths leader.) Why didn’t lockdowns work in the UK, but would have in Sweden?
The answer of the lockdown lemmings is usually population density. Supposedly having a greater landmass per capita means that Sweden with its 88% urbanization rate is less densely populated than the UK with an 84% urbanization rate, and this makes all the difference.
In reality, Sweden’s three largest metro areas contain fully 32% of its population (for the UK that figure would be 22%) with most of the rest also living in densely populated (if smaller) cities and towns (disproportionally along the coast). That these historical maritime Baltic trade cities come with vast swathes of frozen northern wasteland attached, does not mean that Swedes are somehow stretched out across secluded permafrosted mountain villages. To the contrary, the very fact that Sweden is much more rugged than Britain means its population is much more concentrated in the few “good” parts of the country.
But anyhow, Sweden is only ever to be compared to its “neighbors”. But in this context what exactly is a “neighbor”? Denmark and Sweden are actually separated by a strait albeit since 2000 there is a 12-kilometer bridge-tunnel across/underneath. Sweden and Finland technically share a border, but that is in the far north where few ever visit and even fewer live. Actual Swedish-Finish links are maritime across the Baltic Sea.
Despite the theoretical land route, historically Finland functioned as a Swedish overseas possession, communication to which was maintained by sailing past the Åland islands and then up the Gulf of Finland (and up the Gulf of Bothnia when it’s not frozen). Another trans-Baltic possession of the Swedes was Latvia (Duchy of Livonia). Finland was lost to Russia during the Napoleonic period and Latvia to Peter the Great a century earlier.
The pair gained independence from Russia at the same time in 1918, but Latvia experienced a “second stint” under the Soviets from 1940 to 1991.
Owing to Swedish (and earlier Baltic German) influence Latvia remains a Lutheran country with recognizable northern historic architecture.
Finland had been under Swedish rule for basically forever, while Latvia was originally conquered and Christianized by mainly German-speaking crusaders who secularized and switched to Protestantism after Luther.
Latvia speaks a Baltic language very different from Germanic Swedish, and Finland speaks a Finnic language that is not even in the Indo-European family of languages.
A ferry from Stockholm to Helsinki takes 16 hours and 15 minutes and runs five times a week. A ferry from Stockholm to Riga takes 18 hours and 30 minutes and runs once a week. (Helsinki is twice the size of Riga and there are more reasons to go there.)
So if we are allowed to compare Covid outcomes in Sweden and in its former overseas territory of Finland,may we also be so bold as to compare it to the outcome inits (previously German-ruled) former territory of Latvia?
Let’s say that we are.
If we do that we find that Latvia has been extremely gung ho on lockdowns, locking down early, hard, and often, and garnering considerable praise for doing so. We also find that despite coming out of the first wave almost completely unscathed and continuing to dutifully lockdown ever since Latvia by now has 20% more per capita Covid deaths than never-lockdown Sweden and rising.
Latvia with 1,750 deaths per million and quickly rising
Lockdown enthusiasts maintain that Latvia’s lockdown was responsible for the country not experiencing the first wave in the spring of 2020 at all, but since that wave skipped entire Eastern Europe, including neighboring Belarus which never locked down, that is highly debatable. More likely Latvia and the rest of the eastern half of the continent would have never experienced the first wave regardless of what they did. Or what else explains the instruments which supposedly worked so flawlessly in the Spring of 2020 failing so utterly ever since?
A possible argument in defense of Latvia’s Covid record could be that comparison to Sweden is not fair given the latter’s much higher vaccination rate.
That argument doesn’t hold up because Sweden faced both of its major outbreaks before vaccines were a factor. Meanwhile, Latvia has only hit its biggest outbreak now that many of its residents have vaccine protection.
The vast majority of Swedish Covid cases occurred before February 2021, that is to say before vaccines. Meanwhile, Latvia gets the luxury of not having to face its biggest, deadliest wave until it has reached a 57% vaccination rate, and it is lockdown Latvia, rather than laissez-faire Sweden, which is hitting higher peaks and has already accumulated more Covid deaths. Explain that.
Latvia didn’t hit peak Covid until a considerable vaccination rate
And for the record, Latvia’s urbanization rate is 68%. Unlike Sweden, Latvia actually is still significantly rural. (Not that any of that matters in the least, as a cursory glance to lockdown North Dakota and non-lockdown South Dakota will tell you, both of which recorded relatively high Covid deaths despite their low population densities. (Incidentally, like Latvia, South Dakota also completely skipped the first wave, despite never locking down.))
It sounds like a script in a science fiction movie, but it’s not: Emails obtained by The Intercept show that the National Institutes of Health worked together with one of its grantees, EcoHealth, to evade gain-of-function (GOF) research restrictions.
While EcoHealth’s plans for the research “triggered concerns at NIH,” staff went ahead and “adopted language that EcoHealth Alliance crafted” so the work could go on. The Intercept added that none of the featured experiments could have triggered the current pandemic, but the idea of the deceptive move shows what persons in a position of authority at the highest levels will do to circumvent safety rules and regulations.
The violations were serious enough to spark concerns from Jesse Bloom, a virologist at the Fred Hutchinson Cancer Research Center. “The discussions reveal that neither party is taking the risks sufficiently seriously,” Bloom told The Intercept.
Simon Wain-Hobson, a virologist at the Pasteur Institute in Paris, minced no words with his opinion on what happened. “It’s absolutely outrageous,” Wain-Hobson said. “The NIH is bending over backward to help people it’s funded. It isn’t clear that the NIH is protecting the U.S. taxpayer.”
In an op-ed, “Fauci Fooled America,” published Monday in Newsweek, two scientists accused Dr. Anthony Fauci of bungling the government’s response to COVID by getting “major epidemiology and public health questions wrong.”
Martin Kulldorff, Ph.D., an epidemiologist at Harvard Medical School, and Jay Bhattacharya, M.D., Ph.D., professor of Health Policy at Stanford University School of Medicine wrote: “Reality and scientific studies have now caught up with him.”
“The evidence is in. Governors, journalists, scientists, university presidents, hospital administrators and business leaders can continue to follow Dr. Anthony Fauci or open their eyes. After 700,000-plus COVID deaths and the devastating effects of lockdowns, it is time to return to basic principles of public health.”
The authors ticked off a list of “key issues” Fauci got wrong, including failure to recognize natural immunity, protecting the elderly, school closures, masks and contact tracing.
“By pushing vaccine mandates, Dr. Fauci ignores naturally acquired immunity among the COVID-recovered, of which there are more than 45 million in the United States,” the authors wrote. “Mounting evidence indicates that natural immunity is stronger and longer lasting than vaccine-induced immunity.”
Kulldorff and Bhattacharya cited a study from Israel, which concluded the vaccinated were 27 times more likely to get symptomatic COVID than the unvaccinated who had recovered from a prior infection.
They pointed out that the scientific community has known about natural immunity from disease “at least since the Athenian Plague in 430 BC.”
On Fauci’s dictates to mandate the vaccine for healthcare workers, the two argued: “Under Fauci’s mandates, hospitals are firing heroic nurses who recovered from COVID they contracted while caring for patients. With their superior immunity, they can safely care for the oldest and frailest patients with even lower transmission risk than the vaccinated.”
On school closures they wrote: “Considering the devastating effects of school closures on children, Dr. Fauci’s advocacy for school closures may be the single biggest mistake of his career … While children do get infected, their risk for COVID death is minuscule, lower than their already low risk of dying from the flu.”
Kulldorff and Bhattacharya pointed to Sweden, noting that during the 2020 spring wave of COVID, the country kept daycare and schools open for all 1.8 million children ages 1 to 15, with no masks, testing or social distancing.
The authors argued contact tracing “was a hopeless waste of valuable public health resources that did not stop the disease,” and that Fauci failed at protecting the vulnerable.
“After more than 700,000 reported COVID deaths in America, we now know that lockdowns failed to protect high-risk older people,” they said.
On collateral public health damage, they argued that a “fundamental public health principle is that health is multidimensional; the control of a single infectious disease is not synonymous with health.”
They wrote that Fauci: “ … failed to properly consider and weigh the disastrous effects lockdowns would have on cancer detection and treatment, cardiovascular disease outcomes, diabetes care, childhood vaccination rates, mental health and opioid overdoses, to name a few. Americans will live with — and die from — this collateral damage for many years to come.”
In private conversations, Kulldorff and Bhattacharya said, most of their scientific colleagues agree with them on these points but few have spoken up out of fear of “financial censorship.”
“Many are afraid of losing positions or research grants, aware that Dr. Fauci sits on top of the largest pile of infectious disease research money in the world,” they wrote.
In his forthcoming book, “The Real Anthony Fauci,” Robert F. Kennedy, Jr. includes a comprehensive discussion of Fauci’s influence and power over the scientific community, revealing how Fauci uses the “financial clout at his disposal to wield extraordinary influence over hospitals, universities, journals and thousands of influential doctors and scientists — whose careers and institutions he has the power to ruin, advance or reward.” Kennedy’s book is due out Nov. 16.
Jeremy Loffredo is a freelance reporter for The Defender. His investigative reporting has been featured in The Grayzone and Unlimited Hangout. Jeremy formerly produced news programs at RT America.
Would the doctrine of the “Original Antigenic Sin” (OAS) play a heavy role in the existing COVID vaccine strategy — due to the sub-optimal, non-sterilizing, imperfect COVID-19 vaccine?
Experts agree we should never have tried to vaccinate our way out of a pandemic while in a pandemic.
According to the OAS by Dr. Thomas Francis, the initial priming of the immune system (initial exposure to the virus, either in the wild or via a vaccine) gets ‘fixed’ for life. If the initial priming of the immune system is sub-optimal and biased, then that sub-optimal initial priming can effectively derange and bias the immune response long-term, which would guide all future immunological responses.
We should have known that this initial priming, if deranged and wrong, would severely stagger and hobble our immune response for the rest of our lives.
And so, are we setting up our populations — and dangerously, our children — for disaster? With this imperfect and sub-optimal immune priming using COVID vaccines that do not stop infection or transmission in the first place?
The COVID-19 vaccines being administered in the U.S. only reduce symptoms, thus allowing the host to stay alive (an evolutionary future it did not have) while remaining capable of transmitting.
Evidence shows vaccinated persons are indeed susceptible to infection, and as alarmingly, carry as high a viral load as the unvaccinated.
Are we about to rob our children of their most precious gift — a robust, durable, potent natural innate immunity with these imperfect leaky vaccines — an immunity that has always protected them and helps reduce the infectious pressure and helps contribute to population herd immunity? With vaccines that have been shown to be harmful?
I argue we could potentially kill many children with these vaccines because we simply have not done the proper safety tests and studies for the proper duration of follow-up, so as to “exclude harms.”
If we have not conducted the proper studies, how could we justify the safety of these vaccines for our children? To do so is dangerous and reckless, as it deceives the public and parents. It is illogical and irresponsible, and without any credible basis.
We do not know what will happen to our healthy children long-term. This is potentially catastrophic if COVID mass vaccination is allowed in our children.
These public health officials at the U.S. Food and Drug Administration, Centers for Disease Control and Prevention (CDC), National Institutes of Health (NIH), National Institute of Allergy and Infectious Diseases (NIAID) — including Dr. Anthony Fauci and Dr. Rochelle Walensky — have made no valid case as to why our children warrant these vaccines.
Yet they are seeking to vaccinate healthy children with near statistical zero risk — with only the opportunity for harm and no opportunity for benefit.
In addition to the OAS, Read et al also provided us a roadmap to these vaccine and immune system challenges, in their treatise on Marek’s disease in chickens.
In their seminal 2015 PLOS paper, the authors argued some vaccines may boost and enhance the fitness of more virulent strains. They asked a simple question: Could some vaccines drive the evolution of more virulent pathogens?
We say “yes!” This can be explained by natural selection which selects out or culls pathogen strains/variants that are so lethal or “hot” they could kill their hosts if they survive and, thus, inadvertently, kill themselves.
Marek’s disease effect and vaccination may well be at play here with COVID vaccines — moderating symptoms while not stopping infection or transmission, thus posing a danger to the unvaccinated and vaccinated.
We — or at least the virologists and immunologists and vaccine developers — should also have understood the COVID vaccines would drive antibodies against the spike glycoprotein only, while our natural-exposure infection immune response will be broad, robust, durable, long-term — providing immunity against the spike (S) protein, the membrane protein, the nucleocapsid (N) protein, and all the epitopes on the viral ball and all conserved parts of the virus.
No COVID vaccine immunity could be equal to or better than naturally acquired immunity. This should have never even been in question. Assertions otherwise by the CDC, NIH, NIAID or vaccine developers are outright falsehoods and means to deceive the public.
We should have known we could never achieve “zero COVID” as this is a mutable respiratory pathogen. This means, similar to flu and cold viruses, COVID mutates often.
This is what viruses do. They exist to replicate, and the replicating process of their genetic material is unstable and imperfect. Because there are errors in the replication of the genetic material, there will always be mutations.
For example, the original SARS-CoV-2 was the Wuhan strain — now it is the Delta variant. The vaccine for the original strain cannot hit the mutated spike, as the mutations occur on the spike. That’s why we have the immune escape.
So no matter what vaccine you make, you will not be able to vaccinate for the right strain or variant at any time, as the virus would have mutated by the time we vaccinate.
You can never get ahead of a mutating virus with a vaccine.
This is especially true given COVID has an animal reservoir. The virus lives stably in the bat population. Unless we kill off all the bats — and their intermediate hosts, which include civet cats and raccoon dogs and camels — we will always have a “reservoir” for the virus, in animals. Infected animals can in turn infect humans who get close to or interact with them.
This is a very different pathogen and approach than the one taken with smallpox, which did not have an animal reservoir — we only had to remove smallpox from the human population, we didn’t need to worry about it spilling over from other species.
According to Dr. Robert Malone, “The idea that if you have a workplace where everybody’s vaccinated, you’re not going to have virus spread is totally false … a total lie … the vaccinated are actually the “super-spreaders” that everyone was told about in the beginning of the pandemic.”
Malone further states, “if the government isn’t going to disclose what the [vaccine] risks are, and they’re not going to disclose what’s really going on because they think that you can’t handle the news … this is called the noble lie.”
Are we closer to understanding now that vaccinating for COVID under tremendous infectious and vaccine pressure (and ecological pressure) would drive immune escape? That this strategy is indeed a recipe for disaster?
Could COVID-19 vaccines be enhancing the evolution of variants/mutants that are more infectious and capable of spreading much faster and with greater lethality?
Are these COVID-19 vaccines sub-optimally priming the immune system for long-term skewed deranged responding?
Could the use of ‘imperfect’ sub-optimal vaccines enhance the progression of variants that place unvaccinated persons at elevated evolutionary risk of very severe illness, including death? Our children? Is this Marek 2.0?
Where are the safeguards when the proper studies were not done by the vaccine developers, and where is the FDA as the top regulator, in protecting the health and well-being of our children?
Dr. Janet Woodcock, as the head of the FDA, where are you in this? You could not be informed by the science, for there is none to support this grossly reckless and absurd push to vaccinate children.
What is going on here? This certainly is not “about the science.”
I challenge any public health official to sit down with me and my scientific colleagues and explain your science. Debate us. Show us what you are looking at to arrive at these very dangerous statements and decisions.
We may end up killing many children with these vaccines. In fact, not ‘we’, ‘you’ — Fauci and Walensky and Dr. Francis Collins — may end up killing many of our children.
Please stop this insanity, step back and focus on the vulnerable and elderly where there is risk. Leave the children alone!
“If the CDC, NIH, FDA (Walensky, Fauci, Collins, Marks, Woodcock), vaccine developers and all involved in these COVID vaccines, all the television medical experts, all who are absolved thanks to liability protection, if you feel so strongly that these are safe for our children, then do the right thing: Take liability protection off the table. Stand by the vaccine’s safety. Put some skin in the game — for as we speak, only our healthy children are carrying risk and I fear it could be potentially catastrophic for them.
Dr. Alexander is considered a global expert on COVID-19 generally and in some areas highly expertised. Dr. Alexander holds masters level study at York University Canada, a masters in epidemiology at University of Toronto, a masters in evidence-based medicine at Oxford and a doctorate in evidence-based medicine and research methods from McMaster University in Canada.
During the National Conservatism Conference, held on October 31, tech billionaire Peter Thiel warned against “centralized misinformation” because it creates a “fake consensus.”
Thiel asserted that the centralized misinformation problem is responsible for the silencing of debate on important issues such as inflation of the American economy, COVID-19, and the presence of US troops in Afghanistan.
In his speech, Thiel gave examples of what he described as the “incredible derangement of various forms of thought.” He referenced Stanford’s professor Jay Bhattacharya’s experience. Pictures of the professor were plastered all over the school because he spoke against masks.
He said: “When you have to call things science, you know they aren’t – like climate science or political science,” Epoch reported.
According to Thiel, such excessive dogmatism is the reason for the failed policies by the US government in Afghanistan for more than twenty years.
The PayPal co-founder went on to say that the US is currently experiencing a “runaway, non-transitory inflation” and the “complete bankruptcy of the Fed” because of the inability to tolerate differing ideas and opinions that are unpopular.
“If there’s a misinformation problem, it’s a centralized misinformation problem—and it’s the misinformation coming from the Ministry of Truth,” said Thiel.
UNREPORTED by the MSM was an impassioned speech by an MP in the Victorian Parliament against legislation being pushed through to confer unlimited Covid powers on the State Premier, the egomaniac Dan Andrews, and the Health Minister.
The MP is Steph Ryan, and she is an example to all MPs in threatened democracies worldwide. She is also the deputy leader of the National Party of Australia, known as the Nationals. She certainly deserves wider notice and recognition not just for the stand she is taking but for the quality of her speech. I am grateful to the despairing Australian reader who brought her to my attention:
‘We’re in trouble in this country,’ she wrote to me, ‘From being a free, relaxed and happy nation (after all, one of the stock-standard phrases used when expressing universal optimism was always “She’ll be right, mate!”) we’re now a fearful, cowering, woke country expecting cradle to grave coddling and direction.’
Steph Ryan’s speech is a lifeline for citizens like our reader. I found it truly inspiring. Setting out the very principles upon which democracy and our freedom are based, it is everything that we want and need to hear said by a politician. You can watch it below and the full transcript follows.
Steph Ryan: I feel sick that we are having this debate. I do not think there has ever been a piece of legislation come before this chamber that I have been more vehemently opposed to. I feel sick that Labor MPs are not brave enough to stand up and speak the truth about this legislation. I do not care if you think that the Premier’s handling of this pandemic has been infallible. I do not care if you stand with Dan. I do not care if you think he is the greatest thing since sliced bread. The truth is that this legislation is about handing the Premier and the Minister for Health the ability to rule by decree. Is that power that you want to hand to every future Premier and health minister? It does not matter what you think about the Premier. This is not even about the current government. This is about the management of pandemics but also the ability to trigger these powers for ever into the future. It is about the regime that it has the potential to set up here in this state. That is what is at stake here. Is that what we want as Victorians?
This Bill allows the government to declare a pandemic in Victoria and make orders that lock down the state even when there is no presence of disease here. Yes, the chief health officer needs to publish his or her advice within 14 days of those orders being made, but that advice, even if it contradicts the order made by the Premier or the health minister, does not invalidate those orders if it does not support them.
The Bill gives the government the right to make orders on the ability of attributes – things like race, gender, sexuality. How on earth can people support that? How on earth can members opposite support that? It is extraordinary. It offers no rights of appeal to courts for people who are incarcerated. It sets up a penalty regime of fines that would see an individual face more than $90,000 [c £50,000]. That would send most ordinary Victorians to jail. Who can afford a $90,000 fine? The government says, ‘Don’t worry. That’s just about the worst breaches.’ Well, that is not what the legislation says. It is extraordinary. I cannot believe that those opposite are not brave enough to stand up and speak out about it. I imagine that the member for Altona is going to speak on this legislation. She has been the Attorney-General; she has been a lawyer. She cannot possibly agree with this; she cannot. Where are your values?
There is no Parliamentary oversight of these powers. The Bill sets up a consultative committee of people appointed by the Premier and the health minister, and they do not even need to take the advice of that – it is just a consultative committee. Central to a liberal democracy is a belief in shared power, and central to a liberal democracy is a suspicion of concentrated power. Central to a liberal democracy is the accountability of the executive to the Parliament. Central to a liberal democracy is the preservation of the following rights: freedom to criticise the government, freedom from arbitrary arrest, freedom of worship, the right to a fair trial, the right of assembly, freedom of movement. This Bill hands the government the power to throw out every one of those rights by decree, and there is no oversight of these powers. We are supposed to think critically in this place. We are supposed to come here, representing our constituents, thinking critically. That is why people elected us. Stop being sheep!
I find it inconceivable that a future Premier, for example, might determine that people with red hair cannot hold a job. I find that completely out of the realm of possibility. But do you know what? Two years ago I never contemplated that we would live in a world where someone who is not vaccinated cannot hold a job, cannot go into a shop, cannot go to an event. I never believed that we would come to a place as a state where we would see that – but here we are. These things do not happen overnight; they happen by degrees. Do I trust the Andrews government and all future governments to exercise these powers responsibly? No, I do not, and I think anyone who does is an absolute fool.
Labor MPs protest that this is what we asked for, that we called for elected politicians to be accountable for these decisions. What we called for was proper Parliamentary oversight, and that is why we have proposed that the power to make orders should require the approval of a constitutional majority of both houses of the Parliament.
When the president of the Victorian Bar Council comes out and says that the Stasi would be happy with the powers that this Bill confers, people need to sit up and take note. This is how he summarised it yesterday:
‘The Bill confers on the health minister in a practical sense an effectively unlimited power to rule the state by decree, for effectively an indefinite period, and without . . . judicial or parliamentary oversight . . . That doesn’t add up to good democracy.’
People might argue that ultimate accountability sits with the people at an election. If you do not like what a Premier has done, well, vote them out. But yesterday when we had the Bill briefing, the department could not say whether this Bill gives the power to the Premier to suspend elections. They did not know the answer to that, and they said they would have to come back and give us advice, which we still have not received. That remains unanswered.
The department does not know whether the Premier could use this Bill to suspend an election. Do you realise how extraordinary that is?
The Irish philosopher Edmund Burke said, ‘The people never give up their liberties but under some delusion.’ Those opposite tell us that unprecedented powers are required for unprecedented times. Governments always present compelling reasons to concentrate power. My grandmother came to this country fleeing Mussolini, and I am glad that she is not alive today to see what is happening. I genuinely am. I think she would be absolutely horrified. I honestly never believed that the people elected to this chamber would think that it is appropriate to hand the Premier and the health minister the kind of power to lock people up, to lock people down and to cancel protests without the checks and balances of Parliament – to strip people of their most basic rights without the oversight and the checks and balances of Parliament. The erosion of people’s liberties does not happen overnight; it happens by degrees. Streamline pandemic laws, by all means. We do not argue with that. We know that the government needs a certain degree of flexibility to control dangerous outbreaks of disease. We are not arguing about that. We are arguing for proper accountability and oversight. This Bill does not deliver those measures.
Let me conclude with the proverb that we all know because it is inscribed into the foyer of this building:
Where no Counsel is the People Fall; but in the Multitude of Counsellors there is Safety.
That is the principle of this Parliament, and it is the principle that I urge members of the Labor Party to adhere to. Do not give this unchecked power not just to this government but to future governments. It is wrong.
What happens when you fail in your attempts to create a vaccine for “Covid-19” and then realize you’ve just missed out on a billion-dollar profit-making opportunity?
You hurriedly develop a new drug, rush it through a clinical trial (which you yourself design to ensure good results), and then announce it to the world as the Covid cure we’ve all been waiting for, except no one’s been waiting for it because Covid isn’t any more deadly than the flu, and can be treated by easy-to-procure, inexpensive means (if it exists at all).
But governments are too stupid to know that and you own most of the corrupt politicians making the decisions, so who cares? As long as they’re willing to invest in your new concoction, it doesn’t even have to be necessary, or safe, or effective, or ethical…
Yes, I’m talking about “Molnupiravir”, Merck’s latest poison being promoted as an effective treatment against covid-19 (hang on, I thought that’s what the vaccines were for?).
This unapproved (yes, unapproved) drug costs $700 per course and the US government has just agreed to buy 1.7m courses. That’s a 1.2 BILLION dollar investment.
The deal is part of the Biden administration’s pledge to “respond to the health needs of the public”, but, in actuality, it’s simply a money-siphoning operation, with the American public coming off second best.
Molnupiravir is being sold to the public as the next big breakthrough in Covid-19 treatment off the back of what appears to be a SINGLE study, which was never even completed. Furthermore, the study was conducted by Merck (the makers of the drug), who chose not to disclose any adverse events. If that isn’t suspicious enough, the study was never published in a peer-reviewed journal.
Media press releases are apparently the new standard when it comes to evaluating medical treatments. After all, why would you wait for independent confirmation of your results or objective peer-review when you can get paid journalists, without a shred of medical expertise, to convince the public that they need your new drug?
If government scientists with integrity were in charge of assessing Molnupiravir, not bribed pharma shills, they may be alarmed at the lack of testing or the failure to disclose adverse events, they may even notice that vitamin D has had FAR superior results in combating “Covid-19”. In fact, one study, published in the highly respected and influential Journal of Clinical Endocrinology and Metabolism, found that vitamin D reduced mortality among severe covid-19 patients by 79%.
Compare that to the alleged 50% reduction offered by Molnupiravir for “mild-to-moderately ill” patients. Not to mention the difference in cost. As stated earlier, Molnupiravir runs at $700 per course, while vitamin D costs a fraction of that (probably less than $10!).
Furthermore, while Merck chose not to disclose adverse reactions, years worth of reliable data shows that vitamin D supplementation is extremely safe. And not only is taking vitamin D safe, but it also has a wealth of benefits for a variety of conditions including depression, anxiety, pain, inflammation, hypertension, cardiovascular disease and more.
As was obvious from the very beginning of the “pandemic” when nutritional medicine experts were slandered in the press for recommending “lethal” doses of vitamins, world health has been hijacked by the profit-hungry, empathy-dead, toxic cartel of Big Pharma “medicine”, and our governments have been in bed with them all along.
Furthermore, this has been going on longer than most people think. In fact, more than a decade earlier, governments were locking in billion-dollar deals to buy stockpiles of “Tamiflu”, an equally useless influenza drug that was later found to have no effect on reducing hospitalizations, deaths or complications from influenza.
In fact, Tamiflu was subsequently found to cause a raft of serious adverse reactions including delirium, panic attacks and even hallucinations. The “milder” side effects include nausea and vomiting.
In 2020, an unsealed whistleblower lawsuit revealed that drug company Hoffman-La Roche, the maker of Tamiflu, misrepresented clinical studies and made false claims regarding the effectiveness of the drug to treat influenza. In a 2020 article, Nasdaq quotes attorney Mark Lanier as saying that:
As alleged in the complaint – Tamiflu does not do what Roche promised… Roche hid this fact for many years by selectively citing its studies and suppressing the data about Tamiflu. The company utilized lobbyists, key opinion leaders and ghostwriters to promote Tamiflu with a deceptive promise to governments fearful of an influenza pandemic.”
Nonetheless, the medicine remains on the World Health Organization’s “essential medicines” list. The US and UK governments spent $1.3 billion and $703 million respectively buying “strategic reserves” of Tamiflu in preparation for a global flu pandemic.
At the time, the media (which had not yet totally sold out to Mr. Global) condemned the investments as a waste of money.
Governments made these outlandish investments off the back of “incomplete” data, which is exactly what has occurred with the latest deal to procure Merck’s Molnupiravir. And I’ll bet that when more data comes out, it will be found, once again, that governments wasted millions of dollars of taxpayers’ money.
Bribed politicians would rather deepen their pockets than institute sensible health policies or invest money into procuring and promoting vitamin D, which would not only save lives but help to improve mental health in a woefully deficient population ravaged by anxiety and depression.
As functional medicine expert, Dr. Alex Vasquez states in his latest blog,
… viral infections and the fear and ignorance around them have become a great way for drug companies to sell worthless drugs to their bribed politicians. If we spent that money on heath-promotion rather than fear-promotion, we’d be freer, stronger, healthier, and we’d emancipate ourselves from the mental slavery of fear, ignorance, and dependence.”
Furthermore, the importance of sunlight cannot be overstated, for apart from being our principal source of Vitamin D, it also induces the production of several powerful antiviral metabolites that aid the body in fighting off illness.
This article would not be complete without at least mentioning some of the corrupt dealings, legal cases and blatant crimes that Merck has been involved in over the years. The most egregious of these offenses, and one of the largest scandals in medical history, was the company’s promotion of its anti-inflammatory drug, Vioxx.
During its height, Vioxx was earning Merck $2 billion in revenue per year and estimations have found that around 25 million patients were prescribed the drug. In September 2004, Merck was forced to recall Vioxx on account of it being shown to cause adverse cardiovascular events, such as heart attacks and stroke.
Merck was slammed with a massive class-action lawsuit that was eventually settled for $4.85 billion in 2007. Not only did Merck cover up data suggesting its drug was dangerous, they illegally promoted it as an “off-label” treatment for rheumatoid arthritis, without any indication of its effectiveness.
According to the testimony of Dr. David Graham, the Associate Director for Science and Medicine in FDA’s Office of Drug Safety, Vioxx caused 55,000 premature deaths from heart attacks and stroke.
Even years after taking the medication, patients often still experience problems, indicating that Vioxx may have killed far more people than the conservative estimate made by Dr. Graham, who, after all, works for the FDA, the organization that was responsible for assessing the drug’s safety.
In fact, after analysing US national mortality data starting from the year Vioxx was released up to the year it was withdrawn, Ron Unz, [former] publisher of The American Conservative, came to the startling conclusion that Vioxx may have been responsible for up to 500,000 deaths, mostly in the elderly (age 65+) population.
After the scandal, Merck hired the services of PR company, Burson-Marstellar (whose past campaigns include covering up genocide in Nigeria, fighting health authorities on the issue of second-hand cigarette smoke, and playing down Apple’s abuse of Chinese factory workers), to help clean up its public image and assert them as an “ethical player in the healthcare arena”.
And it seems to have worked, for here we are, 15 years later with another worthless – and possibly quite dangerous – Merck drug being promoted around the world as a treatment for “Covid-19”. Predictably, the UK government has now expressed interest in Molnupiravir, with many more countries expected to follow suit.
But Merck’s criminal history stretches further back than 1999 when Vioxx hit the shelves, for, as early as the 1960s, Merck faced controversy regarding its arthritis medication, Indocin. Although the drug had been approved by the FDA, it was later revealed that the medication had not been adequately tested for efficacy or side effects.
Less than a decade later, Merck’s drug DES (diethylstilbestrol), alleged to prevent miscarriages, was found to be carcinogenic, causing cases of cervical cancer and other gynaecological disorders. And last (but certainly not least), in 2007, Merck’s cholesterol drug, “Zetia” was shown to cause liver disease, a risk that was known to Merck who intentionally concealed the damning trial results.
For those who think the media are simply biased towards pharmaceutical drugs, this is a naive assumption. Behind the headline-making newspapers, magazines and television programs is a coordinated socio-political power vortex seeded in Big Pharma/Big Money corruption.
Medical journals are inherently biased towards publishing pro-drug articles. These then serve as advertisements for the pharmaceutical industry which pays millions of dollars for journal reprints.
Mainstream media outlets such as newspapers, magazines, TV shows and online publications then republish the pro-drug information, much to the delight of the pharmaceutical industry.
Medical science and mainstream media then become a pro-drug echo chamber for biased, Big Pharma propaganda.
Drug companies increase their sales, gaining profits and building influence to the point where they have more power than governments.
Pharmaceutical companies infiltrate medical education, media, and health policy; they pay “researchers” to publish and teach information favourable to the pharmaceutical paradigm.
Governments then write policies and make investments that favour drug companies rather than the citizens of that country.
At the time of writing, Molnupiravir has not yet been FDA approved. However, Merck has asked the FDA to grant “emergency” approval on account of the drug’s alleged effectiveness. Considering the decisions made by the FDA thus far, along with the fact that funding from pharmaceutical companies like Merck makes up 75% of the FDA’s drug review budget, what do you think the chances are of Molnupiravir’s approval being granted?
And would you trust a doctor who prescribed it to you?
Dr. Peter McCullough, an internist, cardiologist and trained epidemiologist, not only sees patients every week but is the editor of two medical journals and has published hundreds of peer-reviewed papers. Prior to the pandemic, he was involved in the interface between heart disease and kidney disease — but that all changed.
McCullough is now a “hunted doctor” who’s been threatened with disciplinary actions, including suspension or revocation of his medical license, by the American Board of Internal Medicine for the “dissemination of misinformation.”1 He stepped forward during the COVID-19 pandemic because he saw something very wrong was going on early in 2020, and he felt compelled to do something about it.
In the video above, you can view McCullough’s October 27, 2021, presentation with the Association of American Physicians and Surgeons (AAPS). I urge you to set aside one hour to view it in its entirety, as it’s packed with data that call into question the true motivations behind the mass injection campaign, which he believes should have been shut down in January.
Red Flags Showed Jabs Were Unsafe From the Start
According to McCullough, by January 22, 2021, there had been 186 deaths reported to the Vaccine Adverse Event Reporting System (VAERS) database following COVID-19 injection — more than enough to reach the mortality signal of concern to stop the program.
“I know data, and I know safety. The FDA knows I know safety. In fact, I’ve chaired data safety monitoring boards for the National Institutes of Health and Big Pharma,” he said.3 It’s standard to have an external critical event committee, an external data safety monitoring board and a human ethics committee for large clinical trials — such as the mass COVID-19 injection program, but these were not put into place.
“With a program this size, anything over 150 deaths would be an alarm signal,” he said. The U.S. “hit 186 deaths with only 27 million Americans jabbed.” McCullough believes if the proper safety boards had been in place, the COVID-19 jab program would have been shut down in February 2021 based on safety and risk of death.4
Such was the case in 1976, when a fast-tracked injection program against swine flu was halted after an estimated 25 to 32 deaths.5 “We are far beyond that now,” McCullough said.6
While many have been silenced, McCullough found a way to share his concerns via regular contributions to The Hill and, back in August 2020, he warned that putting off early treatment in favor of waiting for an experimental injection was taking a gamble with people’s lives:7
“Warnings and barriers have prevented hundreds of thousands of patients from being treated at home with appropriate non-labelled use of off-target antivirals (zinc, hydroxychloroquine, azithromycin, doxycycline), steroids (dexamethasone, prednisone, budesonide, colchicine), and antithrombotics (low-molecular weight heparin, oral anticoagulants).
It has become apparent that America has adopted a late-illness hospitalization model while waiting patiently and painfully for the panacea of a COVID-19 vaccine.”
The Jab’s Spike Protein Is a Deadly Protein
The whole world seems to be in lockstep with one narrative — that an injection is the only way out of the pandemic. What’s been kept quiet is the significant health risks that come with the experimental jabs. “Spike protein is a deadly protein,” McCullough said.8 It should be noted that McCullough is not antivaccine — he’s recently had a flu shot. However, the COVID-19 jabs are different:9
“It’s the first time in human medicine that we are injecting vaccines and we’re asking the human body to make a potentially lethal protein. The hope is we make a small enough amount of it and it would create just enough of an immune test that we form immunity to this deadly protein.
The gamble was, what if we make too much? What if we make it for too long of a period of time? What if these lipid nanoparticles go to the wrong organs and don’t stay in the arm, and we start to produce this lethal protein …?”
In August 2021, a large study from Israel10 revealed that the Pfizer COVID-19 mRNA jab is associated with a threefold increased risk of myocarditis,11 leading to the condition at a rate of one to five events per 100,000 persons.12 Other elevated risks were also identified following the COVID-19 jab, including lymphadenopathy (swollen lymph nodes), appendicitis and herpes zoster infection.13
Vaccine-induced immune thrombotic thrombocytopenia is another serious complication of COVID-19 injections,14 and fertility concerns have also been raised. Pfizer’s biodistribution study, which was used to determine where the injected substances go in the body, even showed the COVID spike protein from the shots accumulated in “quite high concentrations” in the ovaries.15
In May 2021, McCullough was one of 57 authors to sign a paper demanding answers to urgent questions on the jabs’ safety and calling for the mass injection program to be halted immediately if safety cannot be adequately proven and monitored.16
At the very least, McCullough noted, pregnant women, women of childbearing age and COVID-19 survivors shouldn’t have been vaccinated, as these groups were excluded from the jabs’ clinical trials because “they knew they weren’t going to work or would cause excessive harm” in these populations.17
Even with all of these blatant risks, health officials haven’t given any updates or regular briefings on the jabs, such as which one of the three — Pfizer, Moderna or Johnson & Johnson — works “best” or is preferred. A “vaccine ‘report card’ on safety is long overdue,”18 according to McCullough, who believes, “The disability that we are going to see due to these vaccines will go down in history as an unbelievable atrocity.”19
Injection Deadlier, Statistically, Than COVID-19
People are dying from COVID-19 jabs. In an analysis of COVID-19 vaccine death reports from VAERS, researchers found that 86% of the time, nothing else could have caused the death, and it appears the vaccine was the cause.20 Despite this, the U.S. Centers for Disease Control and Prevention continues to say that no causal link has been found between COVID-19 and the deaths.21 That’s malfeasance, McCullough says.
Even more shocking is a Toxicology Reports study that found the injections are deadlier, statistically, than COVID-19.22 “Because not everybody gets the respiratory infection, and because the respiratory infection is treatable and manageable, in fact one is more likely to die after the vaccine than just take their choice with forgoing the vaccine and potentially getting COVID-19. Statistically, in every age group, that’s the case,” he stated.23
You can see the data for yourself in the study’s graphical abstract, below. The researchers explained:24
“A novel best-case scenario cost-benefit analysis showed very conservatively that there are five times the number of deaths attributable to each inoculation vs those attributable to COVID-19 in the most vulnerable 65+ demographic. The risk of death from COVID-19 decreases drastically as age decreases, and the longer-term effects of the inoculations on lower age groups will increase their risk-benefit ratio, perhaps substantially.”
Vaccine Failures Can’t Be Denied
Along with the health risks are the undeniable cases of “breakthrough infections,” otherwise known as vaccine failures. As of October 12, 2021, the CDC stated that 31,985 people who were fully injected against COVID-19 were hospitalized or died from COVID-19.25
Yet, media reports keep referring to the pandemic as a crisis of the unvaccinated, which is simply inaccurate since COVID-19 continues to affect and spread among those who have been vaccinated. The CDC’s Morbidity and Mortality Weekly Report (MMWR) posted online July 30, 2021, details an outbreak of COVID-19 that occurred in Barnstable County, Massachusetts — 74% of the cases occurred in fully vaccinated people.26
With breakthrough cases on the rise, on May 1, 2021, the CDC stopped monitoring most COVID-19 infections among vaccinated people.27 “The CDC started to do asymmetric reporting to start to craft a narrative that this was going to be a failure of the unvaccinated, a crisis of the unvaccinated,” McCullough said. “But the CDC data continued to come in showing us just the opposite.”28
Pivot to Early Treatment Is Necessary
The data are clear that a pivot away from mass injections to early treatment for COVID-19 could save lives, and McCullough and colleagues recommend that you demand early treatment if you have COVID-19, whether or not you’ve been vaccinated.29
McCullough’s early treatment regimen initially includes a nutraceutical bundle of zinc, vitamin D, vitamin C and quercetin. While you’re recovering at home, open your windows and get plenty of fresh air and ventilation in your home. If symptoms persist or worsen, he recommends calling your doctor and demanding monoclonal antibody therapy.
The treatment progresses to include anti-infectives like HCQ or ivermectin, antibiotics, steroids and blood thinners. If your doctor refuses to treat COVID-19 in the early stages, find a new one and/or visit a telemedicine clinic that will help, as “the prehospital phase is the time of therapeutic opportunity.” You can also download McCullough’s and colleagues’ Guide to Home-Based COVID Treatment.30 He states:31
“I have not let a single one of my high-risk patients get slaughtered by the virus. And any doctor who has — and there’s been a million doctors who have — is immoral, is unethical and, from a clinical and civil perspective, is illegal. And I think there is going to be a price to pay.
It’s going to be years in the future, but there’s going to be a price to pay for all of these patients who have died. And if you look through the records on all of them, I will tell you they were all inadequately treated. Every single one of them.”
Outrage Over Forced Injection Grows
With the injections causing harm and failing to protect as promised, frustrations are mounting worldwide due to increasing injection mandates. McCullough noted:32
“The tension is ratcheting up all over the world as the Delta outbreak continues to flare in many heavily vaccinated regions of the world. When more than 25% of the population takes the ill-advised COVID-19 vaccine, this promotes a super-dominant mutant that can easily evade the vaccines’ weak protection, which has happened with Delta.
… Frustration is coming out in folk songs, and the pop music industry, as shown in Eric Clapton’s ‘Enough is Enough’ and ‘Waking Up’ … Expect more to come as many wake up to the reality that our government agencies have failed us on the science, transparency, and safeguarding Americans from conflict of interest.“
McCullough is among a growing number of experts who believe COVID-19 injections are making the pandemic worse instead of better, while effective solutions are being ignored and intentionally suppressed.
“Early ambulatory therapy with a sequenced, multi-drug regimen is supported by available sources of evidence and has a positive benefit-to-risk profile,” he explains, while “COVID-19 genetic vaccines have an unfavorable safety profile and are not sufficiently effective, thus they cannot be supported in clinical practice at this time.”33
Unfortunately, “censorship and reprisal are working to crush freedom of speech, scientific discourse and medical progress”34 McCullough calls on everyone to stand up against the propaganda, but especially doctors, who he believes can save lives by offering early COVID-19 treatment to their patients.
In a shocking departure from traditional hospital policies, a hospital admission has become like reporting to prison. Prisoners in America’s jails have more visitation rights than do COVID patients in America’s hospitals.
One family member, a professional psychologist with a career focus treating victims of trauma, said that in many hospitals COVID patients are treated “little better than animals.”
Shocking recordings of Mayo Clinic-Scottsdale and Banner Health System hospital executives have been released by an attorney on the Legal Advisory Council of Truth for Health Foundation, an Arizona public charity. Executives were discussing coordinated efforts to restrict fluids and nutrition for hospitalized COVID patients and to suppress all visitations for COVID patients.
The COVID protocol that hospital physicians must follow, in lockstep across the U.S., appears to be the implementation of the 2009-2010 “Complete Lives System” developed by Dr. Ezekiel Emanuel for rationing medical care for people older than 50.
Dr. “Zeke” Emanuel, who was the Senior White House Health Policy Advisor to President Obama and has been advising President Joe Biden about COVID-19, stated in his classic 2009 Lancet paper: “When implemented, the complete lives system produces a priority curve on which individuals aged between roughly 15 and 40 years get the most substantial chance, whereas the youngest and oldest people get chances that are attenuated.”
“Attenuated” means rationed, restricted, or denied medical care that commonly leads to premature death.
In 2021, whistleblower doctors, nurses, attorneys, patient advocates, and journalists have exposed egregious hospital abuses, neglect of patients, denial of vital intravenous fluids and basic medicines to hospitalized COVID patients across the U.S.
The Complete Lives Protocol apparently derives from the 1990s UK National Health Service “Liverpool Pathway,” which in effect constituted euthanasia.
Now we see its malevolent manifestation in the “COVID Protocol.” Age-based rationing is happening every day on COVID units of our hospitals, since the overwhelming majority of COVID patients are older than 50, the age at which Emanuel claims that a life is “complete” and not worth the use of medical resources.
“Complete Lives System” and the “COVID Protocol” are pathways leading to suffering and premature death, mainly of older Americans. They achieve the government’s goal of reducing Medicare costs. At the same time, hospitals make untold extra millions with extra incentive payments for COVID patients during their tortured path to death, while they are chemically and physically restrained and isolated from families, pastors, priests, and rabbis.
The heartbreaking story of Veronica Wolski, a well-known Chicago Freedom advocate, was widely publicized. Once hospitalized in ironically named Resurrection Hospital, Veronica was given remdesivir, which she had repeatedly refused, denied proper basic medical care that could have been life-saving, and was not allowed access to her family, priest, or healthcare power of attorney. The hospital blocked Veronica leaving the hospital when she and her attorneys demanded release. Her healthcare power of attorney was removed by hospital security. Veronica died alone as a medical prisoner in a Catholic hospital denied even a priest at the end of her life.
Unconscionable hospital violations of human rights, including even violations of the Geneva Convention codes established following World War II to prevent abuses of prisoners, are occurring daily across the U.S.
Patients are coerced to take rapidly approved drugs like Remdesivir, in spite of known risks of kidney and liver failure, and to be placed on ventilators, both of which bring in incentive payments and create huge profits for hospitals.
Patients are denied adequate fluids and nutrition, as well as vitamins, inhaled and intravenous corticosteroids, antibiotics, antivirals, and adequate doses of “blood-thinners” (anticoagulants).
Patients suffer inhumane isolation with use of chemical and physical restraints, in violation of existing guidelines for patient protection.
Hospitals are using law enforcement to deny access to hospital grounds for family and advocates.
Patients and their advocates have been denied information on benefits of early treatments and denied access to such treatment. Autopsies have confirmed many patients died because of inadequate doses of standard anticoagulation, even after family members went to court to demand therapeutic doses to help save lives.
Doctors and nurses risk their careers, their licenses, livelihoods, and even their lives as they courageously speak out to inform their patients and the public with life-saving information. One ICU physician colleague posted this on social media recently:
Just finished a 10-night stretch in the ICU. Patient bashing and blatant meanness have taken on a whole new level within our healthcare colleagues. How can we NOT spiral downwards towards despair when this behavior is allowed and is being normalized?? … I feel I’ve been thrown into a Mean Girls sequel. Making fun of patients and families for not being V’d is the cool thing now. … I don’t mind taking care of COVID patients. But this hateful vibe that has permeated my world is what’s going to end my career if it doesn’t end.”
Welcome to the brave new world of government-directed medical care carried out by obedient, profit-focused hospital executives eager for the government handouts of incentive payments for following the “COVID Protocol.”
About the author: Dr. Vliet is the President and CEO of Truth for Health Foundation, a 501(c)(3) public charity, and the creator of the Foundation’s innovative six initiatives that advocate for early outpatient COVID treatment, assist families of hospitalized patients denied effective treatment, defend medical freedom, and provide international educational and training programs focused on effective strategies for COVID and on the interconnections of health, faith and lifestyle approaches for restoring resilience and quality of life.
Since February 2020, Dr. Vliet has been part of the team of frontline physicians treating COVID early at home to reduce hospitalizations and death. With Dr. Peter A. McCullough, she is a co-author/editor of the Guide to COVID Early Treatment: Options to Stay Out of Hospital and Save Your Life. (https://www.truthforhealth.org/patientguide/patient-treatment-guide/). Dr. Vliet is a 2014 Ellis Island Medal of Honor recipient for her national and international educational efforts in health, wellness, and endocrine aging in men and women. She is also the 2007 recipient of the Voice of Women from the Arizona Foundation for Women, and a past director of the Association of American Physicians and Surgeons (AAPS) and a member of the AAPS Editorial Writing Team since 2009.
Dr. Vliet has been a leader in patient centered, individualized medical care. Since 1986, she has practiced medicine independent of insurance contracts that interfere with patient-physician relationships and decision-making. Dr. Vliet is the founder of Vive Life Center with medical practices in Tucson AZ and Dallas TX, specializing in preventive and climacteric medicine with an integrated approach to evaluation and treatment of women and men with complex medical and hormonal problems from puberty to late life.
Dr. Vliet’s consumer health books include: It’s My Ovaries, Stupid; Screaming To Be Heard: Hormonal Connections Women Suspect– And Doctors STILL Ignore; Women, Weight and Hormones; The Savvy Woman’s Guide to PCOS, The Savvy Woman’s Guide to Great Sex, Strength, and Stamina.
Dr. Vliet received her M.D. degree and internship in Internal Medicine at Eastern Virginia Medical School and completed specialty training at Johns Hopkins. She earned her B.S. and master’s degrees from the College of William and Mary in Virginia. Dr. Vliet has presented hundreds of professional CME programs for physicians and allied health professionals, healthcare Town Halls addressing the economic and medical impact of government intrusion into medicine, free market reforms, and consumer seminars and radio shows on integrated approaches to Men’s Health and Women’s Health.
Dr. Vliet speaks as an independent physician, not as a spokesperson for any healthcare system, pharmaceutical company, insurance plans, or political party. Her allegiance and advocacy is to and for patients. Dr. Vliet’s medical and educational websites are www.TruthForHealth.org And www.ViveLifeCenter.com
The drug-induced nipple secretions of trans women are as good as mothers’ breast milk for babies, the University of Sussex Hospitals NHS Trust claimed in a letter to campaigners made public in a report by British think tank the Policy Exchange on Sunday.
The healthcare trust’s medical director, Rachel James, argued that the off-label prescription drug cocktail men transitioning to female take in order to produce milk was “similar to the natural hormones which encourage lactation to develop when the baby is newly born.”
“The evidence which is available demonstrates that the milk is comparable to that produced following the birth of a baby,” James wrote in the letter, sent to Children of Transitioners last August.
Biological men who wish to lactate must first take hormones to grow milk glands and then take high doses of either domperidone or metoclopramide to stimulate milk production. Neither drug is approved for this use, though they are occasionally prescribed off-label to biological women who have trouble lactating.
However, domperidone’s own manufacturer, Janssen, warns patients the drug “may cause unwanted side effects affecting the heart in a breastfed baby” and “should be used during breastfeeding only if your physician considers this clearly necessary.” … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.


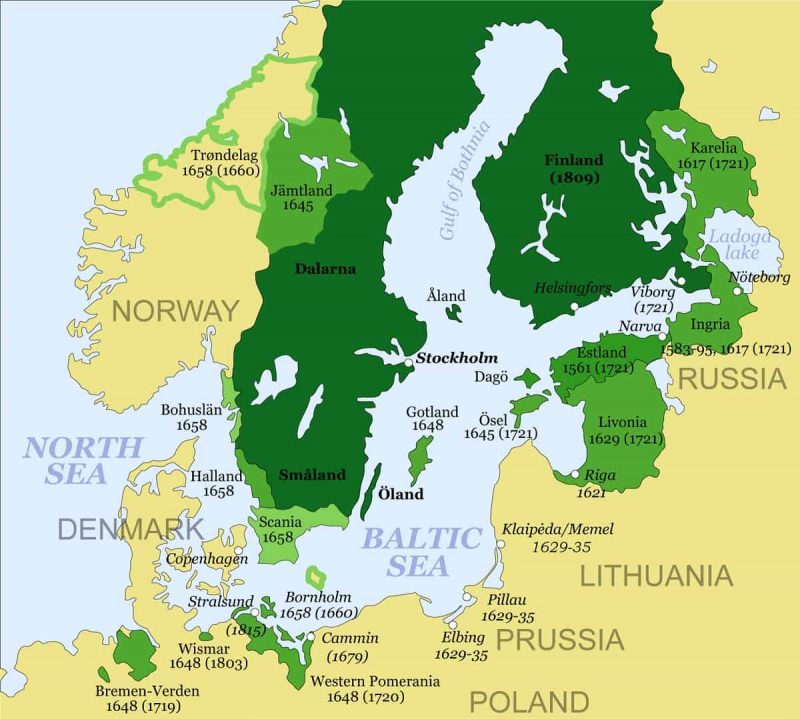
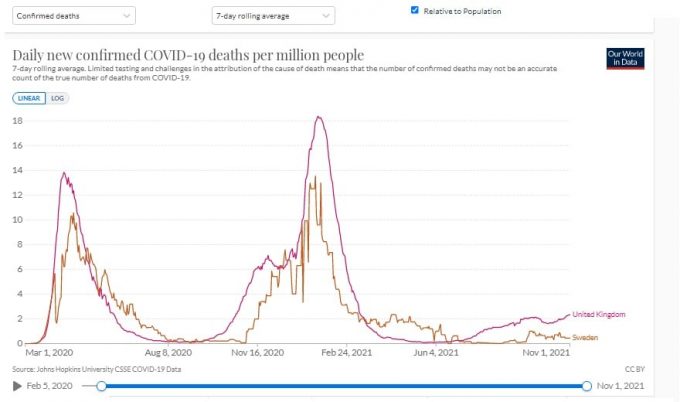
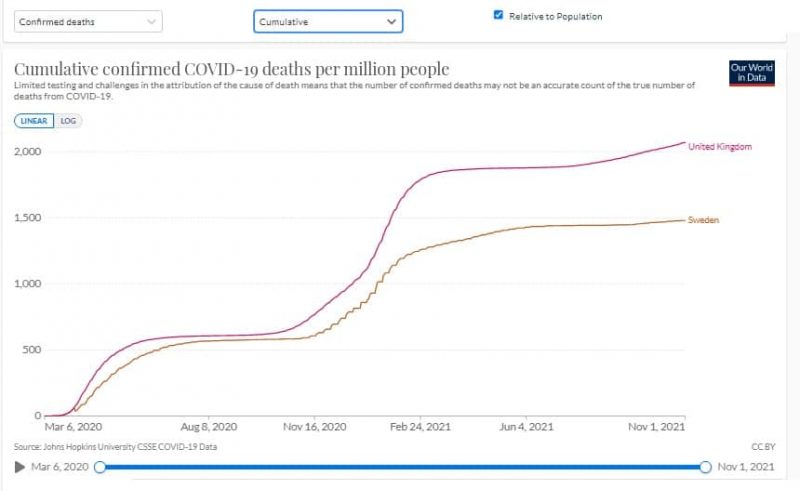

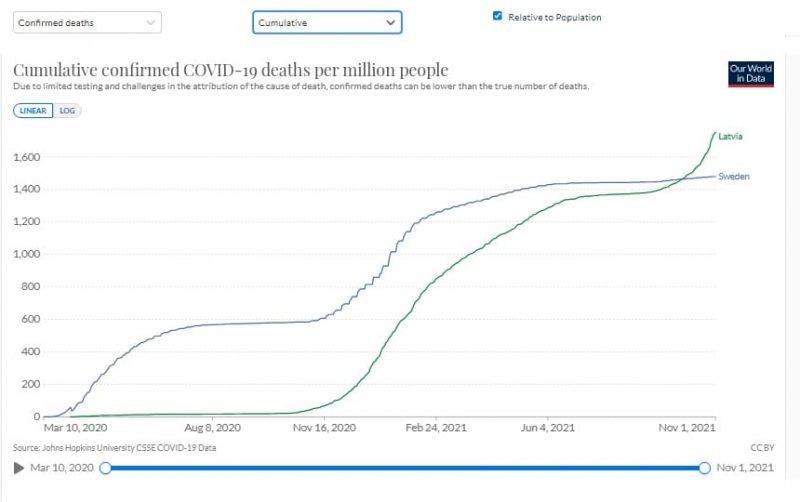
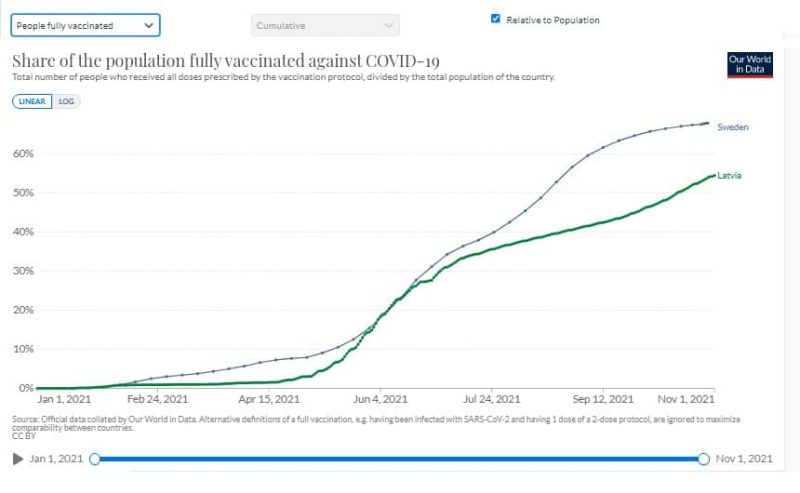
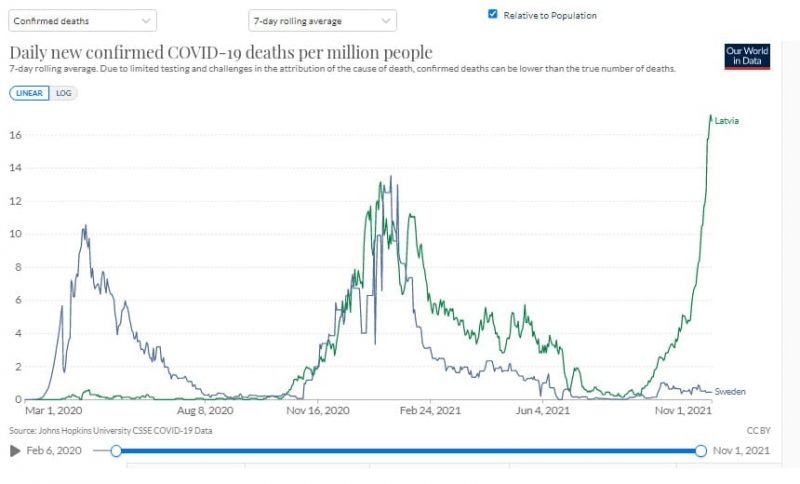






 Aletho News
