Patrick Vallance’s Defence of SAGE Modelling Fails to Convince
By Will Jones | The Daily Sceptic | December 24, 2021
Chief Scientific Adviser Sir Patrick Vallance has come to the defence of SAGE and its modelling after some torrid headlines this week following a Twitter exchange between lead modeller Professor Graham Medley and Spectator editor Fraser Nelson in which Professor Medley revealed that SAGE had not been asked to model less disastrous scenarios.
Writing in the Times, Dr. Vallance appeared directly to contradict some of the statements made by Prof. Medley, leaving observers baffled as to which of the two is correct as it is unclear how both can be. Dr. Vallance claimed that modelling of other, less severe scenarios, had been done and presented to Government, while Prof. Medley said it had not, at least by his team at the London School of Hygiene and Tropical Medicine (LSHTM). Dr. Vallance writes:
The modellers always have to make assumptions and do so across a wide range of possibilities, some optimistic and some pessimistic. They do not, contrary to what you might have heard, only model the worst outcomes. They will make assumptions about vaccine effectiveness, they will model different levels of viral transmission, mixing patterns and different levels of disease severity. The range of assumptions modelled can be very broad; for disease severity for Omicron one model explored a range from 10% of Delta severity through to 100%. For immunity a range of assumptions on vaccine efficacy, speed of vaccine rollout and vaccine coverage in different parts of the population were explored.
This claim is backed up by the minutes of the most recent SAGE meeting, published yesterday, although it doesn’t square with what Prof. Medley told Fraser Nelson. Prof. Medley, who chairs the SAGE modelling committee, said that lower virulence scenarios don’t “add any further information” and implied his committee – SPI-M – had not been asked to provide them.
Fraser asked Prof. Medley: “I guess the question is why LSHTM did not (like JP Morgan) include a scenario of lower virulence – given that this is a very-plausible option that changes outlook massively.”
What would be the point of that? Not a snarky question – genuine to know what you think decision makers would learn from that scenario… If somebody draws a line on a graph it doesn’t add any further information. Decision-makers are generally only interested in situations where decisions have to be made… That scenario doesn’t inform anything. Decision-makers don’t have to decide if nothing happens… We generally model what we are asked to model. There is a dialogue in which policy teams discuss with the modellers what they need to inform their policy.
Fraser later observed that Prof. Medley appeared to be saying his brief was very limited and did not include less severe assumptions and outcomes.
He seemed to suggest that he has been given a very limited brief, and asked to churn out worse-case scenarios without being asked to comment on how plausible they are… Note how careful he is to stay vague on whether any of the various scenarios in the SAGE document are likely or even plausible. What happened to the original system of presenting a ‘reasonable worse-case scenario’ together with a central scenario? And what’s the point of modelling if it doesn’t say how likely any these scenarios are?
From what Professor Medley says, it’s unclear that the most-likely scenario is even being presented to ministers this time around. So how are they supposed to make good decisions? I highly doubt that Sajid Javid is only asking to churn out models that make the case for lockdown. That instruction, if it is being issued, will have come from somewhere else.
Dr. Vallance, on the other hand, says:
Often the job of scientific advice is to allow ministers to understand both a central case and the uncertainty surrounding it, what drives that uncertainty and when the uncertainty might be reduced. Speaking scientific truth to power is a difficult but necessary part of the democratic process if ministers are to be able to make an informed decision. This is what SAGE does.
If Dr. Vallance is accurately describing the advice given to ministers by SAGE, why did LSHTM not model those scenarios and estimate their likelihood? Why did the chairman of the SAGE modelling committee state that such scenarios had not been requested because they do not add anything useful to the discussion? The only explanation I can think of is that the broader range of scenarios referred to in the minutes of the SAGE meeting dated December 20th was not reflected in the SAGE memo circulated to ministers for that afternoon’s Cabinet meeting. That is, SAGE modelled less gloomy scenarios but didn’t bother to include them in the advice it gave to the Cabinet.
Dr. Vallance claims SAGE is a neutral adviser, being neither pessimistic nor optimistic and not pushing for any “dogmatic” answer or directive.
It is not the job of SAGE to take a particular policy stance or to either spread gloom or give Panglossian optimism. Ministers and the cabinet need to hear the information whether uncomfortable or encouraging. They of course need to factor it in to all the other information that provides inputs to policy decisions. SAGE does not provide dogmatic answers or directives, it provides information, advice, scenarios and helps determine possible consequences of actions. Part of the advice may contain a “reasonable worst case scenario” – data that are often seized upon.
But they are just that – a reasonable worst case scenario and one of many possible outcomes and trajectories presented to ministers for planning purposes and decision making.
But Dr. Vallance is failing to acknowledge the reason that prompted the need for his defence of SAGE modelling in the first place, which is that the chairman of his main modelling committee had stated that they had not been asked to provide alternative scenarios to ministers because it “doesn’t add any further information”. Dr. Vallance implies that others are at fault for having arbitrarily “seized upon” the reasonable worst case scenario presented to ministers, ignoring that the present controversy arose because the Government’s lead modeller said no other scenarios were modelled because they were pointless.
Dr. Vallance is also being, at best, naïve about the key role SAGE’s projections and advice have played in pushing the Government into making extreme interventions. His comments here about it being “not the job of SAGE to take a particular policy stance or to either spread gloom or give Panglossian optimism” are contradicted by his enthusiastic endorsement of boosters earlier in the same article – “Vaccine boosters are crucial” – and by what he told the BBC in October about his risk-averse approach to the pandemic.
My mantra for a long time during this (pandemic) has been… you’ve got to go sooner than you want to in terms of taking interventions. You’ve got to go harder than you want to, and you’ve got to go more geographically broad than you want to. And that is the Sage advice. And that’s what I’ve been saying. And I will say it going forward, and the prime minister knows that’s what I think. And he knows that’s what I would do in that situation.
That sounds very much like he’s offering policy recommendations to me, and recommendations of precisely the kind he’s denying SAGE makes in his Times article.
Dr. Vallance concludes with a defence of the role of science and the scientific method in the pandemic.
Science has served us extraordinarily well during this pandemic and has given us many insights as well as new diagnostics, vaccines and therapeutics. Science is self-correcting, and advances by overturning previous dogma and challenging accepted truths. Encouraging a range of opinions, views and interpretation of data is all part of the process. No scientist would ever claim, in this fast-changing and unpredictable pandemic, to have a monopoly of wisdom on what happens next.
Yet two of America’s top scientists, Francis Collins and Anthony Fauci, have been exposed as plotting to smear the eminent authors of the Great Barrington Declaration. Dr. Collins wrote to Dr. Fauci that the declaration was the work of “three fringe epidemiologists” and “seems to be getting a lot of attention”. He added that “there needs to be a quick and devastating published takedown of its premises. I don’t see anything like that online yet – is it underway?” Shortly afterwards an online ‘fact check‘ appeared, courtesy of a team that included U.K. Government-linked MP Neil O’Brien.
So much for challenging accepted truths and encouraging a range of opinions.
It’s good to see the gloomy lockdown zealots on the back foot for a change and having to defend themselves. I just wish they could stick with the facts rather than spinning make-believe and changing the ‘facts’ to fit the narrative rather than vice-versa.
Stop Press: Dr. Jenny Harries, Chief Executive of the UKHSA, has also taken to the airwaves in defence of the advisers’ doomy forecasts, telling the BBC that while there’s “a glimmer of Christmas hope in the findings that we published yesterday”, it “definitely isn’t yet at the point where we could downgrade that serious threat”, referring to her earlier claim that Omicron was “probably the most significant threat we’ve had since the start of the pandemic”. For evidence she pointed to the “quite staggering” speed of spread compared to previous variants – despite her own agency publishing data this week showing that the household secondary attack rate (the proportion of household contacts an infected person infects) of Omicron is lower than the direct secondary attack rate (an almost equivalent measure) of the Alpha variant this time last year.
State Climatologist Falsely Claims Climate Change Causing More Severe Weather
By H. Sterling Burnett, Ph.D. | ClimateRealism | December 21, 2021
Near the top of the results of Google new search of the phrase climate change today is a post from KPTM Fox 42 in Omaha, Nebraska claiming climate change is contributing to an increase in extreme weather events. This is false. Real-world data and the most recent report from the U.N. Intergovernmental Panel on Climate Change (IPCC) indicate the incidences of extreme weather events are not increasing, nor are the duration or severity of such events worsening.
For the article, titled “State Climatologist says climate change is contributing to severe weather,” KPTM Omaha interviews Martha Shulski, Nebraska’s state climatologist concerning recent severe weather events which hit the state.
Shulski linked these events to climate change.
“‘Climate change is something that it is real and here now,’” Shulski told KPTM, continuing, “‘It really impacts everything, the question is not did climate change cause it, the question is more how much worse was it made with climate change. There is a climate change signature on all of these events we experience, its really just a matter of how strong of a signature.’”
Nobody disputes climate change is occurring. Climate has changed on local, regional, continental, and global scales across the course of history. However, available data does not show ongoing climate change is making instances of extreme weather more common or more severe.
The KPTM article discusses a recent spate of tornadoes which struck Iowa and Nebraska in mid-December. Concerning tornadoes, the IPCC states, “There is low confidence in observed trends in small spatial-scale phenomena such as tornadoes.”
As discussed in Climate at a Glance: Tornadoes, data conclusively shows the number of tornadoes has been declining for the past 50 years, and, as shown in the figure below, the number of strong tornadoes, F3 or higher, has been dramatically declining for the past 50 years.
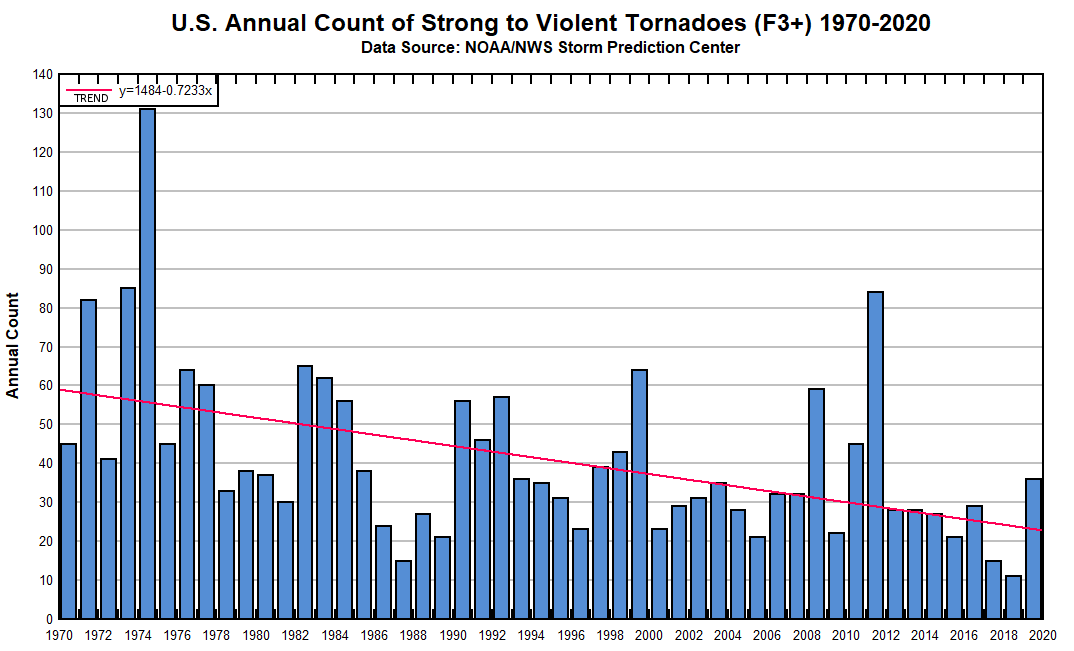
From 2017 through 2018, the U.S. set a record for the longest period in history without a tornado death. Also in 2017 and 2018, the U.S. set a record for the longest period in history without an F3 or stronger tornado. The two record-low years for number of tornadoes both occurred this past decade, in 2014 and 2018, a decade which climate alarmists have regularly described as the warmest on record. Even counting the recent December tornadoes, the number of tornados recorded in 2021 has been below average.
Concerning flooding, another extreme weather event Shulski links to climate change in the KPTM story, there has been no increase flooding frequency or severity as the climate modestly warms. The IPCC admits having “low confidence” in any climate change impact regarding the frequency or severity of floods. Although the IPCC states in its recent 6th Assessment Report, “the frequency and intensity of heavy precipitation have likely increased at the global scale over a majority of land regions with good observational coverage,” it explicitly states “heavier rainfall does not always lead to greater flooding.”
In addition, the IPCC writes, “Confidence about peak flow trends over past decades on the global scale is low, … [and] there is low confidence in the human influence on the changes in high river flows on the global scale.”
The best available evidence shows extreme weather is neither more frequent, nor more severe than it has been historically. Shulski was wrong to say otherwise, and KPTM was wrong to report her claims without checking the facts.
Two thirds of recent UK “covid hospitalizations” are not for covid
el gato malo – bad cattitude – decmeber 26, 2021
at what point will the world wake up to the fact that we are currently inhabiting far more of a testdemic than a pandemic?
data from the UK is showing that only 1 in 3 recent “covid hospitalizations” is actually in the hospital for covid. the vast majority were there for something else and tested positive after admission. this is literally tripling the reported count of new patients.
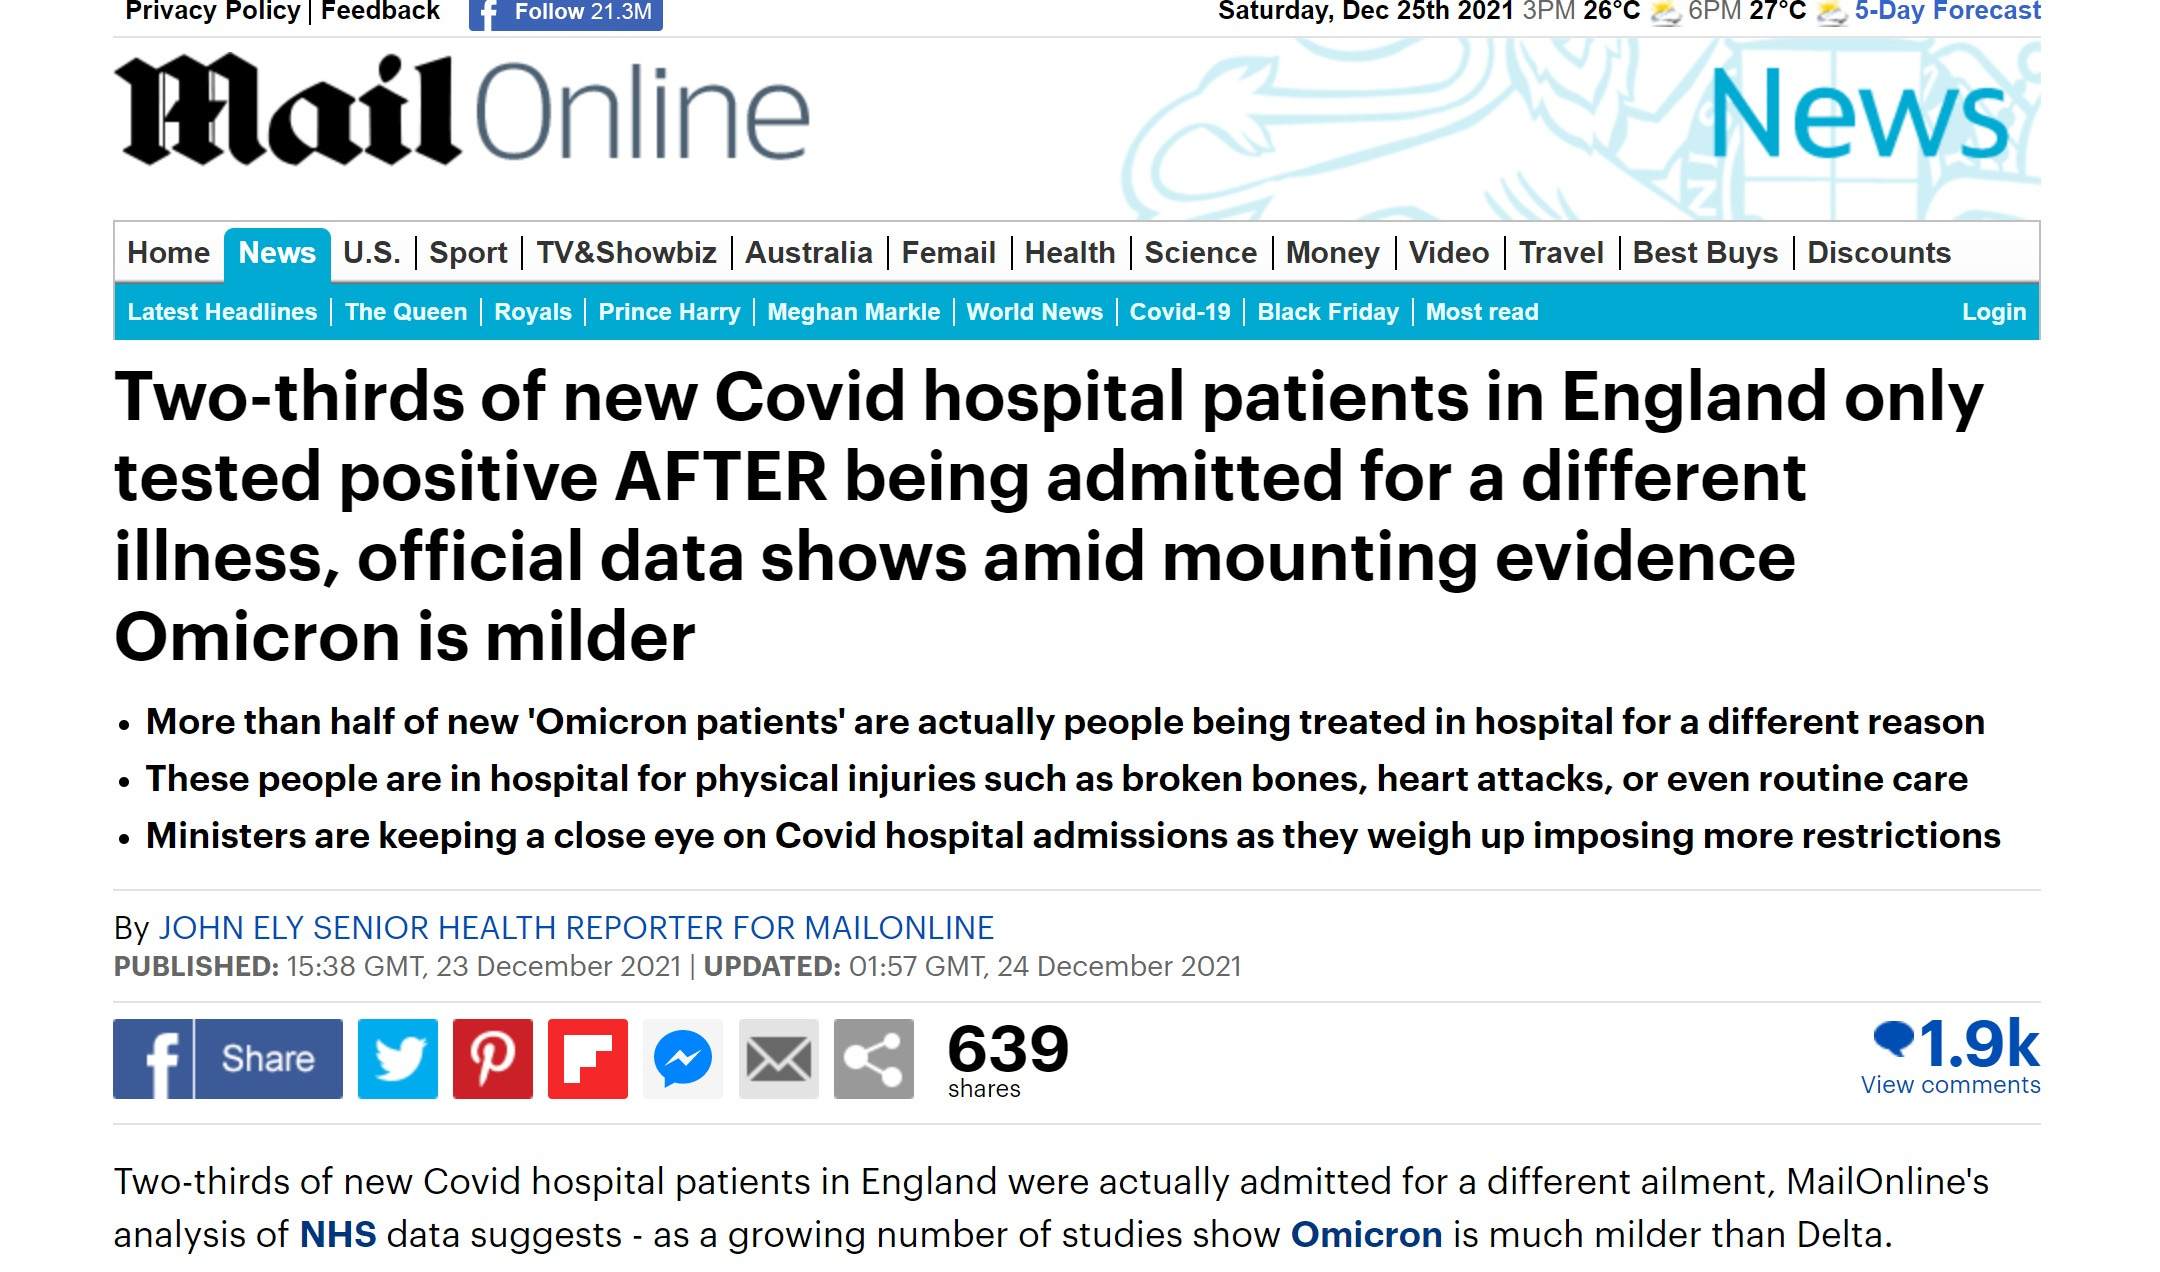
“Two-thirds of new Covid hospital patients in England were actually admitted for a different ailment, MailOnline’s analysis of NHS data suggests – as a growing number of studies show Omicron is much milder than Delta.
In the two weeks to December 21, hospitals in England recorded 563 new coronavirus inpatients — the majority of which are believed to be Omicron now that the variant is the country’s dominant stain.
But just 197 (35 per cent) were being primarily treated for Covid, with the remaining 366 (65 per cent) only testing positive after being admitted for something else.
Experts told MailOnline it was important to distinguish between admissions primarily for Covid so that rising numbers do not spook ministers into more social restrictions or scare the public from going to hospital.
The rising number of so-called ‘incidental cases’ – people who are only diagnosed with the virus after going to the NHS for a different ailment – is in line with the picture in South Africa.
Studies in the epicentre Gauteng province have shown up to three-quarters of Omicron patients there were not admitted primarily for the virus.”

how, at this stage of affairs and after 2 years of time to learn to get the stats straight is everyone still getting this all so wrong? it outright beggars belief.
how is anyone supposed to make decisions or analyze data when the quality is this low?
if you relentlessly test everyone in sight, symptomatic or no, for covid using overclocked PCR tests at 40+ Ct you’re going to find it everywhere. these tests were never actually suited for purpose and have been locking onto trace virus, dead virus, and all manner of other non-clinical positives.
this is not a sound basis for analysis or behavior.
this has been widely known for ages. and yet it persists unabated.
it has spilled over into every other statistic.
hospitalization has been massively tainted by it as nosocomial spread is rife at the trace level. this issue gets amplified by the payout for finding such “cases” as it allows for more billing on new codes and access to additional insurance and coverage pools. this has turned the hyper-aggressive hunt for cases in hospitals into a huge profit center.
deaths are the same. death with (or within 30 days of) discernable trace virus detection by super sensitive assay is an outlandishly inclusive definition that vastly exceeds actual “death from covid” as a primary or even significant cause.
nothing else is counted this way. ever.
not in all of human history has anything remotely like this taken place.
we’re running more covid tests in a week in the US that we’ve run flu tests in entire decades and more in a season than we’ve run flu tests in the history of the nation.
is it any wonder that with such inclusive definitions, over-amplified detection modalities, and obsessive and malincentivized testing regimes that this all looks so “unprecedented”?
of course it does. we’ve never looked for anything in all of human history the way we’re looking for covid. what other result could one even plausibly expect?
we’ve tested our way into a pit of inescapable dodgy data quicksand.
continuing to treat this “data” as though it is clinically or societally meaningful has become a far greater problem than the disease itself.
the cure, of course, is simple:
stop this OCD level testing strategy.
- stop testing the asymptomatic altogether
- dial down the amplification on PCR to 30Ct at a max and probably something more like 26
- stop obsessively testing healthy children
- stop encouraging people to test themselves over and over and to demand the same from their friends and family
sending out rapid tests to everyone is not good public health policy. it’s epidemiological derangement.
it’s cosplay medicine that perpetuates panic through performative ritual and obeisance. it serves no useful end save digging this hole deeper.
it will not end, assuage, or mitigate spread or the pandemic. it will only lead to more misguided perception and response.
this is not normal. it’s not science. it’s not even sane.
in another big win for irony (who, let’s face it has been having a banner year) the relentless fear and overtesting is actually becoming a problem for hospitals.
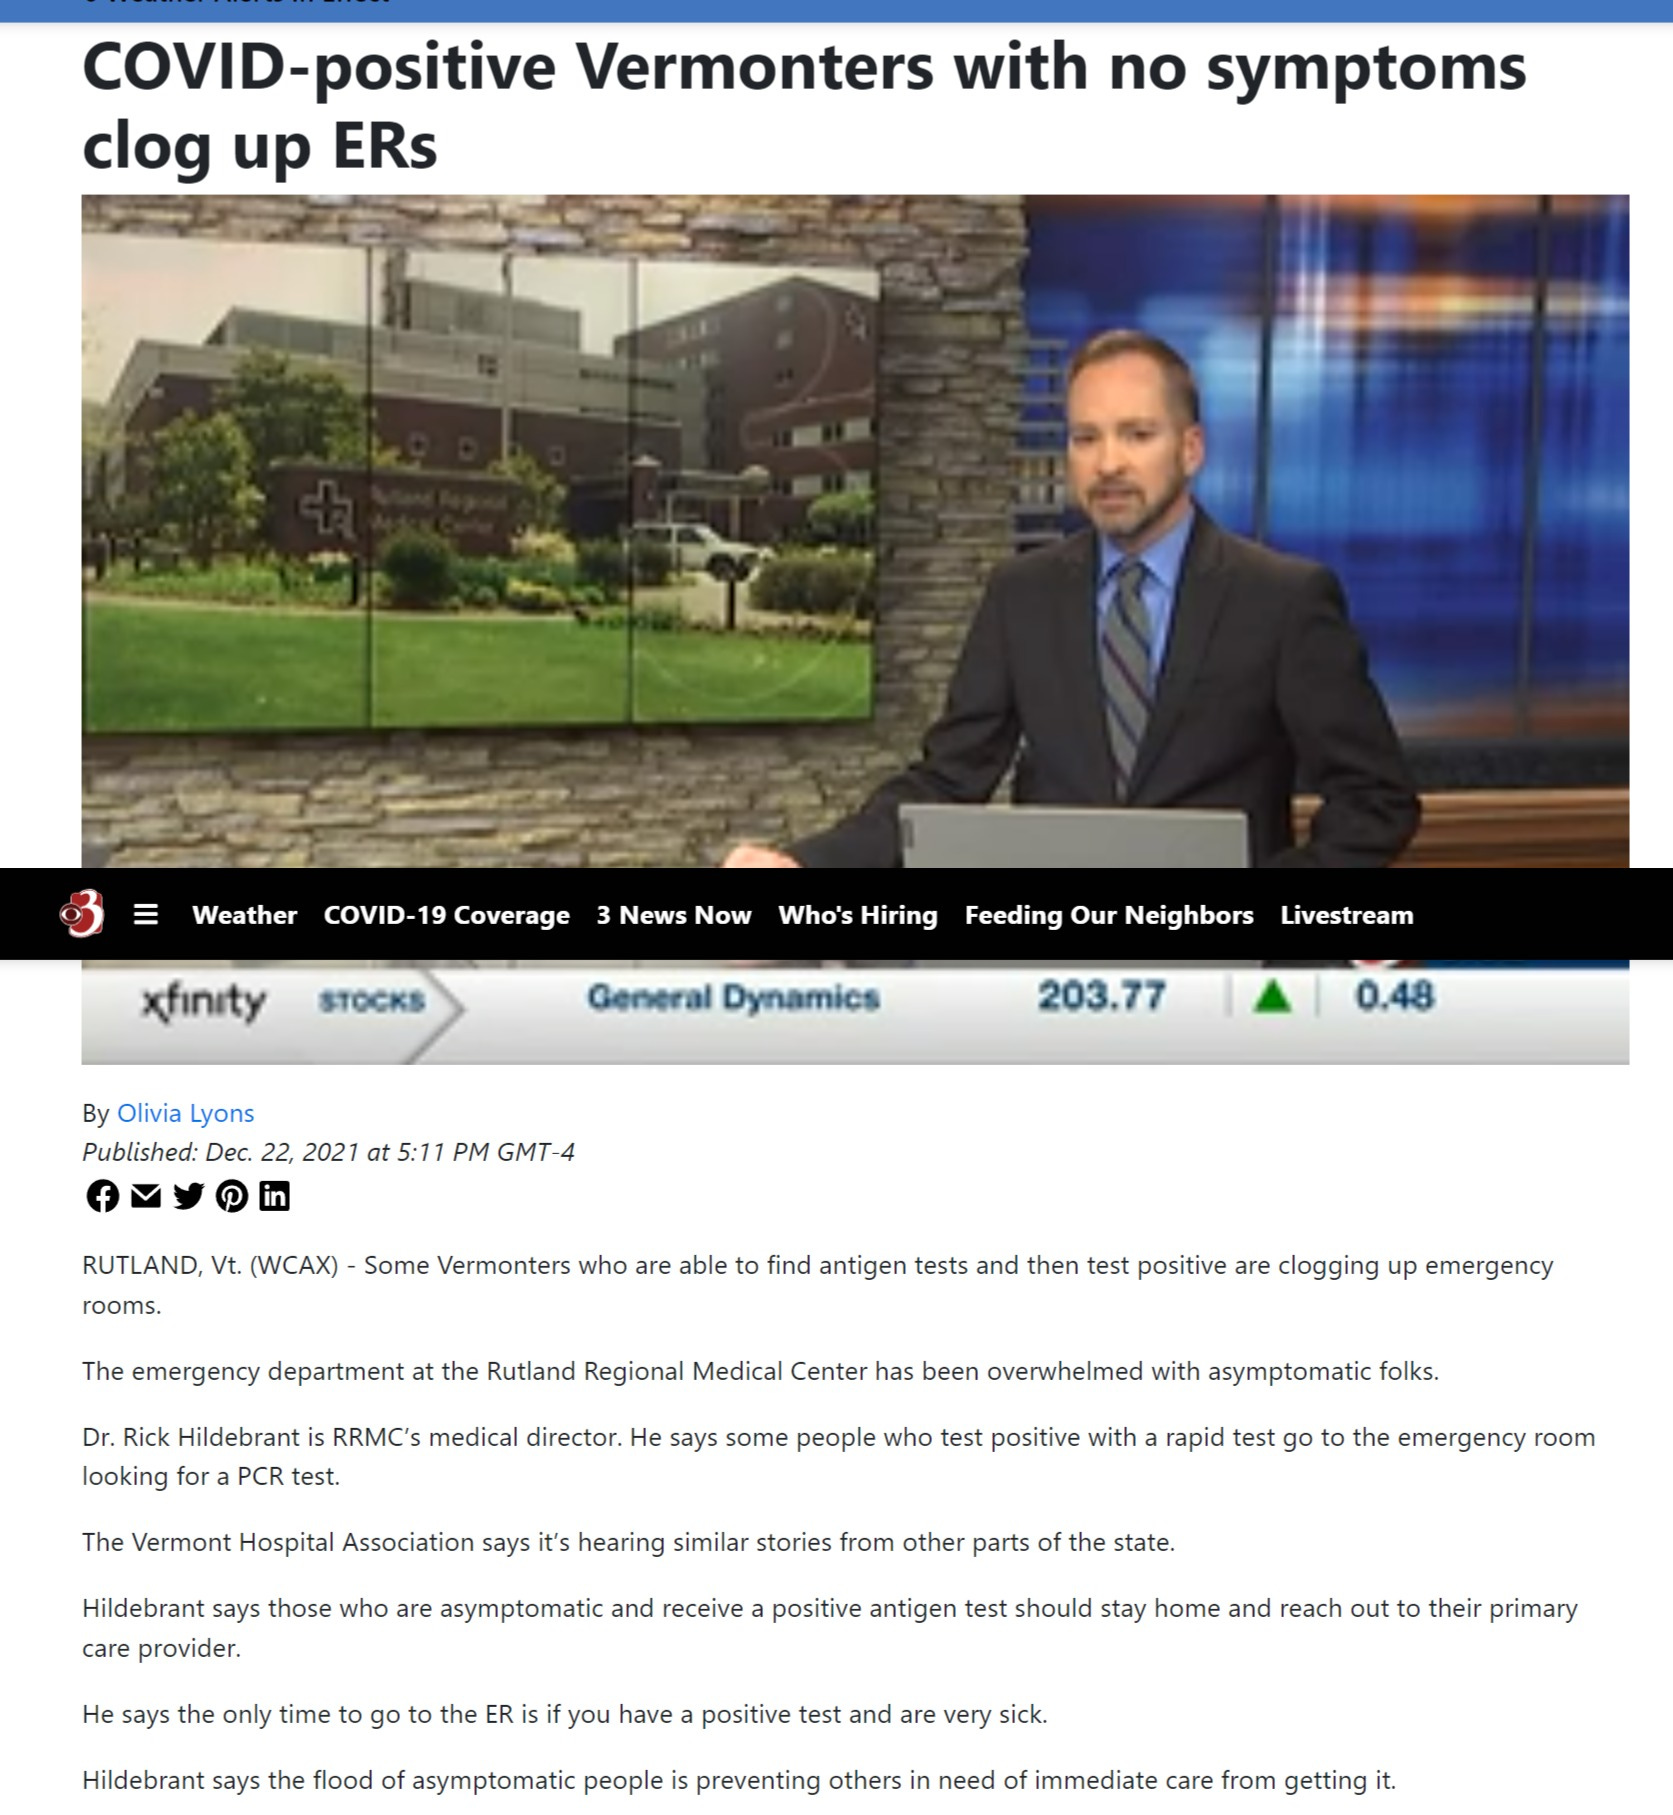
the testdemic has become the problem and is combining with a profound lack of perspective to generate astonishing harm.
“a virus so dangerous that you need to test for it to tell it apart from the common cold” is a laughable pretext for hijacking half the planet.
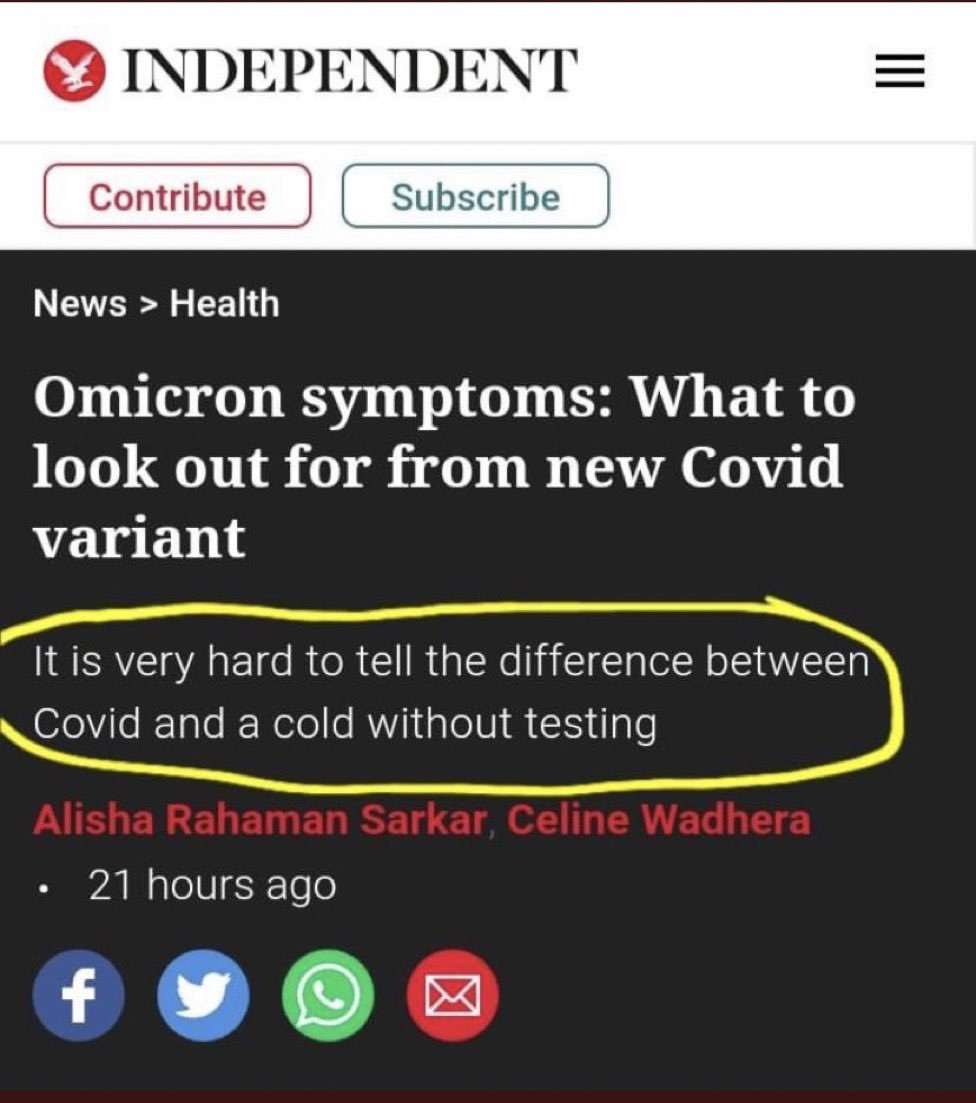
it’s clear these folks cannot hear themselves anymore.
public health has turned into some sort of golem that cannot be turned off and will mindlessly keep digging a trench until the heat death of the universe unless someone steps in and disables it.
so stop it. stop getting tested.
when you play stupid games, you win stupid prizes and this is a very, very stupid game we’re all taking part in…
The Beginning of the End? The virus part of the pandemic will probably soon be over.
eugyppius | December 26, 2021
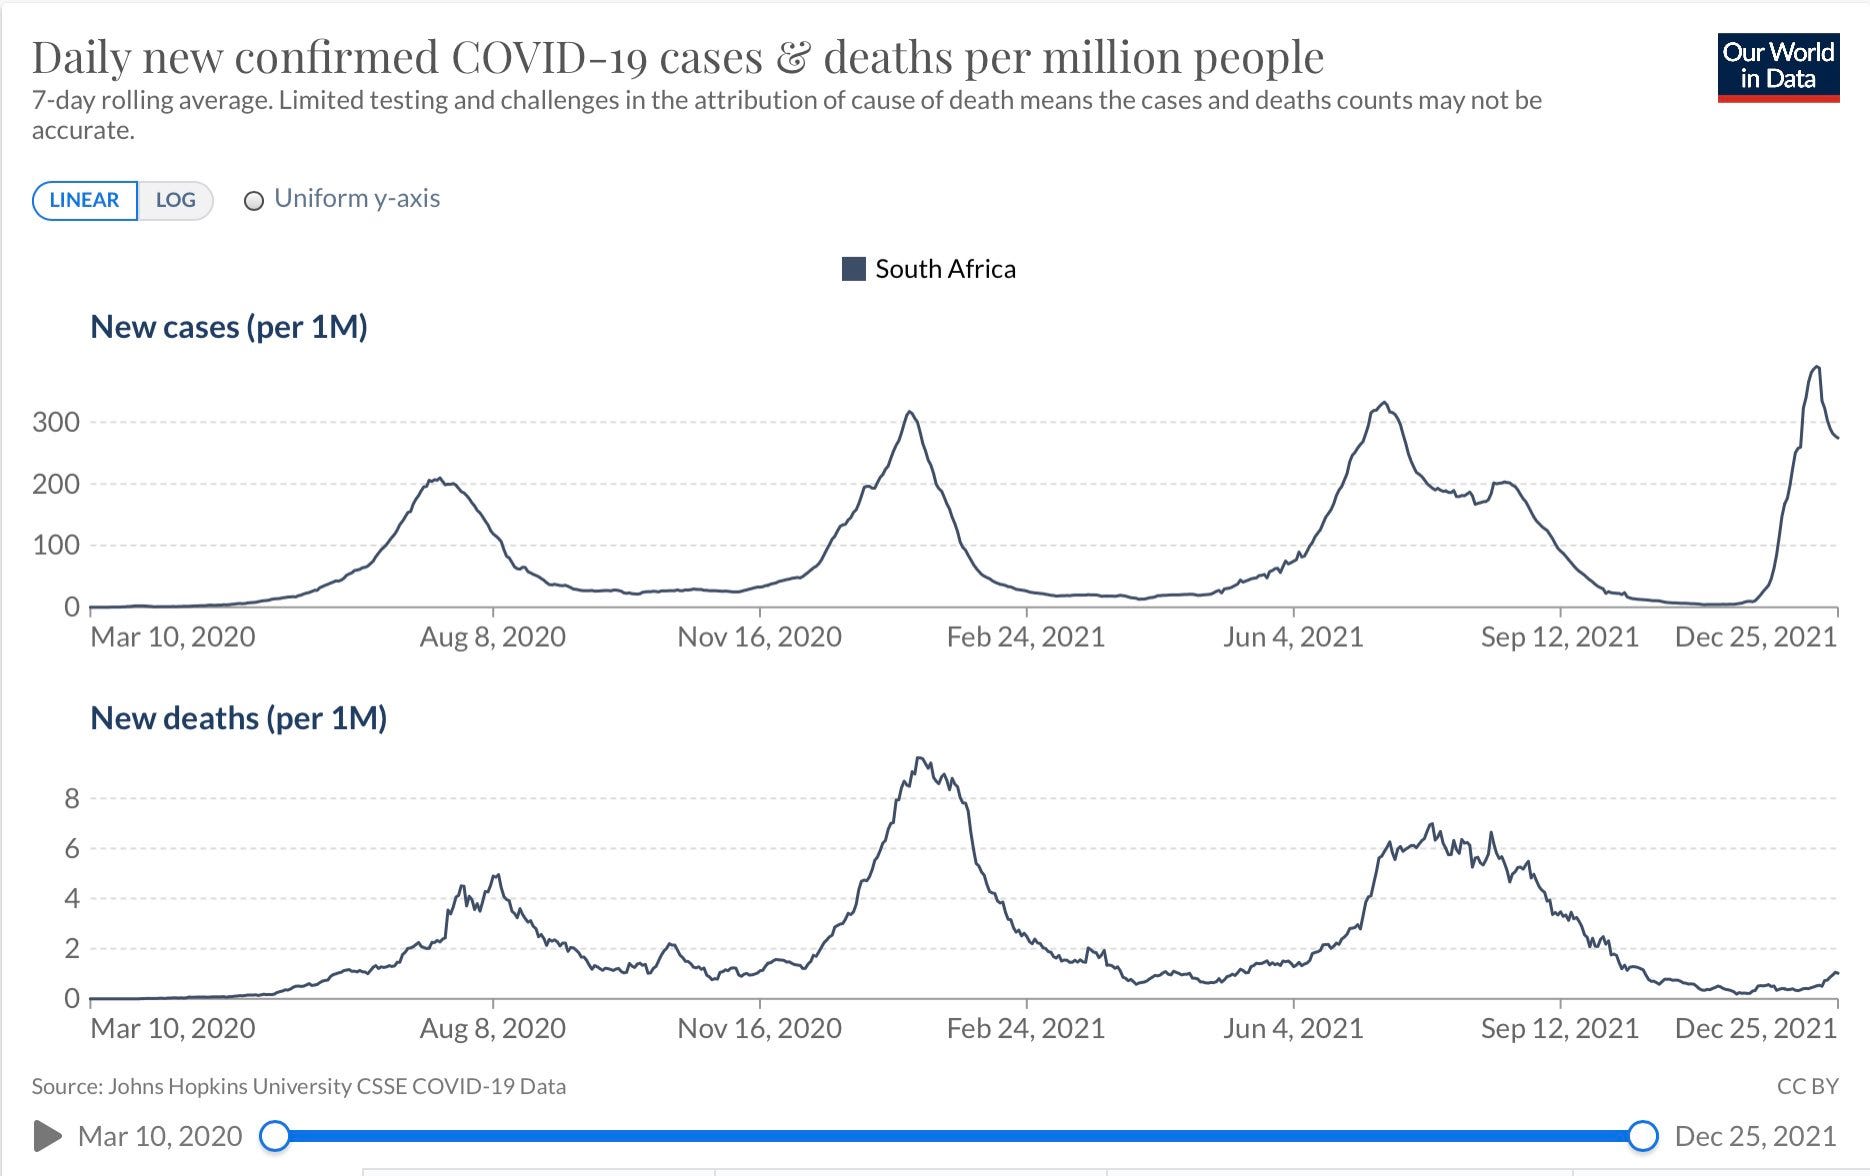
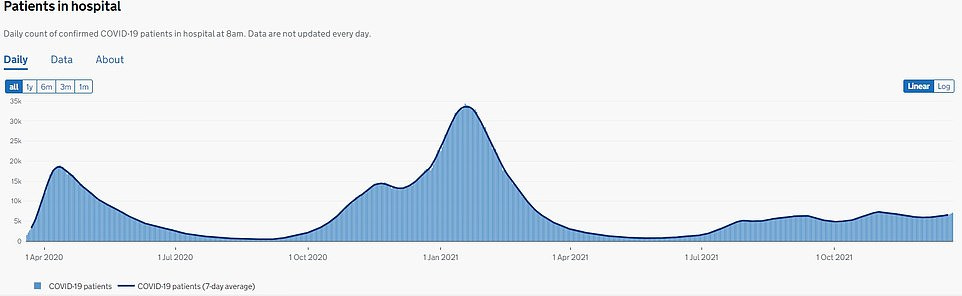
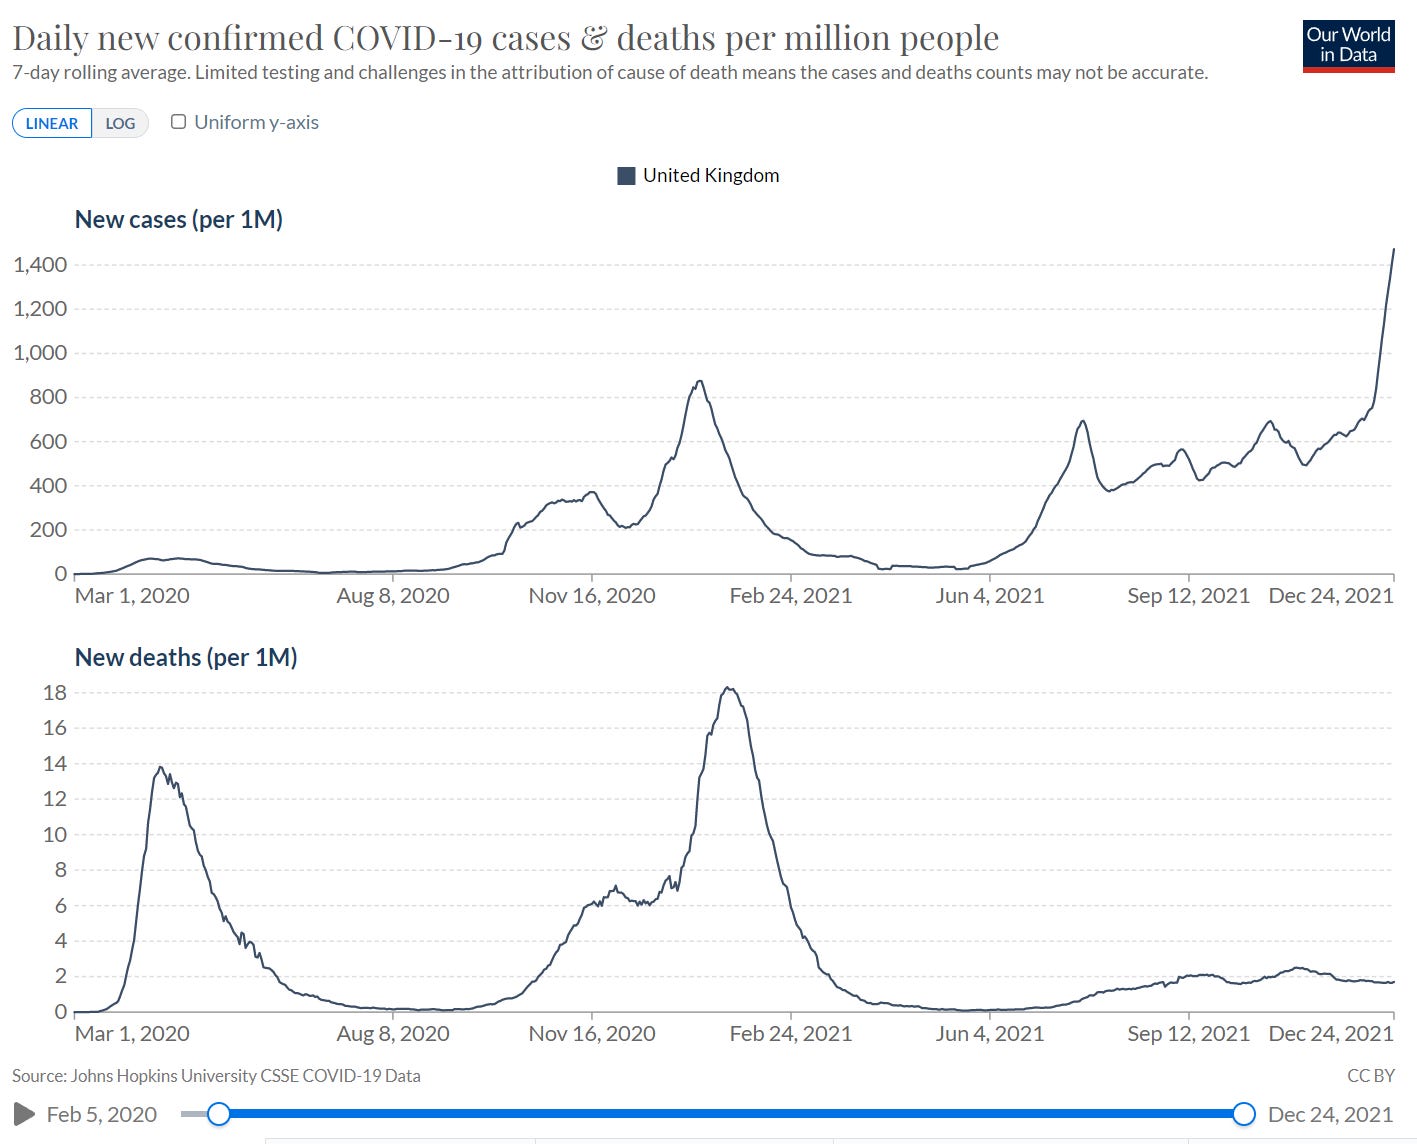
Early reports that Omicron is substantially milder than other SARS-2 strains are every day confirmed by new data. A month into the unprecedented South African case spike, driven entirely by Omicron, Corona deaths remain low. It’s earlier days in the United Kingdom, where Omicron is only just over half of cases. So far, though, it is the same story there:
In the coming months, Omicron will outcompete all other lineages everywhere in the world. At that point, Corona will have completed its transformation into a mild coronavirus that nobody should care about, in the same way that nobody cares about other common human-infecting coronaviruses like hCoV-OC43. Unforeseen developments are always possible; Omicron might in time acquire greater pathogenicity. Particularly if we insist on vaccinating widely, we might drive its evolution in new and potentially dangerous directions. Those are, however, mere possibilities. Right now, everything tells us that the virus part of the pandemic will soon be over.
The major question, is how the rest of the Corona Circus will respond. Some thoughts on that:
In the short term, rising cases will probably fuel demand for more vaccinations. This is the blunt, stupid way that our public health experts respond to infections now, but it is not a game that will go well for the vaccinators. The vaccines will fail even more profoundly in stopping Omicron transmission, and there will be far fewer severe outcomes for them to prevent. I don’t know how long the crackpot vaccination regime can survive overt absurdities like this.
Omicron will probably also unwind the broader containment regime. South Africa has already abandoned their most intrusive tracing, quarantine and isolation policies, declaring a shift towards mitigation (which is what they should have done in the first place). Trying to defeat a minimally symptomatic highly contagious virus with the comically inadequate tools of the contact tracer is simply too ridiculous.

In the longer term, things look much more uncertain. It is hard to shake the feeling that Corona has swept away the last vestiges of liberal democracy in Europe, and perhaps in the whole world. I don’t think these political systems have been very good for the West, but our new theocratic regimes steered by the Corona astrologers have been vastly worse. As soon as the hysteria boils off, many of these villains will begin trying to get the panic machine up and running again. The alternative is a future where nobody much cares what they have to think, where they’re no longer able to interfere in millions of lives, and – perhaps most crucially – where a lot of politicians, journalists, and ordinary people begin to realise what utter failures they and their policies have been. There are failures that lose you your job, there are failures that make you a public disgrace, and then there are their failures, the kind that lead to arrest, indictment, imprisonment, and worse.
WHO approves Novavax and COVAXIN
By Steve Kirsch | December 26, 2021
ICYMI: On December 17, the WHO has granted the Novavax vaccine Emergency Use Approval.
The Novavax vaccine was granted emergency use authorization in November in Indonesia, the first country to do so, and was soon followed by the Philippines. The company has also filed with the U.K. and the European Medicines Agency, with plans to apply to the U.S. Food and Drug Administration before the end of this year.
This is good news because this vaccine is a “traditional” vaccine that does not transfect your existing cells, so it “should” have a much better safety profile than any of the three vaccines now available in the US for two major reasons:
- No transfection. All of the existing vaccines basically invade your cells and tell them to express a spike protein; your immune system may then start attacking your own organs and kill you as explained here. This doesn’t happen with Novavax because you are injected with the antigen.
- A controlled amount of antigen. The other major safety benefit is that a controlled amount of antigen is injected. With the mRNA vaccines, the amount of antigen that is ultimately expressed is a complete crap shoot.
Does this mean that Novavax is “safe.” No, it just means it has the potential to be safer assuming they didn’t screw up anything else. And even if they got everything right, simply injecting particles with the spike protein could be dangerous. In short, it’s possible that there may not be a safe vaccine for this virus.
Certainly Dr. Richard Fleming doesn’t think the Novavax vaccine is safe. One of my followers wrote: “it’s viral like particles (spikes) adhered to plastic inner core, mixed with proprietary saponin adjuvant called Matrix M1.”
Are you feeling lucky?
However, I seriously doubt the FDA will approve it for use in the US since it would take away market share from the other manufacturers
The FDA doesn’t approve things based on science or safety anymore. Those days are gone.
If this vaccine were approved in the US, everyone in the US would want it and avoid the other three existing vaccines like the plague. Their market share would drop to zero. So it isn’t going to be available here. The FDA will make up a reason it isn’t safe. So it will not be accepted in the US (e.g., for satisfying the unethical vaccine mandates) even if it works just as well as the other vaccines. Mandates are not about safety; they are about forcing compliance with what the government wants you to do.
The good news is that other parts of the world will have a safer alternative which is better than what they have now. So in that sense, this is “good news.”
COVAXIN approved on November 3, 2021
COVAXIN is another traditional vaccine that was approved by the WHO on November 3, 2021. Many people believe it is a safer option than any of the alternatives.
The vaccine is formulated from an inactivated SARS-CoV-2 antigen.
What I would do today: avoid all of them
If I were forced to make a choice of vaccine today, and COVAXIN and Novavax were among the options, I would definitely look at the current evidence and make a choice.
However, if I weren’t forced to choose a COVID vaccine now, I would still refuse to be vaccinated because COVID isn’t deadly or dangerous if you know how to recognize and treat it.
Only after the safety profile is well established in large populations, would I even consider it. I’ve learned my lesson never to trust the regulatory agencies and drug companies again.
“In VAERS we trust.”
What we are doing to college kids is total madness
By Vinay Prasad | December 24, 2021
This is a post about the absolutely insane, crushing restrictions being imposed on young, healthy vaccinated (often booster and often naturally immune) people by institutions of knowledge. In order to prove my thesis that these policies are misguided, let me start with some basics.
When it comes to COVID19, there are only 3 things any of us can do:
- We can lower the risk of bad outcomes when we encounter the virus.
- We can delay the time to meet the virus
- We can engage in theater which does not delay the time to meet the virus
What goes in these buckets?
Category 1 (risk reduction) is easy. You can’t modify your age, a huge risk favor, but you can modify your vaccination status, and you can modify your weight and general health.
Category 2 (delay time to virus) is harder. We don’t have many well done studies, but theoretically if you sealed yourself in a bunker and ate canned food, you would do this. Wearing a snug n95 might also delay the time to meeting the virus. The challenge with these interventions is they are not sustainable by most people, and may lead to fatigue or backsliding, and thus the effect is transient.
Delaying serves 2 purposes:
- For the individual, it makes sense if, by delaying, you can do something for category 1 that you cannot do today. If you are waiting for your vaccine, for instance, by all means delay.
- For the community it makes sense, if, by some delaying, the pandemic trajectory is bent and hospitals are less likely to be overwhelmed.
Delaying also has a downside. It may hurt your mental health, particularly when you do it effectively. If you need evidence of this damage: please see twitter.
Category 3 (useless, virtue signaling theater) is the most common. Wearing your mask when you enter a restaurant and walk to your table, but not when you sit there for 2 hours laughing and drinking is one example. The fact this policy exists reflects serious impairment in thinking & total failure of policy makers.
Making a 2-4 year old wear a cloth mask in day care (which the American Academy of Pediatrics recommends against the advice of the World Health Organization), but, of course, kids take the cloth mask off to nap next to each other for 4 hours in the same room! Theater.
Closing beaches and other outdoor activities. Wearing a mask outside. The list goes on and on, and most things we did fit in this category. On a side note: Here we review all data on masking.
Enter young, healthy college kids.
The vast majority are either double vaxxed or have natural immunity or both, and some are also boosted. They are young (lucky them!), and the majority are healthy. What more can such students do for Category 1? Nothing.
What about category 2? It appears that many universities are making college kids wear masks, restricting their movement, banning gatherings etc. Here is just one example of how extreme they are:
These severe restrictions might actually delay the time till college kids meet the virus! But it does so with a huge disruption to their lives. All the wonderful things of being young require being very close to other people. Many simply cannot occur with a mask on.
Will these restrictions benefit the college kids? Absolutely not. When they eventually meet the virus— and they will— on vacation or next semester— they will just be a little older, but have similar great chances of doing well.
Will the restrictions benefit society? Doubtful. After all, everyone not on a college campus is not following any of these ridiculous rules, and the pandemic trajectory will be dictated by those (aka 99.9%) of places.
It will likely not even protect the faculty and staff on campus, who will largely face risks when they leave work and go home and on vacation, and again, if these folks have already optimized Category 1, delay makes little sense.
Will it harm the college kids? Absolutely, it will. Their mental health will surely suffer from this isolation. It has already. I will say again: all of the joys of youth require being close to other people.
What is the net balance? The net balance is these policies are catastrophically detrimental to them. Moreover, there is no countervailing benefit to staff or society to justify the huge imposition. It is morally and scientifically bankrupt.
Truly, I can’t even understand how anyone thinks these policies are justified. I am also surprised college students have accepted them with scant protest. I can only surmise that many have been mislead into thinking this sacrifice serves a broader interest (i.e. believe they are being altruistic), or that the incentives on their lives and career for conformity are so great they are afraid to speak up.
I suspect the strong link between restrictions and political party may also affect them. After all, the youth most strongly leans left, and thus adheres to the identity badges of the left (but in my case, sadly, I spent too many years studying & publishing on scientific evidence to turn my brain off).
In short, draconian restrictions on vaccinated young people or those with natural immunity living in tiny pockets of college campus makes no sense, and is a policy that contributes to a harm in societal well-being. The policy is unethical and illogical.
To young people: I am personally sorry that those of us who recognized the futility and harm of these policies could not have done more to shield you from the anxieties and risk aversion of the irrational.
Paxlovid: What we should know about Pfizer’s new COVID treatment medicine
By Joel S Hirschhorn | December 24, 2021
The pro-drug industry mainstream media are insanely positive over the newly FDA approved Pfizer antiviral COVID treatment pills.
The drug, Paxlovid, received an emergency use authorization by FDA for use in patients 12 years old and up who have tested positive for COVID-19 and are at high risk.
Now is the time to speak calmly and accurately about Paxlovid. First, everyone should appreciate that there was very little testing of the short- and long-term safety of this product, exactly what happened with COVID vaccines. Really good testing of a new drug should take many months or even years.
All you get is positive news for this new drug – actually a combination of drugs.
Here are brief summary statements about this new product:
It was approved by the FDA without any external meetings, serious reviews of test data or opportunity for public input. Pretty much all the regulatory work was done behind closed doors. Terrific for Pfizer. Bad for the public.
Of importance, note that in the trials only 21% of people had a comorbidity, while in reality 94% of COVID deaths have at least one comorbidity, and the average number of underlying medical conditions is four.
As to antiviral science, protease enzymes must be present for the virus to successfully infect by completing the cycle before taking the cell over. Paxlovid or any drug classified as a ‘Protease Inhibitor’ will inhibit or decrease the protease enzyme interfering with the virus. Paxlovid blocks the 3CLPro protease from chopping up the long protein into pieces. The virus can’t separate out which pieces to cut out and assemble. It can’t make copies of itself. The covid infection quickly stops
Contrary to what the government says, ivermectin is the most successful and proven protease inhibitor in use worldwide. Just as with Paxlovid, ivermectin decreases the protease enzyme but… there are benefits of ivermectin in covid treatment that are not present in Paxlovid. Additional actions of ivermectin include anti-coagulant action and anti-inflammatory actions, both observed in covid infections. And IVM has been safely used for decades and there have been many medical studies as well as clinical results showing its antiviral and anti-inflammatory effectiveness.
Paxlovid requires combination with an HIV/AIDS drug, Ritonavir, preventing the breakdown of the Paxlovid so it may inhibit or decrease the enzyme interrupting the viral life cycle. Ritonavir acts as a booster for Paxlovid, keeping it active inside a person’s body. Ritonavir also has its own black box warning and side effects include life-threatening liver, pancreas and heart issues. Does the public really want to take an HIV/AIDS drug?
A course of the treatment is 20 Paxlovid pills and 10 ritonavir pills taken over five days. Taking 6 pills daily can pose challenges for many elderly people in particular.
According to Pfizer’s press release, for people with proven COVID infection, Paxlovid reduces hospitalization/death by 89% when taken within three days of symptom onset. So in the treatment group there was 5 of 697 hospitalized with no deaths compared to 44/682 hospitalized with 9 subsequent deaths.
Also reported was an approximate 10-fold decrease in viral load at day 5, relative to placebo, indicating robust activity against SARS-CoV-2 and representing (supposedly) the strongest viral load reduction reported to date for a COVID-19 oral antiviral agent.
How interesting it would have been to test the Pfizer drug against an ivermectin protocol.
For example, how does the Pfizer drug compare with the Dr. George Fareed and Dr. Brian Tyson protocol? Well, Fareed and Tyson had many more patients (about 7,000) taking the drug combo and yet they had fewer hospitalizations (4) and the same number of deaths (0). So, you’re way better off with the Fareed and Tyson protocol. And the safety protocol of IVM after billions of uses globally is far better proven than for the Pfizer product.
For a good discussion on how IVM compares to Paxlovid see this article. Especially on scientific evidence of ivermectin’s ability to block 3CL protease.
In terms of safety, the most common side effects reported during treatment and up to 34 days after the last dose of Paxlovid were dysgeusia (taste disturbance), diarrhea and vomiting. But what more serious side effects may turn up months or years later?
Paxlovid must not be used with certain other medicines [but it has not been said exactly which ones], either because due to its action it may lead to harmful increases in their blood levels, or because conversely some medicines [which ones?] may reduce the activity of Paxlovid itself. The list of medicines that must not be used with Paxlovid is included in the proposed conditions for use [not yet fully disclosed]. Paxlovid must also not be used in patients with severely reduced kidney or liver function.
Paxlovid is not recommended during pregnancy and in people who can become pregnant and who are not using contraception. Breastfeeding should be interrupted during treatment. These recommendations are because laboratory studies in animals suggest that high doses of Paxlovid may impact the growth of the fetus.
As to availability, Pfizer CEO Bourla recently said the company can manufacture 80 million courses in 2022, with 30 million available in the first half of the year. That is not enough to serve many millions of Americans coming down with symptoms and a positive test result.
This too was said, tens of thousands of the pills will ship in the US before the end of 2021 and hundreds of thousands more are expected at the beginning of 2022, a Pfizer spokesperson told the Wall Street Journal. The US government is paying Pfizer $5.3 billion for 10 million treatment courses that will be delivered by the end of next year, according to the paper. Will medical insurance cover $530 per course?
Always follow the money. A month ago, SVB Leerink analyst Geoffrey Porges projected the drug will generate $24.2 billion in 2022 sales. Together with the company’s megablockbuster COVID-19 vaccine, Pfizer could be looking at $50 billion in peak pandemic vaccine and drug sales, Cantor Fitzgerald analyst Louise Chen wrote earlier this month. No surprise that some top Pfizer executives have become billionaires.
Israeli authorities remove original name of neighborhood in occupied Haifa
Quds News Network | December 25, 2021
Occupied Haifa – The Israeli municipality of the 1948-occupied city of Haifa has removed the original Palestinian name of Wadi Al Jimal neighborhood and refused to add it to signs and official documents, replacing it with the Hebrew name ‘Ein Hayam’.
The Israeli move sparked outrage among residents of the neighborhood, who are all native Palestinians.
Wadi Al Jimal is located in the southwest of Mount Carmel in occupied Haifa. It was constructed in the second half of the 19th century by native Palestinians.
Over 3000 Palestinians live in the neighborhood, which was a main station for travelers from Syria and Lebanon to Egypt before the city was occupied by zionists in 1951.
Israeli right-wingers have been pushing towards removing the neighborhood’s name since 2016.
‘Israel’ changed the names of most of the cities and villages that it occupied, however, Palestinians could keep the names of many places.
COVID Jabs: Ineffective, Oppressive and Dangerous
By Iain Davis | OffGuardian | December 23, 2021
There is no moral, legal or logical argument for mandatory vaccination. The only logical argument, from a public health perspective, would be either to reduce the spread of infection or reduce the impact on health services via some other mechanism.
We will explore the evidence which shows that the COVID-19 supposed “vaccines” are incapable of achieving either.
That didn’t stop the UK parliament voting to allow the government to mandate vaccination for NHS staff. In doing so, they laid the path clear for a wider, national mandate.
Prior to the vote, the British Medical Journal published the protestation of concerned medical professionals who highlighted that there is insufficient evidence to support a mandate.
UK MPs apparently decided that the doctors and nurses didn’t know what they were talking about and were not interested in the scientific evidence they cited. While this illustrates that decision making is not led by science, perhaps this is not the primary concern.
Whatever the political or popular opinion may be, to insist that an individual must submit to injection against their will is to deny them their inalienable right of bodily integrity.
This right was described by Professor David Feldman in Civil Liberties and Human Rights In England and Wales:
A right to be free from physical interference. [This] covers negative liberties: freedom from physical assaults, torture, medical or other experimentation, immunization and compelled eugenic or social sterilization, and cruel or degrading treatment or punishment. It also encompasses some positive duties on the state to protect people against inference by others.”
Both the European Convention on Human Rights (Article 3) and the Universal Declaration of Human Rights (Articles 1 & 3) allegedly guarantee the integrity of the person.
However, these are “Human Rights” written on pieces of paper by politicians and lawyers. As such, they can be overruled by governments and other politicians and lawyers. Human Rights are not rights, they are government permits and permits can be rescinded.
More importantly, in the UK, there is a clear legal precedent for the concept of bodily integrity. In Montgomery vs Lanarkshire Health Board the Supreme Court ruled:
An adult person of sound mind is entitled to decide which, if any, of the available forms of treatment to undergo, and her consent must be obtained before treatment interfering with her bodily integrity is undertaken.”
If society decrees that the population no longer has a right to bodily integrity then the people become the slaves of that society. A society that advocates mandatory vaccinations equally advocates slavery. Those who advocate mandatory vaccination support slavery in principle. None of the justifications they offer negate this fact.
The legal definition of ownership is the “exclusive legal right to possession.” A vaccination mandate decrees that the individual no longer has legal possession of their own body. It removes the individual’s legal right to ownership of their physical being and hands it over to the state. This constitutes slavery.
Slavery is defined as:
The condition of being legally owned by someone else and forced to work for or obey them”
There are those who suggest that the “common good” warrants slavery. They state, based upon assumption and ignorance, that when a person refuses COVID-19 vaccination they are putting others at risk and behaving in a way that jeopardises the common good.
They maintain that society should have the right to violate the bodily integrity of its slaves.
As pointed out by many, a mandate differs from law. However, a government mandate is something the state uses to claim the non-existent right to force people to obey. Individuals can be punished–fined or even imprisoned–for failing to abide with a state mandate. The right to bodily integrity is denied by mandate and all citizens are made slaves by virtue of it.
Some anti-rationalists have argued that a mandate does not constitute “force.” This is a ridiculous contention.
Threatening to fine people is coercion and warning of potential imprisonment is the threat of violence. This is the literal definition of the use of force:
Coercion or compulsion, especially with the use or threat of violence.”
Where violence is defined as:
Extremely forceful actions that are intended to hurt people or are likely to cause damage”
Those who believe in the concept of the common good, debating the point at which it overrides individual sovereignty, accept that some group they choose to empower has the right to force others to obey.
Regardless of whatever rationale they claim, by ultimately insisting that no citizen has the right to bodily integrity, they promote slavery, including their own.
Some people are a bit squeamish about admitting their support for slavery and prefer to pretend that forcing compliance through other means is not slavery.
The head of Ryan Air, Michael O’Leary, apparently thinks that denying people access to society, employment, food and medical treatment is not a “mandate” and therefore forcing them to take the vaccine through this mechanism doesn’t amount to slavery.
O’Leary’s suggestion is that those who decline the vaccine should be punished for their disobedience. He thinks that threatening people with poverty, starvation and a shorter life expectancy is perfectly acceptable in order to force them do as he wishes. He believes that, if this isn’t officially mandated, doing so will somehow protect their rights:
[A mandate] is an infringement of your civil liberties. But you simply make life so difficult. Or [make it that] there are lots of things that you can’t do unless you get vaccinated”
Proponents of the “common good,” who insist that getting vaccinated is the “right thing” and therefore not complying is wrong, cannot both proclaim society’s alleged authority to ignore the inalienable right of bodily integrity and simultaneously pretend they oppose slavery.
If, as a society, we allow the government to mandate or if, like O’Leary, we choose to enforce vaccination by other means, then we have collectively consented to live in a slave state where we are all slaves.
If we go down this path we condemn future generations to slavery. Yet somehow those who decline the offer of slavery, who oppose it in principle, are considered to be selfish by wider society.
The supporters of slavery justify this to themselves because they believe the extremely limited public health impact of a low mortality respiratory disease is more important than human freedom.
This opinion is informed by the flawed and irrelevant assumption that the jabs protect others. The efficacy and safety of the vaccines is immaterial. To deny an individual’s right to bodily integrity is slavery. It does not matter what the claimed justification is.
There are already many slaves being traded, exploited and abused in the UK. While the experience of those who suffer the daily hell of modern slavery is in no way comparable to merely being forcibly injected with a drug once or twice a year, the principle of slavery is the same. It seems odd that the suggested “common good” doesn’t demand freedom for those currently living as slaves. Perhaps society no longer cares.
Putting aside the lack of moral and legal legitimacy, there are other reasons why we should reject any notion of a vaccine mandate. Primarily that the so-called vaccines don’t work and are dangerous.
THE JAB BASICS
The word “infection” is defined as:
“The state produced by the establishment of one or more pathogenic agents (such as a bacteria, protozoans, or viruses).”
If you had looked at the medical definition of “vaccine” in 2019 you would have understood a vaccine to be:
A preparation of killed microorganisms, living attenuated organisms, or living fully virulent organisms that is administered to produce or artificially increase immunity to a particular disease”
Where immunity was defined as:
The quality or state of being immune; especially: a condition of being able to resist a particular disease especially through preventing development of a pathogenic microorganism or by counteracting the effects of its products.”
A vaccine was a drug that “especially” reduced infection. It could theoretically stop a pathogenic agent, such as a bacteria, protozoans, or virus from establishing itself in a biological system. Thus reducing the incidents of disease and subsequent transmission of the pathogen.
However, in the wake of the pseudopandemic, that is not what the changed definition of “vaccine” has come to mean today. The only thing an alleged, so-called vaccine is required to demonstrate is immunogenicity:
A preparation that is administered (as by injection) to stimulate the body’s immune response against a specific infectious agent or disease”
Purely by changing the definition, a “vaccine” is now a drug that stimulates an immune response. It says nothing about how effective or safe that immune response is. Inflammation is an immune response and it is potentially lethal.
Absent the ability to protect against infection, most people would consider a drug which only reduces the severity of disease to be a treatment, not a vaccine.
While it is true that language constantly evolves and definitions change all the time, where that change fundamentally redefines the commonly accepted meaning of a word, everyone needs to be aware of the new interpretation. If not, they could accept an implied meaning that no longer exists.
For example, people could easily be fooled into believing a COVID-19 “vaccine” stops infection. To draw a distinction between what most people imagine “vaccine” to mean and what it now means, we will refer to the alleged COVID-19 “vaccines” as jabs.
THE JABS HAVE NOT COMPLETED & DO NOT NEED TO COMPLETE ANY CLINICAL TRIALS
Unlike every vaccine that preceded them, the jabs have not completed clinical trials prior to being given to more people than any other vaccine in history.
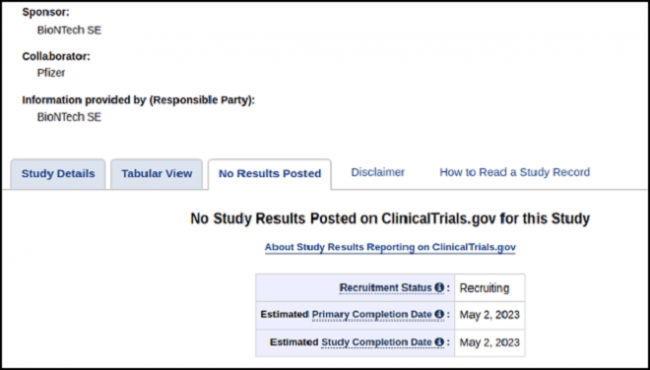
At the time of writing there are no results posted for the NCT04614948 trial of the Pfizer-BioNTech mRNA jab; none for the NCT04516746 Astrazeneca jab; there are no results from Moderna’s NCT04470427 trial nor any from J&J’s NCT04368728 trial of their Jansen jab.
When the UK medicines regulators, the MHRA, said that they “carried out a rigorous scientific assessment of all the available evidence of quality, safety and effectiveness,” prior to allowing the jabs’ Emergency Use Authorisation (EUA,) they did not mean they had studied the results of any clinical trials. They couldn’t, because there aren’t any.
What they meant is that they had received interim reports from the manufacturers and their sponsors (UK Research and Innovation, National Institutes for Health Research (NIHR), Coalition for Epidemic Preparedness Innovations (CEPI), Bill & Melinda Gates Foundation, Lemann Foundation etc.) The MHRA, as other regulators around the world, based their decision to grant the EUAs on these interim reports, not upon the results of any clinical trials.
This enables the mainstream media to report news agency statements which mislead the public:
Massive coronavirus vaccine trials involving tens of thousands of participants have so far surfaced no signs of serious side effects.”
The continual impression given is that the jabs are clinically proven to be safe and effective. In reality, few adverse reactions have been reported in the trials because no trial results have been posted.
The trials were designed to be blind Randomised Control Trials (RCTs.) As they were trialling the first proposed vaccines for a novel disease, the standard RCT approach to determine the safety and efficacy of the jabs was to compare the long term health outcomes of jab recipients to those of a placebo group. These would be “blinded,” meaning that the trial participants were not told if they had been jabbed or received a placebo.
The secondary outcomes for the trials were designed to assess the effects of the vaccines. This including assessment of any adverse drug reactions (ADRs) for up to 2 or more years after the final dose. So far, none of the secondary outcomes have been measured because we are more than a year away from the end of the minimum trial periods.
There is now no chance that these clinical trials will ever reveal any meaningful results. As reported in the British Medical Journal both J&J and Moderna have “unblinded” their trials by giving their jab to their placebo groups. They have abandoned the secondary outcomes, years before the trials are complete. When asked, neither Astrazeneca nor Pfizer-BioNTech denied doing the same.
In any event, it appears their trials were poorly designed and lacked scientific credibility. It is strongly alleged that Pfizer-BioNTech, at least, falsified data, unblinded their study, failed to adequately train staff and were reluctant to follow up on reported adverse events.
When independent researchers used a Freedom of Information request (FoIR) to ask UK regulator, The Medicines and Healthcare products Regulatory Agency (MHRA), why the Pfizer-BioNTech NCT04614948 clinical trial hadn’t assessed the vaccine’s impact upon pregnant women, the MHRA stated:
The above trial was not conducted in the UK, the MHRA did not assess its content and are therefore not in a position to answer specific questions relating to it.”
Not bothering to consider the primary clinical trial doesn’t appear to be a very “rigorous scientific assessment.” Rather, it seems the MHRA are among a group of regulators who unquestioningly accepted whatever the manufacturers claim without genuinely scrutinising anything.
The MHRA have now formally adopted this laissez-faire approach to future jab regulation. Having aligned themselves with the Access Consortium of regulators (Australia, Canada, Singapore and Switzerland), the MHRA are among those who see no reason for any further regulatory scrutiny prior to the approval of new jabs.
The Consortium believe new iterations, responding to allegedly new variants of COVID-19, can effectively be waved through automatically. This is based upon the impossible.
The MHRA assert that their initial EUA reflected their appraisal of the “pivotal clinical trials,” for which there are no posted results. Having authorised the jab roll-outs without any substantiating evidence, the MHRA now claim that, for all tweaked future versions:
Clinical efficacy studies prior to approval are not required. Regulatory Authorities request bridging data on immunogenicity from a sufficient number of individuals”
This speeds up the process of getting jabs straight out of the corporate labs and into the arms of a broadly misinformed public. Whatever tweaks the manufacturers choose to make will just be rubber stamped by the Consortium as long as the pharmaceutical corporations submit the appropriate immunogenicity claims.
The issuance of an EUA is not the same as regulatory approval of a medicine. As explained by the U.S. regulator, the Food and Drug Administration (FDA,) an EUA is a temporary authorisation of an investigational medication:
An EUA for a COVID-19 vaccine may allow for rapid and widespread deployment for administration of the investigational vaccine to millions of individuals”
The FDA also state that an investigational drug, still in trials, is an experimental drug:
An investigational drug can also be called an experimental drug.”
The current COVID-19 jabs are still in trials and are “experimental drugs.” So-called fact checkers have been dispatched to mislead the public into believing this is not the case.
For example Full Fact, the UK based political activists who work with policy makers to market their own business, claimed:
The three Covid vaccines currently approved for use in the UK have already been shown to be safe and effective in clinical trials.”
This was a factually inaccurate statement. In terms of issuing EUAs, all that was known from the phase 3 trials was the interim results.
These reported what little data was available from the first two months of phase 1. This was merely a claim that the jabs were relatively safe for a small cohort of fit and healthy, predominantly younger people. We will shortly discuss why even this assertion is false.
All we can say at this juncture is that there is no perceptible regulation of the jabs. They are effectively unregulated.
The trials have yet to demonstrate that the jabs are either safe or effective. The exclusion criteria for all the trials ruled out trialling the jabs on those most vulnerable to COVID-19. The interim reports from phase 1 only claim efficacy and safety among those least susceptible to apparent COVID-19 risks. Now those trials will never be completed.
The interim trial reports claimed efficacy in terms or relative instead of absolute risk reduction. This enabled the manufacturers to claim a 95%+ reduction in mortality (efficacy.) This was then reported to the public who were swayed by this reporting bias.
The claimed absolute risk reduction (efficacy) was typically less than 1%. Had this been reported to the public the people would have been less enthusiastic and perhaps more sceptical about the jabs, which is why it wasn’t.
The EUAs, on both sides of the Atlantic, also came with immunity from prosecution for the manufacturers. In the UK, the Human Medicines (Coronavirus and Influenza) (Amendment) Regulations 2020 extended the liability protection offered to administering medical practitioners to the pharmaceutical corporations.
Immunity from prosecution is an apparent deal breaker for the drug companies. In early 2021 the managing director of the World Bank, David Malpass, reported that some jab manufacturers would not distribute their jabs to countries that did not fully indemnify them against prosecution:
The immediate problem is indemnification. Pfizer has been hesitant to go into some of the countries because of the liability problems, they don’t have a liability shield. So we work with the countries to try to do that.”
There is no doubt that the jabs are experimental drugs that have not completed any clinical trials. As such the population who have received them are part of a global medical experiment. In partnership with government, that experiment is being conducted by global pharmaceutical corporations which have no liability for any harm they may cause.
This fact is then covered up by the global media corporations and appointed fact checkers, who also work in partnership with government.
Statements from the NHS such as “The COVID-19 vaccines are the best way to protect yourself and others” or “any side effects are usually mild and should not last longer than a week” are not based upon any clinical trial evidence. They are speculative, misleading and potentially dangerous proclamations.
Unless, before being jabbed, recipients were explicitly made aware of these facts they cannot possibly have given informed consent.
In each and every instance, despite the fact free denials of the comically misnamed fact checkers, this constitutes a breech of the Nuremberg Code.
BLAMING THE UNJABBED
Following the comments of the health secretary, Sajid Javid, the MSM dutifully reported that there are around 5M “unvaccinated” people in the UK. This figure appears to be only partially accurate.
According to figures released by the UK Health Security Agency (UKHSA), by mid December 2021, with the booster roll-out well underway, of the approximate 44.6M adults in England, around 38.6M had received at least two doses and were therefore temporarily deemed to be “fully vaccinated.”
This means that currently about 6M adults in England alone are officially “unvaccinated.” England represents approximately 84% of the UK population. Assuming similar vaccine distribution figures for the whole of the UK, this suggests that at least 6.9M adults are officially unvaccinated. This represents nearly than 13% of the adult UK population.
The size of the unvaccinated population is set to grow. The UK government have already said that a booster will be needed for the NHS COVID Pass (certificate) for international travel.
Initially the UK government said that they didn’t intend to extend this to the domestic vaccine passport but they also repeatedly denied that they would introduce vaccine passports.
Subsequent comments from the Health Secretary clarified the government’s intention to continually shift their definition of “fully vaccinated.” To be fully vaccinated the slave must always agree to the next jab.
With the jab sales force insisting that boosters will be needed for years to come, it seems “fully vaccinated” status will last for about 6 month.
The MSM, on behalf of the government who fund them, have propagandised the nation into believing that it is the unvaccinated who are “overwhelming” health services. With headlines like ICU is Full Of The Unvaccinated – My Patience With Them Is Wearing Thin, it is no wonder that the jabbed majority are turning their hate towards the people who don’t want the jabs. It is extremely common to read social media comments such as:
Unvaccinated people are taking beds from other sick people, some of whom become sicker as a result. Not being vaccinated during a pandemic is an act of selfishness hiding behind the facade of individual liberty.”
The “ICU is Full” Guardian article was from an anonymous source. No one was willing to put their name to it. It was primarily an appeal to emotion and offered no evidence to back up any of its claims. This is because the evidence does not support any aspect of the published story. The only apparent reason for the article was to incite hatred.
Real journalists, like Kit Knightly from the OffGuardian, which is censored by the social media platforms, have been willing to put their name to the reporting of the facts.
As he shows, ICUs are not overwhelmed at all. They are quite busy, as usual, but they are certainly not overrun with COVID-19 “cases,” as the Guardian and others have deceptively claimed.
Currently there are 4330 critical care beds in England. On December 14th 2021, 925 were occupied by so-called COVID-19 patients, a COVID-19 ICU bed occupancy rate of 21.4%. There were 775 (17.9%) unoccupied ICU beds with 2657 beds (61.4%) taken by patients who had not tested positive for the selected COVID-19 nucleotide sequences.
In their Week 50 Vaccine Surveillance Report UKHSA state that, for the preceding 4 week period, 2965 alleged COVID-19 adult hospital patients had not received a jab and 4557 had received at least one. Therefore UKHSA claim that the un-jabbed represent 39.4% of total COVID-19 hospital admissions.
For the same 4 week period, UKHSA also reported that 715 of the 3083 total adult deaths, within 28 days of a positive test, were people who were not jabbed. This represents 23.2% of alleged COVID-19 deaths. With 28 deaths attributed to those with an unknown jab status, the remaining 2340 were jabbed. The jabbed represent 76% of all alleged COVID-19 deaths.
Similar data for Wales also belies the false claim that it is the unjabbed who are “overwhelming” health services. In November 2021 12.8% of hospital inpatients were “unvaccinated.” The “vaccinated” accounted for 84.5% of hospital inpatients with 2.7% of unknown jab status.
The anonymous claims reported in the Guardian weren’t even remotely accurate. The tale was a propagandist disinformation. It was “fake news.”
Yet the politicians are desperate to peddle the same lie, with the assistance of their compliant MSM. Once again, the Guardian reported the comments of the Health Secretary as if they were realistic. Speaking about the people who have considered the evidence and have decided not to take the jab, Javid said:
They must really think about the damage they are doing to society. They take up hospital beds that could have been used for someone with maybe a heart problem, or maybe someone who is waiting for elective surgery.”
At no point did the fearless journalists at the Guardian inform the public that what he was saying was total nonsense. Instead, they doubled-down on the lies with added disinformation of their own, claiming that “nine out of 10 of those needing the most care in hospital are unvaccinated.” Yet another example of absolute fake news, intended to deceive the public.
As we will discuss shortly, it is the seeming clamour to “get boosted,” incessantly pushed by the MSM and the politicians, effectively shutting down primary healthcare, that presents a far greater risk to public health. The mendacity of Javid’s disinformation was breathtaking.
The people who are queuing for their jabs aren’t selfish, just misinformed. However, the 13% of adult the population who don’t want one aren’t selfish either.
The MSM and the politicians persistently try to drive a wedge between the jabbed and the unjabbed. They seek to cause divisions based upon disinformation, lies and propaganda.
The reason for this is clear. Just like all tyrannical regimes throughout history, the current UK dictatorship wish to scapegoat a minority in order to avoid wider public attention turning on them. They do this to reduce the chance of the people questioning the tyrants who are enslaving them. It is nothing more complex than divide and rule.
THE JABS DON’T WORK
Speaking in October, the current UK Prime Minister, Boris Johnson, effectively admitted that the jabs are not “vaccines.” They do not function like any vaccines we are familiar with. Apparently, they are much more like a treatment:
Double vaccination provides a lot of protection against serious illness and death but it doesn’t protect you against catching the disease, and it doesn’t protect you against passing it on.”
Johnson’s observation was partially accurate. Recent research from the US found that there was no difference in viral load between the vaccinated and the unvaccinated. These findings appear to be corroborated by a study from Singapore, which strongly advocated the jabs for their claimed ability to reduce mortality, but also noted:
PCR cycle threshold (Ct) values were similar between both vaccinated and unvaccinated groups at diagnosis, but viral loads decreased faster in vaccinated individuals […] viral load indicated by PCR Ct values was similar between vaccinated and unvaccinated patients.”
For the jabs to function as a vaccine, in the traditional sense, the higher the jab rate the lower disease prevalence should be. This is an obvious point, but seemingly one that needs to be stressed as the wider public appear to be largely unaware of this.
There is no statistical correlation between population jab rates, infection rates and disease prevalence. A joint U.S. and Canadian study, which assessed statistical reports from 68 countries and 2947 US counties found:
At the country-level, there appears to be no discernable relationship between percentage of population fully vaccinated and new COVID-19 cases in the last 7 days. In fact, the trend line suggests a marginally positive association such that countries with higher percentage of population fully vaccinated have higher COVID-19 cases per 1 million people.”
Yet, somewhat contrary to their own findings, the researchers still promoted the jabs as part of broader approach to disease mitigation using non pharmaceutical interventions, including wearing face-masks, lockdowns and social distancing. As we will discuss shortly, promoting the official narrative is now a prerequisite for peer review and publication.
Presumably, to stay within the permitted boundaries of the official scientific consensus, the researchers maintained the new definition of “vaccine,” describing a drug incapable of reducing infection rates that acts like a treatment:
Vaccinations offers protection to individuals against severe hospitalization and death.”
The peninsula of Gibraltar, with a population of around 34,000, was delighted to declare that it had achieved a 100% jab rate. Thereafter it suffered a surge in reported cases.
In the Republic of Ireland, the city of Waterford has a 99.7% jab rate and the highest case rate in Ireland.
In Israel, where the definition of “fully vaccinated” means someone received two initial jabs and a booster (3 jabs,) there have been 67 recorded cases of the Omicron variant. Of these 54 (nearly 81%) were fully jabbed. Of the remaining 13 cases we don’t know if any of them were genuinely unjabbed. They could have received one or two jabs and still be categorised as not “fully vaccinated.”
If we look at a recent map of vaccine coverage provided by CNN we can identify some interesting comparisons.
Brazil, with jab coverage of 150 jabs per 100 people, has more than 103,000 COVID cases per million people (CPM). Neighbouring Bolivia, with 77 jabs per 100, has a case rate of just under 47,000 CPM. Paraguay has a slightly higher jab rate of 88 and a slightly higher case rate of 64,000 CPM. Argentina, with the highest jab rate of all, at 220 per 100, also has the highest CPM of all, at just over 117,000.
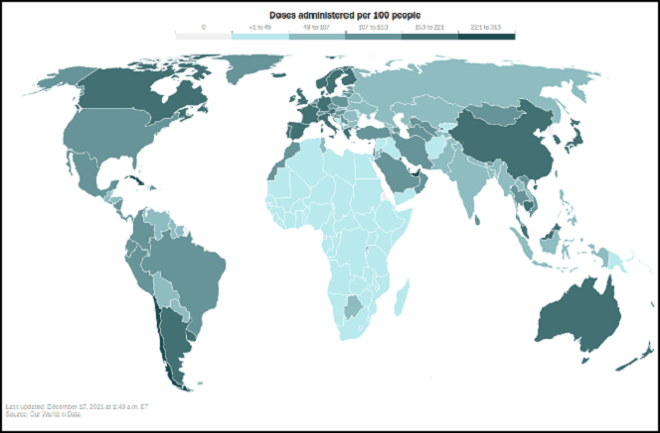
The most striking feature of the CNN map is the very low vaccinations rates in Africa. Nigeria, Tanzania and Zambia, for example, have less than 10 jabs per 100. They are among the countries with the lowest case rates in the world. Zambia has just over 11,000 CPM and Nigeria and Tanzania much less. By contrast Botswana, with a relatively high African vaccination rate of 62 per 100 people, has a CPM of nearly 82,000.
Some scientists are apparently mystified by the low rates of COVID-19 in Africa as a whole. They offer a range of possible explanations. They point towards a younger population or early border closures, some suggest lower urban density or perhaps more outdoor activity to account for the obvious anomaly.
Calling it a “mystery” Prof. Wafaa El-Sadr, global health lead at Columbia University, said:
Africa doesn’t have the vaccines and the resources to fight COVID-19 that they have in Europe and the US, but somehow they seem to be doing better.”
African nations are certainly doing better than the U.S. With approximately 4% of the World’s population and a vaccine rate of 147 per 100 people, the U.S. account for more than 36% of the current 27,586,743 active global cases.
In fact, the list of the top 20 nations with the highest case rates around the world is predominantly composed of the countries with the highest vaccination rates.
Scientists are looking at all the variables to try and figure out what could possibly explain the African mystery. The only factor they aren’t considering is the most obvious one.
Despite most African nations having no first wave, the global scientific and medical authorities are hell-bent on preventing the second with the jabs. Prof. Salim Abdool Karim from the South Africa’s University of KwaZulu-Natal said:
We need to be vaccinating all out to prepare for the next wave.”
Professor Karim was invited to join the World Health Organisation’s (WHO) science council in April 2020. The WHO have made jabbing African populations its next priority.
There are multiple studies which demonstrate that natural immunity derived from infection is considerably better than any imparted by the jabs. A recent Israeli investigation suggests that natural immunity, following infection, is up to 27 times more robust than any conferred by the jabs.
Regardless of scientific debates about antigens, T-cells and immunogenicity etc., which all relate to how the jabs supposedly function, very basic statistical analysis is sufficient to clearly demonstrate that they do not work as vaccines.
The only remaining claim for the jabs efficacy is that they reduce hospitalisation and death. Unfortunately, there is a lot of evidence which casts doubt upon this claim too.

Anthony Fauci (left) & Salim Abdool Karim (right)
If the jabs are incapable of stopping infection and transmission and serve only to reduce natural immunity, there is no possible public health rationale for a jab mandate. An uninfected individual is no more likely to catch COVID-19 from an unjabbed person than they are from a jabbed citizen. According to the official definition of a COVID-19 case, the statistics show that the jabs don’t make any difference whatsoever to the spread of disease.
In his more recent address to the nation, pushing the unregulated booster jabs, Boris Johnson said:
Over the past year we have shown that vaccination is the key to beating Covid and that it works […] It is now clear that two doses of vaccine are simply not enough to give the level of protection we all need […] we must urgently reinforce our wall of vaccine protection to keep our friends and loved ones safe […] As we focus on boosters […] it will mean some other appointments will need to be postponed until the New Year […] If we don’t do this now, the wave of Omicron could be so big that cancellations and disruptions, like the loss of cancer appointments, would be even greater next year”
Johnson’s speech was utterly incoherent. On the one hand the vaccines work but on the other they don’t and a booster is required. To fend off a wave of cases, defined by a test that can’t identify cases, apparently trivial health interventions, like cancer screening appointments, need to be cancelled for the benefit of the nation’s health and the common good.
Shortly following Johnson’s plea to “get boosted now” the UK government clarified that GP surgeries across the land would focus upon jabs and emergency appointments only.
By declaring a “national mission” to jab as many people as possible, primary care has practically been suspended in the UK. This has been done in the winter, in the middle of an alleged respiratory disease pandemic. The Health impact from this will be disastrous.
The British Medical Association has already warned that the reconfiguration of the NHS, first into a COVID-19 only service and now a jab only service, has terrible public health consequences.
Just in the 3 month period following the first lockdown there were up to 1.5M fewer elective admissions to hospital; first time patient attendance, for all conditions, dropped by 2.6M; urgent cancer referrals were down by an alarming 280,000, with up to 26,000 fewer patients starting treatment, of which 15,000 would normally have first come to light via a GP referral.
Yet, knowing all this, the government would have you believe that their intention is to save life. This claim is not credible.
THE JABS ARE DANGEROUS
Further evidence from Israel suggests that the the period between the first and second jab, and shortly thereafter, increases the COVID-19 mortality risk. Vulnerability to disease is significantly greater during this 3 to 5 week period.
Prof. Dr. Seligmann (Ph.D) and his research partner calculated the base rate likelihood of COVID-19 mortality for different age groups prior to being jabbed. For example, for those over 60, it was 0.00022631% per day. He then contrasted this with the official Israeli data for mortality immediately post jab.
During the 13 day period after the first dose of the Pfizer jab, the COVID-19 daily mortality risk for the over 60’s was 14.5 times higher at 0.003303% per day. After 13 days this risk increased to 0.005484% per day, more than 24.2 times greater. This rose further, up to 6 days after the second dose, to 0.006076% per day, representing a 26.85-fold increased risk of COVID-19 mortality for the jabbed.
Prof. Seligmann found similarly huge increases in the COVID-19 mortality risk for all the jabs during what he called the “period of vaccination.” Once the recipients were “fully vaccinated” Seligmann found some benefit for the jabbed, as they afforded a marginal reduction in COVID-19 mortality risks when compared to those of the unjabbed.
He calculated that, for this benefit to outweigh the massive increase in risk during the “period of vaccination,” the jabs would have to provide near 100% protection for more than two years just to offset the initial health cost of being jabbed. This benefit is not seen in the data.
A recent Swedish study is one among many to show that any possible COVID-19 benefit, once fully jabbed, wanes quickly. Unable to protect those most vulnerable to COVID-19 after 6 months, Dr Seligmann’s research indicates that there is no COVID-19 health benefit associated with the jabs.
Official risk/benefit analysis suggests that being fully jabbed provides some marginal protection against hospitalisation. There is also a barely discernible statistical signal suggesting that they also reduce mortality, to a very limited degree.
Prof. Seligmann found the same. However, this only related to the COVID-19 statistics and they are based upon non-diagnostic RT-PCR test results. Official claims take no account for the additional “period of vaccination” risk identified by Seligmann.
Prof. Selligman and Dr. Spiro P. Pantazatos, assistant Professor of Clinical Neurobiology at Columbia University, subsequently undertook further evaluation of the all cause mortality risk following the jabs.
Their research showed an estimated U.S. Vaccine Fatality Rate (VFR) of 0.04%, suggesting that the CDC declared VFR of 0.002% underestimates mortality caused by the jabs by a factor of 20. The scientists found that the data indicated U.S. jab related deaths of between 146,000 and 187,000 for the period between February to August 2021.
Pantazatos and Seligmann also identified a significant increase in the all-cause mortality risk in the first 5-6 weeks following the first jab. Again, demonstrating that the initial risk of being jabbed is not offset by the short-lived benefit once “fully vaccinated.”
There is little reason to accept the officially reported statistics.
The attribution of COVID-19 to mortality is spurious. Death within 28 or 60 days of a positive RT-PCR test is used, depending on whose statistics you look at. This is not “proof” that COVID-19 was the cause of death.
Attribution of COVID-19 to hospital admissions is equally weak. Research by independent auditors shows that people with a range of non-COVID related presentations, such as limb or head injuries, are often admitted to hospital as supposed COVID-19 patents.
The researchers found that, in more than 90% of alleged COVID-19 admissions, there was no clinical reason to describe them as such.
All alleged benefits of the jabs are based upon these woolly definitions and questionable statistical assertions. Consequently, if we truly want to understand the possible benefits of the jabs, we need to look at all cause mortality.
This can be considered more reliable because it is simply an anaylisis of all registered deaths, irrespective of the cause.
If the jabs work and are safe, then a difference in all cause mortality between the the jabbed and the unjabbed should be observed. While the jabbed aren’t protected against other causes of death, they are supposedly protected against COVID-19 and this should be detectable in the data.
A team of statisticians from Queen Mary University London conducted a study of all cause mortality data in England. They examined the vaccine surveillance monitoring reports issued by the Office of National Statistics (ONS).
They noted that initially, as we’ve discussed, these official reports seem to show a benefit from the jabs. However, they identified a series of anomalies in the data.
They found that non-COVID-19 mortality patterns, for the supposedly unjabbed, had peaks that correlated with the jab rollouts. After the “period of vaccination” the Non COVID-19 mortality for both the jabbed and allegedly unjabbed cohorts remained similar and relatively stable. Further, in general, the unjabbed appeared to have unusually high non-COVID-19 mortality while the jabbed seemingly had unusually low non-COVID-19 mortality.
They also looked at the different categories of jabbed people. These were “within 21 days of first dose,” “at least 21 days after first dose,” and “second dose.”
They found a consistent but large variation in the mortality figures between these groups. “Second dose” non-COVID-19 mortality was persistently below baseline mortality, while “within 21 days” mortality was always far above baseline.
Most striking was the different patterns in mortality between the three studied age groups. Historical data shows that for those in the 60-69, 70-79 and 80+ age groups, while all cause mortality increases with age, the three groups always shared the same mortality distribution pattern, typically with a peak in the winter months. This is often referred to as “excess winter mortality.”
Yet in 2021, not only did the three groups have separate periods of peak mortality, dispersed unseasonably throughout the year, for the unjabbed that mortality corresponded directly with the jab rollouts in each age group. Nor did these peaks in unjabbed mortality corrolate to supposed waves of COVID-19. They followed the jab rollouts.
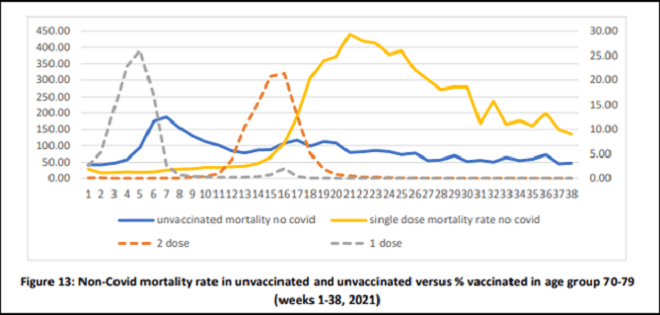
The researchers concluded:
Whatever the explanations for the observed data, it is clear that it is both unreliable and misleading […] we believe the most likely explanations are systematic miscategorisation of deaths between the different groups of unvaccinated and vaccinated; delayed or non-reporting of vaccinations; systematic underestimation of the proportion of unvaccinated [and] incorrect population selection for Covid deaths. With these considerations in mind we applied adjustments to the ONS data and showed that they lead to the conclusion that the vaccines do not reduce all-cause mortality, but rather produce genuine spikes in all-cause mortality shortly after vaccination.”
The head of the research team, Prof. Dr. Norman Fenton, gave a radio interview where he explained why his paper had not been peer reviewed or submitted to a journal for publication:
The unvaccinated seem to be dying after not getting the first dose and the single dose are dying after not getting the second dose […] the vaccinated are dying within 14 days of vaccination and are simply being categorised as unvaccinated […] There is no evidence for their efficacy when it is measured by the only sensible way to measure it, which is all cause mortality […] When we first started doing research on this we had no problem getting our work into peer reviewed papers, because we weren’t challenging the narrative […] As soon as it became clear, you know, with the sort of mass testing of asymptomatic people, that the potential for false positives for asymptomatics was inflating case numbers and COVID so-called hospitalisations and deaths, as soon as we started raising those concerns in our work, as soon as we submitted it for publication, it was being rejected without review. Something I have never had before.”
Rejecting science, because it doesn’t abide by the official narrative, is not a new problem but it is “anti-science” and suggests a coordinated effort to deceive. The work of Prof. Seligmann and others, looking at both COVID-19 and all cause mortality, appears to independently corroborate the finding of Queen Mary team.
There is no doubt that the jabs can kill. There have been a number of inquests that have found that death was caused by complications following the jabs.
Causes of death have included venous infarction thrombosis, intracerebral haemorrhage, anaphylaxis, vaccine-induced thrombosis & thrombocytopenia and “unrecognised consequences of elective COVID-19 vaccines,” to name a few. The only question is the scale of the mortality caused by the jabs.
US researchers found a 19 fold increase in myocarditis (heart inflammation) among the 12 – 15 year olds which directly correlated with the jab roll-out. The study was peer reviewed and then published, before being withdrawn by journal editors without explanation.
Myocarditis is extremely serious for young people and often requires a heart transplant in later life, significantly reducing their life expectancy.
Just as some in the scientific community are mystified by the almost perfect correlation between jab and COVID-19 “case” rates, so the medical profession are similarly bewildered by the marked rise in cardiac emergencies in Scotland. These too followed the jab rollout for the impacted age groups.
Apparently doctors haven’t got the faintest idea what the cause could possibly be. They are not investigating if it could be the jabs.
Why they aren’t could be seen as yet another mystery, because the statistical evidence indicates that the jabs are lethal. If we look at statistics from the ONS it is evident that, between January and October 2021, the jabbed under 60’s in England were dying at approximatly double the rate of the unjabbed.
This is not an insignificant fact but comes with important caveats. Prof. Fenton and his team did not analyse this age group because it is too broad. Depending on the progress with the jab rollouts, with older people jabbed first, the jabbed cohort is likely have a higher baseline mortality risk than the jabbed.
Taken in isolation this statistic doesn’t reveal much. It is more telling in context with a German study which also found a clear correlation between the jabs and mortality.
Together these add further corroboration the other statistical findings we’ve discussed. The German scientists, Prof. Dr. Rolf Steyer and Dr. Gregor Kappler, concluded:
The higher the vaccination rate, the higher the excess mortality. In view of the forthcoming policy measures aimed at reducing the virus, this figure is worrying and needs to be explained if further policy measures are to be taken with the aim of increasing the vaccination rate.”
The only rationale that can explain how the ONS, MHRA, EMA, FDA and other official bodies around the world are maintaining the lie that the jabs save lives is that they have chosen, or have been ordered, to release disinformation that knowingly endangers public health. There is yet more evidence from the clinical trials that this is the case.
The FDA, MHRA, EMA and other supposed regulators granted EUA’s for the Pfizer/BioNTech jab based upon 2 months of extremely limited, interim trial data. Research by the Canadian COVID Care Alliance has exposed this wholly untrustworthy process. There was no mention in the original, interim trial data, submitted by Pfizer, of the scale of the ADRs caused by their product.
Using relative risk they claimed their jabs were amazing and nearly everyone, including the regulators, simply took their word for it. Those who didn’t were vilified as “covid deniers” or “anti-vaxxers.”
Six months into the jab rollout Pfizer released more data with another interim study. They made more claims about the efficacy and safety of their BNT162b2 jabs:
BNT162b2 continued to be safe and have an acceptable adverse-event profile. Few participants had adverse events leading to withdrawal from the trial.”
However, this wasn’t true at all. In their released report, published by “respected journals” like the Lancet, they forgot to analyse the supplementary evidence concerning ADRs, also contained within their findings.
This revealed a consistent elevated risk of Adverse Events (AEs) for the jabbed. For example, “related events” are adverse health events that are deemed to be caused by the jab. For the jabbed the related risk ratio was 23.9, for the unjabbed it was 6. This is nearly a 300% increase in the risk of health harm if you take the Pfizer jab.
Serious adverse events are likely to put you in hospital. For the jabbed the risk was 0.6, for the unjabbed it was 0.5. In other words the jab increases your risk of being hospitalised by 10%.
A drug that increases illness in the population is not an “effective vaccine.” Reducing “case numbers” for one ailment is an utterly pointless exercise if population levels of illness and hospitalisation increase as a result. It gets worse.
Prior to unblinding their own trials, thereby ending the supposed RCTs years before completion, jabbed and unjabbed cohorts were equal in size. 15 people died in the jabbed cohort and 14 died in the unjabbed cohort. Following unblinding a further 5 jabbed people died, including 2 who were previously unjabbed.
The jab increases the mortality risk. This is precisely as observed by Seligmann, Fenton, Steyer, Kappler, Pantazatos and many other scientists and statisticians.
Pfizer were eager to report the 100% reduction in COVID-19 mortality in the main body of their study. Of the 21,926 people in the jabbed cohort only 1 died with a positive RT-PCR confirmed COVID-19 “case.” Whereas 2 of the 21,921 placebo group died. Hence Pfizer’s 100% improvement claim of efficacy.
They failed to mention that their product doubled the chance of you suffering a cardiovascular event and they definitely shied away from the most unpallatable reality of all. There were 4 heart attack deaths among the jabbed compared to 1 in the placebo group. A 300% increased risk of fatal heart failure following the jab.
If the objective of the jabs is to “save life” then it is impossible to understand how they ever received EUAs.
Fully indemnified against prosecution and with carte blanche from the regulators to do whatever they like, the pharmaceutical corporations are fully committed to jabbing all our children, including infants.
This is something our governments and the majority of the population wholeheartedly approve of. If you question it you are selfish.
THE REGULATORS SEEMING EFFORTS TO HIDE THE TRUTH ABOUT THE JABS
It is common to read claims from the regulators, and everyone else who advocates the jabs, that the benefits of the vaccines outweigh the risks.
This is based on the alleged risk of COVID-19, which is practically impossible to assess due to the massive corruption of the data, and an apparent blank refusal to consider any risks from the vaccines.
At first glance, the safety profiles for the jabs look appalling. So far, in the UK alone, there are 1,822 possible jab related deaths recorded via the MHRA yellow card scheme.
In response to a Freedom of Information Request (FOIR,) the MHRA revealed that they had received:
“[…] a total of 404 UK spontaneous suspected ADR reports for any vaccine between 01/01/2001 – 25/08/2021 associated with a fatal outcome.”
With more than 1,800 suspected fatalities reported for the COVID jabs already, currently they potentially account for three and half times more fatalities than all other vaccines combined over the last two decades. This is a statistical pattern repeated in every nation that has rolled them out.
We also know that the vast majority of possible ADRs remain unreported. A 2018 survey study of paediatric healthcare professionals found that 64% had not reported known ADRs. Of the total surveyed 16% didn’t even know the Yellow Card system existed and 26% didn’t know how to use it, with only 18% having undertaken any relevant training.
So it is not at all surprising that the MHRA state:
“It is estimated that only 10% of serious reactions and between 2 and 4% of non-serious reactions are reported.”
There is no evidence that the MHRA have done anything to improve yellow card reporting. Apparently they have promoted the Yellow Card Scheme, it is just that no one noticed. With nearly 400,000 COVID jab ADR reports on the system already, it is likely that the true figure is in excess of 10 million and possible UK deaths caused by the jabs could certainly exceed 18,000.
This is necessarily speculative to a degree, because the MHRA have not investigated any of the recorded ADRs. They have no idea how many people have been killed by the jabs and have shown no interest in finding out.
While they claim their role is to investigate potential ADRs, to provide an “early warning system” for possible vaccine harm, they also say:
The suspected ADRs described in this report are not interpreted as being proven side effects of COVID-19 vaccines.”
This is reasonable if those reports are then investigated. That is not what the MHRA do. Their position and their statements are wholly unreasonable.
To date, they have provided nothing that proves these reports are not evidence of ADRs. Their given interpretation, that these reports provide no proof, is meaningless. Nothing can ever be proven if you don’t bother to examine the evidence.
There is no commitment from the MHRA that they will ever investigate any Yellow Card reports for the jabs. All they will do is highlight possible safety issues, note the reports, and maybe discuss these with other national regulators. There is no expressed intention to question the manufacturer’s claims for the jabs at all.
The UK’s MHRA claim that a dedicated team look for “signals” in the data and where a signal is found they will discuss this with some selected experts.
Given that they acknowledge both the under-reporting and that current monitoring suggests the jabs have a mortality rate orders of magnitude worse than any vaccine, you would imagine that the MHRA would have identified a very concerning “signal.” Indeed they admit:
Yellow Cards in isolation are sufficient to allow signal detection.”
Yet they choose not to use the Yellow Cards as an “early warning.” There is no record of them following up on any Yellow Card reports. Instead they first apply a number of relative risk calculations to see if the signal is worthy of further discussion.
In particular, they use the MaxSPRT (Sequential Probability Ratio Test). This compares reported ADRs to the general population, or background, risk of the same adverse event. If the likelihood ratio test (LRT) indicates that the risk is higher following a jab, then a signal has been identified. However, dishonesty lurks within this approach.
MaxSPRT is based upon a series of assumptions about the data. Specifically that it is constantly monitored in real time and that there is a matched exposure between the jabbed and the unjabbed to contrast incident rates.
When we are talking about 40M jabbed compared to 7M injabbed adults, the disparity between and the size of the jabbed and the unjabbed cohorts invalidates this methodology.
Many biostatiticians have pointed out the limitations of using MaxSPRT for large volume database analysis:
This particular LRT, which conditions on the total number of events, is designed for the rare event case in which only one event is expected to be observed per exposure […] However, when events are not extremely rare, or when the probability within a stratum of more than one event occurring is not small, the assumptions of this LRT are violated.”
In other words the MHRA appraisal is highly sensitive to extremely rare ADRs but is likely to hide, rather than reveal, the more common side effects that are killing people. The MHRA are using a system that will obscure serious problems with the jabs. The only signals their dedicated team might discuss with experts will be “extremely rare.”
They won’t see any signals for more common adverse events and can therefore overlook the obvious and ignore the danger.

MHRA – Dedicated Team
Presumably this is why the MHRA have chosen not to use the “Yellow Cards in isolation.” The raw data clearly indicates huge reason for concern. It has to be reworked and remodelled in order to ignore the glaringly evident. Again, this is a common feature of all jab safety monitoring (pharmacovigilance) systems, which scientists have described as “utterly inadequate.”
Correlation does not prove causation, yet where correlation is persistent and pronounced the chance of it not demonstrating causation diminishes rapidly. Wherever we look, the jabs appear to be causing severe ADRs on an alarming scale.
COVID JABS: INEFFECTIVE, OPPRESSIVE AND DANGEROUS
There is no evidence to substantiate any official or MSM claims about COVID-19 jab efficacy or safety. They are experimental drugs with unknown risk profiles that are being forced upon people without offering them any opportunity to give their informed consent. The jab roll-outs breech numerous international conventions including the Nuremberg Code.
What data does exist is alarming, to say the least, and all the indications are that the jabs are extremely dangerous. There is no doubt that they can kill. Those who support a jab mandate are advocating that people should be forced to take a potentially lethal injection. Those who are aware of this, understandably, do not wish to take them.
For this they are being demonised by government, the MSM and a large percentage of those who have elected to be jabbed. If they try to raise any concerns they are dismissed by the same as anti-vaxxers, conspiracy theorists, covid-deniers or dangerous refuseniks and are accused of being selfish. Despite that fact that it is the jab obsession that is destroying public health and medical services.
There is clear evidence of obfuscation and denial to hide the dangers of the jabs from the public. This seems to cross the threshold of criminality in nearly every nation state where the jabs are deployed. National populations are clearly under attack by their own governments and their partners.
However, perhaps the most insidious aspect of the jabs is their central role within a new system of governmental authority that is enslaving humanity. Our jab status is the required license to participate in a technocratic, behavioural control and surveillance grid. Not only will our vaccine passport (app) monitor and report where we go, who we meet and what we are allowed to do, it will also determine what services we can access.
Those who think the jabs are essential to protect themselves and others, against a low mortality respiratory virus, have either not been given, or choose to ignore, the information required to make this judgement. They believe that they are free because they can now register to use the services that hitherto were freely available to all. They have accepted that they need permission from the government simply to conduct normal, everyday activities.
They are committed to take whatever drugs are given to them for the rest of their lives. If they wish to retain their societal permits, this is not negotiable. Their imaginary freedom is conditional upon their continued compliance.
They do not own their own body and are no longer, in any sense, free. They are elective slaves and are seemingly content to condemn future generations, including their own children, to the same fate.
You can read more of Iain’s work at his blog In This Together or on UK Column. His new book Pseudopandemic, is now available, in both in kindle and paperback, from Amazon and other sellers. Or you can claim a free copy by subscribing to his newsletter.
New study shows vaccines must be given monthly to be effective against Omicron
By Steve Kirsch | December 24, 2021
If you are worried about Omicron, guess what? The vaccine they gave you is going to make you MORE likely to get infected, not less. If you stay on the vaccine treadmill, it will be even harder to get off in the future. In short, we’ve been lied to about the vaccine.
Everyone needs to stop listening to the CDC now and start listening to people who have been saying to ditch the vaccines and aggressively promote early treatment with repurposed drugs.
Alix Mayer alerted me to this game changing tweet which instantly went viral as you can see from the number of retweets:
I want to tell you what this really means and how it is being attacked.
Summary: Refuse to comply with mandates
This paper means we will need to inject people every 30 days if we want to “protect” them. Based on what the vaccines do to our immune system, it’s likely that the needed interval will shorten with each booster.
If people don’t get boosted as required, they will be MORE vulnerable to Delta and Omicron than if they weren’t vaccinated. That’s what NEGATIVE vaccine efficacy means. It doesn’t mean the protection wears off (like we were told). It means the OPPOSITE of what you were told: it means the vaccine helps the virus to infect you (by suppressing your immune system). It means we were lied to.
In short, the vaccine is like a heroin addiction: once you’ve had a taste of it, you are hooked: you have to continue it for life if you want protection. If you stop it, you’re a sitting duck for the virus.
What’s worse is our government is mandating this now. In light of this paper, they will change the vaccine mandates to force you to get vaccinated every month or you will be fired from your job. Their next move could well be to make it illegal not to be vaccinated. This seems like where things are headed based on what is happening in other countries where they are quickly stripping away your rights to do anything without a vaccination.
And we have no clue what monthly (and later weekly) vaccination will do to your body. This has never been tested.
My advice is simple. If you have been vaccinated, you need to stop now. Do not get the booster. My friend Dr. Robert Malone is fond of repeating the old addage, “When you find yourself in a hole, stop digging.”
Sadly, most people cannot afford to lose their jobs, so they will get vaccinated.
The details
First, the link in the tweet is to the outdated version of the paper. The current version can be found here.
Start at the comments, both from social media and also from medrxiv readers.
Check out the social media portion of the comments
Here are some comments (on old and new version of the paper):
- So assume the results you like (high VE for recent vaccination) are causal, but hand wave confounders at results you don’t like (negative VE for distant vaccination)? Science?
- This is a superb paper, especially the careful approach to CNV calling and the Bayesian methods used throughout.
- Looking at the graphs, I see both vaccines lose all effectiveness at 90 days, but worse, actually drop into strong negative effectiveness after that time.This would mean that these vaccines *increase* one’s chances of infection after the initial 90 days “honeymoon” period.Am I getting this right?If so, why are governments pushing third doses as Omicron is becoming dominant?
The key material is in the full PDF:

The graphs above tell the story. Negative VE means the vaccine is helping the virus, not you.
So at 60 days, the protection is close to zero, so if you want to maintain protection, getting vaccinated every 30 days is required.
This isn’t a vaccine at all. This is basically stimulating your immune system so it is already “geared up” to fight the virus. That’s not what a vaccine is supposed to do.
Furthermore, the negative VE after 90 days means you are hooked for life and I would guess (based on the mechanism of action), that we will need shorter and shorter dosing intervals for every booster you get (since it kills off your immune system every time).
So it could very well be monthly boosters after the 2nd dose, weekly boosters after the 3rd dose, and perhaps daily boosters after the 4th dose to maintain your “immunity.”
You can’t stop after that because if you stop, you’re in worse shape than if you never started.
The stunning conclusion of the paper
In light of the exponential rise in Omicron cases, these findings highlight the need for massive rollout of vaccinations and booster vaccinations.
All I can say is “wow.” This should be a wake up call: the vaccines do not work. Stop repeating the insanity. Early treatments like the Fareed and Tyson protocol are 10X better than any new therapy, they don’t “hook you,” and they don’t cause disability or death.
If doctors started prescribing the Fareed and Tyson protocol, we’d have virtually no deaths, and few hospitalization. But they can’t do that since medical board will take away the licenses of any physicians who prescribe ivermectin, etc. This is happening now.
We are in this mess because the NIH, CDC, FDA are corrupt and incompetent and they will not hold themselves accountable in an open debate. This has been going on for 20 years in the vaccine space… it’s nothing new. The book “Evidence of harm” documents all of this. Kirby was deliberately neutral in his presentation (being non-judgmental like reporters are supposed to be), but any neutral thinking person will side against the authorities.
Why the paper went viral
So, the reason this paper went viral is because
- It is well done,
- It was done by PhDs in infectious disease and epidemiology,
- The results show what is really happening, and
- Nobody has been able to attack the paper with a credible argument, even on Twitter.
- It confirms what my team of experts has been saying about negative VE
Here are some of the ridiculous attempts to discredit the paper:
https://twitter.com/robertnorton_/status/1474130702236991501
https://twitter.com/SwingTrader1114/status/1474160045231415298?s=20
Supporting evidence
The paper isn’t a fluke. There is lots of other evidence in support of it.
Here’s the data from Canada:
In Ontario in the last few days, cases per capita among the vaccinated have skyrocketed above cases per capita among the unvaccinated. Clearly, mandates are nonsensical at this point, because the entire case for restricting unvaccinated people is their presumed higher per capita infection rate.
Here’s the UK data:
I have more, but substack limits the size of an article. Links include
- Vaccine efficacy declines in the UK
- Booster protection fades within 10 weeks against Omicron: UK study
- Booster shots protect against symptomatic Omicron infection for about 10 weeks, study finds — which could mean more doses for some in 2022
- This is a video with fake subtitles but you’ll enjoy watching it. It’s humor.
- This article looks at the Danish study (described here) and the UK data. Note that the VE numbers in the two studies are different because if you separate out Omicron, you get a very different picture of VE compared to analyses that don’t separate this out: Denmark: Vaccine a DANGER to the vaxxed
Featured Video

Spain train disaster raises questions over Israeli-linked security contractors
or go to
Aletho News Archives – Video-Images
From the Archives
Are There 50,000 ‘Israeli-born’ Individuals Living in the UK?
By Professor David Miller | August 18, 2026
Recent disclosures by the Zionist regime show that some 2,069 British nationals were serving in the IDF as of March 2025, according to Freedom of Information (FoI) requests submitted to the occupation forces (1,686 dual British-Israeli, plus 383 multinational). We cannot tell from the figures how many of these were already settler colonists and intend to stay in the colony, and how many will return or have returned to the UK. Presumably, those returning to the UK will number far fewer than 2,000, since many are known to have become permanently residents of the colony.
Additionally, the IDF figures only provide a snapshot, and do not tell us how many have served in the Jewish supremacist military either before or after March 2025. One way into the question of how many genocidaires are living in Britain is to ask how many current British residents were born in the Zionist colony. There is data on that, as we shall see. … continue
Blog Roll
 Aletho News
- Europe, US face higher heating bills amid Iran war fallout
- The Leak That Arrived Right on Cue
- No, New York Times, California’s Climate Has Always Been a Land of Flood, Drought, and Fire
- Are There 50,000 ‘Israeli-born’ Individuals Living in the UK?
- German CDU MPs Seek Climate “Misinformation” List
- The ‘Gaza Treatment’: How Media Headlines Obscure Who is Bombing Yemen
- Ro Khanna urges Democrats to strip Israel ‘integration’ provision from defense bill
- Why Iran designated British MI6, Royal Navy, and RAF as hostile, terrorist organizations
- Armenian opposition politician dies in custody
- US still trying to recycle failed hypersonic missile programs
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- German Authorities Start Initiative To Evaluate Public Register For Climate “Disinformation” Spreaders!
- Zonal Asymmetry of Temperature Change in the Antarctic Circumpolar Current
- New Study: The Net Fossil Fuel Contribution To Rising Atmospheric CO2 Has Been Zero For 500 Years
- Germany’s Green Energy Transition Becoming Increasingly Expensive…Another 6 Trillion Euros!
- Sudden Stratospheric Warming, Powerful El Niño Combination May Lead To Extreme Europe Cold, Energy Crisis!
- Two New Studies Find Thwaites Glacier Melt Cannot Be Driven By Human Activity Or A Warming Ocean
- E-Cars Reduce CO2 Emissions By Only 41% Compared To Internal Combustion Engine Vehicles
- Predictions Made By Renowned Climate Professor Over Past Decades Have Been Proven To Be Poor
- New Study Suggests Large Regions Of The Pacific Ocean Have Been Cooling For The Last 80 Years
- Germany’s Green Energy Debacle: High Energy Costs Force Kahla Porzellan to Close After 182 Years!

