February 9, 2022
VIA FEDERAL EXPRESS and EMAIL
Dear Dr. Janet Woodcock:
We write to you on behalf of Children’s Health Defense (CHD), a non-profit organization devoted to the health of people and the planet. We have actively followed your work to evaluate, authorize and approve vaccines for the American public, and particularly children.
We are aware that you are likely to grant Emergency Use Authorization (EUA) of Pfizer’s BioNTech SARS-CoV-2 vaccine for children aged six months up to five years old following your upcoming meeting on February 15, 2022. We are writing to put you on notice that should you recommend this pediatric EUA vaccine to children under five years old, CHD is poised to take legal action against you. CHD will seek to hold you accountable for recklessly endangering this population with a product that has little, no, or even negative net efficacy but which may put them, without warning, at risk of many adverse health consequences, including heart damage, stroke and other thrombotic events and reproductive harms.
We briefly outline why such a recommendation would be reckless for nearly 20 million children in the United States, and millions more around the world.
-
There is no COVID emergency for children under five years old. Children have a 99.995% recovery rate and a body of medical literature indicates that almost zero healthy children under five years old have died from COVID.
-
A large study conducted in Germany showed zero deaths for children under 5 and a case fatality rate of three out of a million in children without comorbidities.
-
A Johns Hopkins study monitoring 48,000 children diagnosed with COVID showed a zero mortality rate in children under 18 without comorbidities.,
-
A study in Nature demonstrated that children under 18 with no comorbidities have virtually no risk of death.
-
Data from England and Wales, published by the UK Office of National Statistics on January 17, 2022 revealed that throughout 2020 and 2021, only one (1) child under the age of 5, without comorbidities, had died from COVID in the two countries, whose total population is 60 million.
-
Another study in Nature from April, suggests children’s bodies clear the virus more easily than adults.
-
This study published in December in Nature demonstrated how children efficiently mount effective, robust and sustained immune responses.
-
Over one third of all children are estimated to have natural immunity to COVID, according to CDC’s own data. There is no ethical justification for superfluous vaccination that will put children at elevated risk of vaccine harm.
-
The risks demonstrably outweigh the benefits of COVID vaccination in young children. A study out of Hong Kong, showed one out of every 2,700 12-17 year old boys being diagnosed with myocarditis following the 2nd dose of Comirnaty vaccine, or 37 per 100,000 vaccinated. A study from Kaiser found the same rate of myocarditis in 12-17 year old American boys, 1/2700.
-
While the CDC is saying that myocarditis is a mild disease, cardiologists know otherwise. CDC’s own preliminary data, reported at the February 4 ACIP meeting, revealed that nearly half of the young people diagnosed with myocarditis still had symptoms 3 months later, and 39% had their activity restricted by their physician. We know this serious adverse event occurs frequently in teenagers. But no one knows how often it occurs in younger children. This is of major concern for babies and younger children.
5. The clinical trials for children 2 through 4 years old failed., You’re proposing to use a product and schedule that failed in its clinical trials, and you may potentially add a third dose later in the spring. This is an unprecedented proposal not backed by science. It does not meet the risk-benefit standard of 21 U.S. Code § 360bbb–3 “the known and potential benefits of the product, when used to diagnose, prevent, or treat such disease or condition, outweigh the known and potential risks of the product.”
6. Some children likely will die and others will be permanently injured from these vaccines based on reporting to the current VAERS database. The latest data shows a total of 1,088,560 reports of adverse events from all age groups following COVID vaccines, including 23,149 deaths and 183,311 serious injuries between Dec. 14, 2020, and Jan. 28, 2022.
7. The pediatric clinical trials for the COVID vaccines were too small to detect safety signals–especially for a population in the tens of millions.
8. There are a) no long-term safety data for COVID vaccination of young children, and b) the proposal is to vaccinate children under the Emergency Use Authorization. Both a) and b) establish that vaccinating small children for COVID will be an experiment, not a standard medical procedure.
9. Unethical coercive pressure will be applied to children and their parents, as has occurred with older children and adults. To grant authorization is to abet this unethical coercion that violates the Nuremberg Code’s first principle.
10. There is no available care for children injured by COVID shots. There is no way to remove the spike protein and other toxic byproducts of vaccination, which may be produced for a considerable period of time following inoculation of messenger RNA. The science and medicine have not yet developed, and most families will be unable to cover the costs of potential catastrophic injuries.
11. First, do no harm. You are a physician who owes a duty to patients and medical ethics. If you recommend these shots to this age group, given all you know, will you be upholding your oath? If not, is it possible that your acts could later be seen as reason to remove your medical licenses?
12. The liability-free nature of your deliberations may not stand the test of time. In the fullness of time, your decisions may not have the liability protection that they currently enjoy. Under the PREP Act of 2005, all actors advancing an EUA agenda for medical countermeasures enjoy liability protection, absent willful misconduct., Nonetheless, if at a later point these shots are deemed non-therapeutic gene products that you knowingly and recklessly recommended, and which were then distributed to children as a direct result of your decision, it is possible that liability could later attach.
13. There are safer drugs that could be used prophylactically and therapeutically for COVID in children. There is extensive and compelling medical evidence for this assertion; and the choice to eschew use of these drugs in favor of a demonstrably dangerous vaccine is arbitrary and capricious.
14. The vaccines do not prevent transmission. They do not prevent infection. There is no statistically valid evidence that they prevent severe disease or deaths in children. Which begs the question: what are you actually trying to accomplish by vaccinating small children? What is your goal?
15. On August 23, 2021, FDA’s letter to BioNTech explained that neither the VAERS nor the VSD surveillance systems were adequate for FDA to determine the risk of myocarditis resulting from the Pfizer vaccine. Therefore, Pfizer and BioNTech were instructed by FDA to carry out a series of studies of myocarditis to ascertain the risk in different groups, including children. These studies were scheduled to produce final reports to FDA over the next five years. If the FDA is willing to wait until 2027 to learn the actual risks of myocarditis from the vaccine for children, shouldn’t it be required to wait until 2027 before inoculating millions of small children with a vaccine anticipated to provide them no benefit and possibly substantial risks?
16. An important Cell article in press, written by scientists from Stanford, has shown that, based on lymph node sampling after mRNA vaccination, spike protein and its mRNA remain present in the germinal centers of draining lymph nodes for up to 60 days, which is when sampling ceased. This was not supposed to happen. The demonstration of vastly prolonged spike protein production has revealed that the dose of spike protein produced in vivo by mRNA vaccines is unpredictable. FDA, however, requires uniformity of dosing. This fact alone should disqualify all authorizations and approvals of mRNA COVID vaccines.
We ask that you carefully consider all the information above before making any recommendation for Pfizer’s vaccine in the 6 months to under 5 year age group at your meeting on February 15, 2022.
_____________________________________
Robert F. Kennedy, Jr. Meryl Nass, M.D.
Unfortunately, the footnotes are missing from this version. They can be found at:
https://childrenshealthdefense.org/wp-content/uploads/CHD-Letter-to-FDA__EUA-Under-5_2-9-2022-1.pdf
February 13, 2022
Posted by aletho |
Science and Pseudo-Science, War Crimes | COVID-19 Vaccine, FDA, United States |
Leave a comment
in the age of government sponsored science driven by grants, sinecure, and sponsorship, scientists face a difficult set of choices.
they must, if they wish to continue receiving the largess of the gold-givers toe the party line of state or commercially sponsored science. he who has paid the piper demands to call the tune and producing work that does not suit “the narrative” is career suicide. your funding will dry up. so may your position, your prospects for advancement, and even your tenure. you will not be asked to join committees, interviewed for articles, citied, or supported. you may be outright attacked. i discuss this in more depth HERE.
but scientists also face another constraint: they need to be accurate. they need to run good experiments, collect good data, and relay it faithfully. if they do not, they will get called out and revealed as incompetents or frauds. this too will end one’s career as it means that not only are you doing no useful work (apart from to propogandists) but will reveal that you have sold out integrity for lucre and that is the end of peers taking you seriously. you play for team lysenko now.
the need to thread this needle and appease and please both demands has led to an odd practice:
many times, the claims made in the abstract or in the conclusions are not supported by the actual data.

i know this sounds a little bizarre, but as someone who reads perhaps 1000 such papers a year, allow me to assure you, it is stunningly common in any politically loaded sphere. (and you would be amazed how many are politically loaded. it need not be government pushing it. watching geneticists tie their conclusions in knots to claim that you can breed horses for speed and endurance or dogs for intelligence but that of course there is no such thing as eugenics in humans because that would be unspeakable despite your having just proved that there is in fact, eugenics in humans is really quite something. they go to astounding lengths in the introductions of their books to disavow what they are about to prove.)
this odd compromise sort of works, but mostly, it doesn’t.
it gives those who fund studies and the journals who curate them for ideological purity their bone. the abstract says “X means Y.” this is what they want for the press releases and for waving around.
it also puts the actual data out into the world. this is what researchers, both those who did the work and those who will read it in detail, actually need. they can see the facts and will not be gulled in by the claims in the conclusion as they are adept at drawing their own conclusions.
this leads to the weird outcome of the public and the politicians frequently having one idea about what a study says and the experts in the field having more or less the opposite take.
the “experts” all know what the data means and why they are not allowed to say it. it works a bit like the foils used by renaissance dialogue writers to ape at being fools while presenting the actual case being made while the “authorities” presented the “narrative” and were made fools of by those able to read between the lines.
in the age of the internet, this sets up a bizarre and deeply frustrating conflict: those who can and do really read studies are constantly having to pick them apart and explain to the “google and spam” crowd who just selectively confirm their biases and skim the lead paragraph of a study why the study they just cited does not, in fact, say what they are claiming it does.
and, of course, trying to convince someone that the authors deliberately misstated the facts in the summary is like trying to teach a new trick to the very oldest of dogs. they are just not having it.
this has created a rancorous and dangerously stupid level of debate and an impossible burden for any one individual to carry. it takes 10 seconds to search, skim, and spam with a study you never read and start yelling “peer review!” over and over as if that means something.
it can take hours to pick the study apart and see if it really does support the conclusions stated in the summary and then hours more to convince someone who has not even read it (and probably does not know how). that’s unwinnable. it’s like sisyphus getting and additional rock to push back up the hill every time he reaches the top. pretty soon it’s 20 boulders and nothing is going anywhere.
fortunately, the internet age has produced a large group of folks interested in picking these studies apart and publishing their takes. and we form communities and help one another. so no one has to do ALL the work when the CDC publishes yet more self refuting “wave around” data.
this is, in fact, what real peer review is. it’s supposed to be hostile and to pick holes.
the upshot here is that you should be very careful taking studies you have not actually read at face value.
you need to read them. thoroughly. waving them around as if you did when you have not is a recipe for being wrong.
let’s take a simple and straightforward recent example:

this article is being used to push boosters. this is because the authors said this:

i have not spoken to them. perhaps they believe this, perhaps they do not but felt they had to say it or be pariahs. i have no special insight there. but i can read data.
so let’s see what the data says.
this was a big study, but also a retrospective study with post facto matching. the matching was by age, sex, and municipality. it is tainted by the ever present “we counted no one as vaccinated until 14 days post dose 2” issue which will inevitably deeply favor vaccine efficacy through a mathematical rig job (especially in the short run) and can even produce it from zero VE and looks to have had large effects in canadian data.
so we have some ingrained bayesian issues with our cohorts that may inject serious bias toward making vaccines look effective.
the data itself was rendered quite challenging to read. (heavy text, few graphics)
it was also truncated in a somewhat misleading fashion.
if you read it closely, you’ll see that even the longest follow ups on infection data were lumped after 210 days, several were 180 (before it really gets bad) others were 120.
this is just typical bayesian datacrime and presentation bias as we’ve seen so many times before. and it does not really speak to the interesting issue of “are the vaccines preventing severity?”
this is, in fact, omitted from the study. but they did collect the data, they just made it REALLY difficult to find. you need to go HERE to the supplemental materials page. you then need to download the actual PDF as the data is not on the webpage. then you need to go to the very last page of that supplement.
those who do so (and i’m guessing we’re down to a very few folks by then) will be rewarded with this graph:

and this one has profound and powerful implications.
- it shows that efficacy against severe outcomes like hospitalization and death also wanes very rapidly
- it shows that this efficacy keeps waning over time
- it shows that it could easily be strongly negative based on the huge downside bias to the error range (gray shaded area)
- and it shows that this data is of very low quality in terms of error magnitude.
at 9 months, midline expectation is ~15% reduction. (i’m eyeballing) but look at the confidence interval: it runs from (ballpark) +63% to -90%. that is not a useful range upon which to base anything. it implies that there is a very strong chance that vaccination is associated with greatly increased risk of severe outcomes for a great many people.
this pattern implies that boosters are likely, at best, a treadmill that will need constant refreshing, likely 3X a year or so, if you want to sustain efficacy. vaccine fade after 4 months degrades rapidly. (and frankly, the first 4 could well be an illusory halo generated by the dose 2 +14 vaccinated definition as linked above)
given the adverse events profile and the lack of severity of omicron this seems a truly odious proposition that looks likely to fail for most people on any sort or risk/benefit analysis. it is telling that the researchers here did not even attempt to take risk reward into account before claiming:
“The results strengthen the evidence-based rationale for administration of a third vaccine dose as a booster.”
what is also telling is the other part of the data required to make this claim:
do boosters work? do they refresh clinical immunity and mitigate severity? could they ever have done so and is this data even relevant with the emergence of omicron that seems to be at least an escape variant and far more likely a full blown hoskins effect/OAS variant that is enhanced, not mitigated by the vaccines.
because the evidence there looks quite persuasive that they do not.
note that all this data is from before oct 4th 2021, so it has no omicron impact whatsoever in it. claiming it bolsters the case for boosters without presenting evidence of booster efficacy on this new variant makes their claim feel like a rote bolt on, placed there to mollify and placate patrons and authorities.
there is absolutely no data here to validate that point.
the study does not even speak to the data that would be needed to make such a claim.
“efficacy wanes, so boost” is not a valid argument unless we know that boosters work, yet any evidence that boosters actually do anything to help is absent and all past data shows such rapid fade on efficacy vs severity as to make boosters a poor appearing proposition.
there is no data whatsoever on the new variant.
and boosters are sure not seeming to help in the UK. omi is driving rates of infection in the boosted at roughly double the rate of the unvaxxed.

the swedish study uses possibly irrelevant data and not only fails to prove out the ostensible interpretation, but winds up far more consistent with the conclusion that boosters are a waste of time and will provide ephemeral, at best, protection.
having seen this, go back and read the “interpretation” again.
now do you see my point about “the abstract says one thing while the data says another?”
i mean, they literally buried the lede at the very end of a hard to find supplement. it’s like putting the actual object of a video game inside of an easter egg.
most vexing, this easter egg also shows that vaccines may be making immunity to severe covid outcomes significantly worse.
call me mister suspicious, but i have a hunch that’s WHY they put it there.
let’s explore that a bit further:

what would be REALLY interesting is to see how this population distribution looks.
if it barbells then we likely have a serious confound going on. we really have no idea what the prior incidence of covid was in those who got vaccinated. one could expect it to be quite meaningful.
if vaccines look like they are working well in some and are strongly negative in others with not much in the middle (this is suggested but not proven by the skew in the confidence interval) then i would posit that the most likely explanation is that what looks like VE is actually naturally acquired immunity.
if you had covid then got vaxxed, vaccines look like they work, especially as the high risk groups got vaxxed more and these same groups likely had higher risk of prior infection. this gets magnified by the 2 week worry window of TLR suppression post vaccination that results in well documented decreases in immune function and a doubling of the rate of covid contraction in that period vs unvaxxed.
but if you got vaxxed without having had covid, it could be acting as an immunosuppressant or driving hoskins effect/OAS antigenic fixation that makes you more vulnerable.
this, along with all cause deaths in vaxxed vs unvaxxed measured from the moment you got your first jab is some data i’d really like to see.
it’s continuing non-availability certainly frustrating and likely telling. this data absolutely exists.
why we are not getting to see it is fast becoming a question too big to ignore.
February 13, 2022
Posted by aletho |
Corruption, Deception, Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine |
Leave a comment
In lockstep in multiple countries
As with so many things that are happening at the moment, the attack on free speech is happening in multiple countries at the same time.
Firstly in the UK.
A draft Online Safety Bill was first presented to Parliament in May 2021 but has been strengthened in the last few weeks. Originally the draft Bill focussed on large web companies but the government has recently announced that more changes would be made and new criminal offences added.
One of these new offences would be spreading Covid-19 disinformation under a crime of sending a false communication. This offence would be committed if a person sends a communication they know to be false with the intention to cause non-trivial emotional, psychological or physical harm. The maximum sentence is 51 weeks.
The average person might think it is reasonable to imprison somebody for communicating something they know to be false with the intention to cause harm. However, what is “false” and what is “harm”? The last few years have shown us that these are now very subjective topics. Information that was true in 2019 became false in 2020 and is starting to be true again in 2022. A truth that is communicated to somebody who believes it to be false may cause them emotional or psychological harm. Intention is necessary for the crime to take place but if something is deemed to be false and deemed to cause harm then it could be argued that if the person who communicated the information, knew the information was on the “harmful list” then intention was there.
And who is deciding what information is false? The government? That almost sounds like a punchline to a joke. We’ll just end up with news articles such as the one below – Sponsored by the UK Government (see the text in blue).

The Bill was already censorial enough, making online companies remove content which was deemed to be harmful but not illegal. As we have seen in recent times, corporations’ misinformation policies have been arbitrary enough, which will only worsen with governments deciding what is true and what is false. Now, in a step one-removed from pre-crime, these companies will be made to proactively “prevent people being exposed in the first place”.
The government press release on the strengthening of this bill says that “to proactively tackle the priority offences, firms will need to make sure the features, functionalities and algorithms of their services are designed to prevent their users encountering them and minimise the length of time this content is available. This could be achieved by automated or human content moderation, banning illegal search terms, spotting suspicious users and having effective systems in place to prevent banned users opening new accounts”.
In almost Orwellian double-speak the press release says the Bill “will better protect people’s right to free expression online”. What this means is, it will better protect people’s free expression of government approved material. It continues by saying “it will have to be proven in court that a defendant sent a communication without any reasonable excuse and did so intending to cause serious distress or worse, with exemptions for communication which contributes to a matter of public interest”. So the government says something is a matter of public interest (e.g. vaccines) and suddenly intention doesn’t have to be proven.
Please sign this online petition to remove requirements that specifically target lawful speech from the Bill.
Next to the US.
At almost the same time, the US sent out a bulletin “Summary of Terrorism Threat to the U.S. Homeland”.
This states that “the United States remains in a heightened threat environment fueled by several factors, including an online environment filled with false or misleading narratives and conspiracy theories, and other forms of mis- dis- and mal-information (MDM) introduced and/or amplified by foreign and domestic threat actors. These threat actors seek to exacerbate societal friction to sow discord and undermine public trust in government institutions to encourage unrest, which could potentially inspire acts of violence”.
According to the bulletin, “the proliferation of false or misleading narratives, which sow discord or undermine public trust in U.S. government institutions” has “increased the volatility, unpredictability, and complexity of the threat environment”.
Key factors contributing to the current heightened threat environment include “widespread online proliferation of false or misleading narratives regarding unsubstantiated widespread election fraud and COVID-19”.
Furthermore, “as COVID-19 restrictions continue to decrease nationwide, increased access to commercial and government facilities and the rising number of mass gatherings could provide increased opportunities for individuals looking to commit acts of violence to do so, often with little or no warning. Meanwhile, COVID-19 mitigation measures—particularly COVID-19 vaccine and mask mandates—have been used by domestic violent extremists to justify violence since 2020 and could continue to inspire these extremists to target government, healthcare, and academic institutions that they associate with those measures”.
So in a step up from the UK’s response, the US is labelling individuals who produce any MDM as terrorists. Obviously, any language that incites violence is unacceptable but to confuse people encouraging unrest with those discussing whether Ivermectin could help save lives is completely unacceptable.
And finally in Canada.
Again, as if in lockstep, Justin Trudeau is trying to revive his controversial Internet legislation bill. Once known as Bill C-10, to fool those unintelligent Covid deniers, it has been changed to Bill C-11.
There are concerns that the legislation could be used to censor social media. The government have denied this but experts hold the opposite view. Who to believe, hmmm? The Toronto Sun reports that Trudeau is using the current national tensions as a smokescreen to let them slip in unpopular pieces of legislation. Never let a good crisis go to waste!
When we remove freedom of speech and censorship of controversial topics becomes common place, we turn into a dangerous society. Not only can authors be imprisoned for airing their views but, just as importantly, debate becomes restricted resulting in truths being hidden and novel and radical ideas supressed.
But if they can’t censor you, maybe they’ll just give you a morality pill so you don’t produce the stuff in the first place!

February 12, 2022
Posted by aletho |
Civil Liberties, Full Spectrum Dominance, Science and Pseudo-Science, Timeless or most popular | Canada, Covid-19, COVID-19 Vaccine, Human rights, UK, United States |
Leave a comment
A Professor of Surgery at John Hopkins, Dr. Marty Makary, said that a research letter he helped author was censored by LinkedIn for violating the platform’s “Professional Community Policies.” The post was reinstated later “after a friend complained to the CEO.”
The censored post contained a link to a research letter published in the Journal of the American Medical Association (JAMA). The letter is a study Makary conducted about the “prevalence and Durability of SARS-CoV-2 Antibodies Among Unvaccinated US Adults.”
According to the screenshots Makary shared on Twitter, LinkedIn removed the letter “because it goes against Professional Community Policies.”
The policies prohibit users from sharing “false or misleading content.”
They also forbid users, including researchers and scientists, from posting “content that directly contradicts guidance from leading global health organizations and public health authorities.”
It is not clear how the study Makary posted violated any of LinkedIn policies.
February 12, 2022
Posted by aletho |
Civil Liberties, Full Spectrum Dominance, Science and Pseudo-Science, Timeless or most popular, War Crimes | Covid-19, COVID-19 Vaccine, United States |
Leave a comment
On December 17, 2021, Pfizer announced that the clinical trial of its mRNA shot in kids under age 5 had failed. Rather than withdraw this product, Pfizer “amended” its clinical trial to add a third dose. So Pfizer kept the original trial going and subjected these little kids to yet another shot of genetically modified mRNA.
The drug dealers at the FDA said, ‘sounds great, let’s proceed with authorization even in the absence of data.’ That created a huge public backlash as parents rightly protested that the FDA should not approve a drug for kids that failed in a clinical trial.
Yesterday (Feb. 11, 2022), the FDA was forced to admit defeat and Pfizer pulled its Emergency Use Authorization (EUA) application to inject kids under age 5.
Pfizer and the FDA claimed that they were “waiting for more data” that would be available in early April. We now know that this was a lie.
Buried deep in an article on page A13 of the NY Times this morning we learned the real reason why Pfizer withdrew its EUA — the clinical trial had failed, again.
Remember, Pfizer kept the clinical trial going after December 17. So between then and yesterday’s announcement, there was now roughly 55 more days worth of data. And it was truly terrible.
From the NY Times :
Then, late on Thursday [Feb. 10], Pfizer alerted the F.D.A. that it had more recent data, from mid-January on, showing a more discouraging picture as the Omicron variant bore down. The new data revealed that two doses were not sufficiently effective in preventing symptomatic infection.
Read that again. They have the data. And the data show that this shot does not work.
But even here, I think there is reason to believe that they are still lying. We already knew that “two doses were not sufficiently effective” — Pfizer announced that in December. The “more recent data, from mid-January on” is not the two dose regimen anymore, that phase of the trial is finished.
I think there is every reason to believe that this is now the three dose trial that they are describing. If the three dose trial was on track and showing promising results, they would have proceeded with authorization. So now we likely have the first evidence that the three dose trial has failed as well.
(Here’s my math: Pfizer likely injected the third dose into these kids between Dec. 17 and mid-January. So “from mid-January on” (to Feb. 10) is looking at the data in the 25 days after the third injection. In the comments, please let me know if you interpret this differently.)
So it is definitely NOT the case that this is just an incomplete trial that they are waiting to finish up in early April. All of the existing data is bad. Pfizer is now scrambling to find ways to save this product even though the clinical trial has now failed twice. And what’s Pfizer’s plan going forward — to just hope that the data in the next 60 days (from now through early April) magically turns the corner!? Talk about wishful thinking!
Just when I think the cartel and its enablers in the mainstream media could not possibly get any more cynical they sink to new lows.
Janet Woodcock and Peter Marks at the FDA must be fired and prosecuted for reckless endangerment of children. Pfizer must stop this grotesque clinical trial immediately and permanently suspend any plans to inject genetically modified mRNA into children under 5. Anything less is savagery and barbarism.
February 12, 2022
Posted by aletho |
Deception, Science and Pseudo-Science, War Crimes | COVID-19 Vaccine, FDA, Janet Woodcock, Peter Marks, Pfizer, United States |
Leave a comment
This is what happens when you demand speedy production in an era of politicized regulation
All these tragedies have been due to failures of testing or failures in manufacturing processes. Most occurred before vaccine manufacturers were given virtually complete protection from liability in 1987. With the duration of patent exclusivity determining how much new products earn, products are rushed to market as quickly as possible, most using a shortened path for FDA review. Recalls and market removals of approved products are much more common than they used to be. We can only expect more of these disasters in the future, especially if the products are mandated for everyone.
- 1955: (Improperly inactivated) live polio vaccine caused polio in 40,000 children
The Cutter (now part of Bayer) Incident of 1955: This early US Salk polio vaccine contained live polio virus, which had not been inactivated. It caused 40,000 cases of polio; 200 of these recipients became paralyzed; and ten died. Other companies also had problems with viral inactivation. The NIH director lost his job in the aftermath, since NIH scientist Bernice Eddy had earlier warned this lot of vaccine paralyzed monkeys, but her findings were suppressed in the rush to vaccinate.
http://www.ncbi.nlm.nih.gov/pmc/articles/PMC1383764/
https://books.google.com/books?isbn=0199726590
- 1950s-1960s: SV-40 (Simian Virus 40, a potentially cancer-causing virus) contaminated polio vaccines given to millions of Americans.
SV-40 can cause cancer in animals and has been found in human cancers, though its relationship to human cancers remains uncertain.
http://www.sv40foundation.org/cpv-link.html
- 1970s-1985: Factor 8 Concentrate a pooled blood product used to prevent bleeding in hemophiliacs, was contaminated with HIV and Hepatitis C, but was sold worldwide even after manufacturers became aware of the contamination
Its manufacturers knew it was contaminated with HIV (and Hepatitis C), which spread through the injectable blood products used by hemophiliacs. About 8,000 US hemophiliacs at the time developed HIV infections this way, and an estimated 150,000 developed Hepatitis C, which frequently results in chronic liver disease, cirrhosis or death. The practice of distributing contaminated blood was widespread internationally, with many companies involved, and continued even after the problem was identified. It led to suits against pharmaceutical companies in a number of countries. It led to thousands of deaths. Doctors went to jail.
Cutter/ Bayer knowingly sold HIV-contaminated products in the US and overseas, seemingly having learned nothing from its polio-contaminated vaccine disaster 25 years earlier.
http://en.wikipedia.org/wiki/Contaminated_haemophilia_blood_products
http://www.thelancet.com/pdfs/journals/lanhiv/PIIS2352-3018%2815%2900007-7.pdf
http://www.nytimes.com/2003/05/22/business/2-paths-of-bayer-drug-in-80-s-riskier-one-steered-overseas.html?pagewanted=print
- 1976-1977: Swine flu vaccine given to 45 million Americans for a non-existent disease, causing hundreds of cases of paralysis
A new flu virus was discovered in a soldier who died at Fort Dix, NJ. Concern that the virus might cause a 1918-like influenza pandemic led to a huge federally-instigated program to develop a vaccine and vaccinate every American against the virus. But the epidemic never occurred. And the affected soldier, despite having an acute infection, had been on a rigorous march before he died. No one knew if the flu had killed him. US vaccine manufacturers agreed to produce vaccine on a short timeline, but only if they received a waiver of liability for possible vaccine injuries. The decision to use the vaccine was strongly influenced by political considerations, according to a National Academy of Sciences investigation of the program, commissioned by HEW Secretary Joe Califano. The report gives a bird’s eye view of how personal and political agendas came together to supercede considerations of the public health.
45 million Americans received the new vaccine, of whom 400 people developed autoimmune paralysis (Guillain-Barre syndrome) at a rate 6-8 times expected during the six weeks post-inoculation, and about 30 died.
http://iom.edu/~/media/Files/About%20the%20IOM/SwineFluAffair.pdf
http://jama.jamanetwork.com/article.aspx?articleid=394635 (unfortunately now behind a paywall)
- 1999: Rhesus rotavirus vaccine (Rotashield) caused intestinal damage
This oral Rotashield vaccine was designed to prevent a mild form of gastroenteritis. However, it caused 1-2 cases per 10,000 recipients of intussusception of the bowel, and many affected babies required surgery to repair “telescoping” of the gut. Several died. Months after being licensed, the vaccine was taken off the market.
http://www.cdc.gov/mmwr/preview/mmwrhtml/mm4843a5.htm
- 1998-2001: Lymerix vaccine likely caused autoimmune symptoms, taken off market
https://www.ncbi.nlm.nih.gov/pmc/articles/PMC2870557/pdf/S0950268806007096a.pdf
- 2009-10 Pandemrixswine flu vaccine caused over 1300 cases of narcolepsy in Europe
Children aged 5-19 were about 15 times more likely to develop narcolepsy if they received the GSK Pandemrix brand of swine flu vaccine, which was not sold in the US. Other age groups were also at an increased risk of narcolepsy, but to a lesser degree. Narcolepsy is caused by autoimmune destruction of cells in the brain’s Locus Ceruleus, and is newly recognized as a vaccine adverse reaction. The narcolepsy cases were severe, often preventing children from attending school.
https://www.sciencemag.org/news/2015/07/why-pandemic-flu-shot-caused-narcolepsy
http://ecdc.europa.eu/en/publications/publications/vaesco%20report%20final%20with%20cover.pdf
http://www.cdc.gov/vaccinesafety/Concerns/h1n1_narcolepsy_pandemrix.html
** The adverse effect profile of drugs and vaccines is generally not well known until millions of people have received the drug or vaccine. New federal legislation (21st Century Cures Act of 2016 etc.) that speeds up licensing of vaccines, and removes liability from the manufacturers for all vaccines placed on the childhood schedule, all vaccines recommended by CDC for pregnant women, and new, potentially unlicensed products used during declared emergency situations — increases the potential risk of vaccines. http://www.fda.gov/RegulatoryInformation/Guidances/ucm125127.htm#categories
http://en.wikipedia.org/wiki/Public_Readiness_and_Emergency_Preparedness_Act
February 12, 2022
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | United States |
Leave a comment
A FRIEND of my ex-wife is so angry about lockdown lunacy and its associated abuses that she lets rip on busloads of cowed, mask-wearing passengers, letting them know they have been horribly duped.
I thought of her yesterday when I saw a large caravan parked in the centre of Worthing, the seaside town where I currently live, encouraging passers-by to drop in for a Covid jab.
Despite waiting lists now said to be likely to hit nine million, the NHS still finds the money to try to terrorise people into submitting to this experimental procedure. I am happy to say there were no customers as I passed.
Just how experimental the rollout remains is brought home by a new international study looking at what happens in our bodies when injected with the mRNA vaccines made by Pfizer and Moderna, and comparing that with natural infection. A 73-page report, with 43 authors, has been posted online as a preprint by the scientific journal Cell.
A key finding is that for up to two months following the jab, our bodies continue to produce a protein that has been associated with risks to the heart and blood vessels. It may be longer – 60 days was as far as the researchers went.
Most readers are by now familiar with the infamous spike protein, the ‘gain-of-function’ feature through which American and Chinese scientists made a bat virus a danger to humans, causing the Covid-19 pandemic.
The vaccines inject copies of a genetic code that causes production of this protein, alerting the immune system to the danger it presents so as to limit damage from actual virus infection. The Cell study confirms that in the short-term, the immune system response to the vaccine is broader than that seen in severely ill, naturally-infected patients.
But the researchers found mRNA from the vaccine still present on days seven, 16 and 37 post-jab, ‘with lower but still appreciable specific signal at day 60.’ Production of actual spike protein was ‘abundant’ 16 days after the second dose, and still present as late as 60 days.
Ninety-six per cent of vaccinees had the protein circulating in their blood in the first day or two after the jab, and 63 per cent at day seven, although the level fell dramatically during that first week.
What does this mean? According to Dr Robert Malone, an American virologist and immunologist whose work paved the way for mRNA vaccines, it means we are in the midst of a ‘health public policy nightmare’.
That is because the protein is now recognised as a danger in itself, regardless of the virus. The fact that it continues to be produced for weeks or months after the jab helps to explain the record numbers of reports of post-vaccination deaths and injuries.
Once in the bloodstream, the genetic instructions are carried throughout the body, and cells that line our blood vessels are particularly prone to taking it in. When they produce the ‘spike’, lymphocytes of the immune system recognise it as foreign and start attacking the cells, provoking the formation of blood clots of varying sizes.
Studies in patients who have died post-injection have shown how the lymphocytes infiltrate heart muscle in particular, causing inflammation. Lungs, liver, kidney, uterus, thyroid and skin appear vulnerable to a similar reaction.
Cardiac surgeon Dr Steven Gundry has reported that in the wake of the jab, most patients show changes in biochemical markers signalling damage to the heart and circulatory system.
‘These changes persist for at least two and a half months post second dose of vaccine,’ he said in a November 2021 alert to the American Heart Association.
‘We conclude that the mRNA vaccines dramatically increase inflammation of the endothelium and T-cell infiltration of cardiac muscle and may account for the observations of increased thrombosis, cardiomyopathy, and other vascular events following vaccination.’
His alert prompted a big reaction from some fellow professionals and a watered-down version appeared soon afterwards.
But a similar warning was issued as far back as last June by Canadian vaccine expert Dr Byram Bridle, who used freedom of information laws to obtain a previously confidential ‘biodistribution’ study in animals, conducted for Pfizer by Japanese researchers. It showed that the spike protein does not just act at the site of the jab, but is carried through the circulation to many sites in the body.
‘I’m very much pro-vaccine, but always making sure that the science is done properly and that we follow the science carefully before going into public rollout of the vaccines,’ Bridle said. With Covid, the rollout was a big mistake, he added. ‘We didn’t realise that by vaccinating people we are inadvertently inoculating them with a toxin.’
He said it was now known that ‘the spike protein, on its own, is almost entirely responsible for the damage to the cardiovascular system, if it gets into circulation. Indeed, if you inject the purified spike protein into the blood of research animals, they get all kinds of damage to the cardiovascular system, and it can cross the blood-brain barrier and cause damage to the brain.’
At first glance that might not seem too disconcerting, he said, because the jab was injected into the shoulder muscle. ‘The assumption, up until now, has been that these vaccines behave like all our traditional vaccines: They don’t go anywhere other than the injection site, so they stay in our shoulder. Some of the protein will go to the local draining lymph node in order to activate the immune system.’
But for the first time, the biodistribution study had allowed scientists to see where the mRNA goes after the jab. ‘In other words, is it a safe assumption that it stays in the shoulder muscle? The short answer is, absolutely not.’
Malone says the Cell findings may mean that a genetic device inserted in the Moderna and Pfizer products, aimed at avoiding immediate destruction of the mRNA by the immune system, ‘is working so well that the mRNA is completely evading the normal clearance/degradation pathways.’ Consequently, spike protein levels are even higher after the jab than seen in a person with severe Covid-19 disease.
‘That this has not been published or investigated more demonstrates the gross regulatory dereliction of duty by Pfizer, BioNTech, Moderna, NIAID VRC (the Vaccine Research Centre of the National Institute of Allergy and Infectious Diseases) and that whole crew … I do not know how to write this more strongly.’
February 12, 2022
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine |
Leave a comment
ADDING vaccines to countries’ immunisation schedules is meant to be the function of expert advisory groups. It can also be influenced by lobbying, sponsored by industry, to create the perception of a public demand for increased access to certain vaccines.
Indeed, many of governments’ senior medical and scientific advisers have close links with, or interests in, pharmaceutical companies and the crossovers are multiple.
Take a closer look for instance at the Supporting Active Aging Through Immunisation (SAATI) partnership. It was founded in 2011, as the so-called Decade of the Vaccine began, at the instigation of the Confederation of Meningitis Organisations (CoMo).
In 2013, SAATI entered into a collaboration agreement via a memorandum of understanding with Vaccines Europe. This organisation was previously known as European Vaccine Manufacturers, the vaccines specialist group within the European Federation of Pharmaceutical Industries and Association.
A 2014 SAATI report calling for more adult immunisation was prepared by Hill and Knowlton, the international PR agency and funded by Pfizer.
Professor Dr Javier Garau, chair of SAATI, said: ‘As we get older, the immune system weakens, increasing our risk of contracting infectious diseases. Furthermore, acquired immunity to certain infections (tetanus, whooping cough, diphtheria) declines with age; due to this, vaccination and revaccination are a particularly relevant prevention strategy for adults.
‘We are determined to engage with all relevant stakeholders to make life-course immunisation the norm as part of healthy ageing, public health or prevention strategies.’
The acquired immunity Garau speaks of comes from vaccines and the decline in protection over time is called secondary vaccine failure. Vaccines do not confer lifelong immunity. As the protection conferred fades, more vaccination is required.
CoMo was created in 1994 and receives funding by Pfizer, Sanofi and GSK. One American charity affiliated to it, the Emily’s Dash Foundation, successfully lobbied the US Centres for Disease Control and Prevention (CDC) to lower the age at which children could be given a meningitis vaccine.
CoMo receives additional financial support from the Coalition for Life-Course Immunisation (CLCI)whose individual sponsors include MSD, Sanofi-Pasteur and Vaccines-Europe and whose members are Moderna, Sanofi-Pasteur, MSD, Novavax, Pfizer, Seqirus, Takeda and VBI Vaccines.
Seqirus is under contract with the Biomedical Advanced Research and Development Authority, a US government agency, to develop next-generation self-amplifying mRNA vaccines for influenza. It is also developing new Covid-19 vaccines using technology that purports to have fewer side-effects than first generation mRNA gene therapy vaccines.
The World Bank has now ‘financialised’ epidemics and pandemics through bond issues, making them a vehicle for profit that entrenches their permanency. Vaccine bonds were introduced in 2011 to finance GAVI. In 2017, before we’d even heard of Covid-19, a pandemic bond and a finance facility had been introduced. In May 2021, 750million dollars in Covid-19 vaccine bonds underwritten by the Rockefeller-linked JP Morgan Bank were released.
‘No one in the world is safe from the threat of Covid-19 until everyone is safe,’ said Seth Berkley, chief executive of the GAVI Alliance. ‘And this transaction will help us supply lower-income countries with the vaccine doses they need to roll back the pandemic in its most acute phase.
‘Proceeds from the bonds will also strengthen GAVI’s continuing support for its core vaccine programmes to ensure that routine immunisation does not fall behind and hard-earned gains against vaccine-preventable disease are not lost.’
All but the very poorest countries are expected to take on additional debt burden to purchase and distribute the vaccines. By June 2021, reluctant to do so, developing countries had only availed themselves of 3.9billion dollars of the 100billion dollars the World Bank had set aside to finance Covid vaccines.
It is hard to see Covid-19 vaccines as anything other than a cash cow for the industry. In February 2021, two months after the UK’s watchdog Medicines and Healthcare products Regulatory Agency (MHRA) issued a temporary use authorisation for Pfizer’s vaccine, the firm’s chief financial officer, Frank D’Amelio, told investors the profit margin for the vaccine was in the upper 20 per cents.
That was based on what he called ‘pandemic pricing’ – charging 19.50 dollars per dose compared with a normal price of up to 175 dollars. He added that the percentage could go higher depending on economies of scale.
Pfizer chief executive Albert Bourla said ‘a durable Covid-19 vaccine revenue stream like is happening in flu’ was likely for the firm, because booster shots would be needed and emerging variant strains would have to be countered.
The Covid vaccines, smashing conventional wisdom, were cleared for use in what were meant to be exceptional circumstances. Bourla said: ‘I believe the Covid thing has created a new normal.’
Even at discounted ‘pandemic pricing’ levels, the financial bonanza for the firm was astronomical. In November 2021, Pfizer executives told institutional investors the 39billion dollars in revenues from its Covid-19 vaccine accounted for 44 per cent of its record 88billion dollars total revenue for the year.
In the euphoria following the granting of emergency use authorisations for the Covid vaccines and the huge profits, many new vaccines are being planned and industry expectations have been raised.
As I mentioned in Part 1 of this investigation, the international health policy expert William Muraskin warned in 2017 that ‘an all-out war on microbes is being planned right now by eradication proponents who intend to prevail regardless of developing-country governments’ or their peoples’ choices.’
Like the ‘war or terror’, it was an open-ended concept, ambiguous and useful to justify a range of actions.
Muraskin argues that vaccination has been prioritised at the expense of, and to the detriment of, the already limited resources of the health systems of developing countries.
Covid-19 has now hijacked the resources of the industrialised world’s health systems and undermined their economies in an unprecedented way. Israel has just authorised its fourth booster in a year, even as the toll of adverse events and deaths mounts in their wake. It is now evident that the revenue stream is for the time being more ‘durable’ than any protection derived from the vaccines.
The public health agenda was long ago seized by private interests. The campaign to eradicate Covid-19 and other diseases through vaccination reflects the biases of GAVI, the Vaccine Alliance partners, and more especially those of its founders.
The rationale may be questionable, but the approach is certainly lucrative. Eradication appears a fools’ game, but one in which we will all be forced to participate if vaccination passports become a permanent mechanism for accessing our everyday lives.
As of 2013, a pipeline of 120 new vaccines was in development and only half were directed at tropical diseases afflicting developing countries. There are more now.
How many of these are destined to be added to national immunisation schedules and indiscriminately used? How many might become mandatory? Society needs a wider debate on the merits of the war on microbes before it sweeps us all away.
February 11, 2022
Posted by aletho |
Corruption, Science and Pseudo-Science, Timeless or most popular | COVID-19 Vaccine, GAVI |
Leave a comment
[Note: This essay is abstracted from my eBook Myths: Widely Held But False Beliefs In The Climate Change Crisis, available on Amazon]
In their Fifth Assessment Report the IPCC, the ‘internationally accepted scientific authority on climate change’, gave their opinion of how much of the recent global warming was caused by human activity: ‘It is extremely likely [95-100 percent confidence] more than half of the observed increase in global mean surface temperature from 1951 to 2010 was caused by the anthropogenic [i.e. man-made] increase in greenhouse gas concentrations and other anthropogenic forcings together’. Reflecting that opinion Wikipedia states that the ‘Scientific consensus on climate change’ is that ‘the Earth is warming and… this warming is mainly caused by human activities’. It claims that 97-100% of actively publishing climate scientists endorse this opinion. Similarly, NASA claim that, ‘A consensus on climate change and its human cause exists… human activities are the primary cause of the observed climate-warming trend over the past century.’ And in an October 2020 interview on CBS’s 60 Minutes climatologist Dr Michael Mann said, ‘There’s about as much scientific consensus about human-caused climate change as there is about gravity.’ So is it actually true that 97-100% of climate scientists explicitly or implicitly endorse this key IPCC opinion?
Although science is not remotely democratic (it only needs one scientist to prove that the ‘consensus view’ is wrong and it is wrong) the fact remains that if this 97-100% consensus assertion is true then it is indeed very powerful. If the ‘internationally accepted scientific authority on climate change’ says something is almost certainly true and almost all climate scientists in the world agree then it almost certainly must be true – mustn’t it? Whilst there is undoubtedly almost total scientific consensus amongst the scientific authorities (literally dozens of scientific academies from around the world explicitly or implicitly endorse the IPCC’s opinions) that does not necessarily reflect the consensus view amongst climate scientists themselves. So what exactly is it that climate scientists agree on?
The consensus argument is epitomized by Barack Obama’s 2013 tweet that, ‘Ninety-seven percent of scientists agree: climate change is real, man-made and dangerous’. He tweeted this immediately after the publication of the most famous climate change consensus survey, Quantifying the consensus on man-made global warming in the scientific literature (John Cook et al, 2013) conducted by Skeptical Science, a small group of climate change activists, who, despite their name, are precisely the opposite of climate change skeptics (their strapline is ‘Getting skeptical about global warming skepticism’). This study examined the Abstracts from 11,944 climate science papers published over the twenty-year period from 1991 to 2011. It concluded that 97.1% of the Abstracts (that actually expressed an opinion on the causes of global warming) endorsed the view that man-made greenhouse gas emissions (or, at least, greenhouse gases) cause global warming. Although this was 97% of Abstracts, not 97% of climate scientists, it is not unreasonable to suppose that, based on this survey, about 97% of climate scientists endorse the view that man-made greenhouse gas emissions (or, at least, greenhouse gases) cause global warming. It said nothing whatsoever about how much warming those emissions were causing and whether or not such warming was ‘dangerous’. It is probably the case that at least 99.9% of people who might describe themselves as climate scientists (including those most skeptical about the climate change crisis idea) endorse the view that man-made greenhouse gas emissions (or, at least, greenhouse gases) cause global warming, i.e. some global warming. That is not in any serious dispute. The dispute is about how much global warming human activity is causing and whether or not it is ‘dangerous’. So the study revealed nothing that was not already well known and uncontroversial.
Skeptical Science summarized their findings with the statement, ‘97% of climate papers expressing a position on human-caused global warming agree: global warming is happening and we are the cause’ – where ‘we are the cause’ clearly implied ‘we are the sole cause’ instead of what it actually found, viz. that we are the cause of some of the global warming. If the study had been able to show convincingly that 97% of climate scientists endorsed the IPCC’s opinion that human activity was the predominant cause of global warming between 1951 and 2010 then that would certainly have strongly supported the view that there was almost total scientific consensus that the IPCC was right. But of all the Abstracts reviewed in this study only 0.3% explicitly endorsed that central IPCC opinion1. Even (ex-IPCC) Mike Hulme has noted that, ‘The Cook et al study is hopelessly confused… in one place the paper claims to be exploring “the level of scientific consensus that human activity is very likely causing most of the current GW [Global Warming]” and yet the headline conclusion is based on rating abstracts according to whether “humans are causing global warming”. These are two entirely different judgements.’ The recently published paper Greater than 99% consensus on human caused climate change in the peer-reviewed scientific literature (Lynas et al, 2021) claims that the consensus is actually 2% higher – but once again only actually finds a 99% consensus that human activity contributes to climate change to some extent2; in fact about 99% of the papers reviewed in this study failed to explicitly quantify the extent. A survey3 of more than 1,800 climate scientists conducted in 2015 concluded that just 43% of them would endorse the IPCC opinion about our recent predominant role in global warming (and how many of them were agreeing based primarily on their faith in the IPCC and/or their self-interest in staying ‘on message’ to the climate change crisis narrative?)
Mike Hulme has stated that, ‘Claims such as “2,500 of the world’s leading scientists have reached a consensus that human activities are having a significant influence on the climate” are disingenuous. That particular consensus judgement, as are many others in the IPCC reports, is reached by only a few dozen experts.’ Supporting that view, an independent study4 found that the views expressed by the IPCC were the consensus of a leadership cadre of just 53 (about 2%) of them, 44 of whom were very closely linked professionally, having co-authored papers with one another and so very likely to share the same opinions. The author of the study, John McLean (climate data analyst at the Australian Climate Science Coalition and an Expert Reviewer for the IPCC’s Fifth Assessment Report), concluded that ‘Governments have naively and unwisely accepted the claims of a human influence on global temperatures made by a close-knit clique of a few dozen scientists, many of them climate modellers, as if they were representative of the opinion of the wider scientific community.’
One of the most comprehensive reviews5 ever performed of surveys of the scientific consensus on climate change concluded:
- The articles and surveys most commonly cited as showing support for a ‘scientific consensus’ in favor of the catastrophic man-made global warming hypothesis are without exception methodologically flawed and often deliberately misleading.
- There is no survey or study showing ‘consensus’ on the most important scientific issues in the climate change debate.
- Extensive survey data show deep disagreement among scientists on scientific issues that must be resolved before the man-made global warming hypothesis can be validated. Many prominent experts and probably most working scientists disagree with the claims made by the United Nations’ Intergovernmental Panel on Climate Change (IPCC).
So what is the real scientific consensus on climate change? There is almost total scientific consensus that carbon dioxide concentrations in the atmosphere are increasing, that that increase is predominantly due to human activity, that the climate system is warming, that climate change is happening and that human activity has contributed to some extent to the warming, changing climate. Note again that skeptical scientists, like Dr Roy Spencer and Dr Judith Curry and Dr Richard Lindzen, are part of this ‘scientific consensus on climate change’; the idea that they constitute the 3% of scientists who do not support the scientific consensus on climate change is a false idea, misrepresenting what the ‘scientific consensus on climate change’ actually is6. This misrepresentation is designed to bolster the ‘climate change crisis’ narrative and to marginalize and neutralize the skeptical scientists by making their views appear to fall far outside the overwhelming consensus view, even though they actually share that consensus view. Basically, the ‘consensus’ breaks down over the issue of whether or not human activity has been predominantly responsible for recent warming – and whether or not that warming is ‘dangerous’. The power of the false ‘97% scientific consensus that human activity has been predominantly responsible for climate change’ meme, perpetuated by Wikipedia, NASA, Facebook (and many others) is that it can be used very effectively to strangle at birth any debate about the science. As Dr Richard Lindzen has put it, ‘The claim is meant to satisfy the non-expert that he or she has no need to understand the science. Mere agreement with the 97 percent will indicate that one is a supporter of science and superior to anyone denying disaster. This actually satisfies a psychological need for many people.’
So if we return to Dr Michael Mann’s statement that, ‘There’s about as much scientific consensus about human-caused climate change as there is about gravity’ this is very disingenuous. Whilst there is almost total scientific consensus that climate change is ‘real’ and happening and that there has been some human-caused influence, there is no such scientific consensus over the extent of the human-caused influence and whether or not it could reasonably be described as ‘dangerous’, let alone a ‘crisis’.
References
1 Legates et al. (2015), Science & Education and ‘Consensus? What Consensus?’, GWPF Note 5, thegwpf.org, September 2013 and ‘Richard Tol’s Excellent Summary of the Flaws in Cook et al. (2013) and ‘The Infamous 97% Consensus Paper’, wattsupwiththat.com, 26 March 2015 and ‘The Cook ‘97% consensus’ paper, exposed by new book for the fraud that it really is’, wattsupwiththat.com, 12 March 2016
2 ‘Cooked Up Consensus: Lynas et al “Should Rather Be Classified As Propaganda, Bad Science”’, wattsupwiththat.com, 26 October 2021
3 Bart Strengers, Bart Verheggen and Kees Vringer (2015), Climate Science Survey, Questions and Responses, PBL Netherlands Environmental Assessment Agency, pp 1 – 39
4 ‘Prejudiced authors, prejudiced findings’, John McLean, (Science and Public Policy Institute), July 2008
5 Why Scientists Disagree About Global Warming (2015) – Craig D. Idso, Robert M. Carter, S. Fred Singer
6 ‘Study: 3% Contrarians Derailing the 97% Climate Consensus’, wattsupwiththat.com, 18 December 2021
February 11, 2022
Posted by aletho |
Book Review, Deception, Science and Pseudo-Science, Timeless or most popular | Facebook, IPCC, NASA, Obama, Wikipedia |
Leave a comment
It shouldn’t be needed, but it is. Florida governor Ron DeSantis has introduced a patient protection bill, so that ‘if you’re in a hospital or long-term care facility, you have a right to have your loved ones there present with you.’ Every other state and country will hopefully follow. Some places have even prevented the dying from dying in the company and warmth of loved ones.
Reacting to the Governors bill, Brownstone scholar Dr. Jay Bhattacharya tweeted:
“Perhaps the cruelest lockdown policy: preventing people from visiting their sick loved ones in hospitals or long-term care facilities”
Many people commented on that post. The stories came pouring in. Among the many, here are some:
“No perhaps about it… it was heartless, ineffective and cruel. I lost my mother during this; I am not sure I can ever forgive the hospital policy makers for this.” – Danny Peoples, USA (@Danny99634068)
“We were allowed to see my mom for 5 minutes the day of her death. 2 by 2, though. We couldn’t be with her all together as a family. The 9 weeks prior she suffered alone in ICU surrounded by people in space suits. No visitors. She never had Covid. She died with no dignity.” – ClownBasket (@ClownBasket)
“My grandma passed away in May 2020. The last time the family saw her was outside the window at her assisted living facility, unable to actually speak due to her difficulty hearing.” – Analytical Badger, Wisconsin (@BadgerStats)
“My mom got kicked out of the hospital by security (in FL, only 6 months ago) trying to visit my dad on Day 3 of his hospital stay. They assured her they were taking care of him. He passed from a heart attack 2 days later. The lack of allowing for patient advocacy is sickening.” – Psyche’s Dagger (@PsychesDagger)
“My grandma didn’t deserve her last ten months of isolation.” – Mark Changizi (@MarkChangizi)
“I’ll never be over my blind father having to advocate for himself alone in a hospital for 3 1/2 weeks. Never. I have his messages of pure fear.” – Jennifer Hotes, Seattle, WA (@JenniferLHotes)
“I was in hospital, heart attack in BC a year ago. Scariest moment in my life, [they] wouldn’t let my wife visit me.” – hear.the.truth.now, Penticton, BC, Canada (@MandelbrotG)
“How I wished Mass General Hospital would have done things differently. An old woman wanted her husband to accompany her upstairs for a doctor appointment, but MGH wouldn’t allow it. She was nervous and terrified. I will never forget what they did to people.” – Fibci, MA (@Fibci2)
“No fan of DeSantis but currently some hospitals in CA prohibit someone from seeing their depressed spouse, family members from coming in to help a mildly delirious loved one, kids from seeing their parents unless they’re gravely ill. Even if family’s vaxed x3… It’s not right.” – James Lim, MD, Southern California (@JLimHospMD)
“Agreed. My dad walked into a hospital last year and came out on hospice because my mom was not allowed to see him.” – Tia Ghose, San Fransisco, CA (@tiaghose)
“My wife’s abuelo was taken out of his Bogota apartment by men in hazmat suits, not allowed to say goodbye to his wife of 50 years, died alone in hospital, funeral in a parking lot. When abuela got covid they didn’t call the hospital. She stayed home. Everyone got to say goodbye.” – Team Sweden (@SwedenTeam)
“In New York, my 84-year-old mother had sepsis. We had to literally drop her off at the door. She was unable to advocate for herself and we were not able to speak with her for days. It was incredibly hard to reach her doctor or a nurse. It was an unmitigated disaster.” – thedatadon, Florida (@thedatadonald)
“Our good friend was only 44 and had no idea he had stage 4 colorectal, liver, lung, and lymphatic cancer. He fought as long as he could but none of us were ever able to see him in his final days in the hospital. Final months really. One visitor per day. Today is his birthday.” – Dave (@Dave31952257)
“My vaccinated Dad wasn’t able to go see his vaccinated Mom (my Grandma) last Mother’s Day because of a ban on “non-essential” travel between Quebec and Ontario. She died 2 days before the ban was lifted. Her brother was killed by Nazis. Lest we forget.” – Adam Millward Art, Montréal, Canada (@nexusvisions)
“My aunt died in an empty hospital in Amarillo from breast cancer in late 2020. She was so scared of the virus she didn’t go to the doctor until her breast literally started to atrophy and she collapsed. No visitors. I had to help her son sneak in to see her and we were kicked out.” – razumikhin (@cw_cnnr)
“I’m afraid to let my family members [be admitted] to the hospital. Not afraid of covid at all, we’ve all had it, but worried about having family isolated and no one to advocate for them.” – Donna H, Pleasant Grove, Utah (@Donna_H67)
“My dad was in assisted living, in good health except unsteady on his feet. When prolonged Covid restrictions prevented any of us, his family, from visiting, and kept him confined to his room even for meals, he told an aide ‘This is no way to live’. 10 days later he went to Heaven.” – Tray Shelley, (@tlsintexas)
“Yesterday my husband’s cousins were not allowed in the hospital where their mother was dying (non-covid related). It was unexpected and it is obscene that they were unable to say goodbye. They needed it and she needed it.” – Yada yada yada (@3girlsmommd)
“This brings me to tears because I worked in a nursing home through the pandemic, and it broke my heart that dying patients couldn’t have their families with them! We had to be their family, but it was tragic!” – Jean Walker (@JeanWal33859349)
“The people who will remember the (fear) pandemic response the most are not people who got sick and recovered, but rather people barred from seeing their loved ones who died while hospitalized.” – Dr. NotWoke Setty, Tampa, FL (@hsettymd)
“I had to fight the VA, hospital administrators and threaten to sue to bring my father home. He passed quietly with my Mom next to him, surrounded by family. It breaks my heart that our most precious population has been treated so cruelly.” – Sherry (@sherryande)
“My father had pancreatic cancer. We were forced to leave his bedside due to the lockdown he was alone his final days the hospital called in his final moments but when we got there he was gone. He died alone. Tomorrow is his birthday.” – foodforlife123456 (@foodforlife1231)
“In December 2020, my wife took a prayer blanket to the hospital that she had made for her mother in the hospital. No one in the hospital would come to take it to her room. She died the next day which was Christmas morning while our girls were opening presents.” – Postman, Texas (@postman2421)
“I couldn’t visit my Dad in the hospital for 2 weeks before he died. I was “allowed” to see him the day he died but it was too late.” – Gary (@gmangehl)
“I work with dementia residents. For a year and a half these residents couldn’t communicate with their families because they weren’t capable of phone calls or window visits. That is a long time for someone with dementia. They deteriorate further or pass in that time. So inhumane.” – paige (@pgs300)
“My mom passed away in April of 2020 at a retirement home. She was 102, in surprisingly good health, but declined immediately following the lockdown. The facility did break rules to allow family in to be with her over her last week or so. There was no opportunity for a funeral.” – Prickly Mystic (@MysticPrickly)
“My grandma has been dying in hospital for about a week with us waiting in the lot begging to visit for five minutes. No. I think she’s simply losing the will to live. Genuinely wonder how many excess deaths are deaths of despair and loneliness.” – goldnecklace (@goldnecklace2)
“In 2020 Melbourne my mother was in residential care. Our first lockdown took her mind. When I saw her after this, she didn’t know who I was. We were then locked down for a second time. This second lockdown took her life. Cruel and unnecessary.” – HegelOrHegel (@HegelorHegel)
“I have seen this firsthand in the nursing facilities I go to. So many of my patients died from sheer loneliness. It has been incredibly hard for me as a behavioral health provider to witness. Kudos to Gov Ron DeSantis for making sure this doesn’t happen in Florida.” – Dr Deepan Chatterjee, Maryland (@DrDeepChat007)
“I live in BC, Canada; my elderly aunt literally starved when her daughters weren’t allowed to see her and help her eat, went from 100 to 71 lbs. and admin kept telling my cousins she was ‘fine’. Finally concerned care aides contacted them to tell them she wasn’t fine.” – Marion Ambler, Vancouver, Canada (@MarionAmbler)
“I brought my Dad who has dementia to see my stepmom in a rehab facility during the lockdowns. Luckily, she had a first-floor room with a window. We stood outside in the POURING rain talking to her. He was so confused and mad that she wouldn’t let him in.” – Kfaria (@Kfaria8)
“I wasn’t able to see my grandma before she died. My dad luckily was, but his brother was not. He stayed in town for weeks hoping they’d let him see her. They said if she went into a critical condition, they’d let us see her. They never did. She died alone.” – Marie (@mariecaun)
“A family member died of cancer during one of the many lockdowns in Canada. No one was allowed to see him. His funeral was only allowed to be 10 people. It’s like their lives didn’t matter. So so sad.” – Fern (@fern_forrest_)
“I worry constantly that my 87-year-old blind mother will need medical treatment and she will be alone. She says she will not go for fear of not coming out. The thought terrifies me, I have many sleepless nights.” – goodnightfromthelowerlevel (@mmmaybe)
“Of everything in my ICU career, what will stick with me most is being in patients’ rooms when they died, alone, while their distraught loved ones watched through an iPad because they weren’t allowed to be in the hospital.” – Trucker Enthusiast (@_Spolar_)
“In Canada I couldn’t visit my grandmother in the hospital, but they allowed skype calls via the hospital iPad. They never charged the iPads. She died and I never got to see her even remotely.” – Vovin, Toronto, Canada (@vovin5)
“My father-in-law died alone with no last rites. We watched on zoom. He was petrified. There were no services. The following week BLM rallies in Boston started and those were totally fine. I was called a racist for being angry.” – Mom Loves Wine, Boston, USA (@Momloveswine1)
“Yep. Was prevented from seeing my Grammy for all of 2020 until her death in 2021. 99 years young. She died alone.” – Concerned Citizen, Encinitas, California (@mercury941)
“Yup. And women giving birth alone. SHAMEFUL.” – Kelley (@kelley14419438)
“Also, not allowing husbands in for important ultrasound visits to be with their wife, where there may be something wrong with the baby.” – ec47c (@ec147c)
“My elderly father had procedure in Florida hospital 2 weeks ago. Frustrated at being alone and not understanding all that was going on, he complained so much they discharged him 48 hours later. At home, next morning, his bed sheets were soaked in blood. He healed. But we had a scare.” – Ewetopian (@Ewetopian)
“My mom is in the hospital (non-covid related) and she’s only allowed 1 named visitor her entire stay. She’s been in for weeks and sobbing and depressed all day. It’s torture and cruel and is protecting no one.” – Free and Loud (@ohiogirl81511)
“Because of these monsters, my grandmother spent almost a year in isolation in her tiny room. She met her two newest great grandchildren through a window and started talking to pictures on the wall. Fortunately, we eventually got her out. Never forgive, never forget.” – Danny Hudson, Nashville, Tennessee (@FinEssentials)
“To all the nurses that snuck people in – you are HEROES.” – Divinely Placed Texan, Hillsborough County, Florida (@Maskingchildbad)
“My friend in Alabama’s dad was in assisted living facility with Parkinson’s. Family barred from seeing him from March-Aug 2020, when they received call saying he was at end of life and that ‘he had declined significantly since his fall in April’ that they had never been told about!” – Here Is Publius, Virginia (@hereispublius)
“I have an elderly extended family member who died of non-Covid reasons – who was not permitted contact with any family member during the last 3 months of her life. Because of the insanity that took over epidemiology.” – Falskerbra (@UnitedAirPR)
“My husband is going in for open heart surgery this week. I’ve had Covid and recovered. I’m being told I won’t be able to see him in the hospital while he’s in recovery. (Illinois) it’s sick and disgusting!” – plain belly sneech (@skjohns1965)
“My grandfather in law was unable to see his daughter, my mother-in-law, before she passed away from cancer. My coworker was unable to visit her daughter in the hospital and didn’t find out she had died until three days after.” – Babs, Massachusetts (@MantiB)
“My mom passed away after a month in a rehab facility after surgery 8 months ago. Only my dad was allowed to see her, only 2 hours/week. Rest of us had to wave to her through the window. She died alone. All of us were fully vaxed.” – A Parent of CPS kids, Chicago, IL (@AcpsParent)
“The nursing home tried to keep me out, but my daughter had the two of us listed as “compassionate caregivers” and they were forced to let us in. Thanks to Gov. DeSantis my mother did not die alone, and I will always, always be grateful.” – Carolyn Tackett, South Shore, Florida, (@CarolsCloset)
“My friend’s dad in Florida had to go check himself into the hospital with internal bleeding. His liver transplant was postponed. His wife crying in the parking lot. Thank God he was released, and he passed in his sleep at home. 10 people at his funeral. June 2020. Never forget.” – OrangeChickenMH (@OrangeChickenMH)
“My grandmother did not have covid. And died after a month of isolation from her family and suspected neglect. Staff too stretched thin and emotionally worn. She died two days before she was set to come home. On their 70th anniversary. She would have been 93 today.” – SAEDogmom (@SaeDogmom)
“My adult son was recently hospitalized for appendicitis; I was not allowed to see him. Fortunately, all went well, but it was very upsetting just in that minor instance. I can’t imagine if you had elderly parents or God forbid a spouse you couldn’t see in a more dire situation.” – AverageAmerican (@Average00037367)
“I had an older friend who died of prostate cancer during the pandemic. I wrote this piece as a tribute to him and so I can always remember how we treated dying people during COVID.” – Dr. Jay Bhattacharya, California (@DrJBhattacharya)
“Haven’t seen my grandma in 2 years. She lost my papa just before all this started. Married for 68 years. She was put in a home for her safety. Now she is alone and grieving on her own Broken heart. She has rapidly declined because only one person has been allowed to see her” – Karl, Vancouver, Canada (@K59096598)
“My severely mentally and physically handicapped cousin. Went in for viral pneumonia. Tested positive in hospital, moved to covid ward. No visitors allowed. Died alone, afraid and confused. Unforgivable.” – Deb (@Deb08795065)
“My 94-year-old dad with red heart problems was in a board and care home. I could only stand on the front porch luckily his room faced the street, and he didn’t have his hearing aids, so I’d have to yell. The neighbors thought I was nuts. I got to see him four a few minutes the day before he died.” – FlowerPowerKatie, Silicon Valleey, California (@nileskt)
“You can think DeSantis is wrong on so many other fronts, and he’s still right about this. Loneliness is a cruel punishment for people whose only crime is being old.” – Shannon Brownlee, Washington DC (@ShannonBrownlee)
“My best friend’s mother got sick but put off going to the hospital because she was terrified of being there alone. It got bad enough she finally went- a week later she was dead. Alone. Family wasn’t permitted to be with her even in the final hours.” – Sam M (@iamsamh2)
“Imagine how many people died because they avoided hospitals for this exact reason.” – Meredith (@Opportunitweet)
“Last time I saw my grandmother she said, ‘live your life honey’, repeatedly. I was lucky she was in a private facility that allowed visitors. The day she left this world we were having the first dinner party since the beginning of all this. I lived my life that day.” – nooneinparticular (@SweateyYeti)
February 11, 2022
Posted by aletho |
Science and Pseudo-Science, Timeless or most popular | Covid-19, Human rights, United States |
Leave a comment
Ever since I realised the devastating effects lockdowns would have all over the world, I have actively fought them. My first task, in October 2020, was hosting an interview with world-renowned epidemologist Martin Kulldorff, one of the authors of the Great Barrington Declaration, which argues for focused protection instead of blanket lockdowns.
Incidentally, Kulldorff was involved also in my first really memorable encounter with the so-called fact-checkers. Last summer the Icelandic Chief Epidemiologist said in an interview he believed herd immunity would never be reached by vaccination, only through infections. I posted a link to the interview on LinkedIn. Kulldorff shared my post, and the next thing he knew his reshare had been removed. Clearly a fact-checker hadn‘t liked what our Chief Epidemiologist said, and decided the public shouldn‘t know.
Part of my activities as an active lockdown sceptic has been managing a large and fast-growing local Facebook group, dedicated to providing a broad view of the Covid situation, including negative effects of lockdowns, and later on, growing concerns with the effectiveness and safety of mass-vaccination. This is a difficult task as we must always be very careful not to accept posts that for some reason contain material that doesn‘t comply with the worldview of the fact-checkers. We get a few strange conspiracy theories of course, but mostly the material we have to reject is simply inconvenient facts or well-argued opinions, even by respected scientists, that just happen to go against the official narrative.
Fact-checking is nothing new, and until recently it was just that, checking for facts. But since very early in the pandemic, fact-checkers have become less concerned with facts, but more, and in some cases exclusively, with censoring anything that goes against their own opinions. Every day, hundreds of such articles are published and then used to justify censorship. The following example is a typical one.
Recently, official Scottish data has shown COVID-19 infections, hospitalisations and deaths are becoming more frequent among the double-vaccinated than the unvaccinated. The latest report shows the infection rate among the double-jabbed is now double the rate for the unjabbed, and 50% higher for the triple-jabbed. Hospitalisations are higher among the double-jabbed than the unjabbed and the death rate is double. This is a concerning development and has garnered some attention from those who follow such statistics. I wrote a short Facebook post on this the other day, quoting an article discussing this development. A few days later the familiar warning of ‘false information’ had been slapped on my post.
I decided to follow up on the ‘fact check’ referred to in the warning, an article by Mr. Dean Miller, managing editor at Lead Stories, one of the agencies that frequently publish articles used to justify censorship. Mr. Miller holds an undergraduate degree in English and seems to have no science training whatsoever.
Mr. Miller begins by claiming there is a consensus among health statisticians “working independently” that vaccination reduces the probability of hospitalisation and death, and that as the vaccinated tend to be older than the unvaccinated, “amateur statisticians” often reach false conclusions based on official data. Mr. Miller then quotes an epidemiologist who suggests various factors that “may” affect the numbers. First, that the vaccinated are more likely to get tested, quoting test and trace data but providing no reference. Second, that the vaccinated tend to be older than the unvaccinated and therefore more vulnerable in general. Third, that the vaccinated may behave differently from the unvaccinated when it comes to social interactions. Fourth, that the unvaccinated are more likely to have been previously infected by the virus.
None of this is necessarily untrue. But the article provides no references showing that vaccinated people behave differently from unvaccinated people, which would make them more likely to come into contact with infected persons. We also have no way of determining if the opposite is true. In other words, this is pure speculation, for which no evidence is provided. Whether vaccinated people are more likely to get tested is speculative also and there is no data provided to back up this claim. The same goes for the claim that the unvaccinated are more likely to have been previously infected. In fact, as numerous studies have already demonstrated that infection provides strong and lasting protection, this suggestion seems highly unlikely.
So, three of Mr. Miller‘s arguments are pure speculation, unquantified and not supported by any evidence. But what about the last argument, that the vaccinated tend to be older and therefore more likely to be hospitalised or to die? This certainly looks like a valid point, since we know it is primarily the elderly who become seriously ill with COVID-19. But how valid, or relevant is this really?
To start with, being vulnerable to serious illness or death if infected has nothing to do with the probability of infection. Rather than increasing it, it might rather decrease it, as a vulnerable person might be more likely to avoid situations where they are likely to get infected. As for hospitalisation and death, the data presented in the Public Health Scotland reports is in fact age-standardised. This means the age-related probability of death is already accounted for in the statistics. Mr. Miller‘s key argument, and the only one that isn‘t purely speculative, is therefore simply invalid. It seems he either failed to familiarise himself with the methodology used, or did not understand what it entails.
The weakness of Mr. Miller‘s argumentation does not however stop him from categorically denying that comparison of infection rates is a valid indicator of vaccine effectiveness. And of course it does not prevent the media and social media using his claim, based on speculation and lack of basic understanding of the data, to censor the discussion of a disturbing development that most certainly calls for thorough investigation.
When I showed the data to a Scottish friend recently, he suggested it was of no relevance for other nations, as the Scots were genetically different from other people due to a long-standing diet of nothing but chips, Marlboros and Irn-Bru. I can only say his explanation makes just as much sense as Mr. Miller‘s do.
But Scotland is not the only country experiencing this disturbing trend. A couple of weeks ago I published an article in the Daily Sceptic discussing a similar trend in Iceland: early January data showed the double-vaccinated to be twice as likely to get infected as the unvaccinated. This undermines the aforementioned dietary explanation, as in Iceland we boil our potatoes, smoke Camels rather than Marlboros and Irn-Bru has never been available. No ‘fact check’ has yet been published trying to invalidate this data. However the already published infection rate for the unvaccinated suddenly rose by 20%, without explanation, soon after this development was pointed out.
Unfortunately Mr. Miller‘s article is not the only example of a ‘fact check’ that ignores or distorts the facts, or counters hard data with pure speculation. This sloppy kind of reporting seems to be the fact-checkers’ standard way of working when it comes to the pandemic. Some have even admitted their fact-check labels are nothing but opinion. And the general press is no exception. For example, the Scottish Herald recently published an article on this subject, also failing to acknowledge the fact that the data is age-standardised.
It is a noble endeavour to try to make sure facts rather than fiction influence public opinion. But unfortunately, it looks as if the champions of ‘fact-checking’ have little respect for facts. Most of the material they produce consists of low quality, highly opinionated articles, lacking not only references, but more importantly the clarity of thinking that must be required of anyone who takes upon themselves the important and difficult task of deciding what is true and what isn‘t.
Thorsteinn Siglaugsson is an economist who lives in Iceland. Find him on his blog.
February 11, 2022
Posted by aletho |
Deception, Full Spectrum Dominance, Science and Pseudo-Science | COVID-19 Vaccine |
Leave a comment
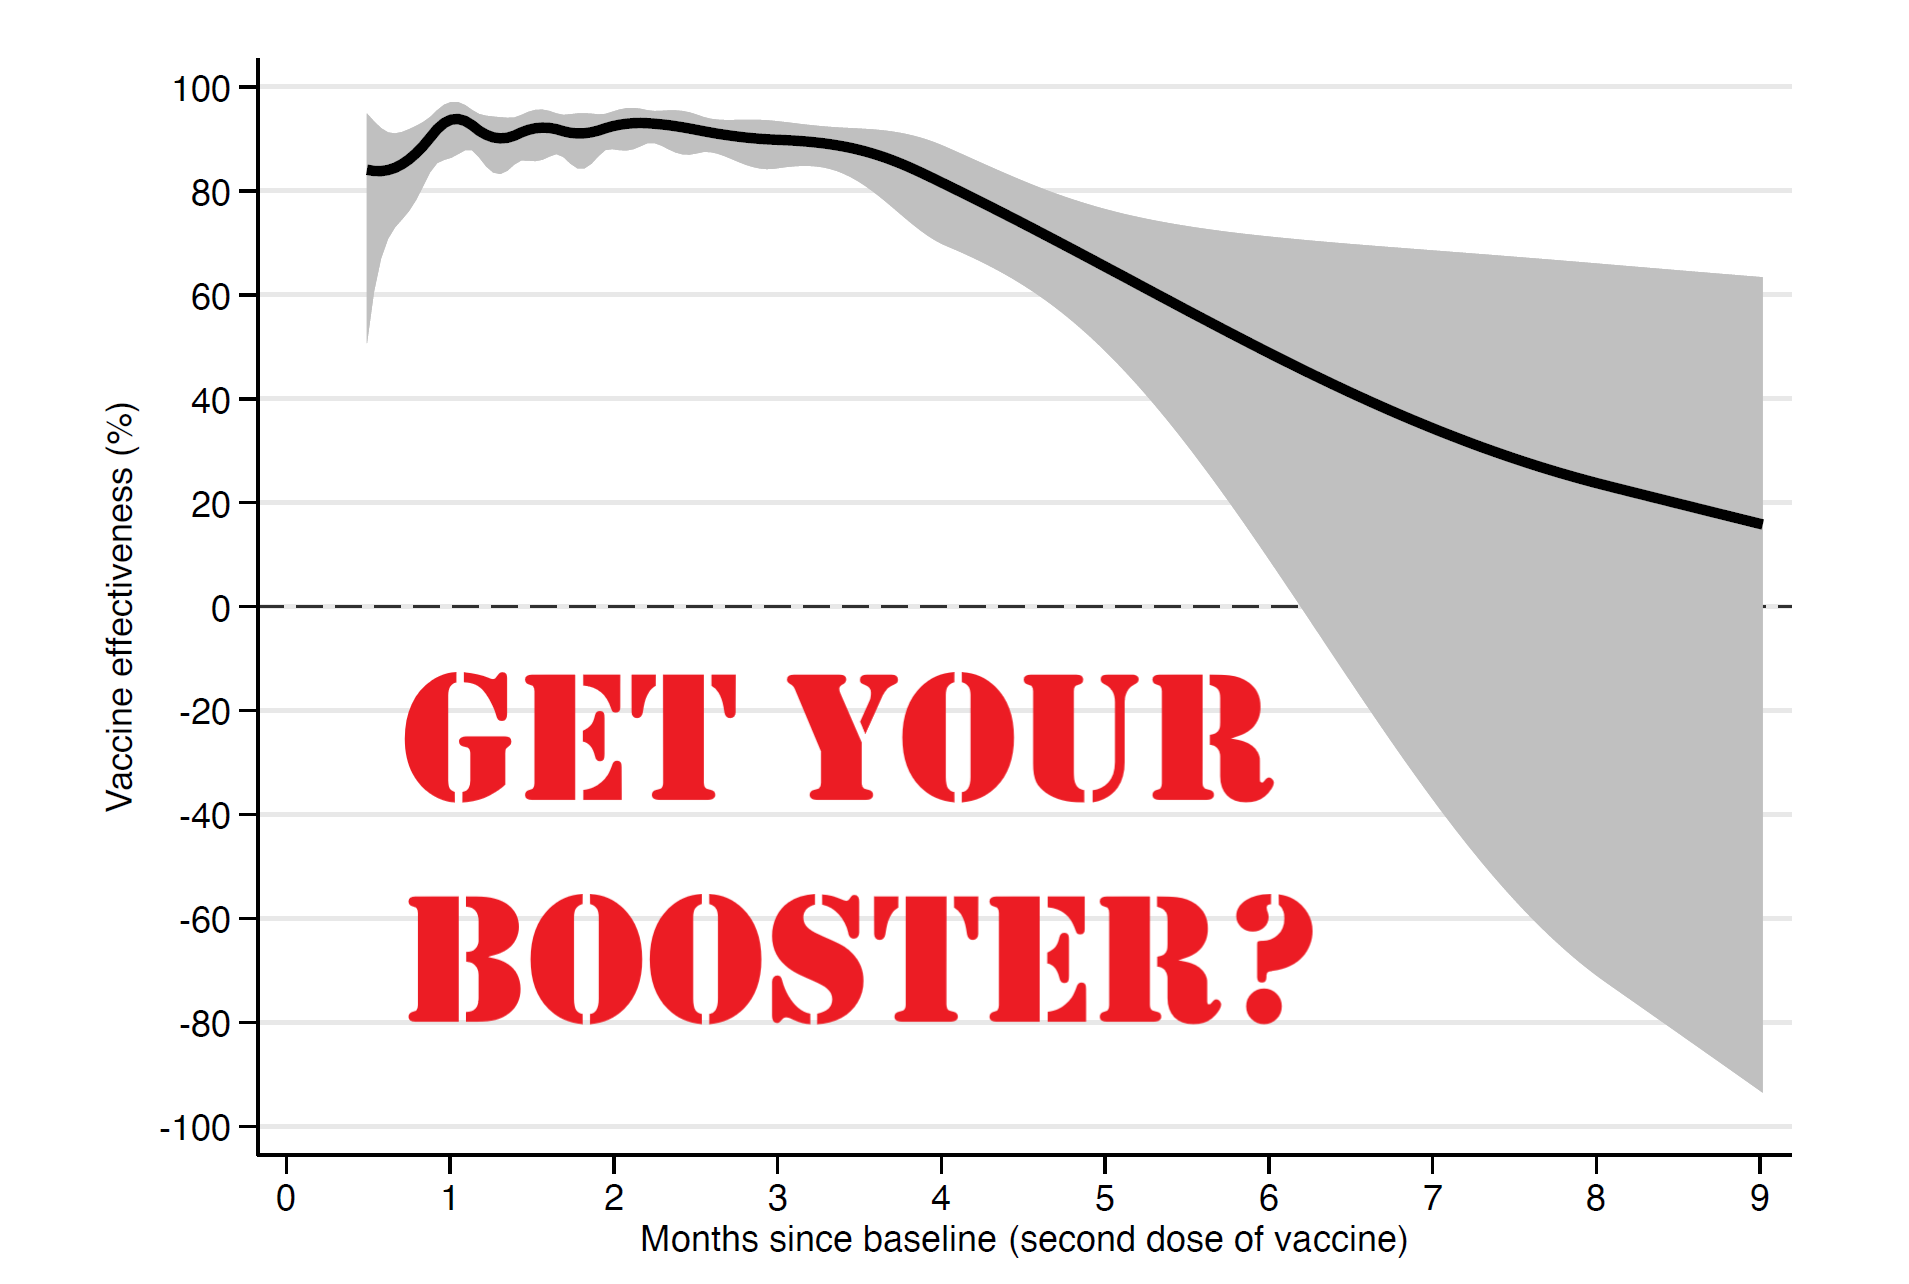


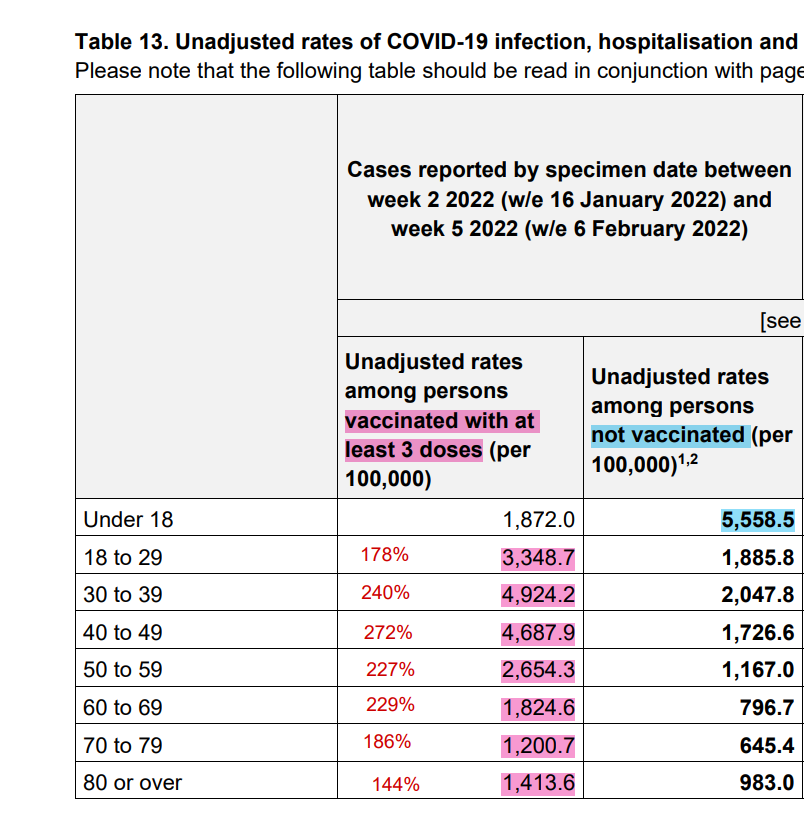
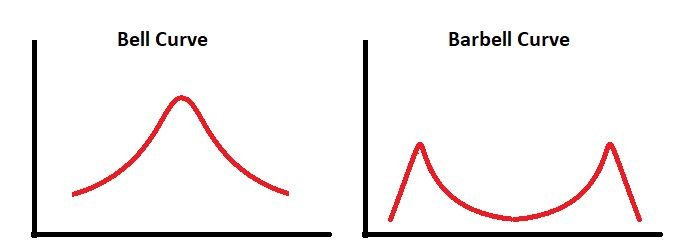
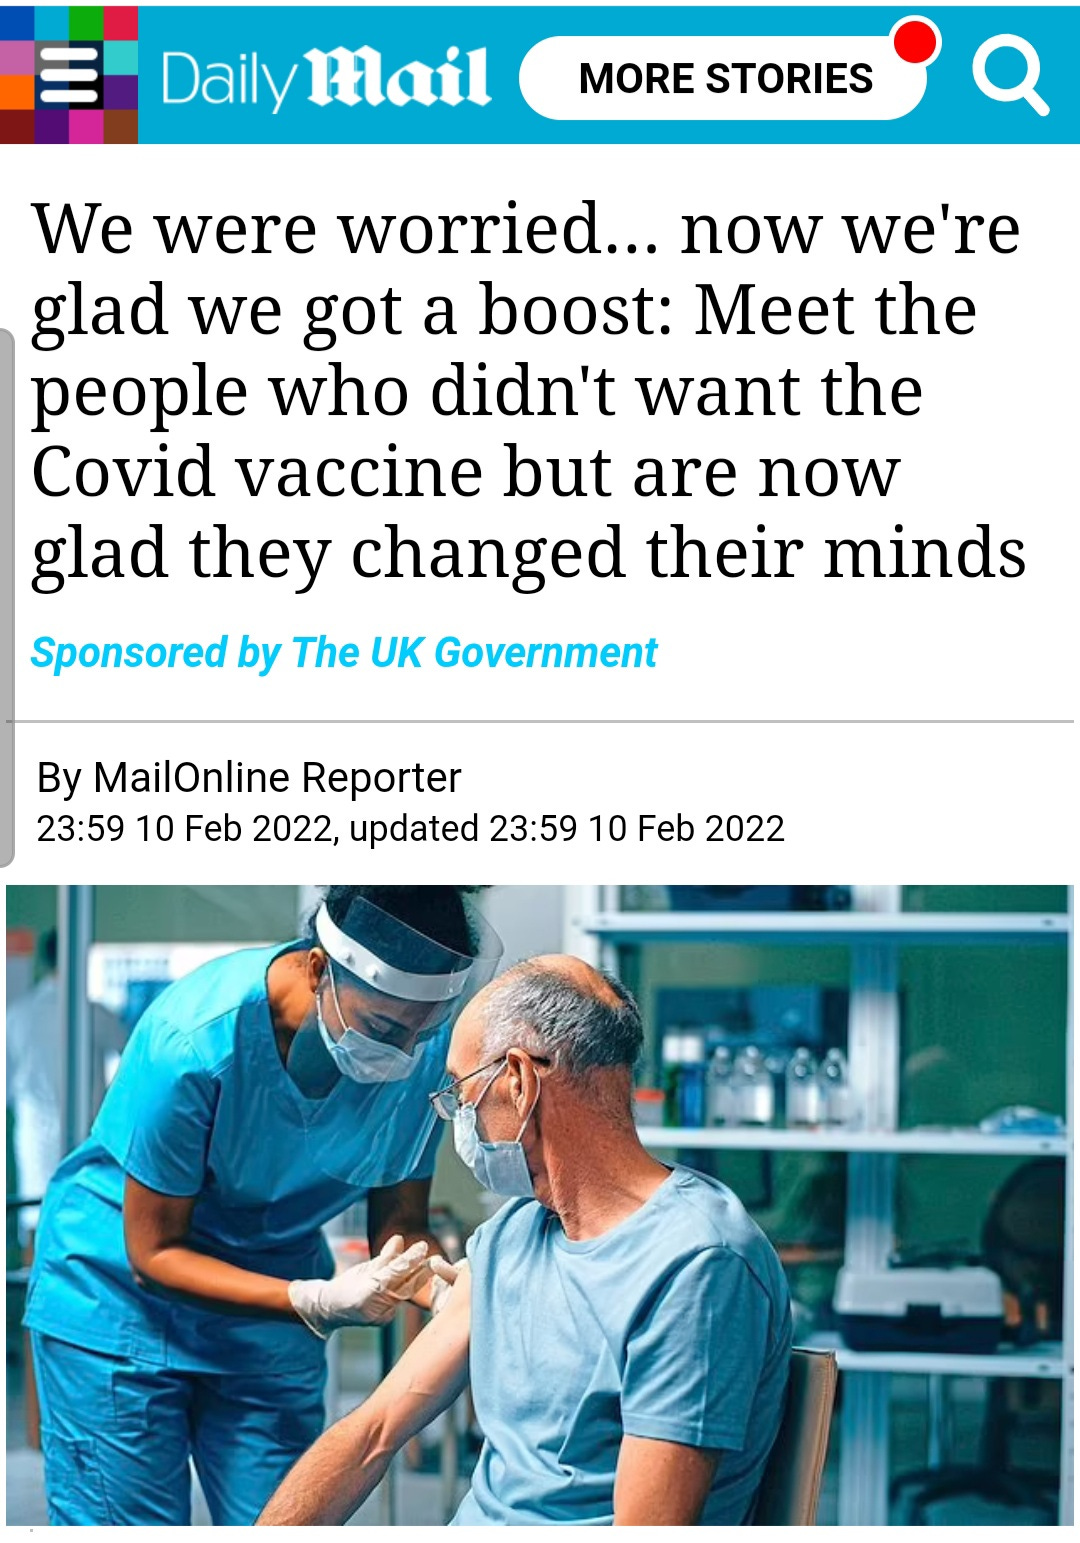


 Aletho News

