Mandatory vaccination coming soon in Marin. Your town is next.
By Steve Kirsch | January 8, 2022
Public Health Officer Matt Willis and Deputy Public Health Officer Dr. Lisa Santora speak out on requirements to get boosted. The evidence doesn’t matter and no questions will be tolerated.
Here is synopsis of Marin [county in California] Health meeting from 2 nights ago (from a parent).
Basically, the public health officers do whatever the hell they want, they refuse to answer questions from the audience, and none of this is based on solid science, and nobody can stop them. Welcome to 2022. Coming to your town soon (if not already).
Matt Willis presented charts and graphs. One was very interesting but I couldn’t take a picture in time. The majority infected are vaccinated. I believe the number 504. I believe a thousand in attendance from a source who tried to get in.
Lots of us put in questions but he answered none of them.
After that one chart showing the vaccinated getting infected more the next charts showed how Omicron has gone up and that kind of stuff.
Then Lisa Santora came on and gave the real bad news regarding the quarantine of unvaccinated students and staff and the modified quarantine of vaccinated and boosted. So per Willis you have to be boosted to be considered able to be on modified quarantine and parents have to be boosted to see their kids do sports or perform indoors. And a lot of infected have been boosted too but the efficacy of the vaccine was never called into question.
Our questions were how do you justify continuing quarantine and support for boosting if it doesn’t prevent transmission. If vaccinated and boosted spread the virus equally why are we quarantining unvaccinated or vaccinated without a booster? They never answered our questions.
Lisa Santora was super creepy and said “we expect that all students and staff are vaccinated and get their boosters”
So they prepared us for more variants with possibilities of more boosters. This pandemic keeps them relevant and in power and torturing the rest of us. Vaxxing testing masking again and again. Those are my words.
Willis said the vaccines will be mandatory in July 2022. My understanding is this will be mandated at the school year after the FDA approves the vaccines for kids so how can they even know??
When a kindergartner recently was registering the parent was told vaccines will be mandatory in July 2022. And the trials have not even been done.
CDC and FDA are being sued to release their safety data which they wanted to release in 75 years!! [ Editor’s Note: The FDA was recently ordered to speed up the timetable by 100X at 55,000 pages per month instead of 500 pages per month. ]
Is ensuring people’s compliance with future diktats the key reason for the re-imposition of masks in the classroom?
Masking is not normal and should not be normalised

Health Advisory & Recovery Team | January 8, 2022
In the week when the requirement (or is it only a ‘recommendation’?) to mask children in the classroom was reinstated, it is worthwhile to consider the likely reasons underpinning the decision to return to a restriction that is both ineffective and harmful. Undoubtedly, there has again been pressure from the education unions for pupils to cover their faces, motivated either by a baseless belief that such a measure will reduce the risk of teachers contracting the virus, or perhaps a desire to further damage Government credibility by causing more disruption in our schools. Whatever their reason, at this juncture it is timely to revisit the range of circumstantial evidence that supports what HART believes to be the most plausible reason for compelling the healthy to wear face coverings: to increase compliance with future COVID-19 restrictions and the vaccination rollout.
Prior to June 2020, public health experts did not endorse masking healthy people in the community as a means of reducing viral transmission. In March 2020, Dr Jenny Harris (England’s Deputy Chief Medical Officer) was unequivocal when she stated, ‘For the average member of the public, masks are really not a good idea’ and that ‘People can put themselves at more risk than less’. North of the border, Professor Jason Leitch (Scotland’s Clinical Director) was equally emphatic when – in April 2020 – he said, ‘The global evidence is masks in the general population don’t work’. Strikingly, in December 2020 – several months after mask mandates had been imposed in the UK – the World Health Organisation (WHO) published a document titled, Mask use in the context of COVID-19 that formed the conclusion that, ‘There is only limited and inconsistent scientific evidence to support the effectiveness of masking healthy people in the community’. Many contemporary public figures spread a similar message.
So what changed in 2020 that flipped the public health experts into a pro-mask narrative?
One thing is clear: it was not in response to the advent of robust scientific evidence showing that face coverings significantly reduce viral transmission. On the contrary, a review of 14 controlled studies, published in May 2020, concluded that masks did not significantly lessen the spread of influenza in the community, protecting neither the wearer nor others. Although it is not possible to draw an unequivocal conclusion about the reason for the volte-face, several factors are consistent with masks being deployed primarily to enhance compliance with the Government’s COVID-19 interventions.
Deborah Cohen, a medically-qualified correspondent working for the BBC Newsnight programme, stated (in July 2020) that various sources had informed her that the WHO had recommended masks in response to political lobbying, and when she put this possibility directly to the WHO they did not deny it. Also, in her book, A State of Fear, Laura Dodsworth interviewed Gavin Morgan – an educational psychologist and member of the SPI-B (the behavioural science subgroup of SAGE) – who told her that his antipathy to masks had been nullified by some colleagues in the group who believed they were useful in promoting a sense of ‘solidarity’, strengthening people’s feelings of cohesion in the collective fight against the virus.
Further support for the compliance explanation derives from an examination of the activities of the Government’s behavioural scientists who, throughout the pandemic, have recommended the use of covert psychological ‘nudges’ as a means of promoting people’s acceptance of COVID-19 restrictions and the subsequent vaccine rollout. Masking healthy people (adults and children) significantly enhances two fundamental ‘nudges’ used within this campaign. First, the exploitation of fear to promote compliance with Government diktats has been well documented. Masking people in community settings, as well as being one of the restrictions fuelled by fear, is also a powerful way of perpetuating fear. Acting as a crude reminder that danger is – purportedly – all around, face coverings will also prevent disconfirmation of anxious beliefs, preventing the wearer from concluding that our communities are now safe enough to re-engage with in a normal way. A self-reinforcing restriction; something that would strongly appeal to our ethically-compromised behavioural scientists.
Second, the awareness of ‘norms’ – the prevalent views and behaviour of our fellow citizens – can exert pressure on us all to conform, and this widely-deployed ‘nudge’ is also greatly strengthened by mask wearing. Normative pressure (otherwise known as peer pressure or scapegoating) is less effective in changing the behaviour of the deviant minority if there is no visible indicator of pro-social compliance rooted in communities. A face covering, or lack of one, enables instant recognition of the rule followers and rule breakers, thereby escalating the pressure to comply.
These observations as a whole are consistent with the premise that masking healthy people is primarily a compliance device. Clearly, widespread wearing of face coverings in community settings is an effective way of keeping the British public on board with any future restrictions the state decides to impose in pursuit of its agenda. Would the Government have so easily capitulated to union pressure to re-mask children in the classroom if this was not so?
Turning point
eugyppius | January 8, 2022
“Where’s the vaccine mandate they promised us?” whines Daniel Brössler, reporter for the Süddeutsche Zeitung, disappointed because yesterday’s Corona summit of German minister presidents returned nothing but some adjustments to quarantine and sharpened testing rules. The double vaccinated will now have to submit negative tests if they want to eat at restaurants. Markus Söder, lockdown- and vaccine mandate-loving minister president of Bavaria, criticised even these milquetoast restrictions, with some bluster about how he’d already taken a hard line against bars and discos. This is after leading German Corona astrologer, Christian Drosten, used his state media podcast to suggest that Germany should start tolerating some of degree of SARS-2 transmission, and that breakthrough infections among the vaccinated should be considered normal. Such statements, which almost surely reflect sentiments within the coalition government, destroy most of the rationale for ongoing restrictions and vaccine mandates.
Meanwhile, in Austria, the thrice-vaccinated chancellor Karl Nehammer has tested positive for Corona. The news comes as Austria announces they will delay implementing their vaccine mandate by two months. It will now take effect in April, if at all. Gerald Gartlehner, an epidemiologist and sometime governmental adviser, suggested that mandates (or at least their enforcement) might have to be re-evaluated in light of Omicron and the widespread immunity the new variant will elicit across the Austrian population. There is every reason to think that Austria will be past the peak of the Omicron wave in April, and that a majority of Austrians will have SARS-2 antibodies by then.
In the United States, former Biden advisers have published a series of editorials in the Journal of the American Medical Association, arguing that it is time to normalise containment and begin managing SARS-2 as one of various seasonal respiratory infections.
It is obvious that we are at a turning point, even if everyone has yet to realise it – even if France is sharpening vaccine requirements, even if Italy has imposed vaccine mandates for everyone over 50, and even if Canada is for the moment determined to remain a prison state. This is the first time since the Floyd riots in America, that major political leaders and public health authorities have said that preventing Corona can no longer be the highest goal of western society.
It is a commonplace observation, but a true one: Since the vaccines began to fail in August, the vaccinators have been progressing through the proverbial five stages of grief. They spent a lot of time in denial, before becoming very angry and punitive. Then they began bargaining, hoping that SARS-2 would go away after four doses, or after five, with just the right dosing intervals, with a return to double masking, with child vaccinations. Now they appear to be drifting finally into depression and acceptance. They have realised, not a second too soon, that there is nothing to be done [outside of improving personal health and early treatment protocols].
Omicron is a highly contagious variant with immune escape features. The vaccinators can vaccinate all they want, but their vaccines will not stop the waves of infection to come. A lot of the hyperbolic rhetoric about Corona was put about in the hopes that most everyone wouldn’t be infected. They thought they could terrify people for a few years, vaccinate them, and harvest their gratitude for saving them from the worst respiratory virus since SARS. Now, though, it’s clear that everyone will have personal experience with Corona infection, whether or not they are vaccinated. This will destroy popular faith measures, it will erode their confidence in the vaccines, and it will do away with their fear of the virus. Maybe a few people somewhere will still support containment, after two years of heavy restrictions, mandated vaccinations, and infection, but I doubt there will be very many of them. It’s the beginning of the end.
The climate scaremongers: Extreme weather, 1961 style
By Paul Homewood | TCW Defending Freedom | January 7, 2022
FOR several years the public have been bombarded with threats of extreme weather to brainwash them about the dangers of climate change. Every bit of bad weather is relayed by the 24/7 media, which naturally has the effect of making the public believe ‘things are getting worse’. This is then backed up by repeated claims that global warming is to blame, making such events more frequent and more severe.
As part of this propaganda onslaught, the BBC has been broadcasting a monthly Climate Check video for the last couple of years, usually presented by weatherman Ben Rich, who they hope will give a flavour of authenticity. Last month’s edition was a summary of 2021. According to the introduction: ‘Fires, floods, heatwaves and drought – 2021 has been another year of remarkable extremes around the world.’
The video then goes on to cover a heatwave in Canada, floods in Canada, Germany, China, India and Australia, Hurricane Ida, wildfires in Greece and a drought in East Africa. None of these were unprecedented, yet there was the usual sloppy assertion that global warming is making all these types of events worse. No evidence or data is given to back up these absurd claims, which are purely derived from computer models sexed up by alarmist scientists.
Is our weather really any worse than in the past? Recently I looked back at the world’s weather 50 years ago, in 1971. The weather that year was every bit as bad as anything seen either this year or in the recent past.
Was 1971 exceptional? Let’s go back to 1961 for another viewpoint.
It’s ironic that Ben Rich began last month’s report by saying ‘If anywhere in the world sums up a year of extreme weather, it’s Canada’, because he could have said exactly the same if he had been doing his Climate Check 60 years ago.
The drought that summer on the Canadian prairies was reckoned at the time to be even worse than the dustbowl years of the 1930s. Many places had received no proper rainfall for a year and a half, and harvests were devastated, as this CBC video describes.
Wildfires burned millions of acres across much of Canada in what was called at the time ‘The Angriest Summer’.
To cap it off, flash floods killed a family of five in Timmins, Ontario in August, following six inches of rain in 12 hours.
Catastrophic floods hit many other parts of the world that year. New South Wales suffered some of the worst floods in its history in November 1961, probably only surpassed by the ones in 1900. The Nepean Times reported: ‘During a week of rain in which 474mm of rain were recorded at the post office, Penrith received half its annual rainfall on two days.’
In the very same week, the BBC was reporting on flood-stricken Somalia: ‘Unconfirmed reports put the number of homeless at 300,000 . . . The Prime Minister said nearly all Somalia’s food crops have been destroyed, and said food will have to be found for about 600,000 people for eight months, until the next harvest.’
The USA was also badly affected by flooding in 1961. ‘Widespread, prolonged and disastrous’ floods hit Mississippi, Louisiana and Alabama in February and March, followed by the Midwest in May, and Idaho in June. The most tragic flood of the year was in July in Charleston, West Virginia when a small area cloudburst flood caused 22 deaths. Severe flooding also occurred in December in Mississippi, Louisiana and Alabama.
The worst floods that year in the USA were brought by Hurricane Carla in September, a Cat 4 storm with winds of 170mph, which left a trail of devastation from Texas to Illinois, including 34 dead, 1,900 homes destroyed and a record number of tornadoes.
The Atlantic hurricane season in 1961 saw two in the most powerful Category 5, Esther and Hattie, making it one of only seven Atlantic hurricane seasons to feature multiple Category 5 hurricanes in one season. Hattie devastated Belize City, damaging 70 per cent of the buildings. The damage was so severe that the government relocated inland to a new city, Belmopan.
1961 was certainly not an exceptional year and history is littered with weather disasters like these. The idea that today’s weather is any more ‘remarkable’ or ‘extreme’ is not only ridiculous, it has no basis in fact. But Ben Rich has no intention of presenting an objective account of the weather last year. His final statement gives the game away: ‘2021 has brought into sharp focus the impact that severe weather is having on peoples around the world. Limiting the rise in global temperatures to 1.5C was at the top of the agenda at COP26 in Glasgow, with scientists urging world leaders to commit to cutting greenhouse gases to stave off a climate catastrophe.’
There is just one purpose in all of this: to brainwash the public into accepting the UN’s climate agenda.
Making it up as you go along
You might have thought that when the head of the Environment Agency was giving a speech on climate change to the Royal Society he would check his facts first. Not Sir James Bevan.
The agency’s chief executive recently stood up to give a talk ludicrously titled ‘Drought risk in the Anthropocene: from the Jaws of Death to the Waters of Life’. In an attempt to show that climate change was making floods worse, he made the claim that ‘in England, three of the five wettest winters on record have happened in the last eight years’. However according to the Met Office only one of the five has occurred in that period, in 2013/14. The other four were 1876/77, 1914/15, 1989/90 and 1994/95.
Bevan also claimed that winters are wetter than in the past on average, but they were just as wet in the early 1900s.

UK Met Office
He went on to warn that climate change was making our summers drier, increasing the risk of drought. As you have probably guessed by now, summers in England are not becoming drier, or for that matter wetter. They are no different from summers in the past!

UK Met Office
Bevan worked as a diplomat all his career prior to joining the Environment Agency in 2015. His ignorant speech makes his lack of qualifications for his job glaringly obvious.
Landscapes will be altered for ever, warns National Trust!
Not to be outdone by the Environment Agency, the National Trust has just published its annual Weather and Wildlife Review. As you would expect from an organisation taken over by the far Left years ago, it carries apocalyptic warnings about the so-called climate crisis.
The report begins: ‘The climate crisis presented serious challenges for nature across the UK this year. A warm winter, low levels of rain and gale-force winds all contributed to various natural disasters, causing devastation across precious landscapes and affecting the wildlife they support.’
As usual they confuse ‘weather’ with ‘climate’.
According to the BBC, the report warns that some of the landscapes under the Trust’s control are being altered for ever as climate change makes some forms of extreme weather the new normal.
Yes, the same landscapes which have remained largely unaltered for thousands of years, other than by mankind: through the warmth of the Middle Ages and the cold of the Little Ice Age, and many other previous climate cycles, and through the huge differences which we see from year to year. Do the National Trust think we are all a bunch of idiots?
And their evidence for this absurd claim?
1) Moorland fires, due to dry springs caused by climate change.
Only one slight problem though. Our springs are not getting drier, or for that matter wetter:

2) Ash dieback – caused by ‘warmer/wetter winters’
Climate has nothing whatsoever to do with dieback, a disease caused by fungal infestation. It has been spreading rapidly across Europe since its introduction about 30 years ago from eastern Asia. It thrives in all climates – warm, cold, wet and dry.
3) Stormy weather
Storms have blown down trees since time immemorial. But just because the Met Office now give them silly names, the National Trust think they must be getting worse. In fact, the opposite is true, as Met Office data clearly proves:

Incredibly their report ends:

Isn’t it time they concentrated on their real job instead?
El Camino Hospital CMO admits that 57% of their hospitalized COVID patients are fully vaccinated
By Steve Kirsch | January 7, 2022
In an internal memo sent by El Camino Hospital CMO Mark Adams to hospital staff, he disclosed three things that nobody is supposed to know and that the mainstream press is just never going to cover.
But hey, I’m not in the mainstream press, so I will cover it.
Here are the three key admissions:
- “Currently, 57% of our hospitalized COVID patients are fully vaccinated.” In other words, a clear majority, almost 2/3 of the COVID patients in the hospital, are fully vaccinated. This suggests that the vaccines hardly work at all since this is slightly less than the vaccination rate in the area.
- “Only one patient is on a ventilator which is consistent with the evidence that the Omicron variant is more contagious but less virulent.” This suggests that all the panic and lockdowns to prepare for Omicron are insane.
- “SCC public health has issued a new order that potentially might cripple our ability to provide patient care. This is the only county in CA that is mandating that no health care worker (HCW) that is not boosted or has an approved exemption from vaccination can continue to work after January 24.” In short, in my opinion, Dr. Adams has correctly determined that Santa Clara County Health Officer Dr. Sara Cody is a complete bozo and is deliberately compromising patient safety because she can’t interpret the science correctly. He’s just making this accusation a lot more tactfully and diplomatically than I ever would. This just shows you how out of control our public health officials are. There is effectively no oversight for the reckless decisions of these people.
Kudos to Dr. Adams for telling the truth.
Here’s the memo:
MEMO
To: El Camino Health Medical Staff
From: Mark Adams CMO
Subject: COVID-19 Update
Date: January 6, 2022Colleagues:
We are now in the midst of a COVID-19 surge driven by the Omicron variant.
…
Currently, 57% of our hospitalized COVID patients are fully vaccinated. Most have underlying medical conditions such as immunocompromised. Only one patient is on a ventilator which is consistent with the evidence that the Omicron variant is more contagious but less virulent. Unlike during previous surges, our biggest challenge this time is not the patients but staffing. We are seeing many community acquired infections in our employees making it difficult to fully staff the hospitals. To help maintain adequate staffing and still maintain a safe environment for patients we have modified our isolation and quarantine policies to reflect the differences in the behavior of the Omicron variant. Anyone who is exposed but asymptomatic can continue to work unless symptoms develop without the need for testing. Anyone who becomes symptomatic and tests positive must isolate for 5 days then if asymptomatic for 24 hours may return to work without testing. For physicians who are symptomatic but need to work, we continue to offer special testing. The physician can contact the house supervisor (AHM) who will bring a test kit to the car in the parking lot, the physician swabs themselves, the AHM then delivers the test to the lab and provides the rapid test result to the waiting physician. This is only for symptomatic must work situations. (Asymptomatic testing is now in short supply so cannot always be readily available.)
SCC public health has issued a new order that potentially might cripple our ability to provide patient care. This is the only county in CA that is mandating that no health care worker (HCW) that is not boosted or has an approved exemption from vaccination can continue to work after January 24. We believe this is an overreach and is not consistent with the evolution of the effects of the Omicron variant. Hopefully, this will be reconsidered.
Because of the potential for a continued increase in hospitalized COVID-19 patients and further staffing shortages we may need to reduce/restrict elective procedures at our facilities. We are monitoring this on a day to day basis but please be prepared that this could be necessary in the near short term. We will keep you updated on that possibility.
We do have a limited supply of sotrovimab for IV infusion for high risk patients that test positive to prevent worsening symptoms. This is administered in the ED. Paxlovid distribution will be controlled by the state and has not yet been released.
The bottom line is that the “pandemic” is changing to “endemic” so will most likely be with us for an extended period of time. This means that while it is no longer an emergency or crisis it is something that we must adapt to and accept as a regular part of our health care business.
Mark Adams, MD, FACS
Chief Medical Officer, Administration Department
2500 Grant Rd, Mountain View, CA 94040
Pandemic of the unvaccinated?
Just one more thing…
Didn’t the CDC say earlier this year that this is a “pandemic of the unvaccinated”?
For example, this article from US News and World Report (July 16, 2021) says:
The head of the Centers for Disease Control and Prevention on Friday warned that COVID-19 is becoming a “pandemic of the unvaccinated.”
CDC Director Rochelle Walensky said that cases, hospitalizations and deaths from the coronavirus are increasing nationwide, adding that over 97% of new hospitalizations are in patients who are unvaccinated.
“There is a clear message that is coming through,” Walensky said at a press briefing. “This is becoming a pandemic of the unvaccinated. We are seeing outbreaks of cases in parts of the country that have low vaccination coverage because unvaccinated people are at risk, and communities that are fully vaccinated are generally faring well.”
Someone is lying to you. Hint: It isn’t Mark Adams.
Of course it is certainly possible that El Camino Hospital is a statistical outlier. But that’s a huge difference from what is claimed, so is statistically unlikely.
And for those accusing me (without any evidence) of cherry picking from confidential internal memos meant for hospital staff only, let me clarify that this is the only such memo of this type I’ve ever received. So you can’t use the cherry picking argument.
Maybe it is time for our CDC Director to start telling the American people the truth?
Nah. Not going to happen.
Sounds like the NYT is telling its readers the Biden OSHA vaccine mandate is going down
By Alex Berenson | Unreported Truths | January 7, 2022
I know the liberal judges still seem to have no idea that the vaccines don’t end infection or transmission, but they aren’t the majority.
Here’s the current lead of the New York Times article about today’s Supreme Court hearings on the mandates. It shows the conservative justices – importantly, including Chief Justice John Roberts – have serious questions about the most important mandate, the Occupational Safety and Health Administration rule that covers workers at big companies:

The OSHA mandate is clearly at the greatest risk, as it is the biggest reach both legally and medically. The Centers for Medicare and Medicaid Services mandate on health-care workers at least fits with what CMS does, and trying to protect patients from communicable disease is a worthy goal. (Too bad the Covid vaccines don’t stop infection or transmission.)
I suspect the OSHA mandate goes. What happens to health-care workers may depend on whether Roberts and Brett Kavanaugh know the science well enough to understand how useless the vaccines have become. If not, they might just decide to split the difference and allow the CMS mandate to move forward. That would be a (seemingly) reasonable decision, and Roberts likes to seem reasonable…
Instead of FDA’s requested 500 pages per month, court orders FDA to produce Pfizer COVID-19 data at 55,000 pages per month
By Aaron Siri | Injecting Freedom | January 6, 2022
On behalf of a client, my firm requested that the FDA produce all the data submitted by Pfizer to license its Covid-19 vaccine. The FDA asked the Court for permission to only be required to produce at a rate of 500 pages per month, which would have taken over 75 years to produce all the documents.
I am pleased to report that a federal judge soundly rejected the FDA’s request and ordered the FDA to produce all the data at a clip of 55,000 pages per month!
This is a great win for transparency and removes one of the strangleholds federal “health” authorities have had on the data needed for independent scientists to offer solutions and address serious issues with the current vaccine program – issues which include waning immunity, variants evading vaccine immunity, and, as the CDC has confirmed, that the vaccines do not prevent transmission.
No person should ever be coerced to engage in an unwanted medical procedure. And while it is bad enough the government violated this basic liberty right by mandating the Covid-19 vaccine, the government also wanted to hide the data by waiting to fully produce what it relied upon to license this product until almost every American alive today is dead. That form of governance is destructive to liberty and antithetical to the openness required in a democratic society.
In ordering the release of the documents in a timely manner, the Judge recognized that the release of this data is of paramount public importance and should be one of the FDA’s highest priorities. He then aptly quoted James Madison as saying a “popular Government, without popular information, or the means of acquiring it, is but a Prologue to a Farce or a Tragedy” and John F. Kennedy as explaining that a “nation that is afraid to let its people judge the truth and falsehood in an open market is a nation that is afraid of its people.”
The following is the full text of the Judge’s order, a copy of which is also available here.
UNITED STATES DISTRICT COURT
PHMPT, Plaintiff v. FDA, Defendant, No. 4:21-cv-1058-P
ORDER
This case involves the Freedom of Information Act (“FOIA”). Specifically, at issue is Plaintiff’s FOIA request seeking “[a]ll data and information for the Pfizer Vaccine enumerated in 21 C.F.R. § 601.51(e) with the exception of publicly available reports on the Vaccine Adverse Events Reporting System” from the Food and Drug Administration (“FDA”). See ECF No. 1. As has become standard, the Parties failed to agree to a mutually acceptable production schedule; instead, they submitted dueling production schedules for this Court’s consideration. Accordingly, the Court held a conference with the Parties to determine an appropriate production schedule.[1] See ECF Nos. 21, 34.
“Open government is fundamentally an American issue” – it is neither a Republican nor a Democrat issue.[2] As James Madison wrote, “[a] popular Government, without popular information, or the means of acquiring it, is but a Prologue to a Farce or a Tragedy; or, perhaps, both. Knowledge will forever govern ignorance: And a people who mean to be their own Governors, must arm themselves with the power which knowledge gives.”[3] John F. Kennedy likewise recognized that “a nation that is afraid to let its people judge the truth and falsehood in an open market is a nation that is afraid of its people.”[4] And, particularly appropriate in this case, John McCain (correctly) noted that “[e]xcessive administrative secrecy . . . feeds conspiracy theories and reduces the public’s confidence in the government.”[5]
Echoing these sentiments, “[t]he basic purpose of FOIA is to ensure an informed citizenry, [which is] vital to the functioning of a democratic society.” NLRB v. Robbins Tire & Rubber Co., 437 U.S. 214, 242 (1977). “FOIA was [therefore] enacted to ‘pierce the veil of administrative secrecy and to open agency action to the light of public scrutiny.’” Batton v. Evers, 598 F.3d 169, 175 (5th Cir. 2010) (quoting Dep’t of the Air Force v. Rose, 425 U.S. 352, 361 (1976)). And “Congress has long recognized that ‘information is often useful only if it is timely’ and that, therefore ‘excessive delay by the agency in its response is often tantamount to denial.’” Open Soc’y Just. Initiative v. CIA, 399 F. Supp. 3d 161, 165 (S.D.N.Y. 2019) (quoting H.R. REP. NO. 93-876, at 6271 (1974)). When needed, a court “may use its equitable powers to require an agency to process documents according to a court-imposed timeline.” Clemente v. FBI, 71 F. Supp. 3d 262, 269 (D.D.C. 2014).
Here, the Court recognizes the “unduly burdensome” challenges that this FOIA request may present to the FDA. See generally ECF Nos. 23, 30, 34. But, as expressed at the scheduling conference, there may not be a “more important issue at the Food and Drug Administration . . . than the pandemic, the Pfizer vaccine, getting every American vaccinated, [and] making sure that the American public is assured that this was not [] rush[ed] on behalf of the United States . . . .” ECF No. 34 at 46. Accordingly, the Court concludes that this FOIA request is of paramount public importance.
“[S]tale information is of little value.” Payne Enters., Inc. v. United States, 837 F.2d 486, 494 (D.C. Cir. 1988). The Court, agreeing with this truism, therefore concludes that the expeditious completion of Plaintiff’s request is not only practicable, but necessary. See Bloomberg, L.P. v. FDA, 500 F. Supp. 2d 371, 378 (S.D.N.Y. Aug. 15, 2007) (“[I]t is the compelling need for such public understanding that drives the urgency of the request.”). To that end, the Court further concludes that the production rate, as detailed below, appropriately balances the need for unprecedented urgency in processing this request with the FDA’s concerns regarding the burdens of production. See Halpern v. FBI, 181 F.3d 279, 284–85 (2nd Cir. 1991) (“[FOIA] emphasizes a preference for the fullest possible agency disclosure of such information consistent with a responsible balancing of competing concerns . . . .”).
Accordingly, having considered the Parties’ arguments, filings in support, and the applicable law, the Court ORDERS that:
1. The FDA shall produce the “more than 12,000 pages” articulated in its own proposal, see ECF No. 29 at 24, on or before January 31, 2022.
2. The FDA shall produce the remaining documents at a rate of 55,000 pages every 30 days, with the first production being due on or before March 1, 2022, until production is complete.
3. To the extent the FDA asserts any privilege, exemption, or exclusion as to any responsive record or portion thereof, FDA shall, concurrent with each production required by this Order, produce a redacted version of the record, redacting only those portions as to which privilege, exemption, or exclusion is asserted.
4. The Parties shall submit a Joint Status Report detailing the progress of the rolling production by April 1, 2022, and every 90 days thereafter.[6]
SO ORDERED on this 6th day of January, 2022.
[1] Surprisingly, the FDA did not send an agency representative to the scheduling conference.
[2] 151 CONG. REC. S1521 (daily ed. Feb. 16, 2005) (statement of Sen. John Cornyn).
[3] Letter from James Madison to W.T. Barry (August 4, 1822), in 9 WRITINGS OF JAMES MADISON 103 (S. Hunt ed., 1910).
[4] John F. Kennedy, Remarks on the 20th Anniversary of the Voice of America (Feb. 26, 1962).
[5] America After 9/11: Freedom Preserved or Freedom Lost?: Hearing Before the S. Comm. on the Judiciary, 108th Cong. 302 (2003).
[6] Although the Court does not decide whether the FDA correctly denied Plaintiff’s request for expedited processing, the issue is not moot. Should the Parties seek to file motions for summary judgment, the Court will take up the issue then.
Omicron Today: January 6th, positive news
By Robert W Malone MD, MS | January 6, 2022
Omicron’s feeble attack on the lungs could make it less dangerous. Kozlov M. Nature. 2022 Jan 5. doi: 10.1038/d41586-022-00007-8. Epub ahead of print. PMID: 34987210.
“Early indications from South Africa and the United Kingdom signal that the fast-spreading Omicron variant of the coronavirus SARS-CoV-2 is less dangerous than its predecessor Delta. Now, a series of laboratory studies offers a tantalizing explanation for the difference: Omicron does not infect cells deep in the lung as readily as it does those in the upper airways.”
Importance: I discussed this back on December 15th in my Substack article:
“Has Omicron shifted receptor binding specificity away from deep lung tissue? Could this be why it appears that Omicron is less severe than other variants?”
Now this has been confirmed in an animal model.
The importance of this research is also that it answers the question of whether those who have neither been infected or vaccinated will have a less severe course of disease. That answer is good news. Omicron is milder for everyone, significantly milder.
The CDC has now approved boosters for ages 12-17 years of age. Of course we all know that this age cohort, particularly young men, has significant adverse events. So, we all have to ask why is this happening? Omicron is mild, there is no need for a vaccine or a booster that does not stop transmission. In fact, there is even evidence that the vaccinated are catching Omicron more easily!
The truth is most of us have had some variant of COVID-19. But even if we haven’t, we will experience Omicron as a cold. But the vaccine has many adverse events – here are just a some of the peer reviewed literature on these side effects and death.
So, please parents – do your homework – make your decisions based on facts.
Omicron Variant (B.1.1.529): Infectivity, Vaccine Breakthrough, and Antibody Resistance. J Chem Inf Model. 2022 Jan 6. doi: 10.1021/acs.jcim.1c01451. Epub ahead of print. PMID: 34989238.
Abstract
“… Here, we present a comprehensive quantitative analysis of Omicron’s infectivity, vaccine breakthrough, and antibody resistance. An artificial intelligence (AI) model, which has been trained with tens of thousands of experimental data and extensively validated by experimental results on SARS-CoV-2, reveals that Omicron may be over 10 times more contagious than the original virus or about 2.8 times as infectious as the Delta variant. On the basis of 185 three-dimensional (3D) structures of antibody-RBD complexes, we unveil that Omicron may have an 88% likelihood to escape current vaccines.
… However, its impacts on GlaxoSmithKline’s sotrovimab appear to be mild.”
Importance:
Based on modeling, the Omicron may have an 88% likelihood to escape current vaccines.
Do I need to write more?
Age-associated SARS-CoV-2 breakthrough infection and changes in immune response in mouse model. Emerg Microbes Infect. 2022 Jan 6:1-36. doi: 10.1080/22221751.2022.2026741. Epub ahead of print. PMID: 34989330.
Highlights:
Older individuals are at higher risk of SARS-CoV-2 infection and severe outcome but the underlying mechanisms are incompletely understood. In addition, how age modulates SARS-CoV-2 re-infection and vaccine breakthrough infections remains largely unexplored. Here, we investigated age-associated SARS-CoV-2 pathogenesis, immune responses, and the occurrence of re-infection and vaccine breakthrough infection utilizing a wild type C57BL/6N mouse model.
- The study demonstrates that interferon and adaptive antibody response upon SARS-CoV-2 challenge are significantly impaired in aged mice in comparison to young mice, which results in more effective virus replication and severe disease manifestations in the respiratory tract.
- Aged mice also showed increased susceptibility to re-infection due to insufficient immune protection acquired during primary infection.
Importance:
“In mice, a two-dose COVID-19 mRNA vaccination conferred limited adaptive immune response among the aged mice which rendered them susceptible to SARS-CoV-2 infection.”
The significant adverse event profile of the genetic vaccines, combined with the more mild disease profile of Omicron has to raise the possibility that the boosters may not be good “medicine,” even for the elderly.
We will have more variants- natural immunity is robust and more broadly protective. Omicron is going to rip through the US population.
Maybe it is time to entirely re-evaluate our entire SARS-CoV-2 vaccination program?
Welcome to the new normal: 13-year-olds dying from cardiac arrest
By Steve Kirsch | January 7, 2022
Before the COVID vaccines, cardiac arrest = very rare
Before the COVID vaccines, it was very rare for a healthy 13-old-year to die from a heart attack.
After the COVID vaccines, cardiac arrest = not so rare
Now, with the rollout of the COVID vaccines, it is becoming commonplace.
Remember Jacob Clynick, the 13-year old from Minnesota who died of cardiac arrest on June 20, 2021, just 3 days after his second Pfizer shot?

Here’s his VAERS record memorializing his death. Here’s the Defender story that appeared shortly after his death.
Fast forward 6 months later, there is still no investigation into his death! See this story which appeared in the Defender yesterday. It references emails which indicate that the autopsy had been completed prior to June 28, 2021. Silence from the CDC regarding the cause of death. Seriously?!?!? Jacob dies just 3 days after the jab due to cardiac arrest and six months later, despite the myocarditis link that they admit, they cannot figure this one out? WTF? Where is the accountability?
Ernest Ramirez’s son died of cardiac arrest as well, but he was 16. Dr. Peter McCullough looked at the death records and determined the death was caused by the vaccine. No acknowledgement from the CDC. Again, where is the accountability? Does the CDC have a better qualified expert than Peter McCullough? Did McCullough goof? Well, we don’t know because nobody is talking.
I’m pretty sure there isn’t any accountability left at the CDC. They completely glossed over the fact that the causes of death of the 14 kids (age 12-17) reported in VAERS were totally unusual. Five of the 14 kids died from cardiac arrest. That’s not normal, but they didn’t say anything.
Another 13-year-old bites the dust from cardiac arrest after vaccination
For the record, here’s the latest healthy 13-year-old to die from a heart attack.
Although this happened 6 months after his second shot, as we learned from the Bhakdi study, death from the vaccine can still happen 6 months after the shot. And we learned from that study that unless you know what to look for, the medical examiner is almost sure to miss the cause of death.
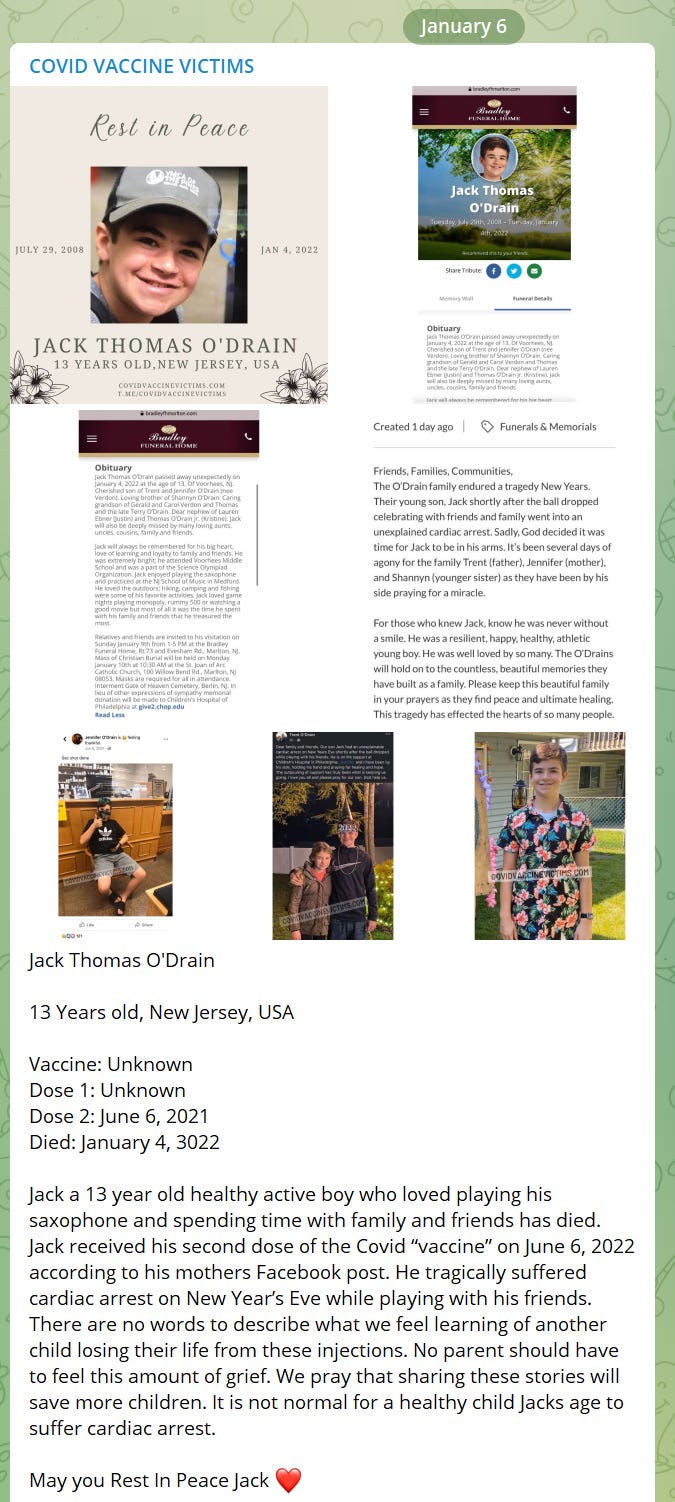
How many kids have to die before they acknowledge that the vaccines are killing kids?
I just wanted to memorialize Jack’s death so that it is not forgotten.
I hope that someday, someone will connect the dots and at least acknowledge that these kids were killed by the vaccine. Is that too much to ask?
This is going to keep happening until they halt the vaccines.
As I explained earlier, an estimated 800 kids have been killed by the COVID vaccines to date. We’ve already killed more kids from the vaccines than have died from COVID.
I’m forwarding my article to all of the CDC people involved in investigating Jacob’s death. I doubt I’ll hear anything back. But I wanted to make sure they are aware of all this. For the record.
The Day Jake Tapper Sold His Soul to Pharma

Photo Credit: “Jake Tapper-Caricature” by DonkeyHotey — licensed under CC BY 2.0
By Robert F. Kennedy, Jr. | The Defender | January 6, 2022
Apparently, appalled by robust sales of my bestseller, “The Real Anthony Fauci,” CNN anchor Jake Tapper — in lieu of critically reviewing the work — used his Twitter feed to unleash a barrage of ad hominem insults against me.
Breaking with the traditional restraints of journalistic neutrality, professional propriety and intellectual rigor, he branded me “dangerous,” a “menace,” a “liar,” a “grifter,” a fraud, “unhinged” and more.
But Tapper’s defamations hang in the atmosphere without substantiation or citation. If I’m a liar, then what was my lie? If I’m a grifter, then what is my personal profit or advantage? If I am a fraud, then where is my inaccurate statement?
I concede that I’m a dangerous menace, but only to the pharmaceutical industry, its captive technocrats and its media toadies.
When I responded to his slander with a respectful tweet inviting him to debate me, Tapper declined, explaining he would not debate a “conspiracy theorist.” Characteristically, he neglected to cite any conspiracy theory he believes I promoted.
And is it credible to dismiss me as a conspiracy theorist unworthy of debate? After all, I am founder and former president of the world’s largest water protection group, and founder and current chairman of one of the largest children’s health advocacy groups.
I’ve won hundreds of successful lawsuits, including milestone victories against Monsanto, DuPont, Exxon, Smithfield Foods and leading polluters from the chemical, carbon, pharmaceutical and agricultural industries. (Many of these also initially dismissed me as a “conspiracy theorist.”)
My current book, “The Real Anthony Fauci,” may be the most heavily footnoted volume to ever sit atop global best-seller lists for six consecutive weeks. With 500,000 copies sold, it has attracted a whopping 5,500+ five-star reviews (92%).
Despite extreme hostility toward this volume from mainstream media and the medical cartel, no one has yet identified a factual inaccuracy in its 250,000 words.
If my book is baseless conspiracy theories, then shouldn’t Mr. Tapper welcome an opportunity to correct me with facts or arguments that go beyond name-calling?
Allow me, then, to offer my own theory for Mr. Tapper’s apoplexy.
Many people make Faustian bargains during their lives, trading personal integrity for material advantage. Oftentimes the metamorphosis occurs as a gradual erosion of moral fiber. Occasionally it happens in an instant; a man stands at a moral crossroads and chooses the dark side.
I happened to have a front-row seat when Jake Tapper had his moment of moral crisis. I’m guessing his fierce vitriol toward me is a reaction to his embarrassment that I was witness to the instant when Mr. Tapper chose career over character.
In July 2005, Jake Tapper was ABC’s senior producer when the network ordered him to pull a lengthy exposé on the Centers for Disease Control and Prevention’s (CDC) secret 2000 Simpsonwood conference.
Here is the background:
In 1999, in response to exploding epidemics of autism and other neurological disorders, CDC decided to study its vast Vaccine Safety Datalink — the medical and vaccination record of millions of Americans, archived by the top HMOs — to learn whether the dramatic escalation of the vaccine schedule, beginning in 1989, was a culprit. CDC’s in-house epidemiologist, Thomas Verstraeten, led the effort.
Verstraeten’s initial data run suggested that mercury-containing hepatitis B vaccines — administered during the first month of life — were associated with a wide range of neurological injuries, including a dramatic 1,135% rise in autism risks among vaccinated children.
Verstraeten’s findings propelled CDC into DEFCON 1. The agency’s top vaccine officials summoned 52 pharmaceutical industry leaders, the foremost vaccinologists from academia and the American Academy of Pediatrics (AAP), and public health regulators from the National Institutes of Health, U.S. Food and Drug Administration (FDA), CDC, World Health Organization (WHO) and European Medicines Agency to a secret two-day meeting at the remote Simpsonwood retreat center in Norcross, Georgia, to strategize about how to hide these awful revelations from the public.
In 2005, I obtained the explosive transcripts of this meeting and was about to publish excerpts in Rolling Stone (Deadly Immunity, July 18, 2005). Those recordings, ironically, portrayed these leading kingpins of the vaccine cartel poised at their own moral brink, and chronicled their collapse into corruption over two sickening days of debate.
Most of these individuals were physicians and regulatory officials who had committed their lives to public health out of idealism and deep concern for children. Verstraeten’s data confronted them with the fact that the cumulative mercury levels in all those new vaccines they had recommended had overdosed a generation of American children with mercury concentrations over a hundred times the exposures the U.S. Environmental Protection Agency considered safe.
In recommending a vast battery of new vaccines for children, public health regulators had somehow neglected to calculate the cumulative mercury and aluminum loads in all the new jabs.
Dr. Peter Patriarca, the then-director of the FDA Office on Vaccine Research and Review, expressed the general feeling of horror when he asked why no one had calculated the cumulative mercury exposure to children as policymakers added this cascade of new vaccines to the childhood schedule: “Conversion of the percentage thimerosal to actual micrograms of mercury involves ninth-grade algebra. What took the FDA so long to do the calculations?”
In the tense days leading up to the Simpsonwood conclave, children’s health champion Dr. Ruth Etzel of the EPA pleaded with her fellow public health leaders to publicly admit they made a terrible mistake by inadvertently poisoning American children, and to repair the damage.
Dr. Etzel urged AAP and the government regulators to handle the crisis with the same honesty and public remorse that Johnson & Johnson had demonstrated on discovering toxic chemicals in its Tylenol formulations:
“We must follow three basic rules: (1) act quickly to inform pediatricians that the products have more mercury than we realized; (2) be open with consumers about why we didn’t catch this earlier; (3) show contrition. If the public loses faith in the Public Health Services recommendations, then the immunization battle will falter. To keep faith, we must be open and honest and move forward quickly to replace these products.”
Confronted with scientific proof of their role in the chronic disease calamity, the cabal did exactly the opposite. The shocking Simpsonwood transcripts show Dr. Patriarca and the other public health panjandrums warning each other of their reputational liabilities, their vulnerability to litigation by plaintiffs’ lawyers and potential damage to the vaccine program.
Dr. Patriarca cautioned that public disclosure of CDC’s explosive findings would make Americans feel that the FDA, CDC and vaccine policymakers had been “asleep at the switch” for decades in allowing Thimerosal to remain in childhood vaccines.
Over two days of intense discussion, these Big Pharma operatives and government technocrats persuaded each other to transform their disastrous error into villainy — by doubling down and hiding their mistake from the public.
Tapper saw an early draft of my Rolling Stone story and proposed that, in exchange for exclusivity, he would do a companion piece for ABC timed to air on the magazine’s publication day.
Tapper spent several weeks working on the story with me and a team of enthusiastic ABC reporters and technicians. During his frequent conversations with me over that period, he was on fire with indignation over the Simpsonwood revelations. He acted like a journalist hoping to win an Emmy.
The day before the piece was to air, an exasperated Tapper called me to say that ABC’s corporate officials ordered him to pull the story. The network’s pharmaceutical advertisers were threatening to cancel their advertising.
“Corporate told us to shut it down,” Tapper fumed. Tapper told me that it was the first time in his career that ABC officials had ordered him to kill a story.
ABC had advertised the Simpsonwood exposé, and its sudden cancellation disappointed an army of vaccine safety advocates and parents of injured children who deluged the network with a maelstrom of angry emails.
In response, ABC changed tack and publicly promised to air the piece. Instead, following a one-week delay, the network duplicitously aired a hastily assembled puff piece promoting vaccines and assuring listeners that mercury-laden vaccines were safe.
The new “bait and switch” segment precisely followed Pharma’s talking points. “I’m putting my faith in the Institute of Medicine,” ABC’s obsequious medical editor, Dr. Tim Johnson, declared in closing. Two pharmaceutical advertisements bracketed the story.
After that piece aired, I called Jake to complain. He neither answered nor returned my calls.
During the 16 intervening years, Pharma has returned Mr. Tapper’s favor by aggressively promoting his career. Pfizer shamelessly sponsors Tapper’s CNN news show, announcing its ownership of the space — and Mr. Tapper’s indentured servitude — before each episode with the loaded phrase: “Brought to you by Pfizer.”
Under the apparent terms of that sponsorship, CNN and Tapper provide Pfizer a platform to market its products and allow the drug company — a serial felon — to dictate content on CNN.
This arrangement has transformed CNN’s The Lead with Jake Tapper into a propaganda vehicle for Pharma and effectively reduced Mr. Tapper to the role of a drug rep — shamelessly promoting fear porn, confusion, and germophobia, and ushering his audience toward high-yield patent pharmaceuticals.
Tapper’s main thrust during the pandemic has been to promote levels of public terror sufficient to indemnify all the official lies against critical thinking.
All that Pharma money naturally requires that Mr. Tapper kowtow to Dr. Fauci, and the CNN host’s slavishness has helped make Tapper’s show the go-to pulpit for the National Institute of Allergy and Infectious Diseases (NIAID) director.
It’s a safe place for Dr. Fauci to hit all Jake’s reliable softballs out of the park.
“The bootlicking competition at CNN is pretty nauseating,” observed investigative journalist Celia Farber who has chronicled Dr. Fauci’s mismanagement at NIAID for more than 25 years. “It’s ruinous for both democracy and for public health.”
Another journalist has compared Tapper’s mortifying on-air servility toward Dr. Fauci to the adulation of a loyal and obedient canine. “It’s like a dog watching a chess match,” says former New York Times reporter Alex Berenson. “So much intensity and so little understanding.”
Tapper has gone two years without asking Dr. Fauci a single tough question. He has covered up Fauci’s involvement with Wuhan, suppressed news of vaccine injuries, gaslighted the injured, and defended every official orthodoxy on masks, lockdowns, social distancing, vaccines, remdesivir, ivermectin and hydroxychloroquine.
He has never asked about the public health, mental health, and economic costs of lockdown, about the disproportionate burdens of Dr. Fauci’s policies on minorities, the working class and the global poor.
He has never asked Dr. Fauci to explain why countries and states that refused Dr. Fauci’s prescription have consistently experienced dramatically better health outcomes. For example, why are U.S. death rates 1,000x the death rates of African countries like Nigeria and Indian states that widely use hydroxychloroquine and ivermectin? Mr. Tapper simply never allows contrary views on his show.
He continues to extol COVID vaccines as a miracle technology that individuals can take four times and still both get and spread the illness.
“He never calls Dr. Fauci on his vacillating science-free pronouncements,” said Farber. “Dr. Fauci seems to be able to paralyze the curiosity features of Tapper’s brain.”
Tapper has to ask Dr. Fauci why, under his direction, America suffered the world’s highest body count. With 4.2% of the global population, our nation suffered 15% of COVID deaths.
Instead, he functions as high priest of every official orthodoxy, working to deify Dr. Fauci and anoint all his absurd, vacillating and contradictory pronouncements with papal infallibility. The sure way to earn Tapper’s indignation is to criticize Dr. Fauci.
Here are just a few examples of Mr. Tapper’s brazen deceptions:
On Feb. 2, 2021, Tapper “debunked” claims that baseball great Hank Aaron may have died from a COVID shot. The home run king submitted to a CDC-staged press conference 17 days earlier. Tapper assured his audience that the Fulton County coroner had determined Aaron to have died from “natural causes.”
When the Fulton County coroner subsequently denied ever having seen Aaron’s body, much less performed an autopsy, Tapper refused to correct his story.
In August 2021, Tapper gave Dr. Fauci a platform to spread the rumor that deluded Americans were poisoning themselves with a “horse medicine” called ivermectin.
In an Aug. 29, 2021 interview, Dr. Fauci told Tapper, “There’s no evidence whatsoever that that works, and it could potentially have toxicity… with people who have gone to poison control centers because they’ve taken the drug at a ridiculous dose and wind up getting sick. There’s no clinical evidence that indicates that this works.”
Tapper never corrected Dr. Fauci. He never pointed out that there were by then 70 peer-reviewed studies demonstrating ivermectin’s miraculous efficacy against COVID.
He didn’t dispute Dr. Fauci’s characterization of ivermectin as a horse medicine by noting that the drug had won both a Nobel Prize and WHO’s listing as an “essential medicine” for its miraculous efficacy against human illnesses, and that people have consumed billions of doses with no significant safety signals.
Mr. Tapper never thought to ask Dr. Fauci if he was trying to discourage use of a cheap, effective drug that might compete with his experimental vaccines.
Instead, Tapper abjectly parroted Dr. Fauci’s talking points: “Poison control centers are reporting that their calls are spiking in places like Mississippi and Oklahoma, because some Americans are trying to use an anti-parasite horse drug called ivermectin to treat coronavirus, to prevent contracting coronavirus.”
It mattered not to Tapper that both Mississippi and Oklahoma officials quickly denied that anyone in their state had been hospitalized for ivermectin poisoning. Tapper never corrected his false story.
On Sept. 14, 2021, Tapper obligingly gave Dr. Fauci a platform to dispute rapper Nicki Minaj’s worry that COVID vaccines may affect fertility. Dr. Fauci simply declared, “The answer to that, Jake, is a resounding no.”
As usual, Tapper did not ask Dr. Fauci to cite a study to support this assertion. He never pointed out to Dr. Fauci that all of the COVID vaccine manufacturers acknowledge that their products are not tested for effects on fertility, or that recent data has shown dramatic upticks in miscarriages and pre-eclampsia in vaccinated women.
Nevertheless, based upon Dr. Fauci’s word alone, CNN rushed on to defame and discredit the rapper and to assure the public that Minaj was wrong. Dr. Fauci, after all, had spoken!
It’s easy to see how two years of such obsequious deference emboldened Dr. Fauci in November 2021 to declare that “I represent science.”
There are too many other examples of Tapper’s uncritical promotion of government and pharma falsehoods to even summarize. These are not harmless lies. Each of them has potentially disastrous consequences for public health.
The term “psychological projection” describes the uncanny precision with which a certain sort of person applies the very pejoratives to others that most accurately depict their own shortcomings.
When Mr. Tapper calls me “unhinged,” a “menace to public health,” a “fraud,” a “liar,” is he falling victim to projection?
The critical functions of journalism in a democracy are to speak truth to power, relentlessly expose official corruption, and to forever maintain a posture of skepticism toward government and corporate power centers.
What Jake Tapper does is the opposite of journalism. Tapper, instead, aligns himself with power, and makes himself a propagandist for official narratives and a servile publicist for powerful elites and government technocrats.
No wonder his fury at those who challenge their narratives.
© 2022 Children’s Health Defense, Inc. This work is reproduced and distributed with the permission of Children’s Health Defense, Inc. Want to learn more from Children’s Health Defense? Sign up for free news and updates from Robert F. Kennedy, Jr. and the Children’s Health Defense. Your donation will help to support us in our efforts.
Featured Video

EUROPE FEARS RUSSIA’S NEXT MOVE / Ian Proud
or go to
Aletho News Archives – Video-Images
New Book
New Book: No Autoimmunity The Body Doesn’t Attack Itself
Lies are Unbekoming | September 24, 2026
 The label for Humira, once the best-selling drug in the world, lists its risks in plain print. One of them, in the label’s own words, is new “autoimmune” disease.
A drug prescribed for a condition labelled autoimmune carries a warning that it can cause a condition labelled autoimmune. That contradiction sits in every box, on a folded paper almost nobody reads.
My new book starts there.
No Autoimmunity: The Body Doesn’t Attack Itself
For seventy years, “your body is attacking itself, and we don’t know why” has ended the conversation for people diagnosed with multiple sclerosis, lupus, rheumatoid arthritis, Hashimoto’s, Type 1 diabetes, Crohn’s and psoriasis. More than eighty conditions now carry the autoimmune label. The diagnosis comes with a prescription for life. It almost never comes with a question about cause.
This book asks the question and answers it from the framework’s own records: its drug labels, its journals, its regulatory filings, and its own experiments. … continue
Blog Roll
 Aletho News
- Italy and France debunk reports CIA issued ‘Russian drone threat’ warning
- How Russia is Rewiring the Global South
- Britain’s elites want you ready to die for a war they keep imagining
- Inside Ukraine’s propaganda operation targeting Americans
- Hackers From US, France, Singapore Tried to Disrupt Russian Elections – Internet Provider
- New Book: No Autoimmunity The Body Doesn’t Attack Itself
- EUROPE FEARS RUSSIA’S NEXT MOVE / Ian Proud
- Big tech hands in its DSA censorship reports to the EU
- ‘A Big Victory’ – Palestine Chronicle Wins Two-Year Legal Battle
- IAEA inspectors cannot return to Iran amid US threats: Russia
- If Americans Knew
- An error has occurred; the feed is probably down. Try again later.
- No Tricks Zone
- New Study: Earth And Venus Surface Warmth Largely Explained By Convection And Lapse Rate, Not CO2 Or Radiation
- 2025 Nature Paper Claiming Worsening Global Drought Gets RETRACTED …Heavily Flawed
- New Study: ‘Global Drought Shows No Detectable Recent Acceleration Under Climate Warming’
- Economic Masterminds: German Socialists Suggest Taxing Productivity Gains Stemming From Using AI
- The South China Sea Has Not Been Cooperating With The Climate Change Narrative
- Energy Crisis: Germany Enters Heating Season With Historically Low Gas Reserve Fill Levels
- New Study: The Antarctic Ice Sheet Gained Mass From 2020-2024 Due To Staggering Snow And Ice Accumulation
- Study: Ocean Heating Rates From Thousands Of Years Ago ‘Dwarf’ Modern Ocean Heating Rates
- Climate Extremists Target, Attack Large-Scale Power Grid Infrastructure In Germany!
- New Study: Antarctic Ice Melt Has Contributed Less Than 1 Centimeter To Sea Level Rise In The Last 30 Years

