A LOT has been said about the psychological effects of Covid on the public. Worryingly, the management of an unpredictably mutating virus which is always one step ahead is fraying the composure of our leaders too.
In the last couple of weeks, Presidents Joe Biden and Emmanuel Macron have lashed out at fellow citizens who defy government orders to be vaccinated because they doubt ‘the science’ is truly settled in favour of a jab which has not been subjected to the full range of tests for side-effects later in life.
Exasperated by resistance to their Covid dictates, the American and French leaders appear to be losing their minds and their manners in the battle between the risks of vaccination and the risk of becoming serious ill with the virus.
Biden, alarmed by the refusal of one third of Americans to be vaccinated while Omicron is on the loose – though it causes mainly flu-like symptoms – warned them at Christmas that they faced a ‘winter of death’. Not one person in the US is yet known to have died from the latest Covid variant.
‘We are looking at a winter of severe illness and death for the unvaccinated, for themselves and their families and the hospitals they’ll soon overwhelm,’ quoth the ancient prophet of doom at a White House briefing whose message was that the unjabbed are not just selfish, they endanger the lives of everyone else.
Biden fingered them officially as ‘bad persons’, an unwelcome term in America where being a good person is vital to many. Not unnaturally, his presentation was badly received, reinforcing as it did the political polarisation between Democrats and Republicans, whom the former accuse of being the main vaccination hold-outs.
People, including essential workers, are being fired across America for defying Biden’s vaccination mandates.
Macron went further this week in a newspaper interview, threatening to ‘emmerder les non-vaccinés jusqu’au bout’. A polite translation of this is that he intends to go after them hard until they give in.
Emmerder – literally, to smear with sh*t – is a commonly used expression and is offensive or not according to context. Macron deliberately used it at its rudest and got the reaction he hoped for.
A session of parliament to discuss the government’s introduction of an updated vaccination passport restricting the freedom of movement of the unvaccinated was suspended in uproar when members heard the explosion of Macron’s little bomb.
He changed the focus of the argument from the virus to his brutal language. It’s likely to be a talking point for his opponents during his campaign for re-election this spring.
The fashion for politicians insulting the people they rely on to elect them was set by President Obama referring to ‘bitter clingers’ and Hillary Clinton describing some Midwestern voters as ‘deplorables’. (Those bad persons again.)
Biden and Macron forgot that these remarks were never forgiven by their targets and in Clinton’s case helped her to lose the race for the presidency.
Boris Johnson has at least grasped that, after two years of unprecedented exposure to the arbitrary powers of government, it is politically counter-productive to strain people’s patience with constant loosening and re-tightening of a Covid regime unknown in free countries outside wartime.
What is shocking about Biden, Macron, Obama and Clinton is the openness of their contempt for the people they govern as if being in public office conferred on them a wisdom that separated them from the common voters rather than the duty to lead with their consent.
There is nothing in our democratic system, adversarial as it is, that entitles politicians to treat us angrily. How many people, hearing the Biden and Macron anathemas, rushed out with arms bared to the needle?
I was vaccinated promptly myself because the odds pushed me that way. But I understand the motives of those who see obligatory vaccination – along with a sustained media campaign to vilify them – as a step too far by an overbearing state.
The certitudes of government’s own scientific advisers are offset by the determination of so many health professionals – including my own GP – to refuse the vaccines. What right do political leaders, themselves scientifically uneducated, have to threaten doctors and nurses who have daily experience of how medical treatments work and which can be trusted?
‘My body my choice’, the battle cry that worked so well for supporters of abortion, is suddenly off the table when the principle doesn’t suit politicians.
Biden and Macron weren’t showing leadership. What they expressed was frustration that, with all their power, they cannot force obedience on free-thinking citizens and anger that they will be blamed for the consequences. Macron especially forgot that the way we speak to each other in public matters. If you abuse people, they remember.
The European (EEA and non-EEA countries) database of suspected drug reaction reports is EudraVigilance, verified by the European Medicines Agency (EMA), and they are now reporting 36,257 fatalities, and 3,244,052 injuries following injections of four experimental COVID-19 shots:
From the total of injuries recorded, almost half of them (1,540,852) are serious injuries.
“Seriousness provides information on the suspected undesirable effect; it can be classified as ‘serious’ if it corresponds to a medical occurrence that results in death, is life-threatening, requires inpatient hospitalisation, results in another medically important condition, or prolongation of existing hospitalisation, results in persistent or significant disability or incapacity, or is a congenital anomaly/birth defect.”
A Health Impact News subscriber in Europe ran the reports for each of the four COVID-19 shots we are including here. It is a lot of work to tabulate each reaction with injuries and fatalities, since there is no place on the EudraVigilance system we have found that tabulates all the results.
Since we have started publishing this, others from Europe have also calculated the numbers and confirmed the totals.*
Here is the summary data through January 1, 2022.
Total reactions for the mRNA vaccine Tozinameran (code BNT162b2, Comirnaty) from BioNTech/ Pfizer: 16,471 deaths and 1,546,829 injuries to 01/01/2022
42,225 Blood and lymphatic system disorders incl. 230 deaths
50,455 Cardiac disorders incl. 2,379 deaths
467 Congenital, familial and genetic disorders incl. 45 deaths
20,812 Ear and labyrinth disorders incl. 11 deaths
293,748 General disorders and administration site conditions incl. 1,740 deaths
1,004 Hepatobiliary disorders incl. 66 deaths
5,228 Immune system disorders incl. 35 deaths
36,265 Infections and infestations incl. 564 deaths
13,023 Injury poisoning and procedural complications incl. 188 deaths
24,589 Investigations incl. 191 deaths
12,747 Metabolism and nutrition disorders incl. 113 deaths
164,732 Musculoskeletal and connective tissue disorders incl. 144 deaths
704 Neoplasms benign malignant and unspecified (incl cysts and polyps) incl. 34 deaths
228,601 Nervous system disorders incl. 1,095 deaths
586 Pregnancy puerperium and perinatal conditions incl. 19 deaths
194 Product issues incl. 1 death
20,622 Psychiatric disorders incl. 65 deaths
4,226 Renal and urinary disorders incl. 71 deaths
16,282 Reproductive system and breast disorders incl. 3 deaths
40,154 Respiratory thoracic and mediastinal disorders incl. 963 deaths
50,986 Skin and subcutaneous tissue disorders incl. 59 deaths
1,581 Social circumstances incl. 6 deaths
1,686 Surgical and medical procedures incl. 28 deaths
28,023 Vascular disorders incl. 497 deaths
Total reactions for the COVID-19 vaccine JANSSEN (AD26.COV2.S) from Johnson & Johnson: 2,245 deaths and 114,229 injuries to 01/01/2022
1,113 Blood and lymphatic system disorders incl. 46 deaths
2,196 Cardiac disorders incl. 186 deaths
40 Congenital, familial and genetic disorders incl. 1 death
1,227 Ear and labyrinth disorders incl. 3 deaths
93 Endocrine disorders incl. 1 death
1,548 Eye disorders incl. 9 deaths
9,141 Gastrointestinal disorders incl. 87 deaths
30,336 General disorders and administration site conditions incl. 623 deaths
143 Hepatobiliary disorders incl. 13 deaths
509 Immune system disorders incl. 10 deaths
5,832 Infections and infestations incl. 187 deaths
1,060 Injury, poisoning and procedural complications incl. 23 deaths
5,197 Investigations incl. 126 deaths
709 Metabolism and nutrition disorders incl. 55 deaths
16,069 Musculoskeletal and connective tissue disorders incl. 50 deaths
80 Neoplasms benign, malignant and unspecified (incl cysts and polyps) incl. 8 deaths
21,863 Nervous system disorders incl. 234 deaths
52 Pregnancy, puerperium and perinatal conditions incl. 1 death
29 Product issues
1,627 Psychiatric disorders incl. 21 deaths
485 Renal and urinary disorders incl. 29 deaths
2,625 Reproductive system and breast disorders incl. 6 deaths
4,115 Respiratory, thoracic and mediastinal disorders incl. 283 deaths
3,506 Skin and subcutaneous tissue disorders incl. 10 deaths
372 Social circumstances incl. 4 deaths
785 Surgical and medical procedures incl. 69 deaths
3,477 Vascular disorders incl. 160 deaths
*These totals are estimates based on reports submitted to EudraVigilance. Totals may be much higher based on percentage of adverse reactions that are reported. Some of these reports may also be reported to the individual country’s adverse reaction databases, such as the U.S. VAERS database and the UK Yellow Card system. The fatalities are grouped by symptoms, and some fatalities may have resulted from multiple symptoms.
The Government on Wednesday published the evidence informing its recent controversial decision to recommend all secondary school pupils wear face masks in classrooms.
The new document from the Department for Education (DfE) explains that the decision “has been taken on the recommendation of UKHSA and is based on a range of evidence”. It says the Government has “balanced education and public health considerations, including the benefits in managing infection and transmission, against any educational and wider health and wellbeing impacts from the recommended use of face coverings”.
While conceding that the “direct COVID-19 health risks to children and young people are very low” – and rejecting SAGE’s advice to recommend masks in primary school classrooms (yes, really) – it claims that “the balance of risks for secondary classrooms has changed at this point in time, in accordance with the evolving evidence and the phase of the pandemic”.
The document summarises its evidence as follows:
Face coverings can be effective in contributing to reducing transmission of COVID-19 in public and community settings. This is informed by a range of research, including randomised control trials, contact tracing studies, and observational studies – assessed most recently by UKHSA, described in a review conducted in November 2021. The review’s conclusions were broadly in line with those of a previous Public Health England review; however, the addition of randomised control trials and substantially more individual-level observational studies increases the strength of the conclusions and strengthens the evidence for the effectiveness of face coverings in reducing the spread of COVID-19 in the community, through source control, wearer protection, and universal masking.
In fact, though, the UKHSA review from November 2021 found no high quality studies (except, it claims, the ONS study, which really isn’t high quality). Of the two randomised controlled trials (RCTs) that have been done and which were cited by the UKHSA, the one from Denmark found no statistically significant reduction in COVID-19 incidence from surgical masks (the study didn’t look at cloth masks) while the Bangladesh mask study found no benefit from cloth masks and the reported benefit from surgical masks was just 11%, with a 95% confidence interval that included zero. The UKHSA review also considered 23 observational studies, which it said had “mixed” results and many of which were of low quality and small.
This does not seem a strong basis to claim a large effect for mask wearing. A recent more comprehensive review (which included earlier evidence for other flu-like viruses) by Ian Liu, Vinay Prasad and Jonathan Darrow for the Cato Institute, entitled “Evidence for Community Cloth Face Masking to Limit the Spread of SARS‐CoV‑2: A Critical Review“, concluded that: “More than a century after the 1918 influenza pandemic, examination of the efficacy of masks has produced a large volume of mostly low- to moderate-quality evidence that has largely failed to demonstrate their value in most settings.”
That is a better summary of the evidence than the DfE managed.
Needless to say, the DfE gives the propaganda value of masking a nod: “It can be a visible outward signal of safety behaviour and a reminder of COVID-19 risks.”
Notably, there is no mention in this document of the potential harms of wearing a mask for an extended period, such as the impact on breathing, the heart, or the skin. Contamination gets a brief mention, though it’s quickly dismissed:
Face masks and coverings will become highly contaminated with upper respiratory tract and skin micro-organisms. Disposal of single-use face coverings could theoretically pose a risk of transmission for inappropriately discarded face coverings, but it is very likely that the reduction in transmission risk due to reduced droplet and aerosol emissions from wearing a face covering significantly outweighs any potential for enhanced risk of transmission through inadvertent contact with a contaminated face covering. This is likely to hold regardless of duration that the face covering is used.
The reference provided for these claims is a SAGE document from September 2020, “Duration of Wearing of Face Coverings.” This is an interesting document, but it can scarcely be said to support the claims the DfE is making. On harms from masks, for example, it says:
Neither surgical masks nor face coverings are designed for use for extended periods. Wearing a face covering for an extended period can maintain a higher moisture level around the face which can be uncomfortable for some people and may increase the likelihood of skin complaints. Masks will become highly contaminated with upper respiratory tract and skin micro-organisms. A review of the downsides of face masks and face coverings (by Bakhit et al) found 20 studies reporting irritation and discomfort from using masks. Participants in studies with surgical or cloth masks reported difficulty breathing (12%-34%), facial irritation and discomfort (11-35%). More serious symptoms of headache, acne, rashes were associated with use of N95 and goggles. A study among healthcare workers (by Han et al) associates acne with extended duration of wearing. …
In a clinical study of extended wearing (by Chughtai et al), 124/148 participants reported at least one problem associated with mask use including pressure on face, breathing difficulty, discomfort, trouble communicating with the patient and headache. …
Measurements of heart rate during activity (by Li et al) showed significantly lower rates with a surgical mask compared to N95. In a study (by Fikenzer et al) of healthy young male volunteers surgical masks and FFP2/N95 respirators, both had a significantly marked negative impact on pulmonary capacity (FEV, PEV and PEF) while wearing the mask (with a spirometry mask) during exercise.
The DfE document omits to mention any of these issues. It does, however, include some recognition of the negative impact on education. It mentions a survey conducted by the Department in March 2021 that found “80% of pupils reported that wearing a face covering made it difficult to communicate, and more than half felt wearing one made learning more difficult (55%)”. It also mentions a DfE survey from April 2021 that found “almost all secondary leaders and teachers (94%) thought that wearing face coverings has made communication between teachers and students more difficult, with 59% saying it has made it a lot more difficult”. It adds:
Research into the effect of mask wearing on communication has found that concealing a speaker’s lips led to lower performance, lower confidence scores, and increased perceived effort on the part of the listener. Moreover, meta-cognitive monitoring was worse when listening in these conditions compared with listening to an unmasked talker. A survey of impacts on communication with mask wearing in adults reported that face coverings negatively impact hearing, understanding, engagement, and feelings of connection with the speaker. People with hearing loss were impacted more than those without hearing loss. The inability to see facial expressions and to read lips have a major impact on speech understanding for those with hearing impairments. The worse the hearing, the greater the impact of the mask.
What about the evidence for the claims the document does make – that it is “very likely” that the transmission reduction from wearing a mask “significantly outweighs any potential for enhanced risk of transmission through inadvertent contact with a contaminated face covering” and that “this is likely to hold regardless of duration that the face covering is used”. This is what the cited SAGE document says:
There is a lack of good evidence relating to the wearing of face coverings, with very little data relating to duration of wearing. In particular we suggest that the following aspects would benefit from further research:
• Effectiveness of face coverings as a source control after longer duration wearing, including analysis of the influence of moisture on the performance of different types of face coverings.
• Analysis of the potential risk of transmission due to contaminated face coverings (during and after removal).
• Assessment of the prevalence of skin complaints associated with face coverings, including an understanding of the factors that contribute and potential mitigation.
• Analysis of user acceptability of face coverings for long duration use in different settings.
In other words, there was no good evidence on the things the DfE is claiming are “likely” or “very likely”, or on much else really.
The DfE also carried out its own analysis of the impact of masks in schools.
DfE has also undertaken initial observational analysis based on data reported by 123 secondary schools that implemented face coverings during a 2-3-week period in the autumn term 2021, compared to a sample of similar schools that did not. The preliminary findings demonstrate a potential positive effect in reducing pupil absence due to COVID-19.
What did it find? It found that COVID-19 absences fell by 0.6% more (absolute reduction) in secondary schools that used face masks compared to similar schools that did not over a 2-3-week period, which amounts to an 11% relative reduction.
In a weighted sample of secondary schools that did not use face masks, the average COVID-19 absence rate fell by 1.7 percentage points from 5.3% on October 1st 2021 to 3.6% in the third week of October. This is equivalent to a 32% decrease.
In secondary schools that did use face coverings (either face coverings only or a combination of face masks and additional communications e.g. providing more communications to parents but not introducing any further measures such as increased testing), the average COVID-19 absence rate fell by 2.3 percentage points from 5.3% on October 1st 2021 to 3.0% in the third week of October. This is equivalent to a 43% decrease.
At surface level, this suggests that COVID-19 absence fell by 0.6 percentage points more (an 11% relative difference) in secondary schools that used face masks compared to similar schools that did not over a 2-3-week period.
However, the study had numerous limitations, which made the finding a “non-statistical and unknown clinical significant” reduction, i.e., it may just be chance.
There is a level of statistical uncertainty around the result. The analysis is non-peer reviewed and with the current sample size, shows a non-statistical and unknown clinical significant reduction in infection in a short follow up period, including that a ‘false positive’ (i.e. finding that face coverings saw reduced absence when the finding is actually by chance) would emerge around 15% of the time; a 5% threshold is widely used to declare statistical significance in academic literature.
Therefore, further work should be done to extend the analysis in terms of scope: for example, looking at different statistical methodologies, capturing different and longer treatment time periods and controlling for a wider number of school and local area variables to ensure this is a consistent finding.
The statistical uncertainty around the result was such that the 95% confidence interval for the effect size included zero (note in the below the upper CI is positive).
What’s more, the control group of 1,192 schools that didn’t use masks were very different to the 123 treatment schools which did, so that the above findings only emerged after significant weighting was added to the control group schools using a process the document calls “entropy balancing”.
Exploration of the data showed that the control and treatment group had differing characteristics, so weights for the control group schools were calculated using entropy balancing.
Prior to this weighting, the non-mask schools actually had lower average absence rates throughout the study period – though the treatment schools reduced more from their higher starting point.
Prior to weighting, the mean absence rate of the control group increases across the treatment period, whereas the mean absence rate of the treatment group decreases. However, the absence rates in the control group remain lower overall than those in the treatment group.
All-in-all, not exactly robust, compelling evidence of the benefits of masking, particularly given all the well-documented harms, which the document itself either sets out or cites other documents which do.
The document at one point hints at what I suspect is the real reason masks were brought back into classrooms: “In a Unison survey of support staff, 71% said face coverings in secondary school classrooms are an important safety measure.” Conservative MP Jonathan Gullis wrote in the Times this week that: “Face masks have been a central demand of teaching unions.” Sounds vey much like politics rather than science to me. (See this recent Daily Sceptic article by Ben Irvine on the role the teaching unions played in forcing the Government to lockdown in March 2020.)
When are we going to stop harming our young people with pointless interventions to deal with a virus that poses no threat to them and let them live normal lives again?
Stop Press: Oxford Professor of Evidence Based Medicine Carl Heneghan tells Julia Hartley-Brewer he is unimpressed by the Government’s “evidence” for masking in classrooms.
Education secretary Nadhim Zahawi has published the "evidence" for pupils wearing face masks in schools.
Professor of Evidence Based Medicine Carl Heneghan says the study is "not fit for purpose" and actually shows evidence for NOT wearing masks.@JuliaHB1 | @carlheneghanpic.twitter.com/OhqK0a9nUJ
The pro-drug industry mainstream media are insanely positive over the newly FDA approved Pfizer antiviral COVID treatment pills.
The drug, Paxlovid, received an emergency use authorization by FDA for use in patients 12 years old and up who have tested positive for COVID-19 and are at high risk.
Now is the time to speak calmly and accurately about Paxlovid. First, everyone should appreciate that there was very little testing of the short- and long-term safety of this product, exactly what happened with COVID vaccines.
Really good testing of a new drug should take many months or even years.
All you get is positive news for this new drug – actually a combination of drugs.
Here are brief summary statements about this new product:
It was approved by the FDA without any external meetings, serious reviews of test data or opportunity for public input. Pretty much all the regulatory work was done behind closed doors.
Terrific for Pfizer. Bad for the public.
Of importance, note that in the trials only 21 percent of people had a comorbidity, while in reality 94 percent of COVID deaths have at least one comorbidity, and the average number of underlying medical conditions is four.
As to antiviral science, protease enzymes must be present for the virus to successfully infect by completing the cycle before taking the cell over. Paxlovid or any drug classified as a ‘Protease Inhibitor’ will inhibit or decrease the protease enzyme interfering with the virus.
Paxlovid blocks the 3CLPro protease from chopping up the long protein into pieces. The virus can’t separate out which pieces to cut out and assemble. It can’t make copies of itself. The covid infection quickly stops.
Contrary to what the government says, Ivermectin is the most successful and proven protease inhibitor in use worldwide. Just as with Paxlovid, ivermectin decreases the protease enzyme but… there are benefits of ivermectin in covid treatment that are not present in Paxlovid.
Additional actions of ivermectin include anti-coagulant action and anti-inflammatory actions, both observed in covid infections. And IVM has been safely used for decades and there have been many medical studies as well as clinical results showing its antiviral and anti-inflammatory effectiveness.
Paxlovid requires combination with an HIV/AIDS drug, Ritonavir, preventing the breakdown of the Paxlovid so it may inhibit or decrease the enzyme interrupting the viral life cycle. Ritonavir acts as a booster for Paxlovid, keeping it active inside a person’s body. Ritonavir also has its own black box warning and side effects include life-threatening liver, pancreas and heart issues.
Does the public really want to take an HIV/AIDS drug?
A course of the treatment is 20 Paxlovid pills and 10 ritonavir pills taken over five days. Taking 6 pills daily can pose challenges for many elderly people in particular.
According to Pfizer’s press release, for people with proven COVID infection, Paxlovid reduces hospitalization/death by 89 percent when taken within three days of symptom onset. So in the treatment group there were 5 of 697 hospitalized with no deaths compared to 44/682 hospitalized with 9 subsequent deaths.
Think about that statement of taking this drug combo within three days of symptom onset. Here are critical problems facing ordinary people:
How can you accurately identify COVID symptoms from similar symptoms from the flu or a bad cold;
How can you get a fast test; how can you get in touch with your doctor within just a day or two and decide whether you really have COVID (don’t have drug interactions) and if so get a prescription; how can you get the prescription filled quickly?
None of these are easy to address and overcome. All this makes this new combo medicine unrealistic and impractical for nearly everyone.
Also reported was an approximate 10-fold decrease in viral load at day 5, relative to placebo, indicating robust activity against SARS-CoV-2 and representing (supposedly) the strongest viral load reduction reported to date for a COVID-19 oral antiviral agent.
How interesting it would have been to test the Pfizer drug against an ivermectin protocol.
For example, how does the Pfizer drug compare with the Dr. George Fareed and Dr. Brian Tyson protocol? Well, Fareed and Tyson had many more patients (about 7,000) taking the drug combo and yet they had fewer hospitalizations (4) and the same number of deaths (0).
So, you’re way better off with the Fareed and Tyson protocol. And the safety protocol of IVM after billions of uses globally is far better proven than for the Pfizer product.
For a good discussion on how IVM compares to Paxlovid see this article. Especially on scientific evidence of ivermectin’s ability to block 3CL protease.
In terms of safety, the most common side effects reported during treatment and up to 34 days after the last dose of Paxlovid were dysgeusia (taste disturbance), diarrhea and vomiting. But what more serious side effects may turn up months or years later?
Paxlovid must not be used with certain other medicines, either because due to its action it may lead to harmful increases in their blood levels, or because conversely some medicines may reduce the activity of Paxlovid itself. The list of medicines that must not be used with Paxlovid is included in the proposed conditions for use.
That list includes a very large number of drugs and supplements used by many millions of people, including, for example, Lipitor and St. John’s Wort. Paxlovid must also not be used in patients with severely reduced kidney or liver function.
Paxlovid is not recommended during pregnancy and in people who can become pregnant and who are not using contraception. Breastfeeding should be interrupted during treatment. These recommendations are because laboratory studies in animals suggest that high doses of Paxlovid may impact the growth of the fetus.
As to availability, Pfizer CEO Bourla recently said the company can manufacture 80 million courses in 2022, with 30 million available in the first half of the year. That is not enough to serve many millions of Americans coming down with symptoms and a positive test result.
This too was said, tens of thousands of the pills will ship in the US before the end of 2021 and hundreds of thousands more are expected at the beginning of 2022, a Pfizer spokesperson told the Wall Street Journal. The US government is paying Pfizer $5.3 billion for 10 million treatment courses that will be delivered by the end of next year, according to the paper. Will medical insurance cover $530 per course?
Always follow the money. A month ago, SVB Leerink analyst Geoffrey Porges projected the drug will generate $24.2 billion in 2022 sales. Together with the company’s megablockbuster COVID-19 vaccine, Pfizer could be looking at $50 billion in peak pandemic vaccine and drug sales, Cantor Fitzgerald analyst Louise Chen wrote earlier this month.
No surprise that some top Pfizer executives have become billionaires.
Do you want to do what is right for you, or terrific for Pfizer?
It’s been the most astonishing two weeks for American public life, with so many prescient changes, from new censorships, admissions, backtracks, experts speaking out, public outrage, and what strikes me as a progressive unraveling of every orthodoxy imposed nearly two years ago.
Not even the influential and powerful are in a position to defend what has happened to us. They seem to be gradually pulling away from public life, unable to say things that connect to what everyone knows.
Above all else, what’s remarkable right now is the undeniable arrival of Covid to a degree to which hardly anyone could have imagined all that time ago, when so many experts set out to deploy their fabulous new system for stopping the spread of a disease.
There was a goal (stop cases). There was a method (state compulsion). And there was a test (cases were supposed to go down and go away). There would be a war on a virus and the state would win! And now we look around and see the evidence of failure so pronounced, so impossible to deny, that we must face that which so many have worked so hard to deny for so long.
The best way I can describe this is by observation. In the Northeast of the US, and in many other parts of the country, everywhere you go, right now, you see sick people milling around. They don’t admit it and they don’t talk about it with strangers simply because there is such shame attached to having Covid. They complain of a cold, of a flu, or just suffer in silence. But there it is.
After nearly two years of work to control the spread, after brutal shutdowns of the whole country – shutdowns that happened two years too early, as judged by actual case trends (but of course lockdowns never should have been considered in the first place) – Covid is here. Not just here. It is everywhere. The case counts are beyond anything anyone on the planet could have imagined a year or two ago. The spikes make everything that came before look like child’s play.
Here is the global chart.
And we are talking really sick. Not so much death. Not even out-of-control hospitalization. We are talking about being sick in bed or walking around with misery. The nasty bug lasts maybe two days, maybe two weeks, maybe longer but it is vexing and wicked, not like a cold or flu but something more electric and strange.
Which variant? Two weeks ago, the CDC wanted to blame it all on Omicron. That is no longer possible. Perhaps that constitutes 20%; we just do not know for sure because tracking is so weak. Most of it is evidently Delta, meaning very sick but with no serious loss of taste and smell. Most everyone eventually gets well, and that’s what happens here.
We get to endemicity perhaps in a month or so and life will move on, my experts tell me, at least in some areas of the country. What’s striking and truly shocking is that all of the efforts, all of the propaganda, all of the astonishing spending and compulsion – the shutdowns, masking, size limits, travel restrictions, vaccination requirements, the track and trace, the endless testing, the enforcement, the intimidations, the censorship – and what do we have to show for it?
Lockdown architect Carter Mecher promised us as follows: “If you got everyone and locked each of them in their own room and didn’t let them talk to anyone, you would not have any disease.” They attempted a version of that, experimenting on the human population in ways without precedent. And let’s say that is true (it probably isn’t). That is not life. That is not society. That is not freedom. That is something else unimaginably horrific.
It was unsustainable. They pushed their theory without regard to the history of public health or, really, the whole of human experience. And now, the true pandemic finally arrived. And what is it? There are a ton of sick people. People are calling in sick because they cannot come to work. Institutions are having to shut down, not because government closed them but because people are too sick to come to work. This is the normal course of events – exactly what one would expect in a pandemic.
And it’s not just Covid. The head of an Indiana life insurance company reports that deaths among people aged 18-64 are up 40%, an astonishing increase. It’s suicide, drug overdoses, and every other manner of horror. And that’s just death. Many others are just sick from other things.
I personally know dozens and they each know many dozens of more people in the Northeast right now who are down for the count, miserable and pathetic, but still testing negative for Covid. Why would this be? It’s because immune systems have decayed over two years. The lack of vitamin D, the lack of exposure to normal germs in life, the isolation and depression, the overconsumption of liquor and drugs – it’s all been a terrible drain on health.
Meanwhile, the actual pandemic of Covid has certainly arrived. And it is far worse than the data indicated. Look at Massachusetts, New York, Pennsylvania, Rhode Island, Connecticut, any of these states, and including some Southern and Midwestern states, and what you find is increases of 500-1,000% in cases. And keep in mind that these are just cases as discovered by official testing spots.
Go to any CVS or Walgreens and you find long lines of people buying testing kits. If they are available. If they are not, the wait is weeks. They are $23 a kit and people are buying as many as possible. Why? Partially it’s because employers and schools are demanding negative tests, but it is also just curiosity. People are sick as dogs and want to confirm their illnesses.
People are estimating that real cases are 50x to 100x what the official data say.
But let’s talk now about a real scandal. When you are sick, you need treatment. Every competent medical professional I know is pretty darn sure that the best hope for dealing with Covid is a combination of Zinc, Vitamin D, and (sorry to mention the dreaded name) Ivermectin. This is not ideological. This is what experienced doctors are saying right now. I’m on many email lists with serious medical professionals and they are all saying the same thing. We can add HCQ to the list if you catch it early enough.
But here’s the kicker – and let me be clear that I’m NOT giving ANY medical advice here, merely just reporting the sense of the community out there. What’s remarkable is that people are having a very difficult time getting these basic therapeutics. Vaccines are everywhere but things to make you well once the virus penetrates the vaccine? Those are hard to come by.
There is a problem getting a prescription because state medical boards are actually barring people and preventing them from serving patients if they prescribe HCQ or Ivermectin, as incredible as that sounds. But once you get the prescription – if you have a doctor brave enough to risk it – finding a pharmacy to fill it is another challenge.
Most people in the UK today are getting their therapeutics from India. Americans get them from Mexico. And some are shipping to the US and they are being distributed via gray markets for anyone who is lucky enough to have a contact. It’s a speakeasy nation but this time for distributing basic therapies.
I feel like I’ve seen horrible things for almost two years now, and you feel the same way. But of all the scandals, and there are so many, this one seems to top the list, namely that once the real pandemic has arrived, there are no effective medicines that are widely available. Doctors are actually being blocked from doing their jobs.
Beyond belief. But you know this. I’m sure you have your own stories. I suspect that many of our readers have encountered this virus for the first time in the last two weeks and have dealt with the horrors of just getting basic medicines to get through this.
The NIH has funded almost no serious trials of these generic drugs. It is not in the interest of pharmaceutical companies to fund them either. As a result, we are truly at a loss – nearly two years into a pandemic at a time when people need meds more than ever.
Meanwhile, the FTC is spending its time cracking down on pharmacies that advertise that they have therapeutics available for people. They are sending cease and desist letters all over the country as a way of intimidating providers. I’ve seen these letters. They have invited me to post them but I’ve declined in the interest of keeping people out of trouble.
One merciful upside to all of this is that there is no more talk of lockdowns. At last, even the experts are saying that society must function. Lockdowns are not even being considered. The whole country is fed up with the phony baloney enterprise of virus control. It did not and cannot work.
Nearly two years ago, they deployed a new experiment in stopping a pathogen. It was a plan that was 15 years in the making, hatched by fanatics who imagined that state policy could outwit a virus.
The wreckage was astonishing, and yet what was the payoff? Here we are today with a wave of sickness that defies every prediction, and with collateral damage beyond even the worst predictions (including my own). And the truth of this is all over the data that anyone can see and the stories that anyone can hear.
The country is right now sicker than it has ever been in our lifetimes.
What a stunning repudiation of state policy – the worst failing of public health and public policy perhaps in the history of the US if not the entire world. We are right now living in its last days. Remember these days, my friends. They are legion and mark what is likely the end of the great fiasco.
And yet it is not really the end. There will be decades of hell to pay for what has happened to us.
Jeffrey A. Tucker is Founder and President of the Brownstone Institute and the author of many thousands of articles in the scholarly and popular press and ten books in 5 languages, most recently Liberty or Lockdown.
A huge new study has found the risk of serious heart problems called myocarditis in men under 40 soars with each dose of a Covid mRNA vaccine – and is sharply higher than the risk from a coronavirus infection itself.
The findings call into sharp question the efforts by American colleges and universities to make their students receive booster shots before returning to school this January – especially since other studies have shown that the risk of post-vaccine myocarditis is concentrated not merely in men under 40 but in those aged 16-25.
The study, which British researchers released in late December, showed that the risk of myocarditis almost doubled after the first Pfizer shot in men under 40. Then it doubled again after the second and doubled again after the third – to almost eight times the baseline risk.
For the Moderna vaccine, the risks were even higher, reaching 16-fold after the second shot. (The risk of a third Moderna shot could not be calculated because too few people received it.)
Because each Moderna shot contains 100 micrograms of mRNA, while each Pfizer shot contains 30, the findings suggest strongly that the heart risks are dose-related and likely to continue to rise with each additional shot.
The study also contained some evidence that post-vaccine myocarditis might be more dangerous than other forms of myocarditis. It showed a trend towards higher death rates in people hospitalized for myocarditis after vaccination compared to other myocarditis cases.
Both myocarditis and pericarditis are forms of heart inflammation that can be very serious, even deadly. In an appendix, the researchers reported that 263 Britons were hospitalized for myocarditis within four weeks of receiving a Pfizer shot; of those, 38, or 14 percent, died. Only about 9 percent of people hospitalized for myocarditis that did not follow an mRNA vaccination died.
The researchers did not look at other potential cardiovascular risks, such as heart attacks or irregular heartbeats, although American and European databases of post-vaccine side effects contain many reports of those as well.
The findings come even as many colleges and universities – including public schools like the University of Massachusetts at Amherst, large private schools such as Syracuse University, and Ivy League institutions such as Princeton University – demand that their students receive a booster Covid shot before returning to campus.
For nearly all these students, an mRNA shot is the only viable option, as the Johnson & Johnson shot is no longer in common use.
These colleges are likely subjecting their male students to a risk of myocarditis and pericarditis, a related illness, that is much higher than the overall risk of Covid, which is vanishingly small for healthy teenagers and young adults. Many larger universities are likely to have multiple cases of male students hospitalized for myocarditis as a result of the mandates.
The massive study was is based on data from 42 million Britons who received at least one Covid vaccine dose, including roughly 22 million who received the mRNA vaccines.
About half were given the mRNA vaccines, while the rest received AstraZeneca’s DNA/AAV vaccine, which is not available in the United States. The AstraZeneca vaccine, which works similarly to the Johnson & Johnson vaccine, had a lower risk of myocarditis than mRNA vaccines.
Nearly two years into the phenomenon labeled COVID-19, more and more people recognize that a global coup d’état is underway — a push by central bankers and technocrats for “totalitarian control of your transportation, your bank account, your movement, every aspect of your life,” said Children’s Health Defense Chairman Robert F. Kennedy, Jr. in a speech he delivered in November 2021 in Milan.
As Kennedy recently argued, “Forcing an entire population to accept an arbitrary and risky medical intervention is the most intrusive and demeaning action ever imposed by the U.S. government, and perhaps any government.”
Concerned about a rapidly advancing bio-surveillance state that would like to make participation in society dependent on vaccine passports and repeat injections, many people are wondering what they can do to resist.
Kennedy described one action that is obvious, if not necessarily easy: Say no “to buying products from the companies bankrupting and seeking to control us.”
In this instance, saying “no” requires casting a wide net, boycotting not just Big Pharma offenders like Pfizer and Johnson & Johnson (J&J) — whose products fill most Americans’ medicine cabinets — but also felonious big banks angling in the shadows for complete digital control over private resources.
Boycotts are not easy, and market analysts sometimes dispute their effectiveness. On the other hand, argues Catholic writer Dusty Gates, “When we complain about something with our lips, but continue to participate in it with our pocketbooks, our complaint loses its volume and clarity.”
Taking moral responsibility “for our personal exercise of purchasing power” and withdrawing support from entities that “degrade the common good” may not be sufficient to halt tyranny in the short term, but history shows such actions can pay long-term dividends.
Remembering the boycott’s origins
It is uncertain how many people know or remember the boycott’s 19th-century Irish origins, but the 1880 tale — one of resolute determination in desperate times — offers powerful lessons that are far from outdated.
At the time, Irish tenant farmers were in the throes of a severe famine and had hit a wall in attempting to renegotiate rents with English land agent Charles Cunningham Boycott.
When Irish nationalist Charles Stewart Parnell encouraged tenants, laborers and local shopkeepers to cut the intransigent Englishman off “from all economic and social relations with the rest of the population,” the nonviolent effort was so successful — and so devastating to Boycott’s day-to-day existence — that the man ended up fleeing Ireland in disgrace.
In his 2015 essay on “why we need boycotts,” Dusty Gates noted there is a difference between what a boycott “most often is” and what a boycott “ought to be.”
Referring to the 1880 events, Gates emphasized that the reason for the Irish tenant farmers’ actions and for the boycott’s resounding success “was specifically that people were being treated unfairly” and were losing their livelihood.
With so much at stake, the boycott was “for people, not publicity.”
Reasons to boycott Pfizer
From all appearances, few of the Americans who last year accepted novel coronavirus injections paid much attention to the corporations making the jabs, instead naively accepting the companies’ “frontrunner” status as a guarantee of trustworthiness.
But while Americans might be forgiven for knowing little about secretive upstart Moderna, the public’s willingness to overlook the known and published offenses of behemoths like Pfizer and J&J is a bit more surprising.
As law firm Matthews & Associates observed in November 2020, just prior to the rollout of Pfizer’s experimental injection, “it would seem reasonable to share all the information available on a company millions of people are expected to trust with their health, perhaps their very lives.”
The firm then outlined key elements of Pfizer’s checkered history, describing it as “rife with … subterfuge and under-the-table dealing.”
In 2010, in a published paper, Canadian health economist and policy analyst Robert G. Evans summarized Pfizer’s record as one of “persistent criminal behavior.”
In a similar assessment, a Pfizer whistleblower stated, “The whole culture of Pfizer is driven by sales, and if you didn’t sell drugs illegally, you were not seen as a team player.”
A small sampling of Pfizer’s unsavory track record includes:
A settlement of $2.3 billion for fraudulent marketing practices in 2009 — at the time, “the largest health care fraud settlement in the history of the Department of Justice.”
Additional settlements that reveal alleged patterns of racketeering and hiding important information about drug risks, sometimes for decades.
An “illegal trial of an unregistered drug” in infants and children in Nigeria that killed 11 children and left others with brain damage and paralysis, ultimately resulting in a $75 million settlement; Pfizer tested the drug on the children without the parents’ informed consent.
Four years ago, Pfizer ranked dead last in a reputational rating of pharmaceutical companies and was considered one of the companies “most associated with arrogance and greed.”
But COVID shots have been very good for business. In 2020, before the Emergency Use Authorization of Pfizer’s vaccine, two products (the blood thinner Eliquis and the Prevnar-13 vaccine) accounted for more than one-fourth of the company’s total revenue.
In 2021, not only did Pfizer’s COVID injections become the year’s top-selling drug worldwide, but top executive Albert Bourla snagged CNN’s honorific of CEO of the Year.
Agreeing with Forbes “there is money to be made and influence to be gained by having people think positively of you,” Bourla gleefully told CNN, “we are enjoying high levels of corporate reputation right now. People like us.”
To keep it that way, Pfizer is now leading the charge to block legislation that would strengthen whistleblowers’ ability to expose corporate fraud. Pharmaphorum rates Pfizer as the sixth largest lobbying presence in Washington.
As recounted in The Intercept, if the whistleblower legislation were to pass, it would strengthen anti-retaliation protections “and make it more difficult for companies charged with fraud to dismiss cases on procedural grounds.”
Buttressed by a fleet of high-powered lawyers and lobbyists, Pfizer and other Big Pharma felons such as Merck, AstraZeneca, Amgen and Genentech — all of whom have a history of paying large settlements for healthcare fraud — are working to make sure the bill does not pass.
They may well succeed, given Pfizer stock is one of the most popular holdings of U.S. lawmakers.
Reasons to boycott J&J
By revenue, J&J was, as of 2020, the world’s largest healthcare company. The company’s combined consumer, pharmaceutical and medical devices groups have displayed steady growth since the mid-2000s, with 55% higher annual revenue in 2020 compared to 2006.
In October 2021, eager to offload its talc liabilities, J&J created a subsidiary and then promptly filed for its bankruptcy protection. In November, meanwhile, J&J announced plans — billed by Reuters as “the biggest shake-up in the U.S. company’s 135-year history — to spin off its consumer health division to focus on the pharmaceutical and medical device division.
J&J is also betting big on “novel solutions” and technologies like robotics and artificial intelligence (AI). Back in 2015, J&J announced a partnership with Google to develop AI surgical robots.
Prior to COVID, J&J had virtually no experience developing vaccines, but COVID shots have been just as good for J&J’s bottom line as for Pfizer’s.
Despite the spate of negative publicity about vaccine-related blood clots and other adverse events, which plagued J&J throughout 2021, for the 12 months ending Sep. 30, 2021, the company reported a 13.1% year-over-year increase in revenue as well as a steadily climbing stock value.
The financial outlook for J&J’s COVID shot may change in 2022, however. In mid-December, the Centers for Disease Control and Prevention (CDC) told the public it “preferentially recommends” getting a Pfizer or Moderna injection rather than J&J’s, despite all three jabs carrying similarly worrisome risks of blood-clotting disorders.
CDC continues to endorse J&J’s shot for vulnerable prison and homeless populations (or when the other two are unavailable), but one of CDC’s advisors told the press she “wouldn’t recommend [her] own family take the J&J shot.”
In addition to adverse events, J&J’s COVID shots have attracted attention for “deficiencies” at its Baltimore production plant, where its notoriously subpar contractor “accidentally” mixed up ingredients and ruined doses.
J&J’s manufacturing woes are neither new nor unique to vaccine production, however. Back in 2013, describing “poppy-seed sized bits of plastic” in infant Motrin and injectable medications marred by mold, a reporter criticized J&J’s hypocritical “warm and fuzzy” marketing, concluding that the “out of control” company had “too many subsidiaries and outsourcing of products to third-party manufacturers for responsible oversight.”
Reasons to boycott felonious banks
In CHD.TV’s new weekly series, “Financial Rebellion,’ former investment banker and Solari Inc. President Catherine Austin Fitts explained the importance of reclaiming financial independence from the “monopolizing grip of the central banks and digital currency titans.”
Fitts argued central banks are using the pandemic to engineer an all-digital control system “that will allow them to extract tax without representation” while exerting 24/7 control over our ability to transact.
Fitts explained how members of the public have a powerful tool at their disposal to disrupt the central bankers’ plans: People can stop banking with the juggernauts that are the largest shareowners of the New York Fed — for example, JPMorgan Chase, Citigroup, Goldman Sachs, Morgan Stanley and Bank of New York Mellon (as well as other megabanks such as Bank of America, Wells Fargo and State Street) — and instead reward well-managed local banks and credit unions with their business.
It is the largest of the 12 “in terms of assets and volume of activity” and, unlike the other Reserve Banks, has “unique responsibilities” that include buying and selling U.S. Treasury securities on the open market to regulate the supply of money and intervening in foreign exchange markets.
The New York Fed has exercised “unprecedented powers” since the 2008 financial crisis and has used the cover story of the pandemic to steadily broaden those powers.
The New York Fed’s ringleader bank, JPMorgan Chase, is the largest U.S. bank (when ranked by total assets), owns 62% of all stock derivatives (valued at $3.3 trillion) held at federally-insured U.S. banks and is one of the top 10 stock holdings of U.S. lawmakers.
But, like Pfizer and J&J, JPMorgan Chase is a “criminal recidivist.” The five-count felon bank facilitated “the largest Ponzi scheme in history” (the Madoff scheme) and racked up $42 billion in civil and criminal penalties between 2002 and 2019. Recent whistleblower allegations describe a culture of fraud.
Nor is JPMorgan Chase alone as an admitted felon among New York Fed member banks. In 2015, Citigroup joined JPMorgan Chase in pleading guilty to rigging foreign exchange markets. In 2020, Goldman Sachs was charged with two felony counts.
Every action counts
Academic studies show the impact of boycotts is most significant when the companies in question already have a bad reputation and a history of frequent past scandals.
This suggests that boycotting Big Pharma, which before COVID had a long-standing reputation as “the most loathed industry in the country,” ought to be an easy sell.
Although companies like Pfizer and J&J may be benefiting from a short-lived “vaccine-led reputation boost,” their COVID injections’ nontrivial dangers are becoming so evident that even the complacent may have trouble discounting the risks.
Dr. Peter McCullough described the shots as the “most dangerous biological medicinal product rollout in human history.”
For some members of the public, connecting the dots to private central banks represents a more challenging conceptual leap.
However, it is vital to recognize the unfolding global coup as an effort coordinated across multiple sectors, not least of which is the financial sector. And — as central bankers step out of their financial silos and brazenly lecture the world about getting vaccinated — their role in the engineering of tyranny is becoming ever more obvious.
Ending tyranny will require action from each of us, beginning with saying “no” to the disastrous COVID shots.
Admittedly, it may be harder to have as immediate an impact on today’s mega-corporations and billionaire tyrants as was achieved when laundresses, postal messengers and blacksmiths so effectively shunned Charles Cunningham Boycott in the 19th century.
But severing our financial — and energetic — ties with the pharma and banking entities that are harming us is still a powerful place to begin.
Boycotts, if driven by a strong “moral impetus,” can have clout.
Products and subsidiaries you can boycott
For boycotting purposes, we include below a partial list of products manufactured by Pfizer and J&J, and a selected list of their numerous acquisitions and subsidiaries.
The founder and CEO of ‘revolutionary’ blood-testing health technology company Theranos, has been found guilty on four counts of wire fraud and conspiracy to defraud investors, but not patients.
Elizabeth Holmes, 37, was found not guilty on four charges revolving around “wire fraud against Theranos paying patients,” and the jury in California also remained deadlocked on three other charges on Monday. But with a partially guilty verdict she could still face up to 20 years in prison for each count, although some observers believe she is unlikely to receive the maximum sentence.
Theranos was once a $9 billion Silicon Valley wonder that promised to revolutionize blood testing. It was founded by Holmes in 2003, after she dropped out of Stanford University at age 19. The company’s board of directors at some point included former senators, future Defense Secretary James Mattis, as well as former Secretaries of State George Schultz and Henry Kissinger.
Praised as a self-made billionaire and “future Steve Jobs” of biotechnology, Holmes would appear at events alongside former Alibaba CEO Jack Ma, former President Bill Clinton and even then-Vice President Joe Biden, claiming that her company could offer blood tests for 240 diseases using just a few drops from a fingertip pin-prick instead of a needle or syringe.
The entire enterprise collapsed following a 2015 Wall Street Journal report by John Carreyrou, which exposed the fact that the company’s miracle technology did not actually work. This triggered an inquiry by federal agencies that led to indictments against Holmes and former Theranos COO Ramesh Balwani in 2018. Balwani is set to stand his own trial next month.
The Centers for Disease Control and Prevention on Dec. 31, 2021, released new data showing a total of 1,000,229 reports of adverse events following COVID vaccines were submitted between Dec. 14, 2020, and Dec. 24, 2021, to the Vaccine Adverse Event Reporting System (VAERS). VAERS is the primary government-funded system for reporting adverse vaccine reactions in the U.S.
Foreign reports are reports received by U.S. manufacturers from their foreign subsidiaries. Under U.S. Food and Drug Administration (FDA) regulations, if a manufacturer is notified of a foreign case report that describes an event that is both serious and does not appear on the product’s labeling, the manufacturer is required to submit the report to VAERS.
Of the 9,623 U.S. deaths reported as of Dec. 24, 20% occurred within 24 hours of vaccination, 25% occurred within 48 hours of vaccination and 61% occurred in people who experienced an onset of symptoms within 48 hours of being vaccinated.
In the U.S., 499.7 million COVID vaccine doses had been administered as of Dec. 23. This includes 291 million doses of Pfizer, 190 million doses of Moderna and 18 million doses of Johnson & Johnson (J&J).
Every Friday, VAERS publishes vaccine injury reports received as of a specified date. Reports submitted to VAERS require further investigation before a causal relationship can be confirmed. Historically, VAERS has been shown to report only 1% of actual vaccine adverse events.
U.S. VAERS data from Dec. 14, 2020, to Dec. 24, 2021, for 5- to 11-year-olds show:
The most recent death involves a previously healthy 15-year-old girl from Wisconsin (VAERS I.D. 1963633), who experienced a cerebral and intraventricular hemorrhage secondary to a ruptured aneurysm. She also tested positive for SARS-CoV-2 despite having been fully vaccinated.
61 reports of anaphylaxis among 12- to 17-year-olds where the reaction was life-threatening, required treatment or resulted in death — with 96% of cases
attributed to Pfizer’s vaccine.
579 reports of myocarditis and pericarditis with 568 cases attributed to Pfizer’s vaccine.
146 reports of blood clotting disorders, with all cases attributed to Pfizer.
U.S. VAERS data from Dec. 14, 2020, to Dec. 10, 2021, for all age groups combined, show:
19% of deaths were related to cardiac disorders.
54% of those who died were male, 41% were female and the remaining death reports did not include the gender of the deceased.
The agency did not consult its expert panel of vaccine advisors, who in September, overwhelmingly rejected boosters for healthy people 16 and older.
The FDA also shortened the time for both adolescents and adults to receive a booster from six months to five months after receiving a second dose and authorized a third shot for immunocompromised children aged 5 to 11.
Dr. Peter Marks, director of the Center for Biologics Evaluation and Research at the FDA, said in a statement the agency made its decision because a third dose “may help provide better protection against both the Delta and Omicron variants.”
The FDA said it reviewed real-world data from Israel of more than 6,300 individuals 12- to 15-years-old who received a booster at least five months after their second Pfizer dose and found no serious safety concerns.
Likewise, additional data showed no problems giving anyone eligible for a Pfizer booster an extra dose at five months instead of six, the Associated Press reported.
The FDA said it will continue to review the information and communicate with the public if data emerges suggesting booster doses are needed for the younger pediatric population.
Pediatrician weighs in on FDA decision: children aren’t ‘mini-adults’
Dr. Michelle Perro, pediatrician and co-author of “What’s Making Our Children Sick,” disagreed with the FDA’s decision, pointing out that “children are not mini-adults.” In an email to The Defender, Perro said children’s rapid growth, quick cellular turnover and less efficient detoxification pathways are factors that must be considered whenever any new therapeutics are being introduced.
Perro said:
“This newest immunomodulating therapy, the mRNA inoculation, has already been shown to have produced multisystem negative health outcomes in children garnered from the CDC’s own database.”
Perro outlined five reasons she believes this “experimental therapy” must be immediately withdrawn:
Gene-edited injectables have not been adequately studied in children as per Pfizer’s own data, where they meshed childrens’ and adults’ data together.
The injection utilizes nanotechnology which is now part of the emerging technology in vaccinology research. These nanoparticles are so small in size they can cross the blood-brain barrier which can adversely affect our already fragile population of children.
The mRNA itself is unstable and is thus encapsulated in a lipid biosphere comprised of a polyethylene glycol shell which in itself is toxic.
The number of children suffering from already documented irreparable side effects from the inoculations, such as those occurring in their hearts (myocarditis), is not only unacceptable but immoral.
Children’s healthcare providers are neither educated or proactive in diagnosing and treating the effects from this experimental therapy.
Perro questioned the FDA’s motives, given that children suffer nearly zero morbidity and mortality from COVID infections.
She also said the FDA is “veering from” its own historical stance.
“When previous true vaccines were introduced historically (rotavirus vaccine), after just a few cases of adversity, they were immediately withdrawn,” Perro told The Defender. “The FDA must adhere to its own historical position regarding their assigned task of the protection and oversight of our country’s greatest asset: our children.”
Fauci says hospitalization numbers for kids with COVID are overcounted
Dr. Anthony Fauci, director of the National Institute of Allergy and Infectious Diseases, in an interview on MSNBC, said statistics for hospitalizations among children with COVID are overcounted, making clear the distinction between children hospitalized with COVID and children hospitalized “because of COVID.”
Speaking to MSNBC’s Ayman Mohyeldin, who was filling in for Rachel Maddow on Dec. 29, about the rise in hospitalizations among children amid the Omicron variant, Fauci said the surge is due to two contributing factors — more children getting infected and the way COVID cases are counted.
“And what we mean by that — if a child goes in the hospital, they automatically get tested for COVID. And they get counted as a COVID-hospitalized individual,” Fauci said. “When in fact, they may go in for a broken leg or appendicitis or something like that. So it’s overcounting the number of children who are, quote, ‘hospitalized with COVID,’ as opposed to because of COVID.”
I was totally shocked to hear the claims by a fire scientist I had once admired and often quoted in my blog posts about wildfire. In a National Public Radio interview Jennifer Balch said, “Climate change has lengthened the state’s fire season”. Then she said “”Climate change is essentially keeping our fuels drier longer. These grasses that were burning, they’ve been baked all fall and all winter.”
Having studied fire ecology for 30 years and knowing her published science, I could only believe she had been corrupted by the need to attract large amounts of funding, and these days that comes to those who blame the climate crisis. And here’s why I now hold that opinion so strongly.
Colorado’s Marshall Fire was a grassfire that happened with temperatures hovering around freezing. All fire experts and fire managers know grasses are 1-hour lag fuels. That means in dry conditions grasses can become flammable within hours. Attempting to link CO2 global warming, she and other alarmists were now blaming the Boulder area’s grass flammability on the warm dry conditions from July through November. But dry conditions in the past months are totally irrelevant. Those months could have also been cold and wet, but just one day of dry conditions is all that is needed for grasses to burn.
To minimize recklessly set fire that often occurs as people burn away unwanted dead vegetation, the Nova Scotia government felt the need to counter the Myth that “It’s safe to burn grass as long as there is still some snow on the ground.”
The Fact is: “Within hours of snow melting, dead grass becomes flammable, especially if there have been drying winds. Grass fires burn hot and fast and spread quickly around, and even over, patches of snow.” That’s a fact that Balch and every other fire expert should know!
Apparently, Daniel Swain, a climate scientist at the University of California Los Angeles and the Nature Conservancy and acolyte of climate alarmist Michael Mann and Noah Diffenbaugh, also failed to understand grasses are 1-hour fuel. He stated in an interview for NBC’s article How climate change primed Colorado for a rare December wildfire that “Climate change is clearly making the pre-conditions for wildfires worse across most fire-prone regions of the world,”
But dry grasses are not the pre-condition to be worried about. The pre-conditions that neither Swain nor Balch shared with the public is well known: Boulder County’s invasive grasses increase fire danger. The “main offender is cheatgrass, which was likely introduced to the area alongside agriculture and ranching” and “is increasing fire danger by 29%”
In fact, in 2013 Balch published, Introduced annual grass increases regional fire activity across the arid western USA (1980–2009), writing “Cheatgrass was disproportionately represented in the largest fires, comprising 24% of the land area of the 50 largest fires” and that “multi-date fires that burned across multiple vegetation types were significantly more likely to have started in cheatgrass.”
It was also very disingenuous for Balch to say “Climate change has lengthened the state’s fire season”. It is the very same meme that every climate alarmist regurgitates that climate change has made “a year-long fire season the new normal”. But in 2017 Balch published in Human-started wildfires expand the fire niche across the United Statesthat human ignitions “have vastly expanded the spatial and seasonal ‘fire niche’ in the coterminous United States, accounting for 84% of all wildfires”. Balch’s published graph clearly shows that human ignitions have extended fire season all year long. Based on her own research, a more relevant comment would have mentioned that Louisville, Colorado’s population had jumped 10-fold; from 2,000 in 1950 to about 20,000 today. Does a 10-fold increase in population create a 10-fold increase in fire probability. The Marshall Fire was not naturally started by Lightning.
In 2015, Balch created the Earth Lab program at Colorado University. In 2017 it became part of CIRES, a partnership of NOAA and CU Boulder. Earth Lab, got increasing attention from mass media that’s always seeking click-bait. As Earth Lab’s team began blaming more fires on climate change, it got more attention and Balch got more interviews.
Earth Lab hired Natasha Stavros as Earth Lab’s Analytics Hub Director. In videos posted by the Washington Post, she claimed climate change causes “longer, hotter, and drier fire seasons” reflecting Balch’s conversion to a climate crisis narrative. To get around Balch’s earlier scientific research Stavros deflected, “We are not talking about the ignition source” or the “availability of fuels”, “what we are talking about are the conditions of those fuels”. But in the case of the Marshall Fire, 1-hour grass fuels have nothing to do with climate change. It only takes a few hours to be in highly flammable conditions. That’s weather, not climate!
Although lacking in scientific integrity, pivoting to a climate crisis narrative worked in Balch’s favor. The U.S. Geological Survey has selected the University of Colorado Boulder to host the North Central Climate Adaptation Science Center (NCCASC) for the next five years. Balch, as director of CIRES’ Earth Lab, and now NCCASC Director had attracted $4.5 million in funding. Universities around the country similarly create such centers to attract such major funding. Certainly, blaming fires on a climate crisis attracts more funding than if its director sounded like a “denier” blaming invasive grasses and human ignitions.
The politics of funding research requires a major level of group think. Daniel Shechtman won the Nobel Prize for discovering quasi-crystals that are now used in surgical instruments. But when he first announced his observations, he was kicked out of his lab by his colleagues. They saw him as a threat to the lab’s prestige and funding because observing quasi-crystals contradicted the consensus that was enforced by Linus Pauling that quasi-crystal did NOT exist.
Similarly, esteemed atmospheric scientist Dr Cliff Mass was criticized by Washington University administrator’s for detailing how an episode of problematic acidic waters that had been pumped into the state’s oyster’s hatcheries, was due to natural upwelling events, not climate change. But contradicting the climate crisis angle threatened funding to WU’s Ocean Acidification Center. Up until then Mass had been the Seattle Times go-to person for all weather events, but that stopped when his one analysis didn’t support climate crisis groupthink. Dr Peter Ridd was fired for presenting evidence showing his colleague’s claims of coral reef destruction were exaggerated. So, all savvy university professors know you can’t contradict the meme if you want funding, or worse, keep your job.
Climate crisis groupthink, also ignores natural climate change, as did Balch and Swain. But one meteorologist confidently blamed the lack of snow and dryness on a natural La Nina. The science is well established that depending on how colder Pacific surface waters set up during a La Nina, atmospheric currents can carry higher or lower amounts of moisture to different regions. California had record snowfall this December while Colorado snowfall was very low. And if the Marshall Fire had been ignited just 2 days later, there would have been a snowfall to suppress the fire.
However too often, alarmist scientists cherry-pick one-year events. They weaponized this year’s low snowfall while ignoring that last year’s Colorado snowfall was far above normal. In November last year, Fort Collins received more than 15 inches of snow on its way to 80 inches, which is 25 inches more than normal. Again, such variations in snowfall are weather, not climate.
Alarmists also weaponized the dry conditions as solely due to global warming drought. They ignored the drying and warming effects of the Chinook winds that are very common in Colorado. Chinooks are known as “snow eaters” because as the winds pass over the mountains of the western USA they are forced upward and precipitate all their moisture. When those winds descend from the Rockies down to Boulder, temperatures rise adiabatically (due to pressure not added heat) and the warm dry air quickly removes moisture or snow from the surface. Southern California’s Santa Anna winds are similar and drive large fires.
Sometimes Boulder’s winds reach speeds of 100+ mile per hour. NOAA reported The Chinook Wind Events Winter of 1982 during which peak wind gusts more than 100 mph damaged areas around Boulder. Weatherwise journal reported 100+MPH winds over Boulder on January 7, 1969, which snapped power poles and toppled planes as seen in the photographs below. In November 2021 the weather service gave a red flag warming due to the high winds from a Chinook event. But without a coinciding human ignition, there was no rapidly spreading fire.
I would like to believe that Balch’s Earth Lab scientists have been campaigning for the housing developments in Boulder’s suburbs of Louisville and Superior to create a system of firebreaks and defensible space. Those suburbs had built into easily ignited grassland in a region where fires are rapidly spread by the dry Chinooks descending from the Rockies. Such natural fire danger is not always obvious to the public looking for affordable housing. But it is not obvious that was ever done, at least not as obvious as faulty climate change narratives.
Fire experts should have pushed for building codes, requiring adequate spacing between new houses. As a story in Wildfire Today reported today, one common feature of the surviving homes was they were more distant from neighboring homes. Many houses in the devastated subdivisions were only 10 to 20 feet apart. Without adequate fire breaks or defensible space, if just one house allowed the fire to reach it, the heat of that burning house is enough to ignite any house next to it. Similar dynamics were seen in California’s Tubbs and Camp Fires that demolished neighborhoods.
But perhaps local governments were greedy. Eager to build a tax base a growing Louisville population was most important. Politicians had worked hard to present Louisville as one of the top 10 most livable little cities. Putting natural fire danger front and center, might put a damper on the city’s attractiveness. And not surprisingly the Denver Democrats didn’t waste time to capitalize on the Marshall Fire devastation. The released a statement claiming “This fire has also punctuated our climate crisis and made abundantly clear the need for bold action. The science is clear, and the impacts are very real. We will continue to work with our community and legislators to ensure climate change is treated with the urgency and attention it deserves.”
But the science does not show a connection between the Marshall Fire and Climate Change. And due to the greed of the media, politicians, and selfish scientists, only scientific integrity is facing a real crisis.
Finally, it is worth noting that some scientists are acutely aware of the increasing fire danger presented by the build-up of dead vegetation. To remove that hazard prescribed burns are being performed. But sometimes prescribed burns get away and burn down people’s homes. So prescribed burns are carefully planned for times when fires are most easily controlled. So, one must wonder just how unusually dangerous local conditions were if the City of Boulder planned a prescribed burn on Monday, December 13, 2021, just 2 weeks before the Marshall Fire. Had climate change really made conditions so dangerous?
Jim Steele is Director emeritus of San Francisco State University’s Sierra Nevada Field Campus, authored Landscapes and Cycles: An Environmentalist’s Journey to Climate Skepticism, and proud member of the CO2 Coalition.
Back in October, I shared the story of the brave Dr. Patricia Lee, a fully vaccinated intensive care unit physician and surgeon, who stepped forward after witnessing numerous serious injuries in her patients following COVID-19 vaccination.
Since that story was published, Dr. Lee had a Zoom meeting with six federal health officials, including Dr. Peter Marks of the FDA and Dr. Tom Shimabukuro of the CDC. The meeting left Dr. Lee more frustrated than she had been prior to the meeting – the officials had no interest in the specific harms she detailed, even after hearing the heartbreaking and traumatic stories that Dr. Lee shared about her individual patients. Without asking a single question or reviewing any of the relevant medical records, Dr. Lee was effectively told that COVID-19 vaccines did not cause these injuries in her patients.
Given the lack of interest in understanding the harm to her patients, Dr. Lee made only one request. She asked that both the FDA and the CDC publicly announce that physicians should not be retaliated against for advocating for their injured patients, so that they would not fear reporting injuries from COVID-19 vaccinations. The individuals in the meeting indicated that they welcomed those reports and that they view physicians as partners in monitoring safety. However, to date, no such public statement has been made, even after a follow-up letter was sent requesting just that. Nor has any other action been taken.
Dr. Lee is not willing to let this go – as a physician, she has an ethical duty to her patients. And so she has now reached out to the oversight committees in Congress. You can read her letter to these committees below highlighting the federal health authorities’ refusal to even recognize vaccine injuries, let alone address this serious issue and those whose lives have been devastated by these injuries. Hopefully these elected officials do the right thing:
New plans, announced before Christmas, will require every secondary school pupil in the UK to take an on-site Covid test when school resumes after the Christmas break.
The government plans, allegedly to “monitor” Covid infection in students, go on to suggest that every child should receive a follow-up test 3-4 days later.
There are roughly 3.5 million school pupils aged 11-16 in the UK and they plan to test them all twice.
If just 2% of them test positive just once, the media will scream about 140,000 new “cases” of Covid in children.
Further, the “recommendations” suggest children should then continue to be tested twice a week, every week, or “more frequently if asked to do so”:
Secondary, college and university students and education staff and early years staff should then continue to test themselves twice a week, and more frequently if they are specifically asked to do so, such as in the event of an outbreak.
At least 7 million lateral flow tests per week, every week.
It’s not hard to see where it goes from there, with the headlines blaring that lack of social distancing over the holidays gave rise to a “fourth wave” (or would it be fifth? I’ve lost count).
I would start preparing for a new lockdown, if I were you.
The label for Humira, once the best-selling drug in the world, lists its risks in plain print. One of them, in the label’s own words, is new “autoimmune” disease.
A drug prescribed for a condition labelled autoimmune carries a warning that it can cause a condition labelled autoimmune. That contradiction sits in every box, on a folded paper almost nobody reads.
My new book starts there.
No Autoimmunity: The Body Doesn’t Attack Itself
For seventy years, “your body is attacking itself, and we don’t know why” has ended the conversation for people diagnosed with multiple sclerosis, lupus, rheumatoid arthritis, Hashimoto’s, Type 1 diabetes, Crohn’s and psoriasis. More than eighty conditions now carry the autoimmune label. The diagnosis comes with a prescription for life. It almost never comes with a question about cause.
This book asks the question and answers it from the framework’s own records: its drug labels, its journals, its regulatory filings, and its own experiments. … continue
This site is provided as a research and reference tool. Although we make every reasonable effort to ensure that the information and data provided at this site are useful, accurate, and current, we cannot guarantee that the information and data provided here will be error-free. By using this site, you assume all responsibility for and risk arising from your use of and reliance upon the contents of this site.
This site and the information available through it do not, and are not intended to constitute legal advice. Should you require legal advice, you should consult your own attorney.
Nothing within this site or linked to by this site constitutes investment advice or medical advice.
Materials accessible from or added to this site by third parties, such as comments posted, are strictly the responsibility of the third party who added such materials or made them accessible and we neither endorse nor undertake to control, monitor, edit or assume responsibility for any such third-party material.
The posting of stories, commentaries, reports, documents and links (embedded or otherwise) on this site does not in any way, shape or form, implied or otherwise, necessarily express or suggest endorsement or support of any of such posted material or parts therein.
The word “alleged” is deemed to occur before the word “fraud.” Since the rule of law still applies. To peasants, at least.
Fair Use
This site contains copyrighted material the use of which has not always been specifically authorized by the copyright owner. We are making such material available in our efforts to advance understanding of environmental, political, human rights, economic, democracy, scientific, and social justice issues, etc. We believe this constitutes a ‘fair use’ of any such copyrighted material as provided for in section 107 of the US Copyright Law. In accordance with Title 17 U.S.C. Section 107, the material on this site is distributed without profit to those who have expressed a prior interest in receiving the included information for research and educational purposes. For more info go to: http://www.law.cornell.edu/uscode/17/107.shtml. If you wish to use copyrighted material from this site for purposes of your own that go beyond ‘fair use’, you must obtain permission from the copyright owner.
DMCA Contact
This is information for anyone that wishes to challenge our “fair use” of copyrighted material.
If you are a legal copyright holder or a designated agent for such and you believe that content residing on or accessible through our website infringes a copyright and falls outside the boundaries of “Fair Use”, please send a notice of infringement by contacting atheonews@gmail.com.
We will respond and take necessary action immediately.
If notice is given of an alleged copyright violation we will act expeditiously to remove or disable access to the material(s) in question.
All 3rd party material posted on this website is copyright the respective owners / authors. Aletho News makes no claim of copyright on such material.


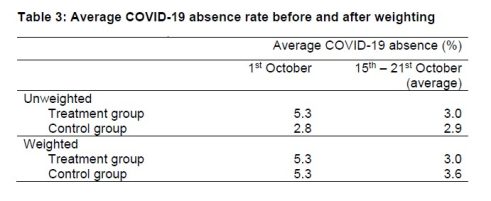



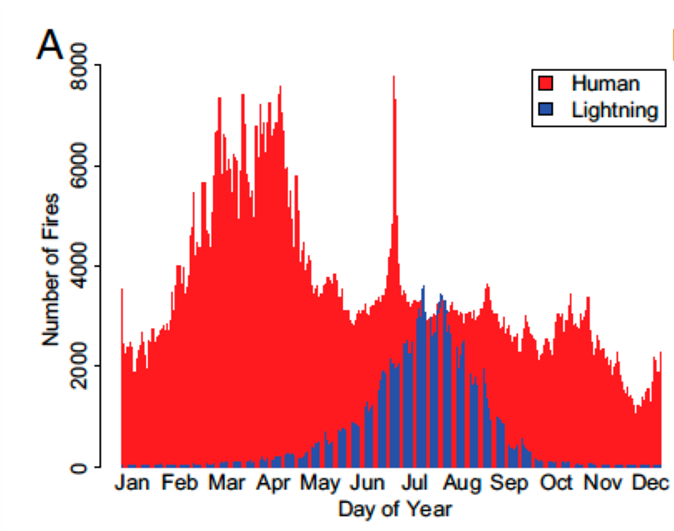






 The label for Humira, once the best-selling drug in the world, lists its risks in plain print. One of them, in the label’s own words, is new “autoimmune” disease.


